Radiocarpal Joint
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Great Medical Encyclopedia details the anatomical structure, ligaments, synovial cavities, and biomechanical movements of the radiocarpal joint. It describes the articulation between the forearm bones and the first row of carpal bones, along with variations and clinical landmarks.
Encyclopedia article (1928–1936)
RADIOCARPAL JOINT (articulatio radio-carpea) connects the hand to the forearm. The name art. radio-carpea indicates that of the two forearm bones, only the radius directly articulates with the hand. The ulna does not reach the hand; its lower end is separated from the wrist by a triangular cartilage (cartilago triangularis, syn.: lig. triangulare, discus articularis). The mentioned cartilage has the shape of a triangular plate; one of its sides is attached to the articular notch of the lower end of the radius, while its apex is connected by means of a thick and short ligament (lig. subcruentum) to the styloid process of the ulna. The morphological significance of the triangular cartilage is not entirely studied. In the embryo, a bone is found on the lower surface of the cartilage, which, due to its position between the radius, ulna, and the first row of carpal bones, received the name of the intermediate bone of the forearm (os intermedium antebrachii). The older the embryos, the less frequently this bone is found; in adults, it is almost never observed; to date, only one case of such an anomaly is known; this bone must be considered morphologically extinct and phylogenetically extremely ancient. Thilenius points to its presence in marsupials (Phaseolomys) and in some anthropoids (gibbons) (Testut). The radiocarpal joint belongs to arthrodias, the so-called capitular or elliptical joints (condylarthrosis according to Cruveilhier) (Lesgaft). Of the two articular surfaces of the joint, one belongs to the forearm, the other to the wrist. The articular surface of the forearm is concave (Fig. 1), has the shape of an ellipsoid, the major axis of which stretches from one styloid process to the other. This articular surface is formed by the expanded end
of the radius with a cartilaginous extension (discus articularis) toward the ulna. The articular surface of the radius is triangular in shape, with an outward-facing apex, on the surface of which slight depressions are noticeable—imprints of the scaphoid and lunate bones adjacent to it. The articular surface of the wrist is formed by three bones: the scaphoid, lunate, and triquetrum; the pisiform bone belongs to sesamoid bones and has no direct relation to the formation of the joint; the gaps between the bones of the first row of the wrist up to the level of the articular surfaces are filled with ligaments, resulting in an almost smooth joint head, elongated in the transverse direction of the hand. The number of bones in the first row of the wrist sometimes increases due to the doubling of some of them; for example, a double scaphoid bone is found [os naviculare bipartitum, syn.: os naviculare radiale, os naviculare ulnare: ossa navicularia secundaria radiale et ulnare (Gruber)]; a double triquetral bone (os triquetrum bipartitum, syn.: os triquetrum radiale, os triquetrum ulnare). The line of the radiocarpal joint runs obliquely from outside inwards and from bottom to top. The concavity of the articular surface of the radius precisely corresponds to the convexity of the scaphoid and lunate bones; the participation of the triquetral bone in the joint is negligible, which can be judged by its very small articular surface corresponding to the most lateral part of the triangular cartilage. The joint line on radiographs is thin and clearly visible; the posterior edge of the epiphyseal end of the radius casts a slight shadow on the lunate bone; in the ulnar part, the joint line is wider.
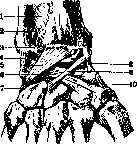
Ligaments of the joint. The bones of the joint are held together by a fibrous capsule and the ligament apparatus reinforcing it. The upper edge of the capsule is attached along the edge of the articular surface of the radius and along the edge of the triangular cartilage (discus articularis); the lower edge of the capsule is attached to the edge of the articular surface of the first row of carpal bones. The capsule is reinforced on the outside by ligaments. Although the ligament apparatus forms an almost continuous connective tissue layer around the joint, it is nevertheless customary to distinguish and describe separate bundles of ligaments running in various directions: on the palmar side, there is a wide radiocarpal ligament (lig. radio-carpeum volare) (Fig. 2), running from the styloid process and the palmar edge of the articular surface of the radius with several bundles to the lunate, triquetral, and capitate bones; the second ligament of the same surface runs fanwise from the base of the ulnar styloid process to the triquetral and capitate bones (Testut). These ligaments are related to the supination of the hand; during the transition of the hand from pronation to supination, the radius pulls the hand behind it with their help. The ligaments of the dorsal side of the joint are weaker, cover only about a third of the posterior surface of the joint, and stretch from the radius to the triquetral bone, sometimes to the lunate and capitate bones (Fig. 3).
Figure 2. Radiocarpal joint from the palmar surface: 1 and 2—inter-ligamentous protrusion of the synovial membrane of the joint; 3 and 4—lig. radio-carpeum volare; 5—lig. collaterale carpi radiale; 6—lig. interosseum antebrachii; 7—inter-ligamentous protrusion of the synovial membrane between the radius and ulna; 8—lig. radio-ulnare distale; 9—the same in front of the styloid process; 10—lig. carpo-ulnare; 11—lig. collaterale carpi ulnare; 12—the same between the pisiform and triquetral bones. Dorsal ligaments are closely connected with the fibrous sheaths of the extensors. These ligaments become taut during pronation of the hand. From the radial styloid process to the scaphoid bone runs the outer collateral ligament (lig. collaterale carpi radiale); from the ulnar styloid process to the triquetral bone is stretched the inner collateral ligament (lig. collaterale carpi ulnare). The entire inner surface of the joint capsule is covered by a synovial membrane ending precisely at the edges of the articular cartilages. The radiocarpal joint communicates with the inferior radio-ulnar joint (40%) through a slit-like opening at the base of the triangular cartilage. In half of the cases, the cavity of the radiocarpal joint communicates with the joint between the triquetral and pisiform bones, and only in exceptional cases does the radiocarpal joint communicate with the wrist joints (Testut). In addition, the joint cavity in some cases gives off, as it were, outgrowths, pockets, cavities between bundles of ligaments (Figures 2 and 3); these protrusions are true synovial hernias that have penetrated through the fibrous capsule of the joint, and are the beginning of cysts (hygromas) of the joint. The boundaries of the radiocarpal joint are established by various authors differently and conventionally. The upper boundary is formed by a horizontal plane passing just above the head (capitulum ulnae) of the ulnar bone; the lower boundary—by a plane drawn parallel to the previous one just below the pisiform bone.
Movements in the radiocarpal joint can be considered only jointly with movements in the joints between the first and second rows of carpal bones, i.e., here movement occurs as in a complex joint with a bone meniscus formed by three bones of the first row of the wrist. In this complex joint, movements around the transverse and anteroposterior axes are possible: flexion, extension, adduction and abduction, and the totality of movements around these axes—circular rotation. During flexion, the palm leans toward the anterior surface of the forearm; during extension, the opposite movement occurs. The participation of both parts of the complex joint in these movements is clearly visible on radiographs (Figure 4). The bone meniscus (the first row of carpal bones) leans toward the forearm during flexion; in the same direction, the inclination of the second row of carpal bones also occurs (Figure 4); this double movement occurs around the transverse axis passing through the highest point of the head of the capitate bone. By adduction or ulnar flexion is meant the movement in which the ulnar edge of the hand tilts toward the ulnar edge of the forearm; abduction or radial flexion is called the opposite movement. This movement occurs around the anteroposterior axis passing through the center of the head of the capitate bone; while upon the inclination of the base of the capitate bone outwardly (abduction), the lunate bone sitting astride the first,
Figure 4. Radiograph (diagram) in profile of the radiocarpal joint in the position: A—intermediate between flexion and extension; B—in flexion; C—in extension; 1—radius; 2—os lunatum; 3—os capitatum; 4—third metacarpal bone.

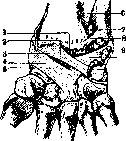
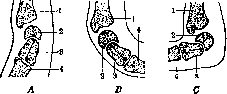
deviates inwards and vice versa; consequently, the articular surface of the first row of the wrist glides along the articular end of the forearm in the transverse and opposite direction to the hand, i.e., during ulnar flexion the wrist moves towards the radius, and during radial flexion towards the ulna (Fig. 4); circular rotation is obtained as a result of a sequential transition from flexion to abduction, extension, and adduction. The range of motion in this case is greater around the transverse axis of the joint, i.e., during flexion and extension, than around the anteroposterior axis—abduction and adduction (Saprey); therefore, the base of the cone of rotation described by the hand is not a circle, but an ellipse (Testut). Normally, the range of motion from full extension to full flexion is slightly less than 180°, with more than 90° falling on the movement in the radiocarpal joint and less on the joint between the two rows of carpal bones (Testut); Lesgaft considers the arc of this movement to be 135–140° and around the anteroposterior axis—up to 75°. - Of the listed movements, flexion in the radiocarpal joint is produced either only by the muscles acting directly upon it, such as: the radial flexor of the wrist (m. flexor carpi radialis), the long palmar muscle (m. palmaris longus) and
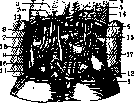
the ulnar flexor of the wrist (m. flexor carpi ulnaris), or these muscles together with the remaining flexors. All extensors participate in extension. Abduction is produced as a result of the combined action of m. flexor carpi radialis, both radial extensors of the wrist (mm. extensores carpi radialis brevis et longus), the long muscle abducting the thumb (m. abductor pollicis longus), and both extensors of the thumb (mm. extensores pollicis brevis et longus). Adduction is produced by m. flexor carpi ulnaris and the extensor of the wrist (m. extensor carpi ulnaris).
The flexor muscles lie under the aponeurosis of the flexor surface of the joint and are arranged in 4 layers (Fig. 5); in the first layer (counting from the radial edge to the ulnar) run the tendons of the brachioradialis muscle (m. brachioradialis), the radial flexor of the wrist (m. flexor carpi radialis), the long palmar muscle (m. palmaris longus) (Testut), more precisely: the tendon of this muscle passes in the bifurcation Figure 5. Flexor surface of the radiocarpal joint region: 1 - skin and aponeurosis incision; 2 - m. brachioradialis; 3 - m. flexor carpi radialis; 4 - m. palmaris long.; 5 - m. flexor digitorum communis superficialis et profundus; 6 - m. flexor carpi ulnaris; 7 - m. flexor pollicis long.; 8 - m. pronator quadratus; 9 - m. abductor pollicis long.; 10 - m. extensor pollicis brevis; 11 - thenar; 12 - hypothenar; 13 - a. radialis; 14 - a. ulnaris; 15 - a. et n. interossei; 16 - n. medianus; 17 - n. ulnaris. of the volar carpal ligament (ligamentum carpi volare) and m. flexor carpi ulnaris; in the second layer - four tendons of the superficial flexor of the fingers (m. flexor digitorum sublimis); in the third layer - the long flexor of the thumb (m. flexor pollicis longus); four tendons of the deep flexor of the fingers (m. flexor digit. profundus); in the fourth layer - the pronator quadratus (m. pronator quadratus). In the tendon canal passing from the palm to the forearm, there are two synovial sheaths: one for the long flexor of the thumb and the second for the common flexor of the digits (see Hand); in the fifth layer - the skeleton. - Between the tendons of the brachioradialis muscle (laterally) and the radial flexor of the wrist (medially) runs the radial artery (a. radialis) with its two companion veins; the radial nerve (n. radialis) has departed higher onto the dorsal surface of the forearm; the artery lies on the pronator quadratus muscle and can be easily compressed against the radius; covered only by skin and aponeurosis, the artery is easily accessible for pulse examination; approaching the base of the styloid process of the radius, the artery changes its direction and goes to the dorsum of the joint; on the flexor side, the radial artery gives off a superficial volar branch (ramus volaris superfic.) and a carpal volar branch (ramus carpeus volaris), running in a transverse direction along the lower edge of the pronator quadratus muscle and anastomosing with the corresponding branch of the ulnar artery. Between the tendons of the ulnar flexor of the wrist (medially) and the superficial flexor of the fingers (laterally) run the ulnar artery with two companion veins and the nerve of the same name, lying nearby and medial to the artery. Beneath the pronator quadratus muscle passes the volar interosseous artery (a. interossea volaris), which passes through the interosseous ligament to the extensor surface of the forearm. Of the nerves, there is also the median nerve (n. medianus); running with the nerve is the artery of the same name (a. mediana), lying on its anterior surface; the nerve passes under the long palmar muscle at the radial edge of the superficial flexor of the digits, separating the sheath of the long flexor of the thumb from the sheath of the superficial flexor of the digits. All these muscles, vessels, and nerves are directly enveloped by an aponeurosis, which at this place is thicker than on the forearm and forms a strong ligament with transverse fibers (lig. carpi volare), 3-4 cm wide. Above, it passes into the aponeurosis of the forearm, below - into the palmar aponeurosis; some of the muscles of the eminences of the thumb and the fifth finger originate from it; with one end the ligament is fixed to the pisiform and hookate bones, with the other - to the scaphoid and greater multangular bones; bundles depart from the deep layer of the ligament to the anterior surface of the carpal bones. Under the ligament there are channels for the passage of flexor tendons; through these same channels pus can spread from the hand to the forearm. Subcutaneous tissue here is never rich in fat, even in obese people; in this layer pass the superficial veins, which are the beginning of the basilic vein system (venae basilicae), and nerves, which are the continuation of the nerves of the forearm: along the radial edge runs the lateral cutaneous nerve of the forearm (n. cutaneus antebrachii lateralis), in the middle - the palmar branch of the median nerve (ramus palmaris n. mediani), along the ulnar edge - branches of the medial cutaneous nerve of the forearm and the palmar cutaneous branch of the ulnar nerve (rami n. cutanei antebrachii medialis et ramus cutaneus palmaris n. ulnaris). The skin in this place is thin, devoid of hair, has transverse folds, is fused with the aponeurosis, and therefore is little displaceable. The extensor muscles lie under the aponeurosis of the dorsal surface of the radiocarpal joint; here the aponeurosis forms the dorsal ligament of the wrist (lig. carpi dorsale), the fibers of which run in a transverse direction, attaching with the ulnar end to the triquetral and pisiform bones, and with the radial end to the lower end of the radius. The ligament above passes into the aponeurosis of the forearm, below - into the aponeurosis of the hand. From the deep layer of the ligament, septa depart to the bones of the forearm and form 6 channels for 12 extensor tendons, arranged
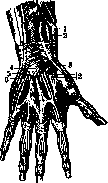
Figure 6. Synovial sheaths of the tendons of the hand dorsum: 1 - m. abductor et extensor pollicis brevis; 2 - mm. extensores carpi radialis long. et brev.; 3 - m. extensor pollicis longi; 4 - m. extensor digitorum communis; 5 - m. extensor digiti V propr.; 6 - m. extensor carpi ulnaris.
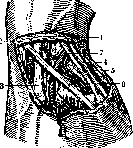
Figure 7. Region of the anatomical snuffbox (right hand): 1 - skin and subcutaneous tissue with superficial veins and nerves; 2 - superficial aponeurosis; 3 - mm. extensores carpi radialis long. et brevis; 4 - m. abductor pollicis long.; 5 - m. extensor pollicis brevis; 6 - m. extensor pollicis long.; 7 - a. radialis.
in the following order, starting from the radial edge (Fig. 6): the long muscle abducting the thumb (m. abductor pollicis longus); the short extensor of the thumb (m. extensor pollicis brevis); both muscles pass through the first channel, having a common synovial sheath rising 2-3 cm above the upper edge of the ligament; the radial extensors of the wrist (mm. extensores carpi radialis longus et brevis) pass through the second channel ---
also in the general synovial sheath, which is divided at the top and bottom into two separate sheaths; above them, in the third canal, the m. extensor pollicis longus runs obliquely from the ulnar edge to the radial side; its sheath extends 1-2 cm above and below the ligament. The interval between the long and short abductor of the thumb is called the anatomical snuffbox (la tabatiere anatomique); on its floor, under the tendons, the a. radialis runs obliquely to the first interdigital interval (Fig. 7). The next in order are: the muscle extending the index finger (m. extensor indicis proprius), the common extensor of the fingers (m. extensor digitorum communis); their tendons pass through the fourth canal, covered by one sheath rising 1 cm above the ligament and descending to halfway and below the metacarpal bones; the extensor of the little finger (m. extensor digiti quinti proprius) in the fifth canal; its sheath begins at the level of the head of the ulna and reaches halfway of the fifth metacarpal bone; the last is the extensor carpi ulnaris (m. extensor carpi ulnaris) in the sixth canal; its sheath runs from the head of the ulna to the upper end of the fifth metacarpal bone. - The synovial sheaths of the tendons, cylindrical in shape, consist of two layers: the parietal, lining the bony-fibrous canal, and the visceral, enveloping the tendon itself; these two layers are connected to each other in places by synovial folds extending from one layer to the other and called "mesotendo"; through them pass the vessels and nerves nourishing the tendons; therefore their destruction can lead to tendon necrosis. The vessels and nerves of the back of this area are of less importance than on the flexor surface. The superficial arteries are all small. The main artery is the radial, giving off the dorsal carpal branch (ramus carpeus dorsalis), anastomosing with the corresponding branch of the ulnar artery; here also pass the terminal branches of the palmar and dorsal interosseous arteries. - The arteries nourishing the joint arise from several sources: from the front - from the transverse arch of the wrist passing along the lower edge of the m. pronator quadratus and the ascending branches of the volar arcus prof.; from the back - from the a. interossea and from the rete carpi dorsale; on the radial edge - from the a. radialis, on the ulnar edge - from the a. ulnaris. - The joint receives nerves from the front from the nn. medianus and ulnaris, from the back from the n. radialis and the dorsal branch of the n. ulnaris. - Lymphatic vessels here, as on the anterior surface, divide into superficial and deep; they usually run with the veins and partly empty into the ulnar lymphatic glands, and partly pass directly to the axillary glands. - The superficial veins of the subcutaneous layer are well developed, have no constant location, and are the beginning of the venae cephalicae. The subcutaneous tissue is richer in fat; often in this layer above the styloid processes of both forearm bones there exist serous bursae. The skin here is thicker than in front and more mobile, covered with hair, and has many small transverse folds. A. Sirorkin. Pathology of the R. joint. In view of the special significance of the hand and fingers as the main working organ of man, injuries and diseases of the R. joint region acquire great importance. This region is especially frequently subjected to injuries in the very process of work. These include injuries by hand tools, the material being processed, glass, machine injuries (getting into shafts, drums, etc.), and finally burns, both thermal and chemical. Injuries can be: 1) closed - contusions, sprains, strains, fractures, and (extremely rarely) dislocations (Fig. 8) and 2) open - wounds (incised, contused, lacerated and gunshot wounds) and burns. As regards open injuries, they are dangerous first of all due to the anatomical peculiarities of this region, abundant in tendons, nerves and vessels, secondly due to the possible entry of infection, which is especially dangerous precisely in the R. joint region, where infection easily and quickly spreads along the course of the tendons, often causing their necrosis, thirdly these injuries, giving rise to extensive and deep scars upon healing, disrupt the function of the hand and fingers. Even superficial skin injuries, giving rise to scar contractures after healing per granulationem, strongly limit the normal function of the hand and fingers. In cases where the tendons of the flexors or extensors lying directly under the skin are compressed by a scar, limitation of movement of the hand and fingers occurs. Knife wounds and glass wounds of the R. joint region are very often complicated by the cutting of the flexor tendons. Besides professional factors, domestic ones also play a role here: wound

Fig. 8.
Spontaneous subluxation of the wrist. stab wound in a fight, injury by bottle glass in a state of intoxication, etc. At the same time, the ends of the severed tendons (especially the central ones) retreat far to the sides due to muscle contraction, and finding them often presents great difficulties. Along with injury to the flexors, damage to the immediately passing vessels and nerves is always possible. While the vessels (arteriae and venae radiales and arteriae and venae ulnares) make themselves known by severe bleeding that forces the victim to immediately consult a doctor, nerve and tendon injuries remain unnoticed. Hence it is clear that in any injury in the region of the radiocarpal joint, it is necessary to make an accurate diagnosis, i.e., to navigate the concomitant injuries of deeper-lying organs. Tendon injuries can be judged by the loss of function of the corresponding fingers, and nerve transection by the loss of sensitivity. Once and for all, the unjustified probing of such a wound must be abandoned. It gives nothing to the examiner, but gives suppuration to the patient. Damage to the articular capsule with penetration into the joint and damage to the bones, possible in deep wounds (especially from the dorsal side), will be discovered during the wound toilet itself, which must be undertaken upon delivery of the patient to an institution where the wound toilet can be performed in an appropriate, sufficiently aseptic setting (outpatient clinic, admission ward, hospital). If the wounded person reaches the doctor no later than the first day after the injury, primary wound toilet should be performed immediately by excision and freshening of its edges. A thorough examination of the wound performed after this, in conjunction with the preceding examination of function (movements and sensitivity of the fingers and hand), will give an exact idea of which organs (tendons, nerves) are damaged. Widening of the wound, necessary for finding the ends of the tendons, will provide an opportunity to verify damage to the joint itself and the corresponding bones. After excision of the edges, thorough examination, and arrest of bleeding, one should proceed to finding and suturing the tendons and nerves, and then to layer-by-layer closure of the articular capsule. When finding and suturing the ends of the tendons of the long flexors, one should remember the position of the median nerve, which differs from the nearby shiny tendons by a matte color and a special structure on cross-section (cases of erroneous suturing of the median nerve to a tendon have been described; Hesse and others). Finding the ends of severed flexor tendons sometimes presents great difficulties, and therefore this task should not be undertaken either in an insufficiently aseptic setting or by a physician who does not possess the appropriate technique and knowledge of anatomy. Primary suture of tendons and nerves in the region of the radiocarpal joint, with correctly performed primary wound toilet (during the first day), is the method of choice. In incised wounds and machine injuries, it is necessary to excise all crushed and mangled tissue areas especially carefully and completely, and in intra-articular bone injuries, not to hesitate with their partial resection (see Tendon suture, Wounds, Injuries). Gunfire wounds of the radiocarpal joint present a great danger 1) in connection with anatomical destructions of functionally important organs, often not corresponding to the small size of the external wound, and 2) due to favorable conditions for the development and spread of infection in the region of the radiocarpal joint. The narrow and long wound tract in a gunfire wound of the radiocarpal joint usually does not provide the possibility, due to anatomical conditions, to sufficiently radically excise the edges and bottom of the wound and perform its proper treatment, without which the application of a primary suture is unacceptable. Therefore, in gunfire wounds of the radiocarpal joint, expectant treatment without the application of a primary suture is recommended. In vascular injury, widening of the wound and ligation of vessels. In cases of developing inflammatory or purulent processes, timely incisions, with subsequent treatment by baths and passive hyperemia. As for closed injuries, the radiocarpal joint is particularly often subjected to contusions—upon a blow or shock, which is accompanied by hemorrhages, intra-articular or only into the soft tissues surrounding the joint. In both cases, clinically there is a tumor, edema, and temporary limitation of mobility. Unsuccessful turns of the hand, lifting an unbearable load, pulling on the hand in children gives a sprain (distorsio) of the radiocarpal joint. Such a sprain of the articular capsule is accompanied by rupture and tearing of the auxiliary ligaments of the radiocarpal joint. Clinically, distorsio of the radiocarpal joint is expressed by slight swelling and sharp pain upon pressure and movement. A less sharp tug, shock, or twist usually causes dislocation in other joints, but the radiocarpal joint (as well as the ankle joint) does not yield dislocation thanks to the extreme strength of the collateral ligaments. In these cases, as for example in a fall on an outstretched hand, a fracture of the radial epiphysis and the styloid process of the ulna occurs. As a rule, dislocation of the hand in the radiocarpal joint is accompanied by a fracture of the radius in loco classico. These fractures of the radius can be considered as an intra-articular fracture, since it occurs below the attachment of the capsule, and the interarticular cleft of the radiocarpal joint communicates with the corresponding pouch of the capsule located between the radius and the ulna. As for intra-articular fractures of the small bones of the radiocarpal joint, before the existence of X-rays they were diagnosed extremely rarely. At present, X-ray images (see separate table, pages 371-372, figure 8) make it possible to detect fractures of these bones where previously only distorsio was thought of. Most often, typical fractures of the navicular bone and dislocation of the lunate bone occur. According to large statistical summaries, fractures of the navicular bone account for 1 to 2% of all fracture cases. Clinical signs of fracture of the navicular bone: swelling and smoothing of the folds in the region of the anatomical snuffbox and sharp pain upon pressure in the same region; upon pressure on the heads of the I, II, and III metacarpal bones, pain is transmitted along the axis of these bones to the region of the fractured navicular bone. All these signs should force the attending physician to subject the patient to an X-ray examination, which can finally establish the differential diagnosis between distorsio and a fracture of one of the small bones of the radiocarpal joint. A transverse fracture of all the small bones of the hand can occur when the hand and forearm get caught between rollers. (For more details on carpal bone fractures, see Hand.) Acute inflammatory processes arise in the radiocarpal joint 1) as a result of the introduction of infection with direct damage to the radiocarpal joint (penetrating wounds, stab and gunfire wounds); 2) upon the transition of inflammatory and purulent processes from surrounding tissues (from the hand or forearm); 3) as metastatic foci in a generalized process—in pyemia, general sepsis, scarlet fever, and other infectious diseases; phlegmons of the hand and forearm, tenosynovitis, osteomyelitis of the radial epiphysis, etc., acquire a particularly formidable character upon transition to the radiocarpal joint. Purulent processes, which are a frequent complication of injuries to the fingers and hand, spreading along the subcutaneous tissue, infect the entire region of the radiocarpal joint, causing a sympathetic inflammatory process in the joint itself. Of particular danger are purulent inflammations of the tendon sheaths, especially of the I and V fingers, which pass under the volar carpal ligament and are also in contact with the articular capsule; such purulent processes can easily spread to the joint as well. The capsule is destroyed, the cartilages necrose, and severe purulent arthritis of the radiocarpal joint develops. In cases where the etiological moment of purulent arthritis of the radiocarpal joint is osteomyelitis of the radial epiphysis, the process initially proceeds sluggishly, slowly capturing the spongy part of the bone and causing a sympathetic serous effusion in the radiocarpal joint. When the entire radial epiphysis is impregnated with pus, the pus easily penetrates into the joint, and an outbreak of purulent arthritis occurs. Purulent arthritis of the radiocarpal joint clinically proceeds violently with a high temperature. The cartilaginous surfaces of the bones are involved in the process, and necrosis of the adjacent small bones of the hand occurs. The process is serious, requiring wide arthrotomy, and sometimes resection of the joint. Arthritis of the radiocarpal joint associated with osteomyelitis of the radius or multiple flexor tenosynovitis proceeds especially violently; they not infrequently end in amputation of the forearm. In those cases where the limb is successfully preserved by timely incisions (and sometimes with the help of resection), its function remains severely impaired. Destruction of the cartilaginous surfaces of the joint results in its persistent ankylosis, to which is joined complete limitation of finger movement as a result of the death of the tendons (mainly flexors) of the fingers, which are usually involved in the process to a greater or lesser extent. Thanks to timely arthrotomy and a number of additional incisions, it is sometimes possible to save the tendon, but even in the best cases, mobility is severely limited as a result of abundant adhesions, scar tissue, and scars, which are the end result of inflammatory processes in the vicinity of the joints.
In cases where there is an evident possibility of ankylosis in the carpal joint and stiffness of the fingers, appropriate splints should be used immediately to give the hand the correct functional position: dorsal flexion of the hand at an angle of 60° and volar flexion of the fingers at an angle of 60°. Only in such a position, even with ankylosis of the wrist and limited movement, can the hand be used as a working organ. Physical therapy and mechanotherapy after the end of the process are of enormous importance in treating the stiffness of the radiocarpal joint. It must be remembered that prolonged inflammatory processes in the radiocarpal joint lead to changes not only in the tendons, but also in all the bones of the hand and fingers, which is confirmed by X-ray examination—atrophy ( rarefaction) of the bones of the hand and fingers after purulent arthritis. Among acute inflammatory diseases of the radiocarpal joint, gonorrheal inflammation of the radiocarpal joint is quite common. Gonorrheal arthritis of the radiocarpal joint occupies 3rd place among other gonorrhea-arthritides, according to Mockler (Mauclaire), and 2nd place according to Velyaminov, who considers this localization very characteristic of the gonorrheal process. Gonorrheal arthritis of the radiocarpal joint occurs more often in women than in men, most often in the form of serous-fibrinous synovitis with characteristic periarticular infiltration and with damage to the tendon sheaths. Along with the serous-fibrinous form of gonorrheal disease of the wrist joint, the form arthritis gonorrhoica phlegmonosa is encountered with a small effusion and with the concentration of the process around the joint, in the ligamentous apparatus and periarticular tissue. The process is accompanied by softening of the ligaments, looseness of the joint with subsequent subluxation. Among chronic inflammations of the radiocarpal joint, specific diseases should be mentioned: tuberculosis, lues, rheumatism. Tuberculous arthritis of the radiocarpal joint is relatively rare (according to Tikhov, it makes up 6% of all tuberculous arthritides); in men more often than in women. Most often it occurs in the form of synovitis; however, it should be noted that a focal form is also frequently encountered, localized in individual bones, and there is a tendency to fungoid growths, caseous decay, suppuration, and the formation of abscesses and fistulae; the anatomically close relationship between the tendons and the joint capsule causes the frequent transition of the tuberculous process from the radiocarpal joint to the tendon sheaths. The clinical picture corresponds to the picture of fungoid tuberculous arthritis: swelling, thickening of the joint, and pain. Early impairment of finger functions and atrophy of the muscles of the forearm and hand are characteristic. The anamnesis and course facilitate differential diagnosis. The prognosis for tuberculosis of the radiocarpal joint is quite favorable, but in old age the outcome is significantly worse (phenomena of dissemination are possible, e.g., miliary tuberculosis). In terms of restoring working capacity

Figure 9. Puncture of the radiocarpal joint from the dorsal surface at the radial edge of the tendon of the extensor indicis proprius muscle.
the results are extremely unfavorable due to the fact that the finger flexor tendons are involved in the process.—Treatment. Along with conservative methods of treatment of tuberculosis of the radiocarpal joint (immobilization in a functionally convenient position, stagnant hyperemia, quartz lamp treatment, heliostherapy, etc., drug therapy— iodine, iodoform emulsion, creosote, etc.), some surgeons also use surgical intervention methods, in particular resection. Along with proponents of resection in tuberculosis of the radiocarpal joint (König, Ollier, Kocher, etc.), who insist on complete resection of the radiocarpal joint as an operation that provides not only cure but also restoration of working capacity, Garré, Velyaminov, Krasnobaev, and others consider this operation contraindicated specifically in tuberculosis of the radiocarpal joint. Some surgeons use partial resection, scraping of fistulae, combining these methods with drug therapy, heliostherapy, or treatment with fixed bandages. Amputation of the forearm for tuberculosis of the radiocarpal joint is allowed only in cases of a severe generalized process, where there are vital indications; in all other cases, they try to achieve if not the restoration of function (which is far from always possible), then ankylosis in a functionally advantageous position, i.e., maximum restoration of working capacity.—Syphilis of the wrist joint is extremely rare. Velyaminov describes hydrops fibrinosus villosus, a disease easily distinguished from other diseases of the wrist joint by the fact that under no other diseases of the radiocarpal joint is dropsy of this joint, bulging of the capsule, looseness, and relative painlessness of the joint usually observed.—Deformations and deformities of the radiocarpal joint—see Hand. Of other diseases of the radiocarpal joint, ganglion and Kienböck's disease are also found (see). Surgical approaches to the radiocarpal joint. Typical operations on the radiocarpal joint are performed: 1) For inflammatory (purulent) processes: a) puncture, b) arthrotomy, c) resection of the radiocarpal joint. 2) For ankylosis: a) resection, b) arthroplasty. 3) For looseness of the radiocarpal joint (in infantile paralysis and radial nerve palsy): arthrodesis and plastic operations on tendons. 4) Atypical operations—for intra-articular fractures, for fractures and dislocations of the navicular and lunate bones, for tumors, and for other diseases. In view of the large number of tendons adjacent directly to the radiocarpal joint, approaches to it, especially

from the palmar side, are extremely difficult. The most convenient place for penetrating the cavity of the radiocarpal joint is its dorsal surface. For puncture of the radiocarpal joint, the favorite place is the space located at the intersection of the line connecting the styloid processes of the radius and ulna, and the line passing between the long extensors of the thumb and index finger (on the ulnar side of the II metacarpal bone) (Figures 9 and 10).—Arthrotomy of the radiocarpal joint is performed most often from an incision passing on the dorsal surface of the joint; however, in cases where the purulent process associated with purulent tenosynovitis of the flexors predominantly captures the palmar surface of the forearm, one has to go with incisions located on the volar surface of the joint. As a general rule for incisions in this tendon-rich region, after
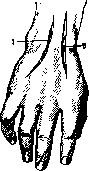

Figure 11.
Figure 12.
Figure 11. Incisions for opening the radiocarpal joint: 1—according to Kocher; 2—according to Langenbeck.—Figure 12. Arthrotomy of the radiocarpal joint according to Langenbeck: 1—dorsal carpal ligament; 2—common extensor digitorum and extensor indicis proprius muscles; 3—extensor carpi radialis brevis muscle; 4—extensor carpi radialis longus muscle; 5—carpal bones; 6—extensor pollicis longus muscle.

Figure 13. Arthrotomy according to Langenbeck: 1—extensor digitorum muscle; 2—lunate and triquetrum bones; 3—tendon of the extensor carpi radialis brevis muscle; 4—navicular bone; 5—radius.
In cases of tuberculosis processes and finally in ankyloses, arthroplasty is performed. Classical incisions. 1. Dorsoradial Langenbeck incision; it begins at the middle of the II metacarpal bone and proceeds along the axis of the limb for 10 cm upward, ending at the middle of the radius epiphysis. 2. Dorsoulnar Kocher incision; it is carried out slightly arched from the middle of the V metacarpal bone along its axis through the middle of the width of the joint and upward for 4–5 cm. After the fascia and lig. carpi dors. are incised, the joint is opened. The edges of the joint capsule are seized with a hook, the ligaments, periosteum, and the tendons lying on it are separated in the ulnar direction. The operation is performed subperiosteally. The soft tissues are retracted in the ulnar direction, after which the ligaments and tendons are separated from the ulnar and palmar surfaces of the joint. The hamulus of the hamate bone is driven in with a hammer, and after the tendons are separated, the small bones of the wrist are skeletonized. The ligaments and tendons of the radial part of the incision are also separated subperiosteally. Kocher pays special attention to preserving the attachment site of the m. extensor carpi radialis on the II metacarpal bone, considering that only this muscle, which supports the bone in the extended state, cannot be replaced in case of its loss. Having thus separated the joint ends subperiosteally from the tendons and ligaments, the joint can be freely dislocated and the joint ends sawed off. 3. Maisonneuve and Titze perform a resection incision not on the side but in the middle along the axis of the limb. 4. Other authors (Lister, Bourgery) open the joint with two incisions from opposite ends of the joint. The advantage of these incisions is that they are technically simple and lie far from the aforementioned dangerous sites. The Bourgery incision, starting from the styloid process of the ulna, is carried upward for 5–7 cm, passing layer by layer between the flexor and extensor muscles of the hand. The incision reaches the bone. After the periosteum is removed all around, the epiphyseal end of the ulna is sawed off with a Gigli saw and removed. The same is done on the radial side, the second incision passing between the m. extensor carpi radialis and the m. supinator longus. After partial removal of the radius and ulna, access to other parts of the joint is easily obtained, and by dislocating the articular surface of the carpal bones into the wound, it can be scraped, trimmed, or sawed off. The simple Bourgery technique provides good access to the joint and spares the tendons. In cases where resection was performed for ankylosis of the radiocarpal joint and the goal of the operation is to restore mobility of the radiocarpal joint, arthroplasty is added to the resection. After resection, the bone ends are covered with a freely transplanted strip of broad fascia of the thigh or a piece of fat is placed between the newly formed joint ends. The success of the operation depends: 1) on asepsis, 2) on whether the newly formed joint space is wide enough, and 3) on whether movements in the radiocarpal joint were started in time. After arthroplasty of the radiocarpal joint, some authors apply traction, others place a fixing bandage for the first 1–11/3 weeks after the operation; but the whole point is to start movements as early as possible, systematically continuing them for several months. Subsequent movements, gymnastics, physio- and mechanotherapy are indispensable conditions for the success of radiocarpal joint arthroplasty. Arthrodesis-fixation of the radiocarpal joint is performed for laxity of the radiocarpal joint, for a hanging hand, which is most often a consequence of infantile paralysis. Since the most favorable position of the hand in terms of function is dorsal flexion, it is usually desired to give the hand a position of dorsal flexion and, having achieved ankylosis, to keep the hand in that position. To achieve ankylosis of the radiocarpal joint, there are several methods: open the joint with one of the resection incisions, dislocate it, and, removing the joint ends with a knife and a sharp spoon, expose the bone surfaces of the wrist and forearm, after which the hand is fixed in the desired position for a long time. However, it is not always possible to obtain a stable ankylosis in this way. In these cases Spitzy applies osteoplastic operations, driving a transplant from the tibia through the styloid process of the ulna and through all the carpal bones. Wittek inserts a bone transplant into a bony groove which he makes on the dorsal surface of the radius, wrist, and at the base of the first metacarpal bone. However, experience shows that these bone transplants also often break or are resorbed. Other authors try to achieve stable fixation of the hand in dorsal flexion through plastic operations on the tendons: shortening the extensors and simultaneously transplanting healthy flexors to the place of the paralyzed extensors. However, these operations do not always achieve the goal. Then the help of a prosthesis is resorted to, which, embracing the hand like a cuff, holds it in the required position without interfering with work, by V. Gorinievsky.
Related articles
Mentioned in
Cite this page
“Radiocarpal Joint.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/radiocarpal-joint/