Patella
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the first edition of the Great Medical Encyclopedia covers the anatomy, development, blood supply, innervation, and pathology of the patella, with a primary focus on fractures and their clinical presentation.
Encyclopedia article (1928–1936)
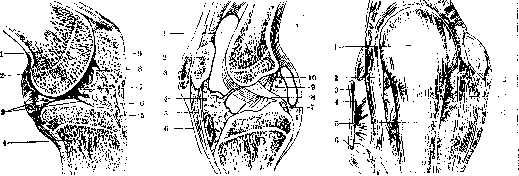
PATELLA. Anatomy of the Patella. The patella, or kneepan, patella, is a flat, rounded bone embedded as a sesamoid bone in the tendon of the quadriceps muscle in front of the lower end of the femur. The anterior surface of the patella is convex, rough, with numerous vascular foramina, and covered by periosteum; the posterior, articular surface (facies articularis) is for the most part covered with cartilage and divided by a low ridge into two unequal facets—a larger lateral and a smaller medial one; the upper end of the patella, the base (basis patellae), is wide and slightly sloped from above downwards and from behind forwards; the tendon of the quadriceps muscle of the thigh attaches to this end; the lower end of the patella, the apex (apex patellae), is slightly elongated; the patellar ligament (ligamentum patellae) attaches to it; the two borders of the patella, lateral and medial, are slightly pointed; the lower bundles of the broad muscles of the thigh attach to them. When the leg is straightened at the knee, the patella is located on the articular surface of the femoral condyles, on the so-called facies patellaris; during flexion, the patella moves downwards and somewhat backwards, coming to lie in front of the intercondylar fossa (Fig. 1–6). The patella belongs to the class of short bones and, like all such bones, consists in the center of spongy bone covered at the periphery by compact bone, which is thicker on the anterior surface than on the posterior. The patella develops as a short bone: up to the age of two, the patella is merely a cartilaginous nucleus; by two years of age (sometimes earlier, at one year, or sometimes later—at 3–5 years), a center of ossification appears within its substance, growing in all directions, though somewhat faster posteriorly; ossification of the patella is completed by 15 or even 20 years (Testut). The patella receives its blood supply from the arterial network of the knee, specifically from its anterior part, from the so-called prepatellar arterial circle (cercle artériel prérotulien, Testut), formed by four articular branches of the popliteal artery (a. poplitea), the superior genicular artery (a. genu superior), and the recurrent branch of the anterior tibial artery (a. tibialis anterior). The nerves of the patella are derived as branches of the saphenous nerves and sympathetic branches accompanying the arteries. Pathology of the Patella. Congenital anomalies of the patellar apparatus—see Knee Joint; an increased number of patellae (patella bipartita), described by Gruber, occurs in rare cases and is even bilateral; Petty describes a case where there were two patellae in each leg, one located above the other; each pair was subsequently sutured into a single bone with a good functional result. Fracture of the patella is not frequent (1–2% of all fractures) and occurs almost exclusively at an age over 30; fractures of the patella are not seen in children, probably due to its softness. Fractures are observed three times more frequently in men than in women. Fractures of the patella are usually transverse; the fracture line typically runs from above and laterally downwards and medially; longitudinal fractures are described as a great rarity; patellar fractures occur no higher than the middle of its height, usually below it; the lower fragment may in turn break into several pieces—in which case the fracture line will be stellate. All this depends on the mechanism of injury—direct trauma to the patella or indirect trauma, the so-called avulsion fracture of the patella.
Fig. 1
Figure 2.
Figure 3.
Fig. 1. Right knee joint (sagittal section): 1—condylus lat. femoris; 2—capsula articularis; 3—meniscus lat.; 4—condylus lat. tibiae; 5—bursa infrapatellaris profunda; 6—lig. patellae; 7—plica alaris; 8—cavum articulare; 9—patella.
Figure 2. Sagittal section of the knee joint: 1—bursa suprapatellaris; 2—patella; 3—bursa praepatellaris subcutanea; 4—anterior fat pad of the joint capsule; 5—lig. patellae; 6—bursa infrapatellaris prof.; 7—medial tubercle of eminentia intercondyloideae; 8—lig. cruciatum post.; 9—posterior fat pad of the joint capsule; 10—lig. cruciatum ant.
Figure 3. Knee joint from the front: 1—patella; 2—retinaculum patellae lat.; 3—m. biceps femoris; 4—lig. collaterale fibulare; 5—lig. patellae; 6—lig. capituli fibulae; 7—lig. collaterale tibiale; 8—retinaculum patellae med.; 9—capsula articularis.
injury—direct trauma to the patella or indirect trauma, the so-called avulsion fracture of the patella. Fractures of the patella are divided into complete, through the entire thickness of the patella, and incomplete; an incomplete fracture of the patella may manifest as a bone crack without displacement of fragments; fragments of the patella may lie freely in the joint (Volkovich). When the patella fractures, the fragments separate to varying degrees due to the pull of the quadriceps muscle: with a small rupture of the extensor tendon of the leg, the separation of the patella fragments will be insignificant; otherwise, the fragments will separate far—up to 15 cm or more. The fracture lines of the patella and the rupture of the extensor tendon of the leg usually do not coincide; the latter runs higher, creating a flap of soft tissues that can interpose between the patella fragments and thereby become an insurmountable obstacle (without surgical intervention) to the healing of the fragments. When the patella fractures, the synovial membrane of the joint ruptures and causes significant hemorrhage into the joint; the joint increases in volume, and the patella fragments, under the influence of increased intra-articular pressure, separate even further and rotate forwards along the fracture line; the blood poured into the joint penetrates into the soft tissues of the thigh upon rupture of the upper pouch of the joint capsule, and upon rupture of the prepatellar bursae, it fills them as well, producing the picture of prepatellar bursitis. Palpation of the knee reveals a transverse groove on the anterior surface of the patella and a difference in height between the injured and healthy patellae compared to the healthy knee, with the former standing higher; fracture of the patella can be determined by the crepitus of fragments rubbing against each other; in cases of significant separation of fragments, a transverse depression is visible to the naked eye on the anterior surface of the knee, at the bottom of which the femoral condyles can be palpated directly beneath the skin; easy displaceability of the fragments, especially the upper one, completes the clinical picture of a patellar fracture. In general, the picture of a patella fracture is in most cases so clear that radiography can only confirm what has been elucidated by conventional methods of examination. Immediately after a patella fracture, some patients can still get up and take a few steps with difficulty, while extension of the leg at the knee is hampered alongside freer flexion; simultaneously, the ability to lift the leg at the hip joint is impaired (Volkovich); the knee is held somewhat flexed; the leg extensor is significantly weakened during a patella fracture, which manifests in a standing patient as an unexpected buckling of the leg at the knee. Prognosis in patella fracture depends on the following factors: 1) to what extent the quadriceps muscle has retained its strength and whether far-advanced atrophy has set in; 2) how much time has elapsed since the fracture: the shorter it is, the greater the chances of success; 3) the degree of fragment separation: the smaller it is, the more grounds there are to expect a good outcome of treatment; 4) whether there are complications in the fracture of the patella, accompanying damage to the soft parts of the joint, massive hemorrhage into the joint, interposition of soft tissues between the fragments, etc.; 5) whether treatment has been conducted correctly and systematically.
Figure 4.
Figure 5.
Figure 6.
Figure 4. Bursae of the patella: 1—tractus iliotibialis (Maissiat); 2—bursa praepatellaris subcutanea; 3—bursa infrapatellaris subcutanea; 4—bursa subcutanea tuberositatis tibiae. Figure 5. Ligaments of the patella: 1—lig. patellae; 2—retinaculum patellae laterale; 3—tractus iliotibialis; 4—tuberositas tibiae; 5—tendo m. sartorii; 6 and 7—retinaculum patellae mediale; 8—m. vastus medialis. Fig. 6. Ligaments and bursae of the patella: 1—patella; 2—lig. patellae; 3—bursa m. sartorii propria; 4—divided m. sartorius; 5—bursa anserina; 6—insertion of mm. gracilis and semitendinosi; 7—meniscus medialis; 8—retinaculum patellae mediale.
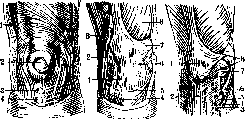
Methods of treating patellar fractures fall into conservative and operative categories, depending on the nature of the fracture and the injury to the tendon of the rectus femoris muscle. If the latter is not ruptured and the separation of the patellar fragments is insignificant, a conservative method of treatment can be applied. In the period immediately following the fracture, it is necessary to straighten the leg at the knee and ensure the elimination of hemorrhage in the joint, for which rest and a pressure bandage on the joint are used; if the blood is not absorbed within about half a month, joint puncture is indicated for the purpose of extracting the blood; it is never possible to remove all the blood due to its clotting, but it is sufficient to remove a significant portion of the blood and thereby relieve the joint capsule from the high intra-articular pressure that is harmful to it. Rest must not be prolonged; after only 2-3 days, massage of the muscular apparatus is initiated, and in 2-3 weeks, one transitions to active and passive movements of the knee joint, striving to get the patient back on their feet. Volkovich recommends using a supporting cardboard-plaster splint to maintain the function of the extremity and its nutrition; this splint is positioned as a strip 3-4 fingers wide along the posterior surface of the leg from the upper third of the thigh to the lower third of the lower leg; the splint is placed over a carefully applied lining bandage; the leg is given a slightly bent position at the same time. Great success should not be expected from variously applied gauze or adhesive plaster bandages (most often in a figure-eight shape), except perhaps with a very insignificant separation
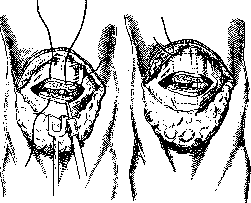
Figure 7.
Figure 8.
Figure 7. Passing of the threads when suturing the patella. Figure 8. U-shaped suture of the patella. of the patella fragments. - The second group of methods for prolonged approximation of the fragments involves the use of instruments; such instruments include Malgaigne's clamp; the points of the clamp are driven through the skin into the patella fragments, which are then approximated by turning the clamp screw; now hardly anyone uses this method, since without opening the joint it is almost impossible to achieve complete approximation of the fragments, if only due to the possibility of soft tissue interposition between the fragments. With a simultaneous rupture
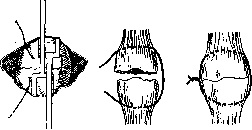
Figure 9.
Figure 10.
Figure 11.
Figure 9. Tying of the threads. The fragments are held by blunt hooks. Figures 10 and 11. Peripatellar suturing with wire and tying it. of the quadriceps tendon and significant separation of the patella fragments, treatment can only be surgical, especially since it is immeasurably easier to approximate and unite the fragments by operative means. The operation of suturing the patella is performed through an incision that opens access to both fragments, crafting a flap with the base pointing downward so that the skin scar is removed from those parts of the knee that touch the floor when kneeling, and does not coincide with the line of the fracture and sutures of the patella and ligamentous apparatus; after opening the joint, blood clots are removed and soft tissues trapped between the fragments are freed; two holes are drilled in both fragments if the threads are to be passed through the thickness of the patella; the fragments are approximated with various instruments (bullet forceps, blunt hooks placed behind the upper edge of the upper fragment and the lower edge of the lower fragment), sutures of thick silk or bronze-aluminum wire are passed; the sutures are tied with obligatory instrumental approximation and retention of the fragments, otherwise, when trying to approximate the fragments by tightening with the sutures, the latter may break or cut through the holes in the patella (Figures 7-12). Catgut sutures are applied to the ruptured parts of the joint capsule and ligamentous apparatus on the sides and on the anterior surface of the patella. Skin suture. Plaster splint bandage on the posterior surface of the leg, as described above; after 15 days, cautious active and passive movements; light massage of the thigh. The best method of suturing the patella must be recognized as suturing by applying a peripatellar suture, since in this case there is no need to make holes in the bone and subject it to the risk of an additional fracture when making the holes. In chronic patellar fractures with a large separation of fragments, it is impossible to approximate them without special techniques that facilitate the approximation of the fragments - plastic lengthening of the quadriceps tendon or partial tenotomy of the patellar ligament. The entire operation of suturing the patella must proceed under very strict asepsis. The results of blood treatment for patellar fractures speak in favor of this
on the patella. Active methods of treatment yielded a 1% mortality rate and almost as many recurrences; conservative methods yielded a 3% mortality rate and about 15% recurrences (Sozon-Yaroshevich). Dislocations of the patella (luxatio patellae) belong to the category of rare injuries (0.6–0.7%). Displacement of the patella is observed mainly outward (luxatio patellae externa); the cause of such a dislocation is either external direct violence or muscular pull; the patella in this case protrudes outward from the lateral condyle of the femur and faces its posterior surface toward the femur; the joint capsule in this dislocation ruptures, hemorrhage into the joint and its swelling occur; the functional disorder of the knee is significant, the knee is in a position of genu valgum and slightly flexed. The prognosis in fresh cases is favorable. Treatment consists of reduction of the patella, easily accomplished by flexing the leg at the hip joint to relax the quadriceps muscle, extending the knee, and pressure on the kneecap; sometimes anesthesia is required. For several days (no more than 8–10), the leg is placed in a splint, and then massage, active and passive movements in the knee are initiated. - Inward dislocation of the patella (luxatio patellae interna) is a great rarity. A further degree of displacement of the patella is its position with a raised edge, a position on the ridge, which is placed between the condyles of the femur, while the surfaces of the patella face sideways. Such a dislocation is called vertical (luxatio patellae verticalis); the patellar ligament is twisted; the leg is sometimes extended, sometimes flexed; complete functional disorder is noted. Reducing the patella is not easy, and sometimes it is necessary to resort to open reduction via arthrotomy. With an even greater rotation, the patella turns to face forward with its posterior surface; this is a rotational dislocation of the patella (luxatio patellae rotatoria). Such a dislocation results from very great violence and probably a longer patellar ligament than usual. The joint capsule in this case ruptures on both sides of the patella with significant hemorrhage into the joint. The function of the joint is completely disrupted. Reduction presents the usual difficulties of reducing a dislocated patella. - The rarest dislocation is horizontal (luxatio patellae horizontalis). The patella lies in a transverse position, with its articular surface facing downward toward the tibia or upward toward the femur, positioned in the joint space. The cause is significant direct violence; simultaneously, the integrity of the integuments, ligamentous apparatus, joint capsule, etc., may be compromised. Upon palpation of the joint, the patella is not in its usual place, but a transverse bony ridge, the edge of the patella, protrudes from the joint space. Reduction of such a patella dislocation is performed under anesthesia; if conservative reduction fails, one has to resort to the open method. In all cases of patella dislocation, radiographs make it possible to more accurately diagnose both the position of the patella itself and possible concomitant joint injuries. Habitual dislocations of the patella (luxatio patellae habitualis) are recurrent dislocations in cases where good restoration of the integrity of the damaged tissues did not occur during the first dislocation, or in individuals with weak musculature and a valgus knee. Dislocation occurs very easily, it is only necessary to bend the leg at the knee or simply push the patella with the hand. These dislocations are just as easily reduced. (For surgical methods of patella fixation, see Knee joint.) In the surgical treatment of habitual dislocation, which consists of transferring the tibial tuberosity 1.5–2 cm inward and fixing the transferred bone in a new place with a nail or a careful periosteal suture, it is necessary to take into account the possibility of an even greater disruption of leg function in the knee in case of failure, i.e., in the case of poor fusion of the transferred tibial tuberosity: at the very first strong extension of the leg in the knee, during a jump, etc., the tibial tuberosity is torn off its new place, and the patella moves high upward; atrophy of the quadriceps muscle sets in due to the absence of the attachment of its lower tendon. In exceptionally stubborn cases of habitual dislocation of the patella with a sharply expressed genu valgum, supracondylar osteotomy of the femur is proposed (Broca and Monod). Primary, isolated lesions of the patella. Infectious osteomyelitis of the patella (osteomyelitis patellae infectiosa) is a rare (2%; Creite) disease, expressed in the development of a suppuration focus in the anterior section of the bone, with a stormy course; in this case, pus usually breaks outward anteriorly or along the course of the quadriceps tendon into the soft parts of the thigh. The knee joint may be involved in the process secondarily. The process sometimes ends with a central sequestrum and a fistula (Creite). In the absence of knee involvement, the picture of a lesion of the anterior section of the knee emerges: severe general condition, young age, stormy onset, median position of the focus of greatest painfulness; on the X-ray in acute cases, only an unclear pattern of bone structure. In the absence of a rupture of the inflammatory process into the joint, the prognosis is favorable. Treatment reduces to opening the focus and careful removal of the affected area with a sharp spoon, so as not to open the joint cavity. The wound can be sutured tightly. Rest. In chronic osteomyelitis, it is better to remove the entire bone. - Tuberculosis of the patella (tuberculosis patellae) is even rarer (0.1%, Tikhov). Women are affected more often; no age predisposition is noted; tuberculosis of the patella manifests in two forms: periosteal and osteomyelitic (central). The first form is rarer; the process is usually localized in the anterior section of the patella, with the periosteum thickened, forming a cold abscess; upon rupture into the joint, secondary gonitis occurs. The osteomyelitic form of patella tuberculosis is observed more frequently; the process nests in the deep posterior parts of the patella; from here pus can penetrate into the joint or forward to the external integuments; the bone is usually destroyed; on the X-ray: the bone is rarefied (rarefying ostitis) or the picture of a cavity with uneven contours in the case of the formation of fungous masses, or finally, typical tuberculous sequestra. The clinical picture of patella tuberculosis has no sharp features; the most constant sign is fistulas, then a swelling of the anterior part of the joint, while its lateral and posterior sections are normal. The integuments in front are tense, shiny, or ulcerated. Joint movements are not severely impaired. The prognosis in an isolated tuberculous lesion of the patella is favorable until the process has spread to the knee joint. The best method of treatment must be recognized as the complete removal of the patella, especially since such an intervention relatively little impairs the function of the extensor apparatus of the leg. - Isolated syphilitic lesion of the patella (lues patellae) is not frequent; the process manifests in gummous destruction of the bone. Diagnosis is based on anamnestic data, the Wassermann reaction, and fluoroscopy: the femur and tibia are healthy, the contours of the patella are blurred, especially the upper one, the entire bone is rarefied, and its rarefied areas appear as numerous small foci (Kitayevsky, Tikhonov). The clinical picture of syphilis of the patella reduces to signs of bone lues; sometimes it is clearly expressed, and sometimes it becomes clear only after prolonged observation. Treatment is specific; in the presence of extensive destruction, surgical methods are indicated. Tumors of the patella. Benign tumors of the patella are very rare; among them are fibroma, developing from the anterior surface of the patella, osteoma, and chondroma. Osteoma usually develops on the anterior surface of the patella; some authors consider inflammatory processes to be the etiological moment of osteoma formation, thereby classifying osteoma as hyperostoses, periostitis; cases of undoubted bone tumors are also known (Bull). Accurate diagnosis is based mainly on X-rays. Treatment is surgical—chipping off the tumor. Malignant tumors of the patella, sarcomas, are more common. The clinical picture of patella sarcoma is uncharacteristic; a small tumor can be confused with knee tuberculosis; at large sizes, it is difficult to settle on a diagnosis of sarcoma of the patella alone, and this is of no significant practical interest, since the prognosis for sarcoma of the patella alone or the entire knee is equally dismal, and treatment will differ initially only quantitatively in terms of the breadth of the tissues removed. The patella is removed along with the surrounding tissues, or the operation immediately consists of amputation of the thigh, depending on the general condition of the patient.
Related articles
Mentioned in
Cite this page
“Patella.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/patella/