Breech Presentation
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This historical encyclopedia article from the 1930s details the diagnosis, mechanism, and management of breech presentations and multiple births during labor, outlining complications such as cord prolapse and outlining obstetric interventions.
Encyclopedia article (1928–1936)
The back always turns such that the bent upward leg is located posteriorly, and the fallen-out leg anteriorly. Diagnosing this is not always easy. Some of the main causes are: narrow pelvis (especially in primiparae), multiple pregnancy, hydramnios, pendulous abdomen, placenta previa, hydrocephalus—in a word, all factors that either hinder the fixation of the head in the lower uterine segment or give the fetus great mobility. The diagnosis of breech presentations, as with cephalic ones, is made on the basis of external and internal examination. Upon external examination, the head is palpated in the uterine fundus as a dense, round, ballotable, mobile body; above the symphysis, a more voluminous, uniformly dense, non-ballotable presenting part is determined. High standing of the uterine fundus (at the scrobiculus cordis) is characteristic of frank breech presentation. The heartbeat is auscultated corresponding to the position (on the left for the first, on the right for the second), above the navel, at the level of the fetal shoulder. Upon internal examination, a soft, voluminous presenting part is palpated, without sutures or fontanelles. When the pelvic end stands above the pelvic inlet, the presenting part is poorly accessible to examination. After rupture of the amniotic sac and with sufficient dilation of the uterine os, the anus and the sacrum with its crista sacralis media can be determined. The coccyx and the cleft between the buttocks are the most characteristic signs of a breech presentation (Fabre). Due to the birth tumor, it is not always possible to clearly recognize the external genitalia of the fetus. In footling presentation, it is important not to confuse feet with hands (pay attention to the calcaneus, short toes, and the round contours of the knee with a mobile patella). The position and its variety in a frank breech presentation are determined by the position of the sacrum and the genitalia of the fetus: the back of the fetus faces the side where the sacrum is palpated; in footling presentations, the position and variety of position are also recognized by where the heels of the fetus are directed. How to distinguish a frank breech presentation from a face presentation has already been mentioned above. Course of labor: In the dilation stage, unlike cephalic presentations, premature rupture of the amniotic sac with prolapse of small parts and the umbilical cord is more common. To prevent early discharge of waters, the parturient woman must observe bed rest during the dilation stage. The expulsion stage differs significantly from that in occiput presentations, primarily because the head in breech presentations comes not first, but last. Due to this, the soft birth canal is not sufficiently dilated (in this respect, footling presentations have the worst prognosis), which leads to tears (of the cervix, perineum), arm entrapment, head entrapment, etc. Finally, with the aftercoming head, the umbilical cord is inevitably and obligatorily compressed (asphyxia of the infant). Mechanism of labor: The fetus enters the pelvis in one of its oblique diameters with its linea intertrochanterica. If the back is turned more posteriorly, the buttocks pass in the right oblique diameter; if anteriorly, in the left oblique. With the development of uterine activity, the buttocks descend lower and lower, with the anterior buttock as a rule descending lower than the posterior, i.e., it is the leading point (the birth tumor is also located on it). On the pelvic floor, the buttocks already stand in the direct diameter: one anteriorly, the other posteriorly. The mechanism of expulsion occurs as follows: through the vulvar ring, the anterior buttock is the first to emerge, which is fixed under the pubic arch in the region of the iliac bone (hypomochlion); around this point of fixation, the pelvic end is born, and the spine makes a very strong lateral bend. The torso passes through the vulva in the direct diameter. After the birth of the fetus up to the navel, the rest of its body is usually born in 2-3 contractions. First, the chest emerges with the arms crossed over it, and then the anterior shoulder appears under the symphysis, while the posterior one at this moment rolls over the perineum. The head during the emergence of the shoulders stands on the pelvic floor in its oblique diameter and immediately passes into the direct diameter. As soon as the suboccipital fossa (hypomochlion) appears in the genital cleft, it is fixed under the pubic arch, and the chin, face, and forehead roll over the perineum. In the expulsion stage, the role of the physician in breech presentations until the birth of the fetus to the navel is passive and observational. After the birth of the fetus to the navel, asphyxia may occur (the head engaging in the pelvis at this moment inevitably compresses the umbilical cord) if the birth of the head is delayed for any reason. The physician must stand ready with disinfected hands in case of the need to render so-called manual aid (see Obstetric manual maneuvers). Of all types and varieties of breech presentations, the most unfavorable for the management of labor is the frank breech presentation. In prolonged labors (especially in primiparae with rigid soft parts), it is often necessary in the interest of the fetus to resort to extraction by the pelvic end. This operation in frank breech presentation represents one of the most difficult in operative obstetrics (see Obstetric manual maneuvers). Some authors suggest for these types, when the buttocks are still above the pelvic inlet, prophylactically bringing down a leg so as to have a support point in the brought-down leg during subsequent extraction by the pelvic end (if it is needed). Previously, this technique was very widespread. At present, it is far from being used by all. Prophylactic bringing down of the leg in frank breech presentation is performed by the majority of obstetricians only according to specific indications. Prognosis: In breech presentations, in view of the complications indicated above, the prognosis is significantly worse than in occiput presentations. Maternal mortality is on average 5% higher than that in cephalic presentations. Multiple births. The recognition of twins (practically, one can only speak of them) presents great difficulties at all stages of pregnancy (see Multiple pregnancy). With the onset of labor, the diagnosis in multiple pregnancy is somewhat facilitated (the presence of two amniotic sacs, Naegele inclination in the absence of a narrow pelvis, palpation of one or another part of the fetus next to an intact sac), but nevertheless in difficult cases, if one does not resort to radiography, it often remains in great doubt. "There is only one sure way to know if a woman is pregnant with twins," said Capuron (Capuron), "that is when you see that one child is born and another is felt in the abdomen." The course of labor in twins also presents certain distinguishing features. In the dilation stage of multiple births, we have a slower course, uterine inertia, irregularity of contractions, poor formation of the amniotic sac, and often premature discharge of waters with prolapse of the cord and small parts. The role of the obstetrician in the dilation stage comes down, as in normal labors, to observing the character of labor pains (strength, rhythm), the heartbeat of the fetuses, the temperature and pulse of the parturient woman, and the state of the bladder and rectum. Complications during the expulsion stage are observed more often and more seriously in twins. These complications are associated with malpositions of the twins. With a longitudinal lie of both fetuses (which is observed most often) and a normal pelvis, complications are rare, and the mechanism of labor is usually not disturbed. The birth of the first twin occurs normally, sometimes, however, slowly if the fetus is large and its forward movement is hindered due to weak contractions and dry labor. After the birth of the first fetus, the second twin is usually born in 30-40 minutes (cases have been described where the birth of the second twin occurred after 3 weeks, Surovtsev's case), and its expulsion proceeds without any difficulties. The assistance of the obstetrician in such cases is the same as in normal labors (monitoring the heartbeat and protecting the perineum). After the birth of the first twin, it should be ascertained by external and, if necessary, internal examination whether there is a normal lie and presentation of the second fetus, whether there is a presentation of small parts, the umbilical cord, etc. If there are no complications and if 40 minutes have passed since the birth of the first twin (approximately the time necessary for the formation of the second amniotic sac—Fabre), while the amniotic sac remains intact, it should be ruptured, leaving the birth of the second twin to its natural course. It is important after the birth of the first child to carefully ligate the umbilical cord between two ligatures to avoid heavy blood loss in the remaining second twin through the umbilical cord of the first, which can occur in monozygotic twins in the presence of anastomoses in a common placenta. In the presence of dangers threatening the fetus, or with incipient bleeding (premature detachment of the placenta), it is necessary to hasten the expulsion of the second fetus (forceps, version and extraction). In transverse lie (in twins we have breech presentation and transverse lie in 50% of cases, especially in monozygotic twins) and cord prolapse, version must be performed immediately.
A rather serious complication encountered in twins is the simultaneous engagement of both heads in the pelvis (caput occlusivum). The extraction of one twin hinders the passage of the second. As a rule, the first fetus usually dies. It is recommended in these cases to apply forceps to the head of the second fetus and then extract the first. If the first fetus is dead, then upon Küstner's suggestion, to save the second, decapitation of the first twin should be performed. Sometimes the incarceration of both heads can be so strong that only perforation relieves the doctor of difficulty and the woman of danger. In the third stage of labor in multiple pregnancy, one can expectatonic hemorrhage.
M. Malinovsky. III. Mechanism of labor. The mechanism of labor is the aggregate of physical phenomena during labor occurring both in the maternal birth canal and observed on the part of the fetus. These physical phenomena depend on three mechanical systems: 1) the feto-container, which during the birth act with the participation of the abdominal press turns into an expelling apparatus, 2) the birth canal, and 3) the object of labor—the fetus. The entire complex of mechanical phenomena occurring during labor in the interrelations and interactions of the indicated three systems constitutes the mechanics (physics) of labor in the modern understanding. By the beginning of labor, the fetus lies in the longitudinal-oval feto-container in such a way that its longitudinal axis coincides with the long axis of the maternal body, and hence with the long axis of the feto-container, and in the overwhelming majority, the cephalic end of the fetus faces its lower pole (correct longitudinal lie of the fetus). The interrelation of the individual parts of the fetus is such that the head is in an unconstrained state, intermediate between flexion and extension. The spine is moderately flexed forward, by virtue of which the trunk is concave on the abdominal side. The limbs are located on the anterior surface of the fetus, with the legs pulled toward the abdomen, being flexed at the hip and knee joints, and the arms crossed on the chest. With a large amount of amniotic fluid, the small parts are located more freely; with a small amount, they adhere more closely to the trunk, as a result of which the fetus assumes a typical ovoid shape. The head in the cervical part of the spine is not turned relative to the trunk. As a result, we have the correct attitude of the fetus. The relation of the back of the fetus to the inner surface of the uterus characterizes its position. From the moment a close mechanical relationship is established between the presenting head and the pelvic inlet, one speaks of presentation—occipital or other. In multiparae at the beginning of labor, and in nulliparae mostly already in the last weeks of pregnancy, the head enters the space of the pelvic inlet, which represents the upper aperture of the bony birth canal and has a transverse-oval Figure 31. Primipara. Beginning of the expulsion period. The head in a state of moderate flexion, movable still above the pelvic inlet. The anterior part of the cranium and occiput stand approximately at the same height.
"transverse-oval shape, with the largest transverse diameter and the smallest direct one." The longitudinal oval of the head is inserted into the transversely oval pelvic inlet either strictly transversely or somewhat obliquely (correct high transverse or oblique position of the head), and at the beginning of this process, the head stays in its indifferent, intermediate between flexion and extension state (Fig. 31). Even in nulliparae, in whom the head stands already at the end of pregnancy
Figure 32. Axial, or synclitic insertion of the cranium.

in the pelvic inlet, the head usually retains the indicated middle position, which has been proven by Warnekros radiographically. Nevertheless, there is no doubt that in a number of cases, the head turns out to be in a state of more or less pronounced flexion, so that the occipital part of the cranium is located deeper than its anterior section, and the small fontanelle stands significantly lower than the large one. During this process, the sagittal suture is mostly at an equal distance from the anterior and posterior walls of the pelvic inlet, the cranium stands vertically on the plane of the pelvic inlet—synclitic insertion (Fig. 32). However, often the sagittal suture stands extra-medially, located closer to the sacral promontory—typical anterior asynclitism, Naegele obliquity (Fig. 33). Under the influence of pressure arising in the uterine cavity during labor pains (general intrauterine pressure of Schatz), or the force acting from above from the uterine fundus on the fetal spine (axial pressure) and through the latter on the presenting part, the head advances along the birth canal. Due to the fact that the spine adjoins the base of the skull not at its center, but more posteriorly, toward Fig. 33. Anterior asynclitism, anterior-parietal insertion (obliquity according to Naegele).
the occiput, a two-armed lever is formed, wherein one arm of the lever is shorter (occiput), and the other is longer (anterior section of the cranium). The consequence of pressure on such an unequal-armed lever will be that the short arm of the lever will drop, and the long one will rise: upon pressure on the fetus from above, the occiput drops, sinking deeper into the pelvic cavity, the frontal part of the head lags behind, delayed in its forward movement; as a result, the head passes into a state of strong flexion, the chin is pressed Figure 34. Primipara. Beginning of the expulsion period: head in strong flexion with the occiput lowered downward, the small fontanelle is located at the lower pole of the presenting part, becoming the "leading point"—the first moment of the mechanism of labor occurs—flexion of the head (flexio) (Fig. 34). Flexion
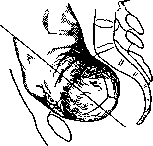
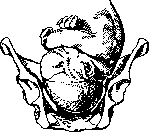

ion of the head is most simply and easily explained precisely by the action of the two-armed lever. For this, it is necessary to recognize the presence of pressure on the fetal axis (axial pressure, Fruchtachsendruck). If one recognizes only the general intrauterine pressure, then the first moment of the mechanism finds the explanation given by Lahs: with an ovoid placed obliquely on an orifice, according to the laws of motion along an inclined plane, resistance is less at the pole of the ovoid closest to the orifice. Applied to local conditions in labor upon pressure on the head entering the pelvis (ovoid), the occiput (closest pole) encounters less resistance and descends faster than the other pole of the ovoid—the frontal part of the head, i.e., flexion occurs. After the flexion that has taken place in the plane of the pelvic inlet, it is no longer the plane of the head mentally drawn through its direct diameter (planum occipito-frontale) that stands, but the plane drawn through its small oblique diameter, a plane significantly smaller than the first (planum suboccitipo-bregmaticum). In a state of strong flexion, the head descends into the cavity of the lesser pelvis and here rotates around its longitudinal axis so that the occiput, sliding along the lateral wall of the pelvis, is directed anteriorly, toward the symphysis, while the anterior section of the head departs posteriorly, toward the sacrum. During this rotation, the sagittal suture gradually changes its position, passing from the transverse diameter into the oblique (Fig. 35), and from the oblique into the direct diameter of the pelvic outlet (Fig. 36). In cases where the occiput was initially directed laterally and posteriorly (posterior view), the sagittal suture from the oblique diameter of the pelvic cavity passes first into the transverse,
then through the opposite oblique passes into the direct diameter of the pelvic outlet. In the first case Figure 35. Second rotation: the occiput turns forward, the sagittal suture has passed from the transverse into the oblique diameter.
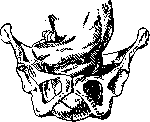
Figure 36. Second rotation completed. The occiput under the pubic arch. The sagittal suture passes in the direct diameter of the outlet. The back in its rotation has lagged behind the head and is still turned somewhat to the left.
in the first case, the occiput moves along an arc of 90°, in the second case of 135°. This movement of the head around its vertical axis, a movement having as its ultimate goal the positioning of the occiput behind the symphysis and the forehead in the sacral hollow with the sagittal suture running straight from front to back, constitutes the second moment of the mechanism of labor—the internal rotation of the head (rotatio capitis interna). Opinions regarding the causes of this movement are contradictory. The "theories of internal rotation of the head" are numerous. The simplest explanation is as follows: advancing through a canal of such a whimsical shape as the pelvic ring, the head encounters planes of different sizes in its various sections. The largest dimension of the pelvic inlet is the transverse, of the cavity the oblique, and of the outlet with a deflected coccyx the straight. For physiological advancement, the head must on its path pass its long axis through the largest dimensions of the various sections of the pelvis, resulting in its internal rotation. Such an interpretation of internal rotation is too simplified, and according to Spiegelberg, this rotation is caused, on the one hand, by the direction of the rami of the ischial bones and especially by the opposition of the prominent ischial spines, which force the part of the head lying anterior to them to turn forward, and the part lying posterior to them toward the sacral hollow; on the other hand, by the resistance of the pelvic floor, which, deflecting the direction of the head anteriorly, acts first of all in this sense on the part of it that lies deepest of all, i.e., on the occiput. Tololinov saw the immediate cause of the rotational movement of the head in the direction of the expulsive forces. The resultant of these forces must pass through the long axis of the fetus, the end of which, with strong flexion of the head, abuts against the occiput. The latter is the main object of the application of expulsive forces and therefore, of necessity, must advance ahead of other parts of the head. Since the posterior, predominantly bony wall of the pelvis is long and sloping, and the anterior is short and below the symphysis presents the least resistance, the occiput turns precisely in this direction.

For a long time, the opinion accepted by the majority of authors was that the decisive factor in the origin of internal rotation is the architecture of the pelvic floor, in particular the levator ani muscle. This muscle, which dome-like encloses the pelvic outlet, has as it were a cleft in it running from front to back along the midline, which space (hiatus) contains the urethra, vagina, and rectum. Advancing toward the pelvic outlet, the head inevitably must pass through the hiatus, positioning its long axis within it, as a result of which the sagittal suture ends up in the straight diameter of the outlet. Some authors (Naegele, Varnier) believe that the force producing the internal rotation of the head lies in the active contractions of the muscles of the pelvic floor. Thus, Stumpf suggests that the musculature of the pelvic floor, experiencing pressure during expulsion from the head standing in the oblique diameter of the pelvis, by its contractions forces the head to turn its occiput directly forward or directly backward, i.e., to place its long axis in the straight diameter of the pelvis.
A number of authors strive to find the secret of the internal rotation of the head in other factors. Thus, Sutugin expressed the thought that the cause of the head rotation lies in the fact that the entire trunk of the fetus "twists along its long axis." The change in the position of the shoulders entails the rotation of the head. Olshausen, Eichenstedt, Trillat, and Pollosson also see the essence of rotation in the rotation of the trunk around its longitudinal axis. In their opinion, after the accomplished flexion of the head, the trunk and head represent as it were an inseparable whole. The uterus during the expulsion period flattens, the back of the fetus turns anteriorly, and this movement is transmitted to the head, by virtue of which the occiput is passively directed toward the symphysis. Since the back of the fetus is more often turned anteriorly, the occiput is more often directed toward the anterior periphery of the pelvis than toward the posterior. Even in those cases where at the beginning of labor the back is turned posteriorly, later on, when the trunk turns with its back anteriorly, the occiput is directed toward the symphysis. Mikhnov, recognizing for the pelvic musculature only an auxiliary role, proposed his own theory of internal rotation of the head, based on the study of the shape of the head. According toikhnov, picturing the head as an ovoid or ellipsoidal body, as is generally accepted, cannot explain the mechanism of internal rotation. The fetal head as an object of the birth act must be considered as a kidney-shaped body. The kidney-shaped curved head has two poles, mentally connected to each other by the "line of head curvature." This is an imaginary arc-shaped line passing from the chin to the occiput and facing with its convexity toward the region of the large fontanelle.
The task of explaining the mechanism of internal rotation is reduced to studying the question of the movement of a solid body of a definite shape through a canal of a definite shape with solid walls. This canal (birth canal) has a sharply curved shape, characterized by a line concave anteriorly—the guiding axis of the birth canal or the "line of curvature of the birth canal." The movement of the kidney-shaped head through the curved birth canal will be most perfect, and the lumen of the canal will be most advantageously utilized in the event that the most complete possible coincidence of the "line of head curvature" with the "line of curvature of the birth canal" occurs. With the coincidence of both these curves, the head and the birth canal can be considered to a certain extent a "kinematic pair." Other authors shift the center of gravity of the question to the physical properties of the fetal body. Kaltenbach was the first to point out the importance for the mechanism of labor of the unequal compressibility of the spine in various directions. The theory of Selheim is distinguished by the greatest depth. He believes that neither the expulsive force nor the type of the birth canal can explain the rotations of the body around its long axis; the participation of the main mechanical factor is necessary, and this factor is the unequal flexibility in various directions of different parts of the fetal body. According to Selheim, the fetal body during the birth act turns into a cylinder, the individual sections of which exhibit unequal flexibility: in the cervical part of the spine, the body is most easily bent backward, in the thoracic and lumbar parts to the right and left. Selheim's physical experiments proved that a uniformly elastic cylinder passes through a curved canal without rotation, whereas a cylinder easily bendable in one direction and difficult in another, during passage through a curved canal, rotates around its longitudinal axis until it assumes a position in which it bends most easily corresponding to the curvature of the canal along which it goes. Applying these physical observations to the birth act, Selheim established that the occiput of the expelled fetus turns anteriorly because only with this rotation does the easiest bending of the cervical part of the spine coincide with the curvature of the birth canal. At the heart of this rotation lie elastic stresses arising in a non-uniformly flexible body when it is forced under pressure through a curved canal. This view of Selheim (the doctrine of Biegungsfacilitimum) constitutes only a part of his complex doctrine of the mechanism of labor, which will be briefly outlined below. Having completed the internal rotation, the head in a state of strong flexion establishes itself
Figure 37. Soft birth canal in its full development. Sagittal section according to Farabeuf and Varnier.
above the pelvic outlet, with the occiput facing the posterior surface of the symphysis, the forehead in the sacral hollow, and the sagittal suture maintaining a strictly sagittal direction. The head has to overcome the resistance of the soft parts enclosing the pelvic outlet (pelvic diaphragm, perineum, vulvar ring). The head finds the least resistance in the anterior section of the pelvic outlet in the arcus pubis; it is into this locus minoris resistentiae that the occiput, driven by labor pains, rushes. At this time, the coccyx, movably connected to the sacrum in the articulatio sacro-coccygea, is deflected backward, thereby increasing the straight diameter of the outlet. The entire complex of soft parts of the outlet, yielding to the pressure on it from above by the head, unfolds, forming as it were an additional canal-tube to the bony pelvis (Fig. 37). The occiput, having inserted itself into the pubic arch under the influence, on the one hand, of labor pains and, on the other hand, of the pressure of the stretched perineum, emerges from under the symphysis, leaving the boundaries of the pelvis and being born into the world. At this time, the forehead bypasses the tip of the coccyx, the soft parts of the outlet bulge out dome-shaped, driven by the head, and first the posterior perineum bulges out
Fig. 38. Molar incarnation of the head during occipital presentation. The occiput rolled out under the pubic arch, the forehead passed the tip of the coccyx, the 3rd rotation begins:
extension.
and the perineum. The stretchable muscles of the pelvic floor press the emerging head against the lower edges of the pubic arch, the area of the suboccipital fossa firmly presses against the lower edge of the symphysis, after which the extension of the head begins—the third moment of the mechanism (deflexio) (fig. 38). This rotation of the head around its transverse axis begins when the occiput and the parietal tubercles have been born, and consists in the fact that the cervical part of the spine extends; the chin moves away from the chest; with each contraction, a larger and larger segment of the head passes through the vulvar ring. The latter experiences the greatest stretching when the area of the anterior fontanelle and the upper part of the forehead enter it. As soon as the frontal tubercles have passed the perineum (fig. 39), the latter, due to its elasticity, is pulled back, sliding along the emerging face of the fetus. The perineum, being pulled along the facial skull of the fetus, completes the extension of the head, and the birth over the chin suture ends the 3rd moment of the mechanism. During this moment of the mechanism, the head passes from a state of maximum flexion to a state of maximum extension, making an excursion of 120-130° respectively. This movement becomes easily understandable in light of Zelgeim's teaching on the 'easiest bendability' (Biegungsfacillimum). However, even before Zelgeim, Kaltenbach pointed out the important significance of the flexibility of the cervical part of the spine, saying that 'the emergence occurs the more easily, the greater the mobility and range of motion of the spine in the sense of rotation, which the presenting part of the fetus must perform around the lower edge of the symphysis'. The head is born. The body remains to be born. During the passage of the head through the soft birth canal of the pelvic outlet, the upper part of the body enters the small pelvis, invariably with the transverse diameter of the shoulders entering one of the oblique diameters of the pelvic inlet. If the fetus was in the 1st position, the shoulders occupy the left oblique diameter of the inlet, in the 2nd position they enter the right oblique diameter. After the head is born, the shoulder girdle is already in the pelvic cavity, with the diameter bisacromialis occupying the same oblique diameter in all planes of the pelvis. Only when it advances to the pelvic floor do the shoulders begin their internal rotation, quite similar to that of the head. The shoulder located forward and to the side rotates toward the symphysis, the other shoulder backward toward the coccyx. The internal rotation of the shoulders is completed when the diameter bisacromialis stands in the anteroposterior diameter of the outlet. It is clear that this rotation of the shoulders is transmitted to the born head. If it is immediately after birth facing straight down (rather backward), then as the rotation of the shoulders is completed, the face turns to the side, toward one of the thighs of the parturient, in the first position to the right thigh, in the second to the left. This last rotation of the fetus—the internal rotation of the shoulders or the external rotation of the head—is the fourth moment of the expulsion mechanism (rotatio capitis externa). After it, the anterior shoulder enters the pubic arch and emerges under it, the posterior shoulder, somewhat delayed by the coccyx, protrudes the perineum in front of itself and, with significant lateral curvature of the body, is born over the perineal raphe. After the birth of the shoulder girdle, the expulsion of the remaining parts of the fetus's body remains. But since there are no more parts that could encounter any obstacle from the walls of the birth canal, the rest of the body is expelled along the birth canal dilated to the maximum without any special mechanism. The physical phenomena occurring in the uterine cavity and the relationships and interactions of all three mechanical systems—the uterine cavity, the birth canal, and the fetus—are as follows. Immediately before labor, the uterus represents a huge sac with rather thin walls. To the inner surface of this flaccid muscular sac adhere the fetal membranes, weakly fused with the uterus. In the cavity of the sac are the amniotic fluid and the fetus floating in them. To this sac (the body of the uterus) below is attached the cervix, communicating with the uterus via the isthmus. The cervical canal is connected with the uterine cavity not by an opening (internal os) but by a canal of certain, though insignificant, length. If in a non-pregnant woman and in the first three months of pregnancy the isthmus is preserved as such and the internal os lies at the level of the upper opening of the isthmus, then from the 3rd month the isthmus becomes part of the walls of the uterine cavity, its mucosa undergoes a decidual reaction and enters into close contact with the egg membranes, the walls of the isthmus fuse with the walls of the uterine body, forming the lower uterine segment, and the internal os will correspond to the lower opening of the isthmus. The latter has been proven by the classic research of Stieve (1928). With the onset of labor activity, the previously flaccid walls of the uterine cavity begin to contract rhythmically (fig. 40). Its contents are subjected to compression from all sides, creating increased pressure in the uterine cavity (general intrauterine pressure). The liquid contents of the uterine cavity, under the influence of this pressure, rush toward the only 'place of reduced resistance' available in the walls of the uterine cavity. And this place is the lower pole of the uterine cavity, which has an opening in its wall—the internal os. As soon as this opening has somewhat enlarged, the lower pole of the fetal sac, located directly above the os and easily movable relative to the walls of the lower segment, begins to bulge into it. The significance of the muscular work of the uterus during the dilatation period lies in the unfolding of the cervix and its expansion to the possible limits, in its transformation into an exit tube—a wide, thin-walled channel capable of ser

ving as

Figure 39. Emergence of the head in occiput presentation. 3rd rotation completed: the head is fully extended, the frontal tubercles have passed the perineum.
the uterine cavity. The physical phenomena occurring in the uterine cavity and the relationships and interactions of all three mechanical systems—the uterine cavity, the birth canal, and the fetus—are as follows. Immediately before labor, the uterus represents a huge sac with rather thin walls. To the inner surface of this flaccid muscular sac adhere the fetal membranes, weakly fused with the uterus. In the cavity of the sac are the amniotic fluid and the fetus floating in them. To this sac (the body of the uterus) below is attached the cervix, communicating with the uterus via the isthmus. The cervical canal is connected with the uterine cavity not by an opening (internal os) but by a canal of certain, though insignificant, length. If in a non-pregnant woman and in the first three months of pregnancy the isthmus is preserved as such and the internal os lies at the level of the upper opening of the isthmus, then from the 3rd month the isthmus becomes part of the walls of the uterine cavity, its mucosa undergoes a decidual reaction and enters into close contact with the egg membranes, the walls of the isthmus fuse with the walls of the uterine body, forming the lower uterine segment, and the internal os will correspond to the lower opening of the isthmus. The latter has been proven by the classic research of Stieve (1928). With the onset of labor activity, the previously flaccid walls of the uterine cavity begin to contract rhythmically (fig. 40). Its contents are subjected to compression from all sides, creating increased pressure in the uterine cavity (general intrauterine pressure). The liquid contents of the uterine cavity, under the influence of this pressure, rush toward the only 'place of reduced resistance' available in the walls of the uterine cavity. And this place is the lower pole of the uterine cavity, which has an opening in its wall—the internal os. As soon as this opening has somewhat enlarged, the lower pole of the fetal sac, located directly above the os and easily movable relative to the walls of the lower segment, begins to bulge into it. The significance of the muscular work of the uterus during the dilatation period lies in the unfolding of the cervix and its expansion to the possible limits, in its transformation into an exit tube—a wide, thin-walled channel capable of serving as

Figure 40. Action of uterine contractions during the dilatation period.
life for the passage of the fetus. Thus, functionally the uterus during labor is divided into two parts: the upper part — active, contracting, corresponding to the body of the uterus, possessing enormous muscular strength, with walls progressively thickening during labor, a motor, a hollow muscle, and the lower part — passive, poor in musculature but rich in elastic fibers, corresponding to the cervix, progressively stretching, with walls becoming thinner and thinner. The boundary between these anatomically and functionally distinct parts of the uterus is the contraction ring. In connection with the aforementioned ancient dispute regarding the origin of the lower segment, the question stands as to whether the contraction ring corresponds to the internal os or not. While P. Müller believed that the boundary between the active and passive parts of the uterus strictly coincides with the internal os (Müller's ring), Bandl's doctrine states that already during pregnancy the uppermost part of the cervix unfolds and becomes part of the fetal receptacle, that Müller's ring is not the internal os, but the boundary between the upper, unfolded section of the cervix and the rest of it, and that thus the internal os should be sought somewhere above Müller's ring (Bandl's ring). Aschoff's doctrine on the division of the uterus into 3 parts is fully corroborated by Bandl's propositions and sheds light on the question of interest to us. Still, the dispute is far from being considered settled. Suffice it to indicate that some authors believe the boundary between the active and passive parts of the uterus lies above the internal os, that the lower uterine segment is part of the stretching cervix, while others assume that the body of the uterus contracts, the cervix stretches, and that thus the natural boundary between them is indeed the internal os. Genther agrees with Stieve and believes that the lower segment is the isthmus that has become part of the fetal receptacle, while the boundary between the active part of the uterus (the hollow muscle) and the passive part (the outlet tube) corresponds to the upper opening of the isthmus. The indicated dispute has purely scientific and theoretical interest; practically, however, it is important that there is a sharp boundary between the contracting and stretching parts of the uterus, that this boundary is truly a "ring," as every obstetrician can easily verify during an obstetric version or manual removal of the placenta. The physiological phenomena occurring during labor in the uterine musculature are very complex. The arrangement and direction of the smooth muscle elements are very different in the body of the uterus and in the cervix. While in the body the muscles are located predominantly longitudinally to the axis of the uterus, in the cervix they have mostly an oblique or circular arrangement. Labor pains have a twofold effect on the uterine musculature. Periodically contracting in the active part of the uterus, the musculature becomes more and more powerful, the wall of the hollow muscle progressively thickens due to a peculiar relocation of its elements. After each relaxation, the muscles do not return to their initial state, but remain in the position they assumed as a result of the preceding contractions. Each subsequent contraction leads to a further relocation of the fibers, and thus the musculature of the entire hollow muscle, thickening, gradually shifts upward along the fetus toward the bottom of the uterus. This physiological phenomenon is called retraction (see above). On the other hand, due to the peculiarities of the arrangement of the fibers and their interrelationship, the active work of the hollow muscle has a peculiar effect on the cervix. The circular muscles of the cervix are stretched eccentrically, each subsequent contraction contributes to the further expansion of the cervical canal, which also does not decrease during the pauses between contractions (distraction). Into the progressively expanding cervical canal, the lower part of the ovum is driven; under the influence of the general intrauterine pressure, the amniotic fluid drives the fetal membranes ahead of itself, the "bag of waters," which in turn contributes to the opening of the cervix. Thus, the work of opening the cervix consists of two factors: the pressure driving the lower pole of the ovum into the cervical canal, and the tension, which in turn consists of the retraction of the hollow muscle and the distraction of the cervix. The result is the original action of two forces acting in opposite directions (Stöckel): the bag of waters is displaced downward by virtue of pressure, the hollow muscle is displaced upward by virtue of contraction, and the combination of these two mechanical moments leads to the smoothing of the cervix, its gradual opening, and the transformation of the narrow, thick-walled cervical canal into a wide, thin-walled outlet tube. If the retraction of the uterus could occur unhindered to extreme limits, then the expulsion of the fetus could not take place, because the hollow muscle would retract upward along the fetus — the useful work would be equal to zero or almost zero. In reality, however, retraction cannot reach such degrees because the hollow muscle is fixed to the pelvis by a whole series of organs and tissues, such as the vagina, the ligament complex (broad, round, and uterosacral), which "keep it anchored" (Zelheim). These formations hold the hollow muscle as if on reins and fix it to a certain extent so that the retraction of the hollow muscle cannot be limitless. The force going into the retraction of the hollow muscle, upon its reaching the maximum possible retraction, turns into pressure on the contents of the fetal receptacle. By this moment, the cervix has already turned into an outlet tube stretched ad maximum, the membranes of the ovum cannot withstand the high intrauterine pressure, they rupture, thereby eliminating the last obstacle to the forward movement of the fetus through the sufficiently dilated birth canal. From this moment, the contractile work of the upper part of the uterus is directed no longer at the retraction of the musculature, but at the expulsion of the fetus. The uterus has become a "birth motor." Speaking of the work of the uterine musculature in labor, one cannot fail to mention Verbov's theory (1912). Based on his observations, Verbov speaks of the "law of peristaltic movement in the physiology of the birth act." The uterus, according to Verbov, is a muscular organ which, like any hollow organ, rids itself of its contents due to the work of its longitudinal and circular muscle elements contracting phase-by-phase. In the 1st phase, predominantly longitudinal muscles work (the period of dilatation), in the second — circular ones (the period of expulsion). During the first phase, the cervix shortens and opens, and the fundus of the uterus, standing at the beginning of labor only slightly below the xiphoid process, descends by the end of the dilatation period by 4 fingers below the xiphoid. The shape of the uterus, initially oval, turns into spherical, since the uterus becomes shorter and wider (the latter at the expense of the relaxation of the circular musculature). In the 2nd phase, predominantly circular muscles work. The fundus of the uterus gradually moves upward and goes under the ribs. The uterus becomes narrow and long and during a contraction bends in an arc anteriorly, stretching the abdominal wall. As a result, the contraction reflexively causes bearing-down efforts, and the uterus finds support, on the one hand, in the lungs, increasing in their volume during inspiration, and, on the other hand, in the anterior abdominal wall. Verbov's views largely diverge from the opinion of all obstetricians, although apart from his personal observations they are also based on the anatomical investigations of N. Z. Ivanov, who showed that there is no division into active and passive parts in the uterus, but that all parts of the uterus are active during labor. If Verbov considers the activity of the uterus to be the same in all parts, both in the lower and in the upper, this contradicts the firmly established doctrine of the hollow muscle, the outlet tube, and the contraction ring. Verbov does not ascribe any independent significance to the work of the abdominal press, recognizing its role as purely auxiliary, while in reality the work of the abdominal press, classically described by Bumm, creates a force which, according to Malinovsky's research, constitutes 2/3 to 3/4 of all work on the expulsion of the fetus. It is also hardly possible to look at the uterine musculature as a sum of longitudinal and circular elements. It is much more complex in structure. Chistyakov says: "If we are not even able by precise dissection to establish the muscular structure of the uterus, we have only to study it as the action of a machine in order to judge its structure from this." The research of Kuramshina (Kushtalov's clinic) is interesting. Observations were made using an apparatus consisting of a belt with two rubber chambers filled with air and equipped with mercury manometers. The belt was applied to the abdomen of the parturient woman so that each chamber was located evenly on the sides of the uterus. Contractions and bearing-down efforts were revealed on the apparatus in the form of mercury oscillation in the manometers, which outside of a contraction fell again to the established norm. Interesting curves were obtained, and it is especially important that the oscillation of the mercury in the manometers on both sides of the uterus is usually unequal. Such oscillations in the manometers occur due to the uterus itself depending on the position of the fetus. The expulsion of the fetus occurs apparently amidst phenomena of torsion of the uterus in one direction or the other.
Such twisting is mentioned by Schröder as well, who believed that during contractions the uterus not only rears up, but also projects further forward with one corner. According to Kuramshina-Kushtalov, this manifests not so much the action of the longitudinal or circular musculature, but rather of the oblique. Closely embracing the fetus during a contraction, the musculature particularly develops its strength on the side where the large part of the fetus lies. It is here that the greatest force is developed, generated by the contraction of the oblique and circular elements. The uterus, while contracting, does not remain in place, but makes a forward translational movement, not equal on both sides, but in a state of torsion to one side or the other, depending on the position of the fetus. The foregoing convinces us that the physiology of labor has not yet been perfectly studied, and one cannot disagree with Chistyakov that the doctrine of uterine contractile activity is not yet complete. After the work on cervical dilation is completed, labor enters the second period, which aims at the expulsion of the fetus. The birth canal, representing an expanded cervix in its upper section, continues downward into the sleeve or vagina. The latter is largely elastic; stretching in length and easily expanding in width, it cannot present an obstacle to the expelled fetus. The situation is different in the lower section of the birth canal, in the region of the pelvic floor. Here, a powerful muscular-fascial-cutaneous complex closing the pelvic outlet presents a strong obstacle to the advancing fetus. The work of the expulsive forces is directed not only toward the mechanical overcoming of this obstacle, but also toward the creation from this tissue mass of an additional part of the outlet tube, protruding far beyond the limits of the vagina (Figs. 41 and 42). To the same extent as in the dilation period, the cervix, expanded by distraction, lengthens
Figure 41. Semi-schematic combined drawing according to Sellheim; showing both dilation (complete dilation of the uterine os, vaginal part smoothed out) and, for the first time at the end of the expulsion period, the ensuing transformation of the pelvic floor into an additional tube to the vulva (between lines I and II). The apex of the urinary bladder, owing to the descent of the head into the pelvis, is already higher than the symphysis. The anus is gaping due to the stretching of the pelvic floor. The guidance line marks the path along which the head must travel (resp. the small fontanelle).
the outlet tube upward, so in the expulsion period the unfolded pelvic floor lengthens it downward, forming an additional part of it, curved forward. von Jaschke regards the soft birth canal as consisting of two contiguous tubes. The inner tube is the uterus and vagina, undergoing typical transformations and changes in the dilation period; the outer tube is the unfolded pelvic floor, undergoing this peculiar transformation under the influence of the head advancing in the expulsion period. During this process, the muscle layers of the pelvic floor, arranged in a shingle-like manner, shift relative to each other so that edge meets edge, resulting in the formation of a wide tube,
growing out of the pelvic outlet and having a forward and upward direction. The axis of this additional
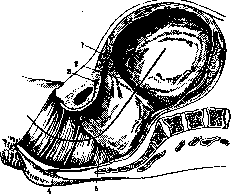
Figure 42. Birth canal (according to Lee): 1 - marginal venous sinus of the placenta; 2 - contraction ring; 3 - urinary bladder; 4 - anus; 5 - external uterine os. The pelvic musculature has turned into an upwardly and forwardly directed superstructure.
tube, being a direct continuation of the pelvic axis, has a different direction. The pelvic axis, falling vertically onto the plane of the pelvic inlet, passes, almost without changing direction, to the pelvic floor, forming the "guidance line," and only here at the pelvic outlet curves sharply forward and upward, forming the "knee of the birth canal" (Sellheim). During labor, owing to contractions of the uterine musculature, an increased pressure is created within it. The expelled fetus is under this "general intrauterine pressure." In order for this pressure to be fully utilized for the successful advancement and expulsion of the fetus, it is necessary that the walls of the uterus "closely adhere" to their contents. Before the discharge of amniotic fluid, the walls of the birth canal adhere to the fetal sac; after the rupture of the membranes, they must closely adhere to the head, creating a "zone of contact." Only then can the syringe piston successfully serve its purpose when it closely and comprehensively adheres to the walls of the syringe; otherwise, part of the useful work is lost. Likewise in the process of fetal expulsion. If there is no "close adherence" of the walls of the birth canal to the presenting head, then part of the useful pressure will be aimlessly lost, rushing between the head and the walls of the birth canal. Sellheim calls this "close adherence" "internal adherence" (innere Abdichtung). In addition, Sellheim introduces the concept of "external adherence" (aussere Abdichtung). The expulsive forces will be most perfectly utilized only in the case where both internal and external "close adherence" is most perfectly achieved. These mechanical moments, along with the fixation of the uterus to the pelvis (anchoring—Verankerung), are necessary prerequisites for the successful expulsion of the fetus. While the movements of the fetal head set forth above ("4 moments of the mechanism") were explained by all old authors by the structure of the bony pelvis and soft birth canals, Sellheim established that expulsion is explicable only by the interaction of the fetal body and the birth canals. He attaches primary importance to the features of the ovum and, chiefly, the fetal body. The ovum changes its shape, "is shaped," and the ability to change shape (Verformbarkeit) of the individual constituent parts of the ovum varies. The amniotic fluid changes shape the easiest, the soft parts of the fetal body more difficultly, and its skeleton most difficultly. In labor, when, by virtue of the contractions of the hollow muscle, increased pressure is created within its cavity, the contents of the uterine cavity move downward, toward the side of least resistance; the amniotic fluid enclosed in the fetal membranes forms the fetal sac; later, the soft tissues of the presenting part form the caput succedaneum, and the presenting part is configured (Figs. 43, 44). Sellheim attaches special importance to the change in shape of the fetal body; it is "shaped," "corseted" (Schnurung des Kindes). The physiological attitude of the fetus, surrounded by amniotic fluid, allows
Figure 43.
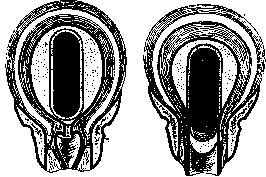
Figure 44. Figure 43. Uterus before the onset of the dilation period (schematically according to Sellheim). Outside—abdominal musculature fixed to the pelvic walls, further inward—uterus and sleeve, wavy line—peritoneum, inward from the uterus—sac with fluid; the fetal skeleton is depicted in black, the soft parts of the latter in gray outward from it, between the sleeve wall and pelvis—sites of fixation. Figure 44. Uterus at the end of the dilation period (schematically according to Sellheim). Designations are the same as in Fig. 43. Internal and straight compaction zones. Straight-line soft birth canal. Thickening of the hollow muscle. Thinning of the lower segment. Tension of fixation sites. Various forms of uterine contents (fetal sac ready for rupture, caput succedaneum occurring of course after sac rupture, adaptation of the head bones to the pelvic inlet).
it to make certain free movements during pregnancy. During the act of labor, the fetus increasingly assumes a forced position. Owing to the fact that the birth canal turns into a cylindrical tube, the fetal body is forced to assume the shape of a cylinder; the muscular canal "shapes" the fetal body. The latter, experiencing pressure from above and the corseting action of the circular muscles of the birth canals, turns into a cylindrical body whose shape fully corresponds to the shape of the outlet tube. The fetus is "shaped" into a "fetal cylinder" (Fruchtwalze) (Figs. 45 and 46). The circularly corseted fetus is simultaneously under pressure from above (on the part of the hollow muscle) and from below (due to the resistance of the pelvic floor). Under the influence of such comprehensive pressure, the fetal body decreases in volume, and the friction between its surface and the walls of the birth canal also decreases. The fetus, thus transformed into a cylindrical body ("cylinder") with varying compressibility in its different sections, is expelled along the birth canals, performing in the process the typical rotations already set forth above. The elliptical shape of the head corresponds to the same shape
Figure 45.
Figure 46. Figure 45. Transformation of the fetus into a cylinder. (According to Sellheim.) Formation of the head and chest. Figure 46. Completed transformation of فران the fetus into a cylinder. (According to Sellheim.) of the outlet tube, as well as to the ellipse of the pelvic inlet: the long diameter of the head stands in the transverse diameter of the plane of the pelvic inlet. In the pelvic cavity with its rounder boundaries, the ellipse of the head cannot stand transversely for long. The comprehensive "corseting" of the head by the walls of the birth canals forces the head to place its long diameter in the direct size of the pelvis: the head performs its internal rotation, wherein the sagittal suture, which stood transversely in the pelvic inlet,
Figure 47. Head on the pelvic floor, which has not yet stretched. Strong flexion of it. Large caput succedaneum sitting like a cap on its rear part. The coccyx is deflected somewhat backward, owing to which the direct size of the pelvic outlet is elongated. (According to Lee.)
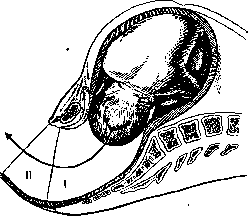



is found in the pelvis already standing obliquely and at the pelvic outlet coincides with its anteroposterior diameter. Simultaneously with this rotation, there occurs significant molding of the head, its further flexion, and the increase of the birth tumor (fig. 47). The compressing effect of the birth canal, following the head, affects the rest of the fetus's body. The fetus's spine straightens, the body lengthens, the crossed arms on the chest are pressed more tightly to the body, the shoulders rise and fill the space between the head and the shoulder girdle, so that the entire upper end of the fetus turns into a solid cylindrical body. The legs, bent at the hip joints, even out the irregularities of the fetal pelvic end. The entire fetus has turned into a 'fetal roller', all its parts have approximately the same volume and the same shape. Only at the end of expulsion do the straightening legs make this uniform cylinder gradually tapering. Thus, the fetus is forcibly 'molded', it stands under 'molding tension' (Ver-formungsspannung), its individual parts in a tense posture (Haltungsspan-nung), from which they strive to escape and assume a more free position. This tendency to escape from the tense state is especially noticeable when the fetal cylinder reaches the lower part of the birth canal and enters the additional outlet tube, directed forward and upward. The fetus bends in accordance with the curve of the birth canal. It has already been pointed out above that the flexibility of different parts of the fetal cylinder varies. If the cervical part of the fetus is most difficult to flex (KnepeflH('Biegungsdificillimum'), then it is most easily flexed backward ('Biegungsfacilli-mum'). The forward-flexed cervical spine of the fetus tends to straighten toward its extensor 'Facillimum', which explains the typical deflexion of the head at the moment of birth. The typical turns of the fetus, known under the old name of mechanism moments, find their explanation in the 'law' established for the mechanism of labor by the same Selheim (see above). This law explains both the internal rotation of the head and its extension in the outlet tube, and the internal rotation of the shoulders. Individual parts of the fetal cylinder undergo corresponding flexions in sequence, as they enter the area of the bend of the birth canal. The head, having reached during the expulsion phase the knee of the birth canal on the floor of the pelvic cavity, rotates separately, independently of the body, there occurs torsion of the fetal cylinder (Torsion der Fruchtwalze). While the head, standing at the pelvic outlet, performs its extension, the shoulder girdle enters into the transverse ellipse of the pelvic inlet. After the birth of the head, it is the turn for the typical flexion of the shoulders, which are most easily flexed sideways. This lateral flexion is possible only when the transverse diameter of the shoulders passes from the transverse diameter of the pelvis through the oblique diameter into the anteroposterior diameter of the outlet. Here, with the shoulder girdle standing in accordance with the anteroposterior diameter of the outlet, the body can reveal its greatest ease of lateral flexion, and it indeed bends, adapting to the direction of the birth canal, in an arc toward the symphysis; there occurs the 'shoulder emergence' (Selheim). The doctrine of the mechanism of labor has been thoroughly discussed in recent years, especially in connection with the introduction of a new method for studying the act of labor, namely radiography. Warnekros has given a detailed work on 'pregnancy and labor on the radiogram'. Many positions of Selheim find confirmation in the radiograms of Warnekros. Under the influence of labor contractions, the posture of the fetus changes. The spine in the dilatation period flexes, and here one can observe the different flexibility of different parts of the spine in the sense of Selheim. After the rupture of the membranes, the fetus is stretched in length, the thoracic part of the spine straightens, and the lumbar part compensatorily curves forward (lordosis). The entire vertebral column assumes such a position that it can withstand the pressure coming from the floor of the uterus. Warnekros, in contrast to Selheim, recognizes the existence of axial pressure (Fruchtachsen-druck). This last is transmitted to the head, which moves forward, at the same time performing flexion and rotation movement—a movement called by Olshausen turbinal, a term accepted by Schroeder and others. The 'molding' of the fetus into a cylindrical body (Fruchtwalze of Selheim) Warnekros could not prove radiographically. It is interesting that in Warnekros's radiograms, the rotation of the body with the spine forward precedes the internal rotation of the head, which supports Olshausen's theory of primary rotation of the body, which entails the internal rotation of the head. It cannot be overlooked that Selheim's doctrine has opponents, among whom A. Müller stands out, demanding a strict distinction between the mechanics of L. and the physiology of L.; his entire doctrine is built on the laws of geometry and physics. 'Labor is the passage of a cylindrical body through a curved tube consisting of soft parts and bones. The fetus consists of 3 solid cylindroids: the head, the thoracic cage, and the pelvis'. The position of the body in a hollow space is determined by the law of equilibrium and the law of the inclined plane. Its movement occurs in the direction of least resistance, namely along the inclined plane in the direction of the greatest open angle. Since in an elliptical space only the shortest and longest radii are perpendicular to the tangents (in contrast to a circle, where all radii are perpendicular to all tangents), the body (head), penetrating this space (pelvic inlet) under the influence of a certain force (contraction), performs a rotating movement until stable equilibrium is achieved by the long dimension of this body coinciding with the long axis of the ellipse. This explains why the head (or buttocks) enters the transversely oval pelvic inlet in its transverse diameter, and in the longitudinally oval pelvic outlet stands in its anteroposterior diameter. In the wide part of the pelvic cavity, which in cross-section has the shape of a circle, no rotation occurs. The straight-line movement of the head through the pelvic canal, due to the inclined plane of the posterior wall of the pelvis and the elastic resistance of the pelvic floor, at the pelvic outlet deviates forward to the symphysis. If the point of attachment of the spine to the head (foramen magnum), as in most cases, is located more forward, closer to the symphysis, then simultaneously with the forward movement of the head, the action of a lever comes into play, as a result of which the head curves around the lower edge of the symphysis and is born, extending. Müller denies the formation by the fetus of a 'Fruchtwalze', denies also the 'forced tension', and the significance of the 'greatest ease of flexion' of different parts of the fetal cylinder.-It is clear that one cannot reduce all the complex plastic processes occurring during the act of labor in the woman's organism to simple physical movements of solid and liquid bodies, explaining these subtle processes by the physical laws of the wedge, lever, and inclined plane, as Müller does, Dr. Henter. IV. Management of labor. The necessity of providing special obstetric help was realized already at the lowest stage of cultural development. And understandably so. In a woman's life, the time of L. is one of the most difficult periods, when to her heavy experiences are added a number of serious dangers in the form of infection, trauma, bleeding, mental excitement, etc. Hence follows the necessity of the presence at L. of a knowledgeable experienced person, able by word and deed to help the parturient cope with her difficult task, able to foresee and eliminate those dangers that threaten her. Unfortunately, the state of modern obstetric science does not even allow a very experienced doctor to predict all possible complications during labor. Even in apparently completely normal pregnancy and normally proceeding L., at any moment of L. complications may appear threatening the life of both mother and fetus. The sooner the danger is diagnosed, the sooner preventive measures are taken, the more perfect and productive our help will be. The help itself can be very complex and often can be provided only in a special obstetric institution. Wherever L. is conducted, before us stands a certain goal: to give the parturient the maximum achievements of science as much as possible and to bring the quality of obstetric help to the level of a properly organized clinic, obstetrics. Such a formulation of the question places special demands on clinic, obstetrics. In its scientific-practical work, the clinic should pay maximum attention to developing such methods of care and management of parturients and puerperal women, which, while being fully equivalent, can be easily applied under extraclinical conditions. Preparation for L. has extremely important significance in the prevention of maternal morbidity after childbirth. The doctor should pay special attention to it, since the most insignificant in appearance details in this area of obstetrics, as shown by large numbers obtained by a number of serious scientific institutions, can significantly affect the percentage not only of maternal morbidity but also of mortality.
The first measure upon admission of a parturient woman should be the measurement of body temperature. Parturient women with elevated t°, if childbirth is conducted in an institution, must be separated from healthy women and strictly isolated. The rectum and bladder must be thoroughly emptied. As a rule, each parturient woman, regardless of whether she has had a bowel movement or not, receives a large-volume enema of 1.5-2 glasses of soap solution made from boiled water at room temperature. If labor lasts more than 10-12 hours and the presenting part has not yet reached the pelvic floor, the enema is repeated. After emptying the rectum, hair on the external genital organs is shaved or clipped with scissors, after which it is desirable to thoroughly wash the entire surface of the woman's body with warm soapy water. This can be done either by washing the parturient woman, standing or sitting on a stool in a bathtub, with soap and rinsing her with warm water from a shower or pitcher, or by prescribing her a soap bath. At present, most obstetricians refuse to prescribe ordinary baths, since a number of researchers (O. Kustner, Sticher, Struganov) have pointed out the possibility of numerous microbes, vegetating on the woman's skin, getting into the bath water and from there into the vagina. Although Struganov's experiments, verified by a number of researchers [Nikitin, Libov and especially Winternitz], have not been confirmed, however, the washing method as a simple and hygienic procedure that completely excludes the possibility of introducing infection into the vagina from the bath undoubtedly deserves widespread adoption. After the bath, the parturient woman puts on sterile or freshly ironed linen and proceeds to the delivery room. The choice of room, where it is possible to make one, should be carefully considered. It is necessary to take into account good ventilation, sufficient size of the room, as well as the quality of its lighting. All unnecessary furniture and items should be removed from such a room, leaving only a bed, two tables, 3 stools, and a washstand. All curtains, drapes, and carpets should be removed from such a room in advance. If the physician is called already at the moment of R., it is better not to touch any of this and to prefer conducting R. in the usual setting, not raising dust by cleaning drapes, carpets from walls, etc. The bed is also of great importance for conducting childbirth. In clinics and maternity institutions, metal, strong, high beds are very widespread, an excellent example of which should be considered the Rakhmanov bed. This bed is built from gas pipes and consists of two parts: the head part - larger and the foot part - smaller. The second part is inserted into the first. Thanks to the fact that the mattress, like the table, also consists of two parts, at the moment of head crowning, the foot part of the mattress can be removed from the bed. In this case, the woman's legs rest directly on the lid of the foot half of the bed. This avoids the need to place a polster under the buttocks. If operative assistance is required, the foot part of the mattress should be removed, and the foot half of the bed inserted into the head part. In this way, very quickly, without moving or transferring the b-ny, we create an excellent table under her for obstetric operations, for which there are also special, easily attachable leg holders. For home births, it is best to choose a strong, firm and as high as possible bed that does not sag in the middle. If the bed is soft and sags like a trough under the woman, it is necessary to place as wide a board as possible under or on the mattress. The mattress should be covered with as wide a oilcloth as possible, which should protect the mattress from penetrating liquid and blood. Over the oilcloth, a freshly ironed sheet is spread. It is very useful to lay a second sheet, folded several times, over the first sheet. This so-called underpad is placed only under the pelvis, thereby, as the only
...as this sheet gets wet, it is easily replaced with a fresh, dry one, thereby protecting the first, main one from getting wet. Antiseptic treatment of the external genitalia and vagina. Up to the present time, a number of obstetricians still apply the treatment of the external genitalia and vagina with various disinfectants during the management of labor, using by analogy the method introduced by surgeons for treating the operative field. It is doubtful, however, whether such an analogy can be drawn without taking into account the specifics of the genital sphere. We know that the vagina possesses the capacity for self-cleaning. We know on the basis of the studies by Döderlein, Krönig, Menge, their teacher Zweifel, and many others, that even with purulent—pathological—vaginal secretions, disinfectants at best can only temporarily alter the vaginal flora and that they do more harm than good, destroying not only bacteria but mainly the body's protective mechanisms for fighting these bacteria. The practice of large clinical obstetric institutions of the Union, as well as extensive statistical data from foreign clinics (Leipzig, Freiburg, Tübingen, Munich), have demonstrably shown that the postpartum period proceeds better in those cases in which treatment with disinfectants was not performed, and worse in those in which it was used. Of all disinfectants, up to the present time, only one has stood out—lactic acid, which constitutes an integral part of normal vaginal secretion (Döderlein). R. Zweifel, Schweizer, E. Zweifel, then Thaler and Zuckermann, systematically using lactic acid in the form of prophylactic douches with a 0.5% solution, recognized this method as valuable. However, even with respect to lactic acid, opposite views are noted (Hamm). The prophylactic trend of Soviet medicine has compelled a number of Russian authors to take up this area of prophylaxis again and recall old attempts to reduce the percentage of postpartum diseases. This can explain the attempt by Okintchitz's clinic to test anew the prophylactic significance of lactic acid, using this acid in the form of douches in pregnant women at the consultation clinic of the Snegirev Maternity Hospital. Unfortunately, the cited figures are extremely small to draw any conclusion. Almost simultaneously, the Guzikov brothers made an attempt at the prophylactic application in obstetrics of rivanol, which is very widespread at present in both surgery and obstetrics, after the preliminary use of mercuric chloride douches even before labor had given them "tangible" results in terms of reducing postpartum diseases. The authors call their method "two-step." They carry it out as follows. After the usual measures of cleanliness, the parturient woman entering the maternity hospital is douched with a 1 : 2,000 mercuric chloride solution. 1 hour after labor, a 1 : 500 rivanol solution in the amount of 6–10 cm3 is introduced into her vagina using a Braun syringe. The same manipulation with the same amount and concentration of the solution is repeated on the 2nd day after labor. If the parturient woman undergoes an internal examination, this examination is accompanied by the introduction of 3–6 cm3 of rivanol solution into the vagina. After operative interventions (version, extraction, forceps, manual removal of the placenta, etc.), 10–20 cm3 of rivanol solution is introduced directly into the uterine cavity. The authors are very pleased with their results, although they applied this prophylaxis in only 500 cases of labor. The Guzikov method, with some modifications, was tested by a number of subsequent researchers (Nikolaev, Butomo, Lositskaya and Voskresensky, Antoshina, Emelyanov and Petrun kina), and all of them point to its good aspects and the necessity of giving it full attention. Despite the above, the question of the expediency of applying disinfecting treatment to the vulva and vagina before and after labor can by far not be considered resolved, even when using a rivanol solution. Skrobansky considers disinfection of the vagina harmful, but at the same time does not deny the usefulness of disinfecting the external genitalia and the region of the anus. In recent years, a number of researchers have sought to develop prophylactic methods by which one could raise the body's protective forces to fight an infection that might enter it. Such methods must first of all include attempts to obtain hyperleukocytosis by injecting nucleic acid, to activate protoplasm by injecting foreign protein or butyrol, and finally, active immunization of the female body, especially against streptococci and staphylococci, which most frequently are the cause of puerperal infection. The latter idea was especially propagated by Bumm and his pupil Louros, who proposed his own streptococcal vaccine. The idea of immunization was also very energetically taken up by a number of Russian physicians and served as the topic of a series of reports at the 7th All-Union Congress of Obstetricians and Gynecologists (Yankelevich, Feyertag, Mironova, Yelkin), which provoked lively debates at the congress. However, unfortunately, this method is also subject to further scientific clinical processing and therefore cannot be widely recommended. In Skrobansky's clinic, the following order of preparation for incoming parturient women has been adopted, which in its simplicity is applicable in any conditions. After admission of the patient, temperature measurement, and the usual enema, the genital organs are shaved. The abdomen, external genitalia, and inner surface of the thighs are washed with soap and hot water and irrigated with a mercuric chloride solution, after which they are dried with a clean towel. A clean gown is put on, and the parturient woman is transferred to the delivery room. Washing the entire body surface of parturient women in a bathtub is performed only in cases where the woman is very dirty; mainly the legs are washed. The simplified technique of preparing parturient women nevertheless gives results no worse than those obtained by a number of other institutions, despite the fact that students and young doctors are trained in the clinic and internal examinations are widely performed. Thus, according to Klenitsky's data, the total morbidity figure per 12,254 births is 6.7%; if one excludes one-day temperature rises, the morbidity percentage will be 3.1%, while the mortality percentage is 0.03%, i.e., in any case no worse than the results obtained with the use of rivanol and with abstention from internal examination. Diet of the parturient woman. Labors are associated with a large loss of energy, and if they last a long time, the rational replenishment of this loss becomes urgently necessary. During labor, a woman is so absorbed in her pains that she forgets about food and demands only drink. Only a few parturient women remember food and whimsically pick at what is offered to them. If there are no special indications, parturient women are usually given food in small portions in the form of easily digestible dishes: milk, coffee, cocoa, various milk porridges, broth, kisel, etc. The comparatively large amount of fluid consumed by parturient women should prompt the physician to carefully monitor the frequent emptying of the bladder, inviting the woman to urinate every ½ or 1 hour. Diagnosis of labor. In order to properly manage labor, one must have a clear idea of the course of labor and answer the following series of questions: 1) has labor begun; 2) the character of labor—physiological or pathological; 3) if labor has already begun, in what period of labor is the woman; 4) if labor is pathological, in what does this pathology consist; 5) are there any signs threatening complications in the future. To resolve these questions, it is necessary to study the woman thoroughly, applying methods of objective examination and studying her anamnesis in detail. For Soviet obstetricians, this difficult task is significantly facilitated by the broad setup of maternity protection work, especially in cities and large industrial centers; the parturient woman comes for obstetric help in the majority of cases having already visited a maternity protection station more than once, examined by a specialist doctor, with an established diagnosis of the duration of pregnancy, with an indication of those complications that exist or can be foreseen, with the anamnesis of past labors. In her pregnant woman's card we often find: results of repeated urine analysis, Wassermann reaction (RW), erythrocyte sedimentation rate (ESR), and measured blood pressure. The results of repeated objective examinations of the pregnant woman must also be noted in this same card. Careful familiarization with the pregnant woman's card immediately upon the admission of the parturient woman is the first duty of the obstetrician. The first of the questions facing the obstetrician—the question of whether labor has begun—must of course be resolved even before the admission of the parturient woman to the institution. In the vast majority of cases, this question does not present great difficulties for resolution, since the woman is admitted under medical observation in most cases with already pronounced labor activity. In rare cases, when labor begins ahead of time or when it is a matter of "false" labor pains, the diagnosis of the onset of labor can become not only difficult, but at times impossible. Placing the hand flat on the abdomen, one can quite distinctly observe periodically occurring contractions of the uterus, making it at times as hard as stone to the touch.
These contractions alternate with relaxations; the uterus becomes soft and poorly palpable. If these contractions repeat every 5-10 minutes, we are justified in concluding that labor has already begun. The person observing the parturient woman must, however, remember well that frequently even well-expressed contractions die down two or three times not only for several hours, but even for several days, after which the true labor activity finally begins. Each contraction of the uterus is accompanied by a definite sensation of pain, which is why uterine contractions are called labor pains. In very rare cases, contractions are completely painless, and the woman feels them hardly at all, resorting to obstetric assistance only when the amniotic fluid discharges. In other cases, contractions are especially painful and cause the woman to seek the obstetrician's help already at the very beginning of labor. With proper organization of obstetric care, a woman should come under the observation of the obstetric staff right from the beginning of labor activity in order to avoid various complications that may occur even at the beginning, such as premature rupture of the membranes, improper engagement of the presenting part, prolapse of soft parts, etc. The resolution of the remaining questions noted above is made on the basis of anamnestic and objective data of the examination collected by us (see Obstetric examination). It must be additionally noted that in the management of labor, one of the first questions facing the obstetrician is the question of the membranes. As long as the membranes are intact, neither the mother nor the fetus is exposed to any danger that may arise in the process of labor, and the physician can, without haste, proceed to collect the necessary anamnesis and a thorough, as complete as possible, examination.-The anamnestic information that the physician managing labor must have at his disposal relates chiefly to the following points: 1) age of the parturient woman, 2) previous pregnancies (which labor, course of previous pregnancies and labors, what operations were performed and by whom), 3) time of the last menstruation and first fetal movement, 4) past illnesses, especially shortly before labor, 5) when and with what pains true labor began, 6) time of rupture of membranes, 7) whether there was any bloody discharge during pregnancy and during labor. Already during the collection of the anamnesis, the physician can cautiously proceed to the external examination of the parturient woman, which can be supplemented by a rectal or vaginal examination (see Obstetric examination). Management of labor without a detailed examination and a clear idea by the obstetrician of the position of the fetus and presenting part, the period and course of labor, the character of the pelvis, and so on, is the management of labor blindly, often leading to the fact that the person managing labor misses the time when heavy consequences can and should be corrected and prevented in a timely manner by insignificant measures. This is why a good examination technique must be mastered by everyone who considers himself entitled to manage labor. There is no doubt that by external examination alone, sufficiently convincing data can often be obtained so that, relying only on them, the obstetrician can consciously manage labor. However, neither external examination, even when well mastered, nor rectal examination can provide, especially in difficult cases, the full completeness of the necessary information. We believe that the fear of internal examinations is completely groundlessly exaggerated. Abstention from this examination in some cases brings considerably more harm than the method itself harbors danger. On a large material of tens of thousands of labors (part of them reported by Klenitsky), Skrobansky was able to convince himself that maternal morbidity and mortality in the years when examinations were not performed did not differ, either in percentage or in the nature of the observed forms, from the morbidity and mortality of those thousands of parturient women whose labors were performed with internal examination, and that repeatedly-by one resident and one student. However, this cannot argue that the internal examination should be performed indiscriminately, at every labor; there must be completely definite indications for it, and it should be performed with the most meticulous observance of all precautionary measures (for example, the most thorough treatment of hands, disinfection of the external genitalia). Management of the dilation stage. The dilation stage, while contractions are not yet very strong, is one of the most peaceful periods for the staff managing labor (see below methods of labor anesthesia, labor anesthesia). After the performed examination, there is usually still enough time to take care of preparing everything necessary for labor. It is necessary to stock up a sufficient amount of freshly boiled water, provide oneself with freshly ironed or sterile linen, boil instruments, umbilical scissors, catheters, tape for tying the umbilical cord, a syringe for necessary injections, and, if there is no sterile cotton wool necessary for delivery, boil cotton balls as well; scorch basins with alcohol, prepare solutions of sublimate or other disinfectants. As long as the pains are not very strong, if the head is already engaging in the plane of the pelvic inlet, there is no need to put the parturient woman in bed. On the contrary, movement around the room can only strengthen weak labor activity and therefore in some cases is even desirable. If the pains are especially strong, the woman herself usually asks to be put in bed, and her request should of course be satisfied. If the head is mobile above the inlet and especially has a tendency to deviate toward one or another iliac bone (or if there is any deviation in general), it is necessary to put the parturient woman in bed as early as possible with a twofold purpose: 1) to prevent premature rupture of the membranes and discharge of water, and 2) to promote the correct engagement of the presenting part by the woman's position on the corresponding side. If, with a high standing of the presenting part, the membranes rupture prematurely, and especially if after this the fetal heart rate changes, it is necessary to urgently perform an internal examination. Only a timely performed internal examination makes it possible to determine the prolapse of even a small loop of the umbilical cord and save the life of the fetus with timely help. A woman with a pendulous abdomen should be put to bed earlier and made to lie on her back in order to better utilize the work of the uterus. For the same purpose, it is good in such women to give the pelvis a higher position by raising the lower end of the bed. Toward the end of the dilation stage, the intensifying pains often spread especially toward the lower back. Many women ask at this time to have their lower back rubbed or to have a folded roller sheet or a hot water bottle placed under it. These small techniques sometimes bring the parturient woman great relief. Although the physician in the first stage of labor should limit his actions to the extremely few measures listed above (to which it is necessary to add observation of the timely emptying of the bladder), his presence and his observation of the parturient woman can be of enormous significance. It is precisely in this period of labor that the physician must master the will of the parturient woman, he must accustom her to the maximum advantageous use of her strength; he must by the force of his authority force her to abandon unnecessary and useless movements and shifts in order to preserve a maximum of strength for the more responsible, although less prolonged, next period of labor—the expulsion stage. Management of the expulsion stage. Usually, when the os is fully dilated, the membranes rupture, and the waters discharge. If after full dilation the membranes do not rupture spontaneously, indications arise for the artificial rupture of the amniotic sac, which can be done either with a finger, or the end of a dressing forceps, or, for example, the end of one blade of umbilical scissors (see below—pathology of labor caused by anomalies of the birth object). However, this procedure is simple and easily performed only in the case when the head is already descending into the pelvic cavity or at least is tightly pressed against the plane of the inlet and if loops of the umbilical cord or small parts of the fetus are not palpated behind the membranes. With a mobile head, this simple manipulation must be given special attention. It is best to proceed as follows: the pelvis is raised by placing a large bolster under it. It is necessary to enter the vagina with the whole hand and, as it were, tampon it. Having pressed the head to the inlet with the external hand, one must grasp and rupture the membranes with the internal fingers, after which, without removing the hand, the waters are allowed to flow out slowly. By this technique, it is easiest to avoid the prolapse of the umbilical cord and small parts.—The expulsion stage begins with the characteristic work of the abdominal press and the entire muscular system of the woman. The proper utilization of this enormous work can significantly facilitate labor and shorten the duration of this period. It is necessary to place the parturient woman at this time in a supine position with her head raised on a pillow. It is necessary to teach the woman during bearing-down efforts to strive to maximize the use of her muscular strength, and between efforts to give the organism complete rest.
To better utilize the force of contraction of the abdominal wall muscles, diaphragm, pelvic floor, and the entire system of muscles of the chest, upper extremities, and neck, it is very good during bearing-down efforts to give the parturient woman "reins"—the ends of towels tied on both sides of the bed to its foot end. The muscles of the abdominal press and lower extremities are strained by the woman firmly resting her feet, bent at the knee joints, against the bed. With each bearing-down effort, the parturient woman should spread her knees as wide as possible and generate the maximum energy of contraction of her entire muscular system. At the same time, she experiences a sensation very similar to that which she feels during difficult defecation. While before the rupture of the membranes the fetus was not subjected to any dangers, during the expulsion period, after the rupture of the membranes, its life is subjected to a great test. During a bearing-down effort, the placental circulation, experiencing the full force of the bearing-down activity, changes. The heartbeat of the fetus slows down, and in some cases fetal asphyxia even sets in. During this period, systematic auscultation of the fetal heartbeat is of particularly important significance. It can be considered that normally the frequency of the fetal heartbeat individually fluctuates between 120–160 beats per minute. A heart rate below 100 and above 160 already indicates pathology. Slowing of the heartbeat is especially dangerous where a normal number of beats was previously auscultated and if the heartbeat frequency does not recover outside of a bearing-down effort. An increase in heart rate in itself is not dangerous. Especially dangerous, in the sense of developing asphyxia, is the uneven work of the fetal heart. Sellheim advises keeping a record of the fetal cardiac activity during this period, auscultating it every 15 minutes, and every 5 minutes in case of slowing, compiling a curve of cardiac activity. This suggestion deserves full attention, as it is one of the factors contributing to the reduction of fetal mortality sub partu. With long-lasting labors, the forces of the parturient woman may become exhausted and a state of complete exhaustion of the woman's body may set in. Systematic observations of the woman's cardiac activity and registration of the parturient woman's pulse provide valuable indications. In these cases, subcutaneous administration of morphine can calm the woman, giving her 2–3 hours of beneficial sleep, after which labor activity is restored (see below—anomalies of the expulsive forces). At the end of the expulsion period, the obstetrician-accoucheur faces a responsible task—protection of the perineum. It is hardly acceptable for modern obstetrics that the opinion of a small number of old obstetricians (Scanzoni, Wigand, and some others) that protection of the perineum from ruptures does not achieve its goal or is even harmful (Mendes). On the other hand, it is undoubtedly true that under certain conditions (large head, reduced tissue elasticity in old primiparae, large scars, unfavorable engagement, etc.), even an experienced obstetrician, supporting the perineum, is not in a position to protect it from rupture. Daily experience teaches us that the main moments contributing to rupture of the perineum during labor are: 1. The speed with which the head or shoulder girdle passes through the genital hiatus. The slower the head is born, the more perfectly it stretches the tissues and the fewer the chances of rupture. Of course, the degree of elasticity and compliance of the perineal tissues is also of great importance in this regard. That is why in young primiparae at 18–20 years of age ruptures are immeasurably rarer than in old primiparae after 30 years of age. That is why a perineum already ruptured during previous labors and sutured is particularly easily torn. On the same basis, edematous perinea covered with sharp condylomas or varicose nodes are more predisposed to rupture. 2. Discrepancy between the size of the head and the dimensions of the genital hiatus. A large head ruptures the perineum more easily than a small one. With a narrow genital hiatus—in infantilics—the perineum also tears very easily. This also includes the discrepancy arising as a result of the head passing through the genital hiatus with an unfavorable dimension, which happens with incomplete flexion of the head in occipital presentations or its incomplete rotation in the pelvic cavity (oblique or transverse presentation during birth, extensor presentations, posterior types). 3. The anatomical structure of the perineum, genital hiatus, and pelvis. High, unyielding perinea are encountered, which it is impossible to preserve even for an obstetrician with great experience. There is no doubt that in narrow pelves with an acute pubic angle, the perineum is subjected to greater tension, since the head cannot use the entire space under the pubic arch and deviates toward the perineum, thereby creating favorable conditions for rupture. The smaller the pelvic inclination, the more anteriorly the genital hiatus is located, and the stronger and more prolonged the head's passage strains the perineum. Rational perineal protection can eliminate or weaken some of the moments contributing to rupture. However, as already noted, this is not always successful, and in approximately 25% of cases, as Stockel indicates, the perineum still tears. According to the considerations presented, perineal protection has the task of: 1) slow passage of the head through the genital hiatus, 2) its passage in the most favorable—smallest—diameter, 3) weakening the tension of the perineal tissues.

Protection or support of the perineum is conducted by the majority of obstetricians in the USSR in the dors-Knee position, although in some countries (England) it is also performed in the side-lying position. In the supine position, a hard roll-pillow about 20 cm high is placed under the sacrum. The attendant stands at the right side of the parturient woman, who should spread her knees as wide as possible and bring her thighs as close as possible to the trunk with strongly flexed knee joints. The right hand, with the thumb abducted, is positioned so that the palm corresponds to the anus, the thumb is located on the right labium majus, and the remaining 4 fingers on the left (Fig. 48). The entire hand should closely adjoin the vulva and perineum with its entire surface, leaving its upper edge 1–2 cm free. It is a mistake to work only with the tips of the fingers. In order that the hand is not soiled by fecal masses squeezed out from the anus at each bearing-down effort, even in cases where the rectum was previously well emptied, it is recommended to place a flat piece of cotton wool moistened with a sublimate solution between the palm and the anus, which is desirable to change when soiled. The left hand is placed on top of the occiput region with possibly all fingers. Initially, work is done mainly with the left hand, trying with each bearing-down effort to promote greater flexion of the head and the appearance
under the pubic arch of the occiput. When the head begins to be born finally, with the same left hand, using the tips of the thumb and index finger, during a pause they try to carefully slide and tuck the tense edges of the labia and the frenulum of the clitoris behind the occipital tuber and finally release it. The right hand is brought into play only when the head begins to strain the perineum, stretching the entire genital hiatus and anus. The task of this hand consists of the following: 1) in the event that the head begins to rush out, make it pass more slowly, which is done with the palm; 2) with the same palm, support the perineum, giving it a good and wide support; 3) with the thumb and remaining fingers, by drawing the labia majora downwards, weaken the tension of the perineum. The birth of the occipital, anterior head part of the head and the upper half of the forehead should proceed with the most active bearing-down activity. The moment of rolling out from behind the perineum of the forehead and face—the most dangerous for perineal rupture—it is desirable to conduct with possibly weak bearing-down work.
To weaken the bearing-down efforts, the woman should be made to open her mouth wider and breathe with a full chest and during this time pass the head. Delivery of the head is performed with the help of both hands: the left embraces with all fingers the entire, already born part of the head, striving to strongly extend it. The right, remaining in its previous position, works in the opposite direction, striving through the stretched perineum and soft lateral parts covering the face to push the head anteriorly and simultaneously preserve the integrity of the perineum (Figs. 49 and 52). This method (instead of Ritgen's method) makes unnecessary the proposal of Olshausen, Ahlfeld, and others to enter the index finger into the rectum and from there, bending it hook-shaped, push the head out by the chin. If, applying the stated method, we are convinced that the head cannot pass without perineal rupture, it is better, without bringing it to a rupture, to perform the operation of episiotomy or, as suggested by Ott, perineotomy, since a cut wound heals better than a torn one. One should not early proceed to perineal protection: not earlier than the moment when crowning of the head occurs, i.e., when the head is already tightly engaged in the genital hiatus and no longer recedes from it outside of bearing-down efforts. Earlier perineal protection only harms the natural mechanism of birth. On the other hand, one should not be late with support, which is observed by no means rarely.
Breech Presentation

Protection of the perineum requires the most meticulous observance of the rules of asepsis and cleanliness of the hands of the attendant. It is necessary to begin disinfecting the hands well in advance, remembering that, especially in multiparous women, the head can cut through in 2-3 bearing-down efforts. After the birth of the head during a normal course of labor, a short break usually occurs. The bearing-down efforts, which up to this moment were very strong and frequent, sometimes subside for 1 1/2-2 minutes. This time must be used to clear the nose and mouth of the newborn from mucus, which is secreted from them in a viscous and abundant mass, as well as to wipe separately each little eye with pieces of cotton wool moistened in a sublimated solution, in order to remove any pus containing gonococci that might have gotten into it. After the birth of the head, one should not hurry with the extraction of the trunk. Such unhurried management of this moment of labor, according to Stoeckel, is beneficial to both the fetus and the mother: to the fetus because it frees the mouth and nose from mucus for subsequent free breathing, to the mother because the contractions in this period facilitate the separation of the placenta from the uterine walls, which eases the course of the third stage of labor. After this short but important procedure, the head is grasped with both hands through the ears and, making the parturient woman bear down and pulling gently on the head, an attempt is made to help its natural rotation with the face toward the corresponding thigh of the mother. When this rotation is completed, the neck becomes more accessible, and if there is a coiling of the umbilical cord around the neck, usually with a finger one can easily loosen its loop. Only in those cases where there are
phenomena of asphyxia, is it necessary to finish labor quickly. One should not waste time on freeing the umbilical cord coiled around the neck and excessively tightened, but rather simply cut it with scissors and already after the birth of the fetus tie it or apply a clamp. The delivery of the shoulders, although it usually proceeds more easily, is nevertheless also a critical moment, since sometimes the perineum, which remained intact during the passage of the head, tears during the delivery of the shoulders. The reason for this in most cases is the haste of the attendant and the failure to follow the necessary rules. It is best to begin the delivery of the shoulders when the anterior shoulder makes a full rotation and locates under the pubic arch. When delivering the shoulders, both hands grasp the head through the ears so that the ends of the 4 fingers of each hand are located at the neck of the fetus, and the thumb lies at the occiput (fig. 50). The head grasped in this manner must be pulled downwards, simultaneously forcing the woman to bear down. This leads to the appearance of the anterior shoulder from behind the pubic bone. When the anterior shoulder has passed (as much as possible), the left hand grasps with all fingers the downward-facing surface of the fetal head widely

Figure 51.
spread fingers (fig. 51). With this hand, the head is strongly lifted anteriorly and thus the posterior shoulder is extracted from behind the perineum. Simultaneously, the right hand is positioned in the exact same way as during the crowning of the head from behind the perineum. With the indicated technique, it is very easy to preserve the perineum while extracting the shoulders, after which the entire trunk slips out of the vaginal opening without difficulty. Only in rare cases can a difficult birth of the trunk be accelerated by extracting it with index fingers inserted into the armpits of the fetus. Now the newborn is positioned between the mother's thighs, face up so that it can breathe freely. The umbilical cord, if it is coiled around the neck, is freed and, in the absence of asphyxia, without haste, one observes how the newborn begi
Figure 52. Protection of the perineum with the parturient woman lying on her side.
ns its extrauterine life with the first movements of the limbs and often a piercing cry. Management of the third stage of labor. The methodology of ligation and transection of the umbilical cord - see Umbilical cord. Birth of the placenta. Despite the fact that in the majority of labors the third period—the birth of the placenta—proceeds without special difficulties for the parturient woman, this period is nevertheless no less critical in its consequences, and severe complications and sometimes a fatal outcome are frequently the result of unskillful and hasty management of this period. The dangers lying here are of a twofold nature: bleeding in the process of separation of the placenta and membranes, and incomplete separation of the placenta with parts of it left in the uterine cavity. At the present time, in order to avoid all these complications, the majority of obstetricians adhere to the expectant method of managing the third period, which can be rationally conducted if we at every time segment are easily able to navigate the course of the mechanism of separation of the placenta. To manage the third period within the limits of physiological conditions of the separation of the placenta and membranes, rough interventions and manipulations that traumatize the uterus should be avoided. Each rough palpation, rubbing, or pressing on the uterus leads to an uneven contraction of its walls, especially in the area of the placental site, and to complications even in cases where completely physiological conditions exist. The most dangerous moment of this period is undoubtedly the moment of detachment of the placenta from the uterine walls. After this detachment and after the expulsion of the placenta into the area of the outlet canal, the genital canal (isthmus and cervix), a less critical period of labor begins, which is why many obstetricians from this time change their line of conduct, carrying out more active measures. From what has been said, it is clear how important it is to be able to determine whether the placenta has already separated
Figure 53. Birth of the membranes, drawn along by the freely hanging placenta.
from the uterine walls, whether the placenta has left the uterine cavity or whether it is firmly attached to its walls. It is not surprising that over recent years a number of practical guidelines have been proposed for determining these moments, some of which are undoubtedly of great practical interest (fig. 53-55). After the birth of the fetus, a period of lull usually ensues. The pains cease, and the woman lies quietly, absorbed in interest in her newborn. It is best at this time to lay the parturient woman on her back, cover her with a warm blanket, and provide complete rest if possible, observing

Figure 54. Twisting of the membrane into a cord.
every 3-5 minutes the contraction of the uterus and the amount of blood lost. During this period of time, the amount of blood discharged from the vaginal opening is usually very small. The physician must observe the discharged blood, for which it is best, having placed the tied end of the umbilical cord on the abdomen, to press the genitals tightly with a large piece of sterile cotton wool and make the woman press her thighs tightly together. Thanks to this, in the event of bleeding, the blood does not flow downwards, but rises anteriorly, and the appearance of bleeding can be noted immediately. No rough palpations or massage should be performed at this time; on the contrary, the parturient woman should be given complete rest in the supine position.
* It must be remembered that the onset of detachment of the placenta from the uterine walls is signaled by the appearance of bleeding. This bleeding also should not serve as an indication for any interventions and may force the obstetric
Fig. 55. Position of the hand during the Crede maneuver and expressio placentae. One should resort to a series of measures only in case it becomes excessive. In order to assess the degree of bleeding, it is necessary to take into account: 1) the pulse of the woman in labor, 2) the amount of blood being discharged from the vagina, and 3) signs of separation of the placenta. With a slow pulse and good filling, there is no reason to fear the consequences of bleeding and at least for the next x/a hours, no measures should be taken. The amount of blood is determined either by simple observation or by collecting and weighing it, for which purpose a flat sterile vessel is immediately placed under the buttocks after the birth of the fetus, into which the blood flows and in which it can be weighed. To determine the degree of placental separation, it is necessary to consider the following circumstances. Immediately after the birth of the fetus, the fundus of the uterus is at the level of the navel. As the placenta and membranes separate from the walls of the uterus, its cavity changes its shape: the uterus elongates and flattens in the anteroposterior dimension. As a result, the fundus of the uterus rises upward and usually deviates to the right, sometimes reaching the height of the right hypochondrium. With the loss of the spherical shape of the uterus and the flattening of its walls, the lateral edges of the uterus (margins) become accessible to palpation. According to Steckel, these signs indicate that the placenta has separated from the walls of the uterus but has not yet been expelled from its cavity. After the birth of the placenta, the uterus drops sharply. Its fundus stands somewhat higher than the midpoint - between the navel and the pubis. These three positions can be determined very easily and accurately. They can be masked only by passive elevation of the uterus when the bladder is full of urine or by expulsion of the placenta into the dilated cervical canal. But in the latter case, the presence below of a firm, well-contracted uterus of a soft, visible protrusion under the pubis decides the question without error. If the placental period proceeds normally, then usually after 20-30 minutes the placenta is found to have already separated and been expelled into the cervical canal. Many obstetricians, even in this case, consider it necessary not to interfere with the course of labor. Others make the woman in labor bear down periodically to expel the placenta. The effectiveness of bearing down in the case where the placenta does not come out can be increased by the Baer maneuver: both hands grasp the abdominal wall in a fold so that the rectus muscles of opposite sides are grasped by the fingers. If the woman in labor is now made to bear down, the effect of the bearing down is increased (due to the fact that this maneuver eliminates the diastasis of the rectus muscles and significantly reduces the volume of the abdominal cavity), and the placenta comes out easily. However, it is undoubtedly true that even a placenta that has separated from the walls of the uterus can remain unexpelled for a long time due to the lack of the necessary contractile activity of the uterus. At present, in such cases, waiting for spontaneous expulsion of the placenta is not considered rational, and most obstetricians consider it necessary to reduce the waiting period to 3 hours, 1 hour, and even to half an hour, after which they proceed to express the placenta [the maximum waiting period should not exceed 4 hours (Selitsky)]. In general, it is possible to resort to expressing the placenta as soon as, on the basis of observations, we are convinced of its complete separation from the walls of the uterus. Expressing a placenta that has not separated from the walls of the uterus and has not been expelled into the cervical canal is permissible only in the case of pathological bleeding or if, after at least 3 hours after the birth of the fetus, there is no spontaneous separation of the placenta from the walls of the uterus. Technique of expressing the placenta. Knowledge and proper execution of this maneuver has great practical importance. Excessive haste and improper application create the pathology that leads to serious consequences. Before applying the expression of the placenta, which is called expression according to Crede (see Obstetric manual maneuvers), it is first necessary to empty the bladder, either by making the woman in labor urinate or by resorting to a catheter. Failure to observe this rule often leads to the fact that all efforts are futile: a full bladder is located in the path between the part of the genital tract in which the placenta lies and the lower segment of the cervical canal and prevents the exit of the placenta. One should not pull on the umbilical cord, although moderate pulling on it can help to straighten the vaginal walls and thus facilitate the exit of the placenta. This maneuver can be repeated 2-3 times.

Fig. 56. Examination of the maternal surface of the placenta. The lobules are intact.
If after the birth of the placenta the membranes are retained and do not slip out of the genital cleft, it is best to take the placenta in both hands and, turning it clockwise, roll the membranes into a spiral. In this way, in most cases, it is possible to prevent tearing off part of the membranes. One can clamp the membranes as high as possible with a clamp (Kocher) and carefully extract them, moving the clamp higher and higher, until all the membranes are expelled. This concludes the entire act of labor. After this, the obstetrician only has to perform a thorough examination of the genital sphere, clean the external genitalia from clots of blood and pieces of vernix caseosa that may adhere to them. It is rational after labor to perform a thorough washing with warm boiled water and soap of the vulva, the inner surface of the thighs, and the lower part of the abdomen. Usually these manipulations are performed by the midwife, while the doctor at this time should attend to a thorough examination of the placenta and membranes. Turning the placental surface of the placenta outward, he inserts both hands into the uterine cavity and, placing the placenta on them, carefully verifies the integrity of the entire placenta (fig. 56-58). It is necessary to be convinced not only of the integrity of the placenta, but it is also necessary to carefully examine the membranes on a light source: whether a complete accessory placenta has been left in the uterus. This is not difficult to verify: if on the membranes, when examining them on a light source, we see a lighter window (only the amnion) and vessels approach the edge of this window, the presence of an accessory placenta left in the uterine cavity is undoubtedly present. It is not always easy to reconstruct all the membranes when examining them, however, this also succeeds in most cases. The important significance of accurately determining the integrity of the placenta has led a number of authors to seek, besides examination, other ways of proving the integrity of the placenta. Thus, O. Küstner proposed his milk test, consisting in injecting milk into the umbilical vein with a large syringe. If with such an injection milk does not seep from the uterine surface of the placenta - it is intact and the test is negative. If milk appears on the surface, the test is positive - the placenta has defects (Korkia). The so-called air test has also been proposed. Instead of milk, air is introduced into the umbilical vein, and the placenta itself is placed in water. The appearance of air bubbles in the water indicates a violation of the integrity of the placenta (Franken, Derchinsky). This test has been somewhat modified by Sachs and called the swimming test, because an intact placenta after air injection floats on the surface of water in a horizontal position, while a placenta with defects either sinks or takes an oblique position in water (Korkia, Derchinsky, Hanutin and others). Of these three tests, apparently the last one - the swimming test - most satisfactorily resolves the question, although it cannot be considered fully conclusive. The absence of a placental lobe or even a complete accessory placenta is an extremely unfavorable phenomenon. Having convinced himself of this, the doctor is obliged, while observing the strictest rules of asepsis and under anesthesia, to examine the uterine cavity manually and remove the remaining pieces of placenta from it. Undoubtedly, the retention of only the membranes does not have such important significance as the retention of pieces of placenta, and therefore does not require the extremely undesirable introduction of the obstetrician's hand into the uterine cavity. The birth of the placenta ends the period of labor. The woman in labor should be given complete rest in a clean and fresh bed. However, the person who conducted the labor should remember that the first 2 hours the woman in labor requires the most careful observation: the uterus may relax and severe atonic bleeding may occur, therefore as a rule the doctor or midwife should not leave the woman in labor during the first two hours, while in obstetric institutions she spends this time in the delivery room.
Fig. 58. Examination of the fetal membranes. The membranes are torn.
beyond examination, other ways have been sought by a number of authors that prove the integrity of the placenta. Thus, O. Küstner proposed his milk test, consisting in injecting milk into the umbilical vein with a large syringe. If with such an injection milk does not seep from the uterine surface of the placenta - it is intact and the test is negative. If milk appears on the surface, the test is positive - the placenta has defects (Korkia). The so-called air test has also been proposed. Instead of milk, air is introduced into the umbilical vein, and the placenta itself is placed in water. The appearance of air bubbles in the water indicates a violation of the integrity of the placenta (Franken, Derchinsky). This test has been somewhat modified by Sachs and called the swimming test, because an intact placenta after air injection floats on the surface of water in a horizontal position, while a placenta with defects either sinks or takes an oblique position in water (Korkia, Derchinsky, Hanutin and others). Of these three tests, apparently the last one - the swimming test - most satisfactorily resolves the question, although it cannot be considered fully conclusive. The absence of a placental lobe or even a complete accessory placenta is an extremely unfavorable phenomenon. Having convinced himself of this, the doctor is obliged, while observing the strictest rules of asepsis and under anesthesia, to examine the uterine cavity manually and remove the remaining pieces of placenta from it. Undoubtedly, the retention of only the membranes does not have such important significance as the retention of pieces of placenta, and therefore does not require the extremely undesirable introduction of the obstetrician's hand into the uterine cavity. The birth of the placenta ends the period of labor. The woman in labor should be given complete rest in a clean and fresh bed. However, the person who conducted the labor should remember that the first 2 hours the woman in labor requires the most careful observation: the uterus may relax and severe atonic bleeding may occur, therefore as a rule the doctor or midwife should not leave the woman in labor during the first two hours, while in obstetric institutions she spends this time in the delivery room.
Fig. 58. Examination of the fetal membranes. The membranes are torn.
K. Skrobansky. Obstetrical Examination in Labor. Obstetrical examination in labor, generally speaking, repeats the obstetrical examination used at the end of pregnancy. The essential difference lies in the fact that obstetrical examination at the end of pregnancy collects and analyzes data characterizing the condition of the pregnant woman and fetus at a strictly defined moment—it is, so to speak, static. Obstetrical examination in labor consists of a series of repeated examinations and seeks to determine not only the condition of the parturient and fetus at the given moment, but also all those changes that occur during the process of labor—it is dynamic. Some modern obstetricians seek to limit themselves in labor to only external examination, since it is obvious that it is precisely in labor that the danger of internal examination in terms of introducing infection into the birth canal of the parturient is especially great. And indeed, in the vast majority of cases, the questions posed to the obstetrician in conducting labor are fully resolved by external examination alone. Thus, by external examination, the question of the position of the fetus, its presentation, position, and variety is resolved. However, unlike examination during pregnancy, external examination in labor sometimes gives less distinct data than during pregnancy. The reason is that with the onset of labor activity, the uterus even in the intervals between contractions is still in a contracted and tense state, and this greatly hinders palpation of the fetus and its individual parts—hence the data obtained are not always completely distinct. Measurement of the pelvis in labor differs in no way from measurement of the pelvis during pregnancy, except that measurement of the diagonal conjugate becomes impossible when the presenting part of the fetus has descended into the upper part of the pelvic cavity. When evaluating the pelvis during labor, in addition to direct measurement with a pelvimeter, it is also necessary to pay attention to the relationship between the capacity of this pelvis and the presenting part of this particular fetus. This is achieved both by observing the engagement and further descent of the presenting part and by applying the maneuvers of Hofmeier and Müller (see Obstetrical Manual Maneuvers), with the help of which the presenting part is as it were pressed into the pelvis of the parturient and thus the chances of its passage through this pelvis are determined. Of the questions that directly relate to the act of labor itself, the first is whether labor has already begun. This question is usually easily resolved by observing the condition of the uterus: if the uterus contracts periodically, if these contractions are strong and sensitive, and if mucus slightly tinged with blood appears from the sexual organs, then we have true labor contractions, and therefore labor has begun. Contractions are quite clearly determined visually by the change in the shape of the abdomen, but they are determined more precisely by touch: with the hand placed on the uterus, not only its contractions but to a certain extent their strength and duration are determined. It is already more difficult to resolve by external examination how far labor has progressed, and this is especially difficult in the dilatation period. Indeed, the dynamics of labor in the dilatation period are characterized by the degree of effacement of the cervix (in primiparas) and the degree of dilatation of the external os. In labor proceeding normally, these changes in the cervical canal can be judged to a certain extent by inference, taking into account the number and strength of individual contractions, for which, of course, constant observation of the given parturient is necessary, which in practice is almost completely unfeasible. However, even with such observation, major errors are possible, since the character of the cervix itself is an unknown quantity (for example, after repeated artificial abortions, after inflammatory diseases of the cervix, finally in healthy but elderly primiparas, the cervix may change in its structure so much that its effacement and dilatation may proceed quite atypically). The proposal to judge the dilatation of the cervix by the condition of the boundary (contraction) ring over the symphysis pubis is not always justified in practice, although individual observers speak in favor of the sufficient accuracy of this method (thus, Kuznetsov obtained only 29 unsuccessful determinations out of 920 examinations verified by internal examination). In the expulsion period, the progressive movement of the fetus can be judged with considerable accuracy by determining externally the gradual engagement of the presenting part into the cavity of the lesser pelvis and supplementing this determination by repeated auscultation of the best audibility of the fetal heart sounds, which also moves downward and toward the midline as the fetus advances. When the presenting part descends into the lower part of the pelvic cavity and begins to enter the pelvic outlet, the progress of the fetus can be followed from the perineal side as well, by pressing with fingers in the direction of the presenting part and observing with the eye its bulging during contractions and the gradual dilatation of the anal opening and vulvar cleft. However, even now such examination can be misleading if a large labor tumor forms on the presenting part. From the foregoing it is obvious that even with the normal course of labor and with constant observation of the parturient, the obstetrician on the basis of external examination alone still cannot always give a precise answer to such details of the act of labor as the degree of dilatation of the cervix and the degree of descent of the presenting part through the birth canal. Meanwhile, the answer to these questions in the vast majority of cases is obtained easily and simply by means of internal examination. Hence it is already clear that internal examination greatly simplifies and facilitates the purely practical tasks of the obstetrician; however, it becomes necessary when the obstetrician has not observed the given labor from the very beginning or has observed it with large intervals, and yet due to circumstances it is necessary for him to form, even if only an approximate, but sufficiently precise idea of the state of the act of labor at the given moment. Needless to say, more detailed questions related to observation of the act of labor are difficult to resolve without internal examination. The task of studying all the intricacies of the mechanism of the act of labor is completely insoluble without it. Meanwhile, the obstetrician quite often has to deal with anomalies of the mechanism of labor having direct practical significance, and the ability to determine and evaluate these deviations from the norm is given only by means of long and persistent cultivation of one's stereognostic tactile sense. This same sense proves to be absolutely necessary for all obstetrical manipulations and operations performed 'blindly', 'by feel'. Hence it is obvious that practice in internal examination of parturients is an essential prerequisite not only for diagnostic purposes but equally for the precision of operative work. Let us note here that immediately before obstetrical operations, internal examination is sometimes useful to perform not with one or two fingers, as usual, but with four fingers—II, III, IV and V, i.e. 'half-hand' or even the whole hand. The inestimable advantages of internal examination and at the same time the desire to do without it have led to the proposal that instead of examination through the vagina, examination through the rectum be performed. It is quite obvious that rectal examination does not present the dangers in terms of infection to the parturient that are inherent in examination through the vagina. Unfortunately, however, rectal examination far from gives such precise data as are necessary to clarify existing deviations from the norm, for which reason many obstetrical schools do not use it at all. This is understandable if one takes into account that between the presenting part and the examining finger, besides the glove, there also lies the rectovaginal septum, which in pregnant women is often edematous and thickened due to dilation of the venous plexuses (hemorrhoidal condition). If one is to evaluate the above-mentioned methods of obstetrical examination, it is necessary to recognize that all of them have and should have their application at the bedside of the parturient, and that internal examination plays the main role in all doubtful and complicated cases of labor. It is also necessary to recognize that for the study of obstetrics it is absolutely necessary to go through the school of internal examination, because even the fineness and precision of external examination are developed in the obstetrician only insofar as in the beginning of his activity he verifies by internal examination the data that he obtains by means of external. In purely practical terms, the exclusion of internal examination has its definite negative aspects, for example, it often leads to delay in providing necessary obstetrical assistance, for which reason the average duration of labor conducted with only
Figure 59. Apparatus for internal hysterography: Champetiey's balloon introduced into the cervix and inflated with water under pressure from a reservoir. The manometer allows to account for pressure, * the pressure transmitter records the curve by means of Marey's drum.
by external examination will be greater than that in widespread use and internal. (This however by no means indicates the need for the routine performance of internal examination in every breech presentation.) Apparently the positive and negative aspects of internal examination are more or less balanced and in the final outcome the abandonment of internal examination does not in the majority of cases bring the advantages that were expected from it. Precise clarification of all 'pros and cons' does not seem possible, it would seem, through mass observations and statistical generalizations--such works exist, but they have not yet led to a final and indisputable solution to this vexing obstetrical question.-Besides the above-mentioned ordinary methods of obstetrical examination, other methods are also used for scientific purposes in studying the act of labor. Among these methods, first of all we should
Figure 60. Apparatus for hysteroscopy with pneumatic transmission.
not, it would seem, through mass observations and statistical generalizations--such works exist, but they have not yet led to a final and indisputable solution to this vexing obstetrical question.-Besides the above-mentioned ordinary methods of obstetrical examination, other methods are also used for scientific purposes in studying the act of labor. Among these methods, in the first place we should
Figure 61. Apparatus for external hysteroscopy with recording (direct).
point to tokometry or, more precisely, to tokodynamometry and to radiography (radioscopy is still little used in obstetrics, since with simple screening it is not possible to obtain a sufficiently clear image of the fetus on the screen). Tokodynamometry was proposed in 1872 by Schatz and during the past 60 years this method has been repeatedly used both for studying the act of labor and in particular for studying the effect of various medicinal ^, agents on the labor contractions of the uter-^ us and abdominal press. The meaning of the method *^ is that a small rubber balloon ? I (prototype of the metrerenter) is introduced into the uterus, connected
Figure 62. Apparatus for mixed (internal and external) hysteroscopy.
by a tube to a Mareev drum (peloton). Fluctuations in pressure in this system are recorded with the aid of a kymograph. Fabr-called the experimental study of uterine contractions and their depiction by means of special apparatus in the form of a graphic curve- hysteroscopy. which depending on whether the study of uterine contractions is carried out by introducing the balloon into the uterine cavity or by using writing apparatus on the abdominal wall, can be external or internal. Fabr considers that external hysteroscopy has all the advantages and that with its help one can accurately visualize uterine contractions during labor and control them when introducing various agents acting on uterine musculature. Without dwelling on criticism of the method itself from the standpoint of its accuracy, we will note here only that in terms of introducing infection into the uterus, various methods of internal hysteroscopy may 56 55 54 53 52 51 50 49 48 47 46 Intrauterine balloon Hysterotraf UUVjLA/ 12 6 0 54 48 42 36 30 24 18 12 Intrauterine balloon -<-.------- External hysteroscope Figure 63. Curves of uterine contractions, perceived
_,„ s. -.,.,.,™ „;,-,„„„„,, p„„„opa -„.„. TO;o«<, nmrrnnoim™,, ™ uimrinuM nv
menno perceived by the internal and external routes. Fast curve-1 cm per minute.
tem> Slow curve-1 cm in 6 minutes.
50 g sugar 50 g sugar 50 g sugar Figure 65. Effect of sugar in cases of primary uterine weakness. Each dose of 50 g sugar produces several contractions which quickly disappear.
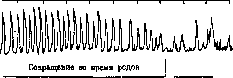
Contraction during pregnancy Figure 66. Transition of contractions during pregnancy to rhythmic labor contractions.
Figure 67. Effect of ergotin in weak labors (2 centigrams). Contractions became paired (+).
present a certain danger. One can reconcile oneself to the use of this method for strictly scientific research, but in everyday practice it naturally has not found wide application, and yet completely objective registration of the number and strength of labor contractions could have considerable practical importance <fig. 59-67). Attempts were made to replace intrauterine tokodynamometry with external - by attaching the peloton directly to the abdominal wall of the parturient above the uterus-or also internal, but by introducing the balloon not into the uterus but into the rectum (proctotokcgraphia). If intrauterine tokodynamometry is highly vulnerable from a methodological standpoint, then it is quite understandable that external and rectal methods are vulnerable to an even greater degree. However, it would be wrong to completely deny the significance of these methods of studying the labor process both in scientific and in applied aspects. Some hopes were placed on the possibility of studying labor activity by means of electrogisterography (by analogy with "electrocardiography"). This also includes the study of cardiac activity of the fetus during labor (and pregnancy) by means of the same Einthoven string galvanometer (Eint-hoven), as well as by means of apparatus used in radio (amplifiers, loudspeakers). At present this technique has not gone beyond the "first steps" stage. It is quite certain that the most brilliant future awaits the development of the X-ray method of research. Already the data that have been obtained to the present time have introduced much that is new into the field of obstetrical research, and with further improvement and simplification of technique one can expect that the X-ray apparatus will become an integral part of the delivery room, and then questions that now sometimes present insurmountable difficulties will be solved quickly, simply and without the slightest danger to mother and fetus.-To conclude the question of obstetrical examination in breech presentation, we should also speak of the methods of examination in the placental period of labor.-up to the present time these methods consist of external observation of uterine contractions, of the condition of its fundus and finally of the expulsion of the placenta itself into the vagina. By all these methods, quite sufficient data are obtained for judging the course of the placental period of labor. For completeness only, it should be noted that in the very recent time American authors have proposed to follow the course of the placental period by means of internal vaginal examination. One must think that this proposal will not find many supporters. For scientific research purposes, the X-ray method has been introduced into the study of the placental period (examination by filling the vessels of the placenta with a contrast medium), but the accuracy of this method meets particularly strong objections from a methodological standpoint precisely in this area.
M. Kolosov. VI. Anesthesia in childbirth. Traces of primitive obstetric anesthesia as the embryos of modern methods of anesthesia in childbirth can still be observed now among peoples who have remained at the level of primitive culture. The history of obstetric anesthesia as a scientific method begins only in the middle of the 19th century, i.e., from the time of the introduction of chloroform and ether into surgical practice. Its initiator, who gave it the first scientific substantiation and developed it practically, should be considered the Edinburgh professor Simpson, who first used ether for childbirth (January 19, 1847), and then chloroform (November 8, 1847). Thus England became the birthplace of obstetric anesthesia. Having become widespread here, it gradually won its rights of citizenship long ago and everywhere. Childbirth "royal style" ("a la reine"), first performed by Simpson on Queen Victoria of England, became quite common first "among the privileged classes of English society", and then among the general population of England, America and other countries. Simpson, who wrote a number of valuable articles devoted to anesthesia in childbirth and made several reports on this topic to the Edinburgh Obstetrical Society, came to the conclusion that anesthesia in childbirth, while fully achieving its purpose, at the same time does not exert any noticeable harmful effect on either the mother or the fetus, but of course only on the condition of its skillful and very careful application. Soon after Simpson, many English obstetricians published their reports on the use of chloroform in childbirth, and in most cases with positive encouraging results. In later English literature, similar reports appeared comparatively rarely because obstetric anesthesia (both with chloroform and ether) took root in England quickly and successfully thanks to Simpson, without causing particular objections, and was used in hundreds of thousands of cases of normal childbirth with good results. In England, after Simpson, many authors used ether for anesthesia in childbirth. The English and American literature is very rich in reports on the successful use of ether in childbirth.-In France, Dubois, and after him many others, for a long time were skeptical about etherization in childbirth. In contrast to England and America, in France, especially at the end of the 1870s, a real war was declared on the defenders of any kind of anesthesia in childbirth. Prominent representatives of the French obstetric school (Pajot, Tarnier, Pinard, Poulet) treated obstetric anesthesia partly skeptically, partly quite hostilely (Pajot was especially an ardent opponent). However, among French obstetricians, ardent supporters of obstetric anesthesia were also found. The reason for these disagreements was that opponents of obstetric anesthesia understood and applied it irrationally, i.e., they used ordinary "surgical" anesthesia, whereas the initiators and propagandists of this method meant by "obstetric anesthesia" a very superficial and moreover intermittent semi-anesthesia (minimal doses at the very beginning of contractions or pushing, which for a long time maintains a state of light sleep). In Germany, obstetric anesthesia, although it did not have as many ardent supporters as in England and America, also did not meet with particular opposition (with the exception of Winckel, Donhoff and some others). The most zealous defenders of it here were Spiegelberg, Schroeder, Zweifel, and in later times Steinbuehel, Kronig, Gauss and Siegel (Freiburg clinic). This clinic developed and vigorously propagated a special method of obstetric anesthesia, achieved by combined scopolamine-morphine anesthesia, causing a state of half-sleep, drowsiness (Dammerschlaf), sufficient for anesthesia in childbirth. The technique of this method is as follows: complete isolation of the parturient, darkened room, elimination of all visual and auditory irritations (as mandatory prerequisites, all these conditions are hardly achievable in the setting of a large maternity hospital). Dosage - morphine 0.01 (subcutaneously), scopolamine (also subcutaneously 0.0003; if necessary, both can be repeated). Coming into a state of half-sleep, the parturient, although she still reacts more or less noticeably to external irritations, perceives them so vaguely that contractions and pushing do not cause her a clear painful sensation, so that later she almost completely retains no painful memories of childbirth. The amount of morphine and scopolamine administered varies individually and is established empirically, ad hoc. Siegel proposed a "simplified schematic Dammerschlaf"; he replaced the usual scopolamine with an undecomposable stable preparation of it, and morphine - first with narcophine, and then with amnesin. (Injections begin already in the period of dilatation and are repeated every hour until the end of the expulsion period, and after every third injection of scopolamine, amnesin is added.) However, the reviews of this "simplified schematic" method were almost entirely negative. In general, scopolamine-morphine anesthesia proved to be very dangerous, often leading to fetal asphyxia and associated with unpleasant side effects in parturients. In Russia, one of the most ardent supporters and in fact the initiator of obstetric anesthesia was N. Sochava, who studied it in its homeland in England and wrote a number of works on this question as early as the 1860s of the last century. He was the first, relying on the vast English literature and his own observations, to persistently call on Russian obstetricians to come to the aid of the suffering parturient and to fight against any stagnation in this matter, against the former prejudice against anesthesia in childbirth, which, in his opinion, had no scientific basis. In general, the merits of N. Sochava in the development of this question in our country are very great.-Further, such a doyen and founder of Russian obstetrics as Prof. Krassovsky, also successfully using anesthesia in childbirth (chloroform), definitely spoke in favor of it, emphasizing that it should be used in minimal doses, at which point it does not reach complete anesthesia. Professors Gurevich (from the clinic of Prof. Gorvits), Dobronravov, and Prof. Yasinin spoke in the same favorable sense. Prof. Lazarevich in his textbook of obstetrics also pointed to the beneficial effect of light chloroformization in childbirth (of its half-sleeping effect). In 1895-96, Russian (and German) obstetric literature was enriched with very valuable works by Bukoysky. He conducted his clinical observations with the help of a tokodynamometer and, contrary to all authors who used this method (Shats, Poulet, Donhoff, Pullo), came to the conclusion that chloroform as a means of anesthetizing childbirth is quite appropriate, although it is inferior in this respect to ether. Bukoysky's carefully conducted experiments brought a great deal of valuable material to the problem of anesthesia in childbirth. He precisely proved that small doses of chloroform do not weaken uterine contractions; if it sometimes causes some slowing down of childbirth, it is so insignificant (of course with small doses) that it has no practical significance and is completely harmless to the parturient. As for ether, according to Bukoysky, it not only anesthetizes childbirth, in no way slowing them down, but due to its general exciting action, it can increase the strength of uterine contractions and therefore often even accelerates childbirth, without adversely affecting either the mother (in terms of sequential bleeding or in terms of disruption of postpartum involution) or the fetus (children were born normal, without signs of asphyxia). In 1906, a monograph by Kurdinovsky on the question of anesthesia in normal childbirth appeared. Kurdinovsky based his work first on experiments on the rabbit uterus (both as an isolated organ and on the uterus in vivo). The final conclusion of Kurdinovsky comes down to the fact that carefully applied anesthesia in the sense of true, purely obstetric anesthesia, as it is used mainly by English and American obstetricians, contrary to the opinion of many authors, by no means slows down the act of childbirth and, on the contrary, by regulating excessively painful uterine and abdominal press activity, sometimes accelerates labor, without adversely affecting either the mother or the fetus. The explanation for these facts, which find confirmation in many similar reports in the literature, is as follows. In the concept of "labor pains" two main features must be distinguished. The main one is the contractions of the uterus and abdominal press, equally necessary as objective moving factors determining childbirth. The second feature is purely subjective (painful sensations), being constant but entirely secondary to the first (i.e., contractions), in itself has no significance in the mechanism of childbirth. Both features usually coincide in time, but without the first, childbirth is unthinkable, while the second can sometimes be absent, and the normal course of childbirth does not suffer from this [cases of relatively painless, almost imperceptibly proceeding childbirth (Sturzgeburt), catching the woman unawares]. The complete confusion of these, although related, but essentially different features, is the main reason for the fundamental disagreements in the question of the influence of obstetric anesthesia on childbirth.
If the anesthesia is superficial, i.e., if it does not go beyond the limits of the first stage, which provides, although not always complete analgesia, but in any case significant dulling of pain sensitivity, then such pain relief does not noticeably affect either the uterine contractions or the work of the abdominal press. The latter sometimes even increases under the influence of the excitement characteristic of the initial stages of the action of narcotic substances (ether, morphine). The uterine muscle, like any smooth muscle, undoubtedly possesses (this can be easily verified in an experiment on an isolated organ) independent, i.e., independent of any central influences and local nerve apparatuses, purely myogenic excitability. If all these influences are eliminated or weakened by any means, then the uterus always has in reserve another source ensuring its further contractile activity, namely myogenic excitability, by which impulses for contractions already arise in the smooth muscle fibers themselves.-Apparently all narcotic substances acting primarily on the nervous system do not noticeably affect the smooth muscle tissue as such. Only this can explain the well-established fact of the indifferent attitude of the animal uterus even to very large doses of narcotic substances and numerous observations of the smooth course of labor in women despite the use of anesthesia in the form of superficial obstetric anesthesia. The technique of such light intermittent (chloroform) anesthesia (as most accessible to the doctor under any conditions) is described in detail by Kurdinovsky. Superficial anesthesia, not crossing the border beyond which relaxation of striated muscle begins, also does not affect the activity of the abdominal press and therefore ultimately cannot cause a delay in labor. It is important to keep in mind that at the very end of the expulsion period, very superficial anesthesia may already be insufficient for pain relief; therefore, in the most painful moments (crowning of the head), it always has to be deepened. In connection with this, the question usually arises as to how anesthesia affects the preservation of the perineum. Kurdinovsky, based on literary data (Simpson and others) and on his own experience, resolves it as follows. Anesthesia plays a dual role here. On the one hand, its intensification, inevitably somewhat weakening the contractions, should slow down the too rapid crowning of the head. On the other hand, by relaxing the striated muscle tissue of the perineum and reducing its resistance, it should accelerate the crowning, however, this does not at all increase the chances of perineal rupture, and precisely because under the influence of anesthesia it becomes more pliable. Other types of inhalation anesthesia are also used in labor, namely: nitrous oxide ('laughing gas') together with oxygen (especially in America), as well as brief stunning with chloroethyl (during crowning of the head).-As for spinal anesthesia, recommended by many, it has not become widespread and cannot be considered suitable for pain relief in labor for many reasons (far from every doctor possesses the proper technique of this anesthesia; in addition, it often turns out to be insufficient precisely at the most needed, most painful moment, and so anyway one has to resort to rapidly acting chloroform, and finally it is often associated with a number of very unpleasant side and sometimes rather persistent phenomena).- Also relatively little spread are the following types of local anesthesia. 1) Sacral, limited to pelvic organs anesthesia by Steckel,-injection of a solution of the following composition: Novocain 1.0, Natr. bicarbonicum 0.25, Natr. chlor. 0.35, Natr. sulf. 0.5, Aqua destillata 100.0, directly into the sacral canal; the advantage of the method is that it is applied extradurally, far below the dural sac; completely safe compared to lumbar anesthesia and technically simpler: its technique--the woman lies on her left side with strongly pulled thighs; hiatus sacralis is easily palpated above the crest of the sacral bone, directly above the coccygeal process (in not too obese women), in the form of a kind of fontanelle; insertion of a needle into it is achieved without difficulty and painlessly; Steckel himself admits that the effect of this anesthesia is not always reliable and sufficient, but when it succeeds, pain relief at the very end of the expulsion period is often fully achieved and moreover safely for both mother and fetus; at the same time, relaxation of the perineal tissues is observed, which facilitates its protection and almost eliminates the danger of rupture. 2) Zigel recommended paravertebral and parasacral conduction anesthesia, but this method has been little tested so far. 3) So-called 'pudendal anesthesia' by Selgeim [in which a solution of novocaine with adrenaline is injected into both ischial tuberosities (the site of passage of the main trunks of n. pudendi), which anesthetizes the perineum and thus allows painless crowning of the head] has also not yet received general recognition. The latest proposal (Oettingen and others) to conduct labor in a state of hypnotic half-sleep is still in the development stage. Recently, some have adopted a new, so-called synergistic method proposed by Gwatmey, consisting in the combined use of morphine, magnesium sulfate, ether, quinine, and oil [along with the administration of morphine (once 0.01) and magnesium sulfate (up to 3 times 2 cm3 of a 25% solution)- after an hour rectal anesthesia (Chinini hydro-brom. 1.2, Alkohol 12.0, Aeth. sulf. pro narcosi 70.0,01. oiivarum ad 120.0)]. The favorable effect of the combination of morphine with magnesium is explained by the fact that magnesium promotes greater fixation of morphine in nerve cells. However, this method has not received special distribution either in the West or in the USSR. Along with the good results described by the authors, a state of extreme excitement, mental disturbance, and, in the expression of Ecke and Taubert (Ecke, Taubert), parturients give the impression of being insane, e. Kurdinovsky. VII. Influence of various factors and external conditions on the course of the labor act. The significance of constitution for the labor act has not yet been sufficiently revealed. This circumstance is explained by the complexity of the problem of constitution as such, the difficulty of differential characteristics of individual constitutional types and exclusion of other very diverse factors that can influence the labor act, due to which it is extremely difficult by means of clinical observations (and there are no other ways of studying this problem) and analysis to evaluate the isolated value of each individual factor and in particular constitution. In studies devoted to the influence of constitution on the course of the labor act, constitutional types were predominantly characterized by their morphol. features as most accessible in the maternity ward, although morphol. characterization, being a valuable element in assessing the constitutional profile, by no means exhausts it. Many indicators of the course of the labor act such as: frequency of premature labors, duration of the labor act, time of rupture of membranes, frequency of complications and trauma in labor, course of the postpartum period, etc., are observed to varying degrees in one or another constitutional type. Especially supposedly 'inadequate' in this sense are the groups of hypoplastic and infantilic women (Serdjukov). The insufficient persuasiveness of this conclusion follows at least from the very low specific weight that this group has among the parturients and therefore extremely modest material of observations. Greater interest and significance are the data characterizing the attitude to the labor act of the most frequently occurring picnic, asthenic, and 'average' between them types. Indicators of the course of the labor act in asthenic women, according to the data of many authors, are worse than in picnic women. The percentage of premature labors is higher in asthenic women than in picnic women. The same and in relation to premature rupture of membranes. Duration of labor is longer in asthenic women (Serdjukov), but according to the data of Terebinskaya-Popova, on the contrary, the longest duration of labor is in picnic women. The percentage of complications is also higher in asthenic women. The frequency of forceps application, which may be an indirect characteristic of the frequency of complications, weakness of labor activity, etc., according to the data of Terebinskaya-Popova, is 3 times higher in asthenic women compared with picnic women. Approximately the same ratios are also observed in relation to complications and interventions in the postpartum period.
The main drawback of all this data, which significantly diminishes their value and persuasiveness, is: a) the small number of observations, the multiple classification of constitutional types, with the introduction of a number of intermediate categories with indistinct boundaries and characteristics (infantile asthenics, infantile picnics, non-characteristic asthenics, etc., a total of 9 groups in Seryukov); b) in some places methodologically incorrect assessment of conclusions (the frequency of perineal tears in asthenic women is 10.7%, while in picnics and infantile picnics it is 11%, which is characterized as a 'definite regularity' by Seryukov); c) the absence in the analysis of these conclusions of consideration of the possible average error, which must necessarily be taken into account in clinical-statistical research. Summarizing what has been said, it must be concluded that at present we do not have precise, scientifically verified positive data on the influence of constitution on the course of labor. The study of this question in obstetrics is possible only through its development by large obstetric institutions according to a pre-planned program, which could ensure both sufficient volume and the scientific and methodological unity necessary for solving this important problem. The significance of physical education for the course of labor, in connection with its widespread mass dissemination among the working population, especially in industrial centers, currently has great practical interest. There are no exhaustive concrete data on this question. Along with numerous observations indicating the favorable influence of physical education on labor, there are individual observations indicating an unfavorable course of labor in persons who engaged in physical education for a long time (increased pain of contractions, prolongation of the dilatation period, rigidity of soft parts, higher frequency of tears, etc.). However, these observations are isolated and are lost in the mass of observations of the opposite order. The practical importance of this question makes it necessary to verify the data on the influence of physical education on the course of labor on a large amount of material, which is currently being undertaken on the initiative of the obstetric-gynecological commission at the Moscow Soviet of Physical Culture in a number of obstetric institutions in Moscow. Of the individual types of physical exercises and complexes for women's physical education, from the point of view of their influence on the course of labor, dynamic exercises are more suitable, affecting individual systems and the entire organism as a whole, in contrast to static exercises with their predominant orientation on exercising individual, although important (but in themselves not determining the entire course and outcome of labor), components, such as abdominal muscles, pelvic floor, etc. A considerable number of studies are devoted to the influence of professional labor on the course of labor. But in their vast majority, they are methodologically completely flawed material, considering labor outside its historical specificity and isolating it from the social connections and environment in which it takes place. Hence the one-sided characterization of labor as a 'professional harm' during labor, which in the most extreme formulations in this direction takes the form that 'labor is incompatible with motherhood' (M. Hirsh). There are definite data (Geller and others) that in female workers of various types of production, the course of labor does not differ from that of non-working women. There are undoubtedly data on the favorable influence of labor processes in women on the course of labor. The significance of age differences in the course of labor in primiparas has not yet received exhaustive illumination. This circumstance is explained by the extremely small number of first births, both very young (14-15 years) and very old (40 years and above), while individual observations, as well as statistical analysis on a small amount of material, do not provide a sufficient criterion for evaluating the role of the age factor in the course of labor. The most favorable age for labor is 20-28 years. But even cases of first births exceeding the specified limits, at ages 16-20 years and 29-35 years, as daily observations show, as a rule do not show significant differences from the course of labor in the optimal period for this function. The question is somewhat different for very young women (under 16 years). Rare cases of this kind either give a higher percentage of premature labors or show more frequent operative interventions, and pathology associated with pregnancy (toxemias) is also more often noted in them. The activity of expulsive forces and the condition of the soft birth passages apparently do not give significant deviations in the unfavorable direction (elasticity of tissues in young age). Individual authors (Garbar, 1914) point out that anomalies of uterine labor activity are rare. Relatively more elements of pathology are observed in labor in elderly primiparas, and ancient obstetricians said: 'Senescentes mulieres difficillime pariunt'. The greater rigidity of the soft birth passages creates difficulty for the normal course of the first stage of labor, prolongs it, and thereby makes the entire act of labor longer. These same circumstances are the basis for the relatively more frequent cases of premature rupture of membranes, penetration of infection into the upper birth passages with the consequences usually accompanying this circumstance. Traumatism in this category of parturients is higher than in young primiparas. Tears of the soft birth passages (vagina, perineum) occur twice as often as the frequency of tears in primiparas aged 26-27 years. The more frequently occurring secondary weakening of labor activity in this group, along with the above-mentioned circumstances, is the cause of the higher frequency of operative interventions during labor.
I. Feigel. VIII. Pathology of Labor (Dystocia). Pathology of labor caused by anomalies of the birth canal. According to the view that was until recently generally accepted among representatives of obstetrical science, and is still shared by many of them at present, pelvic contractions are of the greatest importance among all anomalies of the female birth canal in the pathology of labor. Encountered quite frequently, these contractions sometimes make the delivery of a full-term fetus per vias naturales completely impossible, and if appropriate surgical assistance is not provided to the parturient woman in time, both mother and child inevitably perish in such cases—the mother usually from uterine rupture, the child from asphyxia. In other cases, where the pelvic contraction is less significant, labor ultimately ends by the forces of nature, but the child is either born dead or dies shortly after birth, while the mother develops various injuries to the birth canal on the basis of birth trauma, sometimes extremely severe, or falls victim to puerperal infection (see Contracted Pelvis). Anomalies of the soft birth passages. If until very recently the role that the soft birth passages play in the pathology of the labor act was considered insignificant compared to the role of the hard passages, i.e., the bony pelvis, at present the views of obstetricians in this respect have changed drastically. Krönig was the first to establish that difficulties in the course of labor depending on the soft parts of the birth canal are encountered in practice much more frequently than those depending on pelvic anomalies; subsequently, this fact was confirmed by the observations of a number of other modern obstetricians and especially by the works of Seitz. Seitz calculated that 63 thousand children are born dead in Germany annually, of which 50 thousand perish during labor, with 16 thousand perishing mostly in the expulsion period depending on disorders in the normal course of labor on the part of the soft birth passages. The immediate cause of death of children is most often a disturbance of gas exchange in the placenta between the fetus and the mother, and less frequently such moments as compression of the umbilical cord, cerebral hemorrhages, etc. Along with the death of children, labor complicated by anomalies of the soft birth passages often leads to sad consequences for mothers as well, in whom, as happens with pelvic contractions, ruptures of various parts of the birth canal are observed and, in connection with the protracted course of the labor act, the morbidity rate increases. At the heart of the aforementioned harmful influence of soft birth canal anomalies on the mother and child lies the insufficient extensibility of these passages, which affects the course of the labor act all the more unfavorably because the work of the expulsive forces in these anomalies is also frequently insufficient. As a result, labor, especially its second period, is prolonged, and this leads to the consequences that have just been noted. The causes of insufficient extensibility of the soft parts of the birth canal are very diverse. Among them, cicatricial strictures of various sections of this channel should be noted first of all. Localizing mainly in the region of the external uterine os, the vagina, and the vulvar cleft, they can arise, firstly, depending on accidents—burns, injuries, etc.; of course, strictures of this kind most frequently arise in the lowest sections of the genital tract. Sometimes they are the result of criminal manipulations performed with the aim of expelling the fetus in pregnant women, disfiguring the woman, etc. Not so rarely, their cause is the improper application of therapeutic measures; if, for example, strong cauterizing agents like lapis in substantia or in strong solutions are used to heal true and false erosions of the vaginal portion, a tissue defect results at the site of the erosion, which heals with a scar that, by shrinking, causes a stricture of the external uterine os; similarly, overly energetic curettage of the cervical canal and the operation of amputation of the vaginal portion of the cervix can lead to strictures of the cervical canal, and operations undertaken for the treatment of prolapse and long-term wearing of vaginal pessaries to strictures of the vagina. Very strong cicatricial strictures can further arise on the basis of birth trauma in women with a contracted pelvis, and also be the consequence of ulcerative processes accompanied by tissue necrosis in the external genitalia, vagina, and uterine os. Particularly significant changes of this kind are observed after the disease that was first described in our country by Marconet in 1865, and then by Weber, Lingen, and others under the name perivaginitis phlegmonosa dissecans, but to which it would be more correct, as Haputin does, to give the name paravaginitis phlegmonosa dissecans. In this disease, which represents a paravaginal phlegmon, sometimes the entire vagina together with the vaginal portion of the uterine os completely necrotizes, sloughs off, and in its place a cicatricial cord is formed, in some cases with a narrow channel in the middle. The influence of cicatricial strictures of the birth canal on the labor act is, of course, various depending on the degree of stricture, its localization, prevalence, time of occurrence, etc. In some cases, the stricture is so significant and the walls of the birth canal in its region are so unyielding that labor per vias naturales turns out to be completely impossible; in others, the presence of strictures leads only to a protracted course of either the dilation period, or the expulsion period, or both together. In this case, of course, stricture of the uterine os will predominantly hinder the dilation of the uterus, stricture of the vagina will slow down the expulsion of the fetus, and stricture of the vulvar cleft will make the crowning of its presenting part difficult. As for therapy, if the cicatricial stricture is insignificant or the scar is still fresh and yielding, labor can be allowed to take its natural course. In other cases, one has to resort either to non-blood expansion (with fingers, dilators of various designs) or to incision and excision of the scar. In those cases, finally, where the cicatricial stricture is too significant, where, for example, the entire vagina is turned into a narrow cicatricial passage, the only possible method of delivery is Cesarean section. In addition to operations aimed at forming a convenient path for delivery in cicatricial strictures of the birth canal, as well as in cases of its insufficient extensibility depending on other causes listed below, it is sometimes necessary to resort to operations whose object is the fetus and which are aimed at helping it overcome the resistance from the walls of the birth canal; in a living fetus, extraction by the pelvic end (sometimes after preliminary version) and forceps are most frequently used among such operations, and in a dead fetus, perforation and cranioclasis. Besides cicatricial changes, the unextensibility of the birth canal can depend on the rigidity of its tissues, the loss of elasticity by the latter. This rigidity is usually observed in elderly primiparas, as well as in women who have suffered for a long time from chronic inflammatory processes in the uterine os and other sections of the birth canal. It is most sharply expressed mostly in the region of the external uterine os and in the region of the vulvar cleft, and in the region of the external os, the narrow ring of tissue immediately surrounding the lumen of the external orifice is apparently distinguished by the greatest rigidity. The tissues of the birth canal are also rigid, dense, and poor in water in women with certain constitutional anomalies, e.g., with the so-called Zukunftsform of Mathes, in women of hypoplastic and intersexual types. It is precisely on the basis of the rigidity of the external os, according to some authors, and according to others on the basis of agglutination, The insufficient extensibility of the soft parts of the birth canal during labor is also a common phenomenon in malformations of the uterus and vagina, especially in infantilism. In this very frequently encountered malformation, on the one hand, both the cervical canal and the vagina are narrower than normal, and on the other hand, their tissues are characterized by rigidity; both of these factors create the basis for a protracted course of the labor act, especially in primiparas, especially since the labor activity of the uterine musculature in an infantile uterus is usually weak. Among other anomalies of the soft parts of the birth canal causing purely mechanical obstacles to the expulsion of the fetus during labor, various neoplasms—fibromas, cancers, cysts, etc., originating both from the walls of the canal itself and from neighboring organs—should be noted; regarding the role that these neoplasms play in the pathology of the labor act, see below. Besides neoplasms in the proper sense of the word, among the anomalies of the soft parts of the birth canal making labor difficult, one can point to acute edema of the vaginal portion, hypertrophy of the cervix so often encountered in prolapse, hematomas of the vagina and vulva, elephantiasis of the vulva, etc. All the listed anomalies have one or another pathoanatomical substrate at their base, but along with them, no small importance in the pathology of the labor act belongs to purely functional irregularities on the part of the anatomically normal soft parts of the genital tract.
Among these abnormalities, the first place is occupied by spasmodic contractions of the circular musculature of the uterus in the region of the internal os (strictura uteri) and external os (trismus uteri), as well as the muscles forming the pelvic floor, especially the constrictor cunni and levator ani muscles. (V. Gruzdev). From the lower segment of the amniotic sac and the mucosa of the cervical canal, a peculiar phenomenon develops on rare occasions (according to Huggisberg, once in every 5,000 to 6,000 labors), known as conglutinatio orificii uteri externi. This phenomenon consists in the fact that the external os in laboring women, despite energetic uterine contractions, shows no tendency to dilate, although the canal of the isthmus is already fully dilated, the walls of the cervical canal are strongly stretched, and the fetal head is situated deep in the pelvis, and sometimes, as was the case described by Jentzer, even with a significant part of it having emerged from the genital hiatus (Fig. 68). The practical significance of the anomaly under discussion lies in the fact that upon insufficiently careful examination, the thinned walls of the cervical canal can be mistaken for the amniotic sac, leading to the misdiagnosis of complete dilation of the os.
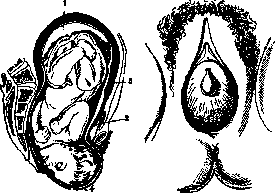
Figure 68. Conglutinatio
Figure 69. Protrusion of the
amniotic sac orificii externi according to Jentzer
through the intact contraction ring: 1 - placenta; 2
opening of the hymen during labor. (After Ahlfeld.)
urinary bladder; 4 - external
uterine os.
...where there is no "disclosure." Therapy of conglutination orificii uteri externi consists in dilating the external os with a finger or inserting the end of a uterine sound into it and using the latter to strip the fetal membranes from the walls of the cervical canal. Usually, shortly after this, the os begins to dilate rapidly, and then expulsion of the fetus follows. As for the treatment of rigidity of the soft parts of the birth canal in general, the same measures may be used here as were indicated above for cicatricial strictures thereof, including surgical dilation in the form of incisions of the rigid external os or episiotomy in case of rigidity of the tissues surrounding the vulvar cleft. - Excessive inelasticity of the hymen may also be referred to the group of obstacles to labor under discussion. Sometimes the latter turns out to be so dense that it does not tear during sexual intercourse and remains intact until the very expulsion of the fetus (Fig. 69). If the rupture of such an inelastic hymen is left to the pressing presenting part, extensive injuries with severe bleeding may result; furthermore, the crowning of the fetal presenting part is greatly delayed thereby. Therefore, it is better in such cases to perform early hymenotomy - a cruciate incision of the hymenal septum with scissors. IX. Pathology of labor caused by malformations of the female reproductive sphere. Common to all malformations of the reproductive sphere is the fact that these malformations generally exhibit functional insufficiency of the main motor of the birth act - the uterus. In certain malformations, mechanical obstacles to the advancement of the fetus may also be observed with relatively adequate labor activity and with correspondence of the fetus to the dimensions of the bony pelvis. Uterine hypoplasia, as the most frequent malformation, takes first place. High degrees of hypoplasia (uterus fetalis, infantilis, pubescens, rudimentarius solidus) exclude the very possibility of pregnancy and therefore are of no pure obstetric interest. Lesser degrees of hypoplasia - hypoplasia uteri - do not exclude the possibility of pregnancy, but pregnancy is often terminated either by miscarriage or premature labor. Furthermore, in cases where pregnancy reaches term, we often have, in uterine hypoplasia, a fetus smaller than normal dimensions, and consequently in these cases uterine labor insufficiency may not play a large role in the pathology of the labor act itself. This insufficiency is fully manifested only in those cases where, with a hypoplastic uterus, we have a fetus of normal size. This insufficiency manifests itself in the form of so-called "primary uterine inertia": labor activity from the very beginning of labor proceeds sluggishly, the dilation period is greatly prolonged, which, especially with premature rupture of the membranes, is associated with a definite risk of infection. The expulsion stage proceeds no better, since here, besides uterine insufficiency, the simultaneous hypoplasia of the vagina - its narrowness and low elasticity - begins to influence the course of labor. Prolonged labor provides a relatively frequent indication for the use of obstetric forceps, and this operation is often accompanied by significant traumatic injuries to the birth canal (perineal tears, lacerations of the vaginal entrance, and in particular deep tears of the vagina itself). The placental stage of labor often gives complications in the detachment of the placenta. The fact is that uterine hypoplasia is not limited to the musculature alone; it also manifests itself in the insufficiency of the structure of the mucous membrane of the uterus. Such a membrane does not provide a full-value decidual metamorphosis, and under these conditions, with a hypoplastic uterus, all possible varieties of what is called "placental accreta" in the broad sense of this term can be encountered. Finally, the postpartum period is not free from pathology associated with uterine hypoplasia: in the immediate hours after birth, atonic hemorrhages are possible, and subsequently, abnormal postpartum involution of the entire maternal organism. In individual cases of uterine hypoplasia, such a catastrophic complication of labor as uterine rupture is possible - even with careful monitoring of the course of labor. Unlike uterine rupture with its functional normality, when the catastrophe approaches with a sharply expressed Bandl symptom complex, with uterine hypoplasia its rupture often creeps up completely unnoticed: the insufficient uterine wall gradually "crawls apart" as it were, and the rupture is discovered already post factum. Double malformations of the uterus occupy second place in importance among malformations in labor pathology: all kinds of degrees of uterine doubling belong here, starting from complete bifurcation (double uterus) and ending with a "unicornuate uterus" with the complete absence of the second half of the Müllerian system. All these malformations are characterized by all those complications described above for uterine hypoplasia. On the other hand, labor with these malformations can proceed without any complications, and sometimes a double uterine deformity is discovered in women who have had many abortions and births and consequently have repeatedly been under the direct supervision of experienced medical specialists. Facts of this kind generally force us to take a rather calm attitude toward the prognosis of labor and give the right to adhere to expectant management of labor. However, with the timely recognition of a double deformity in the presence of pregnancy, modern obstetricians prefer to recommend to pregnant women either immediate surgical intervention to terminate pregnancy or Caesarean section at the end of pregnancy or at the beginning of labor with subsequent sterilization. Such an attitude toward these malformations is justified to a certain extent by the fact that in each individual case it is impossible to foresee all possible complications. Even the most innocent of these malformations - uterus arcuatus - predisposes the pregnant woman to transverse presentations of the fetus, sometimes difficult to correct even by internal version. In other, more pronounced doublings of the uterus, abnormal presentations of the head are often observed, which is explained both by the deviation of the pregnant uterus from the midline and by the wrong direction of the force of uterine contractions, not coinciding with the axis of the pelvis. Furthermore, the second uterus or the second half of the doubled uterus may find itself, as it were, in the path of the fetus and purely mechanically prevent the engagement of the head, as is sometimes observed with fibromas, especially cervical ones, or with ovarian cysts that have dropped below the presenting part. In uterus septus, a particularly serious complication is observed in cases where the placenta is attached to the septum itself: here labor is generally complicated in the placental stage during the detachment of the often adherent placenta, and after the separation of the placenta, dangerous hemorrhages are almost inevitable due to insufficient contraction of the septum. In those - very rare - cases where the septum does not reach the bottom of the uterus or has an opening in it communicating both halves of the pregnant uterus, it may happen that the fetus lies in one half of the uterus and the placenta in the other. Naturally, the birth of the fetus may proceed more or less successfully, but the delivery of the placenta will turn out to be highly difficult. A particularly severe complication is given by pregnancy in a rudimentary horn of the uterus. True, in most cases such a pregnancy does not reach term and is interrupted by the type of ectopic (interstitial) pregnancy, but one can imagine how severe this complication must be if the pregnancy in the rudimentary horn reaches term and completely barren contractions begin. Only timely laparotomy can save the pregnant woman in this case. Malformations of the vagina also make their contribution to the pathology of labor. These include vaginal duplications, narrowings, and congenital annular stenoses. Regarding vaginal narrowings, it was said above that they give deep tears when forceps are applied, but such tears are also possible with other obstetric operations and even with the introduction of the obstetrician's hand. With a double vagina, the septum can be an obstacle to the forward movement of the fetus, but this obstacle is easily eliminated by a simple incision of the septum. The same can be said regarding annular stenoses - they either stretch themselves during the forward movement of the fetus, or are stretched by the obstetrician's fingers, or finally are dissected with a knife. Only in individual cases do vaginal malformations give an indication for Caesarean section. Thus, for example, a case was observed where a "normal" vagina ended in a blind pouch, and a "normal" uterus flowed into another narrow vagina, communicating with the "normal" one only by a pinprick opening through which the patient menstruated unhindered and through it became pregnant after many years of barren marriage. In this case, a Caesarean section was performed. X. Pathology of labor caused by anomalies of the expulsive forces. The pathology of labor caused by anomalies of the expulsive forces is diverse, but in each individual case it is far from always possible to find out where the root cause of the pathology lies - whether in the anomaly of the expulsive forces itself or in those complications causing it or accompanying it that are present in given labors.
Thus, for example, in moderate pelvic contractions, one has to observe both labor inertia and excessively strong (spasmodic) contractions, wherein in both cases the forward movement of the fetus may be greatly slowed down or even completely halted, although there is a sufficient correspondence between the presenting part and the pelvis. The question arises: is the pathology of the birth act in this case caused precisely by an anomaly of the expulsive forces? If this is joined by malposition of the head or a deviation from the normal mechanism of labor, the question and the answer to it become even more complicated. Undoubtedly, however, in individual cases, anomalies of the expulsive forces can be observed, so to speak, in their pure form. This applies especially to primary labor inertia in young primiparas and in elderly multi- and grandmultiparas with a normal pelvis. In the former, labor inertia often depends on functional weakness of an incompletely developed uterus; in the latter, there is usually a specific anatomical substrate in the form of connective tissue proliferation at the expense of the muscle fibers of the myometrium. In both cases, the pathology of labor may manifest itself only in that the duration of labor will be significantly greater than the usual average norm. By itself, this is of no special significance, but nevertheless, under these conditions, there is an increased morbidity and increased mortality of puerperae, as well as a high stillbirth rate. Labors are richer in pathology when contractions and pushing efforts are excessively strong. In the best case, the matter ends in precipitous delivery (partus praecipitatus, Sturzgeburt) without damage to the soft birth canal. Rapid and insensitive labors sometimes lead to fetal injury, e.g., when falling to the floor, and sometimes to death (delivery in a toilet). These cases necessitate forensic medical examination. Since the insensitivity of the birth act is often caused by a disease of the nervous system, it should become a rule to subject women whose labors proceeded without pain to an examination by a neuropathologist. Sharp pain of contractions in the dilation period is a specific anomaly and depends either on increased pain sensitivity of a neuropsychic order or on remnants (residua) of an inflammatory process in the uterine wall itself or in the surrounding organs and tissues (gonorrhea). The very course of labor with sharp pain of contractions may not deviate from the norm. Secondary labor inertia, as the name itself shows, occurs secondarily in labor, i.e., after a period of time with normal labor activity. Such weakness depends most often on fatigue and usually passes by itself after some rest, without requiring any intervention. True spasmodic contractions, and even more so tetanus of the uterus (tetanus uteri), are almost always caused by obstacles to the advancement of the fetus (pelvic narrowness, rigidity of the cervix, excessive size of the fetus or presenting head). In rare cases, spasmodic contractions depend on the improper administration of uterus-contracting agents (formerly mainly ergot preparations, at present pituitary preparations - see Pituitrin). The pathological side of excessively strong contractions lies in the fact that they are ineffective - the fetus does not make a forward movement even in those cases where the obstacle could have been overcome with normal labor activity. These contractions usually lead to asphyxia and fetal death, because they are too prolonged and the pauses between them are so short that placental circulation does not have time to recover. However, in the presence of, for example, a narrow pelvis, fetal death may turn out to be a favorable factor, because after death the fetus quickly macerates and in this form easily passes through the narrowed place, and as a result, labor activity also takes on a normal character. If the obstacle is insurmountable, excessively strong labor activity leads to stretching of the lower segment of the uterus with the formation of a high-standing retraction ring and ultimately to rupture of the uterus. Excessive pain of labor in the expulsion period often depends on painful stretching of the pelvic floor and perineum, but the pain from the integument is perceived as uterine pain. This pain essentially cannot be attributed to anomalies of the expulsive forces proper. Finally, to the pathology of the expulsion forces one must attribute the so-called hypotension or atonia (see Puerperal period - postpartum hemorrhage). Besides the pathology of labor caused by the anomaly of contractions, the slowing of labor can also depend on the weakness of pushing efforts due to flabbiness, stretching, or obesity of the abdominal walls. Such pushing weakness is often successfully eliminated by the use of a Verbov bandage or similar devices made ex tempore from towels or a sheet. Excessively strong pushing activity can develop during the crowning and birth of the head; it must be moderated to avoid large perineal tears; this can usually be accomplished by psychological influence or by applying such measures as, for example, pinching the nose or forcibly opening the mouth. Agents regulating labor activity are not very numerous, but on the whole, they achieve good results. Agents that enhance labor activity include sugar, quinine and its derivatives, ergot preparations, and posterior pituitary preparations. Sugar apparently acts mainly by its caloric content, supporting musculature exhausted by work. The action of quinine does not always manifest itself, but in cases where quinine acts, it causes good, near-normal contractions. Ergot preparations very sharply enhance labor activity, but unfortunately this action is more pronounced on the circular muscles, and therefore one does not get rhythmic peristaltic contractions giving forward movement to the fetus, but contractions that long compress the contents of the uterus; in this case, fetal asphyxia easily occurs, and if only the placenta remains in the uterus, its incarceration (placenta incarcerata) can occur; therefore, at present ergot preparations are given only upon complete emptying of the uterus from the ovum, i.e., in the postpartum period; in combating atonic hemorrhages, ergot is the most effective preparation. The best agents enhancing the expulsive forces at present are posterior pituitary preparations (see Pituitrin). Unfortunately, they act on the uterine musculature selectively, mainly in the expulsion period. In the dilation period and before the onset of labor, pituitary preparations act only after sensitization of the uterus, e.g., with quinine, castor oil, thymus gland preparations (thymophysin), but even with sensitization their action is far from certain. However, even in the expulsion period, pituitary preparations are far from an ideal agent, because in all cases they give too long a period of contraction of the uterine wall, which often disrupts placental circulation and hence fetal asphyxia. Furthermore, these preparations, even standardized in certain units, still do not give a strictly defined effect: sometimes even large doses do not cause a sufficient enhancement of labor activity, and sometimes, on the contrary, a very small dose causes violent spasmodic contractions, and one has to resort to anesthesia to weaken them, while in the meantime the fetus is subjected to very great danger. By virtue of this, the administration of pituitary preparations must be done after strict weighing of all circumstances and with completely precisely established data from internal examination. Finally, even in those cases where the influence of the drug proved completely effective and gave a rapid delivery, sequential atonic hemorrhages, which are not easy to combat, are far from infrequently observed. Until recently, the negative side of these preparations was also the fact that simultaneously with the enhancement of uterine contractions, they strongly constrict blood vessels and thereby sharply increase blood pressure. This made them contraindicated in many cases when it would be desirable to use them (for example, in heart diseases, in eclampsia). At present, American and German pharmacologists have succeeded in preparing separately agents acting on the uterine musculature alone and on the blood vessels alone. Perhaps it is worth mentioning here the ancient method of enhancing weakened labor activity with hot baths or hot vaginal douches. These agents are quite effective, but modern obstetrics denies them out of fear of infection. However, they should not be forgotten altogether. Too strong or irregular labor activity has long been successfully regulated, i.e., weakened, by the use of painkillers and narcotic drugs - opium, morphine, atropine. The best remedy is still chloroform drop anesthesia: with anesthesia, one can truly regulate the expulsive forces, giving it in exactly the amount required, whereas the agents listed above, administered internally, can exert an excessive effect and completely suspend labor activity, which is not always desirable.
Thus, the modern obstetrician has at their disposal a sufficient assortment of medicinal agents to influence the work of the expulsive forces and especially their anomalies, yet the use of these agents requires a very thoughtful analysis of the labor data, and subsequently extremely attentive observation of their course.
M. Kolosov. XI. Pathology of labor caused by anomalies of the birth object. Transverse and oblique lie of the fetus. Transverse and oblique are called irregular lies of the fetus in which the axis of the fetus does not coincide with the longitudinal axis of the uterus, but forms a right or acute angle with it. In practical terms, transverse and oblique lies are equivalent and therefore are considered together under a common name. Distinctions are made for the first (left) position, when the head is on the left, and the second (right), when the head is on the right, the anterior variety (dorso-anterior), if the fetal back faces anteriorly, and the posterior (dorso-posterior), if it faces posteriorly. Transverse lies occur, according to the statistics of Schurig, covering 655,770 clinical and non-clinical labors, in 0.75% of all cases. This percentage, however, fluctuates in one direction or another depending on the nature of the material (various countries and regions). The occurrence of transverse lies is promoted by everything that increases the mobility of the fetus, such as polyhydramnios, small fetal volume (premature birth), flabbiness of the abdominal wall and ligamentous apparatus (due to which it is more common in multiparae, especially grand multiparae), mechanical moments preventing the engagement of the head in the lower segment of the uterus, such as a contracted pelvis, placenta previa, uterine myomas, ovarian cysts, uterine malformations (e.g., uterus arcuatus), twins (the second fetus lies in a transverse lie in 12.5%). Frequently, transverse lie occurs as a result of the combined action of several causes. The diagnosis of transverse lie during pregnancy and labor is established by external examination of the abdomen. The abdomen is stretched in the transverse direction; the shape of the abdomen and uterus is irregular. The fundus of the uterus stands lower than is appropriate for the period of pregnancy; there is no presenting part above the pubic symphysis. In the fundus of the uterus, it is also impossible to palpate a large part of the fetus, but to the side of the midline, most often in the right or left iliac region, a ballottable, dense, round fetal head is determined, while on the opposite side, another large, non-ballottable part—the buttocks. Between these two large parts lies the smooth back or nodular small parts. The fetal heartbeat is auscultated at the level of the navel, closer to the side where the head is located, which in unclear cases helps determine the position. Upon internal examination at the beginning of labor (during pregnancy, external examination methods alone are quite sufficient) with an intact bag of waters, the absence of a large presenting part is noted, or small parts or the umbilical cord are palpated. The arm lying inside the birth canal can be distinguished from the leg by the greater length of the fingers and the absence of the calcaneus. If the arm is outside the genital slit, then to establish whether it is right or left, one can "shake hands" with it or turn the palm upward. If the thumb faces the mother's right thigh, it is the right arm. The characteristic feature of the shoulder, in contrast to the buttocks, is the armpit, ribs, clavicle, and scapula. On the side toward which the armpit opens lies the head. Thus the position is determined. With the scapula anterior and the clavicle posterior, there is an anterior variety. The following table (Kaplan) greatly simplifies the determination of the variety (p. 211): Anterior variety Posterior variety If the head is on the right or the armpit is closed to the right, and the left arm has prolapsed If the head is on the left or the armpit is closed to the left, and the right arm has prolapsed If the head is on the right or the armpit is closed to the right, and the right arm has prolapsed If the head is on the left or the armpit is closed to the left, and the left arm has prolapsed It is necessary, with the help of external examination, and in case of its insufficiency, internal examination, to accurately orient oneself in the position and variety of the fetus, since the correct management of labor and the successful execution of operative aid depend on this. In neglected
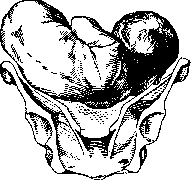
Figure 70. Transverse lie. Dilatation stage: membrane is intact, forewaters communicate freely with upper waters.
transverse lie, the prolapsed arm is edematous and cyanotic, the shoulder is impacted immovably into the pelvis and pushed somewhat to the side by the chest beginning to engage. The cervix of the uterus is strongly stretched upward. Until the discharge of waters, external examination for diagnosis, except for cases of hydramnios,
Figure 71. Shoulder presentation. The uterine os has collapsed again after the rupture of the membranes.
is quite sufficient. After the discharge of waters, it is necessary to perform an internal examination, if necessary, even with the whole hand. In neglected transverse lie, the examination must be performed very carefully so as not to cause a uterine rupture. Maternal mortality with timely assistance is 2-3%, fetal mortality considering all cases of transverse lie is 30%, and of those where appropriate assistance was timely provided—5-10% (Martius). Course of labor. Transverse lie is a very serious complication of the birth act and requires the most pedantic observation of the parturient woman. With it, one or another pathological deviation is frequently observed. Thus, in the period of cervical dilatation, premature rupture of the amniotic sac very often occurs, which leads to prolapse of the umbilical cord, prolapse of the arm (according to Mikhailov, in 26.5%) and increases the danger of infection. Spontaneous labor is possible only in very rare cases by spontaneous version, spontaneous evolution, or conduplicato corpore. Spontaneous version can occur accidentally with a sufficient amount of amniotic fluid (predominantly before the rupture of the membranes) under the influence of moderate and infrequent contractions or a change in the position of the parturient woman to the side where the head of the fetus is located. Spontaneous evolution is possible with a capacious pelvis and a small macerated fetus. It consists of the following: the shoulder engages in the pelvis, the head of the fetus, folded in half, remains above the pelvic inlet, the buttocks and legs are pushed past the shoulder, then the upper
Figure 72. Neglected transverse lie.
part of the trunk and finally the head are born. Two variants of spontaneous evolution are distinguished: the first, described by Douglas (1819), and the second, described by Denman (1785). In the first, the deeply impacted shoulder is born first, and the trunk glides through the posterior half of the pelvis past the neck extended behind the symphysis. In the second, the head is retained in the pelvis above the linea innominata, the shoulder remains impacted in the pelvis or even rises somewhat from it, while the pelvic end is pushed through the lateral and anterior section of the pelvic cavity past the upper part of the trunk occupying the opposite lateral and posterior part of the pelvis. Labor by conduplicato corpore (first described by Roederer, 1756) is possible only with a macerated or very small (premature) fetus folded in half. First, the shoulder with part of the chest is born, then the head together with the abdomen, and finally the buttocks. This mechanism of labor is encountered, according to von Franque, in 2.5%, according to Mikhailov, in 1.8% of all transverse lies; spontaneous version according to von Franque in 0.6%, according to Mikhailov in 6.5%. The frequency of spontaneous evolution by the method of Douglas to that by Denman is 3:1. In the vast majority LABOR
214 of cases, if timely assistance is not provided, the fetus under the influence of contractions is driven into the pelvis in a flexed position, the presenting shoulder is impacted, and a so-called neglected transverse lie arises, characterized by immobility
Figure 73. Spontaneous evolution.
of the fetus. Contractions acquire a convulsive character, the lower uterine segment stretches, and finally a uterine rupture occurs, which is a catastrophe for the mother and fetus (Figs. 70-79). Management of labor. In the dilation stage with intact membranes, normal uterine activity, and in the absence of a narrow pelvis, placenta previa, neoplasms, etc., one can attempt external cephalic version or place the parturient woman on the side where the head or pelvic end is located, depending on which of these parts is closer to the pelvic inlet. When performing external version, a number of precautions must be observed: the bladder and intestines must be emptied, it must be performed between contractions and must not be accompanied by any painful sensations. Upon the appearance of even minor pain, all attempts at external version must be stopped. To prevent premature rupture of the fetal membranes, some recommend the introduction of a colpeurynter into the vagina (which, however, has not received widespread use); with full dilation of the cervix and intact membranes (if, of course, there is no pelvic contraction), a combined external-internal version is performed, and if necessary, subsequent extraction, which significantly improves the prognosis for the fetus. With intact membranes, but not at full dilation, all the obstetrician's attention must be focused on preserving the fetal membranes until full dilation (placing the woman on her side, forbidding pushing, using a colpeurynter, tireless monitoring of labor activity, and timely measures in case of any deviations on its part). If rupture of the fetal membranes occurred before full dilation, labor can be managed in two ways: 1) either perform version at incomplete dilation, or 2) wait until full dilation and subsequently perform version. Waiting, recommended as early as 1886 by Winter, gives better results, especially for the fetus. In the case of a dead fetus, prolapse of the umbilical cord or arm, hemorrhages, or with appropriate indications on the part of the mother, the operation of version is used before full cervical dilation. The process of cervical dilation after the discharge of waters can be accelerated using a metreurynter. At full dilation, if a long time has elapsed since the discharge of waters, the decision on the possibility of version depends on the state of the uterus. Spasmodic, painful contractions, a prolonged state of uterine contraction, signs of incipient stretching of the lower uterine segment are absolute contraindications to performing version. In neglected transverse lie, it is necessary to immediately perform decapitation or embryotomy, while in a live fetus, in the presence of appropriate conditions (just as with non-neglected lie), Cesarean section is indicated (in certain cases also Porro's operation), which has been used by many clinics with success. Labor with prolapse of small parts. A distinction should be made between presentation, when with intact membranes some small part is felt through the fetal membranes, and prolapse, when a small part prolapses into the vagina after the discharge of waters. These complications occur when the inlet to the minor pelvis is free or not tightly closed by the presenting part, as happens, for example, in transverse lie, high standing of the head in multiparae, hydramnios, flat pelves. Prolapse of small parts is significantly more common in breech presentations, while in cephalic presentations they are a relatively rare occurrence (according to Sachs, in 0.5%), and even then they are noted with incorrect engagement of the head in pelvic contractions. Presentation and prolapse of a foot next to the head are observed in 0.035% of all labors (Benda), predominantly
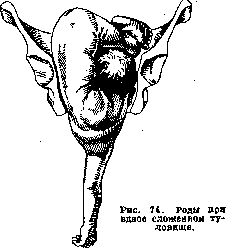
in premature and macerated fetuses, as well as in twins. Therefore, it does not have great practical significance. To correct this deviation, the parturient woman is placed on the side where the fetal back is located. With a full-term fetus, the foot is pushed back into the major pelvis or version is performed. Presentation and prolapse of the arm can occur in all fetal positions. In presentation of the hand, the woman is placed on the side opposite to the one from which it presents. In prolapse of the arm and with a mobile head, the woman is placed on the side where the arm has prolapsed. Inserting the entire hand into the vagina and 2 or more fingers into the uterus, the prolapsed hand is pushed back up, the head is guided to the pelvic inlet with the external hand, and then the woman is turned onto the other side. The position with a raised pelvis is also used. Narcosis facilitates the execution of the maneuver. If repositioning fails and the arm prolapses again, podalic version is performed. In an impacted head, labor is left to spontaneous course or, if necessary, forceps are applied, avoiding grasping the arm with them. Some authors (Küstner, Braun, etc.) advise trying to reposition the arm in these cases as well. With a
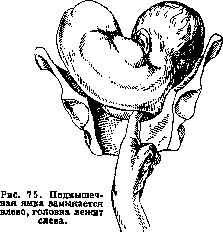
dead fetus, perforation of the head is performed. Prolapse of the arm in transverse lies occurs, according to Martius, in 50%, according to Mikhailov, in 26.5%. It has no independent significance. The prolapsed arm should not be repositioned; it is placed in a loop so that during podalic version and birth of the trunk it does not become retroverted behind the head.
Prolapse of the umbilical cord does not present an obstacle to labor, but threatens the life of the fetus. In cephalic presentation, the danger
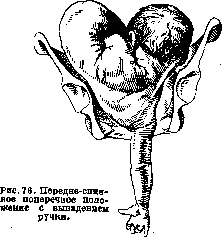
of compression of the umbilical cord against the pelvic wall and disruption of the fetal circulation thereby is greater than in breech presentation. Strangulation of the umbilical cord anteriorly between the head and the pubic bone leads to fetal asphyxia sooner than strangulation between the head and the posterior pelvic wall. Prolapse of the umbilical cord occurs in 0.62-0.8% of all
deliveries (Eberlin, Porshnyakov, Gusev), according to German authors (e.g., Küstner, Schweitzer, Martius) in 1-1.3%. In multiparae, it occurs 4-6 times more often than in primiparae. Infant mortality is 50% on average; it is lowest in transverse lies, in which umbilical cord prolapse occurs most frequently. Contributing causes, besides those common to the prolapse of small parts, are excessive length of the umbilical cord, velamentous insertion, membranous attachment, low placental attachment, intrauterine interventions, e.g., metreurysis, etc. Diagnosis is usually not difficult. The degree of compression is judged by pulsation; prolonged absence of pulsation indicates fetal death. In this case, in the absence of other complications, labor is left to its natural course. With a live fetus, intervention is necessary, the nature and timing of which depend primarily on the position of the fetus and other conditions, such as pelvic dimensions, degree of dilation, integrity of the membranes, etc. With small cervical dilation and umbilical cord presentation, measures must be taken to preserve the membranes if possible
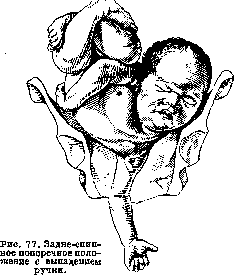
until full dilation (prohibition of pushing, position of the parturient woman on her side, introduction of a colpeurynter). After cervical dilation, rupture of the membranes and podalic version. Umbilical cord prolapse at cranial presentation and full dilation indicates immediate delivery using version or forceps; at incomplete dilation, reposition of the umbilical cord, metreurysis, or combined version. Recently, at incomplete dilation, vaginal or abdominal Cesarean section has found application. In breech presentation, it is recommended to bring down the foot after the discharge of waters; in footling presentations, extraction is accelerated if the fetal heartbeat worsens. In transverse lie, umbilical cord prolapse does not require other measures besides those necessary for treating the main anomaly.
Rupture of the umbilical cord is very rare. Forsell found it in 14,639 labors
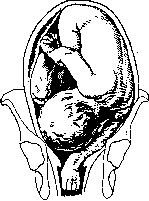
Figure 78. Prolapse of the arm next to the head.
2 times, Ahlfeld - 4,000 births 8 times. Rupture of the umbilical cord is observed both during pregnancy on the basis of trauma, and during all periods of the act of labor, but most often with sudden labor, especially in the standing position or sitting in the toilet, etc., with rapid extraction of the fetus. According to Henter, rupture of the umbilical cord can occur in any position of the pregnant woman. Research by a number of authors has shown that when falling from a height equal to half the length of the umbilical cord, a load of 1,000 g is sometimes already sufficient to cause rupture of the umbilical cord. Contributing factors are primary shortness, shortening due to multiple winding around the fetus's body, membranous attachment, as well as insufficient development of elastic tissue in the umbilical arteries, varicose vein dilations, looseness of Wharton's jelly, lues. The site of rupture is most often in the fetal third of the umbilical cord, sometimes at the umbilical ring; in rare cases the umbilical cord is torn from the placenta (Strassmann, Ahlfeld, etc.). The diagnosis of rupture may have medico-legal significance. Severe bleeding is rarely observed due to the low blood pressure in the vessels of the umbilical cord, the presence of a powerful muscular layer in the vessel walls, as well as due to the twisting of the torn end as opposed to the smooth edge of the cut umbilical cord (Strassmann). Fatal ruptures of individual umbilical cord vessels belong to great rarities. According to Schmidt (Schmidt), rupture of the umbilical artery is described 2 times, while rupture of the umbilical vein occurs somewhat more often; it usually leads to the formation of an umbilical cord hematoma. Fatal bleeding is observed in ruptures of the umbilical cord very rarely. Asphyxia threatening to the life of the fetus may occur. Therapy consists in rapid extraction of the fetus if it has not yet been born, ligation of the umbilical cord and combating asphyxia. Nuchal cord - a frequent phenomenon (according to Bumm in every 4 births, according to Sellheim in 25%). Its causes are the great mobility of the fetus and excessive length of the umbilical cord. Contributing factors are considered to be falling, sharp movements, especially rotational ones, which according to Selheim give the fetus an impulse to intensified rotational movements. The longer the umbilical cord, the greater the chances it has to wind around the fetus. According to Fog's statistics, the average length of 12,000 umbilical cords that were wound was 66.54 cm, i.e. 7 cm longer than normal. Among 113 cases, Sazonov found only 14 where the length of the umbilical cord was close to normal. Most often the windings are around the neck. Windings can be multiple (in Vygodsky's case - 7, in Gray's case - 9-fold). Excessive length of the umbilical cord can favor the formation of true knots of the umbilical cord, as well as windings that disrupt blood circulation in the umbilical vessels. When tightening around the limbs into knots, a long umbilical cord can lead to amputation of the limbs. The consequences of the winding are rarely manifested during pregnancy, but mainly during labor. According to Mikhailov, in 2.3% of children with nuchal cord are born dead. During labor, nuchal cord, leading to relative shortening of it, can cause delay in labor, rupture of the umbilical cord, premature separation of the placenta, inversion of the uterus, winding around the neck, extension or transverse positions. During the act of labor, it can only be suspected if there is a prolonged noise of the umbilical cord and passage of meconium, if there are no other reasons to explain these phenomena. Previously, it was recommended to immediately after the birth of the head to feel whether there is a nuchal cord around the neck, and if it is present, to free it. Schultze advises not to do this: if the release succeeds, it was unnecessary, since it did not cause difficulties anyway, and if it does not succeed, only time is lost. In breech presentations, it is necessary to slip the loop off the fetus, otherwise after the birth of the buttocks the tension of the shortened umbilical cord can lead to asphyxia of the fetus before extraction of the head. Shortness of the umbilical cord can be primary. It also affects the mechanism and prognosis of the act of labor. Anomalies of various parts of the ovum and their influence on the course of labor. Anomalies of the fetus. 1. Abnormal size of the fetus. Excessively small size of the fetus can lead to incorrect positions, e.g. transverse or breech presentation. In cephalic presentations, incorrect insertions, incorrect mechanism of labor, for example the extension type, are observed. Disturbing the correct mechanism of labor, the small fetal head rarely disturbs the correct course of labor, and labor usually proceeds easily. Excessively large size of the fetus can cause significant disturbances in the course of labor. In the literature, cases are described where the weight of the fetus reached 11.5 kg, and the length - 76 cm. According to Tsangmeister, out of 158 fetuses with a weight above 4,000 g, only a quarter were born in time, the rest 8/4 were post-term. On the other hand, not in every post-term pregnancy is the fetus excessively large. Mothers of giant fetuses are usually multiparous. According to Seitz, the cause of excessive size of the fetus may be disorders in the interaction of the organs of its endocrine system, due to which Brindeau's conclusion becomes understandable that fetuses with very high weight (above 5,500 g) are almost always born dead, and if they survive, they are difficult to raise. Labor of fetuses weighing up to 4,500 g mostly proceeds correctly, although sometimes an elongation of the expulsion period and more frequent ruptures of the soft birth passages are observed. Labor of giant fetuses may encounter serious difficulties, because for their volume even a normal maternal pelvis is narrow. The head as the most voluminous part of the fetus in cross-section cannot enter the pelvis or is delayed in it for a long time, because in addition to its size such heads often differ in density and poor ability to configure. With a fetal weight over 7,000 g, spontaneous labor becomes impossible, according to Marcius. With a smaller volume, the head often passes through the pelvis relatively easily, but the fetus is delayed in the pelvis by its shoulders. This complication is most often encountered in post-term fetuses. The prognosis of labor with excessive size of the fetus worsens both for the mother and for the fetus. According to Tsangmeister and Lehn, the mortality rate of fetuses weighing 6,000 g reaches 70%. In conducting labor, it is necessary to be guided by the same principles as in the therapy of a narrow pelvis. Since statistics show that extreme degrees of fetal gigantism are rare and only in them are significant obstacles to labor observed, in most cases labor should be conducted expectantly. If an excessively large fetus, as is often the case, is delayed in the pelvis by its shoulders, then in order to bring them out, they first resort to the same techniques as in normal labor, i.e., grasping the head with both hands and pulling it backward towards the perineum, they bring the anterior shoulder under the symphysis. If this technique does not lead to the goal, then the index finger is inserted into the axillary fossa of the anterior shoulder and pulled down until the shoulder appears under the symphysis. One can first insert the finger into the axillary fossa of the posterior shoulder, which is more accessible, or insert index fingers into both axillary fossae of the fetus. If this technique also fails, then the help of a blunt hook or unilateral or bilateral cleidotomy is resorted to. The latter is more often applied in a dead fetus. Extraction of the delayed shoulders is significantly facilitated after the performance of episiotomy (see). 2. Anomalies of the fetal head. Hydrocephalus. Head dropsy, hydrocephalus interna, as well as hydrocephalus externa, is accompanied by an increase in the volume of the fetal head and usually is an obstacle to labor. According to Ivanov's data, out of 131,523 births in the former Moscow maternity institution, there were 45 cases of hydrocephalus. The head of a hydrocephalic fetus can reach a significant volume and contain a large amount of fluid - 5 liters or more. In a dead and macerated fetus, the head of a hydrocephalus can take an elongated shape and pass through the pelvis. In a living fetus, this happens only with small degrees of hydrocephalus or in cases of spontaneous rupture of the head. Usually with unrecognized hydrocephalus, the head becomes an absolute obstacle to labor, so that if appropriate measures are not taken in advance, rupture of the uterus occurs, the lower segment of which is stretched even before the onset of labor contractions. In addition to spontaneous rupture of the uterus, which is observed in 7-8%, forced ruptures of the uterus are also observed during the performance of obstetric operations with incorrect diagnosis, deep ruptures of the cervix and vagina, necroses with the formation of fistulas. After emptying the overstretched uterus of a hydrocephalus, atonic bleeding is observed. Breech presentations of hydrocephalic fetuses are encountered, according to Hammerschlag, in 2/3 of all cases. Maternal mortality according to old statistics reached 20%. The prognosis depends on timely diagnosis. During pregnancy, suspicion of hydrocephalus may be caused by a large volume of the abdomen, a large volume of the head, parchment-like softness of its bones.
With very thin abdominal covers, it is sometimes possible to feel excessively wide sutures and abnormally large fontanelles. Bimanual examination facilitates diagnosis. After the onset of labor, suspicion of hydrocephalus arises if, with a normal pelvis and good labor progress, the head fails to engage in the pelvis for a long time. Internal examination then reveals the aforementioned characteristic features of the head, to which is added the discrepancy between the size of the cranial and facial parts of the head. The diagnosis is more difficult in breech presentations before the birth of the trunk. Once it is established that the obstruction for delivery is hydrocephalus, it is necessary to puncture the head in the area of the suture or fontanelle using a needle or trocar. After the fluid escapes, the reduced head is born spontaneously. Hydrocephalics after puncture may be born alive and even survive. If, despite puncture, the head does not deliver or signs of uterine overstretching occur, then to complete the delivery, perforation and cranioclasia are resorted to. Puncture or cranioclasia is also applied to the subsequent head in breech presentation. The rotation recommended by some authors in cases of hydrocephalus is hardly advisable, as it may prove dangerous due to stretching of the lower uterine segment. The application of forceps in recognized hydrocephalus is contraindicated. Agania (s. anencephalia) and hemicephalia (s. hemicephalia). In this developmental anomaly, the head as a whole has a small volume and delivery can proceed without any obstacles. In some cases, disruption of the labor process is observed because the onset of delivery is delayed and the fetus reaches a large size. The birth of the shoulders may encounter difficulty also because, due to the small size of the head, the soft birth passages are not sufficiently dilated for the birth of the trunk. Anencephalics, as well as hemicephalics, are usually born in face presentation. In diagnostic terms, this developmental deviation gives rise to errors, e.g., confusion with breech presentation. Negri and Viana point out that pressure on the base of the skull causes lively movements in an anencephalic. According to Popandopulo, in cases of suspected hemicephaly, pressure on the cerebral tubercles should be applied, which causes convulsive movements of the fetus. With a large trunk, timely rotation is beneficial. 3. Anomalies of the fetus in the neck area. Deliveries of fetuses with brain hernias as a rule proceed without deviations. Disorders of the labor process are observed in some cases when a large hernia is located on the occiput. The danger arising for the parturient then necessitates removal of the hernial sac or performance of cranioclasia. In the presence of a congenital tumor on the front of the neck (thyroid gland tumors, lymphangiomas, tumors originating from branchial arches), an extension type of labor mechanism is observed. Location of the tumor on the side of the neck causes asynclitic insertion. 4. Anomalies of the fetal trunk. Excessive size of the fetal trunk may be caused by: congenital dropsy (hydrops foetus universalis), accumulation of fluid in the thoracic and abdominal cavities, retention of urine in various parts of the urinary tract, cystic tumors of the kidneys, liver, spleen, ovary. The anomaly of the fetal trunk can be recognized when after the birth of the head or breech the trunk is retained and the introduced hand discovers a voluminous bladder. Treatment consists in puncture and evacuation of fluid. Spina bifida does not lead to complications during delivery, except in rare cases of very large spina bifida cystica sacralis. Dense sacral tumors, such as teratomas, lipomas, lymphangiomas, etc., are analogous to these in obstetric terms. 5. Conjoined twins. From an obstetric point of view, according to Veit and Seitz, they are divided into three groups. The first group consists of twins fused at the heads or buttocks, i.e., at the 'narrow' ends—craniopagi, ischiopagi, and pygopagi. Delivery in double malformations of this group usually proceeds without major deviations, as here the twins can pass through the pelvic ring one after the other. In craniopagi lying side by side, it is necessary to bring down the leg of one fetus. With small fetuses, delivery in the double position is possible. The second group includes twins fused by anterior, posterior, or lateral surfaces of the trunk. These include thoracopagi [see separate table (art. 255-256), figs. 2 and 3], sternopagi, xiphopagi. In delivery here, great difficulties may be observed because sometimes large parts of the twins enter the pelvis simultaneously, or because after the birth of one fetus or its part, the remaining fetus in the uterus is found lying transversely. Moreover, twins of this group are often fully mature. Xiphopagi, possessing great mobility relative to each other, may be born such that the head of one twin emerges simultaneously with the legs of the other, the latter being followed by the head of the second twin with the legs of the first. With small fetuses, the second twin lying transversely may be born duplicato. Often the birth of the second twin is possible only after its rotation to a breech position. The third group includes twins in which only one end—the head or breech—is completely separated, while in the other there is fusion. These include dicephalus, diprosopus, dipygus, as well as cephalothoracopagus. In dicephalics, significantly greater difficulties are observed during delivery than in thoracopagi. In rare cases, spontaneous delivery is possible. This is favored by breech presentation, so in these cases, if possible, rotation to a breech position should be performed. If it is not possible to sequentially extract one head after another, recourse is had to their division or reduction in volume of at least one head. In the rarely encountered form of division of the breech end, delivery may proceed without special difficulties, as most fetuses are premature. Difficulties in this type of malformation may arise during delivery due to the peculiar arrangement of the doubled number of legs, some of which may catch on the edges of the pelvic ring, therefore during rotation it is recommended to bring down all 4 legs. Fetuses of the cephalothoracopagus and diprosopus (janus) type are also usually born premature, which makes spontaneous delivery possible for them. If, however, they reach full maturity, then to extract them, destructive operations on the fetus must be resorted to. In the so-called asymmetric double malformations (epignathus, epipygus, thoracopagus parasiticus), delivery usually does not encounter great difficulties. Acardiacus, classified in the same group of malformations, may present considerable difficulties for delivery due to its large volume on the basis of edema. Early and late rupture of membranes. With the onset of labor, part of the amniotic fluid with each contraction moves from the upper part of the sac into the lower, bulging the lower pole of the membranes (amniotic sac). Bulging with each contraction through the cervical os, the amniotic sac contributes to the dilation of the cervix purely mechanically; on the other hand, the amniotic sac, by its pressure on the pericervical nerve apparatus, reflexively intensifies uterine contractions. During the pause between contractions, part of the amniotic fluid moves in the opposite direction from the lower part of the sac into the upper. With full dilation, the head is impacted deeper into the pelvis, the reverse flow of fluid is hindered, and the sac remains tense even during the pause. Finally, the amniotic sac, unable to withstand the intrauterine pressure, ruptures, and the 'fore waters' flow out. Fabr distinguishes the flat sac, when it forms no bulge, the cylindrical or sausage-shaped, when it protrudes significantly through the dilated cervical canal into the vagina, and the pear-shaped, when it protrudes into the vagina with slight cervical dilation (figs. 80-82). The latter indicates a delay in cervical dilation,
Figure 80.
Figure 81.
Figure 80. Flat sac. Dilation is almost complete. There is very little amniotic fluid between the membranes and the head. Figure 81. Cylindrical amniotic sac. The membranes form a bulge through the cervix, dilated approximately 8 cm. Examine carefully and in the intervals between uterine contractions.

amniotic sac. Dilation progresses little, the amniotic sac bulges into the vaginal cavity. One can think of a narrowed pelvis or incorrect presentation.
absence of advancement of the presenting part, discrepancy between it and the pelvis, which, on the other hand, serves as a poor prognostic sign (Fabre). In more than half of all cases, the time of rupture of the fetal bladder coincides with complete dilation of the cervix. According to Fabre, timely rupture of the bladder is observed only in 25% of cases. In more than 20% of all breech presentations, rupture of the fetal bladder occurs before complete dilation (Hugenberg). The following are distinguished: 1) timely rupture of the fetal bladder with complete dilation of the cervix, 2) premature rupture of the fetal bladder, when the latter ruptures before the onset of labor or during the first contraction with the vaginal portion preserved, and 3) early rupture, when it occurs after the beginning of contractions with a shortened vaginal portion with dilation of the cervix to 1-2 fingers. Premature rupture can lead to extra-amniotic pregnancy at the beginning of pregnancy, if miscarriage does not occur. The main causes: hydramnios, direct or indirect trauma. According to some authors, the frequency of premature rupture of the fetal bladder in the post-war period in Germany has increased. Consequences may be premature labor, which usually occurs after 4-5 days, and sometimes after several weeks. Premature rupture of the fetal bladder increases maternal morbidity and maternal mortality and stillbirth. The best prevention is strict observance of hygienic and dietary rules by pregnant women. The best results are obtained with a strictly conservative line of behavior and strict observance of aseptic rules. The latter condition dictates the necessity of admitting all cases of preliminary rupture of the fetal bladder to the hospital. For management of breech presentation when fever appears, see below - fever during labor. Among the causes of early rupture of the fetal bladder (early escape of waters), mechanical hydrostatic causes are in the first place. If the entrance to the pelvis is not tightly closed by the presenting part (narrow flat pelvis, incorrect position and insertion, etc.), then the amount of forewaters increases with each contraction, and as a result of excessive tension of the fetal bladder, it ruptures early. The degree of separation of the lower pole of the egg and the amount of amniotic fluid (hydramnios) also play a certain role, as well as direct and indirect trauma. According to histological research by Naujoks and Niderere, it is possible that in individual cases, insufficient primary development of the subamniotic and subchorionic layers of connective tissue reduces the resistance and elasticity of the fetal membranes. In very rare cases, according to research by Hauptmann, Naujoks, and Schmidt, the etiological factor may be inflammatory infiltration and maceration of the membranes in the lower pole of the egg, especially on the basis of gonorrhea. The unfavorable effect of early escape of waters on the course of the labor act ('dry labor') has been known for a long time. The role of early escape of waters in the etiology of postpartum diseases became the subject of study with the beginning of the bacteriological era. Early escape of waters weakens labor activity and prolongs labor only in some cases. According to Hugenberg, dry labors have a prolonged course only when the rupture of the bladder occurs too early, but if the rupture occurs with dilation of 1-3 transverse fingers, then the labor act proceeds even faster than normal. According to Guggisberg, a normal course of the labor act (and sometimes its acceleration) is observed when, under normal conditions, the head soon enters the pelvis and acts as a powerful irritant, with the exception of cases where the presenting part is small or soft, as in foot or breech presentations, transverse positions, or where the presenting part meets an obstacle to entering the pelvis (incorrect insertions, pendulous abdomen). Early escape of waters has an especially unfavorable effect in cases of pelvic anomalies. Weakness of labor activity is manifested mainly at the beginning of labor, immediately after early escape of waters. As the presenting part descends, even slowly, into the pelvis and enters into a more intimate connection with the cervix, labor activity increases. Early escape of waters leads to prolonged labor, large tears of the cervix, promotes the penetration of infection into the uterine cavity. Early escape of waters in a narrow pelvis, which in many cases is the cause of this complication, has in the first degree of narrowing the special clinical significance that after rupture of the fetal bladder, the presenting part approaches the bony pelvis. If this happens at the moment when the thickness of the wall of the lower uterine segment is 1-17 mm, the latter, in the presence of a small discrepancy, is compressed and fixed between the pelvic wall and the presenting part, thereby increasing the previously existing small discrepancy. If the rupture of the fetal bladder occurred after complete dilation of the uterine cervix or at least when the thickness of the wall of the lower uterine segment had decreased by half, the discrepancy would not have been to the same extent. In addition, early escape of waters reduces the mobility of the entire fetus, and what is especially important, the optimal mobility of the presenting head in relation to flexion, deflexion, and lateroflexion. The prognosis in early rupture of the fetal bladder depends to a large extent on the causes that condition it. In head presentation, breech presentations can proceed without complications. In other presentations, with hydramnios, with multiple pregnancy, especially with a narrow pelvis, this complication can lead to serious consequences. According to Vogel, in 10% of cases, an increase in temperature is observed. For the prevention of early rupture of the fetal bladder in cases where there is a direct threat of this complication in the presence of conditions contributing to it, it is first of all necessary to put the patient to bed. The treatment technique depends on the presence of the underlying pathology that led to the complication in question. Late rupture of the fetal bladder (late escape of waters) occurs, according to Schmidt, more often than early. Its main causes, according to Alfeld - small amount of amniotic fluid, weakness of expulsive forces. The density of the fetal membranes is also often found. Their thickness itself plays, according to Alfeld, Naujoks, and Niderere, a lesser role than the compactness of the connective tissue bundles. During a contraction, the bladder tenses like a drum. Contractions can be strong and properly alternate. Often the bladder remains intact during expulsion, and the child is born in the fetal bladder ('in a shirt'). Usually, delayed rupture of the fetal bladder does not have a harmful effect on the outcome of labor. In some cases, complications are still observed. These include: prolonged labors, extremely painful contractions, bleeding. Late rupture of the fetal bladder is not indifferent to the fetus, since the expulsion of the latter in an intact bladder can lead to premature detachment of the placenta and asphyxia of the fetus. Therefore, when spontaneous rupture of the fetal bladder is delayed, there is an indication for its artificial rupture (amniotomy). Other indications for artificial rupture of the fetal bladder are in some cases hydramnios, marginal placenta previa, artificial termination of pregnancy, twins (see above - multiple births), and finally, artificial rupture is performed as an aid preceding one or another obstetric operation. Technique of rupture of the fetal bladder. The rupture of the fetal bladder is performed at the time when it is maximally tense, i.e., at the height of a contraction. Under this condition, it is usually sufficient to press on it vigorously with the index finger to rupture it. Difficulties may arise with very dense membranes or with a small amount of forewaters, when the membranes are closely applied to the presenting part. Then resort to the help of instruments introduced under the control of the other hand - bullet forceps or a tenaculum. It is better to use an instrument when rupture of the bladder is used in placenta previa, as the finger can easily further detach the placenta from the uterine wall, which will cause increased bleeding. A tenaculum, with which the membranes are grasped, pulled, and twisted, and thus torn, is preferable in cases where a piercing instrument can easily injure the fetal head, i.e., with a small amount of amniotic fluid. For maximum observance of asepsis, the bladder should be torn in the center. In hydramnios, it is better to tear the bladder somewhere to the side, after slightly detaching the fetal membranes from the uterine wall. This promotes a slow outflow of amniotic fluid and prevents the prolapse of small parts, especially the umbilical cord. To prevent too rapid outflow of amniotic fluid and associated complications, the hand, under the control of which the operator introduced the instrument, remains in the vagina, while the outer hand, using the Müller maneuver, presses the head into the pelvis.
To prevent the consequences of rapid rupture of the membranes - prolapse of small parts, premature detachment of the placenta - the rupture of the amniotic sac is recommended to be performed when the cervix is sufficiently dilated so that in case of these complications, one can resort to one or another operative procedure. The operation of rupturing the amniotic sac, performed not for strict indications and without the necessary conditions, can lead to serious consequences for both the mother and the fetus.
Braude. XII. Pathology of labor in multiple pregnancy. Labor in multiple pregnancy, generally speaking, can proceed quite favorably for the mother and fetuses, and at times, e.g., in a narrow pelvis, a multiple pregnancy can end more favorably than a singleton pregnancy, since each twin, due to its relatively small size, can pass through the pelvis with such narrowing that would be insurmountable for a fetus of normal size. Nevertheless, it is hardly possible to speak of the physiological (normal) course of labor in multiple pregnancy, since in each individual case of multiple births, there are one or another pathological features. Already the fact that labor in multiple pregnancy occurs before term in almost half of the cases makes them pathological, although such labor can proceed and indeed do proceed quite favorably. Furthermore, multiple pregnancy is relatively much more often complicated by toxicosis in its second half than singleton pregnancy, and in connection with this, eclampsia and eclampsia are observed much more frequently in multiple births, especially in primigravidas. Such a serious complication of labor as placenta previa in multiple pregnancy also occurs significantly more often than in singleton pregnancy. In those cases where multiple pregnancy goes to term, labor often has the following pathological features: due to the strong stretching of the uterus, its contractions from the very beginning of labor turn out to be relatively weak (primary uterine inertia), as a result of which the dilatation period can be prolonged beyond the average norm. The expulsion period, if both fetuses are in longitudinal position, can proceed even faster than in singleton pregnancy, since each fetus individually, due to its smaller size, encounters relatively less resistance to its forward movement during its passage through the birth canal. However, in the expulsion period, uterine weakness of both primary and secondary nature is often observed. This is especially the case when passing the second fetus, since the rupture of the second amniotic sac is as a rule very delayed (in practice it is therefore often artificially ruptured, which significantly shortens the total duration of labor, however, this is not taken into account in many statistical data on multiple pregnancy). The rupture of the second amniotic sac is delayed because after the birth of the first fetus, the uterus, although it collapses, does not do so to the extent that it would immediately tightly enclose the second fetal egg. As a result, further contractions do not lead to a sufficient increase in intrauterine pressure, consequently they do not lead to an increase in pressure in the second fetal egg, hence the flaccidity of the second amniotic sac and its longer preservation of integrity. Only gradually, with the subsequent collapse of the uterus, its contractions finally lead to the goal - the second sac ruptures and the second fetus is expelled. Such a delay with the rupture of the second sac is aggravated in those cases when it is formed from the septum between both fetal eggs, since this septum consists of both relatively strong amniotic membranes. In dizygotic twins, the situation is even worse, since here the septum already consists of four layers - two amniotic and two chorionic membranes, which in their aggregate already present considerable resistance to rupture. Difficulties with the rupture of the second sac lead to the fact that the birth of the second fetus can occur many hours and even days after the birth of the first (cases are described where the birth of the second fetus occurred on the tenth day after the first). Before the rupture of the second sac, partial detachment of either the common placenta or the single placenta of the already born fetus can occur, which is already a very serious complication for both the mother and the second fetus. The entire course of the expulsion period is complicated especially when there is an abnormal position of both fetuses or one of them, and yet the correct position, i.e., cephalic presentation of both fetuses, occurs in only 40% of all multiple births, but even with cephalic presentation of both fetuses, both heads sometimes strive to enter the pelvis simultaneously, which makes the labor pathological from the very beginning. In the placental period, the pathology of multiple births again stems from the overstretching of the uterine wall, but also depends on the size of the double placenta (or two placentas). In general, it can be said that the placental period in multiple births is more often accompanied by bleeding and therefore artificial removal of the placenta is more often required. Finally, after the detachment of the placenta in multiple births, atonic bleeding is often observed, explained again by the previous stretching of the uterus and its inability to normal retraction after such stretching. All the listed complications in the course of the labor act lead to the fact that labor either is prolonged or requires one or another operative intervention, as a result of which the course of the postpartum period can also be complicated, which, significantly more often than in singleton births, proceeds with fever, and therefore gives higher maternal morbidity and mortality (fig. 83 and 84).
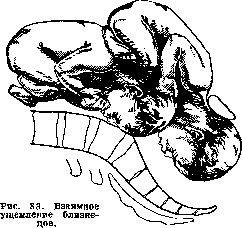
m. Kolosov. XIII. Pathology of labor complicated by local and general diseases of the mother. A. Labor and neoplasms of the female genital sphere. Labor and fibromyoma of the uterus. The course and prognosis of labor in fibromyoma of the uterus in most cases appear favorable for both the mother and the fetus. Despite this, one must always remember that various complications are possible. The prognosis of labor to a significant degree depends on the nature of the neoplasm - its size, the presence of multiple fibromatous nodes, its location in relation to the individual layers of the uterus (submucous, interstitial, subserous fibromyomas), as well as in relation to the long axis of the uterus (fibromyomas located in the upper or lower part of the uterus) (fig. 85). The significance in terms of influence on labor activity can also have a fibrotomy performed during pregnancy (see below). Complications during the labor act can be extremely diverse. The presence of a tumor, especially if it is of a multiple nature, can primarily affect
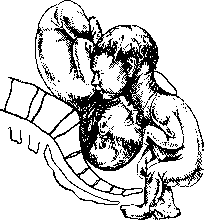
Figure 84. Mutual impaction of twins.
already born fetus, which is already a very serious complication for both the mother and the second fetus. All the listed complications in the course of the labor act lead to the fact that labor either is prolonged or requires one or another operative intervention, as a result of which the course of the postpartum period can also be complicated, which, significantly more often than in singleton births, proceeds with fever, and therefore gives higher maternal morbidity and mortality (fig. 83 and 84).
m. Kolosov. XIII. Pathology of labor complicated by local and general diseases of the mother. A. Labor and neoplasms of the female genital sphere. Labor and fibromyoma of the uterus. The course and prognosis of labor in fibromyoma of the uterus in most cases appear favorable for both the mother and the fetus. Despite this, one must always remember that various complications are possible. The prognosis of labor to a significant degree depends on the nature of the neoplasm - its size, the presence of multiple fibromatous nodes, its location in relation to the individual layers of the uterus (submucous, interstitial, subserous fibromyomas), as well as in relation to the long axis of the uterus (fibromyomas located in the upper or lower part of the uterus) (fig. 85). The significance in terms of influence on labor activity can also have a fibrotomy performed during pregnancy (see below). Complications during the labor act can be extremely diverse. The presence of a tumor, especially if it is of a multiple nature, can primarily reflect
Figure 85. Fibromyoma of the uterus in the lower segment.
on the very process of delivery, due to possible changes in the uterine musculature that can occur under the influence of fibromyoma. Thus, deliveries may be more prolonged and drawn out, primary and secondary weakness of labor may be observed, and more frequent indications for surgical intervention (forceps) may arise directly related to this. Some note a higher percentage of placenta praevia, abnormal fetal positions, prolapse of the umbilical cord, and small parts. In cases of large tumor size, the presence of a significant number of fibromatous nodes, or finally, low placement of the tumor (even if single), which directly obstructs normal delivery per vias naturales, more radical surgical intervention may be necessary—classic cesarean section (conservative with enucleation of individual nodes), Porro's operation, or even complete removal of the uterus. Indications for these latter operations may include significant overstretching of the uterus threatening rupture of the uterus, as well as abnormal fetal position, especially when there is a large number of fibromatous nodes. The choice of one or another method of operation (cesarean section, subtotal or total hysterectomy) is directly dependent on both the nature of the tumor, its extent, and the multiplicity of the neoplasm. In the latter case, leaving the uterus is undesirable (some, for example, N. Z. Ivanov, generally consider it irrational to leave the uterus after cesarean section due to possible subsequent bleeding, suppuration, necrosis, and even sepsis, and therefore advise after removal of the fetus to resort to subtotal or total hysterectomy). Complications may also occur after the birth of the fetus—in the placental and postpartum periods. Thus, bleeding in the placental period may occur, retention and attachment of the placenta (when it develops on the tumor), hypo- and atonic bleeding after delivery, and finally bleeding at a later time. Extremely rare complications are various degenerative changes in the tumor itself, its necrosis, and the occurrence of septic postpartum infection. However, these complications are not often observed, and in the vast majority of cases, delivery ends favorably for both mother and child (von Franque and others), thanks to which the advice of Pinar, Pobedinsky and others about expectant management of delivery in cases of uterine fibromyoma remains fully valid. Indeed, clinical observations show (for example, Selitsky, 1932) that all these individual complications occur not often and that in a fairly large percentage of cases of combination of delivery with fibromyoma, the presence of the tumor does not significantly affect either the act of delivery or the course of the postpartum period. A fairly common phenomenon is sluggish, abnormal labor activity, significant blood loss in the placental period, more abundant bloody discharge in the first days after delivery, and relatively often encountered poor involution of the uterus. Indications for major operations are not frequent, while necrosis (or suppuration) of the tumor is an exceptional phenomenon. Artificial premature deliveries, just like artificial abortion, should under no circumstances be performed; artificial termination of pregnancy should never be resorted to (Mikhnov), and these operations, as F. A. Alexandrov quite rightly notes, should be excluded from the number of operations used in pregnancy complicated by uterine fibromyoma. The question of myomectomy during pregnancy is currently resolved negatively by the majority of authors; it should be undertaken only in the presence of certain vital indications and threatening phenomena. Latest data also show that myomectomy should be performed only in the presence of specific indications. Thus, N. Z. Ivanov, considering that it gives extremely uncertain results, advises resorting to it only when the patient is threatened with immediate danger, while Lurie, proceeding from the considerations that premature termination of pregnancy may occur, and that various complications encountered in any operation may also be observed, believes that myomectomy should be performed only under the most strict indications (for example, severe pain, twisting of the tumor, necrosis). Selitsky pointed out (1932) that he generally takes a fundamentally negative attitude toward myomectomy during pregnancy, since clinical experience shows that along with a certain percentage of pregnancy termination after the operation, various abnormalities of labor activity, overstretching of the uterus, more frequent need for delivery operations, more frequent complications in the placental period, and increased maternal morbidity rate are more often observed. Generally, a quite definite impression is formed that performing myomectomy during pregnancy often creates indications for intervention during delivery. (However, this does not exclude the possibility that with appropriate indications, myomectomy may be a quite appropriate measure.) The same viewpoint was expressed by the majority of French gynecologists (at the congress in Brussels in 1929), namely, that indications for myomectomy during pregnancy are rare and that intervention is necessary only in the presence of the most serious complications (Brindeau, Reeb, Boquel, Favreau and others). The opinion of Turetskaya (All-Ukrainian Congress of Gynecologists, 1927) that myomectomy during pregnancy is an ideal form of treatment (Turetskaya quite often resorted to subtotal hysterectomy during pregnancy) met quite substantial objections from a number of congress participants (Bublichenko, Kudish, Matveev, Tikhanadze and others). Delivery and cancer of the cervix, ovarian neoplasms—see Pregnancy, Ovariectomy. B. Delivery after previous operations (on the sexual sphere and on neighboring organs) and after inflammatory diseases of the female sexual sphere (delivery after pelviotomy, see Pelviotomy). Delivery after various types of operations that fix the uterus may proceed quite normally; various complications and even very serious ones requiring not only some delivery operation per vias naturales but also surgical intervention may not be infrequently observed; thus, Franke over 10 years (1913-1923) collected in the literature 10 cases of cesarean section after ventrofixation and 6 after vagino-fixation. The position of the uterus that can be artificially changed, loss of its physiological mobility due to this, adhesions that develop after surgery, especially widespread or involving the upper parts and fundus of the uterus, fully explain the complications that may arise after antefixation of the uterus not only during delivery but also during pregnancy. The occurrence of torsion of the uterus, its dislocation, which also has a certain significance in the disruption of the rhythm of labor activity and generally in the pathology of the act of delivery, finds sufficient explanation. Significant forward bending of the uterus (at an acute angle), significant overstretching of the uterus (especially of its anterior wall and absence of its development), threatening and completed rupture of the uterus have been noted not infrequently. When performing cesarean section (for antefixation of the uterus), significant widespread adhesions were found, forcing the surgeon to operate in situ to avoid ruptures and trauma to neighboring organs, to make an incision on the posterior wall of the uterus, and in some cases, in the presence or absence of infection, to even perform total hysterectomy. In addition to all these complications, cases ending fatally have been described. Gubarev described a case of cesarean section after ventrofixation of the uterus, performed because the cervix of the uterus was positioned so high that it was impossible to reach it without risk even with the entire hand. In the case of Vorster after ventrofixation of the uterus, cesarean section was applied because the entire uterus lay transversely, there was transverse position of the fetus, but turning or bringing down the leg was impossible because the cervix of the uterus was positioned very high, sharply inclined to the right and adjacent to the pelvic wall. In Selitsky's clinic (1928), cesarean section was also performed after previous ventrofixation of the uterus due to significant thinning of the middle part of the anterior surface of the uterus and threatening rupture. During the operation, dislocation of the uterus, its torsion, almost complete absence of musculature in its thinned part were found; the left round ligament was attached to the anterior abdominal wall, while the right one was torn off. A whole series of complications after various types of antefixation operations of the uterus has been described by other authors. Along with the mentioned complications, there is also statistics with favorable outcomes of delivery after one or another operation that fixes the uterus. The opinions of gynecologists regarding various modifications of operations (antefixation of the uterus) in terms of their effect on subsequent deliveries are extremely different. Some consider ventrofixation more ensuring normal course of pregnancy and delivery, others—ventro-vesicofixation, vaginofixation, third—the Alexander operation. The viewpoints of authors on various modifications of these types of operations are also not the same. For example,
Davidson gives preference to ventrofixation and points out that it does not have a bad effect if only the proper method is chosen and if low fixation according to Delbe is performed. The importance of the place of fixation of the uterus was also indicated earlier, and many authors especially emphasized this, saying that the complications are the greater, the closer to the fundus the uterus is fixed (thus, even Olshausen wrote that fixation should not be performed higher than 1-2 cm above the internal os, and that severe disorders arise only with high vaginofixatio uteri); fixation near the fundus of the uterus prevents it from rising upward, promotes its improper growth. All the available data on this question, described and by no means isolated cases of severe complications after various operations antefixatio uteri, definitely speak in favor of approaching the performance of these operations in the childbearing age with extreme caution, since in a number of cases even a correctly chosen method and technically properly performed operation do not ensure in full measure the normal course of pregnancy and labor; if the operation is necessary, one can fully agree with Commandeur that preference should be given to abdominal hysteropexy, in which only the lower part of the uterus should be fixed, while vaginofixatio should be finally condemned in women in whom conception is not excluded, since after it complications are observed more often and of the most severe nature. In general, Baisch is right that all operations of hysteropexy connected with antiphysiological fixation of the uterus should be considered contraindicated in the childbearing age. It should also be remembered that various disorders and complications after operations fixing the uterus, which may even require surgical intervention, can occur without pregnancy and labor. Labor after operations antefixatio uteri (in Schauta's expression 'Antefixationsgeburt') should attract the greatest attention of the obstetrician; taking into account all the possible complications that may be the result of the operation, he must prevent their occurrence by taking timely measures (fig. 86-89). To orient oneself in the course of 'Antefixationsgeburt,' one can, following Schauta's advice, divide them into three degrees depending on the location of the os. If the os stands high, but still remains below the promontory, labor can most often proceed spontaneously. Along with this mild degree of deviation of the os, there may be cases of the os being at the level of the promontory or slightly above, and finally the most severe, third degree is the location of the os above the promontory, in the lumbar part of the spine. In the second degree, the probability of normal labor is significantly lower, and it is already necessary to resort to one or another intervention, such as incision of the anterior part of the cervix, metreurisis, version on the leg, hysterotomia vaginalis anterior (the possibility of cesarean section is by no means excluded); in the third degree, in the vast majority of cases, it is already necessary to resort to radical measures, often accompanied by complete removal of the uterus. Along with the location of the os, it is necessary to take into account the character of the labor activity, its deviations, the condition of the uterus and the degree of its tension and overdistention (one should not forget the relative frequency of incorrect positions of the fetus). The course of pregnancy and labor after a number of other operations also deserves no less attention - ovariectomy, operations for ectopic pregnancy, low, classic cesarean section, after perforation throughout the uterus and rupture of the uterus, after appendectomy and others. Although after all these operations normal spontaneous labor is quite possible (in cases of cesarean section, of course, when it was undertaken not on account of a narrow pelvis), various complications can still occur, sometimes even during pregnancy (for example, rupture of the uterus in the area of the scar after cesarean section), for which reason pregnant women and parturients who have undergone an operation should be under special care of the consultation and hospital; pregnant women should be placed in the maternity ward in advance for preventive purposes, and when labor occurs, their management requires the most meticulous attention from the obstetrician. After operations of appendectomy, ovariectomy (regardless of whether
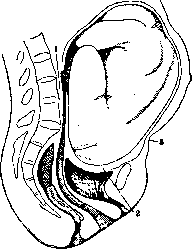
Figure 86. Violation of the act of labor due to ventrofixatio uteri according to Buram: 1- external opening of the uterus (at the level of the fourth lumbar vertebra); 2- anterior wall of the uterus; 3- place of fixation of the fundus of the uterus.
thinning of the uterine wall after antefixatio uteri according to Wertheim: 1- fundus of the uterus; 2- cervix; 3- posterior wall of the vagina; 4- anterior wall of the vagina; 5- anterior wall of the uterus (schematically).
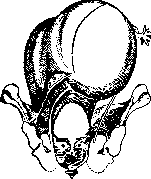
Figure 88. Stretching of the posterior wall of the pregnant uterus after vaginofixatio according to Kastner.
the operation was performed for a tumor or for some other disease), the same rules apply as after hysteropexy. After cesarean section, the management of labor depends on the indications for which it was performed. If it was performed for a narrow pelvis, then in subsequent pregnancies, when the pelvis has not changed, the same indications for cesarean section remain. If, however, the operation was performed for some other reason (placenta previa, inertia, etc.), then in subsequent pregnancies, labor can proceed normally, but it should be remembered that in such cases the uterus is weakened and the scar may give way, so that such women should be in the hospital from the very beginning of labor and the labor should be conducted with the greatest care. After operations for rupture of the perineum, the same rules apply as after other operations on the pelvic floor. After operations for retroversion of the uterus, the course of labor depends on the degree of retroversion and the condition of the pelvic floor. In mild cases, labor can proceed normally, but in severe cases, when the retroversion is accompanied by a significant relaxation of the pelvic floor, it may be necessary to resort to manual correction of the position of the uterus. After operations for fibromyomas of the uterus, the course of labor depends on the size and location of the tumor and the condition of the pelvic floor. In small tumors located in the lower part of the uterus, labor can proceed normally, but in large tumors located in the upper part of the uterus, it may be necessary to resort to cesarean section. After operations for ovarian tumors, the course of labor depends on the size and nature of the tumor and the condition of the pelvic floor. In small tumors, labor can proceed normally, but in large tumors, it may be necessary to resort to cesarean section. After operations for ectopic pregnancy, the course of labor depends on the condition of the pelvic organs and the extent of the operation. In mild cases, labor can proceed normally, but in severe cases, when the operation was extensive, it may be necessary to resort to cesarean section.

Figure 89. Pregnant uterus after ventrofixatio uteri. Cesarean section. The uterus has the shape of an elongated egg, its sharp end is located in the left hypochondrium. There is no presenting part. Two transverse fingers above the symphysis, thickened round ligaments of the uterus are palpable. Scar of the abdominal wall.
whether they occurred during or outside of pregnancy) labor usually proceeds normally. Great, if not exclusive, importance is attached to the course of the postoperative period. In the event of any postoperative complications, suppuration of the wound, formation of adhesions, development of adhesions, etc., various deviations may occur in subsequent labors and even premature termination of pregnancy. These deviations most often consist of anomalies of the expulsive forces, of abnormal labor activity, primary and secondary labor weakness. The changeable position of the uterus on the basis of adhesions, its displacement, deviation to one side or the other from the midline may be the cause of abnormal fetal positions, abnormal presentations and presentations. Similar complications may also be observed after laparotomy for ectopic pregnancy, but, as clinical practice shows, in a fairly large percentage of cases pregnancy and labor after it proceed normally. Deviations may also occur after the birth of the fetus in the placental period; thus, indications for one or another intervention are more frequently encountered than under ordinary conditions, and placental and postpartum hemorrhages are more frequently observed. Labor after complications observed in previous labors (fissure, ruptura uteri) or after the operation of artificial abortion (perforatio uteri) (if, of course, these complications were not so serious as to necessitate resorting to sterilization) may also proceed spontaneously and without the presence of any indications for one or another intervention. In a number of cases, however, complications (which are not so rare) may occur, and even Stolz quite rightly pointed out that after a previous rupture of the uterus during labor, the danger of a new rupture in the future is not only not excluded, but is quite possible, and that it may occur even during pregnancy. Winter, however, believes that this danger should not be overestimated, and that a rupture of the uterus in the area of the scar can always be prevented by resorting in individual cases to artificial premature labors (to the latter, however, one must relate with great caution, since the various methods of accouchement force used in such cases may aggravate the threatening phenomena; it is better not to resort to them at all and, when real symptoms of a possible repeated rupture of the uterus appear, to proceed to its elimination by the abdominal route, depending on the case, with subsequent sterilization or removal of the uterus). According to Winter, scars are so stable that they withstand not only pregnancy and labor, but even the operation of version, and the ensuring of the normal course of pregnancy and labor after a previous rupture of the uterus should consist in the smooth course of the postoperative period and in the primary healing of the wound. For the prevention of quite possible complications during labor, it is necessary to take a number of measures even during pregnancy (rational way of life, prohibition of heavy physical labor, wearing a bandage, etc.), and when labor begins - the most meticulous observation of its character and, above all, of the condition of the uterus and the degree of overstretching of its walls. In the event of any threatening phenomena, a gentle acceleration of the labor act (but not forced delivery), depending on the preparedness of the soft birth passages, is quite indicated. In case of insufficient opening of the cervix, in case of its rigidity, there is justification for cesarean section with subsequent sterilization or supravaginal amputation of the uterus. Labor after a small cesarean section (with various incisions of the uterine wall - longitudinal, transverse, on the posterior wall) and its various modifications - extraperitoneal cesarean section, cervical (deep or low), Porta's operation - have been described by a number of authors. Despite the existing statistics of quite favorable course of pregnancy and labor after the operation, one must always keep in mind the possibility of various, sometimes very serious complications, caused mainly by one or another pathological course of the postoperative period. The technical details of the production of the operation itself, the conditions of its production are the main preventive factors ensuring not only the normal course of the postoperative period but also guaranteeing against deviations in subsequent pregnancies and labors. Labor after low cesarean section require the most profound attention; the attention of the obstetrician should be focused on the character of labor activity, the intensity of uterine contractions, the condition of the cervix, anomalies in its dilatation, the size of the head, the position of the fetus and the character of the presentation of the presenting part; in case of any dystocia it is necessary to resort to a repeated operation to avoid the occurrence of serious complications, and in cases of complete dilatation of the cervix, with the head in the pelvic outlet, the prophylactic application of forceps is recommended. Hornung, describing 55 cases of labor per vias naturales after cesarean section, points out that in 43 (37 - head presentation, 6 - breech presentation) labor proceeded normally, in 8 abdominal and outlet forceps were applied (for prophylactic purposes), in 4 there was perforation of the head (in 2 - of a living fetus due to threatening rupture, but the women refused a repeated section). Hornung especially dwells on the placental period and notes the need for more frequent intrauterine intervention (20%), significantly exceeding the usual (average figures of Steckel's collective statistics 1.33%). Hornung, however, believes that every pregnant woman and parturient who has undergone cesarean section in the past is threatened by one or another danger, consisting in the possible insufficiency of the scar and in the attachment of the placenta in the area of the scar. - The main line of conduct of the obstetrician in relation to women who have undergone cesarean section in subsequent pregnancies and labors should be expectant. If any threatening phenomena appear during pregnancy, it should be interrupted. The best method should be considered cesarean section, which also allows, at the same time, to often perform the necessary sterilization in such cases; artificial premature labors, insertion of balloons, puncture of the membranes, introduction of pituitrin are contraindicated, as they may aggravate the danger (further thinning, overstretching of the scar, lower segment) for which the operation is undertaken. Pregnant women shortly before labor (10-14 days) should be hospitalized, and when labor begins, they should be conducted in the most meticulous manner so as not to miss a developing complication and to provide timely operative assistance. The placental period also requires special attention, giving a fairly large percentage of deviations. The course of pregnancy and labor after inflammatory diseases of the female genital sphere (e.g., gonorrhea, local and postpartum diseases, parametritis, thrombophlebitis, etc.) constitute still a little studied chapter of obstetric pathology. The possibility of pregnancy occurring after one or another infection is confirmed by a number of clinical observations. In a number of cases, pregnancy may be interrupted at earlier or later stages, not infrequently it proceeds completely normally and ends in normal, spontaneous labors and an afebrile postpartum period. Thus, e.g., Seitz, Gross and others believe that in acute inflammatory processes pregnancy is almost as a rule interrupted, and its interruption is not an exception even in chronic diseases. The interruption of pregnancy may be due to the further spread of the process (in acute cases), the insufficient capacity of the affected uterus for further growth and carrying of the fetus (changes in the mucous membrane, myometrium, widespread adhesions of the uterus with the peritoneum, with neighboring organs), and also to a large extent by those widespread adhesions which may be observed after the disease. On the other hand, cases of the opposite order have been described; these cases show that pregnancy after inflammatory processes not only can proceed completely normally, but can even become a factor that finally cures the previously existing pathological process of the female genital sphere (e.g., parametritis). Akimova (1932) cites, e.g., the cases of Kolosov, Selitsky, in which pregnancy occurred in the presence of a large parametritis, which completely disappeared during the pregnancy, with subsequent normal course of labor and the postpartum period. Similar cases have been observed by other authors; Yurasovsky, among others, believes that inflammatory processes in the small pelvis under the influence of pregnancy resolve and disappear without a trace, but that this does not apply to far advanced diseases. When labor begins, one must take into account certain basic points that may serve as the cause of one or another dystocia in labor.
Thus, deviations may occur in the first period and be caused by disorders in the mechanism of dilation of the cervix due to its chronic inflammatory condition (one must also remember the possibility of cong-lutinatio orificii uteri externi), its displacement, abnormalities of labor activity (primary and secondary labor weakness) due to reduced functional capacity of the uterine muscular motor, and finally displacements of the uterus (its dislocation), overstretching of the lower segment on the basis of limited or more extensive adhesions, and with possible abnormalities in fetal position and abnormal presentations of the presenting part. Along with all this, due to pathological rigidity of the cervix, as well as changes in the myometrium, contractions can very often be extremely painful, especially after gonorrhea. The course of labor can be extremely varied and be in direct dependence both on the degree of the inflammatory process undergone and on the condition of the sexual sphere at the time of delivery (e.g., presence of unabsorbed exudate, adhesions, altered position of the uterus, etc.). In a number of cases, especially with processes that ended before the onset or during the pregnancy itself, with chronic processes, with minor adhesions, with relative or not sharply expressed displacement, with normal fetal position and normal relationships between the pelvis and the presenting part, labor may end spontaneously; however, in the presence of any of the aforementioned conditions, active intervention, including cesarean section, is indicated. Some believe (e.g., Eberlin) that cesarean section is fully justified in such cases and it is better to proceed with it directly (which gives significantly better results) rather than after various types of vaginal manipulations. A particularly instructive case is described by Akimova, in which the only method of delivery was classic cesarean section, which gave entirely favorable results (cesarean section was performed in the presence of purulent parametritis, a fistula in the vagina, hemolytic streptococcus in the discharge; along with this, there were sharply expressed rigidity of the cervix, placenta praevia, abnormal fetal position, and marked elevation of the uterus, and during the operation extensive adhesions of the uterus with the peritoneum, intestinal loops, and the omentum were found). Of the methods of cesarean section, in the overwhelming majority the classic method (with operating in situ) is the most suitable (and sometimes the only one), since the high position of the uterus, the presence of infiltrate, and adhesions exclude the possibility of operations in the lower segment, or of Porro or Porta operations.-When allowing labor to proceed spontaneously, they should be conducted with extreme care, taking into account possible complications and their timely elimination. All methods of forced delivery, the introduction of pituitrin, should not be used in such cases. Labor in various types of acute and chronic infections may also present certain peculiar features and be accompanied by various complications. The onset of labor in certain infections can lead to exacerbation, worsening of the process, accompanied by a rise in temperature, weakening of cardiac activity, collapse (thus, even Gusserow pointed out that in typhus the onset of labor leads to exacerbation of the disease, rise in temperature, chills), and also give a relatively high maternal mortality rate. In individual cases, one must also consider the possibility of intrauterine death of the fetus (cases of intrauterine infection, developmental disorders have been described). The course of labor in one or another infection is often quite normal. Thus, for example, Frenkel (Frankel) stated regarding typhus that it has no effect, Seitz also noted that in typhus labor usually proceeds without complications and that there is only a tendency to strong postpartum hemorrhages (this is confirmed by others, e.g., N. Z. Ivanov); in dysentery, Gogoberidze speaks of a certain slowed course of labor; in malaria, also slowed labors 1 are noted in 1/3 of cases (lengthening of the first period—Kharitonov, Yurtaykin), they proceed more difficultly and more often, due to weakening of the tissues and decreased elasticity, edema and a higher frequency of forceps application, atonic hemorrhages, retention of membranes (Gogoberidze), and increased blood loss (Zakrzhevsky); Dubarry, however, notes special weakness of labor pains in cachexia. Management of labor in most acute infections should be expectant; if any intervention is necessary, it should be carried out in the most careful manner and with the strictest observance of aseptic rules. The importance of expectant management was already emphasized by Gusserow, Litten, and others, and they pointed out the special predisposition to puerperal septic infection. Induction of artificial premature labor in certain infections (e.g., typhus, influenza) is condemned by most modern obstetricians. In managing labor, it is necessary to monitor the general condition, cardiac activity, and pay attention to the condition of the uterus (especially in the second stage and in the first hours of the puerperium—danger of hypo- and atony of the uterus!). Some recommend for preventive purposes during the expulsion stage the application of forceps. The least favorable results are given by influenza, maternal mortality in it reaches 50% and more (Seitz and others). Mortality is also great in pneumonia (20-30-40%); the mortality rate varies depending on the complications that arise—mainly pulmonary edema, failure of cardiac activity. In influenza and pneumonia, there is also a tendency to uterine hemorrhages. In pneumonia, especially when threatening symptoms are present, acceleration (careful) of the act of delivery is indicated: under appropriate conditions—forceps, with unprepared soft passages—hysterotomia vaginalis anterior. Labors in tuberculosis, syphilis in the overwhelming majority of cases proceed normally. In tuberculosis, in processes accompanied by anemia, exhaustion of the body, primary and secondary labor weakness may occur, the need for more frequent forceps application, but one must also consider (especially in more pronounced cases) the possibility of complications in the third stage (retention of the placenta, hypo- and atony). For some of the same reasons as in acute infections, forceps application is recommended in tuberculosis. Labors in various heart diseases can proceed quite normally. As clinical observations show, great importance is attached to timely hospitalization of each case regardless of the nature and degree of heart damage. Along with this, the most strict individualization is also necessary, since, as is evident from clinical practice, with a certain pedantic regimen even the most severe diseases can proceed quite favorably during labor and without any signs of decompensation. Age, as well as the number of pregnancies undergone, affects both the course of pregnancy and especially the act of labor; it is also necessary to consider the nature of the course of the given pregnancy; pregnancies complicated by multiple pregnancy, polyhydramnios, concomitant diseases; on the 24 other hand, kidney diseases, proceed more severely, give more deviations during labor and in the puerperium. In managing labor, constant observation by the obstetrician is necessary, especially in cases of existing decompensation, which can worsen considerably during labor, especially during the expulsion stage and immediately upon removal of the fetus. One must also consider significant fluctuations in blood pressure (especially a rise during the expulsion stage) and the possible negative effect of a decrease in intra-abdominal pressure immediately after removal of the fetus. In a number of cases, artificial rupture of the membranes is quite indicated (sometimes also acceleration of delivery, e.g., introduction of metrerinter; with the latter the obstetrician's vigilance must be even more increased), shortening of the second stage of labor (which some, for example, Yakub, especially recommend) by application of forceps or another appropriate operation (sometimes the indication for performing these operations may be the not infrequently observed secondary labor weakness). Heart diseases, admittedly in rather rare cases, may also be indications for cesarean section (under local anesthesia). After expulsion of the fetus, in connection with the fairly rapid decrease in intra-abdominal pressure, it is necessary to apply weight on the abdomen (sandbag). Along with this, one must consider the possibility of hemorrhages in the third and puerperium periods, especially frequent in cases even of relatively mild decompensation. In managing labor, the appropriate position of the parturient (elevated, semi-sitting) is also of great importance, which is maintained even when performing one or another delivery operation, and the administration of one or another cardiac remedy under certain indications. In severe cases, in cases of decompensation, distinctly expressed myocardial insufficiency, one must consider not only the possibility of a sharp exacerbation but even the possibility of sudden death.
Such cases have been described by a number of authors. However, in general, serious complications during breech presentation (cyanosis, collapse) are rarely observed, and the cause of death in these cases, as Leyden indicated, is collapse or pulmonary edema, which may occur during breech presentation or immediately afterward (according to Leyden, these complications more often occur in mitral stenoses). In cases of acute cardiac insufficiency, or with acutely or suddenly developing decompensation, the primary importance is given to the application of the usual arsenal of cardiac remedies and other appropriate measures (Jagic recommends intramuscular or intravenous administration of digitalis, caffeine, strophanthin); the rational use of oxygen is indicated; in other cases with cyanosis and dyspnea, moderate venesection is beneficial. As for the course of breech presentation in various nervous and mental diseases, whether observed before pregnancy or developing directly on its soil, such a course, as old and recent observations show, can proceed in the overwhelming majority of cases without any complications. Thus, normal deliveries have been described in tabes dorsalis (Yakub), in sclerose en plaques (Betyutskaya), in general paralysis (Sukhanov), after transferred chorea of pregnancy, toxic polyneuritis, etc.
s- selshchiy. XIV. Bleeding in the first and second stages of labor. Bleeding in the first and second stages of labor can depend on various causes, and in each individual case a thorough analysis of the research data is required to make a correct diagnosis, especially in cases where internal examination is avoided. First of all, it must be kept in mind that all labors as a rule begin with bleeding, although usually insignificant. This bleeding is due to the separation of the lower segment of the ovum from the walls of the uterus: the amniotic sac is formed, and the small maternal blood vessels supplying this part of the membranes are ruptured. The flowing blood mixes with the cervical mucus and is excreted along with this mucus, which is also one of the signs by which the actual onset of labor is judged. Subsequently, this initial bleeding is maintained not by the separation of the sac, but by tears in the mucous membrane of the cervix itself as it gradually dilates. Such bleeding can also be quite significant if there are venous dilations and nodes in the cervical mucous membrane. During strong labor activity in the expulsion stage, not only the mucous membrane but also the tissue of the cervix itself can be torn. In this case, the bleeding could take on quite abundant character if it were not stopped due to the fact that the presenting part, by making rapid forward movement, presses the bleeding sites against the walls of the pelvis. However, after the birth of the fetus, such tears and ruptures of the cervix begin to bleed again, sometimes very strongly, but they are already considered as bleeding of the placental or postpartum period. If the bleeding in the first and second stages of labor has a more prolonged and intense character, then it cannot be explained by the above-mentioned causes - here we are dealing with other kinds of complications - most often low attachment of the placenta, its presentation, or premature detachment with normal attachment (see Placenta). Such bleeding already presents a certain danger to the parturient and very great danger to the fetus - they constitute a very important chapter in the pathology of the act of labor. With low attachment of the placenta, its lower periphery is easily separated at the very beginning of labor when the amniotic sac is formed. The mechanism of bleeding is the same as with normal separation of the amniotic sac, but the vessels that are ruptured in this case will naturally be of much larger caliber, and therefore the bleeding no longer has the harmless character of a small admixture to cervical mucus, but can be quite strong. The density of the membranes and the so-called "shortness" of them are of considerable importance in this case - both of these prevent the formation of a good amniotic sac. The diagnosis of this complication is easy: with the help of internal examination, one is convinced that there is no placental tissue in the os and near it; further, the examining finger observes the character of the amniotic sac during the pause and during the contraction: if the membranes are dense and short, then the surface of the sac remains flat or slightly convex ("flat sac"), and the membranes forming the sac are stretched during the contraction, like the skin of a drum. The therapy, if required by the nature of the bleeding, is as simple as the diagnosis and consists in breaking the sac with a finger or instrument. This not only stops the bleeding but often significantly accelerates the stage of dilation, and the contractions themselves become much less painful than they were before the rupture of the sac. If the examining finger feels the tissue of the placenta itself in the os or immediately at its edge, then we are dealing not with low attachment, but with placenta previa (see). Detachment of the placenta can also occur with attachment of the placenta in the usual place, i.e., on the anterior and posterior walls of the uterine cavity. This complication as a nosological unit is called "premature separation of the placenta" (see Placenta). In the second stage of labor, bleeding is caused by tears of the vaginal walls; if there are dilated veins or venous nodes in them, the bleeding can be quite abundant, but usually these bleeding also stop as the presenting part advances, which compresses the bleeding sites, as is the case with deep tears of the cervix during the dilation stage. In the expulsion stage, tears of the perineum and tears of the clitoral labia usually occur - and in both cases, bleeding is usually discovered only after the birth of the fetus, and sometimes after the expulsion of the placenta, which is why these bleeding are usually considered in the section on placental and postpartum bleeding. The diagnosis of these bleeding is easily achieved by careful examination of the external genital organs. The therapy consists in applying sutures to the perineal tear and to the bleeding sites. In addition to the main causes listed here that cause bleeding in the first and second stages of labor, bleeding in these same periods can occur as an accidental and rare complication of labor on the basis of one or another pathological change in the birth canal. Thus, the presence of a cervical polyp can first be discovered in labor precisely by bleeding. Also, a cancerous disease of the uterine cervix can first manifest itself in labor - the fragile cancerous tissue under the influence of stretching begins to tear and bleed. In contrast to the above-mentioned premature separation of the placenta, which is distinguished as a separate form, premature separation of the placenta can occur in the second stage of labor from purely mechanical causes - most often from absolute or relative shortness of the umbilical cord. A short umbilical cord is strongly stretched during the forward movement of the fetus and as if tears the placenta away from the wall of the uterus. Naturally, bleeding occurs in this case, but it is never accompanied by such formidable phenomena as described above, and usually represents a danger only to the life of the fetus. One can suspect that the bleeding is of exactly this origin by observing the process of engagement and passage of the presenting part - at the end of the expulsive efforts, the presenting part sharply returns to its original position, being pulled back by the elastic umbilical cord. When listening to the fetal heartbeat, sharp fluctuations in its frequency and rhythm are noted, sometimes it is possible to hear the "noise of the umbilical cord." All the bleeding listed above depends on the violation of the integrity of the uteroplacental blood vessels and naturally, the blood lost in this case will be the mother's blood. Only with placenta previa, sometimes along with the rupture of uteroplacental vessels, the vessels of the chorionic villi are also ruptured, and then both the mother and the fetus lose blood. This partly explains the enormous mortality of fetuses in placenta previa. However, cases are occasionally observed when bleeding in the first and second stages of labor depends exclusively on tears of the blood vessels of the fetus itself, i.e., its membranes - here the blood flows only from the fetus, and the mother is not threatened with any direct danger. Such complications are possible with incorrect "velamentous" attachment of the umbilical cord (insertio velamentosa funiculi umbilicalis), in the presence of an accessory lobe of the placenta, located at a great distance from the main placenta and connected with it by long blood vessels; finally, in exceptionally rare cases, "lost" blood branches of the umbilical vessels (vasa aberrantia) are located in the thickness of the fetal membranes. With each of the mentioned anomalies, it can happen that a section of the membranes with vessels passing through it becomes "presenting" and goes to form the amniotic sac. Obviously, with stretching of the amniotic sac and especially with its rupture, the abnormal blood vessels passing through it can easily be torn or ruptured. As a result, bleeding will occur, but the blood will flow exclusively from the fetal circulatory system, which will lead to its exsanguination and death during labor. Such a complication can be diagnosed if during internal examination on the sac it was possible to determine the presence of similar vessels. Theoretically, diagnosis is possible by microscopic and biological examination of the flowing blood. In reality, however, the diagnosis of this complication and its explanation are made post factum - after the birth of a dead or exsanguinated fetus and upon examination of the placenta with membranes. With timely diagnosis of this type of bleeding, therapy should of course consist in the earliest possible delivery for the purpose of saving the FETUS.
m- Kolosov. XV. Anomalies of the timing and duration of childbirth. Normally, childbirth in a woman occurs, as was already known to the ancients, after 40 weeks from the first day of the last menstruation or after about 273 days after conception, and this term, even under normal conditions, can represent fluctuations in either direction, i.e., childbirth can occur on the 39th and 41st week, counting from the first day of the last menstruation. In all these cases, childbirth will be on time or mature (partus maturus). Often, however, pregnancy in a woman is interrupted before the specified time. If the termination of pregnancy and the onset of childbirth occurs between the 28th and 38th week, the child is usually born capable of extrauterine life, and such childbirth are known as premature (partus praematurus). The etiology of premature childbirth in general is the same as that of miscarriages (see Abortion), but they proceed in their main features in the same way as timely childbirth. On the other hand, childbirth can occur later than the specified time, and such childbirth receive the name of delayed (partus serotinus). This term is understood differently by various authors: Winckel, for example, speaks of delayed childbirth if the fetus developed in the uterus longer than 41 weeks; Yaschke and Pankow consider childbirth delayed if they occur 300 days or more after the last menstruation, Bumm and Ruge II - where pregnancy lasted more than 302 days from the time of conception. Children in delayed childbirth usually have larger than normal dimensions, since in general, the longer the fetus develops intrauterinely, the larger dimensions it reaches. Therefore, delayed childbirth usually proceed with greater difficulties than timely ones. It should be noted, however, that the degree of development of the fetus in these cases does not always strictly correspond to the duration of its stay in the uterus; the fact is that when the pregnancy ending with delayed childbirth reaches a certain term, the fetus usually dies, and often remains after the death of the child (b. or m.) for a long time in the uterus, undergoing maceration here. Cases where it would remain alive longer than 302 days from the time of conception belong to very great rarities; the longest duration of a living fetus in the uterus was observed by Becker: the death of the postmature fetus occurred only after 340 days from the first day of the last menstruation; dead children, however, can remain in the uterus much longer, sometimes even for several years; in the Russian literature, for example, there is a case described by Solovyov, where the retention of the fetus in the uterus lasted 6 years. The reason why postmature fetuses, upon reaching a certain term of development, die, is a question that has not yet been fully clarified to this day. A special type of delayed childbirth consists of the so-called unfulfilled childbirth, missed labour. This term was first introduced into obstetric practice in 1847 by Oldham, and Oldham himself understood missed labour simply as childbirth not occurring at the normal time, i.e., delayed childbirth, but most modern authors apply it only to those cases where in pregnant women, when pregnancy reaches the normal term, pronounced labor activity begins, but this activity does not lead to the expulsion of the fetus, labor contractions cease, and the fetus remains in the mother's womb for several more weeks, months and even years (in one case described by Abramovich - 4 years) and is born - or extracted operatively - only later, dead and macerated, and in individual cases putrefied decomposed or turned into lithopaedion. The causes of such a peculiar course of pregnancy are again precisely unclear. Bumm explains the origin of missed labor by insufficient excitability of the uterus depending either on anomalies of the nervous system, central and peripheral, or on patho-anatomical changes in the uterine musculature. Fast, street, road, prolonged childbirth. The average duration of normal childbirth is defined differently by modern authors: Huggisberg, for example, says that childbirth in primiparas on average lasts 15-20 hours, in multiparas 10-12 hours; Nurnberger determines the duration of childbirth as 18 hours for the first and 8 for the second, and indicates that of this time 16 hours in primiparas and 7 hours in multiparas lasts the dilatation period, and 2 hours in the first and 1 hour in the second - the expulsion period; other authors give different figures. If childbirth proceed significantly faster than the specified terms, they receive the name partus praecipitatus. In such accelerated childbirth, or both of their periods - the dilatation period and the expulsion period - are shortened, or, even more often, only the expulsion period proceeds very quickly, while the dilatation period can have a normal duration or even last longer than normal. The reason for the accelerated course of the act of childbirth may lie either in excessively strong work of the expulsive forces, or in the insignificance of resistance from the walls of the birth canal, or in both together; therefore, fast childbirth are more often observed in multiparas. For the fetus, they are rather favorable, but for the mother they comparatively often lead to ruptures of the soft birth passages. It is precisely in excessively fast childbirth that it often happens that the parturient woman does not have time to arrive for delivery at a maternity institution, and the infant is born on the street, in a vehicle, etc. ("street", "road" childbirth), and sometimes even the parturient woman does not have time to take the appropriate position for childbirth, for example, to lie down in bed, and gives birth standing, while walking, sitting in the toilet, etc. Such childbirth, however, can also occur with sufficient duration of the act of childbirth, if the parturient woman, due to either the slight painfulness of labor contractions or simply from unfamiliarity with the course of childbirth, is unable to realize that the moment of delivery is approaching for her; therefore, according to observations of some foreign authors, such precipitous childbirth - Sturzgeburt, as German obstetricians call them - often occur in primiparas. If the child in such childbirth appears into the world when the mother is standing or walking, its weight sometimes breaks the umbilical cord, and falling on a hard floor or cobblestones, it can severely bruise the head. In the parturient woman, in such cases, due to traction on the umbilical cord, partial detachment of the placenta can occur, accompanied by more or less significant bleeding. In contrast to excessively rapid course of childbirth, they sometimes drag on much longer than the usual time, and again, excessively prolonged can be either only the dilatation period, or only the expulsion period, or both together. The cause of such prolonged childbirth may lie either in excessively weak activity of the expulsive forces (see Anomalies of expulsive forces), or in excessively significant resistance from the birth canal, depending either on anomalies of the fetus (transverse position, excessively large dimensions of the entire fetus or its individual parts, incorrect mechanism of childbirth, etc.) or on anomalies of the birth canal itself - its hard (narrow pelvis) or soft parts (see above). Whatever the cause of the prolonged course of childbirth, it threatens serious dangers both for the fetus, which often dies from asphyxia at this time, and for the mother (ruptures of the uterus, general exhaustion, infection), which is why in such cases it is necessary to resort to one or another type of obstetric intervention (see below).-If a woman dies during childbirth from one reason or another without delivering, the child can sometimes appear into the world after her death ("cadaveric childbirth"), in individual cases - when the mother is already in the coffin. Such cases have been described for a long time, but for a time they were attributed to the realm of fairy tales. At the present time, it can be firmly established that cadaveric childbirth are quite possible, precisely in those cases where death catches the parturient woman in that stage of childbirth when the uterine cervix is sufficiently dilated in her, i.e., at the end of the dilatation period or in the expulsion period. Such postmortem childbirth were described in the Russian literature by Nikitin, Reiman, Teplyashin, Stupnikov, etc. In the origin of cadaveric childbirth, two factors play a role: firstly, postmortem contractions of the uterus (it has been experimentally established that the uterine muscle continues its contractile activity for some time even "after the death of the parturient woman, and some authors, for example among us Sochava, could observe this clinically as well), and secondly, a strong increase in intra-abdominal pressure due to postmortem development of gases in the abdominal cavity. Under the influence of this second factor, in a relatively large percentage of cadaveric childbirth, simultaneously with the expulsion of the fetus, uterine inversion also occurs, sometimes with its extrusion from the genital slit, as for example was in both cases of postmortem childbirth observed by Stupnikov. These cases present not so much an obstetric, as a medico-legal interest.
V. Gruzdev. XVI. Fever during childbirth. Fever during childbirth (febris sub partu, febris intra partum) - a name applied to cases occurring with subfebrile or elevated temperature. In view of the existing disagreement among obstetricians regarding which cases with what temperature should be considered as febris intra partum, and in view of observed cases of infection without fever, some authors propose that all cases of infection during childbirth, regardless of whether they occur with normal or subfebrile temperature, be considered as intrapartum infection. The majority, however, adhere to the term 'febris intra partum', understanding it as cases occurring with elevated temperature, and they divide them into cases of genital and extragenital origin (extragenital includes various acute and chronic infections; cases of eclampsia with high temperature are not included in this category, as the elevation of temperature during seizures is caused by other reasons). The viewpoint regarding what elevation of temperature should be considered as cases of febris intra partum is also not uniform. Thus, many believe that only cases starting from 38° (under the arm) or 38.5° (per rectum) should be considered as fever, since a slight elevation of temperature is observed in every parturient, while others include cases with temperature of 37.5°. Selitsky believes that although 37.5° is a very arbitrary criterion for differentiating cases with febris intra partum, it should still be taken as the exact criterion, because often, especially in cases of extragenital fever (in chronic, acute general infections - tuberculosis, influenza, sore throat, etc.), the temperature is below 38° and the predominant symptom is not elevated temperature, but symptoms from the muscular motor of the uterus, generally the birth canal, as well as from the entire organism (e.g., increased pulse, chills, etc.). The etiological factor in febris intra partum in the vast majority of cases is infection. The question of whether so-called 'functional', 'physiological' fever can exist remains controversial and unresolved to this day. Although bacteriological studies by Krenig have proven the presence of microbes in the uterine cavity and amniotic fluid, Warnecros, Sachs, and others have established the role of infection in the occurrence of febris intra partum and largely refuted the opinion of Olshausen, Glockner, and some others about the predominant significance of functional factors, it is hardly possible to completely deny them. Undoubtedly, if in the vast majority of cases the cause of febris intra partum is infection, at the same time cases of elevated temperature without the presence of infection can be observed; such cases may be caused by the act of childbirth itself, and in them the elevation of temperature can be considered as functional, physiological, along with the general physiological reaction of the entire organism and individual organs (e.g., physiological albuminuria sub partu) both during childbirth activity and immediately after its completion. But this does not mean that every febris intra partum should be considered as functional; it is only necessary to differentiate between fever of functional and infectious nature, and in differential diagnosis to consider not so much the temperature (as, for example, Sachs thinks, who considers that 38.0° is already a sign of infection), but the general condition of the parturient, the frequency of the pulse, shaking chills, and other symptoms indicating obvious infection of a local or general nature, of genital or extragenital origin. Arguments against the possibility of functional febris intra partum, such as the fact that it usually has weak labor pains (whereas if febris intra partum is considered functional, one would expect the opposite - more intense work of the uterus), cannot be convincing, because very often prolonged labors with primary and secondary uterine weakness ultimately lead to an elevation of temperature (with its critical drop immediately after completion of labor) precisely on the basis of functional fatigue of the uterus due to its insufficiency or other anomalies of the act of labor (this, on the other hand, does not exclude the possibility of infection occurring in prolonged labors). Meyer-Ruegg considers functional fever as 'aseptic' and believes that it always proceeds mildly. As for the infectious fever, which occurs much more frequently, its mechanism of occurrence is not yet sufficiently clear. Thus, the question is not resolved whether fever of genital origin is caused by the direct transition of bacterial toxins into the blood or whether there is first an ascent of bacteria along the genital tract, their penetration into the uterine wall, and then their entry into the bloodstream. Therefore, the question of whether toxemia or bacteremia is present has not been clarified. Warnecros believes that after the penetration of microbes, decomposition of the amniotic fluid occurs first (while the blood remains sterile), and fever is caused by the absorption of the resulting toxins due to the presence of pathogenic microbes in the uterine cavity. He considers this toxemia as the first and transitional stage of febris intra partum, which subsequently leads to placental bacteremia, which, in his opinion, is always present in severe forms. Fever can also be caused by retention of a dead fetus and its putrefactive decomposition on the basis of the penetration of putrefactive microbes into the uterine cavity. Due to the ensuing putrefaction, gases accumulate in the uterus and a tympanic sound appears on percussion (physometra or tympania uteri). Attempts to determine the degree of severity of infection, to speak about prognosis on the basis of bacteriological studies can hardly be considered successful, because, as Siegert quite rightly notes, the vaginal flora changes depending on the environment, and bacteriological research cannot give an idea of the hemolytic action of staphylococci and streptococci, nor can it take into account the essential factor - the protective ability of tissues. In practical terms, it also gives little, because one cannot be guided by bacteriological research (Ehlich) because the establishment of a bacteriological diagnosis occurs when labor is mostly already over; according to Bublichenko, bacteriological research does not give definite data for prognosis. Therefore, the data of bacteriological research have only relative significance; of course, it is necessary to take them into account, but one has to be guided (especially in the choice of therapy) mainly by the clinical picture of each individual case. The frequency of febris intra partum (Table 1) Table 1. Frequency of fever during childbirth Authors, institutions Number Number of cases of births fever during labor % frequency % mortality Selitsky - Prosolupov. Clinic of obstetrics and women's diseases of the State Scientific Institute of Okhmatdet named after Lebedeva. 1925-29 (Selitsky) 5,000 2.7 Layakovich. Moscow Oblast Institute of Okhmatdet (maternity hospital named after Lepekhin). 1924-28 (Ilkevich) 22,127 4.5 0.6 Khuntsev. Infectious postpartum department of the Kiev City Hospital named after the October Revolution. 1926-30 (Khuntsev) - 2.34 1.9-operative labor 0.5-spontaneous labor Ehlich. Universit. Frauenklinik. Würzburg. 1923-23 (Gauss) 3,105 1.77 1.8 reduced 0 (death from anemia) Zangemeister - Wieloch. Universit. Frauenklinik. Königsberg. 1915-27 (Zangemeister) 14,499 3.7 - Hilgenberg. Universit. Frauenklinik. Münsterberg (Esch) 3,558 4.23 2.7 4.6 died - 6 Ernst. Universit. Frauenklinik. Berlin. 1923-30 (Stoeckel) 10,279 died 15, of which 1 from anemia * Ahlfeld - 2.9%, Kronig - 2.9%, Ihm - 2.8%, Henkel - 3.6%. is subject to relatively large fluctuations; these fluctuations can partly be explained by the fact that the concept of febris intra partum is interpreted differently by different authors, in addition they undoubtedly can also depend on the rational organization of obstetric care, well-established work in consultation, protection of pregnant women from various accidental infections, timely isolation from sick family members, etc. Among predisposing factors, premature rupture of the membranes, placenta praevia, narrow pelvis, abnormal fetal positions, primiparity and internal examination outside the clinic are mentioned. As for the opinion of some (for example Singermann and others) that I-para are particularly predisposed to febris intra partum, it is not confirmed by subsequent observations (Layakovich. Ehlich; Selitsky and Prosolupov note febris intra partum in I-para in 27.2%, while in M-para in 72.8%); if one can speak of a greater predisposition of I-para, it is only of elderly primiparas due to the rigidity of tissues, their greater vulnerability, and the associated greater predisposition to infection (Ehlich). The frequent coincidence of placenta praevia with febris intra partum is also not confirmed by all; thus, while Hilgenberg points out that in cases of fever placenta praevia is noted in 2.67%, while in non-febrile births only in 0.96%, there are statistics in which placenta praevia was not encountered even once.
The data regarding the frequency of febris intra partum in cases of pelvic anomalies is also conflicting; for example, some state that a narrow pelvis occurs in 16% of cases of febris intra partum, but only in 4.4% of normal deliveries (Hilgenberg), while others have not observed such a significant difference. Abnormal fetal positions are quite common in febris intra partum. Coitus plays a significant role among predisposing factors, especially in cases where it occurred closest to delivery or after the waters had already broken. Clinically, two forms are distinguished - local and general infection (mostly of a septic nature). Local infection can occur in a milder or more severe form. The main difference between mild and severe forms is not the height of the temperature, but primarily the frequency of the pulse, repeated shaking chills, and poor general condition. Meyer-Rügg, distinguishing between two forms of fever - mild and more severe - also believes that the main indicator of its severity is not so much the temperature as other clinical phenomena, since very high temperatures can also be observed in mild cases. Table 2. Results of spontaneous and operative deliveries in febris intra partum (in %). Authors Spontaneous deliveries Operative deliveries 1st day of fever or 1st degree of infection Mild complications or 2nd degree of infection Moderate and severe complications or 3rd degree of infection Selitsky-Prosolupov 90.2 63.8 14.6 15.6 6.0 9.8 44.5 - 11.0 44.5 Lankowitz 1st stage 2nd stage 46.0 70.0 43.0 25.0 11.0 5.0 4 cases 25.0 42.0 - 50.0 42.0 25.0 16.0 0 2 cases Khuntuntsev 69.5 62.0 24.0 13.0 0.6 30.5 37.0 32.0 30.0 6.0 Ernst 54.3 59.0 - 35.0 5.5 6.7 6.0 2.0 45.7 39.0 47.0 14.0 8.0 Hilgenberg 55 cases (46.6) 15 cases with ruptured membranes 56.3 45.7 34.5 26.7 1.8 13.3 1.8 13.3 80 cases 53.3 38.7 33.7 3.7 3.7 5.0 Sachs 63.0 17.0 14.5 5.5 - 37.0 15.5 25.0 15.5 7.0 Zangemeister Wieloch 52.1 59.3 60.0 37.6 36.8 FEVER 0.8 2.1 2.0 2.1 INFECTION 2.0 REMAINS 47.9 OF DELIVERY 39.6 | THE 41.0 43.7 45.0 5.2 5.0 8.5 8.0 6.1 6.0 Ehlich - 61.5 - 23.1 15.4 - 24.1 27.6 48.3 - in the absence of chills and with a pulse corresponding to the temperature. The persistence of temperature sub partu varies and can depend to a large extent on the method of managing delivery; in any case, a drop in temperature to normal before the end of delivery is not uncommon (for example, in the clinic of the L. Institute of Maternity and Infancy named after Lebedeva with conservative therapy, it was observed in 31.9%). The therapy of febris intra partum has exceptional importance both for a favorable outcome of delivery for the mother and fetus, and for the course of the postpartum period. The opinion that prevailed for many years (cited in some manuals even of the most recent time) that febris intra partum not only serves as an indication for the rapid termination of delivery when the birth canal is prepared, but even for forced delivery, has been largely shaken by carefully followed observations from not individual clinics. These observations (Tables 2 and 3) with sufficient persuasiveness show that at present one can speak of the opposite, namely, that spontaneous deliveries in febris intra partum give better results for both mother and fetus, while the fever itself not only does not serve as an indication for operative intervention, but is often even a direct contraindication to it. The observations of Sachs, confirmed by a number of other authors, have established that operative intervention, giving worse results compared to spontaneous deliveries, is also not equivalent for different types of operations. Thus, Sachs divided all operations according to their effect on the postpartum period into dangerous and non-dangerous operations (Table 4) (among the former he included combined delivery, difficult forceps, especially with subsequent ruptures and bruises of tissues, manual removal of the placenta and deep episiotomy). Dangerous interventions and complications associated with them should also include accouchement forceps and mainly metritis. Some also include destructive operations on the fetus and ruptures of the perineum in this category (Hilgenberg), especially if they are observed in combination with manual removal of the placenta. Thus, Ernst (Ernst) on 207 operative and spontaneous deliveries without intervention in the postpartum period reports 3% mortality, while on 50 deliveries with intervention - 12% mortality. As for perforation, Khuntuntsev indicates that the worst results were obtained by him in operations violating the integrity of the fetus, namely 45% severe infection and 12.5% mortality (Ernst in the same operations obtained 16% maternal mortality). According to Khuntuntsev, operative deliveries pose a greater danger also from the point of view of subsequent atonic hemorrhages (as is known, febris intra partum itself predisposes to greater blood loss during delivery; thus, according to calculations by Hilgenberg, blood loss of more than 500 cm³ in normal deliveries is observed in 9%, while in febris intra partum in 32.3%). All these data eloquently show that the modern obstetrician should manage delivery with fever as conservatively as possible, and if operative intervention is necessary, perform it as carefully as possible, avoiding dangerous operations, trauma to tissues, and ruptures of the perineum (Wieloch especially advises abstaining from active therapy with high and prolonged temperature). Some operations should not be performed at all in febris intra partum. Thus, despite the advice of some authors to resort to the application of trial (or generally) high forceps (Stroganov), they should not be used at all, as without giving any benefit to the fetus, they only aggravate the danger to the mother (Ernst) and give particularly poor results (Ihm, Mittelacher). Purely surgical obstetric operations - vaginal and abdominal cesarean section - must be considered separately. As for the latter, it should be used in febris intra partum only in the most exceptional cases; often in such cases it will be accompanied by subsequent hysterectomy or performed according to the latest proposal of Portes. To speak definitively regarding the application of vaginal cesarean section is premature at present, although the favorable outcome of cases both in late miscarriage with high temperature and in term deliveries (in the presence of severe and even septic endometritis when rapid and gentle emptying of the uterus is required), in placenta praevia, hydatidiform mole, etc. (Kalmykov, Okinichits, Pobedinsky, Seitz, Wenzel and others) shows that it can be used in this complication, although the exact indications must still be developed, although in general it is undoubtedly that the scope of application of vaginal cesarean section, especially in severe infection, should be significantly limited. Adopting the principled standpoint of conservative management of febris intra partum, one should not forget that its frequent companion is primary and secondary labor weakness (classified by Bumm as septic), which is sometimes all the more pronounced the higher the temperature. And the therapy of labor weakness must be approached cautiously, managing delivery carefully, since it is necessary to take into account that the uterus (its muscular motor) also suffers in febris intra partum, its functional ability is reduced, and for this reason the effect of various chemical and mechanical factors that enhance labor activity or promote faster dilation of the cervix will differ significantly from the effect of the same means in normal deliveries, in deliveries occurring without elevated temperature. For these reasons, one should completely abstain or at least avoid all those means whose effect is not always the same, can cause incorrect, violent contractions, and finally means that can cause various complications and worsen the course of delivery in febris intra partum.
For this reason, one must with great caution resort to the use of pituitary gland preparations, especially to their administration in strong and repeated doses (and under no circumstances conduct their 'generous' prescription, as, for example, Zaks recommends), since they not only may turn out to be completely ineffective (Bumm), but also may be harmful, causing spasmodic, tetanic contractions with all their unpleasant consequences. Contrary to the advice of some (Bublichenko), the introduction of any balloons whatsoever, including the meter-rinther, should be completely abandoned. A confirmation of this is also a number of clinical observations; thus, Ehlich after their introduction observed shocking chills and an increase in fever, Khuntsev noted after the use of the meter-rinther 65% of severe infections and 33% mortality. Hot vaginal douches are not rational, if even not harmful. Quinine, administered regularly and periodically (every 7-1/2-1-2 hours) in small doses (0.1-0.3), can be of great benefit; a positive effect can also be expected from the use of sugar water or tea with sugar. It is necessary to remember that sometimes uterine inertia can be confused with other abnormalities of labor activity, namely short, frequent, abrupt, extremely painful spasmodic contractions, which must be noticed in time and eliminated with appropriate means (narcotics-morphine or enemas-1/2 glass of water 8-10 drops Tincture of Opium and 25 drops Tincture of Valerian). Along with constant observation of the feverish puerperal woman, the utmost aseptic conduct of labor and care for the puerperal woman, especially with a longer duration of labor [care for the external genital organs, timely emptying of the bladder and rectum, in certain cases care for the oral cavity, maximum use of all methods of external obstetric examination, performance of internal examination only for the most strict indications; the use of vaginal douches should be considered inadvisable, while the advice of some, for example, Hilgenberg, to perform them (with 1/3% solution of creosote soap) before every internal examination and obstetric intervention is not shared by all and is hardly necessary]. The question of subsequent postpartum therapy should be resolved within the same conservative frameworks. One must adhere to the principle-as few interventions as possible on the diseased uterus, as more careful management of the period immediately following the act of labor. For this reason, Zweifel's (E. Zweifel) proposal about systematic washing of the uterus in all feverish women (especially after operative delivery) with a solution of Mea-Jodin or Sagrotan (abundant washings of 2-3-5 liters immediately after labor and only once) is hardly rational; many (Bumm, Krenig, Val'tgard) consider uterine washings in septic diseases even contraindicated. Similarly, hardly beneficial is Zangmeister's advice about the introduction (for the purpose of more correct outflow of secretions) to reduce postpartum morbidity and mortality of a gauze or metal drain 1-2 hours after the expulsion of the placenta (with exposure of the vaginal portio with specula and gentle traction of the cervix with Muse's forceps downward) and leaving it for 24 hours (although there are favorable data by Wigger about its use after intra partum fever, without, however, indicating the nature of the cases of intra partum fever with and without the use of the drain), S. Selitsky. XVI. Pathology of the third stage of labor. The course of the third stage of labor in the modern cultured woman almost always has a somewhat pathological character, since in the vast majority of cases the placenta is expelled spontaneously only from the uterus, and from the vagina it is expelled not spontaneously, but with the help of one or another artificial method, not always rational, and often directly dangerous. Retention of the placenta in the vagina is explained by the fact that the woman's vagina is poor in muscle fibers and therefore its peristaltic contractions are insufficient to expel the placena outward, as should be the case in normal conditions. The functional insufficiency of the female vagina is further aggravated by the fact that during the passage of the fetus it is relatively overstretched by the very large head of the human fetus. The musculature of the abdominal press is also not strong enough, since the abdominal wall is also overstretched during pregnancy and labor, and in the first few hours after the birth of the fetus, even a strong puerperal woman is usually unable to develop sufficiently strong bearing-down efforts to expel the placenta from the vagina outward. To this must be added that retention of the placenta in the vagina to a certain degree may also be due to the horizontal position of the puerperal woman during labor. However, it should be immediately stipulated that the proposal made in this connection to make puerperal women expel the placenta while squatting has in general not given satisfactory results when carried out. In practice, therefore, it is considered normal for the third stage of labor to proceed when the placenta is expelled without complications and without any intervention from the uterus not outward, but into the upper part of the vagina within the first two hours after the birth of the fetus. From the vagina the placenta is then expelled by manual manipulation- elevation of the uterus, grasped by the hand of the accoucheur in exactly the same way as is done when expelling the placena from the uterine cavity according to Credé's method. A longer retention of the placenta in the uterus, even if it is not caused and is not accompanied by any complications, is still considered pathological, since prolonged retention of the placenta in the uterus interferes with its good contraction and promotes ascending infection of its cavity from the lumen of the always contaminated vagina. Of course, the two-hour period is taken conventionally and to a certain extent is determined not only by the interests of the puerperal woman, but also by the interests of the personnel caring for her, and in obstetric institutions by the interests of the institution itself-the necessity to free up beds in the delivery rooms as quickly as possible. In the pathology of the third stage of labor, two aspects are distinguished: 1) pathological detachment of the placenta and membranes from the uterine wall and 2) pathological (delayed) expulsion from the uterus of the already detached placenta and membranes. In normal conditions, the placenta detaches from the uterine wall immediately after the birth of the fetus, and may even be earlier-after the birth of only the head, since after the birth of the head the entire body of the fetus exits from the uterus into the vagina, and the uterus itself collapses so sharply that the conditions for detachment of the placenta from the contracted uterine wall are already present. The detachment of the placenta occurs in the thickness of the spongy layer of the decidua, and this layer in normal conditions is so loose and the partitions in it are so thin that detachment can indeed occur very quickly and usually proceeds very rapidly. However, the physiological process of placental detachment is easily disrupted if its attachment is stronger than should be the case in normal conditions. In individual cases, such a stronger attachment may depend on a greater than normal thickness of the partitions of the spongy layer or on a greater than normal strength of the blood (arterial) vessels that pass through these partitions, extending from the uterine wall to the intervillous space. This type of structure of the spongy layer we have as normal in premature labors and in late miscarriages, when there are not yet present the degenerative changes in the decidua that are observed at the very end of pregnancy. Therefore, delayed detachment of the placenta in premature interruption of pregnancy depends essentially for the most part not on pathological changes in the decidua, but on its 'immaturity'. At term labor, such 'immaturity' is observed, as stated, only in individual cases, and in the majority of cases of pathological attachment of the placenta we have definite pathological changes in the decidua. They can (conditionally) be divided into three degrees. The first degree-the mildest-is observed in the case if the spongy layer of the decidua is poorly expressed or is completely absent, then between the chorionic villi and the uterine musculature we will have an interlayer of one compact layer of the decidua. The placenta is as if firmly glued to the uterine wall and can detach from it only after a prolonged time, when the cytolytic process will dissolve the cells of the compact layer and in this way destroy the connection between the placenta and the uterine wall. This type of pathological attachment of the placenta is called placenta adhaerens. With such attachment, the placenta can sometimes be removed even by simple expression according to Credé. If, however, it is necessary to resort to manual separation, such separation usually does not meet great difficulties. If, however, the chorionic villi attach themselves directly to the musculature (placenta accreta) or even grow into it up to the peritoneum (placenta increta), then there will be an accreta of the placenta (see Placenta, placenta accreta). Pathological expulsion of the detached placenta from the uterine cavity-retention of it (retentio placentae)-very often depends on improper management of the third stage of labor.
Observations of the natural course of this stage of labor show that after the birth of the fetus, the uterus needs some time to adapt to its new state, after which several rather strong contractions occur and by the force of these contractions the placenta is gradually expelled from the uterus into the vagina. If this regular course is disrupted by premature attempts to forcibly expel the placenta from the uterus or even by a simple 'uterine massage' applied with the best intentions, then either irregular contractions occur that do not give the desired effect, or the uterus goes into a state of tetanic retraction. Such retraction usually involves the circular muscles of the lower part of the uterus and its cervix, resulting in a strong spasm of this muscular ring—the placenta is either 'trapped' in the uterus or 'impacted' in the cervix (placenta incarcerata; placenta captiva). In former times, this kind of retention of the placenta was quite frequently observed when ergot preparations were administered before the expulsion of the placenta. In contrast to this excessive contraction of the uterus, retention of the placenta is sometimes also observed due to weakening of the uterus after the birth of the fetus. In this case, the uterus contracts so weakly that it cannot expel the already separated placenta with membranes from itself. A disturbance in the course of the placental stage is usually accompanied by bleeding, and this constitutes its immediate danger. The cause of bleeding in cases of uterine weakness is clear—it is the same as in postpartum hypo- and atony, i.e., it depends on the gaping of the blood vessels of the placental site, not compressed as in the normal case by the contracted uterine musculature. In cases of partial placenta accreta, bleeding also occurs from the blood vessels of the placental site, but only on that part of it where the placenta has already separated, since this part cannot contract as long as on another, even very small, part of this site there is still a non-separated placenta. In complete placenta accreta, as well as in its incarceration, bleeding usually does not occur, but instead the placenta is not expelled not only after the conventional two hours, but even after many hours of waiting. It is precisely bleeding that is the most frequent indication for intervention in the pathological course of the placental stage. Here a reasonable uterine massage and medicinal agents (instead of ergot preparations, preparations of the posterior lobe of the pituitary gland are now mainly used) may be appropriate. However, if these measures do not achieve their purpose—bleeding continues and the placenta does not come out—then it is customary to proceed in a certain sequence, namely: first, the placenta is expressed from the uterus by the method of Credé, and if this succeeds, then of course the placenta is immediately expelled from the vagina. If expression by Credé does not succeed and there is no obvious hypotonia or atony of the uterus, then Credé is repeated under anesthesia, which significantly increases the chances of success of this method, since it eliminates the tension of the abdominal press of the parturient and relaxes the spasm of the uterine cervix, if present. (In an atonic state of the uterus, anesthesia, especially chloroform, is contraindicated, because it in turn increases uterine atony.) If expression by Credé does not succeed even under anesthesia, then one has to resort to manual separation (see Obstetric manual maneuvers). This operation, simple in concept, is not so easy in practice and requires very delicate touch, otherwise separation is performed in the improper layer and either the uterine wall is traumatized or individual parts or even entire lobes of the accreted placenta are left in the uterus. The main danger of the operation, however, lies in the fact that during it the uterine cavity is very often infected independently of the obstetrician, with all the resulting consequences. Precisely because of this last reason, manual separation of the placenta gives morbidity and mortality of mothers exceeding those in all other obstetric operations, not excluding cesarean section. The difficulties and dangers associated with the expulsion of the placenta by the method of Credé, and even more so with its manual separation, and at the same time the indications of experience that often an 'accreted' placenta at its manual separation is already separated—all this taken together forces obstetric thought to work on improving the technique of placental expulsion and inventing new methods (fig. 90). This includes the above-mentioned proposal to deliver the placenta in a squatting position, to which also belongs the method of Abladze (the rectus abdominis muscles are grasped by the obstetrician in a fold, after which the parturient is asked to bear down) and a number of other methods. Without denying the rationality of all these methods, it must still be borne in mind that they give success only in cases of placental retention. Where there is placenta accreta, one will inevitably have to resort to manual separation. Its danger will be reduced when methods of preventive vaccination and therapeutic therapy, including serotherapy, of sepsis are found, and mainly when hygiene and dietetics in general and for each pregnant woman in particular are more thoroughly carried out in consultations. For now, every attention must be paid to the fight against anemia of parturients, so often accompanying the pathology of the placental stage of labor. Up to the present time, it must be said, blood transfusion is still not widely enough applied in this matter, and if it is performed, then only in cases of acute anemia, as ultimum refugium; meanwhile one can think that blood transfusion can play a major role in the prevention of septic diseases in anemic parturients, since observations show that the very virulence of infection in these cases depends not so much or not only on the virulence of bacteria, but on the reduced resistance of the anemic organism. M. Kolosov.

Figure 90. Incomplete separation of the placenta with hemorrhage.
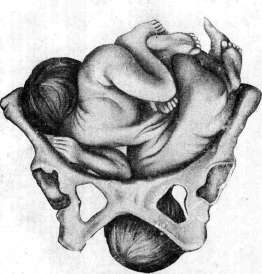
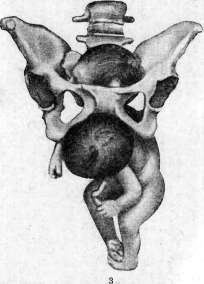
Figure 1. Ttecheial rash after childbirth. Figure 2. Eight-month-old thoracopagi. One head was born spontaneously during strong deviation of the second fetus (from Stoeckel). Figure 3. The same. Spontaneous exit of one head during strong deviation of the other (from Stoeckel).
Among the dermatoses associated with pregnancy, labor, and the postpartum period, emphysema, urticaria, and purpura (Selitsky) are encountered. Dermatoses during labor are extremely rare (much less frequently than during pregnancy and the postpartum period). Besides emphysema, purpura haemorrhagica (see separate table, fig. 1) (Selitsky, 1929), subcutaneous facial petechiae (Keller, 1932) have been described. Jadasson observed severe urticaria that began during contractions and disappeared 3 days after delivery. The appearance during labor of transverse grooves on the nails has also been described, which however have no practical significance (they occur not only in the mother but also in newborns). Emphysema of the skin is a very rare phenomenon during labor; only about 80 cases have been described (Rosmark, 1932). Wiener (1924) believes that there is 1 case of emphysema per 2,000 labors, which occurs in severe cases of labor, especially in primiparas. A very characteristic case is described by Besson and Salmon: in a primipara at the height of labor activity, a large tumor with characteristic snow-like crepitus appeared in the subclavian and sub-sternal regions. All this happened within a few minutes, without general symptoms, without dyspnea, asphyxia, and without an increase in temperature. The patient experienced only the usual feeling of discomfort. Lasting 8 days, the tumor spontaneously disappeared, starting from top to bottom. No deviations from normal in the heart and lungs were observed at any time. Therapy—only compresses.—In a prognostic respect, according to Besson and Salmon, it must be taken into account that there may be cases with limited spread of emphysema and finally more extensive ones that may have a fatal outcome. In cases of the latter category, acceleration of the labor act by the application of forceps is always indicated. The etiology of emphysema remains unexplained. Usually it occurs on the basis of rupture of lung parenchyma \ damage to the trachea as a result of crying and straining in severe complicated labors, in narrow pelvis, in large fetus, obstacles from the soft birth canal, especially in primiparas. According to the statistics of Schener, out of 55 cases of emphysema, 51 cases were observed in primiparas and only 2 cases in multiparas and grand multiparas.
d. Mazo. XIX. Obstetric shock, sudden death of parturient women, puerperal women (embolism). Cases: of a sharp weakening of parturient women or puerperal women shortly after the birth of the fetus are relatively rare phenomena in obstetrics. This condition is usually associated with collapse arising on the basis of severe external or internal hemorrhage, the presence of diseases of the cardiovascular system, or with "obstetric shock" when the aforementioned phenomena are absent. A distinction is made between obstetric shock with and without hemorrhage; the latter includes hypoglycemic shock, cardiac shock, and shock of thyroid origin (on the basis of dysfunction of the thyroid gland). Clinically, this condition manifests as a sharp deterioration in the condition of the parturient-puerperal woman. Instantaneous paleness of the skin and mucous membranes with a cyanotic tint appears; the patient complains of ringing in the ears, darkening before the eyes. The pulse is irregular, of very weak filling, sometimes completely impalpable on the a. radialis. Consciousness is preserved, but the patient is frightened, answers questions in a whisper, giving the impression of a mortally ill patient. This condition lasts for 1½ hours or more, after which the patient comes to her senses. In other cases, obstetric shock ends fatally. The essence and mechanism of occurrence of obstetric shock, as well as of shock in general (see Shock), are very complex and not entirely clear in all their details. Great importance in this phenomenon is attached to the irritation of the peripheral endings of sensory nerves, paralysis of the cardiovascular tone and as a result of this uneven distribution of blood, sharp congestion of vessels in areas innervated by the n. splanchnicus. The patho-anatomical picture of obstetric shock is usually very meager. Quite often it is impossible to find an anatomical substrate even on the dissecting table. In some cases (Mandelstam) on autopsy hypoplasia of the aorta, flabbiness and fatty degeneration of the right heart were found. Moments favorable to the occurrence of obstetric shock are the severe pain of labor exhausting the parturient woman, recently infectious diseases, as well as extensive trauma (rupture of the uterus, etc.). Although in the latter case the clinical picture of obstetric shock is largely obscured by the phenomena of the underlying disease, the significance of obstetric shock even in cases with extensive traumatic damage to the birth passages is evidenced by the fact of rapid death of some such patients with very insignificant blood loss, both external and internal (Feigel). These forms of obstetric shock bring their pathogenesis closer to surgical shock. The therapy of obstetric shock consists in providing the patient with complete rest first of all, since one must always remember that new trauma can only increase the shock. Therefore, any interventions, such as the Credé method, intrauterine interventions, suturing of the perineum, etc., are contraindicated for the entire time of being in a state of shock. Warming the patient (hot water bottle, bottle to the head and other parts of the body) is beneficial. The administration of cardiac agents, although carried out extensively in such cases (camphor, caffeine, strychnine, physiological solution), however, the actual effectiveness of these agents in shock is doubtful. Based on the pathogenesis of obstetric shock, it makes sense not to burden the patient with numerous procedures and injections, but on the contrary, to increase rest by administering small doses of narcotics (½ ampoule of pantopon) and only then to use cardiac agents. The introduction of 10% glucose (Kegelmayer) is also recommended, from the intravenous administration of which (in saline solution - 500 cm³) some (Gusakov) saw very favorable results. Gusakov considers blood transfusion the best remedy, while others recommend for raising peripheral tone the introduction of saline solution with adrenaline, pituitrin. Individual authors advise the introduction of colloidal solutions (Lapenta). It is extremely important in these cases to exclude the presence of internal hemorrhage, which requires completely different behavior from the physician. Prevention of shock is extremely difficult and should consist in eliminating infectious diseases during pregnancy and shortly before delivery (influenza), in careful monitoring of the condition of the cardiovascular system of the parturient woman and in careful delivery (Zelgeim) by anesthetizing with small doses of narcotics especially painful contractions of the uterus during labor. Sudden death of parturient women (puerperal women) without any visible reason to the observing obstetric personnel is a very rare phenomenon in obstetric practice. The predominant cause of death in such cases is air embolism, i.e., the entry of air through the uterine veins and its obstruction of the pulmonary artery, coronary artery, etc. Although air embolism is found on the dissecting table as the cause of death, however, the possibility of its occurrence in the postpartum uterus is probably exaggerated. As experimental data have shown, even the introduction of a large amount of air into the bloodstream is tolerated by animals without harm. (Clinical picture and therapy of air embolium see Embolium.) One of the sources of air embolism can also be the introduction of a tampon with ether into the postpartum uterus to stop atonic hemorrhage. With insufficient outflow from the uterine cavity, liquid ether, passing into a vapor state, can penetrate into the dilated veins of the placental site. Prevention of air embolism during labor consists in eliminating intrauterine manipulations in the lateral and especially the knee-elbow position of the parturient woman (puerperal woman), when negative pressure is formed in the abdominal cavity and the danger of air entering the bloodstreams through the placental sinuses increases. Observance of elementary rules when prescribing vaginal and especially uterine douches (preliminary removal of air from the nozzle by a stream of liquid), the use of a catheter with double outflow during intrauterine manipulations or ensuring sufficient outflow in some other way from the uterine cavity, low pressure (not higher than 1 liter from the level of the bed) - the main prevention of embolism. In addition to air embolism, the causes of sudden death of parturient women and puerperal women can be emboli detached from thrombi of placental vessels, as well as from thrombi of other parts of the vascular network (in the postpartum period). In the latter case, among the preventive measures in addition to those mentioned above, one should also include preventing the puerperal woman from getting out of bed at the slightest suspicion of the presence of a thrombus (difference in pulse rate and t°, etc.; details see above - pathology of the postpartum period). Feigel. XX. Ruptures of the soft birth passages and the bony ring. During labor, ruptures of the cervix and body of the uterus, ruptures of the perineum, clitoris and vagina, violations of the integrity of the bony ring of the pelvis and associated damage to the bladder and rectum can occur. Ruptures of the cervix. Minor multiple tears of the mucous membrane in the area of the external os, occurring during the period of dilatation and not causing significant hemorrhage, are physiological phenomena of the act of labor. Such tears of the cervix under normal conditions are facilitated by weak uterine musculature, poor ability of the cervical mucous membrane to stretch and the absence during labor of counterpressure for the freely hanging vaginal part. Ruptures of the cervix, which should be classified as pathological phenomena, can have the following causes: 1) abnormalities of the presenting part - insertion of the head in a state of extension, excessively large volume of the presenting part; 2) peculiarities of the cervix - rigidity of the cervix in an infantile uterus in primiparas of advanced age, in chronic inflammatory processes of the cervix, in changes associated with syphilis and cancerous lesions of the cervix, peculiarities of the cervix in placenta previa; 3) excessively rapid passage of the head and rapid stretching of the cervix during stormy labor; 4) forced dilatation of the cervix (e.g., with a Bossi dilator, metreurinter or when applying forceps with incomplete dilatation of the cervix). The main, almost sole symptom of cervical rupture is hemorrhage; the higher the rupture goes, the closer it approaches the supravaginal part of the cervix, the vaginal vault and the parametrium, the greater the chances of damage to large vessels (rami descendentes, a. uterinae) and the basis for profuse hemorrhage, which sometimes requires urgent surgical intervention for vital indications. The first signs of cervical rupture often appear already during labor in the form of slight bleeding, which after the birth of the fetus takes the form of significant hemorrhage. In differential diagnosis, a characteristic feature of hemorrhage due to rupture of the uterus, as opposed to hemorrhages in uterine atony and remnants of the placenta or membranes, is the continuing hemorrhage despite satisfactory contraction of the uterus. In individual cases, where the rupture, despite its extent, does not involve large vessels, the hemorrhage may stop spontaneously, and the rupture may remain unrecognized if the cervix was not examined with mirrors.
The prevention of cervical tears should mainly consist of avoiding forced dilation of the cervix, especially by instrumental means, and forced delivery in breech presentation by traction on the leg or by applying forceps when the cervix is not fully dilated: these interventions should be particularly avoided when the cervix is rigid and when there is significant development of the vascular system with a low-lying placenta. Therapy consists of hemostasis and suturing the wound edges of the cervix. The technique of the intervention consists of the following points: the vagina must be well opened with wide and long mirrors (obstetric), the anterior and posterior lips of the cervix are separately grasped with Muse forceps, and the cervix is pulled downward. The upper end of the tear is determined visually or with a finger in case of severe bleeding, and a suture is placed slightly above it, capturing the entire thickness of the cervix (Figure 91). If placing this suture presents technical difficulties, an additional pair of bullet forceps is applied to the wound edges of the cervix, which further lowers the cervix and thus makes the upper edge of the tear more accessible. After placing this main suture, which ensures hemostasis, a series of separate sutures are applied, which bring the wound edges of the cervix together. In tears extending above the attachment of the cervix to the vagina, where there is already disruption of the fornices and even the parametrium, stopping bleeding may present considerable difficulties. In such cases, placing sutures requires great care both in terms of the possibility of accidentally ligating the ureter and of creating dead space with sometimes extensive hematoma formation, which can even reach the area of the kidneys. The most important conditions for successful suture placement are good exposure of the operative field and proper assistance. In individual cases where time needs to be gained, temporary application of a Momburg tourniquet and placement of clamps on the parametrium according to Henkel's method are indicated (cave! - avoid catching the ureters). In tears of the fornices penetrating the parametrium and giving parenchymatous bleeding, tight tamponade with leaving the tampon in place for 24 hours cannot be excluded. In vital indications, when it is impossible to achieve hemostasis from the vaginal side, it may become necessary to perform an extirpation of the uterus through the abdominal cavity. According to their nature, tears are divided into: 1) incomplete tears of the cervix, limited to the mucous and submucous layers of the cervix; 2) complete tears of the cervix, penetrating the entire thickness of the cervix uteri; 3) tears of the cervix uteri proper; 4) tears of the cervix uteri with disruption of the integrity of the fornices and parametrium. All these tears
Figure 91. Suturing a tear of the cervix (Zweifel).
Figure 92. Circular avulsion of the cervix. (no-Futh'y.)
have a longitudinal direction and begin at the external os. In rare cases, cervical tears have an atypical character; these should include central tear and circular avulsion of the cervix. Central tear of the cervix occurs under the same conditions as central tear of the perineum. The tears in this case occur through a central tear of the posterior wall of the cervix, and the tear does not reach the external os. The etiological factor for this rare type of tear is mainly the rigidity of the cervix in the area of the external os, observed in infantilism, severe ap-tef leXIo, elongatio colli in elderly primiparas, scarred processes of the cervix (e.g., after amputation of the cervix), etc. During vigorous labor activity, due to excessive stretching of the external os, the posterior wall is excessively stretched, thinned out, and ultimately gives way to a central tear. Circular avulsion of the cervix, in which the lower portion of the cervix is separated in the form of a ring, occurs under the same conditions as central tear of the posterior wall of the cervix uteri (Fig. 92). This form most commonly occurs in elderly primiparas with an unyielding external os and spatial discrepancies between the presenting part and the pelvic ring, which together create favorable conditions for circular crushing of the cervix, ultimately leading to complete avulsion of its lower portion. Tears of the uterus. There are two theories of the mechanism of uterine rupture: the theory of Bandl-Freund (Bandl, H. W. Freund) and the theory of Verbov. Bandl distinguishes two parts of the birth canal (see above). During the process of labor, the active part - the fundus and body of the uterus - is increasingly pushed upward by the head and body of the fetus, which creates increasingly marked stretching of the passive segment - the lower segment. The stretching and thinning take on an even more pronounced character in cases where, due to disproportion between the pelvis and the presenting part, the moment of entrapment of the lower part of the cervix between the head and the pelvis occurs, resulting in fixation of the lower segment of the cervix and its inability to move upward over the head. Under these conditions, the thinning and stretching of the lower segment become maximal. The thinning of this segment becomes even more significant when there is incompetence of the ligamentous apparatus of the uterus and the abdominal press; as a result, the fundus and body of the uterus move upward, the uterus elongates, the lower segment is further stretched and thinned, and in the presence of vigorous tetanic labor activity, this case ends in uterine rupture. Where the cervix has been pushed upward over the head, the rupture is localized in the area of the cervix or even the upper part of the vagina (Fig. 93). Verbov's theory explains the rupture not by stretching of the lower segment (which by no means constitutes a passive part according to this theory), but mainly by the pathological changes in the uterine wall that cause its greater fragility and vulnerability. At present, the mechanism of uterine rupture can hardly be explained exclusively by one or the other theory: cases where rupture occurs during pregnancy outside any labor activity speak against the exclusive importance of the Bandl-Freund theory, and cases where the most careful microscopic examination in the area of uterine rupture gave
no grounds to assume any changes in the histological picture of the uterine wall.
Etiology. Thus, the most important factors contributing to uterine rupture should be considered excessive overstretching of the lower segment and to some degree loss of elasticity of the lower segment on the basis of various pathological changes in the uterine wall. Etiological factors for excessive stretching of the lower segment and cervix are all those conditions that create spatial discrepancies between the presenting part and the pelvis, and other obstacles to the normal act of labor. These should include: 1) from the mother's side-narrowing of the pelvis, pendulous abdomen, stenosis and atresia of the soft birth canal, tumors located in the pelvis; 2) from the fetus-excessive size, fetal malformation, hydrocephalus, incorrect insertion of the head, transverse and oblique positions of the fetus; 3) from the egg-hydramnios. Etiological factors for loss of elasticity of the uterine wall are all kinds of degenerative, inflammatory processes and scars in the uterus (especially after previous cesarean sections), thinning of the uterine walls at the site of placental attachment and destructive growth of chorionic villi, infantilism of the uterus with insufficient development of muscular tissue in it, syphilis. The symptom complex of threatening rupture is almost or completely absent in a number of cases, and rupture occurs suddenly and is already established as a completed fact. The symptoms of threatening rupture are most pronounced where there is overstretching of the lower segment. In the presence of amniotic fluid, there is no immediate danger of rupture. After the waters break, the absence of progressive movement of the presenting part in the presence of vigorous labor activity requires the physician to carefully determine the nature of the existing obstacle. Here should be considered: the possibility of a narrow pelvis, abnormal fetal positions, excessive size of the fetus, hydrocephalus, malformation, pendulous abdomen, tumors, etc. At the same time, the anamnesis of the patient should be studied with the utmost care in terms of factors that could cause pathological changes in the uterine wall itself. All pathological factors of previous labor deserve special attention, in particular the course of labor and the postpartum period, and the use of various operative interventions (cesarean section, perforation of the uterus, application of forceps, manual separation of the placenta, prolonged labor, febrile course of the postpartum period, etc.). All these factors require double attention, especially if there are symptoms of overstretching of the lower segment, which Freud attributes to the following signs: 1) the contraction groove is already between the symphysis and navel or even higher; 2) the conspicuous oblique position of the uterus (deviation to the right); 3) marked tension of the round ligaments, especially the left; 4) violent contractions; 5) severe pain and tension in the lower abdomen; 6) edema of the incarcerated part of the cervix; 7) presence of a cephalic tumor with a remaining free sacral cavity. The symptom complex of completed rupture is determined, according to Freud, by the following signs: 1) sudden cessation of the previously violent labor activity; in incomplete rupture, a gradual fading of it is often observed; 2) pain at rupture, which often coincides with the cessation of labor activity; sometimes pain may be absent; 3) shock, in contrast to the first two signs, is a constant symptom, at least in complete rupture; 4) changes in the general condition and behavior of the parturient; 5) external and internal bleeding, the intensity of which depends on the degree of violation of the integrity of the vessels and on the presence of conditions facilitating tamponade by the fetus; accordingly, acute anemia or a transient state of collapse develops; 6) changes in the abdomen; when the fetus exits the uterine cavity, parts of the fetus can be clearly palpated next to the uterus located to the side, having the size of an adult head; in the case when the fetus remains in the uterine cavity, the presenting part, which was previously tightly pressed against the pelvis, becomes extremely mobile; 7) in incomplete ruptures, a rapidly developing hematoma often develops next to the uterus, and when the presenting part is displaced upward, external bleeding intensifies; 8) the placenta is retained. Therapy of threatening and completed rupture. Threatening rupture requires immediate termination of labor. Under clinical conditions, cesarean section may be indicated (see). In choosing the operative intervention, the interests of the mother should take precedence over the interests of the fetus. Therefore, destructive operations on the fetus, such as perforation of the head in cephalic presentation, decapitation, embryotomy in neglected transverse positions, which in many cases represent a less risky and more careful form of delivery, must be fully justified under clinical conditions. On the contrary, application of forceps and version operation are absolutely contraindicated interventions. In completed rupture, the parturient should be operated on immediately, since operative intervention provides better guarantees against bleeding and further infection. The method of choice should be laparotomy, in which, depending on the peculiarities of the case, either total extirpation or supravaginal amputation of the uterus is performed. Removal of the uterus per vaginam is largely inferior to laparotomy, the advantage of which is the possibility of careful hemostasis and comprehensive assessment of the nature of the injury. Suturing the rupture (unless it is minor and linear) is not indicated. An important condition for the outcome of the intervention is its timely performance. According to Klin's statistics, those operated on within the first 2 hours had 29% mortality, while those operated on later had 56%. Under the conditions of district work in completed rupture, the patient should be urgently transferred to a surgical hospital with maximum care. In the absence of conditions for laparotomy, the parturient should be immediately delivered by destructive operations on the fetus. In case of complication of rupture with bleeding, tamponade is indicated as a measure that allows time to gain for the transport of the patient for radical therapy-performed with counter-pressure on the uterus from the side of the external abdominal coverings. As a measure of the same order, Momburg's tourniquet is indicated. Types of ruptures. Ruptures can be complete and incomplete, i.e., penetrating through the entire thickness of the wall or only through part of it. The latter ruptures, i.e., incomplete ones, can be external, when the rupture goes from outside to inside, or internal, when the rupture begins from the side of the uterine mucosa; ruptures can be traumatic or spontaneous-the latter are most common (80%-Ledovsky, Mikhailov). Ruptures are most often localized in the area of the lower segment. Ruptures are observed in 0.016%-0.2%, i.e., 1 rupture per 500-6,000 births (Leopold, Bandl, Koblanck). Ruptures are most common in multiparas (85%). Ruptures of the perineum. Despite protection of the perineum during labor, ruptures of it are a fairly common phenomenon. According to Mikhailov's combined statistics, they occur in 6.36% of all labors, but in reality they are observed more often, as many ruptures are not registered. Relatively rarely they are observed in multiparas, much more often in primiparas and especially often in elderly primiparas. Operative interventions associated with forced delivery create particularly favorable conditions for ruptures. There are three degrees of ruptures: 1st degree, when the posterior commissure ruptures, and the rupture, being about 2 cm in length, reaches the middle of the perineum; 2nd degree, when the rupture extends to the sphincter, and 3rd degree, when the rupture involves the sphincter and even a section of the rectum. As a rare form, the so-called central rupture of the perineum is also observed, in which the posterior commissure and anus remain undamaged, and ruptures form in the center of the perineum. Etiological and contributing factors for rupture are: peculiarities of the anatomical structure of the perineum (high perineum, narrow and low pubic arch), insufficient elasticity of the perineum (in elderly primiparas), excessive stretching of it by a large presenting part, especially the head in extension, rapid delivery, especially associated with operative procedures.-Symptoms come down to an acute burning sensation of pain during rupture, the appearance of more or less significant bleeding, often already noted during the crowning of the head. Subsequently, in case of 3rd degree rupture, incontinence of gas and feces occurs.-Prevention consists in proper protection of the perineum during labor, in delivering the head in flexion, preventing rapid crowning of the head; when a rupture is impending, with the aim of replacing a lacerated wound with an incised one, episiotomy is indicated (see).
Figure 94. Suturing
Figure 95. Suturing of perineal rupture
perineal rupture. (According to J. Witridge
style. (According to J. Witridge Williams).
Williams).
the rational application of an additional buried suture. An important condition for the correct suturing of second-degree tears is the approximation of the levator ani muscle legs, which is achieved by placing two separate buried catgut sutures on them. In third-degree tears, the essential condition is the careful restoration of the integrity of the sphincter and rectum. The suturing is performed as shown in Fig. 96. Separate buried sutures are placed on the edges of the torn rectum and sphincter, then a separate or continuous buried suture on the perineum with mandatory inclusion of the levator ani muscle legs, and finally the perineum coaptation is performed with separate silk sutures or simply with Michel clips. In addition to perineal tears as such, more or less deep vaginal tears are often observed, which also require careful suturing to prevent healing by second intention and the formation of deep scars later on.-Particular attention should be paid to tears in the area of the clitoris, which occur very rarely but sometimes cause profuse bleeding. The application of sutures in these tears is not always appropriate, as
Figure 96. Suturing of a third-degree perineal tear: I-suturing of the rectum and sphincter; II-deep sutures; III-perineal coaptation with Michel clips.
each puncture sometimes creates a new source of bleeding. In these cases, tight tamponation of the tear area should be attempted. Bladder tears are observed mainly during operative delivery and most frequently during pelvotomy (see) and the application of high forceps. In addition to traumatic bladder tears associated with one or another operative intervention, bladder tears are observed with uterine ruptures. Bladder tears may either open into the abdominal cavity (intraperitoneal), be located extraperitoneally, or extend toward the vagina.-Therapy in the first case, i.e., with intraperitoneal ruptures, requires laparotomy and suturing of the tear from the abdominal cavity side. In significant extraperitoneal ruptures, it is most advantageous to expose the bladder between the ends of the symphysis in order to directly apply a suture to the site of rupture (Latzko W., J. Schiffmann). Finally, with ruptures penetrating into the vagina, one can either immediately apply sutures from the vaginal side or later operate on them as fistulas. In all cases, insertion of a catheter demeure is required, which with minor damage may already lead to complete recovery on its own. The outcome largely depends on the presence of concomitant infection.-Rectal rupture is usually observed with extensive perineal tears, in which the integrity of the sphincter and lower part of the rectum is violated (see above). Injuries and ruptures of the pelvic bony ring. In connection with pregnancy, the pelvic joints undergo loosening and edematous infiltration, as a result of which they have greater mobility and at the same time less strength. Even Phenomenon pointed out that predisposing factors to injuries of the pubic joint are pathological changes exceeding the norm observed in it during pregnancy. In connection with this, ruptures of the pubic and sacroiliac joints and fractures of bones are possible. Rupture of the symphysis during childbirth is not an exceptional rarity. In most cases, rupture of the symphysis is observed when forceps are applied, in the presence of a discrepancy between the presenting part and the bony ring, especially when under these conditions horizontal traction is performed prematurely with forced extraction of the head. Rupture of the symphysis can also occur with spontaneous R. (on symphysis ruptures see Pubic joint). Injuries to the chest, ribs are extremely rare; they occur during the expulsion period and are caused by the efforts and tension observed during this stage of labor. They usually heal spontaneously, but sometimes suppuration may occur. The therapy for a recognized chest injury should consist in the immediate termination of R., and subsequently-in the usual therapy and immobilization of the chest.
Arkhangelsky. XXI. Effect of labor on the organism of the woman. Due to the expulsion of the fetus, the exclusion of placental circulation, and the removal of the placenta, sudden changes occur in the woman's circulation and blood composition, alongside sharp changes of the reverse order in the metabolism and vital functions of the organism (see Puerperium - physiology). The act of labor itself, associated with strong mental and physical shock due not so much to severe as to prolonged and repetitive pain, exceptional physical exertion, and sometimes significant blood loss, places great demands on the woman's organism and harbors significant dangers. However, by virtue of a number of adaptations developed over many periods of human development as the most perfect species of animal organism, the act of labor as trauma usually does not leave behind significant and prolonged harmful consequences. On the contrary, labor along with pregnancy is the impetus through which a woman achieves the highest point of her development and turns into a mother-woman. At the same time, both the psyche of the woman and her external appearance change. The woman flourishes. Despite the mental and physical trauma, labor generally has a beneficial effect on the woman's organism. Women who have given birth look younger in appearance than nulliparous women (Bublichenko, Nadezhdin). True, this takes place up to 4 labors. After numerous and frequently successive labors, women, on the contrary, look older than their age. The harmful consequences of labor as trauma in such a highly differentiated species on the zoological scale as man in the overwhelming majority stem from pathological complications. In addition to the pathological deviations from normal labor described above, the act of labor to one degree or another can affect the nervous system of the woman, both central and peripheral, as well as the state of the birth canal. Postpartum paralyses and neuralgias. As a result of birth trauma, the following may develop: 1) psychoses, 2) paralyses and neuralgias. Aside from psychoses developing in the postpartum period (see Puerperium - postpartum psychoses), during labor itself sometimes (relatively rarely) transient mental disorders are observed, expressed in hallucinatory delirium, compulsive acts (suicide attempts, infanticide), in an excited or depressed state. These mental disorders bear the character of an affect and pass quickly upon the termination of labor or in the first days after labor. At the same time, there may be a fever with severe chills. The appearance of protein in the urine has been observed (Sigwart). Such mental disorders are often the occasion for forensic medical investigation. - Paralyses can be cerebral (cerebral and spinal) and peripheral. In rare cases, cerebral paralyses can occur without any patho-anatomical changes - hysterical paralyses. They appear without any painful signs and disappear quickly (Fürth). Despite the young age of women in labor, paralyses can occur due to cerebral hemorrhages as a result of sharp increases in blood pressure, especially in eclampsia. According to the data of the Central Scientific Research Institute of Obstetrics and Gynecology, there were 20 fatal hemorrhages per 74,750 admissions, which constitutes 1 apoplexy per 3,738 women in labor. Cerebral hemorrhages can also occur during pregnancy and in the postpartum period. Predisposing causes are constitutional features of the vascular system, alteration and degeneration of vascular walls on the basis of septic infection, early sclerosis of vessels, nephritis, and other incidental diseases. The onset of apoplexy may be preceded by heralds, chiefly headache, then tinnitus, insomnia. Often apoplexy leads to death during labor, in the nearest hours or days after labor. Some of the paralyses may depend on localized cerebral edema in eclampsia. In rare cases, albuminuric amaurosis may appear. Cerebral paralyses occur comparatively rarely as a result of the embolism of small emboli into the brain through a patent foramen ovale in septic endocarditis and thrombophlebitis, as well as due to progressive thrombosis of cerebral vessels. The prognosis is most unfavorable in view of the presence of septic bacteria in the emboli and thrombi. As for spinal cord damage, in difficult labors with surgical interventions caused by the need for urgent delivery in connection with albuminuria and eclampsia, hemorrhages into the substance of the spinal cord may occur. Labor and the puerperium apparently do not affect the course of such diseases as tabes dorsalis. Cases have been described where multiple sclerosis and myelitis developed in the postpartum period. As an etiological factor, neuropathologists put forward the formation of toxic substances during pregnancy and in the postpartum period. Cases are known when myelitis improved and passed after the termination of pregnancy in the postpartum period, and appeared again during a new pregnancy. It is possible that in such cases the cause of myelitis was puerperal infection. Transient paralyses of spinal origin can occur as a result of severe postpartum hemorrhages and the application of Momburg's tourniquet. Lesions of the peripheral nervous system can be in the form of paralyses and neuralgias. Aside from paralyses of myopathic origin (in osteomalacia), lesions of the peripheral nervous system can develop as a result of true nerve inflammation. These include: 1) postpartum neuritis of traumatic origin, 2) neuritis developing as a result of inflammatory processes in the pelvis, 3) neuritis of toxemic character as a result of puerperal infection. Traumatic neuritis of the lumbar and sacral plexuses rarely develops in labor without surgical intervention (when the head presses strongly and long on the pelvic nerves). More often, traumatic neuritis develops after surgical aids (forceps), when injuries are inflicted quickly with a forcibly guided head or the ends of the forceps. When the head is high, the trunks of the lumbosacral nerve and the obturator nerve crossing the linea iliopectinea are injured. Together with the lumbosacral trunk, the upper and lower gluteal nerves emerge. The femoral nerve is affected less, since it passes deeper. Thus, in accordance with topographical and anatomical relationships, pressure paralysis is most strongly expressed in the region of the sciatic nerve and the peroneal nerve, although paralyses are also encountered in the region of the tibial nerve. The symptoms of traumatic postpartum neuritis vary, ranging from more or less pronounced pains that spread to the lower extremities and pass in the first days of the postpartum period or last several weeks, to paresthesias and paralyses. The prognosis is the more serious, the more pronounced the signs and the more extensive the lesion area. Neuritis due to inflammatory processes in the pelvis develops either through the direct transition of the inflammatory process to the nerve trunks (purulent infiltration of the neurilemma) or the compression of them by inflammatory tumors and infiltrates. With the resorption of exudates, the signs of neuritis also gradually pass. Neuritis of a toxemic character on the basis of puerperal infection is explained by the action of toxins produced by bacteria, by virtue of the fact that certain poisons have an affinity for certain nerves - typical diphtheria, lead paralyses (Möbius). Characteristic of postpartum infection appears to be the preferential lesion of the median and ulnar nerves, although the lesion of others is also observed. For the treatment of paralyses and neuralgias, see Neuralgia, Neuritis, Paralyses, pareses. The prognosis is mostly good. Postpartum hematomas are formed comparatively rarely: according to Sutugin - 1 : 3,285, according to Dmitriev - 1 : 2,464, according to Winkel and Beckmann - 1 : 1,690. According to the data of the Central Scientific Research Institute of Obstetrics and Gynecology over 25 years, 23 hematomas were observed out of 44,879 labors, i.e., 1 : 1,951. Bar divides postpartum hematomas into 3 groups in relation to the levator ani muscles: 1) lower, or vulvar hematomas, 2) middle, or vaginal, in the vaginal part of this muscle, and 3) upper, or pelveoperitoneal, located above the levator ani muscles. From the point of view of etiology and clinic, their division by topography, location in relation to the pelvic fascia into: 1) infrafascial, located below the pelvic fascia, and 2) suprafascial, above it, is of essential importance. The latter, according to their origin, Beckmann divides into primary, or true blood tumors, and secondary ones resulting from small incomplete tears of the cervix. As etiological factors in the origin of hematomas, pathological changes in the vascular walls, vascular sclerosis, heart defects, congenital insufficiency of the vascular system, cavernous dilations of veins, aneurysms of branches of the uterine artery, malnutrition, and changes in the vascular walls depending on general diseases (nephritis, hemorrhagic diathesis) are pointed out.
General predisposing factors are pregnancy and labor, which in themselves are associated with significant blood stasis in the venous system of the small pelvis, with an increase in blood pressure, and with the compression of the inferior vena cava by the head. In particular, postpartum hematomas are observed with narrow and flat pelves, after operative aids ( forceps, rotations, expression of the placenta according to Credé), but they frequently occur also after labors without intervention and even independently of pregnancy and labor, for example after accidental contusions of the genital organs and during intercourse. According to the data of the Central Research Institute of Obstetrics and Gynecology (TSNIAGI), hematomas develop more often on the left side. On this basis, Moshkov believes that the asymmetrical development of the lower cardinal veins, with a lag of the right-sided ones in the postnatal life of a woman, predisposes to the origin of hematomas on the left side. The volume of postpartum hematomas ranges from the size of a chicken egg in the vulva to a child's head in the parametrium. Postpartum hematomas are formed mostly during labor or in the first hours of the postpartum period. The exact determination of the moment of their formation is difficult, because the pains at this time are mixed with labor pains. Hematomas of the external genital parts are easily determined upon inspection, vaginal ones upon examination or inspection with specula. Large suprafascial hematomas can give symptoms of internal hemorrhage and are determined by palpation from the outside or by bimanual examination, which is prompted by sharp pains, often accompanying the formation of hematomas, and signs of internal hemorrhage. Postpartum hematomas, if the integrity of the wall is violated, can cause severe hemorrhage. Closed hematomas either resorb or can become infected and putridly disintegrate. A suprafascial hematoma can simulate parametritis (Bublichenko). The outcome of hematomas is the more unfavorable, the higher they are located relative to the birth canal. A comparatively high percentage of mortality in old statistics (about 20%) must be attributed to infection. At present, the prognosis for this complication is much more favorable than before. Most obstetricians do not recommend opening hematomas shortly after their formation, excluding cases when they form before labor and impede delivery. Ice and pressure are usually recommended (colpeurynter for vaginal hematomas), followed by resorptive treatment. Hematomas that have undergone putrid decomposition are subject to opening. However, according to the material of TNIAGI, out of 23 cases of hematomas, in 5 cases the hematomas were emptied by incision and re-closed with sutures, which led to a significant reduction in the treatment period. In 4 cases, hematomas after incision were drained. - Injuries of the bony ring of the pelvis, soft birth canals - see above.
L. Bublichenko. XXII. Fetal birth trauma. Fetus
as an object of labor, passing through the birth canal, experiences pressure on individual parts of its body. In most cases, this pressure is compensated by the elasticity of the tissues of the fetus itself and passes without harm to the presentation. In those cases when there is a discrepancy between the pressure forces from the side of the soft and hard parts of the birth canal and the elasticity of the fetal tissues, the danger of violating the integrity of the tissues of the latter arises. The circumstances contributing to the occurrence of fetal birth trauma are on the part of the mother: rigidity of the uterine os, moderately narrowed pelvic dimensions; on the part of the fetus: prematurity of the latter, breech presentation, and others. The fact that not only the pressure forces on the fetus from the maternal tissues play a role in the etiology of the occurrence of birth trauma, but also the degree of maturity of the fetal tissues, is convincingly proved by the fact of a greater frequency of fetal tissue damage in premature infants compared to full-term ones. Operative aid is a factor that significantly increases the danger of fetal trauma. Full-term spontaneous labors give only 10% of stillbirths and mortality in the first days of life (out of the total number of stillbirths and mortality in this category), where the cause of death is associated with birth trauma. The specific weight of the latter, both absolutely and relatively, exceeds the above-mentioned percentage several times in cases of labor with operative interventions. For a description of birth injuries of newborns, see Newborn, Cephalhematoma. The question of the significance of birth trauma in the future pathology of the child and adult is currently not yet resolved and constitutes the subject of complex studies by an obstetrician, pediatrician, and neuropathologist. The problem of preventing fetal birth trauma depends not so much on the therapeutic measures of the obstetrician, but stems from the entire organization of obstetric care, measures to reduce prematurity (the main source of fetal birth trauma), reduce pathological lesion rates (prevention of a narrow pelvis), and thereby reduce the frequency of vaginal delivery operations by increasing spontaneous labors. A measure capable in certain cases of preventing fetal birth trauma is perineotomy in primiparas with breech presentations, especially in elderly primiparas - from 36 years of age and above. - Asphyxia of newborns - see Asphyxia. I. Feigel. XXIII. Artificial premature labor (partus arte praematurus). The excitation, induction, or "opening" of premature labors is called the artificial termination of pregnancy at such times when the fetus is already viable (after 28 weeks). The termination of pregnancy pursues the goal of preventing danger threatening the mother, the fetus, or both together. In cases where the excitation of artificial premature labors is performed exclusively according to indications from the fetus (e.g., at certain degrees of pelvic narrowing in order to obtain a live fetus), they should be undertaken only at the 34th-36th week of pregnancy, because fetuses born earlier than the 33rd week, although viable, are in the overwhelming majority imperfect and often die in the very first days of life. The methods of inducing artificial premature labors are extremely diverse, and in general terms they can be divided into methods: 1) mechanical, striving to induce labor activity by irritation of the inner surface of the uterus or in a reflex way, and 2) pharmacological, pursuing the goal of affecting the muscular motor of the uterus by the introduction of certain medicinal substances. Of the very numerous mechanical methods, many are currently not used at all in clinical practice and have only historical significance. Thus, the excitation of artificial premature labors by galvanic (Schreiber, 1843) and inductive (Hoenig, 1857) current (recommended in its time by Lichkus in 1886, Mironov in 1901, and others), separation of the fetal membranes in the lower pole of the ovum (Hamilton, 1800; Tarnier, 1862), vaginal tamponade (Scholler, 1841), hot vaginal douches (Kiwisch, 1846), douches with carbon dioxide (Scanzoni, 1856), irritation of the mammary glands (blisters, mustard plasters - Friederichs, 1839; dry cupping - Scanzoni, 1853, etc.), uterine massage according to Outrepont (d'Outrepont, 1822) or Ritgen (Ritgen) with simultaneous irritation of the cervix and general hot baths (Gardien, 1807), etc., have been completely abandoned. Part of these methods have been abandoned due to their ineffectiveness, extremely slow action, the appearance of new, more perfect and reliable methods, while another part (e.g., tamponade) also in view of unsafety in the sense of infection. Most modern obstetricians treat these methods negatively, and among them Hauch (1931) considers many of them incorrect and extremely dangerous. It is necessary, however, to point out that very recently (1932) some German obstetricians (Hellendal) again recommend hot vaginal douches according to Kiwisch in combination with Stein's method (Stein) (see below); at the same time, they point out the need for careful use of quinine (danger to the fetus), and in order to avoid a harmful effect on the fetal heart, the woman should be given 20 drops of cardiazol with each dose of quinine. It is hardly to be hoped, however, that Kiwisch's method even in a modified form will find many followers.
Figure 97. Sterile bougie for introduction in artificial premature labor.
Of other mechanical methods, which are predominantly methods of forced delivery (see Accouchement force) [introduction of bougies into the uterine cavity (between the uterine wall and fetal membranes - Krause's method, 1856) (Fig. 97 and 98), infusion into the uterine cavity (also between the uterine wall and fetal membranes - Cohen's method, 1846) of various kinds of liquids (tar water - Cohen, glycerin - Pelzer, NaCl solution - Mironov) with

Figure 99. Manual dilatation of the os during labor.
the aid of special tubes (tin - Cohen, silver - Krassovsky, elastic - Lazarevich) or a simple Esmarch mug (Kufferath), introduction of rubber balloons, puncture of the fetal membranes, manual or mechanical dilatation of the cervix (Bossi, Mensinga, etc.)], find application in modern
Figure 100. Manual dilatation of the cervix. Bimanual dilatation of the os during labor.
In clinical practice only the puncture of the fetal membranes, met-reiz (see), and manual dilation of the cervix or in older modifications (see Accouchement force) or by the most recent method of Delmas (see Delmas method). Although the insertion of bougies, the injection of fluids into the uterine cavity, and are recommended by some authors (e.g. Mironov, 1927, strongly recommends repeated injections of a 5% sterile solution of table salt - 400.0-600.0), however, this can hardly be agreed with, since there are quite convincing clinical data showing that both the use of bougies and the introduction of fluids into the uterine cavity are methods not only of little effect, unreliable, extremely slow-acting, but also far from safe. According to many (e.g. Stoeckel) they should
Figure 101. Two-handed dilation.
Figure 102. Two-handed dilation. be completely abandoned, and in his textbook on obstetrics Stoeckel does not even stop to consider these methods. This is confirmed by reports of complications observed when bougies are introduced. Rhenter (1922) in 153 cases observed hemorrhage in 15, 4 times quite severe, in 49 cases it was necessary to introduce several bougies (up to nine), while the duration of labor on average was from 38 to 71 hours, reaching in individual cases even up to 12 days. The method of Krause has been condemned by many before 3, outer diameter 17 mm), attached to a wooden pole. The use of the apparatus

Figure 103. One-handed dilation.

Figure 104. Notched thimble for artificial rupture of the fetal membranes. is not complicated, the introduction of the balloon is carried out according to the usual principles and with all the precautions taken in general during met-reiz (see). Into the burette is poured 160 g of a 2% solution of boric acid, colored with eosin (the burette is placed 40 cm above the bed). The beginning of oscillations of the liquid in the burette indicates the beginning of uterine contractions, which at first are insignificant, but subsequently acquire a rhythmic character. The pressure of the liquid in the rubber balloon is controlled and regulated by raising and lowering the burette (Areshchev on the basis of 15 cases of Sobestiansky and 53 of his own comes to the conclusion that this apparatus is extremely simple to use and that it gives, without violating the 'anatomical integrity and relationship of pelvic organs', quite satisfactory results). Artificial premature labor can also be performed by the classical cesarean section or vaginalis anterior du-stertomy; these operations take place in those cases where along with the necessity of interrupting pregnancy it is important to have immediate, rapid delivery and to protect the woman from a number of reflex irritations that may have a harmful effect, associated with forced methods of artificial induction of labor (e.g. severe general diseases, nephropathies and nephroses of pregnancy, eclampsism, eclampsia, etc.). The medicinal substances used for inducing artificial premature labor are few; at present they are usually not applied in isolation, but their introduction is combined with one or other mechanical means (e.g. puncture of the fetal sac, met-reiz). The ergot, cobert's cornutine, hydrastine, pilocarpin hydrochloride, etc., recommended in the 19th century by some obstetricians, are now abandoned by all, since test observations with them showed not only their unreliability but also their unsafety for both mother and fetus. Of medicinal substances, at present quinine (per os, subcutaneously) is used alone or in combination with pituitrin. Some obstetricians use the combined method proposed in 1913 by Watson (ol. Ricini, Chinin, Pituitrin and repeated enemas at intervals of an hour or more) with various modifications. Watson in 1922 published 195 cases and notes 90% positive results (but infant mortality is still, as in Scott's statistics, quite high, namely 5%). All these methods, however, are not used at all by many schools; their application (on the advice of Vernon Bayley) in placenta praevia marginalis et lateralis, in severe albuminuria and threatening eclampsia is hardly advisable at all.-The indications for inducing artificial premature labor may be from the fetus or the mother. Thus, they are used by some schools in narrow pelvis (see Narrow pelvis, therapy of narrow pelvis), in postmaturity, habitual death of the fetus, in acute polyhydramnios, in placenta previa, and in various diseases both not depending on pregnancy (e.g. heart defects, chronic nephritis, etc.) and directly related to it (toxemias of pregnancy).
s. sepitsky.
Related articles
Mentioned in
Cite this page
“Breech Presentation.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/breech-presentation/