Umbilical Cord
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
The umbilical cord is a cord connecting the navel of the fetus to the placenta, containing vessels that serve the purposes of nutrition and respiration of the fetus. It develops from the abdominal stalk and contains remnants of the allantois and yolk duct.
Encyclopedia article (1928–1936)
UMBILICAL CORD (funiculus umbilicalis), synonym pupochtnyy kanatik, represents a cord connecting the navel of the fetus with the placenta and containing vessels which serve the purposes of nutrition and respiration of the fetus (umbilical vessels-2 arteries and 1 vein), as well as remnants of the allantois and yolk duct. Embryology of the umbilical cord. The origin of the umbilical cord in the embryo begins at the time when, due to the development of the amniotic cavity, the embryo separates from the egg membranes, remaining in connection with them only by means of the abdominal stalk (see Embryo); in the latter are placed the yolk duct (see Intestine, development of) and the developing allantois (see), enclosed in a mass of gelatinous embryonic tissue. The amniotic membrane begins from the skin of the fetus on its abdominal surface in the place where the lateral parts of the abdominal wall, bending outward, transform into a tube for the formation of the abdominal stalk; here the water membrane, stretched by the fluid accumulating in it, covers the organs emerging from the abdominal cavity, the yolk duct and allantois, compresses them together with the gelatinous embryonic tissue into a common cord and passes to the inner surface of the chorionic sac. The formation of the cord proceeds progressively in both directions-toward the fetus, where with the completion of the development of the abdominal wall it ends with the formation of the navel, and toward the villous membrane, where the amnion accompanies the umbilical cord to the place where the placenta subsequently forms. The allantois as a hollow organ (urinary bladder) begins to disappear already from the 2nd month of embryonic life; remain its vessels-2 arteries and 2 veins; the latter subsequently merge into one, while the arteries are limited only by an anastomosis which they form before entering the placenta. With the establishment of placental circulation, the yolk duct with the yolk sac and yolk vessels (vasa omphalomesenterica) atrophies. Thus, in the umbilical cord only the former vessels of the allantois remain functioning, now greatly developing and receiving the name umbilical vessels. In the development of the latter, peculiar features are noted: first, a tendency to spiral growth is observed, sharply manifested in the arteries and less noticeable in the vein, where it is expressed by the appearance of grooves on the outer surface of this vessel and folds or valves (valvulae Hobokeni) on the inner; second, a more rapid growth of the arteries compared to the vein; as a result of these two properties, the arteries spiral around the vein, most often from left to right (counting from the embryo); spirals of the arteries begin to become noticeable from the 2nd month of embryonic life; their number can reach 40 or more (95-according to Meckel). The rapid growth of the arteries is also expressed by the development of coils (Fig. 1) and corkscrew twists, due to which nodular-like thickenings appear on the umbilical cord, bearing the name of false nodes (nodi arteriosi). Other false nodes of the umbilical cord are formed by varicose dilatations of the umbilical vein (nodi varicosi), as well as local accumulations of Wharton's jelly (nodi gelatinosi), which develops unevenly along the umbilical cord. False nodes should not be confused with true nodes, which form as a result of tying the umbilical cord (see below). In the further development of the umbilical cord, it is necessary to note the appearance of spiral twists of the entire cord, occurring due to the rotational movements of the fetus; they are observed in greater or lesser numbers, directed in one direction or another; they may sometimes be completely absent; they apparently arise at a time when the fetus is small and possesses considerable mobility. Structure of the umbilical cord. In its fully developed state, as we see it in the newborn, the umbilical cord represents a grayish-white cord with blood vessels visible through it in places; its length varies greatly in different cases, on average equaling 50-60 cm; the thickness of the umbilical cord also fluctuates, on average equaling the thickness of a finger (11-13 mm); it varies in different fetuses depending on the amount of Wharton's jelly (in this respect, thin umbilical cords are distinguished-about 14% of all cases, medium-75% and fat, or juicy-10-11%). The umbilical cords also differ in strength; they withstand a load of 3 to 12 kg, on average-up to 6 kg; the vessels possess the greatest strength, then the amnion and the end of Wharton's jelly, which easily tears when the umbilical cord is stretched. Starting from the navel of the fetus with a sharp transition of subcutaneous tissue into Wharton's jelly and the skin into the amnion, the umbilical cord ends on the placenta, attaching to it most often in the region of the center (central attachment-insertio centralis); the vessels of the umbilical cord immediately after attachment diverge over the placenta, penetrating it with their branches. Eccentric attachment of the umbilical cord (ins. excentrica) is also quite often observed; much less frequently the umbilical cord attaches at the very edge of the placenta (marginal attachment-ins. marginalis); in individual cases it does not reach the placenta, attaching at some distance from its edge to the membranes of the fetal sac (membranous, or membranous attachment, see Insertio velamentosa); sometimes the umbilical cord attaches to the placenta already being divided into 2 branches-ins. furcata. The amnion, passing from the placenta to the umbilical cord, forms on it the so-called caruncles-multiple formations arising due to the proliferation of epithelium with the oral
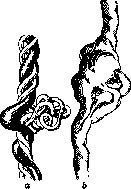
Figure 1. False nodes of the umbilical cord: a-nodus arteriosus; b-large varicose node of the umbilical vein. <
surface of the umbilical cord. The umbilical cord consists of: 1) blood vessels-2 arteries and 1 vein; 2) the remains of the allantois in the form of Wharton's jelly; 3) the amniotic membrane covering the cord. The arteries have a thicker wall than the vein; their lumen is narrower. The vein is wider and has a thinner wall. The arteries are twisted spirally around the vein. The umbilical cord is covered by the amniotic membrane, which forms caruncles on its surface. Wharton's jelly fills the space between the vessels and the amniotic membrane. It is a gelatinous substance containing mucin, fibroblasts, and collagen fibers. The umbilical cord varies in length and thickness depending on the amount of Wharton's jelly. The strength of the umbilical cord also varies, with the vessels being the strongest part. The attachment of the umbilical cord to the placenta can be central, eccentric, marginal, membranous, or bifid. The umbilical cord is a vital connection between the fetus and the placenta, providing oxygen and nutrients to the fetus and removing waste products.
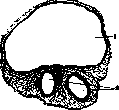
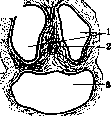
Figure 3. Cross section of the umbilical cord of mature fetuses: 1-v. umbilicalis; 2-aa. umbilicales.
Figure 4. Cross-section of the umbilical cord of mature fetuses: 1-arteries; 2-remnant of the allantois; 3-vein. The umbilical cord is covered by an amniotic sheath, tightly fused with the underlying tissue. The main tissue of it is Wharton's jelly (fig. 2). This tissue becomes denser toward the center of the cord, forming here a kind of core, sending processes to the umbilical vessels around them (chordae funiculi umbilicalis). 7& The vessels, besides the thickening of connective tissue around them, are also provided with a well-developed muscular membrane. Generally, the vessels of the umbilical cord have thicker walls than other vessels of the fetus's body. On a cross-section of the umbilical cord (fig. 3 and 4), with the help of a magnifying glass, one can find remnants of the allantois in the form of a cluster of cells, located in the middle between two arteries; closer to the navel this remnant lies more peripherally, then it shifts to the center and finally at the placental end approaches the vein; in places (not always and far from on all sections) remnants of the yolk duct are also found in the umbilical cord in the form of clumps of epithelial cells. The umbilical cord apparently does not possess its own vessels and nerves; there are also no true lymphatic vessels in it, but only juice canals, through which the nutrition of its tissues occurs. The function of the umbilical cord is the connection of the fetus with the sources of its nutrition and respiration-after the formation of the placenta, it falls exclusively on the umbilical vessels; along the arteries, the fetus's heart pumps the used blood into the placenta, and from the latter, oxidized, purified and enriched with nutrients blood returns to the fetus through the vein. The umbilical cord is an organ of exclusively intrauterine life and dies after the birth of the fetus. In the umbilical cord of a newborn child, the pulsation of the vessels is clearly felt, but after a short time the pulse in it begins to weaken and after 5-15 min. stops altogether. The weakening of the pulse wave comes from the placenta, and in the segment closest to the navel, the pulsation lasts the longest. The cessation of the activity of the umbilical vessels depends on two reasons: first, the respiratory movements of the child and the sucking force of his chest, in connection with the increase in the blood vessel area in the lungs, cause a decrease in blood pressure in the distant umbilical vessels; secondly, the umbilical vessels, very sensitive to cooling and stretching, strongly contract, and their strong musculature pushes the inner vascular membrane into the lumen of the vessel in scallops until the lumen is completely closed (Stravinsky). The umbilical cord has found technical application as a resorbable ligature material for replacing catgut. Bykov (1924) split the little-coiled umbilical cords lengthwise, threw out the vessels and prepared threads, which he successfully tested on animals and humans. Pathology of the umbilical cord. A. Irregularities of development. 1. Anomaly of length. Excessive length of the umbilical cord-up to 11/2-2 m and more-can be the cause of incorrect positions of it (entanglements, true knots, prolapses-see below), which in some cases can be the cause of death of the fetus. (Cases of L. up to 3 m-Schneider are described.) Excessive shortness of the umbilical cord-30 cm and less-usually does not cause complications until the expulsion of the fetus during labor; when the progressive movements of the fetus begin (in the second stage of labor), it can lead to their delay, to premature separation of the placenta, and with a close connection of the placenta with the uterus-to its inversion and finally to the rupture of the umbilical cord with the risk of fatal bleeding for the fetus. Such excessive shortness of the umbilical cord can be suspected during labor if the expulsion of the fetus is delayed without other visible apparent causes, under seemingly completely normal conditions; at this time signs of asphyxia of the fetus appear due to tension and compression of the umbilical vessels. Another sign of it may be the appearance of a cup-shaped depression on the wall of the uterus, in the place corresponding to the position of the placenta and the attachment of the umbilical cord (beginning inversion of the uterus). In all cases where shortness of the umbilical cord is suspected, it is recommended to accelerate the delivery (expulsion of the fetus by Kristeller's method, Verbov's bandage, forceps, etc.); a direct indication for intervention here is asphyxia of the fetus; one must keep in mind the possibility of intrauterine rupture of the umbilical cord and the need in such a case for its speedy ligation (see below). The shortness of the umbilical cord can reach its complete absence. In such cases we have to deal with the eversion of the fetus's internal organs, accompanied by other developmental defects; the fetus in this case turns out to be non-viable. 2. Umbilical hernia (hernia funiculi umbilicalis, syn. eventratio, exomphalos, omphalocele), sometimes incorrectly called umbilical hernia, represents underdevelopment of the anterior abdominal wall, the umbilical ring and the umbilical cord, arising in the early period of embryonic life (3rd-5th week) (fig. 5). In essence
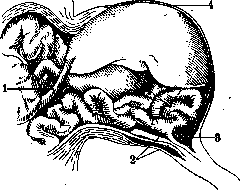
Figure 5. Umbilical hernia: 1-v. coeliaca; 2-umbilical arteries; 3-ductus mesentericus; 4-liver.
this is a malformation—not a hernia, since here there are no hernial gates (the matter did not go as far as the formation of the navel), nor the protrusion of the internal organs into these gates, since they do not protrude, but on the contrary, are retained in the cavity of the abdominal stalk, from which the umbilical cord is formed. Several forms of umbilical cord hernia are distinguished depending on the degree of development of the malformation: a) stalk-like hernias with a narrower neck, formed as if by an elongated navel, and a round tumor covered by the amnion and usually containing only the intestines; b) hernias with a broad base, where the underdevelopment of the abdominal wall is already clearly visible; the tumor has a dome-shaped form, with its broad side communicating with the abdominal cavity, and on the apex of its amniotal covering it bears the attachment of the umbilical cord; such hernias often contain the liver, more or less deformed, and other organs (stomach, spleen); these two forms bear the predominant name of umbilical cord hernia; c) the third form is given the predominant name 'eventration'; the form of the tumor here is irregular, the walls of the abdomen are clearly defective, sometimes passing into the amnion already on the lateral parts of the abdomen; due to the underdevelopment of the diaphragm, such hernias may contain the heart; they are accompanied by numerous malformations in other parts of the body. The coverings of the hernial sac in umbilical cord hernia consist of the amnion and peritoneum, and in severe degrees of malformations—of only an avascular amnion, since the peritoneum, like the abdominal wall, also turns out to be underdeveloped; sometimes in the lateral parts of the sac it is possible to find embryonic rudiments of the abdominal muscles. The membranes in a healthy (non-inflamed) and fresh state are transparent, allowing the contents of the hernia to be seen. In 60% of cases there are only loops of intestines, in 25%—the liver, one or together with intestines, more rarely the stomach, heart, kidneys, uterus with ovaries are found. Among the accompanying malformations, the following should be noted: lordosis, curvatures and underdevelopment of the limbs, spina bifida, labium leporinum, extrophy of the bladder and other underdevelopments of the urogenital organs, amniotic adhesions, etc. Umbilical cord hernias occur in approximately 0.02% (1:5,000) of births, in boys almost one and a half times more often than in girls. Many theories have been put forward to explain the occurrence of umbilical cord hernias. Until the 19th century, they were explained by the mechanical squeezing out of the internal organs (Sandifort, 1799). Oken (1810) was the first to point to developmental delay, namely the insufficient retraction of intestinal loops into the abdominal cavity, and Meckel (1812)—to the underdevelopment of the abdominal coverings; Neugebauer (1850) introduced the element of underdevelopment of the intestinal ligaments; in Panum and Dareste (1892) the idea is first expressed of embryonic inflammation as the cause of many malformations, and Preobrazhensky (1900) to explain the genesis of umbilical cord hernias puts forward the idea of focal embryonic inflammation caused by toxic causes. The theories cited in their totality create a coherent doctrine of the genesis of this malformation, whereas other explanations (Scarpa, 1822—pulling out the internal organs by a too short or twisted umbilical cord; Simpson, 1839—fetal peritonitis and adhesions of the internal organs with the vaginal process of the umbilical cord; St. Hilaire, 1832—amniotic adhesions, Alfeld—persistence of the ductus omphalo-entericus, pulling the intestine into the umbilical cord; Aschoff—lordosis of the spine, etc.) proved to be either incorrect or applicable only to individual cases. Recognition of umbilical cord hernia before birth is difficult; it can be palpated during internal examination only when it is presenting, i.e., in the transverse position of the fetus; it has happened that the eviscerated intestine of the fetus (in case of intrauterine rupture of the hernial sac) was confused with the umbilical cord and even with the intestine of the mother herself, which had penetrated into the uterine cavity in what was apparently a rupture of the latter. Sometimes umbilical cord hernia can mechanically slow down the birth of the fetus by itself, due to its size or due to the associated shortness of the umbilical cord. At birth, the hernia threatens the fetus with rupture of the membranes with subsequent death from peritonitis or from internal bleeding on the basis of damage to the umbilical vessels, liver vessels, etc. Peritonitis occurs due to necrosis of the amniotal covering. From peritonitis, those newborns who cannot be helped surgically due to the extent of the defect or for other reasons usually die. Treatment. Only very few, small hernias can heal spontaneously, by scarring of the defect in the abdominal wall after the umbilical cord falls off. Other hernias, of small and medium size, can be cured by surgical means, with the reconstruction of the skin-muscular abdominal wall. In the literature, only about 200 cases of operation for umbilical cord hernia have been published with 67% recoveries. In these cases, mainly the radical operation was used—a circular incision through the intact skin, opening of the abdominal cavity, ligation of the umbilical vessels, freeing the organs from adhesions, reducing them, suturing the abdominal wall, as in ordinary laparotomy. In this way, hernias up to the size of two fists or the head of a newborn were operated on (Colley, Lindfors, etc.) with resection of the liver, Meckel's diverticulum, intestines, etc.; among the complications, asphyxia and colic should be noted when reducing the internal organs into a narrow abdominal cavity, due to compression of the diaphragm and pressure on the heart. Umbilical cord hernias in newborns should be operated on as soon as possible, before the onset of necrosis of the membranes. Among other surgical aids, the method of Olshausen, which does without opening the peritoneum, and the so-called subcutaneous ligature of Breus can be mentioned. The operation can be performed without anesthesia (newborns do not react to incisions with pain), chloroform was found necessary only for the reduction of the internal organs, to suppress the reflexes.
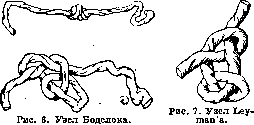
3. Velamentous attachment (see Insertio velamentosa) is observed in 0.5-1.0% of all births. In most cases, this anomaly proceeds without complications and is recognized only after birth. It acquires clinical significance in those cases when the vessels passing between the membranes are found in the lower pole of the egg, near the uterine os; then when the membranes rupture they can also easily rupture and cause fatal bleeding for the fetus; the fetus can be saved only by its rapid extraction. In velamentous attachment, sudden intrauterine ruptures of vessels have also been observed, apparently due to the shortness of the umbilical cord and movements of the fetus. B. Incorrect position of the umbilical cord. 1. Twists of the umbilical cord around the body, limbs, and neck of the fetus occur very often (in 25% of all births). In the vast majority of cases, due to the slipperiness of the umbilical cord and the protective role of Wharton's jelly, they remain harmless; however, where the twists are tight or multiple, the following can occur: a) tension and compression of the umbilical cord vessels, and during auscultation of the pregnant woman's abdomen, blowing sounds synchronous with the fetal heartbeat (umbilical cord noises) may be heard; b) difficulty in blood circulation in the constricted limbs, their retardation in development, formation of grooves and even complete separation of them (spontaneous amputation); c) difficulties in the expulsion of the fetus (especially in cases of twisting around the neck), similar to those observed with a short umbilical cord (see above) and with the same consequences; if difficulties occur when the head is not yet born, the threatening asphyxia of the fetus forces the use of forceps with the risk of rupturing the umbilical cord or turning the uterus inside out; when the head has already been born with the neck twisted by the umbilical cord and with difficulty in further expulsion of the fetus, it is recommended to slip the loop of the umbilical cord off the head or to cut it on the neck, clamping both ends with torsion forceps. 2. True knots (tying the umbilical cord in a knot, fig. 6 and 7) also occur due to the movements of the fetus, when it slips through a loop of the umbilical cord and then tightens it; for this to happen, the umbilical cord must be very long or the fetus must be small, which is why this complication occurs most often in early periods of pregnancy. The tightening knot gradually causes atrophy of Wharton's jelly at the points of pressure, obstruction of the umbilical vessels and death of the fetus. In later periods, knots can occur during childbirth itself, during the passage of the fetus through the loop of the umbilical cord and the birth canal; in these cases they usually do not lead to harmful consequences. An extremely rare phenomenon is knots in twins, when the umbilical cord of one fetus is wound or tied around that of the other (for this it is necessary that both fetuses have a common amniotic cavity, which occurs once in 30-35,000 births); in this case both fetuses usually die due to disruption of the placental circulation. 3. Presentations and prolapses of the umbilical cord. Normally, the umbilical cord, folded in a loop, is placed with its main mass on the abdominal side of the fetus, between its small parts. Being a long movable organ, it is easily displaced and if the lower segment of the uterus
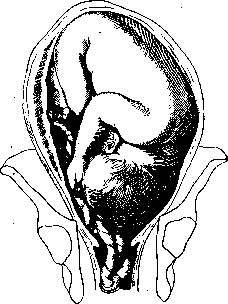
Fig. 8. Prolapse of the umbilical cord in cephalic presentation.
If, upon examination, we feel it in this position with the waters not yet discharged, then there is present a presentation of the umbilical cord; but if the sac is already gone, then we speak of prolapse of the umbilical cord (fig. 8). Not always does presentation of the umbilical cord, upon discharge of the waters, turn into its prolapse—the presenting part, inserting itself, may push the cord upward; sometimes, on the contrary, the displacement and prolapse of the loop of the cord occurs only at the moment of rupture of the sac, when suddenly flowing waters carry along with them the movable cord, before the large presenting part has had time to insert itself. Among the factors favorable to presentation and prolapse of the cord should be mentioned excessive length of the cord, large amount of amniotic fluid, distensibility of the lower segment of the uterus, multiple pregnancy, pendulous abdomen, narrow pelvis, asymmetrical pelvis, small volume of the presenting part (small head, breech, legs), transverse position, incorrect insertion of the head, and finally, low attachment of the placenta. Prolapse of the cord is observed in 0.6-1.0% of births; it is least common in cephalic presentations, more common in breech (10%), footling and transverse (20%), and occurs more easily in multiparas than in primiparas; it is relatively frequently observed in premature births. Completely indifferent for the mother, prolapse of the cord is extremely dangerous for the fetus, which during expulsion compresses the cord and dies from asphyxia. In spontaneous births, fetal mortality from this anomaly reaches 90%; often the fetus dies despite the assistance provided, and here the position and presentation of the fetus play an important role: in cephalic presentations 44% of fetuses die, in breech 33%, in transverse position 32%, in footling presentations 22% (Gusev). This abnormality is diagnosed only by internal examination, very easily when the fetal sac is absent and with some difficulties when the waters have not yet discharged; a valuable sign in this case is the palpable pulsation of the umbilical vessels. Before internal examination, suspicion of compression of the prolapsed cord may be aroused by the sudden onset of signs of fetal asphyxia during the entry of the presenting part into the pelvis in the presence of the aforementioned predisposing conditions. If such suspicion arises, one must immediately resort to internal examination, in which the presenting cord is most often found in the sacroiliac articulation area; generally the cord prolapses more easily through the lateral parts of the pelvis. The therapy of this anomaly has in view exclusively the interests of the fetus. If the latter is dead (absence of pulsation in the prolapsed cord between contractions, absence of fetal heartbeat), then labor is managed expectantly; but if the fetus is alive but is in immediate danger (the cord is compressed during contractions, there are present signs of fetal asphyxia), then prompt delivery is indicated, the form of which is determined by the conditions existing in this particular case. Specifically, with full dilation of the cervix, the fetus is immediately extracted by the method that is most suitable for the given position and given presenting part—with the head that has entered the pelvis, extraction is performed with forceps; with a still mobile head or transverse position—version to a footling extraction; with breech presentation—lowering of a foot with extraction or extraction by the breech; finally, in some cases the question of cesarean section may arise, if conditions are suitable and the mother absolutely desires to have a living child. With incomplete dilation of the cervical os, conditions are forcibly created for extraction of the fetus (by digital or instrumental dilation of the cervix or, under suitable conditions, vaginal section) and further management proceeds as indicated above. It goes without saying that for measures involving danger to the mother, her consent is required. In other cases, where the cord is not yet compressed, e.g., when the sac is still present and the fetus is not in immediate danger, one should, sparing the mother, adopt measures as gentle as possible toward her. Here the question first arises of replacing the prolapsed or presenting loop of the cord. This replacement, with the sac intact, sometimes succeeds by changing the position of the parturient (she assumes either a position with the pelvis elevated or the knee-chest position, or on the side opposite to that from which the cord prolapses); if this method does not succeed in replacing the cord, one can try to push it back by hand, and in order to avoid entrapment of the cord upon repeated prolapse, one should preserve the fetal sac as much as possible. A prolapsed umbilical cord is replaced with more difficulty than a presenting one. Its replacement is again performed directly by hand, preferably with the parturient's pelvis elevated, under anesthesia; the loop of the cord is pushed upward with the fingers behind the presenting part (head) and then one tries to fix the latter in the pelvis during a contraction or artificially, by pressing it into the pelvis, so that further prolapse does not occur. In former times, replacement of the prolapsed loop of the cord was recommended with the aid of instruments, so-called repositories—probes or sticks with a loop into which the cord was placed; fig. 9 shows such a Brown stick, with which the loop slips off upon reverse extraction of the instrument, freeing the cord, which remains in the uterine cavity; elastic repositories, e.g., Robertson's, were left in the uterus until the birth of the child; now, however, repositories are rarely used due to the comparative lack of success and danger of their application. It should be kept in mind that replacement of the cord very often fails (in three-quarters of cases); furthermore, frequently (in almost half of cases) the cord replaced by hand ceases to pulsate (spasm of the vessels due to cooling and irritation); finally, replacement with the hand introduced into the uterine cavity gives a considerable number of postpartum infections; therefore, if the conditions of labor are such that labor can be quickly completed without harm to the mother, it is completed without prior replacement of the cord. If replacement of the cord for some reason is undesirable or has failed, then the prolapsed cord is protected as long as possible from compression by the following methods: a) the parturient is placed in a suitable position (see above); b) external version to the breech is performed, which easily succeeds with a sufficient amount of fluid or in a premature fetus (this is often the case with cord prolapse); the resulting breech presentation provides more favorable conditions for the fetus.

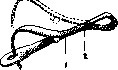
Fig. 9. Robertson's Brown's repositorory.
and for further manipulations when significant dilation of the cervix occurs; c) with sufficient dilation of the latter (2 fingers or more), a combined version can be performed, during which the umbilical cord is also repositioned using the methods indicated above; d) many authors recommend, in cases of small cervical dilation and ruptured membranes, inserting a metreurynter, which, by pushing the presenting part upward, does not allow it to press on the umbilical cord and at the same time facilitates the dilation of the cervical canal. With the indicated operative aids undertaken in the interest of the fetus, it is, however, far from always possible to save its life, and fetal mortality with them reaches 17-20%; therefore, in those cases where the mother is willing to take the risk for the sake of saving the child's life, the question of performing a Caesarean section—vaginal (Doederlein, Seitz, and others) or abdominal (in cases of a narrow pelvis—Lebedev, Shirshov, Serezhnikov-Pekarskaya, Couvelaire, Lepage, and others)—may arise even before urgent indications for terminating the labor occur. B. Diseases and other irregularities of the umbilical cord. 1. Torsion of the umbilical cord and obstruction of its vessels. Spiral torsions of the umbilical cord may sometimes be absent; in other cases, they may be very numerous (Hyrtl, for example, once counted up to 380). With a small amount of Wharton's jelly, such torsions can lead to compression of the umbilical vessels and death of the fetus. Obstruction of the umbilical vessels can arise, apart from torsion, also in certain diseases, for example, in syphilis, when obliterative processes are observed, sometimes leading to complete closure of the vascular lumen. 2. Neoplasms of the umbilical cord. During the short life of the umbilical cord, only a few forms of neoplasms, predominantly of embryonic origin, manage to develop in it. These include, for example, allantoic cysts with greenish-yellow contents consisting of secretions from the fetus's intestine and kidneys (Ahlfeld), and cysts of the bile duct (Ruge)—small formations (the size of a pinhead or larger) found on the periphery of the umbilical cord and filled with fatty-degenerated epithelial cells, detritus, and calcareous masses. Bidin described the only case of a teratoma of the umbilical cord in a full-term fetus; the tumor in this case consisted of several sections containing cavities lined with stratified squamous epithelium, blood clots, smooth muscle fibers, cartilage, bone, etc. Fava and Panciera described a cyst of the umbilical cord the size of a two-year-old child's head, lined internally with endothelium and containing clear fluid. It is also necessary to mention false cysts of the umbilical cord, resulting from the liquefaction of Wharton's jelly and having the appearance of small vesicles, which in exceptional cases reach the size of a chicken egg; inflammation of the umbilical vessels, edema of Wharton's jelly, and torsion of the umbilical cord play a role in their formation. Most tumors of the umbilical cord were found in premature (4-7-month) fetuses. False cysts of the umbilical cord may possibly be of postmortem origin. Tumors of the umbilical cord have no clinical significance. 3. Varicose veins of the umbilical cord are encountered quite often. Being expressed to an insignificant degree, they have no practical significance and do not cause any harm. In more pronounced cases, they can be the cause of intrauterine fetal death (due to rupture of a varicose node during pregnancy or labor). Hematoma of the umbilical cord is among the extremely rarely encountered complications. 4. Inflammatory diseases of the umbilical cord are encountered rarely. Most often they are observed in syphilis. They can lead to thrombosis of the umbilical vessels, which is often encountered in the umbilical cord of dead and macerated fetuses. 5. Ruptures of the umbilical cord. The umbilical cord can usually withstand the weight of the fetus, but with jolts and in certain pathological conditions of its own, it can rupture relatively easily; thus, for example, in the experiments of some researchers, it ruptured when a weight of 500 g suspended from its end was dropped from a height of one meter. Most often, the umbilical cord ruptures during labor in the mother's standing position, when the falling child tears it with its weight; however, ruptures of it are also frequently observed in the lying position of the parturient woman, during precipitous labor (in 20-30% of them), when the child is thrown by the last contraction some distance from the mother's genital parts. Furthermore, ruptures of the umbilical cord have been observed during normal labor in cases of its excessive shortness, during the release of nuchal cords, during accidental lifting of the parturient woman's pelvis while the fetus is not yet separated and the placenta has not yet been delivered, in cases of velamentous insertion of the umbilical cord, in insertio furcata, and during operations—version, forceps; in individual cases, finally, difficult-to-explain intrauterine ruptures of the umbilical cord have been described. Predisposing to ruptures are painful conditions of the umbilical cord, inflammatory infiltration, weak development of Wharton's jelly and its loose structure, varicose veins of the umbilical vessels, and their excessive tortuosity and thin-walled nature. Upon rupture, the umbilical cord stretches, the amnion tears; the vessels withstand the longest. The edge of the rupture is most often oblique, uneven, and jagged, which distinguishes it from an incision. In the majority of cases, the umbilical cord ruptures in its fetal segment, less often in the placental one, and even more rarely in the middle; sometimes (about 20% of cases) the umbilical cord is torn off at the very navel; there have been cases of rupture of the umbilical vessels even in the abdominal cavity of the fetus. Ruptures of the umbilical cord in the majority of cases bleed almost not at all, since the strong tension preceding the rupture causes contraction of the vessels, and the curling of the ruptured intima contributes even more to the closure of their lumen; nevertheless, significant, even fatal hemorrhages can sometimes take place here, especially when the rupture of the vessels occurs in the region of the navel itself or even inside the abdominal cavity. Cases of the latter kind, if only the diagnosis of the rupture was made in time, require immediate laparotomy for ligation of the vessels; if the umbilical cord has torn off at the very skin of the navel and the latter is bleeding, then the umbilical vessels are grasped and ligated in isolation; if it is impossible to grasp them, one has to suture the navel; in other cases, one proceeds with the umbilical cord in the usual manner, ligating it to avoid subsequent hemorrhages. Ruptures of the umbilical cord in cases of fetal death can have forensic medical significance (infanticide, leaving a newborn without assistance). Separation of the fetus and ligation of the umbilical cord. Mammalian animals separate the fetus after the birth of the placenta, gnawing through the umbilical cord with their teeth; predators eat the placenta, starting with the placenta; eating of the placenta has also been observed in non-predatory animals, for example, the horse; thus, separation of the fetus occurs in animals some time after birth. Primitive peoples bite off, tear, grind between stones, or burn through the umbilical cord, leaving a rather large umbilical remnant; separation of the fetus is performed by them also after the birth of the placenta—among some peoples only on the day after birth. All these methods, unconscious or empirical, tend to ensure the cessation of bleeding from the umbilical vessels for the newborn. But waiting too long contributes to the contamination of the umbilical cord and infection of the fetus, whereas too early can cause bleeding. Therefore, among the majority of civilized peoples, early separation of the fetus (before the delivery of the placenta) is practiced with ensuring hemostasis by ligation of the umbilical cord. At the same time, despite the simplicity of the named operation, there still exist various opinions regarding the method of separating the fetus and handling the umbilical remnant, in connection with which various methods of them are also practiced. The differences in these methods boil down mainly to the handling of the umbilical remnant and are expressed in techniques which can be divided into three main groups: 1) ligation of the umbilical cord, 2) crushing it with instruments, 3) leaving it unligated. Common moments in all methods are: a) waiting with manipulations until the complete cessation (or in any case significant weakening) of the pulsation of the umbilical cord and b) the final act of cutting with scissors. Waiting for the cessation of pulsation in the umbilical cord has the purpose not only of better hemostasis in the umbilical vessels but also of establishing equilibrium in the amount of blood between the fetus and the placenta. A newborn fetus, which has been subjected to significant compression in the birth canal, is anemic, and during the time of the continuing extrauterine pulsation of the umbilical cord, it receives from the placenta the so-called "reserve blood" in an amount from 50 to 200 g, which is far from indifferent for the economy of the newborn's organism. Furthermore, according to existing observations, the exsanguinated placenta separates better from the uterine wall. For cutting the umbilical cord, so-called "umbilical scissors" (fig. 10) are used; they are curved along the edge, with relatively long branches, with blunt, rounded ends so as not to injure the child during its accidental movements, and with not very sharp cutting edges: they must somewhat traumatize the cut umbilical vessels to cause the curling of the intima in them and better occlusion of the vascular lumen of the vessel.
Cutting of the umbilical cord is usually performed at a distance of 1.5 to 2 cm from the site of the ligature applied to the umbilical cord with forceps or similar; the umbilical remnant is bandaged to the abdomen of the newborn after preliminary treatment with drying or anti-putrefactive substances (Runge's mixture—potato flour with boric acid, gypsum according to Sutugin-Fagonsky, dermatol, salicylic acid, alcohol according to Ahlfeld, collodion and bismuth according to Rogak, etc.).
Ligation of the umbilical cord. The oldest and most common method of handling the umbilical cord is ligation with a strong linen tape, about 0.5 cm wide; it is preferred over a silk ligature, which easily cuts through the tissues of the umbilical cord. The tape is applied at a distance of 1.5–2 cm from the navel, i.e., as close to the latter as the thickness of the umbilical cord allows, so as not to cause irritation of the navel with the ligature. The knot of the tape must be tightened firmly, as it easily loosens on the yielding mucous tissue of the umbilical cord. In view of this, it is recommended to tighten the umbilical cord with two knots, specifically, having tied the tape with a surgical knot on one side, move its ends to the other side and tighten it there again with a double knot. It goes without saying that the ligation must be done with sterile material; the tape is boiled and stored in a sublimate solution until use. Despite careful ligation, cases of secondary hemorrhages from the umbilical vessels are still sometimes observed, hemorrhages that are all the more unpleasant because they are difficult to monitor; to avoid heat loss, newborns are usually well wrapped, and
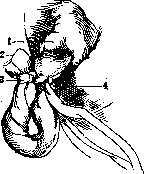
Figure 11. Reliable ligation of the umbilical remnant: 1—skin knot; 2—site of umbilical cord cutting; 3—first knot; 4—second knot.
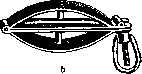
often it is discovered only after the child has already lost a significant amount of blood. True, fatal hemorrhages from the umbilical remnant are very rare (on the material of maternity hospitals, Kakushkin found 3 cases out of 220 thousand births), but even less significant blood losses cannot be considered indifferent for newborns. The causes of these hemorrhages, not to mention cases of poor ligation (done by the mother's own hands or unskilled people around her, or even intentionally performed by a weak-minded person for the purpose of infanticide, or finally, ligation for which poor, stretching material was used), are mostly irregularities in the structure of the umbilical cord, changes in its vessels due to inflammation, syphilis, as well as hemophilia, etc.; hemorrhages occur more easily in poorly breathing and asphyxiated children. The fear of secondary hemorrhages led to the use of double or two-stage ligation of the umbilical cord (Ahlfeld, Jaschke, Pfaundler, Bumm, Pinard (Fig. 11), whereby the latter is ligated first at a distance of a palm from the navel and cut, and then, after bathing, the ligated end of the umbilical cord is bent toward the navel and the tape is tied again with a knot near the skin navel; thus, the umbilical remnant remains hanging in the form of a loop. Hemostasis is excellent, but the long umbilical remnant, representing a significant mass of dead tissue, is disadvantageous in terms of facilitating infection. In general, with the tape method of ligation, some authors saw a certain chance for infection in the tape itself, which easily becomes moist and therefore hinders the drying (mummification) of the umbilical remnant. Therefore, proposals were made to ligate the umbilical cord with an elastic rubber cord (Budin, 1880), or to apply a tight rubber ring to the umbilical remnant (Lebedev, Kuzmin, 1898); with the latter method, the umbilical cord is first cut, and then a rubber ring is applied to it with the help of a special instrument, which lies almost at the skin navel (Fig. 12). Omphalotripsy. With the aim of possibly reducing the umbilical remnant and at the same time achieving good hemostasis, it was proposed to crush the umbilical cord with an angiotribe (e.g., Tuffier's device) or another strong instrument with strong clamping surfaces (omphalotribe). After grasping the umbilical cord, the instrument is fixed by an assistant, and the operator closes its branches using a lever or other device; during crushing, the traumatized intima folds and plugs the lumen of the vessel under the compressed area, which turns into a thin plate. Later, heavy instruments were replaced by lighter ones, of the forceps type, which could be left on the umbilical cord for 3–36 hours after clamping. Kakushkin (1905) proposed using ordinary Kocher forceps with cut-off teeth for omphalotripsy, applying them so that the rings were turned toward the child's chest, and Bar (Baar, 1907) designed a special instrument (Fig. 13), which now enjoys sufficient fame. In the vast majority of cases, it is sufficient to leave the instrument on for 3 hours; however, secondary hemorrhages were sometimes observed even 30–40 hours after the birth of the child. Recently, Dubinchik proposed a new clamp for the umbilical cord. The Dubinchik clamp has an ellipsoidal shape and consists of 2 arcuate flaps connected to each other by a hinge and clamped with the help of a folding screw (Fig. 14). On the inner surface of each flap, there is a narrow crossbar; on one crossbar, there is a depression, and on the other, corresponding to this depression, a protrusion. When both flaps are closed, the umbilical cord is compressed until the lumen of the umbilical vessels is completely closed. The clamp is light, portable, does not traumatize the delicate skin of the newborn, and does not injure the amniotic layer of the umbilical cord. The clamp is removed after 3–4 hours, after which the umbilical segment remains completely dry under a light, replaceable sterile dressing until it falls off. Clinical observations (Gok-Smrcek and Sarne) have shown the expediency of using this clamp in practice. Separation of the fetus without ligation of the umbilical cord. The negative aspects of the ligature method of caring for the umbilical cord—secondary hemorrhages due to loosening of the ligature, irritation of the navel caused by a foreign body, inflammation of the umbilical vessels, delay in the mummification of the umbilical remnant—led to the proposal to do without ligation of the umbilical cord altogether. The basis for this proposal was empirical observations, which pointed to the rarity of hemorrhages during ruptures of the umbilical cord, slipping of the ligature, etc., further—examples of animals and primitive peoples who do without ligation, and finally, familiarization with the physiological properties of the umbilical cord, namely the spontaneous cessation of blood circulation in it after the birth of the fetus. Non-ligation of the umbilical cord was first proposed at the beginning of the 18th century. With this method, the umbilical cord is cut no earlier than the complete cessation of pulsation in it (12–18 min.) at a distance of 4–4.5 cm from the navel (so that it could be ligated in case of immediate or secondary hemorrhage); if drops of blood appear after cutting, it is recommended to massage the umbilical remnant with pressing movements from the navel to the periphery; the infant remains under vigilant supervision for 2–3 hours. In 16 thousand births conducted in this way (Rakhmanov), the umbilical cord had to be ligated in 17% of cases, predominantly pathological ones (immaturity of the fetus, asphyxia, hemorrhage in the mother, which prevented waiting, etc.). This method, inconvenient due to the long waiting period and not giving confidence that everything has been done for hemostasis, either went out of use or appeared again; at the present time, it is almost nowhere applied. Among other methods of caring for the umbilical cord, one can mention cauterization of the umbilical remnant with heated forceps, burning off the umbilical cord with a Paquelin (Martin) (both methods require great caution due to the danger of burns to the fetus), and excision of the navel with subsequent suturing.
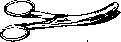

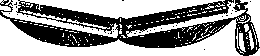
Related articles
Mentioned in
Cite this page
“Umbilical Cord.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/umbilical-cord/