Sacrum
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
An anatomical overview of the sacrum, its structure, variations, and clinical significance. This section covers its development, relations to the pelvic girdle, and associated pathologies including fractures, congenital anomalies like sacralization, and tumors.
Encyclopedia article (1928–1936)
SACRUM, together with the coccyx, constitutes the terminal part of the spine, which, in the form of a wedge, closes the pelvic ring posteriorly. In the vast majority of cases, the sacrum consists of 5 vertebrae, which are separated from each other only in youth, and in adults are fused together into one common mass. However, variations exist both in the direction of an increase in the number of vertebrae and in the direction of a decrease. An increase in the number of vertebrae making up the sacrum to six is more often observed in men (Braus). This increase can occur from the upper (anterior) end of the sacrum, when the lowest lumbar vertebra is partially or completely fused with the sacrum (sacralization); or

Figure 1. Sacrum from the front: 1- proc. articul. sup.; 2- for. sacral. ant. a numerical increase is noted from the caudal end of the sacrum. A sacrum made of four fused vertebrae is much less common. Quantitative and qualitative variations of the spine in the lumbosacral region often lead to trunk deformity (scoliosis). The vertebral bodies and lateral parts (rudiments of the ribs) of the sacrum, fusing together, decrease in size from top to bottom, which is why the sacrum has the shape of a triangle, the apex of which connects with the coccyx, and the base with the last lumbar vertebra (Figures 1 and 2). The lateral parts of the sacrum connect with the corresponding surfaces of the iliac bones via the facies articularis, forming the sacroiliac joints (Figure 3). The anterior surface of the sacrum, facing the pelvic cavity (facies pelvina), appears slightly curved, creating a larger volume to accommodate the pelvic organs. The four anterior sacral foramina (foramina sacralia ant.) on the anterior surface serve for the passage of large nerve plexuses. The upper end of the sacrum at the junction with LV, on the contrary, projects significantly forward in the form of a promontory (promontorium). The posterior convex surface of the sacrum (facies dorsalis) has a well-defined median sacral crest (crista sacralis media) in the middle, formed by the spinous processes, and two lateral crests (crista sacralis articularis), which represent fused articular processes. The superior processes (proc. articulares sup.) articulate with LV; the inferior ones—in a rudimentary form (cornu sacrale)—symmetrically limit the entrance to the sacral canal. The latter has a triangular shape and curves according to the curvature of the sacrum. The upper opening of the sacral canal, located at the base of the sacrum, serves as a direct continuation of the spinal canal. The lower opening (hiatus sacralis) is covered by the outer (periosteal) layer and the superficial posterior sacrococcygeal ligament (lig. sacrococcygeum post. superficiale). Due to the fact that the conus medullaris ends at the level of SII, below it, down to the hiatus sacralis, there remains a space of 6–9 cm, which is called the extradural or epidural cavity (cavum extradurale or epidurale). The opening closing the sacral canal from below can be of significant size, which depends on the non-fusion of the rudimentary arches of the sacral vertebrae.
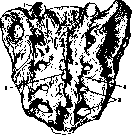
Figure 2. Sacrum from behind: 1- proc. artic. sup.; 2- crista sacr. med.; 3- for. sacr. post.; 4- crista sacr. artic.
Through the transversely running intervertebral (intersacral) foramina, the sacral canal communicates with the anterior and posterior sacral foramina, which serve for the passage of nerve trunks. Puncture through the hiatus sacralis is commonly used for the purpose of sacral anesthesia. The landmarks are the sacral cornua, which limit the lower opening of the canal on both sides. The injection is made in the middle with a needle, which is first positioned at an angle of 20° to the longitudinal line of the body, then advanced by 4–5 cm along the body line (Figure 4). The four openings located on both sides of the lateral sacral crest (foramina sacralia post.) serve for the passage of the posterior sacral nerves. A number of ligaments run from the anterior and posterior surfaces of the sacrum to the pelvic bones (lig. sacrotuberosum, sacrospinosum, sacroiliaca anteriora, sacroiliaca posterius longum et breve, etc.), which hold the bones making up the pelvic ring in a firm connection. Of the muscles, the piriformis and coccygeus (mm. piriformis and coccygeus) are connected to the inner surface of the sacrum; posteriorly, the sacrum is covered by the tendinous endings of the long muscles of the back (m. sacrospinalis). The synergistic action of individual muscle groups (back, abdominal, and gluteal) and the strength of the ligamentous apparatus hold the mobile part of the spine (above the sacrum) in a certain position relative to the sacrum, which is advantageous from the point of view of the mechanics and statics of the spine. The lower immobile part of the spine, including the sacrum and coccyx, is at a certain angle of inclination to the horizontal. This angle usually approaches 60° or 67°, according to Fick (inclinatio pelvis). In accordance with this angle, the physiological curves (lordosis and kyphosis) of various parts of the mobile part of the spine fluctuate (Figure 5). From the point of view of mechanics, the sacrum can be viewed as an object balancing on a transverse axis through the sacroiliac joints. The weight of the trunk presses the sacrum forward and downward. When the trunk is bent and a load is lifted simultaneously, the pressing force increases, resulting in excessive tension on the ligaments holding the sacroiliac joint. Under the influence of a sudden turn during excessive tension and chronic stretching of the ligamentous apparatus, a rotatory displacement can occur in the sacrum (for details, see Sacroiliac Joint). Fractures of the sacrum also occur in severe pelvic injuries. Fractures of the sacrum with a longitudinal fracture line have been observed, and this type of fracture by itself does not cause severe functional disorders, or causes
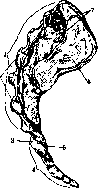
Figure 3. Lateral surface of the sacrum and coccyx: 1- sacrum; 2- crista sacr. med.; 3- cornu coccyg.; 4- os coccygis; 5- vertebra coccyg. I; 6- fac. auric.; 7- tuberositas.

them to a much lesser extent than, for example, fractures in the region of LV. Transverse fractures of the sacrum occur more often from direct application of force and are observed mostly below the sacroiliac joint. Of the congenital anomalies of skeletal development (dysplasia) of this part of the spine, besides the non-fusion of the posterior wall of the sacral canal, sacralization has practical significance, which can be in the form of a symmetrical connection of the transverse processes of LV with the sacrum, and then is less clinically apparent; if, however, one half is sacralized,
painful phenomena are more often observed. Not infrequently, a semblance of a joint develops between the transverse process of LV and the sacrum. Tumors of the sacral region and coccyx have a very diverse structure. In addition to pure forms of myelocystocele and myelomeningocele, teratomas and congenital lipomas are found here. Along with simple and complex dermoids, sarcomas and subcutaneous parasites presenting as a tumor are also observed. Tillmanns, out of 110 pelvic sarcomas, notes localization on the sacrum in 29 cases. More benign exostoses and enchondromas, often located on the border of the sacrum and ilium, have also been described. The sacrococcygeal region presents many interesting features in terms of embryogenesis and phylogenesis, and therefore tumors that are not usually observed elsewhere sometimes occur here. Such are, for example, chordomas arising from the chorda dorsalis. According to Coenen's classification, such tumors can be cranial, vertebral, and caudal. Caudal or sacrococcygeal chordomas can be presacral, retrosacral, and central sacral. Melnikov collected 36 cases of caudal chordomas in the literature, to which he added his own 37th case. Surgical intervention for tumors of the sacrum and sacrococcygeal region must be radical for most tumors, which tend to recur with palliative interventions,
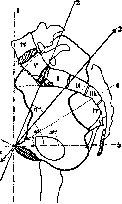
Figure 5. Diagram of inclination angles: 1- vertical line; b - horizontal line; 2- anatomical conjugate; 3- line of inclination of the iliac bone; 4 - normal conjugate.
giving an unfavorable prognosis. Radical removal of the tumor in most cases must be combined with resection of the coccyx and partial or complete resection of the sacrum. Among inflammatory diseases of the sacrum, tuberculous osteomyelitis is most frequently noted. - Osteomyelitis of the sacral bone, like other pelvic bones, proceeds severely, requires rapid recognition and radical intervention. Denier observed 3 cases, which ended in death with symptoms of general septicopyemia. Out of 8 cases, Klemm had 4 recoveries thanks to early and radical intervention. Tuberculous lesions of the sacrum proceed more slowly and favorably. An infiltrate often arises near the sacroiliac joint, but destruction involves a larger or smaller part of the sacrum. In this case, such severe disorders are not observed as in osteomyelitis: patients often continue to work for a long time. Abscesses arise almost exclusively on the posterior surface of the sacrum and extremely rarely break forward. Therapy, in contrast to osteomyelitis, should be conservative. Abscesses are punctured according to the type of cold abscesses. Fistulas heal persistently under the influence of heliotherapy. Systemic injections of a mixture of Calmette also have a favorable effect. Syphilitic lesions of the sacrum in the form of tertiary gummous osteitis are observed more rarely. In individual cases, along with specific treatment, removal of necrotic foci by surgical means is indicated. - The sacrum together with the coccyx is also an object of surgical intervention in diseases of pelvic organs, especially for access to the rectum. Such is, for example, the posterior approach according to Kraske. In recent years, anomalies of the spine and especially the 'transitional' fifth lumbar vertebra in combination with the sacrum have been thoroughly studied and explain the causes of many unclear 'lumbar pains', as well as the causes of deformity formation of the spine. In the study of spinal anomalies, scientists of the USSR also contributed a certain share of work, among which the works from Turner's clinic (N. I. Chirkin) and from Vreden's clinic (A. A. Kozlovsky) occupy a prominent place.
Related articles
Mentioned in
- Achondroplasia
- Asynclitic Presentation
- Bandages (a198)
- Bedsores
- Breech Presentation
- Center of Gravity
- Coccygodynia
- Coccyx
- Coitus
- Douglas Space
- Electrodiagnosis
- Gaffky and Haff Disease
- Gluteal Region
- Haematometra
- Hirsutism (hypertrichosis, hypertrichia, polytrichia,)
- Identification in Forensic Medicine
- Iliac Region
- Innominate Bone
- Leyden Type of Dystrophy
- Lordosis
Cite this page
“Sacrum.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/sacrum/