Scoliosis
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Soviet Great Medical Encyclopedia defines scoliosis as a lateral curvature of the spine and details its various forms, including congenital, rachitic, school, and occupational types. It discusses the etiology, mechanical development, and anatomical changes associated with the condition, such as torsion and rib deformation.
Encyclopedia article (1928–1936)
SCOLIOSIS (from the Greek skolios—crooked, a term introduced by Galen in the 2nd century), a lateral, or frontal, curvature of the spine. A very common deformity, especially in the past, before the popularization of methods of physical education for the rising generation. Thus, according to Hoffa, scoliosis accounts for 27.6% of all orthopedic ailments, according to Dollinger—27.9%, according to Fischer at the National Orthopedic Hospital in London—12%, and according to Tubby later, in the same hospital—8.1%. According to data from the Kazan Orthopedic Clinic for the period 1920–1930, severe forms of scoliosis were noted in 2.6%. The female sex is affected 3–6 times more often than the male. About 75% of all scoliosis cases occur between the ages of 5 and 15. Depending on the height of the spinal curvature, one distinguishes: cervical, cervicothoracic, thoracic, or dorsal, thoracolumbar, lumbar, and lumbosacral scoliosis. In addition to the indicated partial curvatures of the spine, complete, or total, scoliosis is encountered. Each of the listed forms can be left- or right-sided. When a frontal curvature of the spine is combined with a sagittal curvature, it is called kyphoscoliosis. Etiologically, congenital and acquired scoliosis are distinguished. A hereditary predisposition is noted, calculated at from 12% to 25% (Karewski, Eulenburg). Congenital scoliosis is encountered in approximately 5% of all
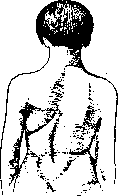
Figure 1. Congenital left-sided thoracolumbar scoliosis.
Scoliosis. The mechanism of its development lies in the underdevelopment of individual vertebrae (wedge shape, spina bifida) and some other skeletal anomalies (Sprengel's disease, cervical ribs). Congenital scoliosis, as a rule, is discovered only in the second decade of life, is localized most often in the lumbosacral, somewhat less often in the thoracolumbar, and even less often in the cervicothoracic region; it involves a small number of vertebrae, has a small arc of curvature, and is little inclined toward compensatory counter-curvatures and toward torsion, i.e., rotation of the spine along the vertical axis (Fig. 1). The overwhelming majority of scoliosis cases are of acquired origin: rachitic, school, occupational, functional, traumatic, cicatricial, paralytic, syringomyelic, and reflex-pain. The last three forms can be combined into a general group of neurogenic scoliosis. In first place are rachitic and school scoliosis. In practice, they are often inseparable from each other, since the mechanism of their development largely coincides. Rachitic scoliosis is encountered in no less than half of all cases of scoliosis. It is revealed at the age of 6 to 12 years, begins at the thoracic region, especially often from DXII, has a total character, leads to compensatory counter-curves, is accompanied by sharply expressed torsion, and is very inclined toward fixation (Fig. 2). School scoliosis is noted by various authors in 10–20–30% (Spitzy, Haglund, Schulthess) of all schoolchildren. In our Soviet schools, the number of scoliosis cases is about 10%. One of the main factors in the development of school scoliosis is the prolonged motionless sitting of children in school. The extensor muscles of the back, overfatigued by prolonged static tension, weaken, the child hunches (becomes kyphotic), overburdens the ligamentous apparatus of the spine, and instinctively finds an easier posture in an asymmetrical, slanting sitting position. With the passage of time, the posture becomes habitual. For scoliosis to develop, a lowered elastic resistance of the spinal skeleton itself, its rachitic state, is also necessary. Thus, school scoliosis develops under the influence of four interacting agents: chronic overstrain of the spinal musculature, habitual asymmetrical posture, rachitic plasticity of the spine, and the resistance force of the organism, consisting

Figure 2. Rachitic scoliosis of the thoracic region with a sharply expressed compensatory curvature of the cervicothoracic region.
in the potential energy reserve of the living tissues of the body. The severity of the scoliotic deformity depends on the degree to which the first three factors are expressed, and on the magnitude and moment of the transition of the organism's potential energy reserves into a kinetic state. In the early stages of school scoliosis, the spine is distinguished by its pliability, i.e., its pathological curvature is corrected at the moment of manual redressment or during vertical traction in a Glisson loop. But then, after several years, the lateral hump assumes an increasingly fixed character due to the nutritive shrinkage of the muscles of the concave half of the torso and persistent elastic changes in the ligamentous-capsular apparatus, as well as the deformation of the cartilaginous and bony tissues of the vertebrae themselves, presenting in this respect an analogy with the development of contractures. Figure 3 can serve as an illustration of school scoliosis. Occupational scoliosis is observed in teachers, persons of sedentary and clerical work, engravers, watchmakers, violinists, and representatives of many other professions. Here, as with school scoliosis, the basis also lies in a habitual asymmetrical posture with chronic unilateral overloading of the back muscles. The difference is that the deforming moments in occupational scoliosis develop in persons with already completed skeletal growth. Thanks to this, the resistance force of the tissues is greater, the curvature develops more slowly and does not reach such large dimensions as in school scoliosis. Functional scoliosis is the name given to those that develop due to the unequal length of the limbs, especially the lower ones, after unilateral amputation, after infantile paralysis that resulted in a lag in the growth of one leg or arm; after a leg fracture that healed with shortening of the bone; after contractures of the knee and hip joints, on the basis of congenital high standing of the scapula (Sprengel's disease). Traumatic scoliosis develops as a result of injuries to the spine and can be primary or secondary. Primary traumatic scoliosis arises immediately after gross anatomical injuries as a result of an unreduced dislocation or an improperly healed fracture of the vertebrae. Secondary traumatic scoliosis develops chronically on the basis of microanatomical changes in the internal structure of the spine, which disrupt the nutrition of the latter and lead to its secondary deformation. Cicatricial scoliosis represents the result of unilateral cicatricial contracture of the back tissues after burns or after severe purulent-inflammatory processes of the subcutaneous tissue and muscles. A special form of cicatricial scoliosis is observed after empyema of the thoracic cavity (retrecissement thoracique). Paralytic scoliosis develops predominantly as a result of infantile poliomyelitis; it has a total form,

Figure 3.
School scoliosis. It is accompanied by a decrease in the electrical excitability of the paralyzed muscles with normal skin sensitivity. Rarely, paralytic scoliosis is encountered due to progressive muscular atrophy and on the basis of hereditary Friedreich's ataxia. Syringomyelic scoliosis represents one of the firm and early symptoms of syringomyelia; it is localized in the cervicothoracic vertebrae and is of small size; it arises due to central disturbances of muscular coordination and trophic osteoporosis of the vertebrae. Reflex-pain scoliosis is observed as a symptom of unilateral painful processes with the most diverse localization: in sciatica, in inflammation of the sacroiliac joint, in rheumatic lumbago, in appendicitis, in renal and hepatic colic. Accordingly, one distinguishes scoliosis ischiadica, scoliosis sacro-iliitica, scol. lumbagica, scol. appendicitica, scol. nephritica, scol. hepatica. The anatomical changes of the spine in scoliosis consist of its lateral curvature and torsion, i.e., a spiral bend around the vertical axis like a grapevine. In this case, the apex of the wedge of the scoliotic vertebra looks toward the side of the concavity and somewhat posteriorly; the bony trabeculae of the spongy part of the vertebral body have the same oblique direction. The vertebral bodies turn with their anterior parts from the midline toward the side of the convexity, and the spinous processes toward the side of the concavity. The transverse processes of the vertebrae follow one another like the steps of a spiral staircase (Fig. 4). Increased load on the concave side of the spine causes here a plastic compaction of the bony trabecular structure and the layering of peripheral bony protrusions, which, in connection with the wedge-shaped atrophy of the intervertebral cartilages, leads to ankylosing synostosis of the vertebrae. The muscle-ligamentous apparatus on the convex side is stretched and weakened; on the concave side, it is shortened, scar-hardened, and rigid. The ribs are curved; on the convex side, they protrude in the form of a hump; the intervertebral spaces on this side are widened, while on the concave side, on the contrary, they are narrowed to the point that they overlap like tiles and compress the nerves passing there. In kyphoscoliosis, mainly rachitic, the thoracic cage often has a keel-like character (pectus carinatum). The disfigurement of the external form of the thoracic cage causes a corresponding displacement and disfigurement of the lungs and heart contained within it, which in turn reflects on their functional activity. Respiratory ventilation of the lungs
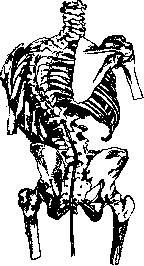
is weakened, in them catarrhal phenomena, emphysema, atelectasis easily develop. The heart is often dilated, hypertrophied. Bachmann, who investigated in this direction 154 cases of curvature of the spine, found in 87 cases (56.4%) hypertrophy and dilation of the right heart, in 27 (17.5%) such a lesion of the left heart, and in 40 cases (25.9%) a lesion of both halves of the heart.
The first symptom of the most common forms of S. (ricketic, school, and professional) is rapid fatigue of the back. To this is added a slight lateral curvature of the spine, especially noticeable by the end of the day. On the contrary, in the morning, when the muscles are fresh, the curvature may be completely absent. Later, pains appear, concentrated in the back or in the lumbar region, often radiating along the course of the intercostal nerves. With the years, the deformation progresses, becoming more and more fixed, so that in the end S. does not disappear even with forced attempts at correction. This moment corresponds to the rigid degeneration of the muscle-ligamentous apparatus and deforming changes in the skeleton of the spine, which is especially sharply expressed in the area of Dviii-Dx. The X-ray reveals torsion and wedge-shaped tilting of individual vertebrae, uneven density of the spongy structure, osteophyte growths. Simultaneously, compensatory counter-curvatures develop, the chest is deformed. Both halves of the shoulder girdle are set in an oblique plane: the shoulder and scapula of the convex side in S. of the thoracic department stand higher than on the concave side. Pathological disorders of respiratory and cardiac activity have been mentioned above. These disorders explain the fact that the average life expectancy of scoliotics does not exceed 40-50 years of age. The diagnosis of S. is based on the consideration of anamnestic data (age, profession, past illnesses), evaluation of clinical symptoms (fatigue of the back, pain, its localization, character), special examination of the spine with a scoliosisometer (see) and by the X-ray method. The prognosis is worst in ricketic, paralytic, as well as in all cases of old, fixed forms of S. in general. The most favorable prediction is for congenital and late-developing forms of professional S. Prevention of S. has exceptionally important significance, since it is much more effective than the treatment of this stubborn suffering. When the first signs of congenital S. are detected, the child should be provided with a physical culture regime that facilitates the work of the inadequate (convex) side of the spine: massage, mobile games, oblique sitting (on an inclined plane; in the simplest form - a book under one of the buttocks, corresponding to the convex half of lumbar S.). For ricketic weakening of the spinal column, several hours of special daily rest in the prone position, sun-air and salt baths, vitamin-rich food are indicated. The main preventive measures for school S. are: rational construction of school furniture, hourly physical culture minutes, and for younger children every half hour, based on the principle of unloading, balancing, and correcting movements; mobile games in the fresh air, swimming, rowing. The idea of harmonious development of the intellectual and physical forces of the child, implemented in our Union by the method of polytechnicalization of the school, has enormous importance for the prevention of S. and deformities of the body in general. The socio-prophylactic significance of the principles of Soviet protection and organization of labor is equally effective: general sanitary-hygienic norms of work premises, rationalization and mechanization of the most tiring production processes, wide coverage of workers with physical culture in everyday life and in production, one of the most vivid expressions of which (physical culture) is the preparation and passing of standards for the GTO badge (Ready for Labor and Defense).

The treatment of S. is mainly based on gymnastic exercises. They are divided into general mobilizing and specifically correcting exercises. Gymnastics is conducted 2-3 times a day for 5-10-15 minute sessions. The character of gymnastic exercises (gymnastic prescription) is extremely diverse depending on the form of scoliosis and individual properties of the patient (age, general state of health). Examples of general mobilizing exercises: 1. Standing position. Arms are extended upward along the head. Bending and straightening of the trunk in the hip joint, without bending the spine (fig. 5). 2. Standing position. Hands on the waist. Active upward extension of the trunk and return to the starting position (fig. 6). 3. Hanging position, holding with hands for the bar. Pulling up and lowering of the trunk. Examples of correcting exercises for total left-sided scoliosis. 1. Standing position. Right arm is raised upward along the head. Left arm is bent at the elbow and rests with the palm on the side, closer to the back. Bending of the trunk to the left and slightly backward, then to the starting position. 2. Lying position on the stomach. Right arm is extended upward along the head. Left arm grasps the lower part of the left shin, bent at the knee. Extension of the spine and return to the starting position. 3. Standing position with the left side to a Lorenz roller. The roller is grasped with the left hand. Right arm is raised upward, bent at the elbow. Bending to the left side slightly backward, strongly pressing against the roller (fig. 7). Examples of correcting exercises for right-sided dorsal scoliosis with compensatory counter-curvature of the lumbar region. 1. Standing position. A long stick is brought behind the back. Its upper end is grasped by the right hand over the right shoulder, and the lower end of the stick is grasped by the bent elbow of the left hand. Pressing with the stick against the dorsal convexity, extend the trunk backward and to the right. 2. Lying position on the stomach. Right arm grasps the lower part of the left shin, bent at the knee. Left arm is extended upward, along the head. Extension of the trunk.

Figure 5. General mobilizing exercise.
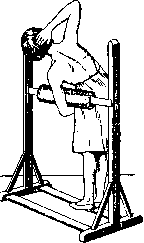
Figure 6. Active extension of the spine.
In addition to free gymnastic exercises, medical-gymnastic exercises on various apparatuses are sometimes used: vertical or on an inclined plane traction in Glisson's loop, lateral traction, exercises on Zander's, Krukenberg's and other apparatuses. Parallel to gymnastic exercises, massage is applied 1-2 times a day for 5-10 minutes: stroking, rubbing, kneading and tapping of the muscles, and for paralytic S. also vibration and faradization. The greatest attention is paid to the massage of the convex side of the back.
In severe cases of deformity, supportive or even corrective corsets are prescribed. The purpose of the former is to provide static support to the muscles until they become strong enough to do without the support of the apparatus. The supportive corset is removable, as it is only worn during the day for sedentary work. Corrective, otherwise called redressing or, as they are also called, 'active' corsets, are made of non-removable plaster. The 'active' Hoffa-Schede corset covers the pelvis and the convex side of the rib hump, which is maximally bent in the opposite direction at the time of application; sometimes the plaster also includes the thigh on the concave side. The corrective Abbott corset is also applied in the corrected position of the spine in a special frame or with the patient on all fours. The arm corresponding to the dropped shoulder is raised up, resting on a bench; the main scoliotic curvature is bent in the opposite direction. Several pieces of dense felt are applied to the scoliotically concave side of the back. Then a circular plaster cast is applied, covering the entire torso. The armpit on the concave side should be strongly supported by the corset, while the armpit on the convex side should be free, for which the edge of the plaster is cut low here. Two windows are cut in the back: opposite the concavity and opposite the convexity of S. From the window of the concave side, one layer of felt is removed and transferred to the opposite side, where it is slipped under the edge of the window. The large window corresponds to the scoliotically concave side, which here, as it should be, is hypercorrected. Finally, the windows are closed with a circular soft bandage. The transfer of subsequent layers of felt from the concave side to the convex side is done every 5-6 days. Such treatment lasts for several weeks and even months, sometimes requiring a change of corset, until stable hypercorrection is achieved. The external wedge effect of 'active' corsets is often good, but unfortunately short-lived, because this method only mechanically stretches the tissues in the desired direction, without fixing the results by strengthening the muscles and corresponding anatomical changes in the skeleton itself (Port). Therefore, in recent years, the results of preliminary correction of S. have been increasingly fixed by subsequent surgical fixation of the spine according to the Albee or Henle-Whitman method. The first method consists of autoplastically transplanting a plate of the tibia into the split of the spinous processes of the vertebrae; the second method consists of transplanting two plates, preferably a split rib, on the sides of the vertebrae, into the groove between the transverse and spinous processes, under the thickness of the muscular ridge located here. After the operation, a plaster fixing corset is applied for several months. Success, i.e., reduction and arrest of the scoliotic curvature, reaches 70% in the hands of some authors (Hibbs, Risser, Ferguson). Attempts to correct the hump by resection of the convex side (Volkmann, Hoffa and others) or by incision and excision of the concave side, expecting its subsequent straightening (Hoessly, Lange, Sauerbruch), proved to be life-threatening and ineffective. In individual cases, satisfactory results were obtained from muscle-plastic operations. Thus, Krukenberg achieved mobilization and partial correction of lumbar S. by incising the shortened aponeurosis of the t. obliq. abdom. ext. and incising the t. psoas on the concave side.
Related articles
Mentioned in
Cite this page
“Scoliosis.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/scoliosis/