Kyphosis (or round)
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
A historical overview of kyphosis (round back) from the early 20th century, detailing its etiology, clinical presentation, and treatment methods. The article discusses various forms including rachitic, senile, and hereditary types, emphasizing corrective gymnastics and orthopedic supports.
Encyclopedia article (1928–1936)
KYPHOSIS, or round back (kyphosis, dorsum rotundum), is characterized by a uniform curvature, usually of the thoracic spine, with a posterior convexity and a slight compensatory lumbar lordosis (Figures 1 and 2). Antero-posterior curvature (kyphosis) in its pure form is encountered less frequently than lateral curvature. Haglund, in a study of 1,599 children in Stockholm, found kyphosis in 170 cases. Groenberg, in a study of 8,250 children, established spinal curvature in the antero-posterior direction 715 times, with kyphosis proper established in 66.9%, kypho-lordosis in 20.8%, and lordosis in 12.3%. In the etiology and pathogenesis of kyphosis, one must consider congenital peculiarities of the spinal structure; muscle weakness of the entire torso and specifically the dorsal muscles; and a prolonged flexed position of the spine caused by profession (e.g., in miners) or the school environment of a growing organism. Jones points to a possible etiological factor expressed in the overloading of the shoulders by inappropriate clothing. Rickets, which underlies a number of spinal deformations, can be a cause of kyphosis. Rachitic kyphosis in children is often well-pronounced in the lower thoracic and lumbar regions of the spine. Such kyphosis is characterized by a uniform curvature of the spine that easily disappears when lying on the stomach or—in more severe cases—upon stretching.
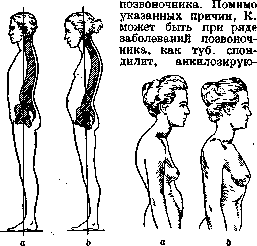
Figure 1.
Figure 2.
Figure 1. a—physiological kyphosis in a normal standing position; b—kyphosis in round back. Figure 2. Round back: a—before treatment; b—after treatment. Kyphosis is also observed in: ankylosing spondylitis (see Spondylitis)—spondylosis rhizomelica; in traumatic injuries of the spine; osteitis deformans; in paralysis of the dorsal muscles as a residuum of poliomyelitis anterior (see Infantile Paralysis); and in rarer cases—in muscular dystrophy. Hysterical kyphosis has also been noted. Strongly pronounced forms of kyphosis of the upper thoracic part are observed in so-called hypertrophic pulmonary emphysema. Finally, kyphosis of the thoracic spine can be combined with a tuberculous process in the lungs, predominantly with the cirrhotic form. Senile kyphosis stands apart. To a certain extent, it represents a physiological phenomenon and is caused by senile degeneration and shrinkage of the intervertebral cartilages, as well as loss of muscle tone. Due to the loss of elasticity of the intervertebral cartilages, the vertebral bodies come into close contact, which disrupts the functional curves of the spine characteristic of youth. Finally, there are reliable data on genotypic kyphosis, and a striking similarity in the form of spinal deformity within the same family should be noted. Thus, Aschner and Engelmann observed a pair of identical 9-year-old twins with a completely identical form of kyphosis. From the genealogies described in the literature, Paulsen's case should be mentioned, where kyphosis was noted in 5 generations as a clearly expressed dominant trait. The same occurred in Levit's case (3 generations, Figure 3). The clinical picture of kyphosis is quite characteristic. In addition to the antero-posterior curvature of the spine, predominantly in the thoracic region, there is a simultaneous flattening of the chest, displacement of both shoulders anteriorly from the frontal plane; compensatory lordosis in the lower spine, a pear-shaped abdomen with relaxed walls, and ptosis. It should be noted, however, that although ptosis is sometimes combined with
round back,
it is far from always manifested by
any painful symptoms.
The incorrect position of the torso,
caused by kyphosis and compensatory lordosis, does not remain without influence
on the internal organs of the chest and on the general state of the growing organism. General muscle weakness, a sunken chest, insufficient lung ventilation, and a protruding abdomen characterize juvenile kyphosis. The etiology, mechanism of formation, and therapy of kypho-scoliosis have much in common with scoliosis (see). In the treatment of true kyphosis of non-inflammatory origin, predominantly in childhood and adolescence, one should distinguish between 1) mobile kyphosis and 2) fixed kyphosis. If the kyphosis easily yields to passive correction, satisfactory results can be achieved through systematic gymnastics, massage of the dorsal muscles, and training the patient's will toward a correct torso position. Gymnastic exercises should be aimed at developing the muscles of the back and abdomen. Simultaneously, other harmful factors (inappropriate clothing, unfavorable school conditions, etc.) must be eliminated. Fixed forms of kyphosis must first be converted into mobile ones through cautious and skillful gymnastic exercises. Active corrective exercises with a bolster placed under the area of the kyphosis are good for this purpose. Lorenz's apparatus ("Lorenzsches Wolm") is also very convenient for corrective gymnastics. In fixed kyphosis, especially of the thoracic region, tuberculosis must be carefully excluded before resorting to mobilization. After good correction is achieved, in individual cases, the wearing of upright-holding corsets is indicated, built according to the type of Nyrop's upright-holder. If there is simultaneously a pear-shaped sagging abdomen with stretched abdominal walls, a corset that also encompasses the abdominal walls is indicated. Therapy for other types of kyphosis should be applied depending on the underlying condition (see Spondylitis).
Figure 3. Kyphosis, Levit's case (diagram). Symbols: square—kyphosis (male); circle—kyphosis (female); dot inside—personally examined by the author.
Related articles
Mentioned in
Cite this page
“Kyphosis (or round).” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/kyphosis/