Lumbar Region
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
The lumbar region forms part of the posterior abdominal wall, bounded by the XII rib, iliac crest, posterior axillary line, and spinous processes of LII-V vertebrae. It contains important muscles, fascia, and structures including the erector trunci, quadratus lumborum, and psoas major muscles.
Encyclopedia article (1928–1936)
LUMBAR REGION (regio lumbalis) constitutes part of the posterior abdominal wall. Its boundaries: superiorly - the XII rib, inferiorly - the iliac crest, laterally - the posterior axillary line, and medially - the line of the spinous processes of LII-V vertebrae. More precisely, the superior boundary is defined by a line drawn from the spinous process of LII through the free end of the XII rib to the outer third of the XI rib, the lateral vertical line extending from the end of the XI rib to its intersection with crista ilii, and the inferior line extending from the point just mentioned to spina iliaca post. sup. The boundary between the lumbar regions on either side is the spinal groove, which is more pronounced the more developed the long back muscles are. In its depth in the upper portion, the spinous processes can be palpated; in the lower portion, palpation reveals the posterior surface of the sacrum and the iliac crests with spina iliaca post. sup. The long muscles (m. erector trunci, s. sacro-spinalis) are usually well contoured, but the other muscles of the area are noticeable only with well-developed musculature. Under the skin, which gathers here into folds well and stretches when the spine is bent, is a layer of usually satisfactorily developed adipose tissue. The deeper-lying superficial fascia separates the subcutaneous tissue layer from the adipose mass (massa adiposa lumbo-glutaealis), which is most pronounced in the lower portion. Behind this last layer is
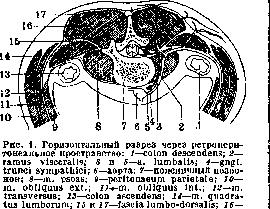
m. erector trunci. (According to Corning.)
the broad muscle of the back (m. latissimus dorsi), the fibers of which, directed obliquely from below and behind upward and forward, originate from the proc. spinosi of the five or six lower thoracic vertebrae, all lumbar vertebrae, crista sacralis media, from the superficial lamella of fascia lumbo-dorsalis, from the posterior third of the iliac crest (labium externum) and from the 3-4 lower ribs, and attach to crista tuberculi minoris humeri. The listed layers are common to the entire lumbar region. The outer edge of the powerful m. sacro-spinalis divides the area into two parts: medial and lateral. In the medial part, the next layer is fascia, s. aponeurosis lumbo-dorsalis Virchowi, a strong fibrous formation consisting of three lamellae and originating from the spinous processes of the thoracic, lumbar, and partly sacral vertebrae and from the iliac crest. From it, m. obliquus abdom. int. and m. transvers. abdominis partially originate (see Abdominal Wall). The lamellae form a sheath for the muscles, with the deep lamella separating the ventral musculature (m. quadratus lumborum, m. ilio-psoas) from the dorsal (m. erector trunci and m. latissimus dorsi) (fig. 1). In the upper portion, this lamella is thickened and along the course between the XII (sometimes XI) rib and the transverse process of Li forms the ligament - lig. lumbo-costale, s. ilio-costale, s. arcus tendineus fasciae lumbo-dorsalis, s. retinaculum costae ultimae, s. lig. costo-transversale Henle. With a narrow thoracic cage, this ligament fixes the XII rib so much and hinders access to the kidney from behind that it is necessary to resort to incision of the ligament or resection of the rib. Deep under the middle lamella is revealed m. quadratus lumborum (fig. 1 and 2), which originates from the posterior part of labii interni cristae ilii and the transverse processes of three to four lower lumbar vertebrae and attaches to the last rib, the transverse processes of the four upper lumbar vertebrae, and to the body of Dxn. In the upper portion, this muscle is almost completely covered by m. erector trunci, but in the lower portion it protrudes from under its outer edge. Lamina profunda fasciae lumbo-dorsalis, located immediately deeper than m. quadratus, forms the ventral part of the sheath of this muscle and, originating like the middle lamella from proc. transversus of the lumbar vertebrae, weaves into the aponeurosis of m. transv. abdominis. This lamella is less pronounced than the middle one, but in the upper portion it is thickened and forms a ligament-like structure - lig. arcuatum Halleri. Deeper and more medially, on the lateral surfaces of the bodies of the vertebrae, adjacent to the transverse processes, is located the large psoas muscle (m. psoas major) and the inconsistently existing m. psoas minor. The first originates from the lateral surfaces of the bodies of Dxn, Li-IV and the transverse processes of all lumbar vertebrae. Below it lies adjacent to m. iliacus, with which it (m. ilio-psoas) passes through lacuna musculorum and attaches to trochanter minor femoris. M. psoas minor originates from the lateral surfaces of the bodies of Li, rarely Dxn, passes into fascia iliaca and lig. ilio-pectineum. The fascia surrounding m. psoas major originates from the anterior surfaces of the bodies of the lumbar vertebrae, also extends to m. iliacus (fascia psoatis and fascia iliaca) and attaches to linea terminalis of the pelvis and to labium internum cristae iliacae. Laterally, this fascia merges with the deep lamella of fasc. lumbo-dorsalis and, closing the sheath of m. psoatis, forms
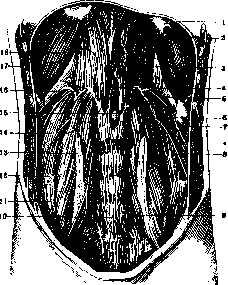
Fig. 2. Posterior wall of the abdominal cavity: 1-diaphragm; 2-esophagus; 3-trigonum costo-lumbale; 4- hiatus aorticus; 5- costa XII; 6-n. inter-costalis; 7- projection of the left kidney; 8-n. ilio-hypogastricus; 9-n. genito-femoralis; 10-promontorium; 11- m. iliacus; 12- crista iliaca; 13-m. psoas; 14 - m. quadratus lumborum; 15 - dome of the diaphragm; 16-arcus lumbo-costalis lat.; 17-arcus lumbo-costalis med.; 18 - projection of the right kidney. (According to Corning.)
forms part of the fascia endoabdominalis. Thus, the fascia iliaca separates two masses of connective tissue, one of which is located anteriorly between the fascia and the peritoneum, while the other accompanies the muscle enclosed in a fibro-osseous bed. The latter serves as a pathway for the spread of purulent accumulations arising along the origin of the m. psoas (from the lateral surface of DXII) and passing under the Poupart's ligament to the anterior surface of the thigh. In the outer section of the lumbar region, under the m. latissimus dorsi, are located the m. obliquus abdominis externus, serratus inf. post., obliquus internus, and transversus (see Abdominal wall). The layer following them consists of the fascia transversa and fascia endoabdominalis. The former arises from the transverse processes of the lumbar vertebrae and lines the muscle of the same name from the inside. The latter is a complex formation consisting of the fascia transversa, fascia quadrata, fascia psoatis, fascia iliaca, fascia diaphragmatica, and fascia pelvis (see Retroperitoneal space). Deeper lie, in sequence, the textus cellulosus retroperitonaealis and the fascia retroperitonaealis, consisting of two leaves (fascia retrorenalis Waldeyeri and fascia praerenalis Gerota), between which is embedded the connective tissue—the paranephron, which transitions into the paraureteron and surrounds the kidney and ureter with their vessels and nerve plexuses (see Retroperitoneal space). Thus, the layers of the lumbar region in its medial and lateral parts can be compared as follows: Medial part: 1. Skin, 2. Subcutaneous tissue, 3. Fascia superficialis, 4. M. latissimus dorsi, 5. F. lumbo-dorsalis, 6. M. erector trunci, 7. Lamina media fasciae lumbo-dorsalis, 8. M. quadratus lumborum, 9. Lamina profunda fasciae lumbo-dorsalis (f. endoabdominalis). Lateral part: 1. Skin, 2. Subcutaneous tissue, 3. F. superficialis, 4. M. latissimus dorsi, 5. M. obliquus abdom. ext., 6. M. obliquus abdom. int., 7. Aponeurosis m. transv. abdominis, 8. F. transversa and f. endoabdominalis, 9. Textus cellulosus, 10. F. retroperitonaealis, 11. Paranephron (paraureteron, kidney).
Vessels of the lumbar region. Arterial supply is provided by five pairs of aa. lumbales, of which the four upper ones arise directly from the abdominal aorta, and the lower one often from the a. sacralis media. The two upper branches pass behind the m. psoas major and are covered by the crura of the diaphragm; the lower ones penetrate into the bed of the m. psoatis major and divide into rami dorsales et ventrales. From the former arise branches (rami spinales), which pass through the intervertebral foramina to the spinal cord, while the rami ventrales, passing behind the m. quadratus lumborum, head toward the broad abdominal muscles and anastomose with the aa. epigastrica inf., ilio-lumbales, and circumflexa ilii. From the upper aa. lumbales arise branches that anastomose with the aa. intercostales, and branches supplying the capsula adiposa renis (see Retroperitoneal space). Veins (vv. lumbales) drain into the v. cava inf. or into the vv. lumbales ascendentes. In the retroperitoneal connective tissue, the veins anastomose with the portal vein system (see Portal vein and Cavae venae) and communicate with the veins of the fatty capsule of the kidney, the ureter, and the pararectal connective tissue (Vishnevsky, Torkacheva). Nerves of the lumbar region consist of the dorsal and ventral branches of the lumbar nerves. The former partly innervate the m. erector trunci, and partly (except for the branches of the last 2 nerves, which are motor), by penetrating through the superficial leaf of the f. lumbo-dorsalis, branch out in the skin on the sides of the spinous processes. The rami ventrales of the lumbar nerves form the lumbosacral plexus (see). In this, the first two nerves of the plexus—the n. ilio-hypogastricus and n. ilio-inguinalis—often pass as a single trunk through the ventral surface of the m. quadratus lumborum, pierce the m. transversus abdominis, and continue between this muscle and the m. obliq. abd. int., having already divided and running almost parallel to each other and to the twelfth intercostal nerve; the latter is located in the same layer and emerges from the gap between the m. quadratus lumborum and the m. psoas major. In the thickness of the latter muscle, the n. genito-femoralis is formed from the I and II roots, which emerges on the anterior surface of the muscle and heads downward. In the muscular mass of the m. psoatis maj., the n. obturatorius is formed from the II, III, and IV nerves, heading toward the
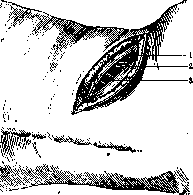
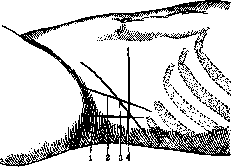
Figure 3. Incisions for exposing the kidney: 1—according to Simon; 2—according to Czerny; 3—according to Bergmann-Israel; 4—according to Pean. can. obturatorius (see Obturatoria arteria, vena), and from the I, II, III, and IV nerves—the n. femoralis, which, upon emerging into the groove between the m. psoas maj. and the m. iliacus, heads through the lacuna musculorum to the thigh. The arrangement and direction of the nerves and the construction of the plexus itself are inconstant both in terms of the number of trunks, anastomoses, loop formation (large- and small-looped), the demarcation between its lumbar and sacral parts (n. furcalis), and in the sense of relationships to muscles and connection with the sympathetic nerve boundary trunk.
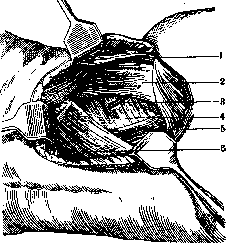
Figure 4. Incision of soft tissues down to the muscles: 1—fascia superficialis; 2—m. obliquus abdominis ext.; 3—m. latissimus dorsi. Diseases of the lumbar region concern all its elements. Most often, one has to deal with a clinical symptom consisting of shooting pains, called "lumbago" (see Lumbago). The lumbar region is particularly susceptible to injuries both from external blunt force and due to the significant mobility of the lumbar part of the spine and the power of its musculature. Significant violence (falling from a height onto the back, blows to the lumbar region, etc.) can lead to serious damage to deeply located organs. This concerns mainly the kidney, which in such a case is subject to rupture, especially in the presence of a simultaneous fracture of the XII rib. Strain and overstrain of the musculature during significant physical exertion and fatigue during prolonged physical tension (walking, forced bent position, etc.) can lead to injury, sometimes unnoticed at the first moment, but subsequently entailing a prolonged loss of working capacity. Such injuries include tears and ruptures of muscles both along their belly and at the site of tendon attachment, accompanied by extra- and intramuscular hematomas, tears and ruptures of fascial sheaths with compression of nerve roots by the hematoma, etc. Such cases concern mainly the m. quadratus lumborum and the m. psoas maj., predominantly the latter. According to Kleemann (Kleemann)
Figure 5. Topography of muscles: 1—m. obliquus ext.; 2—
m. obliquus int.; 3—vasa et n. intercostalis XII; 4—m. transversus; 5—m. quadratus lumborum; 6—m. serratus post. In 26 cases of m. psoatis hematomas, only 14 had an obvious injury; in the majority of the remaining cases, the occurrence of the hematoma was facilitated by an underlying ailment (in 7 cases hemophilia, in 1 case leukemia), but there was still always an injury, even if only in the form of a relatively sharp tension of the abdominal press, bending, etc. It is observed predominantly in men. Diagnosis, especially with an unclear anamnesis, is difficult. It is necessary to differentiate from psoitis, phlegmons, cold abscesses (tumor albus), tumors, osteomas of the m. ilio-psoatis, cysts, echinococci, perirenal hematomas, retrocecal abscesses (retroparasigmoiditis). Inflammation of the lumbar muscle (see Psoitis). Often the m. psoas is involved in the process during spondylitis (see) of the thoracic and lumbar vertebrae, caries of the ilium, or the sacroiliac joint.


patRr*
In the lumbar region, incisions (lumbotomia) are performed for the purpose of extraperitoneal access to the organs of the retroperitoneal space or for opening the latter due to purulent processes within it. A large number of incisions have been proposed, pursuing the goal of minimal trauma to muscles and nerves (XII intercostal, n. ilio-inguinalis, and n. ilio-hypogastricus) and the greatest breadth of the surgical field. Their choice is determined by the extent and localization of the process and the features of the lumbar region depending on the shape of the chest (angle of inclination of the ribs) and the pelvis (height of the iliac crest). The most common are the incisions of Bergmann-Israel, Pean (Fig. 3), and Fedorov. After dissecting the skin, subcutaneous tissue, and superficial fascia, one reaches the muscles and dissects them layer by layer in the direction of the skin incision (Figures 4–6), taking care not to injure major nerves. Upon dissecting the f. transversa, connective tissue appears in the depth of the wound, indicating the proximity of the peritoneum (Fig. 7). Trial lumbotomy is performed more often for the purpose of clarifying the condition of the kidney when tuberculosis is suspected, when other methods of examination do not make it possible to reach a definitive conclusion.
Figure 6. Dissection of the fascia. Figure 7. Liberation of the fatty capsule (1).
Related articles
Mentioned in
- Abdominal Cavity
- Acanthosis Nigricans
- Addison's Disease
- Autotomy
- Bicycle Sport
- Cremaster Reflex
- Discrimination
- Encephalography
- Fennel (medicinal or Florentine, fennel, Foeniculum)
- Gluteal Region
- Hyperglycorrhachia
- Iliac Region
- Incisions
- Kyphosis (or round)
- Lasegue Sign
- Lumbago
- Myelography
- Obstetric Examination
- Pouring
- Psoitis
Cite this page
“Lumbar Region.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/lumbar-region/