Lumbar Puncture
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article describes the technique, clinical applications, and potential complications of lumbar puncture as understood in the 1930s. It details the anatomical landmarks, necessary equipment, and patient positioning required for safely accessing the subarachnoid space.
Encyclopedia article (1928–1936)
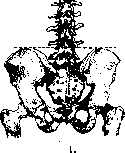
LUMBAR PUNCTURE (punctio lumbalis, lumbar puncture) is performed to obtain cerebrospinal fluid from the spinal canal. According to Quincke, lumbar puncture is performed between LIII and LIV. According to Tuffier, the puncture should be made between LIV and LV, and according to Chipault, between LV and SI. Lumbar puncture was first performed by Quincke in 1890 on a 2-year-old child suffering from hydrocephalus. Even earlier, Corning (1885) developed the question of the effect of injections of medicinal substances into the spinal cord. Subsequently, lumbar puncture began to be widely used for diagnostics and therapy in diseases of the nervous system, for spinal anesthesia according to Bier, and recently for encephalography. The puncture is made into the subdural sac (cavum subarachnoidale), which at this level contains only the filaments of the cauda equina, freely floating in the cerebrospinal fluid. In the lumbar part of the spine, the cavum subarachnoidale is expanded in the form of a cisterna terminalis extending from LII to SII. In this section of the spine, a puncture can be performed in any interspinous space without the risk of injuring neural elements. Most physicians orient themselves to LIV by means of the so-called "Tuffier's line" or Jacobi's line, performing the puncture above or below it. This line is drawn between the highest points of the iliac crests or is determined by stretching a sterile towel across the iliac crests. The intersection of Tuffier's line with the line of the spinous processes is the tip of the spinous process of LIV (Fig. 1).
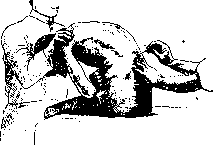
The instrumentation for lumbar puncture: sharp steel needles 7–8 cm long with a short-beveled end or thin (diameter 1–1.3 mm) trocars of the same length and an ordinary Record syringe (5.0–10.0). There are special needles by Quincke, Bier (Fig. 2), Krönig, Tomashevsky, and others. Lumbar puncture must be performed in a hospital setting and, like any operation, strictly aseptically. The puncture is performed in a sitting or lying position. The patient is seated either across the table with legs lowered onto a stool, or with legs stretched out along the table (Fig. 3). The latter position is recommended (Borszeki, Sellheim, Furbringer, and others) to avoid lordosis of the spine at the moment of the puncture (cases of needle breakage). One can also seat the patient astride a chair, facing the backrest. The patient's forearms
rest on the thighs. The back and neck are bent in an arc ad maximum forward. It is better if the head and shoulders are fixed by an assistant from the front. Such a position provides a distinct protrusion of the spinous processes, their divergence, and better orientation regarding the puncture site, especially since the nerve roots of the dural cavity gather into two bundles, diverging to the sides, which favors the insertion of the needle. Lumbar puncture is also performed in a lying position (Fig. 4), especially in severe patients and in infants: the patient is turned on their side, the legs are bent at the knee and hip joints, the torso is bent forward ad maximum, and the head is brought to the chest. - Technique of lumbar puncture. Having marked the spinous process (LIV) with the index finger of the left hand, an energetic puncture of the skin is made below it, in the interspinous space (according to Quincke, 0.5–1 cm from the midline). In the sitting
position, the needle should go almost horizontally, with a slight upward inclination; in the lying position, the needle is at an angle of 70° to the torso. The needle passes through the skin, subcutaneous tissue, lumbar fascia, intervertebral yellow ligaments, and the dura and arachnoid mater. The depth of the puncture varies depending on the patient's obesity and muscle development, on average from 4 to 7 cm in adults and from 2 to 5 cm in children. When passing through the dura mater, a cracking sound is felt, sometimes audible at a distance. After the sensation appears that the needle is in the subarachnoid space, the stylet is removed. The entry of the needle into the cisterna terminalis is determined by the appearance of clear, yellowish fluid, which flows in a stream or frequent drops. One should not advance the needle further after this. An admixture of blood indicates a puncture of the veins of the epidural space or an incorrectly taken direction. In that case, the needle should be removed and the puncture repeated again. The fluid is released in an amount of no more than 10.0 g in adults and 5.0 g in children (only in meningitis from 20.0 to 40.0 g). During the puncture, the pressure under which the cerebrospinal fluid flows out is determined, as well as its color, and then a series of analyses are performed (for protein, Wassermann reaction, and various other physical, chemical, bacteriological,
and cytological studies). The normal pressure under which the fluid flows out ranges from 125–150 mm of fluid. The pressure is measured by the Quincke method, using a Claude manometer, which measures pressure in millimeters of water column. All movements of the body after lumbar puncture must be performed slowly and carefully. After the puncture, the patient is placed horizontally, initially with the abdomen down to avoid spontaneous leakage of fluid, and then turned onto the back; it is better to place the patient's head lower; in this position, they remain for 1–2 days depending on the general condition. Lumbar puncture is used for spinal anesthesia (see); furthermore, it is a diagnostic tool for diseases of the nervous system. By means of lumbar puncture, air is blown into the cavities of the brain (see Encephalography), as well as lipiodol. Lumbar puncture serves as a therapeutic measure to lower intracranial pressure (in hydrocephalus, head injuries, brain tumors), to remove part of the infected fluid (in meningitis, encephalitis), and finally, lumbar puncture is used for the introduction of various medications (urotropin, collargol, antimeningococcal serum, etc.). Contraindications to lumbar puncture include the presence of neoplasms in the brain, mainly in the posterior cranial fossa—the lowered pressure makes it possible for the tumor to shift and press on vital centers; lumbar puncture also presents a danger in cases where lowered pressure can cause repeated hemorrhage (in strokes), rupture of vessels (in uremia), etc. Lumbar puncture should not be performed in the presence of a nearby infectious focus—a bedsore, furuncle, carbuncle, etc. Lumbar puncture is avoided in persons with heart disease or general malnutrition. It is contraindicated to perform lumbar puncture on an outpatient basis. Subsequent complications of lumbar puncture: headaches, back pain, convulsions, dizziness, numbness, tingling sensations, rise in temperature, nausea, vomiting, phenomena of the so-called "meningism" or "aseptic meningitis." The latter is explained by damage to the membranes by the needle (irritation) with subsequent leakage of fluid into the cavum epidurale (Baruch) (a scar forms according to Bungart after 8–10 days). Adverse consequences are often observed in psychopathic and hysterical subjects in the form of vomiting, a sensation of pressure in the head, and phenomena of irritation of the lower extremities. Cases of paresis and paralysis and even death after punctures have been described. The latter is observed mainly in cases of brain tumors. The frequency of complications according to various authors ranges from 10% to 30%. Treatment of complications: horizontal position in bed with the foot end raised, pituitrin, pilocarpine, infusion of NaCl, intravenous administration of a 40% solution of urotropin, etc. A variation of lumbar puncture is the suboccipital puncture according to Ayer and Eskuchen (see Myelography), performed between the occipital bone and the atlas; the patient sits with the head tilted forward; the needle is inserted to a depth of 4–5 cm. This method is not safe for the patient due to the proximity of the medulla oblongata and is used only with direct indications for it (for the introduction of lipiodol into the subarachnoid space).
Figure 1.
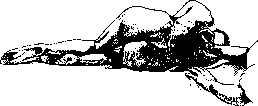
Figure 3.
Figure 4.
Related articles
Mentioned in
Cite this page
“Lumbar Puncture.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/lumbar-puncture/