Hip Joint
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This 1930s encyclopedia article provides a comprehensive anatomical, biomechanical, and developmental description of the hip joint, detailing its bony structures, ligaments, musculature, blood supply, and innervation.
Encyclopedia article (1928–1936)
HIP JOINT, articulatio coxae (coxa, ae—Old Latin word; French cuisse), a term introduced by Vesalius. The joint is formed by the head of the femur and the articular cavity (fossa acetabuli) of the hip bone. The head is considered spherical in shape, somewhat elongated in the frontal direction and flattened on the upper and anterior sides, which is why the hip joint is also called nut-shaped (see Hip bone). The heads of the femurs bear the load of the entire trunk transmitted by the pelvis, forming a parallel pair of connected broken levers of the first kind. During standing, the posterior lever arm is counterbalanced by the weight of the trunk, and the anterior arm by the ligaments and tone of the pelvic muscles. The pelvis can also rest and be supported on a single femoral head (when walking or standing on one leg). The main movements of the hip joint are flexion and extension, i.e., rotation around a transverse axis passing through the centers of the heads. Flexion ends upon the tension of the posterior muscles, and extension upon the tension of the anterior ligament of the joint (see below). The range of flexion and extension in the hip joint is 90°, and together with the pelvis, 130°. Abduction and adduction occur within 60°, and outward rotation around 50°. The phylogenetic development of the hip joint is associated with the position of the body and the shift of its support to the lower extremities. Snakes and some lizards lack lower extremities; in other cases, there is a rudimentary pair in the form of small appendages situated on the sides of the anus, and therefore the hip joint is absent. A number of fossils (Saurischia) had well-developed hip joints—their bodies were held in a vertical or inclined position by the extremities and tail. In reptiles, in connection with the development of the pelvis (see), one observes the fusion of all three constituent bones and the formation of an articular socket for the femur. In crocodiles, an independent cartilage (cartilago acetabularis) separates, displacing the pubic bone from participation in the formation of the articular cavity. In mammals, independently ossifying bones make up the acetabulum, the acetabular bone of which (os acetabuli) is not homologous with the acetabular cartilage of crocodiles. In humans, the primordium of the lower extremity skeleton appears in the mesenchymal base as a growing island. In the 2nd month of embryonic life, segmentation of the extremity bud occurs with the formation of the hip joint and other joints. Cartilaginous preformation begins with the limb girdle. The cartilaginous primordium of the hip bone consists of three independent parts. The epiphysis of the femoral cartilage—a wide plate—as the extremity grows in length, gives the characteristic shape of the femoral head. Ossification of the femur begins in the 6th week. In the 4th month, ossification centers of the acetabulum appear. The process proceeds very slowly, leaving a Y-shaped layer of cartilage for a long time; final ossification occurs by 13-14 years of age, which is of great practical importance. In the adult, the upper epiphysis develops into the head of the femur, and the deflected part of the diaphysis forms the neck. In women, the neck is relatively shorter; the angle formed by the neck and the body approaches a right angle. In children, the femoral head approaches a sphere, becoming variable with age. Towards old age, the upper and anterior sides of the head flatten—the site of greatest load, where pathological processes arise (malum coxae senile). With age, the angle between the neck and the body decreases, the bones become osteoporotic, and the edges of the acetabulum become more sharply outlined and rough. The acetabulum is formed at the site of fusion of three bones: from above—the ilium, from the inside—the pubis, and from below—the ischium. The acetabulum (acetabulum—vinegar cup) is bounded by a raised, pointed edge, the upper, strongly protruding segment of which is called the eyebrow of the acetabulum (supercilium acetabuli). Increasing the depth of the articular cavity, a so-called cartilaginous rim (labrum glenoidale), consisting of fibrous connective tissue, is attached along the entire bony margin. The width of the rim is 0.5 cm; in cross-section, it is triangular in shape and transitions without sharp boundaries into the cartilage of the joint cavity and into the fibers of the hip joint capsule. The anteroinferior margin of the acetabulum is interrupted by a notch (incisura acetabuli), which is filled by the transverse ligament of the acetabulum (lig. transversum acetabuli). At the bottom of the acetabulum there is a rough fossa (fossa acetabuli), surrounded anteriorly, superiorly, and posteriorly by a horseshoe-shaped, concave lunate surface covered with cartilage (facies lunata). From the edges of the notch and the transverse ligament of the acetabulum runs the round ligament (ligamentum teres femoris), covered by a synovial layer and attaching to the fossa of the femoral head. The articular capsule of the hip joint originates along the margin of the articular cavity, external to the rim, thanks to which the latter is placed within the joint cavity. On the femur anteriorly, the capsule attaches above the intertrochanteric line, and posteriorly medial to the intertrochanteric crest; therefore, the greater part of the neck falls into the joint cavity. The joint capsule is reinforced by a series of interwoven ligaments (see Dislocations, Fig. 9-11). The iliofemoral ligament (lig. ilio-femorale, s. Bertini), embracing the joint anteriorly, starting from the anteroinferior spine, attaches along the entire length of the intertrochanteric line. This ligament is the strongest in the human body (about 1 cm in thickness). On the inferomedial circumference of the hip joint is the pubocapsular ligament (lig. pubo-capsulare), running from the pubic bone to the upper circumference of the lesser trochanter. The posterior ischiocapsular ligament (lig. ischio-capsulare) begins from the ischium and passes with one part into the circular fibers of the capsule, and with the other attaches to the trochanteric fossa. In the depths, the capsule is reinforced by the circular zone (zona orbicularis, s. lig. zonale femoris), surrounding the middle of the femoral neck like a ring. The fibers of the above-described three ligaments, weaving into the zona orbicularis, create support for the femoral neck. Between the ligaments are weak spots of the hip joint capsule, which rupture during dislocations (see). Between the iliofemoral and pubocapsular ligaments is the anterior thinned place of the capsule. Between the iliofemoral and ischiocapsular is the posterior thinned place of the capsule, and between the pubocapsular and ischiocapsular—the inferior. Somewhat lateral to the hip joint, between the iliofemoral ligament and the iliopsoas muscle, lies the iliopectineal bursa (bursa ilio-pectinea), sometimes communicating with the joint cavity, which is of practical importance due to the possibility of mutual transition of pus (see Human muscles, Fig. 10 and Mucous bursa, Fig. 4). Further fixation of the hip joint is accomplished by muscles weaving into the capsule, passing over it, and causing various movements of the joint. Flexion is produced by: the iliopsoas (see Human muscles, Fig. 9-13), rectus femoris, tensor fasciae latae (partially), sartorius, gracilis, pectineus, adductor magnus (upper section), adductor brevis (upon flexion of the leg up to 50°), gluteus maximus (anterior fibers upon inward rotation of the thigh) (see Thigh, Fig. 1). Extension—semimembranosus, semitendinosus, biceps femoris (long head), partly gluteus maximus, adductor magnus (upon flexion of the thigh over 50° by the upper and middle parts), gluteus superficialis [sic] (posterior section), etc. (see Thigh, Fig. 2 and 3). Abduction—gluteus medius, gluteus maximus (middle part), gluteus minimus, piriformis, partly sartorius, tensor fasciae latae, etc. (see Thigh, Fig. 2 and 3). Adduction—adductor magnus, longus, brevis, gracilis, partly biceps femoris, semimembranosus, semitendinosus, pectineus, etc. Outward rotation—quadratus femoris, obturator externus and internus, piriformis, partially gluteus maximus (with extended leg), gluteus medius (posterior section), iliopsoas (simultaneously with flexion) (see Thigh, Fig. 2 and 3). Inward rotation—gluteus medius (anterior section), gluteus maximus (upon strong flexion) in combination with the action of adductor muscles (see Thigh, Fig. 2 and 3). Blood supply to the hip joint is provided by branches of the inferior gluteal artery (system of the hypogastric artery), the medial circumflex femoral artery (a. circumflexa femoris med.—branch of the deep artery of the thigh), and the obturator artery (a. obturatorria). From the latter departs the artery of the acetabulum (a. acetabuli), penetrating under the transverse ligament of the notch into the joint. Here it divides into two branches—to the cavity and for the femoral head, which it enters via the round ligament. Venous outflow from the hip joint proceeds via the systems of the deep vein of the thigh and the hypogastric vein with their numerous anastomoses. Lymphatic vessels of the hip joint through the obturator canal penetrate into the pelvis and drain into the hypogastric lymph nodes. Nerves to the anterior part of the hip joint capsule come from the femoral nerve (n. femoralis) and obturator nerve (n. obturatorius); to the posterior part of the capsule—from the sciatic nerve (n. ischiadicus). Topically, the projection of the hip joint is determined as follows: through the middle of the line connecting the anterior superior spine to the symphysis, a vertical line is drawn, dividing the acetabulum and the femoral head in half. In normal standing, the middle points of the hip joints are located above the centers of the knee joints.
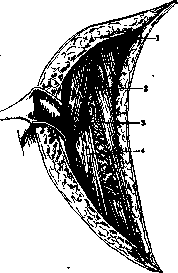
The deep position of the hip joint makes it impossible to examine its contours by palpation; the latter is successful in cases of marked muscle atrophy and dislocations, when the head emerges from the acetabulum, disrupting the relations of the Roser-Nelaton line (see). The syntopy of the hip joint is clearly visible on frontal and horizontal sections. The figures show that the greatest muscle mass is located on the anterolateral and posterior sides of the hip joint. The neurovascular bundle lies on the anteromedial side, the sciatic nerve on the posteromedial side, etc., which is of great practical importance for judgments about surgical approaches to the hip joint (see below).
G. Richter. Pathology. Congenital changes in the hip joint. Congenital absence of the hip joint is observed together with cases of very rare congenital absence of the femur (see Thigh). Various degrees of this deformity can manifest either in the absence of the proximal epiphysis or in the insufficient or defective development of its elements. There is a marked shortening of the femur with coxa vara (see below), absence of a differentiated hip joint, and synostosis between the femoral head and the acetabulum. These congenital deformities are of the greatest rarity and their origin has not yet found a completely exact explanation (Figs. 1, 2, 3). This deformity is of the phocomelia type, in the origin of which several factors may play a role, e.g., amniotic bands disrupting the vascularization of individual areas. This especially applies to the subtrochanteric region, which in the embryo depends for its blood supply on the femoral diaphysis. There are no muscles here, and the blood supply to this area of the bone depends on the nutrient arteries, which run along the muscle attachments of the linea aspera of the femur (Reiner). There are definite relationships between vascularization and ossification in the embryo. In some cases, blockage of the feeding vessels from various causes can be assumed. Sometimes the possibility of a defect in the primary anlage or an intrauterine fracture is not excluded. Indications for treatment are either very strong leg shortening (of course with unilateral lesion) or the presence of contracture accompanying coxa vara (see below), or a flail joint. Wearing a brace-and-socket apparatus extended in the form of
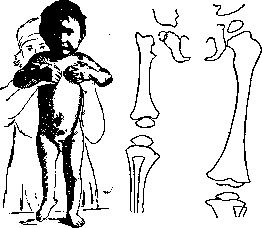
Figure 1. Congenital partial defect of the femur in a child (1 year 10 months), shortening 6 cm.
Figure 2. Diagram of an X-ray of the thighs of the same child (see Figure 1) with a defect of the proximal end of the femur. a prosthesis can alleviate the distressing symptom of "flailing" and compensate for the shortening, which is sometimes very significant in these cases. Surgical measures in the form of myotomies (section of the adductor muscles), osteotomies (see below) can sometimes correct the malposition of the hip joint. The most frequent congenital disease of the hip joint is its congenital dislocation and subluxation (see Dislocations). According to Isigkeit, 0.2% of all live-born infants possess this anomaly,
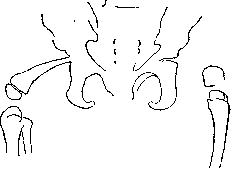
Figure 3. Bilateral defect of the femur in a 4-year-old
child together with the absence of the fibula on the left. subluxations, according to Calot, are encountered even more frequently upon careful study of X-ray images. If these conditions are not recognized in time and treated correctly (closed reduction in unilateral dislocation in children up to 7 years gives good joint function in more than 80%, in bilateral lesion up to 5.5 years - from 50% to 80%), persistent disorders of hip joint function remain, along with significant disorders of statics when walking and standing. The essence of these disorders lies in the fact that the femur loses its support on the pelvis, because the femoral head, not being located in the acetabulum, under

load slides freely along the lateral wall of the iliac bone, reaching in severe cases as high as the iliac crest. The passive apparatus for maintaining the balance of the trunk in relation to the femur during standing fails, because the ligamentous apparatus of the hip joint, which is decisive for this function, ceases to function, especially the iliofemoral ligament (see anatomy). The loss of function of the gluteus medius and gluteus minimi muscles, the points of origin and attachment of which come too close together, entails the loss of the function of actively maintaining the balance of the pelvis in relation to the femur during walking and standing. The first cause causes lordosis of the lumbar spine as a factor maintaining the passive state of balance, the second cause gives patients a characteristic waddling gait with the Trendelenburg sign (see Dislocations). The same picture, only in a somewhat mitigated form, is also found in subluxations. There is a series of intermediate forms connecting dislocations and subluxations. Despite the insignificance of the displacement of the head, sometimes measured only in millimeters, the symptomatology in subluxation can closely resemble that in dislocations. In subluxations, the acetabulum can be very flattened, the femoral head can be flatter, roller-shaped, mushroom-shaped (Fig. 4). The flat shape of the head
Figure 4. Congenital of a young girl, although this is difficult to prove. In the majority of cases, such a shape of the femoral head is the outcome of pathological processes that were accompanied by softening of the head and subsequent deformation (Perthes disease), osteomyelitis in early childhood, epiphysiolysis, deforming arthritis, etc. (coxa vara see below). Some authors (Calot, Waldenström, etc.) made an attempt to isolate the flat head into an independent nosological unit - coxa plana, however, the majority of surgeons consider this deformation secondary. A very complex and heterogeneous group of pathological conditions, united under the name of coxa vara and coxa valga, includes both congenital and acquired diseases. The name coxa vara means a deformation in which the axis of the femoral neck forms an angle with the axis of the femoral diaphysis that is less than normal, while coxa valga means greater than normal. The dimensions of this angle normally range between 130° (in men) and 120° (in women). Pathological conditions are apparently determined first of all not by the dimensions of the angle, not by morphology, but by functional disorders associated with this condition. For clinical purposes, the following definition is more suitable: coxa vara is such a morphological and functional deviation from the norm in which the femur, during concentric standing in the acetabulum, is in a state of adduction (Fig. 5), while in coxa valga it is in a state of abduction (Fig. 6) (Hagelund). A decrease in the angle can be caused by almost all diseases of the hip joint. Due to the heterogeneity of the diseases included in the coxa vara group, their classification was built by authors on various principles. By location: 1) coxa vara capitalis, 2) coxa vara epiphysata, 3) coxa vara S29 trochanterica. By origin: 1) coxa vara congenita, 2) coxa vara rachitica, 3) coxa vara statica, or essentialis, or juvenile form, 4) traumatic coxa vara, 5) coxa vara after inflammatory diseases. Considered by many
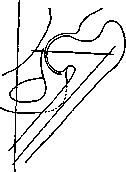
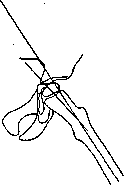
Figure 5. Schematic drawing of coxa vara.
Figure 6. Schematic drawing of coxa valga. to be convenient is the classification of Hoffa and Drevermann: A. Congenital coxa vara. B. Acquired coxa vara: 1) symptomatic: a) rachitic (Fig. 7), b) osteomalacic (Fig. 8), c) inflammatory, d) traumatic; 2) coxa vara essentialis (adolescentium, or static).
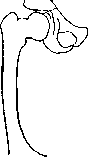
Figure 7. Coxa vara rachitica with rachitic curvature of the femur.
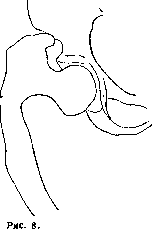
Coxa vara osteomalacica.
The mechanism of origin of coxa vara is simple in fractures of the femoral neck. The diaphysis is established at a more acute angle to the neck due to the pull of the adductor muscles. In other forms, the mechanism is more complex. A gradually forming bend is assumed due to pathological softening of the bone or a decrease in its strength. Etiological factors: rickets, malaria, fibrous osteitis, inflammatory diseases, endocrinopathies. In the case of static coxa vara, the static-dynamic factor comes into play, which includes both abnormal loading for a given neck and abnormal muscle pull (adductors). Patients suffering from static coxa vara (juvenile, essentialis), predominantly rural residents aged 12 to 18 years, attract attention with the bulkiness, massiveness, and cyanotic appearance of their extremities. Bilateral lesion is more frequent than unilateral. Gradually, pain radiating to the thigh, knee, and perineum makes itself felt more and more strongly; the pain increases with walking and subsides in
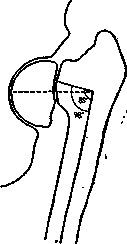
Figure 9. Angle of the neck base (98°) and diaphyseal-epiphyseal angle (85°). In congenital coxa vara, the angles may not coincide.
rest. Patients begin to limp. The leg assumes a position of adduction and outward rotation. The greater trochanter rises above the Roser-Nelaton line, and Trendelenburg's sign appears. When kneeling, the patient's thighs cross. The thigh musculature becomes somewhat atrophied. After 1-1.5 years, the pains subside; there remains rapid fatigue upon walking, shortening of the thigh, adduction and external rotation, sometimes with hyperextension in the knee joint. Anatomically, this is coxa vara epiphysata. Radiologically, decalcification of the head and neck and a gradual decrease in the collo-diaphyseal angle are revealed. Subsequently, the epiphysis settles more and more, producing the picture of epiphysiolysis (see below); the femoral head flattens, and later condenses and assumes a mushroom shape. The epiphyseal cartilage ossifies (Figures 9, 10). Regarding congenital coxa vara, doubts are expressed as to the possibility of its diagnosis: in early childhood, radiographs are rarely taken, while the interpretation of a radiograph of the femur in a newborn or infant presents the greatest difficulties. On the other hand, there is reason to believe that some cases of static and rachitic coxa vara are congenital, but only manifest themselves later. The indication for treatment is the degree of functional disorders, rather than morphological signs, no matter how pronounced they may be. Treatment in the initial acute stage consists of rest, continuous traction with a weight of 2-3 kg; after the pain subsides, the wearing of a removable unloading brace for several months, massage and gymnastics every evening in a lying position, and the hip joint must be in a state of internal rotation, abduction, and flexion. When the process is complete, if limitation of mobility, pain, leg fatigue, and Trendelenburg's sign persist, surgical intervention is indicated. Redression, osteoclasis of the neck, subtrochanteric osteotomy (see below) of various types, joint resection, and arthroplasty are used; oblique subtrochanteric osteotomy is most willingly employed.
Coxa valga is rarer and has comparatively small clinical significance, but on the other hand, great biological interest. It can also be congeni

Figure 10. Coxa vara in an 8-year-old child with congenital changes in the epiphyseal nucleus.
hip joint is a congenital disease. In muscle atrophies and paralyses of the adductor and extensor muscles, coxa valga is always observed, especially if the patient cannot use their extremities for a long time. Proper muscle play and load on the femur are necessary for the formation of the cervical angle; otherwise, coxa valga develops from inactivity. Coxa valga as a result of past inflammation or trauma is a great rarity. Clinical picture: narrow hips, the greater trochanter stands low and significantly more medially, limitation of adduction and increase in abduction of the thigh, clumsy gait with inward turning of the foot. Sometimes coxa valga is combined with insufficient development of the acetabulum. In this case, the head in relation to the acetabulum is in a state of subluxation and easily dislocates, thereby giving a complete analogy with luxatio coxae congenita. This latter form is termed coxa valga luxans. This last form must be managed according to the principles of treatment of congenital hip dislocations, whereas all other types of coxa valga usually do not require treatment, only occasionally giving cause to combat muscular contractures, to wear orthopedic apparatuses, or for fixing operations in muscular paralyses of the hip joint. Traumatic injuries, like other diseases of the hip joint, should be divided into intra-articular and extra-articular, open and closed. Fractures of the femoral neck occupy first place both in frequency and in practical significance. According to Bruns, 6% of all fractures fall on the femur, of which 1.5% are of the femoral neck; after 70 years, [missing text] of all fractures fall on the femoral neck. According to anatomical criteria, Matti distinguishes the following types: 1) fracture of the head, 2) subcapital or medial fracture of the neck, 3) intertrochanteric fracture of the neck, 4) lateral fracture of the neck, 5) fractura colli femoris intertrochanterica, 6) fractura pertrochanterica, 7) fractura subtrochanterica, 8) isolated detachments of the trochanters (Fig. 11). For the clinician, the important fact is that the first 3 groups are intra-articular injuries. Lateral fractures of the neck can sometimes be both intra-articular, and finally, the last 4 groups are always extra-articular injuries. Fractures of the femoral head, of its cartilaginous part, are relatively rare. They are diagnosed with difficulty both clinically and radiologically. Dupuytren already asserted that in a fall on the leg or on the greater trochanter, compression fractures of the femoral head often occur, which are not recognized and are considered bruises of the hip joint. Interpretation of the X-ray in this case is a difficult task, and damage to the head is often overlooked. A longer-lasting swelling, persistent soreness upon percussion along the axis of the diaphysis or femoral neck, and prolonged functional disorders of movement upon loading the hip joint make one suspect a fracture of the head. Treatment: initially, unloading by means of traction for up to 2 weeks. After resorption of the hemorrhage, movements, application of heat in the form of hot and dry-air baths
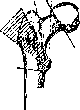
Fig. 11. Classification of femoral neck fractures. (According to Matti.)
according to Bier. The prognosis quo ad functionem is always serious, since secondary severe deforming changes in the joint may arise. These deforming arthritides sometimes indicate secondary operations: joint resection of the arthroplastic type in young people and arthrodesis in old age. Intra-articular fractures of the neck represent a disease occurring somewhat more frequently in women and characteristic of age over 50 years. In youth and sometimes in children, medial neck fracture occurs almost exclusively in the form of a rupture of the epiphyseal cartilage and traumatic detachment of the epiphysis. Kocher, Volkovich, and others established that the mechanism of the fracture is usually as follows: a fall on the greater trochanter, with the blow falling more often on the posterolateral surface of the trochanter major, along the axis of the femoral neck; the force of the blow is directed from behind and below upwards and forwards, from this compression along the long axis of the neck a compression fracture is produced at the weakest place, immediately beneath the head. The central fragment is fixed by the edges of the acetabulum, while the peripheral fragment begins to slide forward and upward. The crista intertrochanterica, protruding significantly posteriorly, presses on the neck from behind, causing the fragments to move anteriorly, and the thigh to rotate outward in the process. During its forward movement, the neck rests against the immobile lig. Bertini, and the further action of the force creates conditions for an additional bending fracture. In this case, the posterior edge of the peripheral fragment can embed into the spongy substance of the central fragment and sometimes produce a so-called impacted fracture. When falling on the foot, when the force is directed along the axis of the femur, a pure form of fracture from shear of the peripheral fragment—unsupported by anything—against the fragment with the head, well fixed in the joint, may result. A pure form of fracture from external rotation can take place when falling on the side, if the leg is fixed in the process, and the torso turns inward. Epiphysiolysis in children is a complete analogy to subcapital fracture in old people. It can be the result of a very strong simultaneous trauma, sometimes repetitive. First, a loosening of the epiphyseal junction occurs, and then its complete separation. There is reason to believe that in many cases the trauma affects a growth cartilage that is already pathologically altered, and epiphysiolysis is easily added here additionally. Such traumatic detachment of the epiphysis is more often observed in children with a hypophysial type habitus (dystrophia adiposogenitalis). The displacement of the femoral neck fragments corresponds to the fracture mechanism. Usually, the central fragment is in a position of abduction and internal rotation, the lateral fragment in an internally rotated and adducted position. Medial fractures resulting from a fall on the back are almost always adduction fractures with a high-standing trochanter and a strongly adducted thigh. Clinical picture: the leg is turned outward, pains are spontaneous and upon palpation of the inguinal region and the region of the hip joint, sometimes radiating to the knee, sometimes to all sides of the thigh. A jolt to the greater trochanter or along the axis of the femur sometimes causes significant pain. In most cases, one can establish some shortening of the thigh (up to 2 cm). The most constant sign is functional impairment. Patients cannot actively adduct and abduct the thigh and lift it. Passive movements are possible, but are still accompanied by pain. The greater trochanter stands higher than the Roser-Nelaton line. The distance from the anterior superior iliac spine to the apex of the greater trochanter is shorter on the affected side. Bryant's triangle on the affected side ceases to


Figure 12. Bryant's triangle on the healthy side.
to be isosceles—the vertical leg decreases, the horizontal elongates (Fig. 12, 13). An X-ray photograph may present difficulties in interpretation in cases of incomplete fracture, impacted fracture, and in very rare cases in pathological fracture. In such patients, only repeated structural radiographs clarify the matter and allow differentiation from a bruise or sprain of the hip joint. The prognosis in medial fractures must be stated very cautiously, since in the majority of cases it concerns old people, for whom prolonged immobilizing treatment carries a number of dangers in the form of exacerbation of purulent bronchitis, hypostatic pneumonia, thromboses with subsequent embolism, urinary retention with subsequent cystitis, bedsores, and weakening of cardiac activity. Obtaining complete bony union and restoration of function in these patients appears to be an extraordinarily difficult task. Kocher speaks of this as an exception; according to Hübner, 74.8% of poor fracture unions are obtained. Complete consolidation of the fracture sometimes occurs after 8–10 months, or even only after a year. Causes of poor healing: 1) senile osteoporosis, 2) atrophy and resorption of the crushed neck, 3) absence of periosteum (bone-forming) on the neck, 4) interposition of parts of the hip joint capsule, 5) unfavorable vascular anatomy. In a fracture of the neck with complete rupture of the joint capsule, the central fragment may completely lose its nourishing vessels and undergo aseptic necrosis. Under such conditions, a bone callus forms only on the peripheral fragment. With the integrity of at least half of the capsule, the blood supply is sufficient. A very important factor is insufficient reposition and fixation of the fragments, and finally, early weight-bearing. Recent work suggests that with correct treatment technique, the percentage of successes can be brought to 80–90%, while in the remaining cases a pseudarthrosis is obtained. under general anesthesia, the fragments are repositioned. This is achieved by turning the leg, i.e., the peripheral fragment, inward, followed by abduction of the leg and slight flexion. Only in this position does contact occur with the central fragment, which is in a position of abduction and inward rotation. In this case, the capsule is stretched and strengthens the fragments. The fragments are fixed in the achieved position either by a plaster cast or by traction. At the present time, the Whitman plaster cast is accepted, applied from the axillary region down to the toes. The cast is kept on for 2–3 months. After this, one transitions to active and passive gymnastics in bed, with the leg remaining in a state of abduction and inward rotation all the time. Weight-bearing is allowed no earlier than 1/2 year. Sometimes in this cast the patient can move about on crutches. In
Figure 13. Bryant's triangle on the affected side.
The treatment of a medial fracture of the neck is conservative in the majority of cases. Large statistics indicate that surgical treatment yields only 40–50% success. Newer data (Böhler, Smith-Petersen) give somewhat better figures. Under local anesthesia or Figure 14. Reposition of femoral neck fragments according to Tavernier. After verification by X-ray, fixation of the fragments with a special screw. in the above-mentioned position, the leg can also be fixed using skeletal or adhesive plaster traction. Fixation continues until the patient can actively lift the leg. Throughout the entire bed rest, the patient does gymnastics, moves within the limits of the possibility, and participates in physical culture exercises. Weight-bearing is also not earlier than 1/2 year, when the X-ray photograph indicates bony union of the fragments. This method has been successfully used recently at the Sklifosovsky Institute of Emergency Medical Care in Moscow. Löfberg, after correct alignment of the fragments by a blow of a hammer (of his design), effects impaction of the fragments and fixes them in such a position. Reposition
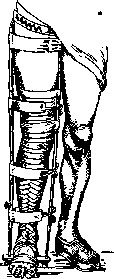
of the fragments sometimes encounters difficulties: it is necessary to apply greater traction (up to 10 kg), use Tavernier's method during reduction (Fig. 14), etc. All the described methods are not applicable in very old, obese, emphysematous, prostatic individuals, and others. For them, concern for function stands in the first place, rather than the correct anatomical alignment of the fragments. They cannot be kept in bed for long due to the danger of the onset of various complications and marasm. Walking on crutches in the Volkovich apparatus, Thomas splint (Fig. 15), and other devices provides the patient with a tolerable existence.
As for surgical treatment, its goal after exposing the site of the fracture is to produce a connection of the fragments by one method or another. Connection by wire suture, by screws passed through the entire neck and both fragments, by all kinds of clips (Bolzung) from autoplastic material (tibiae plates), heteroplastic material (bovine bone plates), and all kinds of metal plates and screws is proposed. Kocher, believing that bony union can generally not be achieved in medial fractures, removed the head and inserted the neck into the acetabulum even in fresh cases. Large statistics show that these surgical measures in fresh cases give worse results (no more than 40% success) than conservative ones (up to 80%). Causes: significant rarefaction of the bones from the presence of a foreign body, because of which the fixation of the fragments weakens, then secondary fracture of the graft, suppuration of the wound, poor regenerative capacity of the bones in old people. Despite the authority of Lexer, Delbet, Henderson, and others (Lexer, Delbet, Henderson), surgical intervention in fresh cases of femoral neck fracture takes a back seat to conservative methods. However, recently many authors (Smith-Petersen, Böhler, Tavernier, Hotz) have again raised the question of the open treatment of neck fractures. After reduction of the fragments, a nail originally constructed by Smith-Petersen, consisting of 3 edges, is driven into the region of the greater trochanter. Each edge represents a thin and sharp plate. Such a nail is easily introduced and tightly fixes both fragments, preventing them from shifting. The Smith-Petersen incision (Fig. 16) begins immediately below the anterior superior iliac spine, goes downward and somewhat bypasses posteriorly the base of the greater trochanter; upon opening the fascia, the tensor fasciae latae muscle is bluntly separated and retracted outward, and the rectus femoris and sartorius muscles inward, after which the anterior capsule of the hip joint is exposed (Fig. 17). Upon opening the joint, the fragments are reduced (Fig. 18), and from this same incision into the region of the subtrochanteric fossa under visual control, the Smith-Petersen nail is introduced (Fig. 19), which is passed through both fragments (Fig. 20, 21). Correctness
Figure 16. Smith-Petersen's incision: 1—crista iliaca; 2—incision line; 3—m. tensor fasciae latae; 4—greater trochanter; 5—lower end of the incision, site of intersection of the iliotibial tract.
of the operation is controlled by the restoration of passive movements in the hip joint. The postoperative period is 7–10 days. A short plaster cast, after which crutches are used, sometimes even without any cast. According to Hotz, from a small incision below the greater trochanter after reduction of the fragments, a screw (10–12 cm long) is passed through the head neck and acetabulum. The direction and depth of introduction are determined by an X-ray photograph using pre-marked lines on the skin. A control radiograph must be taken immediately. In case of correct fixation of the femur to the pelvis (Fig. 22), walking is permitted as early as the 2nd day. The above-mentioned method of fragment reduction according to Tavernier is likewise supplemented by fixation of the fragments with a special screw under the control of a portable X-ray apparatus. Traumatic epiphysiolysis in children is treated in the same way as medial fractures. In severe cases with complete separation of the epiphysis and its significant displacement, surgical treatment with possible installation of the fragments into the correct position and preservation of the growth cartilage is performed. It is fixed in such a position for a month.
Lateral and intertrochanteric femoral neck fractures have the same clinical picture, prognosis, and therapy. The fracture results from a fall on the greater trochanter, sometimes with its crushing and detachment of the lesser trochanter. A fracture can also result from a fall on the leg with the action of a force along the axis of the femur (bending fracture). The clinical picture is— Figure 19. Smith-Petersen's nail.
Figure 20. The fragments are connected in the correct position using a special instrument consisting of a protector and head holder, a fragment fixator, and a special pusher for the nail.
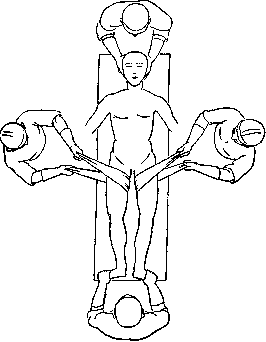

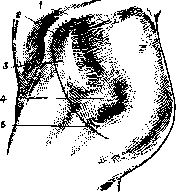
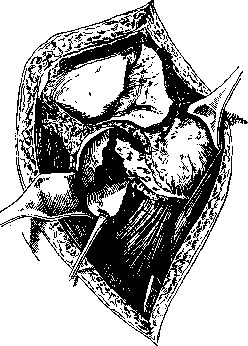

resembles a medial fracture, only the outward rotation of the thigh is less, while the shortening of the limb is usually greater (up to 4 cm). The angle of inclination of the neck, i.e., coxa vara traumatica, is always more pronounced. The conditions for fracture healing are much simpler than in a medial fracture, and a strong bone callus can be achieved
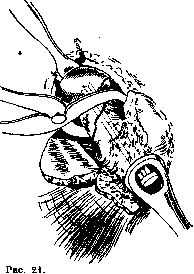
The fragments are well fixed with a nail.
zole in a relatively short time. A very unpleasant complication of these fractures is extensive crushing of the greater trochanter and the surrounding bone, which subsequently produce voluminous calloused masses extending onto the capsule of the hip joint. This results in prolonged and persistent limitations of mobility and pain during movements in the hip joint. In sometimes encountered lateral intra-articular fractures, the course of the disease can be just as severe as in a medial fracture of the neck with poor fracture consolidation and meager callus formation. Impactions of this area may sometimes not be recognized in time, are treated as bruises, and with early weight-bearing and movement lead to very severe forms of coxa vara traumatica or coxa adducta traumatica. These patients sometimes require subsequent surgical assistance (see osteotomy below).-Treatment. Under local or spinal anesthesia, less often under general anesthesia, traction is applied to the broken limb. If the neck angle is greatly reduced, then skeletal traction via the femur or the upper end of the tibia in a state of very strong abduction of the thigh—up to 50°. With minor changes in the neck angle, traction via the soft tissues is recommended—flexion in the hip joint of no more than 30°. Outward rotation of the thigh is corrected either by a special traction turning the thigh inward, or by a Volkmann splint, or by securing the lower leg and foot. Traction is maintained for 2-21/2 months, followed by at least a month of wearing a Thomas apparatus or a plaster cast, under constant control of the state of the neck angle. In very elderly people, a light plaster cast can be applied immediately in a state of abduction and they can be put on crutches. In rare cases where it is impossible to set the fragments correctly using various tractions, surgical treatment is resorted to. An incision in the region of the greater trochanter is used to perform an open reduction of the fragments. After this, they are screwed together with a Lambotte screw or fixed with wire or other material wrapped around them (Fig. 23, 24).
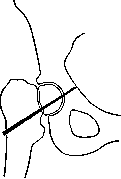
Figure 22. Method of fixing fragments together with the pelvis according to Hotz using a long screw. 839


Figure 23.
Figure 24. Intertrochanteric fractures occur most often from a sharp hyperextension of the leg during a fall backward and from a forced rotation and adduction of the thigh during a fall in the opposite direction. The peripheral fragment is usually displaced forward and inward. In the clinical picture, what catches the eye is the sharp protrusion of the greater trochanter, its immobility during the rotation of the femoral diaphysis, and the significantly anteriorly displaced peripheral fragment can often be felt; shortening of the leg by 3-5 cm, outward rotation of the thigh. The treatment of these fractures requires significant flexion of the thigh and knee joint; otherwise, they are treated in the same way as intertrochanteric fractures. Isolated fractures of the greater trochanter are exceptionally rare. These are usually avulsion fractures due to uncoordinated action of the gluteus medius muscle and others, which upon contraction can displace the fragment significantly upward and backward. In the absence of large displacement of the fragment, treatment is conservative. With a large separation, the fragments must be sutured or screwed together. The duration of treatment is 5-6 weeks until the restoration of impaired movements of abduction and outward rotation of the thigh. An isolated fracture of the lesser trochanter is an equal rarity, representing an avulsion fracture from the forced contraction of the iliopsoas muscle. Characteristic symptoms are restriction of outward rotation of the thigh and the inability to lift the thigh in a sitting position with an extended knee joint (Ludloff's symptom). This phenomenon is explained by the fact that raising the thigh is possible in such a position only with the help of the iliopsoas muscle, since the rectus femoris muscle cannot function under such conditions, and the activity of the iliopsoas muscle has ceased due to the avulsion of its attachment site. Treatment is usually conservative, from 2 to 6 weeks. Subtrochanteric fractures in their mechanism and the course of the disease have much in common with fractures of the upper third of the thigh. Complex pictures of combinations of fractures at several levels of the neck are encountered. Despite the continuous improvement in the methods of treatment of neck fractures, especially recently, reputable world statistics state that no least 20% of femoral neck fractures do not unite. According to Anschütz, out of this number, about 20% die from the consequences of the fracture or complications (pneumonia, bedsores, marasmus). In approximately 30% of patients of low weight and not thick, these fractures proceed well with the most conservative methods. In these cases, although there is no bone union, nevertheless, the peripheral end with teeth and marginal protrusions from the formed callus penetrates deep into the lesser trochanter or another part of the central fragment and thus provides a solid support for the leg, and the patient does not need serious assistance. 50% of patients need surgical help. Indications for surgery: constant pain and a sharply expressed Trendelenburg sign, i.e., the complete inability to bear weight on the leg.
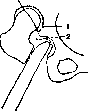
Figure 25. Bifurcation according to Lorenz; oblique osteotomy in the sagittal plane: 1-capsule of the head on the os ilium; 2-acetabulum.
Operations are bloodless and bloody. Bloodless operations aim to place the distal fragment in a position where it has support. Inversio, according to Lorenz—transfer to a position of inward rotation, abduction, and extension, i.e., transfer to the opposite position and fixation in such a position; transposition, according to Drevermann—the fragment is transferred to an anterior position for support of the pelvic bone. Finally, the repeated application of Whitman's plaster cast after reduction of the fragments. Bloody operations. There are a wide variety of methods: extra-articular and intra-articular (in the area of the fracture), preserving movement and not preserving movement (creating only support), preserving normal anatomy and disfiguring (arthroplasty). Of the extra-articular ones, subtrochanteric transverse or oblique angular osteotomies have been very willingly used lately. The distal fragment is usually abducted by 30-35°, placed in the correct position, and the leg is fixed using a plaster cast or traction for 11/2-2 months. In subsequent treatment, massage and gymnastics. In 1918, Lorenz proposed an oblique osteotomy for longstanding congenital dislocations of the hip, which provides a solid support to the leg in the normal place in the region of the acetabulum. The bone is dissected in the sagittal plane at the level of the acetabulum, the lower fragment is inserted into the acetabulum, and the upper fragment adjoins it from the side, forming an angle. After bone fusion, the proximal end of the femur acquires a similarity to a fork with two teeth, on which the pelvis firmly rests (Fig. 25). Hass proposes to make the bone dissection in the frontal plane to avoid a sharp displacement of the central fragment anteriorly due to the pull of the iliopsoas muscle (Fig. 26). The operation is called bifurcation (according to Lorenz, Hass, Kirmisson, Bayer) and also provides valuable services in the treatment of pseudarthrosis of the femoral neck; the fork in this case embraces the central fragment of the neck with the head, resting against it (Fig. 27). Incision along the outer side of the thigh from the greater trochanter downwards. After dissection of the bone, traction downwards, abduction up to 40-45°; after the lower fragment has shifted to the desired place under the femoral head, fixation for 2-3 months. Schanz's osteotomy also provides support and eliminates adduction of the thigh, but is based on a different principle. A transverse deep osteotomy of the femur is performed at the level of the ischium. An angle open outwardly is made between the fragments. The central fragment approaches the pelvis.
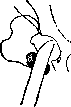
Figure 26. Bifurcation according to Hass; osteotomy in the frontal plane.
fragments, the Trendelenburg phenomenon disappears, since the pelvis can no longer lower onto the healthy side, resting against the diseased thigh. Before dissecting

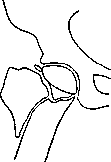
Figure 27. Bifurcation according to Lorenz in pseudarthrosis of the femoral neck: 1-before surgery; 2-after surgery.
ing the bone, 2 special screws are inserted (Fig. 28) above and below the fracture site, parallel to each other. After the osteotomy, they are set at the desired angle (35-40°) (Fig. 29), their protruding ends are fastened, and a plaster cast is applied to the entire limb down to the toes. A month later, the screws are removed by making a window in the cast. Another month to a month and a half later, the plaster cast is removed. Schanz's operation gives
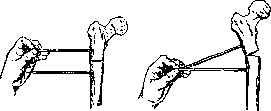
Figure 28.
Figure 29. a weaker support, but on the other hand shortens the leg less and provides greater mobility than Lorenz's operation (Fig. 30).-Similar to Schanz's method is Pauwels' operation, used by a number of authors for the treatment of neck pseudarthrosis (Fig. 31). After wedge osteotomy and setting the fragments at an angle,
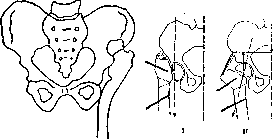
Figure 30. State of the hip joint after Schanz's operation.
Figure 31. I-before osteotomy according to Pauwel'y; II-after the operation. When opened outward, the pseudarthrosis line becomes almost horizontal and thus the force of gravity compresses the fragments of the femoral neck rather than separating them, which eliminates painful phenomena. To restore function to the weakened mm. glutaeus medius and minimus, the greater trochanter with attached muscles is detached and transplanted to the diaphysis more peripherally, to return proper function to the muscle deprived of its normal attachment point. This operation (Veau-Lamy) as a standalone procedure is unreliable, but when combined with other operations it secures their success. Good functional results are given by operations in which the freely lying head is removed and the neck is inserted into the acetabulum (fig. 32, 33).-If the neck is short, different methods have been proposed for its lengthening: part of the greater trochanter is detached, both trochanters are moved peripherally, various wedge-shaped osteotomies are added (Schlegel, Golyanitsky and others). König, Borchard, Schmieden and others insert the greater trochanter into the acetabulum. The leg is fixed in a plaster cast for 2½-3 months in an abducted position. With these methods, ankylosis of the hip joint is expected, i.e., restoration only of the supporting function.
Figure 33. A-plane of detachment of the greater trochanter; B-transplanted greater trochanter; C-joint capsule.
Lexer's plastic operation provides not only support but also restores movement in the joint (fig. 34). Incision of skin and fascia (see below-operation of Murphy, Lexer), after opening the joint-removal of the head; by free transplantation of a piece of bone taken from the removable head and placed subperiosteally, the overhang in the area of the acetabulum edge is increased; then the neck is shaped, wrapped with a flap of fascia with fat taken from the thigh, and inserted into the acetabulum; layered sutures on the wound. After a month of fixation, active and passive movements. Lexer's results are good.-If the head is not necrotic and the patient is not old, there are indications for bone synthesis with complete restoration of both function and anatomy of the femoral neck. Fragments of the femoral neck in pseudarthrosis are fixed with the help of an inserted wedge (Bolzune) into the acetabulum with interposition of fascia and fat between the head and acetabulum; the greater trochanter is transplanted lower according to Veau-Lamy; A-freely transplanted piece of head for increasing the overhang above the head.

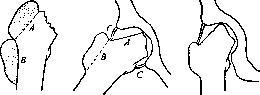
Figure 34. Plastic operation of Lexer for pseudarthrosis; i-before the operation; ii-after removal of the head; the neck is inserted into the acetabular cavity with interposition of fascia and fat between the head and acetabulum; the greater trochanter is transplanted lower; A-freely transplanted piece of head for increasing the overhang above the head.
If the head is not necrotic and the patient is not old, there are indications for bone synthesis with complete restoration of both function and anatomy of the femoral neck. Fragments of the femoral neck in pseudarthrosis are fixed with the help of an inserted wedge (Bolzune) into the acetabulum with interposition of fascia and fat between the head and acetabulum; the greater trochanter is transplanted lower according to Veau-Lamy; A-freely transplanted piece of head for increasing the overhang above the head. Heteroplastic (metallic nails, screws and others). A wedge can be introduced either extra-articularly from the area of the greater trochanter (Delbet, Lexer and others) or using the incision for arthrotomy of the hip joint (see above incision of Smith-Petersen, Goetz) (fig. 35). The negative side of the osteosynthetic method is indicated above. Braytsev succeeded in obtaining a good long-term result by using the following method: he scraped out the removed head and left only the shell of cartilage and a thin layer of bone and fitted it onto the neck. A short neck covered with articular cartilage resulted. The theoretical basis: the established fact that articular cartilage is nourished by the synovial fluid. One can speak of pseudarthrosis no earlier than a year, before this period one may be dealing with an unhealed fracture of the neck. Closed injuries include contusion and sprain (distorsion) of the hip joint. By contusion is meant injury to the internal parts of the joint, mainly the synovial membrane, by direct violence followed by effusion of blood into the joint. The articular cartilage can sometimes be damaged, torn, detached. Usually there is also contusion of the para-articular soft parts of the skin, a hematoma that gives a crunch on palpation. Movements, standing and walking are painful but possible. After hemarthrosis, hydrops of the joint with its instability often persists for a long time. X-ray film excludes fractures, with large hemorrhage it gives diffuse darkening. The greater trochanter is not displaced.-Distorsion of the hip joint is the result of indirect force, it is the result of action on the long lever arm, as in dislocation. In this case, the joint capsule can rupture, ruptures of the reinforcing ligaments (lig. Bertini and others) occur, para-articular large hemorrhages, sometimes also hemarthrosis. Diagnosis: tenderness on palpation of lig. Bertini or other torn ligament and with certain movements of the joint when the ligaments are tensed. In general, joint function is not impaired. The skin is usually unchanged.-Open injuries to the soft parts of the hip joint area are significant when the joint or bones or nearby pelvic organs are simultaneously injured, especially if the wounds are infected. The very deep position of the joint often makes correct diagnosis difficult.-Gunshot wound to only the soft tissues of the hip joint is conceivable only as a tangential wound. In all other cases, either the bone or, more rarely, only the joint capsule is injured. Injuries to bones vary in degree-from detachment of a small piece of the head to its complete comminution and of the pelvic bones with simultaneous injury to the perineum, pelvic organs, nerves and vessels. In gunshot wounds with a small zone of injury, diagnosis of injury to the hip joint is difficult. Cases without suppuration leave no consequences. Cases with suppuration give an extremely severe picture of suppurative coxitis; very severe pain, the joint capsule is stretched by purulent content but meets resistance in the huge muscular mass of the hip joint, hence high fever and pain. Langenbeck's symptom appears (the a. femoralis on the affected side is better palpated than on the healthy side, due to its elevation by the stretched hip joint). The prognosis is severe. The American war of 1866 gave 93% mortality, the Franco-Prussian-74.7%, the last imperialist war also a large number, although exact data are lacking. Long-term results (Erlacher) also indicate the severity of the disease: out of 100 cases-65 ankyloses of the joint, 14 unstable joints, 12 severe limitations of mobility, 7 minor limitations of mobility, 2 normal. For contaminated wounds, active intervention is necessary: primary treatment, resection of the joint, in more rare, very extensive injuries, disarticulation in the hip joint. In subsequent treatment, timely additional arthrotomies, counter-incisions, drainage which have to be kept for a long time. Fixation with splint, plaster cast or traction. Sometimes infection becomes noticeable only from the 5-6th day.
Figure 35.
Non-traumatic diseases of the hip joint. Acquired extra-articular diseases of the hip joint can involve the skin, subcutaneous tissue, fascia, muscles, vessels, nerves, mucous bursae and bones. Of the large number of mucous bursae in the hip joint area (from 14 to 21), the large bursa trochanterica under the tendon attachment of m. glutaei maximus, on the lateral posterior surface of the greater trochanter, bursa ilio-pectinea in front on lig. ilio-femorale under m. ilio-pectineus, often communicating with the joint, and bursa at the attachment of t. ilio-psoas to trochanter minor have great practical importance. Into these bursae hemorrhages, effusions can occur, they can be in a state of inflammation, arising both hematogenously and by transition from adjacent tissues. Hygromas, tuberculous, gonorrheic, purulent bursitis are observed. For differential diagnosis with lesions of the hip joint, strictly localized local tenderness, limitation only of those movements in the hip joint in which the bursa is compressed, but other movements in the hip joint remain free, e.g., in bursitis trochanterica-limitation of inward rotation, in burs, ilio-pectinea-limitation of extension, in burs, troch. minor (see above)-Ludloff's symptom. Treatment depending on etiology.-Of diseases of the fascia, the so-called snapping hip joint (hanche a ressort, schnappende Hüfte) deserves attention. The snapping phenomenon is clearly perceived by touch, and sometimes even by the ear, in a certain position of the thigh or with certain movements. At this, a jumping of a strong cord over the posterior edge of the greater trochanter is noticeable, accompanied by pain. The mechanism of this phenomenon depends on the shortening of tractus iliotibialis fasciae latae, to which m. tensor fasciae latae and m. glutaeus maximus are attached, or on the thickening of the greater trochanter. Thus the etiological factors are different: scar contraction of tractus Maissiatius, changes in the gluteus maximus muscle and m. tensor fasciae latae, periostitis, tumors in the area of the greater trochanter, bursitis of the greater trochanter bursa and others. The essence is that the thick fascial band with difficulty jumps over the posterior edge of the
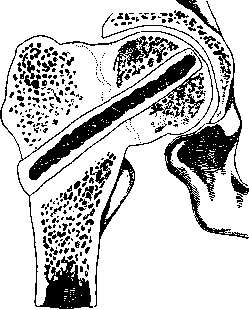
the greater trochanter. The snapping phenomenon is clearly perceived by touch, and sometimes even by the ear, in a certain position of the thigh or with certain movements. At this, a jumping of a strong cord over the posterior edge of the greater trochanter is noticeable, accompanied by pain. The mechanism of this phenomenon depends on the shortening of tractus iliotibialis fasciae latae, to which m. tensor fasciae latae and m. glutaeus maximus are attached, or on the thickening of the greater trochanter. Thus the etiological factors are different: scar contraction of tractus Maissiatius, changes in the gluteus maximus muscle and m. tensor fasciae latae, periostitis, tumors in the area of the greater trochanter, bursitis of the greater trochanter bursa and others. The essence is that the thick fascial band with difficulty jumps over the posterior edge of the
greater trochanter. The snapping phenomenon is clearly perceived by touch, and sometimes even by the ear, in a certain position of the thigh or with certain movements. At this, a jumping of a strong cord over the posterior edge of the greater trochanter is noticeable, accompanied by pain. The mechanism of this phenomenon depends on the shortening of tractus iliotibialis fasciae latae, to which m. tensor fasciae latae and m. glutaeus maximus are attached, or on the thickening of the greater trochanter. Thus the etiological factors are different: scar contraction of tractus Maissiatius, changes in the gluteus maximus muscle and m. tensor fasciae latae, periostitis, tumors in the area of the greater trochanter, bursitis of the greater trochanter bursa and others. The essence is that the thick fascial band with difficulty jumps over the posterior edge of the

greater trochanter. The snapping phenomenon is clearly perceived by touch, and sometimes even by the ear, in a certain position of the thigh or with certain movements. At this, a jumping of a strong cord over the posterior edge of the greater trochanter is noticeable, accompanied by pain. The mechanism of this phenomenon depends on the shortening of tractus iliotibialis fasciae latae, to which m. tensor fasciae latae and m. glutaeus maximus are attached, or on the thickening of the greater trochanter. Thus the etiological factors are different: scar contraction of tractus Maissiatius, changes in the gluteus maximus muscle and m. tensor fasciae latae, periostitis, tumors in the area of the greater trochanter, bursitis of the greater trochanter bursa and others. The essence is that the thick fascial band with difficulty jumps over the posterior edge of the
of the trochanter and gives the phenomenon of clicking. There are people who can cause this phenomenon voluntarily and without any pain, so the presence of the phenomenon does not yet indicate disease. Treatment depending on etiology. In surgical intervention, it is sometimes necessary to perform 'tractotomy,' chiseling off the protruding part of the greater trochanter, suturing the fascia to the greater trochanter and aponeurosis of m. vasti lateralis, etc. Intra-articular diseases (see Arthritis, Coxitis, Perthes' disease and Joints). Among non-infectious diseases, deforming arthritis (see) is relatively common, for which a more correct name, arthrosis deformans, has recently been proposed. This is a chronic degenerative process, which is characterized by a combination of atrophic and proliferative processes in the bones and articular cartilage, thickening and overgrowth of the articular villi, and the formation of marginal protrusions, cartilaginous and bony. Due to impaired nutrition, the cartilage softens and splits into separate fibers at the sites of greatest stress, the bone is polished and sclerosed. Individual ulcers and tubercles appear on the articular surface. Ultimately, the shape of the head changes sharply, taking on the most bizarre outlines. When this disease develops after 40 years, it is considered the result of tissue wear and is called malum coxae senile. However, similar forms are also found in significantly younger ages. The onset resembles chronic joint rheumatism, it develops (sometimes bilateral, often in people engaged in heavy physical work and exposed to cooling, more often in full, massive people. Pain appears, sensitivity to

Figure 37. Langenbeck's incision-spreading of muscles.
cooling, to load. Sometimes at the beginning of the disease there are no symptoms except very severe pain, which leads to recognizing neuralgia of the joint, coxalgia (coxodynia, coxagra) and differentiating it from sciatica. Later, limitations of movement join-first rotation outward and abduction, and then
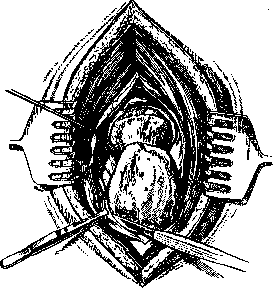
Figure 38. Exposure of the greater trochanter for subsequent temporary detachment with a chisel; according to Langenbeck, the trochanter is not severed.
flexion. The patient develops a jumping g; walking with small steps. X-ray film reveals changes in the shape of the head and marginal protrusions. Treatment: unloading and enhancement of local tissue nutrition. Hot sulfur baths, mud therapy, iodine; for unloading and rest-splint apparatus, cane,
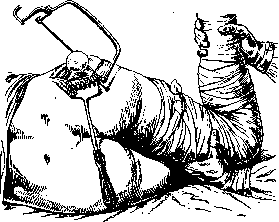
Figure 39. Operation according to Langenbeck-filing of the femoral head.
rubber soles, moderate mechanotherapy without load. In severe cases-arthrodesis or arthroplasty of the hip joint. Deforming arthroses of neurogenic origin in the most severe form occur as arthropathies, more often in tabes, less often in syringomyelia. _ Here a most varied picture of atrophic and hypertrophic processes is observed

Figure 40. Kocher's incision.
with displacement of the acetabulum, spontaneous dislocation and fractures, disappearance of the head and neck. New bone formation occurs not only in the joint but also on the articular capsule and surrounding ligaments and muscles. Clinical picture: extensive exudate, range of motion exceeding normal, movements are accompanied by clicking and crepitation with complete absence of pain. The patient walks freely but limps. X-ray film gives a typical picture of disfigured articular ends with extensive free bodies and disappeared areas of bone. A rare finding in the hip joint-osteochondritis dissecans (see Osteochondritis), and the diagnosis is complicated by the fact that it is very difficult to radiologically establish the joint mouse in the hip joint. The pathological processes listed above, both infectious and non-infectious, often result in either significant limitation of mobility or complete ankylosis, sometimes a sharply painful, non-functioning hip joint, sometimes a loose one. Often with this, there is also a faulty position of the thigh-adduction and flexion. A number of operations necessary to correct the position of the thigh are listed above (see above osteotomy). In a sharply painful as well as a loose joint, extra-articular arthrodesis (see Coxitis) or resection of the joint is often indicated. Technique of hip joint resection. The most common lateral and posterior incisions. The lateral incision of Langenbeck is made
Figure 41. Surgical anatomy, modified anatomy during the incision described by König: before dislocation of the head: 1-mm. gemelli and obturator internus; 2-piriformis; 3-posterior part of the joint capsule; 4-t. piriformis and spina iliaca posterior superior; 5-m. glutaeus medius and minimus; 6-m. glutaeus maximus; 7-m. glutaeus medius; 8-anterior part of the joint capsule; 9-trochanter.
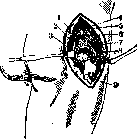
15 cm long, on the middle line of the thigh, and penetrates to the bone (fig. 36). With wide hooks, the muscles are spread apart, the anterior and posterior edges of the greater trochanter with the muscles attached to it are chiseled off (fig. 37, 38, 39). If the remaining part of the greater trochanter is removed, wide exposure of the joint is obtained, the head is dislocated and sawed off. Langenbeck does not sever the greater trochanter. Wreden's incision begins slightly below spina iliaca anterior superior, runs arcuoid to the posterior edge of the greater trochanter and bends slightly
downward. The exposed trochanter is driven upward and inward and is turned upward with the muscles. At the end of the operation, the greater trochanter is fixed in place with a nail or periosteal sutures.
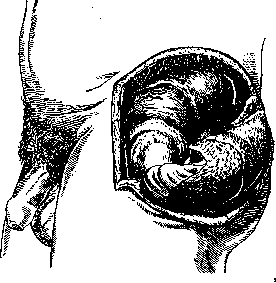
Kocher's method. Arcuate incision with convexity forward around the greater trochanter,
Figure 42. Hip joint exposed by incision according to Sprengel.
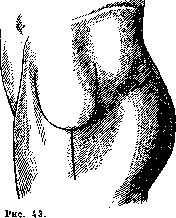
its upper half runs along the fibers of m. glutaei max. (fig. 40), the lower one along the axis of the thigh. M. glutaeus max. is split along the fibers, the greater trochanter is exposed. To the neck, one approaches in the interval between m. piriformis and m. glutaeus med. (fig. 41), the capsule is opened and the head is removed after dislocation.-Anterior incision of Sprengel-from spina iliaca posterior (fig. 42) along crista ilii to spina iliaca anterior, from here it turns at a right angle and ends at the base of the greater trochanter; after exposure of crista ilii, all muscles attached to os ilii are stripped off, and going along its surface, the acetabulum is opened after pulling the entire flap downward. Clapp (Klapp) makes the incision forward from the middle of crista ilii, 2 cm below it, the vertical part of the incision is carried around the trochanter
posteriorly, cuts through m. glutaeus med. and minim to the bone and strips it downward, and between the anterior edge of m. glutaei med. and tensor fasciae latae goes, bluntly separating, to the acetabulum and joint capsule. In bilateral ankylosis of the hip joint or multiple joint involvement in immobility of non-infectious origin, arthroplasty may be indicated, i.e., obtaining a movable
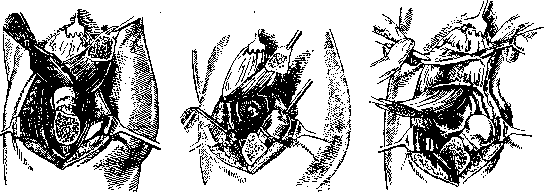
Fig. 45. Figure 46: Arthroplasty according to Murphy; cutting out a flap of fascia with fat from the skin flap on a pedicle.
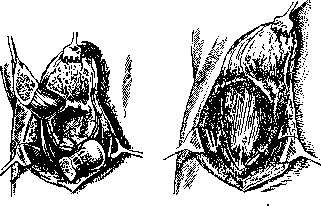
Figure 47
Figure 48
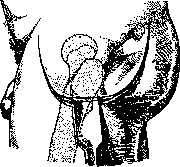
Figure 49. Arthroplasty according to Lexer;
skin incision and removal of the greater trochanter.
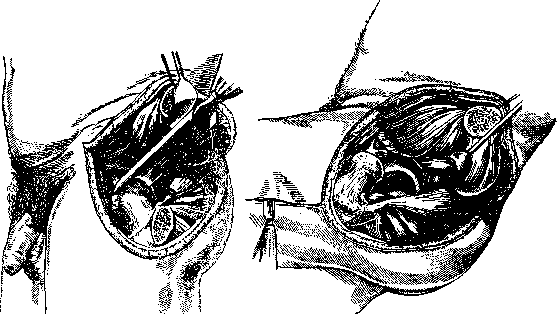
Fig 50
Figure 51. joint. Contraindications are usually tuberculosis and fresh purulent processes. Technique of the operation according to Murphy. ^The patient lies on the healthy side. A Y-shaped incision goes around the greater trochanter downward 5 cm, forward 4 cm and backward 2½ cm,
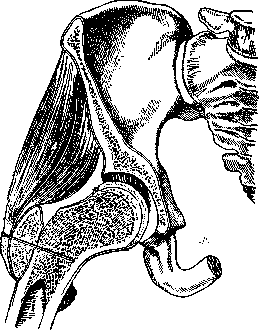
Figure 52. Arthroplasty according to Lexer; diagram of the final result of the operation. "vertically goes upward; from the lowest point of the U-shaped flap, a longitudinal incision along the thigh (fig. 43). The wound is spread with hooks; with a Gigli saw the greater trochanter is sawed off with attached muscles, the muscles are freed and the large flap is turned upward. Then with a wide chisel the ankylosis is separated, the head is dislocated (fig. 44). With the help of special instruments-a spherical trepan and a hollow rasp-the articular ends are modeled and smoothed (fig. 45). Then from the skin flap a flap of fascia with fat on a pedicle is cut out (fig. 46), placed in the newly formed acetabular cavity and sutured at the edges (fig. 47). The head is placed in the acetabulum, the greater trochanter is fixed in place. Layered sutures on the wound (fig. 48^. Plaster cast for 2½ weeks, then traction 3-4 weeks. Passive and active gymnastics.-Technique of arthroplasty according to Lexer. U-shaped incision (fig. 49, 50, 51, 52). The greater trochanter is severed with a chisel and turned upward with the muscles. Then, according to Murphy, only with free transplantation of fascia with fat. Postoperative treatment without immobilization, early movements. The above-mentioned incisions of Sprengel,

Figure 53. Saddle-shaped osteotomy of the femoral neck according to Rauh.
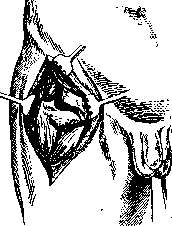
Figure 54. Saddle-shaped osteotomy according to Rauh.
Smith-Petersen and Clapp are also convenient for arthroplasty, allow for good inspection of the wound and are less traumatic. Patients are operated on in the supine position. In order to obtain slight flexion and extension of the hip joint, Paire (Raug) proposed (Figs. 53, 54) a simpler operation for ankylosis—a saddle-shaped osteotomy of the neck with a fascial graft between the fragments. Tumors. Intra-articular primary tumors of the hip joint are extremely rare, while para-articular ones are comparatively more common. On the bone in the area of the greater trochanter, enchondromas, chondrofibromas, myelogenous sarcomas, and exostoses are observed. From the soft parts, tumors of the skin, lymph glands, metastases of cancer of the uterus, penis, etc., angiomas, and neurofibromas may originate. Relatively often in the area of the greater trochanter, metastatic cancers originating from cancer of the breast, hypernephromas, and the thyroid gland are encountered. They begin with severe tearing pains when neither clinically nor radiographically can a tumor be established, and they quickly lead to spontaneous fractures, which clarify the diagnosis.
a. shnee.
Related articles
Mentioned in
Cite this page
“Hip Joint.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/hip-joint/