Human Muscles
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This part of the comprehensive encyclopedia article on human muscles details various anatomical entries, including the thyroepiglotticus, tibialis anterior, tibialis posterior, trachealis, and transversus abdominis muscles, outlining their origins, insertions, innervations, and variations.
Encyclopedia article (1928–1936)
HUMAN MUSCLES
No. Latin and Russian name. Synonyms. Form and position Origin and insertion Innervation and relation to segments Thyreo-epiglotticus (thyro-epiglottic M.). Syn.: thyreo-epiglotticus inferior, s. major, thyreo-membranosus inferior, dilatator vestibuli laryngis, stratum thyreo-membranosum. Part of m. ary-epiglottici, namely those fibers thereof which depart from the thyroid cartilage to the epiglottis Origin: thyroid cartilage - facies interna. Insertion: epiglottis N. vagus - n. laryngeus inferior, its g. anterior Thyreo-epiglotticus major and minor (greater and lesser thyro-epiglottic M.) Designation for separate parts of m. thyreo-epiglotticus N. vagus - n. laryngeus, its g. anterior Thyreo-hyoideus impar (azygos) (Soemmering) (superior unpaired thyro-hyoid M.). [Variation.] See m. thyreo-hyoideus Thyreoideus superior (par), s. minor (Morgagni) (superior paired thyro-hyoid M.). [Variation.] See m. thyreo-hyoideus 46) Thyreo-glossus lateralis (Fürbinger) (lateral thyro-lingual M.). [Variation.] See m. thyreo-hyoideus Thyreo-mediastinalis (Macalister) (thyro-mediastinal M.). [Variation.] See m. sterno-thyreoideus Thyreo-syndesmicus (Soemmering) (thyro-ligamentous M.). [Variation.] See m. thyreo-hyoideus Thyreo-triticeus (Macalister). [Variation.] See m. thyreo-hyoideus Tibialis anterior (anterior tibial M.). Syn.: tibialis anticus, hippicus, tibiaeus, catenae. Long prismatic muscle located on the lateral surface of the leg directly on the tibia. The muscle begins tendinously and already on the leg forms a flat, long terminal tendon passing to the dorsum of the foot. The muscle lies directly under the skin and fascia cruris, adjoining laterally first m. extensor digitorum longus, and then m. extensor hallucis longus and covering m. tibialis posterior - through membrana interossea Origin: femur - condylus lateralis and facies lateralis femoris, fascia cruris and membrana interossea down to its lower third. Insertion: First cuneiform and first metatarsal bones N. peronaeus profundus. LIV (v) and SI Tibialis posterior (posterior tibial M.). Syn.: tibialis, s. tibiaeus, s. tibicus posticus, s. internus, nauticus. Bipennate prismatic long M., located on the posterior surface of the leg under m. triceps surae on the interosseous membrane itself between m. flexor digitorum longus and flexor hallucis longus, partly covered by it. A flat, long tendon wraps around malleolus medialis (sulcus malleolaris) and through the medial border passes to the sole; here on the bones themselves the tendon forms a whole "bouquet" of tendons to the tarsal and metatarsal bones Origin: membrana interossea and adjacent parts of tibia and fibula down to the distal fourth and fascia cruris profunda. Insertion: navicular bone - tuberositas ossis navicularis, I (II and III) cuneiform bones - their plantar surface, talus - sustentaculum tali and II, III and IV metatarsal bones, basis ossis metatarsalis II, III and IV N. tibialis. LV and SI(II) Trachealis (Guiysse) (M. of the trachea.) Tunica muscularis parietis membranaceae of the windpipe Trachelo-mastoideus minor (Luschka) (trachelo-mastoid M.). Syn.: trachelo-mastoid accessorius - accessory tracheo-mastoid M.). [Variation.] See m. longissimus Tragicus (tragic M.). Syn.: tragi. Small plate of vertical, sagittal, frontal muscle fiberlets on the anterior surface of the tragus Origin: tragus - below tragus. Insertion: auricle - tragus, its outer surface N. facialis Blood supply Action Variations Pulls the epiglottis forward and thereby enlarges the entrance to the vestibulum laryngis Tarin describes two M.: the major from the lateral part of the thyroid cartilage and the minor from its medial part A. tibialis anterior and a. recurrens tibialis anterior Dorsiflexes (extends) the foot 1) The tendinous part of the M. may partially or entirely divide into two bundles; 2) a bundle may frequently depart from the M. to lig. cruciatum - this is m. tensor fasciae dorsalis pedis; 3) M. may attach to articulatio metatarso-phalangea; 4) may have a musculo-tendinous connection cm. extensor longus digiti II and m. extensor hallucis brevis A. tibialis posterior and a. peronaea Plantarflexes the foot, supinates and adducts 1) Absence of M. described; 2) the muscular part of the M. may double - m. tibialis secundus; 3) may attach: a) to II, III and IV os metatarsale; b) to os cuboideum; c) to m. flexor hallucis brevis; d) to the fifth toe; e) to the tendon of m. peronaei longi Function unknown No. Latin and Russian name. Synonyms. Form and position Origin and insertion Innervation and relation to segments Transversalis cervicis anticus (Luschka) (anterior transverse neck M.). Syn.: singularis in collo, transversarii cervicis anteriores, intertransversarius lateralis longus, transversarius cervicis medius. [Variation.] See ram. intertransversarii ventrales Transversus abdominis (transverse abdominal M.). Syn.: transversalis abdominis, abdominis intimus. M. represents a flat, wide plate of parallel transverse muscle fibers, having the shape of a triangle with a truncated apex; the apex is directed dorsally, and the base neutrally. The muscle is located on the lateral surface of the abdominal wall, in the space between the costal cartilages and the iliac bone, covered by both oblique M. of the abdomen and adjoining inwardly to fascia retroperitonealis and to the peritoneum. The muscle fibers posteriorly and anteriorly pass into tendinous aponeuroses. The posterior aponeurosis in the form of a quadrangular plate attaches to the transverse processes of the lumbar vertebrae. The anterior aponeurosis begins with a semilunar line (linea semilunaris Spigelii); in the upper two-thirds this aponeurosis goes to form the posterior wall of the rectus abdominis muscle sheath, and in the lower third - its anterior wall; therefore there is an oval cleft in it through which m. rectus abdominis passes - this is linea semicircularis Douglasii. At the place of its origin from the ribs, the M. is in close connection with m. transversus thoracis Origin: VII-XII cartilaginous ribs - their inner surface, fascia lumbodorsalis - deep leaf (lumbar vertebrae - their processus transversus), iliac bone - crista iliaca, its labium internum and lig. inguinale. Insertion: linea alba Spinal nerves nn.
intercostales (VII-XII) and nn. hypogastricus and io inguinalis. Dij - XII and Li-in Transversus auriculae (transverse muscle of the auricle). A long series of short parallel muscle fibers passing into tendinous fibers; located on the posterior surface of the auricle between eminentia conchae and the beginning of the cauda helicis. Orig.: auricle, its posterior surface - eminentia conchae. Ins.: auricle - its edge, beginning of the cauda helicis. N. facialis. Transversus colli (Luscka) (transverse muscle of the neck). [Variation.] See m. sterno-thyreoideus. Transversus glabellae (Rouge) (transverse muscle of the bridge of the nose). [Variation.] See m. orbicularis oculi. Transversus linguae (transverse muscle of the tongue). Syn.: stratum musculare linguae transversum. Numerous muscle bundles located in the thickness of the tongue in a transverse direction between the upper and lower longitudinal muscles of the tongue (m. longitudinalis linguae sup. and inf.). Orig.: septum linguae. Ins.: lateral margins and dorsum of the tongue. N. hypoglossus. Transversus manus (Halette) (transverse muscle of the hand). [Variation.] See m. adductor pollicis. Transversus menti (transverse muscle of the chin). [Very frequent variation, see also m. triangularis.] Transverse muscle fibers which run from the mandible in the extent between the tuberculum mentale and fossa digastrica of either side, terminating posteriorly along the linea submentalis. N. facialis. Transversus nuchae (Schultze) (transverse muscle of the nape). Syn.: corrugator posticus, occipitalis teres ac minor (Santorini), suboccipi- Orig.: linea nuchae superior and protuberantia occipitalis externa. Ins.: skin of the lateral part of the occiput. N. facialis. Blood supply. Action. Variations. A. circumflexa ilium interna and a. epigastrica inferior from a. iliaca externa and aa. musculo-phrenica and epigastrica superior from a. mammaria interna. Takes part in the formation of the abdominal press. 1) Complete absence of the muscle was observed very rarely; the portio inguinalis may be partially absent; 2) the number of costal bundles can vary, increasing up to seven and eight and decreasing to five; 3) fusion of the portio inguinalis of the muscle with m. obliquus internus abdominis is possible; 4) cases of partial doubling of the muscle have been observed; 5) the muscle can extend more caudally than the funiculus spermaticus even to the spina pubica, then it is pierced by the spermatic cord; 6) tendinous intersections have been described by only one author; 7) the muscle may be in connection with m. intercostalis intermedius and m. intercostalis internus, with the lateral fibers of m. recti abdominis; 8) additional bundles are frequently observed in the region of the fovea inguinalis: this is m. interfoveolaris (Hofmann) - bundles of muscle fibers along the lateral margin of m. recti abdominis, located ventrally from vasa epigastrica inferiora interna; these fibers can run from the lower surface of m. transversi abdominis or from its aponeurosis or between two layers of aponeurosis and can reach the lig. inguinale reflexum and lig. lacunare; the same muscle is described under other names (see m. interfoveolaris); m. tensor fasciae transversalis - muscle fibers which can run starting from lig. lacunare and up to the level of the linea semicircularis (Douglasii), and pass into the fascia transversalis, sometimes one can see that this muscle lies dorsally from vasa epigastrica inferiora interna; m. tensor laminae posterioris vaginae m. recti et fasciae transversalis abdominis (Gruber) - three bundles of muscle fibers which started tendinously on the upper surface of the fascia transversalis or, diverging cranially beneath the last bundle of m. transversi abdominis, ended in thin tendons in the fascia, with the medial ones reaching the linea semicircularis. Draws the helix closer to the auricle dorsalis profunda linguae. Protrudes the tongue upwards. The place to which the muscle attaches varies especially significantly; this can again be the linea nuchae superior, or the dorsal margin of m. sterno- No. No. Latin and Russian name. Synonyms. Shape and position. Origin and insertion. Innervation and relation to segments. Name and is o O o o. tails. [Frequent variation (27-72% according to various authors).] Muscle bundles of very different shape and size in the nuchal region under the skin. Transversus perinaei profundus (deep transverse perineal muscle). Syn.: transversus perinaei anterior, s. superior, constrictor urethrae membranaceae, ischio-urethralis, prostaticus internus, transverso-analis, triangularis perinaei, s. trigoni urethralis, Wilsoni, Guthrie. A muscular plate lying in the perineum between both leaves of the perineal fascia - fasciae diaphragmatis urogenitalis superioris and inferioris in the space of the trigoni urogenitalis. Muscle fibers which are stretched between the pubic bones - rami inferiores and intertwine with the fibers of the opposite side and with the fascia diaphragmatis urogenitalis. N. pudendus. Transversus perinaei superficialis (superficial transverse perineal muscle). Syn.: transversus perinaei medius, s. posterior, ischio-perinaealis, transverso-analis. A small muscular ribbon located in a transverse direction in the perineum immediately beneath the skin and fascia perinaei superficialis, along the posterior edge of the trigoni urogenitalis, between the ischium and the fibrous plate near the raphe bulbi; both antimeres pass into each other along the midline. Orig.: ischium - ramus inferior, its medial surface and fascia superficialis perinaei. Transversus radicis nasi (Eisler) (transverse muscle of the root of the nose). [Variation.] See m. orbicularis oculi. Transversus thoracis (transverse muscle of the thorax). Syn.: transversus anterior, s. pectoris, infracostalis anterior, sterno-costalis, triangularis sterni, intracostales. Represents a series of flat muscle bundles located on the medial surface of the sternum and cartilaginous ribs (II-VI), in an oblique direction in the upper bundles and in a transverse direction in the lower ones. Orig.: sternum - corpus sterni and processus xiphoideus; their posterior surface, cartilage of the VII (VI) rib. Ins.: II-VI costal cartilages. Nn. intercostales II-VI. Trapezius: pars descendens, pars transversa and pars ascendens (trapezius or hood muscle, capuchin muscle). Syn.: cucullaris, mensalis. Represents a large, flat, wide, triangular-shaped muscle located on the dorsal surface of the neck and chest, directly beneath the skin and superficial fascia of the back and neck. The truncated apex of the triangle is located laterally on the shoulder, and the wide base on the back along the midline on the vertebral column. According to the direction of the fibers, three portions are distinguished, between which, however, there are usually no definite boundaries. The origin of all portions is tendinous, but the so-called tendinous mirror (speculum Helmonti) is especially significant; the insertion is also tendinous. The muscle in turn covers mm. semispinalis capitis, splenius, levator scapulae, supraspinatus, rhomboideus, serratus posterior superior and partly mm. latissimus dorsi and infraspinatus. Orig.: pars descendens: occipital bone - linea nuchae superior, protuberantia occipitalis externa, lig. nuchae and I-IV vertebrae - processus spinosus; pars transversa: VII cervical and I (II) thoracic vertebra - processus spinosus; pars ascendens: II-XI (XII) thoracic vertebrae - processus spinosus. Ins.: pars descendens: clavicle - its lateral part; pars transversa: clavicle - extremitas acromialis, scapula - processus acromialis and spina scapulae, its upper edge; pars ascendens: scapula - trigonum spinae scapulae. N. accessorius Willisii and branches of the cervical nerves (II), III and IV. C(3), III and IV. Blood supply. Action. Variations. cleido-mastoidei or fascia superficialis colli, or m. occipito-parotideus, or m. auricularis posterior - this is m. auriculo-iniacus; the ventral end of the muscle can pass into the most cranial bundles of m. platysma or into atypical muscular formations which can run towards the os hyoideum into the pharynx or into m. sterno-cleido-mastoidei; once a muscle was found consisting of three portions, all of them originating from the protuberantia occipitalis externa and running: one together with m. auricularis posterior, the second to the fascia parotidea, and the third to the dorsal edge of m. sterno-cleido-mastoidei and terminating in the fascia superficialis colli. The existence of this muscle is not recognized by all anatomists (see
Le Double) 1) Sometimes the muscle may be absent; 2) the origin and insertion of the muscle may split into two muscles—this is the m. transversus perinaei alter; 3) they may originate on the lower leaflet of the perineal fascia, obturator fascia, and pelvic diaphragm fascia; 4) some bundles may pass: a) into the m. sphincter ani externus; b) into the m. bulbo-cavernosus; 5) it may receive accessory bundles from the aponeurosis of the gluteal muscles—this is the m. glutaeo-perinaealis 1) May be completely absent or replaced by tendinous fibers; 2) often breaks down into separate bundles or into two completely separate portions or separated from each other only cranially; 3) cranially may reach the seventh rib; 4) the number of bundles can range from six to two or even one; 5) from the second rib, a bundle may run across the third rib to the fourth; 6) a two-layered muscle on both sides was once observed; 7) bundles to the linea alba and the aponeurosis of the m. transversi abdominis were observed once A. transversa colli and a. transversa scapulae from the a. subclavia, rr. dorsales from the aa. intercostales, and a. occipitalis from the a. carotis externa All portions, acting together, bring the scapula closer to the spine; the pars descendens elevates the scapula and clavicle; the pars ascendens depresses the scapula 1) Often or even constantly both antimeres are unevenly developed, with the right half usually longer, wider, and more massive; 2) the origin on the occipital bone on one side can be strongly spread out or, on the other hand, completely absent when the muscle attaches to a tendinous arch stretched from the external occipital protuberance to the tendon of the m. sterno-cleido-mastoidei; 3) the origin of the cervical part may have a wide tendinous mirror—a cranial continuation of the rhomboideus (speculum Helmonti); 4) the origin of the partis ascendentis can be reduced to the eighth thoracic vertebra (even the fifth and fourth); 5) the caudal tendinous triangle can merge into the initial tendon of the m. latissimi dorsi; 6) attachment to the clavicle can decrease to complete disappearance; 7) elongation of this part until fusion with the m. sterno-cleido-mastoideus is more frequent; 8) a tendinous bundle from the ventral edge of the muscle to the sternum was observed once; 9) a transition of tendinous fibers into the m. deltoideus occurs; 10) division into two independent muscle layers has been observed; 11) division of the muscle into three independent muscles is possible; 12) the pars descendens occasionally has a tendinous inscription; 13) with athletic development, division into separate layers can occur; 14) this same stratification can explain the existence of mm. subcucullarium, which run from the speculum rhomboideum or from the spinous process of the third thoracic vertebra to the tendon of the m. trapezii; 15) bundles on the dorsal surface of the muscle as remnants of the dorsal musculature of the trunk—m. dorso-fascialis—were occasionally observed; these are bundles from the spinous processes of the thoracic vertebrae into the speculum rhomboideum; 16) a bundle of muscle fibers—m. subtrapezius—was also observed beneath the m. trapezius, which with good development originates from the lower surface of the tendon of the m. trapezii at the level of the fourth to sixth thoracic vertebrae (spinous process) and attaches to the base of the spine of the scapula A. labialis inferior and a. submentalis from the a. maxillaris externa and a. mentalis from the a. maxillaris interna Pulls the corner of the mouth backward and downward 1) The dimensions of the muscle can vary considerably; 2) sometimes it is divided into several portions, more often into three; 3) lateral bundles can pass into the facial part of the m. platysma; 4) individual bundles can pass into the mm. buccinator, zygomaticus, caninus, and quadratus labii superioris; 5) a connection of the medial bundle under the chin with the antimere in the form of a loop from one corner of the mouth to the other sometimes occurs—this is the m. transversus menti; but this same name is also sometimes assigned to a well-developed muscle that begins in the region of the medial tubercle and runs under the chin toward the opposite one. This m. transversus menti (Santorini) divides the two parts of the "double chin" A. circumflexa humeri posterior from the a. axillaris Extends the forearm at the elbow joint. The long head additionally moves the entire arm backward (extension) 1) Cases where the origin of the long head may extend along the axillary margin to the inferior angle or descend onto the humerus (shoulder capsule) are very rare; 2) the muscle may turn into a quadriceps, and an additional bundle may originate: a) from the coracoid process; b) from the shoulder bursa; c) from the tendon of the m. latissimi dorsi; d) from the surgical neck of the humerus; 3) the most frequent connection (even as a rule) of the long head with the tendon of the m. latissimi dorsi; in the presence of muscle fibers in this connection, the muscle is called the m. dorso-epitrochlearis; 4) closer relationships with the following muscles are observed: a) m. infraspinatus, b) teres major, c) anconaeus, d) flexor carpi ulnaris; 5) the muscle can also turn into a quadriceps as a result of the division of the long head into two muscles, if this division is complete—more often it is incomplete Pulls the uvula upward and backward A. circumflexa femoris lateralis and perforating branches from the a. profunda femoris Extends the leg at the knee joint 1) Its place of origin can vary greatly within the limits from the intertrochanteric line in cases of strong development and almost to the knee joint in the case of weak development; 2) closer relationships are possible: a) with the m. vastus medialis; b) vastus lateralis; c) rectus femoris, and d) articularis genu No. Name in Latin and Russian. Synonyms. Form and position Origin and insertion Innervation and relation to segments Vastus lateralis (lateral broad muscle of the thigh). Syn.: vastus externus, extensor cruris vastus.
Voluminous mass of muscle fibers directed obliquely from above downwards and from without forwards on the lateral surface of the thigh. The anterior surface in its lower part is aponeurotic and then passes into the terminal tendon, dividing into several bundles. Origin: femur-greater trochanter, its lateral surface, intertrochanteric line, gluteal tuberosity and linea aspera of the femur, its lateral lip. Insertion: patella-lateral and upper angle. Nerve: femoral nerve. Vastus medialis (medial broad muscle of the thigh). Syn.: vastus internus. Mass of muscle fibers directed obliquely from above downwards and from within forwards on the medial surface of the thigh. The tendon, which began inside the muscle, then emerges outward, lies adjacent to the tendon of the rectus femoris muscle, partly crosses it in front, and partly is attached to the patella. Origin: femur-linea aspera of the femur, its medial lip, below the intertrochanteric line, terminal tendons of the adductor longus and magnus muscles. Insertion: patella-medial margin, to the common tendinous expansion of the quadriceps femoris. Nerve: femoral nerve. Velum palatini et faucium See glosso-palatinus, levator veli palatini, pharyngo-palatinus, tensor veli palatini, uvulae muscles. Ventricularis (muscle of the laryngeal ventricle). Syn.: arytaeno-epiglotticus inferior, compressor sacculi laryngis, thyreo-arytaenoideus minor, s. superior, s. medialis. Muscle bundle of the arytenoid-epiglottic muscle. Origin: arytenoid cartilage-its lateral margin. Insertion: epiglottis-lateral margin of its lower part. Nerve: vagus nerve-inferior laryngeal nerve. Verticales linguae (vertical muscles of the tongue). Bundles of muscle fibers penetrating the entire thickness of the tongue from the upper to the lower surfaces of the tongue-in its free part. Origin: dorsum of the tongue. Insertion: lower surface of the tongue. Nerve: hypoglossal nerve. Wilsoni See sphincter urethrae membranaceae muscle. Vocalis (vocal muscle). Syn.: thyreo-arytaenoideus inferior major, s. internus, aryvocalis. Part of the muscle fibers of the thyroarytenoid muscle. Origin: thyroid cartilage-inner surface of the thyroid lamina. Insertion: arytenoid cartilage-vocal process. Nerve: vagus nerve-inferior laryngeal nerve, its anterior branch. Zygomaticus (zygomatic muscle). Syn.: zygomaticus major, malaris. Small flat ribbon of parallel muscle fibers on the lateral surface of the cheek, immediately beneath the skin and superficial fascia, in the space between the zygomatic bone and the angle of the mouth. Origin: zygomatic bone-malar surface of the zygomatic bone. Insertion: skin of the angle of the mouth. Nerve: facial nerve-zygomatic branches. Zygomaticus accessorius (accessory zygomatic muscle). [Variation.] See zygomaticus muscle. Zygomaticus minor=caput zygomaticum muscle quadrati labii superioris See quadratus labii superioris muscle. Ypsiloformis. [Variation.] See extensor pollicis longus muscle. Blood supply Action Variations. Lateral circumflex femoral artery and perforating branches from the deep femoral artery. 1) Usually the terminal tendon divides (Le Double, Gegenbaur, Poirier) into 2, sometimes into 4; their own muscle bundles approach them; sometimes they can be more independent and a doubling of the muscle results; 2) The muscle may be in closer relationships: a) with the rectus femoris muscle; b) vastus internus; c) vastus intermedius and d) articularis genu. Lateral circumflex femoral artery and perforating branches from the deep femoral artery. Extends the leg at the knee joint. 1) May sometimes double due to complete separation into two muscles; 2) some tendinous bundles may attach to the tibial tuberosity; 3) closer relationships are possible: a) with the rectus femoris muscle; b) vastus lateralis; c) vastus intermedius and d) articularis genu. Flattens the tongue. Elevates the angle of the mouth upwards and backwards. 1) Rarely absent altogether; 2) its size varies greatly; 3) its splitting into two, three and four portions is possible; 4) there may be an extension of the origin backwards onto the zygomatic arch, onto the temporal fascia, onto the galea; 5) cases of merging with the orbicularis oculi muscle, with the zygomatic head of the quadratus labii superioris muscle are observed; 6) connection with the facial part of the platysma muscle is possible-to this belongs the zygomaticus accessorius muscle; 7) the lateral bundle of the muscle may end: in the skin of the cheek, in the buccinator muscle or adjoin the caninus and triangularis muscles. B. Gindtse. 699
Human Muscles

Figure 1. Muscles above the hyoid bone: 1-mylohyoid muscle; 2-mandible; 3-platysma; 4-masseter muscle; 5-internal pterygoid muscle; 6-styloglossus muscle; 7-hyoid bone; 8-stylohyoid muscle; 9-digastric muscle; 10-omohyoid muscle; 11-sternohyoid muscle; 12-thyroid cartilage; 13-sternocleidomastoid muscle; 14-site of attachment of the digastric muscle.
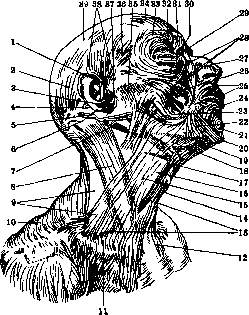
Figure 3. Superficial muscles of the head: 1-major helical muscle; 2-occipital muscle; 3-antitragus; 4-posterior auricular muscle; 5-transverse nuchal muscle (var.); 6-tail of the helix; 7-digastric muscle (posterior belly); 8-sternocleidomastoid muscle; 9-omotrapezoid triangle; 10-trapezius muscle; 11-omoclavicular triangle; 12 and 16-platysma; 13-omohyoid muscle; 14-thyroid cartilage; 15-apex of the carotid triangle (s. carotid fossa); 17-hyoid bone; 18-submandibular triangle; 19-digastric muscle (anterior belly); 20-transverse muscle of the chin; 21-mental muscle; 22-triangular muscle; 23-risorius muscle; 24-quadrate muscle of the lower lip; 25-orbicularis oris muscle; 26-zygomatic muscle; 27-nasal muscle (transverse part); 28-quadrate muscle of the upper lip; 29-orbicularis oculi muscle (palpebral part); 30-procerus muscle; 31-depressor supercilii muscle; 32-corrugator supercilii muscle; 33-orbicularis oculi muscle (orbital part); 34-frontal muscle; 35-parotideo-masseteric fascia; 36-auriculofrontal muscle; 37-tragus; 38-superior and anterior auricular muscles; 39-epicranial aponeurosis.
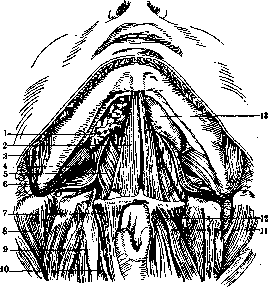
Figure 2. Muscles above the hyoid bone: 1-sublingual gland; 2-geniohyoid muscle; 3-masseter muscle; 4-internal pterygoid muscle; 5-hyoglossus muscle; 6-styloglossus muscle; 7-thyrohyoid muscle; 8-splenius capitis muscle; 9-longus capitis muscle; 10-sternothyroid muscle; 11-omohyoid muscle; 12-sternohyoid muscle; 13-tongue.
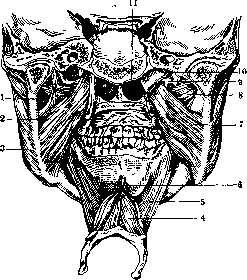
Figure 4. Masticatory muscles from behind (posterior part of the head removed by a cut passing through the temporomandibular joints; tongue, soft palate and pharynx with muscles removed): 1-sphenomandibular ligament; 2-internal pterygoid muscle; 3-masseter muscle; 4-geniohyoid muscle; 5-mylohyoid muscle; 6-genioglossus muscle; 7-internal pterygoid muscle; 8-external pterygoid muscle; 9-pterygospinous ligament; 10-auditory tube; 11-choanae. 701
Human Muscles
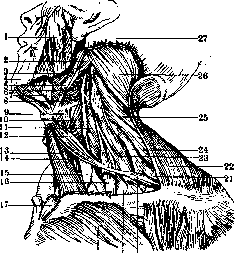
Figure 5. Muscles of the neck: 1-masseter muscle; 2-digastric muscle; 3-styloglossus muscle; 4 and 7-mylohyoid muscle; 5-stylohyoid muscle; 6-hyopharyngeal muscle; 8-hyoglossus muscle; 9-thyrohyoid muscle; 10-laryngopharyngeal muscle; 11-longus capitis muscle; 12 and 20-omohyoid muscle; 13-sternohyoid muscle; 14-sternothyroid muscle; 15-thyroid gland; 16-anterior scalene muscle; 17 and 27-sternocleidomastoid muscle; 18-pectoralis major muscle; 19-apex of the lung; 21-anterior serratus muscle; 22-trapezius muscle; 23-middle scalene muscle; 24-posterior scalene muscle; 25-levator scapulae muscle; 26-splenius capitis muscle.
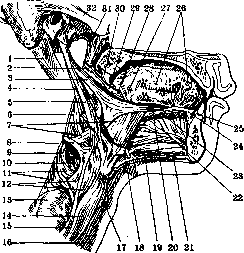
Fig. 7. Muscles of the tongue: 1-digastric muscle (posterior belly); 2-superior pharyngeal constrictor muscle; 3-styloglossus muscle; 4-stylopharyngeus muscle; 5-stylohyoid muscle; 6-middle pharyngeal constrictor muscle; 7-hyoglossus muscle; 8-hyoid bone; 9 and 17-thyroid cartilage; 10-hyothyroid membrane; 11-inferior pharyngeal constrictor muscle; 12-thyrohyoid muscle; 13-thyroid gland; 14-omohyoid muscle; 15-sternothyroid muscle; 16-sternohyoid muscle; 18-tendon of the digastric muscle; 19-geniohyoid muscle; 20-superior longitudinal muscle; 21-mylohyoid muscle (raphe); 22-genioglossus muscle; 23-inferior longitudinal muscle; 24-sublingual caruncle; 25-oral vestibule; 26-fungiform papillae; 27-foliate papilla; 28-glossopharyngeal muscle; 29-mylopharyngeal muscle (cut); 30-palatoglossal arch and muscle; 31-auditory tube; 32-zygomatic arch.
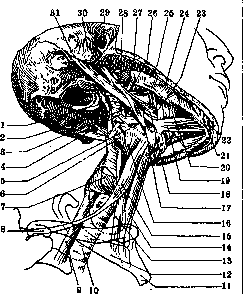
Figure 6. Deep muscles of the neck: 1-superior pharyngeal constrictor muscle; 2-pharyngeal raphe; 3-stylopharyngeus muscle; 4-middle pharyngeal constrictor muscle; 5-hyoid bone; 6-hyothyroid membrane; 7-inferior pharyngeal constrictor muscle; 8-omohyoid muscle; 9-esophagus; 10-trachea; 11-manubrium of the sternum; 12-first rib; 13-sternothyroid muscle; 14-sternohyoid muscle; 15-omohyoid muscle, superior belly; 16-thyrohyoid muscle; 17-stylohyoid muscle; 18-styloglossus muscle; 19-digastric muscle, anterior belly; 20-mylohyoid muscle; 21-triangular muscle; 22-mental muscle; 23-submandibular duct (Wharton's); 24-platysma; 25-masseter muscle; 26-internal pterygoid muscle; 27-parotid gland; 28-external pterygoid muscle; 29-external acoustic meatus; 30-styloid process; 31-digastric muscle, posterior belly.
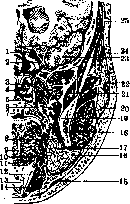
Figure 8. Frontal section of the head: 1-internal carotid artery; 2-sphenoidal sinus; 3-internal pterygoid muscle; 4-nasopharyngeal cavity; 5-levator veli palatini muscle; 6-tensor veli palatini muscle; 7-soft palate; 8-styloglossus muscle; 9-transverse muscle of the tongue; 10-hyoglossus muscle; 11-genioglossus muscle; 12-thyrohyoid muscle; 13-thyrohyoid ligament; 14-sternohyoid muscle; 15-platysma myoides; 16 and 17-submandibular gland; 18-cephalopharyngeal muscle; 19-mandibular ramus; 20-parotid gland; 21-temporal muscle; 22 and 24-epicranial aponeurosis; 23-temporal lobe of the brain; 25-pericranium. ____________.______ ______________ 703
Human Muscles
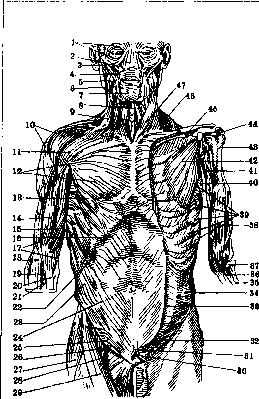
Figure 9.
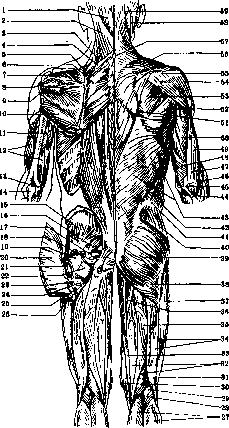
Figure 9. Muscles of the trunk from the front: 1-m. orbicularis oculi; 2-m. quadratus labii superioris; 3-m. zygomaticus; 4-m. caninus; 5-m. masseter; 6-m. triangularis; 7-m. quadratus labii inferioris; 8-m. sterno-hyoideus; 9-platysma; 10-m. deltoideus; 11-pars clavicularis m. pectoralis majoris; 12-pars sterno-costalis; 13-pars abdominalis; 14 and 15-m. biceps brachii: caput longum, caput breve; 16-costal margin; 17-m. brachialis; 18-m. brachioradialis; 19-tendon of m. biceps brachii; 20-lacertus fibrosus; 21-m. pronator teres; 22, 23 and 24-m. obliquus abdominis externus; 25-annulus inguinalis subcutaneus; 26-m. iliopsoas; 27-m. tensor fasciae latae; 28-m. pectineus; 29-m. sartorius; 30-lig. suspensorium penis; 31-lig. fundiforme penis; 32-m. cremaster; 33-aponeurosis m. obliqui abdominis externi; 34-m. obliquus abdominis externus; 35-radius; 36-insertion of m. brachialis; 37-capitulum radii; 38-m. brachialis; 39-m. serratus anterior; 40-m. latissimus dorsi; 41-m. coracobrachialis; 42-m. pectoralis minor; 43-surgical neck; 44-anatomical neck; 45-m. subclavius; 46-m. trapezius; 47-m. sterno-cleido-mastoideus. Figure 10. Muscles of the human body from behind: 1 and 59-m. semispinalis capitis; 2-m. splenius capitis et cervicis; 3-m. levator scapulae; 4-m. serratus posterior superior; 5-m. serratus anterior; 6-m. rhomboideus; 7-m. supraspinatus; 8-m. infraspinatus; 9-m. teres minor; 10-m. teres major; 11-m. coracobrachialis; 12-m. brachialis; 13-epicondylus medialis; 14 and 45-olecranon; 15-m. glutaeus minimus; 16-m. piriformis; 17-m. gemellus superior; 18-bursa trochanterica m. glutaei medii; 19 and 22-m. quadratus femoris; 20 and 21-m. glutaeus maximus and bursa trochanterica; 23 and 25-bursae gluteofemorales; 24-m. adductor minimus; 26-m. biceps femoris; 27-m. gastrocnemius; 28-m. plantaris; 29-planum popliteum femoris; 30-m. vastus medialis; 31-m. sartorius; 32-m. semimembranosus; 33-m. gracilis; 34-m. biceps femoris; 35-m. semitendinosus; 36-m. adductor magnus; 37-tractus iliotibialis (Maissiati); 38 and 39-m. glutaeus maximus; 40-m. glutaeus medius; 41-trigonum lumbale (Petiti); 42-m. obliquus abdominis externus; 43-m. latissimus dorsi; 44-m. anconeus; 46-mm. extensores; 47, 48, 49 and 50-m. triceps (47 and 49-caput laterale, 48-caput mediale, 50-caput longum); 51-m. rhomboideus; 52-m. teres major; 53-m. infraspinatus; 54-m. deltoideus; 55-spina scapulae; 56-m. trapezius; 57-vertebra prominens; 58-m. sterno-cleido-mastoideus.
HUMAN
MUSCLES
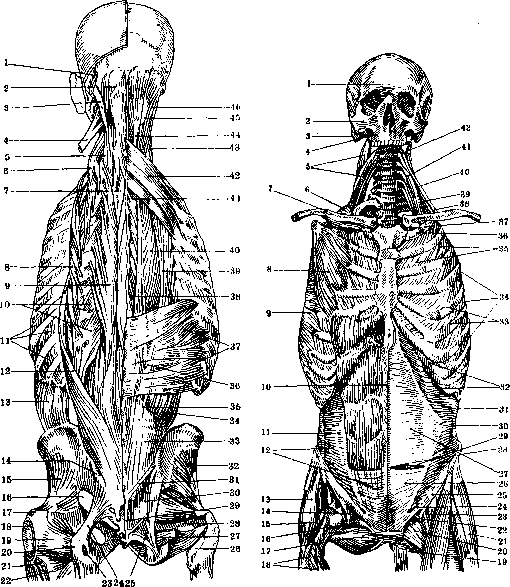
Figure 10.
Figure 11. Muscles of the back: 1-m. splenius capitis; 2-m. semispinalis capitis; 3-m. longissimus capitis; 4-m. splenius cervicis; 5-m. longissimus cervicis; 6-m. iliocostalis cervicis; 7-m. semispinalis dorsi; 8-m. iliocostalis dorsi; 9-m. longissimus dorsi; 10-mm. levatores costarum; 11-mm. intercostales externi; 12-m. iliocostalis lumborum; 13-m. obliquus abdominis externus; 14-spina iliaca posterior superior; 15-m. glutaeus minimus; 16-foramen ischiadicum majus; 17-trochanter major; 18-bursa trochanterica; 19-m. quadratus femoris; 20-tuber ischiadicum; 21-m. glutaeus maximus; 22-m. adductor minimus; 23-bursa ischiadica; 24 and 25-lig. sacrotuberosum; 26-m. obturator externus; 27-m. obturator internus; 28-m. piriformis; 29-lig. sacro-coccygeum posterius superficiale; 30 and 36-fascia lumbodorsalis; 31-origin of m. glutaei maximi; 32-m. glutaeus minimus; 33-tendon of m. longissimi and iliocostalis; 34-m. iliocostalis lumborum; 35-m. longissimus lumborum; 37-m. serratus posterior inferior; 38-m. spinalis dorsi; 39-m. iliocostalis dorsi; 40-m. longissimus dorsi; 41-m. semispinalis dorsi; 42-m. serratus posterior superior; 43-m. longissimus cervicis; 44-m. biventer; 45-m. complexus major; 46-m. longissimus capitis. Figure 12. Muscles of the trunk from the front: 1-frons; 2-arcus zygomaticus; 3-processus mastoideus; 4-maxilla; 5-m. levator scapulae; 6, 9, 33 and 34-m. serratus anterior; 7-clavicle; 8-m. pectoralis minor; 10-linea alba; 11 and 30-linea semilunaris (Spigeli); 12-m. transversus abdominis; 13-m. glutaeus medius; 14-lig. iliopectineum; 15-m. glutaeus minimus; 16-lacuna vasorum; 18-mm. vasti femoris; 17 and 19-m. obturator externus; 20-m. pectineus; 21-m. tensor fasciae latae; 22-lig. iliopectineum; 23-m. iliopsoas; 24-hiatus inguinalis abdominalis; 25-lig. inguinale; 26 and 31-m. transversus abdominis; 27-posterior wall of sheath of rectus muscle; 28-linea semicircularis; 29-m. rectus abdominis; 32-arcus costarum; 35-m. intercostalis externus; 36-sulcus venae subclaviae; 37-tuberculum scaleni (Lisfranci); 38-m. scalenus posterior; 39 and 40-m. scalenus medius; 41-m. scalenus anterior; 42-m. intertransversarius. Great Medical Encyclopedia, vol. XIX, 707.
HUMAN MUSCLES
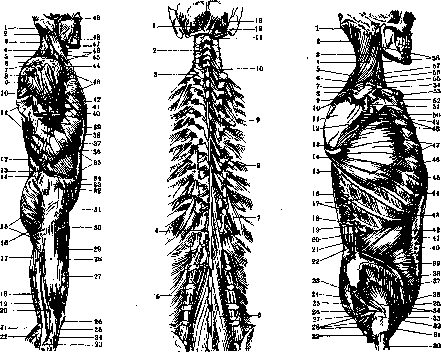
Figure 13.
Figure 14.
Figure 15.
Figure 13. Superficial muscles of the body: 1-m. semispinalis capitis; 2-m. sterno-cleido-mastoideus; 3-m. splenius; 4-m. levator scapulae; 5-m. scalenus medius; 6-m. trapezius; 7-acromion; 8-m. deltoideus; 9-m. infraspinatus; 10-m. teres major; 11-m. latissimus dorsi; 12-fascia lumbodorsalis; 13-trigonum lumbale (Petiti); 14-crista iliaca; 15-m. glutaeus maximus; 16-gluteal fold; 17-m. biceps femoris (caput longum); 18-m. semitendinosus; 19-m. semimembranosus; 20-m. biceps femoris (caput breve); 21-m. plantaris; 22-m. gastrocnemius; 23-capitulum fibulae; 24-condylus lateralis tibiae; 25-lig. patellae; 26-patella; 27-m. vastus lateralis; 28-tractus iliotibialis (Maissiati); 29-m. rectus femoris; 30-m. sartorius; 31-m. tensor fasciae latae; 32-spina iliaca anterior superior; 33-aponeurosis; 34-McBurney's point; 35-inscriptio II et III; 36-costal margin; 37-hypochondrium; 38-inscriptio I; 39-sheath of rectus muscle; 40-pars abdominalis m. pectoralis majoris; 41-m. brachialis; 42-m. biceps brachii; 43-m. pectoralis major; 44-clavicle; 45-m. sterno-hyoideus; 46-m. omo-hyoideus; 47-m. digastricus; 48-m. masseter; 49-m. temporalis. Figure 14. Deep musculature of the back: 1-m. rectus capitis posterior minor; 2-m. interspinalis; 3-m. rotator I; 4-m. rotator XII; 5-m. intertransversarius; 6 and 10-m. multifidus; 7-m. levator costae longus; 8 and 9-m. levator costae brevis; 11-m. obliquus capitis inferior; 12-m. rectus capitis posterior major; 13-m. obliquus capitis superior. Figure 15. Muscles of the trunk from the side: 1-m. semispinalis capitis; 2-m. splenius capitis; 3-m. splenius cervicis; 4-m. levator scapulae; 5-m. serratus posterior superior; 6-m. rhomboideus minor; 7-m. serratus anterior; 8-fossa supraspinata; 9-spina scapulae; 10-margo vertebralis scapulae; 11-fossa infraspinata; 12-margo axillaris scapulae; 13-angulus inferior scapulae; 14 and 53-m. serratus anterior; 15-m. serratus posterior inferior; 16-fascia lumbodorsalis; 17-mm. intercostales externi; 18-m. serratus posterior inferior; 19-XII rib; 20-fascia lumbodorsalis; 21-m. iliocostalis lumborum; 22-fascia lumbodorsalis; 23-foramen ischiadicum majus; 24-m. piriformis; 25-lig. sacrotuberosum; 26-lig. sacrospinosum; 27-foramen ischiadicum minus; 28-m. obturator internus cum gemellis; 29-m. quadratus femoris; 30-femur; 31-m. iliopsoas; 32-trochanter major; 33-tuberculum pubicum; 34-m. glutaeus minimus; 35-m. cremaster; 36-canalis inguinalis; 37-lig. Pouparti; 38-spina iliaca anterior superior; 39-crista iliaca (labium externum); 40 and 41-m. obliquus abdominis externus; 42 and 44-m. obliquus abdominis internus; 43-costal margin; 45-m. rectus abdominis; 46-V rib; 47 and 49-m. serratus anterior; 48-m. subscapularis; 50-tuberositas infraglenoidalis; 51-collum scapulae; 52-incisura clavicularis sterni; 54-acromion; 55 and 56-m. scalenus anterior; 57 and 58-m. scalenus medius. 709
HUMAN MUSCLES
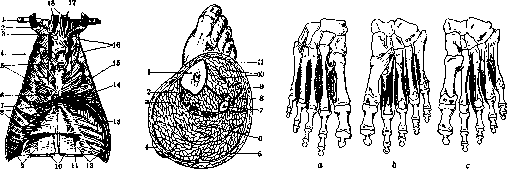
Figure 17.
Figure 18.
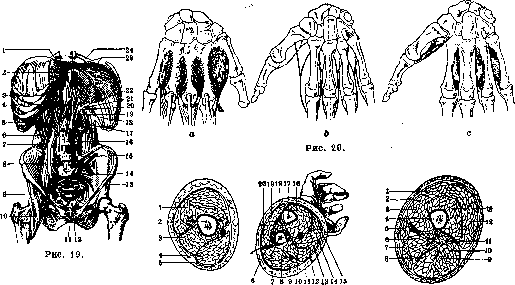
Figure 21.
Figure 16. Internal surface of the anterior thoracic wall: 1-clavicle; 2-first rib; 3-sternothyroid muscle; 4-internal mammary vessels; 5-transversus thoracis muscle; 6-xiphisternal process; 7-seventh rib; 8-transversus abdominis muscle; 9-internal oblique abdominal muscle; 10-rectus abdominis muscles; 11-groove for superior epigastric artery and vein; 12-transversus abdominis muscle; 13-costal part of diaphragm; 14-sternocostal triangle; 15-sternal part of diaphragm; 16-internal intercostal muscles; 17-sternothyroid muscle; 18-sternohyoid muscles. Figure 17. Cross-section of the leg: 1-tibia; 2-flexor digitorum longus muscle; 3-tibialis posterior muscle; 4-heel; 5-gastrocnemius muscle; 6-soleus muscle; 7-fibula; 8-peroneus longus muscle; 9-extensor digitorum longus muscle; 10-tibialis anterior muscle; 11-crural fascia. Figure 18. Interosseous muscles of the foot: a-dorsal interosseous muscles; b-the same from the plantar side; c-plantar interosseous muscles. Figure 19. Posterior wall of the abdominal cavity with the diaphragm: 1-opening for the inferior vena cava; 2-esophageal hiatus; 3-pleura; 4-aortic hiatus; 5-twelfth rib; 6-quadratus lumborum muscle; 7-psoas minor muscle; 8-psoas major muscle; 9 and 10-iliacus muscle; 11-symphysis; 12-site of attachment of pyramidalis muscle; 13-inguinal ligament; 14-anterior sacroiliac ligament; 15-iliolumbar ligament; 16-anterior longitudinal ligament; 17-intermediate crus; 18-lateral crus; 19-medial crus; 20 and 21-medial and lateral lumbocostal arches; 22-lumbocostal triangle; 23-central tendon; 24-eighth rib. Figure 20. Interosseous muscles of the hand: a-dorsal interosseous muscles; b-diagram of attachment of interosseous muscles; c-palmar interosseous muscles. Figure 21. Cross-section of the arm and forearm: 1-triceps muscle; 2-humerus; 3-brachialis muscle; 4-biceps muscle; 5-brachial fascia; 6-supinator muscle; 7-radius; 8-extensor carpi radialis longus and brevis muscles; 9-brachioradialis muscle; 10-pronator teres muscle; 11-antebrachial fascia; 12-flexor carpi radialis muscle; 13-palmaris longus muscle; 14-flexor digitorum sublimis muscle; 15-flexor carpi ulnaris muscle; 16-flexor digitorum profundus muscle; 17-ulna; 18 and 19-extensor carpi ulnaris muscle; 20-extensor digitorum communis muscle. Figure 22. Cross-section of the middle of the right thigh: 1-rectus femoris muscle; 2-fascia lata; 3-vastus medialis muscle; 4-femur; 5-sartorius muscle; 6-adductor magnus muscle; 7-gracilis muscle; 8-semimembranosus muscle; 9-semitendinosus muscle; 10 and 11-biceps muscle, long head, short head; 12-vastus lateralis muscle; 13-vastus intermedius muscle. 23
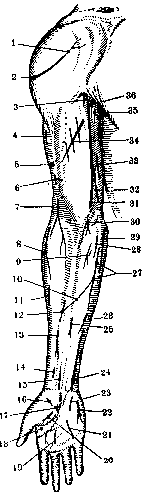
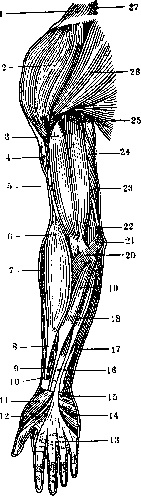
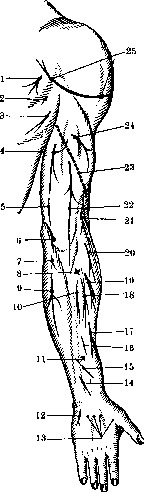
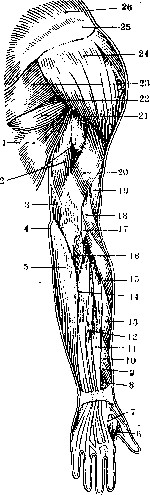
Figure 23. Points and lines of irritation of muscles and nerves of the arm from the front: 1 and 2-deltoid muscle; 3-coracobrachialis muscle; 4-triceps muscle, lateral head; 5-radial nerve; 6-brachialis muscle, lateral portion; 7-brachioradialis muscle; 8-extensor carpi radialis longus muscle; 9-flexor carpi radialis muscle; 10-flexor sublimis digiti III muscle, humeral head; 11-extensor carpi radialis brevis muscle; 12-flexor sublimis digiti III muscle, radial head; 13-flexor pollicis longus muscle; 14-pronator quadratus muscle; 15-median nerve; 16-abductor pollicis brevis muscle; 17-muscular branch of median nerve; 18-first dorsal interosseous muscle; 19-lumbrical muscles I and II; 20-flexor pollicis brevis muscle, superficial head; 21-flexor brevis digiti V muscle and fourth palmar interosseous nerve; 22-abductor digiti V muscle; 23-palmaris brevis muscle; 24-ulnar nerve; 25-distal belly of flexor sublimis digiti II muscle; 26-flexor sublimis digiti V muscle; 27-flexor sublimis digiti IV muscle; 28-palmaris longus muscle; 29-flexor carpi ulnaris muscle; 30-pronator teres muscle; 31-median nerve; 32-ulnar nerve; 33-triceps muscle, medial head; 34-biceps muscle; 35-triceps muscle, long head; 36-radial nerve. Figure 24. Muscles of the arm from the front: 1-trapezius muscle; 2-deltoid muscle; 3-biceps muscle; 4-triceps muscle, lateral head; 5-brachialis muscle; 6-brachioradialis muscle; 7-extensor carpi radialis longus muscle; 8-flexor digitorum sublimis muscle, radial head for digit III; 9-flexor pollicis longus muscle; 10-pronator quadratus muscle; 11-abductor pollicis brevis muscle; 12-flexor pollicis brevis muscle, superficial head; 13-palmar aponeurosis; 14-abductor digiti V muscle; 15-palmaris brevis muscle; 16-flexor digitorum sublimis muscle, digit IV; 17-flexor carpi ulnaris muscle; 18-palmaris longus muscle; 19-flexor carpi radialis muscle; 20-bicipital aponeurosis; 21-pronator teres muscle; 22-brachialis muscle; 23-triceps muscle, medial head; 24-triceps muscle, long head; 25-coracobrachialis muscle; 26-pectoralis major muscle; 27-omohyoid muscle. Figure 25. Points and lines of irritation of muscles and nerves of the arm from behind: 1-infraspinatus muscle; 2-teres minor muscle; 3-teres major muscle; 4-triceps muscle, long head; 5-triceps muscle, medial head, medial portion; 6-ulnar nerve; 7-flexor carpi ulnaris muscle; 8-supinator muscle; 9-flexor digitorum profundus muscle; 10-extensor carpi ulnaris muscle; 11-pronator quadratus muscle; 12-abductor digiti V muscle; 13-dorsal interosseous muscles I-IV; 14-extensor indicis proprius muscle; 15-extensor pollicis longus muscle; 16-extensor pollicis brevis muscle; 17-abductor pollicis longus muscle; 18-extensor digitorum communis and digiti V muscles; 19-extensor carpi radialis brevis muscle; 20-extensor carpi radialis longus muscle; 21-brachioradialis muscle; 22-anconeus muscle; 23-radial nerve; 24-triceps muscle, lateral head; 25-deltoid muscle. Figure 26. Muscles of the arm from behind: 1-latissimus dorsi muscle; 2-triceps muscle, long head; 3-triceps muscle, medial head; 4-medial epicondyle; 5-flexor carpi ulnaris muscle; 6-adductor pollicis muscle; 7-first dorsal interosseous muscle; 8-extensor pollicis longus muscle; 9-extensor pollicis brevis muscle; 10-abductor pollicis longus muscle; 11-extensor digitorum communis muscle; 12-extensor digiti V muscle; 13-extensor carpi radialis brevis muscle; 14-extensor carpi ulnaris muscle; 15-extensor carpi radialis longus muscle; 16-anconeus muscle; 17-lateral epicondyle; 18-brachioradialis muscle; 19-brachialis muscle; 20-triceps muscle, lateral head; 21-teres major muscle; 22-teres minor muscle; 23-infraspinatus muscle; 24-deltoid muscle; 25-acromion; 26-trapezius muscle. (To the illustration of the article Human Muscles.)
Figure 27. Points and lines of irritation of muscles and nerves of the arm from the inner side: 1-deltoid muscle; 2-coracobrachialis muscle; 3-biceps muscle; 4-pronator teres muscle; 5-brachioradialis muscle; 6-flexor carpi radialis muscle; 7 and 23-flexor sublimis digiti IV muscle; 8-flexor sublimis muscle, radial head for digit III; 9-distal belly of flexor sublimis indicis muscle; 10-median nerve; 11-abductor pollicis brevis muscle; 12-muscular branch of median nerve; 13-flexor pollicis brevis muscle; 14 and 15-adductor pollicis muscle; 16-lumbrical muscles I and II; 17-fourth palmar interosseous muscle; 18-palmaris brevis muscle; 19-abductor digiti V muscle; 20-ulnar nerve; 21-flexor sublimis digiti V muscle; 22-flexor digitorum profundus muscle; 24-palmaris longus muscle; 25-flexor carpi ulnaris muscle; 26-proximal belly of flexor sublimis indicis muscle; 27-median nerve; 28-ulnar nerve; 29-triceps muscle, medial head, medial portion; 30-triceps muscle, long head; 31-radial nerve. Figure 28. Muscles of the arm from the inner side: 1-biceps muscle; 2-palmar aponeurosis; 3-abductor digiti V muscle; 4-abductor pollicis brevis muscle; 5-flexor carpi ulnaris muscle; 6-flexor digitorum sublimis muscle; 7-palmaris longus muscle; 8-flexor carpi radialis muscle; 9-brachioradialis muscle; 10-pronator teres muscle; 11-brachialis muscle; 12-triceps muscle, medial head; 13-triceps muscle, long head; 14-coracobrachialis muscle; 15-teres major muscle; 16-pectoralis major muscle; 17-deltoid muscle. Figure 29. Points and lines of irritation of muscles and nerves of the arm from the outer side: 1-infraspinatus muscle; 2-teres minor muscle; 3-teres major muscle; 4-triceps muscle, lateral head; 5-radial nerve; 6-triceps muscle, medial head, lateral portion; 7-extensor carpi radialis longus muscle; 7a-supinator muscle; 8-extensor carpi ulnaris muscle; 9-extensor digitorum communis muscle; 10-adductor pollicis muscle; 11-first dorsal interosseous muscle; 12-extensor pollicis longus muscle; 13-pronator quadratus muscle; 14-extensor pollicis brevis muscle; 15-abductor pollicis longus muscle; 16-extensor carpi radialis brevis muscle; 17-brachioradialis muscle; 18-brachialis muscle, lateral portion; 19-biceps muscle; 20-deltoid muscle. Figure 30. Muscles of the arm from the outer side: 1-trapezius muscle; 2-deltoid muscle; 3-infraspinatus muscle; 4-teres minor muscle; 5 and 6-latissimus dorsi muscle; 7-triceps muscle, lateral head; 8-brachioradialis muscle; 9-triceps muscle, medial head; 10-anconeus muscle; 11-extensor carpi ulnaris muscle; 12-extensor digitorum communis muscle; 13-extensor pollicis brevis muscle; 14-dorsal carpal ligament; 15-lumbrical muscle I; 16-adductor pollicis muscle; 17-first dorsal interosseous muscle; 18-extensor pollicis longus muscle; 19-abductor pollicis longus muscle; 20-extensor carpi radialis brevis muscle; 21-extensor carpi radialis longus muscle; 22-brachialis muscle; 23-biceps muscle; 24-serratus anterior muscle; 25-pectoralis major muscle; 26-omohyoid muscle; 27-sternocleidomastoid muscle. (To the illustration of the article Human Muscles.)
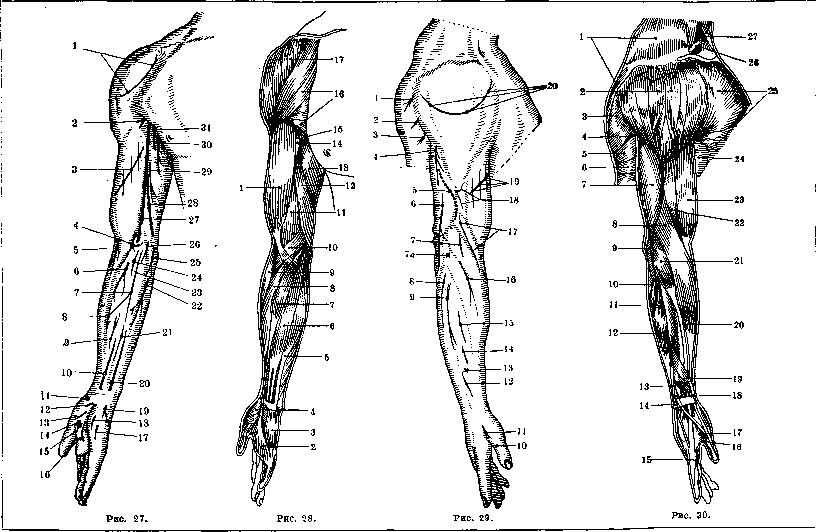
Figure 31. Lines of motor points of muscles and nerves of the leg from the front: 1-m. tensor fasciae latae; 2-m. triceps femoris; 3-m. rectus femoris; 4-m. vastus lateralis; 5-m. peronaeus longus; 6-m. extensor digitorum longus; 7-m. extensor hallucis longus; 8-m. extensor digitorum et hallucis longus; 9-m. abductor digiti quinti; 10-m. interossei; 11-m. abductor hallucis; 12-m. flexor digitorum longus; 13-m. soleus, portio tibialis; 14-m. tibialis anterior; 15-m. gastrocnemius, caput med.; 16-m. vastus medialis; 17-m. adductor magnus; 18-m. gracilis; 19-m. adductor longus; 20-m. pectineus; 21-m. sartorius; 22-n. femoralis; 23-m. ilio-psoas. Figure 32. Muscles of the leg from the front: 1-m. iliacus; 2-m. tensor fasciae latae; 3-m. sartorius; 4-m. rectus femoris; 5-tractus ilio-tibialis; 6-m. vastus lateralis; 7-patella; 8-tuberositas tibiae; 9-m. peronaeus longus; 10-m. extensor digitorum longus; 11-lig. transversum cruris; 12-lig. cruciatum pedis; 13-m. extensor hallucis brevis; 14-m. psoas minor; 15-m. psoas major; 16-m. pectineus; 17-m. adductor longus; 18-m. adductor magnus; 19-m. gracilis; 20-m. vastus medialis; 21-retinaculum patellae mediale; 22-pes anserinus (goose's foot); 23-m. gastrocnemius, caput mediale; 24-m. tibialis anterior; 25-m. soleus; 26-m. flexor digitorum longus; 27-m. extensor hallucis longus; 28-m. abductor hallucis. Figure 33. Lines of motor points of muscles and nerves of the leg from behind: 1-m. glutaeus medius; 2-m. glutaeus maximus; 3-m. semitendinosus, venter superior; 4-m. adductor magnus; 5-m. semitendinosus, venter inferior; 6-n. tibialis; 7-m. gastrocnemius medialis; 8-m. soleus, portio tibialis; 9-n. tibialis; 10-m. abductor digiti quinti; 11-m. peronaeus brevis; 12-m. soleus, portio fibularis; 13-m. gastrocnemius lateralis; 14-n. peronaeus communis; 15-m. biceps, caput breve; 16-m. semimembranosus; 17-m. vastus lateralis; 18-m. biceps, caput longus; 19-n. ischiadicus; 20-m. tensor fasciae latae. Figure 34. Muscles of the leg from behind: 1-m. obliquus abdominis externus; 2-spina iliaca posterior superior; 3-m. glutaeus maximus; 4-apex ossis coccygis; 5-m. adductor magnus; 6-m. biceps, caput longum; 7-m. semitendinosus, tendo intermedius; 8-m. gracilis; 9-m. semimembranosus; 10-m. plantaris; 11-m. gastrocnemius, caput mediale; 12-m. gastrocnemius, caput laterale; 13-m. soleus; 14-mm. peronaei; 15-m. flexor digitorum longus; 16-lig. laciniatum. (To the illustr. of the article Human Muscles.) Figure 31. Figure 32. Fig. 33. Figure 34. Figure 35. Lines of motor points of muscles and nerves of the leg from the inside: 1-n. obturatorius; 2-n. femoralis; 3-m. sartorius; 4-m. pectineus; 5-m. adductor longus; 6-m. rectus femoris; 7-m. gracilis; 8-m. vastus medialis; 9-m. tibialis ant.; 10-m. abductor hallucis; 11-n. tibialis; 12-m. flexor digit. longus; 13-m. soleus, portio tibialis; 14-m. gastrocnemius, caput mediale; 15-m. semimembranosus; 16-m. semitendinosus, venter inferior; 17-m. abductor magnus; 18-m. semitendinosus, venter superior; 19-m. glutaeus maximus and n. ischiadicus; 20-m. obturator int. and n. pudendus; 21-n. ischiadicus; 22-m. piriformis. Figure 36. Muscles of the leg from the inside: 1-m. iliacus; 2-m. piriformis; 3-m. obturator internus; 4-m. pectineus; 5-m. adductor longus; 6-m. rectus femoris; 7-m. sartorius; 8-m. vastus medialis; 9-pes anserinus (goose's foot); 10-tibia; 11-m. tibialis anterior; 12-m. plantaris; 13-lig. transversum cruris; 14-m. extensor hallucis longus; 15-m. psoas major; 16-lig. sacro-tuberosum; 17-m. glutaeus maximus; 18-m. adductor magnus; 19-m. semitendinosus; 20-m. gracilis; 21-m. semimembranosus; 22-m. semitendinosus; 23-m. gastrocnemius; 24-m. soleus; 25-m. flexor digitorum longus; 26-lig. cruciatum pedis; 27-m. abductor hallucis. Figure 37. Lines of motor points of muscles and nerves of the leg from the outside: 1-m. glutaeus medius; 2-m. glutaeus maximus; 3-m. vastus lateralis; 4-m. biceps femoris, caput breve; 5-n. peronaeus communis; 6-m. gastrocnemius, caput later.; 7-m. peronaeus longus; 8-m. soleus, portio fibularis; 9-m. peronaeus brevis; 10-m. extensor digitorum brevis; 11-m. abductor digiti quinti; 12-m. extensor digitorum longus; 13-m. tibialis anterior; 14-m. rectus femoris; 15-m. tensor fasciae latae. Figure 38. Muscles of the leg from the outside: 1-m. latissimus dorsi; 2-tractus supratrochantericus; 3-m. glutaeus maximus; 4-tractus ilio-tibialis; 5-m. biceps femoris; 6-m. gastrocnemius, caput laterale; 7-m. soleus, portio fibularis; 8-m. peronaeus brevis; 9-m. peronaeus tertius; 10-m. abductor digiti quinti; 11-m. obliquus abdominis externus; 12-m. tensor fasciae latae; 13-m. sartorius; 14-m. rectus femoris; 15-m. vastus lateralis; 16-retinaculum patellae laterale; 17-m. peronaeus longus; 18-m. tibialis anterior; 19-m. extensor digitorum longus; 20-lig. transversum cruris; 21-lig. cruciatum pedis; 22-m. extensor digitorum brevis. (To the illustr. of the article Human Muscles.)
Figure 39. Deep muscles of the forearm from the palmar side: 1, 3 and 39-m. brachialis; 2-tendon of m. bicipitis; 4-lig. collaterale laterale; 5-lig. annulare radii; 6-entrance to the canal for the radial nerve; 7-bursa bicipito-radialis; 8-tendon of m. bicipitis; 9-m. supinator; 10-m. flexor digit. sublimis; 11 and 41-m. pronator teres; 12-m. flexor digitorum sublimis; 13-radius; 14-m. flexor carpi radialis; 15-m. pronator quadratus; 16-lig. radio-carpeum volare; 17-m. abductor pollicis longus; 18-m. flexor pollicis brevis; 19-m. flexor pollicis longus; 20-m. interosseus ext. I; 21-m. lumbricalis I; 22-m. flexor digitorum sublimis; 23-m. flexor digitorum profundus; 24-decussation of the fibers of the deep tendon; 25-ligamenta capitulorum transversa; 26-vagina tendinum; 27-m. flexor digiti V; 28-m. opponens digiti V; 29-lig. piso-metacarpeum; 30-lig. carpi transversum; 31-lig. piso-hamatum; 32-os pisiforme; 33-tendon of m. flexor carpi ulnaris; 34-m. pronator quadratus; 35-ulna; 36, 37 and 38-m. flexor digitorum sublimis; 40-epicondylus medialis humeri; 42-lacertus fibrosus; 43-septum intermusculare mediale. Figure 40. Deep muscles of the forearm from the palmar side: 1-m. brachialis; 2-tendinous part of the canal for the entry of n. radialis; 3-bursa bicipito-radialis; 4-m. supinator; 5-m. flexor pollicis longus; 6-tendon of m. extensor carpi radialis longus; 7-m. pronator quadratus; 8-m. abductor pollicis longus; 9-tendon of m. brachio-radialis; 10-lig. carpi dorsale; 11-m. extensor pollicis brevis; 12-m. abductor pollicis brevis; 13-m. flexor pollicis brevis; 14-tendon of m. flexor pollicis longi; 15-m. adductor pollicis; 16-m. lumbricalis I; 17-tendon of m. flexor digitorum sublimis; 18-tendinous sheath; 19-ligamenta capitulorum transversa; 20-m. flexor digiti V; 21-m. opponens digiti V; 22-lig. carpi transversum; 23-m. abductor digiti V; 24-os pisiforme; 25-tendon of m. flexor carpi ulnaris; 26-m. pronator quadratus; 27-m. flexor digitorum profundus; 28 and 29-m. flexor pollicis longus; 30-epicondylus medialis humeri. Figure 41. Deep muscles of the forearm and hand from the dorsal side: 1-olecranon; 2-m. anconaeus; 3, 29 and 30-canal for n. radialis; 4-ulna; 5-m. extensor carpi ulnaris; 6-m. extensor digitorum communis; 7-septum intermusculare; 8-m. extensor pollicis longus; 9-m. extensor carpi ulnaris; 10-m. extensor indicis proprius; 11-entrance for the tendon of m. extensor indicis proprii; 12-lig. carpi dorsale; 13-tendon of m. extensor carpi ulnaris; 14-tendon of the extensor of the little finger; 15-aponeurosis; 16-m. interosseus ext. I; 17-m. adductor pollicis; 18-tendon of m. extensor pollicis longi; 19-tendon of m. extensor pollicis brevis; 20-canal for the tendon; 21-m. extensor carpi radialis longus et brevis; 22-m. extensor pollicis brevis; 23-m. abductor pollicis longus; 24-m. extensor carpi radialis brevis; 25-m. extensor carpi radialis longus; 26-radius; 27-septum intermusculare; 28-m. supinator; 31-lig. annulare radii; 32-epicondylus lateralis humeri; 33-m. brachialis. Figure 42. Attachment of the muscles of the forearm and hand from behind: 1 and 42-m. triceps; 2, 12, 27 and 33-line separating flexors from extensors; 3-m. flexor digitorum sublimis; 4-m. flexor carpi ulnaris; 5-m. flexor digitorum profundus; 6-ulna; 7-m. extensor carpi ulnaris; 8-m. extensor pollicis longus; 9-membrana interossea; 10-m. extensor indicis proprius; 11-m. extensor digitorum communis; 13-m. extensor digiti V proprius; 14-m. extensor carpi ulnaris; 15, 16, 19 and 22-mm. interossei externi III, IV, II and I; 17-m. lumbricalis III; 18-dorsal aponeurosis; 20-m. extensor pollicis longus; 21-m. adductor pollicis; 23 and 29-m. extensor pollicis brevis; 24 and 40-m. extensor carpi radialis brevis; 25 and 41-m. extensor carpi radialis longus; 26 and 31-m. abductor pollicis longus; 28-m. brachio-radialis; 30-mm. extensores carpi radiales; 32-m. pronator teres; 34-radius; 35 and 37-m. supinator; 36-m. anconaeus; 38-m. extensor carpi ulnaris; 39-m. extensor digitorum communis. (To the illustr. of the article Human Muscles.)
Figure 40.
Figure 39.
Figure 41.
Figure 42.
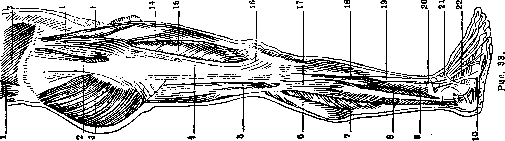
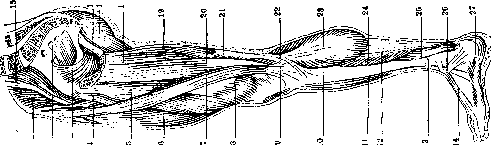
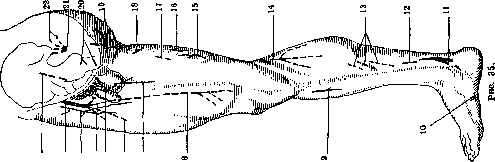
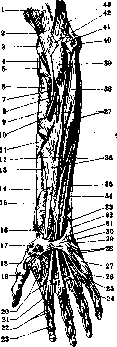
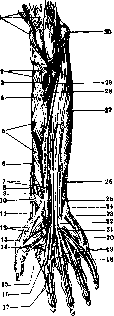
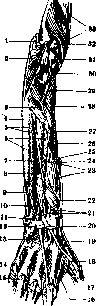
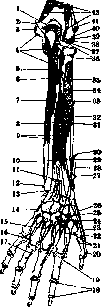
Figure 43. Attachment of muscles on the anterior surface of the forearm: 1 and 14 - m. brachio-radialis; 2 - m. extensor carpi rad. longus; 3 - m. extensor carpi rad. brevis; 4 - m. extensor digitorum comm.; 5 - m. supinator; 6 - m. biceps; 7 - radius; 8 - m. flexor digitorum sublimis (caput rad.); 9 and 47 - line separating flexors from extensors; 10 - m. pronator teres; 11 - membrana interossea; 12 - m. flexor pollicis longus; 13 - m. pronator quadratus; 15 - m. abductor pollicis brevis; 16 - m. flexor pollicis brevis, caput profundum; 17 - m. opponens pollicis; 18 - m. abductor pollicis longus; 19 - m. flexor carpi rad.; 20 - m. adductor pollicis; 21 - m. flexor pollicis brevis, caput prof.; 22 - m. abductor pollicis brevis; 23 - m. flexor pollicis longus; 24 - m. lumbricalis I and m. inteross. int. I; 25 - m. lumbricalis II; 26 - m. flexor digitor. sublimis; 27 - m. flexor digitor. profundus; 28 - m. interosseus int. II and m. lumbricalis III; 29 - m. interosseus int. Ill and m. lumbricalis IV; 30 - m. abductor digiti V; 31 - m. flexor digiti V; 32 - m. opponens digiti V; 33 - m. extensor carpi uln.; 34 - m. flexor digiti V brevis; 35 - m. abductor digiti V; 36 - m. flexor carpi uln.; 37 - ulna; 38 and 39 - m. flexor digit. profundus; 40 - m. pronator teres (caput uln.); 41 - m. flexor pollicis longus (caput uln.); 42 - m. flexor digitor. sublimis (caput uln.); 43 - m. brachialis; 44 - m. flexor digitorum sublimis, m. palmaris, m. flexor pollicis longus; 45 - m. flexor carpi rad.; 46 - m. pronator teres (caput humerale); 48 - m. brachialis. Figure 44. Muscles of the thigh on the medial side: 1 - spina iliaca ant. sup.; 2 and 10 - tendon of m. rectus femoris; 3 - bursa ilio-pectinea; 4 - trochanter major; 5 - lig. ilio-femorale; 6 - m. adductor minimus; 7 - trochanter minor; 8 - m. vastus lat.; 9 - m. vastus intermedius; 11 - m. sartorius; 12 - m. vastus med.; 13 - m. semimembranosus; 14 - origin of Hunter's canal; 15 and 16 - a. and v. femoralis; 17 - m. adductor magnus; 18 - m. adductor brevis; 19 - m. obturator ext.; 20 - m. pectineus; 21 - m. piriformis; 22 - plexus sacralis; 23 - promontorium; 24 - lig. ilio-lumbale. Figure 45. Group of adductor muscles: 1 - bursa ilio-pectinea; 2 - joint capsule; 3 - linea intertrochanterica; 4 - m. adductor minimus; 5 - m. articularis genu; 6 - bursa infrapatellaris; 7 - lig. collat. tibiale; 8 - retinaculum; 9 - epicondylus med.; 10 - bursa suprapatellaris; 11 - hiatus adductorius (Hunteri); 12 - membrana vasto-adductoria; 13 - m. adductor magnus; 14 - tuber ischiadicum; 15 - angulus pubicus; 16 and 18 - os pubis. Figure 46. Muscles of the pelvis and thigh from the front: 1 - tendon of m. psoas min.; 2 - m. quadratus lumborum; 3 - m. iliacus; 4 - spina iliaca ant. sup.; 5 - m. glutaeus minimus; 6 - joint capsule; 7 - caput ext. m. iliaci; 8 - junction of m. vastus lat. and intermedius; 9 - m. vastus lat.; 10 - incision of the tendon; 11 and 17 - retinaculum; 12 - lig. collateral fibulae; 13 - lig. capitulae fibulae; 14 - tuberositas tibiae; 15 - lig. patellae; 16 - tendon of m. gracilis; 18 - lig. collateral tibiale; 19 - m. vastus med.; 20 - m. articularis genu; 21 - m. gracilis; 22 - m. adductor magnus; 23 - m. adductor minimus; 24 - m. pectineus; 25 - cartilage; 26 - m. sacro-coccygeus ant.; 27 - m. piriformis; 28 - m. psoas major. Figure 47. Deep muscles of the posterior surface of the leg: 1 - tendon of m. semimembr.; 2, 3 and 4 - tendons of m. sartorius, m. gracilis, m. semitendinosus; 5 - bursa m. semitendinosi; 6 - m. flexor digit. longus; 7 - m. tibialis post.; 8 - tendinous membrane; 9 - tibia; 10 - groove for a. tib. post. and n. tibialis; 11 - tendon of m. tibialis post.; 12 - fascia cruris; 13 - malleolus med.; 14 - processus post. tali; 15 - lig. laciniatum; 16 - m. tibialis ant.; 17 - junctura tendinum; 18 - tendon of m. flexor digit. long.; 19 - tendon of m. flexor hall. longi; 20 - m. abductor hallucis; 21 - m. flexor hallucis brevis; 22 - mm. lumbricales; 23 - m. flexor digit. V; 24 - m. interosseus int. III; 25 - m. interosseus ext. IV; 26 - m. opponens digit. V; 27 - tuberositas ossis metat. V.; 28 - tendon of m. peronaei brevis; 29 - incision of lig. plant. long.; 30 - tendon of m. peronaei longi; 31 - m. quadratus plantae; 32 - origin of m. flex. digit. brevis; 33 - origin of m. abduct. halluc.; 34 - tuber calcanei; 35 - tendo calcaneus; 36 - tendon of m. plantaris; 37 - m. peronaeus brevis; 38 - m. flexor hallucis longus; 39 - m. peronaeus longus; 40 - groove for a. peronaea; 41 - septum intermusculare; 42 - canal for a. tibialis ant.; 43 - fibula; 44 - origin of arcus solei; 45 - m. popliteus; 46 - m. soleus; 47 - tendon of m. bicipitis. (To the illustr. of the article Human Muscles.)
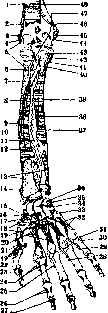
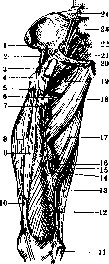
Figure 43.
Figure 44. Figure 45.
Figure 46.
Figure 47. Figure 48. Muscles of the hip joint and thigh on the medial side: 1 - bursa ilio-pectinea; 2 - spina iliaca ant.; 3 - m. glutaeus minimus; 4 and 8 - m. iliacus; 5 - spina iliaca ant. sup.; 6 - m. tensor fasciae latae; 7 - m. sartorius; 9 and 11 - m. rectus femoris; 10 - lig. ilio-femorale; 12 - m. vastus lat.; 13 - m. vastus med.; 14 - patella; 15 - m. sartorius; 16 - tendon of m. adductoris magni; 17 - m. semimembranosus; 18 - entrance to Hunter's canal; 19 and 20 - a. and v. femoralis; 21 - m. gracilis; 22 - m. adductor magnus; 23 - m. add. brevis; 24 - m. add. longus; 25 - m. pectineus; 26 - m. piriformis; 27 - m. obturator int.; 28 - plexus sacralis; 29 - promontorium; 30 - m. psoas. Figure 49. Attachment of muscles in the region of the hip joint from the front: 1 - m. quadratus lumborum; 2 - m. transv. abd.; 3 - m. obliquus abd. int.; 4 - m. obliquus abd. ext.; 5 - m. sartorius; 6 - m. iliacus; 7 - m. tensor fasciae latae; 8 - m. rectus femoris; 9 - m. glut. minimus; 10 - m. glut. medius; 11 - m. quadratus femoris; 12 - m. pectineus; 13 - m. vastus lat.; 14 - m. add. brevis; 15 - m. vastus intermedius; 16 - m. add. longus; 17 - m. articularis genu; 18 - m. vastus lat.; 19 - m. quadriceps femoris; 20 - tractus ilio-tibialis; 21 - m. biceps femoris; 22 - m. sartorius; 23 - m. semitendinosus; 24 - m. gracilis; 25 - m. add. magnus; 26 - m. add. minimus; 27 - m. obturator ext.; 28 - m. pyramidalis; 29 - m. rectus abd.; 30 - m. piriformis; 31 - m. obtur. int.; 32 - m. psoas major. Figure 50. Attachment of muscles in the region of the hip joint from behind: 1 - flexors of the thigh; 2 - m. obtur. int.; 3 - m. adductor minimus; 4 - m. add. brevis; 5 and 14 - m. add. magnus; 6 - m. vastus med.; 7 - m. gracilis; 8 - m. semimembranosus; 9 and 11 - m. popliteus; 10 - m. biceps femoris; 12 - m. gastrocnemius; 13 - m. plantaris; 15 - m. biceps (caput breve); 16 - m. vastus lat.; 17 - to adductor longus; 18 - m. glut. max.; 19 - m. iliacus; 20 - m. pectineus; 21 - m. psoas major; 22 - m. quadratus femoris; 23 - m. obtur. ext.; 24 - m. obtur. int. cum gemelli; 25 - m. piriformis; 26 - m. rectus femoris; 27 - m. glut. minimus; 28 - m. glut. med.; 29 - m. tensor fasciae latae; 30 - m. glutaeus max.; 31 - m. transversus abd.; 32 - m. obliquus abd. int.; 33 - m. quadratus lumborum; 34 - m. latissimus dorsi; 35 - m. ilio-costalis. Figure 51. Attachment of muscles on the anterolateral surface of the leg: 1 - m. tensor fasciae latae; 2 - m. biceps femoris; 3, 7 and 12 - m. peronaeus longus; 4, 6 and 10 - m. extensor digitorum longus; 5 - membrana interossea; 8 - m. peronaeus brevis; 9 - m. peronaeus tertius; 11 - tuber calcanei; 13 - m. flexor hallucis longus; 14 and 15 - m. tibialis post.; 16 and 18 - m. tibialis ant.; 17 - m. extensor hallucis longus; 19 - m. semitendinosus; 20 - m. gracilis; 21 - m. sartorius; 22 - tuberositas tibiae. Figure 52. Attachment of muscles on the posterior surface of the leg: 1 - m. semimembranosus; 2 - m. popliteus; 3 - m. flexor digitorum longus; 4 - membrana interossea; 5 - m. triceps surae; 6 - tuber calcanei; 7 - m. peronaeus brevis; 8 and 11 - m. tibialis post.; 9 - m. flexor hallucis longus; 10 and 13 - m. peronaeus longus; 12 - m. soleus; 14 - m. biceps femoris. Figure 53. Muscles of the posterior surface of the leg: 1 - m. semimembranosus; 2 - m. sartorius; 3 - tendon of m. gracilis; 4 - caput med. m. gastrocnemii; 5 - tendon of m. semitendinosi; 6 - m. popliteus; 7 - pes anserinus profundus; 8 - contour of m. gastrocnemii; 9 - tendon of m. plantaris; 10 - m. gastrocnemius; 11 - tendo calcaneus; 12 - canal for vessels and nerves; 13 - heel; 14 - lamina superficialis fasciae cruris; 15 and 17 - m. soleus; 16 - lamina profunda fasciae cruris; 18 - m. plantaris; 19 - caput lat. m. gastrocnemii; 20 - m. biceps femoris. (To the illustr. of the article Human Muscles.)
Figure 48.
Figure 49. Figure 50. Figure

Figure 52.
Figure 53.
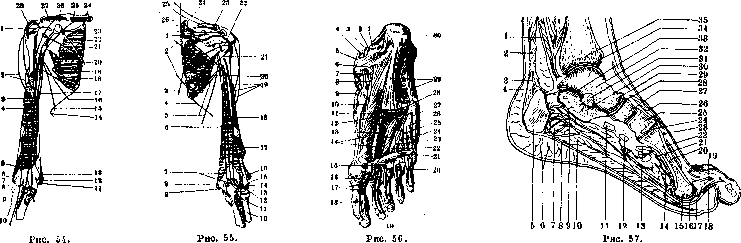
Figure 54. Attachment of the muscles of the arm and forearm (anterior view): 1-m. supraspinatus; 2, 27 and 28-m. deltoideus; 3-m. biceps; 4-m. brachialis; 5-m. extensor carpi radialis longus; 6-m. extensor carpi radialis brevis; 7-m. extensor digitorum communis; 8-m. supinator; 9-m. biceps; 10-m. brachio-radialis; 11-m. flexor digitorum sublimis; 12-m. flexor carpi radialis; 13-m. pronator teres; 14-m. serratus anterior; 15-m. latissimus dorsi; 16-m. pectoralis major; 17-m. coraco-brachialis; 18-m. teres major; 19, 22 and 24-m. serratus anterior; 20-m. pectoralis minor; 21-m. subscapularis; 23-m. omo-hyoideus; 25-m. pectoralis major; 26-processus coracoideus. Figure 55. Attachment of the muscles of the arm and forearm (posterior view): 1 and 3-m. trapezius; 2-m. rhomboideus; 4-m. serratus anterior; 5-m. latissimus dorsi; 6-m. triceps (caput longum); 7-m. triceps (caput mediale); 8-m. flexor digitorum sublimis; 9-m. flexor carpi ulnaris; 10-radius; 11-m. anconaeus; 12-m. supinator; 13-m. extensor carpi ulnaris; 14-m. extensor digitorum communis; 15-m. extensor carpi radialis brevis; 16-m. extensor carpi radialis longus; 17-m. brachio-radialis; 18-m. triceps (caput laterale); 19-m. deltoideus; 20-m. teres major; 21-m. teres minor; 22-m. infraspinatus; 23-m. supraspinatus; 24-m. serratus anterior; 25-m. trapezius; 26-m. levator scapulae. Figure 56. Deep muscles of the foot: 1-m. flexor hallucis longus; 2-processus posterior tali; 3-tendon of m. flexor digitorum longus; 4-m. tibialis posterior; 5-ligamentum laciniatum; 6-sustentaculum tali; 7-m. flexor digitorum longus; 8-m. tibialis posterior; 9-m. tibialis anterior; 10-m. abductor hallucis; 11-m. flexor digitorum longus; 12-m. flexor hallucis longus; 13-m. adductor hallucis; 14-m. flexor hallucis brevis; 15-m. interosseus externus II; 16-m. flexor digitorum longus; 17-ligamentum vaginale; 18-m. flexor hallucis longus; 19-m. flexor digitorum brevis; 20-chiasm of tendons of m. flexor digitorum longus et brevis; 21-m. adductor hallucis; 22-m. interosseus externus III; 23-m. interosseus internus II; 24-m. interosseus externus IV; 25-m. interosseus internus III; 26-m. flexor digiti minimi; 27-m. abductor digiti minimi; 28-m. flexor digitorum brevis; 29-aponeurosis plantaris; 30-tuber calcanei. Figure 57. Sagittal section of the foot: 1-lamina profunda fasciae cruris; 2-lamina superficialis fasciae cruris; 3-tendo calcaneus; 4-bursa tendinis calcanei; 5-tuber calcanei; 6-heel; 7-m. abductor hallucis; 8-aponeurosis plantaris; 9-m. quadratus plantae; 10-m. flexor digitorum brevis; 11-os cuboideum; 12-os cuneiforme III; 13-tendon of m. peronaeus longus; 14-m. adductor hallucis; 15-capitulum; 16-articulatio metatarso-phalangea; 17-tendon of m. flexor digitorum brevis; 18-tendon of m. flexor digitorum longus; 19-aponeurosis dorsalis; 20-os metatarsale II; 21-arcus plantaris (artery); 22-m. interosseus externus; 23-arteria arcuata; 24-articulatio tarso-metatarsea; 25-os cuneiforme II; 26-m. extensor hallucis brevis; 27-os naviculare; 28-articulatio talo-calcaneo-navicularis; 29-caput tali; 30-corpus calcanei; 31-ligamentum talo-calcaneum interosseum; 32-talus; 33-articulatio talo-calcanea; 34-articulatio talo-cruralis; 35-tibia. IV. Pathological anatomy of muscles. In view of the fact that smooth muscles do not constitute an independent system, but are everywhere an integral part of various organs (e.g., blood vessels, the digestive tract, the respiratory tract, the uterus, etc.), pathological changes in smooth muscles very rarely occur independently: in the vast majority of cases they are either common to changes in parenchymatous elements in general (e.g., atrophy in cachexia, fatty degeneration in anemia, intoxications, etc.) or are closely related to changes in the organ in which they are embedded. In this connection, it is very difficult and even inexpedient to consider the pathological anatomy of smooth muscles as a separate chapter: those pathological changes proper to smooth muscles that are common generally to changes in parenchymatous elements are described in the exposition of individual types of changes (e.g., atrophy, fatty degeneration, etc.), while those that are closely related to pathological changes in one or another organ are indicated in the exposition of the pathological anatomy of each of the corresponding organs. Tumors arising from smooth muscles, called leiomyomas [see the separate plate (volume XV, pp. 431-432), figure 5], which are rarely encountered in a pure form (i.e., as tumors consisting solely of smooth muscle fibers), have the significance of an independent change in smooth muscles (see also Myoma). The principal cadaveric change in muscles is rigor mortis, which is manifested in the fact that after death muscles undergo hardening, which fixes the body parts in the position in which rigor mortis finds them (see Cadaver). Rigor mortis may also occur in a fetus that has died intrauterinely. The heart muscles, the muscular tissue of the arteries, and the musculature of the stomach also undergo rigor mortis. Rigor mortis of the arrector pili muscles produces goose skin on the corpse. Cadaveric muscle rigor is of great importance in forensic medicine, as it can help determine the time elapsed from the moment of death to the time of examination of the corpse. Developmental defects of muscles concern mainly defects in the formation of a particular muscle or part of a muscle. The greatest importance among malformations of this kind belongs to developmental defects of the diaphragm. Among developmental defects of other muscles, the absence of the pectoralis major and minor muscles deserves mention, which is observed more often in males (5:1) and on the right side (4:3); sometimes there is simultaneously underdevelopment of the corresponding (2nd, 3rd, 4th) ribs and maldevelopment of the skin (its thinness, poor hair development, less commonly excessive hairiness). Less frequently encountered are defects of the deltoid, supra- and infraspinatus, latissimus dorsi, and trapezius muscles; together with the underdevelopment of the latter, there is also underdevelopment of the sterno-cleido-mastoideus muscle. Some forms of congenital torticollis (see) are based on the underdevelopment of one of the sternocleidomastoid muscles or its intrauterine change (sclerosis) on the basis of abnormalities in fetal position. Developmental defects of certain muscles of the abdomen, limbs, face, and orbit are described quite rarely. Among circulatory disorders in muscles, anemia may be of significance. [It goes without saying that those cases where, depending on general anemia or local causes (compression), muscles turn out to be bloodless and consequently pale and dry, do not present special practical interest.] If there has been a complete cessation of arterial blood flow to a specific group of muscles, this may result in complete bloodlessness, ischemia of the muscle tissue, and its necrosis; the muscle becomes clay-like, dry, and brittle. The causes of muscle ischemia are arterial embolism or, more frequently, traumatic damage to the arterial trunk; it should be noted that in general the arterial network in muscles is so rich in anastomoses that even with the complete occlusion of an artery, ischemia is not observed in the majority of cases; only upon the occlusion of the lumen of a large artery or in connection with the weakening of blood flow from subsidiary causes (shock) do ischemia and necrosis develop. Furthermore, in certain areas (e.g., in the region of the forearm flexors), ischemia and necrosis easily form in view of the weaker development of the anastomotic network here. Ischemia and necrosis of a muscle group underlie so-called ischemic contractures (see). Arterial and venous congestion of muscles, which alters the color shade of the muscular tissue, is of no special significance; according to the observations of Berger and Bier, in congestive hyperemia of muscles, hypertrophy of muscle fibers develops, which is subsequently replaced by some atrophy of them during the proliferation of interstitial connective tissue. Hemorrhage into a muscle occurs during trauma, during muscle ruptures depending on strong contractions (tetanus), and also in various hemorrhagic diatheses (blood diseases, infectious diseases, intoxications, scurvy, etc.); in some cases, the cause of hemorrhage is an alteration of the muscle tissue (waxy degeneration, for example, in typhoid fever, diverse inflammations of muscles). In hemorrhage into a muscle, the effused blood either permeates or infiltrates the muscle tissue, locating between the muscle fibers and their bundles, or forms a hematoma in the muscle (for example, in the rectus abdominis muscle). Edema in muscles manifests as dropsical impregnation of the interstitial connective tissue with the separation of muscle fibers, which in themselves do not present special changes. Frequently in muscle edema, an especially marked manifestation of edema is noted in the muscle spindles. Muscle necrosis may be the consequence of the cessation of arterial blood flow (see above), and is observed in traumatic muscle injury, in inflammations, and in the ingrowth of tumors into muscles. The origin of muscle necrosis developing as a result of concussions and contusions without *?4 disruption of the integrity of the integuments is not entirely clear; perhaps here too the main significance belongs to circulatory disturbance. Dead muscle tissue has a yellow, clay-like appearance, is dry, and lacks luster; necrosis of individual muscle fibers may be imperceptible to the naked eye. Under the microscope, necrotic muscle fibers turn out to be devoid of nuclei, whereas cross-striation is well preserved at first.
Subsequently, a breakdown of muscle fibers occurs, which at first may take the character of disc-shaped splitting (see below), and later takes the form of continuous granular disintegration. By means of an inflammatory reaction in the surroundings, the dead mass is resorbed and replaced by a scar. Muscle atrophy is expressed by the fact that the muscle fibers gradually become thinner and thinner: the diameter of the fiber decreases to 20-15-10 µ (normally about 20-50 µ), and with a severe degree of atrophy down to 5-3 µ and finally to the complete disappearance of the contractile substance. Transverse striation is preserved for a very long time, but disappears in a severe degree of atrophy; longitudinal striation lasts somewhat longer, which can sometimes still be seen in fibers even 3 µ thick. In some cases of atrophy, with a certain degree of thinning of the muscle fibers, dystrophic changes occur in them in the form of coarse-grained disintegration of the protoplasm, resembling waxy degeneration; sometimes one can see longitudinal splitting of the atrophying fibers. Not infrequently, with atrophy, a granular brown pigment appears in the muscle fibers, related to lipofuscin, and sometimes one can observe a finely granular pigment that gives a reaction for iron and is apparently a product of the metamorphosis of the hemoglobin of the muscle fibers. Glycogen begins to disappear from the muscle fibers only at a severe degree of atrophy. A very constant change in muscle atrophy is the amitotic division of muscle nuclei (so-called atrophic nuclear proliferation), which tends to increase as the muscle fibers thin out; at a severe degree of atrophy, the thinned muscle fibers are completely devoid of contractile substance, and their narrow sarcolemma tubes contain rows of proliferated muscle nuclei (Ger. Muskelkernschlauch). Not infrequently, the proliferated muscle nuclei are very pyknotic, arranged in groups in which they fuse with each other and form bizarre figures of "nuclear plates" (Ger. Kernplatten), staining sharply with nuclear dyes. The essence of atrophic proliferation of muscle nuclei is still not clear. Some view this phenomenon as a peculiar degeneration of nuclei, others attribute it to regenerative manifestations, still others connect it with the fact that with a decrease in the volume of the contractile substance, the nuclei of the muscle fibers find themselves in better nutritional conditions; finally, some see in the nuclear proliferation the phenomenon of the formation of special cells ("myoclasts") that resorb the contractile substance. Interstitial connective tissue in the places of muscle atrophy usually proliferates; sometimes, however, a proliferation of adipose tissue occurs, which can be so significant that the volume of the atrophied muscle may exceed the norm (atrophia lipomatosa, pseudohypertrophia). The distribution of atrophic changes in individual muscles is uneven; sometimes atrophy evenly affects all muscle fibers of a given muscle, in other cases atrophy extends to the entire muscle, but the change in muscle fibers is not expressed to the same degree in all fibers; sometimes there is a bundle-like distribution of atrophy, expressed by the fact that in some bundles atrophy affects the muscle fibers entirely, whereas other bundles are completely unchanged; finally, the preservation of individual muscle fibers intact among the atrophying muscle tissue can be observed. Very often, such surviving individual muscle fibers, groups of them, and entire bundles are in a state of hypertrophy, proving to be thickened up to 250 µ or more in fiber diameter. Muscle spindles usually do not participate in the atrophic process. Macroscopically, the atrophied muscle is flabby, paler than normal, and with a severe degree of atrophy begins to resemble fish meat; a yellow hue points to the proliferation of adipose tissue, brown to the presence of brown pigment in the atrophying fibers. The volume of atrophying muscles can be reduced to a very significant degree, while in other cases, due to the proliferation of adipose tissue in the atrophied muscle, it is preserved or even increased. The causes of muscle atrophy are diverse. Some of the atrophies develop as a consequence of diseases of the nervous system (peripheral nerves, spinal cord, or brain), others depend on joint lesions, still others are the result of inactivity or a partial manifestation of senile or marantic atrophy; sometimes muscle atrophy depends on one or another pressure on it (bandages, tumor, hematoma, etc.). In the desire to divide the various types of muscle injuries according to their causes, not a few classifications have been proposed. From the anat.-path. point of view, the following scheme by Meyenburg seems the most convenient: I. Neurogenic muscle atrophies: a) neural muscle atrophies, b) spinal muscle atrophies, c) cerebral muscle atrophies. II. Non-neurogenic muscle atrophies: a) disuse atrophies, b) arthrogenic muscle atrophies, c) myogenic and tenogenic muscle atrophies developing from 1) external causes, 2) internal (unexplained) causes (dystrophies). Regarding the distribution of muscle atrophy in the organism, it can be noted that many of them have only local significance, while others have the character of general diseases of the entire muscular system. Among the first of the neurogenic forms are those atrophies that develop in connection with lesions of individual nerves and limited lesions of the spinal cord or brain; among the non-neurogenic forms are arthrogenic atrophies developing in accordance with the affected joint, disuse atrophies depending on the lack of function, usually in one or another limb, and myogenic and tenogenic atrophies occurring with damage to the muscle itself and its tendon, with inflammation of the muscle, with pressure and other purely local causes. Among muscle atrophies of a general character from neurogenic forms are atrophies in multiple nerve lesions, progressive spinal muscle atrophy, and myatonia adjoining the latter; and from non-neurogenic forms are progressive muscle dystrophy and partly myasthenia. (For details of pathological and anatomical changes in these diseases, see Muscle atrophy in diseases of the nervous system, Dystrophy, Myatonia, Myasthenia.) Of the degenerations in muscles, waxy degeneration is very frequently present. Cloudy swelling, or granular degeneration, is also observed, in which the muscle fibers swell and become cloudy due to the appearance of a mass of small protein granules. Transverse striation disappears in this process. This type of degeneration occurs as a general change in severe infections and intoxications and as a local change in circulatory disorders and near inflammatory foci. Vacuolar degeneration in the form of the appearance of moisture droplets inside the muscle fibers occurs in inflammatory processes, edema, and various dystrophies. Amyloidosis of muscles in the form of local deposition of amyloid in the perimysium internum and in the sarcolemma is extremely rare. Disturbance of fat metabolism in muscles can manifest itself in the form of lipomatosis, i.e., the proliferation of adipose tissue among the muscle tissue, and degenerative obesity (fatty degeneration), expressed by the appearance of a mass of small fat droplets inside the muscle fibers. Lipomatosis can occur with general obesity, but most often it is observed with various muscle atrophies (see above). In degenerative obesity of muscles, occurring in infections (diphtheria), intoxications (phosphorus), severe anemias and cachexias (consumption), and often affecting predominantly the muscles of the diaphragm, small fat droplets can initially be arranged in rows along the transverse striation and longitudinal fibrils; in a severe degree of obesity, the droplets completely fill the entire muscle fiber and merge into larger droplets, with the transverse and longitudinal striations disappearing. All these phenomena often cover mainly those muscles that lie close to the main infectious focus (e.g., neck muscles in scarlet fever, diphtheria, abdominal muscles in typhoid fever). The degree of tension and activity (diaphragm, m. stapedius, m. tensor tympani) is also of importance, which explains the significant frequency of hearing anomalies after infections. In relation to degenerative obesity, it must be kept in mind that in normal muscle fibers, especially of the diaphragm, small fat droplets are found in one quantity or another as a physiological phenomenon. A peculiar degenerative change of muscle fibers is their fibrillar and disc-shaped splitting; in the former, the muscle fiber begins to split into primitive fibrils, and in the second, rarer one, into transverse discs corresponding to the transverse striation. These changes occur in various circulatory disorders, inflammation, muscle edema, and also in their mechanical injuries.
It is interesting to point out that Grawitz saw in the fibrillar cleavage of muscle fibers the signs of a transition of muscle fibrils into connective tissue fibers (formation of myogenic connective tissue).-All the above-named degenerative changes of muscles are reversible; even with significant degeneration of the contractile substance, the latter can recover from those remnants of sarcoplasm which are usually preserved near the muscle nuclei; only strongly expressed degeneration leads to complete disintegration and death of the fibers.-Petrification in muscles may be expressed in the deposition of lime into the interstitial connective tissue of the muscles (perimysium internum et externum) and into the muscle fibers. Cases of the first category relate either to local deposition of lime into scar-altered connective tissue or to a general disease of the lime metastasis type (see Calcareous deposits, metastases), in which a ubiquitous deposition of lime sometimes occurs (calcinosis universalis), in particular also involving the intermuscular connective tissue. The petrification of muscle fibers sometimes occurs in places of necrosis of muscle tissue, in areas of former inflammatory processes, in the vicinity of chronic abscesses (e.g., tuberculous); one must think that in all these cases petrification concerns dead muscle fibers; the deposition of lime into waxy-degenerated muscle fibers has also been described. Hypertrophy of muscles, which in its genesis in most cases refers to working hypertrophies, represents a true hypertrophy and usually has at its base only a thickening of the muscle fibers; most morphological and experimental studies establish that this thickening of muscle fibers is explained by an increase in the amount of sarcoplasm and the number of fibrils; the thickening of fibrils is rejected by the majority. The nuclei increase in volume, but the number of nuclei does not increase, due to which, compared to the volume of the muscle, the number of nuclei turns out to be relatively smaller than normal; if an increase in the number of nuclei is observed, this speaks in favor of existing atrophic changes in the hypertrophied muscle. Some describe in hypertrophy, besides thickening, also an increase in the number of muscle fibers by splitting the former; however, these data are not entirely convincing. It is interesting that muscle spindles do not participate in hypertrophy. Hypertrophy of muscles, besides cases of increased workload of certain muscle groups and besides compensatory hypertrophy of preserved individual muscle fibers and their groups in atrophies and in the death of part of the muscle tissue, is also observed as one of the manifestations of certain special diseases of muscle tissue (e.g., myotonia, myopathia hypertrophica). Regeneration of muscles can lead to complete restoration of muscle damage if the damage is small. With the formation of a significant defect in a muscle, incomplete regeneration takes place, expressed in the development of a connective tissue scar. Regeneration in muscles can proceed in a twofold manner depending on the nature of the damage to the muscle tissue. 1. In those cases where the contractile substance is damaged mainly, while the sarcoplasm and muscle nuclei are preserved to one degree or another, the restoration of the muscle proceeds by a way called the embryonic type of regeneration. It is observed in waxy and other degenerations of muscles, after frostbite, crushing, and after mild damage to muscle tissue. In these cases, the contractile substance of the muscle fiber dies, and the sarcoplasm disintegrates into lumps, partly containing nuclei (sarcolytes); simultaneously, the proliferation of muscle nuclei occurs (amitotic and mitotic). From these nuclei, surrounded by sarcoplasm, cellular elements of a rounded and spindle-shaped form with finely granular protoplasm are formed, called sarcoblasts; they are elements analogous to embryonic myoblasts. If the sarcolemma is intact, the formation of these elements occurs inside the sarcolemma tube, in which the sarcoblasts are arranged in rows, partly merging with each other to form multinucleated syncytial masses. If the integrity of the sarcolemma is violated, then the sarcoblasts (myoblasts) turn out to lie freely, and in such cases they appear in the form of epithelioid cells rich in finely granular protoplasm; subsequently, they take on an elongated form and, with the proliferation of nuclei, also form multinucleated protoplasmic strands (German: Myotubenkerne), on the periphery of which the sarcolemma membrane differentiates. In such protoplasmic multinucleated masses, lying either in the tubes of the former sarcolemma or outside them, fibrils differentiate, which gives longitudinal striation; then transverse striation appears, which results in the restoration of muscle fibers. Sometimes, due to the unfavorable influence of the environment in which regeneration is proceeding (inflammation, proliferation of connective tissue), the formation of muscle fibers from sarcoblasts does not occur, and the latter either degenerate and disappear or remain for a long time among the connective tissue in the form of multinucleated (giant) cells. 2. Another type of muscle restoration is called regeneration by budding; it takes place in those cases where significant damage to the muscle tissue occurs with a violation of the continuity of a number of muscle fibers. The defect formed as a result of the violation of the integrity of the muscle is filled with young connective tissue, while in the ends of the ruptured muscle fibers a bulbous bulging of the sarcoplasm occurs, containing a large number of proliferating muscle nuclei; these formations bulging from the ends of the muscle fibers, called muscle buds, grow into the connective tissue; in those cases where the separated ends of the muscle fibers are located not far from each other, the muscle buds growing toward each other can merge, thereby restoring the continuity of the muscle fiber. In the sarcoplasm of the merged muscle buds, fibrils and transverse striation differentiate. In many cases, however, when either the distance between the ruptured ends of the muscle fibers is significant or the connective tissue in the area of the defect has undergone scarring, such a fusion of muscle buds does not occur; a scar is formed, along the periphery of which the bulbous thickenings of muscle fibers with numerous nuclei are visible for a long time; on cross sections they appear in the form of multinucleated giant cells. Regeneration by the embryonic type can be combined with regeneration by budding; in such cases, both processes proceed side by side, and young muscle fibers formed from sarcoblasts can enter into connection with muscle buds.-Bone formation in muscles—see Myositis, myositis ossificans. Inflammation of muscles—see Myositis. Gas phlegmon of muscles—see Gas phlegmon. Of infectious granulomas, tuberculosis is not often encountered in muscles, and usually it is a question of the transition of the tubercular process to the muscles from bones, joints, pleura, skin, mucous membranes (for example, in the tongue). Under these conditions, tubercular nodes are formed among the muscles, undergoing caseous degeneration, and sometimes suppurating and giving tubercular abscesses; the latter can rupture and leave fistulas or descend and give cold abscesses. In other cases, tuberculosis in the muscle is of a more productive nature and is expressed in the development of fibrous tissue in the muscle, among which caseous tubercles are discovered. Rare cases of hematogenous tuberculosis of the muscle, representing hematogenous metastases (usually from the lungs and lymph glands), but often incorrectly called primary muscle tuberculosis, are characterized by the development of conglomerates of tubercles and tubercular infiltrates, among which the disintegration of muscle fibers occurs; hemorrhages in the vicinity of these foci are frequent. According to Saltykov, the epithelioid cells of the tubercles can have a muscular origin.—Syphilis affects muscles in the late period of the disease and manifests itself in the formation of gummas in the muscles or the development of fibrous myositis. Gummas in muscles can reach significant volume and often appear in the form of large tumors that bulge under the skin; they are prone to disintegration and in these cases form deep crater-shaped ulcers, subsequently healing with strongly retracted scars. Syphilitic fibrous myositis presents a picture often coinciding with banal, nonspecific fibrous myositis; sometimes miliary gummas and obliterating vasculitis are found in the connective tissue. Often fibrous myositis and gumma are combined with each other; in such cases, among the field of fibrous connective tissue, a dry yellowish-gray caseous focus with map-like edges is visible. Most often, syphilis affects the muscles of the shoulder, especially the biceps muscle, the masticatory muscles, the tongue, the muscles of the neck, the muscles of the back.—Granuloma in leprosy can spread to muscles from the skin. Tumors in muscles are relatively rare; at the same time, in relation to neoplasms developing primarily in muscles, one must keep in mind that tumors originating from the interstitial connective tissue, i.e., from the perimysium, are more frequent here, whereas tumors whose source is the muscle fibers themselves are very rare.
The former include fibromas, developing most frequently as a dense node from the fascia of the rectus abdominis muscle, intramuscular and rarer intermuscular lipomas, arising most often in the back and lower limb muscles, myxomas, angiomas, and lymphangiomas; chondromas are rarer. Sarcomas of the muscles are encountered more frequently than the above-listed benign tumors and can arise from the intermuscular and intramuscular connective tissue; most often they belong to round-cell, spindle-cell, and polymorphous-cell sarcomas; besides, liposarcomas, myxosarcomas, and angiosarcomas are encountered. All these tumors during their growth push apart and atrophy the muscle tissue; sarcomas in addition by their infiltrative growth destructure and destroy it. Tumors arising from striated muscle tissue, i.e., having as the source of their development striated muscle fibers, can have a various character. First of all, it can be pointed out that neoplasms consisting of striated muscle fibers (of embryonic type) or having these fibers as one of the constituent parts of the tumor, are most frequently encountered precisely outside the muscle tissue, i.e., where there are no voluntary striated muscles. These benign rhabdomyomas and malignant rhabdomyosarcomas (see Myomas), usually discovered along the course of the urogenital tract and explained as a consequence of maldevelopment of tissues, have no relation to tumors developing from voluntary muscles. From the muscular elements of voluntary muscles, the development of tumors of a twofold kind is possible. 1. Myoblastomyomas, i.e., myomas from myoblasts, tumors consisting of large rounded cells with delicately granular, slightly basophilic protoplasm; it was clarified by Abrikosov in 1925 that these cells represent myoblasts, on the basis of which this above-indicated name was given to these tumors by him, which is at the present time already generally accepted. Sometimes the cells of tumors have a slightly elongated oval form and differentiation of fibrillarity and cross-striation is visible in them. The formation of multinucleated strands with the same differentiation can also be observed. Myoblastomyomas represent benign tumors, most frequently developing in the muscles of the tongue, less often in other muscles; one can think that they can originate from myoblasts appearing in the order of regenerative processes in muscles. Analogous tumors developing in the skin can be a product of embryonic abnormalities during the development of the cutaneo-muscular layer. - 2. Rhabdomyosarcomas, or malignant rhabdomyomas, - tumors from polymorphic, predominantly spindle-shaped cells; fibrillarity and cross-striation are visible in some of them. The course of rhabdomyosarcomas is malignant, similar to the course of sarcomas. Abrikosov's idea that these tumors can also originate from myoblasts, i.e., represent myoblastosarcomas, has been confirmed at the present time by Meyenburg's case, in which transitions from myoblastomyoma to rhabdomyosarcoma were present in a tumor of the tongue. It must be noted that in these tumors cells with fibrillarity and cross-striation can often not be found; in such cases it can easily happen that this muscular tumor will be defined as a sarcoma. Morphologically, rhabdomyosarcomas originating from voluntary muscles are very similar to the same tumors developing extra-muscularly. - Treatment is surgical. Of the tumors secondarily affecting muscles, cancer has the greatest importance, which not infrequently spreads to muscles; e.g., cancer of the breast to the pectoral muscle, cancer of the uterus, cancer of the rectum to the muscles of the pelvis and perineum; in the exact same way other malignant tumors can also spread to muscles. Metastases of tumors (cancer, sarcomas, melanomas) in muscles are comparatively rare. A tumor secondarily growing in muscles causes degeneration, atrophy, and destruction of the muscle tissue, wherein the cells of the tumor (most often cancer grown into the muscle) can penetrate inside the sarcolemma tubes and grow inside them, destroying the contractile substance.
A. Abrikosov. Parasites of the muscles. Parasites can be localized in the thickness of the muscle fibers themselves or be located in the connective tissue layers. To the former belong sarcosporidia, forming Miescher's sacs (Miescher) or Rainey's bodies (Rainey). More than 25 species of mammalian sarcosporidia are known (e.g., Sarcocystis Lindemanni of man, S. tenella of the sheep); sarcosporidia also parasitize birds and reptiles. Myxosporidia can be present in the muscle fibers of fishes (e.g., Myxobolus Pfeifferi). Leishmania-like forms of Trypanosoma Cruzi also occur in muscle fibers. Larvae of Trichinella spiralis become encysted in muscle fibers. In the places of localization of parasites, the muscle fibers are strongly altered - increase in volume, are replaced by parasites, and degenerate. In the connective tissue layers of muscles are localized cysticercus cellulosae of Taenia solium and T. saginata, echinococcus, cysticercus (Sparganum) Diphyllobothrium Mansoni, Sparganum prolifer, Coenurus glomeratus, and others (various mammals). Muscles can undergo deep destruction by larvae of parasitic (e.g., Wohlfahrt fly) and non-parasitic flies upon phenomena of tissue myiasis (see). Lit. - see literature to the article Muscular System.
Related articles
Mentioned in
Cite this page
“Human Muscles.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/human-muscles/