Trachea
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Great Medical Encyclopedia covers the anatomy, development anomalies, inflammatory conditions, tuberculosis, syphilis, benign and malignant tumors, and stenoses of the trachea.
Encyclopedia article (1928–1936)
TRACHEA (from Greek trachys — rough), windpipe. — A n a t o m y. The trachea, being the direct continuation of the larynx, represents the initial segment of the lower respiratory tract in the form of a cylindrical tube 11–13 cm long from the larynx to the bifurcation; it consists of 16–20 tracheal cartilaginous (hyaline) rings connected to each other by dense fibrous tissue (see figure). Posteriorly, the cartilage rings do not completely close, and the tracheal wall is formed here of connective tissue and smooth muscle. This part of the trachea is adjacent to the esophagus along its entire length. In a normal state in an adult, the trachea is located from the CVII or DI to the DV vertebra. The connective tissue surrounding the trachea appears loose and allows large displacements during movements of the larynx and trachea. In its upper part, the trachea lies closer to the surface of the neck; as it descends downwards, it simultaneously deviates posteriorly, being covered by a strongly developed mass of fatty and connective tissue, the anterior muscles of the neck, the superficial fascia, and the skin. Therefore, opening the upper and middle tracheal rings during tracheotomy is considered an easier operation than the lower ones. The mucous membrane of the trachea has a structure analogous to the mucous membrane of the larynx, differing from the latter by a greater number of elastic fibers forming a dense network with a predominance of a longitudinal arrangement of fibers. The cilia of the ciliated epithelium have a direction of movement outward. The blood vessels, lymphatic vessels, and nerves of the trachea present the same relationships as in the larynx. The arteries of the trachea originate from the inferior thyroid artery. Developmental anomalies of the trachea can be in the form of fistulous communications with the esophagus (esophagotracheal fistula), congenital diverticula of the tracheal walls, and more rarely encountered cervicotracheal fistulas, lateral or located along the midline. Lateral fistulas represent remnants of branchial clefts, and fistulas located along the midline are in most cases the result of non-closure of the thyroglossal duct. The treatment of tracheal fistulas reduces to closing them by freshening the outer edges of the fistula. In more difficult cases, various methods of plastic surgery are resorted to. After operations, frequent relapses of the disease are noted. — Inflammatory diseases of the trachea see Tracheitis. Tuberculosis of the trachea occurs in the form of superficial or deep ulcers, initially round, later map-like in shape with the specific features of a tubercular ulcer. Hypertrophic productive forms of tuberculosis and tubercular tumors, as in the larynx, do not occur here. In view of the appearance of tracheal tuberculosis most often in the terminal period of the disease, it has no special clinical significance. — S y p h i l i s of the trachea is observed significantly less often than syphilis of the larynx and represents manifestations of tertiary syphilis in the form of gummatous nodes and infiltrates, upon the breakdown and healing of which scars are formed that constrict and reduce the lumen of the trachea. Upon establishing the diagnosis, energetic specific treatment is necessary to prevent subsequent cicatricial strictures of the trachea. Benign tumors of the trachea in many ways bear a resemblance to such tumors of the larynx, but are encountered significantly less often than the latter. Thus, according to Jurasz, out of 42,635 cases of upper respiratory tract diseases, there were 2,088 cases of laryngeal tumors and only 3 cases of tracheal tumors. Bruns collected a total of 102 cases of tracheal tumors from the literature (from 1767 to 1890): papilloma — 33 cases, fibroma — 23 cases, chondroma and osteoma — 29 cases, intratracheal goiter — 7 cases, adenoma — 5 cases, lipoma and lymphangioma — 5 cases. The most frequently encountered tumors are papillomas, which are often combined simultaneously with laryngeal papillomas. During life, being of small dimensions, they disturb patients very little and are often discovered only at autopsy. Fibromas of the trachea are encountered in the form of small tumors on a stalk or on a broader base. According to the same statistics of Jurasz, there were 23 cases of such tracheal tumors in the literature. Lipomas and endotheliomas of the trachea are a very rare occurrence. Chondromas originating from the tracheal cartilages and osteomas of the trachea are encountered somewhat more frequently. A special kind of tumor is intratracheal goiter (struma intratrachealis); it is encountered rarely and owes its origin to the ingrowth of ordinary goiter into the lumen of the trachea or to a developmental anomaly of the thyroid gland giving a small process into the trachea. In some cases, islands and trabeculae of cartilage and bone tissue develop in the submucosal tissue of the trachea, forming dense protrusions on the mucous membrane. Sometimes these islands are connected with the cartilaginous rings of the trachea, and in other cases they lie freely within the mucous membrane of the trachea. The development of this peculiar disease, which is designated by the term tracheopathia chondro-osteoplastica, is attributed by some authors to congenital separation of cartilage tissue, while others see in this the consequences of inflammatory processes. Analogous to the formation of air tumors of the larynx due to erosion of the thyroid cartilage and protrusion of soft integuments with the formation of an air sac on the neck, air tumors of the trachea — tracheocele — are formed. The clinical manifestations of tracheal tumors are insignificant in the initial stage of their development, but as the tumors grow and the lumen of the trachea decreases, the symptoms become clearer. In cases of emerging unclear stenotic breathing (tracheal stenosis), one should think of a tracheal tumor and undertake a thorough laryngological and bronchoscopic examination of the patient. In some cases, the presence of a tumor causes a semblance of asthmatic attacks in patients; in such cases, in differential diagnosis between a tracheal tumor and asthma, a blood test for eosinophilia can help, an increase of which above normal may indicate the presence of asthma, but not a tracheal tumor. — Treatment of all benign tumors of the trachea is operative. The latter can be performed in two ways: intratracheally — through the natural upper respiratory pathways, and extratracheally — through incision of the trachea. The advantages of the first path are limited by the necessity of having special instruments and special technical training for these operations. This path can be considered especially acceptable for small tumors sitting on a stalk. Conversely, large tumors located on a broad base can present significant difficulties when removing them through the natural respiratory pathways. — Among malignant primary tumors in the trachea, sarcoma and carcinoma are encountered. Tracheal sarcoma has been described in isolated cases, carcinoma somewhat more frequently. In the case of early diagnosis, excision of the affected area of the trachea is recommended. Of the greatest practical importance are s t e n o s e s of the trachea (tracheal stenoses), which are observed 1) upon compression of the trachea from the outside, 2) upon diseases of the tracheal walls, and 3) upon stenosing foreign bodies (see Foreign bodies). Compressions of the trachea from the outside are most often caused by the presence of a goiter. The cylindrical lumen of the trachea in many cases turns into a slit-like channel. In this process, compression of individual cartilage rings occurs, their resorption, and sometimes even the ingrowth of the tumor inside the trachea, especially in cases of malignant goiter. In some cases of far-advanced goiter, complete resorption of the tracheal rings sets in (tracheomalacia). The latter collapses and threatens the patient with suffocation. In such cases, the trachea is fixed with strong sutures to the underlying muscles, which restores the lumen of the trachea and relieves the patient from wearing a tracheotomy cannula. The treatment of goiter as a cause of stenosis belongs to surgical measures (see Goiter); it is only necessary to examine such patients radiologically before the operation, and also subject them to direct or indirect tracheoscopy to determine the degree of tracheal stenosis. Due to the close proximity of the aortic arch, its ascending and descending parts to the trachea and the left bronchus, aneurysms in this area can also lead to narrowing of the tracheal lumen. Among neoplasms of neighboring areas that do not as frequently cause compression of the trachea and main bronchi, it is necessary to mention mediastinal tumors, esophageal cancer, and tuberculosis of the paratracheal lymph nodes.
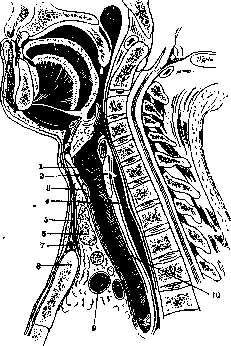
Sagittal section of the neck of an adult human: 1 — cartilago thyreoidea; 2 — lamina cartilaginis cricoideae; 3 — arcus cartilaginis cricoideae; 4 — oesophagus; 5 — musculus sterno-hyoideus; 6 — glandula thyreoidea; 7 — spatium suprasternale; 8 — manubrium sterni; 9 — vena anonyma sinistra; 10 — trachea.
ing them by freshening the outer edges of the fistula. In more difficult cases, various methods of plastic surgery are resorted to. After operations, frequent relapses of the disease are noted. — Inflammatory diseases of the trachea see Tracheitis. Tuberculosis of the trachea is encountered in the form of superficial or deep ulcers, initially round, later map-like in shape with the specific features of a tubercular ulcer. Hypertrophic productive forms of tuberculosis and tubercular tumors, as in the larynx, do not occur here. In view of the appearance of tracheal tuberculosis most often in the terminal period of the disease, it has no special clinical significance. — S y p h i l i s of the trachea is observed significantly less often than syphilis of the larynx and represents manifestations of tertiary syphilis in the form of gummatous nodes and infiltrates, upon the breakdown and healing of which scars are formed that constrict and reduce the lumen of the trachea. Upon establishing the diagnosis, energetic specific treatment is necessary to prevent subsequent cicatricial strictures of the trachea. Benign tumors of the trachea in many ways bear a resemblance to such tumors of the larynx, but are encountered significantly less often than the latter. Thus, according to Jurasz, out of 42,635 cases of upper respiratory tract diseases, there were 2,088 cases of laryngeal tumors and only 3 cases of tracheal tumors. Bruns collected a total of 102 cases of tracheal tumors from the literature (from 1767 to 1890): papilloma — 33 cases, fibroma — 23 cases, chondroma and osteoma — 29 cases, intratracheal goiter — 7 cases, adenoma — 5 cases, lipoma and lymphangioma — 5 cases. The most frequently encountered tumors are papillomas, which are often combined simultaneously with laryngeal papillomas. During life, being of small dimensions, they disturb patients very little and are often discovered only at autopsy. Fibromas of the trachea are encountered in the form of small tumors on a stalk or on a broader base. According to the same statistics of Jurasz, there were 23 cases of such tracheal tumors in the literature. Lipomas and endotheliomas of the trachea are a very rare occurrence. Chondromas originating from the tracheal cartilages and osteomas of the trachea are encountered somewhat more frequently. A special kind of tumor is intratracheal goiter (struma intratrachealis); it is encountered rarely and owes its origin to the ingrowth of ordinary goiter into the lumen of the trachea or to a developmental anomaly of the thyroid gland giving a small process into the trachea. In some cases, islands and trabeculae of cartilage and bone tissue develop in the submucosal tissue of the trachea, forming dense protrusions on the mucous membrane. Sometimes these islands are connected with the cartilaginous rings of the trachea, and in other cases they lie freely within the mucous membrane of the trachea. The development of this peculiar disease, which is designated by the term tracheopathia chondro-osteoplastica, is attributed by some authors to congenital separation of cartilage tissue, while others see in this the consequences of inflammatory processes. Analogous to the formation of air tumors of the larynx due to erosion of the thyroid cartilage and protrusion of soft integuments with the formation of an air sac on the neck, air tumors of the trachea — tracheocele — are formed. The clinical manifestations of tracheal tumors are insignificant in the initial stage of their development, but as the tumors grow and the lumen of the trachea decreases, the symptoms become clearer. In cases of emerging unclear stenotic breathing (tracheal stenosis), one should think of a tracheal tumor and undertake a thorough laryngological and bronchoscopic examination of the patient. In some cases, the presence of a tumor causes a semblance of asthmatic attacks in patients; in such cases, in differential diagnosis between a tracheal tumor and asthma, a blood test for eosinophilia can help, an increase of which above normal may indicate the presence of asthma, but not a tracheal tumor. — Treatment of all benign tumors of the trachea is operative. The latter can be performed in two ways: intratracheally — through the natural upper respiratory pathways, and extratracheally — through incision of the trachea. The advantages of the first path are limited by the necessity of having special instruments and special technical training for these operations. This path can be considered especially acceptable for small tumors sitting on a stalk. Conversely, large tumors located on a broad base can present significant difficulties when removing them through the natural respiratory pathways. — Among malignant primary tumors in the trachea, sarcoma and carcinoma are encountered. Tracheal sarcoma has been described in isolated cases, carcinoma somewhat more frequently. In the case of early diagnosis, excision of the affected area of the trachea is recommended. Of the greatest practical importance are s t e n o s e s of the trachea (tracheal stenoses), which are observed 1) upon compression of the trachea from the outside, 2) upon diseases of the tracheal walls, and 3) upon stenosing foreign bodies (see Foreign bodies). Compressions of the trachea from the outside are most often caused by the presence of a goiter. The cylindrical lumen of the trachea in many cases turns into a slit-like channel. In this process, compression of individual cartilage rings occurs, their resorption, and sometimes even the ingrowth of the tumor inside the trachea, especially in cases of malignant goiter. In some cases of far-advanced goiter, complete resorption of the tracheal rings sets in (tracheomalacia). The latter collapses and threatens the patient with suffocation. In such cases, the trachea is fixed with strong sutures to the underlying muscles, which restores the lumen of the trachea and relieves the patient from wearing a tracheotomy cannula. The treatment of goiter as a cause of stenosis belongs to surgical measures (see Goiter); it is only necessary to examine such patients radiologically before the operation, and also subject them to direct or indirect tracheoscopy to determine the degree of tracheal stenosis. Due to the close proximity of the aortic arch, its ascending and descending parts to the trachea and the left bronchus, aneurysms in this area can also lead to narrowing of the tracheal lumen. Among neoplasms of neighboring areas that do not as frequently cause compression of the trachea and main bronchi, it is necessary to mention mediastinal tumors, esophageal cancer, and tuberculosis of the paratracheal lymph nodes.
Related articles
Mentioned in
Cite this page
“Trachea.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/trachea/