Bronchoscopy
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Soviet Great Medical Encyclopedia details the history, indications, instrumentation, and techniques of bronchoscopy. It outlines the transition from upper to lower bronchoscopy, particularly in pediatric cases, and highlights its life-saving role in removing foreign bodies.
Encyclopedia article (1928–1936)
BRONCHOPNEUMONIA, see Pneumonia. BRONCHOSCOPY (from Greek bronchos - bronchus and skopeo - to view), or tracheobronchoscopy, a direct method for examining the deep respiratory tracts. In the 1880s, Mikulicz developed the method of esophagoscopy (see). Some surgeons accidentally penetrated the glottis with a rigid tube during esophagoscopy and saw the trachea. But the founder of the direct method of examining the respiratory tract is Kirstein, who in 1895 published his method of straightening the oro-pharyngeal arch with a spatula to such an extent that the entire trachea down to the bifurcation could be illuminated and seen. He did not dare to penetrate further with a rigid tube. And only Killian, after careful study on corpses, animals, and patients, proved that the bronchial branches are capable not only of shifting, but also of stretching in transverse diameter to accommodate rigid tubes of a larger caliber than the lumen of the bronchus, and by his method made the entire bronchial tree accessible to the eye down to the second- and third-order branches. Together with his pupil Brü
nings (Brünings), Killian invented a simplified, globally recognized bronchoscopic set and necessary instrumentation, created an entire clinic of bronchoscopy, and placed in the hands of physicians a powerful, purely surgical method for investigating and treating the deep respiratory tracts. Bronchoscopy is performed in a sitting or lying position, under general anesthesia or local anesthesia (or without any anesthesia), especially in early childhood, where the danger of poisoning by chloroform or cocaine is particularly great. The choice of one or another technique depends on the patient, the structure of the neck and jaws, the development of reflexes, the nature of the disease, and so on. The bronchoscopic set consists of tubes of various calibers: for men, women, children, and infants; in addition, a tube for esophagoscopy is attached—the widest one. The tubes are double and sliding, inserted into the electroscope (see Figure 1), onto which is mounted the Kirstein lamp with the modification that the incandescent filaments cross three times and at the intersection a strongly luminous point is formed, the rays of which are gathered into a parallel beam by a lens mounted on the lamp. The light beam is caught by a flat mirror (with a pierced slit) rotating on the frontal axis and is thrown perpendicularly into the tube. Through the slit opening of the mirror, one can see a strongly illuminated field inside the trachea or bronchus. For instrument manipulation, the entire illumination system is extended on a triangular rod from the handle by 6 cm with almost no loss of light intensity. The tube is inserted through the mouth into the glottis and further into the trachea. In order not to remove the bronchoscope and not to introduce a longer tube to penetrate into the bronchus and its ramifications, the inner tube is advanced through the inserted outer tube by means of a steel spring soldered to its upper end. The introduction of the bronchoscope through the glottis is called upper bronchoscopy, in contrast to lower bronchoscopy, in which the bronchoscopy is performed through a tracheotomy wound. Lower bronchoscopy according to Brünings is indicated: 1) in all patients who have already been subjected to tracheotomy for various reasons; 2) in all children younger than 3 and even 6 years of age; 3) in all severely exhausted patients and individuals with sharply pronounced dyspnea; 4) in all persons having foreign bodies in the bronchi which, according to experience, are difficult or dangerous to remove; 5) in all cases,
where, with persistent indications to perform bronchoscopy, for one reason or another upper bronchoscopy has failed (inexperience, sharp reflex, etc.); 6) finally, in those cases where repeated examinations of the respiratory tracts are anticipated. In particular, in children, one must also reckon with the fact that after upper bronchoscopy, edema of the epiglottis (subglottische Schwellungen) occurs, which sometimes necessitates performing a tracheotomy on the first or second day.
Surgical instrumentation is also constructed on the principle of sliding tubes: forceps with screw-on tips (see Figures 2 and 3)—claw-like for removing solid foreign bodies, fenestrated with long teeth on the frame for fruit seeds; with plates standing perpendicular to the long axis for pins and needles; cutting ones for removing tumors, etc., depending on the nature of the application. Bronchoscopy laid the foundation for a new branch of knowledge that can be called bronchology, by analogy with laryngology, the foundation of which was served by the laryngeal mirror (laryngoscopy). An entire clinic of the pathology of the trachea and bronchi was created. Very recently, contrast liquids for bronchography have been introduced through the bronchoscope. Bronchoscopy serves for the scientific study of a number of physiological phenomena inside the chest cavity. In the clinic of foreign bodies, bronchoscopy has won
Figure 2. Sliding forceps according to Brünings.
Figure 3. Tips for forceps.
first place and is a powerful and sole method for diagnosis and treatment. Suffice it to mention that in the pre-bronchoscopic period, the mortality rate from aspirated foreign bodies was 40–50%, and at present has fallen to 7–8%, and with some authors down to 4–5%.


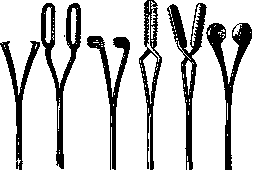
Related articles
Mentioned in
Cite this page
“Bronchoscopy.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/bronchopneumonia/