Esophagoscopy
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Great Medical Encyclopedia details the history, methodology, instruments, and clinical indications for esophagoscopy. It outlines the technical aspects of examining the esophagus using rigid tubes, anesthesia considerations, and potential complications such as perforation.
Encyclopedia article (1928–1936)
ESOPHAGOSCOPY, ESOPHAGOSCOPE. Esophagoscopy is the examination of the esophagus by means of introducing long metal tubes illuminated from the proximal or distal end by electric lamps.
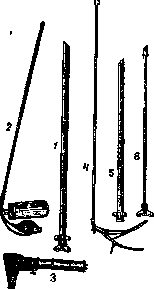
Figure 1.
Fig. 2.
Figure 1. Set for the esophagoscope, comprising: 1, 5, and 6 - straight tubes of various lengths; 2 - suction apparatus for removing mucus and discharge; 3 - Kasper lighting apparatus; 4 - holders for gauze swabs and forceps for removing foreign bodies. Fig. 2. Brünings universal electroscope.
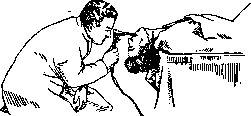
The first attempts at investigations of this kind were made at the beginning of the 19th century (Bozzini), but did not become widespread due to the imperfection of the instruments. In the 1880s and 1890s, thanks to the invention of incandescent lamps and the use of local anesthesia, endoscopic methods of examination and surgery of cavity organs began to develop rapidly, and now a separate branch of medical science—broncho-esophagology—is emerging on the basis of this methodology. Modern bronchoscopic instruments, which also include devices for direct examination of the esophagus, consist of extendable metal tubes of various calibers (from 5 to 14 mm in diameter), an illuminating apparatus arranged either in the form of a projector casting a parallel beam of rays along the axis of the tube (Figs. 1, 2) or in the form of a long rod with a small electric lamp at the end; this rod is inserted, lamp first, into a special groove in the wall of the tube; in this case, only the section of the respiratory tract or esophagus closest to the end of the tube is illuminated. (Both methods compete with each other, having certain advantages and disadvantages.) Esophagoscopes are those tubes of endoscopic sets that are specially designed for the examination of the esophagus. In the older types of these sets, special tubes of wide diameter and maximum length were used for this purpose so that it would be sufficient for the entire length of the esophagus. In modern sets by Brünings, C. Jackson, Kahler, Haslinger, and others, the tubes differ not in their purpose, but only in caliber and length, and the difference in the design of instruments for esophago- and bronchoscopy consists only in the fact that, for example, the insertion extension tube for the esophagus (in the Brünings set) has no side holes for the passage of air, while the bronchoscopic ones are equipped with them. Furthermore, the set includes operating instruments—forceps and hooks for extracting foreign bodies, cutting forceps for test excisions, knives, dilators, cotton holders, tubes for suctioning mucus, sprayers for anesthetic agents, and others (Figs. 3–8). Although the esophagus can be investigated with the same instruments that are intended for the respiratory tract, a complete set usually includes certain additional parts, for example, special insertion tubes (for lengthening the main ones), special, more massive forceps for foreign bodies, and special probes for examining esophageal diverticula. The examination is performed in a sitting or lying position (Figs. 9, 10) of the patient. Great advantages are provided by the prone position on the operating table with its foot end raised somewhat; then it is much easier to eliminate the flow of saliva into the respiratory tract and the stagnation of gastric juice and mucus in the lumen of the tube; in addition, orientation when introducing the tube into the esophagus is also facilitated. For anesthesia, the mouth of the esophagus is preliminarily lubricated using a curved cotton holder with a 10–20% solution of cocaine or another homogeneous substance used for local anesthesia in otolaryngology. There is, however, an opinion that esophagoscopy is preferable to perform without anesthesia, since the nausea reflexes arising in the pharynx from the first touch of the instrument facilitate its deeper penetration, and on the other hand, the procedure of cocaine anesthesia itself can be extremely unpleasant for the patient. Previously, to ensure safe introduction of the esophagoscope, a flexible guide (mandrin) was used and inserted blindly; now this technique has been completely abandoned, because it is not safe for the integrity of the esophageal wall, and furthermore, under visual guidance, the esophagoscope can be introduced even more easily than with the mandrin method. The secret of success lies in the ability to find the upper mouth of the esophagus, which is closed at the level of the posterior wall of the larynx in the form of a slit that is difficult for the eye to distinguish. To get into it with the beak of the instrument, one must first direct it precisely along the midline of the body,
Figure 4. Hacker curette.
and for this, the lumen of the larynx is preliminarily examined and the line of closure of the true vocal cords is determined by eye. By guiding the beak of the esophagoscope along the midline slightly posterior to the arytenoid cartilages of the larynx, one enters the cervical part of the esophagus.
Figure 5. Clamping forceps for gauze swabs by Hacker-Mikulicz.
It is also closed and has a slit-like lumen in the form of a star. Advancing the tube a few more centimeters further, one enters the thoracic, gaping part of the esophagus. The gaping disappears again when the end of the tube reaches the cardiac (gastric) mouth of the esophagus; its lumen has the appearance of closed lips; if this obstacle is also forced, the mucous membrane of the stomach, distinguished by a more saturated red color, will appear in the field of view. Orientation is also possible by
Figure 6. Mikulicz forceps.
the depth of introduction of the tube: the distance from the edge of the upper teeth to the pharyngeal mouth of the esophagus is 14–15 cm, and to the cardia—from 40 to 45 cm (in adults). By means of esophagoscopy, one can recognize the presence of foreign bodies, cicatricial strictures, tumors, dilation and spasm of the esophagus, and one can perform various therapeutic interventions on it, for example, extraction of
Figure 7. Hacker auxiliary instruments (various instruments for grasping, biting off, etc.).
stipulated objects, opening of abscesses in peri-esophagitis, excision of a test piece, introduction of a radioactive capsule in carcinoma of the esophagus, bougienage of strictures, and so on. Difficulties and complications of esophagoscopy: anatomical conditions may favor or hinder its performance; in some it succeeds with striking ease (upon which the possibility of the circus trick of «sword swallowing» was based); in others, predominantly in people with a short neck, spinal curvature, and strongly protruding front teeth, esophagoscopy may prove unfeasible. In children, it succeeds more easily than in adults, but sometimes their resistance and restlessness require general anesthesia to avoid undesirable trauma during forced introduction of the tube. Since the wall of the esophagus bleeds and tears relatively easily, the escape of blood from superficial abrasions during esophagoscopy can rarely be avoided; however, careless advancement of the tube without visual control, especially when the esophageal wall is pathologically altered, can entail a more dangerous complication—its through-perforation and subsequently purulent mediastinitis. With varicose dilation of vessels and even more so with aneurysms, there is a danger of their traumatization and life-threatening hemorrhage. In deep esophagoscopy, the touch of the instrument to the region of the cardia can cause shock, as can the procedure of esophagoscopy itself,
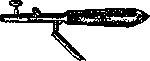
Figure 8. Handle for Hacker forceps.
which is tolerated very heavily by some. The possibility of secondary infection necessitates preliminary sanitization of the mouth, tonsils, as well as the nose and accessory sinuses, but often this cannot be performed radically enough, since, for example, in the case of foreign bodies, extraction has to be done more or less urgently. Where time permits, it is desirable to take an orienting X-ray image before extracting a foreign body (localization of non-transparent foreign bodies, strictures, diverticula), perform possible sanitization, and examine the patient on an empty stomach. Conversely, blind probing of the esophagus, if required for any reason, should follow esophagoscopy rather than precede it, since with the latter combination the chances of traumatizing the esophageal wall increase.
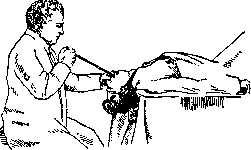
Figure 9. Moment of introduction of the esophagoscope.
Figure 10. Examination of the esophagus.
V. Voyazek
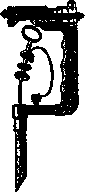


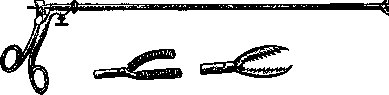
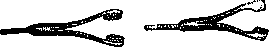
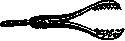
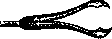
Related articles
Mentioned in
Cite this page
“Esophagoscopy.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/esophagoscopy/