Operating Tables
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
An overview of the historical development and technical evolution of operating tables from the pre-antiseptic era to the advanced adjustable metal tables of the 1930s. The article details various models, special positions such as Trendelenburg, and accompanying surgical accessories like leg holders.
Encyclopedia article (1928–1936)
OPERATING TABLES, which form the center of every operating room (see), have gone through a number of stages in their development, closely tied to the rapid and brilliant progress of surgery during its antiseptic and especially aseptic periods. In the pre-antiseptic era, any bench, table, bed, etc., could serve as an operating table, whereas the modern operating table must satisfy a whole series of special requirements. The principal ones among these are the stability of the table, the ability to disinfect it quickly, and the capability of imparting to it various positions that facilitate the surgeon's access to the operated part of the body or organ. At the beginning of the aseptic era, operating tables were mostly wooden, painted white, with a raised head end. Following Trendelenburg's proposal to operate on pelvic organs with the head end of the table lowered, wooden tables of the Delageniere type (Figs. 1 and 2) became widespread; they can still be found today in small surgical (especially gynecological) departments of predominantly rural hospitals. At the time, these tables were warmly recommended by Snegirev and Gubarev, who pointed out their low cost and simplicity of construction, making it possible to build them locally under any conditions. The rapid development of surgery in general and instrumental technique in particular soon demanded further improvements, and operating tables, at the suggestion of de Quervain and later Hahn, began to be built of metal, equipping them with various auxiliary devices that made it easy to change the position of the patient lying on them (Figs. 3, 4, and 5). Further modifications are merely developments of the original de Quervain model (Fig. 6). At present, numerous models of operating tables are available on the market, but most of them differ from one another only in insignificant, often non-essential technical details. The ideal modern operating table should be considered a table whose upper board is composed of several separate parts (joints); each of them can be given the position required for a given operation using one or another device. The more of these separate parts there are, the more convenient the table, but the higher its cost. The most sophisticated operating table at present is considered to be one whose upper (steel, polished) board consists of 6 separate joints (Fig. 7), corresponding to 1) the head, 2) the neck, 3) the chest, 4) the abdominal cavity and pelvis, and 5) and 6) the patient's lower extremities. The last 2 parts are usually made removable. In operations on the skull (Figs. 8 and 9), the head section of the board can be replaced by a special device—a hoop that firmly fixes the head (Fig. 10). The same figure shows an arch on which a sheet is placed, isolating the anesthetist and the patient's face from the operating surgeon. For operations in the oral cavity and on the chest, the operating table can be given the appearance of an arm chair (Fig. 7), imparting to it a certain tilt with the help of a side lever (wheel). Such a lateral (Fig. 11) position of the table is also very convenient for draining large accumulations of fluid from the abdominal cavity. In this case, the patient's trunk is fixed by various removable devices (Figs. 12 and 13), screwed with special screws to the rails located along the edges of the table (Fig. 14). For operations on the kidney, spleen, and liver, a special oilcloth-covered bolster is placed under the patient (Fig. 15), bringing the operated organ closer to the surface of the body. In the newest models of operating tables manufactured in Germany, this bolster is replaced by a corresponding device (Fig. 16) (Beckenbank, Beckenstutze), which allows the patient's body to be easily given the required curve using a rotating handle. For applying a bandage to a patient under anesthesia, appropriate supports are placed under the sacral region (Figs. 17 and 18), and in newer operating tables, a device analogous to the one shown in Fig. 16. Raising or lowering the operating table in older models was performed by turning a handle located under the upper board of the operating table. In newer tables, an oil pump easily operated by a foot pedal (similar to a dental chair) serves this purpose. Usually, a second pedal is located near the first one, allowing the upper board of the operating table to be rotated 360° around its axis without moving its legs. To give the operating table the Trendelenburg position or the reverse elevated position of the upper part of the trunk, new models have a very ingenious device (a lever with a weight at the end) (Fig. 19), which allows one person to easily give the operating table the required position without removing the patient from the table. For
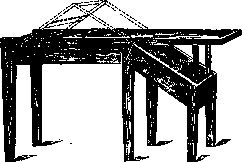
Figure 1. Delageniere table.
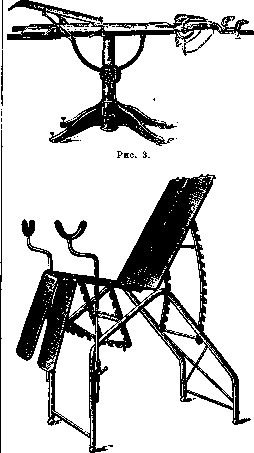
Figure 6. Table for urological manipulations.
operations on the perineum and anus, leg holders (see below) are used, which are screwed to the foot end of the operating table. The cost of an operating table with the listed improvements is very high (about 2,500–3,000 German marks). It should be noted that many surgeons, while giving due credit to the listed improvements in newer operating tables, prefer to operate on simpler operating tables of the Hahn type (Fig. 4), the advantage of which is the absence of complex mechanical
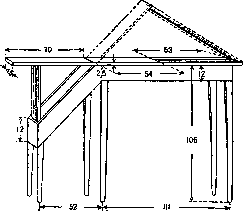
Figure 2. Delageniere table. The dashed line indicates the position of the top in the Trendelenburg position. Dimensions are given in centimeters.
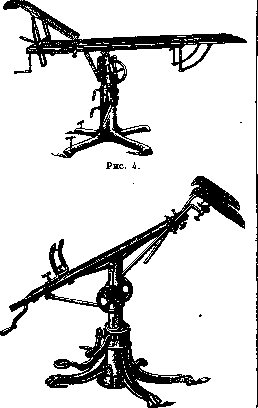
Figure 5.
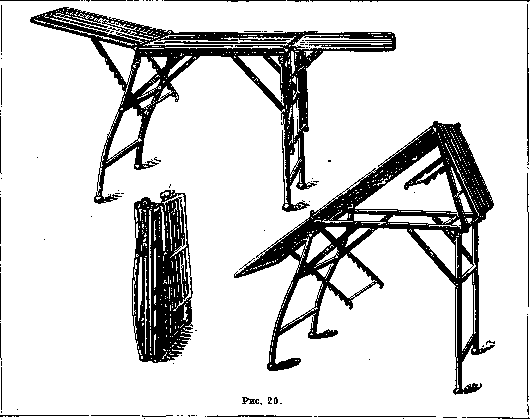
devices that facilitate their easier disinfection. Not a small advantage of the Hahn table is also its low cost. In the USSR at present, operating tables of a standard type following the Hahn type (Fig. 3) with a manual or oil lift are manufactured. Under wartime conditions in mobile field hospitals, various folding operating tables (Fig. 20) of the Tillmanns type can be used. N. Blumenthal.
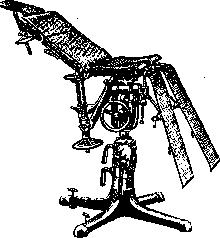
Figure 7.
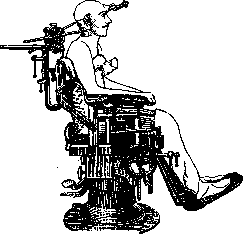
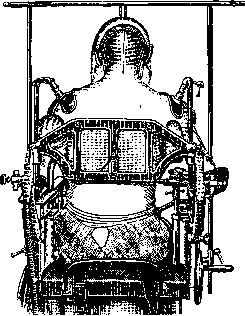
Fig. [Number]. Martel table.
Figure 8. Martel table.
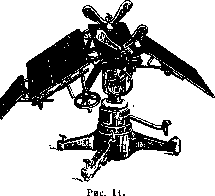
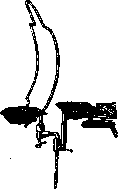


Figure 10.
Figure 12. Figure 13. Leg holder—a device for holding the lower extremities of patients during gynecological, obstetrical, and rectal operations. Sänger as early as 1884 at the congress of German
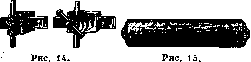
naturalists and physicians in Magdeburg proposed his model of a leg holder. Since then, a number of new models have been proposed, of which the most widespread are
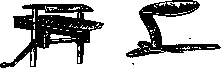
Figure 16.
Figure 17. the leg holders of Zweifel, Fritsch, Dieffenbach, Ott (Zweifel, Fritsch, Dieffenbach). The use of a leg holder is based on the necessity in the aforementioned operations to fix the lower extremities of patients in a strictly defined position. Leg holders pursue the goal of reducing the number of assistants during an operation. The simplest and most convenient is the Ott leg holder, first described by Blumberg in 1886 (Figs. 21 and 22). It consists of a hollow metal rod 0.25 m long, into which a second metal rod of the same length is inserted

Figure 18.
Figure 19. (with notches). The second rod can be extended to a greater or lesser distance and secured in this position by a screw located near the central end of the hollow rod. To the outer ends of both rods are attached rings made of wide leather strap, which are sewn to curved metal plates that fasten using narrow straps and metal buckles. The maximum flexion
such that the lower extremities, flexed at the knee and hip joints and raised to the required height, are sufficiently brought closer to the anterior abdominal wall and spread apart. In addition, the use of a leg holder
of the lower extremities in the hip joints and the approximation of the thighs to the abdominal wall is achieved with the aid of a narrow strap thrown over the shoulder girdle and connected to the other end of the leg holder by a metal buckle located on the second short strap. As a result of the adduction of the thighs, relaxation of the rectus abdominis muscles is obtained, which is very important both during examinations
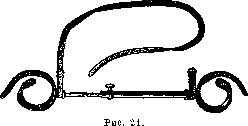
and especially during vaginal and rectal operations. The Ott leg holder is not only simple in design and inexpensive, but most importantly allows
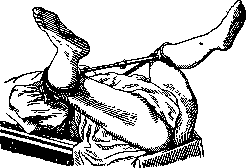
Figure 22.
the necessary abduction of the lower extremities flexed at the hip and knee joints. Among its disadvantages, one must point out the incomplete fixation of the patient's entire trunk, which is especially important during obstetrical operations (forceps, perforation), during which displacement of the patient's entire trunk from the table is possible. In such cases, it is most expedient to use metal, vertically positioned rods fixed at a distance of 10 cm from the foot end of the table using metal clamps. Three screws make it possible to secure the lower extremities, flexed at the knee joints, at the required height (36–38 cm). The Zweifel leg holder (Fig. 23) also makes it possible to widely spread the lower extremities to the sides. Martov (1930) proposed a new model of a leg holder (Fig. 24) built on the principle of maximum utilization, with the help of spherical joints, of the movements that normally take place in the hip and knee joints. This leg holder can be attached
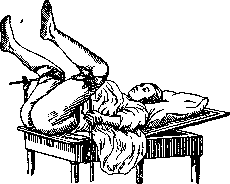
Figure 23.
Figure 24.
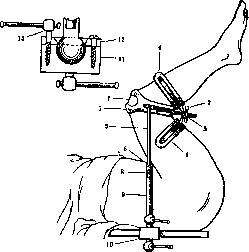
Figure 24. Martov's leg holder: two side bars (6 and 8) made of hollow tubes. One tube (3) is inserted into another (9) as needed. On both sides, the bars with tubes are attached at the top and bottom in the manner of a spherical joint fixation, which makes it possible, thanks to the crater-shaped cover (12) and by means of the clamp (13), to give any direction to the bar (9) and the ring (4) in all planes. Clamp for fixing the leg holder to the table (10 and 11), wooden and metal, which is one of the essential advantages of the leg holder for work in the conditions of district practice. Leather socket for the kneecap (1 and 7). Device (4), with the help of which, by acting on the nut (2 and 5), any position can be given to the knee bend (to prevent blood stagnation).
fit to any table. This last model will apparently also find application in practical life (fig. 25). Of the simple leg holders that allow fixing
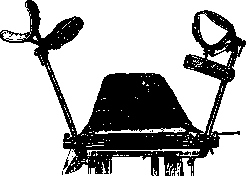
Figure 25.
the lower extremities of patients in the required position directly on the bed, one can mention the leg holder -30; the opium of Zangemeister (fig. 26).- In addition to the complex metal models mentioned, improvised leg holders from an ordinary sheet are widely used in practice (especially in the district), with the help of which the lower extremities are held in the necessary position. Nevertheless
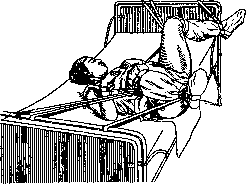
Figure 28.
the most convenient, when there is a sufficient number of assistants, is for assistants to hold the patient's legs. The patient's pelvis is placed slightly in front of the table, and the assistants hold the bent LEGS.
Related articles
Mentioned in
Cite this page
“Operating Tables.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/operating-tables/