Colpotomy
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
Colpotomy is a surgical procedure involving an incision into the vaginal wall to access the pelvic cavity for diagnostic or therapeutic purposes. This article from the 1928–1936 Soviet Great Medical Encyclopedia details the techniques for anterior and posterior colpotomy, their indications, and their limitations compared to abdominal surgery.
Encyclopedia article (1928–1936)
COLPOTOMY, colpotomia (from the Greek kolpos—vagina and temno—to cut), or colpocoeliotomy (colpocoeliotomia), is a method of entering the abdominal cavity in women via the vaginal route for diagnostic and surgical-therapeutic purposes. Colpotomy was first used in 1822 by Sauter (Johann Nepomuk Sauter) in Germany for the removal of a cancerous uterus; then, in 1857, Atlee opened the posterior vaginal fornix to remove an ovarian cyst. Gaillard Thomas in New York in 1870 began to systematically use the vaginal route for the removal
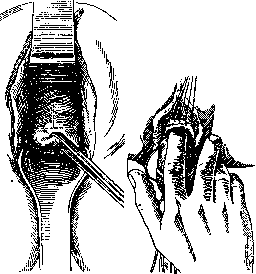
Figure 1.
Figure 2. of ovarian cysts. Later in Germany, Dührssen (1894) and then A. Martin (1903) developed this method in detail and assigned it a definite
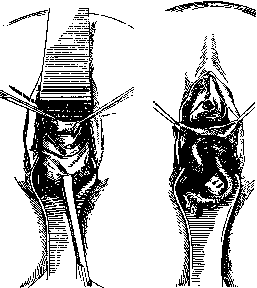
Figure 3.
Figure 4. place in gynecology. In Russia, the vaginal route was first used by Kiter and Elatich for the removal of a cancerous uterus. Two types of colpotomy are distinguished: anterior colpotomy (c. anterior) and posterior (c. posterior). The former consists of opening the abdominal cavity through the anterior fornix, and the latter through the posterior. In addition to anterior and posterior colpotomy in the strict sense of the word, one can also distinguish a special type of combined colpotomy—vaginal hysterectomy, in which both anterior and posterior colpotomy are performed and the uterus is removed. Technique of colpotomy. To perform a colpotomy, the woman is placed on the edge of the operating table with her legs bent at the knee and hip joints and spread apart. The vagina is opened with spoon-shaped specula, and the vaginal portion of the uterus is grasped with bullet forceps or Museux-Doyen tenaculum. When performing an anterior colpotomy, the vaginal portion of the uterus is strongly pulled downward, causing the anterior wall of the vagina to stretch and evert; then, an incision penetrating the entire thickness of the anterior vaginal wall is made—either a longitudinal median one, extending from the external urethral orifice to the vaginal portion, or a transverse or arcuate one. The latter two incisions, 5-6 cm in length, are made in the area where the anterior fornix transitions to the vaginal portion of the uterus (Fig. 1). After the vaginal incision, the bladder is separated from the cervix, partly by blunt dissection and partly with scissors, up to the vesicouterine fold of the peritoneum (Fig. 2), which is then grasped with forceps and cut with scissors in a transverse direction, resulting in the opening of the abdominal cavity in the area of the anterior Douglas pouch (Figure 3). The pelvic cavity can be examined bimanually. In the case of adhesions, the latter are separated. Then, by inserting a flat speculum into the opened fornix, the necessary manipulations are performed—bringing out the body of the uterus, the ovaries, and removing any tumors present in them (Figure 4), etc. After these manipulations and hemostasis are completed, the wound in the fornix is sutured (best of all with catgut), with the vesical edge of the peritoneum being joined to the uterine one, and the edges of the vagina to each other. If the tissues were severely damaged, the wound is left partially open and a drain is inserted into it. A difficult moment of anterior colpotomy, especially for an operator who does not have experience in vaginal operations, is the separation of the bladder from the cervix. Sometimes complications are possible here in the form of a through-and-through injury to the bladder. To avoid this, it is necessary in difficult cases to perform this part of the operation under the control of a catheter inserted into the bladder. Posterior colpotomy is technically easier. To perform it, a sufficiently wide but not long posterior speculum is inserted into the vagina; the vaginal portion of the uterus is pulled

Figure 5
KOLS A
forward and upward with the help of bullet forceps or a Museux-Doyen tenaculum. The posterior fornix, which has become accessible and stretched as a result of this, is opened by either a longitudinal, cruciform, or transverse incision made slightly below the site of the attachment of the vagina to the vaginal portion of the uterus (Fig. 5). First, the vaginal wall is cut with a knife or scissors, then the peritoneum is opened. To stop bleeding and for the convenience of opening the formed orifice, 3 or 4 interrupted sutures are placed on the incision in the posterior fornix, grasping the entire thickness of its wall. Then, the necessary manipulations for which the colpotomy was undertaken are performed, e.g., removal of an ovarian cyst. This latter procedure, depending on the location of the tumor, is done either without pulling the uterus out or by pulling it outward (Fig. 6). Upon completion of all

the necessary manipulations and hemostasis, the wound in the fornix is sutured tightly. In the case of purulent or bloody accumulation in the posterior Douglas pouch, opening the posterior fornix is technically very easy. After cutting the vaginal wall, the bulging peritoneum is opened by blunt dissection, e.g., with a dressing forceps. After emptying the contents, a sufficiently thick rubber tube is inserted into the opening for drainage. In cases of obliteration of the posterior Douglas pouch or adhesion of the small intestines within it, performing a posterior colpotomy becomes very difficult and sometimes even impossible. In these cases, injuries to the rectum and other intestinal segments adhered here occur easily. The advantageous aspects of colpotomy as a method of gynecological laparotomy are 1) the insignificance of trauma and operative shock, 2) good conditions for drainage, and 3) less danger of infection of the abdominal cavity. The disadvantageous aspects are the poor accessibility to the abdominal cavity, the narrowness and cramped nature of the operating field, and hence the impossibility of removing large tumors in their entirety, the difficulty of isolated hemostasis, reperitonealization, etc. In connection with this, colpotomy places greater demands on the technique and skill of the operator. To reduce some of the weaknesses of colpotomy, additional incisions of the perineum and vagina (Schuchardt's incision and the median perineal incision of Ott) and Ott's vaginal specula have been introduced, allowing almost the entire peritoneal cavity to be viewed. Pe- LAW
terior colpotomy is performed for small (up to the size of a fist), mobile, or weakly adhered ovarian tumors lying in the anterior fornix, for the removal of small fibromyomas located in the anterior wall of the uterus, for the correction of retroversion, retroflexion of the uterus, and prolapse, for amputation of the uterine body according to Rieck, etc. Posterior colpotomy is sometimes performed for diagnostic purposes. For therapeutic-surgical purposes, it is indicated for purulent and infected bloody accumulations in the posterior Douglas pouch. In these cases, it is an indispensable operation. Furthermore, it is performed for ovarian tumors located in the posterior Douglas pouch, for uterine inversion, for ectopic pregnancy, etc. With the exception of infected cases, ectopic pregnancy should as a rule be operated on via abdominal laparotomy. Contraindications for colpotomy include extensive, dense adhesions of the uterus, ovaries, and tubes, voluminous cystic, and especially dense and malignant tumors of the genital sphere, suspected inflammation of the vermiform appendix, etc. Some ardent proponents of colpotomy, such as Dührssen, Ott, and others, set the indications for it much more broadly and removed large tumors and even the vermiform appendix by this route; but in doing so, due to the impossibility of finishing the operation via the vagina, they sometimes had to switch to abdominal laparotomy or resort to hysterectomy for technical reasons. From this, it is clear that compared to abdominal laparotomy, the scope of application of colpotomy is limited; it is suitable for relatively easy operative cases. By the majority of gynecologists, it is performed significantly less often than abdominal laparotomy: it accounts for an average of 8-30% (Gruzdev, Okintchits, Döderlein, Franz, and others). Mortality in colpotomy is lower than after abdominal laparotomies.
I. Horizontov. COLLES' LAW (Colles), a proposition published by the Irish physician Colles in 1837, according to which a mother showing no signs of syphilis, of a congenitally syphilitic infant who has infectious manifestations in the mouth that are dangerous to a healthy wet nurse, can breastfeed her child without risk of infection from him. This proposition was confirmed in 1840 by the Lyon physician Baumes (Francois Baumes) and entered the history of syphilology under the name of the Colles-Baumes law. This "law" formed the basis of the paternal (ex patre) theory of transmission of congenital syphilis, according to which a syphilitic virus mixed with the semen, supposedly without infecting the woman's sexual passages, infects either the germ plasm (ovulum) or the already developing embryo. The product of conception infected by one or the other method in turn either infects the mother or immunizes her, making her inaccessible to new infection with syphilis (the "Colles mother"). Subsequently, cases of "exceptions to the Colles-Baumes law" were even published, in which the mother nevertheless became infected from her congenitally syphilitic child. These latter cases made a particularly strong impression. Indeed, one such indisputable case would have been sufficient to prove the possibility of paternal transmission of congenital syphilis without the mother becoming infected. But as early as the 1860s, Norwegian authors Wilhelm Boeck and Ewre (W. Boeck, Oewre) noted that only a mother with syphilis can give birth to an infected child. Later, in 1898, Oedmansson, on the basis of studying a large amount of clinical material, came to similar conclusions. But the most categorical confirmation of this position was found in the classic work of Matzenauer. The latter, in 1903, on the basis of only clinical study of published cases, expressed the conviction that all "Colles mothers" have syphilis and that in the cases of exceptions to the Colles-Baumes law there is no new infection of the mother. In these latter cases, either a previously healthy mother became infected with syphilis from her infant who was born healthy but became infected after birth, or as a result of constant irritation during lactation, chancriform papules appeared on her nipples. Furthermore, these cases can be considered as a result of superinfection due to the constant rubbing of the child's spirochetes into the nipples. Since the time of Matzenauer's work, cases of exceptions to the Colles-Baumes law have been published less and less frequently, and in the last 10 years none have been published at all (Rietschel). One can therefore assert that the "exceptions" in question do not exist in nature at all. The correctness of the views expressed by Matzenauer regarding "Colles mothers" is confirmed by the already sufficiently accumulated clinical and laboratory data. The brilliant discoveries of the early 20th century fully confirmed the bold, for that time, conclusions of Matzenauer, based on a subtle analysis of clinical facts. However, the possibility, though rare, of transmission of congenital syphilis only by the father, without the participation of the mother, is still recognized by some authors, among whom it is necessary to mention the names of such major scientists as Finger, Hochsinger, Almkvist; the latter, in a detailed work (1928), cites 5 cases that seem to testify to the possibility of a healthy mother giving birth to a child with syphilis. However, the cases cited by Almkvist are not without flaw: all the mothers were not examined sufficiently thoroughly (for example, none of them had a spinal fluid examination). Furthermore, Almkvist does not explain the fact that none of these "healthy" mothers became infected with syphilis from their children who had active manifestations of congenital syphilis, and nowhere does he express his opinion on the "immunity" of these mothers. Moreover, all these and similar observations cannot refute the basic fact that to this day it has not been possible to detect either the pale spirochete nor pathological changes in the placenta before the fifth month of pregnancy. And this circumstance stands in clear contradiction with the hypothesis of infection of the egg (ovulum) by a spirochete, whether unfertilized or already fertilized (Meshchersky). Thus, even this work by Almkvist cannot be considered sufficiently convincing. The positions of Oedmanson-Matzenauer remain in force. The more thoroughly "Colles mothers" are studied, the more often they have to be transferred from the ranks of healthy and immune to the category of diseased. Rare cases in which syphilitic infection cannot be established in such a mother testify only to the insufficient sensitivity of modern diagnostic methods, to the extreme diversity of the course of syphilis, and not to their health. Since the fact of spirochete carriers (Nullerbi Kolle) has been established, the "Colles mother" does not represent anything exceptional in the pathology of syphilis (Sobolev). In any case, for practical purposes, it should be remembered that the birth of a diseased child by a diseased mother is such a frequent clinical fact that the birth of a diseased child not only gives the physician the right but also imposes on him the duty to subject the mother of such a child, whatever the results of her examination, to vigorous specific treatment both for the purpose of her personal prevention and for the prevention of her future offspring.
Related articles
Mentioned in
Cite this page
“Colpotomy.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/colpotomy/