Obliteration
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Great Medical Encyclopedia defines obliteration as the closure or destruction of a cavity or lumen through tissue proliferation originating from its walls. It details the causes, physiological and pathological manifestations, and consequences of obliteration in blood vessels, respiratory tracts, internal organs, and serous cavities.
Encyclopedia article (1928–1936)
OBLITERATION (Latin obliteratio - erasure), a term used to designate the closure or destruction of a given cavity or lumen through the proliferation of tissue proceeding from the walls of the given hollow formation. This proliferation most often concerns connective tissue and represents a manifestation either of a productive inflammatory process or of the so-called organization (see) of some dead material located within the lumen of the cavity. More rarely, the proliferation causing obliteration of a cavity is related to tumor growth. Obliteration can be observed in the tubular systems of the organism, for example, blood vessels, respiratory tracts, intestines, gland ducts, vagina, etc., as well as in the serous cavities of the pleura, pericardium, peritoneum; the vaginal cavity of the testicle, joints, and others. Vascular obliteration is expressed in the complete closure of the vessel lumen over a certain extent of it and most often is either the result of the organization of a thrombus formed in the vessel or the consequence of productive inflammation manifested in the progressive proliferation of the connective tissue of the inner coat of the vessel (e.g., in syphilitic lesions of arteries). Furthermore, obliteration of vessels, especially arteries, occurs upon the cessation of blood flow through their lumen, with the lumen collapsing and subsequently becoming overgrown with connective tissue. This happens in the distal part of an artery tied off with a ligature. The physiological prototype of such obliteration is the obliteration of the umbilical vessels and the ductus arteriosus in an infant, occurring after birth. Obliteration of the respiratory tracts takes place as a consequence of various ulcerative processes of the bronchial mucosa, wherein in the area devoid of the epithelial cover, connective tissue proliferation occurs, ultimately closing the bronchial lumen; or else such proliferation has as its basis the organization of a fibrinous exudate located within the bronchial lumen. Obliteration of the intestinal lumen, excretory ducts of glands, bile ducts, and vagina most often has an inflammatory origin and is connected with the scarring processes of various ulcerous defects resulting either from trauma (e.g., in the bile duct from a stone, in the vagina from a pessary) or from non-specific and specific inflammations. Persistent closure of the lumen of the intestine, gland duct, or vagina as a result of obliteration is sometimes called atresia (see). Obliteration of serous cavities, also designated by the term concretio, is expressed in the complete or partial overgrowth of the given cavity (pleura, pericardium, peritoneum, etc.) with connective tissue; in most of these cases, obliteration is a consequence of a past acute inflammation of the cavity with the exudation of fibrinous exudate and the organization of fibrin after the acute period of inflammation has subsided (see Adhesive process). Sometimes masses of fibrin that undergo calcification (obsolescentio) remain preserved among the connective tissue. In rarer cases, obliteration of a serous cavity is the result of chronic productive (e.g., tuberculous) inflammation. In relation to the processes causing obliteration, the adjective "obliterating" (obliterans) is applied; e.g., obliterating inflammation, obliterating endarteritis, endophlebitis, obliterating pericarditis. The consequences of obliteration are very diverse, but in general in tubular systems they boil down to the cessation of their patency, e.g., of blood vessels for blood, respiratory tracts for air, gland ducts for the corresponding excretions, etc., whereas obliteration of serous cavities leads to difficulties and limitations of the mobility of the organs enclosed within these cavities (lungs, heart, intestines) or, in the case of joint obliteration, movement of the limb in the given joint. In turn, these immediate consequences of obliteration can have further results; e.g., obliteration of an artery leads to local anemia, atrophy, or tissue necrosis; obliteration of veins to stasis; obliteration of glandular ducts to the development of retention cysts; obliteration of the bile duct to bile retention and jaundice; obliteration of the vagina to haematocolpos and haematometra. A. Abrikosov.
704 VI. Carbohydrate metabolism.............717 VII. Mineral metabolism............727 VIII. Water metabolism ...............741 IX. Metabolism in children...........750 I. History of the subject. Metabolism and energy. Under this term, representing a translation of the German "Stoff- und Kraftwechsel", is understood not only the direct material and energy exchange between the external environment and the living organism, which constitutes such a characteristic sign of life, but also the entire aggregate of transformations of assimilated substances and energy within the body, which conditions the vital activity of the organism. If it is desired to designate both these parts separately, the first is called general metabolism, and the second intermediate metabolism. French, Englishmen, and Americans use the term metabolism (see) instead of the term metabolism and energy. The dependence of life on the intake of substances into the body from the outside was undoubtedly recognized even in antiquity, yet all the views put forward at that time are merely more or less ingenious intuitions. Aristotle considered that the body needs the intake of food for a threefold purpose: for growth, for the generation of heat, and to cover its material losses. He believed that the generation of heat occurs in the heart by way of boiling, that this heat is carried by the blood throughout the body, and that the task of respiration is to cool the body from excessively generated heat. The authority of Aristotle was so high not only in antiquity but also throughout the Middle Ages, that for this entire period the doctrine of metabolism and nutrition was nothing more than one or another paraphrase of his propositions. A shift in this regard was brought about by the Renaissance, when people moved from speculations about nature to its actual study. In 1613 Sanctorius (Sanctorius, cited according to Voit) published his experiments on weighing food, drink, waste (urine and feces), and the experimental subject himself, establishing a significant shortage of the weight of intake against the weight of output. Weighing a starving person further, when he lost neither urine nor feces, Sanctorius established a significant loss of weight. This invisible path of body losses was named by him insensible perspiration (perspiratio insensibilis) and was accomplished, in his opinion, through the lungs and skin. The result of this first attempt at a quantitative study of metabolism was undoubtedly of great importance, but further steps were impossible due to the complete lack of chemical knowledge and a very vague conception of gas exchange. Around the same time, the famous representative of the iatrochemical school van Helmont (van Helmont; 1577-1644) discovered that during the burning of wood, a gas is formed that cannot support combustion, and that the same substance is formed during the action of acid on limestone, as well as during fermentation. He expressed the thought that metabolism in the body occurs through the fermentation of introduced substances subjected to the action of body juices; in the process, juices used by the body and slag removed from it are formed. Van Helmont already had an idea of chemical elements as indestructible bodies, and of the four basic substances of Aristotle, he denied the indestructibility of earth, fire, and air, but recognized it for water, to which on this basis he ascribed special significance in vital processes, asserting, for example, that the fact of the growth of fish living in water proves the possibility of building animal tissue from water. The important significance of respiration, and consequently of air, for the life of higher animals was, of course, generally known since ancient times, but a clearer conception of this became possible only after the works of Torricelli (1643), Guericke (1602-1686), and Boyle (1662), who proved the materiality of air. Guericke showed at the same time that neither the burning of a candle nor the life of warm-blooded animals is possible in an airless space. In 1674 Mayow (John Mayow, 1645-1679) ascertained that air contains a substance, spiritus nitroaereus, which combines with metals, increasing their weight, turns venous blood into arterial, and reacts during combustion and respiration with combustible substances, as a consequence of which heat is developed. Besides air, this substance is contained in saltpeter (whence its name originated). Mayow's thoughts, which contained the germ of Lavoisier's doctrine, did not receive recognition and were forgotten thanks to the triumph of Stahl's phlogiston theory (1660-1734), which served as a brake on the successful development of chemistry. The doctrine of metabolism, that is, of the entire series of transformations in the body of substances perceived by it from the outside, is the doctrine of the chemistry of life and as such is a branch of chemistry. It is natural, therefore, that it could develop and did develop in connection with and parallel to the successes of chemistry. Lavoisier, the great reformer of chemistry, is at the same time the founder of the doctrine of metabolism in the animal organism. A series of his studies on respiration and his joint work with Laplace on the question of animal heat laid the beginning for the continuous work of subsequent investigators of animal life. In 1789-97 Lavoisier together with Seguin published experiments on the effect on oxygen consumption of food intake, work, surrounding temperature, and the composition of the atmosphere (the oxygen content in it). For connecting the experimental subject with the respiratory apparatus, they used a copper mask that hermetically covered the subject's face. The principles that formed the basis for the construction of later respiratory apparatus, up to and including modern ones, were given by Lavoisier (see Gas exchange, methodology). The main thought of Lavoisier's works: "respiration is a special kind of combustion of substances in the animal body, constituting the main source of animal heat"—contained a program for the development of which the entire 19th century was spent and which passed into the 20th century still far from finished. Lavoisier's successors had to solve a whole series of questions regarding the substances subject to combustion in the body, the quantity and quality of the burning material under various states of the organism, the sites and the very processes of combustion, and so on. The second half of the doctrine of metabolism consists of questions regarding the energy exchange between the external environment and the animal body. The basic proposition of this doctrine, the law of conservation of energy, arose and developed half a century later than the works of Lavoisier and Laplace using examples from the inorganic world; however, the basis for the applicability of this law to the phenomena of animal life—the fact of the generation of heat as a consequence of the combustion of substances in the animal body—was nevertheless given by Lavoisier and Laplace. Lavoisier considered the affinity of oxygen for body substances insufficiently saturated with it to be the cause of combustion in the body, whereas regarding the site of combustion he did not express himself nearly as definitively in favor of the blood of the lungs as his followers came to assert. In any case, both in Lavoisier's time and for almost three-quarters of a century after him, the blood was considered the main site of oxidative processes. After Lavoisier's works, it became possible to compare material intake and expenditure, but only by weight, not by composition, since there were no reliable methods for analyzing complex organic substances of food and excreta. For a fairly significant period of time, investigators of metabolism limited themselves to establishing so-called exchange equations, that is, comparing the weight amounts of elements (C, H, O, N) of food and excreta. At the same time, it was assumed that everything perceived during the day must be excreted during the same time, and therefore the difference in the obtained amounts of elements was attributed to loss through respiration and the skin without any verification of this by experiment. Parallel to these studies went the study of the composition of foodstuffs, nutritive substances, substances excreted by the body and formed within it. Outstanding chemists and physiologists of that time took part in this work: Chevreul, Dumas (1800-1884), Boussingault (1802-1887), Prout (1785-1850), Magendie, Wöhler, Liebig, and others, who laid the foundation for organic and biological chemistry. An outstanding place in this pleiad undoubtedly belongs to Liebig. He not only provided a manual for the analysis of organic substances and in a number of works (see literature) collected and systematized all the scientific material of organic and biological chemistry, but with striking insight and breadth of thought anticipated the paths of further research and practical application of scientific data. Knowledge of the composition of organs and excreta gave him the ability to assert that a gradual transformation of complex compounds into increasingly simpler ones occurs in the organism up to the final products thrown out of the body, and that on the basis of the quantity and quality of these products, conclusions are possible about the quantity and quality of substances disintegrated in the body. He asserted that the urinary nitrogen must be regarded as a measure of the disintegration of protein substances in the body. He saw the task of physiology in studying the course of substance transformations in the body and its changes under the most diverse conditions. Extremely interesting are Liebig's theoretical concepts on the significance of substance transformation in the animal organism: the destruction of organized constituent parts of working organs lies at the basis of all manifestations of the organism's physiological activity, and in particular, therefore, at the basis of the mechanical work performed by muscles.
Therefore, following the opinion prevailing at the time that organized substance consists almost exclusively of protein, Liebig recognized as true nutritive substances only dietary proteins, which were supposed to serve for the restoration of tissues destroyed during work, i.e., for plastic processes (hence the name "plastic substances"). Upon the destruction of tissues, which according to Liebig occurs under the influence of oxygen, nitrogen-containing wastes and a part of the exhaled carbon dioxide are formed. He considered the combustion of protein other than "organized" protein to be completely excluded. Conversely, fats, carbohydrates, and other non-nitrogenous substances do not, in his opinion, take part in the building of body tissues and are oxidized by oxygen in the first place. The oxidation of these substances serves exclusively for warming the body, and therefore these substances received the name "respiratory means" and were not classified by Liebig as true nutritive means participating in metabolism. Protein substances of the food could be oxidized for the purpose of heat production only in the event of a deficiency of respiratory means. B. M. E. vol. XXI. In 1842, an article by J. R. Mayer appeared in Liebig's "Annalen", formulating the law of conservation of energy, and in 1848, his treatise "On Organic Motion in its Connection with Metabolism" was published as a separate book. Sharing the generally accepted view that oxidation takes place in the blood and specifically under the action of oxygen, Mayer links the oxidation processes with muscle work in the following way: "part of the heat arising from the oxidation processes occurring in the capillaries of the muscles becomes latent or expended during muscle activity, and this expenditure is proportional to the mechanical effect produced." Thus, the organized substance of the muscle is merely a transformer of energy, being itself relatively stable: "one cannot deny the wear and tear of organs, but this is an independent question; even in steam engines, wear and tear occurs daily and hourly, yet one cannot equate the materials needed for repairs with the expenditure of coal." Mayer's theory, on the one hand, established a close connection between metabolism and the metabolism of forces, and on the other hand, significantly restricted the main tenets of Liebig's theory: the extreme destructiveness of organized living substance and the exclusively plastic significance of food proteins. [The fact that the life of animals (dogs) cannot be sustained by food devoid of proteins was established by Magendie in 1836.] Due to Liebig's authority, his theory stood in the forefront. A whole series of questions arose from it, which became accessible to experiment thanks to the same Liebig. He provided researchers with a method for the quantitative determination of urea, i.e., the main product of protein breakdown in the body, and Dumas with a method for determining the total nitrogen of food and excreta, and therefore it turned out to be possible to ascertain: 1) whether food nitrogen is entirely excreted by urine and feces, 2) what the effect of various amounts of food proteins is, and 3) how the breakdown of body proteins proceeds during muscular work. Lavoisier's respiration experiments gave him grounds to assert that nitrogen does not take part in respiration, however, a number of researchers of nitrogen metabolism headed by Boussingault could not establish in their experiments the equality of dietary nitrogen and the nitrogen of excreta, whence arose the doctrine of the so-called nitrogen deficit in urine and feces and its excretion through the lungs and skin. The famous study of gas exchange in various animals, conducted (1849) by Regnault and Reiset (see Gas exchange) on a very large scale, gave some foundation to the doctrine of nitrogen deficit, since in many experiments a change in the amount of nitrogen in the apparatus was registered, although small and fluctuating now toward + now toward -. The experiments of Bidder and Schmidt in Dorpat (Bidder, Schmidt; 1852) on dogs and cats, classical in their strict methodology, nevertheless showed the correctness of Liebig's idea that all nitrogenous products of breakdown are excreted with urine and feces, and this was subsequently confirmed by Bischoff and especially by C. Voit and Gruber (Gruber, 1857) in experiments establishing nitrogen equilibrium with verification by sulfur equilibrium. In modern times, Krogh's respiration experiments have finally, one must think, decided this question in accordance with Lavoisier and Liebig. Investigating the influence of various amounts of dietary protein on protein breakdown in the body, Bidder and Schmidt established with certainty an enhanced protein breakdown with an increase in its content in the food and under other equal conditions, with an increase in heat production also taking place. This obviously argued against Liebig's doctrine, according to which only organized protein should have broken down and consequently in these experiments it should have broken down on an enhanced scale only to allow the newly arriving protein to take the place of the old one. Therefore, an amendment was introduced that the animal's need for protein is determined by protein breakdown during starvation, and if more protein is given during feeding than the specified "typical minimum," the excess protein is oxidized by the blood oxygen, just like non-nitrogenous substances, consequently an "excessive consumption" (Luxusconsumption) of this protein takes place as unnecessary for the body's plastics. However, Bischoff rightly pointed out the improbability of the existence of two causes of protein destruction and the groundlessness of oxygen coming into action as soon as the protein supply exceeds a certain limit. Later, the Munich school, headed by Voit and Pettenkofer, using their respiration apparatus (see Gas exchange), proved that during muscular activity, protein breakdown does not increase at all or increases only insignificantly, whereas the breakdown of non-nitrogenous substances (judging by carbon excretion) increases to a significant degree. On the other hand, numerous studies by Voit showed a close dependence of protein breakdown on its intake and the possibility of bringing the organism into a state of nitrogen equilibrium in a short time with very different amounts of dietary nitrogen. Voit further showed that an excess of protein protects non-nitrogenous substances from breakdown, and an excess of carbohydrates in turn spares proteins, so that under these conditions the organism can be brought into nitrogen equilibrium with an amount of dietary protein less than the amount of protein breaking down during the animal's starvation. All these facts contradict Liebig's theory and easily agree with Mayer's theory. Voit's doctrine distinguishes between "organized" protein and protein "circulating" in the body fluids. The former possesses considerable stability and is destroyed only in the process of wear and tear, whereas the latter is easily destroyed upon coming into contact with cellular elements. It remained poorly understood, as Liebig and Pflüger emphasized, how Voit explained the transition of circulating protein into organized protein and vice versa (during starvation). To the Munich school, and in particular to Voit, the science of metabolism is indebted for an extremely systematic elaboration of the chapter on protein metabolism under various nutritional conditions, during starvation, at rest and during work, as well as the doctrine of nutrition. By the beginning of the last quarter of the 19th century, the doctrine of metabolism, extremely enriched by factual material, in its theoretical part continued to remain within the sphere of ideas of Lavoisier and partly of Liebig. The cause of the destruction of substances in the body was recognized as the oxidizing capacity of inhaled oxygen, the site of oxidation as the blood and tissue fluid, the substrate of oxidation as the nutritive substances, and only during starvation the melted organized substance. The latter was recognized as stable, its wear and tear insignificant and replenished at the expense of dietary proteins, since the organized substance itself was considered "living protein." In 1875, Pflüger's famous critical-theoretical article "On Physiological Combustion in Living Organisms" appeared, completely overturning previous notions about the cause and site of oxidative processes in the body. According to Pflüger, it is not the influx of oxygen that determines the breakdown of substances in the body, but, conversely, the intensity of metabolism determines the greater or lesser perception of oxygen, the site of oxidative processes being not the blood, but the cellular elements of the body, i.e., the organized living substance. Pflüger's opinion was reinforced by brilliant experiments from his laboratory, which showed, firstly, that frogs whose circulatory system had been washed out with a physiological sodium chloride solution and filled with it ("salt frogs") continued for a long time to excrete a normal amount of carbon dioxide, and secondly, that normal frogs placed in an atmosphere of pure nitrogen could survive for about 20 hours and excreted a significant amount of CO2 in the process. The experiment of Georg Liebig, proving the excretion of CO2 by frog muscles excised from the body, and numerous subsequent studies of tissue respiration (see Respiration, tissue respiration) made Pflüger's proposition undoubted that "the causes of substance destruction lie in the cells." This same thought is expressed extremely vividly by K.
by Bernard in the following words of his treatise "On the Phenomena of Life Common to Animals and Plants": "if a muscle contracts, will and sensation manifest themselves, thought arises or a gland secretes > then the substance of the muscle, nerve, brain, and gland is disorganized, destroyed, and consumed." At first glance, one might think that scientific thought had returned to Liebig's view, but this would be true only to a certain extent, because the new conception encompassed the functions of all body organs and developed a different point of view on the composition of organized living substance. This latter was no longer considered merely "living protein," but on the basis of studying its breakdown products, it was recognized as being composed "of various substances, including proteins" (Voit), and as being specific in its structure and composition for various organs. These ideas underwent further development in the direction that "living organized substance" is currently viewed not as a homogeneous "substance," but as an extremely complex physicochemical system, specific in each individual case in its structure and composition, in the course and character of the chemical processes occurring within it, and in the products that arise thereby. A general property of these systems, inherent in their structure and composition, is their destructibility and capacity for regeneration, and as a consequence, the metabolism between cellular elements and the surrounding internal environment of the organism—blood and tissue fluid, which is identical for all cells but specifically utilized by each of their types. From this point of view, the specific action of medicinal substances and the specificity of hormones, vitamins, and the like become partly understandable. Now that the study of tissue culture (see) conditions outside the organism has become accessible, when with the help of micrurgy (see) direct action on individual parts of cells has become possible, and with the help of microchemical methods—the study of certain chemical processes in the cell, now the study of tissue metabolism makes further very important advances, especially in the field of cognition of various intermediate stages of substance transformation in tissues. Lavoisier's thought that respiration is a special kind of combustion, serving as a source of animal heat, had already linked metabolism with energy metabolism; however, the principle of energy transformation was not known to Lavoisier, and therefore he could not seek in the process of combustion the source of energy for the mechanical work of the animal. Julius Robert Mayer, who formulated the law of the conservation of energy, pointed out its applicability to the animal organism as well, which, according to Mayer, should be regarded as an energy transformer. However, experimental proof of this was provided for the first time (1891–94) by Rubner in calorimetric studies on dogs, and then (1897–1899) by Atwater on humans. There are two external sources of energy for the animal body: the destruction of food substances or body substances (during starvation) in the body with the release of potential chemical energy from them, and the totality of all influences from the external world on the sense organs or generally on the surface of the body. The magnitude of income from the first source is easily determined by the heat of combustion of substances, determined calorimetrically, but external influences on the sense organs in their totality cannot be measured, and therefore this flaw in the experimental solution of the question is inevitable, but quantitatively it is undoubtedly extremely small. As for the expenditure of energy, during rest and starvation of the animal, it is composed of heat losses (directly by heat or evaporation), of the heat of combustion of excreted urine and feces, as well as of the internal work of blood circulation, respiratory movements, intestinal movements, and the like, which in turn pass almost entirely into heat (the external work of respiratory movements, e.g., forcing air out of the lungs, is obviously extremely insignificant). Hence, under the specified conditions on the part of the animal, both the income and expenditure of energy can be expressed in thermal units, with negligible discrepancies on either side, and compared with each other. It goes without saying that the intake of food or the production of mechanical work, while introducing nothing fundamentally new, only slightly complicates the compilation of the energy balance. The question of whether it is permissible to equate two combustion processes so different in conditions as combustion in a calorimetric bomb and oxidation in the organism with respect to their thermal effects was resolved affirmatively (in 1838) by the St. Petersburg Academician Hess in the form of the following proposition: "the amount of heat accompanying a given chemical process depends only on the initial and final state of the acting bodies and does not depend on the intermediate stages of transformation between them." Therefore, since carbohydrates and fats yield the same products $ ext{CO}_2$ and $ ext{H}_2 ext{O}$ both in the calorimetric bomb and in the organism, their heats of combustion in both these cases are the same; for protein substances, which burn in the organism only to urea, uric acid, etc., a correction must be made. This correction was determined by Rubner, who established the following standard heats of combustion of food substances in the body: 1 g of carbohydrates — 4.1 large calories, 1 g of fat — 9.3, and 1 g of protein — 4.1. Rubner's experiments, and later Atwater's, showed an extraordinary closeness of figures (down to fractions of a percent) of the income and expenditure parts of the balance, which, on the one hand, confirmed the correctness of determining income by heats of combustion, and on the other hand, provided the opportunity to recognize energy expenditure as a summary characteristic of substance breakdown in the body. Proceeding from the energetic conception of nutrition, Rubner conducted a series of observations on the replaceability of food substances by each other and came to establish the so-called law of isodinamics (see) of food substances, according to which under certain conditions of insufficient nutrition, substances destroyed in the body replaced each other in heat-equivalent amounts. From this, the conclusion was drawn that the organism in each given case has a certain "energy requirement," which it can cover with various substances. For protein, however, an exception had to be made: "the impossibility of nourishing the organism exclusively with fat and carbohydrates and completely eliminating the last traces (3–4%) of protein decomposition depends solely on the fact that for certain chemical processes, such as, for example, the replacement of destroyed parts of tissues, protein is necessary, since animals are not able to synthesize this substance" (Rubner). Considering the organism as an energy transformer, Rubner naturally came to the conclusion that in the greater or lesser scale of this transformation, i.e., energy metabolism, one should look for the criterion for the intensity of vital processes. Since, however, energy metabolism is closely connected with substance metabolism, Rubner proposes to speak of general metabolism, even without adding the words "and energy"; in the word "general metabolism" there is already, in Rubner's opinion, an indication of measuring metabolism in a general measure, the energy unit, i.e., the calorie. Rubner's doctrine, revolving in the sphere of ideas of Julius Robert Mayer, while rightly emphasizing the energetic side of metabolism, is nevertheless too one-sided and simplified in its depersonalization of food substances and the valuation of them solely by caloric content. The moment of simplicity undoubtedly played a large role in the popularization of Rubner's doctrine, especially among nutrition practitioners, whereas among physiologists it encountered objections. The failure of experiments with feeding animals mixtures of as pure as possible food substances, calorically fully sufficient, and all the subsequent doctrine of vitamins and one-sided nutrition clearly emphasize the material side of metabolism, without diminishing, of course, in the least the significance of energetics. If we recognize that the basis of the vital activity of "living organized matter" is its destruction, its partial breakdown, and meanwhile this substance undoubtedly possesses dynamic stability, this means that along with the processes of dissimilation and breakdown, processes of assimilation and restoration of losses occur in it at the expense of interaction with those chemical groups and bodies with which it can react and which it can assimilate. This possibility is determined, of course, by the composition and structure of the chemical groups and bodies, and not merely by their energetic significance. P. Research methodology. Research methods for general metabolism and energy are based on the exact quantitative determination of the constituent parts of the income and expenditure of solid, gaseous, and liquid substances. Foodstuffs used in the experiment must be stocked, if they withstand storage, in an amount sufficient for the entire duration of the experiment. Average samples must be taken from the stocks and analyzed according to the task either for food substances (proteins, fats, carbohydrates, salts, fiber) according to the general rules of food analysis or for individual elements ($ ext{C}$, $ ext{H}$, $ ext{N}$, $ ext{S}$, $ ext{P}$, etc.) according to the rules of elementary organic analysis. Of course, preliminary analysis makes sense only in the case when a particular foodstuff is given as food without culinary processing.
Therefore, in experiments with humans, one must in most cases analyze an aliquot part of all proposed dishes, either by mixing these parts or even separately, which of course requires a great expenditure of labor and time. The use of tables of the composition of food products is inadmissible in view of the significant fluctuation in the composition of market products. The use of various kinds of coefficients such as N : C in urine, meat, etc., is also extremely dangerous, an example of which can be seen in Voit's experiments, which according to his calculations prove the formation of fat from proteins, whereas according to Pflüger's calculations with other, more correct coefficients of N : C in urine and meat, they are devoid of any evidentiary value. The duration of the study can, of course, be very different, but a 24-hour period is recognized as the unit of the experiment in time, and the last meal should be no later than 12 hours before the start of the next 24-hour period. At the beginning of each new 24-hour period, after the discharge of urine (in humans voluntarily, in animals by catheter) and, if necessary, after defecation, weighing is performed. Special attention must be paid to the quantitative collection of urine and feces. Urine is usually collected daily, and feces for the most part over the entire period of the experiment. In humans, the collection of urine presents no difficulties with a conscious attitude of the experimental subject; in animals, catheterization is used, but to avoid accidental losses of urine, animals are always placed in cages with a sloping or grid floor, ensuring the flow of urine into a receiver. In cages for small animals, a net of appropriate density is placed obliquely under the grid floor to separate urine from feces. The delimitation of feces belonging to the experimental period is achieved in dogs by giving them a small amount of bones at the beginning and before the end of the experiment, which form a well-formed plug in the intestine, and in humans by giving 300-500 cm3 of milk, which gives a characteristic light milk stool, or charcoal tablets, charcoal suspension, berries, etc. Delimitation in humans is not always sufficiently sharp, but since feces are usually collected for the entire experimental period, lasting at least several days, the error is not of great importance. Methods of urine and feces analysis - see Urine, urine analysis and Excreta, chemical examination. The accounting of gaseous components of intake and output is carried out using respiration apparatuses (see Gas exchange), which make it possible to determine the amount of consumed O2 and exhaled CO2 in long and short-term experiments. The former are necessary where it is a question of establishing material and energy metabolism, while the latter are appropriate when establishing only energy expenditure. Air analyses associated with respiration experiments are carried out according to the rules of gas analysis (see), mostly by the Haldane method. Since in the study of general metabolism of substances and energy, unless there are any special tasks, it is only a question of the metabolism of dynamogenic substances (proteins, fats, and carbohydrates), then the quantitative determination of N and C of urine, inhaled oxygen, and exhaled CO2 is absolutely necessary. Then, from the nitrogen of the urine, the amount of decomposed protein is calculated (N x 6.25), and from the "pure" respiratory coefficient, the share of participation in the expenditure of carbohydrates and fats is calculated, using the Zuntz-Lusk table. Knowing the amount of decomposed dynamogenic substances in the body and their heats of combustion, it is easy to calculate the amount of energy released during this breakdown. Rubner and Atwater's calorimetric experiments, as indicated above, showed excellent convergence of the figures for energy expenditure calculated in this way and established directly in the experiment. If it is intended to establish only energy expenditure, it is sufficient to determine gas exchange or even only the amount of absorbed oxygen; energy expenditure is then calculated from the thermal value of oxygen. Of course, the calculation of general metabolism from the thermal value of oxygen is inadmissible if not only proteins, fats, and carbohydrates burn in the body, but also other substances, e.g., alcohol, or if the transition of carbohydrates into fat takes place in the body, as well as the formation of under-oxidized products, e.g., acetone bodies. Direct determinations of energy metabolism in respiration calorimeters, as requiring expensive and complex apparatus and a large expenditure of labor, are available only to a few laboratories. III. Basal metabolism. General metabolism of substances and energy. A characteristic of the intensity of the general metabolism of substances and energy of the organism in various periods of its life is the so-called basal metabolism, i.e., that breakdown of substances in the body which takes place at the limit possible for a living organism restriction of the activity of all its organs. Basal metabolism therefore embraces the entire totality of those transformations in the body that are necessary to maintain basic vital functions, but as a concept it is still a conditional value, although for a given organism in a definite
Table 2. period of his life is fairly constant. Factors that determine it to a certain extent are weight, height, age, and sex. Taking these factors into account, Harris and Benedict established empirical formulas for calculating normal basal metabolism: for males (over 1 year of age): 66.473 + 13.7516 · kg + 5.0033 · cm - 6.7550 · years; for females (over 1 year of age): 655.0955 + 9.5634 · kg + 1.8496 · cm - 4.6756 · years; for children under 1 year of age: boys - 22.1 + 31.05 · kg + 1.16 · cm, girls - 44.9 + 27.84 · kg + 1.84 · cm. On the basis of these formulas, derived purely empirically, Harris and Benedict compiled tables of basal metabolism, which turned out to be very satisfactory and found wide application. According to these tables, the normal basal metabolism is determined as the sum of two numbers: the base number according to weight and the second number according to height and age, e.g., a man weighing 60 kg, 163 cm, 27 years old. The base number by weight is 892 cal., the second number by age and weight is 647 cal., the basal metabolism is 1,359 cal. (see tables). Table 1. Base number by weight. Weight in kg. For men, For women. Organism weight cannot of course be considered the determining factor of metabolism in view of the varying composition and structure of the organism, therefore calculation per 1 kg of weight, often used for comparison purposes, is very imperfect, but still permissible if we are talking about comparing organisms that are identical at least in external constitution signs. Thus, organisms of close height, weight, muscle development, and stoutness usually also have a close basal metabolism, i.e., they possess a close amount of "organized living substance," referred to for brevity as "living protoplasm," by the vital activity of which the basal metabolism is determined. Folin showed that on a protein-free diet, creatinine is excreted as a product of endogenous metabolism. American researchers (Palmer, Means, and Gamble) compared creatinine excretion with the observed heat production and found fairly constant ratios: in men, 0.98 cal. per 1 mg of excreted creatinine, and in women, 1.26 cal. According to Burger, this creatinine coefficient is a good index of body muscle mass. Rubner considers the body surface as the surface of its cooling to be the main factor determining metabolism, believing that heat loss determines heat production. If this is to a certain extent acceptable in relation to warm-blooded animals and under certain conditions, as a principle it is absolutely incorrect. For practical purposes, relating the magnitude of metabolism to body surface is just as permissible as relating it to weight. The formula of D. and E. F. Du Bois is recognized as the most satisfactory for determining human body surface: surface in cm2 = kg0.425 × cm0.725 × 71.84, or simpler — surface in cm2 = 167.2 × \/kg × \/cm. This formula is very accurate. According to the same authors, the basal metabolism in large calories per 1 m2 of surface and per 1 hour fluctuates in connection with sex and age as follows: At the present time, basal metabolism is calculated either according to Benedict or according to Du Bois, since the results are almost identical. The basal metabolism of a person of average constitution and stoutness is assumed to be equal to 1 calorie per 1 kg of weight per hour, i.e., for example, at 70 kg per day it will be 70 × 24 = 1,680 calories. However, during sleep, metabolism decreases even further in view of an even greater restriction of vital activity and is considered equal to 0.9 per 1 kg per hour. In ordinary life, the so-called working increment is always added to the basal metabolism, caused by muscle activity, the intake and digestion of food, if physical heat regulation is insufficient, etc.
M. Shaternikov. Pathology of Basal Metabolism. Deviations of metabolism from the norm can be noted by tracing those unusual substance transformations that are observed in various diseases. But one can also have in mind the other side of metabolism and evaluate from the most general point of view the amount of substance that has split in the organism or, which is the same thing, determine the amount of heat formed thereby. The data concerning the measurement of the general metabolism thus understood do not characterize the details and changes in the course of individual reactions within the organism. Up to the present time, clinical medicine has been interested chiefly in the changes of so-called basal metabolism and partly in changes of the specifically dynamic action of food. The increase in basal metabolism per se is not accompanied by an increase in temperature, and the excess of generated heat leaves the organism by various pathways. That increase in temperature which is observed in a febrile disease is a consequence of a disorder of thermoregulation with a simultaneous increase in metabolism. The increase in heat production in these cases can be considered a constant phenomenon, but in various stages and cases of the febrile process, it is expressed differently. Being very strong at the beginning with a high and steep rise in temperature, it subsequently becomes smaller. The increase in basal metabolism sometimes reaches up to 48%. According to some authors, the relationship between the increase in metabolism and temperature corresponds to the rule derived for chemical reactions by van't Hoff ("a 10° rise in temperature corresponds to a 2-3 fold increase in the reaction rate"). The respiratory quotient RQ in fever is elevated only during chills as a result of glycogen destruction during muscular movements. The rest of the time it is rather below normal (participation of fat oxidation processes).-Malignant neoplasms and leukemia in many cases likewise increase basal metabolism.-Anemia remains without particularly characteristic effects on basal metabolism, and likewise polycythemia (metabolism is sometimes increased).-Diseases of the liver and kidneys are not associated with an increased metabolism. However, with a significant increase in the spleen in hepato-lienal syndromes, as well as in hypertension, metabolism may, although not necessarily, be increased.-Likewise, no characteristic changes in basal metabolism have been noted for diseases of the lungs and heart. If thus the influence of diseases of various internal organs on basal metabolism is slight, the same cannot be said about lesions of the endocrine glands. The thyroid gland is of greatest importance for the entire pathology of general metabolism. Removal of this organ significantly lowers metabolism (by 20%), myxedema sometimes even more (by 50%). Likewise, one can find lowered metabolism figures in ordinary goiter. In contrast to this, the internal administration of thyreoidin or subcutaneous administration of thyroxine greatly increases metabolism. In Basedow's disease, a typical increase in basal metabolism is observed. By means of these same analyses, it was possible to successfully control the effect of drugs and surgical intervention in diseases of the thyroid gland.-The study of basal metabolism in lesions of the pituitary gland encounters all those difficulties that are met on the path of studying the hypophysis. They consist in the fact that the hypophysis, with its small size and shallow location, is a complex formation and, moreover, irritation of the entire brain region lying near this organ also produces changes in metabolism. In acromegaly, the majority of authors speak of an increase in gas metabolism, while cases of dystrophia adiposo-genitalis are very often associated with a decrease in basal metabolism.-Diabetes insipidus is not accompanied by a change in basal metabolism. General metabolism in diabetes mellitus deserves special attention. For decades, great importance was attached to the question of general metabolism in diabetes mellitus. Mention was made of its increase and its decrease. At the present time, it is recognized that there are no strictly characteristic changes in basal metabolism for diabetes. Only in cases of very severe forms of diabetes can an increase in metabolism be seen as a rule. But these increases, which are amenable to dietary influence, are difficult to attribute entirely to diabetes, since the patient is moreover also emaciated, suffers from ketonuria, and therefore the disturbance of his metabolism depends on a number of factors. Experimental diabetes caused by removal of the pancreas or phlorhizin poisoning is accompanied by an increased metabolism.-Even greater importance than in diabetes was ascribed to general metabolism in obesity, since fat, regarded as a reserve material, ultimately originates from nutrient substances that have not been destroyed in metabolism. Conversely, with insufficient feeding, the missing calories are extracted in the greatest quantity from fat reserves, which noticeably decrease. The expenditure of calories, depending to a significant extent on muscular activity and the expenditure of fat, also increases depending on the mobility and activity of the subject being studied. Thus, the deposition and expenditure of fat are regulated by two factors that are difficult to account for: the activity of the observed subject and his food, which is usually determined in its quantity by appetite. The question arises—can the excessively eaten food also be decomposed down to final products of disintegration (apart from the participation of muscles)? The research on starving individuals and observations during prolonged undernutrition indicate that in principle some change in the magnitude of basal metabolism can occur. In both cases, the magnitude of basal metabolism (i.e., the amount of oxygen consumed) noticeably decreases. From this it follows that one cannot speak of the absolute constancy of the basal metabolism figure, and if metabolism can decrease under the influence of nutrition, it probably can also increase. The increase in metabolism from food is always noted within a few hours. Fats and carbohydrates increase metabolism by an imperceptible amount, protein nutrition acts much stronger. A specifically dynamic action was attributed to proteins. It is possible, however, that not only the postprandial, but also the morning basal metabolism in cases of prolonged overeating (both protein, fat, and carbohydrate) settles at higher figures of oxygen consumption. Such an ability, if it exists, would guarantee the organism against the transformation of excess nutrition into a burdensome fat ballast. Not all investigators recognize the existence of such a "luxus consumption" (Luxusconsumption). For the time being, in the doctrine of obesity, obesity from overeating and from lack of movement is recognized above all else. In these cases, basal metabolism presents no deviations from the norm. In addition, the existence of obesity associated with the state of internal secretion is also recognized. In these cases, it is possible to establish a normal appetite with a decrease in metabolism or, with a normal basal metabolism, a insufficiently pronounced rise from the specifically dynamic influence of nutrition. As regards the manner in which the endocrine influence affects general metabolism, according to some, incretes act directly on the oxidation processes in the organism, while others consider it possible that the endocrine glands, via the central nervous system, act on the entire behavior of the organism, which is closely connected with the work of muscle activity, and in this way lead to an increase in metabolism. E. Fromhold. Pathological anatomy of disorders of substance metabolism can manifest itself in various ways. First of all, it can be pointed out that a whole series of serious irregularities in substance metabolism, e.g., of nitrogen, carbohydrates, salts, may not be accompanied by any morphological changes in organs and tissues. In other cases of general disturbance of this or that substance metabolism, patho-anatomical changes are observed that represent the consequences of incorrect substance metabolism and manifest themselves in atrophic processes or in the form of various pathological deposits (see Arteriosclerosis, Atrophy, Starvation, Gaucher's disease, Diabetes mellitus, Cachexia, Niemann-Pick disease, Obesity, Gout). Local manifestations of metabolic disorders in tissues are expressed in the appearance in cells or intercellular spaces of various materials that in a physical or chemical sense are uncharacteristic of the given tissue, which is conventionally designated as degeneration or infiltration of tissue or deposition into tissue (see below). IV. Protein Metabolism. Nitrogenous metabolism (syn. protein metabolism)—in a broad sense, the totality of all phenomena in the organism associated in one way or another with the metamorphosis and transport of nitrogenous compounds through the body under various conditions of nutrition and state of the organism. These phenomena fall into three groups: 1) digestion and absorption of nitrogenous compounds in the intestinal tract; 2) transformations of nitrogenous compounds and products of their breakdown in the body fluids and tissues (intermediate nitrogenous metabolism); 3) excretion of nitrogenous compounds from the organism through various excretory organs. In particular, nitrogenous metabolism is also understood as the establishment of nitrogen balance (see below). Nitrogenous digestion products—amino acids and certain polypeptides—upon absorption penetrate through the intestinal mucosa into the capillary blood, then into the portal system of the liver and from there further into the general blood circulation, significantly increasing the content of amino acid nitrogen in it.
At the same time, the amino acid nitrogen of tissues absorbing free amino acids from the blood also increases; thus, in an experiment by Folin and Denis, after introducing egg white (61 g) into the loop of the small intestine of a cat, an increase in "residual" nitrogen (non-protein blood nitrogen minus urea nitrogen) in the portal vein blood from 14 to 22 mg%, in the carotid artery blood from 12 to 22 mg% (i.e., by 57% and 83% respectively) was found after 1 1/2 hours; 45 minutes after the administration of glycocoll, the residual nitrogen in the portal vein increased by 433% (from 12 to 64 mg%), in the carotid artery by 140% (from 15 to 36 mg%), and in the musculature by 43% (from 223 to 319 mg%).
In all these experiments, urea nitrogen initially remained unchanged. After a certain interval of time, the amount of amino acid nitrogen in the blood and in tissues decreased (in the former sooner than in the latter), and the amount of urea began to increase. Example: in a human after giving 135 g of gelatin, the amino acid nitrogen in the blood after 1 hour (in mg%) was 9.4, after 2 hours 11.4, after 3 hours 7.2, after 8 hours 6.8 (before taking gelatin - 5.5).
At the same intervals, the urea content in the blood in mg% corresponded to 16.0 - 14.2 - 20.2 - 25.0 (before a meal - 17.3). Different tissues absorb amino acids unequally, as can be seen from the following table: Table 1. Amino acid nitrogen and urea in a dog Before injection (mg%) After intravenous injection of digested meat extract after 1/2 hour (mg%) after 4 hours (mg%). Amino acid nitrogen: in muscles .... in liver .... in kidneys .... Urea in blood .... 4.7 5 70 156 88 13.7 71 71 89 11.
During periods of increased concentration of amino acids in the blood, a certain amount of them manages to pass into the urine. Between the amino acids of the blood (Ak), the amino acids adsorbed by tissues (At), and the tissue protein (Bt), a certain inverse equilibrium must exist, which can be symbolically expressed as Bt ⇄ At ⇄ Ak. The inflow of new batches of amino acids into the blood, and from it into the tissues at the height of digestion, leads to a violation of the indicated equilibrium, and according to the law of mass action, the amount of tissue protein must increase.
However, the amino acids and peptides adsorbed by tissues selectively go toward the synthesis of more complex polypeptides, or protein molecules, in these tissues; unused amino acids can flow back into the blood (during its subsequent relative depletion of amino acids) and be adsorbed again elsewhere. As a result of such redistribution of amino acids, some time after their entry from the intestine, all tissues are to a certain extent "saturated" with them, thereby carrying out the indicated protein synthesis; however, many amino acids remain unused and undergo deamination in tissues (chiefly in the liver), as a result of which NH3 and keto acids are formed: the former in combination with CO2 gives urea (see), the latter partially undergo further oxidation, reaching CO2 and H2O, with the release of energy, and partially can be converted either into glucose and glycogen or into higher fatty acids and fats.
The breakdown of amino acids is a very complex process, many details of which are far from elucidated. Of great importance for understanding the phenomena related here is the observation of Embden (by the method of passing amino acids through a surviving liver) that α-amino acids undergo transformations not like their corresponding fatty acids, but like acids with 1 fewer carbon atoms. Thus, for example, leucine (α-aminoisocaproic acid) under experimental conditions yields acetone just like isovaleric acid (with one C less), whereas the acid corresponding to leucine (isocaproic) does not possess this property. From this, the conclusion was drawn that amino acids upon decomposition are converted into fatty acids with the loss of one carbon atom: R - CHNH2 - COOH → R.COOH.
Thus, during this destruction, three processes take place: 1) loss of the NH2 group (see Deamination), 2) loss of CO2 from the COOH group - decarboxylation, 3) oxidation. The question of in what order these processes proceed in various amino acids has not yet been fully resolved, but a number of facts now make it possible to establish a general scheme for the course of these reactions. Ordinary research methods are as follows: 1) study of the transformations of certain amino acids when passing solutions containing these amino acids through the blood vessels of a surviving liver.
2) Feeding large amounts of certain amino acids, the transformation products of which do not manage to oxidize to the end and are excreted in the urine as intermediate products. 3) Administration (per os, intravenously, per rectum) of such amino acid derivatives that are alien to the animal organism and in their transformations undergo only the initial stages of changes during deamination or decarboxylation and then are excreted in the urine, where they are accounted for. 4) Introduction of certain amino acids into the organism of a diabetic or an animal with experimental diabetes (after depancreatization or phlorhizin poisoning), as well as into the organism of an alkaptonuric (see Alkaptonuria) in order to observe the transformations of the introduced substances (or their derivatives) into sugar (in diabetes) and into homogentisic acid (in alkaptonuria). Similar observations are made in other metabolic diseases arising spontaneously or experimentally.
All these methods led to the concept that the first stage of amino acid transformations is deamination. This would seem to be contradicted by the relatively strong bond of N and C in amino acids, but under the influence of bacteria, as is known, the rupture of this bond occurs easily [e.g., phenylalanine (C6H5-CH2.CHNH2.COOH) is converted into phenylpropionic acid (C6H5.CH2.CH2. .COOH)]; similarly, in the organism after abundant feeding with tyrosine (OH\C6H4/CH2.CHNH2.COOH), it was possible to notice the appearance in the urine of p-oxyphenyllactic acid (C6H4\CH2.CHOH.COOH). According to Dakin, the first steps towards the destruction of the N and C bond probably proceed in such a way that first, according to the general rule, the β-carbon atom is oxidized,
CH2
CHNH2
CNH2 I
COOH
COOH
COOH, after which a double bond appears between the a and Β atoms with the subsequent rearrangement of the compound R - CH - C.NH2.COOH → NH into the imino acid R-CH2-C-COOH and its hydrate OH R-CH2-C-COOH → NH2. The probability of such an assumption follows from the fact that the compound C(CH3)3 - CH.NH2.COOH (a-aminotrimethylpropionic acid), in which a double bond cannot appear between the a and β carbon atoms, is almost not burned in the body. Imino acids or their hydrates, as unstable bodies, easily lose ammonia, turning into keto acids: R.CO.COOH. Thus, the process of deamination is accompanied by oxidation (oxidative deamination). The previously universally recognized notion that deamination proceeds via hydrolysis (R - CH.NH2.COOH + H2O = R-CHOH.COOH + NH3) was based on such facts as the appearance in the urine of hydroxy acids (e.g., lactic acid) after abundant feeding with corresponding amino acids (e.g., alanine), as well as the fact that the fate of the amino acid and the hydroxy acid corresponding to it is in a number of cases the same; e.g., both leucine [(CH3)2-CH.CH2.CH(NH2).COOH] and the leucine acid corresponding to it [(CH3)2-CH.CH2.CHOH.COOH] can be sources of acetone bodies in diabetes (see below).
However, recent studies have established the incorrectness of this view; on the contrary, a number of facts indicate that during deamination, keto acids appear mainly, while alcohol acids (hydroxy acids) appear as a secondary product (reduction of keto acids) or as a product of an accompanying side process. The main facts that compel one to draw such a conclusion are the following: 1) the possibility of mimicking the appearance of keto acids from amino acids in vitro (via oxidation with permanganate); 2) the appearance of keto acid in the urine upon the introduction of foreign amino acids into the organism: for example, phenylglycocoll (C6H5CH.NH2.COOH) yields phenylglyoxylic acid (C6H5.CO.COOH) with an insignificant amount of benzoic (C6H5COOH - decarboxylation product) and mandelic (C6H5.CHOH.COOH - reduction product) acids. In addition, a keto acid is a more reactive body than the corresponding hydroxy acid, and is more capable of reconversion into an amino acid than a hydroxy acid; this gives greater weight to the notion that the main compound during deamination /OH are keto acids, i.e., RC → COOH → R-C - COOH + NH3. However, there are facts that do not fit into such a scheme.
Reactions are also known in which keto acids can arise not via the stage of imino acids; for example, phenylglycocoll (C6H5CH.NH2.COOH) can be converted into phenylglyoxal (C6H5 - C - C - H) and further oxidized into the corresponding keto acid - phenylglyoxylic (C6H5 - CO - COOH). However, this course of the process cannot be considered typical. After the formation of the keto acid, decarboxylation occurs, yielding an aldehyde R - O and then the corresponding acid R - COH. Thus, as a result, we have an acid 1 carbon atom poorer than the initial amino acid, which agrees with Knoop's rule. The general scheme of these transformations is as follows: R → amino acid G = NH imino acid → COOH imino acid hydrate
can be called ketoplastic amino acids, while the amino acids of the first group are aketoplastic. The introduction of aketoplastic compounds in diabetic acidosis as a rule lowers the formation of acetone bodies and consequently they are also antiketoplastic.
3) Of the remaining amino acids, tryptophan, lysine, glucosamine (histidine?) do not belong to either the one or the other group, and therefore can be called aketo- and aglyoplastic amino acids. In the height of absorption and deamination of amino acids (and urea formation), a peculiar phenomenon takes place - enhanced roil
R -NH3 | -CO2 | +O | -> C-O -> C=0 -> C=0 ketocarboxylic acid \ fatty dehydrogenation entry of water The fatty acids resulting from the aforementioned reactions share a fate in the organism common to these compounds (see fat and carbohydrate metabolism). However, a number of reactions that amino acids undergo in the process of deamination and decarboxylation determines to a certain extent their further course of transformation in the organism both in the direction of final combustion to CO2 and H2O, and partly in the direction of synthetic reactions (conversion into carbohydrate and fat). According to the general rule of oxidation of fatty acids (see fat and carbohydrate metabolism), the β-carbon atom acquires an OH group, and then upon further oxidation 2 carbon atoms are split off. However, this rule can apply only to monobasic fatty acids with an unbranched chain and, moreover, a sufficiently long one (five to six C). The fatty "residues" of amino acids, with the exception of normal valeric acid from normal leucine, do not belong to this well-studied group, but for the most part have either shorter chains, or branching, or represent oxy- and keto acids, dicarboxylic acids, etc. Systematic study of various amino acids with respect to obtaining products from them that are excreted through the urine in pathological cases (see above diabetic and alkaptonuric organisms) makes it possible to form some idea of the further transformations after deamination. All known amino acids that make up body and dietary proteins can be divided into three groups: 1) amino acids that can be converted into glucose — glycoplastic: glycocoll, alanine, serine, cystine, aspartic acid, glutamic acid, proline, arginine (histidine?). 2) Amino acids that do not produce gluconeogenesis (in diabetic organisms, in normal ones such gluconeogenesis can be achieved by a longer path) — aglycoplastic: valine, leucine, isoleucine, phenylalanine, tyrosine (histidine?). These amino acids in diabetic organisms produce acetone bodies (see) instead of sugar, therefore their deamination, decarboxylation, oxidation, and entry into tissues lead to an increase in heat output. An illustration can be provided by Lusk's experiment (Figure 1), from which it can be seen that after the ingestion of protein food, the course of heat output and the course of nitrogen excretion in the urine (by hours per day) run completely parallel to each other. Such an influence of protein food substances — Ingestion of protein food 40 Cal. 2.0 g 1.5 'W Hours 22 0 3 6 9 12 16 18 21 — Figure 1. Lusk's experiment: columns at the top — heat output; dashed curve — excretion of N in urine — was known for a long time, and M. Rubner called it the specifically dynamic action. The cause of this phenomenon is still a subject of discussion. In any case, everyone apparently agrees that the penetration of protein digestion products into tissues produces in them (under normal conditions) a kind of "irritation," the result of which is a noticeable rise in heat production (resp. absorption of O2 and evolution of CO2). The specific dynamic action of proteins does not manifest itself 1) under conditions causing increased heat production (low temperature, work); 2) under enhanced synthesis of proteins in tissues occurring at the expense of dietary proteins, e.g., during vigorous growth or after prolonged fasting. Nitrogen balance. Nitrogen equilibrium. With identical day-to-day intake of nitrogen into the organism, in the system protein — tissue amino acids — blood amino acids, such a dynamic equilibrium is established in which the amount of nitrogenous compounds broken down in the tissues (deaminated) is equal (in terms of nitrogen content) to the amount entering. This is expressed externally by the fact that the N balance (N food - N feces - N urine) is equal to 0. Such a state in the organism is called nitrogen equilibrium. If, at an established nitrogen equilibrium, the level of nitrogen in the food is increased and maintained for some time, then due to the influx of amino acids into the tissues, protein synthesis in them will increase, but at the same time the accumulation of protein masses as labile bodies simultaneously enhances the breakdown of protein molecules, and after some time (after several days) a new nitrogen equilibrium is established at a new, elevated level of N entering the tissues. It must be emphasized that the factor establishing the equilibrium is, ceteris paribus, the level of N in the food. With a decrease in dietary N, the relations change in the opposite manner, and as a result nitrogen equilibrium is again obtained at a new, lowered level of nitrogen. An illustration of what has been said can be provided by any experiment on establishing the nitrogen balance. From Fig. 2 (Voit's experiment on a dog) it can be seen that with the transition to a diet with an increased nitrogen content, the dog retained 26.4 g of nitrogen, resp. synthesized 165 g of protein; in the five days after the decrease in food nitrogen, it lost 14.7 g of nitrogen, resp. lost 91.9 g of protein from body reserves. The establishment of nitrogen equilibrium under normal conditions occurs after a short period of time; in convalescents and generally after fasting, partial or complete, the period with a positive nitrogen balance is significantly prolonged, which depends on the preceding depletion of tissues in protein. Positive N balances also occur during tissue growth (in young organisms, in pregnant females) and during periods of training in muscular work, which leads to hypertrophic changes in muscles. Thus, Caspari in a dog (18-day experiment) showed that with identical food (caloric value 2,088–2,099; N=25.11 g pro die) and identical daily work (about 600 cal.), approximately on the 6th day a significant nitrogen retention began to appear, which can be considered a consequence of protein synthesis in muscle tissue. However, with an established muscular system, under normal working conditions, no difference is found in protein expenditure when comparing nitrogen metabolism during periods of work and during periods of rest, as can be seen from Table 8 given below. Table 8. Average figures for 1 day Food Periods N in g Calories Rest (6 days) ... 5.9 2,300 Usual work (9 days) ... 6.0 3,000 Strenuous work (4 days) ... 5.9 3,200 Nitrogen: total 4.77, ammonia 0.35; 4.40, 0.38; 3.94, 0.42; creatine and creatinine 0.605, 0.60, 0.56. From what was said earlier, it follows that the more N there is in the body, the more of it is required in the food to keep the organism in nitrogen equilibrium; therefore, it is completely clear that persons with well-developed musculature require a larger protein ration than persons of the same weight with less developed musculature. On the other hand, it is obvious that low protein regimens, applied for a long time, lead to a decrease in protein reserves in tissues. In this connection, Kestner's experiment, performed during the last economic crisis in Germany on clinic patients not suffering from metabolic diseases, is very demonstrative. Table 9. Days Food N Feces N Urine N Balance N * 7.3 1.8 3.6 + 1.9; 8.6 1.8 3.1 + 3.7; 8.1 1.5 6.4 + 0.2; 7.9 3.6 5.0 -0.7; 12.5 1.4 4.0 + 7.1; 13.9 1.8 4.7 + 7.4; 13.2 3.2 4.3 + 5.7; 8.0 2.3 3.0 + 2.7. Days marked with an asterisk indicate days of giving 110–120 g of meat. From Table 9 it can be seen that with the very low nitrogen content in the food usual for the selected patients (only one of the six cases is presented here), the nitrogen balance undergoes significant fluctuations with positive and negative signs due to the incomplete identity of the food from day to day. When 110–120 g of meat was added to the ration, the nitrogen influx increased significantly (by 60–70%), but the amount of protein broken down in the organism did not increase as we might have expected, so that the N balance increased significantly in the positive direction. This indicates an enhanced protein synthesis in the tissues of the experimental subjects, arising as a result of the extreme depletion of their protein on the starvation regimens of that time: in such a state, the tissues greedily absorbed all the proteinogenic material coming from the intestine. If nitrogen equilibrium still takes place on these low-nitrogen diets, then one can only conclude from this that nitrogen equilibrium is by no means an indicator of the well-being of the organism, but merely gives external expression to the resulting dynamic equilibrium between body protein and nitrogenous substances entering the blood from the intestine. For any normal organism, one can find such a level of food nitrogen below which the organism could no longer come into a state of nitrogen equilibrium, but would always give a negative balance; such a minimum amount of food nitrogen for establishing nitrogen equilibrium in the eyes of some researchers is an indicator of the minimum requirements of the organism for nitrogen (under given conditions); it was called the "physiological minimum".
However, the "physiological minimum" is an indefinite value depending on many causes—on the individual's constitution, the degree of fatness, age, and so forth, as well as, ceteris paribus, on the amount of nitrogen-free (mainly carbohydrate) components of food. By increasing the latter and bringing the caloric value of food to an excessive level, it is possible to achieve nitrogen equilibrium at a very low protein content in the food (see below), which indicates its insignificant breakdown in the body under such conditions. With excessive nutrition exclusively on carbohydrates, the breakdown of protein in the body reaches particularly low values. Rubner regards the nitrogen excreted under such conditions (when protein practically does not serve the body's energy needs at all) as an inevitable loss by the tissues and calls this amount the "wear and tear coefficient" (Abnutzungsquote). The average value of the wear and tear coefficient according to Lauter's calculations is 0.053 g N pro die per 1 kg of weight (human), i.e., with an average weight of 70 kg this amounts to 3.7 g N, resp. 22.2 g of protein per day (assuming 16.6% N in protein). The determination of these values is of purely theoretical interest: practically, the level of protein in food many times exceeds the value of the wear and tear coefficient. The question of human protein requirement was one of the first questions in the history of the science of nutrition. Carl Voit solved it partly by using general statistical material, partly on the basis of more precise observations in individual families. The obtained data were then verified in the laboratory on individual individuals (analyses of food, urine, feces, gas exchange). "As an average value from a large number of observations," Voit writes, "I deduced the requirement of an average worker to be 118 g of protein and 328 g of C on a mixed diet consisting of a certain amount of meat and plant foods." Since 118 g of protein already contains 63 g of C, the remaining 265 g of C can be represented by 500 g of carbohydrates and 56 g of fats. This norm thus related to an "average worker with sufficiently developed musculature to perform average work." Voit believed that food protein is not needed to serve as a source of energy, but to maintain the protein composition of muscles at a constant height; on this basis, he spoke out in favor of increasing nitrogen in the food of individuals having more developed musculature. "To preserve a developed working organ (for example, in a blacksmith) requires more protein than is required by a weak tailor." Later Atwater, using the same methodology, settled on a value of the protein norm of 100 g (for sedentary work) per day. However, this amount of protein seemed exaggerated to some researchers, and they strove to substantiate lower protein norms for humans. All these works boiled down to observations of nitrogen balance in humans at a low level of N in food. Leaving aside short-term experiments, one can first of all point to the work of Neumann (1902), who showed in experiments on himself, lasting 120 and 321 days, the possibility of maintaining weight and nitrogen equilibrium at the level of 79-74 g of protein (when converted to 70 kg of body weight) at 2,737-2,000 cal. (per 1 kg of body weight approximately 1 g of protein and 39-28 cal.) with light work, and the subjective indicators of the state of the body (working capacity, health, etc.) were noted by the author as positive. Soon after, Chittenden (1905) organized a "mass" experiment, lasting 6--9 months, on a group of 25 people (scientists, military personnel, orderlies, and professional athletes), while monitoring weight and examining the nitrogen balance from time to time. Nitrogen equilibrium was sometimes achieved at 9-6 g N in food in soldiers and scientists and at 11.5-9.0 g in athletes. However, nitrogen equilibrium was not always obtained, and some of the subjects could not achieve it at all; moreover, weight losses were sometimes very significant (some individuals, however, gained weight). The author concluded that his experiments proved the possibility of maintaining N equilibrium without loss of strength and working capacity at 40-60 g of protein in food; at the same time, he expressed the conviction that the usually consumed larger amounts of protein adversely affect the body, allegedly burdening it with an excess amount of products of nitrogenous metamorphosis subject to excretion. Some authors (Benedict et al.), criticizing Chittenden's experiment, note a number of essential details that significantly diminish his conclusions. Thus, from the experimental data it is seen that the subjects showed low N digestibility, which should be linked precisely with low protein regimens, since in experiments on animals such a connection has long been studied not only in relation to protein, but also other nutrients. Furthermore, the exhaustion of the majority of test subjects was emphasized, and such organisms, as already indicated above, possess a great ability to retain food protein; the author's reference to the preservation of the subjects' working capacity cannot properly be considered an essential indicator of the satisfactoriness of the diet, since, firstly, there is an element of subjectivity in this concept, and secondly, because the capacity for work is preserved even in fasting subjects. On the other hand, the performance of work (muscular) is the result of the transformation of energy in the body, freed from the destruction mainly of nitrogen-free organic materials, which in Chittenden's experiments were contained in the food in sufficient quantity. A very curious fact is also that Chittenden's athletes returned to their former diets after the cessation of the experiment, which of course they would not have done if Chittenden's diets had fully satisfied them. A few years after Chittenden's work, Hindhede (1913) performed the same long-term experiments on individual humans with continuous determination of nitrogen balance; at the same time, he set himself the goal of showing that it is possible to achieve an even greater reduction of nitrogen in food (4.4-11 g N pro die) by using potatoes with margarine and condiments (onions, fruits) as food. The results of Hindhede's experiments are negative. The regimens he introduced led to permanent N loss. Experiments with a reduced protein content in food, attempting to substantiate the possibility of doing without a low protein norm in human nutrition, are refuted by experimentally established (in animals) cases of a very sharp decrease in the body's resistance to all kinds of infections on low protein regimens. Finally, mention should be made of Haecker's observations on cows that the negative effect of protein-poor diets (weakness, emaciation) manifested itself only in the 3rd year of their application, and before this period the animals did not differ in any way from the norm. These facts with great obviousness should warn against hasty conclusions in favor of lowering human protein norms. The experiments of Neumann, Chittenden, and Hindhede cited above do not in essence contradict Voit's protein norm at all: one could draw only one correct conclusion from them, that a person can maintain nitrogen equilibrium at low protein regimens for a more or less long time in the presence of a sufficient caloric intake in the food to cover energy requirements. Sherman (Sherman; 1920) collected 109 cases from the literature where the protein minimum per 1 kg of weight was established at 0.63-0.64 g (with fluctuations from 21 g to 65 g pro die per person). Discarding the extreme values, the author derives an average of 40.6 g, i.e., 0.58 g of protein per 1 kg of weight. However, it is certain that the establishment of nitrogen equilibrium for a long time at low protein regimens is possible only after the depletion of the body's protein reserves under conditions of sufficient calories. Whether the amount of protein in food corresponding to such a minimum nitrogen metabolism can be considered optimal for humans in general is evident from experiments on overfeeding test subjects with protein food under the condition of a nitrogen minimum. From Kestner's experiment cited above, it follows that the additional food nitrogen in this case does not appear in the urine, but goes to the new formation of protein masses in the body. Similar observations were made at the same time by Hösslin, and earlier by a number of other authors. Thus, in Grafe and Koch (Grafe, Koch; 1912), a 35-year-old factory worker after severe malnutrition gained 20 kg in weight within 6 weeks and retained 535 g N and still had not reached nitrogen equilibrium. Obviously, the abundant nitrogen retention manifested in these cases expresses the incompleteness of the body's protein composition before the experiment (under low protein regimens), since under normal conditions such retention day after day should decrease and in a short time be replaced by nitrogen equilibrium. All these data allow us to interpret the results of studies on the reduced protein regimen in such a way that in them we are essentially dealing with protein malnutrition (Eiweissunterernahrung), and therefore the magnitude of the protein requirement must be sought not in the protein minimum, but at such levels of nitrogen in food at which a sufficient protein reserve (protein depot) is organized, and the shift of nitrogen equilibrium in one direction or the other occurs rapidly.
A number of American authors assume that the minimum allowable amount of protein in the diet should be considered 1 g of it per 1 kg of weight. However, taking into account that dietary proteins are not qualitatively identical, the majority of physiologists consider it possible to raise the protein norm to such a level that the caloric value of protein in the food constitutes 10-15% of the total caloric value of the food (at 3000 calories - 75-110 g of protein). According to Voit, protein (118 g) contained 16% of the food energy. Thus, the Voit norm is higher than all other norms. The correctness of the latter is confirmed by the fact that the majority of people (unless they have to perform very heavy labor, when with the increase in caloric value the level of N in the food inevitably grows, since it is practically difficult to choose such a combination of food where a high caloric value is not associated with a large protein content) consume protein during moderate work precisely within these limits. Thus, the statistical work of Heiberg (1921) on the material of households (1,000 cases) from 1897-1916 established fluctuations for Copenhagen in protein of 94-118 g, in villages - 93-149 g, in provincial cities - 84-103 g. In later times, a number of authors when observing the urine N of a large number of experimental subjects give values indicating the approximate degree of protein expenditure in the body with a free choice of food: Benedict (1919) in student-athletes - 75-81 g, Beard (1927) on 400 female students - 76.7 g, Denis and Borgstrom (1924) on 233 medical students - 76.1 g (all numbers per 70 kg of weight). According to the materials of the Institute of Nutrition Physiology in Moscow, collected on the basis of a very large number of literary data, protein consumption among people of various professions, as can be seen from the attached Table 10, varies either around the Voit norm or slightly lower - 70-80 g of protein, thus confirming the correctness of the above-given values of the protein norm for humans. Quality of proteins. The question of the amount of protein required for a person encounters another question - about the qualitative difference of protein. If dietary proteins reach the tissues in the form of amino acids, then the food protein that contains the amino acids required by the organism in the proper quantity, absolute and relative, will possess the best quality. Since in different proteins we encounter different combinations of amino acids, it is quite obvious that not all dietary proteins possess the same ability to provide the tissues with everything necessary for the synthesis of body proteins in them; those proteins Table 10 Professional groups I! O) O O (g and Distribution of rations according to protein content in g (per day) above 150 Miners ...... 282 Mechanics Locksmiths ........ Blacksmiths ........ Founders...... Weavers......... Dyers..... Intellectual labor . Housewives . . Peasant women..... Peasants....... Joiners ........ Masons...... Cabmen....... Woodcutters, sawyers Ditchdiggers...... Quarry workers 152 43 47 89 270 87 70 54 56 314 78 53 35 38 31 69 3.5 4.6 abs. 181 163 from 100 TO 150 i below 100 g 199 164 197 218 157 22, 26 51 30 29 24 51 48 15 40 39 26 11 37 34 39 26 that have a complete assortment of amino acids can be called complete proteins. The degree of completeness of different proteins could be determined by comparing their amino acid composition, Gr; 40 -20 O 20 40 60 80 100 Phaseolin, beans Maize I Gelatin xv I I > longgluten, lupin >} Gliadin, rye ~} Hordein, barley - V tU I ", "I - / Legumin, pea Ml | || = ^ J Gliadin, wheat ^ / Vargin, pea -} J] Legumelin, pea Glutelin 1 hemp [Edestin | I * -Y Glycine, bean ± -- 4. Glutenin, wheat »> Globulin, cotton. seed c I \ I ^ | Lactalbumin, milk Glutenin, maize > Excelsin, Brazil nut} Globulin, pea :: »} Egg. albumin, egg Casein, milk Egg vitellin, egg yolk Figure 3. T ^ however, even to the present time we do not know this composition with sufficient accuracy and can be guided only by approximate data. Meanwhile, experiments on animals make it possible to establish that proteins of different origins in different cases (e.g., during growth or to maintain nitrogen equilibrium at small amounts of nitrogen close to the minimum) replace abs. 117 1.18 120 121 116 116 121 118 115 122 121 117 118 114 121 118 114 59 66 74 31 50 81 44 37 70 81 48 39 48 67 of various physiological "biological value". each other in unequal and non-proportional amounts with respect to "nitrogen", in other words, proteins possess different qualities, which are determined by differences in the content and grouping of amino acids, or perhaps their aggregates, in the composition of the protein molecule. For illustration, Fig. 3 by Osborne and Mendel is given, from which it can be seen that growth (weight gain) of young animals on different proteins ceteris paribus proceeds unevenly and all proteins presented in the fig. can be divided into groups of different significance or different Table 11. Food Nitrogen-free food ........ 3.0 Same +3.5 g N of meat ...... j 3.0 Same +3.6 g N of wheat protein ..............! 5.0 Same +6.0 g N of wheat protein ............... 6.6 Same +8.8 g N of wheat protein .............. 8.3 Balance 0.5 0.5 0.5 0.5 0.5 -3.5 ± 0.0 -2.1 -1D ± 0.0
A second example is given in Table 11, from which it is seen that to maintain the minimum nitrogen equilibrium, proteins with a lower biological value must be taken in larger quantities. The term "biological value" was introduced by K. Thomas (1910), who attempted to characterize this concept quantitatively by determining the amount of N converted into body proteins per 100 parts of absorbed food N. Thomas's data according to this and other, more complex formulas are given in Table 12 and show how many weight parts of body proteins can be formed from 100 weight parts of absorbed proteins of foodstuffs (the author's numbers are rounded). Other authors either refuted or confirmed Thomas's data. It turned out that the absolute value of "biological value" is not constant for the same protein (let alone a foodstuff); it is influenced by both the amount of food taken (caloric value) and the amount of protein in it. Of course, the state of the organism at the time of the experiment (e.g., protein content) must also be of great importance. Various authors have also established the significance of individual amino acids for the biological value of proteins. A number of proteins and protein mixtures are incomplete due to the absence in them of amino acids that cannot be synthesized in the organism. The addition to such proteins of the missing 7 02 Table 12. Foodstuffs Meat . . . . Milk . . . Various fish Rice ..... Yeast . . Casein . . . Wheat flour . . . d AND! as a I But "§ Scegg YEVs 105-106 100 103- 86 91- 83 73- 66 70- 67 51-29 = a to Foodstuffs Potatoes . Cauliflower . . . Spinach . . . Peas . . . . Corn . v.ci B t? SS§ 80-56 83-77 64-63 56-49 40-12 amino acids makes them complete.

100 g of food [tobacco]
Figure 4. Effect on the growth of rats of adding missing amino acids.
V. Lavrov. Purine metabolism (physiology) - see Uric acid, Nucleoproteins, Purine bases. Pathology of protein metabolism. Quantitative disorders of protein metabolism occur in complete and partial starvation and during feeding with incomplete proteins. An increase in protein metabolism (so-called toxic protein breakdown) is observed in certain types of poisoning (pantopon, carbon monoxide, sublimate, oxalic acid), in malignant tumors, in certain forms of Basedow's disease, in diabetes, especially experimental diabetes, in acute infectious diseases, and in febrile processes. The reverse phenomenon - enhanced protein deposition in the organism (Eiweissmast) - positive nitrogen balance - is most easily achieved after a period of starvation, in chronic undernutrition, and especially easily during convalescence after exhausting diseases. The retention of N in the organism occurs even with comparatively small amounts of administered protein. During enhanced muscular work, protein deposition occurs due to the development of working hypertrophy of the muscles, often accompanied by significant nitrogen retention in the organism. The question of the possibility of achieving protein deposition in a normal state in an adult organism has been subjected to great discussions. The resolution of this question has great practical importance, especially in animal husbandry. Kellner proved that with rational feeding in cows, it is possible to achieve significant protein deposition in the organism. In humans, it is also possible to obtain the deposition of protein substances, measured by a positive nitrogen balance. This retention of N in the organism is achieved both by the enhanced administration of protein substances and by an increase (calorically) in the amount of non-nitrogenous food products that protect a portion of the proteins from energy expenditure. The retention of nitrogen in the organism cannot be reliably regarded solely as a process of protein deposition; nevertheless, large amounts of retained N (Grafe) cannot depend merely on nitrogenous slags, but also result from the accumulation of protein substances, although their formation is not accompanied by the usual retention of water in the organism. In view of the discrepancy in the amount of retained N and water, most authors consider that this formed protein is not identical with protoplasmic protein, but partly circulates in the body fluids (Voit), partly is deposited in the liver (Rubner, Noorden), or in the cells of other organs (Lutje, Berg). To check whether the deposited protein is biologically the same as protoplasmic protein, basal metabolism was studied, which, however, did not show an increase upon N retention. This observation argues against the formation of true protein, which is an integral part of protoplasm, as occurs in cases of protein deposition during working hypertrophy and after exhaustion. Whether such protein deposition presents any advantage for the organism is difficult to say. Some authors consider protein deposition useful due to the fact that these proteins, owing to their lability, protect protoplasmic proteins from breakdown and, furthermore, in case of need, can transform into true proteins. Qualitative changes in protein metabolism. In addition to the physiological proteins of organs and fluids, specific proteins are found during pathological processes, probably originating through the restructuring of tissue protein, namely: amyloid (see Amyloid degeneration) and Bence Jones protein (see Bence Jones protein body). Bence Jones protein usually appears in the urine in multiple myelomas, but not in all cases of this disease. Sometimes crystals of Bence Jones protein precipitate in the myeloma tissue (Wulf). Bence Jones protein was furthermore detected in the urine in osteomalacia, sarcomatosis, hypernephroma, leukemia. Bence Jones protein is mostly excreted simultaneously with serum protein; the diseased kidney allows Bence Jones protein to pass more easily than a healthy one. The site of protein regrouping is unknown; apparently, bone marrow cells influence this restructuring of the protein molecule. Gottschalk draws an analogy between Bence Jones albuminuria and diabetes; in both cases, there is a disorder of intermediate metabolism with the formation of a substance partially utilized by the cells of the organism. Other authors draw a parallel between the formation of melanogen and melanin by pigmented tumors and the formation of the Bence Jones body in myelomas. Upon the injection of Bence Jones protein, kidney damage develops (Krauss). Under the influence of the parenteral administration of Bence Jones protein, immunization processes develop. Changes in amino acid assimilation are important disorders of protein metabolism. In liver diseases, hyperaminoaciduria (in acute yellow atrophy of the liver, crystals of leucine and tyrosine) is observed alongside hyperacidemia. Increased excretion of amino acids in the urine occurs in many infectious diseases, diabetes, and leukemia. There are also diseases characterized by insufficient intermediate utilization of one or more amino acids. Cystinuria or cystine diathesis (Wollaston) is characterized by increased urinary excretion of L-cystine in dissolved form or as a sediment; sometimes cystine forms stones in the bladder or kidneys. The essence of cystinuria is that the organism is unable to cleave the cystine molecule. Apparently, cystinuria is a disorder of intermediate metabolism caused by general insufficient deamination, given that usually, alongside cystine, anomalies in the breakdown of other amino acids (leucine, tyrosine, asparagine) and amines (cadaverine, putrescine) are observed. The appearance of diamines in cystinuria represents a constitutional anomaly and differs in its significance from diaminuria caused by the action of bacteria in the intestine on lysine and arginine, which yield the same amines upon breakdown. Alcaptonuria (see) as a disease does not have great practical significance, but theoretically played a major role in the study of the breakdown of aromatic substances in the human organism. Nucleic metabolism. Physiological and chemical studies of nucleoprotein metabolism in the organism and pathological disorders of this metabolism are of great importance for elucidating the pathogenesis of gout (see). Gout is characterized by the deposition of sodium monourate in cartilage, tendons (tophi); in the blood, the uric acid content is mostly increased, while the excretion of endogenous uric acid in the urine is decreased; exogenous uric acid is also excreted insufficiently and sluggishly. A. B. Garrod, Thannhauser, and Lichtwitz consider that the phenomena of gout depend on primary renal insufficiency regarding uric acid excretion. Brugsch and Schittenhelm explain gout by an increased content of uric acid in the human organism, caused by insufficient enzymatic processes, predominantly a decrease in the activity or absence of the uricolytic enzyme, which normally destroys uric acid formed in the process of intermediate metabolism (see Uric acid, Gout). Creatinuria - see Creatine. The question of the formation and presence of ammonia in the organism has undergone a fundamental revision in recent years. Nash and Benedict found that the main site of ammonia formation is the kidneys. The amount of ammonia excreted in the urine exceeds by many times the amount of ammonia circulating in the blood. The same was confirmed by Ambard and Schmid. In the blood, ammonia is found in two forms (Parnas): first, in a very insignificant amount (0.015 mg % N) in the form of ammonium ion, and second, in the form of adenine nucleotide (2 mg % N) - Parnas's "main ammonia substance" (Ammoniakmuttersubstanz - AMS), which easily splits off ammonia upon standing of the serum. In the kidneys, this nucleotide is cleaved under an acidic reaction, forming ammonia. The formation of ammonia is closely linked to the neutralization of acids, provided they are not burned to CO2 in the organism. From the relationship between ammonia excretion and the presence of acids, the influence of nutrition on NH3 excretion becomes clear. With a meat diet, a large amount of ammonia is excreted because many inorganic acids (sulfuric acid, phosphoric acid) are formed from proteins; with a mixed diet, there is less ammonia, and with a plant diet, very little. Upon oral or parenteral administration of acids, the amount of ammonia in the urine increases. Simultaneously, the amount of ionized ammonium in the serum does not change, but the content of the non-ionized portion (AMS) clearly decreases. The same is observed in endogenous acidosis. The greatest increases in ammonia excretion are observed in diabetes: the amount of ammonia reaches up to 12 g per day instead of the normal amounts of 0.5-1 g. Upon the administration of alkalis, no changes are observed in both ammonia fractions of the blood, but the amount of ammonia excreted in the urine sharply decreases. In renal damage, especially in nephritis, ammonia excretion is decreased. In uremia, despite the state of acidosis and a strong decrease in reserve alkalinity, the amount of ammonia in the urine is sharply decreased; at the same time, the ammonia content in the blood does not increase.
Hasselbalch, who pointed out the significance of NH3 as a regulator of neutralization, noted that under normal conditions a definite relationship exists in the same individual between the ammonia coefficient (the ratio of ammonia nitrogen to total nitrogen) and the concentration of hydrogen ions; in renal patients this coefficient is lower, because the diseased kidney is either completely unable to form ammonia or cannot form it in sufficient quantities. When acid is administered to a nephritis patient, the ammonia in the urine does not increase at all or increases by only a few centigrams, in contrast to a healthy person, in whose urine the ammonia content increases by 1–1.5 grams per 24 hours.
Yu. Geftor. Pathological anatomy of protein metabolism disorders—see Amyloid degeneration, Protein degeneration, Hyaline degeneration, Cachexia, Marasmus, Cloudy swelling, Gout, Uremia. V. Fat metabolism. Fat metabolism in the broad sense of the word is the totality of phenomena representing the fate of "fat" in the organism. This includes the following main aspects: the penetration of dietary fat from the intestine into the blood, the transport of fat to the tissues, its consumption and deposition in the tissues, and the synthesis of fat. The concept of "fat" may also include the concept of fat-like bodies, or so-called lipoids; thus, fat metabolism encompasses: I. Fat metabolism proper; II. Lipoid metabolism. I. Fat metabolism proper. From the intestinal tract after absorption (see Digestion), fats enter the body by two pathways: 1) through the lymphatic capillaries of the villi, forming a sort of fine emulsion in them, which causes the lymph in the larger mesenteric lymphatic vessels to appear as a white mass during periods of absorption; the lymph enriched with fat droplets (chylus) flows through the thoracic duct into the venous blood; according to some observations (e.g., Munk, Friedenthal) on a girl with a thoracic duct fistula, the bulk of the fat passes into the organism precisely by this pathway. 2) Through the capillaries of the villi and further through the portal vein into the circulatory system of the liver, etc. According to observations by Errico, blood taken simultaneously from the portal and jugular veins of animals at the height of the digestive process (fatty diet) had a higher fat content in the portal vein than in the jugular vein, which could not be the case if fat passed into the venous system exclusively through the thoracic duct. From this it follows that fat passes into the blood by both pathways. The appearance of dietary fat in the lymph begins as early as the first hour of digestion, and after two hours the fat content in the chyle of the thoracic duct reaches 3–14% (depending on the fat content of the food and the rate of absorption) against several per thousand in fasting lymph. The fat content in the blood during hours of food absorption also gradually increases (alimentary hyperlipemia). So-called "normal" lipemia, i.e., the fat content on an empty stomach (after a preliminary "average" mixed diet or after a fat-free early breakfast in humans), in different animals and even in different individuals of the same species exhibits very significant fluctuations—from 0.2% to 0.8% (some authors report significantly lower numbers). As an illustration of the distribution of fat (fatty acids) in the blood, the table by Horiuchi is presented. Table 13. Comparative distribution of fatty acids in the blood. Man and animals: Man 0.36, 0.38, 0.40; Woman 0.38, 0.22, 0.30; Dog 0.52, 0.36, 0.36; Rabbit (without fat diet) 0.28, 0.29, 0.42; Rabbit (fat diet) 0.34, 0.36, —. The magnitude of alimentary lipemia is subject to many, partly random influences (rate of absorption and amount of food, the amount of fat in it, its digestibility, enzyme activity, the state of the endocrine system, etc.). Sometimes the blood plasma at the height of digestion becomes opaque due to the accumulation of fat globules in it. As an example of lipemia, Bloor's observations on a dog are cited. Twenty-four hours after eating, the blood fat was 0.6%, 3.75 hours after the administration of 100 cm3 of olive oil—0.73%, 6.25 hours after the administration of 100 cm3 of olive oil—1.20%, and 8 hours after the administration of 100 cm3 of olive oil—0.87%. In humans, alimentary lipemia arises even more easily than in dogs, whereas in rabbits it is detected with difficulty. In fattening geese (in the presence of fat in the feed), alimentary lipemia reaches 3% in the blood and up to 6% in the serum. With abundant carbohydrate feeding, when carbohydrates are converted into fat, lipemia is not observed, provided there is no fat in the food (Bleibtreu, Rosenfeld). The decrease in blood fat content to normal is a consequence of the fact that fat particles are "captured," firstly, by adipose tissue, where fat accumulates in cells as reserve material; such tissues ("fat depots") are the subcutaneous cellular tissue, intermuscular connective tissue, omentum, etc.; secondly, fat particles can pass into other tissues, where fat is consumed for energy or structural purposes. In a number of pathological conditions (see pathology below), during starvation, in experimental pancreatic or phlorhizin diabetes, lipemia also occurs, with fat in this case entering the blood from the fat depots of the organism; such lipemia coincides with the loss of glycogen reserves in the organism, and the mobilization of fat here can be viewed as an adaptation of the organism to new conditions of greatly reduced carbohydrate metabolism. An example of such lipemia is given in Miescher's work on the starving salmon (biological starvation—see Starvation). From all that is known to us about lipemia, it thus appears that conditions can arise in the organism in which the capillary system becomes permeable to fat in either direction. The mechanism of such an adjustment by the organism is completely unknown. Some authors attempted to view the disappearance of fat from the blood after hyperlipemia as a consequence of its cleavage by blood lipase. However, even if such lipolysis does take place, it apparently is not strictly necessary for the passage of fat from the blood, since intravenously administered stained fat transfers the dye to those tissues (liver, bone marrow) to which it is usually transported (Biondi, Neumann). Some researchers attempt to explain the disappearance of fat from the blood based on the assumption that fatty acids and fat form compounds with plasma proteins that can pass beyond the confines of the circulatory system. The following facts speak in favor of the possibility of such a combination of fat with protein: 1) the difficulty of extracting (quantitatively) all blood fat by fat solvents without the preliminary use of pepsin-hydrochloric acid to dissolve proteins; 2) a protein solution in the form of, for example, transudate (ascitic) fluid after mixing it with a certain amount of oil does not entirely release the latter to the fat-extracting solvent: a certain amount of oil remains in the protein solution, passing back into the solvent only after the action of pepsin-hydrochloric acid. The action of bile acids on fat in the blood leads to the same "masking" of fat, resulting in compounds that are soluble in plasma. The work of Biondi and Neumann, who studied the ultramicroscopic picture of human blood, also points to the "masking" of fat; blood taken during fat absorption revealed numerous shiny droplets (hemokonia) in a dark field, and the number of such particles gradually increased as fat was absorbed, reached a certain maximum (6 hours after food intake), fell again, and reached zero in about 12 hours. Hemokonia were absent in blood samples taken from humans on an empty stomach. One can think that small droplets of fat can pass through the capillary wall. The following figures (Mockel) illustrate in percentages the concentration of fat in the tissues of a fat animal (dog): skin—38%, subcutaneous layer—87%, muscles—19.6%, liver—13.4%, brain—12.7%, bones—12.0%. During periods of glycogen depletion in the liver, fat passes abundantly into the liver from fat depots, raising its fat content to 30–40%. The introduction of fat into the organism (as well as the introduction of carbohydrates and proteins) causes a temporary increase in metabolism (specific dynamic action) (see protein metabolism). However, this increase is insignificant compared to the action of carbohydrates and proteins, which is probably explained by the easy transition of fat into fat depots. In an experiment by Magnus-Levy, when a human was given 210 g of butter, the increase in metabolism over the basal level was 9–14% during the seventh hour and 6–8% in the eighth hour. External temperature exerts a very significant influence on the manifestation of the specific dynamic action of fats. Rubner provides the following example: a dog received 171.3 cal of fat per 1 kg of weight. Table 14. External temperature and heat production per 1 kg of weight (in calories).
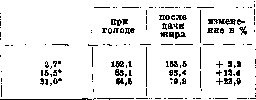
A healthy human (68 kg) contains 12.36 kg of fat (approximately 18% of their body weight). In fattened animals, fat reaches up to 50% of their live weight. That dietary fats, when consumed in significant quantities, are transported to fat depots is evident from a whole series of experiments. Thus, when dogs and mice are fed colored pork fat, the dye passes into all fat depots, with only the liver and adrenal glands remaining uncolored; the dye also passes into milk fat (Jacobsthal); it is obvious that the deposition
of fat in the liver is a secondary process—fat is transported there from other tissues; however, with very abundant fat introduction, liver fat is also colored. In addition, it has been established that "foreign" fat can be deposited in fat depots if it is introduced with food for a long time and in large quantities; thus, dogs after prolonged feeding with mutton tallow accumulate it in their subcutaneous tissue. The same has been noted when feeding mutton tallow to goldfish and carp. Herbivores consuming green fodder have a fat that is harder than with grain fodder (according to Rosenfeld, the fat of green fodder is hard, the fat of cereals is liquid). Various fats—rapeseed oil, linseed oil, sesame oil, cow butter, coconut oil, and mutton tallow—were tested on animals, and all of them could be detected not only in the fat depots of the experimental animals, but also in milk, in chicken eggs, and in the uropygial gland of birds. On the other hand, each animal species possesses its own fat, characteristic of it. This does not contradict the above in the least, since each species also has its characteristic combination of foodstuffs. Finally, large amounts of fat arise not from fats, but from dietary carbohydrates or proteins. Intermediate metabolism of f a t s. Fatty acids during their combustion in the organism undergo a gradual "stepwise" destruction, which is characterized by the oxidation of the /3-carbon atom, with the chain breaking and the carbonyl group forming at this place. CH3 - CH2 - CH2 - CH2 - CH2 - COOH CH3 - CH2 - CH2 - CO -|- CH2 - COOH CH2 - CH2 - CH2 - COOH CH2 - CO + CH2 - COOH CH2 - COOH. It is obvious that at each phase of oxidation two C atoms are split off (in the form of acetic acid or its derivatives); it is also obvious that acids with an even number of C-atoms must pass through the stage of a four-carbon chain—butyric acid; acids with an odd number of C-atoms do not form butyric acid; conversely, one of the final intermediate products for them is propionic acid. Experiments on animals confirm and refine this scheme of fatty acid destruction in the organism. Thus Knoop (Knoop), taking advantage of the observations of Nencki, Salkowski, and others, who showed the difficulty of burning benzene rings in the organism, introduced phenyl derivatives into the organism having various fatty side chains, which did not manage to burn in the body to the end, stopping at certain intermediate products passing into the urine. In this way it was clarified that fatty acids indeed obey the general law of sequential oxidation of /3-carbons and successive cleavage of two-carbon segments from the chain. Thus, /3-phenylpropionic acid CH2-CH2COOH turned into benzoic acid ICOOH, whereas phenylacetic CH2COOH and mandelic acid CH(OH)-COOH were excreted from the organism unchanged (they did not have a /3-atom in the side chain for oxidation); phenylbutyric acid CH3-CH2-CH2-COOH and its /3- and y-derivatives gave phenylacetic acid. Deviations from this law exist, but they do not contradict it and are explained by special chemical conditions; thus, for example, fatty chains with an amino group in the a-position are deaminated before oxidation, and further oxidation, according to the general rule, proceeds at this point of the chain (i.e., in a-C). The different attitude of the organism towards acids with an even and odd number of C-atoms was shown by Embden on the surviving liver, namely, fatty acids, when added to the fluid passed through the liver, give acetone, and the acetone-forming properties of acids with an even number of carbon atoms are significantly higher than those of acids with an odd number; in addition, it was found that with the lengthening of the acid chain, the acetone-forming properties decrease. Table 15. Substances added to the blood passed through the liver Amount of acetone formed in mg of blood Normal butyric acid CH3(CH2)2COOH » valeric » CH3(CH2)3COOH » caproic » CH3(CH2)4COOH » heptylic » CH3(CH2)5COOH » octylic » CH3(CH2)6COOH » nonylic » CH3(CH2)7COOH » decanoic » CH3(CH2)8COOH It is interesting to note here that straight-chain acids with an odd number of C-atoms, when passing through the surviving liver, are not only weak acetone-formers, but also suppress the acetone-forming properties of acids with an even number of C if they are added together with them to the fluid passed through the liver (antiketogenic action). Experiments of Embden's school showed that fatty acids with an even number of C-atoms, when passing through the surviving liver, serve as material for the formation of acetoacetic acid. This whole series of facts makes it possible to conclude that fatty acids with an even number of carbon atoms pass through the stage of butyric acid during their destruction, and acids with an odd number pass through the stage of propionic acid. Both of these intermediate products obey the general law of oxidation at /3-carbons. Thus, butyric acid must turn into /3-oxybutyric acid or acetoacetic acid, propionic acid (similarly to phenylpropionic acid)—into /3-oxypropionic or /3-aldehydopropionic acid and further CH3-CH2-CH3-COOH -> CH3CH2COOH CH3-CO-CH2-COOH, CH3-CHOH-CH2-COOH CH2OH-CH2-COOH CH-CH2COOH into acetaldehyde (for the further fate of this compound see carbohydrate and protein metabolism).
As for the mechanism of /3-carbon oxidation in general, according to Wieland's theory, the appearance of a keto acid is preceded by the formation of an unsaturated compound with one double bond (dehydrogenation) R-CH2-CH2-COOH -> R-CH=CH-COOH. The proof of the presence of this process is the experiments of Leathes and Hartley, who showed that when phenylpropionic acid CH2-CH2-COOH is introduced into the organism of animals, phenylcinnamic acid CH=CH.COOH can be obtained in the urine, and Dakin, in addition, under the same conditions, found /3-phenyl-/3-oxypropionic acid and /3-phenyl-/3-ketopropionic acid, and correspondingly acetophenone and benzoic acid. Summarizing these and other studies, Dakin believes that saturated acids through the stage of an unsaturated acid pass further into oxy- and keto acids, subsequently breaking at the place of the ketone group. The general scheme of oxidation appears as follows: R-CH2-CH2-COOH -> R-CH=CH-COOH -> R-CHOH-CH2-COOH -> R-CO-CH2-COOH.
R-CHOH-CH2-COOH
R-CO-CH2-COOH
4-H2O ->R-CH=CH2-COOH->R-COOH+CH3-COOH. A weak point in Dakin's scheme is the conversion of the oxyacid into a ketoacid. Oxyacids in the body are generally utilized with some difficulty, and it is more correct to imagine that the oxyacid appears as a side reaction of the reduction of the ketoacid; indeed, upon feeding benzoylactic acid (ß-phenyl-ketopropionic acid) C6H5.CO.CH2COOH, the corresponding alcohol acid l-C6H5CHOH.CH2COOH was obtained. Furthermore, the injection of ß-oxybutyric acid under the skin of a starving animal does not increase the excretion of acetoacetic acid and acetone, but such an increase takes place after the injection of butyric acid. On the other hand, it is known that ß-oxybutyric acid in the isolated liver is easily oxidized to acetoacetic acid. The most correct view therefore may be considered to be that of Dakin, that all oxy-, keto-, and unsaturated acids are in a state of mobile equilibrium with each other and can thereby transform into one another. Upon the cleavage of a two-carbon segment at the ß-carbon atom, a carboxyl group arises at the latter, and the cleaved segment itself is probably acetic acid, which can generally either be oxidized to CO2 and H2O or pass through succinic (obtained as a result of the synthesis of 2 molecules of acetic acid), fumaric, malic, oxaloacetic, and pyruvic acids into lactic acid and further participate in the formation of carbohydrates. The conversion of fats into carbohydrates in the body is supported by recent works by Shaternikov and Molchanova on the study of oxygen consumption and carbon dioxide excretion by adipose tissue in a starving ram (by comparing gas exchange before and after the amputation of a significant part of the fatty tail). It turned out that the respiratory quotient (see) in adipose tissue is 0.34-0.35; the theoretical Chauveau coefficient given by him in his formula for the conversion of fat into carbohydrates: 2C57H110O6 + 67O2 = 16C6H12O6 + 18CO2 + 7H2O is equal to q = 0.268. II. Lipoid metabolism. The question of lipoid metabolism (see) first of all encounters the complexity of the concept itself; since a whole series of chemically different groups and compounds [phosphatides, sterols (e.g., cholesterol), cerebrosides, etc.] are united under this concept, when considering metabolism, these groups have to be analyzed separately. Physiology is very poor in information on lipoid metabolism in general; the most studied body of a lipoid nature is lecithin (see), which belongs to the phosphatide group. Under the influence of the enzymatic work of the intestinal tract, lecithin-like substances can break down into their constituent parts: thus, lecithin yields choline, phosphoric acid, and glycerin. All authors note the rapidity of lecithin absorption; the site of this absorption is apparently the small intestine, but the question of whether preliminary cleavage of lecithin is necessary for absorption or not remains unresolved to this day. The pathways of lecithin and other substances beyond the intestines are also not known with exactness; from Eichholtz's experiments it can be seen that after giving large amounts of lecithin, its content in the blood rises by an insignificant amount; it can therefore be assumed that lecithin goes via the portal vein into the liver, where it is retained; at least from some experiments it is seen that the blood of the portal vein is richer in lecithin than the blood of the peripheral veins; Salkowski also pointed out that the liver accumulates lecithin-like bodies after their abundant introduction into the intestine; various organs relate differently to the intake of lecithins: while, for example, the liver accumulates them in large quantities, other tissues, such as the brain, show nothing of the kind. Phosphatides are also absorbed from the intestine through lymphatic pathways: Slovtsov managed to show an increase in lipoid phosphorus and nitrogen in the lymph 5 hours after giving lecithin. The question of the synthesis of phosphatides in the animal organism was posed a very long time ago and was resolved in various ways; it is very difficult to draw conclusions from experimental data. Here we can only dwell on the studies of McCollum et al., which showed that chickens on a diet practically devoid of lecithin (skim milk and rice flour) produced 294.5 g of yolk with 36.51 g of phosphatides, of which 8.83 g fell to lecithin. A similar observation on ducks was made by Fingerling, in whose experiments these birds synthesized lecithin at the expense of inorganic phosphorus of food. Metabolism of lipoids of the sterol group - see Sterols, Cholesterol. The question of the absorption of food sterols in the intestine encounters great difficulty in its resolution due to the fact that a lot of cholesterol is excreted from the organism with bile, intestinal secretions, and shed epithelium. Part of the cholesterol that has entered the intestine from food and bile is absorbed, part is destroyed by bacteria, turning into other sterols (coprosterols). In dogs (14-15 kg of weight) with a biliary fistula, the excretion of cholesterol in the bile was established to be 0.04-0.08 g, while the content of this substance in the feces of a control dog was 0.21-0.32 g per day. Food cholesterol is absorbed in amounts up to 54% (in dogs). The addition of fat increases the absorption of cholesterol, the addition of carbohydrates worsens its absorption. With a significant addition of cholesterol to meat, a noticeable amount of it disappeared from the intestine (almost 38%). However, it still remains unclear whether the disappearance of cholesterol from the intestine can be considered solely as an expression of its assimilation. O. Fürth draws attention to the possibility of partial bacterial destruction of cholesterol in the intestine. Furthermore, it was noticed that an increase in protein in the food (and not in cholesterol) causes an increase of cholesterol in the bile. It is also interesting to note that the breakdown of erythrocytes caused by the introduction of toluylenediamine into the organism increases the excretion of cholesterol with bile. On stationary biliary fistulas, it was furthermore clarified that an increase in the administration of cholesterol (with food) does not directly affect its content in the bile, but causes a (temporary) increase in cholesterolemia, and when the latter reaches a more or less high level, the excretion of cholesterol with bile begins to increase. The mechanism of cholesterol crossing the intestinal wall is unclear; in some experiments an increase of cholesterol in the chylous vessels was established (for example, Munk-Rosenstein's on a girl with a chylous fistula) along with an increase in dietary fat. The opinion was expressed that cholesterol "moves along the same pathways as fat." The question of the synthesis of cholesterol in the organism is resolved positively (observations on the cholesterol content in chicken eggs before and during incubation). In infants with exclusively milk feeding, the excretion of cholesterol exceeds its intake with food by 1.5 to 2.5 times, meanwhile the amount of cholesterol increases during growth; this can be seen from the following tables 16 and 17. Table 16. Cholesterol Factor Food Food feces 540 female 1200 0.050 0.072 0.107 0.070 0.125 0.114 0.212 0.177 0.125 0.424 2.3 2.9 1.7 1.8 3.4 a b Table 17. Age of child, Newborn 3,050 1,507; 3 mo. 3,800 4,272; 5 mo. 5,700 5,883; 9 mo. 6,000 7,682; 18 mo. 9,000 12,140. If during growth the amount of cholesterol absolutely increases everywhere in tissues, as well as in the brain, then in the presence of a constant negative balance, it can be assumed that its new formation is taking place somewhere in the body. With respect to adults, newer studies also emphasize, contrary to old data, the excess of cholesterol output over intake. Therefore, in an adult as well, the new formation of cholesterol in the body can be assumed. The destruction of cholesterol in the organism has not yet been elucidated; in any case, this body is very resistant. In starving dogs that have lost up to 2/3 of their weight and a very significant part of their fat depots, the total cholesterol content in the body turned out to be very close to that of control animals; this shows that cholesterol is not destroyed in the body during starvation (Beumer) and the ratio of cholesterol to higher fatty acids shifts strongly towards the former. It is interesting to note that the ratio of cholesterol to phosphatides remains unchanged. Cholesterol is eliminated from the organism not only through bile, but partially through the skin as well. Cholesterol is always present in the secretion of the sebaceous glands and in some animals is excreted by this pathway in large quantities. Thus, the ram excretes lanolin, which contains a very large amount of complex esters of higher fatty acids and cholesterol. Of other sterols, the most studied in recent times is the so-called ergosterol. (Origin of fats from carbohydrates - see Carbohydrate metabolism; origin of fats from proteins - see Protein metabolism). B. Lavrov. III. Lipoid-carbohydrate metabolism. While the conversion of the body's carbohydrates into fats is a universally recognized fact (see carbohydrate metabolism), the reverse conversion of fats into carbohydrates is still contested by very many authors (Thannhauser). There are only indirect proofs of the possibility of the conversion of fats into carbohydrates via the stage of ketones. Chauveau already emphasized the role of fats in the energetic processes of the body. He believed that the energy necessary for the body is supplied by the direct combustion of carbohydrates, and these can also be carbohydrates derived from proteins and fats. This premise is more and more confirmed by observations of metabolic processes under various pathological and physiological states (see fat metabolism). At the head of the proponents of the theory of glyconeogenesis from fats, and not only under pathological but also under physiological conditions, stands Geelmuyden. The study of lipemia, glycosuria, ketonuria, the D:N ratio, the respiratory quotient under various conditions (diabetes, glycosuria of pregnant women, ketonuria in untractable vomiting of newborns, phosphorus and phlorhizin poisoning, apancreatic diabetes, starvation, anemia, physical exertion, etc.), studies on the fate of a number of ketogenic and anti-ketogenic substances compel one to recognize that carbohydrate and fat metabolisms are interrelated. The intermediate product in the conversion of fats into carbohydrates are ketone bodies. Magnus-Levy showed that the ketones formed during protein breakdown in diabetic coma in no way cover the amount of ketones excreted by the urine; consequently, the role of fats in the formation of ketone bodies should not be doubted. The conversion of fats via acetone bodies into carbohydrates in pathological processes is also almost universally recognized. Geelmuyden, however, believes that ketone bodies are a physiological product of metabolism and that in normality, glyconeogenesis from fats also occurs, albeit to a very slight extent. Ketone bodies circulate in the blood in insignificant quantities, and only if they do not manage to turn into glycogen in the body do they accumulate in excess and are excreted by the kidneys. Embden and his co-workers proved that the liver is the only organ where ketone bodies are formed, while their further processing can proceed both in the liver and in other tissues. The amount of ketone bodies undergoing complete transformation in the liver depends on the presence in it of anti-ketogenic substances (certain amino acids, glucose, and mainly glycogen). In the absence of anti-ketogenic substances in the liver, ketone bodies are carried by the blood to the periphery, where, under the necessary conditions, they undergo final metamorphosis. The conversion of fats into carbohydrates proceeds, apparently, either via β-oxidation (Knoop) or via lysis (Leathes), i.e., via dehydrogenation and then β-oxidation. The regulation of lipoid-carbohydrate metabolism by the nervous system is carried out, apparently, from the floor of the third ventricle, mainly the infundibulum and tuber cinereum, the upper cervical segment of the spinal cord, and the splanchnic nerve. In hormonal regulation, the main role belongs to insulin and adrenaline (Wertheimer, Raab, and others); the role of the hormone of the middle lobe of the pituitary is less clear. The discovery of insulin, which regulates carbohydrate metabolism, promotes the conversion of carbohydrates into fats, and so sharply influences lipoid and ketone metabolisms, provided new evidence for the reality of glyconeogenesis from fats. Wertheimer believes that insulin is a catalyst in the conversion of fats and ketones into carbohydrates, and in the first phase of its action, only fats located in the liver are converted into carbohydrates. Under the influence of large doses of insulin, glycogen disappears; under the influence of small doses, it forms anew (influence either on fat formation or on carbohydrate formation). Under the influence of adrenaline injections, the new formation of glycogen from fat is accelerated and intensified; nitrogen breakdown does not increase, liver glycogen increases, and fat disappears. A number of experimental works also testify, although less convincingly, to the possibility of the new formation of sugar from fats under the influence of pituitrin. S. Zizlin.
Pathology of fat metabolism. Fats are supplied to the animal organism partly in ready-made form, partly formed in metabolism from other substances, and biologically play the role of reserves that enter metabolism under various conditions and can significantly affect general metabolism with their high caloric value. The importance of fat is also seen from the fact that in a healthy state, any organism contains quite a bit of fat, and in chronic diseases, weight loss is observed in the majority of cases, depending mainly on the disappearance of fat. Only extremely rarely does fat practically disappear entirely; usually, a small amount of it can still be detected in fat depots. The cause of the disappearance of fat is far from always clear; sometimes weight loss may depend on a lack of introduced food (refusal to eat, inability to swallow, pyloric obstruction, etc.). Insufficient absorption of dietary fat also leads to the disappearance of already deposited fats. The breakdown and absorption of fats from the intestine suffer from a lack of pancreatic enzymes and the absence of bile. In these cases, severe diarrhea is often observed, which further disrupts nutrition. This same toxic or cachectic disappearance of fat occurs in most exhausting diseases. The disappearance of fat is detected first of all by weighing the patient and during clinical examination. It is much harder to reveal fat loss by controlling metabolism, because the formation and breakdown of fat are slowly proceeding processes requiring long-term observations, and the resulting metabolic products require the use of complex methodology in a form inconvenient for the patient (gas exchange) for accounting. Added to this is the circumstance that the disappearance of fat is also accompanied by loss, and deposition by retention of water in the tissues (up to 40% in adipose tissue). In case of insufficiency of fat deposition, as well as with excessive fat accumulations, the sequence of processes of fat formation or breakdown does not suffer; fat metabolism in its individual stages does not differ from normal, and nowhere in the organism does the formation of intermediate metabolic products occur, nor is the appearance of such noted in exhaled air or urine. Exact measurements allowing one to speak definitely about excessive or insufficient fat deposition do not exist, and all questions concerning the need to fatten the patient or reduce their weight are decided on the basis of the entire clinical picture. It is noted that there are people who remain thin despite unconditional overeating. The inability to replenish fat reserves is even singled out by some authors into a special disease form, which is associated with a disorder of the endocrine glands. More often, however, one has to deal with patients prone to fullness. Here too, endocrine disorders are of essential significance, but what the mechanism of increased fat deposition is, is not entirely clear. The intermediate products of fat metabolism—acetoacetic and β-hydroxybutyric acids—normally disappear almost without a trace, which is explained by their final oxidation. In cases of pathological acidosis, a significant part of the acetone bodies is not oxidized, but is excreted in the urine. The cause causing an excessively large influx of ketone-forming substances into the blood consists in the depletion of the liver in glycogen, following which the strongest mobilization of fatty acids sets in, which leads to the formation of hydroxybutyric and acetoacetic acids. Thus, the development of ketonuria and ketonemia sets in as a secondary phenomenon after the disappearance of glycogen from the hepatic cell; initially, a disorder of carbohydrate metabolism sets in. The antagonism between the deposition of glycogen in the liver and the filling of the hepatic cell with fat is observed, besides various glycosurias, also in all kinds of poisonings (phosphorus, arsenic, chloroform, etc.), under the influence of bacterial toxins, and especially also in the periodic vomiting of children. Among the group of lipoids, cholesterol possesses the most characteristic features, the metabolism of which is studied better than others. Pathological phenomena associated with cholesterol can be distinguished as an increased content of colloidal cholesterol or as deposits of this substance in an undissolved state. There probably also exist changes concerning the ratio of cholesterol esters to free cholesterol (see Cholesterol). The disturbance of cholesterol metabolism with the accumulation of cholesterol in the organism and its deposition in tissues is associated with the origin of arterial atherosclerosis and gallstone disease. Indeed, in these diseases (as well as in diabetes mellitus and sometimes in chronic nephrosis), an increase in the cholesterol content in the blood is found. Experimentally, by administering cholesterol for a long time, it is possible to cause in some animals (predominantly rabbits and guinea pigs) deposits of it in the vessel walls, very much resembling the picture of human atherosclerosis.
e. Fromhold. Pathological anatomy of disorders of fat metabolism in the sense of excessive deposition of neutral fat - see Obesity. The deposition of cholesterol, usually as a result of hypercholesterolemia, manifests in arteriosclerosis (see), in the pictures of xanthelasma and pseudoxanthoma (see Xanthoma), in the formation of cholesterol gallstones. A peculiar patho-anatomical picture is presented by certain special diseases associated with a disturbance of fat metabolism and the deposition of fat and lipoids in tissues (see Gaucher disease, Niemann-Pick disease). Pathological anatomy of local disorders of cellular fat metabolism - see Fatty degeneration. VI. Carbohydrate metabolism. Polysaccharides (starch, glycogen) and disaccharides entering with food undergo hydrolytic cleavage under the influence of digestive enzymes to the stage of monosaccharides, which, like preformed monosaccharides entering with food, are absorbed mainly in the small intestine. Under normal conditions, disaccharides that have not undergone hydrolysis, although soluble in water, are not absorbed. Cellulose entering with plant food undergoes only partial hydrolysis under the influence of intestinal bacteria. - The fate of glucose after absorption. If we trace the glucose content in the blood of the portal and hepatic veins, we will see that the glucose content in the blood of the hepatic vein during digestion changes little; in the portal vein, however, its content during digestion increases sharply; it is also influenced by the amount of carbohydrates in food. Such a difference in the glucose content in the two aforementioned veins is explained by the fact that the excess of glucose entering the portal vein during absorption is retained in the liver, being deposited in its cells in the form of glycogen. The conversion of glucose in liver cells into glycogen is an enzymatic process. Glycogen deposited in liver cells is a reserve carbohydrate; under the influence of enzymes present in the liver, this glycogen can be broken down again into glucose molecules, which pass into the blood. Up to 150 g of glycogen can be deposited in the human liver. Approximately the same amount of it can be deposited in the muscles. In addition, glycogen in small amounts can be deposited in almost every cell of the animal body. If the food contains too many di- and monosaccharides, then a very large amount of glucose is brought to the liver at once via the portal vein, and part of the glucose, without being converted into glycogen in the liver, passes further into the hepatic vein, which causes an increase in the glucose content in the vessels of the systemic circulation, i.e., so-called alimentary hyperglycemia occurs; excess sugar from the blood is excreted by the kidneys, and so-called alimentary glycosuria occurs. Alimentary hyperglycemia and glycosuria cease as soon as the delivery of simple carbohydrates with food decreases. Various carbohydrates are converted into glycogen in the liver and deposited in it with varying ease; for example, the assimilation capacity of the liver for glucose is 100 g, i.e., in a healthy person, glycosuria occurs when more than 100 g of glucose is administered per os at once. The assimilation capacity of the liver in relation to galactose is only 40 g. In liver diseases, especially in diseases of the hepatic parenchyma, the assimilation capacity of the liver decreases. Therefore, the determination of assimilation capacity is used for the functional diagnostics of the liver. Carbohydrates are stored not only in the form of glycogen, but can also be converted into fats, which are deposited in adipose tissue. During starvation, glycogen deposited in the liver is converted into glucose. The latter passes from the liver into the blood, and from the blood enters various tissues, where it is burned. Glycogen and muscular work. During muscle work, the glycogen content in them, as well as in the liver, decreases. This was first established by Claude Bernard, who found that in hibernating animals there is a lot of glycogen in the muscles and liver; when they, waking up after hibernation, began to move, the glycogen content in both muscles and liver decreased. Külz found that in the body of a dog that had pulled a cart with a load for ten hours, there was about 1 g of glycogen per 1 kg of body weight, while in the bodies of other dogs that had not done such work, there was about 38 g of glycogen per 1 kg of body weight. Thus, carbohydrates are expended during muscle work; if the work is short, the glycogen content in the muscles decreases. With more prolonged and heavy work, glycogen reserves in the liver also decrease. The respiratory quotient during intense physical work is equal to one. Intermediate metabolism of carbohydrates in muscles. The transformations of carbohydrates in muscles associated with the release of energy go through a series of intermediate stages leading to the formation of the final products of carbohydrate oxidation, carbonic acid and water. First of all, the glycogen present in the muscles is broken down into glucose molecules. If there is no glycogen in the muscles, glucose enters the muscles from the blood. Then glucose combines with phosphoric acid to form glucose monophosphoric acid (see Lactacidogen). This process occurs under the influence of the enzyme phosphatase. Lactacidogen breaks down into phosphoric acid and an active (labile) form of glucose, which easily undergoes further transformations; the breakdown of lactacidogen occurs under the influence of the enzyme hexose monophosphatase. The next stage of carbohydrate metabolism is the conversion of active glucose into 2 particles of methylglyoxal, and it is possible that methylglyoxal aldol is formed first as an intermediate product. The enzyme catalyzing this process is called glycolase.
CH2OH
CH2
CH2
CH3 ! CHOH
COH or CO I
-NOH I
COH I
-NOH I CHOH
CH2
CH3 !! COH or CO COH
COH glucose
methylglyo
methylglyoxal xanthaldol
(2 particles) Methylglyoxal then under the influence of ketone-aldehyde mutase (or glyoxalase) is converted into lactic acid, which, undergoing dehydrogenation, is then converted into pyruvic acid:
CH3
CH2
CH3 I
1| I
I COH O
COOH
COOH lactic pyruvic acid
ic acid Pyruvic acid can be formed directly from methylglyoxal as a result of the dehydrogenation of its hydrate under the influence of oxidoreductase (dehydrase): CH3 -Ho | CH3
CH3 +H2O soh co n c- ^ co I Pyruvic acid under the influence of the enzyme carboxylase discovered by Neuberg, which catalyzes the cleavage of a CO2 particle from pyruvic acid, is converted into acetaldehyde. Acetaldehyde is then oxidized to acetic acid, and this latter is finally oxidized to CO2 and H2O. ch I co ch3 +HOH ch son ~ acetic I
aldehyde COOH CO2 3-Hj ,H CH, c^on coon \nptt UksUsnaya k-ta ^OH hydrate of acetic alde- The course of carbohydrate conversion in alcoholic fermentation (see) is similar; its study has helped greatly in clarifying carbohydrate metabolism in the animal organism, except that in alcoholic fermentation acetaldehyde is not oxidized to acetic acid, but is reduced to ethyl alcohol. During alcoholic fermentation, hexose also first combines with phosphoric acid, forming hexose diphosphoric acid. The formation of some of the aforementioned intermediate products (e.g., methylglyoxal, acetaldehyde) has been proven experimentally (Neuberg). Zymase (see), which is a complex of enzymes causing the processes of both alcoholic fermentation and glycolysis, can be divided into apozymase and cozymase. Some stages of carbohydrate metabolism proceed only in the presence of both components of zymase, while others can take place in the presence of apozymase alone; for example, the conversion of hexose into methylglyoxal can go on in the absence of cozymase (in the presence of apoglycolase alone); whereas the further conversion of methylglyoxal into lactic acid can proceed only in the presence of the coenzyme (in the presence of apoglyoxalase and coglyoxalase). Neuberg removed cozymase or weakened its action; he then detected the accumulation of methylglyoxal, since in the absence of the coenzyme its further conversion did not take place. Neuberg proved the formation of acetaldehyde using the method of trapping acetaldehyde by binding it with sodium or calcium sulfite. If carbohydrate metabolism proceeds in the presence of sulfite, then acetaldehyde, forming from pyruvic acid, enters into combination with it; such bound acetaldehyde cannot undergo further transformations, and it accumulates as the final product of carbohydrate metabolism (alcoholic fermentation); it can be isolated and quantified. During fermentation, the oxidation of methylglyoxal to pyruvic acid and the reduction of acetaldehyde to alcohol are two opposite, interrelated processes: acetaldehyde is reduced by means of the hydrogen that is released during the oxidation (dehydrogenation) of methylglyoxal hydrate. During fermentation in the presence of sulfite, the reduction of acetaldehyde is impossible, and then another particle of it is reduced by the hydrogen released during the dehydrogenation of methylglyoxal: as a result, glycerin is formed, which together with acetaldehyde (bound to sodium sulfate) and with CO2 are the final products of this form of alcoholic fermentation. Acetic acid during its oxidation apparently goes through the following stages: as a result of the dehydrogenation of its two molecules, succinic acid is formed, which upon further dehydrogenation is converted into unsaturated fumaric acid; the latter, by adding water, is converted into malic acid, which by dehydrogenation is converted into oxaloacetic acid. From oxaloacetic acid, as a result of the elimination of CO2, pyruvic acid is formed, from which another molecule of CO2 is then split off, and acetaldehyde is formed, which is then oxidized to acetic acid. The process continues in the same order, so that the molecules of acetic acid are gradually oxidized one after another to CO2 and water (the hydrogen that is released during the dehydrogenation of the aforementioned intermediate products is oxidized by oxygen to water). The processes of carbohydrate metabolism are reversible reactions: they can proceed in both directions—both in the direction of the breakdown and formation of increasingly simpler products, and in the direction of the synthesis of glucose from the intermediate products of its breakdown. Regulation of carbohydrate metabolism. Two hormones play a huge role in carbohydrate metabolism: adrenaline and insulin. Adrenaline and insulin influence the glycogen function of the liver, and in this regard they are antagonists: adrenaline stimulates the breakdown of glycogen in the liver, in other words, its conversion into glucose; adrenaline also enhances the permeability of the kidneys to sugar. Insulin stimulates the synthesis of glycogen in the liver from carbohydrates, if they are present, or from protein or fat in the case of carbohydrate or total starvation; insulin also stimulates the transition of glucose from the blood into tissues and the oxidation of carbohydrates in tissues. Due to this role of these hormones, the introduction of adrenaline into the body causes hyperglycemia and glycosuria and is accompanied by a decrease in the content of lactacidogen in the muscles. The introduction of insulin causes, on the contrary, hypoglycemia; with the introduction of large doses of insulin, causing severe depletion of tissues in carbohydrates, hypoglycemic convulsions can occur. Insulin, as shown by studies by Neuberg and Gottschalk, and then Ahlgren, enhances the formation of acetaldehyde in tissues. According to some authors (Winter, Smith), insulin stimulates the conversion of blood glucose into an active form of glucose (the so-called gamma-glucose). Carbohydrate metabolism and vitamins. Disorders of carbohydrate metabolism are also observed in the absence of vitamins in food. Funk pointed out that experimental polyneuritis occurs the faster the more carbohydrates there are in the food of pigeons, and that during polyneuritis the blood sugar content changes. The connection between vitamins and carbohydrate metabolism for experimental scurvy (scorbutus) has been studied in detail. It has been established (A. Palladin) that in scurvy caused by the absence of vitamin C in food, the blood sugar curve undergoes certain changes: at first it rises (sometimes after a small short-term drop) and reaches a certain maximum, after which it begins to decrease; finally, hyperglycemia is replaced by hypoglycemia, gradually increasing until the death of the animal. The appearance of clinical symptoms of scurvy (bleeding in the gums, loose teeth, characteristic mouth odor, etc.) coincides with the transition of hyperglycemia to hypoglycemia, i.e., with the moment when the blood sugar content is close to normal. Therefore, when examining the blood sugar content in humans, i.e., at the first appearance of clinical symptoms of scurvy, it is found to be close to normal. Parallel to the change in the blood sugar curve, the diastase content in it also changes. The glycogen content in the liver as scurvy develops gradually decreases, and finally the liver turns out to be devoid of glycogen. Such in general is the picture of changes in the blood sugar curve both in experimental polyneuritis (Collazo), caused by the absence of vitamin B in the food of birds, and when feeding on food devoid of all vitamins. Thus, in the absence of vitamins in the food of animals, the organism loses the ability to utilize carbohydrates in a normal way. Avitaminosis in relation to disorders of carbohydrate metabolism resembles diabetes, all the more so since the introduction of insulin in avitaminosis reduces hyperglycemia, just as it reduces hyperglycemia in diabetes.
A. Palladiy. Pathology of carbohydrate metabolism. Disorders of carbohydrate metabolism are not infrequently encountered. At the patient's bedside, they may not be accompanied by any characteristic symptoms, and their detection requires analyses of urine, respiratory exchange, blood testing, etc. Considering that in normal urine under ordinary dietary conditions only traces of glucose can be detected, which upon overfeeding with sugars increase to quantities precisely determinable, one can establish the limiting number of grams of mono- and disaccharides that does not cause such an increase in normal glucosuria and which characterizes tolerance. An increase in tolerance is noted in cases of dystrophia adiposo-genitalis and in myxedema, when patients sometimes tolerated huge amounts of carbohydrates (500 g of glucose). More often one may encounter the reverse phenomenon—decreased tolerance, which is characteristic of diabetic metabolism. The concept of "tolerance" should be distinguished from the concept of "assimilability" (assimilation), by which is meant the amount of carbohydrates that have entered metabolism (destroyed or retained). If a healthy person is given glucose in an amount exceeding tolerance, then not everything given in excess of tolerance will be excreted in the urine, and the more glucose is given, the more of it will be excreted, but the more will also be consumed by the organism. Impairment of tolerance and glucosuria are sometimes observed even in the absence of diabetes mellitus (poisoning, apoplexy, infections, liver diseases). Various types of sugar enter metabolism and are destroyed with unequal ease. Fructose and galactose, for example, are particularly easily excreted in the urine in liver diseases. Galactose has also been found in the urine of infants with intestinal disorders. Finally, cases of the appearance of fructose and various pentoses in the urine have been described. Cases of pure fructosuria, i.e., the appearance of fructose in the urine without simultaneous glucosuria and provided that fruit sugar is absent from the diet, are quite rare. They proceed like mild diabetes, with which they may be hereditarily linked. Observations of pentosuria are interesting because sometimes pentose is excreted in an optically inactive state, which is extremely rare in animal and plant organisms. Feeding pentosans does not affect pentosuria. Pentoses are part of nucleic acids, and the pentosuric anomaly of metabolism is of interest rather for the field of nucleic acid metabolism than from the standpoint of carbohydrate metabolism; of greatest importance are those quantitative deviations of chemical transformations that occur with carbohydrates in diabetes. It should be noted that in the analysis of both tissues and various fluids and excretions of a diabetic, it is impossible to find any metabolic products completely alien to the normal organism. Even acetone bodies, which represent such a sharp feature of severe diabetic metabolism, although in a significantly smaller amount, are nevertheless encountered in normal metabolism as well. Thus, the diabetic organism creates no new features in its metabolism according to the chemical structure of substances, and all syntheses and decompositions occur with the formation of ordinary intermediate substances. This circumstance makes it possible to some extent to apply data found on a healthy organism to a diabetic as well. This primarily includes the important rule according to which sugars, during their transformations in metabolism, break down until the formation of three-carbon complexes (lactic acid, methylglyoxal), which break down in the further course of metabolism into carbon dioxide and water. On the other hand, many issues essential for normal metabolism find their resolution when considering diabetic disorder. Such is, for example, the problem of the formation of sugar from bodies of non-carbohydrate structure. If one observes the effect of glucose feeding on sugar excretion in a diabetic, it is not difficult to be convinced that under the influence of the eaten glucose, the patient excretes more sugar. However, it would be incorrect to think that the absorbed glucose does not enter into any further reactions, but is directly excreted in the urine. Glucosuria increases under the influence not only of glucose, but also of carbohydrates of another structure, so that one has to admit at least the necessity of rearrangements. The question also arises regarding the cause of the sharp increase in the blood sugar content, which does not occur immediately after the introduction of carbohydrate into the stomach, lasts longer than normal, and indicates a disorder of the complex regulation of glycemia. Food levulose (fructose) although it increases urine glucose, does less so than glucose. On the other hand, a more abundant deposition of glycogen in the liver of the diabetic occurs from levulose. On the other hand, liver glycogen also passes into urine glucose, proof of which is that the Claude Bernard puncture is accompanied by a positive result only with a liver filled with glycogen. Thus, the question of the transition of food carbohydrates into glucose gives grounds to suggest that all food carbohydrates probably preliminarily pass through the stage of glycogen, which is poorly fixed by the diabetic liver and easily released in the form of glucose. One source of sugar is thus found in food carbohydrates and liver glycogen. As for the level of sugar concentration in the blood, its explanation at present encounters great difficulties. The previously prevailing view that a mere increase in concentration is sufficient for the appearance of glucosuria can no longer be fully supported. Due to the possibility of checking the sugar content in a drop of blood by chemical analysis, it is often possible to observe high glycemia without any glucosuria in cases of diabetes mellitus, with an appropriate diet, in hypertension, etc. Glucosuria is not in direct connection with hyperglycemia, and cases of glucosuria occurring without an increase in blood sugar are even encountered (renal and phlorhizin diabetes). The opposite extreme—a low standing of blood sugar concentration—is observed, besides cases of using excessively large doses of insulin, also in Addison's disease, phosphorus poisoning, and experimental excision of the liver. All experimental observations definitely indicate the dependence of the blood sugar level on the glycogen content in the liver. An attempt to find sugar isomers, of which only one passes through the kidney, remained without result. In severe cases of diabetes mellitus, sugar excretion does not stop even when the patient has been eating only fats and proteins for a long time or is even simply fasting. Since the available glycogen reserves are quickly mobilized and lost in the form of urinary sugar, further sugar excretion can be maintained only by the formation of sugar from other starting products. In view of this, one has to admit the possibility of the conversion of proteins or fats, or both, into sugar. At the same time, it does not matter whether sugar formation from these substances occurs directly or by passing through a preliminary stage of glycogen or another substance. It is important that a substance of non-carbohydrate structure can somehow turn into a carbohydrate (of course, we are not talking about using the ready-made carbohydrate group contained in some proteins). To resolve this issue, clinical observation can serve, consisting in the fact that the more protein a severe diabetic receives in food, the more sugar he excretes. To this it should be added that glucosuria also increases from feeding amino acids. Amino acids with an unbranched straight chain of carbons are suitable for the formation of such extra sugar. All these substances are deaminated in metabolism and then, having passed the phase of oxy- or keto-acids, are used as material for the formation of sugar. A prominent role in this process is played by the liver. However, it does not follow with absolute necessity from all this that food protein turns into sugar. Glucosuria may develop not because a large amount of starting material is introduced into metabolism, but because either general metabolism increases due to the specifically dynamic action of protein or from some other influence of eaten proteins on the course of metabolism in general. All this is all the more likely since the relationship between extra sugar and food protein is expressed by a very complex, rather than a simple linear dependence. A known relationship between the amount of excreted sugar and excreted N in diabetes mellitus exists. The coefficient D:N (the ratio of glucose to total urinary nitrogen) varies somewhat depending on the observed case and the setup of the experiment. Its value is sometimes 2.8, sometimes 3.65, and sometimes even greater. The idea that all the formed sugar passes directly into the urine and that the protein decomposition reaction quickly reaches urea is incorrect. It is therefore not surprising that, if calculations are made proceeding from the actually observed D:N, the amount of sugar corresponding to 100 g of protein is no more than 45–58 g. Without doubt, even the relative constancy of D:N deserves great attention. The huge amount of work carried out to resolve the problem of the transition of protein into sugar has led at present to the resolution of this question in the positive sense. The coefficient D:N was also used for their proof by proponents of the view claiming that sugar originates from fat. According to calculations of the coefficient D:N, the formation of carbohydrates from protein in the best case is equal to 6.37 (Geelmuyden).
Meanwhile, various observers have published figures significantly exceeding the limit value. This means that the decomposed protein that yielded nitrogen could not have provided all the excreted sugar, which in these observations could originate only from fat. However, the protein molecule may not decompose directly, but pass through a number of intermediate stages, and besides, the time required for the formation and excretion of sugar and urea may vary. The curves of protein nitrogen and protein sugar excretion would turn out to be shifted relative to each other. Another proof in favor of the formation of sugar from fat was deduced from the respiratory quotient in diabetics. Under normal metabolism, the lowest value of this quotient is calculated for fat and equals 0.707. Meanwhile, in cases of severe diabetes, one can quite frequently encounter figures that are significantly lower. This suggests that the oxygen bound during respiration (the denominator of the quotient) does not eliminate through the lungs all the carbon of the oxidized fat (the numerator of the quotient RQ becomes smaller). This can happen if fats upon oxidation yield carbohydrates, which are excreted in the urine in the form of glucose. But oxygen can also be bound and remain in the body without yielding carbon dioxide, both in the formation of acetone bodies or during other fixation of oxygen in the body. Both proofs of the formation of sugar from fat, based on rather complex calculations, are usually countered by the well-known clinical observation that feeding fats does not increase glucosuria. This proof, based on an extremely striking clinical fact, is disputed on the grounds that the transition of fat into carbohydrates may be very slow, and besides, the body's fat might produce different breakdown products in metabolism than dietary fat and differ in its effect on glucosuria. Thus, the question of the formation of carbohydrates from fats can by no means be considered resolved. It is hampered first of all by the fact that the methodology for observing fat metabolism is still insufficiently developed. It is also difficult to imagine the transition of fat into sugar chemically, since fat metabolism proceeds via intermediate substances with a number of carbons equal to 4, whereas substances with three carbon atoms play an important role in carbohydrate metabolism. Products of an intermediate character between these two types of chemical substances have not been detected in metabolism. Despite this, it is nevertheless fully proven that the reverse path—the synthesis of fat from carbohydrates—belongs among the frequently encountered phenomena in metabolism. It remains to add that the glycerin residue entering into fats can apparently serve as a source of carbohydrate formation in the body. Aside from the question of the sources of sugar, it is also necessary to determine what the essence of the diabetic disorder is. Even substances that are difficult to oxidize are destroyed in the diabetic's body in the exact same way as in a normal person, and there are no grounds to assert that oxidative processes in a diabetic patient are generally lowered. The disorder concerns exclusively carbohydrate metabolism. There are two assumptions to explain diabetes mellitus. The first is that sugar is oxidized more slowly in diabetes than in normal conditions. The introduction of carbohydrates in the intestine therefore little increases the RQ of a diabetic. Due to this, the normal flow of glucose from the intestine and tissues (mainly the liver) fails to undergo timely oxidation, as a result of which glucosuria ensues. But a complete loss of the ability to oxidize sugar is never observed. This would also contradict the modern view of sugar as a source of muscular activity, which does not fade in a diabetic, and furthermore, muscular work even in a severe diabetic increases RQ. The slowing down of sugar oxidation in diabetics is also confirmed by observations on the action of insulin, under the influence of which carbohydrate oxidation in muscles increases in experiment. The second assumption put forward to explain diabetes mellitus speaks of enhanced sugar formation. According to it, the carbohydrate flow, the sources of which are lost in the tissues and intestine, flows more violently than normal, flooding the entire body with sugar that fails to burn in the corresponding organs and is therefore eliminated through the kidneys unused. Moreover, the mechanisms that should prevent a carbohydrate "flood" (glycogen formation) do not operate in a diabetic. Such an assumption is harder to prove than the slowed oxidation of glucose, although enhanced sugar production by a diabetic in a workable state is highly probable. There is nothing impossible in the fact that both sugar formation and sugar utilization are impaired in a diabetic patient. A peculiar deviation of carbohydrate metabolism has been found in tumor cells. Every cell, to maintain its vital needs, extracts energy from carbohydrates either with the aid of oxidation processes or without the aid of oxygen. In the first case, we have before us respiration, and in the second, what is termed fermentation. Both capacities are in a complex relationship with each other. If one experimentally investigates the metabolism of normal epithelial cells proceeding in the presence of oxygen, it is easy to demonstrate their respiration. Cancer cells under these same conditions, besides respiration, energetically ferment glucose into lactic acid. The study of the same objects under anaerobiosis conditions shows that normal epithelium also possesses the ability to induce fermentation, but to a significantly lesser degree than the cancer cell. The ability to induce fermentation in the presence of oxygen is linked by some authors with the atypical growth of cancer. This feature is considered characteristic of cancer metabolism, and it has been proven that venous blood flowing away from cancerous tumors is richer in lactic acid than normal blood.
e. Fromhold. The pathological anatomy of disorders of carbohydrate metabolism is expressed merely in deposits of glycogen in the tissue, which is a consequence of a general disorder of carbohydrate metabolism as in diabetes (see Diabetes mellitus), and sometimes also in local abnormalities of this metabolism, e.g., in tumors and foci of inflammation (see Glycogen infiltration). In cases of prolonged disturbance of carbohydrate metabolism, the pathologico-anatomic picture may be complicated by signs of a general nutritional disorder in the form of cachexia of one degree or another. Mineral metabolism. Mineral metabolism embraces a number of phenomena concerning the absorption of mineral elements, their migration through the body, their distribution among the tissues and fluids of the organism, and their excretion outward. The gross content (in percentage) of mineral substances in the human body is as follows (excluding O2): Table 18. Element % Element % Ca Na Cl Mg Fe 1.5 1.0 0.35 0.25 0.15 0.15 0.05 0.004 0.00004 Zn Si Al, Br, Cu, F, Mn As, B, Pb, Ti, Co, Ni thousandths fractions » ten-thousandths ) fractions ^ hundred-thousandths fractions. Not all elements from the indicated series belong to "bioelements"; some of them, such as Cu, Pb, Co, and Ni, are an optional component part of the body, at least in higher vertebrates. Mineral elements in the body are represented: 1) as individual elements entering into the composition of organic compounds, such as S in cystine, Fe in hemoglobin, J in iodothyrin; 2) in the form of mineral acids and mineral or organic salts, whereby they (acids and salts) can be a) free and in solution in a dissociated or non-dissociated state, b) bound; this boundness can be either weak or more or less strong. Electrolytes, mineral cations and anions, in their distribution among the fluids and cells of the organism create that complex system of concentration differences which can determine the course of diverse osmotic and diffusion processes in the organism. However, the distribution of individual electrolytes in tissues, obeying Donnan's principle, reveals that their role is not limited to the formation of individual osmotic tensions; thus, it is known that the normal excitability of muscles and nerves also depends on a definite combination of electrolytes in it (cf. the composition of Ringer's, Locke's, and other fluids), and changes in the relations between them are permissible within very narrow limits. The mineral composition of the blood and normal tissues of an animal in general is characterized by great constancy (under given conditions), which depends mainly on the action of four factors: on the intake of inorganic compounds from the outside; on the continuous destruction of organic materials in tissues in the process of catabolism, liberating mineral elements in the form of electrolytes, - increases the concentration of mineral substances in the body fluids; on the constant excretion outward of mineral substances by the kidneys, skin, intestine, etc.; finally, on the accumulation or giving up of mineral elements by the mineral depots of the organism—the skeleton and probably many other tissues (depending on the concentration in the blood or under the influence of physical-chemical properties, for example, blood pH). The indicated four factors represent a system where at each given moment mutually opposite actions are revealed: some of them raise the level of mineral compounds in the blood (e.g., the intestine in periods of absorption or depot tissues in periods of depletion of the blood in mineral content), others lower this level [e.g., excretory organs (kidneys) or various depot tissues in periods of their replenishment with mineral compounds]. When the nutrition of the organism changes, the mineral equilibrium shifts in one direction or another only temporarily, until the action of the indicated factors restores it at the former level. Under various (long-term) feeding systems, organisms can show corresponding differences in their mineral composition, especially sharp in cases of defective nutrition. The ability of the organism to create a sort of mobile equilibrium between mineral elements—salts and ions—of the blood and various organs is in turn the result of influences on the metabolism of individual organs, on the one hand, and external influences—on the other. For example, lactic acid arising during muscle work changes the concentration of hydrogen ions, which in turn changes: the ratio between various components of the blood buffer system (see Buffer properties); the composition of the muscle itself, depriving it, among other things, of potassium, which is liberated from colloidal bonds by lactic acid (Burridge; 1906). The increase in H+ (acidosis) in this case also causes greater solubility of Ca, as a result of which a temporary calciuria is obtained. Of endogenous influences on mineral metabolism, one can point to the relations to it on the part of the endocrine and nervous systems. Thus, it has been established that after pancreatectomy (in dogs) hypochloremia develops, which leads to a decrease in the release of Cl in the urine, while its content in organs changes in various ways: it increases in muscle tissue and decreases in the liver and skin (Meyer-Bisch, Ni; 1926, 1927), and the changes in chlorine content proceed completely independently of the Na content. In addition, in a number of experiments it was noted that adrenaline lowers the Cl level in the lymph (retention of Cl by tissues!); insulin and "pituglandol" preparations act inversely to this. There are also a number of indications regarding the participation of the thyroid gland in Ca and P metabolism. According to recent works by Mizokami and Nishimura (Mizokami, Nishimura; 1929) in dogs, there is an increase in Ca excretion after feeding with the thyroid gland and a decrease after thyroidectomy. Similarly, it has also been established in humans (Aub; 1929) that the administration of thyroid substance or thyroxine causes an increase in the excretion of Ca and P. In connection with this, in hyperthyroid states (Basedow's disease, thyroid adenoma) we have an increase, and in hypothyroid states—a decrease in the excretion of Ca and P (Figure 5). The increased excretion of Ca and P in the described cases occurs at the expense of bone substance; recently this has been confirmed fluoroscopically (with prolonged Basedow's disease—greater transparency of the skeleton, with myxedema—the opposite). At the same time, it has also been established that Ca in the blood decreases in Basedow's disease and in a normal person after doses of thyroxine; the reverse phenomenon is observed in myxedema (Leicher; 1922). The parathyroid glands also take part in the metabolism of calcium and phosphorus. Their experimental removal leads to significant hypocalcemia and high phosphatemia, which is associated with simultaneously occurring phenomena of tetany. However, it should be noted that in tetany the lime content in the skeleton that has finished growth, as in muscle tissue, is not lower than normal (Behrendt; 1926), so that the defect in calcium metabolism concerns not the total content of this element in the organism, but its transportation through the body. At the same time, it was clarified that in tetany the excretion of Ca in the urine decreases (Ca retention); the excretion of phosphorus is lowered in exactly the same way, so that in the presence of hyperphosphatemia one can speak of an overload of the body with phosphorus and consider lowered calcemia as a consequence of the enrichment of the blood with phosphates [it has been experimentally shown that the introduction of phosphates (man, animals) significantly
Figure 6: I—normal; II— postoperative tetany; III—normal, 50–55 units of parathyroid hormone; IV—normal, 80–100 units of parathyroid hormone; V—hyperparathyroidism, 0.41 g.
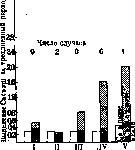
lowers serum calcium (Binger, 1917; Gyorgy, 1924; von Klercker, 1925; Gates, 1927)]. The combination of all these phenomena expresses an alkalotic state of the organism arising as a result of a disruption of the regulatory mechanism when the action of the parathyroid hormone is lost. Conversely, the introduction of this hormone into the organism causes phenomena that are diametrically opposite (Fig. 6). The connection of mineral metabolism with the nervous system is a topic that is still very little developed. The influence of endocrine organs on mineral metabolism implies this connection through sympathetic and parasympathetic innervation. A direct illustration of nervous influences on mineral metabolism can be served by the experiments of Alpern (1925), who demonstrated a change in the potassium content in saliva after irritation of the sympathetic nerve, as well as the studies of Neuschloss and Trelles (1924), which discovered a difference in the potassium content in muscles deprived of their innervation compared to muscles with intact nerves. Furthermore, according to the experiments of a number of authors, the section of the greater splanchnic nerve and the removal of the celiac plexus cause a drop in serum calcium without tetanic phenomena, while the phosphorus level remains unchanged; the section of both vagus nerves raises the calcium level. Absorption of mineral elements. The mineral constituents of food undergo absorption mainly in the small intestines, and not only free salts disappear from the intestinal canal, but also those weakly bound to organic compounds (e.g., with amino acids). The digestive process promotes the release of more tightly bound mineral components of food as well. For alkali metals and chlorine, their very rapid and complete absorbability is noted; in humans, the chlorine content in normal stool is 0.05 g per day (Wendt). An illustration of absorption can be served by Heidenhain's experiment; a loop of the empty small intestine of a dog isolated by two ligatures absorbed a sodium chloride solution in the following manner (see Table 19). Obviously, absorption proceeds faster from hypotonic solutions than from hypertonic ones; from hypotonic solutions, of course, water is rapidly absorbed osmotically, and the solution is concentrated to the sodium chloride content in the plasma (about 0.65%), however, sodium chloride penetrates the intestinal wall despite the fact that its concentration in the intestinal lumen is less than in the blood; the cause of this phenomenon must be sought in the fact that diffusion currents from the intestinal lumen are determined not by the blood (Introduced NaCl, Content of NaCl in solution after | 15 min.)
Absorbed NaCl in 15 min. cm3 | 120 (120 % of introduced cm3) Hypotonic 0.3 0.36 0.60 0.108 0.25 solutions 0.60 0.63 0.23 0.37 Hypertonic 1.00 1.17 0.90 0.67 0.50 solutions 120 1.46 1.75 1.20 1.31 0.44 by its concentration, but by the living epithelium of the villus, the metabolic processes of which are still unknown to us. Hypertonic solutions osmotically cause the secretion of water into the intestinal lumen and inhibit salt absorption. In the observed phenomena, the matter is additionally complicated by the fact that probably the pressure on the intestinal contents arising due to the work of the muscles of the intestinal wall causes it to be forced into the intercellular spaces of the intestinal wall ("filtration" of liquid), similarly to how the peculiar "pump" of the villus acts. The transition of chlorine into the blood after absorption under normal dietary regimens slightly changes the concentration of this element in the blood—from 0.36% to 0.38%. Arterial blood is richer in chlorine than venous blood. Short-term hyperchloremia (e.g., 0.407% chlorine in blood versus 0.364% initially) is observed only after giving a large dose of sodium chloride. The general water-salt regime exerts an influence on the level of chlorine in the blood; a prolonged low content of table salt in the food also lowers the chlorine content in the blood to the lower limits of its normal fluctuations. Constant consumption of very salty food increases the chlorine content in the blood. In the first hours of digestion, a certain decrease in chlorine in the blood is observed under the influence of increased secretion of gastric juice. Similar to chlorine, sodium and potassium after absorption, depending on their content in food, the rate of absorption, and the water regime, can increase their concentration in the blood for some time (normal fluctuations of sodium and potassium in plasma run within the boundaries of 0.28–0.35%, resp. 0.016–0.024% in humans and close to these numbers in other mammals), and a clearly expressed antagonism between potassium and sodium is noticeable: an increase in the content of one of them in the blood decreases the content of the other. The excretion of chlorine and alkali metals from the blood occurs mainly through urine, and also via perspiration; during significant sweating, the organism loses no small amount of chlorides; according to Tuteur, up to 4% of the total chlorine loss goes through the skin. With very abundant perspiration due to mechanical work at a high temperature (e.g., during mountain climbing in hot weather), according to data by Cohnheim, Tobler, and others, up to 10 g of sodium chloride was lost through sweat within a few hours. According to Aggazzotti's data, during travel in the mountains, the loss of chlorine through the skin was so great that for several days sodium chloride did not appear in the urine at all, and significant hypochloremia was observed (up to 0.43% sodium chloride in blood, resp. 0.17% chlorine). Table 19. The question of the assimilation of calcium and phosphorus is complicated because both of these elements are excreted from the organism not only by the kidneys, but also by the intestines, and very significant amounts of these elements are often removed by the latter route; therefore, during ordinary studies of the assimilation of calcium and phosphorus, when comparing their content in the stool and in the food, it is entirely impossible to decide which part comes from unabsorbed food salts and which part was formed as a result of the excretory function of the intestine. From experiments proving the ability of the intestine to absorb calcium and phosphorus, besides old experiments (Voit, Forster, Raudnitz; 1885–1893), one can also point to the experiments of Aristovsky, Walsh, Ivy (1925–1928) with fistulated dogs; it turned out that the resorption of calcium and phosphorus occurs in the ileum, and for phosphorus also in the jejunum, but 40–50% of the introduced elements leave the small intestines without being absorbed. Table 20. Food: 600 cm³ of milk. Excreted into the chyme through the fistula. Percentage of excreted to introduced Ca Ca Ca % 0.595 0.595 0.543 0.578 0.83 0.83 0.84 1 0.84 | 0.224 0.219 0.244 0.230 0.308 0.458 0.493 0.412 37 36 45 39 37 55 58 47 600 meat | 1.34 1 1.34 0.083 | 0.083 ! 0.092 | 0.089 0.187 0.159 7 7 224 190 From Table 20 it is evident that with a diet poor in calcium, a very significant loss of this element through the fistula is obtained, which illustrates the excretory capacity of the intestine. A significant excess of calcium in the feces over its amount in the food was also often observed in humans. In Aub's experiments, on average over a 3-day interval, fecal calcium (in 13 individuals) amounted to 0.60 g versus 0.33 g of calcium in the food. Similar observations reveal the excretory function of the intestines with respect to phosphorus as well (Table 21). Table 21. Authors Tigerstedt Phosphorus of food
In the experiments of R. Berg (1911), increased excretion of calcium and phosphorus through the intestine lasted for some time after the cessation of the intake of calcium and phosphorus in food. Calcium absorbed through the intestine does not produce noticeable changes in the level of calcium in the blood; only very large doses of calcium (up to 30 g of anhydrous CaCl2) cause a slight rise in it, so that the calcium content of blood plasma is very stable (9-13 mg% in almost all mammals), which indicates the active work of calcium depots (bones), which react rapidly to changes in calcaemia. As for phosphorus, its ingestion in food causes, although not always, an increase in blood phosphorus; in rabbits and small children, a gradually increasing phosphatemia has been traced after the administration of phosphates, reaching a maximum after 2-3 hours (up to 180% compared to the initial level). Fluctuations of free phosphates in the blood undergo very significant variations, according to various authors from 4 to 18 mg%; general nutrition also has an effect; with a diet poor in phosphorus, inorganic blood phosphates lower their level. Like other elements, the absorption of iron occurs in the small intestines; this has been proved by various methods, inter alia morphologically (microchemical reaction for iron). (Regarding the question of the forms in which iron is absorbed, see Iron.) As with the previous elements, the quantitative problem of iron assimilation is greatly hindered by the same fact, namely, that in fatal erythropenia, the norm was achieved by the increased administration of iron with food (see below under pathology of metabolism), which speaks in favor of the influence of dietary iron on erythropoiesis. Under normal blood conditions, an increased supply of food rich in iron can increase the content of this element in its depots—tissues (bone marrow, spleen, liver), without affecting the iron content in the blood; thus, when mice were fed iron, the content of the latter in their bodies increased 3 times in comparison with control animals. Mineral substances that have been absorbed and passed into the blood are distributed throughout the body, pass into the corresponding depot tissues, increasing their mass, and replace gaps that have arisen in other tissues; inorganic materials that have not found application leave the organism via the pathways indicated above. Various tissues make different demands on the organism for mineral components, being characterized by a more or less constant composition. It is most constant in bones, although even here various studies yield heterogeneous figures, and even in the same animal, symmetrical bones reveal an unequal content of mineral elements. Tissues: Bone 1780; Striated muscles 80; Smooth muscles 112; Brain 100-180 (white matter —, grey matter —); Liver 60; Skin (to dry matter) 100-143; Spleen —; Blood (see Blood).
\ that the intestine is simultaneously both an absorbing and an excretory organ for iron. It is accepted that the stomach and small intestines perform resorption, while the large intestine performs the excretion of iron; however, there are essentially no solid grounds for such a division of roles within the intestine. In addition to the intestinal epithelium, Fe is also excreted by bile, up to 1 mg pro die in humans; this value is considered constant and independent of the intake of iron in food or parenterally, since it originates from the breakdown of erythrocytes; it is possible that this iron is partially reabsorbed again in the small intestines. According to Hofmeister's calculations, 40–50 mg of Fe should be released from the breakdown of erythrocytes, of which 1–2 mg is excreted by the urine, and the rest through the intestine. Fe absorbed in the intestine penetrates into both blood and lymph; this has been traced morphologically (microchemical reactions), but it has not been possible hitherto to notice an enrichment of these fluids with iron even under conditions of maximum absorption; the fact is that the blood plasma and lymph are considered practically free of iron (according to Erben, 1 kg of blood plasma contains 23 mg of Fe; 1 kg of white blood cells, 95–122 mg) and in routine blood tests the addition of absorbed iron is not amenable to calculation. As for the amount of Fe in whole blood, it depends on the Fe content in erythrocytes (see Blood) and on the number of the latter in the blood. The influence of various dietary regimens on the Fe content in the blood is difficult to trace; only in rare cases of experimental anaemia and experimental Tabl. 22. Content of mineral elements in some tissues (according to various sources) in mg %. Na Ca Mg 320 250 240 400 58–119 7 940 7.5 5 2–17 26–78 5–15 12–21 8–14 9–17 7–10 Fe 15 2 5–10 Cl 70 120 150 3–60 100–200 - 240–480 72 161 P 3 850 - (224) (9) (210) (92) Bone is characterized by a high constancy of its composition, which at one time prompted an attempt to establish a definite chemical "formula" of bone substance (Hoppe-Seyler). However, according to Hofmeister's view (1911), the observed constancy of bone composition depends on the constancy of the composition of the fluid feeding it, namely the blood fluid. Improper nutrition of the organism, various types of salt starvation, can change the content of mineral compounds of bone (see pathology below). A change in blood pH towards the acidic side causes the dissolution of mineral substances of bone and enhanced excretion of Ca and P through the urine, which is characteristic of acidosis. "Artificially" induced acidosis (administration of lactic acid, oxalic acid, weak sulfuric acid, etc.) leads to the depletion of bones of lime. It is clearly seen from the table that bone is very rich in mineral elements and represents indeed a depot tissue for these elements, especially for Ca and P. During starvation, bone tissue "melts" strongly, losing its mineral elements (decrease in bone ash) (Morel, Moulliquand et al.; 1921–1925) and in particular Ca and P (Iwabuchi; 1922). Prolonged calcium deficiency in food can lead to the complete resorption of some bones (Lavrov, Yarusova). Of course, apart from bone mass, mineral elements are also released from other tissues decomposing in the order of catabolism. Guided by the loss of protein in the body (by nitrogen) and assuming that this protein originates from the destruction of muscle mass, one can calculate how many mineral elements should be released in this case (knowing the mineral composition of muscles) and compare their amounts with those in the urine and feces of the experimental subject. In the table (Gamble's observation on a starving girl), each mineral element is expressed in decimilliequivalents, in other words, by the equivalent number of cm3 of n/10 solution. Tabl. Starvation periods (3 days each) Na Mg 13.3 11.5 10.3 0.3 0.9 1.1 0.7 1.0 1.0 0.6 1.1 0.9 _ It is seen from Table 23 that for K and Mg the ratios of the found to the calculated are very close to 1; this indicates that the muscle mass destroyed during starvation is indeed the source of these elements, whereas for Ca the found figure exceeds the calculated one by more than 10 times; consequently, the source of Ca in this case must be another tissue; such a tissue is bone. Comparing the mineral composition of other tissues, we see that most of them are characterized by a comparatively high potassium content and a scarcity of calcium; in terms of iron content, the first places are occupied—while still significantly ceding to bone—by the liver and spleen, which in relation to this element are depot tissues; significant fluctuations of Fe in the liver depend on the "delivery" of the element to this organ, and this "delivery" can be exogenous (from food) or endogenous (from other organs). The skin also attracted the attention of researchers in view of large fluctuations in its mineral composition. The skin made it possible to discover a certain dependence on the type of food with regard to alkali metals and chlorine. Some authors therefore consider the skin as a depot tissue for the just-named elements. In addition to the elements indicated in the table, rarer elements were found in various tissues, the appearance of which is apparently of a random nature, e.g., Zn (3–5 mg%), Cu and Al in muscles, Zn up to 15 mg% (human) and 34 mg% (horse) in the liver, Cu up to 12 mg% there, Sn 10 mg%, and Mn, As, B, F, and others in fractions of mg%. The significance of mineral elements in nutrition is not limited only to the absolute level of one or another element in the body or food, but also to the ratio of these elements to each other. Thus, L. Redina noted the optimal ratio of Na : K as 5:1 (on white mice). It has also been clarified that Ca has a beneficial effect on the utilization of Fe in the organism: with an increase of Ca in food, iron equilibrium can be maintained at lower levels. As for the question of the mutual influences of mineral elements, cases of antagonistic phenomena pertain here. Thus, with well-balanced diets, the administration of magnesium causes the loss of Ca in the organism; the unfavorable effect of Mg injection disappeared after a subsequent injection of Ca. Ca can generally correct the disturbance of inorganic equilibrium; under any anomalous effects experimentally induced by alkalis (Na, K, Mg), Ca acts in a restoring (equilibrium) manner. This also includes the classic experiment of Bunge, who caused abundant excretion of Na from the organism by administering a large amount of K. On the basis of balance observations on pregnant women and on the basis of data from analyses of human fetuses at various stages of development, it was possible to compile the following diagrams for P and Ca (Figs. 7 and 8). The ratio of mineral acids to mineral bases in the blood fluid and in the organism in general. Comparing the analyses of various researchers giving the mineral composition of human plasma or serum, some authors (Heubner, Kramer, Marrack, etc.) were able to compare the acid and alkaline equivalents of the blood fluid (plasma). The difference between acids and bases represented in milliequivalents for plasma amounts to 151–135 = 16 milliequiv. (according to other authors from 10 to 25) in favor of bases, with acids (135 milliequiv.) being fully covered by sodium (139 milliequiv.). The excess of alkalis (16 milliequiv.) is probably bound to acidic proteins, perhaps also to higher fatty acids. Such a setting in the organism, close to neutrality [pH = 7.36–7.32 (37°)], is very essential for a number of physiological processes of intermediary metabolism (see Alkalosis and Acidosis). All cases disrupting this setting require a corresponding reaction on the part of the organism; first of all, the buffer system is used, then the work of the respiratory center, prompting through accelerated breathing the evacuation of CO2, subsequently the dissolution of reserve
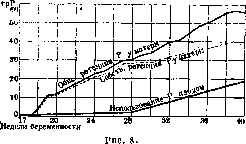
,alkalis from tissues occurs, and finally the splitting off of ammonia from amino acids (resp. proteins) as a neutralizing base; in this latter reaction the liver plays a significant role, and in all stages of the development of acidosis also the kidneys, inasmuch as they are capable of excreting acidic urine. A priori one could imagine that food containing various ratios of mineral acids to bases is capable of producing certain shifts in the pH norm in one direction or another, and only through the compensatory work of depots and excretory organs can this norm be preserved. From this point of view, it is by no means indifferent to the organism what the ratio of acids to bases in food is. This question began to be studied long ago in America in Henry Sherman's laboratory (1911–12), with research primarily concerning ordinary foodstuffs to establish their "acidity" and "alkalinity." A brief table from Sherman's work is given for illustration.
Products | Excess of acid elements in cm³ of n/10 acid per 100 g of product | Products | Corn . . . | Rusks ..... | Fish...... | Eggs...... | Egg white | Egg yolk | Meat ...... | Fish...... | Oatmeal . | Rice....... | Whole wheat | Wheat flour | Apples ..... | 6.95 | 7.81 | 9.89 | 11.10 | 5.24 | 26.69 | 0.05-13.91 | 9.5-16.0 | 12.93 | 7.8 ! | 9.66 ! | 11.6 ! | Beans....... | Beets ...... | Cabbage..... | Cauliflower | Milk..... | Oranges . . . | Peas ...... | Potatoes. . . . | Plums ...... | Radishes ..... | Raisins....... | Turnips ..... It is evident from Table 24 that meat, eggs, and cereals belong to acidic products, while milk, fruits, and vegetables belong to alkaline ones. Thus, a new aspect was introduced into the evaluation of food. It was required to ascertain what the optimum ratio of acids to bases in food should be. However, neither physiology, nor clinical medicine, nor animal husbandry has yet provided definitive developments on this issue. On the other hand, the question of human requirements for one or another mineral element has long been discussed in physiology, with the basis of all research resting on the assumption that for a person of a given age there must be a certain minimum and optimum for each mineral element. Such a formulation of the question is fundamentally incorrect, because in addition to the ratio of acids to bases in food, it is necessary to study the even more complex tangle of dependencies of the requirement for mineral components of food on its organic components, on the water economy of the organism, on the ratios of alkaline elements to each other, on the compensatory abilities of the human organism in relation to the establishment of equilibria in the system: «depot-tissue-blood-consuming and excretory organ», and these abilities in turn are related to occupational habits, exercises, and generally to all living conditions. Therefore, any indications by authors on the level of human requirements for individual mineral elements must be considered a provisional solution to the problem. Thus, Sherman conducted 97 experiments on humans to determine at what level of calcium (also in relation to other elements) equilibrium could be obtained [i.e., when the Ca balance (Ca of food - Ca of excreta) = 0]. It turned out that in different subjects the minimum level of Ca suitable for establishing equilibrium is extremely variable—from 0.27 to 0.82 g per person per day. An average value was taken: 0.45 g. Similar experiments were conducted for phosphorus, where the average turned out to be 0.88 g per person per day (fluctuations 0.52-1.20), and a small number of experiments for iron, which gave fluctuations from 6 to 16 mg per person per day; here they stopped at a rounded number—15 mg. Of course, Sherman proposed increased values for both phosphorus and calcium, namely for Ca—0.68, for P—1.32 g per person per day. These values are adopted in America as HYGIENIC NORMS.
B. Lavrov.
Pathology of mineral metabolism. Mineral salts are an essential component of tissues and fluids; this plastic role of theirs is manifested during starvation, when, along with the excretion of the breakdown products of the organic constituent parts of the organism, mineral salts are also excreted. Deprivation of mineral salts leads to the death of the animal. Prolonged predominance in the food of certain salts and the absence of others apparently to a certain extent |
| may alter the mineral composition of the organism (Noorden demineralization). Some authors believe that a certain ratio of mineral salts in food with a predominance of acidic or basic valences can influence the general metabolism in the organism (Bunge), the course of pathological processes, and wound healing (Sauerbruch, Herrmannsdorfer). Mineral salts have a regulatory significance. Table 24. Excess of alkaline elements in 100 g of product ... for maintaining the constancy of the reaction of tissues and body fluids (see Buffer properties, Reserve alkalinity). Thanks to the blood and tissue buffers, the accumulation of acids or bases in the body does not lead to a change in the active reaction of the blood (compensated acidosis, compensated alkalosis). A shift of the active reaction to the acidic or alkaline side occurs extremely rarely, mostly shortly before the death of the organism. But with compensated acidosis, despite the unchanged blood pH, there is a change in the blood composition: a decrease in reserve alkalinity, a decrease in carbon dioxide tension, a lowering of the CO2 binding curve; furthermore, the amount of bases in the blood decreases, predominantly Na. Sometimes in diabetic acidosis, such Na losses make it impossible to combat acidosis using insulin alone, but require the administration of NaHCO3. The reverse process occurs in alkalosis. Mineral salts regulate the osmotic state (see Osmotic pressure) of tissue fluids, especially blood. A lowering of the freezing point of blood from Δ=-0.56° by a few hundredths of a degree often indicates significant disorders in the body. A transient increase in osmotic pressure is observed with large fluid losses (sweating during work in hot shops, in cholera), and a prolonged one mainly with renal insufficiency. The concentration of mineral salts (electrolytes) is of great importance for the stabilization of colloids and has an influence on the state of cell excitability. Thanks to the studies of Ringer and Loeb (J. Loeb), it has been established that the correct functions of cells are maintained by a mixture of K, Na, Ca, and Mg ions in definite ratios; a change in these ratios can lead to excitation or paralysis. Changes in these ratios are closely associated with diseases of the endocrine glands and with disorders of the nervous system. Kraus and Zondek associate the action of K with the vagus nerve and the action of Ca with sympathetic innervation. A decrease in Ca and an increase in K in the blood are observed in tetany, both parathyreoprivic, idiopathic, and guanidinic; the change in electrolytes is accompanied simultaneously by alkalosis; a decrease in Ca is encountered in hyperthyroidism, and an increase in hypothyroidism. Changes in the composition of mineral salts of the blood occur in allergic states, infections, and fever. Often it is not the absolute content of one or the other ion that matters, but the interrelation of two ions, for example K/Ca in arteriosclerosis (see Blood). Special metabolism of various mineral salts and ions. Sodium chloride. The retention of sodium chloride and its excretion are closely related to water metabolism (see below) (see Edema, Nephritis). In lobar pneumonia and many febrile processes, there is a significant retention of NaCl: the urine contains almost no table salt; at the same time, the amount of NaCl in the blood not only does not increase, but, on the contrary, its content decreases (Monakov). Calcium. During starvation, the amount of Ca excreted in the urine increases, and that excreted in the feces decreases. Parallel to the increase in Ca excretion, the excretion of Mg decreases. The opinion regarding demineralization and loss of Ca in tuberculosis was not confirmed. Calcium metabolism is closely related to phosphorus metabolism: bones are the main site of deposition of calcium phosphate. Besides calcium phosphate, bones also contain calcium carbonate, which can be extracted from bones when there is a large amount of acids in the body in order to neutralize them (e.g., in diabetes). In pathological processes associated with the skeletal system and characterized by insufficient ossification or resorption of bone tissue, as in rickets and osteomalacia, the amount of Ca and P in the bones decreases, but the ratio of Ca++ to PO4"" does not change. In the florid period of rickets, the excretion of Ca and P is elevated (Ca and P in the blood, see Blood). Simultaneously with increased Ca excretion, an observation of Mg retention is made. In osteomalacia, the excretion of Ca and P does not appear uniform; in the bones, as in rickets, a decrease in Ca and P is observed, but their ratio does not change (see Blood). In various forms of calcification and ossification (myositis ossificans, calcinosis, etc.), the interrelation between Ca, P, and CO2 is the same as in normal bones. The deposition of calcareous salts is apparently a secondary process; primarily, a regressive change in tissues develops. The deposition of calcareous salts in various areas of the organism damaged by infection or toxic action (tuberculous lesions, thrombi, arteriosclerotic vessels) is frequently encountered. Vigantol (vitamin D) administered in excessive amounts in recent times often leads to vascular calcification, which may depend on the fact that vigantol alters the connective tissue in which the deposition of calcareous salts subsequently occurs. Phosphorus. During starvation or inadequate nutrition, the amount of phosphates in the urine increases; by calculating the ratio of excreted N:P, it became clear that the urine phosphates are not only of organic but also of inorganic origin. Large losses of phosphorus are encountered when feeding thyroid gland preparations and in Basedow's disease. Retention of phosphates is observed alongside the retention of chlorides in acute febrile diseases and in nephritis (see Blood). Phosphaturia is not a disease of metabolism in the narrow sense; it, like oxaluria (see below), belongs to anomalies of the form of their excretion. Phosphaturia is the excretion of urine in which phosphates are contained in the form of a sediment. The sediment is mostly amorphous [tricalcium phosphate, Ca3(PO4)2, calcium carbonate], partly crystalline [CaHPO4, dicalcium phosphate; triple phosphate - Mg(NH4)PO4]. The urine mostly has an alkaline reaction. Between the formation of the sediment and the total amount of phosphates in the urine, there is no direct relationship. According to Sendtner and Tobler, in phosphaturia the amount of Ca in the urine is elevated, and the amount of phosphates is normal. Apparently, the precipitation of phosphates depends on the state of the urine colloids (Lichtwitz). Some authors (Minkowski, Lichtwitz) regard phosphaturia as a secretory neurosis expressed in the loss of the kidneys' ability to excrete acidic urine. Oxaluria is the appearance in freshly voided urine of crystals of calcium oxalate. The increased precipitation of oxalates in the sediment does not depend on the concentration of oxalate salts; the precipitation of calcium oxalate can take place in acidic, alkaline, and neutral urine. Klemperer and Fischler make the solubility of oxalates dependent on the content of magnesium salts, but magnesium salts do not increase the solubility of oxalates, although they can suppress oxaluria to a certain degree. Lichtwitz believes that oxaluria, like phosphaturia, depends on the state of urine colloids. Yu. Gefter. Pathological-anatomical manifestation of mineral metabolism disorders can be twofold: either it represents the result of a decrease in the amount of salts in the tissue, or it is expressed in the deposition or precipitation of salts in some tissue or cavity. The first concerns calcium, the decrease in the amount of which in bone tissue takes place in a number of special "malatic" diseases of the skeletal system, giving peculiar pathological-anatomical pictures (see Osteomalacia, Osteitis fibrosa, Rickets). The precipitation and deposition of salts can also relate to calcium (see Calcareous deposits, metastases), as well as to other salts (see Gout, Concretions). The pathological anatomy of iron metabolism disorders - see Anemia, Hemosiderin, Hemochromatosis, Iron deposition. VIII. Water metabolism. Water metabolism is essentially the main type of intermediary metabolism, since water is the most important constituent part of the organism. In adults, water constitutes 58-64% of their total body weight, and in newborn children it even reaches a value of 74% and more. Along with this, almost all chemical processes taking place in water metabolism—diffusion of soluble substances, the influence of osmotic forces, swelling and unswelling of blood and tissue proteins, formation of secretions and excretions—proceed either in aqueous solutions or with the indispensable participation of water. In individual organs and tissues, an extreme stability of the percentage water content is noted. Out of approximately 50 substances entering into the composition of bile and blood, only isolated ones can be dissolved also in other solvents besides water (Henderson). In addition, the water molecule, thanks to its dipolarity, is an excellent dielectric (see), due to which conditions are created for the best dissolution of electrolytes in it and their dissociation (see Electrolytic dissociation).
Water also possesses the maximum (after mercury) surface tension, which explains the variety of adsorption phenomena from aqueous solutions. Finally, the dipolarity of the water molecule and the lability of its compounds determine its dispersing effect on colloidal suspensions (see Gels). The maximum water content is noted in the kidneys (82.7%), muscles (75-80%), and nerves (up to 82%), and the minimum in adipose tissue (up to 29%) and tooth enamel. In absolute values, the muscles contain about half of all the water making up the organism (Table 25); furthermore, it remains unclear to this time whether the muscles are a site for the accumulation of the organism's water reserves—its depot—or whether, which is more likely, water serves as a constant participant in the highly intensive biochemical processes occurring in the muscles. The water content in organs is maintained with exceptional constancy, since the artificial removal or loss of 10% of the total amount of water leads to the death of organisms. Table 25. Percentage of water in the main human organs and the distribution of water in them. Organs and tissues: Blood..... Fat...... Skin...... Bone tissue Muscles . . . . Nervous tissue Intestines..... Heart ..... Liver ..... Lung ..... Spleen . . . Kidneys..... Other..... Amount- Percentage
In intermediary metabolism, water participates either as a solvent for molecular particles or as hydration water, which is a component of plasma proteins, cellular protoplasm, lymph, and intercellular substance as hydrophilic colloids (see Gels). Water playing the role of a solvent is characterized by great mobility, fluidity, and is easily absorbed and released by tissues (“intercellular” water); hydration water, especially in cellular protoplasm (“constitutional” water), is the main constituent of tissue colloids, and its loss is sometimes equivalent to the death of the given tissue. At the same time, it is certain that there is no “freely” circulating water in the organism, since even the most fluid pathological transudates are colloidal solutions that also contain a certain amount of salts. By its origin, the water participating in obliteration can be of various natures. The greater part of it is absorbed from the intestine and enters the blood, lymph, and tissues—the so-called alimentary water. Furthermore, in the process of metabolism, and primarily during oxidative processes (for example, the oxidation of carbohydrates and fats), so-called oxidation water is formed in the organism itself; water is also formed as a result of neutralization reactions. Finally, tissue and blood proteins are capable, under the influence of hydrostatic and electroosmotic forces, of swelling (Entquellung of German authors), releasing their constitutional water. At the present time, all the guiding forces and pathways through which intermediary water metabolism is carried out are still far from clear. Thus, water taken by mouth is not absorbed in the stomach, but its presence in the stomach is already sufficient to cause a vasomotor skin reaction and an increase in skin perspiration. With the passage of the same water into the intestine, its absorption begins, the speed of which is determined by the ionic and molecular composition of the ingested fluid. Furthermore, the alimentary water absorbed from the intestine does not immediately enter the general bloodstream and lymph, but is partially retained in the liver, and the degree of this retention depends both on the nature of the solution in the composition of which the water is absorbed (water per se, saline or sugar, hyper- or hypotonic solutions) and on the state of the liver parenchyma and its circulatory system. From a physiological standpoint, it remains unclear whether this “sluice-like” role of the liver for water is due to the specific structure of its venous system (easy permeability of its capillaries, presence of a sphincter or venous valves at the exit of the hepatic veins from the liver) or whether the cause is the exceptional looseness of the liver parenchyma, the ability of its cellular elements to swell, and finally the presence of a huge number of tissue clefts in the liver. A significant part of the water absorbed from the intestine, especially after copious drinking, having passed through the liver, enters the circulatory loop. However, the insignificance and short duration of hydremia (see) even after copious water loads (1–1.5 l) indicate that almost all the reabsorbed water is rapidly removed from the blood. By means of weighing and accounting for diuresis, one can easily verify that the bulk of the drunk water passes into the tissues and lymph and then is only gradually partly excreted in the urine. It is noteworthy that pure water is removed from the blood more easily, respectively causes less hydremia, than an isotonic sodium chloride solution. The further movement of water through the vascular wall and further through semipermeable cell membranes is carried out mainly by three forces: the hydrostatic pressure existing in the vascular bed, the osmotic pressure on both sides of the capillary wall, and the oncotic pressure of blood colloids and tissue fluid. It is quite obvious that all attempts to explain the exit of water from the circulatory system solely by its filtration under pressure (Ludwig) or by the influence of osmotic forces (Starling) have proved futile. Moreover, it should be taken into account that the aforementioned three guiding forces of water metabolism have their point of application in the capillary endothelium, respectively cell membranes, which certainly do not completely obey all those regularities that were obtained in model experiments in vitro (Loeb). While lymph, which is a filtrate of blood plasma, contains a number of molecular particles corresponding to the composition of the blood, cerebrospinal fluid, peritoneal serous fluid, and, under pathological conditions, edema fluid originating from the same blood plasma, have a quantitative salt composition very different from blood plasma. Physical-chemical biology provides explanations for these deviations, teaching that the active reaction of the medium on both sides of the membrane, as well as the qualitative and quantitative composition of electrolytes, determine the permeability of the aforementioned “barriers” (blood-brain, peritoneal, pleural, etc.) for a number of ions and non-electrolytes, and along with them for their solvent—water. Along with this, it is also interesting to note that in most organs and systems, direct water exchange between the blood and parenchymal cells is generally impossible, since everywhere between them there is a greater or lesser amount of connective tissue. The latter plays the role of not merely a supporting tissue: the colloids of its elements possess an exceptional capacity for the adsorption of acid valencies (histochemically they are acidophilic), the consequence of which is a rapid influx of fluid with positively charged hydrogen ions into the intercellular substance and its swelling. Moreover, recent studies (Hulse, Hueck) have called into question the very presence of tissue fluid in intercellular spaces. From this point of view, the colloids of the intercellular substance (with the help of the so-called “tissue current”) themselves carry out the transport of nutrients to cellular elements and the return of dissolved metabolic products back into the blood. In other words, connective tissue is a most important effective physicochemical factor in water metabolism, extremely sensitive to changes in the ion content in the surrounding tissues (blood or organs) and in turn influencing this medium (see also Hydrophilia, hydrophilicity). Numerous observations on the resistance of erythrocytes in neutral salt solutions and on tissue cultures indicate that the swelling and shrinking of cells depend primarily on the osmotic pressure of their surrounding environment. However, not all the water that makes up the cell participates in this exchange with the environment, but only that mobile part of it which plays the role of solvent; constitutional water, as indicated, is given up by the protoplasm with great difficulty and only before the destruction of the cell structure. Therefore, the degree of cell swelling is not in direct proportion to the concentration of the surrounding solution (respectively tissue juices). In addition, complex adsorption processes and changes in surface tension take place on the surface of the cell itself, determining the permeability of cell membranes or their boundary layers. These membranes can themselves favor or hinder the realization of osmotic processes in the cell and the exchange of water in it. The deciphering of such influences is currently difficult if only because all those physicochemical phases and states in which the cell protoplasm, and in particular its boundary layer, is located are little known, as well as by what forces water is held by cells. Submitting to osmotic influences, cellular protoplasm, which itself carries a certain electrical charge but is not capable of diffusion, participates in so-called anomalous osmosis, i.e., creates an unequal concentration in the surrounding fluid and inside the cell for a number of anions (Cl⁻, HCO₃⁻). In other words, the distribution of these ions on both sides of the cell membrane—between the tissue fluid and the cell contents—occurs unevenly according to the laws of the so-called Donnan equilibrium (see Donnan equilibrium). The water balance of the organism is composed of water introduced with food or formed as a result of the vital activity of organs and tissues, on the one hand, and water excreted by means of urination and perspiration (through the lungs, skin), on the other. The introduction of water into the body is regulated by a special physiological sensation—thirst, the degree of which is primarily determined by the content of osmotically active substances (respectively molecular concentration) in the blood and tissue fluids (see Thirst). As for the excretion of water, under physiological conditions it is in strict accordance with the amount of water introduced. With copious drinking, this regulation is carried out rapidly (mainly by the kidneys). The ensuing diuresis is the result of those shifts that occur in the water-salt economy of the organism. These shifts are sometimes elusive and do not always relate to changes in blood composition; thus, the degree of urination is not in direct dependence on blood dilution. Along with the kidneys, however, extrarenal water excretion can also exert a substantial influence on the water economy of the organism, which occurs chiefly at high external temperatures (climate, conditions, work in hot shops) or in fever. The evaporation of water from the comparatively large body surface plays the role of a thermoregulator, contributing under appropriate conditions to maintaining body temperature at a certain level. At the same time, it must be emphasized that with an excess of water in the organism, extrarenal excretion increases sharply even at normal ambient temperatures, and under pathological conditions, for example in hyperthyroidism (especially experimental), the role of extrarenal excretion in the water balance rises sharply, reaching up to 50% of all excreted water. However, already under normal conditions, the amount of water removed extrarenally can reach up to 800 - 900 cm3 per day in humans. Of this amount, 500-600 cm3 is excreted by means of cutaneous perspiration or sweating, and the remaining amount in the form of water vapor of expired air. Incidentally, the qualitative distinction made regarding water balance between perspiration and sweating is little justified, since the former is carried out by the same sweat glands and is simply invisible to the unaided eye. Water loss through the skin affords more extensive possibilities for regulating the water economy than respiration, since cutaneous perspiration is in direct dependence on the innervation apparatus, which is extremely sensitive to temperature fluctuations, labile, and amenable to fine regulation. The amount of water in expired air, which has a rather constant temperature and consequently a stable water vapor pressure, is subject to significantly smaller fluctuations. The ability to maintain the water economy at a certain level, resp. to equalize the water balance, under physiological conditions can be studied by means of the so-called "water test". Upon the administration of 1,000 cm3 of water, the latter is excreted in excess within 3--4 hours, with 80-90% being excreted via the renal pathway in adults and 70-80% in children (see also metabolism in children and Kidneys, - functional diagnostics). The results of the water test are, however, in the closest dependence on preliminary nutrition and in particular on the preliminary saturation of tissues with water and salts. Thus, in rabbits fed "dry" food (e.g., oats), the water test yields results significantly slower than in those fed carrots rich in water (Siebeck). All this applies to an even greater degree to humans consuming an extremely diverse amount of liquid and NaCl in their food (from 5 to 20 g per day). Among the ions Na+ and Cl- included in its composition, the former undoubtedly possesses a hydropigenic property, since other salts containing Na+ cations also contribute to water retention (NaHCO3, Na2HPO4). Strangely enough, the opposite (diuretic) action is exerted by K and Ca cations, which also carry a positive charge, their salts, and foodstuffs containing them (potatoes, fruits). Consequently, the character of preliminary nutrition, not only by its water content but also by its mineral composition, has a decisive influence on the course of water metabolism. All this merely testifies that water metabolism should not be regarded as an independently proceeding process, in particular dissociated from mineral metabolism. Sometimes in experiment (demineralization, artificial polydipsia, overheating), as well as in pathological conditions, one can observe the development of a prolonged negative water balance; in such cases, dehydration occurs (see), accompanied by severe phenomena up to symptoms of acute intoxication. An equally severe picture is presented by cases with a positive water balance; usually these are states that have ensued following a sharp and rapid retention of significant quantities of water in the organism. Similar conditions can be created by the introduction of large amounts of liquid followed by the injection of pituitrin (Vovsi, Itsekson, and Vagon). The picture of "water intoxication" observed in this case (Rowntree) is sometimes characterized by extremely formidable symptoms (tremor, anxiety, pallor, nausea, etc.). Under physiological conditions, however, the equalization of the water balance occurs continuously and extremely rapidly in the organism, creating that relative stability of the water economy which is a prerequisite for the normal course of all processes of intermediary metabolism. Such regulation is accomplished in the first place, of course, centrally, which has been confirmed experimentally by means of the so-called "water" and "salt" punctures. Similarly to Claude Bernard's "sugar" puncture, which is accompanied alongside glycosuria also by polyuria, Meyer and Jungmann, as well as Leschke (Meyer, Jungmann, Leschke) showed that a puncture in certain areas of the tuber cinereum and diencephalon entails enhanced urination. It can be accompanied by a simultaneous increased excretion of common salt ("salt" puncture) or be limited to the excretion of liquid urine poor in salt ("water" puncture). Centripetal impulses are received by these centers apparently either directly from the tissues (see Thirst) or via the hormonal apparatus, the influence of which on the function of water-regulating centers is exceptionally great (see below). Of the internal secretion glands, the posterior lobe of the pituitary gland, the thyroid gland, and the pancreas play a decisive role in the regulation of the body's water economy. Extracts of the posterior lobe of the pituitary gland (pituitrin and its analogues) possess, as is known, a sharp antidiuretic effect, and the question remains unclear whether this effect is caused by a special hormone or whether it is a question of one of the properties of a single pituitary incret (see Pituitary gland). The antidiuretic action of pituitrin is particularly prominently manifested in abundant diuresis: after a water load, after extirpation of the pituitary gland in dogs, or in diabetes insipidus (see Diabetes insipidus). In the blood after pituitrin injection, as a rule, a more prolonged dilution of it is noted, and in the tissues, an accumulation of liquid (resp. an increase in body weight). Meyer and Meyer-Bisch (Meyer, Meyer-Bisch) also showed that the usually observed increased flow of lymph into the thoracic duct from the liver upon the administration of so-called lymphagoga of the first order (see Lymph) does not occur if pituitrin is injected simultaneously with these substances. In the latter case, a small amount of thick lymph flows from the thoracic duct fistula. Along with this, there are numerous observations that even in the kidneys themselves, the action of pituitrin is manifested by a transient, yet sharp constriction of renal vessels and a decrease in renal blood circulation. Therefore, many investigators are inclined to connect the drop in diuresis with the influence of pituitrin directly on the kidneys. In any case, the antidiuretic influence of pituitrin is not self-sufficient and is realized through the central nervous system, and not by direct action on effector organs, because upon sectioning the splanchnic nerves, upon destruction of the cinereal tubercles, or finally upon exclusion of the cerebral cortex, this action either disappears or sharply diminishes. The mechanism of action and point of application of the thyroid hormone, which also participates in water or rather in water-salt metabolism, are completely different. Thyroid substance (thyroidin and its analogues) as well as its hormone thyroxine possess a clearly expressed dehydrating action. With prolonged internal administration of thyroidin, a drop in body weight is usually observed with an almost normal diuresis. This weight loss is caused more by an increase in the extrarenal excretion of water than by an enhancement of urination. The dehydrating action of thyroxine is especially effective in the presence of preliminary retention of water and common salt in the tissues, in particular in myxedema, in edema in decompensated cardiac patients, in nephrosis, in obesity. Due to this, there are all grounds to classify the hormone of the thyroid gland among water- and salt-eliminating substances with a point of application in the tissues. In particular, the weight loss observed with thyroidin intake in the obese is accompanied not so much by an increase in their basal metabolism as by the removal of a significant amount of salts and water from the organism. The increts of the insular apparatus of the pancreas also contribute to water retention in the organism. The retaining influence of insulin, in contrast to the function of the pituitary gland, is manifested, however, only in those cases when a certain amount of Na salts and carbohydrates is introduced into the organism along with water. Apparently, under the influence of insulin, the intensification of the gluconeogenesis process is accompanied by water retention in the liver. Likewise, the increased administration of sodium salts, especially those reacting alkaline (bicarbonates, dibasic phosphates), already in itself promotes water retention in the tissues and even favors the formation of edema. The simultaneous administration of insulin only accelerates and intensifies this process. Pathology of water metabolism. Under pathological conditions, disorders of the water economy take place in a wide variety of diseases. Schematically, all these deviations can be reduced to conditions or symptoms with a positive or negative water balance. A negative balance is observed chiefly in childhood in so-called exicosis (see), atrophies, in acute diarrhea (in particular in cholera and infant dyspepsia), in cachexias, in the initial period of starvation, in overheating, and in diaphoretic procedures. In all these cases, the cause of the negative water balance is predominantly extra-renal water excretion. Excessive fluid loss by the organism also takes place in polyurias of various origins, among which diabetes mellitus and diabetes insipidus must be placed in the first rank. In all these diseases, the elasticity and vital turgor fall, first of all, in those tissues that serve as the body's water depot, such as connective and muscular tissue; along with them, the blood is also dehydrated. The value of the dry residue of the blood (the amount of proteins and salts) reaches high figures. The plasma protein content reaches up to 10%, and sodium chloride up to 650 mg%. Correspondingly, the freezing point of the blood also decreases. The sharp weight losses observed in these conditions are caused primarily by the loss of a significant amount of tissue intercellular water. However, tissue dehydration does not pass without consequence for the colloids of cellular protoplasm, especially of parenchymatous organs, the consequence of which is the enhanced protein breakdown usually observed in the second period of dehydration, with the excretion of excessive amounts of nitrogen in the urine (negative nitrogen balance). Continued urine secretion at a high percentage of sodium chloride and nitrogen in the urine creates the prerequisites for the occurrence of the main symptom observed in a negative water balance—thirst. In cases with a more prolonged or sharply pronounced loss of water, motor restlessness, a feeling of heaviness in the head, a sensation of heat, pain in the extremities, and sometimes psychic excitation are added to the thirst. The described signs of intoxication hardly pertain to water loss alone, but are rather close to the very characteristic picture described by Fischler under the name of meat intoxication and observed when protein cleavage products enter the blood. It is interesting to note that all the mentioned symptoms can also occur with the accumulation of significant amounts of fluid inside the body, i.e., with a seemingly positive water balance, for example, during the increase of ascites in patients with liver cirrhosis. In such cases, these phenomena are pathogenetically caused by the same tissue dehydration, resp. blood concentration, taking place here just as in significant water losses. Polyurias, which as a rule lead to a negative water balance, can stem from the most diverse causes. The most frequent and well-known are polyurias in diabetes mellitus and insipidus, at the beginning of renal insufficiency, in so-called primary polydipsia, and others (see Polyuria, Nephritis, Nephrosclerosis, Polydipsia). An indicator of the occurrence of a positive water balance and a sign of water retention in the organism would naturally be considered oliguria. However, experience teaches that in so-called primary oligurias, caused most often by nervous or endocrine influences (see Oliguria), the water balance is equalized by extra-renal water excretion, and retention of it thus does not ensue. Therefore, conditions characterizing a true positive balance include only those that are accompanied by a rapid increase in the general weight of the patient with or without oliguria. Water retention in the organs is most pronounced during the period of development or increase of visible or latent edema. The latter arise predominantly as a result of a disturbance of one or more of the enumerated factors regulating intermediate water metabolism in the organism. Thus, congestive edemas are most often associated with an increase in hydrostatic pressure in the venous system and a concomitant drop in the permeability of capillary endothelium to water, caused by its oxygen starvation (Landis). Renal edemas, especially nephrotic ones, evidently have a different genesis at their base and are associated primarily with a decrease in the amount of proteins in plasma, a change in the dispersion of their particles, a shift in the albumin-globulin coefficient, and consequently a drop in the colloid-osmotic pressure of proteins, i.e., with a decrease in the force with which proteins retain their water. Finally, shifts in the active reaction of tissues, the accumulation in them of certain cations and anions (Na+, HCO3-), also entail significant water retention in tissues (inflammatory, starvation, alimentary, salt edemas). (For details, see Edema.) A predominantly tissue character is also evidently borne by the significant water retention observed in the initial period of various infectious diseases (for example, in croupous pneumonia). Leyden showed on extensive material that water loss in the febrile period is 2 times less than in the postcritical one. The assumption that the decisive role in this retention belongs to fever is hardly justified, since a similar picture is observed also after tuberculinization. It is only certain that water retention in these cases proceeds parallelly with, and perhaps is even caused by, the sharp retention of sodium chloride and the enhancement of protein breakdown observed in these states. On the pathological anatomy of changes in disorders of water metabolism, see Vacuolar degeneration, Edematous disease, Edema.
M. Vovsi. IX. Metabolism in children. Metabolism and energy exchange in children, especially of early age, compared with the metabolism of adults proceeds in many respects quite peculiarly. To obtain sufficiently accurate results in studying metabolism in children, it is necessary, besides punctually observing the usual general rules for investigating metabolism in adults, to take into account the following main points: 1) the studied group of children should be as homogeneous as possible regarding health status, constitution, age, and feeding method; 2) observation conditions in all compared cases must be completely identical; 3) the duration of observation must be at least 5-7 days; the preparatory period with loading the child with the basic diet must be sufficiently long (3-4 days); 4) it is necessary to take into account the influence of the season, lighting, richness of the solar spectrum in ultraviolet rays and other meteorological factors; 5) special attention must be paid to the careful collection of urine and stool, which in early age children presents particular difficulties and requires a special methodology. For this purpose, many different methods have been proposed, of which the best should be considered the Bendix-Finkelstein method (Bendix, Finkelstein) and the Benjamin method (Benjamin). The position of the child and the urinal when collecting the daily amount of urine - see vol. XIX (art. 107, Fig. 4). The stool is collected on a rubber sheet. To study gas exchange in children, special chambers are available (with the apparatus of Benedict and Knipping) (Benedict, Knipping). For blood research, one has to use mainly micromethods. Otherwise, the study of various types of metabolism in children is usually carried out using the same methods as in adults. Energy metabolism (basal metabolism). The energy received by the child and estimated by the calorific value of the food he takes is expended on maintaining life on an empty stomach in a state of rest (basal metabolism), on growth and increase in body mass, and on muscular activity. Helmreich gives the following approximate distribution of energy in a child and an adult with moderate food: Table 26. Energy distribution. For basal metabolism ...... For growth and deposition of substance ............... For specifically dynamic action ............ For work for moving the body............... For losses by excreta..... In child (in %) In adult (in %) 15 0-5 15 5-10. The basal metabolism in a child depends not only on his living mass, but also on the individually varying intensity of cell metabolism in individual subjects. In the same subject, basal metabolism is distinguished by surprising constancy and fluctuates within about 10%. Between the value of basal metabolism in a child and his age, weight, and body surface, there is a known dependence. To determine the body surface in an infant, the Lissauer formula is suitable: S (body surface) = 10.3 3√weight2; for older children, the constant 10.3 must be replaced by others, varying depending on the child's weight; the value of the constant for boys ranges from 10 to 11.5, for girls from 10.1 to 11.1 (Talbot). Lissauer's formula is suitable mainly for normal children. More accurate is the du Bois formula: body surface = weight 0.425 × height 0.725 × 71.84. Benedict and Talbot for calculating basal metabolism in newborns (weighing up to 6 kg) propose the following formula: daily calorie production = 12.65 × length (in cm) × 3√weight2 (in kg). In newborn children, basal metabolism is very low and approximately proportional to their weight. According to studies by a number of authors (Benedict, Talbot, Bailey, Murlin), daily energy expenditure in a newborn with a weight of 3 1/2 kg is approximately 146 calories, or 42 calories per 1 kg of weight; completely identical relationships between energy expenditure and weight are obtained in children of the first day of life with lower and higher initial weight; by the 2nd-3rd day of life, energy expenditure per 1 kg of weight rises to 48 calories and, increasing gradually thereafter, reaches maximum figures by 1 1/2 years (50-60 calories per 1 kg), and then begins to decrease. In boys aged 2 to 3 years it drops to 52 calories, by 6-7 years to 42 calories, by 10-11 years to 38 calories, and by 12-13 years to 34 calories per 1 kg of weight (Benedict). Thus, it can be considered indisputable that basal metabolism, calculated per unit of weight, is much higher at an early age than in older children. The difference between basal metabolism in boys and girls begins to appear at approximately 1-1 1/2 years; from this age until puberty, energy expenditure in girls is somewhat less than in boys, then the girls' curve overtakes the boys' curve, and only with the end of puberty in males does the predominance of metabolism restore again. This sexual difference, it must be thought, depends on the smaller amount of energetically active tissue in girls, but on the other hand, a larger amount of adipose tissue. Well-nourished children, whose tissues are rich in fat and water, give lower figures of basal metabolism than lean children. During puberty, in some cases apparently an increase in basal metabolism occurs. Age-related changes in basal metabolism in children, calculated not for age and unit of weight, but for unit of body surface, are characterized by the following figures: in a newborn about 612 calories per 1 m2, by the end of the year - about 1,100, by 10 years - 1,000, and by 13 years - 950. The respiratory quotient (see) in the newborn period undergoes the following changes: on the first day 0.80, by the third day it drops to 0.73, and then by the 5th-6th day it reaches 0.81-0.82. The "specifically dynamic action" of food in early age children is somewhat different than in older children and adults. According to Helmreich's studies, the introduction of milk with food in small children almost does not cause an increase in basal metabolism, whereas in older children the increase in calorie expenditure is quite significant and reaches approximately 10%. During puberty, according to Göttche, the specifically dynamic action in 75% of cases was strongly reduced and in the majority of cases (50%) was accompanied by an increase in basal metabolism. The regularity of this puberty reaction (Pubertätsreaktion), as Göttche calls it, cannot be considered finally proven. There is no doubt that the state of energy metabolism in a growing organism is under great influence from the endocrine apparatus. Nitrogen metabolism. Food proteins are absorbed in children predominantly in the form of amino acids and partly in the form of polypeptides. The passage of native proteins through the normal intestinal wall is apparently possible only in newborn children, when certain protein bodies can directly penetrate through the intact mucous membrane. Regarding the further fate in the child's organism of the products of protein cleavage absorbed in the intestine, very little is known. The very process of protein absorption in the intestine, especially in early age children, occurs very perfectly and is almost independent of the child's age and the method of his feeding; in breastfed children, from 70% to 90% (on average about 80%) of the introduced proteins are absorbed, in artificially fed children only slightly less. Increased introduction of proteins with food, as studies by Finkelstein and Jonas show, does not worsen the process of their absorption. As for the assimilation of absorbed amino acids and polypeptides, according to older observations (Langstein, Meyer, Rietschel, and others), the percentage of utilized food nitrogen varies depending on the child's age and feeding method, whereas the amount of protein retained in the organism depends on the child's age and is almost independent of the amount of food proteins. However, newer studies by Rominger and Meyer (Rominger, Meyer H.) show that nitrogen retention in the organism of a healthy infant also largely depends on the amount of administered protein; the child's organism, in contrast to the adult organism, has a pronounced ability for increased protein accumulation, thanks to which the tissues of an artificially fed child are somewhat richer in proteins than the tissues of a child receiving only breast milk. Somewhat peculiar relations are noted in newborn children, in whom, according to observations by Langstein, Niemann, and Birk (Niemann, Birk), a negative nitrogen balance is noted, which quickly and sufficiently perfectly equalizes with natural feeding with colostrum and significantly lingers with artificial feeding. The ratio between the amount of protein in food and the amount of nitrogen excreted with feces remains more or less constant; with normal protein loading in a child, about 10% of the introduced proteins are excreted with the stool.
According to Pintozzi, the amount of nitrogen in the feces can serve as a measure of absorbed nitrogen, since only a comparatively small part of the stool nitrogen is attributable to the nitrogen of digestive juices poured into the gastrointestinal tract, and a completely insignificant amount is due to the end products of protein metabolism excreted by the intestine. The main mass of the latter, as in the adult, is excreted in the urine, but it is distributed in it in a completely peculiar manner. The total amount of urinary nitrogen is relatively very high in newborns, then it decreases somewhat, only to begin to increase again approximately parallel to the amount of proteins introduced with food. In infants, regardless of the method of feeding, about 40-60% of the nitrogen introduced with food is excreted again in the urine. The daily amount of urinary nitrogen in a newborn is on average about 0.5 g, by the end of the first year of life 1.5 g, at the age of 6-7 years 7.5 g, and by the end of childhood about 10 g, which, when recalculated per 1 kg of body weight, gives: 0.12-0.16 g in an infant, 0.45 g in a 6-7 year old child, and 0.31 g in children of puberty. Some general idea of the distribution of nitrogen in the urine of an infant can be given by the following example of Kammerer: out of 5.52 g of the total amount of nitrogen in the urine of a child under observation, 4.8 g was accounted for by urea, 0.29 g by ammonia, 0.065 g by uric acid, and 0.013 g by purine bases. According to the latter author, in a breastfed child, urea accounts for about 75-80% of the total urinary nitrogen, in artificially fed children for about 84%, and in older children from 90% to 94%; the age curve of urea excretion undergoes approximately the same fluctuations as the curve of the total amount of nitrogen. Uric acid during the newborn period is excreted approximately 5 times more than in an adult, and twice as much as in older children, in whom from 0.018 to 0.027 g per die is excreted per 1 kg of weight; this value changes little depending on the age of the child, but largely depends on the food he consumes (Goppoert). Purine bases are excreted parallel to the amount of uric acid (Niemann), but in the urine of newborns they are contained only in traces. Due to urinary ammonia, children excrete more nitrogen than adults; thus, in newborns this value constitutes 9.5-19.5% of the total amount of urinary nitrogen (Reuss, Keller), in infancy 8%, by 3-4 years 7%, and at 13-14 years 6%. The percentage ratio of ammonia nitrogen to the total amount of nitrogen, i.e., the so-called ammonia coefficient of urine, fluctuates in children within wide limits (normally from 3 to 10), changing significantly depending on the state of the acid-base equilibrium in the body, increasing in states of acidosis and decreasing with shifts towards alkalosis, and thus is a rather sensitive indicator of the correct course of general metabolism. Amino acid nitrogen gives high figures in the first days of life; it is especially abundant in the urine of premature infants (up to 9.5-25% according to Gebel); in the infant period this value ranges from 2.7% to 4%, i.e., 2-2.5 times more than in older children, in whom only about 1.6-1.8% of the total urinary nitrogen is excreted as amino acids. The excretion of the end products of nitrogen metabolism in the urine, apart from the child's age, is also affected by his constitutional features (Matorina, Mats, Tur). The distribution of nitrogen in the urine depends on the state of the oxidative capacity of the child's body; as a result of its insufficiency in the newborn, there is an increased excretion in the urine of a large amount of products of incomplete nitrogen metabolism, which indicates the unadaptability of the body to the complete breakdown of proteins and, consequently, the impossibility of sufficiently perfect utilization of food proteins. The energy of oxidative processes increases with age, reaches optimal conditions by 5-6 years, and then decreases again towards puberty. These features of nitrogen metabolism, as well as the fundamental property of the child's body—the energetic course of growth processes, possible only in the presence of a large amount of plastic material—make it necessary to introduce relatively large amounts of proteins into the diet of children. In artificially fed children, along with a large retention of introduced nitrogen in the body, an increased excretion of it in the urine is also noted (Rominger and Meyer), and consequently, the dietary regimen of such children must be richer in proteins than for children fed exclusively on breast milk. Connected with the peculiarity of intermediate protein metabolism in children is the increased excretion of organic acids in their urine: in premature infants and newborns per day 10.1 cm3 of normal acid, in infants and preschool children 12.5 cm3, whereas in adults only 8.2 cm3 per 1 kg of weight (Hottinger). According to the majority of authors, proteins should cover approximately 10% to 15% of the total number of calories in children. The protein requirement in a child of the first year of life is on average about 2.5 g per 1 kg of weight (in breastfed infants from 1.5 g to 2 g, in bottle-fed infants from 3 g to 4 g), at the age from 1.5 to 5 years it is somewhat increased and on average equals 3-3.5 g, by 8-10 years it drops to 2.5 g, and by 12-15 years to 1.5-2 g; in the presence of certain indications, the amount of introduced proteins can be both increased and decreased within fairly wide limits without disrupting the normal course of metabolic processes and the correctness of general development. According to many German authors, the child's requirement for proteins is significantly less. For the correct development of the child's body, the absolute amount of introduced proteins is not as important as their quality, determined by the content and nature of amino acids. Among the vital amino acids for the child are tryptophan, lysine, tyrosine, and cystine; among the less important, but in some cases absolutely necessary ones, are arginine, histidine, asparagine, and glutamic acid. Insufficient introduction of these amino acids inevitably leads to the development of dystrophy, and their complete absence is incompatible with life. The requirement for tryptophan in infancy is 0.058-0.1, in older children 0.055-0.063 per 1 kg of weight. Practically, it is sufficient that about 50% of the introduced proteins are of animal origin. For the proper assimilation of proteins, a certain ratio (correlation) with other main food ingredients—fats, carbohydrates, and water—is necessary. An excess of introduced proteins does not improve, and sometimes apparently even worsens, the utilization of nitrogen, and leads to a state of relative acidosis; excessive introduction of fats, according to some authors (Freund, Neumann), worsens the absorption and retention of nitrogen, according to others (Pintozzi) has no effect; carbohydrates, according to Keller, improve the nitrogen balance, and according to Pintozzi, somewhat impair protein absorption and reduce the requirement for them. A moderate predominance of alkaline equivalents over acidic ones in food improves protein assimilation. Insufficient water intake, due to the pronounced specific dynamic action of proteins, can lead to hyperthermia (Eiweissfieber). The specific dynamic action of proteins increases with the child's age, i.e., with an increase in his body surface; in young children it is less than in older ones, and in the latter less than in adults (Helmreich, A. Seifert); in boys it is greater than in girls. The maximum specific dynamic action of proteins is noted 3 hours after a meal and fluctuates between 9.2% and 31.4% of the fasting figure. Fat metabolism in children also differs by a certain peculiarity. It can be considered established that even in young children, fat splitting begins already in the stomach under the influence of gastric juice lipase; an essential significance for fat digestion in an infant is the presence of a large amount of lipase in human milk. The process of splitting and the mechanism of fat absorption in children basically proceed in the same way as in adults. According to Orgler, Keller, E. and F. Müller, and recent data by Potter, in a breastfed child about 98%, in a bottle-fed child about 95%, and in older children from 95% to 97% of the fats introduced with food are absorbed. The greater part of the fats split and absorbed in the intestine, entering the general bloodstream via the portal vein and liver, leads to the appearance of so-called alimentary hyperlipemia; the latter increases throughout the entire digestive process, reaching a maximum with cow's milk after 3 hours, with human milk somewhat later, and persists in the first case for about 5 hours and in the second for about 9 hours. The blood serum of fasting children contains 170-200 mg% phosphatides, 140-170 mg% cholesterol, and about 400 mg% fatty acids. In the blood of a newborn, lipoids are significantly less, but already by 1-1.5 months their amount increases by 50-75% and then slowly but gradually increases during the first years of life. At the age of 3 to 11 years, the total amount of lipoids is on average 700 mg%, which almost corresponds to their content in an adult. The method of feeding the child does not noticeably affect the amount of blood lipoids.
Unused fats by the organism in an amount of about 5-10% (according to Freund's observations up to 14-18%) are excreted with the stool in the form of neutral fat, water-insoluble free fatty acids, alkaline (water-soluble) and alkaline-earth soaps. Their distribution in the feces of infants and toddlers is somewhat different. In a normal infant, the stool fats contain 10-30% neutral fat, 10% free fatty acids, 40% alkaline soaps, 20% alkaline-earth soaps, 0.8% cholesterol, and an insignificant amount of lecithin; in an artificially fed infant, there is about 35% neutral fat, up to 40% free fatty acids, 10% alkaline soaps, and 13% alkaline-earth soaps. In an infant, more cholesterol is excreted with the stool than is introduced with food, which indicates the possibility of its synthesis in the growing organism; however, Knauer considers this assumption unlikely. The distribution of fat in the stool changes depending on the composition of the food and the state of intestinal peristalsis. The absorbed fats are partly burned in the organism and thus serve as a source of energy generation, and partly, being deposited in the tissues, mainly in the subcutaneous tissue and mesentery, form a reserve fat depot. The fat of an infant is poor in liquid oleic acid; with age, its amount gradually increases. A growing organism can develop for a relatively long time without fats on proteins and carbohydrates alone, and the latter can be the starting material for the formation of fat deposited in the tissues. However, this possibility of replacing fats with isodynamic amounts of carbohydrates testifies only to the great adaptability of the child's organism, but does not give the right to the conclusion made by some authors (Pirquet, Greer) that fats are not absolutely necessary for the organism. Firstly, the fat formed in the organism from carbohydrates differs in its composition from the fat under normal nutrition, and secondly, with a fat-free, but otherwise calorically sufficient diet, sooner or later the child develops phenomena of avitaminosis (Bloch, Wagner), xerophthalmia appears, and the immune forces of the organism drop sharply (Weigert). The normal requirement for fats in infancy is relatively large, usually ranging from 3 to 5 g, on average equal to 4 g per 1 kg of weight, after a year - 3.5 g, from 6 to 12 years - 3 g, and during puberty - 2-2.5 g. If, on the one hand, the child's organism apparently can develop correctly even with a significantly smaller amount of administered fats, then, on the other hand, their amount in the presence of certain indications can be significantly increased (e.g., up to 6 g or more per 1 kg of weight in infancy). However, the excessive administration of fats is not indifferent to the organism and easily leads to the development of a state of true acidosis. The requirement for fats is determined not only by their quantity, but also by their quality; the nutritional value of fats depends on the content of lipoids and vitamins in them, which must be especially taken into account when feeding young children. The correct course of fat metabolism is possible only with the proper correlation of fats with other nutritional principles; in an infant, up to 50% of all introduced calories should be covered by fats, and in older children only 25-30%. Carbohydrate metabolism. The metabolism of carbohydrates in a child, obeying in general the basic laws regulating it in an adult, differs by a number of characteristic features. The exclusion of carbohydrates from food causes a drop in body temperature in a child; this fact confirms the immense importance of carbohydrates for heat production and thermoregulation in the child's organism. The question of the possibility of increasing body temperature in children under the influence of the excessive introduction of sugar cannot yet be considered finally resolved. Carbohydrates are absorbed mainly in the form of monosaccharides (glucose, levulose, galactose), although the possibility of the absorption of dextrins is not excluded. In the blood of healthy infants, the amount of sugar on an empty stomach ranges from 0.07% to 0.09%, in older children from 0.08% to 0.1%, and finally in children 12-14 years old from 0.09% to 0.12%. During the period of digestion, the amount of sugar in the blood rises to 0.16-0.2%; this hyperglycemia is quickly smoothed out, since part of the sugar is oxidized, being used for purely dynamic purposes, part is deposited mainly in the liver and partly in the muscles in the form of glycogen, and finally part is used for the formation of fat. The ability of the child's organism to assimilate carbohydrates introduced with food has a certain limit; if this assimilation limit is exceeded and the amount of sugar in the blood increases more or less steadily to 0.18-0.2%, then the organism corrects the disturbed carbohydrate balance by excreting the excess sugar in the urine. The child's tolerance to carbohydrates is subject to significant individual variations; it depends on the age of the child and the constitutional features of his organism, it is not the same for different carbohydrates and is generally much greater than that of an adult. In an infant, alimentary lactosuria occurs with the introduction of 3.5 - 4 g of milk sugar per 1 kg of weight; in an adult, a mere 1 g is sufficient for this. Cane sugar has the same assimilation limit as lactose; for grape sugar and maltose, the tolerance limit lies somewhat higher, and levulose has a particularly low assimilation limit. According to Aschenheim, alimentary glucosuria in infants occurs with the introduction of 4 g of galactose, 8-12 g of dextrose, 4-5 g of levulose, 6-8 g of lactose, and 6-8 g of sucrose per 1 kg of weight. These absolute figures are of very little value; they change greatly not only depending on the individual characteristics of the child and the state of his gastrointestinal tract, but also on the solvent medium in which these carbohydrates are introduced. The absorption of sugar with human milk occurs faster, and the glycemic curve rises earlier and falls steeper than with whole cow's milk. An aqueous solution of sugar causes a steep (maximum after 1/2-1 hour) rise and early extinction (after 2-3 hours) of the glycemic curve. As Styrikovich's studies show, the glycemic curve reflects, firstly, the state of activity of the gastrointestinal tract and liver (the first rise of the curve) and, secondly, the features of intermediary metabolism (the second half of the curve). Proteins, fats, and carbohydrates introduced simultaneously with sugar characteristically change the glycemic curve, which depends on the changes arising in this case on the part of intermediate metabolism. The peculiarity of glycemic reactions at an early age indicates the tension and mobility of carbohydrate metabolism in children and its close connection with the intermediate metabolism of proteins and fats. As one of the intermediate products of the intermediary metabolism of glucose in the organism, lactic acid is formed. The glycolytic capacity of the organism, as Warburg's studies show, is of great importance for the growth process. According to Gyorgy, Brehme, and Brahdy, the blood of children in the first quarter of the year contains an average of 18.7 mg% of lactic acid, in older infants - 13.8 mg%, whereas in adults only 10.2 mg%. Part of the carbohydrates that have escaped absorption undergoes fermentation under the influence of bacteria. The lower fatty acids arising during fermentation in the intestine in small quantities are useful and necessary for the organism: they stimulate intestinal peristalsis, improve nitrogen and mineral metabolism, and are thus, as Klotz says, catalysts of metabolism. Conversely, large quantities of these acids act destructively, promoting bacterial invasion into the upper parts of the intestine, suppress metabolism, and worsen assimilation. What part of the carbohydrates undergoes enzymatic cleavage and is absorbed and what part undergoes fermentation cannot be established precisely. In the feces of a healthy infant, carbohydrates (monosaccharides) are absent; with accelerated peristalsis, sugar and starch appear in the feces. Carbohydrates, like proteins, are absolutely necessary for the growing organism and cannot be completely replaced by an isodynamic amount of fats. Even short-term complete exclusion of them from food is tolerated by the organism with difficulty, especially if a large amount of proteins and fats is introduced at the same time (tendency to acidosis). The minimum of carbohydrates necessary for the child is apparently individually different and largely depends on the quantity and quality of other food ingredients received by the child. If this minimum of carbohydrates is absent in the child's food, then the organism strives to make up for it at the expense of protein cleavage. Insufficient introduction of carbohydrates leads to a violation of water metabolism as well. The daily requirement of an infant for carbohydrates is about 10-12 g per 1 kg of weight. At the age of 1 to 5 years, on average about 10 g per 1 kg of weight, and according to some authors even less; after 10 years, the daily requirement drops to 8-9 g. The requirement for carbohydrates in absolute figures is about 120-130 g by the end of the first year of life, 150-160 g at 3 years, about 200 g at 6 years, about 225-250 g by 10 years, and up to 350-450 g by 14-15 years. At first, all the child's needs are covered by milk sugar alone; from 5 months onwards, the need for polysaccharides appears.
The ratio with other basic food ingredients in infancy is most favorable when it corresponds to that in human milk, i.e., proteins relate to fats and to carbohydrates as 1 : 2.8 : 5.5, and fats to carbohydrates as 1 : 2. When the amount of protein is taken as 1, the ratios are as follows: 1 : 3.5 : 7. At a later age, these ratios may fluctuate within wider limits, but it is desirable that up to 35-60% of all calories are covered by carbohydrates. Mineral metabolism in the growing organism is even more complex and in many respects even less studied than the metabolism of organic substances. Salts play a very important and extremely diverse role in the economy of the intensively developing young organism; the prolonged absence of even one major ion is incompatible with life and the proper development of the child. Salts to a certain extent predetermine the correct course of water, nitrogen, fat, and carbohydrate metabolism; without them, the construction of new tissue and the renewal of old tissue dying off in the process of work cannot take place. A certain concentration of hydrogen ions is maintained by means of salts, with the violation of which the alkali-acid balance changes; the most insignificant violations of the latter adversely affect the normal course of all vital processes and are often dangerous to the child's life. The preservation of osmotic pressure, the normal state of colloids, the maintenance of a certain equilibrium in the state of excitability of the nervous system, and the normal enzymatic activity of the child's organism are in direct dependence on changes in mineral metabolism. Salts that participate in tissue building are especially important for the growing organism. If mineral substances are removed from the child's food, which is completely full-value in terms of its caloric content, first a delay in growth and then a drop in the weight curve occur. The absorption of salts introduced with food occurs mainly in the small intestines. The absorption of salts in the intestine and their retention in the organism differ somewhat depending on the age of the child and the method of feeding. This ability is already sufficiently well expressed in the newborn, who retains in the organism per day, according to Michels, 170-256 mg P2O5, 181-291 mg CaO, and 95 mg Cl. Long-term observations by Rominger and coworkers give the following average figures characterizing mineral metabolism in children of the first year of life: type of feeding, introduced per day, retained in absolute amount, percentage. The widespread view in the past that the retention of salts in a child's organism does not depend at all, or depends to a very insignificant extent, on the intake of salts into the organism, but is regulated solely by the needs of the organism itself, in particular its growth, can now be considered more or less refuted. From the figures given above by Rominger, it can be seen that in artificially fed children and children on mixed feeding, the absolute amount of salts retained in the organism is significantly greater than in children receiving only breast milk. In an artificially fed child, a particularly large amount of sodium and potassium salts is retained. The percentage of salt utilization in some cases apparently is somewhat lower in artificially fed children than in breastfed ones. However, the increased retention of mineral salts during artificial feeding does not lead to hypermineralization of tissues, since periods of increased salt retention are followed by periods of their increased excretion and perhaps even short periods of negative balance. The balance of individual salts shows significant fluctuations depending on the age of the child and his food, and partly may depend on the season. Part of the absorbed salts (Na, K, hydrochloric and phosphoric acids) is excreted by the kidneys and eliminated with urine, while another part (salts of Ca, Mg, and Fe), having passed through the blood, is excreted back into the intestine and eliminated from the organism with stool. The latter circumstance makes the study of mineral metabolism particularly difficult. The growing organism's need for calcium varies depending on the age of the child, the nature of the food he consumes, and the season. In healthy, naturally breastfed children of the first year of life, the daily requirement for CaO ranges from 0.13 to 0.21 g, averaging about 0.174 g (Orgler); a child of 6-7 years needs to be administered daily 0.3-0.5 g of CaO to ensure the normal growth of his bones, of which about 30% is retained in the organism (Herbst); a 14-year-old child retains about 0.45 g of CaO daily, which is possible with a daily intake of Ca with food in an amount of at least 1.35 g. E. and F. Müller give the following average figures for the required daily intake of calcium with food for older children: at the age of 6-8 years - 0.57-0.68 g, 10-12 years - 0.71-0.92 g, 13-15 years - 0.79-1.02 g CaO. The amount of calcium absorbed in the intestine cannot be calculated; the amount of calcium retained in the organism varies depending on the age and food of the child; with breastfeeding, according to Wang, up to 63% is retained, with artificial feeding up to 47.5%, and finally in older children - about 30% (Herbst). About 5-10% of the calcium introduced with food is excreted in the urine, the rest is eliminated with the stool. Blood serum contains about 10.5 mg% of calcium, of which 2 mg is in an ionized form, the rest accounts for calcium of organic compounds (about 25-30%) and non-dissociated salts (70-75%). Excessive administration of proteins and fats with food apparently somewhat impairs calcium metabolism. The growing organism's need for phosphorus during artificial feeding is significantly greater than during natural feeding; in the first case, 1-2 g of P2O5 must be administered daily with food, in the second - 0.2-0.3 g; 0.1-0.17 g (about 70%) is retained in an infant, and 0.23-0.5 g (about 30%) in an artificially fed child. In children 6-8 years old, the daily retention of P2O5 per 1 kg of weight is 0.04 g, at the age of 10-12 years - 0.034 g, and at 13-15 years - 0.031 g (E. and F. Müller), which is approximately about 32-35% of the total amount of phosphates administered with food. Excess introduced phosphorus compounds are excreted with urine and stool. In blood serum, phosphorus compounds are contained in the form of inorganic (on average about 5.4 mg% P2O5) and organic P; the decrease in phosphates in the blood in early spring and the increase in late summer depend on the richness of the solar spectrum in ultraviolet rays. Magnesium metabolism in children has been studied very little; 37.2% of MgO is retained in infants, 11.5% in artificially fed ones (Langstein, Meyer), and from 14% to 49% in older children (Herbst's observations on 4 children). According to Schloss's observations on rickets patients, there seems to be an antagonism between calcium and magnesium metabolism. Most of the unassimilated magnesium is excreted in the urine, and a smaller part by the large intestines. Magnesium reduces the excitability of the nervous system. Sodium and potassium. In infants (2-4 months), K2O - 0.17-0.19 g is retained per day, in artificially fed ones - 0.21-0.28 g; Na2O at the same age when fed with breast milk is retained in the amount of 0.21 g, in a child receiving cow's milk - 0.22-0.44 g (Langstein-Meyer); in older children, 2-12.2% of the total amount of K2O introduced with food is retained, and Na2O - 19.2-23%, which when converted to 1 kg of weight gives 0.002-0.009 K2O and 0.027-0.032 Na2O (Herbst). Unused alkalis in healthy children are excreted predominantly in the urine, while in sick children their excretion with stool increases significantly. Chlorine. Total blood contains 450-550 mg% of chlorides, plasma - 570-620 mg%; but these figures are subject to significant fluctuations depending on the state of the secretory capacity of the stomach. There are no exact data characterizing the metabolism of chlorides in children of different ages at the present time. In older children, the requirement does not exceed 1-2 g. The excretion of chlorine occurs almost exclusively with urine; the daily amount of urinary chlorides in infants is 0.1-0.14 g per 1 kg of weight, in the second year - 0.45, by 6 years - 0.66, and after 10 years - 0.5-0.57 (Shanyavsky). The amount of chlorides in the urine fluctuates depending on the constitutional characteristics of the child (Mats). Iron. Human milk contains about 1.4 mg%, cow's milk - 0.4-0.7 mg% Fe2O3; during breastfeeding, up to 80.2% of iron is absorbed, during artificial feeding - 28-33% (Krasnogorsky). There are no data on iron metabolism in older children. Iron is necessary for the formation of hemoglobin and, in addition, according to Warburg, plays the role of a catalyst in oxidative processes. The organ of iron excretion is the large intestines, and it is found in urine only in the form of traces. Sulfur enters the organism mainly in the form of cystine and to a lesser extent in the form of inorganic sulfate salts.
The requirement for sulfates in the nursing period is 0.022, in the second year of life 0.056, in the third year 0.075, and 0.06-0.07 per 1 kg of weight in subsequent years. According to Schwarz, a five-year-old child out of 0.103 g of SO3 administered over a day excreted 0.008 with stool, 0.063 with urine, and retained 0.032 g, which constitutes 31% of intake. Sulfur is excreted mainly with urine in the form of inorganic sulfates. Water metabolism. The significance of water metabolism is especially great for the growing organism of a child. The tissues of a child are very rich in water: in a 6-week-old fetus, 97.5% of the entire body mass accounts for water, in a 5-month-old its amount decreases to 90.5%, in a seven-month-old to 82.6% (Fehling), and finally by the time of birth the water content in tissues drops to 68-70% (in an adult about 60%). Throughout the entire subsequent life of the child, starting from the 3-4-month age, a gradual drying of its tissues occurs. The tissues of a child are not only rich in water, but besides that, it is in them in a state of extremely unstable equilibrium (Rominger, Langstein, and Meyer). This hydrolability, peculiar to the child in general, is especially sharply expressed in constitutionally anomalous children—exudatives, pasty ones, lymphatics. The amount of water necessary for the proper development of a child is subject to significant fluctuations depending on age, work performed by him, food, temperature and humidity of the air, constitution, and gender. The requirement for water in the first weeks of life, according to Meyer and Widmer, reaches 150-170 g, by 6 months 110 g, and by the end of the year about 90 g per 1 kg of weight. Approximately the same figures are given by Panteleyeva; according to Shabanova, the requirement for water in older children gradually decreases: from 95 g per 1 kg of weight in the second year of life and down to 40 g by 13 years. A one-year-old child should receive about 800 g of water per day (accounting for the water contained not only in liquid, but also in solid food) (Czerny), a child of 2-4 years should receive 957 g, 5-6 years—1,200 g, 7-10 years—1,333 g, 11-14 years—1,510 g. The requirement for water in girls is somewhat less than in boys. The resorption of water from the intestine in infants is 3 times greater than in adults, the passage of water through the gastrointestinal tract is significantly accelerated, the hydremic reaction during a water test in children sets in faster, water balance after dry eating in adults equalizes only after 5 hours, and in children after 1½ hours (Rominger). All this speaks of extremely intense water metabolism in children; Meyer and Nassau point out that every particle of water during its passage through the child's organism makes the journey at least 5 times: intestine-vessels-intestine. According to Kammerer, in an infant 59-60% of water is eliminated by the kidneys, 33% by the skin and lungs, 6% with the stool, and only 1-2% is retained in the organism. The distribution of excreted water can vary greatly in one and the same child depending on external conditions and the food he takes. Extrarenal elimination of water (through the skin and lungs), or the so-called perspiratio insensibilis, in children is relatively greater than in adults, and is only somewhat lowered during the newborn period. According to Birk and Edelstein, a newborn eliminates in this way during a day 21.7-37.5 g per 1 kg of weight; a normal infant removes extrarenally 32.2-38.3 g per 1 kg of weight (pro die), a robust child—44.4 g (Heubner, Rubner). According to Kammerer, by way of perspiratio insensibilis, about 80 g is excreted per day in a child of the first days, by the end of the 1st week—100-110 g, in the 4th week—130 g, in the 10th—180 g, by the half-year—about 300-400 g, and by the end of the year—about 500 g. After a year, extrarenal elimination grows slowly, constituting on the 10th year 550-650 g, and by 11-12 years 680-780 g. Perspiratio insensibilis in wakefulness is greater than in sleep, during restlessness and crying greater than at rest, in a vertical position greater than in a horizontal one, and finally in dystrophic children (27-40%) greater than in eutrophic children (33-60%) (Lokshina and Alexandrova). Water metabolism is in close connection with carbohydrate and mineral metabolism. The exclusion of carbohydrates from a child's food causes a drop in weight, and, conversely, their introduction promotes water retention. Calcium and potassium intensify the release of water by tissues; NaCl in some cases promotes water retention in the organism, in other cases can intensify its excretion. With concentrated food, diuresis decreases, and extrarenal separation increases (Bosh). Water metabolism is largely dependent on the state of the endocrine system of the child. The restriction of the amount of introduced water leads to phenomena of exicosis: sinking of the fontanelle, drop in tissue turgor, dryness of mucous membranes, cerebral phenomena, concentrated urine, and dry dark stool. Water restriction with sufficient introduction of proteins causes phenomena even more severe, resembling the picture of food intoxication, and is accompanied by an elevation of body temperature (Müller, Richet, Finkelstein). For changes in metabolism in pathological states (diseases of metabolism) and constitutional anomalies, see the corresponding words.
A. Tur. Pigment metabolism, see Pigments.
Related articles
Mentioned in
Cite this page
“Obliteration.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/obliteration/