Hysterectomy
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Great Medical Encyclopedia details surgical techniques for hysterectomy, including abdominal and vaginal approaches, supravaginal amputation, and methods described by Doyen, Kelly, Faure, and others.
Encyclopedia article (1928–1936)
HYSTERECTOMIA (hysterectomy), the removal of the uterus for various diseases, such as: fibromyoma, uterine cancer, inflammation of the uterus, ovaries, and tubes, uterine prolapse, metropathy, and the like (for details see corresponding terms). Hysterectomy is performed via the abdominal or vaginal route and consists of the removal of the entire uterus or only its body (supravaginal amputation). When indicated, the ovaries and tubes are removed along with the uterus. There are several methods of total abdominal hysterectomy. According to Doyen, after opening the abdominal cavity, the uterus is pulled toward the symphysis, and a longitudinal incision is made between the uterosacral ligaments in the region of the cervix. Upon opening the vagina, the cervix is grasped with Museux forceps, pulled anteriorly, and the vaginal fornices are then severed with curved scissors. After severing the anterior fornix, the urinary bladder is pushed back bluntly (see Figure 1). The uterine arteries are grasped with Kocher forceps and ligated, the vesicouterine fold of the peritoneum is opened, and the uterus remains attached only to the broad ligaments, which are severed along its edge. The peritoneum of the urinary bladder is sutured to the anterior wall of the vagina, and the posterior peritoneum to the posterior pouch of Douglas. Peritonization is performed using interrupted or continuous sutures (see Figure 2). Doyen's method is applicable only when the uterus is completely mobile (free access to the posterior fornix). In cases where these conditions are absent, the anterior vaginal fornix is opened to perform the hysterectomy.
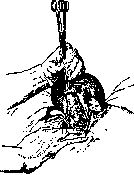
Figure 1. Hysterectomy according to Doyen: the cervix has been severed from the vaginal fornices, the urinary bladder has been separated from the uterus; only the broad ligament and the vesicouterine fold of the peritoneum remain to be transected.

Figure 2. Suturing of the vaginal walls and peritoneum after hysterectomy.
Figure 3. When the vagina is exposed, its anterior wall is grasped with strong forceps and incised with scissors. The cervix, grasped with Museux forceps, is pulled anteriorly, after which the vaginal fornices, uterosacral ligaments, and the peritoneum of the posterior pouch of Douglas are severed with scissors. Some authors preliminarily strip the visceral layer of the peritoneum above the attachment of the uterosacral ligaments. The uterine arteries may be grasped and ligated when severing the broad ligaments and separating the urinary bladder. Others prefer to do this after severing the vaginal fornices from the uterus. Hemostasis is not always easily achieved, and it is often necessary to ligate individual branches of the uterine artery. This should be done carefully to avoid injuring the ureter. Kelly, in cases of a fixed uterus, prefers to descend to the lateral fornix while severing the broad ligament from the uterus and begin the removal of the uterus here (see Figure 4). When the uterus is fixed and the appendages are surrounded by adhesions, J. Faure proposes the bisection of the entire uterus along the midline (total hysterectomy by hemisection). After pushing the urinary bladder downward, the uterus is cut along the midline with strong scissors, starting from its fundus all the way to the vagina, which is also opened. Grasping one of the halves of the uterus, it is pulled out and separated from the vagina (see Figure 5); the tense uterine artery is grasped with Kocher forceps and ligated, after which the broad ligament with its appendage is cut away. After separating the other half of the uterus in the same manner, the operation is completed in the usual way. In uterine cancer, when the surrounding cellular tissue is also removed along with the uterus and its appendages, the operation is performed according to the so-called extended method (see Cancer, Uterus). Supravaginal amputation of the uterus via laparotomy consists of severing the broad ligaments up to the region of the internal os, adhering to the edge of the uterus. The peritoneum of the anterior Douglas pouch is incised; ligation of the ascending branch of the uterine artery is performed. The cervix is cut in a wedge shape, with the apex of the wedge directed

Figure 3. The uterus is pulled upward, the broad ligaments are cut, the vesicouterine fold of the peritoneum is incised, the urinary bladder is pushed downward, the uterine arteries are transected and ligated.

Figure 4. Hysterectomy according to Kelly's method: after severing the broad ligament, the vagina is opened through its lateral fornix.
toward the lumen of the cervical canal, which is painted with tincture of iodine; 2 to 3 interrupted catgut sutures are placed at the incision site, and the peritoneum of the urinary bladder is attached to the edge of the posterior surface of the cervical stump. After placing sutures on the vessels of the broad ligament, peritonization is performed. The performance of supravaginal amputation is facilitated by the removal of the uterine appendages (see Figure 6). Initially, approximately in 1863, an extraperitoneal wound management was used, in which the cervical stump was tied off with iron wire. Later, a rubber tourniquet was placed on the stump, and it was held outside the abdominal cavity by means of two crossed needles, while the rest of the abdominal cavity was closed with sutures. Sloughing of the dead tissue occurred 4–5 weeks later. Intraperitoneal management of the stump began after Schroeder proposed prior midline incision of the uterine body.
Faure's method (hysterectomy with amputation of the uterine body by hemisection). It was recommended to place a rubber tourniquet on the uterine body, which was removed after ligation of the vessels. The proposal to carve separate flaps from the anterior and posterior surfaces of the uterus for better closure of the cervical stump was later abandoned. When the uterus is quite mobile, Faure performs supravaginal amputation in the following manner: having palpated the external os through the posterior fornix and stepping 2–3 cm higher, the cervix is incised from front to back with scissors. After complete transection, pulling the uterus anteriorly, the uterine arteries are exposed and grasped with Kocher forceps. The peritoneum of the posterior surface of the broad ligament is incised on the right,
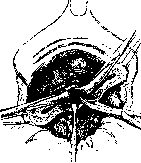
Figure. Hysterectomy with...

Figure 6. Supravaginal amputation of the uterus with appendages (According to Kelly).

Figure 7. Closure of the wound after vaginal removal of the uterus according to Doyen's method through the posterior fornix.
into the resulting space the fingers of the left hand are inserted, the appendages are lifted, and the broad ligament is severed, along with the appendages if necessary. Grasping the uterus with Museux forceps and pulling on the left broad ligament, it is transected; usual closure of the wound surface. In inflammatory changes of the pelvic peritoneum, Faure, after opening the peritoneum of the anterior surface of the broad ligament and incising the vesicouterine fold of the peritoneum, prefers to cut the cervix in the region of the internal os from front to back. Then, grasping the body of the uterus with Museux forceps at the incision site, the body is pulled upward. The uterine arteries are ligated, after which, inserting fingers into the incision site of the broad ligaments, the posterior leaf is protruded, which facilitates the separation of any adhesions and attachments present there. When uterine mobility is significantly restricted, Faure recommends incising the uterus along the midline down to the internal os (uterine hemisection), severing each half of the uterus separately from this point and, after ligating the uterine artery, strongly pulling the uterine stump to transect the attachments of the broad ligaments, adhesions, and remove the appendages. An objection raised against supravaginal hysterectomy is usually the possibility of malignant tumor development in the remaining cervix, but this possibility is small. The advantages of supravaginal hysterectomy are: simplicity of technique, better asepsis, good hemostasis, and speed of the operation. Vaginal hysterectomy was developed by Doyen, Péan, Schauta, Landau, D. Ott. After exposing the cervix with specula, the latter is grasped with strong forceps and pulled downward and forward. The posterior lip and posterior fornix are incised in a sagittal direction, and the fornix is separated from the uterus by lateral incisions. Grasping the edges of the incision and pulling out the uterus, the incision is continued to the anterior surface of the uterus, the vesicouterine fold is incised, and the urinary bladder is separated bluntly, after which the anterior fornix is incised. Clamps are applied to the broad ligament, the proper ovarian ligament, and the round ligament, which are then replaced by ligatures (see Figure 7). Elastic clamps according to Péan can be left in place and removed 2–3 days later. Another modification by Doyen: a circular incision of the cervix; the urinary bladder is pushed upward, after which the peritoneum is opened; the uterus is incised along the midline, strong forceps are applied to the edges of the incision, and the uterus is pulled downward, gradually reaching the fundus of the uterus, after which the uterus is easily everted, brought down to the vulva, and...
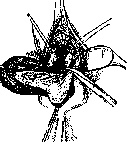
Figure 8. The uterus has been luxated through the anterior fornix; the peritoneum of the urinary bladder has been sutured to the vaginal wall; the appendages have been severed and ligated; the lower section of the parametrium and the posterior attachments of the uterus are transected.
to remove, by cutting the ligaments, peritoneum, vagina, etc. H. by retroverting or anteverting the uterus in cases of significant mobility of the uterus may be performed without preliminary incision of the uterus (see figure 8). When the uterus is immobile or there are adhesions, H. is performed by the "direct descent" method. After a circular incision of the cervix, the bladder is pushed upward, clamps are applied to the paracervical tissue, which is then excised after preliminary ligation (see figure 9). As the uterus is lowered, clamps are applied, the vessels, the superior parts of the tissue, the broad and round ligaments, the proper ligament of the ovary, and the site of origin of the tubes are ligated and cut. After removal of the uterus, the peritoneum is sutured to the vaginal mucosa, to which the stumps of the appendages are also attached, after which usually a gauze tampon is introduced into the abdominal cavity and vagina. In cases of a large uterus (fibromyoma), various methods are used to reduce its size (see Uterus).- Per vaginam hysterectomy may be performed as a partial vaginal or supravaginal amputation according to Rieck: anterior colpotomy, anteversion of the uterus; the appendages and broad ligament are excised to the area of the internal os and ligated, the peritoneum of the bladder is sutured to the uterus below the area of the internal os. The body of the uterus is removed by a wedge-shaped incision at the cervix, and the wound surface is closed with 2-3 nodal sutures of catgut. Sutures on the vagina.
Related articles
Mentioned in
Cite this page
“Hysterectomy.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/hysterectomy/