Vaginal Hysterotomy
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article describes the surgical procedure of vaginal hysterotomy (vaginal cesarean section), detailing the technique of incising the anterior uterine wall to access the uterine cavity. It covers indications, such as obstetric emergencies, and compares the procedure to classical cesarean section, noting its utility for pregnancy termination.
Encyclopedia article (1928–1936)
HYSTEROTOMIA (vaginal), an operation for incising the anterior wall of the uterus; it was proposed by Defontain for digital examination of the uterine cavity, removal of polyps, enucleation of submucous myomas, etc. The cervix is exposed with specula; it is grasped with Museux forceps; a transverse incision is made at the edge of the vaginal portion of the uterus through the mucosa of the anterior fornix, and the bladder is pushed upward. Into the canal of the cervix, which has been pulled downward, one blade of the scissors is inserted, and the anterior wall of the uterus is incised up to the peritoneal fold. The operation is performed extraperitoneally. Upon completion of the operation, interrupted catgut sutures are applied to the uterine wall and the vaginal mucosa. Hysterotomia has found wide application in obstetrics, where it was proposed by Dührssen under the name "vaginal cesarean section." Initially, Dührssen, in addition to the anterior wall, also incised the posterior wall of the cervix. Now it is considered quite sufficient to incise only the anterior wall. Additional incision of the posterior wall is performed only in exceptional cases (in the event of difficulty in pulling the cervix downward). The proposal by Krönig to perform a vaginal cesarean section by means of only a posterior hysterotomy, with opening of the abdominal cavity, has not gained popularity. The operation begins with a longitudinal incision, some distance from the urethral opening, to the outer edge of the cervix; a transverse incision can be added to this incision, at a distance of 1–1.5 cm from the edge of the cervix. Some limit themselves to a transverse arcuate incision of the mucosa (see figure 1). After this, the bladder is separated by a sharp or blunt method (see figure 2), which

Figure 2. Longitudinal [incision] of the vaginal mucosa; separation of the bladder by the blunt method.
incision of the vagina
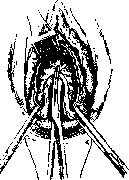
Figure 3. The detached bladder is pulled upward with specula; incision of the uterus along the midline.
due to the looseness of the tissue, is usually performed very easily. After separation of the bladder, it is pushed upward with a speculum, and the peritoneum is separated from the uterus as far as possible. Then the anterior wall of the cervix is incised. Having grasped the edges of the incision with Museux forceps and pulling the cervix downward, the anterior wall of the uterus is incised as high as possible, up to the peritoneal fold (see figure 3). The fetal sac is opened, and version on the foot is performed or forceps are applied; in the case of a dead fetus—perforation. The placenta, in the majority of cases, must be delivered according to Credé or by manual method. The edges of the uterine incisions are sutured with interrupted catgut sutures, without involving the uterine mucosa (see figure 4). When suturing the vaginal wound, some introduce a strip of gauze into its lower section, which is removed after 2–3 days. With careful and cautious separation of the bladder, it is easy to avoid injuring it: if the peritoneum is opened, it is carefully closed with separate sutures; a sufficiently long incision of the uterus prevents its rupture during the extraction of the fetus, and a T-shaped or arcuate incision of the mucosa prevents ruptures of the vagina. The cause of bleeding during the operation ante partum may be excessive deviation from the midline during the separation of the bladder. Significant bleeding is also possible in cases of placenta praevia, in which the tissues of the lower segment become fragile and easily bleed. Various additions to the technique—preliminary dilation of the cervix for good drainage of secretions in the postpartum period, preliminary insertion of a metreurynter and incision of the uterus beneath it, the Schuchardt incision, incision of the perineum along the midline—have not gained wide popularity and are used only for special indications. According to data from Selitsky, the mortality rate from the operation itself is zero. Sufficiently numerous observations have shown that vaginal cesarean section does not affect menstruation and does not influence subsequent4 births.
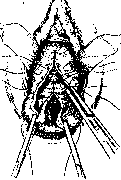
Figure 1. Layer-by-layer suturing of the surgical wound. The sutures on the uterus do not involve the mucous membrane.
According to Selitsky, a necessary condition for performing a vaginal cesarean section is the absence of obstacles from the bony pelvis and free access to the cervix. Indications for performing a vaginal cesarean section can include life-threatening conditions for the pregnant woman or woman in labor (eclampsia, diseases of the heart, lungs, kidneys, etc.), premature detachment of the placenta, prolapse of the umbilical cord, and abnormal positions of the fetus—transverse, oblique. In the presence of obstacles to labor from the cervix (scars), as well as in cases of central or low attachment of the placenta, due to life-threatening bleeding, preference should be given to the classical cesarean section. Vaginal cesarean section is indicated in cases of septic infection of the pregnant uterus with a living or dead fetus. Due to the simple technique of the operation, Hysterotomia has found wide application for the termination of pregnancy, starting from 3–3.5 months. The advantage of Hysterotomia, moreover, lies in the conditions of greater asepsis compared to other methods of pregnancy termination and in the elimination of conditions for accidental injuries to the uterus (cervical ruptures, uterine perforation, etc.). Hysterotomia is the most reliable, gentle, and safe method of artificial miscarriage in late stages of pregnancy. With the goal of avoiding deformation of the vaginal portion of the cervix, which does not always heal after its incision, some authors suggest starting the incision of the uterus above the external os or, by opening the peritoneum of the anterior Douglas space, incising the body of the uterus itself—the Dutzmann operation, sectio caesarea vaginalis vera (Kakushkin).
Related articles
Mentioned in
Cite this page
“Vaginal Hysterotomy.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/hysterotomy/