Cesarean Section
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
Cesarean section is the surgical procedure of extracting a fetus through an incision in the abdominal wall. The article traces its historical development, noting that before the introduction of antiseptic and aseptic techniques, the procedure had extremely high mortality rates for both mothers and infants.
Encyclopedia article (1928–1936)
CESAREAN SECTION (sectio caesarea), the operation of extracting the fetus from the uterus through an incision in the abdominal wall. The concept of "C. s." expanded after the introduction in 1896 by Dührssen of the kolpohysterotomia ant. method, which he called "vaginal cesarean section." At present, the term "C. s." encompasses any operation involving the incision of the pregnant woman's womb. A more precise designation for the main method of the operation is the term "abdominal (abdominal wall) C. s." (synonyms: laparohysterotomia, hysterotokotomia, koeliohysterotomia, gastrohysterotomia); "minor" C. s. refers to abdominal C. s. in early pregnancy. The very name "C. s." arose only in the 17th century (Sicbold, Doderein). According to the widely held opinion, this operation owes its name to the fact that it was used to deliver one of the ancestors of the Roman Caesars. However, there is no historical basis for such an explanation. Historians of the subject derive the adjective "caesarea" not from "caesar" but from the Latin verb caedere. Thus, the term sectio caesarea is a tautology, since the verbs secare, from which "sectio" is derived, and caedere both denote the concept "to cut." C. s. is one of the oldest obstetric operations. The first reliable indication of the performance of C. s. is the mention of it by Guillemeau, according to which French surgeons were already applying this operation on living patients in the 16th century. The first reliably documented case of successful C. s. on a living patient in Germany belongs to Trautmann in Wittenberg (1610). The first C. s. operation in Russia was performed by Erasmus. Until the present era, C. s. was the subject of persistent development and enormous literature. But the results of the operation before the introduction of antiseptic and aseptic techniques continued to remain very poor, especially for the mother. Kayser reports that of 338 cases of C. s. collected from the literature from 1750 to 1839, a fatal outcome for mothers was observed in 62%, and for children in 30%. Murphy (1851) shows similar statistics-477 cases. According to Radford, maternal mortality from C. s. in England and Ireland from 1738 to 1749 was 73%. Stadfeld calculated maternal mortality in Denmark and Norway at 95%. According to Spath, there was not a single case of recovery in the maternity hospitals of Vienna before 1877. According to Gueniot, all 40 cases of this operation performed in Paris before 1870 ended in the death of the mothers. According to Ponomarev's data, C. s. was performed in Russia in the pre-antiseptic period (before 1880) 21 times and resulted in 81% maternal mortality. Even after the introduction of the principles of antiseptic and aseptic techniques into operative obstetrics, C. s. continued to give poor results, despite countless modifications of the technique in terms of the shape and topography of the incisions. 19
CESAREAN SECTION
of the abdominal wall and the uterus, wound care, etc. Thus, according to Ponomarev's data, Cesarean section in Russia during the antiseptic period, over the decade from 1881 to 1890, was performed 61 times with a mortality rate of 49.3% (reduced - 16%). The cause of poor outcomes was hemorrhage and, especially, contamination originating from the wound in the uterus, which healed poorly due to the lack of rest in the organ contracting during the postpartum period and the easy penetration of infection into it. In view of these circumstances, the idea arose to remove the uterus itself during a Cesarean section. The method of extirpation of the uterus during a Cesarean section, theoretically proposed in 1809 by Philipp Michaelis and experimentally verified in 1862 by Jeser, was practically applied to a woman in labor in 1869 by Storer in Boston. The method did not become widespread due to technical difficulties. In 1876, Porro proposed and performed his method of performing a Cesarean section simultaneously with supravaginal amputation of the uterus. Since then, the method has been called the Porro operation. The uterus, freed from the fetus, was cut off after the cervix, to avoid major hemorrhage, was tightened near the internal os with iron wire, and the remaining stump was placed extraperitoneally and sutured to the abdominal wall in the lower corner of the wound. In Russia, this operation was studied by Rein on animals in that same year, 1876. In 1880, it was performed in Russia by Fitsky. The results after the Porro operation began to be better than after a conventional Cesarean section, especially after various technical changes were introduced into the original Porro operation. Thus, P. Müller proposed in 1878 to extract the uterus outward and tighten the cervix with wire before opening the fetal sac (preliminary eventration of the uterus was performed by Rein in animal experiments as early as 1876). Hegar replaced the wire with an elastic tourniquet. Subsequently, the extraperitoneal fixation of the surgical stump was replaced by leaving the latter inside the abdominal cavity. At the present time, this operation is performed by the same method as supravaginal amputation of the uterus for uterine fibromyoma. The reduction in maternal mortality after the Porro operation, however, came at the cost of the loss of childbearing and menstrual function in the operated women, which often heavily affected their well-being and psyche, despite the fact that, to avoid the loss of the internal secretory functions of the sex glands, obstetricians of a period close to ours, whenever possible, preserved the ovaries for the operated patients. This shadow side of the Porro operation forced obstetricians to continue searching for other ways to improve the results of Cesarean section, and to perform the Porro operation, or complete removal of the uterus, only for special indications, such as cancer of the cervix at the end of pregnancy, or in cases of uterine fibromyomas when tumors obstruct vaginal delivery and it is not possible to preserve the uterus after a Cesarean section, or in certain infected cases. A significant step forward in improving the results of the conservative Cesarean section was the improvement of the uterine suture. Until the beginning of the 19th century, the uterine wound after a Cesarean section was not sutured at all. But even later, the question of the uterine suture was treated differently. While Scanzoni (1855), Braun (1857), and Naegele (1867) considered this suture dangerous, Lebas had already developed a technique for the uterine suture in 1769. A step forward was the use in 1852 by Frank E. Polin of silver wire for this purpose. But even in 1881, Zweifel still rejected the uterine suture. A turning point in this matter was the proposal by Saenger and Kehrer not to limit the suturing of the uterus to a single-layer suture, which could not serve as sufficient protection against the leakage of lochia into the abdominal cavity, but to suture the peritoneal covering of the uterus separately. To make this possible, Saenger and Kehrer resected the musculature under the uterine peritoneum and sutured the peritoneum like an intestinal suture. In 1886, Saenger reported on 26 cases operated on by his method, of which 19 recovered, i.e., 76%. From this time on, an improvement in the results of Cesarean section is noted. According to Ponomarev's statistics for the decade from 1881 to 1890, mortality after the operation in Russia was: total 49.3%, and reduced 16.4%; for the last decade of the 19th century, mortality decreased: gross to 17.6%, and reduced to 7.2%. According to Pobedinsky's data, 445 Cesarean sections were performed in Russia from 1886 to 1912, with mortality being 40% before 1890, and 6.6% from 1890 to 1912. According to a report by Routh at the V International Congress of Obstetricians and Gynecologists in 1910, in Great Britain and Ireland during the period 1906-1910, 680 cases of Cesarean section resulted in 7.9% mortality; French authors had, according to Doléris, the following results: Bar in 105 cases - 6.3% mortality, Pinard (1907-1908) - 12, Lepage - 14 cases without a single death, Fournier in 52 cases - 3, Doléris in 41 cases - 2 deaths. Along with the improvement in results, the scope of application of Cesarean section also expanded: the operation began to be used not only for absolute indications, as before, but also for relative ones. In Russia, Lebedev was the first to advocate for such an expansion of indications for Cesarean section in 1886. The improvement of the conservative Cesarean section technique, which made the use of the Porro operation unnecessary in most cases, still did not completely eliminate the danger of infection. This danger increased when the operation was performed a significant time after the rupture of membranes, after multiple internal examinations of the woman, or when examining her without the strictest observance of the rules of asepsis, etc. Thus, to obtain quite good results, it was necessary to limit the use of Cesarean section to so-called 'clean' cases. The desire to expand indications forced a search for «21 new ways and further improvement of the Cesarean section technique. In 1907, Frank proposed temporarily closing the abdominal cavity before opening the eventrated uterus. Since this method did not provide complete protection against infection of the abdominal cavity, Frank attempted to implement the idea of Physick, expressed by the latter as early as 1822, which consisted of performing the operation by an extraperitoneal method by detaching the peritoneum of the bladder and paving a path to the cervix, which was to be opened by a transverse incision. Since this attempt was accompanied by injury to the bladder, Frank subsequently developed the so-called transperitoneal method. The abdominal cavity is opened by a transverse incision of the abdominal wall 2 fingers above the symphysis pubis; the peritoneum (plicae vesico-uterinae) is incised at the bladder itself, separated upward, and sutured to the corresponding parietal layer of the peritoneum. Thus, the abdominal cavity is isolated. The lower segment of the uterus, exposed from the peritoneum, is also opened by a transverse incision. Veit modified this method by making the incision of the abdominal wall, the peritoneum of the lower part of the uterus, and the uterine wall itself in a longitudinal direction. The idea of finding an extraperitoneal path to the uterine cavity was subsequently realized thanks to the work of Sellheim, Küstner, Latzko, and Döderlein. Sellheim proposed performing an extraperitoneal Cesarean section as follows: the abdominal wall is incised according to Pfannenstiel, the peritoneum is detached from the posterior surface of the rectus muscles and further along the midline from the bladder upward. The bladder is pushed downward from the cervix. The lower segment of the uterus and the cervix, thus exposed from the peritoneum, are opened, and the fetus is extracted. Performing this operation without opening the peritoneum is possible, however, only in the case when the transitional fold of the peritoneum, due to the onset of uterine labor activity, is itself pushed high upward and the lower segment of the uterus is stretched. In all other cases, Sellheim was forced to operate according to a method analogous to Frank's method, i.e., transperitoneally. Performing the Cesarean section operation by a purely extraperitoneal method only became successful after Latzko, Küstner, and Döderlein, using Sellheim's anatomical studies regarding the topography of the plicae vesico-uterinae during labor, proposed paving a path to the cervix from the side of the bladder. Such a path was proposed as early as 1806 by Jörg and performed in 1820 by Ritgen, and subsequently in 1870 successfully applied by Thomas and Skene in America. Along with extraperitoneal Cesarean section, the low corporal Cesarean section according to the method of Franz and Henkel became widespread, as well as the intraperitoneal cervical Cesarean section, the so-called transperitoneal-cervical Cesarean section with detachment of the bladder, according to the method of Krönig-Opitz, or the 'low retrovesical Cesarean section' of French authors (some call it the Brindeau method). By applying the operation, French obstetricians significantly expanded the indications for Cesarean section in cases suspected of infection.
To reduce the danger of Cesarean section in cases of clearly expressed infection from the birth canal, Pillore in 1854 proposed the application of a utero-abdominal wall suture, and Sellheim in 1908 proposed the creation of a utero-abdominal fistula, which after some time is freshened and sutured. In 1924, Portes proposed a modification for infected cases, which he called exteriorisation temporaire de l'utérus, in which the uterus, brought out of the abdominal cavity, after being emptied and the incision sutured, is not returned to the abdominal cavity, but remains outside it for a more or less prolonged time (3-4 weeks) and is only subsequently returned to the abdominal cavity. From Couvelaire's clinic, 32 cases of exteriorization of the uterus were published with 2 fatal outcomes. In the USSR, this operation was performed successfully in 1926 by Bublichenko. With the Lestocquoy method, recommended for subinfected cases, the uterus is sutured, and the area of the suture is isolated by being attached to the abdominal wound. The introduction of the extraperitoneal Cesarean section method, the intraperitoneal cervical and, in general, the low uterine incision, the operations of Portes, Lestocquoy, etc., made the operation in question even safer: mortality after it, according to Benthin, is determined at 3-5%, and according to Miller, at 2%. In Russia, according to Ponomarev's statistics for the period since 1901, mortality from Cesarean section has fallen: gross to 7%, and reduced to 1.7%. According to data from Ilkevich, Levi, and Selitsky, 743 cases of Cesarean section performed in Moscow maternity institutions in 1921-27 yielded mortality: general 7.8%, reduced 4.6%. Methodology and results of abdominal Cesarean section. The methodology of abdominal Cesarean section is distinguished by a large number of modifications. Especially many variants are encountered regarding the topography, direction, size, and shape of the uterine incision. Operators of the initial period of the scientific development of the Cesarean section method in the 18th and 19th centuries also used various variants of the abdominal wall incision. Thus, Lauverjat (1788) proposed a transverse incision, Stein an oblique one, Osiander a low oblique one, and Levret a longitudinal lateral one. But already at the end of the 19th century, with the development of operative gynecology, the predominant method of operation became the longitudinal incision of the abdominal wall along the midline. The direction of the uterine wall incision also varied depending on the direction of the abdominal wall incision and for the most part corresponded to the latter. The independent significance of the direction of the uterine wall incision is first seen in Kehrer's proposal to make an incision along the anterior wall of the uterus in a transverse direction slightly above the border of the transition of the peritoneum from the uterus to the bladder. v2* As advantages over the longitudinal incision, the following were cited: 1) the possibility of avoiding injury to the placenta, which is usually located in the uterus above this bridge, and 2) a greater possibility of healing per primam of the uterine wound, because with the longitudinal incision according to Sänger, which is most commonly used even at the present time, postpartum contractions of the circular uterine musculature contribute to the gaping of the wound and therefore act in a direction opposite to that in which the applied sutures connect the wound, whereas with a transverse incision there is no such opposition to healing. The same considerations underlie Fritsch's proposal to make a transverse incision not in the cervical region, but in the fundus of the uterus from one tube to the other. Since the fundal-transverse incision runs parallel to the vessels located in the uterine wall, the blood loss during it should also be less than with a longitudinal incision, which crosses these vessels (Fritsch, Kaiser, Gruzdev, etc.). With a transverse incision, the abdominal wall is opened in a longitudinal direction. The abdominal wall incision must in this case be either located high or have a significant size so that the entire uterus can be brought out. The indicated advantages of the fundal-transverse incision according to Fritsch have not received universal recognition. For example, a number of authors believe that insufficient healing and thinning of the uterine scar are observed more often precisely with this incision. Conditions for the formation of adhesions are very favorable, since the omentum usually comes into contact with the line of the incision with its entire surface. Due to the great development of vessels in the region of the tubes and round ligaments, where the ends of the incision are located, which are involuntarily torn during the extraction of round fetuses, bleeding can be significant. The contents of the uterus can easily enter the abdominal cavity (Serdyukov). On the other hand, Veit, who together with many others is a defender of the Fritsch incision, points out that the fundal-transverse incision allows for the most reliable protection of the abdominal cavity from the inflow of amniotic fluid into it. This circumstance should be of great importance when expanding the indications for Cesarean section and including cases suspicious for infection in the scope of the operation. The transverse fundal incision also has its adherents among us. Even earlier, Caruso, P. Müller, and others also proposed, for the purpose of limiting blood loss, to make an incision in the fundus of the uterus in a longitudinal direction. The incision extends with its edges onto the anterior and posterior surfaces of the uterus. In this part of the uterus, the edges of the wound have significant thickness, as a result of which their adaptation to each other is easier than in the lower part. The fundal-sagittal incision has been widely used in recent years in Moscow at the Grauerman Maternity Hospital. In 1881, Cohnstein proposed incising the posterior wall of the uterus in order to better ensure the drainage of secretions from the unstitched uterus, left as such according to the method prevailing at that time, through the simultaneously opened posterior vaginal fornix. Furthermore, with this method, the uterine wound comes into less contact with the intestines. The same considerations guided Polano later, who proposed making an incision along the posterior wall of the uterus in its lower part. Favorable results have been obtained with this method by many authors. Russian obstetricians rarely used this incision. Thus, out of 743 cases of abdominal Cesarean section collected by Ilkevich, Levi, and Selitsky, the incision of the posterior uterine wall according to Polano was performed only 2 times. When choosing the site of the uterine wall incision, some are guided by the location of the placenta. Pathological-anatomical studies by Gusserow showed that in 77 cases the placenta was attached to the anterior wall, and in 93 cases to the posterior wall of the uterus. Küstner, on the contrary, more often found the placenta attached to the anterior wall during the operation than to the posterior wall of the uterus. It should be thought that the attachment of the placenta to the anterior and posterior walls of the uterus occurs approximately equally often. In order to determine the site of placental attachment before the uterine incision, Palm proposed using the following sign: if the round ligaments, departing from the uterus, diverge upwards, then the placenta is attached to the anterior wall; if they run parallel, or even converge somewhat upwards, then the placenta is attached to the posterior wall of the uterus. This sign is considered unreliable by Olshausen. Of greater practical importance is this author's indication that the attachment of the placenta should be expected in the place where large blood vessels show through. A greater convexity of the anterior wall of the uterus suggests that it is precisely to it that the placenta is attached, while the posterior wall of the uterus exhibits some convexity anyway. Olshausen therefore begins with a longitudinal incision in the fundus of the uterus and, depending on the site of placental attachment, continues it along either the anterior or the posterior wall of the uterus. Macé and Mouchotte try to avoid extensive detachment of the placenta before the extraction of the fetus by making an incision along the anterior wall of the uterus, and if they encounter the placenta here, then, starting from the upper corner of the wound, they detach the placenta in an upward direction only for the width of a finger until they reach the edge of the membranes, and then they continue the started incision. Of the various methods of abdominal Cesarean section, modern obstetricians mainly use corporal and intraperitoneal cervical Cesarean section. The most common method until recently was the corporal, or classical, Cesarean section. Preparation of the operating field is the usual one for laparotomy. When choosing the method of anesthesia, it is necessary to take into account the effect of anesthesia not only on the patient being operated on but also on the fetus. Inhalation anesthesia, if given in abundant quantity before the extraction of the fetus, can lead to one or another degree of asphyxia of the latter. Clinical observations made in this regard are confirmed by experimental studies by Küstner, who found that chloroform and ether during the operation pass into the child's blood. Chloroform and ether anesthesia can also contribute to uterine atony. Many modern obstetricians therefore mainly use local anesthesia. Thus, Frey, out of 200 cases, used local anesthesia in 163, leaving inhalation anesthesia mainly for cases of eclampsia. Labhardt uses local anesthesia before the birth of the child, and general anesthesia at the end of the operation.
Spinal anesthesia, which in some cases (Jaschke, Wagner, and others) was the cause of a fatal outcome, is now abandoned by many. The patient lies in a horizontal position or in the Trendelenburg position, which prevents the eventration of intestinal loops. A longitudinal incision of the abdominal wall is made strictly along the white line, starting 2-3 fingers above the pubis, about 15 cm long, so that the navel is in the middle of this incision. If it is intended to bring the uterus out of the abdominal cavity before opening the fetal sac, then the incision of the abdominal wall should be continued upward. Eventration of the uterus during a Cesarean section presents certain advantages. First of all, it makes it easier to determine the midline along which the incision should be made. When leaving the uterus in situ in the abdominal cavity, the operator, especially a beginner, can easily make a mistake in finding the correct place for the incision, since the physiologically pregnant uterus is rotated around its axis to the right; therefore, upon opening the abdominal wall along the white line, the surface of the uterus lying in the wound and presenting itself to the operator's eyes is not the middle of the anterior surface of the uterus, but its anterolateral part; the midline, along which the incision of the uterine wall should be made, lies to the right and posteriorly. Losing sight of these data, the operator risks making the incision closer to the edge of the uterus, which will lead to heavy bleeding due to the presence of large vessels here. Such a deviation from the midline can acquire special significance when performing a transperitoneal cervical Cesarean section, in view of the possibility of injuring the ureter. Eventration of the uterus facilitates the cessation of bleeding, as well as the suturing of the uterus. Therefore, Dührssen and others, while cutting the uterus in situ, eventrate it, however, during suturing. Eventration of the uterus, first applied by Müller, is necessary for incisions made through the fundus of the uterus or through its posterior wall, and when using temporary compression of the uterine arteries by means of a rubber tourniquet or the assistant's hand. Leopold, Pinard, Veit, and others consider eventration of the uterus a good way to protect the abdominal cavity from the leakage of amniotic fluid into it. In view of these circumstances, eventration of the uterus during a Cesarean section is used by many obstetricians at the present time.

On the other hand, opening the uterus in situ without eventration makes it possible to limit oneself to a smaller incision of the abdominal wall; the incision itself can be made significantly lower, and during the operation, it is easier to avoid the protrusion of intestinal loops, especially if the Trendelenburg position is used. Therefore, the method of eventration also has numerous opponents. The scope of its application is narrowing along with the recently observed spread of the cervical Cesarean section method, which makes the use of eventration unnecessary.
Before opening the uterus, the entire surgical field is covered with compresses. If the uterus is eventrated, it is shifted toward the pubic symphysis and, after first covering the intestinal loops with napkins, the upper corner of the abdominal wall incision is temporarily sutured behind the uterus. The incision is made either longitudinally along the anterior wall of the uterus (Sänger incision), or longitudinally along the fundus of the uterus (fundal-sagittal incision of Müller), or fundal-transverse (according to Fritsch) from one tube to the other. The most common is the longitudinal incision, as it corresponds to the incision of the abdominal wall and less disrupts the function of the longitudinal fibers of the uterus. If the opening of the uterus is intended to be performed in situ, then the uterus is first moved by the assistant's hands close to the abdominal wound so that it stands along the midline and the incision does not fall on its lateral part. The membranes of the fetal sac are ruptured by hand if it has not yet opened during the incision of the uterus, and the fetus is quickly extracted by the leg. To avoid the entry of amniotic fluid into the abdominal cavity, Fournier and other authors proposed extracting the entire fetal egg intact without rupturing the membranes. In the USSR, a supporter of this method is Blagovolin. The disadvantage of this method is the need to make a larger incision and the risk of deep asphyxia of the fetus. In order to protect the abdominal cavity from the leakage of amniotic fluid into it, Lüthy proposed removing the amniotic fluid before opening the uterus using a special pump. Cherepakhin advises, for the same purpose, after extracting the uterus, to protect it with a special rubber cover and make a fundal-transverse incision through it. So that the surgical field is not flooded with blood and amniotic fluid during the operation, de Lee designed an electric suction apparatus, which is readily used by American operators. Benthin warns against using this apparatus in case of atonic bleeding. If the placenta (placenta caesarea) is encountered in the path of the incision, then, ignoring the significant bleeding, the hand is quickly passed between the placenta and the uterine wall and the fetal sac is opened. Two clamps are applied to the umbilical cord and it is cut. At this time, the assistant massages the uterus directly or through the abdominal wall. In case of atony, Pituitrin or ergot preparations are injected. Some use these injections prophylactically at the very beginning of the operation. The placenta is removed while simultaneously pulling on the umbilical cord. In rare cases, it has to be separated by hand. Ott recommends the following technique: a compress is placed into the cavity of the exteriorized uterus, and the uterus itself is vigorously pulled upward by the assistant, who has grasped the upper corner of the uterine wound with a finger. This technique should ensure hemostasis and fix the uterus in a position convenient for suturing. The best method for stopping bleeding after the removal of the placenta, which is examined for integrity, is the suturing of the uterine wound. The sutures, usually catgut, are placed at a distance of 1.5–2 cm from each other in 2 or 3 layers: the 1st, deep row of sutures is passed through the entire thickness of the muscle layer or through its lower 2/3, without grasping the mucosa; however, Everke and Döderlein recommend suturing exactly the decidual membrane, catching a little muscle tissue; the majority do not use this method; the 2nd row of sutures is placed on the peritoneum together with the underlying muscle tissue, with the entry and exit points made somewhat away from the 1st row of sutures and in the intervals between the latter; for both layers, interrupted sutures are often used; the 3rd, superficial, sero-serous suture is usually applied as a continuous one (Figure 1); this suture can be applied like a Lembert suture (Fig. 2). The abdominal wall is sutured in the usual way. The main advantage of the classical Cesarean section is anatomical clarity and simplicity of execution. The disadvantages include: the possibility of the contents of the uterus entering the abdominal cavity and the formation of adhesions, the frequency of which ranges from 50% to 80% (Serdyukov). The results obtained with the classical Cesarean section are illustrated by the following statistical data (Holland, Eardly): in 3,374 cases of classical Cesarean section, where the operation was performed before the onset of labor, the mortality rate was 1.6%; if it was done 6 hours after the onset of labor—1.8%, even later—10.7%. Cesarean section after previous attempts to apply forceps resulted in a 27% mortality rate.

Figure 1.
Figure 2.
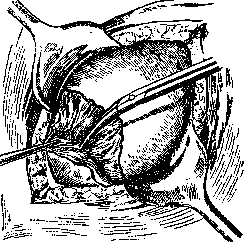
Recently, the low corporal Cesarean section, in which the incision is made in the lower part of the body of the uterus, which remains in situ, and the cervical intraperitoneal (transperitoneal cervical) Cesarean section have become widespread. The latter method differs from the classical Cesarean section only slightly: after opening the abdominal cavity with a longitudinal (from the pubis to the navel) or transverse incision according to Pfannenstiel, with the patient in a position with a highly elevated pelvis, the plica vesico-uterina is dissected in the transverse direction. The lower edge of the plica, together with the urinary bladder, which must be previously emptied, is pushed down along the cervix as deep as possible toward the vagina (Fig. 3). An exposed area of the cervix and isthmus is obtained, sufficient for the extraction of the fetus. The cervix is cut with a longitudinal incision. The incision goes upward to the edge of the uterine peritoneum (Fig. 4).
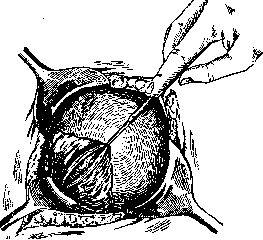
Figure A.
Compared to the classical Cesarean section, the extraction of the fetus during an intraperitoneal cervical Cesarean section can be difficult. In cases of breech presentation or transverse position, the fetus is extracted by the leg; if the incision is located above the head, then the latter is delivered with the help of forceps.
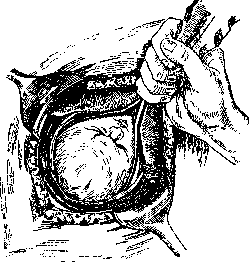
Figure 5. (fig. 5) or by means of a finger introduced into the fetus's mouth while simultaneously squeezing the head from the sides (figure 6). For delivering the head, special instruments have also been proposed. The uterine wound is sutured with catgut in two layers. The lower edge of the vesico-uterine fold together with the bladder is pulled upward through the uterine suture and sutured in place, the peritoneal areas distant from the wound. According to Opitz, the cervix is less susceptible to infection than the body of the uterus, since in the postpartum period infectious agents are less frequently found in it. In subsequent pregnancies, uterine ruptures occur in a smaller percentage of cases. Wetterwald (1926) collected 3,600 cases from the literature with a mortality rate of only 3-3.5%. Brindeau had 1.1% mortality in 88 cases of this operation. In the USSR, proponents of this method include Cherkasov (34 cases with 0% mortality for mothers and children), Pisemsky (24 cases with 1 death), and others. Some authors even in cases of placenta previa (Siegel, Stoeckel, Pankow, Palmov) prefer to apply cervical cesarean section. The disadvantage of the method is the difficulties that may arise when extracting the fetus, and the associated danger of its asphyxiation. Extraperitoneal C. section is performed as follows: with the patient in a position with the pelvis highly elevated, an incision is made in the abdominal wall, starting from the pubic symphysis, 10-12 cm long along the midline (Latsko-Döderlein) or 3-5 cm laterally from it (Küstner). Care must be taken not to injure the highly elevated bladder or peritoneum. With the help of a blunt dissector, the preperitoneal, pre- and paravesical connective tissue is bluntly dissected on the side of the bladder, exposing the vesico-uterine fold and the lateral part of the bladder, which is previously filled with 150-200 cm3 of boric solution or illuminated by a cystoscope introduced into it. The bladder


Figure C.
Figure Figure 8. i.e., perpendicular to the uterine suture, which thereby becomes completely covered and isolated from the abdominal cavity (fig. 7).- The main advantage of this method is less bleeding when making the uterine incision, better chances for healing due to the greater rest of the muscle of this part of the uterus in the postpartum period, and better possibility of peritonization by means of the peritoneal flap of the vesico-uterine fold, thanks to which it is possible to completely avoid postoperative adhesions. During the operation, it is easier than in the case of corporal C. section to avoid prolapse of the intestines and penetration of infection into the abdominal cavity. The bladder is displaced to the right toward the midline, and the vesico-uterine fold is pulled upward as much as possible toward the navel. Having spread the tissues with blunt hooks, the exposed lower anterior part of the uterus is found (fig. 8). Opening of the uterine cavity, extraction of the fetus, and suturing of the uterine wound are generally performed according to the same principles as in intraperitoneal cervical C. section. For the duration of the fetus extraction, the patient is placed in a horizontal position. The abdominal wound is sutured in layers. In cases suspicious of infection, the connective tissue is drained. According to proponents of the method, the main advantage of extraperitoneal C. section is that the contents of the uterus do not enter the abdominal cavity, which makes it possible to operate even in unclean and doubtful cases. Furthermore, the incision is made outside the site of placental attachment, which reduces blood loss, and the suture itself is located extraperitoneally, which eliminates the danger of adhesions and other complications. However, the method also has numerous opponents (Ols-hausen, Schauta, Kronig, Gubarev, and others). The negative side lies in the greater technical complexity and higher infant mortality. In intraperitoneal C. section, the average infant mortality (according to Bentin) is 2-4%, while in extraperitoneal it is 7%. According to Horstrup, all infants are extracted in asphyxia with the extraperitoneal method; Walthard, Franz, Gubarev, and others deny the advantages of this method in infected cases on the grounds that connective tissue is less resistant to infection than peritoneum. According to statistics collected in 1921 by Voigt, 778 cases of intraperitoneal C. section resulted in 2.1%, and 226 cases of extraperitoneal in 2.5% maternal mortality. In 1/4 of all cases of extraperitoneal C. section, damage to the peritoneum occurred, and damage to the urinary tract is also common (about 7%). The extraperitoneal method is not used in England, America, Switzerland, Italy, Spain, and in many German clinics. In the USSR it is also applied very rarely. At the VI All-Union Congress, Novikov reported on 47 cases of extraperitoneal C. section, of which 3 ended fatally. Chertok found in the Russian literature up to that time 63 cases. In Solms' method, which he called Laparokol-pohysterotomia, extraperitoneal C. section is combined with vaginal. Postoperative care after C. section is the same as after typical laparotomy. Special attention should be paid to the danger of sequential bleeding and retention of lochia. The danger of postoperative ileus is small (Haggstrom calculates its frequency at 1%). The main danger comes from infection. Postpartum morbidity equals: according to Bentin-20-33%, according to Holland-55%. Of 650 maternity patients from the material of Ilkevich, Levi and Selitsky, 334 (51.4%) had fevers. According to research by Bride, the childbearing function after C. section is somewhat reduced (50% of operated women subsequently did not become pregnant again). According to Lichtenstein, miscarriages and premature births occur more often than usual. The danger of uterine rupture in subsequent births is assessed differently. With modern techniques, however, it is still small. Uterine ruptures most often occur after corporal C. section. Phaneuf believes that with corporal C. section rupture occurs in 25%, and with cervical in 3%. According to Holland's statistics, ruptures occur in 4%. According to his data, in England out of 448 women who had undergone C. section, 96 women were allowed to give birth "naturally." Of these, 18 had ruptures. Poor condition of the scar was found by Couvelaire in 14%. Schroder, who collected in 1916 63 cases of rupture with mortality of 18.96%, assesses the frequency of ruptures after corporal C. section at 1.2%, and after cervical at 0.3%. Out of 743 cases of C. section from the material of Ilkevich, Levi and Selitsky, there are 5 cases of uterine rupture. According to Wetterwald's statistics, out of 3,600 cases of cervical C. section, ruptures occurred in 0.28%. The strength of the uterine wall after C. section may remain completely unchanged. Research by Audebert (according to Bentin) showed that in 73% after C. section, complete restoration of the myometrium occurs. Complete restoration of the strength of the uterine wall is confirmed by cases of subsequent pregnancies and births after the operation, which ended in spontaneous deliveries or repeated C. sections. The number of repeated C. sections according to the material of Ilkevich, Levi and Selitsky is 4% in relation to the total number of C. sections. According to Siegel (quoted by Bentin), the probability that C. section will be performed again on the same woman in the 2nd or 3rd time is equal to the ratio 2:3. Thorns reported cases where C. section was performed on one woman 4, 6, and even 7 times. Morbidity in repeated C. sections is not greater than in primary ones, and mortality according to some (admittedly small) statistics is even somewhat smaller. The latest statistics by Winter, covering 4,450 cases of C. section operated on during one 1928 year by 384 German operators, gives an overall maternal mortality of 7.1%. After deducting cases where the cause of death was those factors that gave indication for the operation and cases of death from intercurrent diseases, the reduced mortality (result of the operation itself) remains at 4.2%. For comparative evaluation of modern C. section methods, the above-mentioned collective statistics by Winter is most suitable, as it covers a huge number of operations performed by a large number of operators during one last year in one country. According to this statistics, intraperitoneal corporal C. section, performed 438 times, gave mortality of 6.4%; intraperitoneal cervical C. section, performed 3,554 times, gave 3.7%; extraperitoneal C. section, performed 304 times, gave 6.7%, and the Porro operation, applied in 120 cases, gave 6.7% mortality. To evaluate the overall results of C. section under modern conditions, it is necessary to consider the outcome of the operation not only for the mother but also for the fetus, since the expansion of the scope of application of C. section, leading to the performance of this operation not only for absolute but also for relative indications, makes the birth of a living child an indispensable condition, for which the woman agrees to expose herself to the known risks of the operation. In general, the results of C. section in relation to fetuses are relatively good, although their mortality rate fluctuates within rather wide limits: from 0.9% (Leopold) to 16.0% (Frigyesi), averaging 5% in classical C. section (van der Hoeven). According to Winter's statistics, mortality "33
The rate of cesarean sections in children was 5.1%. According to Ilkevich, Levi, and Selitsky, the total loss in children at birth among 743 parturients was 4.5%. Of those born alive, 5.9% died shortly after birth; thus, according to this statistic, the total loss in children during cesarean section was 10.4%. Most statistics show the highest surgical and postoperative infant mortality in cases of placenta praevia and eclampsia, which must be associated with the main complication that indicated the need for cesarean section. The frequency of cesarean sections continuously increased along with improved results. In Russia, according to Ponomarev, cesarean sections were performed 1,010 times over 186 years, of which 21 times in the pre-antiseptic period (before 1880), 61 times during the decade 1881-90, 125 times during 1891-1900, and 598 times from the beginning of the 20th century to 1918. In the Kazan clinic (Gruzdev and Timofeev), the number of cesarean sections from 1900 to 1914/15 was only 0.22%. While in 1921 in Moscow (Ilkevich, Levi, and Selitsky) only 10 cesarean sections were performed per 36,000 births, which is 0.27%, their number in 1927 reached 233 per 53,000 births, which is 4.4 per 1,000. According to Gorizontov in the Tomsk clinic, the percentage of cesarean sections reaches 2. In the Leipzig clinic, cesarean sections were performed 236 times per 7,070 births (3.3%; Schweizer, 1927). According to Mosher, in different places in America the frequency of cesarean sections in 1925 varied greatly: while in Massachusetts in 1922 one cesarean section occurred per 78 births, in 1925 the frequency of cesarean sections was 1 per 46 births. In some states, 1 cesarean section occurred per 861 case of birth. The indications for cesarean section are divided into absolute and relative. The establishment of indications for cesarean section always depended on the degree of danger that the operation represented at that particular time. In ancient times, cesarean section could only be performed on a dead woman. In the 17th century and the first half of the 18th century, the risk of operating on a living woman was still so great that cesarean section could only be undertaken in cases of absolute impossibility of any other resolution of labor. Such an absolute indication for cesarean section is usually significant degrees of narrowing of the bony pelvis, when it is impossible to perform embryotomy and extract the fetus even in parts per vias naturales. In numerical terms, the degree of narrowing of the bony pelvis that gives an absolute indication for cesarean section was usually determined by the length of the conjugata verae at 4.5 cm (John Burns), 5 cm (Fritsch), 5.5 cm (Bumm), 6 cm (Chrobak), 6.5 cm (Scanzoni, Schröder, P. Müller, Schauta), 6.7 cm (J. L. Baudelocque). In addition to deformities of the pelvis, an absolute indication for cesarean section was also the presence of tumors obstructing the pelvic outlet. It appears very difficult to precisely formulate relative indications for cesarean section. In a narrow pelvis, such an indication exists according to Bentin's definition when measurement of the pelvis reveals impossibility or small probability of a live birth per vias naturales or when with slight narrowing of the pelvis birth of a live
In the 34th week of pregnancy, this cannot be achieved with certainty by any other method. The mother's strong desire to have a living child is in modern obstetrics a conditio sine qua non for establishing a relative indication for C. s. Since the course of labor in a narrow pelvis depends not only on the size of the latter but also on many other causes, such as the configurability of the fetal head, the quality of labor contractions, etc., the indication for C. s., if it is only relative, can be conscientiously established only during the labor itself. Therefore, special caution is required when establishing a relative indication for C. s. in primiparas. In multiparas, in whom previous pregnancies, despite proper management, ended each time with the birth of a dead fetus, C. s. is the method of choice even with minor degrees of pelvic narrowing. Purely anatomical assessment of the pelvis is in practice less valuable than was previously thought. Functional assessment of the pelvis is given by the pressing down of the head according to Müller with control per rectum and determination of the engagement or non-engagement of the head into the pelvis after 10-12 hours of good labor activity after the waters have broken (Genter). According to Palmov, with a conjugata vera greater than 7.5 cm, C. s. (transperitoneal cervical) is indicated only after a certain waiting period in those cases where in the second stage, with good labor activity for 3-4 hours, the head does not engage in the inlet, when signs of stretching of the lower segment of the uterus appear, when fetal asphyxia occurs. An essential condition is the mother's strong desire to have a living child. Other indications for C. s. for modern obstetricians are mainly eclampsia, placenta previa and its premature separation, tumors of the soft parts of the birth canal, and scarred narrowing of the cervical canal and sleeve, which do not allow the birth of a living full-term fetus. The frequency of application of C. s. in eclampsia varies greatly in various obstetric institutions. Thus, in the Zurich clinic of Waltgard, C. s. was used (according to Bentin) in all cases of eclampsia both during labor and during pregnancy, and gave 15% maternal mortality and 6.45% child mortality. Holland and Eardly obtained 32% maternal and child mortality. Based on the material of Ilkevich, Levi and Selitsky, C. s. in eclampsia was performed in 107 cases, which is 14.2% in relation to the total number of C. s. Grudzev and Timofeev immediately resort to C. s. in eclampsia, but only in the most severe cases. In placenta previa, C. s. (according to Bentin) gives particularly good results for children. Thus, in pi. praevia totalis et lateralis, which gives 6% maternal mortality, child mortality with combined version is 80-90% and with met-reversion 30-40%; when C. s. is applied, however, the total mortality (according to Hitschmann) is 3.6%. The statistics of individual authors are even more favorable: e.g., in Steckel's 31 cases, there was 0% child mortality and 3.22% maternal mortality, in Pankow's 23 cases with 0% maternal mortality and 5.26% child mortality. In the USSR, for the application of C. s. in pi. praevia under certain indications, Parishchev, Skrobansky, Markovsky, Struganov, Palmov and others spoke out. In general, however, views on the indication for C. s. in pi. praevia are often diametrically opposed. On the above material of Moscow maternity hospitals, on average the percentage of indication for C. s. in pi. praevia is 17.1. The indication for C. s. in pi. praevia is most often given, according to Franz's opinion, in primiparas with a mature fetus. According to Grudzev, the decisive factor in establishing the indication for C. s. in pi. praevia is not so much the form of previa as the strength and danger of bleeding and the anatomical condition from the side of the uterine cervix. Besides the above-mentioned rarer indications for C. s. were: cancer of the cervix, in which in operable cases C. s. is accompanied by extended extirpation of the uterus, heart defects with signs of decompensation, significant development of varicose nodes in the vagina and on the external genital organs, acute edema or extensive condylomas of the vulva, intraperitoneal bleeding from the pregnant uterus, threatening rupture of the uterus with developmental defects and other defects of this organ, previously unfavorable for labor fixation of the uterus, transverse position of the fetus, prolapse of the pulsating umbilical cord, brow presentations, prolonged labor despite strong contractions in elderly primiparas with rigid tissues, etc. Although the list of indications presented to the published cases of C. s. in the literature to a large extent bears the character of casuistry, nevertheless it is evident that according to the modern trend prevailing in obstetrics, any serious deviation in the course of pregnancy and labor can give an indication for the performance of C. s., and in some cases the indications are even preventive. The limits of application of C. s. are inextricably linked to the question of how far the performance of the operation in each individual case satisfies certain conditions. As a condition for performing C. s., the majority of authors require the presence of a living fetus. With a dead or non-viable fetus, C. s. is permissible only in the absolute impossibility of delivery per vias naturales even by embryotomy: with an absolutely narrowed pelvis, obstructing tumors, in far advanced cases of cancer. According to Ponomarev's data on 805 cases of C. s. in the USSR, the operation with a known dead fetus was performed 44 times (5.4%). In the USSR-Grammatikati, in Germany-Kerner (Körpeg) and others, did not consider the life of the fetus a necessary condition and performed C. s. with a dead fetus on account of neglected transverse position. Among other conditions, the absence of any signs of septic infection played a prominent role in former times and to a certain extent at present; some authors, among such conditions, also listed the presence of an intact fetal sac and non-use of vaginal examination of the parturient. Modern modifications of C. s., especially cervical C. s., the operation of Port and others, allow expanding the scope of the operation both in terms of indications and in terms of conditions. According to Vocht's report on 76 'unclean' cases (12 were infected), operated on by various authors, only two patients died. According to Frey's report, in the Waltgard clinic 200 cases of C. s., among which there were also feverish ones, gave a total of 5% maternal mortality. Küstner on 110 cases of extraperitoneal C. s., among which 25% were infected, had not a single case of death from sepsis. Shevaldysh reports favorable results when using C. s. in infected cases. Other statistics show the opposite: thus, according to Winter's collective statistics for 1928, 4,304 non-feverish cases of C. s. gave 6.4%, and 146 feverish ones 27% maternal mortality. 25 infected cases from the material collected by Ilkevich, Levi and Selitsky gave 84% morbidity and 16% mortality. Bentin and others consider C. s. in infected cases contraindicated, despite all the successes of modern methods. According to Döderlein, many obstetricians consider it possible to perform C. s. even for relative indications at home. At present, the struggle between advocates of the expanded application of C. s. (a bright representative of this trend is Max Hirsch) and representatives of a more moderate trend continues. Against the observed in recent years enthusiasm for the operation of C. s. at the last All-Union Congress in 1928, Skrobansky, Solovyov and others spoke out, and at the last congress of German gynecologists-Winter. The choice of time for the operation plays a significantly smaller role. Performing the operation after the onset of labor activity with some dilation of the uterine opening is, in the opinion of many, a favorable factor: it facilitates the technique in the extraperitoneal method, reduces the danger of uterine atony and stagnation of lochia. In pi. praevia and eclampsia, the majority, on the contrary, apply early operation. In general, the time of performance has no significant influence on the outcome of the operation. Death and agony of the mother now serve, as in ancient times, as an indication for the performance of C. s. On a dead woman, the operation is performed without any preparations and consists of a simple incision of the abdominal wall and uterus. When performing C. s. on a dying woman, the same conditions must be observed as in the operation on a living one. The atonal condition of the mother and the viability of the fetus must be determined ex consilio. If operated within the first 20 minutes after the mother's death, about 60% of children can be saved (Linzenmeier). Of course, the cause of the mother's death plays an outstanding role in the prognosis for the child's life. According to Ponomarev, out of 122 C. s. on the dead, performed in Russia from 1759 to 1918, 18 living children were obtained (14.7%), and in the 19th century 82 operations were performed with living children in 2.4%, and in the 20th century-40 operations with 40% living children. Cesarean section on a dying woman was performed on this material 17 times with 9 living children, of which in the 19th century 5 operations with 20% and in the 20th century 12 operations with 66.6% living children. "Small" Cesarean Section is used with the aim of interrupting pregnancy in cases where, due to the late term (more than 3 months), pregnancy cannot be interrupted by a single method through curettage and other vaginal methods. The operation is especially appropriate when, along with interrupting pregnancy, it is also necessary to perform sterilization for medical indications. Indications for "small" Cesarean Section must be established strictly, as the method is not safe (in Genter's clinic, the mortality rate for 200 operations is 0.5%). Where sterilization is not needed, the competing method is kolpohysterotomia ant. (vaginal Cesarean Section).- The technique for performing "small" Cesarean Section is the same as that of ordinary abdominal Cesarean Section, with the only difference that the uterine cavity is emptied with a finger or curette. Winter reports on the primary results after vaginal Cesarean Section; during the period 1903-1922, the operation was performed in his clinic for pregnancies of not less than 8 months' duration-56 times. Of the 15 fatal cases, in only 3 cases was the operation itself the cause of death. Dürsen lost 6 out of 201 cases to infection, Döderlein- 2 out of 186 cases. On average, the primary mortality is 1%, and the morbidity is 15%. Among complications in Winter's material of 75 cases (this includes all cases of the operation, starting from the 5th month of pregnancy), there were ruptures of the uterine wall (8 times), damage to the bladder (4 times), and the rectum (1 time). Of the 57 children who were extracted by vaginal Cesarean Section, 30 were discharged healthy. Of the 27 who died, only 4 died because they were not extracted quickly enough. According to Zhmakin, based on Pisemsky's material of 45 cases, the following complications were encountered: 4 times bleeding (1 time from the incision, 3 due to atony), 2 times opening of the peritoneum. The danger of late complications is negligible. Zhmakin, among 22 cases followed by him for a period from 6 months to 14 years, observed 2 times deformation of the cervix and 2 times disruption of the menstrual cycle. Venator (1913) states that no one has yet observed a rupture of the scar in subsequent births. Selitsky in 1920 observed normal births (including two and three births) after previously performed vaginal Cesarean Section and presents a summary statistics (67 cases); Zhmakin in 1928-174 cases of pregnancy (of which 146 births and 28 abortions).- Vaginal Cesarean Section has a number of well-known advantages inherent in the vaginal method of surgical operations. The greatest development and spread of vaginal Cesarean Section occurred in 1905-12. In recent years, due to improvements introduced in the technique of abdominal Cesarean Section, vaginal Cesarean Section in many cases has begun to yield its successfully won positions to the abdominal method at the beginning of the so-called surgical direction in obstetrics. Nevertheless, to the present day, vaginal Cesarean Section is an operation that in many cases is life-saving for the mother (to a lesser extent-for the fetus) in a number of complications of the act of birth. Hysterotomia vaginalis is especially valuable in cases where it is necessary to perform a late abortion or premature births for serious indications. In 1928, Zhmakin collected 427 cases of vaginal Cesarean Section (of which 324 cases were not published anywhere), performed by 26 famous Russian obstetricians. The main condition for the operation is appropriate hospital conditions and, above all, the experience of the operator in vaginal methods of surgery.
Related articles
Mentioned in
Cite this page
“Cesarean Section.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/cesarean-section/