Maternity Hospital
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Soviet Great Medical Encyclopedia details the history and organization of maternity hospitals in Russia and the USSR. It discusses the transition from charitable institutions to modern inpatient obstetric facilities, comparing the organizational models of large maternity hospitals versus smaller maternity shelters.
Encyclopedia article (1928–1936)
MATERNITY HOSPITAL, maternity shelter, obstetric department of a hospital represent varieties of institutions intended for the provision of obstetric care (inpatient childbirth assistance). Inpatient childbirth assistance began to develop as the population concentrated and cities developed. In cities, there are all the conditions not only favorable for the emergence of these institutions but even urgently requiring the development of precisely the inpatient form of obstetric care. In former times, childbirth assistance institutions were regarded as purely charitable: their main purpose was the care of poor women in labor and especially those giving birth out of wedlock; at the present time, however, inpatient childbirth assistance constitutes an essential link in the entire chain of institutions for the protection of motherhood and infancy. Since childbirth assistance is a branch of preventive medicine, obstetric institutions have enormous general preventive significance (in addition to their special purpose). Obstetric institutions have been known for a long time. Public maternity wards existed in Egypt even in the times of the pharaohs. In Western Europe, the first childbirth assistance institutions appeared only at the beginning of the 18th century (in Strasbourg in 1728). In Russia, the first "maternity hospital" was opened in Moscow in 1764 (now the Clinic of Obstetrics and Women's Diseases of the State Scientific Institute for the Protection of Motherhood and Infancy named after Lebedeva), and in St. Petersburg in 1771 at foundling homes. In 1797, the Midwifery Institute (now the Central Scientific Research Institute of Obstetrics and Gynecology) arose, initially with only 20 beds. The Midwifery Institute in Moscow was founded on November 8, 1800, and opened on January 1, 1801, with 3 beds for women in labor. In 1822, the number of beds was increased to 6 with a total number of 159 births. In 1846, an obstetric clinic with 16 beds was opened on Rozhdestvenka in Moscow. Women in labor were admitted directly from the street into the delivery room, where they were undressed and bathed. They gave birth on a leather sofa covered with an ox hide, which was washed daily and greased with tallow or oil for softness. Doctors and midwives were on duty in frock coats and dresses. The contingent of women in labor consisted of serf soldiers' wives, "household maids," and rarely "noblewomen," i.e., daughters of ruined petty gentry, whose children, on an equal basis with others, were sent to the Foundling Home. Mothers were discharged on the 3rd–5th day. Maternal morbidity reached up to 30%, mortality up to 3%. During developing epidemics of puerperal fever, the clinic was closed; for the summer time, it was always closed for 3–4 months (Pobedinsky). In Kharkov, the first clinic was established in 1829 with 4 beds; in Kazan in 1844 with 14; in Kiev in 1844 with 8 beds. In 1892, according to Grebenshchikov, there were already 10 government maternity hospitals in Russia (3 in St. Petersburg, one each in Astrakhan, Warsaw, Grodno, Mogilev, Moscow, Oranienbaum, Tiflis), 27 municipal ones (10 in St. Petersburg, 7 in Moscow, 6 in Warsaw, one each in Astrakhan, Kineshma, Nizhny Novgorod, Saratov), 5 zemstvo ones, and several private ones (in various cities, not counting small maternity wards at some hospitals and obstetric clinics at medical faculties). In their development, obstetric institutions differentiated into the following main types: maternity hospitals, maternity shelters, and maternity wards. In the largest centers of the USSR—Leningrad and Moscow—inpatient childbirth assistance developed in two different ways: in Moscow—by the type of large maternity hospitals, in Leningrad—by the type of small maternity shelters. Both forms have their advantages and disadvantages. The main ones are as follows. The advantages of maternity hospitals: 1) in a large maternity hospital, a doctor is constantly on duty; this makes it possible to quickly provide assistance in urgent cases; 2) the presence of several doctors allows for the performance of major operations at any moment, for example, laparotomy; 3) the possib
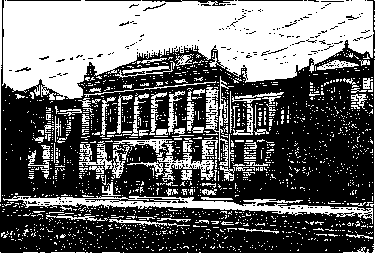
Figure 1. State Central Scientific Research Institute of Obstetrics and Gynecology (Leningrad).
on proper isolation of sick and especially septic mothers. All this is less ensured in small maternity shelters. Furthermore, in several small maternity shelters taken together, there are generally more refusals of admission than if they were combined into one maternity hospital. The main advantages of maternity shelters are the bringing of inpatient childbirth assistance closer to the population due to the reduction of the radius of the served area (given the presence of several maternity shelters instead of one large maternity hospital). With 19 maternity shelters and 6 other maternity institutions in Leningrad in 1916, there were 3.1 km2 per each maternity institution. According to Rutkovsky, in 1909, 508 women in labor were admitted from a distance of 1 verst, and from a distance of 1–2 versts only 146, with 81 of them having sought and not found shelter in other institutions. It goes without saying that the proximity of maternity shelters to the population is conditioned by their correct placement in the city. Furthermore, the cost of maintaining a bed in a maternity shelter is lower (according to pre-war data), and maternal morbidity and mortality in them are lower; however, this latter point is debatable in view of the fact that maternity shelters usually refer all complex and severe cases to maternity hospitals. Recently, in Leningrad (as earlier in Moscow) and in other large centers, there is a tendency toward the organization of large maternity hospitals. In small cities, maternity institutions at hospitals represent more or less separate departments of them. In recent years, in medium-sized cities, in connection with the significant expansion of obstetric care and the concentration of gynecological care in one place, a tendency has increasingly begun to be implemented toward moving maternity wards out of hospitals into special premises. Obstetric-gynecological clinics, of course, always have sufficiently isolated obstetric departments. The Central Scientific Research Institute of Obstetrics and Gynecology in Leningrad originated from the Midwifery Institute founded in 1797 (see above). In 1904, on the initiative of Prof. D. O. Ott, a huge, luxurious 3-story stone building for 208 beds (of which 25 for septic patients) was built by the architect Benois. The area of the building is 10,656 m2 with a volume of 160,845 m3. The cost of the entire construction with equipment was 3,500,000 rubles (Fig. 1). The building was constructed according to the latest word in science and technology. The general plan and all details were discussed in advance by both Russian and Western European medical and technical institutions. On the 1st floor are premises for the outpatient clinic, pharmacy, offices, and apartments for the staff; the 2nd and 3rd floors are occupied by obstetric and gynecological departments, a museum, library, auditoriums, and laboratories (Figs. 2 and 3). The main features of the new building are: the absence of poorly lit daytime places; large and bright corridors with wards only on one side; large bright operating rooms; beautifully equip
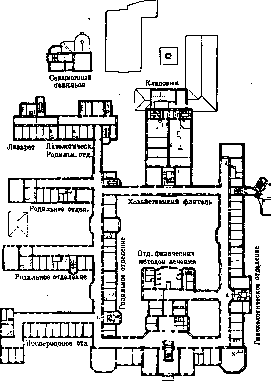
Scientific-Educational Wing Figure 2. Plan of the 1st floor: L-elevators for patients; I-hoisting machines; S-steam sterilizers; P-apparatus for physiological solution.
ped auxiliary institutions (library, museum, laboratories). Ventilation is designed with the calculation of supplying 85,624 m3 per hour of filtered, heated, and humidified air through easily washable and daylight-lit channels. It has its own electrical, water supply, and ice-making stations, sewage system, mechanized laundry, disinfection chamber, bakery, and a central station for controlling heating and ventilation with all necessary control instruments (thermometers, manometers, hygrometers, rheostats, etc.). Wide use of electrical energy for signaling and general and from wards (for calling nurses to patients). Systems of internal telephones and microphones: 1) for signaling
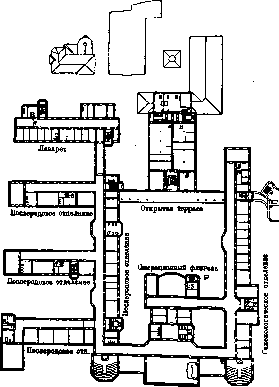
Scientific-Educational Wing Figure 3. Plan of the 3rd floor:- B-hoisting machines; S-steam sterilizers; P-apparatus for physiological solution.
regarding limit temperatures in the premises, the state of heating appliances, the temperature and pressure of hot-water boilers serving heating and ventilation; 2) for apparatuses for monitoring employees at their posts; and 3) for regulating the operation of 153 wall clocks. The obstetric department has 147 beds. Its features consist of 2 delivery pavilions working alternately. The throughput of the obstetric department is 3,000-4,500 births per year. The new women's clinic of Prof. Sellheim in Leipzig. A 5-story building in the shape of an elongated letter P. Wards with patients occupy 17% of the premises. Relatively low ceilings—3.5 m (easily accessible for cleaning). There are no bells. Electric signaling: a button is installed at each bed, upon pressing which a bright electric light turns on in the corridor above the ward door and under the clocks hanging everywhere in the corridor, and in the nurse's room (with sound-dampening walls) a control bell begins to ring. For calling the director by telephone, yellow lights turn on everywhere; for the on-duty doctor, red lights. The obstetric department has 104 beds; the infirmary has 48 beds (together with cancer patients). The principle of small wards—6-8 lying-in women in each. The delivery department has 6 delivery rooms with 2 delivery beds in each. The walls and doors are made using a sound-dampening method so that the cries of the women in labor do not reach neighboring rooms. The delivery rooms are located on 2 floors—3 on each—and communicate with each other by a small internal staircase for medical personnel. The delivery rooms and rooms for on-duty staff are connected to each other by a special telephone and light signaling. The walls are painted a dark gray-blue color, the operating room—a dark gray-green. The septic department has its own large operating room, dressing room, and its own delivery room, equipped the same as in the clean department mentioned above. On the top floor is a department for 40 women in the final months of pregnancy who do not have housing in the city and who are taken from the street; they receive free board, clothing, and everything necessary, help with the care of patients, work in the kitchen, and thus work off their stay during pregnancy, childbirth, and the postpartum period (as in the Maternity Hospital in Charlottenburg). In contrast to German clinics, where obstetric institutions are often merely departments of them, in France, Maternity Hospitals predominate, in view of the fact that obstetrics there is completely separated from gynecology, which is treated as a special department of surgery. A model of simplicity and practicality of design can be the Maternite de l'Hopital St.-Antoine in Paris, opened in 1897. The general plan is depicted in Fig. 4. The Maternity Hospital has 70 beds in the aseptic and 8 in the isolation department. It consists of a main building in the shape of a quadrangle 58 m wide and 69 m long, in the center of which is a small garden with an area of 1,300 m2. Separately, there is an isolation wing and a machine room with laboratories. The total area of the main building is 2,602 m2. The delivery room has 4 beds. Its dimensions: 8.90 x 9.67, height 4.80 m. Throughput is up to 2,000 births per year. The isolation department is located in a separate building, has its own operating room and auxiliary premises, separate personnel, and a household section. At the present time, a typical Maternity Hospital includes the following departments: admission ward, department for pregnant women, delivery department (delivery room) with an operating room, postpartum, suspicious, septic, for newborns, and a consultation center with a milk kitchen. In most Maternity Hospitals (excluding France), there are at least small gynecological departments. Admission ward. In new and well-appointed Maternity Hospitals and clinics, as can be seen from the descriptions, the admission ward consists of at least 3 rooms. In the waiting room, a preliminary interview, temperature measurement, and general examination of the women in labor take place. From the waiting room, they are directed either to the clean obstetric department, or to the suspicious, or to the septic one. Into the clean obstetric department, the woman in labor passes through a "processing room," consisting of 2 rooms: in the 1st, registration takes place, the woman in labor undresses, and from this room, the dress and linen are passed through a separate door or window for storage and to the sterilization room, if one is equipped. Here, or better in a separate room, the woman in labor receives an enema and is washed under a shower; in the next room, her hair is shaved off
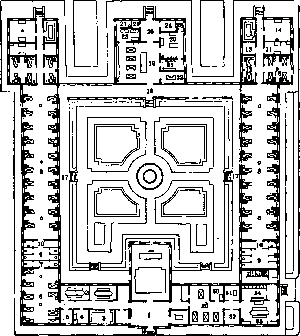
Figure 4. Plan of the St.-Antoine Maternity Hospital in Paris: 1-vestibule; 2-7-department for pregnant women; 8-16-postpartum department; 17-open gallery; 18-closed veranda; 19-28-delivery department with reception; 29-34-consultation center; 35-39-isolation department (separate building).
on the external genital organs and their disinfection is performed. Then she puts on hospital linen and is directed to the delivery room. Furnishings of the admission ward: in the waiting room—sofas, a couch, chairs, a table, and a small cabinet or box for cards and reference records. In the processing room: a table for registration and receiving items; in this same or the next room, a well-equipped restroom, a bathtub (with a shower, cold and hot water); in the 3rd room: a gynecological table, a washbasin, a small cabinet, a table for necessary medicines and dressing

Figure 5. Delivery room of the Central Scientific Research Institute of Obstetrics and Gynecology.
material, brushes, instruments, items for care and processing of the patient, and a stand with an Esmarch irrigator. The delivery department in small and old maternity hospitals represents a small room with several delivery beds (Fig. 5) and washbasins (with cold and hot water), tables for records and storage of birth charts, for care items, and a small cabinet for medicines. The calculation of beds for the delivery department is 10-12 per 100 postpartum beds. In most new obstetric clinics, besides one large delivery room, there are 1-3 small ones for 1 bed for eclamptic patients and for pathological births in general. In new maternity hospitals, the delivery ward sometimes consists of small separate wards for 1 bed, in which women in labor stay until the beginning of the expulsive stage and only with the beginning of the latter are transferred to the general delivery hall. Delivery rooms must have good natural and artificial lighting. Approximately to a height of 1 1/2 m from the floor, they are tiled or painted with oil paint. The traditional white color in delivery wards and operating rooms has recently been yielding to gray-blue or gray-green, which are not tiring for the eyes. An essential part of the delivery ward is the delivery bed, which is often also an operating table (for bringing down a leg, extracting the fetus, suturing the perineum, and even applying forceps; all this, however, is better performed in the operating room). In most cases, delivery beds are somewhat more massive and higher than ordinary ones. In the Snegirev Maternity Hospital, the height of the bed is 1 m, and the partition at the foot end is removed. Prof. Ott's bed is on wheels
in it. Delivery
beds; at its foot end, there is a metal stand with an electric light bulb and sockets for an Esmarch irrigator, a small glass for a thermometer, and nozzles; in addition, a retractable (on a hinge) metal circle at the leg of the bed for a bedpan. The height of the bed is 0.67 m, width—0.75 m (Fig. 6). Rakhmanov's bed (Figs. 7 and 8): length in the extended state—1.75 m, width—0.62 m, and height—0.77 m. It consists of 2 halves. It can easily be converted into an operating table by extending the foot end of the bed on wheels. Leg holders are attached to the foot end. Of the instruments, as well as items of medical care for the delivery room, the following are necessary: metal and rubber catheters, umbilical and straight scissors, a pelvimeter, a centimeter tape, an obstetric and ordinary stethoscope, a razor, a scalpel, a spatula, a nail cleaner, nail scissors, a mask with a dropper for chloroform, a mouth gag, a tongue
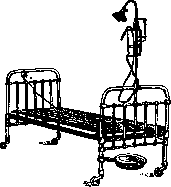
Figure 6. Ott's delivery bed.
holder, a rubber wedge for protection against tongue biting in eclamptic patients, and devices for washing hands (brushes, soap dish, etc.). The delivery ward includes an operating room [usually in a Maternity Hospital there are two: a small
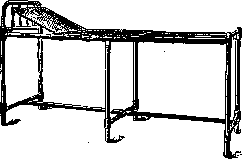
Figure 7. Rakhmanov's delivery bed.
for small, more frequent obstetric operations (suturing the perineum, manual extraction, forceps)—and a large one—for laparotomies (Fig. 9)]. A feature of the obstetric operating room is special instrumentation in addition to the usual instruments for laparotomy (see Obstetric instrumentation). Postpartum department. For the purpose of better service, it is more advantageous to have large wards for 10-20 beds, corresponding to approximately the same number of women discharged daily. In the St.-Antoine hospital, the postpartum wards for 20 beds do not have a corridor, and the lying-in women are therefore under the constant supervision of the on-duty personnel located right here (Fig. 10). Children are placed in these wards around large tables in the middle; small wards—for 2-4 beds—are of course also necessary for the isolation of eclamptic patients, lying-in women after operations, and those with complications in the postpartum period (of a non-infectious nature).
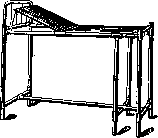
Figure 8. Rakhmanov's delivery bed.

Figure 9. Obstetric operating room of the Vienna clinic.
The calculation of area and volume for the postnatal ward is conducted according to standard hospital norms. An essential component of the postnatal ward is the dressing room, equipped like a small operating room, but with a relatively small number of instruments, mainly long and short forceps, pointed scissors with short and long blades for removing sutures, spoon-shaped mirrors, retractors, lateral mirrors (when examination is necessary), catheters and nozzles for douching. A room for washing rubber sheets is also necessary; sometimes swaddling of infants is also done there (Fig. 11). With the allocation of space for newborns, swaddling and washing of infants is done in the children's room. In many normal postnatal wards in the USSR, so-called

Figure 10. Postnatal ward of the St.-Antoine maternity hospital in Paris.
doubtful wards are allocated for maternity patients suspected of infection. For such cases, each maternity hospital should have an isolated doubtful ward with its own processing room, delivery room, and small rooms for 1-2 beds, served by separate staff. In many maternity hospitals, both in our country and abroad, the arrangement of postnatal wards is adopted, as little as possible resembling a hospital. Beds here can be of the standard type. It is desirable to have a nest at the bottom for a bedpan. The peace that a maternity patient requires makes it

Figure 11. Room for washing rubber sheets and swaddling infants at the TsNIAGI.
necessary to pay special attention to the design of the spring mesh and mattress. At TsNIAGI, since its founding, a mattress designed by Prof. Otto with partitions in an accordion shape has been adopted; individual compartments are filled with hair twisted on a stick (Fig. 12). Bedside tables should be as simple as possible. In foreign maternity hospitals, necessary items for caring for maternity patients are placed on the two lower shelves. For cleaning maternity patients, in well-equipped maternity hospitals, there are mobile tables conveniently arranged to hold everything necessary: cups, vessels with boiled water and solutions, instruments (forceps, specula), compartments 1) for cups, 2) boxes with dressing materials and 3) necessary medicines. Where individual cleaning is strictly carried out, each maternity patient has her own Esmarch's cup,

Fig. 12. Postnatal bed mattress by Otto. nozzle, catheter, dressing material, and, most importantly, a separate bedpan. Isolation ward (lazaret, septic ward). In most foreign obstetric institutions, the isolation ward is located in a separate building and has its own delivery room, operating room, kitchen,


Isolation ward. Laundry and separate staff. Sometimes in the same building as maternity patients, gynecological and even cancer patients are accommodated (Vienna clinic and clinic of Selgeim in Leipzig). However, it is fundamentally important that the isolation ward must have a separate entrance and by no means communicate with the clean obstetric ward. The need for lazaret beds is calculated on average at 15-20 beds per 100 clean postnatal beds (Poltavtsev). Assuming that the percentage of feverish patients averages 10, one can limit oneself to 5-10 beds per 100 if a doubtful ward is available. The isolation ward is arranged with the same components as the clean obstetric ward. In smaller maternity institutions, however, they limit themselves to arranging the so-called doubtful delivery room and a ward for feverish maternity patients. The isolation ward of the Vienna clinic with 36 beds is located in a two-story building: the first floor for obstetric cases, the second for gynecological and in particular cancer patients. Each floor has a separate operating room, laboratory, bathroom, buffet room, and room for orderlies. The plan of the isolation ward of the St.-Antoine hospital - see Figure 13. The TsNIAGI lazaret is located in two floors of a wing, separated from the clean obstetric premises by a long and narrow corridor illuminated on both sides Figure 13. Plan of the isolation ward of the St.-Antoine maternity hospital in Paris: 1-washroom; 2 and 3-toilet; 4-wards; 5-service room; 6-room for midwives; 7-room for nurses; 8-operating room.

Figure 14. Infant bed of the St.-Antoine maternity hospital in Paris.
sides; it also has a separate entrance from the courtyard. In one floor is located the delivery lazaret - operating room and 3 delivery rooms with 2 beds each, 1 room for the duty midwife, 1 for duty students. The other half of the floor and the entire upper floor constitute the postnatal lazaret, 14 wards with 2 beds each, with a dressing room, bathrooms, buffet rooms, linen rooms, and supply rooms, one of each per floor. The arrangement of small rooms for 1-2 beds is advantageous for more convenient sorting of patients. From small maternity departments of provincial hospitals, sick maternity patients are isolated in gynecological or therapeutic departments. The isolation ward should, as a rule, be served by completely separate staff from the very beginning of admission of parturients even from the waiting room. In order to protect clean obstetric departments from infection, as well as for better service of sick patients t and for the sake of economy, in some large cities there is now a tendency to concentrate all septic maternity patients in separate large institutions (Moscow, Kharkov, Berlin). Department for newborns. The separation of newborns from mothers is practiced in our country only in recent years; therefore, in many existing maternity institutions, there are not yet specially arranged rooms for newborns. It is necessary to have at least 2 rooms: one for healthy infants, another for sick infants, preferably with boxes for isolation of various diseases. At TsNIAGI, 4 rooms are allocated for newborns: 1) sorting room, 2) for healthy infants, 3) for sick infants and 4) for healthy infants from sick mothers. Infant cribs are usually arranged with high sides (Fig. 14). Necessary equipment for the newborn department are changing tables (Fig. 15), a table and cabinet for necessary medicines and care items, scales for weighing, and a washbasin with cold and warm water complete the furnishings of the newborn room. Department for pregnant women. The arrangement of these departments pursues various purposes. In many maternity hospitals in Germany and France, these departments are, strictly speaking, boarding houses for poor pregnant women, who, receiving full board in the institution, at the same time perform light work in the kitchen, in
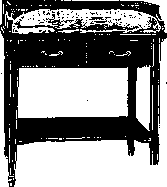
Figure 15. Changing table of TsNIAGI.
laundry, as well as for care of patients and thus work off their keep in the maternity hospital. In the USSR, pregnant women with various deviations from the normal course of pregnancy are admitted to these departments—both those depending directly on the pregnancy itself (e.g., toxicoses, abnormalities of the ovum or fetus—incorrect positions, placenta praevia) and those with conditions that existed before pregnancy—tuberculosis, heart defects, chronic nephritis, etc. In general, all pathology of pregnancy is subject to hospitalization, including pregnant women with a narrow pelvis, especially where the possibility of performing a cesarean section can be anticipated. Pregnant women living far from an obstetric institution are admitted to the maternity ward to avoid the chance of emergency labor. The department for pregnant women, besides its profound preventive significance, also has important educational value. Hygienic regimen during pregnancy is more easily grasped in practice and better put into effect through living example than through instructions. Early admission to this department sometimes saves from excessive household burden. There are no definite guidelines for establishing the necessary number of beds in such departments. For example, in the Vienna clinic, out of 232 beds, 48 are for pregnant women (approx. 20%), in the TsNIAI-20 out of 110 obstetric clean beds (+ 30 isolation beds), in the St.-Antoine hospital—9 out of 78 obstetric beds, in the clinic of Zelgeim—40 beds out of 104 obstetric (48 isolation), etc. Levi calculates the number of beds for pathological pregnancy as 6% of normal postpartum beds. Besides wards in the department for pregnant women, the following are desirable: examination room, bathroom, isolation room, buffet, and dining room. The equipment for the pregnant women's department is usually as follows: pelvimeter, centimeter tape, scales, height gauge, blood pressure measuring apparatus, obstetric and ordinary stethoscopes, stand with Esmarch's bottle and nozzles, catheters, spoon-shaped mirrors, specula, forceps, scissors, Esbach's test tubes, graduated cups for measuring urine quantity, 1-2-10 cc syringes, and examination table. The atmosphere of the department for pregnant women should in no way resemble a hospital. It is necessary to organize sanitary education (lectures, provision of literature, setting up of a red corner). Stay in the department for pregnant women is diversified by non-taxing activities, partly of a hospital nature (preparation of dressing materials). A separate medical staff for healthy pregnant women is not strictly required. They are usually served by doctors working in the obstetric department. From the middle staff in the prenatal clinic of TsNIAI for 20 pregnant women (in the vast majority pathological), 2 midwives and 5 nurses work. Due to the lack of beds for stationary obstetric care, the distance and transportation difficulties at many maternity hospitals and clinics abroad (and with us earlier, e.g., in TsNIAI), obstetric polyclinics have been organized. (Doctors and midwives, along with interns, go out from the maternity hospital on call to provide obstetric assistance at home; in severe cases, the parturient is brought to the clinic.) Obstetric polyclinics in the West are organized on the principle of self-support and usually for insured persons, for whom the insurance fund pays. The improvement of emergency care organization in our USSR has eliminated the need for obstetric polyclinics. The maternity hospital is in direct connection within the chain of institutions of the okhranmatmater with: 1) consultation (see) for women, 2) consultation (see) for infants, and 3) milk kitchen (see). The preventive significance of the maternity hospital is not limited only to the direct prevention of complications of the act of labor. Stationary obstetric institutions are the best practical school for instilling in the broad masses of the population sound concepts about pregnancy, childbirth, care of the lying-in woman and the newborn. Maternity shelters. In Leningrad, a type of normal 10-20-bed rural maternity shelter was developed. For this, the following requirements were considered necessary: a normal 20-bed shelter (figs. 16 and 17) should have an area of 560 m² and a volume of 1,900 m³ with a height of 3.4 m. Of these, 225 m² are household premises and 335 m² are hospital premises (ratio 2:3). Of the hospital premises, 215 m² are occupied by wards and 120 m² by other hospital premises: reception, examination room, processing room, delivery room, operating room (ratio 1.8:1). Of the 225 m² of household premises, 140 m² are allocated for apartments of midwives and nurses. In round numbers: hospital department 5/6 of the total premises, household premises—1/6. Here, wards—3/5, examination room and others—1/5 for staff and
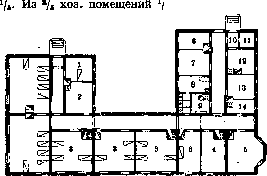
Figure 17. Plan of a 10-20 bed rural maternity shelter: 1-isolation room; 2-midwife's room; 3-wards; 4-delivery room; 5-operating room; 6-linen room; 7-examination room; 8-bathroom; 9-toilet; 10-entrance hall; 11-storage room; 12-kitchen; 13-nurses' room; 14-sterilization room. V5 for kitchen, linen room and other utility rooms. Type of normal 30-bed shelter: area 825 m2, height slightly less than 4 m. Area of hospital premises 500 m2, area of wards 300 m2 with air volume 1,200 m3. Thus per 1 bed there are 10 m2 of area (according to Poltavtsev-9-11.5 ft2) and 40 m3 of air (according to Poltavtsev-30-35 m3). Area of utility rooms-325 m2. Obstetric departments of large clinics by their nature approximate to maternity hospitals, while small obstetric departments of hospitals are similar to maternity shelters. In the latter, it is necessary to observe the imperative rule (from which, unfortunately, deviations are often observed), namely-the obstetric department should not communicate with other departments, should have a separate entrance, special personnel and its own linen. Isolation of sick parturients is usually done by transferring them to the gynecological or therapeutic department. Personnel of maternity hospitals. Calculation of the required number of personnel, with observance of all labor norms, is extremely difficult due to the necessity of constant duty in the delivery department of at least 2 doctors, in order to be able to organize the necessary operative assistance. Often in large maternity hospitals more than 2 doctors are on duty simultaneously, and 1 or 2 permanent staff are joined by non-permanent staff. Non-permanent doctors are on duty for the purpose of improvement. This explains the surprisingly small permanent staff in many maternity hospitals abroad. According to the circular of the People's Commissariat of Health of 30/IX 1929, in maternity hospitals and delivery departments there should be per 1 doctor 35 beds, per 1 member of middle and junior staff-8, not counting the house sister for 40-50 beds and for each department 1 sanitary attendant in the bathroom, 1 at the buffet, cleaners and special personnel for the operating room. For the children's room-1 doctor per 40-50 beds and 1 sister per 12 beds during the day and 20 at night. In most maternity hospitals 12-hour duty is established. Middle and junior staff in the USSR are on duty according to labor norms. In large maternity hospitals doctors conduct deliveries in primiparas and manage deliveries in pathological cases. Midwives conduct normal deliveries and assist in operative procedures. For delivery of infected parturients, separate junior and middle staff and a separate doctor from the team on duty in the clean delivery room are allocated. In severe cases other doctors are also involved. In many foreign clinics the septic department is completely isolated from the clean one. Separate personnel works in the postpartum clean department. The nature of work in maternity hospitals and maternity shelters of large cities differs. Pathological cases are usually concentrated in maternity hospitals. This was especially the case in former times, therefore morbidity and mortality in maternity hospitals were quite high. In the pre-antisepsis period maternity hospitals, especially those where teaching was conducted, were foci of terrible epidemics of puerperal fever. Mortality in them reached such limits that the question of their complete destruction was raised (Le Fort in France). With the introduction of antiseptics and asepsis the danger of infection decreased significantly, although it has not yet been completely eliminated to the present day. Due to the concentration of severe cases in maternity hospitals, operative activity in them is significantly higher than in maternity shelters; therefore a corresponding environment should be created for it. Already in the middle of the 19th century in the St. Petersburg obstetric clinic in 81/2 years for 543 deliveries forceps were applied in 30 cases (5.5%), version to feet-14 (2.6%), to breech-17 (3.1%), manual removal of placenta-26 (4.9%), perforation of head-2, embryotomy-2, cephalotribe-2, cesarean section for ectopic pregnancy-1, cesarean section on dead fetus-2, accouchement force-3 and artificial premature deliveries-1. After the introduction of antiseptics and asepsis, with improvement of operative technique, the so-called surgical direction in obstetrics developed, and the number of operative procedures (cesarean sections) increased significantly, especially in the USA. This in turn increased morbidity and mortality in maternity hospitals. According to Slavyansky's statistics for 1889 in St. Petersburg: Delivery institution Maternity mortality (in %) Non-maternity mortality (in%) In obstetric clinic of medical faculty . . Delivery institution with midwifery school Delivery institution without midwifery school Delivery department of hospital with midwifery 0.43 0.22 0.11 0.48 0.35 0.78 0.39 0.15 0.73 0.71 Delivery department of hospital without midwifery Morbidity in St. Petersburg for 1904-12. Disease In maternity shelter (in %) In St. Petersburg delivery institution (in %) Afebrile period Septic disease Fever without diagnosis . . Non-septic postpartum disease . . General diseases . . . 91.2 1.8 4.9 0.8 1.2 89.4 3.2 5.2 0.9 1.2 Similarly infant mortality due to the same conditions in maternity hospitals is somewhat higher: Born dead Born Institution living macerated unmacerated (in %) (in %) (in %) Maternity shelter . 96.6 1.9 1.5 St. Petersburg delivery institution . 95.5 4.5 Midwifery-gynecological institute 95.3 2.66 | 2.04 The role of maternity hospitals in training personnel. Maternity hospitals almost from their inception served as a school for training obstetricians and midwives both in Russia and abroad. Scientific research activity in maternity hospitals began in Moscow in the time of Richter the father, while in St. Petersburg in the Medico-Surgical Academy from 1848, when Kiter, a pupil of Pirogov, took over the obstetric chair (although pedagogical works and articles were published even before this). Subsequently many maternity hospitals and obstetric clinics became major scientific centers and produced dozens of scientific workers and hundreds of works on obstetrics.
Related articles
Mentioned in
Cite this page
“Maternity Hospital.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/maternity-hospital/