Postpartum Period
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
The postpartum period is defined as the time from delivery of the placenta until the completion of involution of the reproductive organs and other physiological changes that occurred during pregnancy. This article covers the physiology, postpartum hemorrhages, pathology, and postpartum psychoses.
Encyclopedia article (1928–1936)
POSTPARTUM PERIOD. Contents: I. Physiology...................53 II. Postpartum hemorrhages ..........541 III. Pathology of P. p.................555 IV. Postpartum psychoses ............580 Postpartum period - the time from the expulsion of the placenta until the completion of the processes of reverse development of the reproductive apparatus and those changes in the entire organism, in individual organs and tissues of the woman, which arose during pregnancy. I. Physiology. With the expulsion of the placenta, childbirth ends, and the parturient woman (woman in labor) becomes a puerpera. From this time, reverse development of the changes that occurred during pregnancy begins in her, proceeding at a rapid pace for the first 5-10 days (early P. p.), and then more slowly (late P. p.). On average

, 7 ' '

Figure 1. Genital tract of a recently delivered woman: 1-orifitium int. (contraction ring); 2-orifitium ext. (According to Bumm).
the duration of a normal P. p. is determined to be 40-55 days. Reverse development of the uterus. From the size of two fists, the uterus reduces to that of a small pear. In nursing women, the uterus becomes even smaller than normal. By weight, the uterus with 1 kg after birth decreases after 8 days to 72 kg,
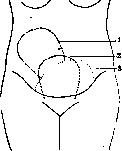
after another 8 days - to 73 kg; after 20 days - to 1/4 kg, and after 40 days - to 50-60 g (Bumm). The length of the uterine cavity, equal to 15 cm after birth, decreases daily by 0.3-0.5 cm and after 15 days reaches 10 cm. Further it decreases more slowly and reaches 7 cm in the remaining 25 days of P. p. The uterine cavity in the anterior-posterior section appears as a narrow slit (fig. 1) with an uneven and rough surface, especially on the placental site, which is 3-5 mm above the rest of the level.
The reduction of the uterus is determined by measuring its length and width through the abdominal coverings with a centimeter tape, a pelvimeter, or transverse fingers. According to Winkel's scheme, after childbirth, the fundus of the uterus is at the level of the navel, 24 hours later - above the navel, on the 2nd day - at the level of the navel, on the 3rd day - 1 transverse finger below the navel, on the 4th day - 2-3 transverse fingers below the navel, on the 5th day - in the middle of the distance between the pubic symphysis and the navel, on the 6th day - 1-2 fingers below the middle, on the 7th - at 3 fingers, on the 8th - at 2 fingers above the pubic symphysis. After 10 days, the fundus of the uterus either completely disappears behind the pubic symphysis or only a small part of it can be palpated above the pubic symphysis (Fig. 2). The reverse development of the cervix occurs from inside to outside: the internal os closes first. 3 days after childbirth, it is passable only for 2 fingers, and after 10 days it is completely impassable or with difficulty passes 1 finger. The external os begins to close from the 15th day. Then the mucous plug described by Walthard is restored. (According to Bumm.) In the area of tears of the cervix, scars remain, by which and by the round shape of the os, former births are recognized. In the muscle fibers of the uterus, degenerative and atrophic changes occur, as a result of which the muscle fibers sharply decrease in size. As a result of such degenerative changes, muscle cells with a length of 208 μ and a width of 10.6 μ decrease by the 4th day after childbirth to 117 μ, and by the end of the 5th week have a length of 32.7 μ and a width of 6 μ (the size of a uterine muscle fiber outside of pregnancy: 24.4 μ in length and 5.1 μ in width). The blood vessels are completely obliterated in part, while their walls undergo degenerative changes, mainly hyalinization. The retraction of muscle fibers is accompanied by postpartum contractions, which are sometimes accompanied by severe pain in the first 3 days of the p.p. (especially in multiparous women). The peritoneal covering of the uterus, corresponding to its reduction, first forms folds, and then becomes smooth. The inner surface of the uterus after childbirth represents a continuous wound surface, the connective tissue base of the mucous membrane is exposed, while remnants of the epithelium are preserved only in the depth of the uterine glands. Healing occurs with the phenomena of small-cell infiltration (granulation tissue), as well as the disintegration and rejection of remnants of deciduous tissue. This is accompanied by postpartum discharges from the uterine cavity - lochia (see). The remnants of deciduous tissue in the area of leukocyte infiltration mostly undergo degeneration and disintegration, are resorbed and replaced by connective tissue elements, while some more deeply lying ones undergo reverse development and transform into cells of the regenerating uterine mucous membrane. From the remnants of the glands of the spongy layer, which approach each other with the reduction of the uterus, epithelial proliferation occurs; by amitotic division, epithelial cells form a new covering epithelium. By the 10th-12th day of the p.p., the inner surface of the uterus is covered with epithelium. At first, it does not yet have a normal structure; later, this provisional epithelium is replaced by the permanent method of degeneration and death of cells of the first generation and the proliferation of new ones from the aforementioned remnants of uterine glands. By the 20th day, the mucous membrane is restored. However, the complete regeneration of the endometrium and its restoration in a functional sense ends only after 40-50 days. The restoration of the mucous membrane at the site of the former attachment of the placenta occurs according to the same type, but may be delayed if the placental vessels close mainly by thrombosis rather than by the collapse of their walls. Then the thromboses formed go through all stages of organization until complete connective tissue transformation and for a long time remain the cause of the characteristic roughness of the surface in the area of placental attachment. The postpartum uterus has great mobility, lies in anteflexion-version and often deviates to the right due to the filling of the bladder and rectum. The fresh lochia excreted from the uterus have certain properties that inhibit the development of bacteria, after 24 hours they are already unquestionably only a nutrient medium and bacteria (Haskin) multiply abundantly in them, which are not limited to the vaginal cavity but also penetrate into the uterus and are observed there even in cases without fever. According to Mansfeld, on the 4th-5th day, the uterus contains embryos in 60% of cases and streptococci in 22.5%. According to Leiser, from the 2nd day of the p.p., they can already be found on the placental site. By the 15th day of a normal postpartum period, the uterus is freed from bacteria. They remain only in the vagina, where the restoration of the normal vaginal flora gradually occurs. The Fallopian tubes in the p.p. change from an oblique to a horizontal position. The same happens to the ovaries. The slight hyperemia that occurs during pregnancy passes. The reduction of the corpus luteum continues after childbirth. The reverse development of the ligamentous apparatus also consists in the partial degeneration of muscle fibers, as in the uterus, in the shortening of the ligaments, and in the reduction of hyperemia and tissue swelling. The reverse development of the vagina, introitus, perineum, and pelvic floor as a whole is expressed in the reduction of hyperemia. Tears of the mucous membrane heal by first intention or secondarily with the formation of scars, which are initially red and dense, then fade and become thinner. Excessively stretched vagina gradually narrows, becomes less flaccid and more elastic. In the p.p., it changes its shape: it remains more stretched in the transverse dimension; the lateral parts are more flattened; sometimes lateral depressions form (Gubarev's maternal depressions). The vaginal mucous membrane loses its rugosity to a significant extent. Multiple tears of the hymen heal with the formation of small scars. The remnants of it appear in a woman who has given birth in the form of small papillae (carunculae myrtiformes). As a result of scar contraction, a distinct narrowing corresponding to the hymenal ring often occurs. The perineum, even without tears, is significantly stretched. In the vast majority of cases, complete restoration does not occur; part of the muscle fibers atrophies and is replaced by scar tissue, which is why the perineum turns out to be insufficient. A complete rupture of the perineum leads to incontinence of feces and even gases. When the urogenital diaphragm is damaged, cystocele and urinary incontinence develop. The abdominal press, the antagonist of the pelvic floor, also undergoes significant changes. The general reduction in the circumference of the abdomen reaches 16%. The reduction of the surface of the abdominal wall is not uniform on its different parts and at different depths (Felsenreich, Krause). The muscular and fascial layers contract better than the skin. Therefore, the latter often forms numerous folds. Numerous 'pregnancy scars' take on a whitish, shiny tint. Sometimes the rectus abdominis muscles diverge. In addition to the above-mentioned changes, insufficiently studied functional changes occur in the organs and tissues of the puerperal woman, which are characterized by a certain decrease in their resistance. Thus, under pressure, e.g., from drainage, necroses easily form in the first days of the p.p. When sewing fistulas before the end of the p.p., tissues easily tear, the sutures cut through, and the sutured surfaces separate. Puerperal women poorly tolerate anesthesia. From the side of the heart, at the beginning of the p.p. (on the 3rd-5th day), a systolic murmur is often heard on the pulmonary artery, possibly due to changes in the position of the heart and large vessels. Many believe that in the p.p. there is a slowing of the pulse, but according to Young and Labhardt, the pulse rarely slows at the beginning of the p.p. Quite often in the first hours after childbirth, it shows a tendency to increase due to the excitement of the woman in labor. After 24 hours, the pulse rate becomes normal. However, other authors deny that the pulse can increase in women in labor. Sometimes, especially in multiparous women, a significant slowing of the pulse to 40 and even less beats per minute is observed. Nowak and Jetter classify such puerperal women as vagotonics. Those authors who confirm that the pulse slows down in the p.p. attribute this phenomenon to the lowering of blood pressure, which has been confirmed by many researchers. The temperature in puerperal women may rise by several tenths of a degree in the first hours after childbirth. This increase is connected with the labor work. During the first 24 hours, the temperature again drops to normal. The chill observed after childbirth is explained by prolonged cooling and fatigue from muscular work. Most obstetricians consider the p.p. normal if the temperature does not rise above 37.9° in the axilla and 38.4° in the rectum. Old obstetricians note as critical days of temperature increase besides the 1st day the 3rd-4th ('milk fever') and the 9th (the day of getting up at the usual time). Most modern obstetricians deny 'milk fever' and consider the temperature increase as coming from the genital sphere (absorption of protein breakdown products, infection, etc.).
On the day of getting up, there may be an increase in temperature, explained by the change in body position, which can lead to some separation of insufficiently healed wounds, rejection of small thrombi, etc. The breathing of puerperal women becomes calmer and deeper; according to some authors, it slows down. The vital capacity of the lungs in the p.p. increases, with abdominal breathing predominating. Changes in the blood composition, increasing by the time of delivery, in the p.p. quite quickly (within 7-10 days) return to normal. The erythrocyte content in the blood of puerperal women is reduced, and the osmotic resistance of erythrocytes somewhat increases (Nikolaev). The leukocyte formula of the blood (Yanchenko) shows a decrease in the total number of leukocytes, and a decrease in the percentage and absolute content of stab and segmented neutrophils. From the 2nd-3rd day of the p.p., an increase in the percentage content of eosinophils, lymphocytes, and monocytes is observed. The coagulability of the blood soon after delivery increases, then after a few days returns to normal again (Ebeler). As for the general metabolism in the p.p., its determination is difficult for a number of reasons. This includes the variety of secretions - blood, lochia, sweat, milk. Hence the discrepancies in research. Some (Grammaticati) believe that metabolism in the p.p. is enhanced due to breastfeeding, while others (Reprev) established a decrease in nitrogen and salt metabolism with an increase in the retention of nitrogen, phosphates, chlorides, and sulfates. According to Zakharievsky, in the first 4-5 days, there is an excess of nitrogenous substances expended over intake. On the 5th day, equilibrium is established, then compensation for losses, and on the 9th-10th day, equilibrium is again established. The amount of urea in the blood, according to Hellmuth, constitutes 50% of the residual nitrogen. The average daily excretion of nitrogen in the p.p. is calculated at 18.1 g, urea at 30.5 g, and uric acid at 0.7 g (Zangemeister). In the first days of the p.p., most patients have protein in the urine and on the 3rd-5th day, sugar (in 52% according to Berberov, in 80% according to Hofmeister). The amount of urine increases in the first days of the p.p. (according to some authors, up to 2,500 g in primiparas). The average daily amount is 1,800 cm3. The specific gravity of the urine somewhat increases (1.018-1.020). Since due to birth trauma, puerperal women often do not feel the urge to urinate, the bladder is often greatly stretched by urine and displaces the uterus upward. Every 100 g of urine in the bladder displaces the uterine fundus upward by 1 cm. As a result of relaxation of the abdominal press and the recumbent position in the first days of the p.p., there is a tendency to constipation. Accumulation of fecal matter displaces the uterus upward and can interfere with its contraction, but does not lead to a significant increase!0. Puerperal women often show a tendency to sweating, which is considered a favorable sign. Healthy puerperal women have moist skin, infected ones have dry skin. Hair on the head often begins to fall out. The body weight of puerperal women decreases in the first 6-8 days of the p.p. The weight loss reaches 2-3 kg according to Gail for a puerperal woman weighing 55 kg. Khazhinsky determines the weight loss at 5%, others at up to 8%. With the removal of parts of the ovum, the changes in the correlation of endocrine glands that occurred during pregnancy regress more quickly in non-nursing than in nursing women. The reverse development of endocrine glands is still insufficiently studied. Some insufficiency during pregnancy in the function of epithelial bodies equalizes in the p.p., and the galvanic excitability of nerves, with rare exceptions, decreases. The enlarged thyroid gland decreases within 14 days of the p.p. Changes in the pituitary gland remain for a very long time (several years). However, the features of the general appearance of pregnant women, apparently due to changes in the pituitary gland - elongated facial features, thickening of the extremities, formation of osteophytes on the inner plate of cranial bones - regress within several weeks. The pigmentation (chloasma uterinum), apparently associated with increased function of the adrenal cortex, deposition of pigment along the white line, on the nipples, and external genital organs, regresses more quickly in the first few weeks, then more slowly; it lasts the longest on the external genital organs (several years). In general, the correlation of endocrine glands, which changed during pregnancy due to the formation of new hormones from the corpus luteum, placenta, and possibly the fetus, although unevenly, returns to status quo ante partum. As for the effect of birth trauma on the psyche, in healthy women it is apparently small, but in general it is subject to significant fluctuations (see Childbirth). In contrast to the usual beginning of reverse development in all organs and tissues of the puerperal woman immediately after delivery, the enlargement of the mammary glands continues in the p.p. and reaches its maximum after 2-3 days, at the time of so-called engorgement. In the first 2 days of the p.p., colostrum turns into milk. The breasts become fuller and more tense. The lobules of the mammary glands are clearly palpable as hardened and, in sensitive individuals, moderately painful. Severe engorgement sometimes causes significant suffering (more in non-nursing women) and lasts for several days. The increase in temperature at this time, formerly (and often now) without good reason attributed to so-called milk fever, is observed. Most authors believe that milk fever does not exist. However, during breastfeeding, an increase in temperature is found under the mammary gland. Some consider it an indicator of the ability to lactate.
The hygiene of the p.p. and care for the puerperal woman require the attention of the obstetrician from the moment of expulsion of the placenta. The room must meet general hygiene requirements, and the bed must be accessible from both sides. In the middle third of the bed, a rubber sheet is placed under the sheet. For the first 2-3 hours, it is important to monitor the contraction of the uterus due to the possibility of the not infrequent occurrence of atonic bleeding during these hours. This is why the person who delivered the baby must not leave the puerperal woman for 2-3 hours after delivery. With appropriate indications, ice on the abdomen, ergot 0.5 per dose 1-2 times; if the uterus is relaxed, rubbing its fundus until contraction is applied. After cleaning, the puerperal woman is given rest for the first hours. In contrast to the requirements of former times - to lie on the back for 8-10 days - now turning on the side is allowed on the very first day. As early as the 90s, Kustner shared his observations on puerperal women who did not remain immobile in bed for 8-10 days after delivery, but already on the 2nd-3rd day made voluntary movements. The observations of Kronig and Gauss on extensive material expanded the indications for early ambulation. In our country, favorable results with early ambulation have been noted by Lozinsky, Selitsky, Stroganov, and others. Thus, these authors noted a smaller percentage of feverish patients, better general condition of puerperal women, and better milk secretion. Contraindications to early ambulation are considered severe labor, significant blood loss, perineal tears, elevated temperature, rapid pulse. Among previously suffered diseases, the main contraindication is gonorrhea. Lichtenstein proposed the squatting position for expulsion of the placenta. In any case, after 2-3 hours have passed after delivery, if the puerperal woman cannot sleep on her back, there is no reason to prevent her from taking a position on her side with slightly flexed thighs - the most favorite and frequent position for sleep. A sutured perineal tear cannot be a contraindication for turning in bed. On the 3rd day, with normal temperature and pulse, a puerperal woman without perineal tears can sit up in bed. On the 4th-5th day, she can sit in a chair, on the 5th-6th day - walk. On the 7th-10th day, the puerperal woman leaves the institution.
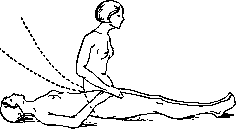
For better reverse development, active movements - gymnastics - were also recommended. Proposed at one time by Seitz, a
Figure 3.
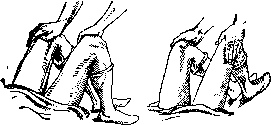
Figure 4.
Figure 5. Gymnastics in the postpartum period, which has already begun to be systematically conducted by the Moscow Obstetrical School (subject to certain precautions and contraindications), has recently become widespread and is used in many institutions. Observations of recent years (e.g., Ilkevich and Nekrasov) confirm the entire rationality of active movements and gymnastics in the postpartum period. Certain schemes (Figs. 3-5) have also been proposed according to a strictly developed system (starting from the 2nd day after childbirth). Thus, for example, at the Central Scientific Research Institute of Obstetrics and Gynecology, together with the Lesgaft Institute, the following scheme of gymnastic exercises for puerperae was developed. 1st session (2nd day of the postpartum period). Breathing exercises—inhalation and exhalation with the mouth closed. 1) Starting position: lying on the back—arms extended along the body, palms turned upward; forceful clenching of the hand into a fist and forceful opening of the hand with separation of the fingers; 2) flexion of the arms at the elbow joints with simultaneous clenching of the hands into fists; extension of the arms at the elbow joints with simultaneous opening of the hands; 3) starting position—on the back, arms extended along the body, legs extended; maximum flexion and extension of the foot; 4) starting position: legs crossed in the area of the upper part of the lower leg; circular movement of the foot of the leg lying on top; movement alternately with both legs; 5) starting position on the back with heels extended and spread to shoulder width; inward and outward rotation of the thigh. - 2nd session (3rd day of the postpartum period). Exercise of the 2nd day with the addition of the following exercises: 6) alternate pulling up of the thighs almost to a vertical position while sliding the feet along the bed or the same exercise with simultaneous pulling up of the thighs; breathing exercises; 7) starting position on the back with arms extended along the body; simultaneous pulling up of the legs to the abdomen, sliding the heels along the bed; the legs extended in the air are slowly lowered onto the bed. - 3rd session (4th day of the postpartum period): 8) to the previous exercises are added: alternate or simultaneous lifting of the straightened legs to 45° and lowering onto the bed; 9) the same exercises, but the legs are in the air the whole time (scissors). - 4th session (5th day of the postpartum period). Exercises of the first 3 days and additionally: 10) lifting the legs to 70° with spreading them to the sides; the exercise is done in 4 counts: a) 1st count—simultaneous lifting of the legs to 70°; 2nd count—possible spreading of the extended legs to the sides; 3rd count—bringing the extended legs together; 4th count—lowering the extended legs onto the bed. - 5th session (6th and 7th day of the postpartum period). All exercises in the postpartum period with the following: starting position on the stomach; raising the torso upward on the arms, resting the palms on the bed at the nipple line. When performing all exercises, breath-holding is not allowed. In case of fresh injuries of the pelvic floor, the exercise with spreading the thighs (10) is contraindicated.
The birth canal of the puerpera requires careful care. To absorb secretions, sterile cotton wool wrapped in gauze or pads made of soft linen are applied to the genital slit, changing them about 4 times a day. The external genitalia are washed with 1% lysol or 0.5% sublimate, from top to bottom, using tweezers, with gloved hands, 2 times a day, preferably also after defecation and urination. In view of the increase in urine output and the occasional absence of the urge to urinate, the puerpera should be reminded of the need to urinate. Sometimes the puerpera loses the ability to urinate—postpartum ischuria, explained by edema and hemorrhages in the mucosa of the bladder floor and the urethra in the sphincter area as a result of birth trauma (Stoeckel). For postpartum ischuria, heat on the abdomen, running water from a tap, mild diuretics (parsley infusion, urotropin), and raising the patient to a sitting position are recommended. In stubborn cases, it is necessary to release urine with a catheter. This should be done with a thick catheter 3 times a day, observing the usual rules of asepsis and antisepsis. With systematic catheterization, it is better to perform daily bladder irrigations with a boric acid solution. For the treatment of postpartum ischuria, injections of pituitrin and intravenous administration of 40% urotropin (5-10 cm3 each) are recommended. Bowel evacuation is achieved with a laxative (castor oil) on the 3rd day after childbirth in the absence of sutures on the perineum; in subsequent days—enemas. In the diet of the puerpera, light dishes (soup, compote, porridges, white meat) are adhered to for the first 2 days; thereafter—normal nutrition. The nipples require careful care in terms of asepsis. Before and after feeding, wiping with a 2-3% solution of boric acid is recommended. Relaxation of the abdominal wall in the postpartum period requires the application of a bandage in the first days and a light binder in the first weeks after childbirth. In subsequent months, rubbing the abdomen with a towel moistened with cool water is useful. After 20 days, a general bath is permitted. Sexual intercourse is allowed no earlier than the end of the postpartum period (after 6-8 weeks after childbirth).
L. Vublichevvo. II. Postpartum hemorrhages. Postpartum hemorrhages are those that arise in the postpartum period after the passage of the placenta and fetal membranes. These hemorrhages can be observed immediately after the end of the third stage of labor, in the nearest hours and days of the postpartum period, and finally significantly later—2-3 weeks after childbirth. The latter type of hemorrhages is assigned a special name—late postpartum hemorrhages; however, some authors also include in this category hemorrhages arising in the first days after childbirth and give them the additional name of secondary, in contrast to primary hemorrhages observed immediately upon the conclusion of the act of labor. Winkel, Fromme, and others classify hemorrhages up to the 10th day of the postpartum period as early postpartum hemorrhages, while hemorrhages after the 10th day are given the name of late postpartum hemorrhages. Postpartum hemorrhages, along with pregnancy toxemias and postpartum diseases, significantly influence maternal morbidity and mortality. Maternal mortality from hemorrhages associated with pregnancy is not only not decreasing but even has a tendency to increase (e.g., in New York). Postpartum hemorrhages also occupy one of the first places among the causes of mortality. Thus, according to data from Grodel—material from the Heidelberg clinic for 1902-1910—there were observed deaths from postpartum diseases—34, from hemorrhages—13, from eclampsia—12, from tuberculosis—5, from meningitis—3, from heart failure—3, and one death each from epilepsy, chorea, pneumonia, nephritis, and appendicitis. The causes of postpartum hemorrhages are extremely diverse; their origin can be of a local or general nature. Deviations in the course of the act of labor and improper management of labor, especially the postpartum period, are also of great importance; deviations during pregnancy, an improper lifestyle, and irrational use of maternity leave before childbirth can also play a definite role. Postpartum hemorrhages can be caused by: 1) retention of pieces or an accessory lobe of the placenta (placenta succenturiata), retention of membranes, 2) rapid emptying of the uterine cavity after surgical intervention (both per vias naturales and per abdomen) or after spontaneous precipitous, rapid labor (so-called Sturzgeburt), and finally 3) long-lasting, prolonged labor accompanied by uterine inertia (primary or secondary) or overdistension of the uterus (with a narrow pelvis, large fetus, multiple pregnancy, and polyhydramnios). A large placenta can also have an influence. Postpartum hemorrhages can also arise as a consequence of various changes in the uterus itself on the basis of past inflammatory diseases of the genital sphere or a suffered postpartum infection, arteriosclerotic changes in the vessels, or hyaline degeneration of the vascular wall. Finally, neoplasms—fibromyoma, cancer—also belong to the etiological factors of postpartum hemorrhage. All these processes significantly affect the uterine musculature, are accompanied by abundant proliferation of connective tissue, and lead to a decrease in tone, to flaccidity, and to less contractile ability of the muscular apparatus of the uterus. In this same sense, inflammatory adhesions and scars after past operations both on the genital sphere and on adjacent organs can also have a definite significance. Recently, among the possible causes of postpartum hemorrhages, insufficiency of the endocrine system is also pointed out, and in particular, for example, Pankov speaks of reduced hormonal activity of the ovary. In all probability, the internal secretory system can play a role in the emergence of postpartum hemorrhages, just as the autonomic nervous system and the reticulo-endothelial apparatus can, but it is more correct to consider these endocrine influences not from the point of view of the dysfunction of any individual endocrine gland, but as a definite constitutional insufficiency (see below), having at its base hypofunction or dysfunction not only of the ovary but also of other glands (e.g., thyroid, pituitary, adrenal), since it is known that many of them can exert a definite influence on the tone and ability to contract of the uterine musculature (thus, for example, a case of fatal atony with hypoplasia of the adrenal system was described by Mansfeld). Causes of postpartum hemorrhage of a local nature can be tears and injuries of the soft birth canal (cervix, vagina, perineum, cavernous bodies of the clitoris—see Labor) and varicose nodes. Along with the indicated causes of a local nature, postpartum hemorrhages can also be caused by changes of a general nature, general underdevelopment, or insufficiency of the entire organism. This insufficiency can be of two types: either it is connected with the peculiarities of the given organism, with one or another type of infantilism or constitutional type, or it arises secondarily as a consequence of a suffered disease associated with pregnancy (toxicosis). Thus, in relation to the first factor, it has been observed for a relatively long time that postpartum hemorrhages are most often encountered in infantile women, with a delicate and fragile build, with hypoplasia and weak development of the musculature. More detailed studies of recent times confirm this even more vividly and state that postpartum flaccidity and relaxation of the uterine musculature (so-called insufficientia uteri) are more often observed in asthenics. Hemorrhages observed with hemorrhagic diathesis, both existing before the onset of pregnancy and appearing for the first time during it, can also be attributed to this same group of causes of postpartum hemorrhages. Postpartum hemorrhages can also arise on the basis of various kinds of infections, diseases of the heart, lungs, and especially the kidneys. The significance of the second factor has been determined by new clinical investigations in the field of pregnancy toxicosis. These observations have shown that there exist such forms of pregnancy toxemia (with predominant significant lesions of the liver) which are accompanied by a special tendency to severe postpartum atonic hemorrhages, often ending fatally. Postpartum hemorrhages, both in the first days after childbirth and later, according to the observations of some authors (e.g., Kermauner), can be a consequence of intrauterine infection. Individual obstetric schools (Couvelaire) believe that later hemorrhages can even be considered as a special subspecies of postpartum diseases, as a hemorrhagic form of postpartum infection. According to Nogueres, the main cause of these hemorrhages is the retention of placental remnants or one or another deviation in the third stage of labor (hemorrhages, artificial separation of the placenta, too early or late application of the Credé method); Keiffer considers such an understanding too narrow and believes that it is impossible to reduce everything to retention or infection, since postpartum hemorrhages can be caused by changes in the uterus and the resulting same insufficientia uteri that existed before and during labor. In his opinion, insufficiency of the uterus (weak ability to contract, sluggish work, delayed reaction or its complete absence to the introduction of pituitrin) can be observed to an equal degree both during labor and after. Hemorrhages appearing for the first time only 2-3 weeks after childbirth have at their base predominantly an improper lifestyle of the puerpera, early discharge from the institution, early start of work, lifting of heavy objects, premature sexual intercourse; in rarer cases, their causes can be placental remnants, a placental polyp, fibromyoma, or postpartum infection. In clinical practice, it is usually customary to divide postpartum hemorrhages into hemorrhages caused by the fact that "something has remained or been retained" in the uterus, hemorrhages with a so-called free, "empty" uterus, but which for one reason or another has lost the ability to contract, and finally hemorrhages arising on the basis of trauma to the soft birth canal. Hemorrhages caused by insufficient contraction of the uterus, loss of the ability to retract in the postpartum period, are given the name of atonic or uterine atony. The clinic of Kurdinovsky (Novikova) divides atonic hemorrhages into two main types: primary uterine atony, depending on some constitutional insufficiency or congenital and acquired pathological-anatomical changes, and secondary (or relative) atony, caused by one or another mechanical factor. Novikova sees the rationality of such a division in the fact that the therapy is determined by the establishment of one or another type of atony (thus, with the primary form, everything should be reduced to raising the muscle tone of the uterus, with the secondary—to the elimination of the mechanical cause). In fact, complete relaxation of the uterine musculature and complete loss of its ability to contract is rarely encountered (true atony, in pure form, with complete loss of muscle tone); more often, one is dealing with a partial loss of the uterus's ability to retract.
Some authors (for example, Schmid) have quite rightly proposed recently to reserve the term "atony" only for cases of complete relaxation of the uterus, while considering partial insufficiency of the uterus as hypotonia, and classifying the hemorrhages observed during it as hypotonic. Frequency of postpartum hemorrhages, predisposing factors. The frequency of postpartum hemorrhages is subject to significant fluctuations and depends on a whole range of factors and external conditions. Statistics of postpartum hemorrhages. Russian authors. Gugenberg (Moscow Maternity Institution). 1875: 3,468 births—32 cases of uterine atony (0.9%); 0% mortality. 1876/77: 7,536 births—61 hemorrhages (0.8%) (including hemorrhages of the third stage of labor); 3 cases of atony; 1 case of death. Onufriev (Yekaterinburg Maternity Hospital, 1877–1887). 2,232 births—115 hemorrhages. Primiparae: 1st stage of labor—1; 2nd stage—0; 3rd stage—24; postpartum—20; Multiparae: 1st stage of labor—5; 2nd stage—2; 3rd stage—26; postpartum—37. Percentage of postpartum diseases during hemorrhages = 26.9. Mikhailov (average Russian obstetric results for 50 years—1840–1890). 96,520 births; percentage of hemorrhages—4.5 (primiparae—30%, multiparae—70%); died from hemorrhages—0.8%. Postpartum hemorrhages—82% of all hemorrhages; uterine atony—54.32% of all hemorrhages. Wolff (Slavyansky Clinic, 1884–1891). Hemorrhages—1.9%; of these, in the 1st stage of labor—4; 2nd stage—4; 3rd stage—43; third-stage hemorrhages—16; at later dates (from the 1st to the 15th day)—4 cases; uterine atony—90 cases. Speranskaya-Bakhmetieva (Ott Clinic, 1904–1907). 8,538 births—400 hemorrhages (4.7%); mortality rate—0.7. Khashinsky (Kharkov University Clinic, 1892–1908). 156 hemorrhages (2.7%). 1st stage of labor—38 (24.3%); 2nd stage—4 (2.5%); 3rd stage—42 (26.9%); postpartum—72 (46.3%); uterine atony—68 cases. Novikova (Kurdinovsky Clinic, 1928). 7,374 births—544 postpartum hemorrhages (7.4%) (including third-stage hemorrhages). Tikanadze (Tikanadze Clinic, 1929). 8,539 births—108 cases of uterine atony (1.2%); mortality rate—0. Shapiro (Moscow, 8th of March Maternity Hospital, 1930). 16,610 births—1,161 hemorrhages (6.9%) (including hemorrhages of the third stage of labor). Foreign authors. Veit (collected statistics). 47,665 births—5 deaths from atony (0.01%); 6,700 polyclinic cases—12 cases of death (0.18%). Studer (1896). 11,109 births—3 cases of death from atony (0.027%). Herff. 38,923 births—22 cases of atony (0.05%). Heimann, 12,000 births—172 cases of severe hemorrhages (1.4%) [14 cases of ruptures, 84 cases of improper separation of the placenta, 84 cases of atony (0.7%); mortality rate—0]. Sundel and Segalowitsch (1923). 1911–1922. 10,412 births—1,341 hemorrhages (excluding ruptures and placenta praevia—5.2%); mortality—0.02%. Digonnet (1924). Secondary hemorrhages—1.02%. Hoffmann (1925). 4,502 births—465 hemorrhages (excluding ruptures) (10.31%). Pistorius (1925) [for 40 years (1885–1925)]: uterine atony—2.3%; placenta accreta—0.02%; ruptures—0.13%. Stoeckel (collected statistics; 1925). 971,487 births: 582 deaths from hemorrhages (0.6‰); from pure atony—278 (0.28‰); total 7,918 severe hemorrhages (blood loss over 1,500 g), mortality—3.5%. Eparvier (1930). 18,213 births—39 secondary (late) hemorrhages (2.14‰). Anderodias and Pery (collected statistics; 1931). 68,758 births: secondary late hemorrhages—1.55%. Frequency of uterine atony (according to collected statistics by Michaeli, 1911). Authors: Number of births, Cases of uterine atony: v. Winkel—12,297—17; Chiar—16,210—17; Michaeli—7,354—17; [The table continues with other data].
There are effectively no precise and complete statistics. The data provided cannot give a clear picture, because the term "atony" itself is understood extremely subjectively, and not only by different schools, but even by individual obstetricians within the same institution. Furthermore, there is no uniformity in the statistics; for example, some include hemorrhages of the third stage of labor in the category of postpartum hemorrhages; there is no differentiation between atonic hemorrhages and hemorrhages caused by ruptures of the soft parts. Mikhailov (1895) already pointed out that no section in reports is presented based on such different principles as the section on hemorrhages, due to which the average figures of such heterogeneous material cannot be considered reliable. Progress in this regard has not occurred even in modern times, and, among others, Anderodias and Pery (1931), while analyzing the issue of secondary postpartum hemorrhages, noted that statistical data have only relative value. The principles of conducting labor and especially the third stage of labor, as well as the qualifications of the obstetric staff, undoubtedly play a role in the fluctuations in the frequency of postpartum hemorrhages; thus, our authors and foreign authors note that among less experienced, young obstetricians, "atony" appears more often, both due to more frequently encountered unjustified intervention and due to the fact that hemorrhages of moderate and even mild degree are classified under "atony."
Other factors can also influence the frequency of postpartum hemorrhages. Thus, a number of authors have noted a significant increase in them during the imperialist war and in the years immediately following it (e.g., Sundel-Segalowitz). Ujama also points to a sharp increase in postpartum hemorrhages in the postwar period (from 1–2% to 17%) and a certain decline in subsequent years (11–13%) and links this to poor nutrition, an increase in the total number of young parturients, and unfavorable conditions of sexual maturation during the war and postwar period. Schonholz attributes this to the increased frequency of the infantile type of women and asthenic constitution; the increased number of postpartum hemorrhages is also explained by worse living conditions, and they are even given a special name, "wartime atony." The increase in the number of postpartum hemorrhages noted by some due to abortions and the spread of malaria is not confirmed by further observations. Thus, in relation to malaria, this is refuted by the data of Tikanadze, Gogoberidze, and Zakrzhevsky (the latter could only note an increase in bloody discharge). The influence of abortion may take place, but only in those cases where the conditions of its performance are not sufficiently weighed and contraindications are not taken into account. The influence of abortion can undoubtedly have an effect when the first pregnancy is interrupted, especially at a young age when the organism is not yet fully formed, or in the presence of certain, even if not sharply expressed, signs of infantilism. And indeed, we see that in primiparae who had abortions in their history, postpartum hemorrhages occur more often than in those who did not. Thus, Weinstein observed atonic hemorrhages in the former in 2.7%, while in primiparae who had not had an abortion before birth, only in 0.41%; in such cases, secondary uterine inertia and a higher frequency of surgical intervention were also observed more often—2.42% and 1.51%.
Observations of recent years in individual large maternity institutions of the Union [e.g., the former Moscow Maternity Institution (Clinic of Obstetrics and Women's Diseases of the State Scientific Institute of Mother and Child Protection for 1926–30)—Selitsky] show that the curve of fluctuations in the frequency of postpartum hemorrhages depends not only on the precise, careful management of the third stage of labor and the clarity of indications for surgical assistance, but also on reasonable prophylaxis during pregnancy. The noted significant decrease in both the total number of postpartum hemorrhages and their severe degrees, and the absence of fatal outcomes, are directly conditioned by preventive measures undertaken in advance, systematic observation of the pregnant woman in the consultation, with special attention fixed on cases suspicious in this regard, and hospitalization in the ward for pregnant women if necessary. The preventive focus, which has been carried out in depth in recent years in obstetrics, undoubtedly mitigates certain shortcomings in the organism, contributes to its greater development during pregnancy, makes the tone of the uterus more stable, and increases the reaction of irritation of its muscular motor and the ability for various kinds of contractions during labor and after its completion. In the decrease in the frequency of postpartum hemorrhages in individual institutions, one can also see the influence of new factors—social maternity insurance, better accounting of physiological processes occurring during pregnancy, prevention of possible harmful external influences, and a changed view on cleanliness and dietetics (for example, the refusal of frequent baths, prolonged, exhausting walks, etc.) during pregnancy. In the future, to leave a precise idea about the frequency of postpartum hemorrhages and the factors influencing their increase, and for greater effectiveness of prophylaxis, it is necessary in statistical data to sharply distinguish hemorrhages before the expulsion of the placenta from hemorrhages that arose for the first time only in the postpartum period; furthermore, these latter must in turn be divided into hemorrhages caused by ruptures, as a consequence of deviations of the third stage of labor, and finally into atony in its pure form (some give this a special name—atonia vera; Zundel-Segalowitz).
Postpartum hemorrhages are more common in multiparous women (according to Mikhailov, over 50 years, in primiparae it was 30%, in multiparae 70%), especially in cases where pregnancies follow one another, after previous difficult labors; cases of recurrent atony (in asthenic women) are also not rare. Speranskaya-Bakhmeteva also notes a greater frequency of postpartum hemorrhages in multiparae and points out that they occurred more often during the 9th, 10th, and 12th pregnancies. Age also has an influence: thus, postpartum hemorrhages are observed more often in young women with still insufficient musculature and in births at an older age. According to the data of some authors (Andérodias and Péry), secondary (late) hemorrhages show seemingly different relationships; thus, hemorrhages with retained placental remnants were observed in primiparae in 47.11%, in 2nd and multiparae in 53.19%; hemorrhages without retention in primiparae in 48.30%, in 2nd and multiparae in 51.70% (in total, in primiparae and 2nd-para they were observed in 77.48%). Clinical aspects of postpartum hemorrhages. Hemorrhages immediately after birth and at a later time (hemorrhages due to deviations in the placental period and tears of soft parts) - see Uterus, Childbirth. Hypotonia and atony of the uterus. Recognition of hypotonia and atony is not difficult. The main symptom is hemorrhage. Hypotonic hemorrhage is differentiated from hemorrhage due to a tear by the fact that it usually occurs later. Braun-Fernwald (1893) stated (which is fully confirmed in practice) that if hemorrhage is absent in the first quarter of an hour after birth, this excludes a tear of the soft birth canal (primarily the cervix); in the presence of a tear, hemorrhage usually manifests earlier and often even during childbirth. A tear can also be indicated by hemorrhage with a well-contracting or contracted uterus and, finally, by the very character of the blood (arterial). Hemorrhage occurs due to the gaping of placental vessels due to partial and complete loss of muscle tone, the loss of its ability to retract. By virtue of this, "paralysis of the placental site" develops (Rokitansky). The character of the hemorrhage can be extremely varied and is in direct connection with the state of the uterus, with the degree of hypotonia; it either has a tendency toward a definite, periodic outflow of blood (in such cases, the discharge of large clots is not rare) or from the very beginning bears the character of an uncontrollable hemorrhage. Along with hemorrhage, a characteristic symptom is the state of the uterus itself—it is large, flaccid, of soft consistency, "like a sack," stands high, and is more often tilted to one side. A rare but extremely severe complication can be inversion of the uterus. The amount of blood discharged can be different and can have a definite influence both on the immediate outcome of the postpartum hemorrhage and on the development of subsequent pathological symptoms (anemia, acute blood loss, cardiac phenomena). Significant blood loss immediately after birth can also have an influence on the course of the postpartum period, lower the body's resistance to infection, and cause a higher percentage of postpartum morbidity and mortality. In the development of subsequent phenomena, the character of the hemorrhage itself can also play a role—the most unfavorable are rapid, profuse (uncontrollable) hemorrhages over a short period of time. The boundaries of physiological and pathological blood loss appear extremely conditional and are difficult to account for. On the basis of a whole series of observations in this direction, the limit of physiological blood loss after birth is considered to be 500 cm3; by some, this figure is increased to 600 cm3 (Segalowitz), and by some it is lowered to 200–300 cm3 (Frey calculated that the average physiological blood loss is equal to 211.7 cm3). Ahlfeld considered even a blood loss of 800 cm3 within the norm (in his material of 6,000 births, he observed 14 cases with a blood loss of 2,500 cm3, 1 case even of 3,000 cm3, and not a single patient died). Although cases with favorable outcomes after large blood losses have been described by other authors as well (e.g., Hoffmann cites a case with a blood loss of 2,500 cm3, which the patient endured without particular harm), a blood loss of over 500 cm3 must still be considered pathology. Blood loss during postpartum hemorrhage is on average equal to 955 cm3 (Hoffmann), while blood losses of 3,000–4,000 cm3 are already fatal (Ahlfeld). The difference in physiological blood losses in primiparae and multiparae does not present significant fluctuations; thus, Ahlfeld's observations showed that the average blood loss in 1st–3rd-para is equal to 400–460 cm3, in 4th–6th-para—500 cm3. All these figures can be accepted only as indicative; the reaction to blood loss can be extremely different in individual puerperae and depends on many factors. In clinical practice, cases are not so rarely observed where women easily endure blood losses above 500 cm3 and, conversely, cases with a more severe reaction to smaller blood losses. The question of the influence of the amount of blood lost on subsequent symptoms and outcomes of postpartum hemorrhage lies in the same plane. Although in principle the point of view of those obstetricians (e.g., Opitz) who believe that there is a definite parallelism between blood loss and postpartum disease is quite acceptable, exceptions to this principle are entirely possible, and along with the amount of blood, one must take into account the reaction of the organism, reckon with the conditions of each individual case, and consider those mounting symptoms that accompany the loss of blood. Secondary, late hemorrhages. The clinical picture of secondary, late hemorrhages can vary to a significant degree; it can depend on the cause that triggered the hemorrhage, on a number of accompanying symptoms, and finally, the time of the onset of hemorrhage after birth can also be of significance. The character and degree of hemorrhage are likewise not uniform; but in all these late hemorrhages, atony in the literal sense of this word is an extremely rare phenomenon (Spiegelberg, for example, observed only once such, as he called it, sequential atony). In late hemorrhages caused by postpartum infection, hemorrhage in the clinical picture is far from always the main or predominant symptom. Andérodias and Péry even view these hemorrhages not as an independent disease, but as a hemorrhagic syndrome of postpartum infection, as a prelude to an incipient septic process. It is not always possible to distinguish hemorrhage that arose on the basis of retained placental remnants from hemorrhage without retention. It is also not easy to decide which cases of this type of postpartum hemorrhage appear more severe in clinical practice. Apparently, the character of the infection plays a large role, and the opinion of Couvelaire is quite fair, who attaches primary importance to the accompanying infection and believes that the severity of the case is conditioned precisely by it and does not depend on whether there is retention or not. Secondary late hemorrhages more often arise suddenly, but in some cases, profuse bloody discharges are observed from the very beginning of the postpartum period, which, gradually increasing, can turn into a real hemorrhage. The time of the onset of hemorrhage is different; it also does not depend on whether there is retention or not. According to observations by Nogueres, Digonnet, and others, it more often arises on the 8th–9th day, but in general, it can begin from the 3rd to the 22nd day. One cannot speak of any classification or grouping; only an indicative scheme is possible. The most satisfactory scheme in this regard can be considered the scheme of Andérodias and Péry. Dividing these hemorrhages into three degrees, the authors point out that this division is artificial, and variations and mixed forms are possible. To the first degree, they attribute mild, favorable cases in which, along with moderate hemorrhage, there is also a mild infection (a slight rise in temperature, usually signs of endometritis). Cases of the second degree proceed with more profuse, recurrent hemorrhages (with a relatively good general condition of the puerpera) and with still moderate signs of local infection (without septicemia). In the third degree—in severe cases with very profuse hemorrhages in the presence of postpartum disease (even without sharply expressed infection)—there is always a serious danger (for details and therapy, see below—postpartum diseases). Hemorrhage (without the presence of infection) in the first days of the postpartum period can occur suddenly, or its onset is preceded by profuse bloody discharges and periodic passage of large blood clots. For hemorrhages of this type, the presence of placental remnants or proliferation of the decidual membrane (endometritis decidualis) is not always necessary. In hemorrhages of a time more distant from birth, almost the same picture is observed, but more often in them, the hemorrhage arises suddenly and not infrequently after a completely normal course of the postpartum period.
These hemorrhages are usually observed already after the patient has been discharged from the institution; they can be very profuse and almost always require inpatient treatment. Prevention of postpartum hemorrhages. In view of the fact that the cause of postpartum hemorrhages can be general or local insufficiency of the organism, irregularities and deviations during pregnancy, labor, and the postpartum period, their prevention should in its main features be based 1) on the fight against early marriages and early onset of pregnancy, 2) on taking into account the anamnesis in general and the pathological course of the given pregnancy in particular, 3) on sufficient intervals between individual pregnancies, 4) on maximum prophylaxis during pregnancy, especially with excessive overdistension of the uterus (twins, polyhydramnios), 5) on prophylactic, reasonable, and aseptic management of labor (always remember to empty the intestine and bladder!), 6) on clear and clinically justified indications for surgical intervention, 7) on rational and timely intervention in multiple pregnancy (a sufficient interval of time is necessary between the birth of the first and second fetus) and polyhydramnios (timely rupture of the fetal bladder), 8) on correct expectant management of the third stage of labor (according to the principle of "hands off the uterus"), the most thorough examination of the placenta, and the clearest indications for intrauterine intervention, and 9) on the observance of the most elementary precautionary measures after the discharge of the puerperal woman from the institution. Therapy of postpartum hemorrhages. Therapy of hypotonia and atonia should strive, along with the use of local agents, to introduce various kinds of substances that influence the increase of uterine tone. When treating, one must also take into account to a significant degree the subsequent pathological symptoms - acute anemia, shock, collapse. Stimulants and cardiac drugs (camphor, digalen) have great application in such cases and provide undoubted benefit. The position of the puerperal woman also has significance; a position with raised legs or raising the foot end of the bed is useful. By individual obstetricians in severe cases, the Trendelenburg position is also recommended [in recent years it has been proposed to combine it with the manual Piskacek maneuver and compression of the aorta (Genter; 1927)]. Local agents pursue the general main goal - to cause irritation of the uterine musculature, raise its tone, and promote contractions. Among them are mechanical means (various manual maneuvers, massage of the uterus - manual, external, and external-internal, instrumental, high tamponade of the uterus, tying it to the symphysis, colpeurysis, etc.) and thermal means (hot vaginal douches, uterine irrigations, ice on the lower abdomen). Measures causing artificial ischemia should be set apart - constriction with an elastic tourniquet of the waist (lumbar constriction according to Momburg) and compression of the aorta, manual or with apparatuses (compressors) specially proposed for this (Figs. 6-12). In exceptional cases, with insufficiency
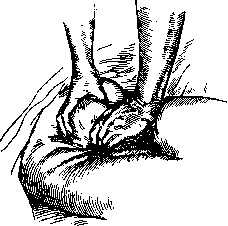
Figure 6. Manual maneuver for stopping hemorrhage. (According to Piskacek.)
and ineffectiveness of all these methods, radical intervention is indicated - extirpation of the uterus. In cases of acute anemia, blood transfusion by the direct or indirect method has been successfully carried out in recent years. In view of the fact that in hypotonia and atonia the pathological picture relatively often unfolds extremely rapidly, catastrophically, the physician must first of all not lose composure and in their actions, depending on the case, adhere to gradualness and a definite
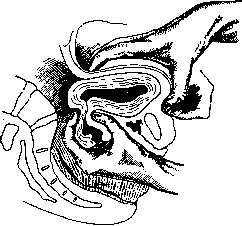
Figure 7. Zweifel's manual maneuver.
plan of assistance provided. In view of the variety of causes of atonic hemorrhages, as well as in view of individually different resistance, it is not possible to outline a predetermined plan of therapy. Usually, external manual maneuvers are applied initially (one- or two-handed massage of the uterus), which for greater effectiveness must be incessant and periodic. N. Z. Ivanov, moreover, points out that greater success is given by massage along the direction of the muscles; rubbing along the midline should be performed from top to bottom, while on the sides - in a transverse-oblique direction (from the uterus to the inguinal canal). Success can also be achieved by using the external Piskacek maneuvers and their modifications according to Genter et al. (Fig. 13). Simultaneously with massaging the uterus, ergot preparations (ergotin, secacornin) or pituitary gland preparations (pituitrin, pituglandol) are injected subcutaneously, while
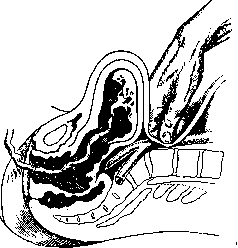
Figure 8. Manual compression of the aorta.
an ice pack is placed on the lower abdomen, on the region of the uterus (it must be taken into account that the effect of pituitrin is immediate, while ergotin acts after 15-20 minutes). Recently, a whole number of authors have reported very favorable cases with the use of Gynergen (Bowing, Lutzenkirchen, et al.) and Pituigan forte
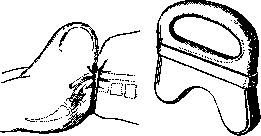
Figure 9. Momburg's tourniquet in situ.
Figure 10. Rissmann's compressor. (Johannsen). In some clinics, intramuscular injections of calcium (10 cm3 of "Calcium Sandoz") find wide application, which in cases of hemorrhage are recommended to be combined with pituitrin and even used prophylactically 1-8 hours before the expected term of labor
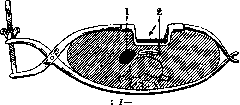
Figure 11. Sehrt's clamp. 1-v. cava inf. 2-aorta. in diseases with reduced blood coagulability and with profuse bloody lochia in the postpartum period. With incipient phenomena of anemia, it is rational to administer (intramuscularly or intravenously) saline solution
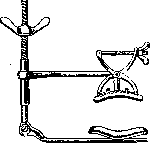
Fig. 12. Aortic compressor. (According to Haselhorst.) (used with success as early as by Ott; 1884) or glucose. After the indicated measures, it is useful, as the rich experience of the Moscow obstetric school shows, to tie the uterus to the symphysis (Figs. 14 and 15). For this, a towel is tightly rolled into a bolster, placed on the abdomen against the fundus of the uterus, and additionally, to hold it in place, it is tied with a second towel around the torso. In more severe hemorrhages, these methods are insufficient, and one has to move on to other means - hot vaginal douches, uterine irrigations, which, being mechanical and thermal irritants, can have a successful effect (when using them, great caution is necessary to avoid air embolism). The use of the so-called high tamponade of the uterus according to Dührssen is rational, which is performed with long forceps (Figs. 16 and 17), dressing forceps, or special tampon-inserters [tamponade of the uterus is currently used rarely; only individual obstetricians consider it the best method; even at the moments of its wide spread, it met with a negative attitude not only by virtue of Fig. 13. Genter's maneuver. a higher percentage of fever, but also by virtue of the complete groundlessness of the method (Ott)]. Expedient and often very useful are means that can be called combined; they consist either in bimanual massage of the uterus or in a combination of manual massaging of it with in


Figure 14. Compressive bandage (method of the Moscow obstetric school.)
strumental. The first method consists either in introducing a hand into the uterine cavity, folding it into a fist (the uterus is as if put onto the hand), and simultaneously rubbing with the external hand, or in bimanual compression, in which the hand introduced inside compresses the cervix of the uterus approximately at the level of the internal os (Fig. 18). In the second method (used significantly less often), instead of a hand, instruments specially proposed for this purpose are introduced into the uterine cavity. The introduction of rubber balloons both into the vagina and into the uterus is now not performed by the majority, and only some obstetricians, e.g., Wagner, consider the introduction of a metreurynter filled with ice water to be a particularly effective means. Of the methods striving to cause ischemia, the simplest is (possible only in thin women) direct compression through the abdominal walls with the fingers (or a fist) of the aorta slightly above the place of origin of the common iliac artery. The application of an elastic tourniquet according to Momburg and the use
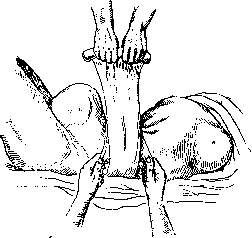
Figure 15. Compressive bandage (method of the Moscow obstetric school.)
of various kinds of instrumental devices in appropriate cases are also a fully indicated aid, provided there is an exact account of contraindications to avoid complications that may occur on the basis of their incorrect application. Experimental studies by Speranskaya-Bakhmetieva have already shown that this is a simple and convenient method for stopping
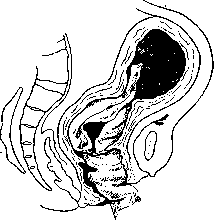
Figure 16. Incorrect tamponade of the uterus.
of hemorrhages. According to Momburg, when using a tourniquet, bleeding stops on average after 15 minutes; anesthesia is not necessary; blood pressure changes less than when opening the abdominal cavity; since the greatest fluctuations in blood pressure occur when applying and removing the tourniquet, it must be removed slowly. The latest classical studies by Bulatnikov (who first illuminated this issue from the point of view of physiology and topographic anatomy) additionally showed that Momburg's method is fully applicable in the postpartum period and is easily achieved in young, lean and well-built women. According to Bulatnikov, applying a tourniquet is safest in the horizontal position (pre-emptying of the bladder and intestine is desirable), and it should be tightened only until the pulsation of the a. femoralis ceases. Bulatnikov does not consider the application of a tourniquet contraindicated even in severe hemorrhages during abortions. Momburg's method is a quite acceptable surgical procedure from a forensic medical point of view, however due to its relative danger, the application of a tourniquet cannot be performed by a midwife or even a young beginning obstetrician. - Among the rarely used methods (due to possible damage to neighboring organs) should be included Hepke's proposal - direct compression of the uterine vessels by applying clamps to the parametrium (figure 19). Individual authors speak of it with great praise (Burgkhardt, Tikanadze), consider that the danger is exaggerated, and advise to test it on a larger material.

17. Uterine tamponade. (According to Stoeckel.)

Figure 18. Bimanual compression of atonic uterus.
applied methods (due to possible damage to neighboring organs) should be included Hepke's proposal - direct compression of the uterine vessels by applying clamps to the parametrium (figure 19). Individual authors speak of it with great praise (Burgkhardt, Tikanadze), consider that the danger is exaggerated, and advise to test it on a larger material. - In the most severe cases of postpartum hemorrhage, which according to Henkel: 1- a. uterina sin.; do not lend themselves to treatment-2 and 4-vagina; 3 -portio vaginalis; 5-i-arametrium.
the effect of any of the above-mentioned methods, a quite indicated intervention is the extirpation of the uterus (abdominal or vaginal) with preliminary blood transfusion (the latter may also take place without the radical operation of uterus removal in cases of acute anemia). The therapy of late postpartum hemorrhages depends on what caused them and what symptoms they are accompanied by. In the presence of infection (see below - Postpartum diseases), one must take into account its nature and be very cautious with various intrauterine interventions even in case of suspected retention of placental remnants. Quite right are those obstetricians (Couvelaire) who say that the problem of therapy of secondary postpartum hemorrhages should be resolved not in the plane of the factor of placental retention, but infection, and that simple manual examination can serve as a push to the development of the most severe disease and turn latent infection into diffuse. The same principles must be followed also in the absence of infection. Every intrauterine intervention must be approached with extreme caution, especially in the first days after childbirth; in any case, the first hemorrhage should not be an indication for intrauterine therapy. If nevertheless the removal of placental remnants seems necessary, it must be done with maximum precautions. This removal must be done with the finger, because the curette is very dangerous in such cases, and even an experienced obstetrician can easily puncture the uterus and cause a severe disease. In the overwhelming majority of cases, conservative therapy is sufficient. Of medicinal agents, ergotin, pituitrin, salt solution, ice on the lower abdomen are successfully used. Some for increasing blood coagulability recommend normal horse serum (Couvelaire). Hot vaginal douches, widely used earlier, are now used much less frequently, as they are often unnecessary and generally prove to be less effective than all the above-mentioned means.
S. Selitsky. III. Pathology of the P. p. In the pathology of the P. p. they distinguish 1) proper postpartum diseases, 2) non-postpartum but related to pregnancy and childbirth, and 3) accidental diseases during the P. p. All three groups of diseases can occur febrile and afebrile. Group 1 consists mainly of febrile postpartum diseases - all infections of the birth canal and intoxications: endometritis, inflammations of the ovaries, tubes, pelvic peritoneum and cellular tissue, diffuse peritonitis, hematogenous infections (puerperal fever), septicemia, septicopyemia, pyemia, thrombophlebitis. From other diseases of the same group should be noted postpartum shock, ruptures of the pelvic joints and soft parts of the birth canal (fistulas), postpartum hematomas (non-infected), subinvolution of the uterus, postpartum hemorrhages. Group 2 includes various diseases of the mammary glands (erysipelas, mastitis), diseases of the urinary tract (cystitis, pyelitis). Also included here: P. eclampsia, cerebral hemorrhages, P. psychoses, neuritis, neuralgias, etc. Group 3 consists of various infectious diseases, such as: influenza, pneumonia, typhoid, malaria, scarlet fever and other acute infectious diseases, as well as some diseases of the heart and blood vessels, diseases of the blood (anemias), skin diseases, kidney diseases, etc. In terms of the number and severity of complications, the diseases of group 1 occupy the main place. From group 2, diseases of the urinary tract are important not only as febrile diseases that can simulate postpartum ones, but also from the point of view of predisposition to the latter. Some diseases of group 3 can also simulate febrile postpartum; they proceed in most cases more severely in the P. p. than outside it, and are often provoked by childbirth (e.g. malaria). To the present time there is no generally accepted principle for identifying febrile puerperal women. Thus, in Germany they include puerperal women with a temperature increase of 37.8° (not counting the first day). In our country, most consider as febrile those with a temperature increase to 38° and above (with double increase) or to 38.5° and above (with single increase). Undoubtedly, infected puerperal women are also among those giving at least subfebrile t° (cases of severe septic diseases occurring with subfebrile and even normal t° are described). Some also accept the division of puerperal women into 1) non-febrile (below 37°), 2) giving subfebrile t° (37°-37.9°) for more than 2 days and 3) febrile with t° 38° and above. Statistics. The frequency of febrile postpartum diseases varies considerably in different clinics and obstetric institutions and at different times. From tens of percent (40-60%) in the pre-antiseptic period, the morbidity has decreased to a few percent. In the Obstetric-Gynecological Institute (Leningrad) the morbidity for 1878-1882 amounted to 43.5%, for 1913-1926 - 8.3%. In the Snegirev Maternity Hospital (Leningrad) the morbidity decreased from 15% to 7% - 6.3%. For small maternity institutions in Leningrad for 1919-1926 years the morbidity was calculated at 12%. According to Sakharov, in Odessa it is 15%. In the Grauermann Maternity Hospital with spontaneous births the morbidity fell to 2.5%. In the Leipzig clinic in 1887 the morbidity was 39.6%, in 1917 - 3.8%; in the Frankfurt clinic for 1913-1922 the morbidity was 7.22%, in Würzburg - 9.94%, in Göttingen - 14.05%, in Marburg - 11.7%. According to Schröder, the overall morbidity from 1918 to 1923 was 8.7%, postpartum - 4.9%. Puppel in Mainz calculated the febrile morbidity after childbirth as 2.7%, after operative - as 22.4%. In Paris in de la Pitie Jeanne and Fureau for 1924-1928 calculated the overall morbidity as 20.8%; in the Tarnier clinic the morbidity with temperature increase to 38° and above was 14%. According to Sigwart, the average morbidity for Germany is 10-12%. Severe septic processes constitute approximately 1/10 part. According to data of the State Obstetric-Gynecological Institute for 11 years, severe morbidity constituted 7.55% of the total number of febrile cases. Mortality from puerperal infection in the pre-antiseptic period reached in Vienna 15-20% of all puerperal women, in Paris - 10% and more. After the introduction of asepsis and antisepsis, puerperal mortality significantly decreased. In Paris in Maternite Port-Royal for 1858-1869 it was 9.31%, for 1870-1880 - 2.32%, for 1881-1889 - 1.05%; in Clinique Baudelocque for 1890-1901 - 0.60%, for 1902-1921 - 0.38%. In recent times (1926) in England the overall mortality is 0.41%, septic - 0.16%; in Germany overall mortality - 0.48%, septic - 0.2-0.25% (Sigwart). In Leningrad the mortality in the pre-antiseptic period reached 6.2% for 1848 (in the Obst.-Gyn. Institute) and 6.1% for 1872 (in the St. Petersburg maternity institution). For it constitutes approx. a/8 of the total and only x/3-g/4 falls on all other complications of pregnancy and childbirth (Bumm). The etiology of puerperal infections is not yet fully worked out. They distinguish
from septic diseases the general mortality from septic diseases in the St. Petersburg obstetric institution at the State Clinical Obstetric-Gynecological Institute Figure 20. Mortality in the postpartum period. in recent years it has decreased to tenths of a percent (fig. 20). In recent years mortality in Leningrad per 1,000 births was: Years General mortality septic 5.23 4.65 4.54 3.61 3.53 3.55 2.79 2.45 1.64 2.09 W24. . . . ^b . .... Selitsky (1930) provides the following mortality figures [Clinic of Obstetrics and Women's Diseases of the L. O. Khmatmold Institute named after Lebedeva (former Moscow obstetric institution)]: for 1921 general mortality-0.37%, septic-0.17%; for 1923 general-0.12%, septic-0.08%; 1926/27 general-0.29%, septic-0.07%; for 1927/28 general-0.06%, septic-0%. In recent years mortality according to some authors has not decreased and has even somewhat increased, for example in America (according to Dickinson). Probable causes-enthusiasm for operative delivery and increase in infected miscarriages (abroad). According to data from the State Obstetric-Gynecological Institute in the pre-revolutionary period mortality from miscarriages was 10 times higher than that from childbirth. After the decree on miscarriages mortality from them in the USSR significantly decreased. In Hamburg as late as 1922 mortality from childbirth was 0.12%, from miscarriages-1.16%. According to sanitary-police statistics in Prussia for 1913-1920 33,996 fell ill after childbirth, 10,179 died. In the USA about 20,000 women die annually from childbirth, of which 43% from infection. In general septic mortality is from exogenous infection-infection from microbes from outside-and endogenous. The latter can be 1) spontaneous, ascending infection and 2) artificial, when sterile instruments and hands carry germs upward from the lower parts of the birth canal. In the understanding of endogenous infection opinions differ. It can occur 1) from distant parts of the puerperal woman's body (abscesses, carious teeth, angina, etc.) from where bacteria can through contact or hematogenous path enter the birth injuries-focal infection; 2) from areas closest to the birth canal: a) Fallopian tubes, b) vestibular glands (in bartholinitis), c) urinary tract (cystitis, pyelitis) and rectum (3rd degree tears), d) from the vaginal cavity, e.g. in chronic cervical catarrh or contamination of vaginal flora (about 15% in pregnant women). Some (e.g. Abladze) deny endogenous infection and consider that infection occurs exclusively due to the introduction of infection from outside, while clinical data quite definitely allow for the possibility of endogenous infection (see Autoinfection). Bacteriology of P. diseases. Of individual causative agents of P. infection streptococci were considered most frequent until recently (in 70-90%). According to Sommer's data in fatal septic diseases streptococci were found in 38.5%, staphylococci-in 32.8%. According to Ilkevich, half of fatal cases fall on hemolytic streptococcus, 1/4-on mixed infection, 1/9-on staphylococci and 1/20-on intestinal bacillus. According to observations by Bublichenko staphylococcal infection occurs more frequently. The causative agents of postpartum diseases often have some biological features by which to some extent their pathogenicity can be judged. Thus, according to Schotmüller's data pathogenic streptococci in most cases cause necrotic deposits and exhibit hemolysis. Pathogenic staphylococci are more often found among golden yellow, gelatin-liquefying, and hemolytic ones. The intestinal bacillus often also has hemolytic properties. Of all pathogenic microbes gonococci are distinguished by their particularly weak stability outside the organism, spread mainly on the surface and only in exceptional cases show a tendency to dissemination. Of the rarer causative agents of postpartum infection are described: Bac. phlegmonae emphysematodes Frankel, Bac. aerogenes capsulatus, Bac. oedematis maligni, Bac. haemophilus, Bac. fusiformis (Vincenti) and others. The nature of the infection to some extent is reflected in the clinical picture of the disease. The comparative rarity of infection despite often non-aseptic conditions during childbirth can be due to a number of protective mechanisms of the organism. These include a certain degree of general non-susceptibility (immunity) due to constitutional features (pyknics are more resistant), the general state of the organism and in particular the reactivity of the reticulo-endothelial apparatus. Causes of infection can be producing and contributing. Producing causes include operative procedures. Through them hands, instruments and dressing material can introduce pathogenic bacteria from outside into the uterine cavity, as well as bacteria from the external genital parts and lower parts of the vagina. In addition due to crushing, mashing and tearing (e.g. of the cervix when applying forceps) the vitality of tissues is lowered and access is opened for bacteria to the most susceptible to infection areas (cellular tissue, peritoneum). Morbidity and mortality depending on operative procedures according to Kiefer until 1926 was as follows (in %): Method of intervention Morbidity Mortality 24.8 35.9 30.4 34.4 36.5 34.4 0.47 0.63 1.3 1.7 4.7 6.8 Manual separation of the placenta Cesarean section . . . Delivery-disrupting According to Zhmakin (Kiev), for 1900 - 1931 years forceps gave morbidity - 40.9%, mortality-1.86%; version and extraction: morbidity-38, 1%, mortality-3.9%; extraction by the breech: morbidity-17.7%, mortality--0%; cesarean section: morbidity-40.2%, mortality-9.75%. It is clear that the increase in morbidity and mortality after operative procedures depends partly on those complications of the birth act for which the operative procedure is performed.- In the origin of morbidity and mortality internal examination also has significance. (Although one must also consider the possibility that the increased morbidity after internal examination can find explanation in those complications which served as the reason for the examination.) According to Krenig, of 600 examined parturients 7.8% had fever, of 600 unexamined-3.8%. According to Poten, of 5,549 unexamined. had fever-12.4%, died-3%; of 5,281 with internal examination and operative procedures had fever 26%, died-5%. According to Gubanova and Kuchaidze (State Obstetric-Gynecological Institute), among examined 15.9% had fever, unexamined-10.2% (on 16,604 births for 1910-1929). Those who had intercourse during the last week before childbirth had fever more often; (4.5%) than those who did not (2.1%) (Lyubimova). Conditions predisposing to infection include early rupture of the membranes, due to which the acidic vaginal environment is averaged and becomes favorable for the development of pathogenic bacteria. According to Rohde, morbidity with spread of infection beyond the uterus and mortality do not depend on the duration of time from rupture of the bladder until the end of childbirth; morbidity due to endogenous infection increases with prolongation of time from rupture of the bladder until the end of childbirth. If childbirth continues 12-24--48 hours or more after rupture of the bladder, then the influence of this circumstance on morbidity is insignificant. According to data from the State Obstetric-Gynecological Institute on 16,604 births for 1910-1929. morbidity and mortality steadily increased with prolongation of time from rupture of the bladder until childbirth: Time (in hours) Fell ill (in %) 0-24 21-48 48-72 72 hrs. and more 4.32 8.21 9.83 14.18 Died (in %) 0.25 0.33 1.61 4.54 Furthermore, low attachment of the placenta and retention of its parts in the uterine cavity, retention of blood clots and liquid lochia; blood loss during childbirth; weakening of the body from acute illnesses shortly before childbirth and prolonged - chronic ones (for example diabetes sharply lowers immunity to staphylococci). As a result of decrease in general and local resistance a change in the purity of vaginal flora before childbirth is possible: up to 16.9% R° III and R° IV are found (according to Narcissus and Kopp). Some (Wirz) consider that the purity of vaginal flora in pregnant women has no influence on the course of P. p., others, most Russian authors, note greater morbidity in parturients with pathological flora during pregnancy (Krasnopolsky). According to E. Kaplun's data at R°I morbidity of parturients-7.5%, at R°III-11.1%. After abortion at R°III morbidity increases 4 times. Accidental infectious foci, e.g. dental caries, angina, can serve as sources of infection due to the fact that the birth canal as a result of trauma represents locus minoris resistentiae. Professional and socio-domestic conditions also do not remain without influence on morbidity and mortality. According to Jedd, the percentage of P. diseases is connected with the number of accidental injuries at production, which can cause puerperal infection. According to data from the State Obstetric-Gynecological Institute in Leningrad morbidity and mortality were greatest among the least privileged classes. Accidental epidemic diseases, e.g. influenza, significantly increase morbidity and mortality in P. p. (Mayer, Litvak).
(See below for more details). Classification. If we do not count Zweifel's proposal to divide fever patients according to the height of temperature, the time of its increase after childbirth, and its duration, then the majority bases the classification on the topographical-anatomical principle with consideration of bacteriological data. All postpartum infectious diseases are divided into local and general, although in both local and general forms, general phenomena of infectious diseases are observed. Local diseases include puerperal ulcers of the vaginal entrance and the vagina itself, endometritis, parametritis, local and general peritonitis, and thrombophlebitis of the uterine and pelvic veins. General diseases include pyemia, septicemia, and septicopyemia. The spread of infection can occur by 3 pathways (Fig. 21): 1) through the tubes, 2) through lymphatic pathways, and 3) through blood vessels. On autopsy material, it can be confirmed that a combination of these 3 pathways of infection spread is also possible. Method of infection spread According to Bel According to Galgin (in %) (in %) 1. Exclusively: a) through the tubes b) through lymphatic vessels (lymphogenous pathway) c) through blood vessels (hematogenous pathway) .... 2. Combined: a) through tubes and lymphatic vessels b) through tubes and blood vessels c) through lymphatic and blood vessels d) through tubes, lymphatic, and blood vessels ;Depending on the nature of the infection, pathways of spread, and localization, various forms of puerperal diseases occur. Classifications based on these principles are generally similar to each other.
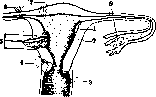
Figure 21, Pathways of infection spread beyond the genital tract: 1~into the thickness of the uterine salpingo-oophorostomy wall (detaching endometritis); 2-directly through the uterine wall; 3-through perineal, vaginal, and cervical ulcers; 4-into the parametrium through cervical ruptures; 5-along blood vessels; 6-through the uterine wall to the peritoneum; 7-directly through lymphatic spaces and vessels through the uterine cervix to its peritoneal covering; 8-along the tubes to the peritoneum of the small pelvis.
rit, parametritis, local and general peritonitis and thrombophlebitis of the uterine and pelvic veins. General diseases include pyemia, septicemia and septicopyemia. Spread of infection can proceed by 3 pathways (Fig. 21): 1) through the tubes, 2) through lymphatic pathways, and 3) through blood vessels. On autopsy material, one can be convinced that a combination of these 3 pathways of infection spread is also possible. Method of infection spread According to Bel According to Galgin (in %) (in %) 1. Exclusively: b) through lymphatic vessels (lymphogenous pathway) c) through blood vessels (hematogenous pathway) .... 2. Combined: a) through tubes and lymphatic vessels 12.7 20.0 39.1 16.4 7.3 3.6 0.9 7.0 29.5 21.6 12.0 2.5 21.0 6.5 b) through tubes and blood vessels c) through lymphatic and blood vessels d) through tubes, lymphatic, and blood vessels ;Depending on the nature of the infection, pathways of spread, and localization, various forms of puerperal diseases occur. Classifications based on these principles are generally similar to each other.
L. Bublichenko. Systematics of postpartum infectious diseases (puerperal fever) was the subject of development by a number of researchers, starting from ancient times. The first attempts of this kind date back to the time of Hippocrates and Galen, when the presence of pus was considered a sign of puerperal fever. If pus was found only in the birth canal, such a form of infection was considered a local form of the disease. When a collection of pus was found only in the uterus, this form of the disease was called "pyometra." If there was no pus in the uterus, but there was a high temperature with retention of lochia, this was called "lochiometra," and if in addition to pus in the uterus there were also gases, this was called "fizometra." If in such a local form of the disease no other abscesses were found on autopsy, they spoke of "septicemia." If pus was found in the blood vessels, they said that there was pus in the blood, and such a disease was called "pyemia." If, however, the disease after childbirth quickly ended in death and abscesses were found in both the sexual organs and the blood vessels and in the lungs and in various places on the periphery, they said that there was both septicemia and pyemia here, i.e., septicopyemia. All these terms, used even in the time of Hippocrates and Galen, are still used by us today, but their meaning is often completely different. The systematic classification of puerperal diseases began much later; the basis of the first classifications was the patho-anatomical changes in organs; along with this, the clinical side and the nature of the course of the process (local, general) were taken into account. An example of one of the first classifications is the Scanzoni classification. Scanzoni's Systematics (1857). 1. Inflammation of the vagina: ulcers of the vagina and its inflammations—catarrhal, croupous, and parenchymatous (with an abscess in the surrounding tissues). 2. Inflammation of the uterus: endometritis, metritis, metrotrombophlebitis (sometimes it extends to the plexus pampiniformis, internal spermatic veins, hypogastric, iliac, inferior vena cava, and the veins of both thighs), metrolymphangitis of the uterus (sometimes extends to the peritoneum and thoracic duct). 3. Inflammation of the peritoneum. 4. Inflammation of the ovaries and tubes. 5. Diseases of the blood—proper puerperal fever (febris puerperalis).—The next systematic attempts were made in the same 19th century, when the bacteriological era, created by Pasteur and Koch, deepened the understanding of the causes of puerperal fever and gave new grounds for the classification of its forms. The systematics of puerperal diseases began to be built not on the basis of the presence or absence of pus, but on the basis of the presence or absence of microbes, both on the surface of the birth canal and in its depths. At the same time, forms of puerperal infection began to be distinguished according to the way the infection spreads in the body (along lymphatic or blood vessels), and the general infectious puerperal process was divided into toxemia, or sapremia, and bacteremia, or septicemia. A prototype of such a classification is the systematics of Lea (W. W. Lea, 1910), who divides all postpartum diseases into 4 main groups: 1. Localized inflammation: vulvitis, colpitis, endometritis. 2. Inflammation spreading along lymphatic pathways and per continuitatem: lymphangitis vulvae, phlegmona vulvae, colpitis gangraenosa, metrolymphangitis, metrothrombophlebitis, metritis dissecans, abscessus uteri, salpingitis, pyosalpinx, abscessus ovarii, oophoritis, pelveocellulitis-localis et diffusa, peritonitis localis et diffusa. 3. Inflammation spreading along blood vessels: metrothrombophlebitis, phlegmasia alba dolens. 4. General infectious process of two types: 1) toxemia=sapraemia (putrefactive microbes); 2) general infection of the blood: a) septicaemia, or simple bacteremia; pathogenic microbes develop in the lymphatic and blood vessels; b) pyaemia, or thrombophlebitic bacteremia; pathogenic microbes develop only in thrombosed vessels. The distribution of cases of puerperal infection according to the bacteriological sign of hemolytic and non-hemolytic nature, according to the sign of saprophytism or virulence, according to the sign of one's own vaginal microbes, into fever from absorption (resorptive fever of German authors) and into septic fever—from the action of virulent streptococcs foreign to the puerperal woman's body, i.e., into true infection, was made by Fromme in 1909 in the following form: 1. Puerperal fever caused by: 1) saprophytic (one's own) vaginal microbes: putrefaction of wounds, one-day fever, intoxication fever, sapremia; 2) saprophytes multiplying in thrombi: thrombophlebitis, thrombosis of pelvic veins, chronic pyemia. 2. Fever caused by pathogenic foreign microbes (virulent streptococci): 1) localized infection: a) colpitis, endometritis septica (streptococcica), b) gangraena uteri puerperalis; 2) progressive infection: through the Fallopian tubes—a) pyosalpinx streptococcica, b) perimetritis circumscripta, abscess of the ovary, abscess of Douglas' space, diffuse peritonitis; through blood vessels—a) pure septicemia (bacteremia), b) acute and chronic pyemia, thrombophlebitis of pelvic veins, lower extremities; through lymphatic pathways—a) puerperal peritonitis, b) puerperal parametritis. This system, however, cannot be considered satisfactory, since non-hemolytic streptococci can be very virulent (Heineman), while the hemolyzing streptococcus can also be in the lochia of a healthy puerperal woman. Subsequent classifications are built not only on the patho-anatomical principle, but also on taking into account the bacteriological features of the infection with the subdivision of bacteria into saprophytic and parasitic. Such are the systematics of Bumm, Bublichenko. Bumm (1908) divided all puerperal processes into wound intoxication and infection. 1. Wound intoxication is caused by: 1) saprophytes, 2) microbes that do not penetrate into deep layers—intestinal, tetanus, and diphtheria bacilli. 2. Wound infection: 1) local processes—infection of wounds of the perineum, vagina, cervix, endometrium, and tubes, 2) spread of infection beyond the wound—a) along blood vessels: thrombophlebitis, pyemia and septicopyemia, b) along lymphatic pathways: metritis dissecans, puerperal parametritis, perimetritis and peritonitis.—Bublichenko (1930) in his systematics divided all diseases into: 1. Diseases caused by virulent microbes (so-called parasitic); in them the infection can be localized (ulcera puerperalia, endometritis septica, abortus septicus) and progressive: 1) through the Fallopian tubes per continuitatem (salpingooophoritis, hydrosalpinx, pyosalpinx, peritonitis circumscripta, pelveoperitonitis, peritonitis diffusa); 2) through lymphatic pathways [metritis dissecans, abscessus uteri, parametritis (more often primary), septicaemia] and 3) through blood vessels (thrombophlebitis, pyaemia, septicopyaemia, septicaemia, s. bacteremia). He also included diphtheria and tetanus toxemia in this group. 2. Diseases caused by non-virulent microbes (so-called saprophytes): 1) localized infection and 2) progressive infection through blood vessels. This subdivision into diseases caused by virulent and non-virulent microbes was not accidental; it consistently developed from Duncan's teaching on so-called sapremia or saprophytism, i.e., poisoning of the body in mild cases of local diseases with saprophytic poison, saprophytic toxin. In connection with this, the concepts of sapremia, saprophytism, and toxemia arose (for more details—see Saprophytes). Defenders of the division of microbes into saprophytic and parasitic (dualists) are Duncan, Spiegelberg, Lea, Bumm, Dederlein, Zweifel, Fromme, Bublichenko, Williams, etc. Defenders of the position that all diseases, both mild and severe, are caused by parasitic microbes (and there is no saprophytism) are Alfeld, Winter, Schotmuller, Hamm, Ilkewich, Pankow, Fabre, Brindeau, Chome, etc. An example of this type of classification of puerperal diseases is the systematics of Hamm, Jaschke and Pankow, Brindeau and Chome. In contrast to the principle of constructing the classification of forms of puerperal infection on the basis of bacteriological data, at the end of the 19th century (1870, school of Hervieux) there appeared a tendency to systematize the forms of puerperal infection only according to the anatomical localization of the lesions and to describe uterine, abdominal, pulmonary, cardiac, arthritic, meningeal, etc. forms. This tendency found no followers. Hamm's Systematics (1912). 1. Infection limited to the wounds of the birth canal: 1) ulcus puerperale perinaei, vaginae, cervicis, 2) endometritis puerperalis. 2. Infection spreading beyond the birth canal and divided into two categories, corresponding to the paths of spread: 1) along lymphatic pathways: metritis, parametritis, salpingitis, abscessus cavi Douglasii, pelveoperitonitis, peritonitis, sepsis et septico-pyaemia and 2) along blood vessels: a) local and further extending thrombophlebitis, b) thrombophlebitis with metastatic suppurations—pyemia.—Jaschke and Pankov's Systematics (1923) is based on the principle that there is no saprophytism—there is only infection.
Depending on the stages of infection arrest during its spread, it is necessary to distinguish: 1) infection of wounds of the vulva, vagina, uterus; 2) spread of infection to the inner surface of the tubes and from there to the ovary and peritoneum; 3) spread of infection along lymphatic pathways: parametritis, peritonitis; 4) spread of infection along blood vessels: bacteremia, septicopyemia, thrombophlebitis, pyemia. The positions put forward by dualists, that saprophytes give mild local forms of diseases ending in recovery, while parasites give severe forms with a fatal outcome (even if microbes cannot be found in the blood), are unconvincing, since the absence of microbes in the blood when it is cultured does not yet prove that they are not there, as they may not grow if they are anaerobes, as has been repeatedly observed in the so-called mixed infection. Mild diseases can also be caused by parasites with a normal reaction from the body, and the infection remains superficial. The hemolytic streptococcus can turn into non-hemolytic, which depends on the properties of the medium. In addition, the properties of microbes are not constant, microbes are not monoform but polyform, cyclic (Utenkov), and can during dissociation give new variants different from the previous ones not only morphologically but also in relation to biological and immunological properties (Arkwright, Levintal, Reniger-Areshova). The same infection with endometritis proceeds differently in different conditions depending on how the body reacts to it, i.e., the nature of the course of endometritis is influenced not only by the nature of the microbe. The same can be said regarding other forms of P. diseases. Therefore, the attempt to delineate P. diseases according to the microbes that caused them, as proposed by Varnier, Doleris, Kronig and Fromme (Varnier, Doleris, Kronig), does not withstand criticism at all. The systematics of Bredo and Shome (1927): 1) vulvovaginal infection, 2) uterine infection, 3) peruterine infection-a) infection of the appendages, b) pelveoperitonitis, infiltration and phlegmon of the broad ligaments; 4) diffuse peritonitis; 5) postpartum phlebitis; 6) postpartum septicemia.-It cannot be considered correct to build a systematics only on one patho-anatomical principle without taking into account the clinic. Patho-anatomical data must be used, but one cannot build everything only on them. These data are auxiliary, but not a guiding principle, just as the bacteriological principle is not guiding, since the course of forms of P. infection is generally the same for all microbes causing P. infection. For this reason, Ilkevich believes that neither bacteriological nor patho-anatomical data are fundamental for systematics and that its basis should be not only the clinic but also the concept of the dynamic course of infection.-Ilkevich based the classification on clinical data and arranged the forms of infection according to the degree of increase in the severity of the disease. The severity of the disease generally runs parallel to the degree of spread of infection, i.e., the more widespread the infection, the more severe the course of the process clinically and the worse the prognosis. From this point of view, all forms of P. infection (which Ilkevich in 1929 named histohaemopathia puerperalis infectiosa) are a process not static but always dynamic, a process not only of the advance of the infectious agent deep into the body but also of a reverse process, a process of attenuation of generalized infection, when the general infection of the body disappears and the so-called local form of infection settlement appears-in the form of a localized focus, in the form of transition to recovery. Ilkevich's systematics (1932) in connection with patho-anatomical and bacteriological data is presented in the following form: general name - histohaemopathia puerperalis infectiosa. The stages of P. infectious histohemopathy are expressed in the following forms. 1. Forms in which the blood is sterile: 1) infection is limited to the surface of the birth canal and uterus - ulcer puerperale vulvae, vaginae, endometritis; 2) infection is not limited to the surface of the birth canal and penetrates deeper a) along lymphatic pathways (lymphogenes): metritis, parametritis, salpingooophoritis, s. adnexitis, pelvioperitonitis, peritonitis diffusa, pyolymphia; b) along veins (phlebogenes): thrombophlebitis with gradually hardening and organizing thrombi - metrothrombophlebitis, thrombophlebitis ligamenti lati, pelvis, femoris et cruris; thrombophlebitis with softening and suppurating thrombi (thrombophlebitis purulenta)-metrothrombophlebitis, thrombophlebitis ligam. lati, pelvis, femoris et cruris; pyaemia. 2. Forms in which the blood contains microbes: 1) septicaemia (histohaemopathia lymphogenes bacteriaemica), which according to clinical course has three degrees: a) mild, b) moderate, and c) severe; 2) septico-pyaemia (histohaemopathia lymphophlebogenes bacteriaemica), having 3 subspecies according to clinical course: a) fulminant, b) developing from septicemia and c) developing from pyemia. Ilkevich considers the main clinical forms of P. infectious histohemopathy to be two: puerperal ulcer and septicemia. Of these, the primary, or initial one is (puerperal ulcer of the entrance, vagina, cervix and endometrium, and the other dynamic stages of infection are secondary, formed from the spread of infection deep into the body. There are two visible clinical pathways of infection spread: lymphatic with connective tissue and venous, although it must be considered in principle that infection always tends to spread simultaneously along both lymphatic vessels and veins. The clinical and patho-anatomical evidence of this is fulminant septicopyemia. Frequency of involvement of individual organs and tissues of those who died from septic diseases (according to Galban and Keller-163 cases): limited peritonitis-10 cases (6.1%); liver abscesses-3 cases (1.8%); liver degeneration-56 cases (34.4%); lung abscesses on the right-28 cases (17.0%); pneumonia on the right-38 cases (24.1%); panophthalmitis-4 cases (2.5%); parotitis-3 cases (1.8%); pneumonia on the left-19 cases (11.6%); subcutaneous abscesses-6 cases (3.7%); lung abscesses on the left-26 cases (15.9%); endocarditis-27 cases (16.9%); abscesses in the heart muscle-3 cases (1.8%); infarction of the spleen-8 cases (5.0%); abscesses of the spleen-4 cases (2.5%); migratory arthritis-8 cases (5%); diffuse peritonitis-50 cases (36.8%); intermuscular abscesses-8 cases (5.0%). Individual forms of postpartum diseases. Forms limited to the surface of the birth canal and uterus. These include postpartum ulcers and endometritis.-Postpartum ulcers of the entrance, vagina and cervix (ulcera puerperalia) are the initial form of P. diseases. The essence of this first stage of P. diseases lies in the infection of cracks formed during childbirth on the surface of the indicated organs, and is expressed by the appearance of films on them. These lesions are sometimes mild and appear as if in a veil. In other cases, where necrosis is more pronounced, the lesions are of the nature of films of gray or grayish color; only in diphtheria are the films white. Necrosis is caused by various microbes, among which streptococcus and staphylococcus are most often found in pure culture or in combination with different other rods and cocci (mixed infection). Microbial toxins irritate the area around the ulcers, redness, swelling and a burning sensation appear. All these phenomena usually begin on the 3rd-4th day after childbirth and are accompanied by an increase in temperature to 38.5-39.0° and a pulse rate of 80-88 beats per minute. Diagnosis is made without difficulty even in cases where there is no edema of the external genital organs. Spreading the labia with cotton swabs and examining the vagina with mirrors easily allows establishing the cause of the feverish condition of the puerperal woman - the presence of necrotic deposits on the cracks, which are also the source of the sensation of pressure and burning in the vagina and external genital organs felt by the puerperal woman. If there are sutures on the perineal tear and the superficial edges of the tear are also covered with necrotic films, the sutures are removed and the separated edges of the tear are washed with hydrogen peroxide and treated with tincture of iodine. This treatment is repeated for several days until all cracks are cleared of deposits and covered with good granulations. The entire febrile stage of the disease lasts 4-8 days, and complete recovery occurs in 10-12 days. If the infection penetrates the surrounding the entrance and vagina cellular tissue, then inflammation of it develops, called paracolpitis. Postpartum endometritis, endometritis puerperalis (see Endometritis), is the same first stage of infection development in the uterus as ulcera puerperalia are for the vagina and cervix. Patho-anatomical changes in the uterus extend to all its layers and do not allow speaking of inflammation of only the inner layer of the uterine wall, but the clinic notes here three independent forms of the disease: endometritis (endometritis), metritis (metritis) and perimetritis (perimetritis). The last two are complicated forms of endometritis with inflammation of the muscular layer of the uterus, on the one hand (metritis), and the peritoneal covering of the uterus on the other (perimetritis).
The histological picture of puerperal endometritis consists in general terms of necrosis of the superficial layers of the decidua of the uterus, mostly in the form of islands around the cervix, with small-cell infiltration around the foci, and edema of the adjacent layer of the myometrium, in which the lymphatic and blood vessels are dilated and in places thrombosed. - The deepening of the infection into the thickness of the uterine muscle is the transition to metritis. When the infection involves the peritoneum covering the uterus, there is perimetritis, and when the infection penetrates into the venous thrombi and the walls of the veins become inflamed - metrotrombophlebitis (metrothrombophlebitis). The most frequent cause of P. endometritis is the hemolytic streptococcus (in 31.4%); mixed infection occurs less frequently (in 19.1%), even less frequently staphylococcus (in 15%), bacillus coli (in 6.4%) and gonococcus (in 2%). A certain number of obstetricians distinguish under the name of resorption fevers special forms of febrile P. diseases caused by decomposition under the influence of bacteria and absorption from the uterine cavity of its contents. With retention and decomposition of lochia, lochiometra occurs (see). Under the influence of bacteria, blood clots accumulating in the uterus due to its insufficient contraction, as well as retained parts of the placenta and membranes, may also undergo decomposition. Other authors classify resorption fevers as mild and abortive forms of endometritis. Severe forms of endometritis have a febrile period averaging 7 days and generally last until recovery 17-19 days. The mortality rate in endometritis is 0. Forms of infection spreading along lymphatic pathways (lymphogenes). These include metritis, parametritis, salpingoophoritis, pelveoperitonitis, peritonitis diffusa and pyolymphia. Lymphatic metritis (metritis lymphatica). In this form of the disease, necrosis affects not only the deciduous tissue but also the deep layers of the uterine muscle adjacent to it. The infection does not stop at the stage of endometritis, but penetrates deeper into the muscular tissue, spreading along lymphatic pathways and only partly along blood vessels. The spread of infection along blood vessels usually does not manifest clinically, except in cases of late P. hemorrhages, when the organization of venous thrombi in the area of the placental site occurs incorrectly and the walls of some venous vessels also undergo necrosis. The size of the uterus is larger than in endometritis. It contracts worse. The temperature reaches 40.0°. The causative agent is more often the hemolytic streptococcus, which is sometimes already visible in chains in smears of lochia. The duration of the febrile period is about 2-21/2 weeks, the duration of the illness is about a month. There are no fatal outcomes, unless the process is complicated by late postpartum hemorrhage with symptoms of acute anemia. It can occur starting from the 2nd day and up to the 22nd and even 29th day after childbirth. This variety of metritis is one of the forms of P. infection, which Couvelaire named metrorrhagic (forme metrorrhagique de l'infection puerperale). In cases where infection and hemorrhage are expressed violently, i.e., where Couvelaire's septic-hemorrhagic syndrome is present, the mortality is high, and even extirpation of the uterus does not always save the patients. Abscess of the uterus (abscessus uteri). Sometimes metritis is complicated by an abscess of the uterus. In this case, the tissue melts along the course of the lymphatic vessels. Sometimes an abscess also forms in metrotrombophlebitis. When an abscess forms under the serous covering of the uterus, it can be confused with a parametric abscess or encapsulated peritonitis. In uterine abscess, the symptoms of severe metritis are complicated by purulent fever. The percentage of mortality depends on the complications with which the abscess is associated. Parametritis (parametritis puerperalis). Puerperal parametritis is defined as inflammation of the cellular tissue around the uterus, which depends on the spread of infection along the lymphatic vessels from tears of the vagina, cervix or the uterus itself (see Parametritis).- Postpartum inflammation of the tubes and ovaries (salpingoophoritis puerperalis, s. adnexitis)-see Salpingitis. The onset of adnexitis falls at the end of the second week after childbirth or miscarriage; adnexitis is more often unilateral (only in gonorrhea it is more often bilateral).- Postpartum pelveoperitonitis (pelveoperitonitis puerperalis, s. peritonitis saccata). After childbirth, pelveoperitonitis begins on the 14th-27th day, and after miscarriage-on average on the 15th day. Diffuse postpartum peritonitis (peritonitis diffusa post partum) more often begins from the 1st to the 5th day after childbirth, but if it is caused by the penetration of pus into the peritoneum from an abscess of the uterus, from a parametric abscess or from a suppurated periphlebitis, it can begin much later. Ilkevich observed the onset of peritonitis on the 16th day after childbirth and on the 30th day after miscarriage. (Clinical picture - see Peritonitis.) Pyolymphia - a disease described by Ilkevich, originates from endometritis et metritis lymphatica post partum, s. abortum and includes the following stages of lymphogenic infection: diffuse purulent peritonitis, purulent inflammation of one or both pleural cavities, purulent inflammation of the pericardium and purulent inflammation of the anterior mediastinum. The blood in this disease remains sterile from the onset of the disease until death. This form must be distinguished from a similar form described by Zweifel under the name pyaemia lymphogenes, which also included purulent lesions of the joints, since the latter complication is already a consequence of former septicemia. This disease is rare (1 case in 200-300 severe P. diseases) and is more often caused by hemolytic streptococcus, less often by a combination of it with staphylococcus and with various bacilli and cocci. It begins on the 1st-4th day after childbirth and always ends in death on the 4th-8th day after childbirth. The changes in the blood are the same as in diffuse peritonitis. Forms of infection spreading along the venous vessels (phle-bogenes) with their involvement. The stages of inflammatory involvement of the veins are: 1) thrombophlebitis with gradually hardening and organizing thrombi of the uterine veins, broad ligaments, pelvis and lower extremities, 2) thrombophlebitis with softening and suppurating thrombi of the uterine veins, broad ligaments, pelvis and legs, 3) pyemia.-1. Thrombophlebitis with gradually hardening and organizing thrombi. Metrotrombophlebitis (metrothrombophlebitis). In inflammation of the uterine veins that has developed after childbirth, pasty thrombi in the area of the placental site and in the veins of the cervix harden. Microbes that have entered them die. The thrombi in the end either dissolve or organize and are replaced by connective tissue. The imperfect organization of thrombi and the inflammatory disruption of the integrity of the venous walls can be the cause of late P. hemorrhages, which, as in metritis, are sometimes dependent on the retention of pieces of the placenta, and sometimes are exclusively an expression of the inflammatory reaction in the shedding uterine membrane, in its muscular and connective tissues and in its venous system. In this case, there is endometritis, metritis and thrombophlebitis of the uterine veins. The size of the uterus is enlarged. The amount of lochia is increased. The complete clinical picture of uterine thrombophlebitis, expressed in repeated chills without profuse sweating, with generally good well-being and a moist tongue, usually develops on the 11th-12th day after childbirth, but can also be present as early as the 4th-5th day after childbirth. In the latter case, the symptoms of endometritis are complicated by chills, and sometimes characteristic tortuous cords are found under the serous covering of a dense, painful and enlarged uterus without any palpable changes in the broad ligaments upon internal examination. The period of chills lasts from 7 to 12 days. The entire disease, if the thrombophlebitis does not spread to the veins of the broad ligaments and pelvis, lasts 5-7 weeks. There are no fatal outcomes in this form. Late postpartum hemorrhage in metrotrombophlebitis can be small, single, but can also be abundant and repeated with symptoms of moderate or acute anemia. In the latter case, a life-threatening hemorrhagic syndrome (see above) described by Couvelaire develops - frequent chills with sharp rises in t° to 41.0° and above, rapid pulse not corresponding to t°, shortness of breath, general poor condition. The curettage of the uterus undertaken to stop the bleeding in severe cases does not help, and even hysterectomy sometimes does not save the lives of such patients, because the generalization of infection occurs especially rapidly.- A special subtype of metrotrombophlebitis is the so-called postpartum dissecting inflammation of the uterus (metritis dissecans, s. gangraena uteri), consisting in the necrosis of a part of the uterine muscle due to thrombosis of all vessels (both blood and lymphatic) in the affected area with suppuration in the demarcation zone. The necrotized piece of the uterus usually comes out on the 3rd-4th week after childbirth. The disease is accompanied by severe febrile symptoms.
Recovery is the exception, as patients more often die from the resulting diffuse peritonitis or septicopyemia. Thrombophlebitis of the broad ligaments of the pelvis and lower extremities (thrombophlebitis ligamenti lati, pelvis, femoris et cruris). When thrombophlebitis extends to the veins of the broad ligaments and pelvis, not all veins are affected in a centripetal or centrifugal direction, but only certain ones, for example, the veins of the uterine plexus, plexus pampiniformis, ovarian, prevesical, pudendal, internal, middle, external, and common iliac veins, and the veins of the legs. When the common iliac vein is affected, the thrombus can reach the vena cava and then descend in the opposite direction into the common iliac vein of the opposite side; similarly, thrombophlebitis that has struck the hypogastric vein can extend through the external iliac vein into the femoral, vena saphena magna, and vena poplitaea. In former times, the latter condition was known as phlegmasia alba dolens (white edematous painful tumor of the leg). Depending on the location of the thrombophlebitis, a more or less dense, tortuous cord can be palpated in the corresponding area of the pelvis, which is usually painful only upon gynecological examination if it is not surrounded by an area of edema. The uterus is larger than normal, and is in retroversio or retropositio. Patients rarely complain of pain. The general condition is satisfactory. The pulse is accelerated to 100 or more. Daily fluctuations in temperature between 37.1° and 38.1° are interrupted by jumps to 40° and even higher for 1-2 hours. Chills recur daily, sometimes every other day, and sometimes less frequently. They usually last 5-7 days, sometimes up to 2 weeks. If the thrombophlebitis of one group of veins subsides, the chills cease, and the patient's condition approaches normal. The disease ends in recovery on average after 40 days; if after this the progression of thrombophlebitis per continuitatem continues into a new group of veins, the wave of temperature rises and chills returns, and the disease either ends at this point or continues to progress until the entire process concludes. Such a course can last up to 2-3 months. Mortality is not more than 1-2%. Changes in the blood are not characteristic; some decrease in Hb and erythrocytes and an increase in the number of leukocytes are noted. Phlegmasia alba dolens more often manifests as noticeable hardening of the subcutaneous tissue in the thigh area and, less frequently, in the leg, with the painful area being most often only the corresponding groin. The disease begins 2-3 weeks after childbirth, lasts 2-3 weeks, and complete recovery occurs after 6-8 weeks. 2. Thrombophlebitides with softening and suppurating thrombi (metrotrombophlebitis and thrombophlebitides of the broad ligaments, pelvis, and lower extremities). The entire proliferating thrombus is sometimes subjected to softening and suppuration, while at other times it only partially disintegrates, with the area of suppuration and softening communicating with the free blood flow. In cases where these changes in the veins of the pelvis and legs remain stationary, they do not produce metastatic foci in the lungs, and peritonitis does not join them per continuitatem; the venous abscesses become encapsulated and either become obliterated or spontaneously rupture into one of the neighboring hollow organs or to the outside. More often, however, the disease passes into pyemia or septicopyemia. Softening thrombophlebitides can begin independently on the 4th-5th day after childbirth, but more often they develop from thrombophlebitides that initially presented as hardening. This transition of the first thrombophlebitides into the second usually occurs on the 2nd-3rd week after childbirth. The clinical picture then changes sharply. The satisfactory general condition is replaced by a severe one; appetite disappears, sleep becomes poor, chills recur daily and even several times within a single day, ending in exhausting sweats. Chills may not be pronounced or may even be absent and replaced by shivering when the suppurating thrombus in the lower part of the broad ligament (more often in the plexus uterinus) is compressed by dense lymphogenous parametritis, the capsule of which then serves as a living ligature on the draining end of the affected vein. The temperature sometimes rises by 4-4.5° during the day, reaching 41.0°. The pulse is above 100, often irregular. Duration varies—from 6 weeks to 3 months or more. Most of these thrombophlebitides are the initial stages of pyemia or septicopyemia. Mortality is therefore different in various cases and reaches 37%. Recovery occurs in cases where venous abscesses remain local to the venous pathway, i.e., when they are surgically incised or rupture into the intestines, urinary bladder, uterus, or to the outside. In cases with a favorable outcome, after the initial decrease in Hb, erythrocytes, and lymphocytes, the blood composition approaches that of thrombophlebitides with hardening thrombi. In cases with an unfavorable outcome, the blood composition gradually approaches that of septicopyemia. In some cases, when purulent inflammation with thrombus disintegration involves not only numerous veins of the pelvis but also a large part of the lymphatic vessels in the pelvis, a dense infiltrate forms, occupying half or more of the pelvic cavity. The infiltrate may resemble parametritis. The uterus appears enlarged, embedded in a dense mass, the urinary bladder is displaced high upward, and the rectum is compressed. Chills are noted, and the temperature reaches 39-41°. The blood composition approaches that of septicopyemia. The blood is sterile. The disease lasts 6-8 weeks. Recovery is rare. When such an infiltrate is incised, the tissue appears like honeycomb, from which blood, mixed with pus in places, flows like from a sponge. Bleeding cannot be stopped during surgical incision of such pelvophlebitides, and patients die from blood loss. 3. Pyemia and septicemia—see* Sepsis.
I. Ilkevich. General symptomatology and diagnostics of postpartum diseases. Symptoms of postpartum diseases are extremely diverse and depend on the nature of the pathogen and the localization. The well-being of patients with local infection in mild cases is little disturbed, but in widespread or general [infection] it is significantly disturbed: insomnia, a feeling of fatigue, malaise, muscle pain, chills, headache. Cardiac activity (heart sounds) and blood pressure reveal characteristic changes (Jaschke). The pulse quickens to over 100, and in cases of peritonitis, to over 120-140. As a rule, the temperature rises. Each form of postpartum disease has its own typical temperature curve. Hematogenous infection (pyemia) is characterized by sharp fluctuations and chills. Smaller fluctuations occur in the presence of abscesses (pelvic abscesses). A relatively constant temperature is characteristic of lymphogenous infection (parametritis, peritonitis). An early and significant rise in temperature on the 2nd-3rd day after childbirth may indicate a severe infection. Bowel movements are usually delayed. In severe septic diseases, on the contrary, diarrhea is observed, sometimes foul-smelling. Blood changes in puerperal infection generally boil down to the decay of erythrocytes, a decrease in the number of blood platelets, an increase in the number of leukocytes (rarely to hypoleukocytosis), a shift of the neutrophilic picture to the left, the disappearance of eosinophils, and a drop in the number of lymphocytes. Blood viscosity decreases, clotting generally accelerates, but in hematogenous infection, it slows down (Brovkin and Robachevsky). The erythrocyte sedimentation rate increases sharply. The content of calcium, opsonins (Wright), complement (Smorodintsev), and catalase (Brovkin) is lowered, while bilirubin is increased. In hematogenous infection, blood cultures reveal the presence of bacteria. Local signs. Lochia change their character. They become brownish, with a putrid odor, or purulent. Microscopic examination reveals the pathogen of the disease with greater (gonococci) or lesser (streptococci) probability. Reverse involution of the uterus is delayed. The cervix is congested and hyperemic. Plaques appear on the mucous membrane of the vagina and cervix, as well as inflammatory tumors and infiltrates; disorders during urination and defecation are not uncommon. All this is accompanied by painful sensations of various kinds in the abdominal area, in the groin, and in the area of the external genital organs. The examination should not be limited only to the genital sphere. It is important to determine the constitution, the state of the cardiovascular system, lungs, kidneys, liver, spleen (enlargement, tenderness), digestive organs (tongue, intestinal bloating), nervous system (paralysis, apoplexy, neuralgia), eyes (hemorrhages and other changes in the retina), ear, nose, and throat as sources of hidden infection. All these additional examinations are important not only for the diagnosis of a postpartum disease but also for its differentiation from any other accidentally occurring disease of a non-puerperal nature (for example, influenza, angina, tuberculosis, etc.). Valuable data are provided by bacteriological examination of the blood and examination of formed elements (according to Schilling): accounting for the ratio of various forms can also be an aid for diagnosis (Schilling index, Krebs, Shepetinskaya, Bublichenko). To establish the character (color, reaction, consistency) of the lochia, as well as to establish the pathogen, their macroscopic...
bacteria by hemolytic...
...properties, blood and lecithin test...
Fromme test, Louros and Fuss test (Louros, Fuss), based on the determination of streptococcal resistance. Figure 22. Smear from the uterus in endometritis: erythrocytes, leukocytes, diplococci.
of streptococci. Like other biological properties, resistance has relative significance. More important is the determination of virulence in relation to a given organism. An attempt to solve this problem can be seen in the method proposed by Ruge and Philipp (Ruge, Philipp) (upon verification, the Ruge-Philipp reaction turned out to be not flawless). Technique of the Ruge-Philipp reaction. 5-7 cm3 of blood is taken from the patient's cubital vein and defibrinated in a small flask. Then 1-3 loops of lochial secretion (depending on the amount of bacteria in it) are stirred into 5 cm3 of meat-peptone broth, and from there, 3-5 loops are transferred into the defibrinated blood. From this mixture, 2 cm3 of blood is added to 10 cm3 of melted and cooled to 40° meat-peptone agar, the mixture is poured into a Petri dish (No. 1) and this dish and the blood with bacteria are placed in a thermostat. After 3 hours, 2 cm3 are taken again from the defibrinated blood with bacteria of the lochial secretion and mixed with meat-peptone agar, as before (dish No. 2). Both dishes are left in the thermostat. If after 12-24 hours there are more bacteria in the second dish than in the first, the bacteria are virulent. For diagnostic and prognostic purposes, skin reactions to the injection of streptococcal cultures, strepto- and staphylococcal antivirus, and Dick toxins were tested. For example, Kohler observed a positive reaction to streptococcal vaccine in the presence of a streptococcal infection. A weak reaction to the antivirus indicates the severity of the disease, a strong one indicates a good prognosis (Ravina). Some authors (e.g., Bublichenko) believe that the reaction is more strongly expressed in women who have ever had a streptococcal infection. A positive skin reaction to the Dick toxin according to Kunz and Nobel (Kunz, Nobel) can be considered as a sign of predisposition to puerperal fever; the Dick reaction is not suitable for prognosis. Tuberculosis disease serves as a source of error when judging the Dick reaction. The main thing for diagnosis is the examination of the genital organs; it consists of an inspection of the perineum and the entrance (presence of tears, character of wound surfaces), and the cervix upon opening with specula (observing antisepsis and asepsis). At the same time, smears from the lochia are taken with a platinum loop or a cotton swab from the middle of the posterior fornix and the cervix, or with special instruments from the uterus (Döderlein tubes, Walgard's pin, Sitsinsky cigarettes) (Figs. 23-25). If necessary and in the absence
Figure 23. Sitsinsky cigarette [drain] for obtaining uterine secretion.
of contraindications (sutures, plaques), a bimanual examination is performed, which determines the state of the cervix, the size of the uterus, position, density, tenderness, and the presence of inflammatory tumors and infiltrates. The height of the fundus is determined by palpation from the outside. Along with the examination of urine, in case of suspected cystitis, a cystoscopy should be performed. Examination of the urinary tract is necessary for differential diagnosis. Clinical observations show that their diseases occur in the postpartum period significantly more often than previously assumed, whereas the usual signs of cystitis—frequent urges, pain during urination—can very often be absent in the postpartum period. It is important to timely and accurately determine the localization of the infection beyond the pelvic organs using appropriate examination methods, adopted

Figure 24. Walgard's pin for obtaining uterine secretion.
in the therapy of internal diseases (percussion, auscultation, for example in pneumonia) and surgery (for example, puncture in metastatic abscesses). The prognosis for postpartum infection is determined in the initial stage by the general resistance of the organism and the local reaction of tissues at the site of bacterial implantation, as well as by the virulence of the bacteria. Since the aggressiveness of bacteria manifests itself more strongly as the resistance of the organism decreases, it is obvious that these two quantities are in an inverse relationship, and it is not always possible to say definitely which manifestations of the infectious process depend on the decrease in the resistance of the organism and which on
Figure 25. Döderlein's tube for obtaining uterine secretion.
of high virulence of bacteria. In an already developed disease, the course and outcome depend on the localization of the pathological process—whether the spread of bacteria is limited to the vagina and uterus or they are localized in the nearest areas beyond the uterus or spread without an adequate response along lymphatic pathways and especially through the blood vessels, through which they can be carried to the most distant parts of the body (metastases). In such cases, the outcome of the disease depends to a large extent on the localization of bacteria in one or another tissues and organs. with Sachs proposed the following formula: P = ~- In this formula P-prognosis-can be expressed in numbers depending on C-resistance of the body, L-localization of the pathological process and M-virul- C ence of bacteria. If the ratio -^ reflects the actual relationship between the body and bacteria, then the introduction of L into the formula as a multiplier is not realistic. Moreover, the exact determination of each value C, M and even L with modern research methods is by no means always easy (for this reason the practical value of the formula is not great). Prevention of postpartum infections consists of: 1) weakening and elimination of infectious material (microbes) from contact with postpartum injuries, 2) elimination of conditions favorable for penetration into the body and development of infection, and i 3) strengthening the general non-susceptibility of the body. Preventive measures can be individual in relation to each parturient and public. Ind i-; vidual profilakt i k a do b e-: remennost i-proper physical. development and physical education, preventing complications of the act of labor.-Prevention during pregnancy aims to: 1) increase immunity, 2) eliminate exogenous infection and 3) destroy or neutralize microbes in the genital tract and its vicinity. To increase immunity, vaccination with killed cultures of streptococci from 100 to 500 million was proposed (Jotten, Lauros, Elkin, Mironova). To avoid the negative phase during vaccination before delivery itself, vaccination and simultaneous introduction of serum were used. Despite the encouraging results of ordinary vaccination in the hands of individual authors, there are reasons to doubt its effectiveness, for which many are negative about it. In particular, vaccination only with streptococci is not flawless in that a fairly significant part of puerperal infections are caused by staphylococci and other bacteria. For the purpose of prevention, subcutaneous injections of strepto- and staphylococcal antivirus were proposed simultaneously at 0.2-0.3 cm3, and -by some (Bublichenko) a decrease in morbidity and mortality was noted. It is important to remove pregnant women from contact with patients with purulent and other infectious diseases, timely treatment of them in the pregnant woman or isolation, for example with dressings, of purulent processes; treatment of diseases of the urinary tract. For the purpose of direct destruction of pathogenic bacteria or weakening their virulence, preventive douching of the vagina in pregnant women with pathological flora with 0.5% lactic acid (Zweifel), with sublimate (Okin-~chits) were recommended. However, the effectiveness of treatment with sublimate, ; as well as with other antiseptics, is ; more than doubtful. An important preventive measure, both in general for complicated pregnancy and labor, and in relation to P. infection, is the proper general regimen and elimination of factors weakening the pregnant woman's body. Prevention during labor consists mainly of measures of antisepsis and asepsis. General baths are not recommended. They are limited to washing under the shower. In many clinics, this is supplemented by shaving hair on the external genital parts, their disinfection, at least in primiparas. Disinfection of the vagina itself is not performed except in operative cases [recently some have proposed the introduction into the vagina before and after labor of disinfectants, e.g. rivanol according to Gusic, in small amounts (with a Brown-ovsky syringe)]. In pathological labor, the introduction of serum was proposed. Proper conduct of labor is important: abstention from internal examination in the absence of precise indications for its performance, replacement with external examination, abstention from operative procedures in the absence of sufficient indications. To prevent the introduction of bacteria from outside during internal examination and operative procedures and even during i normal labor, rubber gloves and other devices (Kampitz), a linen sleeve (according to Okinchits) were proposed. All tears of the perineum and vagina require suturing, tears of the cervix-if of significant size and with bleeding. It is necessary to ensure complete emptying of the uterus-removal*-of blood clots,-retained parts of the placenta and membranes, if they are protruding into the vagina. In the P. p., observation of good contraction of the uterus, individual care (separate cup, tip and dressing material for each parturient), cleaning with gloves and with the help of instruments (forceps, specula), isolation of infected parturients are recommended. Measures of public prevention. This includes the development of stationary obstetric care (see Maternity hospital, Obstetric care). Obstetric institutions-the most perfect form of obstetric care and the best school for introducing into the masses rational views on the process of labor and care for the parturient. A significant role in the prevention of P. diseases is also played by consultations for pregnant women. In consultations, cases of diseases of the urinary tract-cystitis, pyelitis (as etiological factors for increasing t° in the P. p. and the occurrence of P. diseases in the literal sense), and other inflammatory and purulent processes-can be timely detected and subjected to appropriate treatment. In the consultation, the question of the necessity and inevitability, in necessary cases, of placing the pregnant woman in a ward is also decided; no less importance is attached to the san.-educational work in the-; goals of establishing the correct regimen and be-; havior of the woman both in the last period of pregnancy and in the P. p. to prevent postpartum infection (abstinence from sexual intercourse, observance of cleanliness, neatness, etc.). An essential measure is the liberation of women from work, thereby creating favorable conditions for the future parturient's body in terms of general resistance. In this respect, Soviet legislation goes significantly ahead of others, providing working women with 1st/- 2-month leave before childbirth. Further development of socialist construction will bring changes in socio-domestic conditions in the direction of reducing the burden on the pregnant woman from family, household, etc. obligations. The correct line of behavior on the part of society and legislation in relation to miscarriages and illegitimate children, as experience has shown, e.g. on the issue of abortions, has also given positive results in terms of reducing septic morbidity. Treatment. The general principles of treatment of P. infection at present cannot be considered established. There are many transitions from extreme activists to advocates of complete non-interference. Methods of treatment of septic infection can be divided into two groups: 1) local treatment and 2) general, aimed at affecting the whole body. The first may aim to: a) destroy or weaken the infection at the place of its entry into the body, b) contribute to its delimitation, localization. The second can be directed: a) to the destruction of bacteria and their toxins in the blood directly, b) to the general mobilization of all protective mechanisms of the body, c) to maintaining the vital-and n functions 1 ulv\ of the body until /, localization and ] complete destruction of the infection by one or another method. - Disputed. 26. Emptying the contents of the sov m e-cavity of the uterus in case of delay in excre- ^
J tion in the postpartum period by straight-(-ening the T N O G O L uterus located in anteflexion: 1) HI-the uterus through the abdominal coverings. MIChvSKIye* washings of the vagina and uterus with disinfectant solutions (sublimate, manganese, riva-nol and the like), lubrications (tincture of iodine), introduction of deodorizing substances (animal charcoal, etc.); 2) physical: depending on the nature and stage of the disease or the application of cold (ice on the abdomen) or, conversely, after the acute stage-heat (compresses, hot water bottles, warm and hot douches with indifferent solutions, constant irrigation according to Snegirev), application of radiant energy; 3) biological: introduction into the vagina of biolactyl Fournier, bacilosan (Leiser and Schweitzer), cultures of vaginal bacilli in broth with grape-
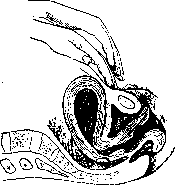
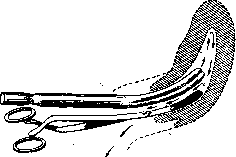
ris. 2 7. Mutual position in the uterine cavity of the Sitsinsky tip and the Rishello forceps at the moment of washing to ensure free outflow of the washing fluid.
with sugar (vagozan), Bezredka's antivirus; 4) mechanical: washings of the uterus with indifferent or hypertonic solutions, drainage of the uterus with gauze and rubber or glass tubes, straightening of the uterus to empty its contents (figure 26), application of a suction cup according to the Bier principle, and surgical treatment (curettage of the uterus, opening of abscesses, etc.). Combinations are possible: thus, Sitsinsky's uterine ligation consists of washing it with a cold solution of sublimate (1:2,000), hot boric acid, strong alcohol, and drainage with iodoform gauze. Irrigation of the uterus and vagina can be single or so-called continuous (for several hours), with a nozzle with a single current (according to Sitsinsky's method, fig. 28. Instrument with two branches for the outflow of fluid during uterine washing. Rischel; fig. 27) or catheters with double current (Fritsch-Bozeman, Doleri; figure 28). Continuous irrigation according to Snegirev (of the vagina) is performed with the help of a nozzle with weak antiseptic solutions, t° 45-50°. Treatment with antiseptic solutions of an infected uterus and vagina cannot be considered radical, but the use of antiseptics in other areas of medicine (urology, ophthalmology), as well as observations by supporters of local treatment of an infected uterus (Sitsinsky), give reason to believe that in the absence of other more effective methods for destroying infection at the site of its introduction, they cannot be excluded from the methods of therapy of P. diseases. The negative side of antiseptic methods, as well as intrauterine therapy in general, is the danger of damage to the granulation belt and generalization of infection. Indications for treatment with antiseptics are initial forms of puerperal infections in the first 2-3 days of increased t°. Uterine washings are contraindicated when the infection has spread beyond its limits (ineffective) and when there are coatings (severe infection). Douching of the vagina without urgent indications (profuse purulent and ichorous discharge) is not recommended before the 7th day of P.p. (recently, some have been used extremely rarely). Indications for uterine washings have also been significantly reduced. Physical methods are favored in conservative therapy as being less traumatic. Continuous irrigation according to Morozov-Snegirev (previously very widespread), in which no actual irrigation is performed, has all the positive qualities of prolonged application of heat; it is especially appropriate in infections of retained parts of the placenta. Radiant energy for local treatment is not currently used. Biological methods of local treatment belong to the future, while those available to us at present are not always effective. Introduction into the vagina of tampons soaked in strepto- and staphylococcal antivirus (together) for 3-4 consecutive days can give good results even with severe coatings and necrosis of the vagina and cervix. Of the mechanical methods of local treatment, washing with indifferent and hypertonic solutions has the same negative sides as washing with antiseptics (trauma). Uterine drainage with gauze acts for a short time (4-6 hours). Rubber and glass tubes for uterine drainage are unnecessary and easily cause necrosis. In case of accumulation of discharge (lochiometra), straightening of the uterus is appropriate (see above). The action of the suction cup may consist of: 1) suction of uterine contents, 2) increased transudation into the uterine cavity of wound secretions, which increases the bactericidal properties of lochia, and 3) causing congestive hyperemia (healing according to Viru in inflammatory processes). In general, indicated for local treatment are initial forms of septic puerperal processes and various forms of resorptive fevers at the first temperature increases (2-3rd day). When the infection has spread beyond the uterus (parametritis, adnexa, and pelvic peritoneum), intrauterine therapy is contraindicated; with septic coatings, intravaginal therapy is also contraindicated. Treatment is limited to external application of cold, antivirus, and smearing of accessible coatings. Mechanical methods of treatment also include surgical procedures. Curettage of the postpartum uterus is dangerous. Curettage and disinfection of the uterine cavity in incomplete infected abortions in most cases gives an immediate decrease in temperature and smooth recovery. It may be indicated in the absence of coatings and clinical signs of the infection spreading beyond the uterus (pain, fresh infiltrates and effusions). In the presence of highly virulent bacteria even without signs of the infection spreading beyond the uterus, curettage does not prevent generalization of infection and may even promote it. Among Russian and German obstetricians, at present some adhere to conservative treatment of febrile abortion, while others prefer active treatment (curettage). In case of retention and infection of placental parts, their removal is recommended only when there is life-threatening and dangerous to the health of the patient bleeding (Winkel). Many French obstetricians recommend curettage and disinfection of the uterus and even subsequent removal if curettage and disinfection do not give results in the coming days. Most German and Russian obstetricians adhere to conservative treatment. Despite the fact that the question of uterine removal has been repeatedly debated at international congresses, it cannot be considered definitively resolved at present. Collections of pus accessible to surgical treatment should be opened. Suppurating parametrites are most often opened above Poupart's ligament, extraperitoneally (Bardenheyer incision) (fig. 29). Limited pelveoperitonitis are opened by colpotomy through the posterior fornix. Purulent pleuritis requires puncture and suction followed by the introduction of rivanol or resection of a rib. The almost complete hopelessness of conservative treatment of peritonitis has forced obstetricians to switch to surgical treatment by opening the abdomen along the midline and in the lateral parts with drainage of the abdominal cavity. The earlier the opening is performed, the better the results it gives. However, P. peritonitis gives the worst prognosis even with surgical treatment, as they are often a partial manifestation of the general septic process. In pyemia, ligation of veins according to Trendelenburg extraperitoneally or better transperitoneally with or without excision of affected areas is recommended. The veins are ligated above and toward the center from the affected area. The epigastric, common iliac, or spermatic vein is ligated on one or both sides. More than 10 cases of ligation of the inferior vena cava have been published; mortality is 50% (Korn). According to Little's collective statistics, out of 100 cases, the overall mortality rate in ligation of pelvic veins is 50%. Recently, interest in vein ligation has increased again. The results are doubtful, indications are not always precise. Methods of general treatment-see Sepsis.
Figure 29. Opening of a pelvic abscess rising above Poupart's ligament; the incision is made parallel to it and slightly higher-extraperitoneal incision: 1- pelvic abscess; 2- line of incision; 3-uterus; 4-adnexa.
d is performed, the better results it gives. However, P. peritonitis gives the worst prognosis even with operative treatment, as very often they are a partial manifestation of the general septic process. In pyemia, ligation of veins according to Trendelenburg extraperitoneally or better transperitoneally with or without excision of affected areas is recommended. The veins are ligated above and toward the center from the affected area. The epigastric, common iliac, or spermatic vein is ligated on one or both sides. More than 10 cases of ligation of the inferior vena cava have been published; mortality is 50% (Korn). According to Little's collective statistics, out of 100 cases, the overall mortality rate in ligation of pelvic veins is 50%. Recently, interest in vein ligation has increased again. The results are doubtful, indications are not always precise. Methods of general treatment-see Sepsis.
l. Bubpichenko. IV. Postpartum Psychoses. Postpartum psychoses encompass an extensive group of mental changes observed in connection with childbirth, the postpartum period, and lactation. Properly speaking, the consideration of postpartum psychoses as a separate nosological unit has rather historical interest. In-depth study of a number of psychoses and familiarity with exogenous forms of reactions have ultimately led to the conclusion that postpartum psychoses represent mental changes of various character and cannot under any circumstances be regarded as a sui generis disease. The primary causes of postpartum psychoses are, above all, infectious, septic processes, auto-intoxication due to metabolic disorders, profuse bleeding, exhaustion of the body, and finally, mental factors. Constitutional features and hereditary predisposition determine a greater or lesser susceptibility to mental changes. Mental changes during the act of childbirth itself are observed very rarely. Satinger reports only one case of mental disorder among 12,215 parturient women. In psychopathic individuals, in isolated cases during childbirth, hysterical reactions, brief twilight states, and outbursts of excitement with violent actions against the staff and a desire to kill the newborn are observed. These conditions are of great importance for forensic psychiatric examination. Among the psychoses observed immediately or in the very nearest time after childbirth, especially great significance is attached to mental changes in connection with eclampsia (see Eclampsia). Mental changes in the postpartum period are observed within the first 8 weeks after childbirth. Engelhardt's statistics, covering 19,910 births, indicate that the number of mental illnesses among parturient women does not exceed 0.14%. The majority of puerperal psychoses fall on amentive forms associated with various infectious, septic processes in the postpartum period. From this point of view, it is quite natural that with the introduction of asepsis, the number of puerperal psychoses has significantly decreased. Along with amentive forms, other exogenous forms of reactions are observed—delirium, twilight and stuporous states. In addition to the large group of puerperal psychoses where infection is undoubtedly the etiological factor, the remainder falls on endogenous mental disorders—schizophrenia and manic-depressive psychosis, and on psychogenic disorders. In his statistics of postpartum psychoses, Runge attributes 25% to amentive forms, 6.68% to eclamptic psychoses, 19.64% to manic-depressive psychosis, 36.84% to schizophrenia, and 7.89% to psychogenic disorders. Endogenous psychoses developing in the postpartum period, in their course, differ in no way from the usual pictures of schizophrenia and manic-depressive psychosis. One can only point to the predominance of catatonic forms in schizophrenia and an anxious-hypochondriacal coloring in depressive states. The course and prognosis of puerperal psychoses depend on the type of mental disorder. Therapy is reduced to combating the infectious, septic process and falls within the framework of general therapy of psychoses. In most cases, the psychopathic phenomena observed in the picture of postpartum psychoses require the internment of the patient in a psychiatric hospital. This internment appears particularly important in cases where suicidal thoughts or aggressive tendencies toward the newborn are noted in patients. With manifestations of motor and speech excitement and impulsive drives, a strict bed regime, daily warm baths at 28-29° are indicated. Motor excitement and insomnia usually lead to significant exhaustion of the body, therefore strengthening treatment and enhanced nutrition are also necessary. Prevention of postpartum psychoses is reduced to eliminating the harmful elements that play a role in the genesis of mental disorders. Patients with neuropathic heredity, who have already once suffered a mental disorder during pregnancy or childbirth, should be very cautiously allowed to consider new childbirth. During childbirth and the postpartum period, it is necessary to protect the parturient woman from any mental trauma and create conditions for her complete physical and moral rest. Among the necessary preventive measures must be included the careful observance of asepsis both during childbirth and throughout the entire postpartum period, as well as the elimination of all factors exhausting the body (prolonged labor, bleeding, metabolic disorders, etc.). The so-called lactation psychoses most often manifest between the 3rd-5th month after childbirth. Older authors attributed too much importance to the phenomena of exhaustion associated with lactation. It should be assumed that in the occurrence of these psychoses, rather, the biological changes occurring in the woman's body during childbirth and for a considerable time after play a role. The number of lactation psychoses is small. According to some authors (E. Meyer), it does not exceed 1.6%. Most often, young, multiparous women become ill. Symptomatologically, lactation psychoses represent in a small percentage of cases amentive forms associated with an infectious process (mastitis or a septic process continuing for a significant period after childbirth), but for the most part, these are only exacerbations of schizophrenia and manic-depressive psychosis. In view of the special affective lability of nursing women, under appropriate circumstances, psychogenic disorders easily arise in them. These include the transient "jealousy delusion of nursing women" (Siemerling), arising from their prolonged, forced sexual abstinence and doubts about marital fidelity.
Related articles
Mentioned in
Cite this page
“Postpartum Period.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/postpartum-period/