Operating Room
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928-1936 Soviet Medical Encyclopedia describes the historical development and technical requirements for operating rooms in medical institutions, focusing on proper lighting, ventilation, and architectural considerations.
Encyclopedia article (1928–1936)
Operating Room, a room specially designated for performing operations. Such a room is provided in the plan of a general hospital institution, a special surgical department, or a surgical clinic; a room for operations can also be allocated and adapted from among the existing rooms in a building, which for one reason or another (for example, during military actions) is designated as a field hospital or infirmary. It is not possible to specify with even approximate accuracy when in Russia a room specially adapted for performing operations was first built. In Y. Chistovich's 'History of the First Medical Schools in Russia', the following note is found: 'hospitals in the proper sense, i.e., as medical institutions not only for care but also for treating the sick, hardly existed in Russia before the middle of the 17th century'. Thus, from the point of view of historical truth, it would hardly be very erroneous to assert that the first operating room in Russia was planned only in the construction plan of the first hospital in Russia, namely the 'Moscow Hof Hospital', built by decree of Peter I, given on May 25, 1706, across the Yauza River 'for treating sick people'. This hospital was also the first medical school or medical-surgical school in Russia. In those times, when neither ether nor chloroform nor other anesthetic agents were known, when operating rooms were rooms of suffering, cries, and groans, the surgeon, choosing a place where he could operate without causing fear to those lying in the wards and awaiting their turn (of patients), had to first think about this room for operations being as far as possible from the hospital wards. In addition, it was required that it at the same time be sufficiently light, well heated, and easily supplied with water. Strictly speaking, these are the minimal requirements that surgeons still make for operating rooms, when they have to adapt some room in a building that is not at all hospital, which had a completely different purpose and was only偶然 allocated for a hospital. With the development of surgery, surgeons' requirements for operating rooms have significantly increased. Antisepsis and asepsis have so deeply entered the surgeon's consciousness that the possibility of achieving maximum 'surgical cleanliness' during operations has now turned into a series of requirements for the architect in constructing the operating room. Technically complex operations that have entered or are now entering surgical practice may also make certain demands on the architect both in terms of the construction itself and in terms of installing various technical devices needed for performing operations. The same can be said regarding the equipment of the operating room with furniture and special instruments. Thus, a series of requirements is made to the builder, which must be taken into account by him when developing the plan of the operating room. They come down to the following: good and proper lighting; good heating, preferably not connected with the heating of the rest of the building; the possibility of easiest and most convenient access to any corner of the operating room for the purpose of cleaning and maintaining maximum cleanliness. Lighting. The greatest convenience for work in the operating room is provided by diffused daylight. Bright sunlight interferes not only because it blinds the eyes, but also because the sun's rays, especially in summer, can heat the air in the operating room so much that it becomes very difficult to work. Therefore, when choosing a location for building the surgical building or when planning the space for the operating room, it is necessary to orient oneself relative to the cardinal points. The windows of the operating room should not face south. It is best if they are located on the north, north-northeast, or north-northwest. If in addition to the window or windows in the front facade wall, there are also windows providing side lighting, then the orientation relative to the cardinal points must be particularly strict and well thought out. The fact is that operating tables are usually arranged perpendicular to the main window, and thus side windows providing additional light, by passing bright sun rays, will only lead to excessive heating. Having adopted as a rule for the operating room the use of diffused light in natural lighting, it is necessary to first ensure that this light penetrates in sufficient quantity, and secondly, that it is distributed evenly throughout the operating room without shadows. Usually, the daylighting of all hospital buildings is done through wall windows, but in operating rooms, sometimes top lighting is added, which is obtained by means of so-called lanterns. Although through a lantern the most diffused, shadow-free light is obtained, the installation of top lantern lighting in a cold climate is associated with overcoming great technical difficulties, as it is necessary to avoid the possibility of condensation on the lantern glasses and thus eliminate dripping over the operating table. For this, it is necessary to install a double or even triple glass ceiling, to install in this ceiling a whole system of pipes or radiators for constant heating of the lantern. In addition, it is necessary to constantly monitor the timely removal of snow. Therefore, it is better to limit oneself only to window lighting, having made certain requirements for the installation of windows. Architectural standards for light ratios vary for different rooms depending on their purpose. For operating rooms, the standard ratio of the area of the light opening to the floor area is adopted as 1:2.5 or 1:3, but this assumes that the window light is not obstructed by anything, and the light area of the windows is taken as the clean area of the window glass without sashes and muntins. For operating rooms, the form of windows that best satisfies proper lighting will be rectangular. For the needs of lighting the operating table, it will be more advantageous if the height of the window is greater than its width. The upper edge of the window should be as close as possible to the ceiling. Instead of top lighting of the operating room with a lantern, it is quite rational to consider raising the front wall of the operating room upward by one to two meters. By raising the window wall in this way, the ceiling is also cut off 1.5-2 m from this wall and stretched upward to connect with the wall, thus forming an angle of approximately 45°. Thanks to this, the light area is correspondingly increased, and the operating table receives, although somewhat oblique, top lighting, which reduces the possibility of the operating field being shaded by people standing around the table during the operation. Such raising of the wall upward can be done not across the entire width of the wall, but only corresponding to the width of the main, central glass, opposite which the operating table stands (see separate table, fig. 1 and 2). In operating rooms, glazing of windows should preferably be done with as large as possible mirror glasses 8-10 mm thick. Window frames should be reduced to a minimum. It is especially necessary to avoid horizontal crossbars in the window frame opposite the operating table itself, as they give a shadow directly on the table. The material for making window frames and their muntins is wood or iron. Iron window frames for operating rooms should be considered the most rational, as they do not rot, warp, swell, and can be made thinner than wooden ones. It should be emphasized that when making operating room window frames, special accuracy must be observed; this same accuracy is also required when fitting them. In our climate, window frames are made double. The space between the two frames in the operating room hall should always be sufficiently wide and fully accessible for inspection and cleaning from all dust (fig. 1). Such
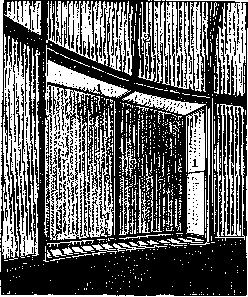
Figure 1. Garnier window system: 1-air filter; 2-inner protective frame from wind; 3-outer protective frame from wind; 4-box for heating.
access for cleaning is always necessary, since despite the greatest care in constantly maintaining cleanliness in the operating room between the frames and on the inner surface of the window panes, settled dust particles can always be found, which is especially noticeable if hospital buildings are heated with coal. The central mirror glass is usually made stationary, with only side sashes in the frame. The side sashes are made opening or rotating around a vertical axis—thereby achieving the possibility of both maintaining cleanliness between the frames and ventilating the room if there is no ventilation in the operating hall or it is insufficient to quickly ventilate the room in case of necessity. Special rubber gaskets are embedded in the window sashes, thereby achieving tightness when closing the window. Central heating pipes are placed between the frames or directly beneath the inner frame itself. This is done with the aim of avoiding freezing at double glazing of the interwindow air layer, which is always possible with a rapid drop in external temperature. Such freezing leads to the formation of dripping due to the condensation of water vapors, which are always sufficient in the operating room. Window frames are recommended to be made either without window sills, flush with the inner surface of the wall, i.e., in other words so that the window frame appears as if it were a direct continuation in the same plane of the inner surface of the wall, or the window sill is made very narrow, sloping downwards. This aims to avoid the accumulation and settling of dust, and furthermore to avoid the use of the window sill by staff for placing various necessary and unnecessary objects on it. All of the above applies only to windows located in the operating room itself. As for windows in rooms auxiliary to the operating hall (in the preparation room, in the sterilization room, etc.), the requirements for their construction by both the surgeon and the architect may not be so strict. These windows may also not be made of solid mirror glass, which can well be replaced here by white, double Bohemian glass (4 mm). The insertion of glasses must be carried out on double putty. As for the sterilization room, in which a lot of steam always accumulates, it is desirable to make the window frames and their sashes of iron in it. No matter how transparent and colorless the glass is, it still retains a certain amount of light and the more so the thicker it is. With double frames, the loss of light can even reach 25–30%. This circumstance also has to be kept in mind when calculating the illumination of the operating room. The pedantic attitude towards cleanliness requirements in the operating room, towards ensuring that there are no extra objects in the operating room that can always be a place where dust accumulates, forces surgeons to completely reject any curtains or blinds on the windows of the operating room. To avoid the possibility of seeing from the outside what is being done in the operating room, the windows in it up to a certain level, different in different cases, are made of corrugated or frosted glass. It is necessary to take into account that corrugated glass absorbs up to 50% of the light, and frosted glass up to 70%. In the question of lighting, a significant role is also played by the color of the walls and ceiling, since the lighter the color, the more rays it reflects and the less it absorbs. Surgeons have generally rooted the opinion that everything in the operating room should be painted white, light, should shine—on white, on light, every speck of dust is sooner noticed. But many surgeons have long pointed out that the excessive whiteness of the operating room acts in a tiring manner on the eyes of the surgeon. Carrel was apparently the first who dared to go against such a requirement of painting the operating room white and painted his experimental operating room at the Rockefeller Institute black. In the Union, the first to speak out against such routine was Oppel. One of the operating rooms in the surgical department of the Mechnikov Hospital (in Leningrad), which he heads, is entirely black. Not only are the walls of the operating room painted with black matte paint black, but also the floor lined with black tiles, tables, stools, etc., linen, gowns, caps, masks. Much earlier, Oppel, having received the propaedeutic clinic in his charge, equipped the operating room in gray. Objections, for example, that the psyche of the patient is depressed by the black color, etc., can be considered completely insignificant, and Oppel is right in saying that these objections cling more to prejudices than have a real basis under them. If we still consider the "black" operating room to be as much an extreme as the white one, then the search for a paint that would be pleasant to the eyes and give them rest is completely understandable. In the question of lighting, a major role is played by the reflective and absorptive capacity of the ceiling, walls, etc., which entirely depends on the color of their paint. Poltavtsev has a table showing the comparative absorption and reflection capacity of various paints. Paint color White ....... Light green . . , Light yellow . . , Light blue . . Dark yellow . . Dark green . . Dark brown Dark blue . . , Black ..... Reflects (in %) Absorbs (in %) 54 60 70 80 90 91 94 99-9. These properties of paints—to reflect and absorb light in a certain percentage—must be taken into account when painting the operating room. When calculating the norms of light illumination, one must also take into account, especially with unilateral illumination, the depth of the operating hall. The depth of the room should not exceed the height of the window frames by more than 2.5 times, and all calculations concerning lighting usually proceed from such a depth; in terms of using the useful area of the operating room, a greater depth also appears completely superfluous. It is much more advantageous if the operating room is wider than long and narrow. All walls and ceiling in the operating room can be painted or laid with colored tiles, or only the panel made to a certain height (approximately human height) can be colored. If we take into account mainly that the eyes of the surgeon and those working in the operating room can rest from intensive work that makes high demands on lighting, as well as the desirability of a certain coziness of the room, then bright colors should of course be considered unsuitable. From the experience of the Botkin and Kremlin hospitals (Moscow), it should be recognized that very successful colors are light blue and light green. In the Botkin hospital, the panel is painted with light blue paint—metal sheets covering heating devices. In the Kremlin hospital, one of the operating rooms is entirely lined (both ceiling and walls) with bluish-green tiles. The operating room makes a very calm impression, the eyes are not tired. Some operating rooms in the Kremlin hospital, small, for one table, are lined with slightly yellowish tiles (cream, ivory color), and at the height of a panel two tiles wide, colored tiles, bluish and greenish, are laid with a wide border. Such colored stripes, interesting in an architectural sense, also provide an opportunity for the eyes to rest sufficiently and can quite be recommended for introduction into the construction of operating rooms. But such wide border stripes will nevertheless sooner come into everyday use for painting small operating rooms, since despite the softness of the light green and light blue tones in large operating rooms painted in pure white, such a border will stand out too sharply. The walls and ceiling of the operating room (it should be noted that all joints between walls, ceiling, and floor are made with rounded corners) can either be lined with tiles of appropriate colors or painted with paint. In the latter case, the paint must be exclusively oil-based so that the operating room can be washed. The paint must be chosen of the best quality: putty, priming, and the painting itself must be done in the most careful way to reduce to zero the possibility of the formation of any irregularities, blisters, cracking of the paint and its peeling. Artificial illumination. Very strict requirements are put forward for the artificial illumination of the operating room. In the case of an emergency in an operating room deployed completely by chance, only temporarily adapted for performing an operation, for example, in combat conditions near the front lines, any light source can be used, even simple candles, observing only some precautions. However, the only fully acceptable light source for the operating room must be recognized as electrical energy. The products of combustion of kerosene, illuminating gas in combination with chloroform give compounds that are far from indifferent to the person being chloroformized; a burning flame can easily cause an explosion of ether vapors when it is used for anesthesia. All these minuses, of course, do not exist with electric lighting. In addition, when using electricity, we can freely bring the degree of illumination of the operating field to the desired brightness. In recent years, various firms have proposed a number of lamps that are built on mirror systems. These lamps make it possible to center strong light exclusively on the operating field. Such concentration of light on the operating field leaves the rest of the operating room almost in twilight, so that additional lighting plafonds in the ceiling or walls are necessary, otherwise it is very difficult for the operating nurse to work with instruments.
The principle of construction of these surgical lamps for the operating room is interesting in that the head and hands of the surgeon and his assistants cast almost no shadow on the operating field—a circumstance of essential importance in the operating process. Soft penumbrae are of no significance, since such shadows from the bent head of the operating surgeon also occur with well-diffused daylight. Most authors who have worked on operating room equipment, as well as surgeons, have now settled on lamps placed directly above the operating table. Apparently, the illumination proposed a few years ago from a powerful arc lamp located outside the operating room has been completely abandoned. This light was captured by spherical mirrors placed at a specific angle already
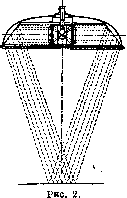
inside the operating room itself, and cast onto the operating table. However, the installation of such lighting was so bulky and expensive that it did not become widespread.
The majority of new operating rooms are now equipped with lamps hanging directly above the operating table. The most commonly used lamps should be considered the following: the "Scialitique", which is particularly warmly recommended by Heller, with which one can fully agree; then the lamp of the French firm Barbier Renard in Turenne with a transverse diameter of 90 and 75 cm; a system of prisms from an incandescent light bulb casts a bright light onto the operating field via mirrors at a distance of about 120 cm from the lamp (Fig. 2). The "Asciatique" lamp (Prof. Resp), also a French model by the firm Gallois et Co. in Lyon. Equally wonderful "shadowless" lamps have been manufactured by the firm Carl Zeiss in Jena (see separate table, figure 2). All these lamps are mounted so that by a system of rods the lamp can always be easily moved forward or backward, as well as rotated in one direction or the other, so that the light can be freely directed to wherever it seems necessary to the surgeon. This ability to maneuver the direction of the light rays is essential when operating somewhere in the depths, especially since during this work in the depths the operator is greatly helped by the absence of shadows from his head. All these lamps have one drawback, which during a more or less prolonged operation becomes quite noticeable: the surgeon's head can feel quite strongly the heat radiated by the lamp. This drawback is apparently least of all present in the Zeiss lamps. Lamps of the indicated models are manufactured not only as hanging over the table, but also in the form of wall sconces, or they are made movable on stands (Fig. 3). The latter model is very convenient both for additional lighting purposes and during gynecological operations, and operations on the rectum, where working with only overhead light is difficult. These mobile lamps are manufactured in various sizes, with diameters of 30, 40, 50, and more centimeters. Spherical, ball-shaped lamps "Kugelspiegellampe" mounted on a spherical hinge were proposed by the Zeiss firm to illuminate the operating table; the light source is a powerful incandescent bulb centered in a mirrored hemisphere so that the reflected light rays, like in an automobile
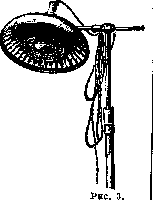
headlight, travel almost parallel, in a weakly diverging beam of light. By placing several such spotlight lamps on the ceiling and using their spherical hinges, all the light coming from them can be concentrated on the operating table. The operating rooms in the Botkin Hospital are illuminated by such Zeiss lamps, and it can be said that these lamps allow good illumination of the depth of the wound, working in cavities, and the penumbrae from them are completely negligible and interfere with nothing. When illuminating with these lamps, the just-mentioned drawbacks—the radiation of heat onto the surgeon's head—are not noted, since the light source is located very high.
Regarding the electrical wiring in the operating room, the following must be kept in mind. Electrical wires must be passed through Bergman insulating tubes, but there is no need to strive for these tubes to be pushed into the wall itself. Such exposed wiring does not spoil the appearance of the wall at all (provided the wiring is done neatly), it is accessible for any inspection of the conducted network, and also in case of need for repair. If the tube is pushed into the wall, then any repair of the network entails a disruption of work in the operating room. When wiring the electrical network, one must always remember that it is necessary to make several sockets of the usual amperage for lighting purposes and higher (20A) for technical purposes in appropriate places: for diathermy, for electrocoagulation, for vacuum cleaners, for cinema equipment, etc. With the improvement of lighting technology, many surgeons began to use local lighting of the operating field even during the day. Can such a decision on the issue of lighting be considered correct from a sanitary and hygienic point of view? This question is also debated in the literature. At the XVIII Congress of Russian Surgeons, Pampulov in his report "The Operating Room from a Sanitary and Hygienic Point of View" spoke out against such widespread use of local artificial lighting in the operating room, considering it harmful to the surgeon's eyes. It is hardly possible to argue against the fact that only with daylight does one get a correct idea of the coloration of tissues, and the ability to have uniform, quite sufficient, non-bright, non-blinding, natural lighting in the operating room is the primary concern when constructing an operating room. But working in the depth of the wound sometimes appears very difficult despite excellent daylight, and having the opportunity at the right moment to cast light into the depth of the wound from rationally arranged electric lamps is highly desirable. Hygienists believe that artificial lighting that meets the requirements of better visibility in the absence of excessive harshness at the same time should be at least 130 lux. (Lux is the illumination of a surface of 1 m2 from 1 lumen, the light of which is distributed uniformly. Lumen is the unit of luminous flux. A lumen is equal to the flux emitted within a solid angle equal to unity by a point light source of one international candle power shining equally in all directions.)
OPERAT
4. Heating. In the climate of the USSR, with its frequent and sharp temperature fluctuations, the question of heating the operating room is a complex task. The heating system of the operating room must be arranged so that it is not connected with the heating of the rest of the hospital premises. This is necessitated by the need for a higher temperature in the operating room in autumn and spring, when hospital wards do not yet need to be heated. In addition, care must be taken to ensure that during operation times the heating works without a noticeable increase in temperature; the maximum increase allowed is 1-2°. This can be achieved by installing good thermostats, which can also be automatic. A certain role in this thermoregulation is played by the influx of fresh air into the operating room, i.e., the corresponding ventilation arrangement (see below). The following requirements apply to heating: the ability to bring the temperature to the desired level and the arrangement of heating devices in such a way that they are not sources of dust, that dust does not settle on them and burn, i.e., that the devices are either concealed or fully accessible for constant inspection and cleaning from all sides. When installing the heating, it must be taken into account that, in order to avoid bringing excessive dirt and, consequently, infection into the premises, the stokers do not enter the operating room itself or even the scrub room. All these listed requirements are easiest to achieve with central heating. Local stove heating can only be tolerated for small hospitals, as it does not lend itself to any more or less strict regulation in terms of temperature uniformity and constancy. When installing stove heating in the operating room, it is necessary to insist that the firebox be in the corridor and that the stove be lined with smooth, glazed tiles to avoid dust burning. When using these stoves, extreme attention to the air vents is also required (soot, the possibility of carbon monoxide entering the room if the stove is not closed in time). Despite all the disadvantages of Dutch stoves for the operating room, they have one significant positive side: when using them, exhaust ventilation is easily implemented. Of the various central heating systems, low-pressure water heating must be placed in first place. With proper monitoring of the firebox and using devices for automatic regulation, the desired uniform temperature can be maintained here with negligible fluctuations in either direction. In terms of installation, this system is 15-20% more expensive than steam, but it is better regulated and is very advantageous in operational terms. The low-pressure steam system, quite common in many hospital institutions in the West (especially Germany), cannot be particularly recommended. It produces excessively dry air, and since the heating devices heat up to 60-80°, particles of organic dust burn on their surface. In other heating systems (Untermark stoves, central hot-air heating, caloric heating), there are even more shortcomings than with Dutch tile stoves. As for the issue of installing the heating system inside the walls, this results in an advantage in terms of the neatness of the operating room, its appearance, and a reduction in the possibility of dust settling, but on the other hand, there is always the threat of breaking the wall for repairs. It is recommended either to place the main pipes in the adjacent scrub room, bringing out into the operating room only short sections of the supply and return pipes, or not to fear dust and to place the pipe risers exposed in the operating room itself. With disciplined personnel and the use of vacuum cleaners, there is absolutely no need to fear dust. But pipes can also be handled differently: they can be laid in specially lined channels that are closed with metal sheets that easily open or unscrew for inspection. These channels must be opened from time to time both to inspect the pipes laid in them and to remove the accumulating dust. Heating devices and radiators must be installed so as to be constantly accessible for inspection and cleaning from all sides. It is more correct to place these radiators in niches made in the walls and close these niches with metal sheets that are, of course, easily removable. Such installation of radiators in niches results in a certain loss of heat, which the technician must take into account in their calculations. In many new surgical departments in Germany, one can find radiators placed completely openly at a distance of half a meter or even a meter from the wall. Such an installation has the convenience that they are fully accessible from all sides not only to the vacuum cleaner, but also to simple wiping. If for some reason the radiators are located in niches under windows and these niches are not closed, it is better not to put these radiators on the floor, but to hang them on brackets so that their distance from the floor is at least 0.12-0.15 m; then it will be quite possible to wipe the floor under them. The distance between the wall and the radiator in such cases should also be approximately the same figures. Radiators must always be smooth; ribbed batteries are under no circumstances allowed, as the accumulation of dust on them will always cause great inconveniences during cleaning. The heating devices are painted with fire-retardant paint. The question of what temperature should be considered optimal seems very simple, namely: the optimal temperature is close to our body temperature. Under such conditions, the cavities opened during operations should undergo minimal changes from the effects of temperature. But this answer is, of course, completely theoretical, since it is completely impossible for a surgeon to work at a temperature close to 37°. Most surgeons consider 25-32° (20-25° Reaumur) to be most acceptable for the operating room, but even at such a temperature it is hard to work if there is no well-functioning ventilation in the operating room. It is easier to work at a temperature of 22° (17° Reaumur). Ventilation. With good, precise fitting of window frames and glass and painting of the walls with oil paint, one should not particularly count on more or less significant infiltration of fresh air through the pores of the walls or through any cracks, and therefore such natural ventilation hardly needs to be taken into account. Natural ventilation of the operating room in summer can be carried out by opening windows, which is best done through transoms. In addition, one should never forget that if the ventilation of the operating room is carried out through opening windows, transoms, or even vents, the outer frame must be equipped with a well-fitted mesh that completely prevents the access of flies and other insects. The disadvantage of all vents is that when they open, outside air enters in a wide stream, creating a strong draft. With a properly arranged transom, such a sensation should not occur. Natural ventilation through windows, vents, and transoms can, of course, be used more or less widely only in summer; in winter, it can be resorted to only as an extreme measure, in the absence of artificial ventilation. Ventilation of the operating room must be supply-and-exhaust with filtration, heating, and humidification of the air. Ventilation must provide for the supply of 2.5-3 air changes per hour in the operating room, and for the exhaust 1.5-2 changes. On average, a double air exchange in the operating room can be considered quite sufficient. A stronger air exchange is not desirable because it will already be perceived unpleasantly. Very often, the ventilation system of a building is arranged so that it is connected with the heating, and the ventilation therefore operates only when the heating network is operating. Such joint operation of both the heating and ventilation networks is the most economical, but it is hardly possible to apply this principle of economy in relation to the operating room and the premises directly connected with it. Not to mention the warm season of the year when buildings are not heated, even in winter ventilation in this case will operate only at certain hours, and work in the operating room can far from always be adapted to these hours of general ventilation. However, it seems necessary to ventilate the operating room constantly. The way out of the situation, at least for supply ventilation, is the installation of additional electric fans. These fans are placed in the exhaust supply ventilation openings that open directly into the operating room. These fans are powered by small motors of 1/8 to 1 horsepower (Fig. 4). Based on the experience of the Botkin Hospital, it can be argued that the installation of these electric fans as an addition to the main ventilation network is entirely appropriate. A rather significant disadvantage of these fans is the loud noise they produce.
Regarding the question of whether it is necessary to filter the air entering the operating room, the opinion that has become quite firmly established in the literature is that in suburban hospitals, where the air entering the intakes is clean and unpolluted, it is possible not to filter the air by placing the air intakes in a garden among greenery. This can be agreed with only if the heating of all hospital buildings is conducted on liquid fuel, i.e., oil. In the Botkin Hospital, the air entering the operating room is filtered through filters made of several layers of gauze. When heating is conducted on oil, this gauze has to be changed very infrequently: once every one and a half to two months; however, when the boilers are heated with coal or peat, the filters become clogged after a few days with particles from the coal and peat, the gauze becomes dirty, black, draws air poorly, and must be changed. The supply ventilation chambers located in the operating room must be equipped with a tightly closing door into which a window is cut, so as to always have the opportunity to control whether the chamber is maintained in proper cleanliness and whether it serves as any kind of storage place. One cannot pass over in silence the proposal to ozonize the air entering the operating room (Henriet system). It is assumed that ozone is a poison for bacteria, and ozonized air enters the operating room as if sterile. There is no data on the high bactericidal action of such ozonized air, but one cannot object to the deodorizing action of ozone, and thus the installation of ozonizers in the supply chambers of septic operating rooms can be considered quite rational. When using ozonizers, one must remember that their operation must be under constant control, because an excessive influx of ozone into the room causes irritation in the respiratory tracts and even attacks of headache. The operating room must be sufficiently provided with water, both cold and warm, and if there is the slightest possibility, even sterile. There is no reason to make any special demands on water pipes compared to the pipes of the heating network, and everything said about the wiring of those pipes remains in force for the water pipes as well. The sewage equipment of the operating room has always been difficult in its technical execution. The reason for this is the fear of having places in the washbasins, in their traps, in their inspection system where dirt and various infectious agents accumulate and stagnate. Hence such a variety of models of washbasins for servicing operating rooms, proposed and offered by various firms. A controversial issue associated with the sewage network is the installation of floor drains in the operating room and preoperative rooms. There are authors who speak out sharply against the installation of floor drains, considering them almost a focus of infection, but the majority of surgeons and builders consider this fear to be groundless. The twenty-year experience of the Botkin Hospital also speaks in favor of floor drains. It is necessary to emphasize here the attentive, conscious attitude of the operating room personnel to cleanliness, to the washing of the operating room; then there is no danger of infection either from the washbasins or from the floor drain. To be able to maintain cleanliness in the operating room, there are certain expedient devices. These are, firstly, a water tap of the fire-hose type, which makes it possible to wash the entire operating room, all its corners, with a strong jet of water using a hose, and secondly, a tap connected to the steam pipeline. Having such a tap, it is possible to fill the entire operating room with steam, which, settling, will carry away with it dust particles with microorganisms accumulated on them. Such cleaning of the operating room can be considered the best. The area and height of the operating room can be given only in very approximate figures, because in calculations of the operating room, all the features not only of the operating room itself, but also of the entire institution that this operating room will have to serve must be taken into account each time: for example, whether it will serve for teaching purposes or not, the expected operating throughput, whether work will be conducted on a single operating table, or whether constant simultaneous work on two tables is assumed. The average figures given by Poltavtsev approximately coincide with the figures of German authors (Winterstein). Area of the operating room per one table: 30 m2, per 2 tables: 35-40 m2. Height: 4.25-5.30 m. In the Botkin Hospital, where constant work is conducted on two tables, one operating room has dimensions of 8.75 m × 5.45 m, and the other 10.85 m × 6.25 m. The dimensions of these operating rooms quite freely allow working simultaneously on three tables. Based on experience, one can object to such simultaneous operations on three tables, as this undoubtedly introduces a certain bustle into the work of the operating room and produces a certain noise, walking, disrupting the general tone of the operating room. (The indicated smaller figures correspond to the depth of the operating room, the larger ones to its width, i.e., its extension along the window wall.) In the Kremlin Hospital, where work is always performed on only one table, the dimensions of the operating room are 5.10 m by 4.75 m. The height in both hospitals is the same: 4.25 m. But in these operating rooms, the front half of the ceiling is raised upward by 1.50 m higher, in order thereby to obtain upper lighting and increase the illumination not only of the operating table itself, but also of the depth of the operating room itself (see separate tables, Fig. 1 and 2).

Figure 4. Ventilation chamber in the operating room of the Botkin Hospital. At the top, the grille of the electric fan is visible. Through the glazed door, heating radiators are visible, warming the incoming air.
dirty, black, sucks air poorly, and it is necessary to change it. Supply ventilation chambers located in the operating room must be equipped with a tightly closing door, into which a window is cut, in order to always have the opportunity to control whether the chamber is maintained in proper cleanliness and whether it serves as any storage place. It is impossible to pass over in silence the proposal to ozonize the air entering the operating room (Henriet system). It is assumed that ozone is a poison for bacteria, and ozonized air enters the operating room as if sterile. There is no data on the high bactericidal action of such ozonized air, but one cannot object to the deodorizing action of ozone, and thus the installation of ozonizers in the supply chambers of septic operating rooms can be recognized as quite rational. When using ozonizers, one must remember that their work must be under constant control, because excessive influx of ozone into the room causes irritation in the respiratory tract and even attacks of headache. The operating room must be sufficiently provided with water, both cold and warm, and if there is the slightest possibility, even sterile. There are no grounds to present any special requirements to water pipes in comparison with the pipes of the heating part, and everything said about the wiring of those pipes remains in force for the water pipes as well. The sewage equipment of the operating room has always been difficult in its technical execution. The reason for this is the fear of having places in the washbasins, in their traps, in their inspection system where dirt and various infectious elements accumulate and stagnate. From here comes such a variety of models of washbasins for servicing operating rooms, proposed and offered by various firms. A controversial issue associated with the sewage network will be the installation of floor drains in the operating room and preoperative rooms. There are authors who speak out sharply against the installation of floor drains, considering them almost a focus of infection, but the majority of surgeons and builders consider this fear to be groundless. Twenty years of experience at the Botkin Hospital also speaks in favor of floor drains. It is necessary to emphasize here the attentive, conscious attitude of the operating room personnel to cleanliness, to the washing of the operating room, then there is no danger of infection either from the washbasins or from the floor drain. To make it possible to maintain cleanliness in the operating room, there are certain expedient devices. This is, firstly, a water tap, of the fire-hose type, which makes it possible to wash the entire operating room, all its corners, with a strong stream using a hose, and secondly, a tap connected to the steam pipeline. Having such a tap, it is possible to fill the entire operating room with steam, which, settling, will carry away with it dust particles with microorganisms accumulated on them. Such cleaning of the operating room can be considered the best. The area and height of the operating room can be given only in very approximate figures, because in calculating the operating room, all the features not only of the operating room itself, but also of the entire institution that this operating room will have to serve must be taken into account each time: for example, whether it will serve for teaching purposes or not, the expected operating throughput, whether work will be carried out on one operating table, or whether constant simultaneous work on two tables is assumed. The average figures given by Poltavtsev approximately coincide with the figures of German authors (Winterstein). Area of the operating room per one table: 30 m2, per 2 tables: 35-40 m2. Height: 4.25-5.30 m. In the Botkin Hospital, where constant work is carried out on two tables, one operating room has dimensions of 8.75 m × 5.45 m, and the other 10.85 m × 6.25 m. The dimensions of these operating rooms completely freely allow working simultaneously on three tables. On the basis of experience, one can object against such simultaneous operating on three tables, as this undoubtedly introduces a certain fussiness into the work of the operating room and gives a certain noise, walking, violating the general tone of the operating room. (The indicated smaller figures correspond to the depth of the operating room, the larger ones to its width, i.e., its extension along the window wall.) In the Kremlin Hospital, where work is always performed on only one table, the dimensions of the operating room are 5.10 m by 4.75 m. The height in both hospitals is the same: 4.25 m. But in these operating rooms, the front half of the ceiling is raised upward by 1.50 m higher, in order thereby to obtain upper illumination and increase the illumination not only of the operating table itself, but also of the depth of the operating room itself (see separate table, Fig. 1 and 2). For the work of the operating room, sufficiently well-equipped sterilization and preparatory rooms are necessary. The sterilization room is a room where everything that comes into contact with the wound surface is sterilized: dressing material, linen. The preparatory room is a room where the surgeon and his assistants wash before the operation. In this same room, as in the previous one, there are sterilizers for boiling instruments. Life has not worked out any special norms for the development of these premises. The sterilization room is usually located in direct proximity to the operating room, and if there are two operating rooms in the construction plan of a given surgical department (e.g., for aseptic operations and for septic ones), it is recommended to place the sterilization room between them, because door communication between the sterilization room and the operating room is usually not made. Some surgeons cut a window in that partition wall that separates the operating room from the sterilization room. In this window, the sterilizer for boiling instruments is then located, which are removed already directly from the operating room. Such an arrangement certainly has an advantage, because the instruments prepared for the operation are always at hand for the operator. But when arranging such a window, it is always necessary to remember that this frame-window, separating the operating room and the sterilization room, should be well fitted and not let excess steam into the operating room from the sterilization room, but at the same time rise and fall well and easily. In view of the constant accumulation of excess steam in the sterilization room, particularly careful attention must be paid to the insulation of electrical wiring; clocks—a necessary accessory of the sterilization room—are recommended to be of the so-called ship type, sufficiently hermetic so as not to let through excess moisture. Special equipment of the sterilization room is an autoclave and an apparatus for sterilizing instruments. Sterilization can be carried out by various methods. Where there is no central steam or electricity, sterilization is carried out on primus stoves or, if there is gas, on gas burners (as an exception, one can find wood- or coal-burning). All these latter methods must be considered only forced. If we consider that the autoclave and the sterilizer for instruments (and silk) are the minimum necessary for performing operations, the maximum equipment of the sterilization room is quite indefinite and extensible. Special firms, e.g., Lautenschläger or Küster (Germany, Berlin), provide sterilization room equipment that can simultaneously be serviced from a special steam boiler or central steam pipeline and from the electrical network if for some reason the steam is not working. This installation includes:
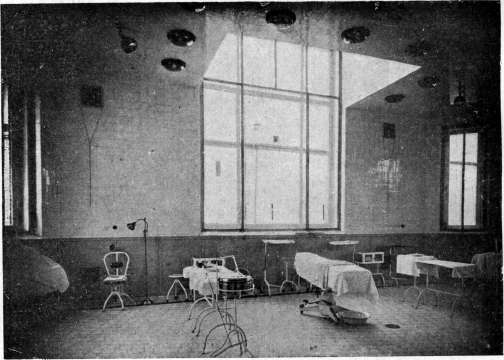
Figure 1. Operating room of the Botkin Memorial Hospital.
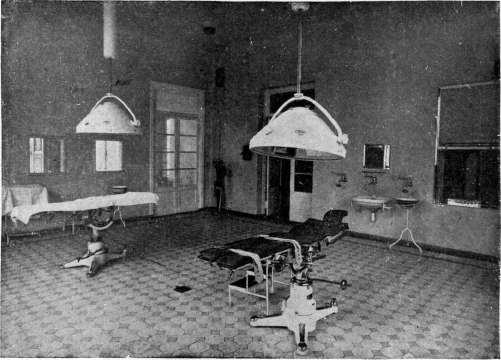
Figure 2. Operating room of the Sklifosovsky Institute of First Aid.
See the article Operating Room. Autoclave, one or two, apparatus for sterilization with dry air, apparatus for sterilizing instruments, for sterilizing solutions, for warming linen, for preparing physiological solutions, for sterilizing water, for obtaining distilled and bidistilled water (Figure 5). If the sterilization room is quite large, it can also serve as a material room where the preparation of dressing material—gauze, cotton, lint—for sterilization drums takes place; it is also recommended to store the drums with spare sterile dressing material here. If this room is small, then a separate room should be allocated for the material room, or it can be combined with the instrument room where instruments are stored. If one or the other institution is severely cramped for space, then some special place must still be allocated for preparing sterile dressing material and for its storage, not a random corner that is constantly changing. Any inaccuracies in sterilization are unacceptable. Drums with sterile material must always be kept under lock. Preparation room. Its basic equipment is washbasins, which come in the most diverse styles and designs; portable washbasins are made either with pedals or with hand faucets and they are easily obtainable everywhere. As for permanent, wall-mounted washbasins, it is necessary to emphasize the need for the faucet handles to be made long, so that the surgeon, when washing hands, can open the faucet without touching it with the already washed hand, but with the help of the elbow. It is highly desirable that warm water also be supplied to the washbasins, and even better if it is sterile. In some surgical institutions, the sterilization of water for washing surgeons' hands is done by ozonation, but this method, despite the sufficient sterilization of ozonated water, has not yet become widespread, and sterilization of water at high temperature is more common. Sterile water, prepared by one or another apparatus, is distributed through pipes to the washbasins. To ensure the sterility of the water, it is necessary that the water pipe be connected to the steam pipe. By passing steam through the pipes during water sterilization, sterility of both the pipes and the faucet itself can be ensured, but it is still recommended to conduct more frequent bacteriological examinations of the water that is considered sterile. The preparation room communicates directly with the O. through a door. This door should open not into the O., but towards the preparation room. Furthermore, it is better to cut the door into the O. not in the middle of the wall, but closer to the side walls. This increases the size of the free space both in the O. and in the preparation room, which can be usefully used for various installations and furniture. Many surgeons quite rightly consider it necessary that when building a special operating department, a separate room—anesthesia room—should be allocated, with an area of at least 20-25 m². There are many patients who are afraid of the sight of the O. and, agreeing to the operation, ask to be put to sleep not in the O.; moreover, for such anesthetics as avertin or rectal ether, isolation of the patient is necessary to carry out such an anesthesia in as much quiet and calm as possible—these two considerations alone fully justify the establishment of a separate anesthesia room. Of the special equipment of the O., operating tables deserve special attention (see). In lecture O.s, it is possible to completely separate from the listeners by glass partitions, who watch the operation through the glass partitions, and the explanations made by the surgeon can be perfectly heard thanks to the fact that a microphone is placed near the operating table, transmitting the words of the operating surgeon through a loudspeaker to the audience behind the partition. But all these innovations have not yet become common in the practice of institutions and O.s. For their popularization, further technical improvements, simplification of installations, and of course, reduction in cost are needed.

Figure 5. Small Küster installation.
Many surgeons quite rightly consider it necessary that when building a special operating department, a separate room—anesthesia room—should be allocated, with an area of at least 20-25 m². There are many patients who are afraid of the sight of the O. and, agreeing to the operation, ask to be put to sleep not in the O.; moreover, for such anesthetics as avertin or rectal ether, isolation of the patient is necessary to carry out such an anesthesia in as much quiet and calm as possible—these two considerations alone fully justify the establishment of a separate anesthesia room. Of the special equipment of the O., operating tables deserve special attention (see). In lecture O.s, it is possible to completely separate from the listeners by glass partitions, who watch the operation through the glass partitions, and the explanations made by the surgeon can be perfectly heard thanks to the fact that a microphone is placed near the operating table, transmitting the words of the operating surgeon through a loudspeaker to the audience behind the partition. But all these innovations have not yet become common in the practice of institutions and O.s. For their popularization, further technical improvements, simplification of installations, and of course, reduction in cost are needed.
V. Rozanov.
Related articles
Mentioned in
Cite this page
“Operating Room.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/operating-room/