Mouth
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
A historical overview of the development and anatomy of the human oral cavity, as described in the 1930s Soviet medical literature. It covers embryological formation, the development of facial structures, and the anatomical boundaries of the mouth.
Encyclopedia article (1928–1936)
MOUTH, ORAL CAVITY. Development. The mouth in mammals develops from the intestinal canal, which is a derivative of the inner germ layer (endoderm). In the earliest stages of development, the embryo's intestinal canal is a straight tube located on the ventral side of the embryo. Anteriorly, this tube ends blindly, and posteriorly it transitions to the dorsal part of the embryo into the neural tube via the canalis neurentericus (see Vol. X, art. 510, figs. 9 and 10). The latter is a temporary formation, as the intestinal canal soon turns into a tube closed at both ends. The anterior part of the neural tube bends ventrally, so that a tubercle forms at the anterior end of the embryo (Fig. 1). The first primordium of the mouth is an invagination of the ectoderm directly behind this tubercle. This is the so-called oral pit (Fig. 1, 3). It begins to grow toward the blind end of the intestinal canal; the contacting planes fuse and then rupture, forming shreds—so-called primitive palatal curtains, which exist only temporarily. The external shape of the oral opening is determined by the five swellings surrounding it (Fig. 2). The anterior swelling, which limits the oral opening from the side of the brain, is called
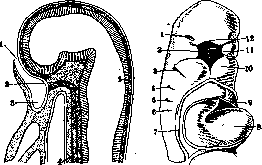
Figure 1.
Figure 2.
Figure 1. Medial section through a rabbit embryo: 1—oral opening; 2—first primordium of the pituitary gland; 3—oral invagination; 4—chorda dorsalis; 5—ectoderm. Figure 2. Head half of a human embryo 4.2 mm long, front view: 1—nasal slit; 2—naso-oral pit; 3–6—corresponding to the 1st, 2nd, 3rd, 4th external branchial grooves; 7—site of the fold of the embryonic water membrane (amnion); 8—heart; 9—pericardium; 10—lower jaw; 11—upper jaw; 12—frontal process. The frontal tubercle or process (Fig. 2, 12), behind which lie the paired maxillary processes (Fig. 2, 11). The groove that separates them from the frontal tubercle is called the ocular slit. The groove lying between the maxillary and mandibular (Fig. 2, 10) processes corresponds to the future corner of the mouth. Laterally and posteriorly to the frontal process is the paired nasal slit (Fig. 2, 1). Behind the oral pit in the cervical region of the embryo, several slit-like openings form in the intestinal wall, one after another, facing the ventral side of the embryo. They form as follows: deep invaginations (internal pharyngeal grooves) appear in the intestine toward the ectoderm, and the ectoderm in turn forms insignificant invaginations (external pharyngeal grooves) (Fig. 2, 3, 4, 5, and 6) directed backward. These invaginations and evaginations come into contact, forming, as in the mouth, a thin membrane, which then ruptures. Thus, four pharyngeal branchial slits arise in higher vertebrates. They are bounded by pharyngeal branchial arches. In fish, the mucous membrane of the branchial arches forms folds, under the surface of which are numerous blood vessels. In higher vertebrates, the branchial slits soon close again and leave grooves bounded by the branchial arches. The first branchial arch—the maxillary or mandibular—is the arch lying in front of the first branchial slit (Fig. 2) [see also the separate table (Vol. X, art. 507–508), Fig. 2], between it and the mouth. The second branchial arch—the hyoid—is the arch lying between the first and second branchial slits. Next follow the third and fourth branchial arches. The face is formed from the frontal process and the mandibular arch. In the 3rd week, the frontal process forms one process on each side, extending downward and forward—the nasal processes (Fig. 3, 8). The mandibular arch limits the naso-oral cavity from below. Even in a 2–3 mm embryo, a protrusion forms on the upper surfaces of the first and second branchial arches, rising upward and forward, toward the nasal process. Thus, the
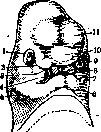
lower jaw; 7—upper jaw; 8—internal nasal process; 9—external nasal process; 10—frontal process; 11—anterior cerebral vesicle (of the cerebral hemispheres).
Figure 3. Head of a human embryo 13.7 mm long: 1—eye; 2—oculo-nasal slit—lacrimal canal; 3—nasal slit—primordium of the nasal passage; 4—oral opening; 5—first ex-
ternal branchial groove; 6—lower jaw; 7—upper jaw; 8—internal nasal process; 9—external nasal process; 10—frontal process; 11—anterior cerebral vesicle (of the cerebral hemispheres). The anterior end of the branchial arch bifurcates, forming two branches or processes: the branches of the upper and lower jaw (Fig. 3, 6 and 7). The slit separating the maxillary processes from the mandibular ones is called the intermaxillary slit and corresponds to the primary oral opening. From each maxillary process grows a palatal plate and a pterygopalatine process. Appearing in the 7th week, the palatal processes grow in a horizontal direction toward one another and come into contact along the midline at the end of the 3rd month. Thus, the palatal septum is formed, supplemented posteriorly by the pterygopalatine processes, dividing the naso-oral cavity into two cavities: the upper—nasal, and the lower—oral. The maxillary processes with the internal nasal processes give rise to the upper lip and upper jaw, fusing at the midline. The mandibular processes, fusing at the midline at the beginning of the 2nd month, give rise to the lower lip and lower jaw with the soft parts surrounding them. The covering lining all tubes and cavities of internal organs is called the mucous membrane (tunica mucosa). Teeth can be considered as ossified papillae of the mucous membrane. Salivary glands appear as invaginations of the oral mucous membrane; these invaginations, due to the gradual growth of individual outgrowths, become solid racemose (acinous) glands. The tongue is formed from an unpaired anterior and a paired posterior primordium. The anterior one is a swelling rising from the floor of the oral cavity; it provides the entire anterior part of the tongue, equipped with papillae; each of the posterior primordia consists of one tubercle located between the second and third branchial arch. From these primordia, the posterior, glandular part of the tongue is formed.
Anatomy. By the oral cavity (cavum oris) is understood that initial section of the digestive tract which extends from the oral fissure (rima oris) to the fauces (isthmus faucium); the latter is the boundary between the oral cavity and the pharynx (pharynx). When the mouth is closed, i.e., in a state of rest, the oral cavity can hardly be called such: in this state, the edges of the tongue adhere to the teeth of the upper jaw, the anterior part of its dorsum is located directly on the hard palate, and only between the soft palate and the posterior part of the dorsum of the tongue is there a narrow space filled with air. From this space, however, a real cavity is immediately obtained as soon as the lips and jaws move away from each other when opening the mouth. The oral cavity is bounded: anteriorly—by the lips, laterally—by the cheeks, the ascending rami of the lower jaw, and the internal pterygoid muscles, superiorly—by the hard and soft palate, inferiorly—by the floor of the mouth, posteriorly—by the anterior palatine arches and the uvula hanging between them. The alveolar processes divide the oral cavity into a part located outside the dental rows—the vestibule of the mouth (vestibulum oris, s. cavum buccale), and a part located between the dental rows and the fauces—the oral cavity proper (cavum oris proprium). The oral cavity is lined with a dense mucous membrane, which transitions on the lips into the outer skin, and at the fauces—into the mucous membrane of the pharynx. On the alveolar process, the mucosa is tightly connected to the periosteum and forms immovable gums (gingivae), surrounding the teeth with a slightly raised rim. This rim, tightly enveloping the neck of the tooth, is called the circular ligament of the tooth (lig. circulare dentis, s. lig. annulare). The connection with the periosteum is also very tight on the hard palate. In addition to the excretory ducts of the sebaceous and mucous glands located in the submucosal layer, the ducts of the paired salivary glands also empty into the oral cavity: the sublingual, submandibular, and parotid. In the so-called corners of the mouth (anguli oris), both lips transition into each other via the commissura labiorum. In the middle of the edge of the upper lip, there is a small thickening (tuberculum labii superioris). A slight depression corresponds to this thickening in the middle of the lower lip. On each lip, one distinguishes the outer cutaneous part (pars cutanea), the transitional part (pars intermedia), and the mucous part (p. mucosa). The red border of the lip (margo labii) consists of the transitional part and the adjacent mucous areas. In the transitional part, there are sebaceous glands in large numbers: if one pulls the skin slightly, they can be seen shining through as yellowish dots. In the mucous part, numerous mucous glands (gl. labiales) are scattered; the site of entry of their excretory ducts is in the mucous membrane. The mucous part of the lips transitions to the jaw, and the place of transition is called the transitional fold of the mucous membrane.

lips. Above the central incisors of the upper jaw and below the central incisors of the lower jaw, at the place where the mucous membrane transitions, a frenulum (frenulum labii superioris, resp. inferioris) is formed (Fig. 4), which in the upper jaw sometimes descends to the interdental papilla (the gingival thickening between the teeth). The mucous membrane of the cheek (bucca) contains sebaceous and mucous glands: they are located mainly in the region of the molars and are collectively called gl. molares, s. buccales. Opposite the crown of the 2nd upper molar, one can constantly see a small, wart-shaped elevation—the opening of the excretory duct of the parotid salivary gland (papilla salivalis superior). The posterior

Figure 5. Walls of the oral cavity: 1-raphe palati; 2-arcus glosso-palatinus; 3-tonsilla palatina; 4-arcus pharyngo-palatinus; 5-frenulum labii inf.; 6-isthmus faucium; 7-plica pterygo-mandibularis; 8-uvula; 9-foveola palatina; 10-frenulum labii sup.
boundary of the vestibule of the mouth is formed by a fold of the mucous membrane (plica pterygo-mandibularis, Fig. 5), which runs to the soft palate and is easily palpable when the mouth is open. The palate (see) is the roof of the oral cavity (Fig. 6).
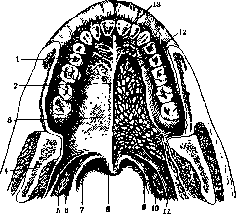
Figure 6. Hard and soft palate: 1-plicae palatinae transversae; 2-raphe palati; 3-foveola palatina; 4-fossa supratonsillaris; 5-arcus glosso-palatinus; 6 and 10-tonsilla palatina; 7-arcus pharyngo-palatinus; 8-uvula (palatina); 9-m. pharyngo-palatinus; 11-m. glosso-palatinus; 12-glandulae palatinae; 13-papilla incisiva.
The salivary glands of the oral cavity are divided into two groups—large and small (see Salivary glands, Parotid gland, Submandibular gland, Sublingual gland). Histology. The mucous membrane of the oral cavity, in particular of the lips, differs little in its structure from the skin. The stratified squamous epithelium of the skin directly transitions into the same epithelium of the mucous membrane. Likewise, the basement membrane of the skin continues directly, without interruption, into the basement membrane of the mucous membrane. The same should be said about the fibrous connective tissue
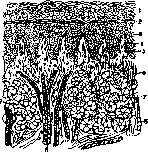
open onto the surface of the mucous membrane, are embedded in the submucous
layer of the skin (corium, s. derma), which continues directly into the base of the mucous membrane (tunica propria) (Figs. 7 and 8). Hair and sweat glands are absent in the mucous membrane of the lips and oral cavity; sebaceous glands are present only in the mucous membrane of the lips, being encountered in other parts of the oral cavity's mucous membrane only rarely. The place of sweat glands in the mucous membrane of the oral cavity is occupied by numerous mucous and serous glands (Figs. 7 and 8). The epithelium of the mucous membrane of the lips is stratified squamous; its layers are arranged in the same way as in the skin, but it does not have a stratum corneum, because its squamous cells are washed away by saliva and gradually desquamate. The numerous salivary glands of the lips, the excretory
ducts of which open onto the surface of the mucous membrane, are embedded in the submucous layer of the skin (corium, s. derma), which continues directly into the base of the mucous membrane (tunica propria) (Figs. 7 and 8). The mucous membrane of the gums is characterized by its density, which is due to a thin layer of bundles of collagen fibers of its base, covering the periosteum of the jaws without an underlying layer; it contains no glands at all. The mucous membrane of the cheeks is homogeneous in structure with the mucous membrane of the lips, only it lacks a submucous layer, therefore the bodies of the numerous complex tubular glands (gl. buccales et molares) enclosed within it are situated in a layer of loose fibrous connective tissue between the bundles of fibers of the underlying muscle (m. buccinator). In the region where the excretory duct of the parotid salivary gland passes, there are larger salivary glands of the mucous membrane.
Figure 7. Perpendicular section of the mucous membrane of a child's lip: 1-layer of keratinizing cells, gradually flattening and desquamating towards the surface; 2-granular layer; 3-layer of polygonal cells with processes (stratum spinosum); 4-germinal layer of the epithelium of the mucous membrane; 5-papillae of the base of the mucous membrane; 6-connective tissue base of the mucous membrane; 7-mucous gland; 8-bundles of striated muscle fibers.
Figure 8. Anterior-posterior section of the lower lip of a newborn child: A-skin; B-zone of non-papillary skin; 1-cross-section of an artery; 2, 4 and 7-cross-section of bundles of striated muscle fibers of the orbicularis oris muscle; 3-epidermis; 5 and 5-labial glands (glandulae labiales); 6-stratified squamous epithelium of the mucous membrane of the lip. The mucous membrane of the hard palate adheres directly to the periosteum without a submucous layer. The mucous glands of the palate owe their location and origin to the epithelium that covers the edges of the two fusing (right and left) palatine processes of the upper jaw; in its structure, this epithelium does not differ from that of the adjacent parts. Only when transitioning to the edge of the soft palate and the palatine arches does the epithelium of the mucous membrane transform from stratified squamous into simple columnar with cilia, characteristic of the respiratory region of the nasal cavity. In the thickness of the mucous membrane of the soft palate lie numerous complex tubular glands—mucous and mixed. Blood vessels are located in the mucous membrane of the oral cavity both in its base and in its papillary layer. Lymphatic vessels begin in the papillary base of the mucous membrane, under which they form dense networks,
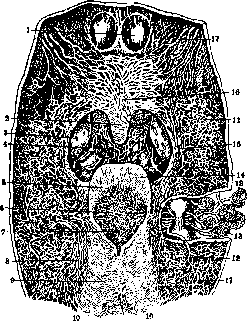
Figure 9. Lymphatic vessels of the walls of the pharynx and larynx: 1-posterior nasal openings (choanae); 2-uvula; 3-tonsils (tonsillae palatinae); 4-root of the tongue; 5-epiglottis; 6-lymphatic network of the larynx and its trunks; 7-entrance to the larynx; 8-greater horns of the thyroid cartilage, connected to the hyoid bone by the thyrohyoid ligament; 9-larynx from behind; 10-lymphatic network of the upper part of the esophageal wall; 11-lymphatic network of the upper-lateral walls of the pharynx; 12-collector trunk of the lower-lateral wall of the pharynx; 13-lymph nodes to which all lymphatic vessels of the pharynx and larynx lead; 14-lymphatic network of the epiglottis; 15-descending trunk; 16-lymphatic network of the posterior surface of the soft palate; 17-lymphatic vessels of this network. (According to Sappey.)
from which small trunks depart, passing through lymph nodes (Fig. 9). For the histology of glands, see Glands and Salivary glands. Physiology. The oral cavity takes part in the following processes: ingestion of food, respiration, formation of voice and speech. In addition to the sense of taste (see), the mucous membrane of the oral cavity undoubtedly possesses pain, tactile, and thermal sensitivity. Healthy teeth do not possess pain sensitivity: the latter appears only in pathological conditions of the teeth (see Teeth). On the other hand, teeth possess a clear temperature sense. A light touch is felt by the teeth quite distinctly, and its location is determined with sufficient accuracy. Under the influence of mechanical and chemical irritations of the oral mucosa, saliva is poured into the cavity of the latter. A number of reflexes originate from the oral cavity: chewing (see Chewing), vomiting (see Vomiting), and coughing. For respiration, the oral cavity is of great importance only in lower animals (amphibians, fish); in humans, however, breathing through the mouth appears only under pathological conditions, mainly in diseases of the nose and nasopharynx; under normal conditions, oral breathing appears only as vicarious: during intense conversation, fast walking, running, and generally during all more strenuous bodily movements, when the need for air is very great. Regarding the participation of the oral cavity in the formation of voice and speech, see Voice and Speech. Bacteriology and immunity. The oral cavity is free of microbes only in the first days of life. Through food substances, respiration, and touching with fingers, microbes are constantly introduced into the oral cavity (see Microflora of man). Given the abundance of microbes and the wide possibility of their introduction into the organism, the rapid healing of wounds in the oral cavity is striking, apparently as a result of the presence in the mouth of still little-studied reactions of local immunity, the bactericidal properties of potassium thiocyanate in saliva, the bactericidal properties of leukocytes, the regenerative capacity of the epithelium of the oral cavity, the mechanical cleansing of the oral cavity by saliva, etc. But in a pathological environment, in the presence of large defects of the mucous membrane and the influx of ever new portions of pathogenic microbes, especially highly virulent ones, these protective mechanisms prove insufficient, and the oral cavity becomes infected. The same occurs under the influence of certain poisons (mercury), in the presence of general infections (e.g., typhus), or constitutional diseases (e.g., diabetes). The floor of the oral cavity is especially sensitive to the influence of all kinds of harmful factors due to the delicacy of its mucous covering, the looseness of its submucosal layer, and the richness of its lymph vessels. A dentist, upon careful examination of the mouth, can often detect diseases, the first manifestations of which are precisely in the oral cavity. On the other hand, a dentist is obliged to always remember the rich microflora of the oral cavity, so that his hands and instruments do not become a means of transferring all kinds of infections. Methods of medical examination. The examination of the oral cavity proper must be preceded by an inspection of the external
pay attention to their mutual
of the parts and tumors clarifies our ideas about the state of the organs of the oral cavity and its surroundings. It is especially important to examine the state of the jaw lymph glands, which often react first to the pathological state of the organs of the oral cavity. Very valuable data can be provided by bimanual (two-handed) palpation, especially for detecting calculi contained in the thickness of soft tissues (in glands, in excretory ducts). Inspection of the oral cavity proper is best performed in daylight, when the slightest changes in the color of the mucous membrane are distinguishable. But in our latitudes and under the conditions of evening work in our medical institutions, one also has to use artificial lighting. Most often, a Telschow reflector is used (Fig. 10); one can also use an ordinary forehead reflector, reflecting light into the oral cavity from

Figure 11.
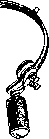
an ordinary (frosted) electric bulb. Even more convenient is the forehead electric lamp shown in Fig. 11. For pushing aside soft parts—lips, cheeks, tongue—all kinds of spatulas, tongue holders, and hooks are used (Figs. 12 and 13), as well as dental mouth mirrors [see separate table, Vol. XI (pp. 83-84), Fig. 2], with which light is simultaneously cast onto the examined part of the oral cavity, and parts of the oral cavity inaccessible to direct inspection by the eye are also examined. For examining the translucency of teeth and accessory cavities, the device shown in Figs. 14 and 15 is used. A very valuable aid for examining the state of the bony parts of the jaws and their processes are X-ray images (extraoral, as well as intraoral, obtained on small films wrapped in black paper and inserted into the appropriate place in the oral cavity). For examining the patency of the excretory duct of the parotid gland, thin probe-tipped probes are used. It is very important to reveal the state of the transitional fold of the mucous membrane, which is smoothed out in the presence of inflammatory processes and bulges in the form of a tumor in the presence of abscesses of its submucosa. For examining teeth, in addition to the dental mouth mirror, a sharp-pointed dental probe is used, with which all surfaces of the teeth are examined, the presence of caries, dental calculus, the state of the floor and
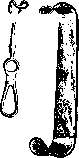

Figure 12.
Figure 13. walls of the carious cavity, and its sensitivity in different places are detected. For examining the vitality of the dental pulp, an inductive current is willingly used, with one electrode placed on the skin of the cheek or hand, and the other on the enamel of the tooth being examined; in this case, teeth with a live pulp react to a current of a certain strength, teeth with an inflamed pulp react more strongly to the same current, while teeth with a dead pulp do not react at all even to a strong current. For examining gingival pockets, Neumann advises using a dental air syringe, the stream of air from which very gently moves the edge of the gum away from the surface of the tooth.
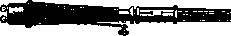
Figure 14.


Pathology. Deformities of the oral cavity. In the oral cavity, among symmetrical deformities, one must note the so-called
Figure 16. Duplication of the lower jaw. epignathus, where the parasite sits on the palate of the autosite; in this case, several varieties of this deformity are observed (according to Schwalbe): 1) in the autosite, the umbilical cord of the parasite is present in the oral cavity (on the palate), 2) parts of the parasite's body hang from the oral cavity of the autosite, 3) a parasite protrudes from the oral cavity of the autosite in the form of a shapeless mass, sometimes in the form of a more formed tissue mass. A number of isolated deformities in the oral cavity arise due to various deviations in the growth of individual parts of the embryo. This includes harelip (see) and cleft palate (see). If, finally, no connection occurs between the maxillary process and the first branchial arch, then a picture of a transverse facial cleft (fissura buccalis transversalis, s. macrostomia) is obtained. Quite often in the upper jaw (less often in the lower) along the midline, a larger or smaller gap is observed between the central incisors—a diastema. The reason for its appearance is the presence behind it of supernumerary teeth, the development of dense bone tissue at the site of the connection of both maxillary bones, or a low attachment of the frenulum.
From deformities of the lower jaw, one should mention the duplication of the latter, when next to the normal jaw there is a second, smaller one (Fig. 16), one of the forms of epignathus. Rarely, a complete absence of the lower jaw is observed (Fig. 17)—agnathia (see), and in such cases, both ears often fuse on the side of the absent lower jaw—synotia (see). The absence of the mouth—astomia (see)—can also be connected with this. From deformities of the tongue, one should mention cleft tongue—lingua bifida—and the rare absence of the tongue. A normally developed tongue may have a short frenulum, which hinders its movements and interferes with speech. A too-long frenulum can lead to choking fits in children. Regarding all kinds of deformities and anomalies in the dental system, see Teeth. From atrophic processes, in addition to physiological senile atrophy of the alveolar process and gums, one should mention the atrophy that occurs in so-called alveolar pyorrhea (see). From progressive processes, one should dwell on hypertrophy of the gums (see Gingivitis). In rare cases, the overgrowth of the gums takes on colossal dimensions and spreads to the palate: a picture of so-called elephantiasis of the gums (elephantiasis gingivae) is obtained. Similar forms of hypertrophy are observed in late forms of syphilis. A special form of hypertrophy of the gums takes place during pregnancy, and the process usually arises towards the middle of pregnancy and persists even after childbirth during nursing.

Figure 17. Agnathia with synotia.
nursing. Therapy in such cases is powerless, but the disease passes by itself upon the cessation of nursing. - Traumatic injuries. More or less significant through-and-through wounds of the oral cavity disrupt the possibility of hermetic closure of the mouth, which upsets the functions of nutrition, speech, and the spitting out of saliva and wound secretions. Injury to the parotid salivary gland and its excretory duct leads to the formation of salivary fistulas. Wounds of the lips and cheeks result, after healing, in disfiguring cicatricial contractions of the mouth. Wounds of the tongue are encountered in the form of transverse and oblique incised wounds or even ruptures of the tongue, sometimes with complete detachment of a larger or smaller anterior part. In gunshot wounds of the oral cavity, bullets or fragments may become lodged in the accessory sinuses, causing profuse bleeding. Through-and-through wounds of the oral cavity are accompanied by fractures of the jawbones, fractures and comminution of teeth, whereby the teeth and bone fragments, embedding themselves in the tongue, cause severe inflammatory phenomena in it. A frequent complication in gunshot injuries of the oral cavity is the formation of phlegmons of the submandibular region and the floor of the mouth. In some cases, acute osteomyelitis arises. Inflammatory processes are observed in all organs of the oral cavity: in its mucous membrane, the mucous membrane of the gums, in the dental pulp, periodontium, salivary glands, and tongue (see Stomatitis, Gingivitis, Pulpitis, Periodontitis, Glossitis). Among acute inflammatory processes, one should dwell on erysipelas of the mucous membrane of the oral cavity—stomatitis erysipelatosa. Here it is a partial manifestation of erysipelas of the face and head, but sometimes it is encountered in isolation (primarily) in the cavity of the mouth and the fauces. In the oral cavity, into which erysipelas often also spreads from the accessory sinuses of the nose, bright redness of the mucosa and its edema spread to the tongue, fauces, and soft palate. The process can take a threatening course if it spreads deeper to the larynx, due to dangerous edema of the glottis. Any local treatment of erysipelas of the oral cavity is ineffective. Among methods of general treatment, one must mention injections of scarlet fever antitoxic or anti-erysipelas serum, autohemotherapy, and treatment with a quartz lamp. In the latter case, ultraviolet rays must be directed directly into the oral cavity. With poor care of the oral cavity in individuals with severe nutritional disorders (scrofula, scurvy), a severe disease of the oral mucosa arises as a result of infection (often vegetating in the mouth even in healthy people) with Plaut-Vincent bacilli and spirochetes, known by the name of gangrene of the oral cavity or stomacace, s. stomatitis ulcero-membranacea (see Stomatitis). Regarding cancrum oris, see Noma. Difficult eruption of the wisdom tooth often leads to severe inflammatory phenomena in the oral cavity. This tooth, due to phylogenetic reduction, erupts from the lingual side of the ascending ramus, whereby the gum located in this place cannot move apart and surround the crown of the tooth. The development of the tooth in the ascending ramus and in an inclined (up to horizontal) position makes its eruption even more difficult. In such cases, a pocket forms over the crown, which becomes the source of an inflammatory process due to the accumulation in it of food residues and secretions, which undergo putrefaction and cause an ulcerative process in it. The process is initially local in character, but subsequently the inflammation spreads to neighboring tissues, masticatory muscles, the cellular tissue of the submandibular region, the mucosa of the fauces, and even the pharynx: severe perimandibular phlegmons arise with sharp trismus and complete inability not only to take food but also to swallow liquids, a severe general condition, and high temperature. In the initial stages of the process, it is possible to achieve a subsidence of inflammatory phenomena by systematic pushing back of the overhanging gum with iodoform strips. In later stages, extraction of the wisdom tooth is indicated. -Regarding phlegmons of the floor of the oral cavity, see Angina Ludovici. Diseases of the lips—see Lips. Among chronic inflammatory processes, one should dwell on syphilis of the oral cavity, which can manifest here in the form of a primary lesion (chancre), secondary manifestations, and in the form of gummatous syphilis. The primary lesion appears as a result of infection from an infected person by means of kissing, infected dental and other instruments, a pencil, or unnatural sexual intercourse, but occurs only in the event that the carrier of the infection possesses fresh virus. The site of primary infection is predominantly the lips, the tip of the tongue, the tonsils, and less often the gums, hard palate, and cheeks. The clinical picture is similar to that in syphilis of the genital organs. At first, there is a superficial defect of the epithelium with hard, ridge-like edges. The induration spreads into the depth, and a nodule arises, which can reach the size of a cherry. The defect is covered with a scab, sitting firmly on the underlying tissue. There is always observed a dense and painless swelling of the regional lymph glands; less often, the glands are painful. Subjective phenomena are surprisingly insignificant. - Secondary symptoms of syphilis on the mucous membrane of the oral cavity manifest in the form of erythematous spots on the palate and tonsils, whereby a picture arises similar to ordinary angina; an afebrile course and simultaneous roseolous rash on the skin make it possible to establish a differential diagnosis. To papular syphilis of the skin correspond papules of the mucous membrane (plaques muqueuses): rounded, sharply demarcated flat elevations with a gray-white surface (as if cauterized with silver nitrate) on the lips, tongue, palate, mucosa of the cheeks, and tonsils. Subjective phenomena caused by papules are for the most part insignificant and are expressed in more or less insignificant pains. Papules are very contagious; therefore, their carriers represent a constant danger to those around them. -Tertiary symptoms appear only many years after the primary lesion in the form of focal lesions with a tendency toward disintegration—gummata—or in the form of various infiltrates. Gummata are encountered mainly on the hard and soft palate and on the tongue, less often on the lips, and very rarely on the mucous membrane of the cheeks. On the hard palate, gummata are usually on the midline and after some time show a tendency toward ulcerative disintegration. The ulcers are characterized by a yellowish, sebaceous base. The process soon spreads to the bone, and a sequestrum is formed, which separates, whereby a communication is established between the cavities of the mouth and the nose. Sequestration of the alveolar process in its frontal section may also occur, with the loss of the corresponding teeth. In the most severe cases, a large part of the framework of the nose perishes along with the soft parts and sections of the upper lip. On the lips, besides gummata of the usual form, there is encountered diffuse hypertrophy of the lips (cheilitis luetica): induration of the lips, dark red coloration of the mucosa, rhagades (fissures) in the corners of the mouth; later—nodular thickenings with retractions between them. So-called Hutchinson's teeth (see Hutchinson's triad) should not be considered as tertiary phenomena of syphilis: they arise as a result of the influence of the secondary stage on the parathyroid glands in the embryonic period. Tertiary syphilis can easily be confused with cancer and tuberculosis, especially on the tongue and lips. Characteristic for tuberculosis are the presence around the ulcer of small grayish tubercles (see below) and the involvement of lymph glands. In doubtful cases, one resorts to excision. Regarding cancer of the oral cavity—see below. Treatment of syphilis of the oral cavity is specific. For defects of the palate, one also uses obturating prostheses and operative closure of the defects (see Obturators). Regarding thrush (soor), gonorrhea of the oral cavity, leukoplakia, foot-and-mouth disease, glanders (malleus), xerostomia, scleroma, actinomycosis, leprosy, and rhinoscleroma—see the corresponding words. -Tuberculous diseases of the oral cavity can be primary and secondary. The oral cavity apparently possesses some immunity to tubercle bacilli, since despite the fact that in patients with pulmonary tuberculosis many bacilli enter the mouth with sputum, tuberculous lesions of the oral mucosa in pulmonary patients are nevertheless observed very rarely. Even greater rarities are primary tuberculous lesions of the oral cavity (except for lupus). Primary tuberculosis in the oral cavity is encountered in the form of: a) lupus, b) tuberculous fissures, ulcers, and infiltrates, and c) in the form of tuberculosis of the jawbones. Regarding lupus—see Tuberculous diseases of the skin. Infiltrates, ulcers, and fissures are observed most often on the lips, palate, and tongue. Ulcers—with a characteristic, uneven, dirtily colored base, undermined edges, and numerous millet-seed-sized tubercles along the periphery. Treatment—cauterization with a thermocautery or 50% lactic acid; X-ray therapy. Primary tuberculosis of the jaws in its symptoms differs almost not at all from the secondary [form] described below. Carious teeth with decomposed pulp give the Koch bacillus the opportunity to penetrate through the canal beyond the apical foramen. As a result of this, tuberculous periodontitis arises, which in its course and symptoms does not differ at all from the ordinary [form], but quickly leads to severe loosening of the teeth. Simultaneously, there is observed sharp swelling of the submandibular and the upper group of deep cervical lymph glands. Treatment: extraction of the tooth, curettage of the socket, and X-ray therapy of the glands. Upon spread to the jawbone, a picture of chronic tuberculous osteomyelitis of the jaws and their processes develops, with the formation of sequestra, fistulas, and scars fused to the bone.
The teeth become very loose and fall out. Treatment of osteomyelitis follows generally accepted principles; in addition, X-ray therapy, tuberculinization, calciotherapy, etc., are used. Balz's disease is characterized by painless swelling of the labial glands and infiltration of the periglandular tissue. The disease runs a chronic course; suppuration occurs in the glands, followed by scarring. There is no swelling of the submandibular lymph nodes. Treatment: internal and external application of iodine. Among the dermatoses of the mucous membrane of the oral cavity, the following are encountered. Eczemas of the lips occur in the form of rhagades, erosions, and brown crusts; the lips swell significantly in this process. In lichen planus, alongside the skin rash, nodules also appear on the lips, the mucous membrane of the cheeks, the palate, and the tongue. Involvement of the mucous membrane of the oral cavity is sometimes also observed in pemphigus and various forms of erythema. Drug-induced exanthems are sometimes observed even from small doses of antipyrine, migrainin, phenacetin, and even aspirin; in this case, the mucous membrane swells in a blister-like manner, and a sensation of tension and burning arises; swallowing is difficult. Herpes zoster is observed on the mucous membrane of the cheeks, tongue, and gums, with vesicles appearing on the reddened mucous membrane, which soon burst. Among animal parasites, one must mention Trichina spiralis, the cysticercus, and the echinococcus. The former is usually localized in the muscles of the tongue, and the disease is accompanied by its severe swelling. Cysticercus and echinococci are observed on the tongue, lips, and in the salivary glands; clinically, they have the appearance of cysts. During or immediately after menstruation, aphthous ulcers sometimes appear on the mucous membrane of the oral cavity. There are reports of vicarious bleeding from the gums during this period; after tooth extraction, there may be severe subsequent bleeding. In pregnant women, the appearance of gingivitis is often observed, sometimes with severe hypertrophy of the papillae and a great tendency toward bleeding from the gums. Tumors of the oral cavity. Papillomas—proliferations of normal papillae—are most often observed on the mucous membrane of the uvula, the palatine arches, and the base of the tongue in the form of warts, often pedunculated, sometimes in the form of growths resembling cauliflower. On the outer side of the lips, papillomas with a sharply defined tendency toward keratinization—cornua cutanea—are encountered. Adenomas originate from various glands of the oral cavity and are more often mixed tumors. They usually grow slowly and less frequently assume a malignant character. With retention of secretion, cysts—cystadenomas—can form. Fibromas of the oral cavity are encountered mostly on the alveolar processes in the form of epulis. Myxomas are encountered in the oral cavity almost exclusively in the form of a mixed tumor—myxosarcoma or myxochondrosarcoma. Lipomas are encountered most often on the tongue (see Lipoma), and less frequently are observed on the floor of the mouth, where they are usually located symmetrically on both sides of the midline under the tongue. Less frequently, lipomas are observed on the cheeks, where they are often subjected to injury; very rarely—on the lips, gums, palate, and tonsils. Cavernous angiomas are encountered most often on the tongue (see), less frequently—on the lips (see), palate, and uvula. Small angiomas often bleed; large ones lead to the emergence of difficulties in speech and eating. Lymphangiomas are encountered in the oral cavity, mainly on the tongue (see), in three forms: nodular, diffuse, and cystic; they are encountered less frequently on the cheeks, lips, and floor of the mouth. Myomas are very rarely encountered in the oral cavity in the form of leiomyomas, and even more rarely in the form of rhabdomyomas. Chondromas are observed at a young age on the lips, gums, and in the salivary glands. Osteomas, single and multiple, are encountered in the oral cavity in the form of exostoses on the alveolar processes and adjacent parts of the jaws. Regarding carcinomas of the tongue and lips—see Tongue, Lips. Carcinomas of the floor of the mouth are very rare; they originate from the epithelium of the glands (submandibular), arise initially in the form of ulcers, but then turn into widespread infiltrates that severely hinder the movements of the tongue. Carcinomas of the cheeks often develop under the influence of irritation of the mucous membrane by sharp edges of teeth, as well as on the basis of leukoplakia. They should not be confused with simple pressure ulcers, which heal quickly upon removal of the cause. Primary carcinomas of the palate are very rare; during development, they can lead to perforation into the nasal cavity or to ingrowth into the maxillary sinus. Secondary ones arise upon the transition of a neoplasm from neighboring parts. Regarding carcinomas of the jaws—see Jaws. Regarding sarcomas—see Tongue, Jaws. Cysts (see) are observed both in the region of the soft parts of the oral cavity and in the jaw bones. Small glandular retention cysts are encountered in the oral cavity everywhere there are glands, especially on the inner side of the lips and the mucous membrane of the cheeks and tongue (see). More important are the cysts located on the floor of the oral cavity, which sometimes reach a significant size and are known by the name ranula (see). Alongside retention cysts on the floor of the mouth, dermoids (see) are encountered in the form of sublingual and submental cysts, always located along the midline (in contrast to ranula). They sometimes reach a significant size and cause disorders of swallowing and speech. Regarding follicular cysts, adamantinomas, cystomas, and odontomas—see the corresponding entries. Regarding salivary stones—see Concretions, Parotid gland, Submandibular gland, and Sublingual gland.—Treatment of tumors and cysts is operative. In malignant formations of the oral cavity, X-ray and radiotherapy, as well as diathermy (electrocoagulation), are used with success. Among occupational diseases of the oral cavity, mercury stomatitis should be noted (see Mercury). Microflora of the mouth—see Human microflora.
Related articles
Mentioned in
Cite this page
“Mouth.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/mouth/