Obturators
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Soviet Great Medical Encyclopedia details obturators, which are dental prostheses and appliances used to close unnatural openings in the walls of the oral cavity, particularly defects of the hard and soft palate. It describes various classifications, historical designs, and functional principles for treating congenital and acquired palatal defects.
Encyclopedia article (1928–1936)
OBTURATORS (from Latin obturare - to occlude), prostheses and devices serving to close or "occlude" unnatural openings in the walls of the oral cavity. Most commonly, obturator-prostheses are used to close defects of the hard and soft palate, in which there is an abnormal communication between the oral and nasal cavities. Obturators are also used to close defects in the alveolar process of the upper jaw penetrating into the maxillary sinus, or to close large openings remaining after trepanation and partial resection of the walls of periapical jaw cysts. Large defects remaining after total resection of the upper jaw are filled with prosthesis-obturators, which restore the bone and dental defect and create a separation between the oral and nasal cavities. The use of obturators is generally indicated only in cases where it is impossible to close the defect by plastic surgery or when the patient refuses surgical treatment. Depending on the location, shape, size, and other characteristics of the defects and on the role that the obturator must play in the function of the oral and nasal cavities, special types of obturators and various types of their construction are distinguished. Obturators of the simplest construction are used to close acquired defects of the hard palate, defects of the alveolar process penetrating into the maxillary sinus, and openings of periapical cysts. In these cases, there are openings surrounded by hard edges that do not change their shape. It is sufficient to adapt a plate made of hard rubber that covers the edges of the defect and partially occludes its lumen, thereby eliminating all functional disorders associated with the defect (Fig. 1). Considerably more complex is the construction of obturators used to restore defects of the soft palate. The size and shape of these defects constantly change depending on the function of the surrounding muscles. The obturator of the soft palate must
of the soft palate and the muscles of the posterior and lateral walls of the pharynx. Due to this, at the moment of muscle contraction, a complete separation is achieved between the nasal and oral parts of the pharynx. By its presence in the area of the defect, the obturator, however, must neither hinder the movements of the soft palate nor the free passage of the air current through the nasopharyngeal passage during respiration. The functional qualities of soft palate obturators are determined, on the one hand, by how well they prevent food from entering the nasal cavity during eating, and on the other hand, by how well the function of the soft palate is restored during speech. The prognosis regarding the restoration of normal speech, however, depends not only on the quality of the obturator, but also on the features of the defect itself and on the functional development of the entire neuromuscular reflex apparatus participating in the act of speech (see Logopathy and Logopedics). Defects of the soft palate in which the use of obturators is indicated must be divided into three groups: 1. Congenital clefts of the soft and hard palate that have not undergone surgical intervention. 2. Congenital clefts of the palate after surgical interventions that did not lead to complete restoration of the soft palate. 3. Acquired defects of the soft palate, most often of syphilitic origin. In defects of the first group, obturators adapted to the movements of the muscles of the soft palate and pharynx are used; in defects of the second group, the mobility of the soft palate is usually severely impaired by scars and tissue tension, making it much more difficult to adapt the obturator so that it does not limit remaining movements, does not cause bedsores, and fulfills its purpose. Closure of the nasopharyngeal passage is achieved due to contractions of the superior pharyngeal constrictor, which forms a protrusion on the posterior wall of the pharynx—Passavant's ridge. It is most difficult to achieve functional restoration when obturating acquired defects of the soft palate after gummas of the palate and pharynx, since in these defects any mobility of both the palatal muscles and the pharyngeal constrictor is often absent.--The functional qualities of obturators also depend on how they are fixed in place. Immobile fixation of the entire obturator, in particular fixation to the teeth, is usually used only for defects in the hard palate or alveolar process. For soft palate obturators, various authors have proposed a number of different designs allowing either complete mobility of the entire obturator (floating obturator) or relative mobility of that part of the obturator located between the muscles (using springs, hinges). However, there are also immobile soft palate obturators that create conditions for the formation of quite normal speech (meat-obturator, Warnekros obturator, etc.). The following obturators are best known: 1. The Kingsley obturator (1864) for the soft palate consists of two plates of soft rubber, connected to each other and attached by means of a hinge to a supporting plate on the hard palate. The upper plate of the obturator is longer than the lower one and contacts the posterior wall of the pharynx. This obturator is no longer used.-- 2. The Suersen obturator for congenital unoperated clefts of the soft palate (Fig. 2) consists of a large
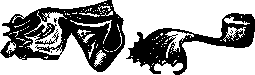
Figure 2.
Figure 3. immobile piece of hard rubber located in the nasopharynx. Separation of the oral and nasal parts of the pharynx is achieved through the contraction of the superior pharyngeal constrictor muscle. The work of the muscles of the soft palate is not taken into account. This obturator is no longer used.--3. The Schiltsky obturator consists of a hollow piece of soft rubber located in the nasopharynx and attached by a spiral spring to a supporting plate on the hard palate (Fig. 3). It is used for an insufficient soft palate after operations that do not provide lengthening of the palate (e.g., after Langenbeck's operation).--4. The Warnekros obturator is a simplified modification of Suersen's and consists of a hard rubber plate filling the lumen remaining at the moment of greatest contraction of the pharyngeal muscles and the soft palate (Fig. 4). The obturating plate with

Figure 4. Warnekros obturators: a—for unoperated cleft; b—for insufficient palate after operation.
unoperated clefts is connected to the supporting plate immovably or by means of a hinge; for an insufficient palate after operation, it is connected to the supporting plate by a thin gold rod.--5. The Case obturator (1904) is used only for unoperated clefts of the soft and hard palate. It consists of a very thin and light plate of black rubber with edges that precisely embrace the edges of the cleft (Fig. 5).


Figure 5.
FIG. 6. The obturator is held only on the edges of the cleft and easily moves—"floats"—between the two halves of the soft palate. The obturator is prevented from falling backward by the upper-anterior surface of Passavant's ridge. The Case obturator is one of the simplest and cheapest in terms of manufacturing technique and at the same time excellent in functional terms. 6. The Schalit-Froschels obturator (1928), called by the authors a meat-obturator, is applicable for all types of soft palate insufficiency. It consists of a piece of hard rubber that closes the openings of the choanae from the nasopharynx side and thereby restricts the escape of air through the nasal cavity (Fig. 6). In the middle of the obturator, there is a permanent channel for breathing. The authors claim that to eliminate nasal speech it is not necessary to achieve complete separation between the oral and nasal sections of the pharynx, but it is sufficient to restrict

Figure 7.
to a certain limit the escape of air toward the nasal cavity.--7. The Warnekros nipple-obturator for feeding newborns with cleft palates consists of a soft rubber plate covering the alveolar process and the cleft of the hard and soft palate, connected by a metal lever and a celluloid ring to a rubber nipple (Fig. 7).--8. The Brophy obturator for breastfeeding newborns with cleft palates consists of a soft rubber plate attached to an extraoral handle by which the mother holds the obturator in place during feeding. The obturator should be used from the first days after birth.--In addition to the described obturators, there are many other proposals, e.g., obturators by Martin, Delair, Brugger, Guerini, Brandt, Pickerill, etc. Pickerill fixes the soft palate obturator on a hinge to a supporting plate on the hard palate, and for greater mobility of the obturator hooks it with a loop created by sewing together the two halves of the uvula of the soft palate. Brandt used a rubber air balloon.
Related articles
Mentioned in
Cite this page
“Obturators.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/obturators/