Bronchi
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Soviet Great Medical Encyclopedia details the embryonic development, anatomy, and histological structure of the bronchi. It covers the bifurcation of the trachea, the differences between the right and left bronchi, their relationship to the lungs and blood vessels, and their microscopic composition.
Encyclopedia article (1928–1936)
BRONCHI (from Greek bronchos—breathing tube), represent the ramifications of the trachea and serve for the exchange of air between the external environment and the air of the pulmonary alveoli. The embryonic development of the bronchi begins in a very early period of embryonic development. Already at a length of 4–5 mm (J. Kollmann, Heiss), the division into right and left sub-sections of the primary primordium of the respiratory apparatus is outlined, which appears by the end of the 1st month (His) in the form of a hollow, sac-like protrusion from the anterior wall of the digestive tube (see Figure 1). The successive branching of the initial two primary, or "main," bronchi leads, in the end, this initially bifurcated vesicle to a complex system of dichotomously diverging channels, i.e., to the appearance of a "bronchial tree." In this process, the growth of the terminal part of the pulmonary primordium, prevailing in its speed over the other parts of the organ, creates a long "stem" bronchus throughout the entire lung, which itself gives off bronchi of the 1st, 2nd, 3rd, etc., order. Anatomy of the bronchi. In the adult state, the beginning of the bronchi, i.e., their departure from the trachea, or its bifurcation, occurs at the level of the IV–V thoracic vertebrae posteriorly (auscultation!) and corresponds to the 1st–2nd intercostal space anteriorly. Age-related fluctuations in the topography of the bifurcation (according to Brünings) occur within the limits between the lower edge of the 1st rib (in children), the upper edge of the 2nd (in adolescents), and the upper edge of the 3rd (in adults). Furthermore, the position of the bifurcation is affected by movements of the head and neck and by acts of respiration. Upon flexion and inspiration, the level of the bronchi descends; upon extension and expiration, it rises. Relative to the midline of the body, the bifurcation is shifted slightly to the right and posteriorly by the aortic arch, which is draped over the left bronchus. The angle of divergence of the main bronchi, on average, is 70.4°, fluctuating from 56° to 90° (Aeby), but, according to Brünings' research on the living, it rarely reaches 90° and is usually greater the shorter and thicker the neck is.
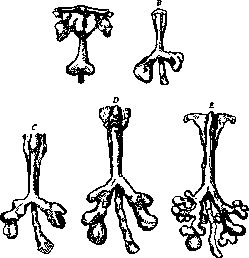
it (see Figure 3). In addition to this, the right bronchus in the frontal plane follows the curvature of the right atrium encompassed by the right lung and has a curvature in the shape of the letter C.
Figure 1. Development of the lungs and bronchi of the human embryo (bottom center—esophagus): A—embryo 4 mm; B—5.9 mm; C—6.7 mm; D—8 mm; E—9 mm (according to R. Heiss). The right main bronchus is wider than the left. Their calibers, according to Branne and Stahel, relate as 100 : 78.4, while according to Brünings' measurements, they have the following dimensions: Bronchi Male Female Child Newborn Right... Left... In millimeters 12-16 10-14 10-15 9-13 7-9 6-8 5-6 4-5. The right bronchus, deviating less from the midline than the left, preserves the direction of the trachea to a greater degree, and therefore, due to its greater width, foreign bodies aspirated through the larynx and trachea fall into it more often (see Figure 2). Before plunging into the lung tissue, both main bronchi are for some distance in the region of the mediastinum and come into contact here with large vessels and lymph nodes (see below). The extent of this mediastinal segment of the bronchi is shorter on the right than on the left (on the right 6-8 cartilages, on the left 9-12). Both the main bronchus and its continuation, the intrapulmonary "stem" bronchus, in their direction, like the trachea, continue to adhere to the curvature of the spine and are located inside each lung, deviating from front to back, from top to bottom, and, lying closer to the posterior than to the anterior surface of the lung, rush with their termination (bronchus terminalis) to the very lowest part, to the posterior-inferior corner.
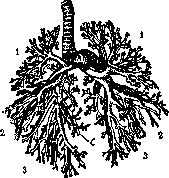
Figure 2. Bronchial tree and pulmonary artery in a newborn (from a corrosion preparation): A—a. pulmonalis; C—bronchus cardiacus; 1—upper lobe; 2—middle lobe; 3—lower lobe (according to Braus).
The left bronchus is twice curved in the same plane in an S-shape, in the upper bend deviating downward and to the right from the aortic arch, and in the lower bend—upward and to the left, under the pressure of the left ventricle of the heart (see Figure 2). Inside the lung, the stem bronchus gives off branches of the 2nd order, longer anteriorly-ventral and shorter posteriorly-dorsal; these branches, in turn, divide into branches of the 3rd and subsequent orders. The branching of the bronchi is closely followed by the adjacent and also branching vessels, the bronchial arteries and veins and the pulmonary arteries and veins. In the left lung, the stem bronchus gives off 4 pairs of branches: 4 ventral bronchi and 4 dorsal bronchi. On the right, to 4 such pairs is added one unpaired bronchus, which, unlike the others, departs from the stem bronchus at a right angle cranially, intended for the upper lobe of the lung, and differs from all other bronchi by its relationship to the adjacent pulmonary artery. Figure 3. Direction of the bronchus in relation to the lung. View from the side; on the left; in the posterior-inferior corner—bronchus terminalis (according to Merkel with modification).
It is located dorsally to the artery and usually above it, which is why it has the name "bronchus eparterialis," whereas the others lie ventrally and below the artery and are called "bronchi hyparteriales." In addition to the above-listed bronchi, a supplementary one is distinguished on the right—the bronchus cardiacus, which departs from the 2nd ventral bronchus and is directed in the pulmonary parenchyma posteriorly, into the lower lobe. It is distinguished by its thickness, strength, and corresponds to the bronchus of an independent "cardiac" lobe in some animals (lobus infracardiacus). In Fig. 2, this bronchus is designated by the letter C. The successive division of the bronchi, both dorsal and ventral, leads them to terminal bronchial tubes 0.4–0.5 mm in diameter, bronchioles (see below—art. 74), which pass into pulmonary smooth musculature, the strength of which decreases in the direction of the alveoli, until complete disappearance in the latter. Muscle fibers, embedded between the cartilaginous plates and the mucosa, have a direction relative to the axis of the tube.
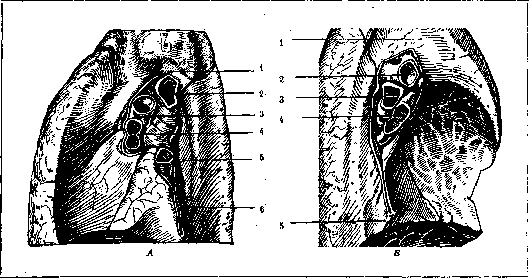
Figure 4. Hilum of the right (A) and left (B) lungs. Relation of the bronchi to the vessels. A: 1—sulcus v. azygos; 2—right bronchus; 3—right branch of the pulmonary artery; 4—right pulmonary veins; 5—sulcus oesophageus; 6—lig. pulmonale. B: 1—sulcus aorticus; 2—left branch of the pulmonary artery; 3—left bronchus; 4—left pulmonary veins; 5—sulcus oesophageus (according to Braus).
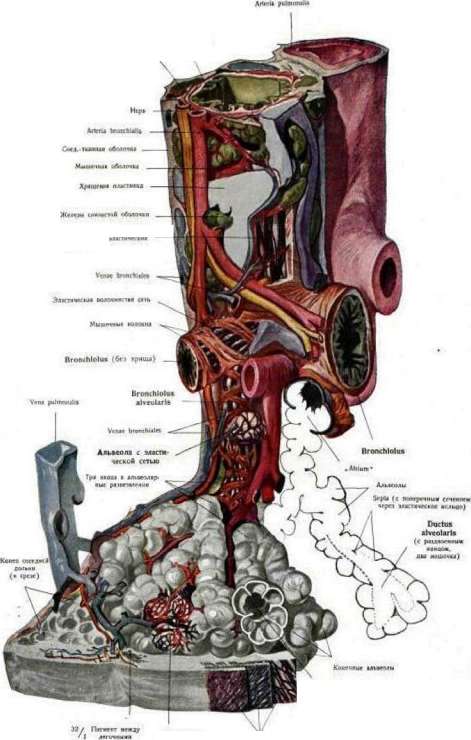
alveolar ducts and alveoli [see separate table (art. 107-108), fig. 1] and correspond to the 5th-6th order number of bronchial division. Their external distinguishing feature is the small "alveoli" visible under a magnifying glass, sitting on their wall, and the presence of respiratory epithelium. In histological terms, the large bronchi repeat the structure of the trachea. The cartilaginous skeleton of the bronchi appears in the form of rings of hyaline cartilage almost completely encircling the respiratory tube, with a small part free of it, which is replaced by a membranous plate containing transverse bundles of smooth muscle fibers. The latter attach to the perichondrium of the cartilaginous rings. In smaller bronchi, of the 2nd-3rd order, the cartilaginous rings are replaced by cartilaginous plates lying tightly against one another. As the tube divides, the sizes of the plates become smaller, and the gaps between them increase (see Figure 5). In small bronchi, of the 5th-6th order, there is almost no cartilage left, and in bronchi less than 0.85 mm in diameter, it disappears completely. The mucous membrane of the bronchi with a strongly developed loose fibrous submucosal layer is usually gathered into folds. The ciliated epithelium sitting on its membrana propria contains a large number of goblet cells. In the submucosal layer, among the loose fibrous connective tissue, mucous-serous glands are embedded, and accumulations of leukocytes and lymphoid follicles are encountered. In this same layer, throughout the entire extent of the bronchial branches, right up to the alveolar ducts, the bronchi are supplied with smooth musculature, the strength of which decreases in the direction of the alveoli, until complete disappearance in the latter. Thus, by reducing the capacity of the respiratory passages, the bronchial musculature has an expiratory significance. It is supplemented by the reverse contraction
tissue (see color table), as a result of which their contraction causes not only a narrowing of the lumen of the respiratory tube but also its simultaneous slight shortening. Thus, by reducing the capacity of the respiratory passages, the bronchial musculature has an expiratory significance. It is supplemented by the reverse contraction
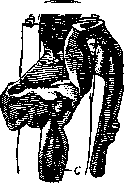
of elastic tissue, which stretches with every breath, embedded in large quantities in the form of longitudinal strands in the fold of the mucous-submucosal layer. The arterial supply of the bronchi and venous outflow occur not only at the expense of the bronchial arteries and veins (vasa privata), but, apparently, also through the pulmonary arteries and veins (vasa publica), since ligation of the bronchial arteries does not have a harmful effect on the nutrition of the organ. Lymphatic drainage from the bronchi proceeds through the bronchial lymphatic system, i.e., through lymph nodes sitting in the angles of bronchial division (lgl. pulmonales), through the glands of the lung hilum (lgl. broncho-pulmonales), and flows into the bifurcation glands. Small bronchus. Figure 5. Bronchial cartilage: C—cartilaginous plates (dark part—hyaline cartilage, light outer part—elastic cartilage); M—contour of the mucous membrane.
Lymphatic vessels of the bronchi (lgl. tracheo-bronchiales), whence through lgl. paratracheales thorac. and truncus broncho-mediastinalis they are directed to the angulus venosus.-Innervation of the bronchi is connected with the pulmonary plexus and originates from the anterior and posterior plexuses (plexus pulmonalis ant. and posterior). The greatest part of the nerve trunks is concentrated on the posterior surface of the main bronchi (necessity of cocainization during lung amputation!).- Syntopy of the bronchi. Over the right main bronchus loops from behind Figure 6. Right main bronchus

and its surrounding organs: 1-n. recurrens n. vagi d.; 2-trachea; 3-v. cava superior; 4-v. azygos opening into it; 5-nerve fibers departing from the vagus and plexus pulmonalis post. to the lung; 6-right bronchus; 7-lung pulled outwards.
the terminal part of the vena azygos, before its opening into the v. cava superior lying anteriorly. The trunk of this section of the azygos vein touches part of the posterior and upper wall of the bronchus. Medially from the vein, toward the posterior side of the bronchus, lies the right n. vagus descending along the right side of the trachea and the adjacent lymph glands (lgl. tracheo-bronchiales). Laterally-partly the lung, partly the lymph glands of its root. With enlargement of the lymph glands, both the vein trunk and the vagus nerve can be displaced and pushed away from the bronchus. The anterior side of the right bronchus touches the right pulmonary artery;
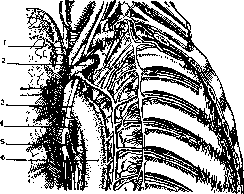
Figure 7. Left main bronchus and its surrounding organs: 1-lung pulled outwards; 2-v. anonyma sin. with v. hemiazygos opening into it; 3-n. vagus sin. and n. recurrens departing from it under the aortic arch; 4-left bronchus; 5-esophagus; 6-aorta.
medially and above it, closer to the bifurcation, the v. cava superior adjoins the bronchus (see figures 4-A and 6). The lower surface is touched by the lower lymph glands of the bifurcation. Over the left main bronchus loops from front to back the aortic arch and, laterally from it, the left pulmonary artery. Between the bronchus and the vessels are located the lgl. tracheo-bronchiales and the n. recurrens sin. departing below the aortic arch from the vagus nerve (see figure 7). Posteriorly, the descending part of the aortic arch adjoins the bronchus and, external to the latter, the trunk of the vagus nerve. From below, the bronchi are touched by the bifurcation glands and w. pulm. (see figure 4 B). Anteriorly, the left bronchus is covered by the posterior parietal leaf of the pericardium (corresponding to the posterior wall of its sinus transversi) and lymphogl. broncho-pulmonales. The relationship of the bronchi with neighboring organs in the roots of the lungs is shown in fig. 4. All the organs listed around the bronchi are separated by loose cellular tissue, allowing significant mutual displacement of them during pathological changes in the organ volume. This cellular tissue is continuously connected with the peribronchial and perivascular interstitial connective tissue of the lungs and can serve as a pathway for the spread of inflammatory and other processes (emphysema, hemorrhage, etc.) from the lung to the organs of the mediastinum and vice versa. Pathological processes in the bronchi. Aside from foreign bodies (see Bronchoscopy), inflammatory lesions originating from various layers of the bronchial wall (see Bronchitis, Pneumonia), and secondary changes caused by them (see Bronchostenosis, Bronchiectasis), traumatic injuries and tumors of the bronchi may have practical significance for the physician. Due to their elasticity, the bronchi, together with the trachea, possess high extensibility; nevertheless, under the action of gravity, compression from without, during extreme stretching of the respiratory tube (for example, with Fig. 8. Lipoma on a sharp forcible knife po... sctoetter...), cases of its rupture have been observed not only in the region of the trachea, but also of the bronchi. Clinical symptoms in injuries have a severe, but not always clear character (retrosternal pain, sometimes audible cracking during respiratory movements, progressive emphysema, pneumothorax, etc.). The prognosis, with very rare exceptions (Krinitsky), is unfavorable. Patients are ruined by complications: emphysema, pneumothorax, bronchopneumonia, gangrene of the lung, and phlegmonous infection of the mediastinum. (On gunshot wounds of the bronchi-see Lungs.)-Tumors of the bronchi can be benign and malignant. Of the former, papillomas, adenomas, lipomas, fibromas, chondromas, osteochondromas are encountered; the tumors are both solitary and multiple, developing in various sections of the bronchial divisions. Sometimes they have a wide base, sometimes a more or less short stalk. Their size can range from a lentil to the size of a hazelnut, reaching in some cases the volume of a fist and a child's head (fibromas and chondromas). During life they may not cause noticeable disorders and are sometimes an accidental finding of the pathologist at autopsy. In other cases, protruding

«3
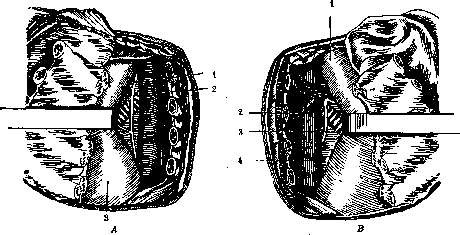
into the lumen, they cause narrowing of the bronchi and disruption of normal breathing (see figure 8). With the development of bronchoscopy, the number of cases of intravital recognition of such tumors is progressively increasing. Their treatment is operative; with particularly favorable locations-using a bronchoscope (see Bronchoscopy), with very large sizes-by a bloody approach to the bronchi (see below). In addition to the listed types of benign tumors, cystic tumors originating in connection with developmental disorders of the bronchi deserve separate mention (see figure 10). Lined on the inside with cylindrical epithelium and connected with the bronchi, they, increasing in size, can reach very large dimensions (up to a child's head in Sauerbruch's case) and turn out to be filled with a transparent mucous mass, which can become infected and produce the clinical picture of an abscess.- Malignant tumors. Depending on the section of the bronchus from which the tumor originates, malignant neoplasms of the bronchi can be localized either in the mediastinum or in the lung parenchyma. Sarcomas (round-cell or spindle-cell from the peribronchial tissue or from the bronchial wall itself) are comparatively rare. Exhibiting energetic growth, they can reach very large sizes, easily reaching the mediastinal spaces, growing through the pleura, heart muscle, and pericardium. More frequently (up to half of all bronchial tumors) cancerous tumors are encountered (see below-p. 75). Operations on the bronchi. Operative approaches to the bronchi. For the removal of foreign bodies or tumors, when the bronchoscopic method is impossible, the bronchi can be approached in two ways: transpleurally (thoracotomia transpleuralis), passing through the lung tissue (see Thorax), or extrapleurally-through the mediastinum (bronchotomia extrapleuralis mediastinalis). According to anatomical conditions, the latter path is most expedient through the posterior section of the mediastinum. Despite all the severity of the intervention due to subsequent possible complications (empyema, local gangrene, emphysema, etc.), both methods nevertheless have successful outcomes with stable results. The transpleural method is usually carried out with an apparatus :left (A) and right (B). Left: 1-n. vagus; 2-aorta; -n. vagus; 4-esophagus (after Garre-Quincke). of increased pressure according to the general rules of such opening of the chest and pneumotomy. The posterior mediastinal method, first developed and proposed in 1888 for access to the esophagus by Russian surgeons Nasilov and Dobro
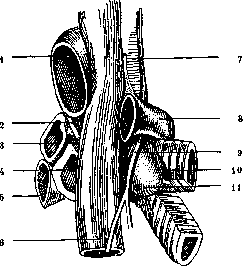
Figure 10. Bifurcation of the trachea. Congenital cyst of the right bronchus (author's observation). View from behind. 1-aorta; 2-n. vagus sin.; 3-a. pulmonalis sin.; 4-left main bronchus; 5-v. pulmonalis sin.; 6-esophagus; 7-trachea; 8-v. azygos; 9-n. vagus dextr.; 10-right bronchus; 11-bronchial cyst.
myslov, was later used also for the approach to the bronchi. It requires subperiosteal resection from a longitudinal paravertebral incision of 4-5 ribs (from III-IV to VII
BRONCHI
rib), over an extent of 4-6 cm, at the level of the transverse processes. After this, the soft tissues of the chest wall are cut (with ligation of vessels), which opens the peripleural cellular tissue (fascia endothoracica), and access to the bronchi is established by
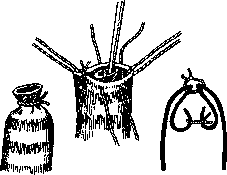
Figure 11.
careful blunt stripping of the parietal pleura and the posterior section of the lung covered by it (see figure 9). When pulling the latter with a hook, the pleura should be protected from tearing and damage. At the end of the operation, a gauze drain is placed at the sutured bronchus. - Incision (bronchotomy) and suture of the bronchi. In operations on the bronchi, the subsequent
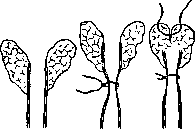
Figure 11.
suture of the wall or closure of the bronchial stump, due to specific local conditions, are especially responsible. Rhythmic air jolts in the area of the suture or the stump of the transected bronchus during breathing require high strength of bronchial closure in order to avoid air forcing (subsequent
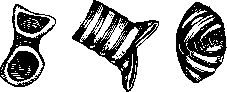
Figure 13.
emphysema, pneumothorax) and the penetration of infection from the lumen of the bronchus. Therefore, it is advisable to perform a bronchotomy in layers. The wall of the bronchus is dissected with a longitudinal incision down to the mucosa, and after stretching the wound to the sides, an incision of the mucosa is made in the transverse direction. The wound is sutured in layers, but in reverse order (Melnikov). To close the stump of a bronchus during its transverse resection, 3 types of methods can be applied: 1) the gaping bronchus is constricted with a ligature, and its stump is closed with a second suture with invagination of the ligated end (see Fig. 11); in addition, it can be further reinforced with fascia, omentum, pleura, etc.; 2) the bronchus can be ligated and its end closed with the surrounding lung tissue, as schematically indicated in Fig. 12, and, finally, 3) for several severed bronchi, the method applied is

Figure 14.
suturing them end-to-end (see Figure 13) or by invagination (see Figure 14). During operations on the bronchi, it is necessary to take into account the poor conditions of their blood supply, especially in large-caliber bronchi, due to which any kind of excessively strong tension by sutures easily leads to necrosis and the complications resulting from it.
Bronchioles, the small branches of the bronchial tree that transition into alveolar ducts (see Lungs). There is no consensus among authors on the question of when exactly a small bronchus should be called a bronchiole: some call a small bronchus with a thickness of about 1 mm entering a pulmonary lobule (bronchus intralobularis) a bronchiole, but the majority apply this name to intralobular bronchi of the 2nd and 3rd order, starting from a diameter of 0.5 mm to the so-called terminal or respiratory bronchioles. The histological structure of the bronchioles was studied in detail by Koelliker. Cartilaginous plaques, which are present in small bronchi, disappear upon the bronchi reaching a diameter of 1–0.85 mm, and the bundles of smooth muscle fibers that connected the cartilages now form networks covering the entire lumen. The thickness of the muscle layer in a bronchiole with a diameter of 0.65 mm is from 114 to 54 µ, and in a bronchiole with a diameter of 0.34 mm, it is from 16 to 21 µ. Inward from the muscle layer is the mucous membrane, consisting of a longitudinal layer of elastic fibers adjacent to the muscles; this layer is followed by fibrous connective tissue with networks of elastic fibers and a large number of cells; the connective tissue part is separated from the epithelium by a thin membrana propria. The epithelium in the bronchioles is multi-layered cylindrical, ciliated, with goblet cells; the mucous-serous glands, which are present throughout the entire respiratory tract, disappear along with the cartilages. The mucous membrane of the bronchioles is permeated with a large number of lymphocytes, forming accumulations of adenoid tissue in places; it forms longitudinally running folds caused by the contraction of the muscle layer. The terminal branches of the bronchioles, the so-called respiratory bronchioles, have a diameter of 0.5–0.4 mm; they are covered for a length of 1.5–3.5 mm by a double-row ciliated epithelium, without goblet cells, and hemispherical protrusions covered by the so-called respiratory epithelium begin to appear on the walls; further on, the ciliated epithelium disappears completely, and the respiratory epithelium begins. It consists of small cubic cells 7–15 µ in diameter, devoid of ciliated hairs, clustered on one side of the bronchioles; then, large flat cells 22–45 µ in diameter wedge in between them, forming a transition to the respiratory epithelium of the alveolus, with hemispherical bulges appearing in increasing numbers on the walls of the bronchioles. In this transitional region, groups of 20–50 small cells are encountered. After 1.5–2 mm, alveolar ducts are already encountered, in which thin, flat cells predominate (see also Lungs).
V. Karpov.
Bronchial cancer, cancer of the bronchus, is the most frequent of the malignant diseases of the lung; like most cancers, bronchial cancer arises in the presenile age; it is observed relatively rarely in young and very old age. Most statistics indicate a predominant susceptibility of men (2:1; 3:1). On the right, bronchial cancer is found somewhat more often than on the left. The etiology of bronchial cancer, like cancer in general, is unclear; in cities, it apparently occurs more often, which some authors associate with a high content of quartz, granite, and coal dust in the air, as well as various products of the combustion of coal, gasoline, and benzene (in connection with the development of automobile traffic); a suggestion is also made about the significance of X-ray exposure and radium emanation, for example, in the mining of ore in Schneeberg, where the ore is rich in radium emanation and where bronchial cancer is the most important disease of the workers. Regarding pneumoconioses in general, there is no definite data; the significance of Ni, Co, and As has not been clarified; for example, in the same Schneeberg, they point to the frequent incidence of bronchial cancer among workers in tobacco factories. Theoretically, however, it should be admitted that any pulmonary process (tuberculosis, pneumoconioses, etc.), insofar as it is accompanied by significant changes in the normal tissue relationships of the bronchi, can serve as a basis (given the appropriate predisposition) for the development of bronchial cancer. Many authors, especially German ones, pay great attention to the influenza epidemic (1918–19),
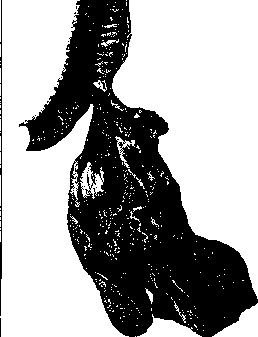
Figure 15. Cancer of the bronchus in the form of an obstructing
polyp. Pulmonary atelectasis (observation by I. V. Davydovsky). after which the frequency of cancer increased especially; on the other hand, the increase in the number of cancers began even before the indicated epidemic, and furthermore, influenza is far from a constant phenomenon in the anamnesis of patients. Bronchial cancer is also encountered in many animals, especially in dogs. Statistics testify to a significant growth of this disease. If at the end of the 19th century bronchial cancer accounted for no more than 2% of all cancers, then by 1914 it accounted for 5%, and in 1924—over 10%. Pathological-anatomical mortality statistics of the Moscow population note the same thing: out of 500 cancers (out of 3,880 autopsies), 56 were bronchial cancer (data for 1925). The same applies to an even greater extent to 1926–27. Lowy-Lenz in 1919–23 had 0.7% bronchial cancer in all autopsy material; in 1913–14—only 0.1%. The large statistics of Hanf also speak of the same thing. Pathologically and anatomically, bronchial cancer is characterized by a large number of variants both in the sense of the size, location of the tumor, its relationship to the lumen of the bronchus, metastasis, and in the sense of its histological structure. Most often, bronchial cancer lies not far from the hilus of the lung, at the lower end of the stem bronchus, at the beginning of the branching of its last branches. A pale gray or white tumor can have the appearance of a clearly demarcated node,

Figure 16. Bronchial cancer (bronchoscopic picture): 1—tumor in the lumen of the bronchus; 2—
either protruding like a polyp into the lumen of the bronchus (see Figure 15 and 16), or surrounding it in the form of a ring; in both cases (especially in the former), the process is accompanied by stenosis or closure of the lumen of the bronchus with corresponding consequences; such clearly outlined cancers have a small size (sometimes the size of a small cherry or pea), and are sometimes found with some difficulty even at autopsy, especially when located along the course of secondary bronchial branches.
Another variety of bronchial cancer is large nodes, also lying, mainly, near the hilus and forming in the order of rapid peribronchial spread, as if branching, of the tumor (see Figure 17); the bronchi overgrown by cancer take on the appearance of thick-walled white tubes with a narrow, sometimes barely noticeable lumen. If the growth of the tumor proceeds mainly along the course of the lymphatic vessels (retrogradely), then one notices a large number of small whitish strands extending from the main node deep into the lung, which, upon reaching the pleura, have a tendency to produce lush growth here on the surface, which is usually accompanied by fibrinous-hemorrhagic effusion into the pleural cavity. Finally, in rarer cases, bronchial cancer takes on the character of a diffusely infiltrating process, when extensive areas of the pulmonary parenchyma (see Figure 18), sometimes entire lobes of the lung, resemble the lung in gray hepatization or carnification, or simulate caseous pneumonia, which can also be facilitated by the presence of cheesy decay, the formation of cavities, etc. The growth of the tumor occurs here, mainly, in the parenchyma itself, along its air-conducting system, and, apparently, multicentrically, i.e., the tumor develops simultaneously in several points of the organ. Some authors believe that in such cases it is a matter of so-called lung cancer, i.e., cancer originating directly from the alveolar epithelium; at the present time, the possibility of such a genesis of the tumor is not denied, but it is more accepted in these cases to speak of bronchial cancer, especially since here, too, one can prove the presence of primary foci in the small bronchi. The histological structure of bronchial cancer is diverse: glandular (adenocarcino
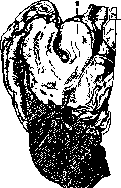
Figure 17. Cancer of the lung hilus, compressing the right main bronchus: 1—trachea; 2—tumor of the bronchus.
ma), squamous cell (sometimes keratinizing), medullary, and basal cell carcinoma; the latter often takes the form of small cell carcinoma, which simulates round cell sarcomas. The starting point of bronchial carcinoma is the covering or glandular epithelium of the bronchi; since a significant portion of bronchial carcinomas are squamous cell (which is unusual for a mucous membrane lined with columnar epithelium), the concept of pre-carcinomatous metaplasia of the bronchial epithelium has been established, i.e., its transformation from columnar to squamous, from which bronchial carcinoma subsequently develops. This metaplasia, indeed, often occurs in the bronchi during various acute and chronic inflammations; here, particular importance is currently attached to influenza and gas poisoning. Bronchial carcinoma is also observed in the walls of tuberculous cavities, bronchiectases, and in anthracotic scars; this must be kept in mind so as not to draw a direct conclusion about the absence of bronchial carcinoma in the presence of, for example, tubercle bacilli in the patient's sputum. The main changes on the part of the tumor-affected bronchus
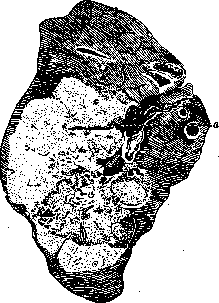
Figure 18. Large (light) tumor node (cancer) with incipient breakdown in the center; a—region of the lung root, narrowing of the bronchus by the tumor and its ulceration. In the part of the lung lying below the stenosed section of the bronchus, atelectasis develops; if the main bronchus is stenosed, the entire lung becomes atelectatic; if the upper lobe bronchus is stenosed, vicarious emphysema develops in the lower sections of the lung. In addition to atelectasis and emphysema of the corresponding lobes of the lung, bronchial cancer produces a number of pathological processes in the lungs that often completely obscure the underlying disease; most frequently appearing here are chronic pneumonias with carnification, purulence (lung abscesses), bronchiectasis, atelectasis, and gangrene; the latter sometimes encompasses the main mass of the tumor itself. All these pulmonary phenomena can also occur with very small bronchial cancers, for example, with cancers that polypously protrude into the lumen of the bronchus. Sometimes bronchial cancer invades the mediastinal spaces, the esophagus (with ulceration, which gives cause for confusion with esophageal cancer), the pericardium, the heart muscle, and the large vessels of the latter. With abundant breakdown of the tumor, erosion of vessels with fatal hemorrhage can be observed; small hemorrhages are a common occurrence. In bronchial cancer, the pleura is often involved in the inflammatory process in the form of either fibrinous deposits on it or the formation of an exudate, serous at first, subsequently acquiring a hemorrhagic character. The clinical picture in these cases initially often differs in no way from ordinary exudative pleurisies. The exudate sometimes persists throughout the entire disease or undergoes complete resorption, encapsulation, and the formation of adhesions. Cytologically, this exudate also often differs in no way from ordinary exudates. Typical giant cells with vacuoles and a nucleus shifted to the periphery, characteristic of carcinomatous exudate, are found in cases where there are metastases to the pleura, and even then not always. Bronchial cancer frequently, and usually early, gives metastases, first to the regional bronchial glands, then to the tracheobronchial glands (at the bifurcation) and, finally, to the glands of the anterior and posterior mediastina. The latter metastases are extremely important, because they sometimes cause compression of large blood vessels and physiologically important nerve trunks. Compression of the phrenic nerve causes paresis of the diaphragm, compression of the recurrent nerve causes paresis of the vocal cords, and compression of the superior vena cava or its large branches entails a circulatory disorder, the result of which is edema of the upper half of the body or one side of it and cyanosis. Some clinicians distinguish a special type of bronchial cancer—"mediastinal cancer"—but in essence, the entire clinical picture is caused by metastases to the mediastinal glands, and not by the bronchial cancer itself, which may be very small in this case. The clinical picture in these cases differs in no way from the picture of mediastinal tumors of another origin. Among the distant foci that result from the metastasis of bronchial cancer, the most important are tumors in the liver, the brain and its membranes, the bones, the adrenal glands, and more rarely in the soft tissues of the limbs, especially the thighs (simulation of thigh sarcoma). Metastases to the cranial cavity often mask the main symptomatology of the affliction, leading to incorrect diagnoses of brain tumor or apoplexy, etc. Cases of metastasis to the pituitary gland with symptoms of diabetes insipidus are encountered; metastases to the vertebral bodies, with invasion of the spinal cord and its roots, simulate primary myelitis, neuritis, etc. Clinically, therefore, it is important to remember that bronchial cancer, being sometimes inconspicuous at the site of its development, can produce extremely variegated and diverse nervous and other symptoms by way of metastasis, which, like the pulmonary complications indicated above, sometimes make the clinical diagnosis completely impossible. As can be seen from all of the above, bronchial cancer can produce a very diverse clinical picture of the disease; some of its main types have already been indicated: stenosis and ulceration of the bronchus; pleurisy obscuring the underlying disease; mediastinal tumor as a result of metastasis, also often obscuring the underlying process. In the initial stage, bronchial cancer generally produces a very scanty clinical picture. One of its early symptoms is cough in the form of paroxysms of a pertussis-like character. The cough may be dry or with sputum (mucopurulent). Sometimes, already in the early period, blood appears in the sputum and even profuse hemorrhage may occur. Sputum impregnated with blood in the form of "raspberry jelly" is considered characteristic. Microscopic examination of the sputum yields little diagnostic data. Relatively rarely, an accumulation of fat droplets in the form of spheres is found in it—apparently fatty-degenerated cancer cells (Lenhartz). An even rarer finding in the sputum is pieces of the cancer tumor. Finally, it should be kept in mind that in bronchial cancer, sputum and even cough may be absent altogether. Sometimes shortness of breath, dull constant pains deep in the chest, or stronger pains increasing with coughing and pressure on the diseased side, resembling pleuritic pains, appear very early; the phenomena of pleurisy are not always present in this case. Subfebrile temperature is observed almost always, sometimes even higher, depending on added complications (suppurative processes in the lung and sepsis). Cachexia is often absent. The duration, counting from the appearance of the first symptoms, is 1/2 to 1, rarely 2–3 years. Physical symptoms. Small tumors without metastases may manifest nothing; with larger nodes, and especially when infiltration spreads to the lung tissue, there are usually obtained: massive dullness to the right or left of the sternum, weakening of breathing and vocal fremitus. With slight stenosis and complication by pneumonia, breathing may be preserved, and then moist rales are auscultated. With stronger stenosis, the phenomena of stenotic breathing—stridor—come to the fore. As a result of tumor breakdown, resp. destruction of tissue by complicating suppurative or gangrrenous processes, characteristic cavitary phenomena are discovered upon examination of the patient. As a result of scarring and shrinking of the tissue after inflammatory processes complicating bronchial cancer in the lung or pleura, or more often as a result of atelectasis, the diseased side appears reduced in volume, and the intercostal spaces are narrowed. Diagnosis is difficult; most often one has to differentiate from pulmonary tuberculosis. When there is bronchial cancer of the upper lobe of the lung with constant temperature, hemoptysis, and chills, the clinical picture gives cause for confusing these two processes. One of the main methods in diagnosis is X-ray examination, which in bronchial cancer is based mainly on the property of the cancer infiltrate, like any dense formation, to produce a shadow on the light background of the lung field. The following features are considered most characteristic for the X-ray picture of bronchial cancer: 1) expansive growth of the shadow, 2) signs of bronchial stenosis, 3) formation of shadows characteristic of metastases in neighboring glands. According to the type of X-ray shadows produced by bronchial cancer, Assmann distinguishes the following types of it: 1) lobar, 2) lung root cancer, 3) diffuse cancer—carcinomatous lymphangitis, 4) miliary carcinosis. The first type produces the following X-ray picture: a continuous homogeneous shadow with a clear lobar boundary is visible on the screen. The primary cancer node in the bronchus is usually not visible in these cases. The darkening is a consequence of either cancer infiltration of the pulmonary parenchyma or reactive pneumonia joining the primary cancer process. And, finally, a continuous homogeneous, but less intense shadow can be the result of atelectasis of the lung tissue due to narrowing of the bronchial lumen. In the latter case, the distinguishing sign of the malignant process, namely the increase in lung volume, is absent, and, conversely, there is a narrowing of the intercostal spaces, upward pulling of the interlobar boundary, and pulling of the trachea toward the diseased side. In the presence of a reduction in the volume of the diseased lung, it is sometimes almost impossible, even on the basis of X-ray data, to distinguish bronchial cancer from a tuberculous process. The spread of the process further to neighboring lobes, the distortion of the contours of the interlobar boundary and the increase in the phenomena of stenosis, as well as the circumstance that the apex, when the upper lobe is affected, often remains free in bronchial cancer, can provide some footholds for diagnosis. Characteristic signs of bronchial stenosis are the displacement of the mediastinal shadow toward the diseased side and the paradoxical type of breathing as a consequence of the suction action on the mediastinum and diaphragm. The second type, hilus cancer, produces a dense shadow on the screen, in the form of a node, in the region of the lung root; radiant shadows depart in all directions from this shadow—a sign of the spread of the tumor along the course of the bronchi and vessels. Syphilis in the region of the lung root also produces darkening in the hilus and cords extending into the lung tissue; it is possible to distinguish it from bronchial cancer in many cases only with the help of other clinical data.
Primary tuberculosis does not show such progressive growth as bronchial cancer and has no tendency to stenosing. Actinomycosis is differentiated by sputum examination data. The third type, carcinomatous lymphangitis, is characterized by thin branching cords forming a network, occurs very rarely, and is seldom diagnosed. The fourth type, miliary carcinosis, as a consequence of hematogenic dissemination, gives small abundant spotting covering both lungs; it is almost impossible to distinguish from miliary tuberculosis, and it is diagnosed extremely rarely (Assmann). Metastases in the regional glands give nodular compact shadows in the region of the hilus and in the anterior and posterior mediastina, differ from the primary cancer node by smooth, often oval contours, and often cause compression of the phrenic nerve; in that case, fluoroscopy exclusively determines a high standing of the diaphragm dome on the affected side and a paradoxical type of respiration. Usually, metastases in the hilus are located on one side; if they are located along the midline, it is often impossible to distinguish them from a tumor of the mediastinum itself—sarcoma, lymphogranuloma. For cases with an unclear nature of the neoplasm in the chest cavity, Borak and Lenk proposed trial X-ray therapy. Sarcoma disappears quickly, lymphogranuloma more slowly, tuberculous lymphoma and chronic pneumonic infiltration even more slowly, while cancerous tumors almost completely do not respond to X-ray therapy. Recently, Lorey, Hasslinger, and Presser proposed using the introduction of 40% iodipin or lipiodol into the bronchi for the diagnosis of bronchial cancer, since it is known that the lesion of the bronchial wall with its destruction and stenosing is inherent, mainly, in bronchial cancer, whereas syphilis and tuberculosis, as a rule, do not destroy the bronchi. It is especially difficult to distinguish bronchial cancer from these two diseases if there are phenomena of decay and cavities are visible on the screen; it is precisely in these cases that bronchography, by revealing a filling defect of the bronchus with deformation of its contours, makes a correct diagnosis possible. In cases complicated by exudative pleurisy, it is recommended to release the exudate before fluoroscopy; sometimes artificial pneumothorax also helps in recognition; if there is a cancerous infiltration of a lung section, it does not collapse during pneumothorax, but protrudes against the light background of the air pocket. In general, the entire symptomatology of bronchial cancer is extremely variegated due to a mass of intervening secondary symptoms, and if the main tumor is not amenable to recognition, the clinical diagnosis often becomes only more or less probable; that is why 40%–50% of bronchial cancers are usually not recognized during life; practically, however, it is useful in all cases of prolonged indefinite pleuropulmonary or mediastinal suffering to reckon with the possibility of bronchial cancer itself. Treatment of bronchial cancer is possible only symptomatically, while surgical intervention presents exceptional difficulties and is not yet practiced. In preventive terms, it is necessary to promote the improvement of the sanitary welfare of populated areas and industrial enterprises, the occupational hazards of which contribute to the development of pneumoconioses and various chronic inflammations of the respiratory tract.
Related articles
Mentioned in
Cite this page
“Bronchi.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/bronchi/