Tracheotomy
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article describes the surgical procedure of tracheotomy, including its indications, techniques for upper and lower tracheotomy, and the types of cannulas used. It details the anatomical considerations and post-operative management of the airway.
Encyclopedia article (1928–1936)
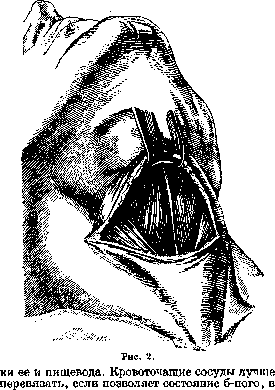
TRACHEOTOMY, throat-cutting, opening of the windpipe, is one of the most urgent operations that saves a patient's life; it is indicated for all more or less rapidly occurring difficulties in breathing in the upper respiratory tract, caused by inflammatory processes of the larynx, tumors, the entry of foreign bodies, trauma, edema, etc. Sometimes tracheotomy is performed as a preliminary act during operations in the mouth and pharynx, as well as in the larynx, with the goal of preventing the flow of blood into the respiratory tract (prophylactic, preliminary tracheotomy). Depending on where the narrowing of the lumen (stenosis) is located in the windpipe, either the trachea alone is opened—upper or lower tracheotomy—or the splitting of the overlying parts of the respiratory tract is added to it: the cricoid cartilage alone or together with the lig. crico-thyreoideum med., s. conicum (cricotracheotomy), or even the thyroid cartilage (laryngotomy); less frequently, individual sections of the windpipe are split—the thyroid cartilage alone or the lig. conicum alone. The upper part of the trachea from the lower edge of the cricoid cartilage to the isthmus of the thyroid gland is opened more often and more easily—upper tracheotomy; the splitting of the trachea below the isthmus of the thyroid gland is called lower tracheotomy; an intermediate tracheotomy was also proposed. Technique of upper tracheotomy. The operation is performed under general or local anesthesia, and in cases of severe asphyxia, without any anesthesia at all. The patient is placed on their back with the head tilted back; a bolster is placed under the shoulders. The surgeon stands on the right side of the patient, fixes the larynx with the left hand between the middle and thumb, searches with the index finger for the space between the thyroid and cricoid cartilages, and makes a longitudinal incision along the midline of the neck from the middle of the thyroid cartilage downwards or a transverse incision (Fig. 1) one finger's breadth below the cart. cricoidea. The skin with subcutaneous tissue and fascia is incised; arteries and veins are ligated and severed; then, between the mm. sterno-hyoidei of one side and the other, the adhesion, which has the appearance of a white line, is separated; these muscles are pushed apart by blunt dissection (Fig. 2 and 3); they are held with blunt retractors, the cricoid cartilage is sought in the upper corner of the incision, and it is pulled forward and upward with a sharp hook; along its lower edge, a transverse incision of the fascia is made, in the thickness of which the isthmus of the thyroid gland is enclosed; it is separated by blunt dissection from the anterior wall of the trachea and pulled downward with a blunt wide retractor; then, keeping strictly to the midline, two or three rings of the trachea are cut, blunt retractors are immediately inserted into the incision, and a cannula is inserted into the widened wound (Fig. 4, 5, and 6). When inserting the cannula into the trachea, one must ensure that its end passes into the lumen of the trachea and does not detach the mucosa or end up between the mucosa and the cartilage; the incision of the trachea must be large enough so that the cannula enters it without effort. When performing an upper tracheotomy, one must carefully avoid injuring the cricoid cartilage, as it leads to the formation of

Figure 1.
persistent stenoses; when opening the trachea, do not go too deep so as not to injure the posterior wall
otherwise leave it under a clamp. Lower tracheotomy is a more difficult and dangerous operation than the upper one, due to the fact that the trachea in this section recedes deeply backward and is intertwined with a dense network of venous vessels
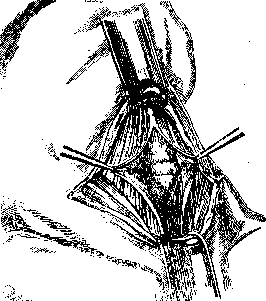
Figure 3.
vessels; the a. thyreoidea ima is also often encountered here. When even the smallest branches are injured, profuse, difficult-to-stop bleeding occurs. The skin incision is made strictly along the midline of the neck from the lower edge of the cricoid cartilage down to the fossa jugularis; having split

Figure 4.
the skin, subcutaneous tissue, and fascia, one penetrates bluntly into the depth between the mm. sterno-hyoidei, splits the loose connective tissue lying on the trachea, exposes the trachea, and, having pulled it forward with a sharp hook, opens it and inserts a cannula (Fig. 7). Lower tracheotomy is indicated where the upper section of the trachea is occupied by edema, a tumor, scars, or a foreign body, as well as in children with diphtheria. Transverse tracheotomy. The skin incision is made transversely at the level of the cricoid cartilage, the veins are ligated, the muscles are separated along the white line, the trachea is opened with a small transverse incision along the
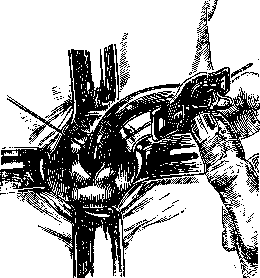
Figure 5.
lower edge of the ring, and a cannula is inserted into the resulting opening. In cases where one must hurry very much with the operation, a cricotomy is performed: a simple or specially adapted knife (cricotome) is plunged into the upper part of the lig. conicum and, advancing
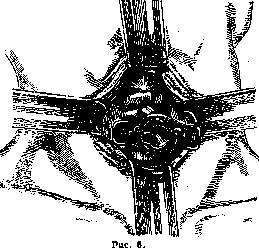
it downward strictly along the midline, the cricoid cartilage and 2 or 3 rings of the trachea are cut; after the bleeding is stopped, a cannula is inserted.
A tracheotomy cannula is a double, slightly curved tube, one fitting inside the other; the outer one is connected to a movable shield serving to fix the cannula on the neck, the inner one, easily removable and insertable, serves for cleaning. The diameter and length of the cannula are determined depending on age, the configuration of the neck, and the location of the obstruction in the trachea. The material for cannulas is silver, platinum, nickel silver, aluminum, hard rubber, or glass. Many modifications of tracheotomy tubes have been proposed, but Luer's silver tubes and Trousseau's hard rubber tubes have mainly remained in practice. Trendelenburg's tamponing tubes have a special design; they not only maintain free breathing but also prevent liquids (blood, mucus) from passing into the depth of the trachea thanks to an inflatable rubber balloon surrounding them; Hahn (Halm) achieved the same thing by wrapping the tubes with compressed sponge. The cannula inserted into the trachea is left there without being removed for 4-6 days; only the inner tube is removed for cleaning as needed; then, during dressing changes, they attempt to remove the entire cannula and, by closing the tracheotomy opening with a tampon, observe how patent the larynx has become; with good, free
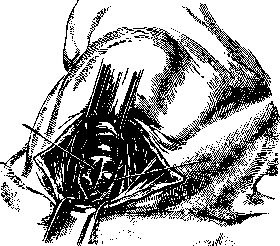
Figure 7.
breathing, the cannula is no longer inserted; how much patency has been restored can be easily determined by using a cannula with a small window (opening) on the upper convex wall and plugging the external entrance opening with a stopper. Removal of the cannula sometimes presents great difficulties (see Decannulation).
A. Pianov. Tracheotomy in operations on animals serves in physiology for establishing artificial respiration in all cases of physiological experiment, for some reason during the experiment natural respiration is turned off. T. is mandatory in experiments on curarized animals, in experiments requiring opening of the chest cavity or a high (below the medulla oblongata) transection of the spinal cord. T. is performed mainly on dogs, rabbits and cats as the most commonly used in experimental physiology and pathology of animals. The technique of T. coincides with the technique of the operation for applying a tracheotomy cannula and is the same for the listed species of animals. The operation is performed as follows. The animal is fixed on the operating table. The hair on the neck is shaved, and in rabbits it is removed with a depilatory. Under anesthesia, the skin is incised precisely along the midline from the lower edge of the thyroid cartilage downward for a distance of 4-6 cm. Then the subcutaneous tissue and the skin muscle (m. subcutaneus colli) are incised. After this, if the incision was made correctly along the midline, a narrow white strip of connective tissue is immediately found between the approximated edges of the sternohyoid muscles (mm. sterno-hyoidei). By pushing apart the edges of these muscles bluntly, the trachea is immediately exposed, which is also separated from the adjacent tissues bluntly. At the same time, care is taken that the n. recurrens definitely moves away from the trachea, because otherwise it may get into the ligature when tying the cannula. After freeing the trachea, a sufficiently strong ligature is passed under it and the trachea is incised transversely between the cartilaginous rings for two-thirds of its lumen. The tracheal end of a cannula selected for size is inserted into the incision and is firmly secured in the lumen of the trachea by tightening the ligature. If the operation was performed correctly, there are usually no complications. It should also be noted that the most convenient place for the tracheal cannula is the midpoint between the lower edge of the thyroid cartilage and the upper edge of the sternum. Tracheal cannulas used for physiological T. vary in shape but differ little in design principle. They are metal or ebonite tubes of various diameters corresponding to the most commonly encountered sizes of the tracheal lumen in the above-mentioned animals, and in factory production are usually sold as a set of five sizes of tracheal cannulas. Among the most commonly used, one can name the tracheal cannulas of Francois-Franck, Ludwig, and Verdin. In the simplest form, the tracheal cannula (e.g., of the firm Zimmermann, Leipzig) is a metal tube with olives at the ends and with a slit-shaped opening located in the lateral wall of the cannula. The slit can be closed by a movable shield to various degrees, which achieves regulation of the magnitude of pulmonary ventilation and facilitates the removal of exhaled CO2. The most complex tracheal cannulas are given a T- or L-shaped form, in the latter case with rotating elbows, which significantly facilitates manipulation with them during the experiment. In addition, some types of tracheal cannulas have valves regulating the direction of air during inspiration and expiration and are used mainly in the study of air exhaled by the animal (e.g., the Verdin valve tracheal cannula). However, in case of need, one can easily do without special cannulas and successfully replace them with a T-shaped glass tee of suitable diameter, on the side outlet of which a rubber tube is fitted, narrowed to the required size by a screw clamp according to the desired magnitude of pulmonary ventilation. A very significant inconvenience when using tracheal cannulas of conventional design is the inability to maintain proper anesthesia, especially ether-chloroform, which is the most accessible and commonly used in the most diverse experiments, especially on dogs. In the simplest case, this inconvenience can be overcome by introducing into the lumen of the tracheal cannula through a side opening a wick made of gauze, moistened from time to time with ether or chloroform. However, this method is not very convenient and does not always achieve the goal. Therefore, it is better to use special apparatuses adapted for anesthetizing tracheotomized animals. The latter includes the simple and easy-to-use apparatus of Tigerstedt (fig. 8). The apparatus consists of a flask d, the lower end of which is connected with a tap e, passing into a cone, with a Y-shaped tee a, the straight leg of which is connected with an artificial respiration apparatus. Tube b also connects the latter with vessel d, which achieves equal pressure in the latter and in tee d, facilitating the outflow of ether or chloroform when tap e is open. The stopping of the outlet opening of tap e is done by a micrometric screw k, which regulates the required depth of anesthesia.
b. Indications. T. is indicated in cases of acute or chronic obstruction of the upper respiratory tract, when the obstruction cannot be removed by other means. The most common causes of such obstruction are: 1) foreign bodies in the larynx or trachea; 2) edema of the larynx or trachea (burns, injuries, diphtheria, etc.); 3) tumors of the larynx or trachea; 4) stenosis of the larynx or trachea (cicatricial, congenital, etc.); 5) paralysis of the laryngeal muscles. In addition, T. is performed in some operations on the neck and upper mediastinum to improve access to the surgical field and to facilitate the management of anesthesia. In military surgery, T. is used as a life-saving measure in cases of gunshot wounds of the neck with damage to the larynx or trachea.
c. Technique. T. can be performed under local or general anesthesia. The patient is placed in a supine position with the neck extended. The skin is disinfected and draped. A midline incision is made from the lower edge of the thyroid cartilage to the suprasternal notch. The subcutaneous tissue and platysma muscle are divided. The sternohyoid and sternothyroid muscles are separated in the midline. The trachea is exposed and a tracheal hook is inserted under it. The trachea is incised transversely between the second and third cartilaginous rings. A tracheal cannula is inserted and secured with tapes. The incision is closed around the cannula.
d. Complications. The most common complications of T. are hemorrhage, infection, subcutaneous emphysema, pneumothorax, and damage to the recurrent laryngeal nerve. Late complications may include stenosis of the trachea and granulation tissue formation. The mortality rate from T. is relatively low, but it depends on the cause of the obstruction and the patient's general condition.
Related articles
Mentioned in
Cite this page
“Tracheotomy.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/tracheotomy/