Diphtheritis
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
An explanation of the term diphtheritis, clarifying that it denotes a general pathological process of diphtheritic inflammation rather than the specific infectious disease diphtheria. It discusses how this inflammatory process can occur in various conditions and tissues, distinguishing it from true diphtheria.
Encyclopedia article (1928–1936)
DIPHTHERITIS (from the Greek diphthera - film), a term often used incorrectly to designate the infectious disease diphtheria; in reality, it represents an abbreviation for a general pathological process, specifically diphtheritic inflammation, which can develop both in diphtheria and in other etiologically distinct inflammatory lesions of mucous membranes (e.g., in the intestine in uremia, dysentery, in the uterus in septic endometritis). One can also speak of diphtheritis of a wound if it is covered with a diphtheritic deposit, which may or may not contain diphtheria bacilli (in the case of wound infection with diphtheria bacilli, one speaks of wound diphtheria). Finally, diphtheria in some cases is accompanied not by diphtheritis, but by ordinary catarrhal inflammation. Thus, the term diphtheritis in etiological and nosological respects does not represent anything specific, and therefore should not be used as a synonym for diphtheria. DIPHTHERIA. Contents: Etiology....................
400 Statistics and geographical distribution
Diphtheria (from Greek diphthera - prepared skin, membrane), an acute infectious, epidemic disease caused by the diphtheria bacilli of Loeffler, which are localized most often primarily on the mucous membrane of the throat, nose, or nasopharynx, less frequently on the mucous membrane of the larynx and trachea, and very rarely on the conjunctiva of the eye and the mucous membrane of the vagina. The inflammatory process is accompanied by the formation of false membranes (deposits), which merge densely with the underlying necrotized tissue of the mucous membranes. By the same process, wound surfaces and even the surface of the skin can also be primarily affected. But wherever the process is localized, the disease, apart from initial local disorders, is characterized by a more or less severe toxemia due to the release into the body of toxin secreted by the diphtheria bacilli. Etiology. Diphtheria bacilli (Bacillus diphtheriae Klebs-Loeffleri, Corynebacterium diphtheriae) were first described in 1883 by Klebs in sections from false membranes. In 1884, Loeffler isolated them in pure cultures. They are the causative agents of the disease. Diphtheria bacilli belong to the group of bacilli united, upon the suggestion of Lehmann and Neumann, under the general name Corynebacterium and characterized by the presence of granularity in the protoplasm and the formation of club-shaped swellings at one or both ends of the rod. Glanders, tuberculosis, and fusiform (fusiformis) bacilli belong to the same group. According to the American classification, the name Corynebacterium is assigned to diphtheria and pseudodiphtheria bacilli similar to them. According to the degree of polymorphism and prominence of Babes-Ernst polar bodies and in relation to glucose, galactose, and sucrose, the following six species of the genus Corynebacterium are distinguished. 1. C. diphtheriae - polymorphic, have typical granules at the ends of the rods, decompose glucose and galactose, pathogenic for humans and virulent for guinea pigs. 2. C. pseudodiphtheriae - completely similar to the first species, but not virulent. 3. C. Hofmann-Wellenhofi - shorter, nonpolymorphic rods with very weak granulation, avirulent, do not decompose the above-listed three carbohydrates. 4. C. xerosis - have typical Babes-Ernst granules, slightly polymorphic, do not decompose carbohydrates, avirulent. 5. C. xerosis - also have typical granules and are slightly polymorphic, but decompose glucose and sucrose, avirulent. 6. C. acnes - bear some resemblance to diphtheria bacilli, but are not always typical, decompose all three carbohydrates, and differ from the five aforementioned species in being anaerobic. Diphtheria bacilli have a very variable length, from 1-2 µ to 6 µ. French authors note short, medium, and long races of diphtheria bacilli. The thickness of the diphtheria rod, on average about 0.8-1.0 µ, increases unevenly toward one or both ends of the rod; sometimes the thickening is negligible, sometimes swellings form, which gives the rods, especially in older cultures and on less favorable nutrient media, the shape of a club or gymnastic dumbbell. In photographs of colonies from agar or coagulated blood serum, the rods are arranged in the form of intersecting, splayed fingers of hands. Being stained, the rods often look like two or more segments with weakly staining intervals. Club-shaped swellings, segmentation, and also infrequently encountered branched forms of bacilli are observed predominantly in old cultures. Such forms are called involution forms. Diphtheria bacilli are nonmotile; they have no flagella, capsules, or spores; they stain by Gram, although with prolonged treatment with alcohol they are easily decolorized. With special staining by Neisser (acetic acid methylene blue with additional staining by Bismarck brown), on a light brown background, dark blue Babes-Ernst granules stand out sharply at the ends of the rod, which are of great importance for distinguishing true diphtheria bacilli from false ones [see separate table (articles 423-424), Fig. 5 a, b, and c]. Diphtheria bacilli develop much better in the free access of oxygen than under anaerobic conditions. The optimum growth is at a temperature of 35-37° and at a medium pH = 7.8. When growing on broth, a rather coarse, brittle film is formed, easily falling to the bottom of the vessel; by the end of the day, the reaction of the broth approaches acidic (due to the decomposition of carbohydrates present in the nutrient medium) in order to return to the initial alkalinity by the end of 2-3 days, and then exceed it. On agar, small, round, translucent colonies are formed, producing on the slanted surface of the agar a delicate, bluish coating, which in old cultures can acquire a more or less pronounced yellow-brown tint. On coagulated blood serum, the colonies are somewhat larger and coarser, of a pearly gray color. Coagulated serum and gelatin are not liquefied; they grow well on milk without changing its appearance. On coagulated serum, diphtheria bacilli retain their viability and toxin production for a long time (6 months or more). They die in a liquid medium at 60° within 10 minutes, at 70° in 5 minutes; in a dried state, they withstand the action of heat at 95°-100° for several minutes, and in dried films for an hour. Dried in a thin layer, diphtheria bacilli die in diffuse light within a few days; direct sunlight kills them within a few hours; in a dark place and covered with a layer of dried mucus or film, they remain viable for several months. Temperatures below 0° are well tolerated by them, remaining in a frozen state for a long time. Solutions of sublimate 1 : 1,000 and phenol 5 : 100 kill diphtheria bacilli in 20 seconds, 3% lysol in 10 minutes, alcohol in 1 minute. Diphtheria bacilli are very virulent for guinea pigs, rabbits, birds, and cats, and much less so for horses, cattle, goats, dogs, mice, and rats. There is a certain parallelism between the virulence of diphtheria bacilli for guinea pigs and their pathogenicity for humans, as a result of which inoculations of diphtheria cultures isolated from humans into a guinea pig are used to determine the latter (methods of Eagleton and Baxter with pure diphtheria cultures, Havens and Powell without isolation of pure cultures: injection of 0.2 cm3 of culture from coagulated serum into the skin thickness of a guinea pig). Very characteristic of diphtheria bacilli is their secretion of specific diphtheria toxins, which are obtained by cultivating cultures on broth of appropriate composition and alkalinity for 7-10 days. These toxins, freed from bacterial bodies by filtration (through Chamberland or Berkefeld candles), are used for the immunization of horses for the purpose of preparing therapeutic serum, as well as for inoculating people to confer immunity to diphtheria (see below). To characterize diphtheria toxin according to P. Ehrlich, it is required to establish the following three doses of it by experiments on a guinea pig: 1) the smallest lethal dose (dosis letalis minima, Dlm) for guinea pigs weighing 250 g, killing them on the 3rd-5th day; 2) the lethal limit, or Lt dose (Limes Tod) - the amount of toxin which, in a mixture with one unit of antitoxin (AE) (one antitoxic unit, according to Behring, neutralizes one hundred smallest lethal doses of toxin), kills a guinea pig weighing 250 g in the same period as Dlm, i.e., in 3-5 days; 3) the zero limit, or L0 dose (Limes Null) - that amount of toxin which, in a mixture with one AE, injected under the skin of a guinea pig weighing 250 grams, does not cause the slightest infiltrate at the injection site. Diphtheria toxin is thermolabile: it is destroyed by the action of temperatures above 60°; at 90° it is destroyed already after 10 minutes, at 100° even sooner. But its attenuation occurs slowly even at room temperature (20-22°), even at the temperature of a room refrigerator (+6°). The addition of 0.5% phenol or toluene (so that the toxin is covered with a layer 2-3 fingers deep) promotes the duration of the preservation of toxicity, especially in a refrigerator and in a dark place; formalin in an amount of 4 per mille or more, on the contrary, promotes the attenuation of the toxicity. Ehrlich first proved that the attenuation of the toxicity of diphtheria toxin does not always run parallel to the loss of its antigenic properties (see Antigens), i.e., despite the decrease in toxicity [which is expressed in the need to increase the dose of toxin to kill a guinea pig (increase in Dlm)], it continues to neutralize the exact same amount of antitoxin (L0 dose does not change) and to the same extent causes the formation of antitoxins upon immunization of animals (conversion of toxins into toxoids, see Anatoxin). Bacillary carrier state. Even Loeffler at the beginning of his research on diphtheria discovered diphtheria bacilli in the mucus from the throat of healthy people. At the same time, as further research showed, diphtheria bacilli are discovered in the throat and nose of healthy individuals not only who had direct contact with patients, but also those who had no contact with sources of infection whatsoever. For those around a patient, the bacillary carrier state is determined from 8% (Kober) to 50% (Welch), and for those who have not had contact with patients, from 2.5% (Kober) to 24% (Muller), but the number of carriers of virulent bacilli is significantly smaller.
Thus, according to data from the British Medical Research Council, among 610 people who had close contact with diphtheria patients, 15% were found to be carriers, with all of them turning out to be virulent; among 10,883 people who had more distant contact, 8% were carriers, of whom only 1% were virulent; and finally, among 7,974 people who had no contact with patients, there were 3.4% non-virulent carriers and only 0.6% virulent ones. Thus, virulent bacillus carriers are much fewer than avirulent ones. From this arises the desire in practical measures to combat diphtheria to limit oneself solely to measures directed against virulent bacillus carriers. Theoretically, this desire appears completely correct, since it is obvious that in pathology only bacilli of the species Corynebacterium diphtheriae (see above), pathogenic for humans and virulent for guinea pigs, can play a definite role. However, detailed studies by Bashenin and Birger with co-workers have shown that upon repeated determinations of the virulence of diphtheria cultures from the same individual, carried out over a long period of time, heterogeneous results are obtained, sometimes positive and sometimes negative, without any discernible reasons to explain such irregularity. Furthermore, the mentioned researchers established that in some closed children's institutions not a single case of diphtheria is observed for a long time despite the constant presence of virulent bacillus carriers, while in others, on the contrary, cases occur in the presence of only avirulent bacillus carriers. Of course, this contradiction is explained by the imperfection of the methodology for determining the virulence of diphtheria bacilli. However, one has to put up for now with an imperfect method that yields a certain percentage of errors, and limit oneself to sanitary measures directed at virulent carriers, since the isolation of all diphtheria bacillus carriers is practically impossible even in closed children's institutions. Diphtheria patients continue to retain diphtheria bacilli in the mucus of the throat and nose for a fairly long time after their recovery. Namely, in almost half of the recovered patients, bacilli are found in the throat mucus for 2 weeks, in a quarter for 3 weeks, and in 10% for 5 weeks from the onset of the disease. Later, the number of carriers sharply decreases, but in individual cases, bacillus carriage was observed for 4-9 months. Bacillus carriage has even been described for several years (Pochon, Neisser). Fortunately, such prolonged bacillus carriage is a great rarity. Unfortunately, there are no reliable means whatsoever to rid carriers of diphtheria bacilli. The best results are given by the extirpation of enlarged tonsils (before the operation, it is necessary to inject anti-diphtheria serum to prevent wound infection with diphtheria). It should be noted that patients and convalescents excrete predominantly virulent diphtheria bacilli, and only later, starting from the 5th-6th week from the onset of the disease, do avirulent diphtheria bacilli begin to predominate in their mucus. This determines the main role in the spread of diphtheria played by patients and convalescents, and the comparatively minor role of healthy bacillus carriers. Discharge from the hospital of those recovering from diphtheria is carried out as a rule on the basis of a two- to three-fold bacteriological examination that has yielded negative results. When it is impossible to be guided by bacteriological examination, discharge is permitted 2 weeks after the disappearance of all clinical symptoms of the disease. (See also Bacillus carriage.) Epidemiology. Diphtheria has a contagious character, spreading either directly from person to person or through the medium of objects contaminated with diphtheria secretions (mucus from the throat and nose, sloughing membranes). Rare cases of diphtheria epidemics arising through food products, in particular through milk (Neisser, Sobernheim, and Nagel), have been described. Spiegelberg and Litterer discovered virulent diphtheria bacilli in chickens, and the latter author observed the successful transfer of bacilli to chickens both from other chickens and from a sick person. The presence of diphtheria bacilli in horses has also been proven (Kliewe, Westhues). However, practically only contact transmission of the infection is of significance, as a result of which diphtheria epidemics never produce such sudden and widespread outbreaks as waterborne epidemics of typhoid fever or cholera. The spread of diphtheria bacilli through the air by droplets sprayed by diphtheria patients and bacillus carriers during shouting and coughing has been proven by the experiments of Jellenigg (1924), who discovered diphtheria bacilli on cough plates at a distance of 35 cm from the bacillus carrier. Diphtheria was isolated as a distinct nosological unit only in 1826-28 by French researchers Bretonneau and Trousseau. However, descriptions of "malignant angina," affecting predominantly children and giving rise at times to epidemic outbreaks, are found already in the Talmud and among the most ancient writers of the Christian era (Aretaeus, Aetius, and others). In the 16th and 17th centuries, diphtheria was undoubtedly significantly widespread in Europe, especially in 1618-42, as well as in the 18th century. The first reports of diphtheria in America date back to the 18th century. At the beginning of the 19th century, diphtheria was extremely poorly developed in Europe. It was known so little that even 15 years after the publication of Bretonneau's works, the famous Viennese pathologist Rokitansky considered diphtheria a "French invention." Only by 1850 was there no longer any doubt about the existence of diphtheria in Europe. From then until 1890, the diphtheria epidemic grew rapidly in both Europe and America, after which the epidemic curve began to decline. According to Kisskalt's studies, the spread of diphtheria in Europe in the 19th century proceeded from the east. In Russia, another epidemic wave of diphtheria was observed, reaching its maximum by 1910. Then comes a continuous decline of the curve, reaching its lowest point in 1919. Over the past 2-3 years, an intensification of the diphtheria epidemic has again been noted in Europe, America, and other countries of the world, expressed in an increase in the number of cases (especially in the intensification of their severity). But the rise of the epidemic curve is still proceeding very slowly. Thus, the epidemic curve of diphtheria periodically rises and falls under the influence of as yet unclear conditions. There are attempts to give an explanation for this interesting phenomenon, observed not only in epidemic factors, and it is confirmed by the seasonal fluctuation of this curve, the rise of which is observed in the autumn-winter season. Gottstein seeks an explanation in the generational turnover of individuals more resistant to diphtheria by those less resistant. Susceptibility to diphtheria depends on age. The decrease in susceptibility to diphtheria with age is explained by the contact of the mass of the population with the pathogen of the disease through the medium of bacillus carriers, as a result of which a constant imperceptible immunization occurs. Polish researchers (Hirszfeld, Brokman) found that a child's susceptibility to diphtheria also depends on belonging to one or another blood group (see Hemagglutination). Thus, if a child belongs to the same blood group to which one of their parents belongs who has a positive Schick reaction, then they also have a positive reaction and, consequently, are susceptible to diphtheria and remain such for life, despite active immunization or even a contracted case of diphtheria, which impart to them only temporary non-susceptibility. Conversely, if a child belongs to the blood group to which the parent belongs who has a negative Schick reaction, then even if the child has a positive Schick reaction, they easily acquire immunity to diphtheria both upon immunization and independently with the onset of maturity. Thus, the role of constitution comes to the fore.
Korshun. Statistics and geographical distribution. - 1. Mortality. Statistics from various countries present a picture of a sharp decrease in mortality from diphtheria following the introduction of serum therapy (1894) and its gradual decline in subsequent years. Table 1 shows the mortality rates from diphtheria over a number of years across various countries (annual average per 100,000 population). Table 1... All these countries show a decrease in diphtheria mortality after 1894. In some countries (England, Germany, the Netherlands, Denmark, etc.), an increase in diphtheria mortality can be noted during the World War or in the years immediately following it. The latest period (1924-27) for all countries is characterized by an unprecedentedly low mortality from diphtheria. Figures 1 and 2 show the curves of diphtheria mortality trends by year for England and Switzerland (since 1876), Germany (since 1892), and the USA (since 1899). In England, for the period from 1876 to 1902, regular periodic rises and falls in diphtheria mortality are noted, with the latter never dropping below 25 per 100,000 population during this period. The maximum rise was observed in 1893 (38.9). Starting from 1903, the curve changes and shows a steady step-like decline (with temporary rises in the process of decline). A small rise is noted for the period from 1914 to 1920, after which a further decline of the curve occurs down to 7 per 100,000 population. The mortality curves for other countries are of approximately the same character. In Switzerland, diphtheria mortality rates for the period from 1876 to 1901 were significantly higher than in England (fluctuating from 27 to 81 per 100,000 population); a steady decline in the curve begins in 1902, and since 1922, diphtheria mortality in Switzerland has been lower than in England. In Germany, for the period from 1892 to 1919, diphtheria mortality rates were higher than in England and Switzerland; a sharp and subsequently steady decline in the mortality curve begins in 1895. A strongly pronounced rise in mortality is evident in 1915-17, after which a rapid decline of the curve ensues, and the mortality rates level off with those of England and Switzerland. The diphtheria mortality curve for the USA almost duplicates that of Germany both in the height of the rates and in its course. It lacks the rise during the years of the World War. The order of individual countries by the height of diphtheria mortality differs before and after the World War. Tables 2 and 3 list individual states in descending order of diphtheria mortality height for the periods from 1901 to 1913 and from 1922 to 1926 (cf. also Figures 3 and 4). Based on an analysis of pre-war materials on the geographical distribution of diphtheria (for 1890-94 and 1906-10), S. A. Novoselsky concludes that 'the spread of diphtheria in Europe increases in the direction from west to east.' Materials for 1901-13 (Table 2) generally confirm this conclusion (except for Romania, where diphtheria mortality is recorded as relatively low). A different geographical distribution of diphtheria has been noted in recent years (Table 3); the highest mortality rates are observed in the western countries of Europe: Spain, England, Scotland, Ireland, and Italy. Central and eastern countries: Austria, Czechoslovakia, Yugoslavia, Bulgaria, Poland, and Romania show significantly lower mortality rates. Among non-European states, the USA, both before the World War and in recent years, occupies one of the highest places in its diphtheria mortality rate; Japan and New Zealand show average mortality rates. Table 4 presents diphtheria mortality rates in some major European cities for the period from 1880 to 1927 (per 100,000 population). Table 5. Mortality from diphtheria... This table gives an idea of the decrease in diphtheria mortality after the introduction of anti-diphtheritic serum (in Leningrad and Moscow, it is less pronounced than in Western European cities) and of the low figures of this mortality in recent years (cf. Figure 5). Table 6 (see p. 407) gives an idea of the trend of diphtheria mortality in major cities of various parts of the world in 1925-27 (per 100,000 population).
Zurich..... Brussels . . . Dresden .... Hamburg . . . Basel..... Munich .... Oslo...... Nuremberg . . 1925 1926 1927 19,8 18,2 9,9 13,0 23,3 10,7 15,5 17,3 15,6 10,5 15,6 8,0 10,0 14,0 10,1 9,4 13,6 3,2 5,7 13,0 9,0 10,4 12,1 11,3 12,5 10,9 3,5 5,1 10,6 6,4 8,5 9,6 10,4 11,7 8,4 4,9 6,9 8,1 9,0 8,2 8,0 6,9 13,2 7,9 10,3 8,0 7,5 5,7 6,3 5,7 - 3,6 5,4 3,8 3,9 0,0 0,0 3,2 5,3 3,6 2,1 0,5 1,7 1,6 1,2 1,9 1,1 1,9 3,2 1,7 1,9 1,4 0,0 0,7 3,5 2,6 0,6 2,0 0,8 0,4 1,8 0,8 0,0 Asia Nagasaki....... Tokyo ......... Calcutta....... Singapore....... Bombay........ Africa Suez ......... Cairo......... Alexandria ..... Johannesburg..... North America Montreal....... Toronto ....... Panama........ New York....... South America Bogota......... Buenos Aires..... Lima......... Australia Sydney ........ Auckland........ 1925 1926 1927 10,5 3,3 4,0 0,5 11,8 36,3 11,4 2,3 16,5 12,1 10,0 11,3 9,2 2,6 5,0 1,6 1926 1927 11,1 7,7 5,0 2,1 0,6 11,8 30,2 12,6 4,1 20,3 17,2 6,0 8,1 13,8 13,0 4,7 11,6 9,4 8,1 1,8 0,5 69,7 44,1 38,9 5,8 31,3 24,5 13,5 12,0 15,1 11,7 3,0 7,8 5,2 in Moscow, Leningrad, and Odessa (annual average per 100,000 population). Table e. Years Moscow Leningrad Odessa 1881-1885 . 1886-1890 . 1891-1895 . 1896-1900 . 1901-1905 . 1906-1910 . 1911-1913 . 1914-1918 . 1919-1923 . 1924-1927 . 63,0 77,5 73,0 63,8 45,8 49,6 45,3 29,2 20,2 15,3 110,0 58,6 53,2 109,0 62,6 56,2 22,7 30,6 27,2 10,2 40,2 62,3 21,2 29,5 13,5 5,5 Overall, across all these cities, one can note a gradual decrease in mortality from diphtheria and particularly low figures for recent years. The curves of mortality from diphtheria by individual years (Fig. 7) give an idea of its periodic rises and falls (cyclical nature of diphtheria epidemics). - Upon reviewing all the tables presented above (1-6), one can note a particularly low mortality from diphtheria in the recent period. This can be explained by two facts: 1) the large epidemic of diphtheria before the war, and for many states and cities also during the World War, followed by a natural decrease in the incidence of diphtheria due to the cyclicity of diphtheria epidemics; 2) the change in the composition of the population (a sharp decrease in the child population after the World War) and a consequent decrease in the incidence of diphtheria. The very latest years (1927-28) for individual states and cities are characterized by the beginning of a new rise in the diphtheria wave. Mortality from diphtheria by sex and age is illustrated by the following table (Table 7). Table 7. Mortality by sex and age in Moscow in 1926 (per 100,000 persons of each group). Among individual age groups, children under 5 years old show the highest mortality. Mortality of children from diphtheria under 5 years of age by individual age groups can be illustrated by the following figures (Table 8). Table 8. Mortality by sex and age of children under 5 years (per 100,000 population). Prussia Age 1905-09 1906-10 M. F. Both sexes M. Both sexes 0-1 year . 1-2 years . 2-3 » 3-4 » 4-5 » 35,0 95,0 99,0 114,0 108,0 30,0 86,0 98,0 120,0 111,0 34,0 84,0 99,0 119,0 109,0 136,6 201,9 152,3 } 115,2 109,6 169,3 137,1 107,3 122,8 185,6 144,7 111,3 Age Males Females Both sexes 0-12 months..... 96,7 78,8 87,9 1-4 years .... 82,7 80,6 5-9 » .... 10,1 23,5 16,8 10-14 » . . . . 1,4 0,7 15-19 » . . . . 0,9 0,5 20-59 » . . . . 60 years and older . 3,7 1,1 Boys under 5 years of age show a slightly higher mortality from diphtheria than girls. At older ages, the mortality of women is higher than that of men. From Figure 3 and 4. In England during the specified period, the highest mortality was observed at the age from 3 years to 5 years; it was slightly lower in children from 1 to 3 years; and lowest in the age group under 5 years - in children under 1 year (Figure 8). In Prussia, the highest mortality was noted at the age from 1 to 2 years, followed by age groups from 2 to 3 years and under 1 year. 2. Fatality rate (case fatality). For individual countries, the number of deaths per 100 registered patients in recent years is shown in Table 9. The case fatality from diphtheria varies widely across individual countries: from 3-4 per 100 cases (New Zealand, Denmark) to 15-18 (Czechoslovakia, Bulgaria) and 24 (Japan). Case fatality in eastern countries is generally higher than in western countries. However, the level of the fatality rate is significantly influenced by the completeness of registration of patients. Hospital mortality for Leningrad for the period from 1886 to 1926 is expressed by such figures (Table 10). Table 10. Case fatality in hospitals of Leningrad (per 100 patients). Years Fatality rate Years Fatality rate 1886-1890 . . . 1891-1895 . . . 1896-1900 . . . 1901-1905 . . . 9,6 18,0 25,6 22,1 1906-1909 . . . 1910-1914 . . . 1915-1921 . . . 1922-1926 . . . 19,5 14,6 16,9 15,8 Fluctuations in case fatality for individual periods range from 9,6 to 25,6 per 100 cases. Case fatality decreases with Table 11. Age Cases Died Mortality C- 5 years . . . 37,3 6-10 » ... 17,0 11-15 » ... 8,4 16-20 » ... 5,1 21-30 » ... 4,1 Older than 30 years . 8,6 Leningrad, the corresponding figures are given in Table 12. The decrease in case fatality after 1895 coincides with the introduction of antidiphtheritic serum. Case fatality in diphtheria is unequal depending on the presence or absence of an epidemic. Thus, in the Virchow Hospital (in Berlin) in recent years, the case fatality (per 100 patients) was:
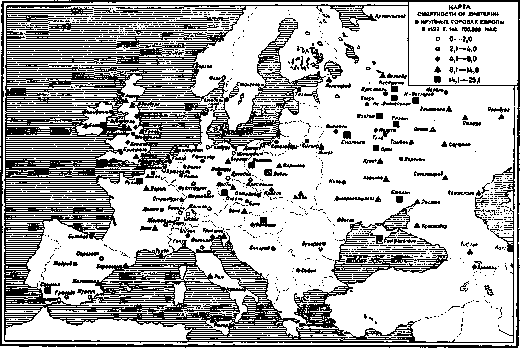
Figure 6.
in 1924—5.0, in 1925—8.7, in 1926—17.4, in 1927—12.8, in 1928 (up to 15/XI)—16.4 (cf. also Fig. 10 and 11). The increase in lethality is explained by Deicher as due to the presence of a large number of severe septic forms of diphtheria that are difficult to treat with diphtheria antitoxin, which is observed at the beginning of the development of a diphtheria epidemic. The increase in lethality during epidemics has also been noted by other authors. 3. Morbidity. For the period from 1919 to 1927, the following number of cases of diphtheria in absolute figures was registered in individual countries (Table 13). For a number of countries (USSR, Bulgaria, Hungary, Italy, Poland), a gradual increase in the number of diphtheria cases has been noted in recent years. From Table 14, it can be seen in what order individual states are arranged by the level of morbidity per 10,000 population over the last 3 years. In recent years, diphtheria has been registered at the highest rates in Europe—in Denmark, England, and Scotland; among non-European countries—in Australia, New Zealand, Canada, and the USA. A number of countries—Romania, Yugoslavia, Belgium, etc.—show very low morbidity rates. The USSR shows an average morbidity rate. Table 13. States 1919 g. 1920 g. 1921 g. 1922 g. 1923 g. 1924 g. 1925 g. 1926 g. 1927 g. England . . . 66 508 Belgium . . Bulgaria . . - - Germany . . - - 37 949 Netherlands . Denmark .... ! 9.904 Italy . . . ; 11.103 - Lithuania .... - - Poland . . . 4,130 Romania . . 2 238 Finland . France . . | 10.009 14,598 Switzerland . Sweden . . . 26,448 Japan . . . ! 14.290 14 522 13 .968 12 776 13 858 15 210 : - 204 235 139 472 119 831 106 192 Australia . . 9 915 New Zealand * ya ^ \ t 1 1 Deaths 1 1 ility from 1 Mo ni Leningrad in Odessa [per 100,000 popul.) 90- 80- 70-60- n o№~ *o- 80-20- ao- \ \ \ i in m ei 1KG pj\ \ Moscow. Ml \ l3 ___________ Leningrad /] f > "> \i J5 i (\ \ \ f <~ \J \ \ \ / [I !va \_ \ b ^ \ \ / \ 1\ \ \, l \. 1 Oj ec( -v st "1 I,! s_ " \ / U' / - jV v_ Years, t j>l 93 93 94 9T t \ 1 1 12 i t j 2fi ebl lefeo 1900 lAo 1920 Figure 7. Table 14. Number of registered diphtheria patients per 10,000 population. Australia... Denmark...... New Zealand Scotland... England..... Canada..... Austria..... Norway (cities) Sweden...... Switzerland.... Germany..... Netherlands.... Estonia...... Bulgaria..... Italy..... Czechoslovakia.. Finland..... Latvia...... France..... Japan...... Lithuania....... Belgium...... Yugoslavia.... Egypt....... Romania..... 1925 g. 1926 g. 1927 g. 15.1 13.2 18.6 15.4 14.8 15.4 19.2 10.8 14.9 13.9 14.9 - 10.9 12.3 13.1 10.5 7.9 7.8 10.3 8.1 7.1 5.0 5.6 5.6 5.1 5.3 5.6 8.1 6.7 5.4 7.0 6.3 5.4 6.8 6.7 4.9 6.1,9 4.8 6.1 6.7 4.7 4.9 4.9 4.2 3.0 3.0 3.9 3.7 3.5 3.7 2.9 3.1 3.7 3.7 3.5 3.3 3.2 3.6 3.3 2.9 3.1 3.2 2.3 2.2 2.3 1.8 2.1 2.3 1.0 0.8 1.5 2.2 1.8 1.4 1.4 1.3 1.3 1.1 1.3 1.1 0.8 0.8 1.1 Morbidity in the USSR. The movement of diphtheria in the USSR, Ukraine, Moscow, and Leningrad for the period from 1886 to 1927 is given in Table 15 (average annual morbidity per 10,000 population), as well as in Fig. 12. In the USSR (Russia), in epidemic-free years, an average of about 15 cases of diphtheria per 10,000 population were registered annually, and in the pre-war period the morbidity rate never dropped below 11.5. The first rise is noted in 1895–97 (up to 22 per 10,000 population). The second wave of diphtheria begins in 1906, reaches a maximum in 1910 (43.1), and holds through 1915 inclusive, i.e., 10 years. After this, a sharp decline in diphtheria follows, and since 1919 (there is no information for 1917–1918), diphtheria has been registered in unprecedentedly low figures. In recent Table 15. Years

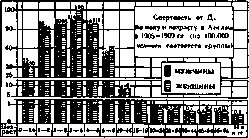
Figure 8.
The comparative morbidity of diphtheria in individual republics of the USSR is given in Table 16, and in individual regions of the RSFSR—in Table 17. Before the World War, the spread of diphtheria in the southern and southeastern provinces of Russia was significantly greater than in the central, and especially in the northern provinces. Table 16. Number of registered diphtheria patients per 10,000 population in individual republics of the USSR. Republics 1924 g. 1925 g. 1926 g. 1927 g. RSFSR . . . Ukraine . . . Belorussia . Azerbaijan Armenia . . . Georgia . . . Turkmenistan Uzbekistan . 4.6 5.0 10.4 3.1 0.4 1.8 4.6 7.0 9.3 3.4 0.4 1.8 1.1 0.8 4.7 8.1 6.8 2.0 0.6 2.6 0.4 1.2 4.8 8.5 7.1 2.6 0.5 3.8 0.8 1.5 Table 17. Number of registered diphtheria patients per 10,000 population in individual regions of the RSFSR. Regions North-Eastern . . North-Western . . . Western ..... Central-Industrial . Central-Chernozem Middle-Volga . . Lower Volga . Vyatka-Vetluga Ural .... Bashkir Republic . . Crimea....... North Caucasus .... Dagestan...... Siberia ...... Kazakhstan..... Kyrgyz Republic . Yakut Republic . . Buryat-Mongol Rep. . Far East . 1924 g. 1925 g. 1926 g. 1927 g. 1.1 0.9 0.9 3.9 3.6 3.3 3.5 7.2 6.1 6.1 6.9 5.6 5.0 6.5 5.6 4.6 6.4 5.9 6.8 5.0 4.2 4.9 6.2 5.5 5.6 6.3 1.9 2.1 2.2 2.3 3.5 4.5 3.2 3.4 3.7 5.4 2.5 2.4 5.6 6.5 7.1 9.2 4.1 6.0 6.6 5.0 0.4 0.4 0.9 0.8 3.4 4.1 4.3 4.0 1.6 1.2 1.5 2.3 .- 1.2 1.3 0.7 - 1.4 1.1 0.6 4.6 6.5 4.6 5.4 7.2 5.2 5.0 a clear idea of this is given by Table 18 (for 1903–1910 according to S. A. Novoselsky). N. I. Tezyakov, based on data on diphtheria morbidity for 25 years (from 1886 to
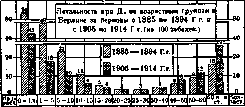
Figure 9. 1910) proposed dividing all provinces of European Russia into 6 groups. The first 2 groups with the highest incidence (from 40 to 54 per 10,000 population) included the former Ekaterinoslav, Kherson, Kharkov, Saratov, and Voronezh provinces. The 6th group with the lowest incidence rates (less than 0.9 per 10,000 population) included all northern, northwestern, and northeastern provinces. Such a distribution can no longer be made: among the individual republics of the USSR, the incidence rates in Ukraine (before the war—the highest) and Belarus (the lowest) are almost identical. Among the individual provinces of the RSFSR, the lowest incidence rates continue to be observed in the northern provinces: Vologda, North Dvina, Novgorod, Zyrian Autonomous Oblast, and the Karelian Republic, as well as in some national republics: Dagestan, Kyrgyz, and Yakut. The difference in incidence between other oblasts is small (cf. Figs. 13 and 14). Incidence by age and sex is illustrated in Table 19. The largest number of cases is observed in children under 10 years of age. At ages up to 5 years, the incidence among males is slightly higher than among females; at older ages, females show a higher incidence (Fig. 15). 4. Spread of diphtheria in cities and rural areas. Data on the spread of diphtheria in cities and Table 18. Number of registered patients per 10,000 inhabitants. Provinces Vologda Moscow Kherson 1903 1904 1905 1906 1907 1908 1909 1910 1926 1927 0.2 0.1 0.1 0.9 1.7 1.6 3.2 2.7 0.7 0.8 21.2 22.7 26.3 31.2 21.7 18.3 26.9 48.2 6.6 8.3 56.9 57.4 71.7 156.9 124.7 87.4 139.0 207.4 8.3 7.8 Table 19. Incidence of diphtheria by age and sex in Moscow and Moscow Governorate (per 10,000 population of each group). Age 0-12 months 1-4 years 5-9 years 10-14 years 15-19 years 20-29 years 30-39 years 40-49 years 50-59 years 60 years and older Moscow Gov. Moscow (1906-1910) (1926) M. 39.3 F. 30.8 35.0 30.0 115.9 40.4 36.3 60.7 64.7 20.4 22.9 33.5 41.2 6.7 11.4 10.0 22.4 2.0 5.8 9.5 1.2 2.8 3.9 6.0 1.2 2.3 1.7 3.5 1.1 1.1 0.5 1.9 0.2 0.5 0.6 0.8 - rural areas are different in different countries. In England, for the period from 1905 to 1909, the mortality from diphtheria at age under 5 years was 99.6 in cities and 61.7 in rural areas per 100,000 population; in older age groups, it was lower in cities than in rural areas: from 5 to 9 years—47.8 and 56.4, from 10 to 14 years—6.7 and 12.3, from 15 to 19 years—1.2 and 3.2, etc. (the first figure shows mortality in cities, the second in rural areas). In Russia, Serbia, and Austria, mortality from diphtheria was significantly higher in rural areas than in cities, as can be seen from the following figures (Table 20): Table 20. Mortality from diphtheria per 100,000 population in cities and rural areas. Table 21. Number of registered patients per 10,000 population. Countries Russia Serbia Austria Years Cities Rural areas 1906-1910 44.6 72.0 1897-1906 34.0 123.0 1909-1910 19.3 27.7 In the USA, diphtheria mortality is higher in cities than in rural areas (Vaughan). As for the incidence of diphtheria, in the RSFSR the number of registered patients in cities is significantly higher than in rural areas (Table 21); this is partly explained probably by better registration in cities. 5. Seasonality of the spread of diphtheria. Figure 16 shows the monthly distribution of diphtheria cases for 1925-27 in Denmark, France, the RSFSR, Ukraine (in absolute figures), and Fig. 17 for Moscow Governorate. Leningrad City Years Cities Rural areas Moscow Gov. Leningrad Gov. 7.4 9.8 3.5 10.0 5.8 2.9 8.9 3.5 9.9 7.7 5.3 4.1 10.0 3.8 9.7 6.6 7.1 2.0 10.6 3.7 14.3 8.3 8.7 3.0 for comparison—the monthly distribution of diphtheria in European Russia and some foreign countries before the world war. In Denmark, the rise of the monthly curve begins in September, the maximum is observed in November, December, or January; the lowest figures are noted in June-August. In France, the rise of the curve begins in October, the peak incidence occurs in December or January, and minimum figures occur in August-September. In the RSFSR and Ukraine, the rise of the monthly curve begins in September, the peak of diseases occurs in October; in some years, a second, less pronounced rise is noted in March.
I. Dobreitser. Pathological Anatomy.
In the pathoanatomical picture of diphtheria, one can distinguish: 1) local phenomena arising in the area of primary fixation of the pathogen, and 2) changes in the entire organism due to the action of the toxin circulating in the blood. As for local phenomena, the most frequent (one might say classic) form of tissue reaction to the introduction of the diphtheria bacillus is fibrinous inflammation in the form of diphtheria or croup. This process usually takes place on the tonsils and the adjacent part of the fauces [see separate plate (pp. 423-424), Fig. 2]; in more severe cases, it can spread on the one hand to the mucous membrane of the pharynx, then the esophagus, and even the stomach, and on the other hand to the floor of the oral cavity, gums, and tongue (the buccal mucosa is almost never affected). Very often, especially in certain epidemics, involvement of the respiratory tract (nasal cavity, larynx, trachea, and even bronchi) is also observed, with the process in the latter three organs rarely arising in isolation, but for the most part in connection with diphtheria of the fauces, pharynx, or nose [see separate plate (pp. 423-424), Fig. 1]. In addition to these usual sites of localization of diphtheria, one occasionally has to observe the same process on various wound surfaces of the skin (in children most often on excoriations of the upper lip formed due to corrosion of the skin by secretion flowing from the nose in diphtheritic rhinitis), on the conjunctiva of the eyes, in the external auditory meatus, and on the genital organs (mainly in girls in the region of the pudendal cleft and in the vagina, occasionally in boys in the preputial sac). In all these cases, infection usually occurs through scratching, wounding, or rubbing in infectious material with infected fingers, which of course happens much more often when there is already a lesion of the fauces or nose (although in individual exceptional cases it can occur
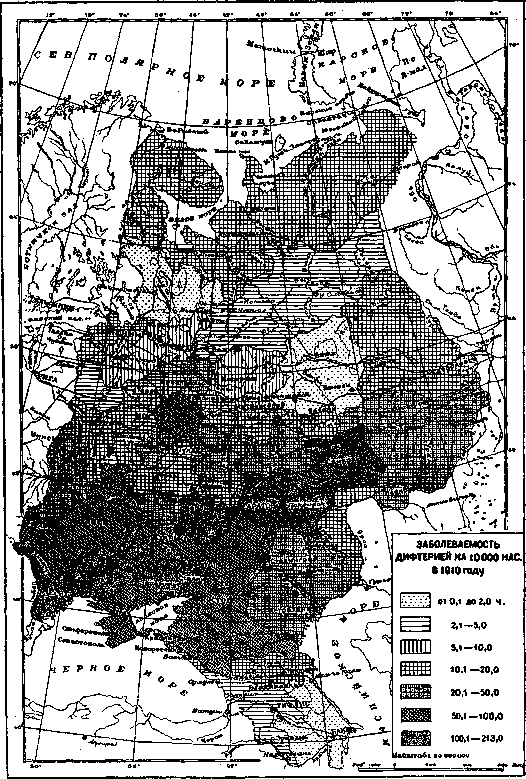
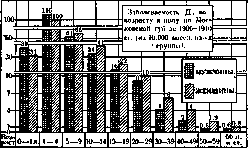
Figure 15.
which characterizes the mildest forms of the disease. Such catarrhs in the fauces and pharynx are relatively rare, but in the nose (especially in small children) they occur more often and, if not recognized in time, can provide a cause for the spread of infection. A characteristic (though optional) feature of diphtheritic rhinitis is the bloody nature of the discharge, which indicates a deeper process than exclusively in faucial diphtheria. Isolated diphtheria of the respiratory tract does not produce hemorrhagic forms, and in general the changes associated with general intoxication (see below) are never significant in it. Corresponding
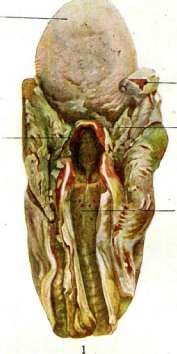
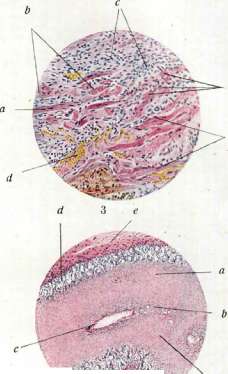
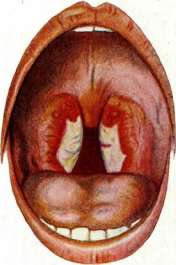
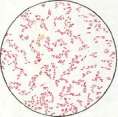

5 cFigure 1. Diphtheria of the larynx, trachea, and bronchi: a — tongue, b — inflamed epiglottis with whitish membranes; c — trachea with false membranes; d — tonsils and pharyngeal walls (d). Figure 2. Diphtheria of the tonsils. (From Pfanndler-Schlossmann). Figure 3. Myocarditis in diphtheria: a — preserved myocardial fibers (cross-striation visible); b — fiber in a state of clumped disintegration; c — cellular infiltrate at the site of destroyed fibers; d — blood vessels. Figure 4. Adrenal gland in diphtheria: a — deep parts of the cortical layer; b — hyperemic medullary substance; c — central vein of the adrenal gland; d — preserved areas of the cortical layer; e — adrenal capsule; f — capsule vessels. (Figs. 1, 2, and 4 from preparations of the Museum of the Pathological-Anatomical Institute of the 1st Moscow State University). Fig. 5. Diphtheria bacilli: a — stained with Löffler's methylene blue; b — double stained by Neisser; c — stained with ink (after Kolle-Wassermann). Fig. 6. Diphtheritic bacilli (Stab-Stäbchen). (After Hiss-Zinsser). To art. Dysentery, Diphtheria. Accordingly, death from lesions of the respiratory tract occurs either from asphyxia—predominantly in cases of extensive spread of fibrinous inflammation along the bronchial tree to its small ramifications (the so-called "descending croup")—or, chiefly (in children in more than 70% of all fatal cases), from pneumonia as a complication. The latter usually has the character of catarrhal bronchopneumonia and is classified as a complication on the grounds that in its etiology diphtheria bacilli apparently play only a secondary role and may not play any role at all; its origin is most frequently due to secondary infection. Local phenomena in diphtheria must also include lesions of the regional lymph glands and collateral inflammatory-toxic edema of the soft tissues adjacent 170 150 130 120 110 100 90 t /- **. i :eur. Russia 906-1910 gg. ROMANIA g/ ch ITALY 1=07-1910gg. y \ / / 1 / / \ \ 11 /1 / \ \ g -g*' > -Uy) v> *"Qi, N/' sh on the anterior chest wall — reaching in exceptional cases down to the scrobiculum cordis. The characteristic relief of the neck thereby completely disappears, and the head appears as if passing directly into the trunk. As regards the changes caused by general diphtheria intoxication of the organism, among them the most profound and constant are the changes in the adrenal glands, the peripheral nervous system, and the cardiovascular system. The lesion of the adrenal glands is particularly prominent in experimental animals (guinea pigs) that died from poisoning by diphtheria toxin. In them, these organs are greatly enlarged and have a dark red color, which microscopically corresponds to extremely marked hyperemia and numerous hemorrhages both in the cortical and medullary sub- 140 130 120 110 100 \ 1908-10 gg. tW'5-10gg. ^ .' "** i l y 1905-09GG \v' l. \ \ / / \ / (.I _ \J / / / ---., ^, / \ 1 \ / 1 / 'V ig Figure 17. Monthly distribution of diphtheria cases for 1905-1910 (average daily numbers). to the site of primary localization. The former is expressed by an increase in the size of the glands (in severe cases very significant), which is based initially on strong hyperemia, inflammatory edema, and often hemorrhages, and subsequently on the proliferation of cellular (mainly reticulo-endothelial) elements. Furthermore, in highly toxic forms of diphtheria in the regional glands (as well as in the tonsils in diphtheria of the throat), a greater or lesser number of whitish or yellowish necrotic foci is always found on cross-section, which together with hemorrhages sometimes permeate the gland (resp. tonsil) to such an extent that almost no normal lymphoid tissue remains in it. Regarding the collateral edema of the adjacent tissues, it must be noted that its development runs completely parallel to the degree of intoxication, thanks to which it is often used in practice to determine the severity of the disease. In severe diphtheria of the throat, it appears extremely distinctly, on the one hand, on the soft palate and faucial pillars, often leading here, thanks to the simultaneous enlargement of the tonsils, almost to the complete closure of the isthmus faucium, and on the other hand, in the intermuscular and subcutaneous tissue of the neck, whence it sometimes extends downwards beyond the line of the clavicles
stance, as well as into the capsule. The chromaffin reaction is either completely absent or significantly weakened. If death does not occur very rapidly (on the 2nd–3rd day or later), extensive destructive changes in the parenchyma (necroses) join this. In humans, during natural disease, the lesion, although not so striking, retains the same character. In cases of death from diphtheria intoxication, significant hyperemia, hemorrhages, and weakening or even disappearance of the chromaffin reaction, clearly indicating a decrease (resp. cessation) in adrenaline production, are always established in the adrenal glands. The cells of the medullary layer turn out to be strongly vacuolated in this process. In the cortical layer, a decrease in lipid content and also vacuolation of the cells are noted, often reaching the point of necrosis (see separate table, fig. 4). In the nervous system, the main changes in diphtheria are concentrated 1) in the peripheral nerves and 2) in the sympathetic and autonomic ganglia. In the former, the picture of changes is very well defined by the term "multiple toxic parenchymatous neuritis" and is composed, on the one hand, of phenomena of edema, circulatory disorders, and slight focal infiltration of the nerve sheaths, and, on the main hand, of phenomena of dissolution and disintegration of myelin. The latter kind of process can reach a very high intensity, and then many nerve fibers are completely denuded of their myelin sheaths. Axial cylinders suffer less, but still a certain part of them (both in myelinated and unmyelinated fibers) perishes with successive phenomena of swelling, deformation, fragmentation, and disintegration. At the same time, at the sites of destruction of myelin and axial cylinders, proliferation of the nuclei of the Schwann sheath is almost always noted. Despite the fact that diphtheria pareses and paralyses usually appear rather late (mostly around the third week of the disease), all the aforementioned nerve changes can be observed in individuals who died from diphtheria intoxication already starting from the 3rd–4th day of the disease, with them being most pronounced in those nerves that are located closest to the site of the primary lesion (in diphtheria of the throat — glossopharyngeal and vagus nerves, to a lesser extent — phrenic nerves). This latter proposition is also justified with respect to the sympathetic and autonomic ganglia, of which the two upper sympathetic cervical ganglia and the nodose ganglion of the vagus nerve usually suffer the most. Here, aside from vascular and infiltrative phenomena, which mostly are not significant, one can find degenerative fatty change, vacuolation, and deformation of ganglion cells, displacement, paleness, or, conversely, pyknosis of their nucleus, destruction of the nucleolus, reduction or disappearance of Nissl substance—in a word, all gradations of gradual karyo- and cytolysis. On the part of the amphicytic sheath, these changes are accompanied either by the proliferation of satellites or, conversely, by degenerative processes in them, often leading to their destruction and to the partial or complete exposure of the nerve cells. The frequency of disorders on the part of the cardiovascular apparatus in diphtheria can be largely explained by the lesion of the adrenal and nervous systems. Indeed, the decrease in adrenaline production and the changes in the sympathetic ganglia and nerves cause a profound paresis of the vessels and a drop in blood pressure, which creates enormous difficulties for the work of the heart. On the other hand, the majority of fibers of both cardiac plexuses originate from the vagus nerves and from the cervical portion of the sympathetic trunks, i.e., from the elements of the nervous system most affected in diphtheria of the throat, and of course damage to these fibers in connection with damage to the autonomic ganglia of the heart itself must extremely severely disrupt its innervation. It is quite understandable that under these conditions the heart becomes the site of least resistance of the organism, upon which the influence of the toxin is manifested with the greatest force and constancy. Changes in the heart muscle in diphtheria intoxication can be of both a purely degenerative and an inflammatory character. The former are more common in cases of early death (during the 1st week) and consist of parenchymatous and fatty degeneration of muscle fibers, their vacuolation, and so-called clumped disintegration (a subspecies of Zenker's degeneration, see separate table, fig. 3). Inflammatory phenomena usually develop from the 7th–12th day of the disease and present a picture of either predominantly parenchymatous or interstitial myocarditis. In the latter case, degenerative changes recede into the background, while hyperemia, hemorrhages, edema, and focal or diffuse accumulations of various cellular elements in the intermuscular tissue (mainly histiocytes and lymphoid cells, to a lesser extent neutrophils, eosinophils, and plasma cells) predominate.
As regards the topography of the process, the walls of the left ventricle suffer most severely in the majority of cases, especially in the layers closest to the endocardium, as well as the papillary muscles. The atrioventricular bundle almost always takes part in all the enumerated changes, although, on the other hand, damage to it is rarely very deep. As in severe myocardial degeneration, and especially in a sharply pronounced inflammatory process, the heart macroscopically acquires a very characteristic appearance. It dilates strongly and becomes so flabby that it frequently loses its normal contours. Its apex becomes smoothed out, and the entire organ assumes the shape of a sack with strongly dilated cavities and a rounded bottom. Voluminous fibrinous clots are usually found in the cavities, and if it is an inflammatory process, then on a cross-section of the muscle made parallel to the surface, dark red stripes and spots of various sizes clearly stand out against a muddy grayish or yellowish background. As for the blood vessels, as was stated, a paretic state of theirs is characteristic of diphtheritic intoxication, as evidenced at autopsy by the external appearance of all organs with their venous and capillary network overfilled with blood and frequently found hemorrhages. Speaking of the state of the cardiovascular system, one cannot fail to mention also the thrombotic processes that frequently arise in diphtheria. The latter are very much favored, on the one hand, by the toxic action of the diphtheria poison on the inner lining and the slowing of the blood flow due to weakening of cardiac activity and vascular paresis, and on the other hand, by the blood coagulability increased under the influence of the diphtheria toxin. The favorite site for thrombi formation here, aside from the venous system (veins of the pia mater, mesentery, vena azygos, hemiazygos, etc.), is the intertrabecular spaces near the apex of the left ventricle of the heart and the region of the left cardiac auricle. The presence of thrombi naturally frequently gives rise to embolisms and the development of infarcts. Of the remaining organs, the spleen, lymph glands, liver, and kidneys deserve mention. The spleen reacts weakly in diphtheria. In pure cases uncompli-cated by secondary infection, its enlargement is insignificant and occurs mainly due to plethora and hyperplasia of the follicular apparatus. At the same time, in the center of the follicles, one can almost always see more or less significant accumulations of large reticulo-endothelial cells, frequently with phenomena of karyorrhexis in them. The same changes are frequently found also in the follicular apparatus of other parts of the organism (follicles and Peyer's patches of the intestines, lymph glands of the mediastinum and abdominal cavity). In the liver in toxic diphtheria, aside from plethora and significant degenerative changes, miliary foci of necrosis are sometimes encountered. The kidney changes characteristic of diphtheria belong to the category of nephroses and boil down to degenerative processes in the epithelium of the cortical layer and the appearance of various types of casts in the tubules. However, in severe cases from the 4th-5th day of the disease, one can frequently observe also a true inflammatory process with corresponding changes in the interstitial tissue or glomeruli. In conclusion, it must be noted that death in diphtheria can occur not only in the acute period of the disease, but also at later periods, 1-2, or even 3 months after the onset of the disease, amidst apparent health. This is the so-called death from late diphtheritic paralysis. It is associated with deep damage to the vagus or other respiratory nerves and can occur at any moment during the time that the destructive (and partly reparative) period of neuritis lasts. Since the vagus nerves suffer more and more often in diphtheria than other respiratory nerves, and since the lesion of the vagus nerves is usually aggravated by myocardial damage, death from late paralysis in the vast majority of cases is cardiac death. At autopsy, upon inspection of the organs with the naked eye in such corpses, as a rule, no changes are found, and only microscopic examination reveals in the nerve trunks (especially in the vagus nerves) the picture of parenchymatous neuritis that was described above, while in the myocardium it shows mostly the consequences of elapsed acute myocarditis in the form of diffuse sclerosis of the heart muscle.
Skvortsov. Clinic. The diphtheria bacillus can penetrate the human body through the mucous membrane of various organs and through the skin. Depending on the localization of the process, a distinction is made between diphtheria of the fauces, nose, larynx, and respiratory tract in general, the eye, ear, genital organs, and skin. The most frequent of these is diphtheria of the fauces. It is this, chiefly, that is meant when speaking of diphtheria. Diphtheria of the fauces. Classification. The clinical forms and course of diphtheria of the fauces are extremely diverse. If one takes as the basis of classification, on the one hand, the size and extent of the pseudomembranes (local disposition to the diphtheria poison) and, on the other hand, the degree of general intoxication (general disposition), all the diversity of clinical forms of diphtheria can be reduced to the following four or even three main types.-I. L o c a l i z e d diphtheria. The diphtheritic process is limited to the cavity of the fauces: the membranes generally do not extend beyond the tonsils, uvula, and pillars. Symptoms of general intoxication are absent or moderately expressed. In its course, this form is the most favorable, responding well to the action of serum.-II. Widespread diphtheria. In this form, the membranes are not limited to the cavity of the fauces: they pass to the nasopharynx and nasal cavity, and may also extend into the oral cavity, but more often, especially in small children, they descend downwards onto the larynx and trachea (croup). General intoxication often runs parallel with the spread of the local process, but by no means always (in croup, for example, despite the extensive spread of the films, general intoxication is sometimes not strongly expressed).-III. T o x i c diphtheria (d. toxica), another generally accepted name: "severe diphtheria" (d. gravis). The membranes are either limited to the cavity of the fauces or more often extend to the nasopharynx, soft and hard palate. Clinically, this form is characterized not by the appearance and extent of the membranes, but by edema of both the soft tissues of the fauces and the cervical cellular tissue. This edema is analogous to the edema observed in the guinea pig at the site of subcutaneous injection of diphtheria toxin. It appears already in the first days of the disease and is the earliest sign indicating the onset of general intoxication. In this form, one can always observe the consequences of general intoxication expressed to a greater or lesser degree (nephrosis, paralyses, cardiovascular disorders, lesion of the vegetative-endocrine apparatus). Some call this form, at the suggestion of Rauchfuss, phlegmonous diphtheria, and French authors—pseudophlegmonous (Aviragnet). Rauchfuss himself subsequently recognized this name as unsuccessful. Indeed, phlegmons and a successive abscess do not occur here, and the edema of the fauces depends on diphtherotoxic changes in the blood vessels. Another, more common, although also incorrect name is septic diphtheria. It gives a false idea of the pathogenesis of toxic diphtheria. Sepsis, i.e., general infection with microbes, is usually absent in toxic diphtheria. The French school, since the time of Roux, held the view that severe diphtheria results from simultaneous infection with the diphtheria bacillus and streptococcus—the streptodiphtheria of Sevestre and Martin (Sevestre, Martin). However, in its symptoms, the so-called streptodiphtheria essentially does not differ from that which is called toxic diphtheria (edema of the cellular tissue, hemorrhages, paralyses). The studies of other authors have shown that streptococcus cannot be found in the blood and organs. Thus, the pathogenesis of severe diphtheria reduces to intoxication by the poison of the diphtheria bacilli alone. Recently, French authors (Aviragnet) have also been leaning towards this view. It is true that in a certain part of the cases of diphtheria, the streptococcus plays a very important role in the pathological process, but exclusively as a microbe of secondary infection. In these cases, it causes the same phenomena that are generally characteristic of streptococcal infection: suppuration of the cervical glands, purulent otitis, pleurisy, etc.; streptococcus can always be isolated from the pus. Such cases are more correctly called diphtheria complicated by streptococcal sepsis; the course of the disease is not always severe. Toxic diphtheria responds poorly to the action of serum and requires very large doses. Most recently (1928), some German authors, in view of the frequency of finding hemolytic streptococcus in toxic diphtheria, are again beginning to ascribe a major role to it in the genesis of this form and recommend combined treatment with anti-diphtheria and anti-streptococcus sera.-As a variety of severe diphtheria, one can also distinguish m a l i g n a n t diphtheria (d. maligna s. gravissima). The clinical picture and pathogenesis may be different. In some cases, malignant diphtheria proceeds as a fulminant or hypertoxic form, when the child dies within 1-3 days amidst phenomena of violently developing intoxication. In other cases, the disease proceeds more slowly, with phenomena of hemorrhagic diathesis (hemorrhages under the skin, from the mucous membranes, into internal organs) standing out noticeably in the general picture of severe intoxication. Finally, in the third category of cases, gangrenous disintegration develops in the fauces, when a mixed infection with various microbes joins the diphtheria bacillus, leading to gangrenous tissue disintegration. Common to all three categories is the malignancy of the course and the almost complete ineffectiveness of the serum. Localized diphtheria. Typical form. The incubation period, as with other forms of diphtheria, is from 3 to 10 days. The disease begins either acutely, suddenly, or gradually, with inconspicuous symptoms. In the first case, the temperature immediately rises to 38°-39°, headache, general weakness, and malaise appear. In the second category of cases, the patient is noticed to have poor appetite and a slight rise in temperature (37.5-38°) for several days. Often even older children do not complain of a sore throat, or it is insignificant. On objective examination, some acceleration of the pulse is found; the cervical glands are usually enlarged on one side and painful on pressure. The tongue is coated, the tonsils (both or usually one of them) are swollen and reddened. On the reddened tonsil, a coating can be seen which in the first hours of the disease resembles a slight burn of the mucosa or a dense spiderweb network; it is even possible to remove it with a cotton tampon, but a new film, which can no longer be removed, appears extremely quickly in this place. By the end of the first or the beginning of the second day, the coating acquires the properties characteristic of a diphtheritic film: its color is grayish or yellowish, it is quite thick, protrudes above the surface of the mucosa, and cannot be removed without bleeding. If serum has been injected, there is sometimes no substantial change in the patient's condition during the first day, and the membranes may even increase. But after 24 hours, a sharp improvement occurs: the temperature drops sometimes to normal, the patient becomes cheerful and merry, appetite appears, the cervical glands decrease, the membranes change their appearance—they become looser, as it were rising above the mucosa, a belt of sharply expressed redness appears along the edges, and the spread of the membranes stops. Over the course of the following days, a significant part of the membranes comes off, and in 2-3 days the fauces are completely cleansed. Consequences of intoxication (paralyses, cardiac weakness) usually do not occur if the serum was not injected late. Without serum treatment, in the majority of cases the disease progresses, the membranes occupy both tonsils and may pass to the uvula and the posterior wall of the pharynx; the cervical glands are enlarged and painful, but there is no cellular edema. There are traces of protein in the urine. There is leukocytosis of varying degree in the blood. A remittent or irregular type of temperature persists for 7-12 days. The membranes come off slowly, leaving no ulcerations or mucosal defects behind. The disease ends by the 7th to 15th day. Sometimes isolated neuropathies (paresis of the soft palate) and mildly expressed cardiac disorders are observed. There may be various deviations from such a typical course. Rudimentary forms. The local process in the fauces may be expressed very weakly in the form of punctate orinsular membranes—punctate diphtheria, or in the form of mere hyperemia of the tonsils, while the fibrinous exudate is completely absent—catarrhal diphtheria. The temperature is subfebrile or normal, and the general condition is good. Such forms have to be observed in adults and older children during an epidemic in a family or household. Diagnosis can be established on the basis of the simultaneous existence of typical cases in the family, and chiefly with the aid of bacteriological examination (so-called bacteriological diphtheria).-In the serious form, the process shows a tendency to spread to the uvula, soft palate, nasopharynx, and posterior wall of the pharynx. The voice takes on a nasal shade, there is a sweetish-acid odor from the mouth, and salivation. The cervical glands are greatly enlarged, but there is no cellular edema. The face is pale, appetite is absent, and the temperature is 38-39°. The serum rather quickly cuts short the process, although repeated injections are required. Such cases are transitional to the widespread and toxic forms.-Protracted form. Sometimes the local process in the fauces drags on for 2-4 weeks and longer. In these cases, the membranes, having disappeared from the tonsils, reappear in the same place or in other areas of the fauces and persist for weeks without yielding to serum treatment.
The temperature is slightly elevated or even normal, the glands are almost not enlarged, and the general condition is good. Such a prolonged course is occasionally observed both in primary diphtheria and especially in secondary diphtheria, when it develops after measles. Apparently, these cases involve a weakening of local resistance in the fauces with a well-expressed general immunity. Localized diphtheria ranks first in frequency—50-60% of all cases of diphtheria. Mortality is low: 1-2 percent. Disseminated diphtheria. Diphtheria of the fauces + diphtheria of the nose. The spread of the process from the tonsils to the nasal cavity is observed no earlier than the 3rd-5th day of the disease and is accompanied by a new rise in temperature and a deterioration of the general condition; special symptoms appear, indicating involvement of the nasopharynx and nasal cavity. The voice acquires a nasal tone, the mouth is open, the tongue is dry and covered with crusts, and a mucous and then blood-tinged discharge appears from the nose, which excoriates the skin near the nostrils and on the lips. On the neck, not only the submandibular lymph nodes swell, but also those located near the sternocleidomastoid muscle. If the process has gone far and seized the anterior parts of the nose, the membranes can be seen with the naked eye after clearing the entrance of the nose from purulent discharge and crusts. The spread of diphtheria to the nose worsens the prognosis, since it is accompanied by an intensification of general intoxication phenomena. Diphtheria of the fauces + diphtheria of the mouth. When the process spreads to the oral cavity, grayish, tightly adhering membranes appear on the palate, the mucous membrane of the lips and cheeks, and also on the tongue. Clinical symptoms: profuse salivation, bad breath, painful chewing and swallowing, severe swelling of the submandibular lymph glands. The membranes shed slowly, leaving long-healing ulcers. Diphtheria of the fauces + diphtheria of the larynx. From the fauces, the process can spread to the larynx, directly extending along the walls of the pharynx or, bypassing the latter, can localize directly in the larynx. Diphtheritic involvement of the larynx and respiratory tract is known as croup. Under "croup" in the clinical sense of the word, it is customary to understand any acute inflammatory disease of the upper respiratory tract proceeding with certain characteristic symptoms (coarse cough, stenotic breathing). True and false croup are distinguished. True croup, or simply croup, is called diphtheritic involvement of the larynx and trachea; in it, in the overwhelming majority of cases, the presence of fibrinous exudate is observed on the mucous membrane. False croup differs from true croup etiologically: it is caused not by diphtheria, but by influenza, measles, and other infections; fibrinous exudate is usually absent in it, and only inflammatory hyperemia and edema are found. Croup (true, diphtheritic) can be secondary if it develops following involvement of the fauces or nose, and primary if the process is localized primarily in the larynx. But in a large number of cases of so-called primary croup, the initial involvement of the nose and nasopharynx remains unrecognized; thus, compared to secondary croup, primary croup is not encountered as frequently. According to symptoms, course, and outcome, both of these forms of croup do not present a substantial difference. Diphtheria of the larynx (croup). The course of croup can be divided into three stages (Rauchfuss). 1st stage—croupous cough. The first sign indicating a beginning involvement of the larynx is a sharp, loud cough, which very soon becomes coarse and barking, and at the same time the voice becomes hoarse, unclean, and then voiceless (aphonia). This period lasts 1-2-3 days and passes into the 2nd stage—the stage of stenosis. Breathing becomes difficult, unclean, and a sawing or whistling sound is heard with every inspiration. Another sign of narrowing of the larynx is the retraction of the yielding places of the chest (supraclavicular and jugular fossae, intercostal spaces, epigastric region). At first, the child copes satisfactorily with the lack of air and remains calm. Then oxygen starvation begins—the child tosses about in bed, jumps up, grasps the bed with its hands, asks to be taken into its mother's arms, throws its head back; the accessory respiratory muscles (sternocleidomastoid, scalene muscles) noticeably tense. If the disease is left to its natural course, in rare cases when the membrane detaches, improvement ensues; in the vast majority of cases, however, the disease passes into the final stage—the stage of asphyxia. The child becomes calmer, drowsier, and lies apathetically in bed. Breathing becomes more frequent, but superficial, and retractions are not as noticeable. The lips, tip of the nose, and nails turn blue, the face is pale, and sweat often appears on the forehead. The extremities grow cold, the pulse is very frequent, thready, sometimes paradoxical. At times, attacks of acute suffocation appear, and sometimes death occurs during such an attack; in other cases, the child perishes after a more or less prolonged agony. Under the influence of serum, the described course of croup can change sharply—the disease can stop at any stage. The causes of stenosis are diverse: edema and fibrinous exudate mechanically hindering the access of air, spasm of the laryngeal muscles, etc. There are cases when the fibrinous exudate descends from the larynx into the trachea and bronchi. These cases are known as descending croup. The patient's condition is extremely severe; neither serum nor intubation or tracheostomy eliminates the stenotic phenomena. Descending croup is observed in young children up to 2 years of age and carries an extremely poor prognosis. Ascending croup is also distinguished, when the process begins in the bronchi and trachea and rises upward to the larynx. But the existence of this form is subject to doubt. Frequency of croup—about 30% of all cases of diphtheria. Mortality 15-30%. Death occurs either as a result of suffocation or, which happens more often, from complicating pneumonia. Toxic diphtheria (d. toxica). This form sometimes develops from localized diphtheria when the process spreads to the nasopharynx and oral cavity, but more often it arises as such from the very beginning. In the latter case, the disease begins suddenly, more stormily than localized diphtheria. The temperature immediately rises to 39-40°, there is headache, repeated vomiting, and pain upon swallowing. The pulse is frequent (140-160), the face is pale, there is general weakness, and sometimes agitation. The submandibular glands are enlarged, painful, and a loose, doughy edema of the cellular tissue is present under the angle of the jaw; sometimes edema appears only on the second day. The mouth is open, with a strong, cloying sweetish odor. The voice has a constricted, nasal tint. Upon examination of the mouth, the tongue is dry and coated, the fauces are dark red and edematous; on one (usually) tonsil, there is a dirty-gray coating that is not removed by a cotton swab. This coating extremely rapidly, within a few hours, occupies the entire tonsil, spreads to the uvula, and sometimes to the soft palate. On the second or third day, the disease reaches full development, and establishing the diagnosis of severe diphtheria is not difficult, even without resorting to bacteriological examination. Despite large doses of serum, the disease continues to progress during the first few days after the injection. However, 2-3 days after the injection, the spread of the process stops, the temperature drops, and the edema of the fauces and cervical cellular tissue decreases. The fauces, although slowly, are cleared, while ulcers with dirty-gray bottoms remain in place of the coatings, which heal very slowly. In the recovery period, the consequences of intoxication are always observed: paralysis, cardiac weakness, from which patients sometimes die in the 3rd-4th week or even later. Without serum, the process progresses unstoppably: the coatings sometimes occupy the entire hard palate up to the teeth, extend to the posterior wall of the pharynx and the larynx, and the cellular tissue edema occupies the entire neck and descends onto the chest. Already due to the severe swelling of the fauces, breathing becomes difficult (pharyngeal stenosis). Despite the spread of the process, the temperature very often drops on the 4th-5th day of the disease, and subsequently the severe clinical picture of the disease continues to develop at a subfebrile or even normal temperature. Recovery is an extremely rare exception; paralysis and decline of cardiac activity usually kill the patient at the end of the 2nd or 3rd week. Toxic diphtheria is most commonly contracted by older children and adults; up to 2 years of age it is observed very rarely, but mortality in young children is very high (80% according to Aegis). According to the Children's Clinic of the 1st Moscow State University during 1901-08, toxic diphtheria constituted 2-8% of all diphtheria cases. In the epidemic of 1908-12, its frequency increased to 17%. Mortality was 34%. In children's hospitals of the city of Moscow during the same epidemic, mortality reached 50%. Malignant diphtheria (d. maligna). The characteristic features of toxic diphtheria (edema of the fauces and cervical cellular tissue) are always observed in this form. But in hypertoxic diphtheria, the local process may appear relatively moderate compared to the extremely rapidly developing general intoxication. Death occurs within 3 days from cardiac failure. This form needs detailed study both in relation to the virulence of the bacillus and in relation to the constitutional characteristics of the organism. In hemorrhagic diphtheria, the phenomena of hemorrhagic diathesis are added to the usual picture of toxic diphtheria.
Its first signs are ecchymoses at the site of serum injection and the hemorrhagic character of the deposits; these signs are sometimes detected from the first days of the disease, but more often in a later period. The pathogenesis is reduced to a deep toxin-induced lesion of the vessels and the hematopoietic apparatus. The number of blood platelets is reduced, clot retraction is insufficient, as a result of which this form is regarded as secondary thrombocytopenic purpura (Benjamin). Gangrenous D. is frequently joined to hemorrhagic; hemorrhages into the tonsil apparently create favorable conditions for the gangrenous breakdown of tissues under the influence of putrefactive bacteria. The frequency of malignant D. is 1-2%. The prognosis is, with rare exceptions, absolutely poor. - Other localizations of diphtheria. D. of the nose is one of the most frequent localizations of D. after the fauces and larynx. Primary D. of the nose is especially frequent in newborns and infants; in view of the underdevelopment of the tonsils, it is encountered in them more often than diphtheria of the fauces (according to Morozov, diphtheria of the fauces in children in the 1st year of life is 9.3%, diphtheria of the nose is 41.8%). Symptoms: sniffling, discharge at first serous and then serosanguineous, usually from one half of the nose; the child refuses to take the breast; attacks of suffocation during suckling and during sleep. Temperature 38-39°; paleness, general restlessness. Under the influence of serum, rapid improvement. Without serum, an unexpected transition, bypassing the fauces, to the larynx is frequent. In children in the 1st year of life, diphtheria bacilli are sometimes found in the nasal cavity without causing clinical manifestations of the disease. In older children, the disease runs a sluggish course: nasal obstruction and serosanguineous discharge from one half of the nose can drag on for 1-2-3 weeks, without causing phenomena of general intoxication. - D. of the eye is encountered rarely, usually as a secondary disease in D. of the fauces and nose. A superficial or croupous form and a deep or diphtheritic form are distinguished. Besides the conjunctiva, the process in the majority of cases also affects the cornea, as a result of which vision suffers to a greater or lesser extent. D. of the external genitalia: a very rare localization, especially in boys, arises most often as a secondary disease, but sometimes in girls it proceeds in the form of a subacute catarrhal form and is recognized only upon bacteriological examination of the discharge of the vaginal mucosa. Sometimes extensive deposits develop with edema of the cellular tissue, which spread to the skin; a fatal outcome has been observed with phenomena of general intoxication. - D. of the skin and wounds. D. of damaged and undamaged skin is distinguished; the latter is encountered exceptionally rarely, and its existence is contested by some (Adler). During the war and famine years, the frequency of D. of the skin sharply increased, according to Lande, up to 20%. The clinical picture is diverse; besides typical cases with films on the skin surface, cases proceeding under the guise of pustules, impetigo, ecthyma, and also under the guise of phlegmons and whitlows have been described. Likewise in D. of wounds, films are sometimes absent, only the poor appearance and protracted course of the wound attract attention; in the discharge are diphtheria bacilli (Lande). Complications of D. - Kidneys. The usual form is nephrosis; glomerulonephritis is encountered rarely, apparently upon combination with a streptococcal infection. The time of appearance is the acute (anginal) stage of the disease. Insignificant albuminuria is sometimes observed even in localized D. In severe D., albuminuria is a constant symptom; the amount of protein reaches 2-8%, with an abundant sediment consisting of epithelium, leukocytes, casts, and salts. Blood is scarce. Blood pressure is not elevated. The functional capacity of the kidneys is altered insignificantly. Uremia is observed rarely, and edema as well. The course is generally favorable. - Nervous system (paralyses). The pathogenesis is reduced to the toxin-induced lesion of the motor neuron (toxic parenchymatous polyneuritis), and the grey matter of the spinal cord is also successively involved in the process (polyneuromyelitis). Diphtheritic poison acts both via the blood and apparently directly on the nerve ramifications in the region of the focus of infection. Diphtheritic paralyses have all the properties of peripheral paralyses (see Polyneuritis): they are flaccid, with muscle atrophy, with the disappearance of tendon reflexes. Time of appearance: the 3rd-4th week of the disease; in especially severe cases they appear early, before the disappearance of the deposits. The more severe the D. and the later serum treatment is initiated, the earlier paralyses appear and the more severe is their course. In the pre-serum period they were encountered very frequently (20%), at the present time they also do not represent a great rarity (8% according to Jochmann). In D. of the fauces, paralyses develop with a typical sequence. First of all, paralysis of the soft palate appears (nasal tinge to the voice, liquid food pours out through the nose). Upon examination of the fauces, the soft palate hangs down and remains motionless during phonation. These phenomena persist for 2-3 weeks and disappear without a trace. Next in order of appearance is paralysis of accommodation (m. ciliaris). Older children complain that they poorly distinguish objects at a close distance, cannot read. Sometimes strabismus (n. abducens) and ptosis (n. oculomot.) are also observed. If paralyses show a tendency to spread, pareses of the extremities appear (ataxia, disappearance of knee reflexes). In severe cases, paralyses of the muscles of the neck and trunk join in. The condition of the patient becomes extremely dangerous when paralysis of the larynx, respiratory muscles, and diaphragm joins in. The patient may perish from suffocation or from pneumonia. - Cerebral paralyses are incomparably rarer, exclusively in very severe D. in the period of cardiac disorders. Genesis: embolism of one of the branches of the art. fossae Sylvii. Apical thrombi of the heart serve as the source of embolism. The onset is sudden - a picture of stroke with sequential hemiplegia. Recovery is observed rarely. Circulatory organs. Diphtheritic paralysis of the heart is the most important complication both in frequency and in view of its life-threatening character. The intensity of the lesion is extremely diverse: from an insignificant pulse change (slowing, arrhythmia) to a sharply expressed decline of cardiac activity, from which the patient perishes within 1-3 days. It is observed even in localized D. with delayed serum injection, but as a constant phenomenon - in toxic D. One should distinguish circulatory disorders in the early period - on the 2nd-6th day of the disease, the so-called early paralysis of the heart, and disorders arising after the disappearance of the films, on the 2nd-4th week, sometimes even later - late paralysis of the heart. Early paralysis is observed in very severe D., especially in the hypertoxic form. On the 3rd-4th day, sometimes already on the 2nd, simultaneously with the rapid spread of the process in the fauces, symptoms of a decline of cardiac activity sharply stand out in the clinical picture: the skin is pale, cold, the pulse is very frequent, easily compressible, soon becomes thready, blood pressure is very low; the heart is dilated, tones are muffled, sometimes a systolic murmur, gallop rhythm or embryocardia. The liver is enlarged, vomiting, abdominal pains. Sometimes upon an attempt to sit up or change position the patient as it were suddenly perishes, in other cases death ensues after a short-lived agony. Late paralysis is observed much more frequently. In severe D. at the end of the 2nd or the beginning of the 3rd week, when the deposits in the fauces have cleared, no improvement ensues in the general condition of the patient: there is no appetite, the face is pale, the patient is apathetic. Urine is scant, it contains much protein and casts. Paresis of the soft palate. The pulse is mostly slowed, dropping sometimes to 60-40 per minute, the dimensions of the heart increase, tones are muffled, splitting of tones, blood pressure is low, the liver is enlarged. In cases not too severe, such a condition holds for some time (1-2 weeks), and the patient recovers. In more serious cases, three ominous symptoms appear one after another: the first symptom is nausea, which passes into persistent vomiting. The second symptom, the origin of which remains unclarified, is abdominal pain. The appearance of a circulatory disorder joining the described picture - gallop rhythm or embryocardia - should be considered especially dangerous. Having reached such a condition, the patient as a rule perishes. In very rare cases, despite repeated attacks of collapse, recovery ensues. Much less frequently one has to observe on the 3rd-5th week a suddenly ensuing paralysis of the heart in patients who before this did not display noticeable signs of a disorder of cardiac activity. - Pathogenesis. The origin of heart paralysis in diphtheria is not yet fully clarified. Diphtheritic toxin is an intense poison for the circulatory apparatus in its entirety, but individual parts of the apparatus are affected apparently in a definite sequence. The adrenals are affected earliest of all, in particular the chromaffin or adrenal substance (Molchanov, Abramov), and also the sympathetic system (Abrikosov, Mogilnitsky). Changes in the vagus nerve and heart muscle are discovered considerably later. Along with diffuse myocarditis, more or less deep changes were sometimes found in the atrioventricular system - in the bundle of His and Tawara; in such cases, complete transverse dissociation and ventricular automatism are observed during life.
However, the condition of the bundle of His and Tawara in the majority of cases corresponds to the condition of the rest of the myocardium, and one cannot view the cause of heart paralysis as an isolated lesion of this bundle. Thus, early heart paralysis is caused primarily by damage to the adrenal glands and the sympathetic system; in late paralysis, the predominant role apparently belongs to changes in the heart muscle and the vagus nerve. Other complications. Pneumonia is quite frequently encountered in croup, as well as in severe diphtheria, accelerating a fatal outcome. Its genesis: in very rare cases, the direct action of the diphtheria bacillus itself, but usually diplococci and streptococci. Purulent complications (lymphadenitis, otitis, pleurisy, etc.) do not present anything characteristic and depend on streptococci. Combination of diphtheria with other acute infectious diseases. Measles creates an increased predisposition to diphtheria; the course is severe (in Moscow from 1923-1927, 194 cases of this kind out of 520 other diphtheria autopsies were subjected to autopsy in city hospitals); transition to the larynx is very frequent, while differential diagnosis from measles croup presents great difficulties. Recognition is also not easy when combined with scarlet fever (165 cases of lethal combinations of "scarlet fever-diphtheria" out of 2,303 other scarlet fever autopsies were autopsied in Moscow in 1923-1927). Recognition in many cases (particularly in rudimentary forms) is possible only with the help of bacteriological examination. But culture examination takes 24 hours; moreover, in undeniable cases of diphtheria upon the first examination, the result is sometimes negative. Meanwhile, the injection of serum must be performed as soon as possible; in toxic diphtheria, delaying it for 12-24 hours means risking the patient's life: the physician must remember that responsibility for correct recognition and timely treatment rests with him, and not with the laboratory. Therefore, he must be able to make a diagnosis based on the clinical picture. The following signs are characteristic of pharyngeal diphtheria: 1) thick films of a greyish-dirty color, rising above the level of the mucosa and sitting tightly on it, 2) the tendency of the films to spread beyond the limits of the tonsils, 3) major swelling of the cervical glands, especially with edema of the cervical cellular tissue, 4) simultaneous lesion of the nose or larynx. When lesion of the pharynx presents with such a clinical picture, it would be a mistake to wait for the result of the bacteriological examination. In differential diagnosis, one must keep in mind the following diseases: lacunar tonsillitis, follicular, ulcerative (or Vincent's angina, in the smear—Vincent's bacilli), phlegmonous or tonsillar abscess (inability to open the mouth due to spasm of the masticatory muscles), pseudodiphtheria (Hoffmann's bacilli), streptococcal and scarlet fever (see) without rash (diffuse redness of the entire pharynx and soft palate), gangrenous stomatitis, syphilis, and also thrush. In the recognition of croup, one should keep in mind first of all false croup. The latter is characterized by a sudden onset (usually at night), rapid (within several hours) development of stenosis and equally rapid improvement with a tendency to recurrence of attacks; discrepancy in the development of individual symptoms (e.g., absence of aphonia with sharply expressed stenosis). In primary croup, diphtheria bacilli in the mucus from the pharynx are often absent. In doubtful cases, serum injection is mandatory. Less frequently, reasons for errors are retro-pharyngeal abscess, aphthous laryngitis, tumors of the larynx, trachea, or those located adjacent to them—papilloma, tuberculosis of tracheobronchial glands, etc. In primary nasal diphtheria in newborns and infants of the first months, one should remember congenital syphilis (other manifestations of this disease). Prognosis. Overall mortality in the pre-serum period in Russia was 30% and higher; after the introduction of serum—14% (Rauchfuss). The prognosis depends primarily on the form of diphtheria (see above), then on age: the prognosis is worse the younger the child. Mortality in infancy is especially great: in croup—40% (Colley), in toxic diphtheria—80% (Eghiz). Furthermore, the prognosis depends on the preceding disease and the general condition of the patient (especially poor is the prognosis when diphtheria develops following measles). Finally, the prognosis is worse the later serum treatment is begun. According to the decree of the Academic Medical Council of the People's Commissariat of Health, children and adults servicing children's institutions who have been in contact with a patient are considered non-contagious in the absence of acute catarrhal processes in their pharynx and nose after a single bacteriological examination; if examination is impossible—one week after isolation of the patient. If the patient remains at home, then these persons are not admitted to institutions and are considered contagious until the final recovery of the patient. The patient himself is considered non-contagious after a two-fold negative examination of the pharyngeal and nasal discharge, performed with a two-day interval after the disappearance of the clinical phenomena of diphtheria, but not earlier than 2 weeks from the beginning of the disease; without bacteriological examination—2 weeks after the complete disappearance of the clinical symptoms of diphtheria. Treatment. Non-specific treatment, both general (care, nutrition) and local (disinfection of the oral cavity, pharynx, nose, etc.), retains its significance even with serum. A diphtheria patient remains in bed as long as the coatings in the pharynx and elevated temperature persist; as soon as the pharynx is cleared and the temperature becomes normal, the patient may get up if there are no complications. At the slightest hint of cardiac dysfunction or starting paralysis, he must be put back to bed. Food in the acute period is liquid and semi-liquid (milk, soups, purée, porridges, fruit juices, etc.). With extensive coatings and major pharyngeal swelling, swallowing even liquid food often causes severe pain, as a result of which patients completely refuse drink and food; in such cases, it is useful to give patients drink through a bent glass straw, thanks to which swallowing becomes less painful. After the disappearance of the coatings, solid food (including meat) is permitted, regardless of the presence of protein in the urine. During recovery, especially from severe diphtheria, sufficient and varied food is of great importance; such patients are recommended to be given food in a concentrated form: cream, meat powder, etc. With a complete absence of appetite and stubborn vomiting, one has to resort to nutrient enemas. Local treatment in the vast majority of cases reduces exclusively to gargling the throat with weak solutions of hydrogen peroxide (1-2 tablespoons per glass of water) or boric acid (2%). With widespread coatings and abundant discharge of thick mucus, spraying with lime water (1 part Aq. Calcis + 2 parts water) or a 2 percent soda solution is prescribed. Pyocyanase, yatren, ichthyol do not present special advantages. Local agents should be used in the form of gargles or sprays. Pharyngeal paintings in the acute period, in view of the trauma inflicted, are inexpedient and even harmful. For nasal lesions—1% yellow mercurial ointment. Specific treatment—antitoxic serum—was proposed in 1894 almost simultaneously by Behring in Germany and Roux in France. Serum is obtained from horses into which small, gradually increasing doses of toxin are injected over several months. Before releasing serum from the institute for therapeutic use, it is subjected to control or testing for antitoxin content (each vial indicates how many units of antitoxin it contains). It is conventionally accepted to consider an antitoxin unit (AE) as the smallest amount of serum that is able to neutralize 100 units of toxin. For treatment, sera are used that contain in 1 cm3 not less than 200, usually 300, 500 AE and even more. According to the generally accepted view, the therapeutic potency of serum depends exclusively on the amount of antitoxin contained in it; its concentration has no significance, although Kraus, Schwoner, and Barykin attach importance to the concentration of serum as well; in their opinion, a 500-fold serum acts weaker than a 300-fold one, since in sera of weak and medium concentration, the affinity (Aviditat) of antitoxin for toxin is more sharply expressed. The essence of the serum's action reduces to the fact that it quickly and easily neutralizes the toxin located in the focus of infection at the moment of its formation (in statu nascendi), as well as the toxin freely circulating in the blood for a short time; but it cannot or can to a limited extent displace the toxin from its combination with the body's cells (nerve, heart muscle, adrenal glands). This is possible if little time has passed since the moment of the toxin's combination with the cells, and the dose of antitoxin is sufficiently large. But often by the time of serum injection, almost all the toxin has already been bound by the cells; thus, serum has a limit to its action: it cannot save those patients in whom a large amount of toxin, exceeding the lethal dose, has been bound by the body's cells even before the start of treatment.
In order to make broader use of the action of the serum and obtain the best therapeutic result, it is necessary when injecting it to be guided by the rules developed by experiments on animals and clinical observations. The success of serum treatment depends on 1) the time of injection, 2) the dose of the serum, and 3) the method of injection. The first and most important condition is the earliest possible injection. According to Kossel, the mortality from diphtheria, if the serum is injected on the 1st day of the disease, is 0, on the 2nd day 3%, on the 3rd 13%, on the 4th 23%, on the 5th 40%, on the 6th 50%. Approximately the same figures were obtained in the Children's Clinic of the 1st Moscow State University (Molchanov). These figures show that the mortality from diphtheria is higher the later serum treatment is begun. Therefore, when dealing with a diphtheria patient, one must not hesitate to inject the serum; this applies especially to toxic cases, in which delaying the serum injection by a few hours can prove fatal for the patient. A precisely developed dosage does not exist. The dosage adhered to by the majority of clinicians has been established empirically, based on clinical experience. Modern doses are significantly larger than those used in the first years of serum treatment, but still smaller than those recommended, for example, by American authors (100,000 units). In prescribing one or another amount of serum in each individual case, one should be guided mainly by 1) partly the form of the disease, 2) the time of injection, and 3) the age of the patient. For the localized form, 4,000-5,000 units are injected; repeating the injection is for the most part unnecessary. With a clearly expressed tendency of the deposits to spread, but without edema of the neck tissue, 6,000-7,000 units are administered, and after a day the same dose is necessarily repeated or, in case of improvement, half of it. In the sharply disseminated form, in croup, especially in toxic diphtheria, 8,000-10,000 units are injected at once, and after 12-24 hours the same dose is repeated. Subsequently, the injection should be continued, but in smaller doses, until the diphtheritic process visibly begins to subside. Usually, 30,000-100,000 units are spent on the treatment of a toxic case (Molchanov). English, American, and German physicians inject 80,000 units and more at once for toxic diphtheria. As for the timing of the injection, in general it can be said that the later treatment begins, the relatively more antitoxin must be introduced. Age is given comparatively less importance regarding dosage. However, children under 1 year old are injected with a quarter of the dose, and from 1 year to 2 years with half the dose adopted for older children. The generally accepted methods of injection are subcutaneous, intramuscular, and intravenous. The subcutaneous method is currently abandoned by almost all, since absorption occurs very slowly with it. Antitoxin is absorbed much faster with intramuscular injection. According to Morgenroth, the concentration of antitoxin in the blood with intramuscular injection is 10-20 times greater than with subcutaneous injection. One can inject into the muscles of the thigh or into the buttocks. For severe cases, the ideal method is intravenous, but it also has drawbacks: the antitoxin is excreted from the body very quickly with it; therefore, having made the first injection into a vein, subsequent injections must be made into the muscle. It is not always easy to find the elbow vein in small children. To avoid anaphylaxis, intravenous injection should not be given to patients who have previously been injected with serum. In general, with any method of injection, for those patients whose anamnesis indicates a previously made injection of any serum whatsoever, it is recommended to apply the Bezredka method (first introduce under the skin or, better, into the muscle 1-2 cm3 of serum, and after 2-3 hours the full therapeutic dose). With timely and sufficient administration of serum in most cases, already after 12-24 hours a break is discovered first of all in the general condition of the patient (improvement in well-being, disappearance of weakness, drop in temperature, etc.), and then also on the part of the local process: the spread of deposits stops, the films swell and peel off more or less quickly (depending on the severity of the case). That the action of anti-diphtheria serum is specific and depends on the antitoxin content in it can now be considered firmly established. In 1918, Bingel tried to prove that the action of anti-diphtheria serum depends on the content of non-specific substances inherent in any foreign serum. However, Bingel's data were refuted by Feer, Birk, and others. Treatment of complications. Nephrosis does not require special treatment. Since uremia and edema are rarely observed, there is no need, especially with a poor appetite, to forbid meat and salt. In paralyses, adequate nutrition of the patient is of enormous importance, but it is not easy to carry out. With paralysis of the soft palate, food must be semi-liquid (porridges, purees, etc.); in severe forms of paralysis, the patient must be fed through a tube or rectally. Massage and electricity in small children with general weakness should be used with great caution (in view of the excitement of the child caused by these procedures). Of pharmaceutical preparations, strychnine internally or subcutaneously. Large doses of serum (30,000 units) recommended for widespread paralyses (Comby, Heubner) did not show a noticeable effect on the course of paralyses in Molchanov's cases. With heart weakness, expressed more or less noticeably, strict rest is in the foreground. Such patients must not only not get up, but also not sit in bed. Of medicinal remedies, caffeine, camphor, digalen, adrenaline [adrenaline dosage: 0.25 - 0.5 - 1.0 Sol. Adrenalini (1:1,000) + 20.0 physiological solution, subcutaneously 1-3 times a day under the control of blood pressure examination]. Treatment of croup. Immediate injection of a large dose of serum: 8,000-10,000 units intramuscularly or intravenously; this dose is repeated before the expiration of the day. Subsequently, half doses are injected until noticeable improvement. Air moistened with steam relieves cough and promotes the discharge of mucus and films. This is most simply achieved with the help of a steam atomizer; most pediatricians have recently abandoned special steam rooms. Schlossmann makes extensive use of fresh cold air, but the applicability of this method in our climate has not yet been verified. Internally, mainly sedatives (bromine, codeine, adalin), and German pediatricians recommend Narcophin. Chloral hydrate and morphine should be avoided. With this method of treatment, about half of the patients (40-55%) recover without surgical intervention. Surgery is necessary when the stenosis has reached a high degree of development and the child is visibly struggling with suffocation (anxiety, sharp and constant retractions of the yielding areas of the chest cage, beginning cyanosis of the lips and skin). This moment corresponds to the boundary between the 2nd and 3rd stages of croup. Surgery should not be delayed until the onset of complete asphyxia (the "expectant" method of Schlossmann), since the child's strength in the fight against stenosis is depleted, cardiac activity weakens, and pneumonia very often develops. Of the two operations—tracheotomy and intubation—intubation is used almost exclusively in childhood (see).
V. Molchanov. Prophylaxis. General sanitary measures are of great importance in the fight against diphtheria; these include early recognition of the disease, isolation, disinfection, and specific treatment (the latter acting as an abortive course for the disease), which explain the reduction in mortality from diphtheria noted in all countries since the discovery of the causative agent of diphtheria and especially the introduction of serotherapy into practice (1894). Mortality, which prior to 1894 was 50 per 100,000 population, dropped gradually to 10 and even somewhat lower (see statistics above); however, further reduction in mortality from diphtheria ceased, and mortality remained at the same level for a long time despite the widespread use of serotherapy. This serves as proof that general sanitary measures in the fight against diphtheria are of only limited importance: the main source of infection is not only patients, but also those who have recovered from diphtheria and healthy bacilli carriers, while the isolation of bacilli carriers is, for obvious reasons, completely unrealizable. Serotherapy yields limited results due to the delayed administration of therapeutic serum, which, moreover, sometimes in particularly severe and rapidly progressing cases, proves impotent even with its early administration. Therefore, the idea of specific prophylaxis of diphtheria has attracted general attention since the discovery of the causative agent. Immunization. Passive immunization. To obtain immunity, it is sufficient to introduce 1,000-1,500 antitoxic units of anti-diphtheria serum. In this case, the organism receives protective bodies "passively" with the serum of an animal previously hyperimmunized with the corresponding antigen (in this case, diphtheria toxin). Therefore, passive immunity sets in a short time after the introduction of the serum, most likely when introduced into the blood (into a vein), later into the muscles, and even later into the subcutaneous tissue. Thus, in the latter case, antitoxins appear in the blood 15-30 minutes after injection, reaching their maximum concentration only after 2-3 days. The main drawback of passive immunity is its short duration: it lasts only 3-4 weeks, because the antitoxin bound to the foreign serum protein decomposes together with the latter and is excreted from the organism. If the antitoxin is introduced with the serum of an animal of the same species (for example, a guinea pig is injected with the serum of an immunized guinea pig, or human-to-human), passive immunity lasts much longer. Repeated introduction of anti-diphtheria serum to prolong immunity does not achieve the goal, because foreign protein upon repeated introduction decomposes much faster and the antitoxin disappears from the blood within 5-7 days. In addition, the first parenteral introduction of foreign protein sensitizes the organism to its repeated introduction, as a result of which one must fear anaphylactic shock. Therefore, the widespread use of anti-diphtheria serum for prophylactic purposes is contraindicated, and passive immunization is used only when there is reason to fear that the child has already been infected and is in the incubation period of the disease. But after the injection of anti-diphtheria serum, it is recommended to immediately begin active immunization. Active immunization. Since immunity in diphtheria has an antitoxic character, diphtheria toxin should be taken as the material for vaccinations in active immunization; however, due to the extreme sensitivity of humans to diphtheria toxin, introducing it into the human body is very dangerous. The first attempts at immunization with toxin were made by Dzerzhgovsky (Leningrad), who applied toxin to the nasal mucosa using cotton swabs. Widespread immunization with toxin could only be achieved from the time when methods were found for introducing detoxified diphtheria toxin into the human body. This goal is achieved predominantly by two methods: either by adding antitoxic anti-diphtheria serum to the toxin (Behring) or by exposing the toxin to formalin (4‰) at t° 40-42° (Ramon). Behring (1913) was the first to carry out active immunization against diphtheria, using as vaccination material a mixture of diphtheria toxin with antitoxin (anti-diphtheria serum) taken in strictly defined proportions so that only a small part of the toxin remained unneutralized by the antitoxin. The war of 1914-18 interrupted Behring's work, which was continued by Park, Zingher, and their coworkers in the USA. The composition of Behring's mixture is unknown. Park proposed his mixture and his immunization method, specifically: initially his mixture contained approximately 3Lt + 3.5 AE in 1 cm3; the mixture was more precisely titrated on guinea pigs in such a way that out of 5 guinea pigs receiving 5 cm3 of the mixture each, 2 died with more acute phenomena, and three survived for 15-35 days (even if with phenomena of paralysis); this mixture was injected subcutaneously into humans at 1 cm3 three times at weekly intervals (regardless of age). Since this mixture produced a significant reaction, starting from 1924 it was replaced by another containing only 0.1Lt in 1 cm3, but being more toxic, so that guinea pigs died from 5 cm3 of the mixture in 5-6 days, and from 1 cm3 in 18-25 days. Park's mixture, besides America, finds application in Ukraine. In Moscow and in some other regions of the RSFSR, Korshun's neutral mixture is used; its preparation is based on the so-called L0 mixture of Ehrlich (1 AE of serum + L0 dose of toxin should not cause the slightest infiltrate at the site of subcutaneous injection in a guinea pig). If the L0 mixture consists of 0.25 cm3 of toxin + 0.002 cm3 of anti-diphtheria serum, then both of these doses are increased by any number of times, and thus the so-called neutral mixture is prepared. Example: (0.25 cm3 of toxin + 0.002 cm3 of serum) x 1,000 = 250 cm3 of toxin + 2 cm3 of serum. The required amount of serum is added with a pipette to the measured amount of toxin with constant agitation. The mixture is left for a day at room temperature, and if it was correctly prepared, a significant loose precipitate falls out (Ramon flocculation). The precipitate is not filtered off, but is thoroughly distributed by gentle shaking in the liquid before its use. 5 cm3 of the mixture, when injected into a guinea pig, causes a significant infiltrate at the injection site, which resolves within 4-5 days. The guinea pigs survive, but sometimes die after 25-30 days with phenomena of paralysis and cachexia. For the first injection, 0.2 cm3 is taken, for the second 0.4 cm3, and for the third 0.6 cm3 (regardless of age). Immunization is performed under the control of the Schick reaction (see). A successful result of immunization is judged by the transition of a positive reaction into a negative one. The third method of immunization, which is finding increasingly wide application, is the subcutaneous injection of anatoxin (toxoid) in amounts of 0.5 cm3 for the first time and 1.0 cm3 for the two subsequent ones. The second injection is given in a week, and the third in 2 weeks. The results obtained with the use of either mixture or anatoxin are equally favorable. Namely, a positive Schick reaction turns negative in 92-97%, and morbidity and mortality are significantly reduced. The duration of immunity after the use of mixtures exceeds 6 years in 90% of cases (the extreme observation period). It should be assumed that once obtained, immunity remains lifelong in those individuals who are generally capable of developing immunity. Contraindications for active immunization are the presence of nephritis, cardiac compensation disorder, and acute infections. Very rarely, anaphylactic phenomena are observed in those vaccinated, apparently due to idiosyncrasy to certain types of peptone used for the preparation of the toxin. Sometimes very severe symptoms (vomiting, cooling of the extremities, weakening of cardiac activity, clouded consciousness, erythematous rash) quickly disappear upon injection of adrenaline solution (1:1,000)—1 cm3 for adults and 0.5 cm3 for children under 5 years old. Simultaneous injection of camphor is useful. The neutral mixture of toxin with antitoxin is characterized by stability, not changing even during prolonged storage under appropriate conditions (in a dark and cool place). S. Korshun.
Related articles
Mentioned in
Cite this page
“Diphtheritis.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/diphtheritis/