Urachus
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Great Medical Encyclopedia discusses the anatomy, embryological development, and pathological conditions of the urachus, including congenital urinary fistulas and cysts.
Encyclopedia entry (1928–1936)
URANOPLASTY, see Cleft palate. URACHUS (from the Greek uron - urine and cheo - I pour), the fetal urinary duct running from the apex of the urinary bladder to the umbilicus (Fig. 1) and representing a derivative of the upper segment of the intraembryonic part of the allantois (see) (Fig. 2). By the time of birth, the urachus becomes obliterated and turns into a connective tissue cord with an admixture of longitudinally running smooth muscle fibers (continuation of the m. detrusor) (see Human muscles), called in anatomy the ligamentum
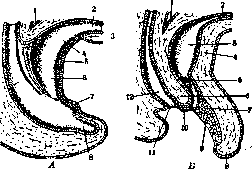
Figure 2. Development of the rectum and urinary bladder (diagrams from Corning). A: 1 - peritonaeum; 2 - urachus; 3 - mesoderm of the anterior abdominal wall; 4 - urinary bladder; 5 - membrana cloacae; 6 - sinus urogenitalis; 7 - site of future rupture of the anal membrane; 8 - tail-like intestine; 9 - rectum. B: 1 - peritonaeum; 2 - urachus; 3 - urinary bladder; 4 - anterior abdominal wall; 5 - site of opening of the Wolffian duct into the sinus urogenitalis; 6 - septum uro-rectale; 7 - orifice of the sinus urogenitalis; 8 - genital tubercle; 9 - epithelial plate on the lower surface of the genital tubercle; 10 - perineum; 11 - anus; 12 - rectum. This cord causes the presence on the inner surface of the anterior abdominal wall of a fold of the parietal peritoneum - plica vesico-umbilicalis medialis, s. media. The connective tissue fibers of the medial umbilical ligament in the region of the umbilicus intertwine with those of the lateral umbilical ligaments. In certain cases, non-closure of the urinary duct is observed even in the postnatal period, preserving either a canal or a narrow fistulous tract between the urinary bladder and the umbilicus - urachus persistens. The urinary duct in such cases is lined with an epithelial cover similar to the internal lining of the urinary bladder (so-called transitional epithelium). Above this layer lie a layer of connective tissue and smooth muscle fibers. As it approaches the umbilicus, the epithelium is at first represented by two layers, and higher up by one. The degree of non-closure of the urachus can vary: complete non-closure (throughout its entire length), obliteration of the segment closest to the urinary bladder or closest to the umbilicus, or both, or finally the preservation of the lumen only in certain sections of the duct. Within the thickness of the medial umbilical ligament, the urinary duct passes either in the central part of the ligament or eccentrically; it has either a rectilinear direction or forms separate outpocketings, dilations. At the transition of the mucous membrane of the urinary bladder into the mucosa of the urachus, a fold is observed that prevents the entry of urine into the urinary duct. Non-closure of the urinary duct leads to the appearance of a number of pathological formations, such as a fistula, cyst, etc. The most frequent manifestation of urachus non-closure as a developmental defect is the presence of a congenital umbilical (urinary) fistula (fistula umbilicalis congenitalis). The latter is more frequently observed in males. The lumen of the fistulous opening can be various (e.g., in Stukkey's case it was 3 mm). The presence of a urinary umbilical fistula leads to urine being excreted to a greater or lesser degree through the umbilicus. Simultaneous sharp disturbances in the development of the urinary bladder or urethra create conditions for the excretion of urine only through the fistula. Aside from fistulas, in rarer cases cysts are observed along the course of the urinary tract, one or several, ranging in size from microscopically small to the size of a bean and larger (Fig. 3). In Walther's case, the cyst was 2.5 cm in length and 1.6 cm in width. The origin of the cyst is explained by the partial obliteration of sections of the tract leaving a closed cavity between them, sometimes communicating with the urinary bladder and filling with urine. Cases of calculi of the urinary duct or its cyst have also been observed. In individual cases (dating back to the developmental period), a connection is established between the biliary tract and the urinary duct, so that there are even observations of the excretion of gallstones through the urachus. (See also Umbilicus, Meckel's diverticulum.)
Related articles
Mentioned in
Cite this page
“Urachus.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/urachoplasty/