Mucous Bursa
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
An overview of the anatomy, formation, location, and traumatic injuries of mucous bursae (bursae mucosae) from the 1928-1936 Soviet Great Medical Encyclopedia.
Encyclopedia article (1928–1936)
MUCOUS BURSA, bursa mucosa, s. serosa (from Greek bursa - hide; in the Middle Ages this term came to designate a pouch or bag). Systematic study of mucous bursae begins in 1784 (Camper). Mucous bursae appear wherever skin, fascia, muscles, and tendons are subjected to continuous pressure in a certain direction over bones, causing them to shift; therefore Langenbeck (Langermok) proposed the name "gliding bursae" (Gleitbeutel) for them. From this, it is clear that the number of mucous bursae is inconstant, that in the newborn, with the exception of a few so-called congenital mucous bursae, they are absent, and later appear in various places depending on the characteristics of a particular profession, constitution, pathological state, etc., for example, on the sternum in shoemakers, under the skin of the cranial vault in head-load carriers, over the protruding spinous process in kyphosis, at the head of the first metatarsal bone in hallux valgus. It is generally assumed that the friction of skin, tendons, and muscles against deeper-lying bony prominences, ligaments, and tendons of other muscles is the factor that causes the formation of mucous bursae; during muscle work, connective tissue fibers located between, for example, skin and tendon, are subjected to tension, loosen, and, gradually thinning, completely disappear, resulting in a cleft which is the cavity of the mucous bursa, but bursae can also develop where friction is absent. Thus, the cause of bursa formation may be the periodically occurring separation of contacting surfaces. An example can be the bursa Achillis, where at the moment of foot extension the tendon moves away from the calcaneus, and the connective tissue located between the tendon and bone loosens, leading to the formation of a cavity. The cavity, initially irregular in shape, in places penetrated by attenuated connective tissue fibers, then gradually forms into a true small sac, the walls of which are very similar to the synovial membrane of joints. The inner surface of the sac is smooth, sometimes uneven, lined, like any other connective tissue cavity, with single-layer squamous epithelium and contains a small amount of fluid of the nature of articular synovia. Presenting in a natural state as a collapsed sac compressed by the tendon and bone or skin, the mucous bursa is fused by its outer surface with the tissue of the organs among which it is located and passes imperceptibly into the surrounding connective tissue; therefore, during dissection, mucous bursae are found with great difficulty and are noticed only when the wall is opened and air enters the cavity; in some cases, due to the condensation of connective tissue fibers, the bursa acquires considerable resistance, and then it is possible to clearly establish the boundaries of the bursa cavity. In anatomy, to study the shape and position of mucous bursae, injection of colored masses into the cavity of the bursa is used, for example, wax, gelatin, lard. Connective tissue bundles in some cases take the form of plates that divide the cavity into several chambers, separated from each other or communicating with one another; these are the so-called multilocular bursae (bursae mucosae multiloculares) in contrast to simple, unilocular ones (bursae mucosae simplices). The same bursa can be both multilocular and unilocular, for example, bursa trochanterica m. glutaei maximi. An example of a multilocular bursa can serve bursa subdeltoidea. The size and shape of mucous bursae exhibit significant variability. Their shape, elliptical or rounded, is determined by the nature of those formations between which they arise. Their size ranges from fractions of a centimeter to several centimeters. Mucous bursae located near joints often communicate with their cavity. Such relationships are characteristic of adults, whereas in the fetus they have a different character. Thus, for example, b. suprapatellaris in the fetus is always separated from the joint cavity, and in adults this occurs only in 1/5-1/6 of all cases (Fick). Protrusions of the synovial capsule of joints should be distinguished from mucous bursae. While the former enter into connection with the joint under the influence of muscle activity, the latter are a direct continuation of the synovial sacs of joints and are formed as follows: upon muscle contraction, the tendon, closely fused with the joint capsule, carries it along during its movement and forms a protrusion (for example, the tendon of m. biceps in the shoulder joint). The factor determining the appearance of joints and bursae is muscle movement; if one takes into account the similarity in anatomical structure of the walls, it turns out to be possible to consider mucous bursae as a special (very simple) type of joint connection (Tonkov). For example, the joint connecting the os triquetrum with the os pisiforme—articulatio ossis pisiformis—originated from a simple mucous bursa. These circumstances are of great importance in understanding the pathological processes occurring in mucous bursae and allowing in some cases to draw a parallel with analogous joint diseases. Located in the places of tendons, mucous bursa,
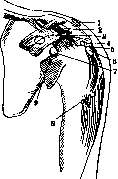
Figure 1. 1-bursa subcutanea acrom.; 2-b. lig. coraco-clavicularis; 3-b. coraco-brachialis; 4-b. subacromialis; 5-b. supraspinata; 6-b. subdeltoidea; 7-b. subcoracoidea; 8-b. pectinei majoris (Merkel); 9-b. subscapularis.
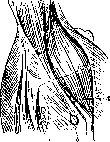
of greatest friction facilitate movements and release part of the muscular energy for useful work; friction occurs not directly between contacting surfaces, but between the walls of the bursa lubricated with synovial fluid. The synovial fluid of mucous bursae, according to modern views, is not a product of the secretory activity of the wall endothelium, but represents tissue decay, mucous degeneration of wall cells with formation of a finely dispersed, homogeneous mass of alkaline reaction, slightly yellowish in color, viscous, containing mucin. Location of mucous bursae: according to R. Redi, mucous bursae, located near joints, can be constant and inconstant. In the shoulder joint, the following constant mucous bursae are distinguished: 1) b. acromialis, 2) b. subacromialis, 3) b. subdeltoidea, 4) b. subcoracoidea, 5) b. subscapularis, 6) b. coraco-brachialis, 7) b. intertubercularis and 11 inconstant bursae (Fig. 1).—In the elbow joint—constant mucous bursae: 1) b. bicipito-radialis, 2) b. subcutanea olecrani and 14 inconstant
5 i
Figure 4.
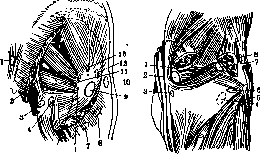
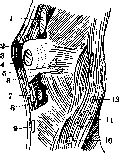
Figure 5. Figure 4. 1-bursa subcutanea sacralis; 2-b. obturatoria inf.; 3-b. tuberis ischii; 4-b. flexorum; 5-b. tendinea m. obturatoris ext.; 6-b. tendinea m. obturatoris int.; 7-b. glutaeo-femoralis; 8-b. trochanterica glutaei max.; 9-b. trochanterica superf.; 10-b. subcutanea troch.; 11-b. m. piriformis; 12-b. glutaei medii ant.; 13-b. glutaei min. Figure 5. 1-bursa gastrocnemia med.; 2-b. semimembranosa; 3-b. semimembranosa propria; 4-b. poplitaei (Merkel); 5-b. bicipitalis inf.; 6-b. poplitaea post.; 7-b. gastrocnemia lat.; 8-b. bicipito-gastrocnemia. mucous bursae (Figs. 2 and 3).—The hand has no constant mucous bursae; of the inconstant ones, two are observed.—In the gluteal region, constant bursae: 1) b. trochanterica superficialis, 2) b. m. bicipitis femoris super., 3) b. trochanterica profunda, 4) b. ischiadica profunda, 5) b. trochanterica m. glutaei medii anter., 6) b. trochanterica m. glutaei minimi, 7) b. glutaei medii post., 8) b. m. obturatoris int. and 5 inconstant mucous bursae (Figs. 4 and 5). In the region of the hip joint, constant mucous bursae: 1) b. ilio-pectinea, in 10% of cases communicates with the joint cavity, 2) b. iliaca subtendinea, 3) b. m. recti.—In the region of the knee joint and popliteal fossa, the following constant bursae: 1) b. praepatellaris subfascialis, 2) b. subcutanea tuberos. tibiae, 3) b. infrapatellaris profunda, Figure 6. 1-bursa supra- 4) b. suprapatellaris (co- patellaris subfasc.; 5-b. patella- municates with the joint), ris lat.; 6-b. lig. colla- 5) b. gastrocnemia media- teralis tibiae; 7-b. in- lis, 6) b. m. semimembra- frapatellaris profunda; nosi, 7) b. m. semimembranosi propria, 8) b. m. poplitaei, 9) b. anserina, b. bicipitis femoris inf. and 14 inconstant mucous bursae (Fig. 6).—In the region
of the foot, constant mucous bursae: 1) b. tendinis calcanei Achillis, 2) on the plantar surface—b. subcutanea digitorum, 3) b. infratendinea m. tibialis post. There are up to 20 inconstant mucous bursae (Figs. 7 and 8). Traumatic injuries of mucous bursae. Open wounds of superficial mucous bursae usually escape the patient's attention and
8-b. infrapatellaris subcut.; 9-b. subcutanea tuberosit. tibiae; 10-b. bicipitalis inf.; 11-b.

physician, since they present no symptoms distinguishing this injury from frequently occurring wounds of the subcutaneous tissue. Wounding of deep bursae is usually overlooked because it recedes into the background before the easily detectable damage to other important structures (blood vessels, nerves, etc.). The danger of wounding mucous bursae is especially great because, in the presence of a direct connection with a joint or via lymphatic vessels, infection easily penetrates into the latter. The treatment of wounds of mucous bursae must be conducted according to the general principle of treating wounds, but in doubtful cases, when there is no certainty that the walls of the bursa are not infected, it is better to limit oneself to excision of the wound edges, without resorting to suturing. If the inflammatory process drags on, accompanied by the formation of cords, scars, and thickenings of the wall of the mucous bursa, then these secondary changes, after the complete cessation of inflammatory phenomena, can give an unpleasant complication in the form of limitation of movements of joints, muscles, and tendons, and then if conservative treatment (heat and gymnastics) is unsuccessful, it is
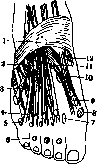
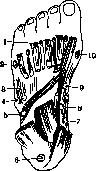
Figure 7.
Figure 8.
Figure 7. 1-bursa tarsi sin.; 2-b. extensoris digitorum comm.; 3-b. subtendinea III peronaei; 4- b. tendinea extensoris subfasc; 5-b. subcut. me-tat.-phal.; 6- b. subcutanea dig.; 7-b. intermeta-tars.-phal.; 8-b. subcutmea metatars.-phal.; 9- b. subtendinea extensoris hallucis long, ant.; 10- b. subtendinea extensoris hallucis long, post.; 11- b. extensoris hallucis brevis; 12-b. subtendinea tibiae ant. Figure 8. l-bursa m. lumbricalis; 2-b. subcutanea; 3-b. flexoris digiti V; 4-b. abductoris digiti V; 5-b. peronaei longi; 6-b. subcutanea subcalcanea; 7-b. tibialis post.; 8-b. subtendinea tibialis post.; 9-b. flexoris hallucis brevis; 10-b. subcutanea. necessary to resort to excision of the altered mucous bursa. Injury to a mucous bursa without disruption of the integrity of the skin (contusio) is determined only when it is accompanied by a serous, serous- bloody effusion or hemorrhage into the cavity of the mucous bursa, which usually resolves independently or, lingering in the bursa, transitions into a chronic form. Treatment consists of rest, the use of pressure bandages, heat; only sometimes, with delayed resolution, is puncture indicated. Inflammation of mucous bursae is divided into acute and chronic. Acute bursitis (bursitis acuta) arises as a result of damage to the wall of the bursa or the penetration of bacteria via lymphatic pathways from neighboring foci. Destruction of the bursa wall by the proteolytic enzyme of an adjoining purulent focus is also possible, or finally, in very rare cases, infection enters the mucous bursa by a hematogenous route. Inflammation of the mucous bursa begins acutely, accompanied by a local rise in temperature, a febrile state with the formation in the cavity of the bursa of a serous, serous- bloody, or serous-fibrinous exudate (Aschoff). Subsequently, the exudate may completely resolve or the process, acquiring a productive character, transitions into a chronic form, or the exudate suppurates (bursitis purulenta). The causative agents of the inflammatory process can be staphylococci, streptococci, pneumococci, gonococci, Escherichia coli (Lexer) and the dysentery bacillus (R. Redi). Pneumococcal bursitis occurs more often in the region of b. subdeltoidaea, b. bicipito-femoralis, b. semimembranosae, b. gastrocnemii, b. praepatellaris, b. ischiadicae; gonococcal—in b. tend. Achillis and in b. iliaca subtendinea. The dysentery bacillus affects the mucous bursae of the lower extremity. The male sex is affected more often than the female, the most affected age being children up to 10 years and adults from 35 to 50 years. The spread and clinical manifestation of acute bursitis depend on the nature of the infection and on the anatomical location of the bursa. Usually all signs of inflammation are present on the face: redness of the skin, fluctuation, swelling, pain, and impairment of the function of the given area of the extremity, but it must be kept in mind that in deep bursitis some symptoms may be absent or weakly expressed, for example, in bursitis iliaca there may be no skin redness. Swelling in these cases is also not detected for a long time due to the large capacity of the bursa and its deep position. With weak virulence of bacteria, an increase in temperature may be absent, but instead a number of symptoms appear, consisting of a forced position of the extremity—for example, in bursitis iliaca the thigh is flexed, abducted outward, and rotated, i.e., it takes a position that minimizes pain sensations; with bursitis subdeltoidea flexio et extensio are possible, while rotation along the longitudinal axis, abduction, and adduction are impossible, which never happens with arthritis. In the knee region, extension is difficult; in the elbow region with bursitis bicipito-radialis, flexion and extension are preserved, but pronation and supination are very painful. If acute bursitis has a tendency to become localized, an abscess forms, lined from the inside by granulation tissue. If the virulence of the bacteria is especially great, then the inflammation can end in necrosis of the bursa with the entry of infection into the surrounding tissues and cellular tissue and the development of phlegmonous inflammation. Sometimes bursitis, left to its own devices, ultimately breaks through to the outside, the consequence of which is non-healing fistulae. In acute bursitis, concomitant phenomena in the form of lymphangitis, lymphadenitis, and erysipelatous inflammation are frequently observed. The danger of purulent bursitis, besides that inherent in general to any purulent focus, lies in the possibility of the spread of infection to the adjacent joint. In this case, bacteria penetrate either via lymphatic vessels or through existing direct anatomical connections of certain mucous bursae (e.g., b. poplitaea, b. semimembranosa) with the cavity of a neighboring joint. Of the bacterial forms encountered, acute gonorrheal inflammation of the mucous bursa deserves attention, which often develops together with arthritis and is usually of a serous, less often purulent, character. Of the mucous bursae, b. calcanea Achillis and b. iliaca subtendinea are affected most of all. The disease usually has a benign character and resolves independently. Swelling in bursitis calcanea is observed on both sides of the Achilles tendon. When walking, pain appears, radiating to the calves—the so-called heel pain, "achillodynia" (also occurs with gout and rheumatism); in this case, the patient, to reduce compression of the bursa, places the foot in a position of pes equinus. A resting position of the extremity, puncture in case of abundant effusion, and timely resumption of movements quickly lead to recovery with preservation of function. Treatment of purulent bursitis consists of a timely incision followed by tampon-free management of the patient. In serous bursites—rest and heat in all forms. Some have seen good results from the use of passive hyperemia according to Bier. With persistent retention of exudate, puncture is indicated. After the subsidence of acute inflammatory phenomena, to prevent contractures, it is necessary to timely initiate active and passive movements. If the process passes into a chronic one with the formation of free bodies and thickening of the wall of the bursa, then the latter is excised completely. Chronic bursitis is subdivided into non-specific and specific; the latter includes tuberculous and syphilitic bursitis. Under the influence of prolonged, frequently recurring or single mechanical insults, chronic non-specific bursitis can develop, the so-called hygroma (hygroma). The latter is especially often observed in places subjected to frequent trauma, for example, in the knee region—bursitis praepatellaris, in the region of the olecranon—bursitis ole
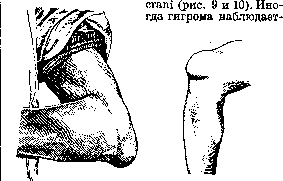
Figure 9. Bursitis olec
Figure 10. Bursitis prae- rani chronica.
patellaris. It is found where bone is located directly under the skin, e.g., the inner surfaces of the base of the big toe in hallux valgus. The bursa praepatellaris is most frequently affected, followed by the subdeltoidea, then the subacromialis, semimembranosa; very rarely the praetibialae, ischiadica. Chronic bursitis develops both in the early years of life and in mature age. The frequency of bursitis, according to Redi (in %): up to 20 years--12, 20-40 years-33, 40-60 years-52, 60-90 years-3. Men are affected more often than women: according to R. Redi, for every 45 men, 21 women were ill, apparently this is connected with the peculiarities of male labor. The cause of bursitis, authors (Tetit) consider trauma in 53%, rheumatism-15%, jaundice, puerperal fever, cooling-2%; in 30% the cause is not determined. Other authors also confirm that the most frequent cause is trauma, understanding by this not only direct injuries but also indirect (improper position, wearing various belts, prostheses, repeated irritation from poorly fitted instruments). Pathoanatomically chronic bursitis may be serous, proliferative and hemorrhagic (according to Bianchetti). Serous bursitis can reach the size of an adult's head, the form varies from a simple tumor to two-, three-lobed and more. The wall of the M. b. in this case shows all signs of chronic inflammation, is infiltrated, has necrotic areas and hemorrhages, in the thickness of the wall a considerable number of vessels is found. Sometimes the wall is infiltrated with cartilage cells and lime deposits, the fluid located in the bursa cavity is usually transparent or slightly turbid, of alkaline reaction, contains mucin. Proliferative bursitis is characterized by significant thickening of the wall, the inner surface appears warty, villous, full of papillary growths. The endothelium disappears in these cases. The fibers of connective tissue thicken (fig. 11). Hemorrhagic bursitis is similar to proliferative. The size of the affected mucous bursa varies, reaching the size of an adult's head. The walls consist mostly of connective tissue. Necrotic areas and hemorrhagic infiltrates deep in the wall are characteristic of it. Free bodies (corpora libera), found in bursae, develop most often in proliferative bursitis, rarely in serous and very rarely in hemorrhagic. Their number varies from one to 200, their size from 2 mm to the size of a rice grain. Their formation occurs due to disturbance of nutrition of the papillary growths located on the wall of the bursa on a stalk. The subjective sensations of patients with chronic bursitis are insignificant, and only during exacerbation pains may appear; besides, the swelling, reaching large sizes, can limit movement. In differential diagnosis it is necessary to consider the possibility of a hematoma of the M. b., cold abscess, aneurysm, joint cysts, soft tumors (myxomas and lipomas). For the treatment of chronic bursitis old authors proposed the method of crushing with subsequent application of pressure bandage and heat; but this method cannot be recommended because of the danger of awakening the dormant infection in the cavity and wall of the capsule; this is especially dangerous if there is an unrecognized tuberculous bursitis. Incision of the capsule and scraping out the contents sometimes lead to adhesion and obliteration of the bursa cavity. The most effective method is complete or partial, in case of adhesion with bone, removal of the M. b.
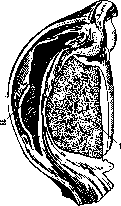
Figure 11. Bursitis praepatellaris: 1-the patella; 2-the expanded bursa praepatellaris with thickened wall.
Besides the described changes in the M. b. lime, uric acid, bone tissue have been found. Thus, three more forms of diseases of the M. b. can be distinguished: bursitis calcarea, urica and ossificans; trauma and preceding infectious diseases can give calcification of the M. b. (bursitis calcarea), which must be considered as a secondary reaction, rarely such bursitis is an expression of diathesis. Most frequently affected are the subacromialis and subdeltoidea. The age of patients is around and above 40 years, men get sick more often. The symptoms of bursitis calcarea are peculiar: the swelling sharply protrudes from the bursa cavity, of dense consistency and small size. Pains are not constant, but very sharp, often appear several years after the cause that caused the anatomical damage. Bursitis calcarea is usually well diagnosed by X-ray, but it must be differentiated from detachment of tuberculum majus, free joint bodies, calcified tuberculous foci. Treatment: heat, massage, iodotherapy, diathermy; especially effective is irradiation with X-rays--after 3-4 sessions the shadow of the M. b. disappears and with it the subjective phenomena. In some cases--removal by operative means. Bursitis ossificans exists as a special form and differs from bursitis calcarea, in which the remaining lacunae among the lime deposits can create a false impression of bone tissue. The development process of bursitis ossificans generally resembles bone development. Vessels of the wall and metaplastic cells penetrate into the lime deposits, from which as the lime is absorbed bone tissue is formed, resembling spongy substance. Bursitis urica occurs in gout, when as a result of metabolic disturbance retention of uric acid and salts can be observed. These salts are deposited mainly in cartilages and joint capsules. In serous bursae and para-articular tissues the deposition of uric acid salts is often accompanied by inflammatory phenomena and sharp pains. Macroscopically in the M. b. white spots and accumulation of white, like chalk, substance are noticeable. Microscopically bundles of crystals in the form of bouquets are noticeable. The part of the wall which they line, after their removal, appears necrotic; necrosis of the wall occurs as a secondary phenomenon as a result of salt deposition. Treatment--anti-gout, locally the same as in bursitis calcarea. Tuberculous bursitis--see Bursitis. Syphilitic bursitis--see Bursitis, syphilitic bursitis.
Tumors of the M. b. are very rare, occur mainly in the form of myxomas and sarcomas. Ombredanne counts in the literature only 6 cases of sarcoma of the M. b. Adrian up to 1909 found in the literature only 19 cases of all tumors of the M. b. Most frequently the praepatellaris is affected by sarcoma, second place is taken by the subdeltoidea, extremely rarely a tumor can develop in other bursae. Usually men of middle age get sick. According to the histological picture the tumors belong to the group of round- and spindle-celled sarcomas and have the usual malignancy characteristic of sarcomas, i.e., they quickly grow into underlying tissues and give metastases. At first the tumor is movable on the underlying tissues, but mobility is quickly lost. As the tumor grows the usual dilation of the superficial venous network develops. The tumor often has the character of myxosarcoma. For recognition it is necessary to consider the following circumstances: the anatomical position of the tumor at the site of a serous bursa, mobility on the underlying tissues at the beginning of development, rapid growth and dilation of the superficial venous network. Confusion is possible with chronic bursitis, non-specific, specific (tbc, lues), with bone and periosteal tumors. Treatment: early and wide excision. With large spread and recurrences--amputation. Primary sarcomas are very rare. In them a bloody exudate accumulates in the joint, movements in the joint are preserved. X-ray examination does not reveal a bone focus.
n. makhov.
Related articles
Mentioned in
Cite this page
“Mucous Bursa.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/mucous-bursa/