Joints
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article defines joints (diarthroses) as the movable, discontinuous connections between skeletal bones, characterizing them as the passive components of the locomotor apparatus. It details the essential elements of true joints—articular surfaces, capsules, and cavities—and classifies them based on their geometric forms, axes of rotation, and degrees of freedom.
Encyclopedia article (1928–1936)
JOINTS. A joint, or diarthrosis (from the Greek diarthroo—I dismember), syn. articulatio, articulus, is a movable, discontinuous connection of skeletal bones. Joints are one of the types of bone connections (see Articulation), characterized by the presence of a gap between the articulating bones, and consequently, the possibility of displacement (movement) of individual bony levers in relation to each other. Together with bones, ligaments, etc., joints are classified as the passive part of the locomotor apparatus. The main elements present in all so-called true joints are considered to be: 1) the articular surface (ends) of the connecting bones (facies articularis), 2) the articular capsule (capsula articularis), and 3) the articular cavity (cavum articulare). At the same time, each of these listed main elements, while having a number of common structural features, reveals in different joints its own anatomical (macro-microscopic) peculiarities, characteristic only for the given joint and determining its functional capabilities. In addition to the main elements, auxiliary (additional) formations of various anatomical structures and functional significance are noted in joints, some of which are more or less constant for almost all joints, while others are observed only in some joints, and often even in only one. Among the auxiliary structures, one should include: ligaments (ligamenta auxiliaria, s. accessoria), intra-articular cartilages (cartilagines intraarticulares, s. interarticulares), synovial (mucous) bursae (bursae synoviales, s. mucosae), etc.
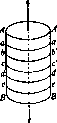
Figure 1. Formation of an ovoid or spindle-shaped body, thanks to the rotation of a segment of a circle around a chord. (According to Fick.)
Figure 2. Formation of a cylindrical body. Line AB—the generatrix of the cylinder. (According to Fick.) From the point of view of mechanics, the forms of the articular surfaces of the connecting bones deserve special attention, since they possess the main guiding role at the moment of movement of individual links of certain parts of the skeleton. The analysis of the mechanics of any given joint begins with an analysis of the shape of the articular ends of the bones, and one resorts to comparing these forms with the forms of various geometric bodies, and based on this, in the mechanics of joints itself (see Biomechanics), laws, formulas, definitions, and terms borrowed from physics are used. But when comparing the forms of articular surfaces with corresponding geometric figures and
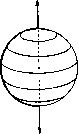

Figure 4. Formation of a trochoid-
shaped body. Curve AB—the generatrix of a grooved cylinder. (According to Fick.) Figure 3. Formation of a spherical body. Black semicircle—the generatrix of a sphere. (According to Fick.) when using this in the analysis of joint mechanics, one should make corrections, taking into account the compressibility, elasticity of cartilaginous coverings, intra-articular cartilages, etc. Before us is a living object of study—the joint of a human (animal), and not a dead body with its mechanical properties. Various geometric bodies of different shapes are obtained as a result of the rotation of a so-called generatrix (e.g., the rotation of a segment of a circle around a chord gives a body in the form of a spindle, an ellipsoid, Figs. 1–4). The surfaces of such bodies are called "surfaces of revolution." Each of these bodies, depending on its shape, has a strictly defined number of axes of rotation and, along with this, depending on the degree of its connection with another body or its free position in space, a certain number of so-called degrees of freedom (Figs. 5 and 6) (see Movements). Consequently, when analyzing joints, one first notes: 1) the shape of the articular
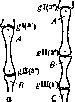
;i(3*) smn Figure 5.
Figure 6. b Figure 5. Connection of bones by joints: dI (3°) with 3 degrees of freedom and fII (1°) with 1 degree of freedom = 4° (diagram from Fick). Figure 6. Connection of bones by joints: c-gI (3°) + gII (3°) - in total 5 degrees of freedom; b- gI (3°) + fII (3°) + gIII (1°) - 6 degrees of freedom (diagram from Fick). surfaces, 2) the number of axes of rotation, and 3) the number of degrees of freedom, which determine the degree of mobility and the main movements in a given joint. In some cases, it is observed that the shape of the articular surface of one of the connecting bones more or less accurately corresponds to the shape of the articular surface of the second (receiving) bone; both surfaces are as if fitted to each other, they coincide, they are congruent. The most congruent surfaces are the surfaces of rounded bodies, and if one bone has a surface in the form of a segment of a sphere, the other has a corresponding depression, a concave area. Articular surfaces in some joints, more often of irregular shape, which do not correspond to each other, are called incongruent. According to the shape of the articular surfaces, joints are distinguished into: 1) spherical joint (articulatio sphaeroidea) (Fig. 7a) with a variety, the nut-shaped joint (enarthrosis, s. enarthr. sphaeroidea); 2) ellipsoid, ovoid joint (art. ellipsoidea) (Fig. 8a); 3) saddle joint (art. sellaris) (Fig. 9a); 4) cylindrical joint (art. cylindroidea) (Figs. 10a, 11a); with the distinction of the wheel-shaped, rotational joint (art. trochoidea); 5) hinge joint, ginglymus (ginglymus) (Fig. 12a), with a variety, the cochlear joint (art. cochlearis) (Fig. 13); 6) plane joint (art. plana) (Fig. 14). According to the number of axes of rotation, joints are subdivided into multiaxial, basically triaxial, biaxial, and uniaxial. The articular surface can be formed either by one bone or be composed of the sum of the articular surfaces of two or more bones lying side by side. Thus, in some joints, only two bones articulate,

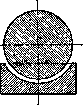
Figure 7: a—axes of rotation of a spherical joint (shoulder joint); b—diagram. in others three or more. The former joints are called simple (art. simplex), the latter complex (art. composita, s. complicata). An example of a simple joint can be the shoulder joint (Fig. 7a), and of a complex joint—the wrist joint (Fig. 8a). The complexity of a joint can also be understood as the complexity of its structure or mechanics, but in that case, the word "complex" is used not as a term ("complex joint"), but only as an adjective. 88 According to mobility, joints are divided into two groups: 1) freely movable, so-called arthrodia (arthrodiae); the term "arthrodia" is often used to denote only spherical joints (Rauber) or art. mobilitatis majoris (R. Fick); 2) stiffly movable, so-called amphiarthroses (amphiarthrosis) (Rau-
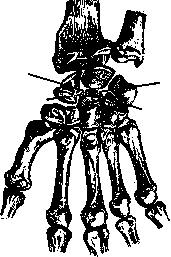
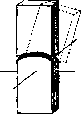
Figure 8: -axes of rotation of an ellipsoid joint (wrist joint); b—diagram (from Fick); c—diagram. ber) or art. mobilitatis minoris (R. Fick). To the first group, one can assign the majority of the joints listed above (when describing the shape of the articular surface), and to the second—joints with a strong, tightly stretched articular capsule, with a strong ligamentous apparatus, limiting
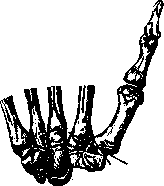

Figure 9: a—axes of rotation of a saddle joint (joint between the greater multangular bone and the I metacarpal bone); b—diagram (from Fick). mobility (e.g., the joint between the lateral surface of the navicular bone of the tarsus and the cuboid, between the cuboid and the III cuneiform, between the cuneiform bones, between the bases of the metatarsal bones) (Fig. 14). Spherical joints are those in which the articular surface of one of the connecting bones approaches the shape of a sphere (a larger or smaller segment), while on the other bone there is a corresponding concave articular cavity (cavitas glenoidalis). The surfaces in such joints are congruent. These joints are the most movable, have three degrees of freedom, and belong to multiaxial joints. Basically, spherical joints have three main axes of rotation, intersecting at right angles at one point—the "center of rotation"—and located in the anterior-posterior, transverse, and vertical directions. The main movements are: abduction and adduction, flexion (lifting forward), extension (lowering, moving backward), rotations (rotation) outward and inward. A typical spherical joint is the shoulder joint (Fig. 7a and b) (see Shoulder joint). If in a spherical joint the articular head and cavity are larger than a hemisphere, as for example in the hip joint, such joints are called nut-shaped, enarthroses (Fig. 15). In terms of joint mechanics, there is no essential difference between a spherical and a nut-shaped joint; the axes of rotation and movements are the same. Ellipsoid joints have on one side a convex, somewhat elongated articular surface in the form of a segment of an ellipsoid, formed by one or several bones, and on the other side a correspondingly concave, more or less congruent to the first, cavity. Such a shape of articular surfaces allows movement along two axes: one—longitudinal, the second—short, running perpendicular to the first. Ellipsoid joints possess two degrees of freedom. The most clearly expressed ellipsoid joint is the wrist joint (Fig. 8a, b, c) with movements—flexion and extension, abduction and adduction of the hand. To the number of biaxial joints, one also refers the so-called saddle joints. The articular surfaces of both connecting bones are more or less identical, concave in one (longitudinal) direction and convex in the other (transverse), but they connect to each other in such a way as if two saddles were placed together. Then the concave surface of one of them would receive the convex surface of the other, and the convex surface of the first would be connected
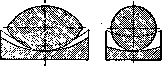
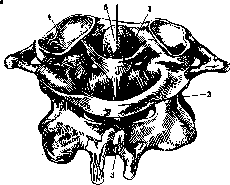
Fig. 10. Axis of rotation of a cylindrical joint (the joint between the atlas and the odontoid process of the epistropheus): 1-lig. transversum; 2-posterior arch of the atlas; 3-epistropheus; 4-fovea articularis sup.; 5-dens epistrophei.
with the concave surface of the second. A saddle joint has 2 degrees of freedom. As an example, one can take the joint between the greater multangular bone of the wrist and the base of the I metacarpal bone (Fig. 9a and b) with movements of flexion and extension of the thumb, its abduction and adduction (see Hand). 8) Cylindrical joints, having the shape of the articular end of one bone, comparable to a segment of a cylinder, and a concave articular surface on the other, are uniaxial joints with one degree of freedom, allowing only the movement of rotation and slight sliding of the cylindrical surface in relation to the articular surface. A striking example of a cylindrical joint can be considered the proximal and distal radioulnar joints (Fig. 11a and b) with the movement of rotation of the radius in relation to the fixed ulna (during pronation and supination of the hand) (see Forearm, Hand). By the nature of the movements, cylindrical joints are also called rotational, some - pivot joints. In those cases when there is a groove on the cylindrical surface, and a ridge on the corresponding concave surface, the joints are given the name of hinge or ginglymoid joints (Fig. 16a and b). These are joints also with one axis of rotation, but the movement of one bone lever in relation to the other is determined by the sliding of the guiding ridge in the guiding groove of the block; possibilities for lateral sliding or displacement cannot exist. Such joints include, for example, the ankle joint, interphalangeal joints of the foot (see Ankle joint, Foot) and hand (see) (Fig. 12a and b) with movements of flexion and extension. In individual hinge joints, the guiding ridge is positioned in relation to the horizontal plane of the articular surface not at a right angle, but is placed obliquely (at various angles) (the guiding groove also has a corresponding direction), so that a helical surface is formed, in joints usually represented only by a small segment of it. Such joints are called screw joints. They, as is evident, are

Figure 11: a-axis of rotation of a cylindrical joint (distal and proximal radioulnar joints): 1-incisura semilunaris; 2-olecranon; 3-processus coronoideus; 4-tuberositas ulnae; 5-tuberositas radii; 6-crista interossea; 7-facies volaris; 8-margo volaris; 9-processus styloideus ulnae; 10-processus styloideus radii, b-diagram.
only a variety of hinge joints and therefore have one axis of rotation and one degree of freedom. The movement of one bone in relation to the other will proceed somewhat obliquely, theoretically with the possibility of translational movement along a helical surface, but since in joints the helical surface is represented by an insignificant segment, practically lateral translational displacements can be excluded, all the more so because lateral ligaments (see Ligaments) will prevent this. To screw joints one can relate, for example, the elbow joint (Fig. 13) in that part where the trochlea of the humerus connects with the greater semilunar notch of the ulna, with movements of flexion and extension of the forearm (see Elbow joint). The last group of joints according to the shape of their articular surfaces are the so-called plane joints. Plane, sometimes somewhat obliquely located articular surfaces of the connecting bones allow only insignificant sliding of the surface of one bone in relation to the other in two directions: up-down and to the sides, as well as combined. The possibilities of displacement are determined, on the one hand, by the size of the articular surfaces, on the other hand, by the strength, degree of tension of the articular capsule and ligamentous apparatus. The latter moment in some plane joints predominates to such an extent that practically these joints ca-

Figure 12: a-axis of rotation of a hinge joint (interphalangeal articulations); b-diagram.
n be classified as stiff joints, which is why some call them also amphiarthroses (see above). To plane joints belong the joints between the articular processes of the thoracic vertebrae, between the bones of the tarsus (between the lateral surfaces of the cuneiform bones), between the bases of the metatarsal bones


Figure 13. Screw joint (joint between the trochlea of the humerus and the notch of the ulna).
Figure 14. Plane joints - amphiarthroses (horizontal section of the foot). etc. (Fig. 14). In some joints, the shape of the articular surface does not lend itself to comparison with a simple geometric figure, it can be complex, composed of segments of any two bodies, e.g., the complex shape of the distal end of the femur (see Knee joint). Joints in which movements occur simultaneously and when moving a bone in one joint, movement in another is mandatory, are called combined, e.g., the right and left temporomandibular joints, the right and left atlanto-occipital articulations. The articular surfaces of the articulating bones are covered with a layer of cartilage (cartilago articularis) of varying thickness in different joints (from 0.2 mm to 6 mm). In the temporomandibular joint and the sternoclavicular articulation, this covering is formed by fibrous cartilage, while in all other joints - by hyaline cartilage. The explanation for this fact is given on the basis of data on the development of joints. Joints in which bones participate, which in the primordial skeleton consisted of connective tissue, receive a covering of articular surfaces from fibrous cartilage; in joints whose articulating bones are prefor-
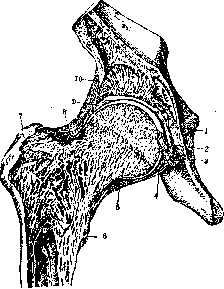
Figure 15. 1-connective tissue in fossa acetabuli; 2-fovea capitis; 3-lig. teres; 4-lig. transversum femoris; 5 and 8-zona orbicularis; 6-trochanter minor; 7-trochanter major; 9-labrum glenoidale; 10-lig. iliofemorale.
med with cartilage, a covering of hyaline cartilage is formed. In the articular cartilage of adults, 4 layers are distinguished with different cell shapes and fiber directions. The most superficial one - with a tangential arrangement of fibers, with flattened cells, the transitional zone - with rounded cells included in an arcuate system of fibers, the third layer - the zone of radial fibers and groups of cells, and the fourth - in which the indicated fibers of the previous layer penetrate into the calcified zone of the bone-cartilage transitional layer between the articular cartilage and the bone tissue of the end of the bone (Benninghoff). In the articular cartilage of a child, the most superficial layer of flat cells is still absent. Articular cartilage is characterized by smoothness, luster; from the point of view of mechanics - by elasticity, easy compressibility, ability to deform. The latter properties of cartilage are important for increasing the congruence of articular surfaces. The physical properties of articular cartilages of children and adults are different (Baer and Gocke). Water-containing children's cartilage deforms more than the "dense cartilage of adults and the elderly."
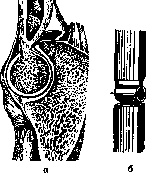
Figure 16: a-hinge joint (section of the elbow joint); t-hinge (diagram from Fick). The articular capsule (capsula articularis), connecting the articulating bones and enveloping their articular ends, together with the latter closes the joint cavity. In it, two are distinguished
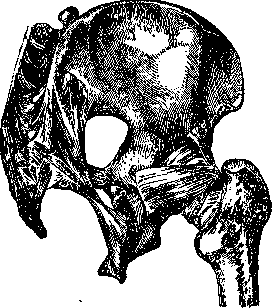
Figure 17. Extracapsular ligaments (and hip joint, posterior view).
layers: 1) an outer layer of varying density of connective tissue elastic and collagenous fibers (stratum fibrosum) and 2) an inner layer, lining the capsule from the side of the joint cavity, the so-called synovial layer (stratum synoviale), synovial membrane. The first layer attaches in most joints along the edges of the articular surfaces of the connecting bones, weaving bundles of its fibers into their periosteum. The articular capsule in almost all joints is reinforced by auxiliary ligaments weaving into it (see Ligament) (Fig. 17 and 18). In some joints, bundles of TENDINOUS FIBERS of NEARBY muscles attach to the fibrous capsule. The thickness, resistance to tension and rupture are different in individual parts of the organism, fibrous fibers are usually arranged circularly and longitudinally, partly oriented in directions determined by the movements in the given joint. The second layer of the articular capsule - the synovial membrane - lines the fibrous capsule from the inside, tightly fusing with the latter, and covers areas
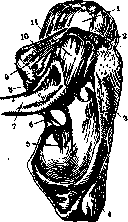
18. Inhibitory ligament - arch of the shoulder joint (lig. coraco-acromiale): 1-articulatio humeri; 2-acromion; 3-
bones located inside the joint, but free from cartilaginous covering. The articular cartilage is not covered by the synovial membrane. This covering also clothes the intra-articular ligaments. Macroscopically, the synovial layer is characterized by smoothness, luster, and is constantly moistened by the fluid secreted into the joint cavity, called synovia (synovia, syn. smegma, serum articulare). Synovia is a serous fluid transuding into the joint cavity with desquamated and fatty-degenerated cells of the articular cartilage and synovial membrane. Previously, it was believed that synovia was a product of special glands, mistaking the fatty lobules of the synovial membrane or the so-called synovial villi (Fig. 19) for glands. These glands were called Haversian glands (glandulae Haversianae). Microscopically, the synovial layer is constructed of connective tissue with an admixture of elastic fibers, in the slits between which individual fatty, rarely cartilaginous, cells are found. The synovial layer has a large number of thread-like, microscopic outgrowths, the so-called synovial villi (villi synoviales), which, upon their detachment, contribute to the formation of free bodies or 'joint mice' in the joint cavity (see Joint mouse). Surface
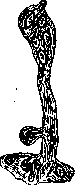
synovial section. (According to Fick.)
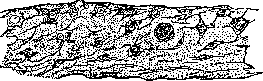
Fig. 20. Synovial membrane—microscopic view. (According to Fick.)
of the synovial membrane is lined not with endothelium, as previously believed, but with connective tissue (Fig. 20). Outgrowths with a fatty lining (plicae adiposae) and folds (plicae synoviales) also protrude from the synovial layer into the joint cavity (Figs. 21 and 22). In many joints, the synovial membrane forms special protrusions, usually between the bundles of fibers of the fibrous layer, located between the bone and the muscle adjacent to it. These protrusions of the cavity, which remain in communication with the general joint cavity, are called synovial, mucous bursae (bursae synoviales, s. mucosae) (see Mucous bursa). Small protrusions of the synovial membrane are also called ganglia. The joint cavity (cavum articulare) appears as a narrow slit remaining between the tightly pressed articular surfaces and increasing somewhat at the expense of the aforementioned cavities of the synovial bursae. The cavum articulare is filled with synovial fluid, the amount of which can vary. The presence in the cavity

Figure 21. Synovial folds—section. (According to Fick.)
of fluid in the joint creates even greater conditions for congruency ('liquid meniscus'—Lesgaft), as well as for the adhesion of articular surfaces. Among the anatomical formations that are not observed in all joints, but appear as features of one or another joint, one should include the so-called intra-articular cartilages (cartilagines intraarticulares, s. interarticulares). Two kinds of intra-articular cartilages are distinguished: discs (discus articularis) and menisci (see Joint menisci) (meniscus articularis). A disc is a cartilaginous or dense connective tissue plate of more or less uniform (throughout its extent) thickness, attaching to the joint capsule and dividing the joint cavity into two isolated chambers. Such joints are called two-chambered. Discs are present in the temporomandibular joint and in the sternoclavicular joint (Fig. 23). Intra-articular cartilages are constructed of dense connective tissue or fibrous cartilage. From the point of view of functional significance, discs and menisci increase or create the congruency of the articular surfaces of the articulating bones, play the role of movable articular surfaces, soften shocks, impacts, etc., in weight-bearing joints (knee joint, etc.), serving as springy cushions between the articular ends. In the mechanics

Figure 22. Synovial and fatty folds. (Knee joint—opened from the front.)
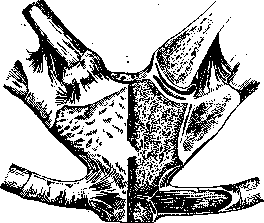
Figure 23. Intra-articular cartilage—disc; two-chambered
joint (sternoclavicular articulation—cross-section). of joints, intra-articular cartilages play a significant role (especially if one takes into account their physical properties: compressibility, elasticity, etc.). A peculiar adaptation for increasing articular surfaces and for strengthening congruency is the so-called cartilaginous lip (labium, s. labrum glenoidale, cartilagineum)—a dense connective tissue rim (with cartilaginous cells included in places), attaching to the edge of the concave articular surface of one of the articulating bones. On the side facing the joint cavity, the cartilaginous lip is covered with the same cartilaginous covering as the rest of the articular surface. Examples: labrum glenoidale of the shoulder and hip joints (Fig. 15).

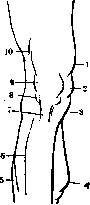
In strengthening the joint, in reinforcing the connections between the articulating bones, along with the joint capsule, a number of other anatomical formations and factors play a significant role: 1) Ligaments of a given joint, which are subdivided into external, extracapsular ligaments (lig. extracapsularia; Fig. 17) and intra-articular (lig. intraarticularia, s. interarticul.). Intra-articular ligaments are observed only in some joints, for example, lig. teres femoris in the hip joint (Fig. 15), lig. cruciata in the knee joint (Fig. 22), and others. At the places of attachment of intra-articular ligaments, the articular surfaces are devoid of cartilaginous covering and blend into the periosteum. 2) Muscles surrounding the joint, which by their constant tension (tonus), and even more so by contraction, actively strengthen the joint, which often has almost no auxiliary ligaments (for example, the shoulder joint). 3) Soft tissues of the joint region, such as fasciae, subcutaneous tissue, skin, etc. 4) Atmospheric pressure (Fig. 24). 5) Adhesion of surfaces due to the presence of synovia in the joint slit. For a physician, it is important to be familiar with the external forms of the region of one or another joint, with the so-called configuration of the joint. The protruding parts of the connecting bones (their shapes, sizes, etc.), external ligaments, surrounding muscles with their tendons, subcutaneous fatty tissue, etc., determine the relief of the surfaces of the joint region. At the same time, some joints (knee, Figs. 25, 26a, b and c, 27a and b, 28a and b, elbow, etc.) are more clearly configured, while others (hip, shoulder, etc.), due to their deep position under strongly developed musculature, do not have a clear relief.
Figure 24. Retraction of the shoulder joint capsule due to atmospheric pressure—when pulling the head of the humerus out of the glenoid cavity of the scapula (diagram from Fick). Figure 25. External forms of the region of the right knee joint—front view: 1—m. vastus medialis; 2—medial condyle of the femur; 3—medial condyle of the tibia; 4 and 5—m. gastrocnemius; 6—extensor of the big toe; 7—lig. patellae; 8—fatty pad; 9—patella; 10—m. vastus lateralis. (According to Schadow.)

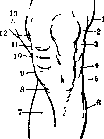
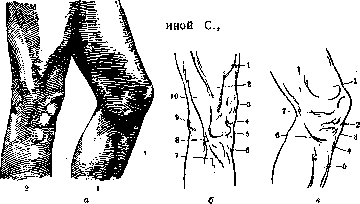
Figure 26: a—relief of the knee joint region: 1—in strong extension; view from the outside; 2—in slight flexion; view from the inside (from Kollmann). b and c—diagrams explaining Fig. a; b: 1—external extensor of the lower leg; 2—tractus ilio-tibialis; 3—patella; 4—fatty capsule; 5—patellar ligament; 6—tuberosity of the tibia; 7—peroneal muscle; 8—head of the fibula; 9—fat; 10—biceps muscle. c: 1—m. vastus medialis; 2—medial condyle of the femur; 3—medial condyle of the tibia; 4—tuberosity of the tibia; 5—anterior surface of the tibia; 6—m. gracilis and m. semitendinosus; 7—medial condyle of the femur.
a Figure 27 a—external region of the left knee joint (front view) in a semi-flexed position (from Kollmann); b—diagram explaining Fig. a; b: 1—m. vastus lateralis; 2—lateral condyle of the femur; 3—m. biceps; 4—tibia; 5—head of the fibula; 6 and 7—m. gastrocnemius; 8—mm. gracilis and sartorius; 9—medial condyle of the tibia; 10—joint; 11—medial condyle of the femur; 12—m. vastus medialis; 13—m. adductor. Nevertheless, in pathological conditions (inflammatory process, dislocation, etc.), the configuration of each joint, the relief of the surface, must change to a greater or lesser extent. In the configuration of a joint, one can notice significant age, sex, type, professional, and individual peculiarities. Joints, as movable connections of bones, play a significant role in the statics and dynamics of the body, especially of the limbs. Corresponding to the axes of rotation in the joint and the degrees of freedom, the muscle groups acting on the given joint are distributed (see Muscular system). Movements in a joint are distinguished into active and passive (see Movements). The range of motion is determined in degrees of angles, which the individual bone levers, links of the skeleton, form in relation to each other. The factors limiting mobility, besides pathological conditions of the joint, are: the presence of bony protrusions on one of the articulating bones, which at a certain moment of movement abut against another bone (e.g., limitation of flexion and extension in the elbow joint, Fig. 16a), the presence of restraining ligaments (Figs. 18 and 13), tension of the joint capsule, etc. Joints have a number of features of blood supply. Most joints receive arterial branches from several nearby arteries. These branches approach the joint capsule also from arteries located above and in the region of the given joint, and finally below the joint [the latter have an ascending direction and are represented by the so-called recurrent arteries (aa. recurrentes)]. All arterial branches in the joint
capsule form a large
number of anastomoses,
and taken together—the joint
an arterial network (rete arteriosum articula-"V »
re) with great possibilities of collateral \ \ blood circulation. With the lymph. \ ' system, Joints stand in their own /l? t* g 13- i and- 4 £i# 7-
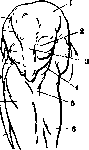
Figure 28: a-external forms of the knee joint area with strong bending-view from the front (from J. Kollmann); b-diagram explaining figure a; b: 1-m. vastus medialis; 2-fatty capsule and femoral condyle; i-patellar ligament; 4-edge of the tibia; 5-inner surface of the tibia; c-calf muscles; 7-extensor hallucis longus; S-arteria tibialis anterior; 9-m. peroneus longus; 10-extensor hallucis longus; 11-edge of the tibia; 12-fatty capsule; 13-tendon of m. vasti medialis; 14-edge of the femoral condyle. figurative relationships. Some authors consider joint cavities as wide lymphatic clefts, from which networks of lymphatic capillaries begin, and then larger carrying vessels (see Lymphatic system).- Joints are the most sensitive structures in the body. Nerve endings are found in the form of numerous Vater-Pacini corpuscles. In addition to true joints between bony links of the skeleton, similar ones are also found between the auditory ossicles and between the cartilages of the larynx. In the formation of Joints, which occurs in the early embryonic stage (in the 3rd month of embryonic life) and in a 10-week embryo leads to the formation of a joint cleft, initially in the area of more centrally located and larger, later in that of smaller parts of the skeleton, there is a noticeable thickening of mesenchyme. A slit appears in the mesenchyme, which will divide this mesenchymal area into two parts, directly adjacent to the future joint surfaces of the bones to be connected. These coverings of the joint surfaces (perichondrium) later disappear, and the cartilaginous ends of the future bones lie directly against each other, enclosed in a mesenchymal sac, which then differentiates into the joint capsule. Ligaments, joint capsule, etc. in the cartilaginous stage of the skeleton represent a continuation of the perichondral layer from one segment of the skeleton to another. In cases where two cavities develop in the mesenchyme between the joint surfaces, a two-chamber Joint is formed with a cartilaginous disc between the two clefts. Underdevelopment of the central part of the disc leads to the development of menisci. Joint surfaces comparatively early take on the forms they have in various Joints of the formed organism. By the time movements begin, Joints are more or less ready, and the further influence of muscles acting on a given Joint on the formation of joint ends and other structures of the joint is insignificant.-The study of Joints is carried out by simple anatomical dissection on cadavers or after preliminary filling of the joint cavity with a colored hardening mass (see Blood vessels) or air; by making series of topographic saws of frozen cadavers, made in different planes through joint areas; by the method of fluoroscopy and radiography. Pathology of joints-see individual joints, as well as Arthritis, Gonitis, Coxitis, Synovitis, Bursitis, Rheumatism.
Related articles
Mentioned in
Cite this page
“Joints.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/joints/