Hand
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the first edition of the Great Medical Encyclopedia covers the anatomy, embryology, and development of the human hand, detailing its bones, joints, ligaments, and structural relationships as understood in Soviet medicine of the 1930s.
Encyclopedia article (1928–1936)
758 Hand (manus), the peripheral part of the upper extremity, located distal to the forearm. Functionally, the hand represents a prehensile organ that easily adapts to the volume of the grasped object and performs both the coarsest and the finest movements with a certain precision. The hand and fingers are the constructive and protective force of man. Embryology. By the 6th week of embryonic development, the main parts of the limb can already be recognized: the hand resembles a flat fin, on the anterior edge of which notches are already visible. Further notches between the thumb and index finger and between the III and IV fingers on the one hand, and the growth of these rudiments on the other, reveal the ray-like outlines of the latter (Hertwig). The future bone skeleton of the hand is outlined as early as the 2nd month. Cartilaginous epiphyses and cartilaginous outlines of the metacarpus appear only in the 1st year of extrauterine life and disappear with the cessation of growth in
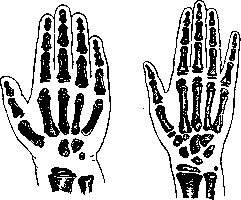
Fig. 1.
Figure a.
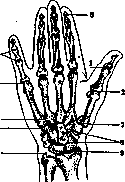
Figure 1. Metacarpal bones of a 5-year-old child. Figure 2. Carpal and metacarpal bones of a 7-year-old child. length of individual bones. On the roentgenogram of the hand of newborns, only the diaphyses of the finger phalanges and metacarpal bones are visible; in the 5th month, the bone nuclei of the capitate and hamate bones. In the second half of the 2nd year, a small flat, rapidly growing bone nucleus forms on the lower epiphysis of the radius. In the second half of the 4th year, the bone nuclei of all fingers are visible, and at the end of the 4th year, the capitate, hamate, and triquetrum; the greater and lesser multangular (trapezium and trapezoid), navicular (scaphoid), lunate (semilunate), and pisiform bones are absent (Fig. 1). In the 7th year, all the bones of the hand, excluding the pisiform bone, are ossified or are in the process of ossification (Wilms) (Fig. 2). At the beginning of the 18th year, the epiphyseal line below the end of the radius and ulna usually disappears (Wilms). Significant deviations from these age changes in one direction or another are considered pathological, such as the acceleration of ossification in local bone tuberculosis
diseases (Rehn). - Phylo- and ontogenesis - see Limbs.
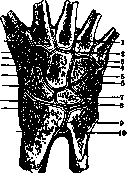
Anatomy. The hand, starting from the forearm, is divided successively into three parts: the carpus (wrist), metacarpus, and fingers (digiti). Carpus. The basis of the carpus is formed by the following groups of bones (from top to bottom): 1) the distal end of the radius and ulna; 2) the first row of carpal bones (counting from the radial edge): navicular (scaphoid), lunate, triquetrum, pisiform; 3) the second row of carpal bones: greater and lesser multangular, capitate, hamate; 4) the proximal ends of the five metacarpal bones. All these bones are connected to each other by means of three groups of joints: 1) radiocarpal, 2) intercarpal, and 3) carpometacarpal (articulatio radio-carpea, intercarpea et art. carpo-metacarpeae; Figure 3). - The radiocarpal joint is located between the radius and the corresponding surfaces of the scaphoid, lunate, and triquetrum; the articular surface of the radius descends distal to the same end of the ulna, a fact that explains the frequency of isolated fractures of the distal end of the radius during falls when the palmar surface of the hand, becoming a point of support, plays a protective role (Gurlt). The consequence of this relationship between the ends of the forearm bones is that the end of the ulna does not take direct part in the formation of the radiocarpal joint. This deficiency on the part of the ulna is compensated for by the so-called triangular cartilage (discus articularis), the base of which is connected to the notch of the radius. This triangular cartilage is of great importance for the mechanism of unimpeded rotations of the radius around the ulna during pronation and supination (Fick). This cartilage does not belong to ordinary interarticular cartilages, but represents a true continuation of the articular cartilage of the radius and participates in all its movements (Gerlach) (Fig. 3). The joint capsule is distinguished by its spaciousness and, thanks to this, lacking sufficient strength, receives support from the reinforcing radiocarpal and collateral ligaments. The fourth bone of the first row of the carpus - the pisiform bone - does not participate in the formation of this joint and is "movably mounted" on the triquetrum, representing a sesamoid bone of the flexor carpi ulnaris (Spalteholz). - Mechanism of the joint. The radiocarpal joint is a free joint (arthrodia). Movements occur in all directions, more in the dorso-palmar direction (180°) than in the lateral direction (80°); at the same time, it is easier to bring the hand closer to the ulna than to the radius, which is explained on the one hand by the presence of the triangular cartilage (Rauber), and on the other hand by the fact that the styloid process of the ulna ends proximal to the process of the radius. - Intercarpal joint. It connects the bones of the first row with the second. The center of the second row of carpal bones forms together an articular head, with the largest convexity of this head being formed by the capitate and part of the hamate (Fig. 3). The distal row serves as a support for the bones of the first row and therefore cannot be as mobile as the first, which forms a very mobile joint with the radius and ulna. - The carpal bones are connected to each other by short ligaments located on the palmar and dorsal sides and between the lateral surfaces of the small carpal bones (ligamenta volaria, dorsalia, interossea). - Carpometacarpal joint. Between the carpal bones and the bases of the metacarpal bones there is a whole series of connections allowing a minimum of flexion and extension movements, and moreover simultaneous with the movement of the second row of carpal bones; both rows of joints represent as it were a single joint (Hyrtl). An exception is the carpometacarpal joint of the thumb, which has an independent connection with the greater multangular bone; in this joint, the most extensive movements of the hand are possible. On the palmar side, the border separating the forearm from the carpus is marked by two furrows, especially pronounced in well-nourished children. In this place, the skin is very thin and tender, and the veins clearly show through. In lean people, a number of long cords are also visible here - the tendons of the flexors (flexor carpi radialis, ulnaris, and palmaris longus), disappearing in the thickness of the thenar and hypothenar eminences. At the radial edge, the protrusions of the scaphoid are clearly palpable, and at the ulnar edge, the pisiform. - The subcutaneous tissue here is rather tightly connected to the underlying layers, as a consequence of which inflammatory processes of the subcutaneous tissue of the palmar side of the forearm do not pass to the palm as quickly as processes in the region of the back of the forearm to the dorsal side
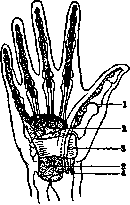
Figure 4. Ligamentum carpi volare-3; 1-thumb; 2-common tendon of the finger flexors; 4-flexor carpi radialis.
of the hand. - The fascia of the forearm forms upon transition to the hand a transverse ligament (ligamentum carpi volare), usually closely connected with the palmaris longus muscle (Rauber). Part of the forearm muscles ends here, while part passes over or under the transverse ligament onto the hand. The palmaris longus muscle passes over the ligament, while all the finger flexors pass under the ligament. Friction created during the movement of all flexors under this ligament is reduced by the presence in this place of a large mucous bursa, which descends distally to the place of origin of the lumbrical muscles and rises proximally 4 cm above the transverse ligament (Fig. 4). In the narrow depression between the tendons of the palmaris longus and flexor carpi radialis runs the median nerve, and on the radial side of the flexor, the pulsation of the rather superficially lying
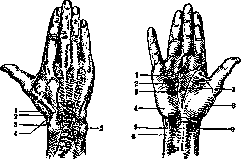
Figure 5.
Figure 6.
Fig. 5. Snuffbox-2; 1 - m. extens. poll. longus; 3 - proc. sty!.; 4 - m. extensor poll. brev. et abduct. poll. Figure 6. Palm lines: 1 - lin. mental.; 2 - lin. cephal.; 3 - lin. fortunae; 4 - hypothen.; 5 - m. fl. carpi uln.; 6 - tendo m. palm.; 7 - lin. vital.; 8 - thenar; 9 - m. fl. carpi rad. covered only by skin and a thin fascial leaflet of the radial artery (a. radialis). The ulnar nerve lies on the radial side of the pisiform bone. - Dorsal side of the wrist. Here the skin is very mobile and is easily pinched into a fold. On this side, the head of the ulna stands out particularly clearly, as well as the tendon of the long extensor muscle of the thumb (Fig. 6).

Upon strong abduction of the thumb, on the dorsal side between the tendons of the long abductor and short extensor of the thumb and the long extensor of the thumb, a triangular depression is formed (the so-called "snuffbox"), at the bottom of which the pulsation of the radial artery can be felt, heading here from the dorsal side of the hand to the palm to participate in the formation of the deep arch (Fig. 5). Through the skin of the dorsum of the wrist, a relatively large vein shines through - v. cephalica pollicis. As on the palmar side, the fascial leaflet of the dorsum of the forearm thickens into the dorsal ligament of the wrist (lig. carpi dorsale), forming sheaths for the extensors.
The synovial membrane of each sheath, bulging, encloses the tendon located in it, forming a sort of "mesenteriolum" in which the vessels supplying the tendon are located (Braus). Above these tendons, the formation of cystic tumors, known as "synovial ganglion," is often observed. Of the vessels of the dorsum of the wrist, the radial artery should be noted, heading between the bases of the I and II metacarpal bones to the palm. Metacarpus. The basis of the metacarpus is formed by 5 independent tubular bones - the metacarpal bones (ossa metacarpalia), connected to the second row of carpal bones and forming distally heads for articulation with the proximal phalanges of the fingers. Palmar surface, palm (vola).
On the palmar surface, the metacarpus is covered, in contrast to the dorsal surface, by a thick layer of soft tissues. The length of the palm is constant, the width is variable and depends on the position of the fingers during abductions and adductions. The palm forms a depression in the flexed position and received its name from this shape (boat - palm). The mentioned concavity (depression), being limited on two sides by muscular elevations - thenar and hypothenar - increases upon adduction of the thumb and flexion of the remaining ones (Fig. 6). The palm is abundantly supplied with nerves and vessels and, consequently, possesses a higher temperature and sensitivity than the dorsal side of the hand.
The skin itself has a large number of sweat glands. The epidermis is distinguished, as generally on the flexor surfaces of the limbs, by tenderness, especially in people of non-physical labor; conversely, in those engaged in physical labor it is significantly denser. The hand and its palmar surface, including the fingers, very frequently bear clear traces of profession, which deserves attention not only in the clinical, but also in the medico-legal respect (Lesgaft). On the skin of the palm, the presence of three lines (palmar folds) deserves attention, the origin of which, according to the opinion of old authors (Hirtl), must be explained by the flexion of the hand in uterine life, since these lines are noted not only in newborns, but also in the embryonic state.
These lines can serve for orientation when determining underlying formations; thus, at the place where the second line crosses the third carpal bone, is the highest point of the superficial palmar arch. These lines almost never disappear during inflammatory processes of the palm, edema, etc. The name of these lines comes from those distant times when palmistry still had the right of citizenship in medicine (Fig. 6). The first - the line of life (linea vitalis) - begins at the wrist, between both muscular elevations of the palm, rises upward along the border of the thenar and ends near the proximal phalanx of the index finger.

The second - the head line (linea cephalica) - usually begins at the place where the first line ends and in an oblique-transverse direction approaches the inner border of the hypothenar, without reaching the edge of the palm. The third - the line of "reason" (linea mentalis) - originates at the base of the middle finger, runs transversely almost to the ulnar edge to the base of the little finger. The inconstant fourth line - the line of "fortune" (linea fortunae) - runs almost parallel to the first. The subcutaneous tissue of the palm is insignificant, but very dense.
In the middle of the palm between fibrous strands are embedded fat lobules, which upon a vertical skin incision seem to bulge out from the wound. Subcutaneous hemorrhages of the palm are almost never observed. The dense sheet of aponeurosis represents a kind of protective organ for the vessels and nerves of the palm. Since the skin of the palm is fused with the aponeurosis, inflammatory processes of the subcutaneous tissue here are extremely painful. Subaponeurotic abscesses of the palm cannot break through the dense fascial leaflet and seek an exit proximally onto the forearm or even through the interosseous gaps onto the dorsum.
Since the palmar aponeurosis sends processes to the skin and fibrous sheaths of the four fingers, it plays a certain role in finger flexion. This becomes especially clear in Dupuytren's contracture. When straightening the fingers, the mentioned processes are taut, as a result of which the underlying fatty tissue diverges in the form of three tubercles between the proximal phalanges of the four fingers. - The muscles of the palm are divided into 3 groups: middle and two lateral. The first is located in the depression between the palmar elevations and is represented by the tendons of the deep and superficial digital flexors, the long flexor of the thumb, as well as the lumbrical muscles (Fig. 10). Standing apart is the group of interosseous muscles (musculi interossei).
as well as the metacarpal bones, are tubular bones, but shorter. One distinguishes the proximal, middle, and nail (distal) bone phalanges (on the thumb, the proximal and nail phalanges). The proximal phalanx is connected to the head of the metacarpal bone by means of a hinge joint. The final phalanx ends in the so-called tuberositas unguicularis—an expanded mushroom-shaped bony outgrowth on the palmar surface. The length of the fingers on the palmar side seems shorter than on the dorsal side, because on the palmar side they reach only the furrow separating the fingers from the palm, and this furrow corresponds to only half of the proximal phalanx on the dorsal side. The skin on the palmar side of the fingers has, just like the palm itself, a wave-like pattern, which plays, as is well known, a huge role in forensic medicine (see Dactyloscopy). Along with this, on each finger there are three lines corresponding, except for the lowest one, to the location of the phalangeal joints. The skin of the thumb joint also bears three lines, of which the last two are devoid of topographical significance. - The subcutaneous tissue of the fingers consists of a dense fatty layer,

Figure 10. Superficial palmar arch and tendons of the fingers.
especially on the nail phalanx, where a dense network of vessels and nerves is located, which is connected with the extremely developed sensitivity of the nail phalanx, which serves as the organ of touch; this also explains the extremely strong painfulness of this phalanx during inflammatory processes, which is further increased due to the presence of dense connective-tissue septa. - Fibrous sheaths on the palmar side of the fingers replace the fibrous fasciae here. For the II, III, and IV fingers, the sheaths begin above the heads of the metacarpal bones and end at the base of the nail phalanx. The sheaths of the little finger and the thumb are significantly longer, because they begin on the forearm. On all four fingers, the mentioned sheaths enclose the flexor digitorum profundus and superficialis, while on the thumb they enclose only the flexor pollicis longus. The tendons do not lie freely in these sheaths, but are connected to them by synovial processes, which play the role of the previously mentioned mesenteriolum (Braus) for the tendon; the vessels nourishing the tendon lie within them. In suppurative tendovaginitis, the vessels of these mesenteriola can become occluded and thereby cause necrosis of the tendon. - On the dorsal side of the fingers, the skin is very mobile and, except for the nail phalanx, is often provided with hairs. Above the middle phalangeal joint, concentric folds are noted (Figure 11), which take the form of dimples in well-fed people. The subcutaneous tissue is poor in fat; beneath it lies the aponeurosis of the extensor tendon, which receives support from the tendons of the lumbrical and interosseous muscles. The aponeurosis is divided into a middle broad one, attached to the second phalanx, and two lateral narrow ones, attached to the third phalanx. A thin layer of tissue is located above the periosteum, and below the periosteum is the bony mass. - The nail represents a horny plate on the dorsal side of the distal phalanx of the fingers, having in man only a protective function (see Nail). - The thumb, according to its functional significance and its structure, presents many features in comparison with other fingers (Figures 9 and 12). While all 5 fingers together have 18 short muscles and 18 tendons of long muscles, the thumb alone has 8 (Braus). It possesses the freest movements and the greatest strength of all the fingers;

Figure 11.
the scope of its movements is so great that it freely comes into contact with the palmar and partly with the dorsal sides of the remaining fingers. Such a scope of movements is caused by the presence at the base of the thumb between the metacarpal and carpal bones of a saddle-shaped joint (Figure 13). The vascular system of the hand is distinguished by a multitude of anastomoses between the major arteries, having the appearance either of arches from which small vessels depart, or of vascular networks located around the main articulations, predominantly the carpal ones. It is obvious that without such a device, with the almost continuous action of the hand and fingers, a circulatory disorder could take place. On the other hand, this multiplicity of anastomoses is the reason for the difficult cessation of bleeding. Art. Figure 12. Little finger: 1 - radius; 2 - distal epiphysis; 3 - radiocarpal joint; 4 - lunate bone; 5 - intercarpal joint; 6 - capitate bone; 7 - carpometacarpal joint; 8 - fifth metacarpal bone; 9 - palmar side; 10 - bone marrow; 11 - epiphysis, cartilage; 12 - distal epiphysis; 13 - trochlea; 14 - fatty fold; 15 - metacarpophalangeal joint; 16 - collateral ligament; 17 - accessory volar ligament; 18 and 21 - interphalangeal joints; 19 - accessory volar ligament; 20 - nail tuberosity; 21 - epiphyseal cartilage. Figure 13. Thumb: 1 - radius; 2 - radiocarpal joint; 3 - scaphoid bone; 4 - intercarpal joint; 5 - greater multangular bone; 6 - carpometacarpal joint; 7 - epiphysis; 8 - metacarpal bone; 9 - bone marrow; 10 - sesamoid. Figure 1.
na bone; 11 - main joint; 12 - nail phalanx of the thumb. Arteria radialis (radial artery) at the wrist passes to the back of the hand below the attachment of m. supinator longus, but first gives off a superficial branch for the palm, running above the small muscles of the thumb and directly under the fascia fusing with the end of the trunk of arteria ulnaris, forming the superficial palmar arch (arcus volaris superficialis). The trunk of the radial artery passes to the back of the hand and lies between the tendons of m. extensor pollicis longus et brevis and then passes again to the palm between the first and second metatarsal bones and, fusing with the deep branch of the ulnar artery, forms the deep palmar arch (arcus volaris profundus). From the dorsal part of the radial artery three digital branches depart: for both margins of the thumb and the radial margin of the index finger. The continuation of the trunk of the radial artery onto the palm is also called the deep palmar branch (ramus volaris profundus arteriae radialis). From it, before the formation of the arch, the first metacarpal artery emerges (arteria metacarpea volaris I); it gives off palmar digital branches along the margins of the thumb and along the radial margin of the index finger. — Arteria ulnaris, the ulnar artery, gives off one branch on the hand to the dorsal arterial network of the metacarpus (ramus dorsalis arteriae ulnaris); from it emerges a branch to supply the ulnar margin of the little finger. At the radial margin of the pisiform bone, the ulnar artery divides into superficial and deep palmar branches. The first forms the superficial arch with the superficial palmar branch of the radial artery; the second, penetrating into the depth of the palm, fuses with an arch with the deep palmar branch of the radial artery (arcus volaris superficialis et profundus). The participation of the ulnar artery in the formation of the superficial palmar arch is much more significant than that of the radial artery. The arch is often formed in another way. The beginning of the palmar arch is covered, besides skin and fascia, also by fibers of m. palmaris brevis, and the continuation — only by skin and fascia. — From the convex part of the arch emerge three common palmar digital arteries (arteriae digitales volares communes). Each of them divides into two palmar digital arteries running along the palmar sides of two fingers. These arteries anastomose at the joints of the finger bones, forming an arch at the ends of the fingers. — The deep palmar arch is formed predominantly by the deep branch of the radial artery, which is thicker than the deep branch of the ulnar artery. From this arch four palmar interosseous arteries originate, which fuse with the common digital arteries. Before this connection they give off perforating branches (rami perforantes) running backward to the dorsal metacarpal arteries. — The dorsal carpal network (rete carpi dorsale) is composed of the dorsal branches of the radial and ulnar arteries. From this network emerge three dorsal interosseous arteries (arteriae metacarpeae dorsales II–IV). These arteries divide into two branches to supply the mutually opposite margins of two fingers. — Veins of the hand and fingers. The beginning of the venous system is made up of digital venous plexuses: the vein of the thumb (vena cephalica), running along the dorsal side of the thumb and from there along the radial margin of the forearm; the vein of the little finger (vena basilica), the beginning of which is located near the little finger, whence it is directed to the ulnar margin of the forearm. On the dorsal side there is a fairly significant plexus of veins merging into a large venous trunk. — Lymphatic vessels are divided into superficial and deep. The former lie on the palmar and dorsal sides of the fingers and hand, converging predominantly on the anterior surface of the forearm, where they form plexuses in the elbow bend. The deep ones also anastomose with the superficial ones, predominantly in the elbow bend, where they pass through deeper-lying glands. Nerves of the hand and fingers. Nervus medianus (median nerve) reaches the hand between the superficial and deep flexors along the midline of the forearm (which is why it is called the median nerve); it supplies all the flexors of the hand and fingers, with the exception of m. flexor carpi ulnaris, as well as m. palmaris longus and both pronators (teres et quadratus). The palmar branch of the median nerve separates from the main trunk near the lower third of the forearm and is lost in the skin of the hand (palm). — Common palmar digital nerves I–IV. They constitute the termination of the median nerve trunk itself and supply nerve twigs to all the muscles of the thenar, as well as the skin on the radial palmar margin of the thumb. The 2nd, 3rd, and 4th palmar digital branches of the median nerve supply on the palmar side both sides of the thumb, the II, III, and the radial margin of the IV fingers. The nerves of both sides at the end of the finger connect and form terminal loops. For details, see Medianus nervus. — Nervus ulnaris (ulnar nerve). Near the metacarpus the ulnar nerve divides into dorsal and palmar branches. The first (ramus dorsalis manus) passes to the back of the hand at the very metacarpus under the tendon of m. flexor carpi ulnaris, supplies the skin at the ulnar margin of the back and usually gives three branches: dorsal digital nerves, which supply both sides of the little finger, the IV and the ulnar side of the middle finger, the skin and tendinous parts of the 1st and the upper part of the 2nd finger joints (phalanx prima). — The palmar branch of the ulnar nerve divides near the pisiform bone into superficial and deep branches (rami volares superficialis et profundus). The superficial branch sends nerves to supply the fingers not covered by the median nerve (the little finger and the ulnar margin of the IV finger) and further anastomoses with the 4th palmar branch of the median nerve. The deep branch penetrates into the depth of the palm between the abductor and flexor muscles of the little finger, runs in an arched fashion under all the tendons flexing the fingers, supplying the muscles of the little finger, the interosseous muscles, and ends in the adductor muscle of the thumb, i.e., supplies all those muscles that are not innervated by the median nerve. For details, see Ulnaris nervus. — Nervus radialis (radial nerve). For the hand and fingers, the superficial branch of the radial nerve is of significance, passing below the middle of the forearm to the dorsal surface between the long supinator and the radius. Here it bears the name of the dorsal branch of the radial nerve and, having given branches to the thumb, anastomoses with the dorsal branch of the ulnar nerve and with the musculocutaneous nerve. After this it gives the dorsal digital branch to the radial margin of the thumb, the dorsal digital branch to the mutually opposite margins of the thumb and index finger, and the dorsal digital branch to the same margins of the II and III fingers. For details, see Radialis nervus. — On the main branches of the median and ulnar nerves on the palmar surface of the hand and on the fingers there are terminal nerve corpuscles, so-called Pacinian corpuscles; on the dorsal side of the hand and fingers they are absent.
R. Hertzenberg. Pathology of the Hand. Congenital deformities. A relatively rare deformity is congenital giant growth of the entire hand or its individual parts. It extends either to all elements of the hand (bone skeleton and soft tissues) or is expressed by the excessive overgrowth of some single tissue. Most often this concerns the excessive development of adipose tissue throughout the hand or in its individual parts. Sometimes it is accompanied by hyperplasia of the nervous and vascular apparatus. With this latter type of deformity, the excessive growth of soft tissues continues even after birth by the type of growth of neoplasms. In order to stop further overgrowths, one can try to stop the process by bandaging the hand. But this rarely helps, and in cases where the deformity interferes with the function of the hand, surgical intervention should be resorted to, which should consist, depending on the case, of either the hand
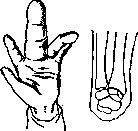
Figure 14.
Figure 15. in the removal of only excess tissue or in the amputation of fingers and even the entire hand, especially in tumor-like proliferation of blood and lymph vessels. In the giant growth of individual fingers (Fig. 14), either their amputation or their surgical removal is indicated, partly for cosmetic purposes, but mainly to improve the function of the hand. Congenital deviations in the structure of the hand skeleton can be divided into the following groups: an excessive number of individual rays of the hand, the presence of defects in the skeleton, and congenital irregularities in the position of fingers. The first group is characterized by an excess of metacarpal bones and fingers (see Polydactyly). Deformities with skeletal defects of the hand are encountered comparatively often and, according to the degree of damage, can in turn be divided into several subgroups: 1) the mildest degree of damage—shortening of one or several fingers with a normal number of their bone elements; 2) shortening of the fingers due to the loss of one or the other phalanx; 3) absence of one or several fingers in the presence of metacarpal bones; 4) absence of fingers along with the corresponding metacarpal bones; 5) complete absence of the hand. In addition, various combinations of the indicated forms are encountered. In the complete absence of the hand, which is very rare, the matter comes down to the complete absence of fingers and metacarpal bones. The wrist, however, although in a rudimentary state, is usually preserved (Fig. 15). The absence of several fingers along with a defect of the corresponding metacarpal bones often forms the so-called fork-like cleft hand, compared to a crab's claw. With this deformity, only parts of the thumb and little finger are present, while the middle fingers are absent (Fig. 16). Sometimes on the ulnar side, the ring finger is preserved, usually in such cases intimately fused with the little finger. Much more often than the aforementioned deformities, syndactyly is encountered (see).--The causes of the occurrence of hand deformities still remain unclear. The role of scarring bands by cords in the amnion should be considered very modest. Traces of such bands are noted in only a small percentage of deformities and are easily noticeable in the form of scars on stumps in finger defects and in some cases of syndactyly. The occurrence of most other, often complex deformities cannot be attributed to amniotic bands, as for example in cases of the absence of basic or middle phalanges in two-phalangeal fingers. The occurrence of deformities should be attributed to the earliest periods of embryonic development. Féré and a number of other authors attach great importance to the origin of deformities in parental syphilis and alcoholism.--The treatment of the above-described hand deformities is limited to the removal of excess and giant fingers and the elimination of syndactyly (Fig. 17). Hand injuries are very diverse and complex and usually affect a whole complex of its individual elements (bones, muscles, nerves, etc.). When planning treatment, one has to take into account the damage as a whole, taking into account the features of damage to individual parts and their interrelation.--Injuries to the carpal bones are rarely isolated. In view of the insignificant size of individual bones, their tight connection by the ligamentous apparatus into one common mass, and the concomitant damage to soft tissues, it is often difficult to make a local diagnosis without an X-ray examination. The pisiform bone and scaphoid bone are subjected to isolated fractures more often than other carpal bones. Usually these are indirect fractures when falling onto the hand in a position of dorsal flexion. With direct violence, fractures are observed simultaneously in the capitate, hamate, and lunate bones. Fracture of the scaphoid bone, in view of its proximity to the radius, is often combined with a fracture of the latter. In order to preserve joint function in fractures of the carpal bones, it is recommended to start massage and movements early in combination with measures that increase resorption processes (hot baths). Fractures of the metacarpal bones are observed somewhat more often. Like most traumatic injuries, fractures of these bones are less common in women than in men. Fractures occur most often as a result of direct violence, during a blow, push, gunshot wound, or when falling on the back of the hand, when bending of the metacarpal bones towards the palm is possible. Fractures from indirect violence are observed when falling on a hand clenched into a fist, when the push acts in the direction of the axis of the hand against the metacarpophalangeal articulation. Statistics (Le Dentu) indicate that fractures due to direct violence are more common. In most cases, fractures are oblique under the action of indirect force and transverse under direct violence (blow). Displacement of fragments is not often noted, and if it does occur, the fragments usually stand at an angle with the apex facing the dorsal surface of the hand. Lateral displacements are rarer. In the treatment of closed fractures with displacement, one should first of all bring the fragments into the correct position by traction on the corresponding finger and pressure on the site of the fracture and fix the achieved contact of the fragments with an immovable bandage for 2-3 weeks. Subsequent treatment consists of massage and the application of heat. Resorption of the bone callus and restoration of hand function is observed only after a long period (up to 6 months).
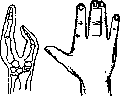
Figure 17. The mechanism of occurrence of fractures of the phalangeal bones is the same as that of the metacarpal bones. Phalangeal bones are also much more often broken by direct violence than by indirect. The method of treatment is the same. In open fractures (e.g., gunshot fractures), initially the matter comes down chiefly to the prevention of infection or to the fight against infection complicating the injury; therefore, the healing period of the fracture itself is significantly longer. In complicated fractures, the matter frequently ends in insufficient consolidation (fibrous) or its complete absence. If it is a question of a single metacarpal bone (except the first metacarpal bone), the resulting pseudarthrosis does not very greatly impair the function of the hand. With pseudarthrosis of all metacarpal bones or the first metacarpal bone, a significant impairment of function occurs, and surgical intervention becomes necessary to achieve consolidation of the ununited fractures. The severity of open fractures also consists in the fact that the consequences of infection and soft tissue injuries are added to the defects of consolidation. As a result, defects are obtained not only in the bone skeleton, but also in the tendons, muscles, and scar changes in the corresponding areas of the skin. Often the hand is so disfigured that it becomes completely incapacitated. Fractures near articular surfaces frequently lead to ankyloses. After a long period, when it is possible to consider the infection eliminated, surgical treatment can be undertaken in order to restore the bone skeleton, but treatment is hindered thanks to soft tissue injuries. The impossibility of making up for losses in muscle tissue, replenishing defects in nerve branches and tendons often makes the task of restoring hand function insoluble. Dislocations of individual carpal bones are rare and recognized even less often. Most frequently observed are dislocations of the pisiform bone and navicular bone. Dislocations in the dorsal direction are produced by forced flexion or by a fall onto a flexed hand. Dislocations in the palmar side occur with violence in the opposite direction. In fresh cases, reduction is possible. For this, with palmar displacement, it is necessary to produce maximum extension, and with dorsal displacement, strong palmar flexion. At the same time, by pressure on the displaced bone, it must be forced to take up its normal position. But in view of the fact that dislocations of the carpal bones are recognized late, non-bloodless reduction is not always successful, and one has to resort to surgical intervention. Cases of metacarpal bone dislocations are also rare thanks to their firm connection with the carpal bones. Most frequently observed is dislocation of the first metacarpal bone. The characteristic violence in the occurrence of these dislocations is excessive palmar flexion with simultaneous adduction. Dislocations in the metacarpophalangeal and interphalangeal joints are encountered more often (6.7% of all dislocations according to Krönlein), with dorsal displacement usually observed. Displacement to the palmar side is rarer. In recognition, differentiation should be carried out with a fracture of the head of the metacarpal bone or the base of the phalanx. Reduction is accomplished without great difficulty with the help of hyperextension in dorsal displacement and hyperflexion in palmar displacement. Of the finger dislocations, the dorsal dislocation of the thumb is observed more often than others. It occurs with excessive extension of the finger and begins with rupture of the articular capsule on the palmar side. The head of the metacarpal bone emerges through the formed gap onto the palmar surface between the bundles of the short flexor. The lumen of this gap decreases thanks to the contraction of the short flexor. The degree of displacement of the sesamoid bones characterizes, according to Farabeuf, the severity of the injury itself. In incomplete dislocation, they lie on the articular surface of the metacarpal bone; in complete dislocation, they are displaced to the dorsum; in complex dislocation, they lie between the articular surfaces. In this case, the tendon of the long flexor usually slips onto the inner surface of the head of the metacarpal bone and can become trapped at the place of transition of the head into the neck. The position of the thumb in dorsal dislocation is perpendicular in relation to the metacarpal bone in the initial period and parallel to the metacarpal bone if subsequent flexion of the finger followed. Upon palpation on the palmar surface, the spherical head of the metacarpal bone is determined, and on the dorsal side, the base of the phalanx. Obstacles to reduction can be the sinking between the articular surfaces of the ruptured capsule with the sesamoid bones and the entrapment of the head of the metacarpal bone by the tendon of the long flexor. Reduction begins by pulling the thumb forward in the direction that the finger took after the dislocation. Then, strong extension of it is applied to bring the dorsal edge of the phalanx closer to the dorsum of the metacarpal bone while simultaneously flexing the nail phalanx to relax the long flexor. In case of failures of bloodless reduction, surgical intervention is recommended, which consists in removing the obstacles to reduction by eye (it is often necessary to remove the sesamoid bone). In old cases, reduction is often successful only after resection of the head of the metacarpal bone. After reduction by one means or another, it is necessary to start movements in the joint in the coming days. Dislocations of the thumb to the side of the palm are a very great rarity. In addition to injuries to individual systems of the hand, complex injuries with a violation of the integrity of bones, tendons, vessels, and nerves are often observed. Such injuries are very diverse and range from single incised wounds of the superficial layers of soft tissues to severe macerations with detachments of parts of the hand. Often in the first hours after injuries in severe cases, it is difficult to recognize the degree of loss of tissue viability and to draw a boundary between dead tissue and living. Hand wounds are easily infected; infection gets in both from the skin of the hands and from the objects causing the injury. In addition to eliminating the dangers of infection for the entire organism, the treatment of hand injuries should be planned in such a way as to preserve the maximum function of the hand. Not only gross injuries affect the function of the hand, but also lighter ones limited only to the skin and subcutaneous tissue. Simple skin scars at the ends of the fingers, especially on their palmar surface, reduce finger function due to loss of sensitivity and tactile ability and due to pain in these scars. Further, open and closed tendon injuries impair finger function. In closed injuries, tendon ruptures (more often extensors) usually occur at the site of their attachment and arise with maximal flexion of the terminal phalanx. Open injuries can be observed in any place in case of incised and stab wounds. In order to preserve finger movement, shortly after the injury, upon refreshing the ends, the integrity of the tendons should be restored by suturing according to the methods of tendon plasty. In case of finger detachments with exposure of bones, their stumps should be urgently treated in such a way as to preserve the maximum working capacity of the hand. Special care should be observed in relation to the thumb in order to preserve the gripping function. When amputating fingers, it should be kept in mind that the stump after disarticulation in the interphalangeal joints, as it atrophies, turns into a protruding pointed process that is easily traumatized. Therefore, it is more rational to perform amputations than disarticulation, preserving the mobility of the basal part of the phalanx. Severe consequences of hand injury include contracture and stiffness or immobility of the fingers. Such a hand is obtained as a result of the destruction of tendons, their scarring, bone and fibrous ankyloses in the finger joints (see Contracture). Extensor contracture may not capture all fingers, but only some. In the latter case, these sticking out fingers with the normal function of the rest extremely complicate the work of the hand, and their removal usually improves hand function. Flexor contracture to a somewhat lesser extent reduces the work of the hand, since with a flexed hand one can carry small weights. Frequently contractures form after prolonged maintenance of the hand in immovable bandages. Therefore, during the treatment period for prophylactic purposes, passive and active movements of the fingers should be started as soon as possible. Ankyloses in the wrist joint disrupt the work of the hand to a greater or lesser extent depending on the position of the hand in relation to the forearm. The most advantageous position of the hand is in extension, and the least advantageous is ankylosis in the position of flexion. One has to fight the tendency to this during the treatment period, since patients usually hold the affected hand in a flexed position. Diseases of the hand. The skin of the hand is the site of development of very many diverse diseases; boils, anthrax carbuncles, eczema, Pendjeh ulcer, lupus, burns, chilblains, warts, corns, and many others are observed here. More often than other diseases on the hand, purulent inflammatory processes are encountered, which can be localized in individual elements of the hand or can simultaneously spread to many systems (skin, subcutaneous tissue, tendon sheaths, nerves, bones). Purulent inflammations are most often observed in the fingers (see Panaritium).
Panaritiums often serve as a source for the development of purulent processes in other parts of the hand. Phlegmons of the hand from a clinical standpoint should be divided into 2 groups: superficial and deep. The former develop superficial to the palmar aponeurosis, while the latter develop beneath it. Superficial phlegmons may arise from a superficial skin injury or without it, primarily in the subcutaneous tissue. Clinical symptoms consist of pain and elevated temperature. Due to the thickness of the skin and its low compliance, the inflammatory swelling does not reach significant proportions quickly. The abscess approaches the superficial layers of the skin most often in the area of the interdigital fold and from this area can pass from the palm to the dorsal surface, where in such a case a significant inflammatory edema appears very quickly. Soon, swelling of the regional lymph nodes in the elbow crease and in the axillary region appears. The entire hand becomes edematous and very painful. The fingers assume a flexed position. In contrast to deep phlegmons (beneath the aponeurosis), finger movements remain possible and painless. Treatment consists of opening the purulent accumulations. Phlegmons developing beneath the palmar aponeurosis are a severe disease. The usual pathway for their occurrence, apart from deep wounds, is purulent inflammation of the tendon sheaths. Pains due to the inflexibility of the palmar aponeurosis and the abundance of nerve endings are very severe. Movement of the fingers is impossible. The purulent process involves the tendon sheaths from the very beginning, through which pus can penetrate into the forearm, causing the formation of a deep phlegmon there as well. In cases where the evacuation of the abscess is not done in a timely manner, purulent melting of the interosseous muscles occurs and pus penetrates to the dorsum of the hand. Under these same conditions, involvement of the joints of the hand in the suppurative process is possible. In order to localize the process, it is necessary to provide an outflow for the pus in a timely manner. In view of the fact that the palmar aponeurosis does not provide the necessary space for the wound tract, it is rational in most cases to make a counter-opening on the dorsum of the hand and conduct treatment with through-and-through drainage. In the postoperative period, the possibility of subsequent hemorrhage from the arteries of the hand, the walls of which may also be ulcerated by the septic process, should be kept in mind. The consequence of a deep phlegmon is impairment of hand function caused by shrinkage of the palmar aponeurosis, cicatricial adhesions of the tendons and their sheaths, and subsequent neuritis caused by infection and cicatricial shrinkage of the surrounding connective tissue. For prophylactic purposes, it is necessary during the treatment period to early apply movement of the hand and its fingers with the simultaneous prescription of heat treatment. Isolated purulent inflammations of the tendon sheaths are characterized by elevated temperature and painful swelling along their extent. Treatment should consist of opening the tendon sheaths with evacuation of the pus. In cases of purulent melting where the process has reached the stage of necrosis, necrotic areas of the tendons should be removed. The inflammatory process in the tendon sheaths may have a chronic course, mainly in specific infections (tuberculosis, syphilis), and sometimes after trauma. In tuberculous lesions, different patho-anatomical forms can be distinguished: either in the form of a serous effusion, often with the presence of rice bodies (see), or in the form of fungous proliferations. In serous forms, the elongated swelling extends to the transverse carpal ligament, passes beneath it, and rises higher. At the level of the transverse carpal ligament, a constriction is formed between two bag-like fluctuating swellings, with the fluctuation being transmitted from the upper accumulation to the lower one and vice versa. In non-tensed bags, it is sometimes possible to palpate rice bodies that move freely or hang by a stalk. In the fungous form, the disease appears as a localized lesion of pasty consistency. Benign-running serous forms sometimes pass into severe fungous ones. In serous forms, good results are obtained from treatment with immobilization and injections of iodoform emulsion. In fungous forms, one has to resort to injections of a stronger irritant in the form of a glycerin emulsion of camphor-naphthol (1:5). Simultaneous or subsequent treatment with the sun or a mercury-quartz lamp leads in the end result to satisfactory hand function. Syphilitic lesions are usually observed in the form of chronically running serous forms, do not reach large volumes, and do not impair hand function. Differential diagnosis with tuberculosis is facilitated by the presence of other manifestations of syphilis. Treatment is specific. A characteristic lesion of the tendon sheaths is so-called tenosynovitis crepitans, usually observed in the sheaths of the extensor tendons of the fingers and expressed by swelling, pain, and a characteristic crepitation sound upon movement of the tendons. The pathogenesis of this disease is associated with overwork of the fingers, mainly in people unaccustomed to this or that form of labor. This disease is frequently encountered in laundresses, dishwashers, carpenters, etc. It is generally accepted that in tenosynovitis crepitans, fibrin deposition occurs on the inner surface of the tendon sheaths, from the friction of which during movement crepitation results. The studies of Küttner and Frisch have detailed the patho-anatomical picture of this disease and established that crepitation is observed not in those areas where the tendon is enveloped by the synovial sheath, but where it, devoid of a sheath, passes among loose connective tissue. This tissue is divided into two leaves with delicate connective tissue crossbars between them. This tissue was named paratenon by Mayer. With excessive labor, a process of exudation and deposition of fibrin occurs in the slits between the leaves of the paratenon. Therefore, Hauck proposes replacing the old name tenosynovitis crepitans with another—paratendinitis crepitans. Treatment in the acute stage of this disease should consist of rest; subsequently—treatment with heat and massage. Prophylaxis with respect to recurrences consists of metered, not very strenuous labor. The bones and joints of the hand are subject to the same diseases that affect other areas of the body. The joints of the hand are frequently affected in rheumatism; in severe cases (deforming polyarthritis), the hand assumes characteristic outlines. The interphalangeal joints are disfigured by nodular thickenings; in the metacarpophalangeal and radiocarpal joints, the hand deviates in the ulnar direction partly due to subluxation in these joints, partly due to displacement of the extensor tendons in the ulnar direction and shortening of the corresponding muscles. As a result of the indicated displacement with simultaneously developing muscle weakness, the disfigured hand becomes disabled. The disease is more frequently encountered in middle and old age (see Rheumatism). Severe disfigurements of the hand respond poorly to regression and are more often irreparable. Gouty lesions of the hand are encountered quite frequently. Chronic forms are observed in the form of recurring joint pains, often with nodular deposits of salts in or near the joints. In far-advanced cases, the hand is disfigured by persistent thickening of the joints with deviation of the fingers in the metacarpophalangeal joints in the ulnar direction. In treatment, anti-gout therapy should be carried out (see Gout). Exacerbations are expressed by the appearance of significant pain, swelling, and redness of the joints without involvement of the regional lymphatic pathways. Relatively rare in the hand are osteoarthropathies in tabes and syringomyelia. Of other lesions of a trophic character, diabetic and spontaneous gangrene, causalgia, and acromegaly should be pointed out. Frequently encountered and still remaining unexplained is a trophic disorder characteristic of the nail phalanges in the form of their club-shaped swelling, so-called clubbed fingers (see). Of infectious lesions, tuberculosis of the metacarpal and phalangeal bones in the form of so-called spina ventosa presents characteristic features. The disease is encountered mainly in childhood and adolescence and is expressed by painless swelling of this or that

Figure 18
other phalanx (Fig. 18). Soft tissues surrounding the affected bone are often edematous with areas of redness. The swelling usually has an elastic consistency, sometimes with areas of softening. The pathological anatomy picture is expressed in the involvement of either the diaphysis or epiphysis of the bone and consists in the gradual disappearance of the spongy part of the bone and its replacement by granulation tissue impregnated with pus. The cortex together with the periosteum is pushed apart by the granulation tissue proliferating inside the bone. The foci of lesions are distributed depending on the topographical features of the blood supply to the bones and usually occur where bone arteries have the character of end arteries. Therefore, in the metacarpal bones, foci of tuberculosis are more often found in the peripheral ends of the diaphyses, while in the phalanges they are found in the central ones. In rare cases, the process begins in the periosteum upon blockage of a tubercular embolus of a periosteal vessel, and from here the process can secondarily spread to the bone. With prolonged progression of the disease, disfigurements of the affected bone may occur, expressed in its curvature and shortening. (According to the latest research by Kozlovsky, spina ventosa appears as a staphylococcal osteomyelitis, to which in the course of the further development tuberculosis infection may join hematogenously.) Treatment is performed according to the methods of conservative treatment of bone tuberculosis in general (care for nutrition, hygienic dwelling, sun, quartz lamp, etc.). Surgical intervention should be as conservative as possible, sparing the growing young bone (removal of small sequestra and scraping of the bone cavity). Impairment of hand functions can be caused by the formation of contractures after injuries and diseases. Elimination of contractures often presents great difficulties. Therefore, in the treatment of the affected hand, preventive measures against their formation should always be taken. Contracture of the hand and its fingers is often formed due to yielding skin scars after injuries, superficial inflammations, burns, and the like. Prevention of such deforming consists of early initiated movements. If there is a threat of skin contractures forming in the palmar direction, it is necessary to keep the hand in a position of extension and vice versa. With dense skin scars, good results are observed from treatment with heat, especially diathermy, mud poultices, as well as iontophoresis with 1-2% potassium iodide, and when ionizing through mud, especially in combination with mechanotherapy. With prolonged failure of conservative treatment, surgical intervention should be tried, which can be diverse depending on the features of the individual case. In general, the operation should consist of excision of scars and replacement of the resulting defect with skin plastics in the form of transplanting skin flaps on a pedicle (Italian plastics or by Filatov) or in the form of free transplantation according to Thiersch. Contractures caused by disruption of tendon integrity can be very diverse. The tendon may be restricted in its movement by abnormal adhesion to underlying tissues, shortened by shrinking after suppuration, or destroyed over various extents by trauma. In such cases, surgical intervention should restore either the possibility of tendon movement or its continuity. In cases where the ends of the tendons have diverged, to bridge the defect, one can use plastics with the formation of pedicle flaps (Fig. 19) or transplant a piece of tendon or fascia lata, which is attached to the diverged ends by sutures. Regarding contracture caused by shrinking of the palmar aponeurosis, see Dupuytren's contracture. A severe disease is the so-called Volkmann's ischemic contracture. This contracture is believed to be the consequence of insufficient blood circulation when holding the limb in tightly applied immovable dressings. If the arterial blood supply due to the pressure of the dressing is significantly reduced, but not enough to lead to gangrene, the contractile substance of muscle fibers sparsely supplied with blood clots, and the matter ends with their scar-like change. Usually, flexors suffer more than other muscles. The sclerosing process affects the muscles not entirely, but in the form of separate nests scattered among healthy muscle areas. Symptoms of ischemic contracture appear soon after the application of the dressing and consist of severe pain, edema in areas free from the dressing, and cyanosis. The hand, freed from the dressing, assumes a characteristic position with heavily bent fingers except for the thumb, which usually remains in a position of extension. At the same time, there is a decrease in skin sensitivity while maintaining muscle electrical excitability. Treatment begins with the removal of the dressing and consists of measures aimed at increasing the blood supply to the affected limb: heat, massage, movement on special apparatus for straightening the fingers. Changes in the hand with lesions of the central and peripheral nervous system see Median nerve, Radial nerve, Ulnar nerve. Working capacity is significantly reduced in so-called occupational cramps. These cramps are observed in individuals whose work consists of prolonged

Figure 19.
monotonous minute movements of the hand: in writers, typists, tailors, violinists, pianists, etc. In this disease, only one specific type of movement associated with the profession is disrupted. All other types of movements are performed freely by the patients. The cramps are expressed as either tonic or clonic muscle spasms. Due to this, during writer's cramp, the patient exhibits extraneous movements in the form of tremor, twitchings; letters turn out irregular and disfigured. Sometimes, instead of cramps, only rapid fatigability and pain in the arm are noted. Pain occurs shortly after the start of work and is so severe that the patient loses the ability to make the slightest movement. Sometimes pain or cramps appear even when attempting to fold the fingers in the manner required for holding a pen, bow, etc. The cause of occupational cramps should be considered fatigue of the neuromuscular apparatus functioning during the given work. It should be noted that such patients usually exhibit symptoms of neurasthenia. It is possible that occupational cramps arise more easily in individuals with generally reduced stability of the nervous system. The disease often drags on for a long time, and after periods of improvement, relapses are frequently observed. Treatment consists primarily of a prolonged rest from the work that causes the cramps. Next, a general strengthening regimen is necessary to eliminate neurasthenia. Of the local remedies, massage of the arm from the hand to the brachial plexus and galvanization are recommended. For writer's cramp, various apparatuses are used that hold the fingers during the act of writing. Neoplasms. All kinds of neoplasms that are observed in other areas of the body are found on the hand and fingers. For some types of neoplasms, the hand is a favored site of origin. Such neoplasms include ganglia, enchondromas, and epithelial traumatic cysts. Enchondromas much more frequently affect the phalanges than the metacarpal bones. Often these tumors are multiple and reach very large sizes (the size of a child's head). In the initial stages of tumor development, the phalanx appears swollen and resembles spina ventosa in shape. With further growth, destruction of the cortical layer of the bone occurs, and the enchondroma continues to grow in the soft tissues. The consistency of the tumor is usually hard; only in late stages, especially in the stage of malignant degeneration into chondrosarcoma, does the tumor become softer. In this same stage, the enchondroma acquires an infiltrating character of growth. Enchondroma most often develops at a young age and grows very slowly over many years. Treatment is surgical. When there is certainty of the absence of malignant degeneration, the operation can be limited to the removal of only the tumor; with incomplete removal, recurrences are possible. If degeneration is suspected, the entire affected bone is removed. On the palmar surface of the hand and on the flexor side of the fingers in adults, mainly in men, small rounded tumors resembling atheromas are found. The skin over such tumors is mobile and usually bears a trace in the form of a scar from a previously sustained injury. The wall of the tumor consists of connective tissue and is lined from the inside by squamous epithelium. The occurrence of such cysts is associated with the introduction of pieces of skin inward during trauma. Treatment is surgical removal. Angiomas, fibromas, neuromas, atheromas (exclusively on the dorsal surface), sarcomas of all kinds, and cancers are also found on the hand. The latter are observed most frequently on the dorsal surface of the hand and originate either from the covering epithelium or from the epithelium of the skin glands. Osteomas and cartilaginous exostoses are not very frequent on the hand and are of clinical interest only in cases where, due to their size, they interfere with the function of the hand or when pain sensations are caused as a result of their compression of nerve twigs. Treatment for these tumors consists in their surgical removal. Operations on the hand. Ligation of the superficial palmar arch is done through an incision in the middle of the palmar depression, intersecting the middle palmar crease. After dissection of the skin and subcutaneous tissue, the superficial aponeurosis is incised in the same direction along a grooved probe, beneath which lies the superficial palmar arch. Disarticulation at the wrist joint with a palmar flap according to Farabeuf. The palmar flap is fashioned so that its width is equal to the width of the palm, and its greatest length lies on the axis of the III finger, at the level of the bases of the metacarpal bones (Fig. 20). The incision is made in a wide arc from the radial styloid process to the ulnar. On the dorsum of the hand, the incision is made 1 cm below the joint line. The skin flap is dissected, the tendons on the dorsum of the joint are cut, and then the joint itself is opened; when the latter is opened and the palmar part of the capsule is severed, the flexor tendons are cut. The ulnar, radial, and interosseous arteries are ligated. The median, ulnar, and radial nerves are resected. In order to prevent muscle atrophy, the flexor tendons are sutured to the extensor tendons. Disarticulation of the thumb together with the metacarpal bone. The incision begins 2 cm below the styloid process, and is led along the dorsal surface of the I metacarpal bone to its middle.

Figure 20. Incisions for exarticulation of the hand: aaa - formation of the palmar flap; bbb - formation of the ulnar flap.

From here, the incision turns in an arc toward the ulnar side and at the base of the I phalanx passes to the palmar surface, goes there along the palmo-digital crease and from the radial edge of the latter along the dorsum of the metacarpal bone reaches the starting point of the lateral incision. The incision is deepened, the flaps are separated, including all the muscles of the thenar in the composition of the palmar one. Having exposed the joint region, the finger is disarticulated. Disarticulation of the II, III, IV, and V fingers simultaneously. Two incisions are made: on the dorsum, the incision goes along the heads of the metacarpal bones; on the palm, along the palmo-digital crease. At the lateral edges of the palm, the incisions converge. The palmar flap is separated up to the level of the heads of the metacarpal bones, the dorsal flap is separated upward, and the fingers are disarticulated one after another. The finger being disarticulated is flexed toward the palm, the dorsal part of the capsule is cut, the finger is deflected to the right, the left collateral ligament is cut, then the palmar part of the capsule, and finally the right collateral. Then they move on to the next finger, etc. (Fig. 21). For the disarticulation of individual fingers, a racquet-shaped incision is used (en raquette); the incision is begun somewhat above the head of the metacarpal bone, led straight down through the head, after which it is deflected to one side and the other toward the palmar surface. Disarticulation is performed as indicated above. Disarticulation in the interphalangeal joints. The joint line is determined by the protrusion formed by the head of the overlying phalanx and noticeable when the finger is flexed. Disarticulation with the formation of a palmar flap is advantageous, which, during disarticulation in the first interphalangeal joint, ends slightly above the head of the middle phalanx; during disarticulation in the second interphalangeal joint, the flap should reach the end of the nail phalanx. Through a dorsal incision, slightly arcuate with convexity toward the end of the finger, one enters the joint, cuts the collateral ligaments, and disarticulates. In the wound, the digital arteries are ligated. Amputations of the metacarpal and phalangeal bones are performed through the same incisions as in disarticulations; only these incisions are made not corresponding to the joint line, but somewhat below the level of the expected
amputation.
Related articles
Cite this page
“Hand.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/hand/