Clubhand
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Great Medical Encyclopedia examines the etiology, pathological anatomy, clinical presentation, and treatment of clubhand (manus vara and manus valga). It details congenital and acquired forms, skeletal defects, soft tissue anomalies, and various orthopedic management strategies.
Encyclopedia article (1928–1936)
CLUBHAND [manus vara and manus valga, Klumphand (Ger.), main botte (Fr.)], deviation of the hand in relation to the axis of the forearm. The deviation of the hand can be volar, ulnar, radial, or dorsal. In the majority of cases, radial-volar or ulnar-volar deformation is observed. Deviation in the dorsal direction is extremely rare. Clubhand is encountered significantly less frequently than, for example, foot deformations in the form of clubfoot, with which clubhand is occasionally combined. Hoffa encountered clubhand once in 1,414 deformations; the data of Panzeri and Fischer approximately coincide with Hoffa's numerical data. Clubhand, just like clubfoot, is more often bilateral and congenital, and in all probability genotypic. However, precise genealogical data exist in very small amounts. Blencke described a case where out of 9 children of healthy parents, four had clubhand. Probably clubhand is inherited as a recessive trait. In rarer cases, it can be acquired. In congenital clubhand, radio-palmar deviation is encountered mainly. All cases of congenital clubhand can be divided into clubhand without skeletal alteration and clubhand with incomplete skeletal development. The first type of clubhand in etiological relation approaches typical clubfoot arising without skeletal alteration, and this type of clubhand is more often observed in the form of palmar or ulnar-palmar deviation. Rosenkranz found approximately 50 cases of clubhand without bone defects in the literature. This sort of clubhand can have as its cause: 1) abnormal position in the uterus; 2) dysplasia of the forearm muscles; Potel draws attention to congenital partial muscular dystrophy; 3) joint dysplasia; congenital rigidity of the wrist joints is usually combined with stiffness of other joints as well. Clubhand in such cases arises not because dynamic factors in the form of muscles partially drop out, but because the development of joints is delayed in a certain embryological phase. Changes in the muscles occur secondarily (Rocher). The main theories of the origin of clubfoot (see) remain valid for clubhand as well, namely: 1) formation of deformation due to mechanical causes (role of the amnion); 2) neurogenic theory; 3) clubhand as a result of vitium primae formationis. While the theory about the role of the amnion can explain a known tenth part of cases of clubhand without defects of the skeletal system, the theory ascribing importance to vitium primae formationis explains the predominant number of cases of clubhand with various skeletal defects. Significantly more often, clubhand has at its base developmental defects of the radius. Data from various statistics (K. Kato, Rabaud, Hovelacque) indicate the predominant frequency of developmental defects of the radius on both sides, in connection with which bilateral congenital clubhand with curvature in the radial direction (manus valga) is more frequently observed. This sort of deviation is encountered in men twice as frequently as in women. Pathological anatomy. With complete or partial absence of the radius, defects on the part of the carpal bones are most often noted simultaneously: absence of the lunate and greater multangular bones, atrophy, underdevelopment, or complete absence of individual phalanges and metacarpal bones, sometimes ankylosis of the interphalangeal articulations. The remaining ulna usually curves. Changes are also noted on the part of the humerus: it is often shortened, there is aplasia of the outer part of the lower epiphysis. All these details are well revealed on the roentgenogram. Anatomical defects in radial deviation are also observed in muscles, blood vessels, and nerves. In muscles, both complete absence of individual groups and absence of differentiation into individual groups are noted, especially on the forearm. Thus, in many specimens carefully studied by Stoffel and Stempel, the biceps muscle had only the short head, while the long head was absent; in some muscles there were variants of muscle origin and defects of differentiation. These defects are explained by a delay in a certain period of embryonic development. The defects in the vascular system are also explained by this: the radial artery is often preserved only in the form of a thin branch of the ulnar artery; changes in the topographical arrangement of other arteries on the shoulder are noted. In connection with the defects of development of the osteomuscular system are innervation defects in patients with clubhand. Attention is drawn to the sharply expressed underdevelopment of the radial nerve, as well as some anomaly in the development of the musculocutaneous nerve. The latter is sometimes absent. Pathological-anatomical changes in deformation of the manus vara type with ulnar and ulnar-palmar deviation present a different picture. In these cases, there is a complete or partial defect of the ulna and often a defect of the carpal bones formed from the ulnar ray. The radius may turn out to be normal, sometimes ankylosed with the humerus, or the head of the radius may be luxated. In the shoulder joint, there is often a limitation of movements; in the elbow joint, complete ankylosis or limitation of movements. The clinical picture of clubhand is very characteristic. Deviation of the hand both in the radial direction (manus valga, figure 1) and in the ulnar direction (manus vara) is usually combined with volar flexion. Simultaneous defects on the part of the carpal, metacarpal bones, and phalanges are frequent, as a result of which the grasping ability of the hand is impaired. With losses of muscles of the shoulder girdle or forearm, noticeable functional disorders are noted. In one case of congenital clubhand in combination with bilateral clubfoot in a 16-year-old girl (observations of Chaklin), the muscles of the shoulder girdle and individual muscle groups of the arm and forearm were paralyzed. Nevertheless, her grasping ability was preserved. Congenital clubhand is sometimes combined with clubfoot (fig. 2); in some cases, other monstrosities are observed: congenital dislocation of the hip, congenital scoliosis,
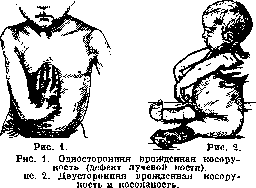
harelip, spina bifida, etc. It should be noted that despite the good adaptability of individuals with congenital defects in general, bilateral clubhand makes the patient more of an invalid than many other deformations, for example, clubfoot.
Treatment of clubhand in its main features has something in common with the treatment of clubfoot. Methods of treatment of clubhand should be chosen depending on whether there is clubhand with a defect in the bone skeleton, clubhand without a bone defect but with expressed contracture of muscles and fasciae, or clubhand on a neurogenic basis. In clubhand with a predominance of muscular or fascial retraction, careful redressing manipulations and massage are indicated. The achieved correction is fixed each time with a splint or a light plaster cast. Orthopedic apparatuses with the possibility of gradual correction in the wrist joint have also been proposed. The apparatus of Redard and Claude Martin is based on correction by elastic tractions. Bloodless manual redressement and staged bandages used for clubfoot give a good result in clubhand as well. If individual tendons present a serious obstacle, tenotomy is indicated. Rocher obtained good cosmetic and functional results by resection of the wrist bones followed by hypercorrection with a plaster cast. Thus, the task of orthopedic therapy in clubhand of the described type consists in correcting the deformation of the hand, acting predominantly on the soft tissues. In clubhand caused by a bone defect, the task of therapy is more complex: not only to correct the deformation, but also to maintain the correct position of the hand in relation
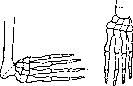
Figure 3. Romano's method.
to the forearm. In early childhood, contracture is corrected by manipulations and massage, and the hand is held in a slight dorsal flexion by means of a leather apparatus until the moment when surgery can be resorted to. Chaklin applied twisting for correcting the deformity in children. There is a series of osteotomies and resections of the ulna for correcting radial and radio-palmar deviation. Osteotomies in the lower third of the ulna, even with soft tissue elongation, do not guarantee against recurrence in the presence of a bone defect. The method of Romano, consisting of wedge resection of the lower third of the ulna with reinforcement of the carpus by a metal or silk suture (Fig. 3), is very convenient. Sayre creates a new joint between the wrist and the ulna by performing a two-stage operation. In the first stage—resection or osteotomy of the ulna with reduction. After several months—the second stage: partial resection of the wrist with insertion of the thinned lower end of the ulna into the defect. Another type of operation consists in replacing the defect of the radius with free bone grafting. Antonelli and Ryerson took a free transplant from the radius, implanting it into the soft tissues at the place where the radius should be, after preliminary correction of the hand. The usual fate of transplants implanted into muscles is resorption, as a result of which such interventions lose practical interest. Albee takes a plate from the tibia for plastic purposes, fixing its upper end in the ulna and its lower end in the carpus (Fig. 4). The fate of such an intervention is more favorable because the transplant fuses with the bone, which is subject to mechanical and functional influences, which consequently extend to the transplant. In all interventions on the hand and forearm, it is extremely important to preserve full freedom of movement of the fingers, which increases the functional effect of the operation. Prolonged wearing of an apparatus that corrects the faulty position prevents recurrence. Like paralytic clubfoot, there is also cubitus varus caused by disorders in the neuromuscular apparatus. A hand deformity of this origin is possible on the basis of both flaccid paralysis (due to damage to the peripheral neuron) and spastic paralysis (damage to the central neuron). In addition, Roche distinguishes another group of cubitus varus based on reflexive contracture. Cubitus varus with signs of flaccid paralysis occurs with traumatic damage to the radial nerve, with obstetric paralysis, and as a consequence of poliomyelitis. Cubitus varus with spastic paralysis is characterized by a tense ulnar-radial position of the hand and often involuntary movements in muscles of athetoid or choreoathetoid type. Spastic cubitus varus can be based on encephalitis suffered in early childhood, as a consequence of Little's disease, and also of hysterical origin. In addition to cubitus varus with radial deviation, there are rarer cases of dorsal deformity of the hand. Such cubitus varus is noted in childhood paralysis (Dejerine, Menciere), in syringomyelia, and in adult hemiplegia. Various hand deformities of paralytic origin, although French authors (Roche) classify them as cubitus varus (main bote), differ sharply from congenital cubitus varus both in etiology and pathological anatomy, as well as in therapy. For the treatment of paralytic cubitus varus, in addition to apparatuses which improve mainly the cosmetic aspect, there is a series of operations aimed at improving hand function. If the flexor group is preserved, it is necessary to set the hand in a dorsal flexion position convenient for function. In such a position, tenodesis of the extensors or arthrodesis of the wrist joint is performed. With good strength of the flexor group, an excellent effect is obtained by transplanting active muscles to inactive extensors and the abductor of the thumb. For this purpose, the methods of Perthes and Stoffel are most suitable. Transplantation of flexors through the interosseous interval is less successful. Of the arthrodesis methods, the method of Albee with transplantation of a tibial transplant to the dorsal surface of the wrist joint is convenient. Interventions on nerves in paralytic cubitus varus have only theoretical significance. For the treatment of spastic cubitus varus, the following methods exist: 1) neurotomy (Stoffel) or alcoholization (Sicard), 2) posterior radicotomy (Forster), 3) ramisectio cervicalis (Royle), 4) hyperneurotization (Spitzy), 5) partial resection (reduction of cross-section) of the median and ulnar nerves (Vreden). Of these methods, neurotomy according to Stoffel is shown for milder cases, posterior radicotomy for the most severe cases. The other methods are in the stage of clinical study. In two severe cases of spastic cubitus varus, Chaklin applied the following method: tenotomy of the palmaris longus muscle, correction of contracture by staged bandages, and then intraosseous tenodesis of the hand extensors. A fully good cosmetic and relatively favorable functional effect was obtained. Summarizing the methods of treating cubitus varus, one can say that in congenital cubitus varus, when function is not particularly disturbed, orthopedic manipulations and operations can achieve a good cosmetic effect and preserve satisfactory function. In flaccid paralytic cubitus varus, especially traumatic, good cosmetic and functional results can be obtained by transplanting active muscles to inactive ones.
Related articles
Mentioned in
Cite this page
“Clubhand.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/cubitus-varus/