Clubfoot
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
Clubfoot is a deformity of the foot with inward rotation and plantar flexion. This article discusses the congenital and acquired forms, their genetic basis, associated anomalies, and various etiological factors.
Encyclopedia article (1928–1936)
CLUBFOOT (pes varus, pes varo-equi-nus, talipes varus, talipes equino-varus according to English authors), a deformity of the foot with inward rotation and plantar flexion. The deformity in C. usually consists of three main components: adduction, supination (talipes varus according to English authors), and plantar flexion (talipes equinus according to English authors). Depending on which element predominates, the deformity is called: pes varus, equino-varus, etc. Opposite deformities of the foot are called pes valgus - deviation of the foot outward, pes calcaneus - pathological position of dorsal flexion (heel foot); a combination of both types of deformity is called pes calcaneo-valgus. These latter types of deformity, in contrast to pes equino-varus, are more often of paralytic origin. - C. in the vast majority of cases is congenital; according to Bessel-Hagen, 73.8% of all cases of C. are congenital, and 26.2% are acquired C. According to Lannelongue, one case of congenital C. occurs in 2,000 births; according to Bessel-Hagen, one case in every 1,100 births. Genetics of C. Congenital C. is in the overwhelming majority of cases a genotypic disease. Not only the anomaly itself but also its degree is usually inherited (Fig. 1). In most cases, C. is inherited as an autosomal recessive trait (Fig. 2), and, as in other similar cases, relatively frequent consanguineous marriages (inbreeding) between parents of patients are observed. However, some cases (Kochs, Müller, etc.) must be interpreted rather as a dominant form of inheritance; finally, individual genealogies by Fetscher indicate the possibility of recessive, sex-linked inheritance (Fig. 3). From the foregoing, it follows that C. is a heterogeneous anomaly, combining clinically similar but biologically (genotypically) completely different cases. The fact mentioned above of clinical differences in the manifestation of C. in different families (with similarity within one family) also speaks in favor of this. In boys, C. occurs twice as often as in girls (Bessel-Hagen, Fetscher). The reason for the more frequent occurrence in the male sex has not been finally clarified. In some cases, this is explained by the probable fact of recessive, sex-linked inheritance; the remaining cases must apparently be interpreted as partial restriction to the male sex. It is extremely interesting that among the sisters and brothers of recessive homozygotes, the male sex predominates: according to Fetscher's data, for 386 brothers there are only 267 sisters. A satisfactory explanation for this phenomenon does not yet exist. As one hypothesis, it can be suggested that there is partial lethality of the C. gene in the homozygous state (assuming that some cases of C. are inherited as a recessive, sex-linked trait). At least this allows interpretation of the data provided by Fetscher. The large number of carefully verified clinical facts forces recognition of the existence of congenital paratypic C. In the not too distant past, the opinion prevailed that this form of C. is predominant, and that primary C. should be assigned a very modest place. Representatives of another group (J. Wolff) energetically objected to this. As exogenous intrauterine factors, pathological position of the fetus, anomalies of the uterus and amnion (uterus bicornis, narrowing of the uterine cavity, deficiency of amniotic fluid, adhesion of the amnion to the surface of the fetus, amniotic constrictions), bone defects, multiple pregnancy, mismatch between the size of the uterus and fetus (Martini, Malgaigne, Liicke, etc.) are cited. All these factors probably play only the role of contributing factors. - C. is often combined with other congenital malformations: spina bifida occulta, torticollis, club hand, syndactyly, harelip, cleft palate, as well as with deaf-mutism, nocturnal enuresis, etc. In his material, Fetscher among 184 patients with C. found mental deficiency in 12% of cases (idiocy in 4.67%); among 460 investigated idiots, C. was present in 20 cases (4.4%), among 407 mentally ill patients - in 4 cases. Such cases must be interpreted as pleiotropic action of the C. gene. As for the question of the mechanism of action of the clubfoot gene, according to B. Ashner (V. Ashner), the area of its manifestation is the corresponding affected limbs; Fetscher, on the contrary, assumes that a lesion of the central nervous system is transmitted, which in turn leads to the development of CLUBFOOT.

I. Rybkina. Congenital C. is more often bilateral (about 60%); when one side is affected, the right side predominates (Whitman, Kirmisson). Acquired C. has several etiological factors. There are forms of static C. due to pathological stress. Such is, for example, C. in pronounced genu valgum, in partial acquired defects of the tibiae (osteomyelitis, extensive resection), after various types of fractures within the ankle joint with partial dislocation of the talus (traumatic C.). Acquired C. with such etiology has very atypical forms - from simple positioning in the va-r position to severely expressed forms. On the basis of scar, dermo-desmogenic and tendogenic contractures after inflammatory processes, C. often develops, Fig. 3. Hereditary
I. Rybkina. Congenital C. is more often bilateral (about 60%); when one side is affected, the right side predominates (Whitman, Kirmisson). Acquired C. has several etiological factors. There are forms of static C. due to pathological stress. Such is, for example, C. in pronounced genu valgum, in partial acquired defects of the tibiae (osteomyelitis, extensive resection), after various types of fractures within the ankle joint with partial dislocation of the talus (traumatic C.). Acquired C. with such etiology has very atypical forms - from simple positioning in the va-r position to severely expressed forms. On the basis of scar, dermo-desmogenic and tendogenic contractures after inflammatory processes, C. often develops, Fig. 3. Hereditary
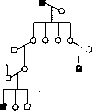
I. Rybkina. Congenital C. is more often bilateral (about 60%); when one side is affected, the right side predominates (Whitman, Kirmisson). Acquired C. has several etiological factors. There are forms of static C. due to pathological stress. Such is, for example, C. in pronounced genu valgum, in partial acquired defects of the tibiae (osteomyelitis, extensive resection), after various types of fractures within the ankle joint with partial dislocation of the talus (traumatic C.). Acquired C. with such etiology has very atypical forms - from simple positioning in the va-r position to severely expressed forms. On the basis of scar, dermo-desmogenic and tendogenic contractures after inflammatory processes, C. often develops, Fig. 3. Hereditary
There are also rheumatic, ischemic, and myogenic forms of clubfoot. Finally, among the various types of acquired clubfoot, a huge group consists of paralytic forms, arising mainly after infantile spinal paralysis. Regardless of the etiological moment, a very typical deformity forms in clubfoot, and rather complex pathological-anatomical relationships arise between the bones of the foot. Pathological anatomy. The deformity that occurs in clubfoot happens due to excessive rotation of the foot around its three main axes. Movement around the transverse axis in the direction of plantar flexion is so sharply pronounced that the surface of the trochlea tali protrudes forward to a significant extent. The neck of the talus is turned inward and downward. Normally, it is turned inward by 35.7° in the embryo, by 12.3° in an adult, and up to 50.7° in clubfoot. The anterior part of the talus is not covered by the articular surface of the navicular bone in such a deformity. The calcaneus is in a position of plantar flexion and rotation around its longitudinal axis, turned around the vertical axis so that its anterior end is located medially, and in addition, there is a twisting of the calcaneus medially in the posterior-anterior direction. Its upper surface faces forward and inward. The articular surface for the cuboid bone faces significantly inward and downward. All bones of the foot are underdeveloped. Due to the adduction and rotation of the anterior part of the foot, the navicular bone is turned inward, posteriorly, and upward so that it articulates with the posterior part of the head of the talus and can come into contact with the medial malleolus. The relationship between the os cuboideum and the calcaneus is also changed: the upper surface of the former faces outward and downward. The malleoli are usually not very changed in their development and mutual arrangement. In chronic cases, twisting of the bones of the lower leg around their longitudinal axis is also noted. This explains the circumstance that even after correction of the foot, the latter seems turned inward in relation to the knee joint. Anatomical changes also occur in the ligaments, fasciae, and muscles. The entire ligamentous apparatus along the inner and posterior surface of the foot and sole is shortened. The tendons of the muscles receive a pathological direction depending on the displacement of the attachment sites. The tendon of the m. tibialis anterior lies directly at the medial malleolus, and in severe cases, even on its inner side. The tendons of all anterior muscles are displaced medially accordingly. The m. tibialis posterior, instead of the normal turn forward behind the medial malleolus, is directed downward, and since the os naviculare approaches the medial malleolus significantly, the section of the tendon below the malleolus is barely detectable. The tendons of the mm. flexor digitorum longus and flexor hallucis longus are also displaced medially depending on the degree of foot deformity. The path of the tendons of the m. peroneus is lengthened; the muscles are overstretched and have lost their tone. The described pathological changes intensify when the patient begins to walk. Usually, the support is not the sole, but the dorsal or, rather, the anterior-outer part of the foot, with the os cuboideum and the anterior-outer part of the calcaneus bearing the greatest weight. A significant callous thickening of the skin forms here, under which a mucous bursa is located. The talus loses its articular cartilage on the protruding anterior surface of the trochlea; the neck lengthens and has a direction downward and inward. Due to the load during walking, gross bone changes occur, especially at the expense of the talus, cuboid, and calcaneus bones, which in neglected cases sometimes serves as an almost insurmountable obstacle to the complete correction of the clubfoot during redressment.
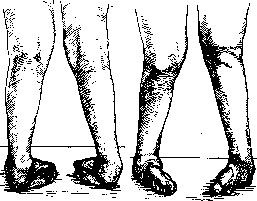
Figure 4.
The clinical picture of clubfoot is extremely characteristic. In addition to the described deformity involving the foot, one's attention is drawn to a certain atrophy of the lower leg muscles, a characteristic disproportion in the development of the limbs and trunk, and a characteristic gait with support on the dorsum of the foot. Due to the persistent varo-equinus position, the dynamics of the muscles are sharply disturbed. The peroneal group is overstretched and inactive; the mm. tibialis anterior and triceps surae, due to the extreme shortening of their path, although they tense actively, do not possess normal contractile ability. The same can be said about other muscle groups of the foot. In its essence, clubfoot represents a contracture of certain muscle groups with subsequent remodeling of the skeleton (Figure 4). There is a significant difference between congenital clubfoot and pes excavatus, which developed later and is always associated with myelodysplasia, with dysplasias of the lower end of the spine (spina bifida occulta), or with infantile paralysis. Congenital clubfoot is more often bilateral, and all components of the deformity are expressed equally sharply; in bilateral clubfoot, the varus element may be less pronounced on one side than on the other. In pes excavatus of paralytic or myelodysplastic origin, the cavus element sharply predominates over other curvatures. Often the deformity \
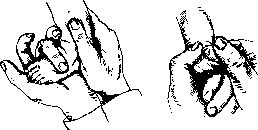
is well expressed on one leg, while on the other there are only traces of it; the deformity of the feet develops gradually in childhood or adolescence during the period of most intensive growth of the skeleton. It should be noted that stubbornly recurring clubfoot, which does not yield to systematic treatment, often finds its explanation upon careful examination of the lumbar spine and the nervous system. Clubfoot in the presence of strangulation bands of amniotic origin on the lower leg also possesses extreme rigidity of soft tissues and stubbornness during treatment. Such clubfoot very much resembles ischemic contracture of the hand. Clubfoot arising due to bone changes that occurred in utero, after trauma or osteomyelitis, is easily recognized radiologically and clinically. Timely classification of clubfoot into one of the indicated groups is important from a therapeutic point of view, since a treatment plan is outlined depending on the etiological moment and pathological-anatomical changes. The treatment of clubfoot depends on the period in which the patient comes to the doctor. Treatment in the early period, starting from the first month up to 1 year, although disputed by a few authors, is still recognized by the majority of major orthopedists as entirely appropriate. The main obstacle to treatment in the first months of a child's life is technical difficulties, the need for painstaking manipulations, as well as the complexity of subsequent treatment and the tendency to recurrences. But the technical difficulties are entirely surmountable, and there is no need to wait until a year or until the child begins to stand on their feet. Harm is avoided by achieving early elimination of the deformity by teaching parents corrective manipulations with subsequent application of a bandage according to Fink-Oettingen. There is a completely false opinion that in weakly expressed forms, the deformity disappears as soon as the child begins to walk. In reality, the deformity increases and will progress under the load of the body. Haglund, being a supporter of early therapy, still believes that in some cases one has to postpone correction. Early therapy can be started by the end of the first month of the child's life. It consists of manual redressment ("closed" redressment) and the application of a bandage. Manual redress
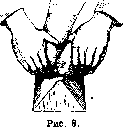
Figure 5. Figure 6.
such correction at this age can be performed without anesthesia, by manipulating delicately. The general principle of correction in C. remains the same here: first, the adduction and supination of the foot are corrected, and only after the complete elimination of these two components of C. is the 'equinus' corrected. Manual correction for clubfoot is performed as follows (figs. 5 and 6): with one hand, the leg is grasped around the ankle joint. The anterior part of the foot is grasped with the other hand in such a way that the foot rests on the palmar surface of the hand; the fingers grasp the outer edge of the foot, and the thumb grasps the inner edge. With slow, elastic movements, adduction and supination are eliminated, and at the same time, the hand holding the ankle joint presses with its palm against the calcaneus, creating a firm point of support. The final phase is the correction of the equinus element, and the heel should be brought completely downward and its inward rotation eliminated so that the foot is set in a slight valgus position and the calcaneus. Before eliminating adduction and supination, the equinus position serves as a good lever for all manipulations, and it would be a great mistake to attempt to correct the equinus immediately, let alone tenotomize the Achilles tendon. To correct the equinus in small children, manual corrective movements in the dorsal direction are usually used, while slightly valgizing the foot. The Lorenz technique is also good, in which one hand pulls the foot in the plantar direction with a loop thrown over the dorsal surface of the foot, while the other hand corrects the foot in the dorsal direction. It is necessary to hypercorrect the entire foot along with the heel, not just the anterior part. In persistent cases and in older children, it is necessary to resort to correction with a hinged board or with the support of a regular board against the chest of the physician performing the reduction. With this technique, considerable force can be developed (fig. 7). Correction in a child can be considered complete if a light touch of the finger to the sole creates the correct position of the foot with a tendency toward valgus. In mild cases, correction can be achieved in one or two sessions through manual manipulation without causing significant pain to the child. In severe cases, corrective manipulations have to be repeated several times with intervals. Immediately following correction, a bandage should be applied to maintain the achieved position. The general requirement for the bandage: it should not correct, but only fix the position achieved by manual correction. Among the many bandages proposed for early childhood, the Fink bandage deserves attention, which is also called the Ettingen-Fink bandage and is applied as follows: after manual reduction, the skin is smeared with kleiol from the lower third of the thigh to the toes. The foot to the ankles is covered with cotton, which is tightly bandaged with gauze bandage. A special aluminum sole is applied to the foot (for better correction of the foot as a whole), after which bandaging with a flannel bandage 2a-4 cm wide is begun. The bandage is applied spirally from the thigh around the calf to the inner ankle, then along the sole to the outer ankle, covers the arch, goes along the sole and returns to the outer ankle, from where it is led upward to the thigh, where the bandage is looped by the assistant and pulled tightly. With further spiral turns, the bandage covers the calf, lies over the first loop, pulling it to the calf and thereby abducting the foot (cf. the heel). This is the first loop for pronation of the heel.
Fig 7 bandage-similar to those described, but bandaging can be conveniently combined with frequent repeated corrective manipulations. All this should be done by the physician himself or a trained assistant until the parents, if they are sufficiently cultured, master the manual manipulations and bandaging perfectly themselves. A bandage of adhesive tape, although it holds the position well, irritates the skin, especially in small children, and is practically less suitable. Tregubov, after reduction and hypercorrection of the foot, proposes to maintain the achieved position with a flannel strip that only covers the foot and attaches to the flannel covering the thigh above the knee. Separate ties on the thigh and foot are tightened, with periodic correction performed. A plaster cast, while holding the position perfectly, is less convenient for infants due to frequent dampening and contamination, but with good care and supervision, it can be used even at the very earliest age. The first cast after reliable correction is usually applied for 4-6 weeks. Then manual correction is repeated again to achieve hypercorrection, obtaining pes abductus and a mild pes valgus. A cast is applied again for 4-6 weeks. Usually it has to be changed 4-5 times, sometimes more. In small children, treatment should be continued until the beginning of walking.
After the period of fixation with a cast, there should follow a period of fixation in an apparatus
in which the child must walk for at least a year. The apparatus is required to maintain the position of abduction and pronation of the foot well. During this period, systematic massage is also necessary. Treatment can be considered complete when the child can actively perform pronation and abduction of the foot using muscular force. If a child is brought to a doctor at the age of 1 year, manual redressement is more difficult; when a child has been walking for several years, manual correction presents serious difficulties, but it must always be attempted before resorting to other types of conservative therapy or surgical intervention. The treatment regimen for clubfoot after 1 year of life remains the same as that described above: first, complete correction, fixation with a bandage, then an apparatus. After one year, redressement must be performed under anesthesia, and deep anesthesia is required at the moment of vigorous manipulations. Here, not all components of clubfoot can be easily eliminated by manual means, and one has to resort to a wedge, on which it is convenient to correct adduction and supination (Figure 8). For the purposes of safe mechanical redressement of more stubborn cases of clubfoot, there are a number of devices. Such are, for example, the 'Thomas's wrench', the Gocht, Phelps, Zwinge forceps, and many others. Their purpose is to replace manual force with mechanical levers, with which one can manipulate more vigorously. The Schultze osteoclast (Schultze table) possesses significant perfection in this regard; although it is complex in design, it combines all the elements of a redressement apparatus: precise fixation, compression, and traction. With the help of the Schultze osteoclast, almost all types of clubfoot, even the most neglected ones, can be corrected conservatively. Correction using the Schultze osteoclast is usually performed in stages: first, the adduction of the foot is corrected with a loop, then, by applying direct pressure on the talus and combining it with simultaneous correction of supination, it is possible to partially reduce the talus. In one or two sessions, the foot can be placed in a valgus position. It is necessary to ensure that no bending of the forefoot occurs. Then, the equinus position is corrected on a board, and in stubborn cases, one should resort to open achilloplasty. Redressement in childhood and adolescence usually has to be repeated several times before the necessary hypercorrection is achieved. After each redressement, a bandage is applied, fixing the corrected position. For the indicated age, a plaster cast is also indispensable; when applying it, the following conditions must be observed: do not make the cotton padding too thick; protect areas subject to the greatest pressure well, best of all with thin felt pads over the cotton; ensure that the protective layers do not slip, for which the skin in these places should be smeared with cleol. The following places must be 'protected' especially carefully in clubfoot, as they are subject to the greatest pressure: the inner side of the forefoot and heel, the outer part in the area of Chopart's joint and the lateral malleolus. Good cotton padding is necessary between the toes; the toes must be spread out, free, and not compressed by the plaster bandage. The soft bandage over the cotton padding must lie smoothly, without folds, not cutting into the areas of flexion. It is necessary right now, before applying the plaster bandages, to give the foot its final position so that the plaster bandage does not perform further correction: the plaster bandage should lie freely, without tightening the foot, going from the inside to the outside, from the dorsal to the plantar side, thus turning the foot, abducting and valgizing it. In children, it is better to apply the plaster cast slightly above the knee joint, giving it a slightly bent position. This prevents the bandage from slipping downwards. For the latter purpose, it is also necessary to model the bandage over bony prominences. In the first 24 hours, the foot is given an elevated position. In case of suspicious loss of sensitivity in the toes, it is necessary to cut and slightly spread the entire bandage from the front, along with the soft bandage. Correct application of the plaster cast in clubfoot is no less important than skillful redressement. Such a bandage should be changed every 3-4 weeks. If, despite vigorous redressement, it is not possible to correct the deformity or if there is a constant tendency to recurrence, then in such cases one has to resort to small palliative operations, such as Ogston's excochleatio tali, dissection of the plantar fascia, or lengthening of the Achilles tendon. The latter intervention, however, should be performed only after the adduction and supination of the foot have been eliminated. In particularly stubborn cases, where complete redressement is not achieved, Erlacher suggests performing freezing of the n. tibialis by an open method in the popliteal fossa. Treatment cannot yet be considered complete after correction and even hypercorrection have been achieved. Immediately following the period of correction and fixation with a plaster cast, there follows a long period of wearing an apparatus with simultaneous massage and active exercises in order to achieve active pronation. From the moment that well-pronounced active pronation appears, there is less risk of recurrence. It is extremely important in this regard that the heel be slightly valgized. In individual cases, despite complete correction of all components of clubfoot, the foot still occupies an incorrect position in relation to the knee joint. This is explained by the torsion of the bones of the lower leg around the longitudinal axis that has occurred. In such cases, one has to resort to an extreme, but the only truly effective measure—osteotomy of the bones of the lower leg with rotation of the distal section corresponding to the normal axis of the limb. Treatment of neglected cases of clubfoot presents the most difficult task. Manual redressement on a wedge and even with the help of the proposed auxiliary redresseurs (Thomas's wrench), etc., does not give a full effect due to the fact that a remodeling of the foot skeleton has occurred. After a series of redressement manipulations, it is sometimes possible to achieve correction only of the forefoot, but this is an illusion of correction, since the rotation of the talus and calcaneus remains uncorrected. The Schultze osteoclast is a powerful means for correcting even neglected cases of clubfoot, but due to its high cost, it is available only to a few orthopedic institutions. And its use in inexperienced hands is unsafe. For the majority of neglected cases of clubfoot in adults, surgical treatment is indicated. Among a number of bloody interventions, some serve only as an additional factor to corrective manipulations. Such are, for example, excochleatio tali, achillotenotomy. Other operations of a more radical type pursue the goal of eliminating the deformity completely by operative means. Surgical intervention is indicated where closed methods of redressement have not led to desired results or where it can be assumed a priori that bloodless measures will not be effective. For a long time, the Phelps operation has been used to correct clubfoot, consisting of open dissection of all soft tissues on the inner side of the foot. Subsequently, osteotomy was added to this. The Phelps operation does not yield favorable results and has been abandoned by most orthopedists. Dissection of the tense soft tissues on the inner side is sometimes done subcutaneously as a preliminary stage before redressement, but no great effect is obtained from these operations. Among other operations on soft tissues, various kinds of tenotomies are widely used. Many surgeons consider it better to perform achillotenotomy by an open method and, in severe cases, to add to it the dissection of the posterior ligament (lig. talo-tibiale posterius), which serves as a serious obstacle to the complete elimination of equinus. Individual authors (Broadhurst) recommend dissection of the tendon of the m. tibialis posterior, which also presents a serious obstacle to correction. More rarely, one has to resort to dissection of the m. flexor digitorum longus and tibialis anterior. A single intervention on soft tissues rarely leads to complete elimination of the deformity in adults. Operations on the skeleton serve this purpose. Excochleatio tali is performed through a small incision in the front; the cancellous substance is scooped out from the head, neck, and body of the talus so that a cartilaginous shell at least 1/2 cm thick is preserved. Thanks to such scooping out, the talus becomes pliable, and correction is easily achieved. This kind of intervention is possible in childhood up to 6-8 years of age. In adults with very significant deformity, complete extirpation of the talus is used, which was developed in detail by Whitman and is called astragalectomy. It was first performed in 1892 (Lund). Through a lateral arcuate incision, the articulatio talocruralis and talocalcaneonavicularis are exposed, the ligamentum talonaviculare and the lateral collateral ligament are dissected, after which the talus, grasped with bone forceps, is removed during sharp adduction and supination of the foot. If, after removal of the talus, the anterior part of the calcaneus hinders correction, it should also be resected so that the os cuboideum can fit freely during hypercorrection of the foot.
Astragalectomy is a simple and highly effective operation for severe forms of clubfoot; it can be performed simultaneously on both legs without previously cutting the Achilles tendon. Cuneiform resection of the tarsus gives good results. Through a transverse incision over the most prominent bony protrusion, the tarsal bones are exposed. From the outer side, a wedge is excised from the calcaneus, talus, and cuboideum so that the wide base of the wedge faces outward, and the apex reaches the os naviculare. With a sufficiently large wedge taken, a completely satisfactory correction is achieved. In stubborn cases with an unfavorable position of the calcaneus, one has to resort to its osteotomy according to Hohmann. The Vreden Clinic has developed (Kuslik) a method of crescentic resection, which spares the skeleton and eliminates all components of the deformity. After bone operations, a subsequent fixation bandage is also required, and then the wearing of an apparatus for 6–7 months. Mention should be made of the Wullstein operation, which combines redressment and tenotomy with muscle transplantation. After dissection of the plantar aponeurosis and separation of the mm. abductor hallucis and flexor hallucis brevis from the calcaneus, the m. tibialis posterior is detached from the os naviculare; redressment on a wedge. Through a medial incision on the lower leg above the ankle, the Achilles tendon is lengthened, and the tendon of the m. tibialis posterior is pulled out here as well, which is then passed through a special incision through the membrana interossea to the anterior surface of the lower leg and fixed subperiosteally to the IV and V metatarsal bones. From an incision on the outer side of the foot, the tendon of the m. peronaei brevis is detached and, with sharp pronation, sutured to the strong tendon of the m. abductoris digiti V. Plaster cast in the corrected position for 4 weeks. The Wullstein operation, although based on the active preservation of abduction and pronation of the foot, cannot, however, provide a significant effect in cases of severe bone deformity. Ludloff, also attaching importance to the m. tibialis posterior, transplants it onto the peronaeus brevis after preliminary correction. Various operative methods for treating clubfoot require a critical attitude and appropriate indications. They do not exclude subsequent orthopedic treatment. In the presence of a bone defect (most often the absence of the medial malleolus) or a partial defect of the tibia, conservative therapy does not yield a good result. Even if it is possible to correct the deformity in childhood, a relapse occurs. In such cases, after correction of the deformity, one should attempt to plastically reconstruct the bone defect or, after correction, wear an apparatus for a long time. In cases of clubfoot arising on the basis of a previous osteomyelitis, scars along the inner side of the lower leg and foot are a serious cause of relapse. In such cases, along with intervention on the skeleton, skin grafting is indicated. Metatarsus varus and pes adductus represent only one component of clubfoot—adduction—and are easily amenable to treatment. In adults, such good functional adaptation usually occurs that they do not notice their defect. In childhood, bloodless redressment is possible, followed by long-term wearing of an orthopedic apparatus until the remodeling of the skeleton in the tarso-metatarsal joint occurs. There are many transitional deformities of the foot (see), which have a specific etiology and a peculiar pathological-anatomical picture and require special orthopedic treatment. The cited methods of conservative and operative treatment of clubfoot, with appropriate selection and systematic application, give reliable and quite satisfactory results. The earlier treatment of congenital clubfoot is started, the easier it is and the better its results.
V. Chaklin.
Related articles
Mentioned in
Cite this page
“Clubfoot.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/clubfoot/