Arm (Humerus)
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article provides a detailed anatomical description of the human arm and the humerus bone, covering its structure, muscle attachments, ossification, and regional divisions. It details the bone's epiphyses, diaphysis, and the various fossae and epicondyles that facilitate joint movement and muscle function.
Encyclopedia article (1928–1936)
ARM (brachium), a part of the upper limb within the boundaries between a transverse line drawn along the lower edge of the pectoralis major, latissimus dorsi, and teres major muscles (above), and a similar line drawn two finger-breadths above the condyles of the humerus (below). The shape of the arm depends on the degree of development of its musculature and its adiposity. In women and children, the subcutaneous fat layer smooths out all the contours of the musculature and gives the arm the shape of an almost regular cylinder; in a muscular man, the arm in cross-section appears elongated from front to back due to the developed musculature of the anterior and posterior compartments of the arm; the volume of the arm is greater at the top than at the border with the elbow region. The skeleton of the arm is the humerus (os humeri) (Fig. 1)—a long, tubular bone; articulating above with the scapula, and below with the bones of the forearm. The upper epiphysis of the humerus is thickened and bears a cartilage-covered head (caput humeri), which has the shape of a hemisphere and is directed upward and inward; the axis of the head is located at an angle of 130–145° to the longitudinal axis of the bone; immediately behind the head there is a constriction of the bone, the anatomical neck (collum anatomicum); below it are two tubercles: the lesser tubercle (tuberculum minus), which faces forward and to which the subscapularis muscle (m. subscapularis) attaches, and the more voluminous greater tubercle (tuberculum majus), which faces laterally; the posterior-upper
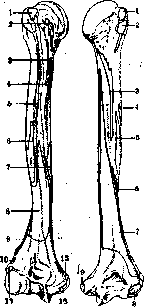
Fig. 1. Humerus with muscle attachment sites. Anterior view (a): 1—m. supraspinatus
posterior surface
surface bears three facets: the upper one is intended for the attachment of the supraspinatus muscle (m. supraspinatus), the middle one for the infraspinatus muscle (m. infraspinatus), and the lower one for the teres minor muscle (m. teres minor). From each tubercle, a crest extends downward (crista tuberculi minoris et majoris); the latissimus dorsi and teres major attach to the first, and the pectoralis major to the second; between the tubercles and their crests is a groove 6–8 cm long, lined at the top with cartilage (intertubercular sulcus—sulcus intertubercularis); the tendon of the long head of the biceps brachii muscle lies in this groove. The part of the humerus immediately below both tubercles, which has a smaller diameter, is called the surgical neck (collum chirurgicum). The middle section of the humerus (diaphysis, body, corpus humeri) is almost straight, twisted along its axis, close to a cylindrical shape at the top, and triangular at the bottom. On it, one distinguishes an anteromedial surface (facies ant. medialis), an anterolateral surface (facies ant. lateralis), and a posterior surface (facies post.); the latter is separated from the first two by a clearly defined, especially in the lower half of the bone, medial border (margo med.) and lateral border (margo lat.). In the upper part of the middle third of the humerus, on the anterolateral surface, there is a V-shaped deltoid tuberosity (tuberositas deltoidea), with its apex pointing downward, serving for the attachment of the muscle of the same name. Behind it, the radial groove (sulcus n. radialis) runs spirally from top to bottom—the location of the radial nerve and the deep artery of the arm with its two veins. Near the middle of the medial border of the humerus is the nutrient foramen (for. nutricium), from which the nutrient canal (canalis nutricius) begins, running toward its lower end. The diaphysis of the humerus serves as the attachment site for several muscles (see below). The lower end of the humerus is flat and wide, bent anteriorly at an obtuse angle, open forward, relative to the long axis of the body of the humerus; on the sides of the lower end of the humerus, on the continuation of the medial and lateral borders, lie rough tubercles, the medial and lateral condyles (condylus medialis et lateralis). The medial condyle is larger and has a flat ulnar nerve groove (sulcus n. ulnaris) on its posterior surface. The lower
end of the humerus has cartilage-covered articular surfaces: the medially located part, the trochlea (trochlea), articulates with the ulna, and the lateral part, the capitulum (capitulum, eminentia capitata), has the shape of a part of a sphere and articulates with the radius; above the trochlea in front is a shallow coronoid fossa (fossa coronoidea), where the coronoid process of the ulna is placed during flexion at the elbow; above the trochlea behind is a deep olecranon fossa (fossa olecrani), into which the olecranon process of the ulna is submerged during extension. The bone between these fossae is very thin and sometimes perforated. Above the capitulum

Figure 2.
lies the radial fossa (fossa radialis). These three fossae are devoid of cartilage. Above the articular parts of the humeral condyles, there are bony projections on the sides intended for the fixation of muscles and ligaments; the medial epicondyle (epicondylus medialis) is more strongly developed, where the medial collateral ligament of the elbow (lig. collaterale ulnare) and five flexor muscles are attached: mm. pronator teres, flexor carpi radialis, palmaris longus, flexor digitorum sublimis, and flexor carpi ulnaris, and occasionally an accessory head of the flexor digitorum profundus; the less developed lateral epicondyle (epicondylus lateralis) serves as the attachment site for the lateral collateral ligament (lig. collaterale radiale) and 6 extensor muscles: mm. extensor carpi radialis longus, supinator (brevis), extensor digitorum, extensor indicis, extensor carpi ulnaris, anconaeus. Internal structure of the humerus. Both ends consist of a relatively thin compact cortical layer and spongy bone occupying the entire remaining mass, consisting of thin bony crossbars, trabeculae; these plates are a continuation of the cortical layer of the bone (Fig. 2), running in various intersecting directions along lines that are drawn by mathematicians in graphic statics when constructing bodies that have the same shape as bones and serve to counteract the same forces that act on the bone (Lesgaft). The cells of the spongy substance are filled with bone marrow. The medullary canal of the diaphysis occupies its entire height, having an average transverse diameter of 8 mm in the lower third, 10 mm in the middle third, and 12 mm in the upper third. The walls of the bone cylinder thin out from bottom to top. The main mass of the lower epiphysis consists of spongy substance with denser crossbars, mostly placed vertically in relation to the articular surfaces. The cortical layer on the lower epiphysis is thicker here than on the upper epiphysis. The development of the humerus occurs from 8 ossification centers (Fig. 3)—one primary and 7 secondary. The primary center appears around the 45th day of intrauterine life in the middle of the length of the diaphysis, growing upward and downward. Of the 7 secondary ones, 3 are in the upper epiphysis and 4 in the lower; the first center of the upper epiphysis appears on the head of the bone in the 2nd–4th month after birth; the centers of the greater and lesser tubercles appear in the 2nd–3rd year. In the lower epiphysis, the first center appears on the capitulum at the beginning of the 3rd year. In the 5th year, the center of the medial epicondyle appears. In the 12th year—the 3rd and 4th centers of the trochlea and lateral epicondyle. The lower epiphyseal line disappears around the 16th–18th year; the same between the medial epicondyle and the epiphysis—a year or two later, but cases where it is present at 25 years of age are not rare. The upper epiphyseal line persists until 25–26 years. The arm is anatomically and functionally divided into two regions: the anterior—the flexor compartment (regio brachii ant.) and the posterior—the extensor compartment (regio brachii post.). The anterior section has the appearance of an oval convex anteriorly, more pronounced with developed musculature. Along the lateral and medial sides of the arm
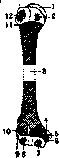
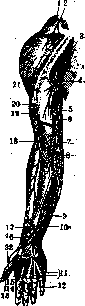
run shallow grooves (sulci bicipitales lat. et med.), separating the anterior compartment of the arm from the posterior; both grooves converge at an acute angle in the cubital fossa; the medial groove is more sharply defined, the lateral is shorter than the medial; at the top, near the lower end of the deltoid muscle, it divides into two branches, of which the anterior passes into the deltopectoral groove (sulcus deltoideo-pectoralis), and the posterior runs along the posterior edge of the deltoid muscle. The skin of the arm is loosely connected to the underlying tissues and is thicker on the lateral surface; it is devoid of hair on the anterior and medial surfaces of the arm. The subcutaneous tissue consists of two layers, between which
Figure 4. Superficial nerves of the arm: 1 and 2—branches from the cervical plexus; 3, 4, 5—cutaneous branches of the median nerve; 6–9—n. cutaneus brachii med.; 10—branch of the n. mediani; 11–15 and 22—cutaneous branches of the nn. mediani et ulnaris; 16, 17 and 19—branches of the n. radialis; 18—cutaneous branch of the musculocutaneous nerve; 20 and 21—cutaneous branches of the axillary nerve. Superficial vessels and nerves are located here. Two large venous trunks extend from the forearm—v. basilica and v. cephalica. The v. basilica runs in the subcutaneous tissue along the sulcus bicipitalis med., but only in the lower half of the groove; higher up, it pierces the brachial aponeurosis and runs in the canal of this aponeurosis, often reaching the axillary cavity or emptying into the brachial vein at the middle of the arm. The v. cephalica runs in the subcutaneous tissue of the sulcus bicipitalis lat., then upward in the deltopectoral groove until it empties into the axillary or subclavian vein. The superficial nerves of the anterior part of the arm (Fig. 4): below—the lateral cutaneous nerve of the arm (n. cutaneus brachii lateralis from the axillary nerve); on the anteromedial surface of the arm above—the intercostobrachial nerve (n. intercostobrachialis) and the medial cutaneous nerve of the arm (n. cutaneus brachii medialis); in the lower half of the arm—the medial cutaneous nerve of the forearm (n. cutaneus antibrachii medialis). The aponeurosis (aponeurosis, fascia brachii) covers the arm like a sheath and continues into the aponeurosis of the adjacent regions of the arm. Thin septa for the muscles extend from the inner surface of the aponeurosis. Between the aponeurosis and the humerus in the frontal plane are located the intermuscular septa of the arm—medial and lateral (septum intermusculare mediale et laterale) (Fig. 5). The aponeurotic sheath is divided by them into two compartments: the anterior—the flexor compartment, and the posterior—the extensor compartment. Both compartments communicate with each other via vessels and nerves passing from one compartment to the other. The anterior compartment is subdivided into two—the compartment of the biceps muscle and the compartment of the brachialis muscle (Fig. 5). The aponeurosis of the arm is thicker posteriorly. The main mass of the aponeurosis fibers consists of circular bundles with a slight oblique inclination; longitudinal bundles (there are fewer of them than circular ones) run perpendicular to the former. The pectoralis major muscle and
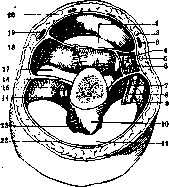
Figure 5. Cross-section of the arm in the lower third (diagram): 1—m. biceps; 2—n. cutaneus brachii med.; 3—v. basilica; 4—n. medianus; 5—n. cutaneus antibrachii med.; 6—a. brachialis; 7—medial tendinous septum; 8—n. ulnaris; 9—a. collateralis ulnaris sup.; 10—humerus; 11—m. triceps; 12 and 20—aponeurosis; 13—sulcus n. radialis; 14—a. profunda brachii; 15—n. radialis; 16—lateral tendinous septum; 17—m. brachialis int.; 18—n. musculocutaneus; 19—v. cephalica.
latissimus dorsi muscle send broad aponeurotic expansions to the aponeurosis of the arm (Sappey). The subaponeurotic layer is occupied by 5 muscles arranged in two layers: in the first are the deltoid and biceps muscles (see Biceps and Deltoideus musculus); the next three muscles—coracobrachialis (m. coracobrachialis), brachialis (m. brachialis), and brachioradialis (m. brachioradialis)—are located under the first two (see Muscles of the human body). In the axillary cavity, the coracobrachialis muscle forms part of its lateral wall; anterior to the muscle lie the deltoid and pectoralis major muscles; posteriorly—the tendons of the subscapularis, latissimus dorsi, and teres major muscles; medially—the neurovascular bundle. Brachialis muscle (m. brachialis)—see Muscles of the human body. Relation to adjacent organs: on the anterior surface of the brachialis muscle lies the biceps muscle; between them there is an intermuscular septum, in which the musculocutaneous nerve runs (Fig. 5), and medial to it is the neurovascular bundle of the arm. The posterior surface of the muscle lies superiorly on the humerus, and inferiorly on the elbow joint. The medial border superiorly borders the triceps muscle, inferiorly—the pronator teres; a groove is formed between them, in which the brachial artery with veins and the median nerve run; the upper part of the lateral border borders the triceps muscle, and the lower part—the brachioradialis muscle; in the groove between them run the radial nerve and the collateral radial artery (a. collateralis radialis). Brachioradialis muscle (m. brachioradialis) (see Muscles of the human body) runs laterally to the brachialis muscle to the forearm, borders dorsally with both radial extensors of the wrist, and on the palmar side—with the pronator teres and the flexor carpi radialis; this muscle attach-
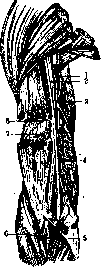
Figure 6. Arteries of the arm from the front: 1—a. profunda brachii; 2—a. brachialis; 3—a. collateralis ulnaris sup.; 4—a. collateralis ulnaris inf.; 5—a. ulnaris; 6—a. radialis; 7 and 8—muscular branches.
-es with a thin, flat tendon to the radius above the styloid process; the tendon of the brachioradialis muscle is often pierced by the radial nerve. Most of the vessels and nerves of the anterior part of the arm pass from the axillary region to the forearm and hand. The main arterial trunk of the arm is the brachial artery (a. brachialis, Fig. 6), which is a continuation of the axillary artery (a. axillaris). The artery runs along the medial side of the arm, along the edge of the biceps muscle, along the projection line from the apex of the axillary fossa to the middle of the cubital fossa. Two accompanying veins (vv. brachiales) run along the sides of this artery. Figure 7. Anastomoses of the axillary artery from behind: 1 and 2—a. transversa colli; 3 and 9—network of anastomoses; 4—a. subscapularis; 5—a. transversa scapulae; 6—a. circumflexa humeri; 7—anastomosis between the aa. circumflexa humeri and profunda brachii; 8—artery, often anastomosing with each other. In the upper third of the arm, on the outside of the artery, lies
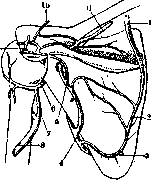
anastomosis between the aa. circumflexa humeri and profunda brachii; 10—a. thoracoacromialis; 11—a. transversa scapulae. In the upper third of the arm, on the outside of the artery, lies
the median nerve (Fig. —see Nerves of the human body), crossing it in the middle of the arm from the front and in the lower third from behind; after the crossing, the nerve is located on the inner side of the artery. The artery, veins, and nerve run along the anterior surface of the medial intermuscular septum, behind which runs the ulnar nerve and the superior and inferior collateral ulnar arteries.
From the upper part of the brachial artery emerges the deep artery of the arm (a. profunda brachii), which immediately goes backward and downward between the lateral and medial heads of the triceps muscle and, with the radial nerve, winds around the humerus posteriorly. The deep artery of the arm anastomoses with branches of the anterior and posterior circumflex humeral arteries, and through them with the a. thoracoacromialis. Figure 8. Anastomoses of the axillary artery from the front: 1—a. axillaris; 2—a. thoracoacromialis; 3—anastomoses between the a. thoracoacromialis and circumflexa humeri; 4—anastomoses between the a. circumflexa humeri and a. brachialis; 5—a. brachialis; 6—a. circumflexa humeri; 7—a. circumflexa scapulae; 8, 10 and 11—network of anastomoses; 9 and 12—a. transversa colli; 13—a. subclavia.
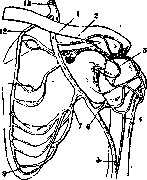
above and with the arterial network of the posterior
of the scapula, as a result of which a collateral pathway is formed from the subclavian artery to the brachial artery (Figures 7 and 8). Directly from the brachial artery or from one of its muscular branches arises the nutrient artery of the humerus (a. nutricia humeri), which penetrates into the bone through the nutrient canal. Next, somewhat below the previous one, arises the superior ulnar collateral artery (a. collateralis ulnaris sup.); it runs with the ulnar nerve to the elbow joint; it branches into the adjacent muscles. Two to three finger-breadths above the medial epicondyle arises the inferior ulnar collateral artery (a. collateralis ulnaris inferior), which runs in front of the epicondyle downwards and participates together with the previous one in the formation of the arterial network of the elbow joint. Variations of the brachial artery. Often, instead of a single trunk of the brachial artery, there are several parallel arterial trunks on the arm, arising either from the axillary or from the brachial artery at its very beginning and then replacing it; such arteries are called vasa aberrantia. Very rarely do they merge into one trunk or provide a continuation again in the form of a single brachial artery; more often, each passes into one of the arteries of the forearm, and six times more often into the radial artery (Giacomini). A case is known of the transition of vasa aberrantia into the artery of the median nerve at its distal end and a case of transition into the superficial palmar arch. Division of the brachial artery very rarely occurs below the cubital fossa (low or late division) and more often (10-12%) above the elbow; such a high or early division occurs most often in the upper third of the arm and very rarely in its middle and lower thirds. The site of division of the brachial artery into branches can rise to the axillary fossa and even to the neck. High division of the artery can occur in one of the following five ways: the brachial artery splits into 1) a. radialis and truncus interosseo-ulnaris, 2) a. ulnaris and truncus interosseo-radialis, 3) a. interossea or mediana and truncus radioulnaris, 4) a. radialis, a. ulnaris, a. interossea, 5) a. aberrans and a. brachialis. This anomaly of the division of the brachial artery (according to Quain) is unilateral in 43 cases out of 61 and bilateral in 18 cases. The volume, length, path, and branching of such arteries are very diverse. Upon reaching the forearm, they often become superficial, i.e., they run between the muscles and the aponeurosis or between the latter and the skin. Often the radial artery on the arm runs not far from the ulnar and, in order to become lateral on the forearm, it crosses the ulnar. Deep veins accompany the arteries in pairs. The external brachial vein runs to the middle of the axillary fossa and there, having crossed the artery from the front, merges with the previous vein. Lymphatic system of the arm—see Lymphatic system. Deep nerves of the anterior compartment of the arm: musculocutaneous nerve (n. musculo-cutaneus) and median (n. medianus)—see Nerves of man, Medianus nervus. Posterior compartment of the arm. The skin is thicker than in the front, mobile, and often covered with hair. Superficial arteries and veins are insignificant; they represent branches of the deep artery of the arm and a network of veins draining into the vv. basilica et cephalica. Superficial nerves—lateral cutaneous nerve of the arm from the axillary nerve, posterior cutaneous nerve of the arm (n. cutaneus brachii posterior), and in the lower part of the compartment the dorsal cutaneous nerve of the forearm (n. cutaneus antebrachii dorsalis); both of the latter are from the radial nerve. The aponeurosis is part of the general aponeurosis of the arm. The main content of the posterior compartment, not counting the lower section of the deltoid muscle, is the triceps muscle of the arm (m. triceps brachii, see Muscles of man). This muscle—a strong extensor of the forearm—consists of 3 portions (heads), one of which, the long head (caput longum), runs by a flat tendon from the infraglenoid tubercle of the scapula (tuberositas infraglenoidalis scapulae) between the teres minor and teres major muscles, partially covered by the deltoid muscle (Figures 9 and 10), and lies posterior and medial to the medial head (caput mediale); the latter begins from the posterior surface of the humerus, below and medial to the radial groove, and from the medial and lateral intermuscular septa; the fibers of the broad muscle belly run downwards, covering the anconeus muscle (m. anconeus); here the fibers pass into a flat quadrangular tendon, with which the tendinous bundles of the long and lateral heads merge. The lateral head (caput laterale) begins from the posterior surface of the humerus, above and lateral to the radial groove and from the lateral intermuscular septum; its fibers run downwards and pass over the radial nerve to the tendon of the medial head. The triceps muscle attaches to the olecranon of the ulna; besides extension, at the elbow, the long head of the muscle adducts the arm. The triceps muscle is innervated by the radial nerve, with the branches for the long head separating from the main trunk immediately below the lower edge of the teres major muscle; for the lateral head, several small branches arise below the previous ones; the nerve of the medial head enters its upper part, reaches the anconeus muscle within the thickness of the muscle, and innervates it (Figure 11). On the arm, the brachioradialis muscle and both radial extensors of the wrist also begin. On the posterior wall of the axillary region, two openings are formed: 1) for. quadrilaterum, bounded above by the m. subscapularis, below by the m. latissimus dorsi and m. teres major, in front by the collum humerale chirurg., behind by the cap. long. m. tricipitis, and 2) for. trilaterum, located medially from the cap. long. m. tricip. and bounded above by the m. subscapularis, below by the m. teres major, in front and laterally by the cap. long. m. tricip. Through the first opening pass the vasa circumflexa hum. et n. axillaris, through the second—a. circumflexa scapulae. The main artery of the posterior compartment of the arm is the deep artery of the arm (a. profunda brachii). Along its entire path, it gives off small branches for the integuments of this region and more significant ones for the triceps muscle; its most significant branches are the deltoid artery (ramus deltoideus), the middle collateral (a. collateralis media).
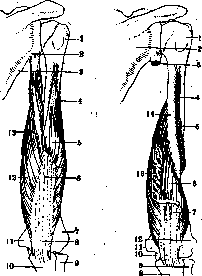
Figure 9.
Figure 10.
Figure 9. Triceps muscle: 1-tuberculum majus; 2-attachment of the long head; 3-edge of the scapula; 4-humerus; 5-lateral head; 6-tendon; 7-condylus lat.; 8-attachment of the muscle tendon; 9-radius; 10-ulna; 11-condylus med.; 12-medial head; 13-long head. Figure 10. Long head of the triceps muscle removed: 1-tuberculum majus; 2-scapula; 3-tendon of the long head; 4-line of attachment of the lateral head; 5-humerus; 6-medial head; 7-tendon; 8 and 9-ulna and radius; 10-attachment of the tendon; 11 and 12-medial and lateral epicondyles; 13-line of attachment of the long head; 14-radial groove.
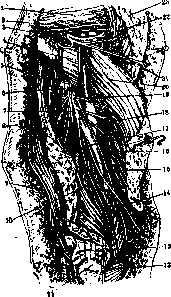
of the lateral head, several small branches arise below the previous ones; the nerve of the medial head enters its upper part, reaches the anconeus muscle within the thickness of the muscle, and innervates it (Figure 11). On the arm, the brachioradialis muscle and both radial extensors of the wrist also begin. On the posterior wall of the axillary region, two openings are formed: 1) for. quadrilaterum, bounded above by the m. subscapularis, below by the m. latissimus dorsi and m. teres major, in front by the collum humerale chirurg., behind by the cap. long. m. tricipitis, and 2) for. trilaterum, located medially from the cap. long. m. tricip. and bounded above by the m. subscapularis, below by the m. teres major, in front and laterally by the cap. long. m. tricip. Through the first opening pass the vasa circumflexa hum. et n. axillaris, through the second—a. circumflexa scapulae. The main artery of the posterior compartment of the arm is the deep artery of the arm (a. profunda brachii). Along its entire path, it gives off small branches for the integuments of this region and more significant ones for the triceps muscle; its most significant branches are the deltoid artery (ramus deltoideus), the middle collateral (a. collateralis media).
Fig. 1. Axillary and radial nerves: 1 - m. pectoralis minor; 2 - n. axillaris; 3 - a. circumflexa humeri post.; 4 - m. pectoralis major; 5 - radial nerve; 6 - a. thoracica longa; 7 - upper branch to the medial head of the triceps muscle; 8 - intermuscular septum; 9, 18, and 21 - cutaneous branch; 10 - medial head; 11 - olecranon; 12 - m. anconaeus; 13 and 17 - lower branch to the medial head; 14 - lateral cutaneous branch; 15 - a. profunda brachii; 16 - lower branch to the lateral head; 19 - upper branch to the lateral head; 20 - lateral head; 22 - branch to m. deltoideus; 23 - m. deltoideus. The deep brachial artery (a. profunda brachii) gives off the medial collateral artery (a. collateralis media), which runs within the substance of the medial head of the triceps muscle to reach the vascular network of the elbow, and a third branch, the radial collateral artery (a. collateralis radialis), which arises slightly below the middle of the arm between the lateral and medial heads of the triceps muscle and enters the elbow network (rete cubiti). In the lower part of the groove, the deep artery pierces the lateral intermuscular septum and enters the anterior compartment of the arm in the region of the cubital fossa. The deep veins accompanying it carry blood either into the axillary or brachial veins. There are no lymph nodes in the posterior compartment; the lymphatic vessels, both superficial and deep, drain into the nodes of the axillary fossa. In the posterior compartment of the arm, two large nerve trunks pass: the radial nerve (n. radialis) and the ulnar nerve (n. ulnaris). The radial nerve, having passed in front of the tendon of the latissimus dorsi muscle, goes to the posterior side of the arm through the gap between the surgical neck of the humerus, the long head of the triceps muscle, and the latissimus dorsi muscle. In the posterior compartment, the nerve runs obliquely from the inside outward and from top to bottom, in the groove, directly on the periosteum of the humerus, enveloped in loose adipose tissue. In the upper part of the groove, the nerve passes between the origin of the medial and lateral heads, covered above by the long head and below by the lateral head of the triceps muscle; in the lower part of its path, the nerve pierces the lateral intermuscular septum and penetrates into the anterior compartment of the arm and further into the region of the elbow joint, where it divides into two main branches. In the arm, the nerve gives off: the posterior cutaneous nerve of the arm (n. cutaneus brachii post.), the dorsal cutaneous nerve of the forearm (n. cutaneus antibrachii dorsalis), muscular branches (rami musculares) for the triceps and anconeus muscles, and after piercing the lateral intermuscular septum - branches for the brachioradialis muscle and for the extensor carpi radialis longus; a thin branch to the brachialis muscle is often encountered. The ulnar nerve runs along the medial edge of the arm along the projection line from the apex of the axillary fossa to the posterior surface of the medial epicondyle of the arm, a few millimeters behind the brachial artery and the median nerve, behind the medial intermuscular septum; the nerve runs accompanied by the superior ulnar collateral artery and its paired veins. Like the median nerve, the ulnar nerve gives off no branches in the arm.
A. Sirotkin - Pathology of the Arm. Congenital anomalies of the arm, like congenital deformities of other parts of the limbs, are caused by irregularities of the germinal primordia or mechanical factors—pressure from the amnion and uterus, the significance of which is especially emphasized by the French school. Complete absence or significant underdevelopment of the arm in combination with a similar anomaly of the forearm, with a more or less developed hand, is encountered in perobrachius or phocomelus (see Phocomelia). In these cases, the developmental defect consists in the absence or hypoplasia of the embryonic main ray of the upper limb. A very rare case of complete absence of the humerus with normal development of the forearm and hand is described by Brandenberg. Spontaneous amputations and amniotic bands of the arm are observed significantly less frequently than in the distal parts of the upper and lower limbs. In some cases, there is a painful conical stump, where the bone is covered only by scar tissue. A reduction in the size of the humerus and its congenital deformities are part of the clinical picture of diseases associated with dystrophic processes, such as chondrodystrophia, osteogenesis imperfecta, osteopsathyrosis, athyreosis congenita, and hereditary osteochondritis syphilitica. In congenital hypertrophies of the arm, as in other parts of the limbs, changes in the muscular, osseous, and soft tissues are observed, which are often combined with dilation of vessels, elephantiasis, and the formation of circumscribed lipomas. Traumatic injuries of the soft tissues of the arm, open and closed, are caused by the direct and indirect action of various kinds of traumatic force, depending on which the nature of the injury is determined. Contusions by a blunt instrument without disruption of the integrity of the skin, when the injury is localized on the inner surface of the arm, lead to significant subcutaneous hemorrhages. Standard treatment consists of a pressure bandage and rest for several days. In cases of large hematomas with detachment of the skin from the underlying tissues, puncture is used to aspirate the extravasated blood. Disruption of the integrity of the skin is caused by wounds from sharp instruments, machine injuries, and thermal and chemical burns. In treatment, under appropriate conditions, the method of choice is: primary suture for incised wounds, primary debridement followed by primary closure for machine injuries, and in the case of large skin defects, with the addition of skin grafting (see Wounds). In extensive burns, subsequent transplantation of skin flaps taken with a broad base from the skin of the back or chest is often indicated. In the case of superficial skin defects, one can limit oneself to Reverdin's epidermal transplantation. In injuries of the inner surface of the arm, and especially the axillary region, correct positioning of the limb in abduction and slight external rotation is important for future function, reducing the possibility of cicatricial contracture. Deeper open injuries of the arm lead to wounds of the muscles and are often combined with disruption of the integrity of vessels and nerves. Closed ruptures of muscles and tendons, which are mainly the result of the indirect impact of a traumatic force, are caused by a specific mechanism: Rupture of healthy muscles occurs from excessive increasing tension, excessive active contraction, or from sudden passive stretching of a muscle that is in a state of active tension (for example, when attempting to support a weight falling from above). Direct trauma to a tense muscle, a sudden blow, its compression, and damage by bone fragments in closed fractures can also cause subcutaneous rupture of a muscle. The injury may be localized in the muscle belly, at the site of its transition into a tendon, or in the area of the latter's attachment to the bone. A predisposing factor for muscle rupture is previous changes in them associated with past infections, alcoholism, or inflammatory processes, such as, for example, the mucous bursa of the biceps muscle in the case of rupture of its peripheral tendon or lacertus fibrosus (Ledderhose). Special significance is attached to changes in the sulcus intertubercularis with involvement of the biceps tendon passing through it in cases of deforming arthritis (Ledderhose, Gurlt). In terms of the frequency of subcutaneous ruptures of the muscles of the arm, the biceps muscle occupies first place; its injury, according to Maydl, is encountered in 22% of all ruptures. Pischler reports 222 cases of rupture of the m. bicipitis, with the long head being predominantly damaged. Rupture of the short head, as well as the m. coracobrachialis, is often observed in laundresses when wringing out laundry (Weber). Ruptures of the m. tricipitis and m. deltoidei are encountered less frequently (for example, Regard found damage to the m. deltoidei in 14 out of 128 cases of ruptures). The typical picture of a rupture consists of pain suddenly arising at the moment of the traumatic force, accompanied by a clear snapping sound and loss of function. Upon contraction of the damaged muscle, a more or less dense tumor forms, which terminates below the site of the rupture and disappears when the muscle is relaxed. In the case of a biceps rupture, the symptom described by Hueter has diagnostic significance—pain in the arm during flexion of the limb in a position of supination, while flexion of a pronated limb is impossible. Treatment: In cases of complete rupture of muscles and tendons, surgical intervention is indicated in the majority of cases; in fresh cases, muscle or tendon suture. In cases with a defect of muscle substance and decreased function of the limb, muscle flap grafting is used. In cases of tendon ruptures, the suture can be reinforced with fascial grafting at the suggestion of Payr. Subsequent methodical physio-mechanical treatment and the elimination of early loading of the damaged muscle are of essential importance to avoid recurrences. The prognosis in terms of restoring working capacity is quite favorable with timely therapeutic intervention on unchanged muscles. However, in the presence of pathological states of the muscles and tendons or with late surgical treatment, when cicatricial changes are already present, a significant decrease in function and a tendency toward recurrence remain. So-called muscle hernias, arising as a result of rupture of the fascia, are often observed in the region of the biceps muscle. Lexer and Baus distinguish between hernias with a damaged and an undamaged muscle; the latter are encountered rarely; they are characterized by bulging of the muscle through the fascial gap only in a state of rest and usually do not require treatment. If a muscle hernia is determined during muscle contraction, then in these cases there is damage to the muscle as well. Closed traumatic injuries of the arm, especially those caused by significant compressive force, can be accompanied by subcutaneous rupture of vessels, which has clinical significance only in the case of damage to large vessels. Disruption of the integrity of a vessel is also observed when it is wounded by bone fragments in fractures and dislocations of the arm, more often during their reduction (see Shoulder joint). Vessels with altered walls are naturally more fragile and are damaged by relatively minor traumas. Both complete rupture of a vessel, usually in a transverse direction, and partial damage to its wall are observed. Herzog collected 61 cases of injuries of the media with subsequent formation of a true traumatic aneurysm, with 18 cases involving damage to the a. brachialis and 7 cases to the a. axillaris. Clinical symptoms and prognosis in closed vascular injuries depend, on the one hand, on the caliber of the vessel, and on the other, on the nature of the injury and the outcome of the wound—the formation of a thrombus, a false or true aneurysm (see). Even complete rupture of such large vessels of the arm as the a. brachialis and a. axillaris does not always lead to necrosis of the limb, which depends on the rich blood supply and the formation of collateral circulation. The prognosis for the viability of the limb worsens with crushing of the surrounding soft tissues with damage to the vascular network and infiltration by extravasated blood. Open vascular injuries are encountered significantly more often in punctured, incised, contused, crushed, and, mainly, gunshot wounds of the arm. In gunshot wounds of an artery, in approximately half of the cases, there is a simultaneous wound of the vein (Haberer), leading to the subsequent formation of an arterio-venous aneurysm. Open injuries of large vessels—the aa. axillaris and brachialis—often cause fatal hemorrhages. In some cases, however, even with a transverse wound of an artery, spontaneous cessation of bleeding can occur due to the closure of its lumen by the clotted intima with subsequent formation of a thrombus. In lateral wounds, closure of the wound opening by adjacent tissues is sometimes observed. In the treatment of open vascular wounds, the primary focus is on combating the initial hemorrhage by applying a ligature (see Blood vessels—surgery). According to Wolff's statistics, necrosis of the limb occurs in 5% of cases after ligation of the a. subclaviae and a. brachialis, and in 15% after ligation of the a. axillaris.
Ligation of the brachial artery above the origin of the circumflex humeral artery is particularly unfavorable, as in these cases the anastomoses with the internal mammary artery and the descending branch of the transverse cervical artery are excluded. The prognosis is worsened by crushing of soft tissues and primary severe wound infection. Open injuries of the vessels, as well as closed injuries, in later stages lead, depending on the nature of the injury, to the formation of a pulsating hematoma, a false, true, or arteriovenous aneurysm with symptoms typical for them, and are subject to appropriate surgical treatment (see Aneurysm). Along with open and closed injuries of the vessels of the arm, traumatic injuries of the nerve trunks are also frequently observed. The mildest form of injury is pressure paralysis, among which a group of paralyses after anesthesia is distinguished, arising from the pressure of the edge of the table on the radial nerve when the arm is hanging down, from the pressure of the humeral head on the nerve bundle of the axillary fossa when the arm is maximally raised and abducted (Braun), or from entrapment of the brachial plexus between the clavicle and the first rib. The radial nerve is often compressed by fragments of the humerus during their dislocation, as well as by excessive callus formed. According to Bruns, out of 189 cases of nerve trunk injuries during fractures, 77 cases involved the radial nerve, with 69.2% of them occurring when the fracture was localized in the middle third of the arm. Cicatricial processes during suppuration, especially in open fractures resulting from gunshot wounds, often lead to the development of secondary, late paralyses due to nerve compression. A peculiar form of traumatic injury is dislocation of the ulnar nerve, arising either as a result of a fracture of the medial epicondyle of the humerus or due to strong sudden flexion at the elbow joint in the presence of a congenital flattening of the ulnar groove (Dubs). In the latter case, habitual dislocation of the ulnar nerve may develop, which requires surgical intervention: fixation with a suture through the perineurium (Tillmanns), plastic reinforcement of the posterior wall of the canal with a bone-periosteal flap (Muller), or deepening of the ulnar groove. Obstetric paralysis in newborns is also traumatic in nature, in which the abductors and muscles rotating the arm outward are most often paralyzed, the so-called upper radicular type of Duchenne-Erb.
Similar to vessels, traumatic injuries of nerve trunks are most frequently encountered in gunshot wounds of the limb. It is primarily the brachial plexus and the nerves of the arm that are damaged directly by the wounding projectile, by bone fragments, and as a result of the indirect impact of the traumatic force. According to American statistics (Toby Conn), among nerve wounds, the ulnar nerve is damaged in 31.6%, the radial nerve in 25.8%, and the median nerve in 23.4%. Deficits of motor and sensory functions to one degree or another, trophic and vasomotor disorders, paresthesias, and causalgias are diagnostic signs of nerve injury, and the combination of these depends on the nature and localization of the wound (see Nerves). Clinical symptoms do not always make it possible to establish the degree of nerve damage, since, on the one hand, the anastomoses of the upper limb are not fully studied, and on the other, anomalies of muscle innervation are often encountered, especially with regard to the ulnar, median, and musculocutaneous nerves. In wounds of the radial nerve, motor symptoms predominate; in wounds of the ulnar nerve, main en griffe often develops; injuries of the median nerve produce a pain syndrome, trophic and vasomotor disorders (P. Marie). Based on work from the Polenov clinic (Lyustritsky), when wounding nerves of the upper limb, symptoms should be ranked by diagnostic value in the following order: data on electrical excitability, motor disorders, and changes in the sensory sphere. Treatment. In mild cases of nerve damage from pressure, physio-electrotherapy can be successfully applied. Compression of the nerve by scar tissue, callus, or displaced fragments of the humerus requires surgical intervention (see Neurolysis). In the case of a complete interruption of the nerve trunk, to avoid secondary traumatic degeneration, the earliest possible nerve suturing is indicated, which, however, does not always yield success (according to Forster—38%, Staffer—57.1%, Perthes—45%) (see Nerve suture). Fractures of the humerus account for about 7% of all fractures according to Bruns; of these, 53% involve damage to the diaphysis along its length; epiphyseal fractures, leading to severe disturbances in the joints, constitute one of the chapters of the pathology of the shoulder and elbow joints (see Elbow joint, Shoulder joint). Most often, oblique fractures of the arm are observed. In the mechanism of fracture occurrence, the direct impact of force plays the leading role, less often indirect, e.g., a fall on the elbow or an outstretched arm. So-called "sports fractures" of the arm are usually encountered in individuals with well-developed musculature when throwing hand grenades, fencing, or playing tennis and gorodki. In their occurrence, the main role is played by the discoordinated action of muscle tension with a fixed shoulder joint. By the nature of the fracture, they are divided into "flexion fractures" with the localization of the fracture line just below the attachment of the deltoid muscle and torsion fractures (Küttner, Levashova). Diagnosis of a diaphyseal fracture is easy, as all typical symptoms of a fracture are usually present. Dislocation of fragments depends on the direction of the acting force and the disturbance of equilibrium in the tension of certain muscle groups. When the fracture is localized above the attachment site of the deltoid muscle, the upper fragment is displaced posteriorly and medially, the lower one anteriorly, superiorly, and laterally. In the most frequently encountered fractures in the middle third, below the attachment of the deltoid muscle, due to the pull of the latter, the upper fragment moves superiorly and laterally, and the peripheral fragment moves superiorly and posteriorly. Displacements of fragments can be ad longitudinem, ad axin, ad latus, ad periferiam, and combined. Complicated open fractures are encountered with the direct action of significant traumatic force due to the tearing of the skin by sharp bone fragments, but most often in gunshot wounds, which, according to Seidel, constitute 1/5 of all gunshot wounds of the upper limbs, with the humerus being primarily damaged. Simple gunshot fractures are observed rarely; mostly, comminuted and crushed fractures take place. The displacement of fragments depends more on the direction of the acting force, and since there is often damage to the musculature in the area of its attachment, the influence of muscle pull on dislocation in gunshot fractures plays a significantly smaller role than in peacetime fractures. Simultaneous damage to nerves is often observed, especially the radial nerve, accounting for 8.4% according to Bruns and 4.1% according to Rietmis. A severe complication in open fractures is wound infection, which, according to Seidel, occurs in 50% of all cases of gunshot fractures. Treatment of fractures without dislocation is reduced to maintaining the limb in the correct position by one method or another with the application of early movements. In the presence of large displacement, reposition of the fragments is performed under general anesthesia or local anesthesia (20 cm3 of a 2% novocaine solution according to Böhler) with subsequent application of extension splints, or treatment is conducted in a lying position using adhesive plaster traction in the physiological position of the limb according to the Bardenheuer principle. Wegner emphasizes that the so-called physiological position is the abduction of the limb from the trunk at an angle of 45°, in a plane standing at an angle of 45° to the frontal plane of the trunk. The transverse axis of the lower end of the arm, i.e., the linea intercondyloidea, must be turned medially in relation to the horizontal plane. In fractures of the arm with large displacement along the length, it is not always possible to eliminate the dislocation by means of adhesive plaster traction, which is why it has been proposed to apply traction directly to the distal fragment of the humerus in fractures of its upper and middle third, moving to skeletal traction (Codivilla-Steinmann nail, wire traction according to Klapp). For fractures of the arm, a wire is used, passed through the ulna 2–3 cm distal to the tip of the olecranon. During the past imperialist war, about 50 different types of splint bandages were proposed for the treatment of arm fractures (collected by Seidel), which can be divided into temporary, retaining splints, serving mainly for the transport of patients, and extension splints, of which, in the opinion of Sitenko, the most rational are the Böhler and Borchardt splints (see also Fractures, Traction). Indications for the use of a circular plaster cast in the treatment of arm fractures are extremely limited; it can be used mainly for immobilization of the limb after surgical intervention, and even then in exceptional cases (with specific indications). Early surgical treatment of arm fractures—osteosynthesis—is indicated in cases of simultaneous injury to vessels and nerves, interposition of soft tissues, or in cases where conservative treatment fails to achieve a satisfactory position of the fragments while preserving the normal axis of the limb. In open fractures, primary wound debridement with primary bone suture yields good results according to Koch and Rimann—up to 70% primary healing, with the key to success lying in the earliest possible intervention (within the first 6 hours after the trauma). Late complications of arm fractures are union in an incorrect position with impairment of limb function, the formation of a false joint, or large defects, which is observed not infrequently in open fractures with suppuration, when significant sections of bone are removed. According to Bruns, fractures of the arm have a definite tendency toward the formation of pseudarthrosis; thus, out of 681 cases of non-union fractures, 33.1% fall to the humerus. Methods of surgical treatment for pseudarthroses are various: free setting of fragments, application of wire suture (from various, preferably non-oxidizing metals), formation of internal and external splints by means of auto- and heteroplastic material. In cases of bone defects of the arm, free transplantation of fresh autoplastic bone material yields quite satisfactory results (Lexer, Eden, Hofmeister), with the transplanted section of bone needing to be sufficiently long. Spontaneous fractures of the arm are encountered in osteomyelitis, syphilitic changes of the bone, bone cysts, ostitis fibrosa, neoplasms, diseases of the central nervous system, and syringomyelia; especially often, according to Bruns, spontaneous fractures are observed in the mentally ill. Acute inflammatory processes can affect either the humerus or the surrounding soft tissues. The infectious agent penetrates into the soft tissues either from the outside during traumatic injuries, especially during wounding of the bone and joint, or per continuitatem, and sometimes the inflammatory process develops as a result of ascending infection along the lymphatic pathways.
Acute lymphangitis is accompanied by symptoms typical for it, with red painful streaks predominantly located in the region of the medial and lateral groove of the biceps muscle. In severe purulent lymphangitis, accompanied by the formation of abscesses along the lymphatic vessels, one can apply the suggestion to perform transverse incisions of the soft tissues of the arm down to the fascia to interrupt the lymphatic pathways. Together with the lymphatic vessels, the lymph nodes of the axillary fossa are also involved in the inflammatory process—lymphadenitis simplex et purulenta (see Lymphadenitis). Tuberculous inflammation of the shoulder joint with the breakthrough of pus through the joint capsule can lead to the formation of a typical cold abscess in the region of the Arm. Primary tuberculous myositis is extremely rare; it is comparatively more often secondary in nature. Tuberculous nodes with caseous necrosis are located either subfascially or directly in the muscle, separating its fibers. The diagnosis presents significant difficulties. It is necessary to differentiate it from a gumma, neoplasm, echinococcal cyst, hematoma, and other diseases. Diffuse syphilitic myositis occurs in the early period of the disease. Among other skeletal muscles, it is more often localized in the biceps and triceps muscles of the Arm. Sometimes their symmetrical involvement is observed (see Muscles). Among other chronic inflammations in the region of the arm, a peculiar inflammatory granulation process is encountered, caused by the appearance in the tissue of free and splitting fat, so-called oleogranulomas (see). They appear in the form of solitary or multiple painful nodules of various sizes, sometimes having a symmetrical arrangement. Oleogranulomas were observed especially often after the typhus epidemic at the site of injections of Ol. Camphorae, but often also independently of them. Abrikosov divides them into injection, traumatic, peri-inflammatory, and spontaneous oleogranulomas. Among parasitic diseases, isolated cases of the localization of echinococcal cysts in the region of the m. biceps (Dupuytren), m. brachialis (Gerdy), and m. triceps (Nelaton) have been described. Acute purulent osteomyelitis of the Arm arises on the basis of exogenous infection in open injuries due to the transition of the process from the shoulder or elbow joint, but mainly by the transfer of infection via the bloodstream, and is caused, just as in the involvement of other bones, most often by Staphylococcus pyogenes. According to the statistics of Gangolphe, involvement of the upper metaphysis of the Arm occupies third place in frequency; according to Haager, it constitutes 11% of all osteomyelitic diseases of the long tubular bones. The symptomatology of the disease does not present any peculiarities, nor do its outcomes, however, it should be noted that the shoulder joint is involved in the process less often than other joints, which is explained by the extra-articular position of the epiphyseal line. The breakthrough of pus to the outside most often occurs at the anterior edge of the deltoid muscle or in the region of the sulcus bicipitalis. Affecting predominantly children, the osteomyelitic process often leads to significant disturbances in the growth of the limb. The observed epiphyseolyses cause deformities of the upper end of the humerus; in spontaneous diaphyseal fractures, the formation of a pseudarthrosis often takes place. The danger of the occurrence of a general septic infection in involvement of the Arm is less than when the process is localized in the region of the thigh and tibia, in accordance with which the prognosis of the disease is also improved. Treatment of acute osteomyelitis of the Arm consists of opening the bone marrow cavity or in a more conservative intervention—incision of the soft tissues and periosteum, which is especially recommended for osteomyelitis in childhood (Krasnobaev). As an accompanying method of treatment, vaccine therapy (polyvalent or autovaccine), proposed for the treatment of osteomyelitis by Wright, gives good results in many cases; it is especially effective in forms not accompanied by general septic phenomena. For acute cases of osteomyelitis of the Arm, an incision in the middle third of the Arm is recommended, starting from the attachment of the deltoid muscle along the outer edge of the biceps; the incision can, if necessary, be continued upward with dissection of the fibers of the m. deltoideus. When extending the incision downward to free the lower epiphysis of the humerus, there is a danger of damaging the n. radialis, in view of which an additional incision can be made on the inner surface of the Arm. In extensive involvement of the Arm, total subperiosteal removal of the diaphysis is performed according to Ollier (Petrov, Romantsev). The significant ability of the periosteum to regenerate, especially in childhood, leads to the complete restoration of the bone defect. In chronic forms of osteomyelitis with the formation of purulent cavities and bone sequestration, an incision along the outer edge of the biceps muscle is usually used for necrotomy and sequestrectomy. Among conservative methods of treatment, the use of a mercury-quartz lamp undoubtedly has a favorable influence on the course of chronic osteomyelitis. The functional prognosis of the disease depends on the localization and extent of the disease, the involvement of joints in the process, and cicatricial changes on the part of the corresponding muscles and nerves.
Primary tuberculous lesions of the humerus diaphysis are rarely encountered as a diffuse disease, somewhat more often as a complication of tuberculous inflammation of the joint, and usually lead to the formation of bone tissue necrosis. When the embolic focus is localized in the cortical substance of the bone diaphysis, with its gradual destruction and the simultaneous formation of compact layers from the periosteum, a form of diaphyseal tuberculosis is observed that is very close to spina ventosa. For the X-ray diagnosis of diaphyseal tuberculosis, it is characteristic that periosteal growths are less pronounced than in acute inflammatory processes. In addition to general conservative treatment, in limited forms, it is possible to perform curettage of the cavity with the subsequent introduction of iodoform preparations, and in some cases, resection of the affected section of the bone. Syphilis of the arm is encountered more often in congenital disease (Stromeyer, Schreiber), and less often in the late stages of acquired affliction in the form of periostitis, diaphyseal and epimetaphyseal osteitis, and specific osteomyelitis. Osteochondritis syphilitica is observed in the region of the upper end of the humerus and leads to significant epiphyseal changes (see Shoulder joint). Among osteodystrophic processes in the humerus, a bone cyst (osteodystrophia fibrosa cystica localisata) is often observed, which, according to Reinberg, is only slightly inferior in frequency to true bone sarcoma. Occurring at a young age, usually under 20 years, a bone cyst is localized in the metaphysis of the proximal end of the humerus, appears elongated in the direction of the axis of the limb, and never occupies more than 1/4 to 1/3 of the length of the humerus. The clinical picture has no characteristic symptoms and is limited, for the most part, only to a uniform thickening of a specific section of the bone. In approximately 60% of all cases, a spontaneous fracture occurs, which also gives mild clinical symptoms: insignificant hemorrhage and soreness and a relatively small limitation of limb function. At the same time, a complete fracture is observed relatively rarely, mainly in diaphyseal cysts of the arm. Another type of localized fibrous osteodystrophy, called a "giant-cell tumor" (Nélaton) ("braune Tumoren" of German authors), in contrast to true bone cysts, rarely affects the humerus. Surgical treatment of bone cysts comes down to opening and curettage followed by swabbing the cavity with caustic substances. Lexer, Kaposi, and others perform resection of the affected section of the bone while preserving the periosteum, which as a rule is unchanged; an auto- or heterotransplant is transplanted into the place of the defect. The prognosis of the disease is quite favorable; surgical treatment gives excellent results. Changes in the humerus observed in widespread osteodystrophic processes, such as Recklinghausen's disease or Paget's disease, are part of the general picture of the disease, and in the first form, the humerus is affected just as often as the tibia, occupying second place in frequency; in Paget's disease, the changes mainly concern the lower extremities. The humerus, among other tubular bones, is a favorite site for the localization of parasitic cysts. Often the disease goes unnoticed and is diagnosed only upon the occurrence of a spontaneous fracture and the formation of an abscess, in the contents of which cholesterol crystals and remnants of the chitinous membrane are found. Treatment consists of removing the entire affected section of the bone followed by replacement of the bone defect. Neoplasms of the soft tissues of the arm do not present any peculiarities. Lipomas are encountered more often than others, sometimes reaching large sizes and originating from subcutaneous, subfascial, and intramuscular adipose tissue. The shoulder region is, after the back, the most frequent site for the localization of lipomas. Intramuscular tumors are observed more often in the region of the biceps, less often in the triceps, and appear either strictly delimited or have a more diffuse character. Their enucleation is performed easily, for the most part by blunt dissection. Among benign metaplastic processes of soft tissues, one should also include myositis ossificans circumscripta, which arises on the basis of acute or chronic trauma. In addition to the ossification process in the m. brachialis encountered after acute trauma, muscle calcifications have been found in the m. biceps (in gymnasts) and m. deltoideus. Surgical intervention is indicated only with negative results of conservative treatment in cases where there is an impairment of limb function. Among malignant tumors of the soft tissues of the arm, primary muscle sarcomas are encountered, originating either from the muscle itself or from its fascia (Küttner). Thus, individual authors have described sarcomas of the deltoid muscle and a spindle-cell sarcoma originating from the fascia of the arm. The prognosis of the disease is extremely unfavorable. Mortality, despite radical surgical treatment, reaches 44% (Landois). Relatively often, neoplasms originating from lymph glands are localized in the axillary cavity. Among benign tumors of the humerus, osteochondromas are observed more often than others; they differ little from osteomas and are localized in the majority of cases on the inner surface of the upper or middle third of the arm. The tumor has a wide base and a nodular surface with sharply defined contours. If the tumor occupies the epiphyseal end of the humerus, it never grows in the direction of the joint, but always eccentrically. Multiple chondromas, which mostly affect the metacarpal bones, can also be encountered in the region of the epiphysis of the arm; in their growth, chondromas do not cause invasion into the joint. Among malignant neoplasms of the humerus, sarcomas are in first place in terms of frequency. Gross, in 165 cases of sarcomas of long tubular bones, had 25 cases of humerus involvement; Kocher, in 65 cases, had 10. Osteogenic sarcomas, i.e., those originating from primitive bone cells, are encountered significantly more often than periosteal fibrosarcomas. Relatively often, osteogenic sarcomas develop from chondromas and cartilaginous exostoses. The most frequent localization is observed in the metaepiphyseal end of the bone, but for the humerus, the region of the deltoid tuberosity is also a typical site. The clinical picture consists of increasing pain, a rapidly growing tumor, and frequently observed spontaneous fractures and functional disturbances on the part of muscles, vessels, and nerves due to pressure or their invasion by the tumor. The X-ray picture can be extremely diverse depending on the size of the tumor, the nature of its spread, the predominance of the destructive process or the osteoblastic factor, and the greater or lesser reaction on the part of the periosteum. Differential diagnosis, both clinical and radiological, presents significant difficulties in the initial stages. The most common surgical intervention for sarcomas is amputation or exarticulation of the arm within healthy tissues. With high localization and widespread sarcomatous process, an interscapulothoracic amputation (see) is indicated. According to Berger, out of 64 cases of arm sarcomas for which an interscapulothoracic amputation was performed, in 3.12% death occurred immediately after the operation, and in 48.38% recurrences of the disease and metastases were noted. In some cases, mainly in the presence of a central sarcoma without periosteal invasion (König), it is possible, according to the suggestion of Mikulicz, to perform an extensive resection of the arm along its length, after which cases of long-term cure were observed. According to Kocher, out of 46 cases of limb sarcomas where an amputation or exarticulation was performed, recovery was noted in 7 cases; out of 5 cases of resection, 2 cures were noted. The prognosis for osteogenic sarcomas is threatening quoad vitam, and despite the most radical surgical treatment, the overwhelming majority of such patients die from recurrences and metastases of the sarcoma to internal organs. Another type of malignant neoplasm, which has a multiple character and is localized in the diaphysis of the bone, is the so-called Ewing's sarcoma, which is encountered at the age of 18-25 and belongs by its histological structure to endotheliomas. The humerus, along with the fibula and ulna, occupies the next place after the tibia in frequency of involvement. The course of this affliction is more benign than that of osteogenic sarcomas, and radiotherapy gives an undoubted effect. Among more rarely encountered malignant neoplasms, one should note multiple myelomas, when the humerus is affected along with other bones of the skeleton (see Myeloma). Among secondary metastatic neoplasms in the humerus, cancerous tumors are observed; the primary focus of the tumor is most often localized in the prostate, thyroid, or mammary gland. The metastatic cancerous process involves mainly the bones of the trunk; of the extremities, their central parts are affected more, which is why cancer metastases are encountered significantly more often in the humerus than in the bones of the forearm, where they are observed only in exceptional cases.
Among other metastatic tumors, one should mention hypernephroma, which can produce solitary metastases that possess a comparatively benign course. Surgical approaches to the arm have been developed depending on the purpose of the surgical intervention: exposure of a vessel, nerves, or the humerus. For the exposure of the brachial artery, there are two routes: direct and indirect. In the first, the incision is made exactly along the projection line of the artery, along the inner edge of the biceps muscle. A landmark is the median nerve, which in thin people, with the arm abducted, is easily palpable and visible through the skin. The median nerve in the upper third of the arm lies outside, in the middle—in front, and in the lower—inside the artery. Anomalies are relatively rare, where the artery lies in front of the nerve, as well as high divisions of it, with the weaker radial artery lying in front and the more powerful ulnar artery behind the nerve. In view of the fact that the posterior wall of the biceps sheath constitutes the outer wall of the arterial sheath, an indirect route appears convenient, in which the incision is made 1 cm outward along the projection line of the brachial artery. After incising the skin and superficial fascia, the sheath of the biceps muscle is opened and the latter is retracted outward; the inner wall of the sheath is incised over the median nerve, and the artery is found depending on the level at which the operation is performed. For the exposure of the radial nerve on the arm, in its upper half, the incision is made from the identifiable depression between the posterior edge of the deltoid muscle and the long head of the triceps and continues downward in the direction of the anterior surface of the medial epicondyle of the arm. After incising the soft tissues and exposing the edge of the deltoid muscle, the space between the long and lateral heads of the triceps muscle is widened by blunt dissection, and the nerve is found on the bone next to the deep brachial artery. From here, partly by blunt and partly by sharp dissection, the nerve can be exposed along its further course. In the lower third of the arm, the incision is made from the lateral epicondyle in the direction of the medial edge of the brachioradialis muscle; the nerve is found through the muscular space between the supinator and brachialis muscles and is accompanied by the radial collateral artery. In the upper two-thirds of the arm, the ulnar nerve is exposed by the same incision as the brachial artery, since it lies somewhat posterior to the median nerve. In the lower third, it curves around the medial epicondyle of the arm, passing through the ulnar sulcus. When exposing it in this section, the incision is made between the olecranon and the inner epicondyle of the arm; the easily palpable nerve lies under the aponeurosis. Exposure of the humerus is performed both for its trepanation in purulent processes and for resection due to neoplasms, bone cysts, etc. The incision is made along the lateral edge of the biceps muscle; after detaching the periosteum, the biceps and brachialis muscles are moved inward, and the triceps and brachioradialis muscles—outward. If it is necessary to expose the upper third of the arm, the incision can be extended upward along the inner edge of the deltoid muscle; when extending the incision downward, it is led between the brachioradialis and brachialis muscles, taking into account the possibility of damaging the radial nerve here. In the lower third, it is possible to make the incision from the outer epicondyle of the arm upward along the palpable edge of the humerus.

High amputations of the humerus (Fig. 12), even at the level of the surgical neck, are more advantageous for the purpose of prosthetics than exarticulation, as they provide a very short, but mobile stump. The scar is placed either on the surface of the stump or in the axillary region. The most common is the single-flap method of Farabeuf. The incision begins along the deltopectoral sulcus with the transection of the tendon of the pectoralis major muscle and the subsequent freeing and ligation of the vessels between two ligatures. The flap skin incision is made according to the outlines of the deltoid muscle; the points of the incision are connected through the axillary cavity, taking into account the specific contractility of the skin. Along the edge of the retracted skin, the deltoid muscle is transected from outside to inside, sparing the axillary nerve. Along the inner edge of the incision, all muscles are transected down to the bone, which is then sawed through.

Figure 13. Schematic representation of a cineplastic stump on the arm according to Sauerbruch: a—after the operation; b—finished. Figure 14. Formation of a loop from the biceps muscle.
In children, to avoid the formation of a conical stump, it is recommended to remove the epiphyseal cartilage. Amputation along the diaphysis of the arm can be performed either by a two-stage circular method or with the formation of two flaps, it being better to cut a medial and lateral flap than anterior and posterior ones. By suturing the antagonist muscles, a reduction in their contractility is achieved, especially of the biceps muscle. For the cinematization of the stump for the purpose of active prosthetics, plastic operations have been proposed by Sauerbruch, Anschütz, and Spitzy in 1916, which are based on the principle of forming muscle channels (Fig. 13 and 14). Osteoplastic operations for pseudarthrosis and defects of the arm are performed according to methods proposed generally for plastic surgery. In cases of large defects of the upper end, a freely transplanted bone-periosteal graft can be directly wedged into the glenoid fossa. Without resorting to subsequent plastic surgery of the arm after resection, Gersuny proposed the following methods that improve the future function of the limb: 1) transferring the attachment points of the deltoid, pectoralis major, and latissimus dorsi muscles, and 2) fixing the cut surface to the axillary edge or the lower angle of the scapula, which is indicated for more extensive resections (up to half of the arm).
Related articles
Cite this page
“Arm (Humerus).” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/brachium/