Scapula Alata
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article describes scapula alata (winged scapula) as a clinical sign of weakness in the muscles that fix the scapula to the thoracic cage. It details the anatomical causes, such as paralysis of the serratus anterior or rhomboid muscles, and notes its association with myopathies, amyotrophies, and other conditions.
Encyclopedia article (1928–1936)
SCAPULA ALATA, winged scapula, a sign indicating weakness of the muscles that fix the scapula relative to the thoracic cage; it consists of the scapula assuming a winged position, with its medial border and especially its inferior angle protruding from the thoracic cage; the scapula slides upward when the patient attempts to abduct the arm and follows the movements of the shoulder passively (see figure), as a result of which movements in the shoulder joint are limited and the patient cannot sufficiently raise or abduct the arm. Scapula alata occurs due to weakness of the serratus anterior muscle (m. serratus ant.), which presses the scapula against the thoracic cage and pulls it forward and outward (innervation: n. thoracalis ant., spinal center in CV–CVII), and the major and minor rhomboid muscles, which pull the scapula inward and upward and bring its inferior angle closer to the spine (innervation: n. dorsalis scapulae; spinal center in CV). Scapula alata is a characteristic sign of various forms of myopathies (Erb's juvenile form, facioscapulohumeral type, etc.) and amyotrophies (Werdnig-Hoffmann type) when the muscles of the shoulder girdle are involved in the disease. Scapula alata can occur with lesions of the spinal centers (syringomyelia), with diseases of the corresponding nerves, and with rickets. In the literature, there are isolated descriptions of scapula alata in healthy subjects, which in this case are explained by the ability to voluntarily relax the musculature significantly. Scapula alata in progressive muscular disease can be the object of orthopedic interventions. In the case of scapula alata due to paralysis of the serratus anterior muscle of traumatic origin, Willig used an operation to fix the scapula to the lig. supraspinale and to the IX rib (by means of a strip cut from the fascia lata) with a good functional effect.
S. Blinkov.

SCARLET FEVER. Contents: I.
608 II.
610 III. Statistics and geographical distribution . .
612 IV.
Pathological anatomy and pathogenesis . . . .
620 V.
630 VI.
652 IX.
657 Scarlatina, an acute infectious disease characterized by elevated temperature, inflammation of the throat, a fine-punctate rash with subsequent desquamation, and a number of typically occurring complications. History. Even to the ancients and in the Middle Ages (Hippocrates, Galen), a disease with throat inflammation and redness of the entire body was known, but it was not distinguished from measles. The first accurate description and modern name (scarlet fever) was given by the English physician Sydenham (1661). In the 18th and 19th centuries, epidemics were described in all countries of Europe and the clinical picture of the disease was developed in detail (Trousseau). From the end of the 19th century to the present time, along with the clinical picture, researchers have paid special attention to the study of etiology—the search for the causative agent, the development of methods of specific prophylaxis and therapy (Babes, Gabrichevsky, Dick, Caronia, and others). I. Etiology. In the search for the causative agent of S., a large number of microbes were discovered (bacteria, spirochetes, protozoa, filterable virus), to which attempts were made to attribute an etiological role in the origin of S. Such are Cyclasterion scarlatinae (Mallory), Chlamydozoa scarlatinae (Gamaleya), spirilla (Pospischill), diphtheroid bacilli (Mandelbaum), streptococci (Loffler, Babes, Moser, Gabrichevsky, and many others). Verification studies did not confirm the etiological role of the discovered microbes; some of them turned out to be accidental parasites, while others (e.g., Dohle bodies) were products of cellular nuclear decay. At the present time, there are three main views on the nature of the causative agent of S. I. The true and sole causative agent of S. is the hemolytic streptococcus, which possesses specific properties. The streptococcal theory of S. has existed for a long time (Babes, Loffler, 1882; Moser, Gabrichevsky, 1902–07), but it received a more or less solid foundation in 1923 after the work of the American scientists, the spouses Dick. The Dicks provide a number of proofs in favor of the streptococcal theory. Hemolytic streptococcus was found by them in all cases of S. They obtained the toxin of the scarlet fever streptococcus, which is neutralized by the serum of those recovering from S.; in this, the Dicks see the main feature of the scarlet fever streptococcus, which distinguishes it from hemolytic streptococci of other origins. The skin reaction with the toxin of this streptococcus (Dick reaction) is as specific for S. as the Schick reaction is for diphtheria: in the acute period of the disease it is positive, and in the recovery period it becomes negative in everyone. Supporters of the streptococcal theory see decisive proof in the Dicks' experiment with scarlet fever streptococcus toxin on humans. The Dicks injected a sufficient amount of toxin (0.1) into young healthy people who had not had S., and in some of them they obtained a disease resembling S.: elevated temperature, malaise, and a fine-punctate rash. Finally, the antitoxic serum obtained by the Dicks produced a very good therapeutic effect in scarlet fever patients. Thus, the Dicks view S., like diphtheria, as a toxicosis with a local infectious focus in the throat, from where toxins enter the blood and cause the clinical picture of S. Immunity in S. is purely antitoxic, which does not prevent streptococci from causing purulent complications in certain cases. At the present time, after numerous studies with scarlet fever streptococcus—bacteriological, experimental, clinical—one cannot fully accept the Americans' doctrine regarding the exclusive and specific role of hemolytic streptococcus and its toxin in the etiology and genesis of S. The specificity of the scarlet fever streptococcus cannot be considered proven, because the serum of those recovering also neutralizes the toxin of streptococci of other origins. The Dick skin reaction, as observations by many authors have shown, including those in the pediatric clinic of the 1st Moscow Medical Institute, remains positive in 25% of cases after recovery from S. The skin reaction with the toxin of septic streptococcus behaves similarly to the Dick reaction in scarlet fever patients (Agrachev). For this reason alone, it is difficult to consider the Dick reaction as the same indicator of immunity in relation to S. as the Schick reaction is for diphtheria. Few experiments with injecting toxin into humans have been performed, and the resulting syndrome has not been investigated with sufficient completeness. According to other authors (Burgers, Towada), a scarlet fever-like disease can be obtained with filtrates of all kinds of streptococci and even staphylococci and Escherichia coli. The pathological process in S. is more complex than in diphtheria, and it cannot be reduced exclusively to toxicosis. Thus, despite the entire importance of the research by the Dicks and other supporters of the streptococcal theory, these studies do not fully resolve the question of the causative agent of S. II. The causative agent of S. is a filterable virus. Some supporters of this theory believe that it exists in symbiosis with streptococcus. As early as 1911, Bernhardt, on the basis of experiments with monkeys, suggested that the microbe of S. should be classified in the group of filterable ones. In 1921–23, the Italian scientists Di Cristina and Caronia, from the organs of children who died of S. and from the filtrate of nasopharyngeal mucus, obtained a microbe anaerobically on media with pieces of tissue, which resembled a diplococcus. On the basis of serological reactions, experiments with rabbits, and mainly on the basis of experiments with children, they came to the conclusion that the microbe they found was the causative agent of S.: after injecting a culture of this microbe into children who had not had S., they observed in some cases diseases which they considered to be S. However, verification studies (S. Meyer, Burgers) did not confirm this view. The majority of modern authors consider the microbe of the Italian scientists to be a product of cellular decay. Among Soviet bacteriologists, the theory of the symbiosis of a filterable virus with streptococcus was supported and developed by Zlatogorov. This theory cannot be considered proven, but it also cannot be considered refuted. The clinical picture of S. provides some grounds for such a dualistic view of the etiology of S. (see below—the clinical picture of S.). III. Anaphylactic theory. According to this theory, there is no need to look for a specific causative agent of S.; it does not exist. S. is an anaphylactic reaction of a sensitized organism to any streptococcus. In the opinion of the extreme supporters of this theory (Szontagh), increased sensitivity to streptococcus can develop not only as a result of repeated infections with streptococcus, but even under the influence of intestinal autointoxication, physical fatigue, and a whole series of other factors of a non-infectious nature. Szontagh has long considered S. to be a non-contagious disease. The anaphylactic theory is held to a greater or lesser extent mainly by German pediatricians (Szontagh, Czerny, S. Meyer, Schlossmann, Fanconi); among Americans, Dochez has recently inclined toward it. At first glance, the anaphylactic theory is appealing due to its simplicity and the possibility of explaining certain facts from the epidemiology and clinical picture of S. (in some individuals in a group, S., in others, angina), and mainly because it assigns the main role in the origin of S. not to the microbe, but to the macroorganism, which corresponds to the modern understanding of the etiology of infectious diseases. However, if one compares it with the basic facts of the epidemiology of S. (the emergence of epidemics in isolated areas after long intervals following the arrival of a scarlet fever patient there, the proven contagiousness of S.), one cannot agree with it. Thus, the question of the causative agent of S. must at the present time be recognized as open; further research is necessary; in any case, it should be noted that all modern theories—some to a greater, others to a lesser extent—assign a significant role to streptococcus in the etiology of S.
fc, II. Epidemiology. In large cities and densely populated areas, scarlet fever exists endemically; at certain intervals of time (5-10 years), more or less severe epidemics break out. The causes of the wave-like course of scarlet fever epidemics are not precisely known; as a more probable cause, periodic changes in the population's susceptibility to scarlet fever are pointed out. Regarding the influence of meteorological factors, there are contradictory data. Brownlee found for London that in rainy years with a large amount of precipitation, the incidence of scarlet fever is higher than in dry years. Benda gives the opposite relationship for Berlin. -Modes of transmission. The source of scarlet fever infection is primarily the scarlet fever patient. Overtly ill patients, especially those hospitalized, are less dangerous than those in whom scarlet fever runs a rudimentary course; the disease in them often remains unrecognized, and the patients are not isolated. Such carriers of scarlet fever infection are usually adults, in whom scarlet fever often runs its course under the guise of tonsillitis. Apparently, healthy individuals can also be carriers of the infection if they are in close contact with a patient for a long time. The scarlet fever virus is contained in the mucus from the throat and nasopharynx and is transmitted to healthy individuals via droplet infection, as well as by direct contact. The infectivity of throat secretions was proven by Stickler in his experiments on healthy children. Urine and feces are not infectious. The question of the infectivity of desquamation, which remained controversial for a long time, is resolved in the negative by the majority of modern authors. Desquamation may prove infectious under special conditions, when the patient is not given baths and the desquamation becomes contaminated with throat secretions. The patient is infectious from the first day of the disease. It is impossible to give an exact answer as to how long the infectivity lasts. Examination of the throat for hemolytic streptococci cannot serve as a reliable criterion. The condition of the throat and the presence of purulent complications (otitis, lymphadenitis) are of greater importance (see below, prevention of scarlet fever). Scarlet fever can be transmitted through objects and things that have been in use by the patient, but how long the scarlet fever virus persists on them is a controversial question. Reports about the infectivity of such objects for many years (Golliner) must be treated critically. Scarlet fever can also be transmitted through food products, e.g., through milk. The portal of entry for scarlet fever infection is the cavity of the throat and nasopharynx. According to Schlossmann, a necessary condition for the penetration of the microbe must be damage to the integrity of the mucous membrane. In rare cases, the infection can penetrate the body through damaged skin and the mucous membrane of the genital organs in women (extrabuccal scarlet fever, puerperal scarlet fever). Predisposition to scarlet fever in humans is generally not great, significantly weaker than in relation to measles. The infectivity coefficient of scarlet fever, according to Gottstein, is about 40%, while for measles it is 95%. It is generally accepted that predisposition depends on 1) age, 2) constitution, and 3) the state of the organism at the moment of infection. Children aged 3 to 10 years are most susceptible (see below - statistics). In the first year, scarlet fever is encountered relatively rarely; during the first 3 months, scarlet fever constitutes a very rare exception. True, cases in newborns have been described, but not all of them are impeccable regarding the diagnosis. The low susceptibility of infants depends mainly on passive immunity received from the mother, but other, little-known causes are also possible (insufficient cell differentiation, lack of sensitization, etc.). The immunity of adults is explained by active immunity resulting not only from overt, but also from rudimentary or even silent infection. The course of scarlet fever in infants and adults presents significant peculiarities (see below, clinical aspects of scarlet fever). The role of the constitutional factor is far from being fully studied. According to Czerny, children with exudative diathesis and lymphatic constitution are especially predisposed to contracting scarlet fever, and it runs a severe course in them. In neuropathic children, scarlet fever also has a severe course. Attempts were made to clarify the role of the constitutional factor in the predisposition to scarlet fever by studying blood groups in children and their parents (Hirszfeld and Brokman, Rubasheva and Jacobi). It turned out that all groups are equally susceptible to scarlet fever; both the form and the complications do not depend on the blood group. But there is a regular connection between the Dick reaction in children and their parents. Children with the same blood group as a parent with a positive Dick reaction persistently retain a positive reaction after scarlet fever; children with the same blood group as a parent with a negative Dick reaction show a negative reaction after scarlet fever. The state of the organism at the moment of infection undoubtedly influences predisposition, but it is difficult to say to what this influence should be most directly attributed. According to Czerny, overfeeding, especially with milk and eggs, increases the predisposition to scarlet fever, as it intensifies the phenomena of exudative diathesis and leads to hypertrophy of the tonsils. Kobrak found that in families with insufficient nutrition, cases of scarlet fever are less frequent than in families with satisfactory and excessive nutrition. The role of socio-living factors is evaluated differently by various authors in capitalist countries. Everyone agrees that mortality among proletarian children is higher, but the incidence of scarlet fever among them, according to the observations of some authors (Flügge, Benda), is higher, and according to the studies of others (Reiche), lower than among the affluent strata of the population. Studies by Soviet doctors have shown that poor socio-living conditions lead both to increased incidence and to a more severe course of scarlet fever. Kaminsky found for St. Petersburg (1900-10) that the incidence of scarlet fever among the wealthy population was 185.8 (per 100,000), the well-to-do 215.9, the needy 248.6, and the poor 261.8; the mortality coefficient among the wealthy was 11.8, the well-to-do 13.2, the needy 16.4, and the poor 19.9. The influence of the housing and living factor is especially great. On one hand, overcrowding and close contact with the sick and carriers of the scarlet fever virus create favorable conditions for infection. The role of overcrowding was proven by Dudley through an epidemiological survey of the naval school in Greenwich (for 1912-24) and some children's collectives; the incidence of scarlet fever was higher in dormitories with a large number of beds and with an insignificant distance between the beds. On the other hand, the lack of light and air adversely affects the child's organism and its immuno-biological state, making it less resistant to scarlet fever infection. There are indications that some races are not very susceptible to scarlet fever, for example, the population of Central Asia in the USSR. But the influence of racial, as well as familial factors, cannot be considered established, and here, first of all, one must take into account cultural and living conditions. Immunity after scarlet fever is not absolute. Undoubted recurrent cases are observed more frequently than recurrent cases of measles.
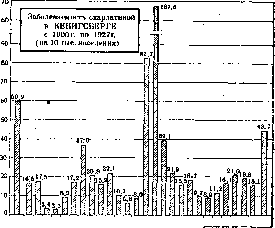
V. Molchanov. III. Statistics and geographical distribution. Scarlet fever is distributed throughout the entire globe. Its morbidity rate shows large fluctuations by individual countries and in individual periods of years. In Western Europe, over the last years, more than 400,000 cases of scarlet fever and about 12,000 deaths from it are registered annually; in the USA—about 200,000 cases and about 2,500 deaths. Tables 1 and 2 present the morbidity and mortality rates for 1921–1930 in different countries. The highest morbidity rates for all these years are observed in England and Scotland, the lowest in North Africa (Egypt, Tunisia, Algeria), in Japan, and Korea. In the second half of the indicated decade, a noticeable rise in morbidity is noted in a number of countries (USSR, Germany, Holland, etc.). Mortality rates by individual countries do not correspond to morbidity: in England and Scotland, for example, where morbidity is the highest, mortality is significantly lower than in Romania and Yugoslavia, where its rates are the highest, and lower than in Italy, Poland, and Czechoslovakia. This discrepancy between the rates can be explained either by the incompleteness of morbidity registration in the latter countries or by unequal lethality (see below). The lowest mortality rates among European countries are noted in Switzerland, and among non-European ones—in North African countries and Japan. The most complete data on the distribution of scarlet fever can be obtained from the materials of large cities (completeness of registration and accuracy of diagnosis). The highest mortality rates over the last 5 years in European countries were observed in the cities of Hungary, Greece, Spain, Italy, Lithuania, Poland, Romania, Estonia, and Yugoslavia (Figure 1); in non-European countries—in the cities of Turkey, Canada, and Argentina. The lowest rates are noted in the cities of North Africa and South America (Brazil, Peru). In the provided Tables 1 and 2, mortality rates calculated for the entire population were presented. Table 3 presents the corresponding rates for some countries, calculated over a long period of years (from 1861 to 1925) for the child population (under the age of 15). These figures speak to a significant decrease in mortality from scarlet fever in the listed countries. To study the patterns in the movement of scarlet fever, a number of authors have carefully collected materials on mortality from it in individual cities over a long period of years. For Königsberg, for example, corresponding materials have been collected starting from 1779 (Kisskalt), for Hamburg—from 1820 (Burgers), for Berlin—from 1861 (Nesemann, Kaiser). Figures 2–4 present several such curves for large cities. Their study indicates the presence of rises and declines in scarlet fever over a number of years. It is not possible to establish regularity in the intervals between these rises. Burgers calculates them for German cities at 8–10–16 years, Robertson for Chicago—at 3–6 years. The causes of these fluctuations in scarlet fever morbidity have not been studied. It must be thought that social factors play the main role among these causes. In particular, there is no satisfactory explanation in world literature for the cause of the decline in scarlet fever in a number of countries after the World War. The theory put forward at one time by Cantacuzene regarding the antagonism between scarlet fever and typhus contradicts the facts and is supported by nothing.
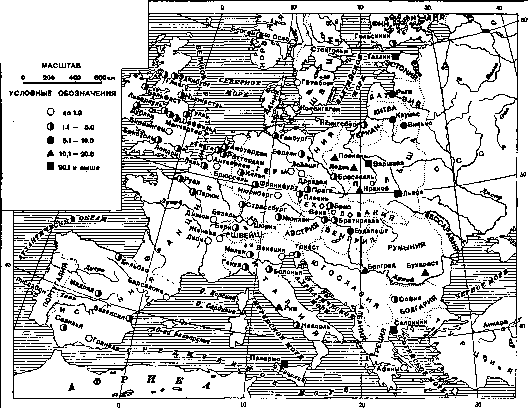
Figure 1. Mortality from scarlet fever in large cities of Western Europe in 1926–1930 (on average per year per 100,000 population).
is not substantiated. The theory supported by a number of authors (Czerny, Kobrak, Schlossmann, and others) regarding the connection between insufficient protein nutrition (in particular milk and eggs) and the decline of Scarlatina also does not withstand criticism. We are inclined to associate this decline in Scarlatina with the decrease in the child population as a result of the World War. Table 3. Mortality from scarlet fever among children under 15 years of age (per 100,000 children of the corresponding age). Years Sweden Scotland 1861-70... 1881-90... 1891-1900... 1901-10... 1911-20... 1921-25... 271 197 94 47 38 16 11 121 28 13 15 7 3 250 210 79 54 26 35 23. Scarlatina in the USSR. In Russia, before the World War, from 400 to 500 thousand cases of Scarlatina were registered annually, from 21 to 32 cases per every 10,000 inhabitants. In terms of Scarlatina morbidity, pre-war Russia occupied an extremely high place compared to the majority of Western European countries. After the World War, a noticeable decline in it is noted. A new rise in Scarlatina ended in 1930, and subsequently, a sharp decline in it is noted (Table 1). Morbidity by individual republics of the Union is not uniform: it is highest in the RSFSR, Ukraine, and Belarus; Scarlatina is registered significantly lower in the Transcaucasian and Central Asian republics (Table 4). The curves of morbidity and mortality from Scarlatina in Moscow, Leningrad, and Odessa give an idea of its movement in large cities of the USSR over a long period of years (Figures 6, 7). Scarlatina morbidity in cities and rural areas. A number of researchers note the uneven distribution of Scarlatina. Table 4. Scarlatina morbidity by individual republics of the USSR (per 10,000 population). Republics 1924 1925 1926 1927 1928. RSFSR... Ukraine... Belarus... Azerbaijan... Armenia... TurkSSR... Uzbekistan... 14.5 14.6 15.0 2.1 0.06 0.8 18.5 18.8 18.5 3.3 0.3 0.6 0.2 0.5 20.6 37.1 29.8 5.1 4.4 1.6 0.09 1.6 21.7 36.5 22.6 9.8 3.7 3.7 1.3 1.5 20.8 24.1 28.5 19.5 1.1 1.1 in cities and rural areas: in the former it is higher than in the latter. According to Reiter in Mecklenburg (Germany) for the period from 1903 to 1927, morbidity per 10,000 inhabitants was 13.7 in the city and 4.1 in rural areas. According to Vaughan, mortality in the USA per 100,000 inhabitants in cities is approximately 2 times higher than in rural areas. The same ratios (higher morbidity in cities) can be seen in the materials for Moscow and the Moscow Governorate (Table 5). The uneven morbidity in cities and rural areas must be explained by reasons of a social nature: great overcrowding in cities, and consequently, more favorable conditions for contact infections. Morbidity and mortality by
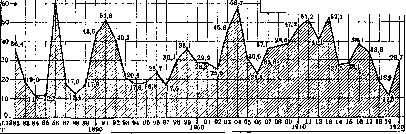
Scarlatina morbidity in BUDAPEST from 1882 to 1920 (per 10,000 inhabitants) Figure 2. age and sex. Corresponding materials are presented in Tables 5 and 6 (see Figures 8, 9). Table 5. Scarlatina morbidity by age groups and sex in Moscow, Moscow Governorate, and Berlin (per 10,000 population of the corresponding age). Moscow, 1926. Moscow Governorate, 1926. Berlin, 1912-14, both sexes. Under 1 yr. 1-4 yrs. 5-9 yrs. 10-14 yrs. 15-19 yrs. 20-29 yrs. 30-39 yrs. 40-49 yrs. 50-59 yrs. 60 yrs. and older. 46 99.1 102.7 144.6 78.7 19.2 Table 6. Morbidity and mortality from scarlet fever by age groups in Leningrad from 1/VII 1926 to 1/VII 1927 (per 10,000 population). Age Morbidity Mortality Age Morbidity Mortality Under 1 yr. 1
2 yrs. 3 yrs. 4 yrs. 5 yrs. 6 yrs. 7 yrs. 8 yrs. 9 yrs. 10 yrs. 75.4 265.4 321.8 381.3 415.3 402.7 390.8 308.8 289.5 282.0 206.3 1 19.9 54.0 41.0 33.7 26.2 11.1 11.1 10.1 6.7 9.6 4.1 11 yrs... 12 yrs... 13 yrs... 14 yrs... 15-19 yrs... 20-29 yrs... 30-39 yrs... 40-49 yrs... 50-59 yrs... 60 yrs. and older. 158.7 140.9 99.3 67.5 29.0 8.1 3.8 1.4 0.7 0.3 1.3 3.4 1.3 0.4 0.7 0.4 0.1 0.1 0.1 The most frequent morbidity is observed at the age of 1 to 9 years (at the age under 1 year it is significantly rarer), the highest mortality is at the age of 1 to 4 years. According to the detailed Leningrad data (Table 6), morbidity is highest at the age of 3 to 6 years, mortality from 1 to 4 years (materials from foreign countries agree with this). The susceptibility of individual age groups to Scarlatina can be judged by its epidemic in 1873-1875 on the Faroe Islands, where there had been no Scarlatina for 57 years prior. In total, 38% of the population contracted scarlet fever (measles - 99%). Hoff calculated the morbidity on these islands relative to the number of inhabitants of certain ages, taking into account only persons who were exposed to the danger of infection (living in houses where there were scarlet fever cases). He obtained the following indicators (Table 7). Mention should also be made of the relatively high Scarlatina morbidity in a number of armies (i.e., among adults) of those countries where its morbidity is generally quite low. An example is the French army, where over the last decade morbidity per 1000 people fluctuated from 1.56 to 2.64, and mortality from 0.009 to 0.07.
From 1886 to 1895, according to Dopter, mortality from Scarlatina in the troops of the Paris garrison (20.4 per 100,000) was 3 times higher than that among men in Paris aged 20 to 24 years (6.5). Table 7. Age 0-1 1-5 5-15 15-20 Percentage of cases 66.6 67.1 63.9 75.0 Age 20-40 yrs... 40-60 yrs... 60 yrs. and older Percentage of cases 23.4 2.9 1.8. Lethality in Scarlatina shows significant fluctuations both in different countries and in the same country (city) in different years, depending on the nature of the epidemic. If we proceed from the figures of registered cases of illness and deaths, then, for example, in 1925, it constituted the following percentage in different countries: in Belgium - 23.0, in Italy - 16.4, in Japan - 11.0, in Czechoslovakia - 4.0, in Germany - 2.1, in England
2.1, in the USA - 1.5, in Sweden - 0.6. In Königsberg for the period from 1900 to 1915, it fluctuated in individual years from 1.4% to 23%, in the hospitals of the city of Moscow for the period from 1900 to 1928 - from 5.1% to 21%. In recent years, in a number of countries (England, Germany, Denmark, Sweden, Switzerland, USA), Scarlatina has been running a mild course with low lethality (1% and lower). Figure 10 gives an idea of the fluctuations in lethality by individual years. The age factor has a huge influence on the level of lethality: the younger the patient, the greater the danger of a fatal outcome. According to data from Moscow hospitals for 1900-28, lethality for individual age groups constituted the following percentage (Table 8, Figure 11). Table 8. Age Lethality Age Lethality 5-9 yrs... 39.2 16.0 5.6 10-14 yrs... 15-19 yrs... 20 yrs. and older 3.3 4.5 7.1. Scarlatina morbidity in RUSSIA and the USSR, for 1890-1928 (per 10,000 population). Similar data have been noted in the hospitals of Leningrad and Western European states.
Seasonality of morbidity. The main mass of scarlet fever cases falls on the autumn-winter period; in summer, their number decreases sharply. Such a distribution of diseases is explained mainly by living conditions - greater overcrowding in the autumn-winter months and the intensification of contact infections in connection with this; in the opinion of some authors - by meteorological factors influencing the increase in the frequency of "colds" in these months, which should contribute to easier susceptibility to scarlet fever infection. Figure 12 shows the monthly curves of Scarlatina for some countries (everywhere calculated as average daily monthly to average daily annual). In the RSFSR and Ukraine, the rise begins in September; the high standing of scarlet fever as a whole in the RSFSR continues through March, in Ukraine through January. In individual cities, the maximum of the curve occupies a shorter period, for example, in Moscow - from October to December.
I. Dobreytser. IV. Pathological anatomy and pathogenesis. The most characteristic tissue reaction at the site of primary fixation of the scarlet fever virus is rightly considered to be necrotizing inflammation, which in acute cases is most often determined on the autopsy table. Less often, this process is catarrhal, and very rarely fibrinous in nature (so-called scarlet fever diphtheria or croup). It should be borne in mind that although mild cases of scarlet fever almost always proceed with catarrhal angina (with the usual localization of the primary scarlet fever affect), one cannot draw the opposite conclusion from this, since the catarrhal reaction in scarlet fever itself (in contrast to diphtheritic catarrh) does not in the least ensure either a mild course or a favorable outcome of the disease. On the contrary, it is a well-known fact that the same reaction is no less characteristic of the most severe, so-called toxic forms. Death from scarlet fever, with the exception of the just-mentioned rare toxic forms, is in the vast majority of cases death from septicemia. Among other factors that can cause a fatal outcome, one should mention kidney damage, erosions and perforations of the cervical vessels due to the spread of purulent-necrotic processes from the surrounding tissues of the neck to them, and finally, pneumonia. Returning to the toxic forms, first of all, it should be noted that the pathological-anatomical picture observed here turns out to be rather poor in characteristic features. The most striking in
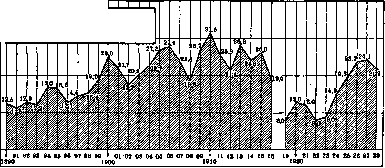
Figure 5.
it, besides the rash, is the lesion of the upper part of the digestive tract, but even this does not represent anything specific. Usually, this is a very sharp catarrh, capturing not only the fauces and pharynx, but almost always spreading to a greater or lesser extent to the esophagus as well. The mucous membrane of the named parts swells, takes on a saturated dark red color, often with a cyanotic tint, and a velvety appearance. The latter is explained by the necrosis of the superficial layers of the epithelium, which deprives the mucosa of its normal luster. If the necrosis of the epithelium goes somewhat deeper, then the color of the mucosa in such places acquires a correspondingly more gray
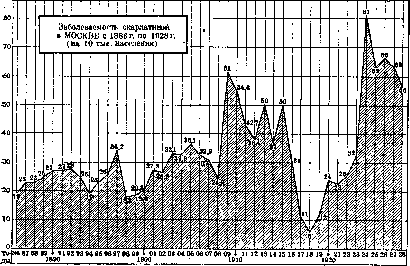
FIG. 6.
ish or yellowish tint. The tonsils usually swell more or less strongly, but this symptom never gains predominant significance here. The surface of the tonsils retains the same appearance as the surrounding mucosa of the fauces, while on cross-section they often reveal necrotic areas, distinguished by their pale whitish color and located mostly along the walls of the crypts, due to which they most often have the appearance of stripes directed perpendicular to the surface. Swelling of the cervical lymph nodes in this form is also usually moderate, sometimes quite insignificant. Its anatomical substrate here, as in all other forms of scarlet fever, is inflammatory edema and hyperplasia of both the follicular and, mainly, the reticulo-endothelial apparatus, occasionally with a fairly clearly expressed myeloid metaplasia of the lymphadenoid tissue along the periphery of the follicles. The glands are tense, succulent, gray-pink or gray-red in color; necrosis in them is observed rarely. Mostly, a reaction from the more distant parts of the lymphatic system is added to this in the form of moderate enlargement of the mediastinal, mesenteric, and retroperitoneal glands, as well as the follicles and Peyer's patches of the intestines. The spleen in toxic forms does not react strongly and mainly from the side of the lymphatic apparatus, and in the most acute cases (so-called scarlatina fulminans) its enlargement may be almost completely absent. Partial necrosis of the follicles may be added to their hyperplasia, due to which they stand out particularly clearly with their whitish color against the dark red background of the congested pulp. In some cases, both in the pulp and along the periphery of the follicles, myeloid metaplasia is clearly expressed. Even more often than in the follicles of the spleen, one can observe punctate necroses in the liver, where they are best seen from the surface in the form of pale yellowish dots shining through the capsule. As the microscope shows, they are sometimes found in the liver tissue in very large quantities, being scattered without any particular order inside the hepatic lobules. It is also necessary to note changes in the sympathetic and parasympathetic ganglia (mainly in the cervical sympathetic nodes and in the gangl. nodosum et jugulare n. vagi), indicating significant damage to the autonomic nervous system. They are mainly destructive in nature and affect the majority of ganglion cells, in which pictures of karyolysis and cytolysis of various degrees are determined, as well
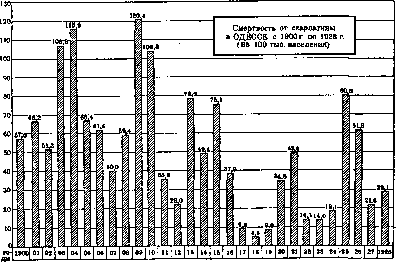
Figure 7.
as degenerative fatty degeneration and necrosis. Inflammatory changes in the interstitial tissue are almost absent here. Otherwise, the damage to the organism in this form boils down to a circulatory disorder in the form of general venous congestion and to protein and fatty degeneration of the parenchymal organs. Thus, on the one hand, shallow local changes, a moderate reaction from the regional lymph glands, the absence of significant, and sometimes any, enlargement of the spleen, as well as inflammatory changes in the stroma of internal organs, and on the other, a sharply expressed drop in the tone of the vascular system—all this fully justifies classifying such forms of scarlet fever into the toxic group. Bacteriological data also speak for this, since not only do blood cultures from the heart give a negative result in these cases, but sometimes streptococcus cannot be detected even in the fauces. Where death occurs in later periods, always, if not in the clinical symptom complex, then upon anatomical and histological examination, certain septic features clearly emerge. The main signs of the septic form are:
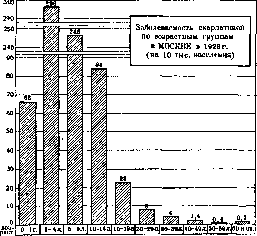
Figure 8. 1. Significantly greater intensity of local changes. Necroses here are always so deep that the underlying vascular network ceases to show through, due to which the corresponding areas of the mucosa receive a cloudy grayish or yellowish color. At first, the mucosa is only cloudy, but soon, due to the detachment of small particles of necrotic tissue, it becomes rough. The deeper the necrosis, the larger the size of the sloughing particles, which either form a layer of crumbly decay on the surface or, mixing with the mucopurulent discharge, turn into a mushy mass, sometimes very reminiscent of softening fibrinous membranes. The tonsils in this form can enlarge particularly strongly; at the same time, they are usually necrotic on the surface and permeated with necrotic foci in the depths. 2. A sharp reaction is observed from the regional lymph glands. The latter are greatly enlarged, very succulent, with a tense capsule, of a characteristic yellowish color, and always contain necrotic foci. Under the microscope, the vessels in them are barely noticeable; inflammatory edema, proliferation of the reticulo-endothelium, and myeloid metaplasia prevail. Often, in the glands, as well as in the tonsils, small foci of incipient purulent melting are discovered. Other parts of the lymphatic apparatus react in a similar way, although to a lesser extent than in the neck. Mortality from scarlet fever by age groups in MOSCOW in 1926 (per 10 thousand population)
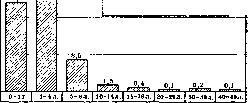
Figure 9.
react in a similar way, although to a lesser extent than in the neck. 3. The spleen is significantly enlarged (2-3-5 times or more against the norm), gives a typical picture of acute hyperplasia, also usually with clearly expressed myeloid metaplasia of the pulp and the peripheral zone of the follicles. An exception to this rule is represented only by very small children (up to 1 1/2 years old) and rachitics, in whom the spleen usually reacts weakly. 4. Degenerative changes (mainly in the form of cloudy swelling) of the parenchymal organs (liver, kidneys, myocardium, adrenal glands) are extremely strong, in which, under the microscope, one can very often also detect an acute interstitial inflammatory process (so-called septic hepatitis, nephritis, etc.). Toxic and septic scarlet fever represent, of course, images of extreme types, between which there exist countless transitions, and furthermore, they concern only particularly severe cases ending in death within the first week of the disease. As for the majority of patients dying from scarlet fever, they end up on the autopsy table in
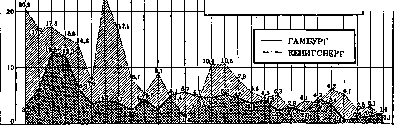
Lethality from scarlet fever in HAMBURG and KONIGSBERG from 1900 to 1927 (per 100 cases) 07 08 09 11 12 13 14 15 16 17 18 19 21 22 23 24 25 26 27 Figure 10. later periods, as a result of which the changes observed here are distinguished by significantly greater number, variety, and depth. First of all, this refers to the primary necrotic process in the fauces and pharynx. The latter does not always spread over the entire surface of the indicated organs, but very often is limited only to individual 62 Lethality from scarlet fever by age groups in MOSCOW hospitals from 1900 to 1928 (per 100 patients)
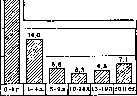
Figure 11.
areas of the most diverse size and shape. In some cases, necrotic changes, as already indicated, involve only the tonsils; in others, they are found almost exclusively on the posterior surface of the soft palate and in the nasopharyngeal cavity, thereby escaping clinical observation during life and complicating the clinical diagnosis; sometimes they reach their greatest development in the deep parts of the pharynx at the edges of the laryngeal inlet, causing swallowing disorders, etc. At the same time, the main and most important feature of the scarlatinal necrotic process is its tendency to penetrate into the depths. Often, from the very beginning, the necrosis crosses the boundary of the epithelium, involving a greater or lesser part of the underlying layer of the mucosa. However, in many cases, the matter does not end there. Due to the fact that a true demarcation line often does not form following the primary necrosis, the necrotic process continues to proceed further even after the separation of the dead tissues, mainly into the depths, but sometimes also along the surface, with varying intensity in different places. Thus, the resulting ulcers do not cleanse themselves for a very long time, but, on the contrary, continue to deepen, and their floor, while retaining its necrotic character, acquires at the same time an extremely uneven, as if pitted appearance. The described progression of the process can continue for 2-3 weeks or longer, leading to extensive destruction of soft tissues, perforations of the soft palate, exposure of individual sections of the underlying bone and cartilage skeleton (horns of the hyoid bone, horns and edges of the thyroid cartilage, posterior edge of the bony hard palate), to damage to the vessels passing here with subsequent bleeding, etc. The spread of the primary necrotic process to the esophagus occurs in approximately 10-12% of all autopsy cases of scarlet fever. The changes are distributed here either without any particular order in the form of separate spots elongated along the length of the organ or, more often, occupy specific places, namely the upper part, corresponding to the level of the larynx and the beginning of the trachea, and the very lowest segment over a length of 2-4 cm before the cardia. Necroses and ulcers in the esophagus are usually not deep, which is why their healing occurs mostly without noticeable deformations of the organ. However, as an exception, the scars developing here can also turn out to be so powerful that they cause a stricture, which is all the more severe the deeper and more widespread the initial process was. The stomach is affected significantly less often (in 3-4% of autopsy cases). Changes in it usually do not differ in either depth or extent and are most often expressed by the appearance of grayish or gray-red cloudy dry necrotic strips, located here and there along the tops of the folds. The formation of chronic ulcers or perforations as a result of them is never seen, but occasionally they can give rise to the development of phlegmonous gastritis, which always ends fatally.
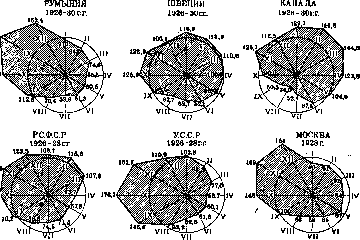
As for the respiratory tract, the most affected parts in it are the nasal cavity and the nasopharynx. Anatomically, the process is expressed here by severe catarrh with superficial necrotic changes and abundant purulent discharge. Occasionally, this process also spreads to the adjacent sinuses—the maxillary, ethmoid, and in older children, the sphenoid. As for the larynx and trachea, they usually remain free; however, this rule allows for quite a few exceptions, especially in some epidemics, and the percentage of lesions of the respiratory tube (mainly the upper part of the larynx up to the vocal cords) occurring together with the throat can sometimes reach 6 or more, and in a small fraction of cases, the larynx and trachea can even serve as the primary site of the lesion, in which the initial changes reach maximum intensity (the initial clinical symptoms are usually 128,* Figure 12.
...along with symptoms of false croup). As a rare exception, cases of scarlet fever are described in which the central point of primary changes turns out to be the bronchial mucosa or the pulmonary parenchyma, but such forms must, of course, always arouse strong suspicion of one or another mixed infection and be treated with great caution. The lymph glands of the neck, during a protracted process in the fauces and pharynx, enlarge particularly strongly. In addition to those changes that have already been described, purulent foci often develop in them as well, which, by enlarging, may give rise to the spread of purulent inflammation to the capsule of the gland and further to the adjacent cellular tissue, i.e., to the manifestation of so-called adenophlegmons. It should be noted, however, that suppurative processes of various characters (retropharyngeal and lateral pharyngeal abscesses, phlegmons) can arise in different regions of the neck and completely independently of the glands due to the penetration of streptococcus from necrotic areas along the lymph vessels into the depth of the tissues. It is worthy of note that a tendency toward early or long-progressing necrosis sometimes appears very distinctly even during suppuration. This manifests itself primarily in the development of so-called 'hard phlegmons,' when some area of tissue (cellular tissue, muscle, skin), after sharp infiltration by leukocytes, does not undergo purulent melting as usual, but, while retaining its density, dies entirely and subsequently separates by way of demarcation inflammation, immediately exposing the organs lying beneath it. On the other hand, pharyngeal abscesses, even after their opening or rupture and evacuation of pus, sometimes do not granulate for a long time, but, on the contrary, continue to increase due to progressive necrosis and suppuration in their walls. This peculiarity leads to the fact that both in the primary necrotic process originating from the mucosa of the fauces and in secondary suppurations in the surrounding tissues, blood vessels passing near the tonsils, arches, and lateral parts of the pharynx are relatively often subjected to destructive changes due to the spread of the necrotic or purulent process to their wall. Especially dangerous, of course, are injuries to arterial trunks, as they almost always end in fatal hemorrhage. Most often, among the arteries, the a. maxillaris externa, a. palatina ascendens, and a. pharyngea ascendens are affected. Upon the spread of the process to the middle ear, it exhibits the same tendency toward tissue necrosis and penetration into the depth; therefore, in no other infection does otitis produce such a large number of subsequent lesions of the adjacent bone tissue as in scarlet fever, not to mention its spread to the antrum. Most often, of course, the mastoid process suffers due to the direct spread of the process from the antrum to the cellulae mastoideae. However, purulent inflammation often spreads directly to the bony walls of the tympanic cavity as well. Of these, of particular importance are: 1) the bony plate separating the middle ear from the Fallopian canal, as from it the process can spread to the sheath of the facial nerve, and along it reach the internal auditory meatus and cause meningitis, and 2) the posterior wall, to which the sinus sigmoideus lies adjacent from the side of the posterior cranial fossa. Necrosis of this wall always entails inflammation or necrosis of the adjacent part of the sinus with subsequent purulent thrombophlebitis of it and with the possible further development of multiple septic infarcts in the lungs and other organs. The most frequent site of localization of purulent foci are the joints and serous cavities, and among the latter, the peritoneum. Thus, purulent arthritis and purulent peritonitis most often figure among the complications of scarlet fever of a septic-pyemic character. -As for later changes in organs not directly connected with the region of the primary affect, among them, lesions of the cardiovascular system, liver, and kidneys deserve mention. -In the heart, the most affected part, especially in septic cases, is the muscle, the changes of which are usually expressed in the form of interstitial myocarditis, for the most part of moderate intensity. This myocarditis began to attract increased attention since it was pointed out by some authors (Schmorl) that its histological picture in some cases can in places be very similar to the picture of Aschoff rheumatic nodules. A number of authors (Aschoff and Tawara, Fraenkel, Fahr, Talalaev) consider, however, that this similarity is far from complete and, if one can speak of it, then only in relation to atypical forms of rheumatic granuloma. The endocardium in scarlet fever suffers very little and very rarely, despite the frequent presence of streptococcus in the bloodstream. Septic endocarditis of the valves, verrucous or ulcerative, is encountered in approximately 0.1–0.15% of autopsy cases, and that mainly, apparently, where the endocardium has been altered by some preceding disease process (for example, in rheumatics). Vessels are affected significantly more often. True, their changes are usually limited to separate insignificant areas in the walls of small arteries and veins of various organs and are determined only histologically; however, in some cases, where the process gains greater spread and strength, their influence can also manifest itself very seriously clinically, leading the patient in the months immediately following the passing of the acute period of the disease to gangrene of the extremities, to renal failure, hemorrhage into the brain, and similar manifestations of sclerosis of the arteries. The morphology of vascular lesions consists of degenerative-necrotic and infiltrative-proliferative changes in the walls, with the size and intensity of both reactions being extremely variable. Apparently, most often the matter here concerns limited damage to the elastic membrane with rapidly following proliferation of subendothelial connective tissue, to which thrombosis with subsequent organization is sometimes added. All this leads to a more or less sharp thickening of the internal membrane and narrowing of the lumen. However, in some rare cases, one can see either significant infiltrates penetrating the vascular wall over a certain space with very small alterative changes, or, conversely, necrotic areas involving a significant part or even the entire thickness of the wall (in small vessels along the entire circumference, in large ones—usually within the limits of one or another segment). The pictures encountered in cases of this latter kind often very much resemble those that characterize so-called nodular periarteritis (see). In the kidneys, besides glomerulonephritis in scarlet fever, nephroses are also observed, especially in the first week in severely ill patients, and interstitial nephritis, as one of the expressions of septicemia (moreover, both the former and the latter, to a greater or lesser degree, almost always join glomerulitis as well). Interstitial nephritis, just like interstitial hepatitis, often determined in septic forms of the disease, does not differ in any way from the corresponding lesions of these organs in any other type of sepsis, with the exception that in scarlet fever, the infiltrates arising in their stroma often contain a rather significant amount of eosinophils. This sign, just like the eosinophilia of the blood constantly observed in scarlet fever, constitutes a very constant distinguishing feature of this disease. Scarlet fever septicemia, like any other, can in some cases take on a hemorrhagic character, causing the appearance of hemorrhages in various organs and cavities (skin, pleura, lungs, mucous membranes, the cavity of the stomach and intestines, etc.), and can also sometimes be accompanied by jaundice. The scarlet fever rash, in a histological respect, does not present anything specific. Under the microscope in the skin, numerous foci of hyperemia, perivascular infiltrates, and slight inflammatory edema are determined with it. The exudate, both liquid and partly cellular, usually penetrates the epidermis throughout its entire extent, giving it a cloudy appearance and sometimes accumulating between the cells in the form of very small vesicles (so-called scarlatina miliaris). Subsequently, the epidermis impregnated with exudate gradually undergoes keratinization, which differs from the normal in that the nuclei in the keratinizing cells do not disappear, and the cells themselves do not separate from each other, but remain in a fairly strong connection, forming a compact layer on the surface (so-called parakeratosis). Thanks to this, the separation of keratinized cells under the influence of new cellular mass growing from the depth occurs not in small, imperceptible scales, as usual, but in much larger areas, reaching, where the epidermal covering is generally thick (e.g., on the palms), especially significant sizes (so-called lamellar desquamation).
M. Skvortsov. The pathogenesis, just like the etiology, has not yet been fully studied. Each of the three theories mentioned above attempts to explain the mechanism of the origin of the clinical picture of scarlet fever in its own way. The pathogenesis from the point of view of the American streptococcal theory is set forth above. According to the second theory (a filterable virus in symbiosis with a streptococcus), the pathogenesis of scarlet fever is more complex. The initial stage of the disease (fever, angina, rash) depends on the primary causative agent of the disease. Often, the entire course of scarlet fever is limited to these symptoms, and phenomena of streptococcal infection are not observed ("pure scarlet fever" of French authors - Lesage). But a portion of the complications is also apparently caused by the scarlet fever microbe ("scarlet fever heart", synovitis). Nevertheless, purulent complications and phenomena of septicopyemia depend on the streptococcus. The anaphylactic theory considers the initial stage as an anaphylactic shock, analogous to the suddenly occurring attack of serum sickness. It is more difficult to explain the second period of scarlet fever with late complications from the point of view of this theory. It is assumed (S. Meyer, Schlossmann) that in the acute period, antianaphylaxis occurs only partially, and the remaining unspent antibodies again enter into combination with the antigen and produce the picture of a relapse and late complications. Clinical study of scarlet fever, regardless of the acceptance of one or another causative agent, forces one to admit that the pathogenesis of this disease is very complex; it is composed of three moments, which sometimes coexist simultaneously and sometimes follow one after another: 1) toxemia, 2) septicemia, 3) allergy. The initial stage, by its entire clinical appearance and by the blood picture (leukocytosis, neutrophilia), should be considered as infectious toxicosis. Elements of toxicosis are present to a greater or lesser degree in all forms of scarlet fever, even the mildest, but they are especially sharply expressed in the severe form, in its toxic and fulminant varieties. Toxicosis in this form manifests itself both from the side of the animal nervous system (disorder of consciousness, convulsions) and, in particular, from the side of the vegetative system. Septicemia, or more accurately streptococcemia, according to some authors (Schleissner), can be detected even in cases of moderate severity; otitis and other purulent complications are observed in these cases not infrequently. But as a constant and prolonged state determining the entire picture of the disease, streptococcemia with purulent metastases in many organs constitutes a characteristic attribute of the septic form. Finally, allergy, since the research of Pirquet and Schick, is recognized by almost everyone as a typical feature of the second period of scarlet fever. Late lymphadenitis, nephritis, relapse of angina, complete relapse of scarlet fever, late rashes, late polyarthritis, endocarditis resulting in valvular defect—all so-called late complications are more correctly considered as a reaction of hypersensitivity of the scarlet fever patient to the streptococcus or an unknown virus of scarlet fever. The typical timeframe for allergic processes is the 3rd and 4th weeks of the disease. These processes in some cases can begin earlier, in others later, sometimes after 6 weeks, depending on a number of conditions, mainly on the degree of sensitization of the organism. V. Clinical picture. The incubation period is of indefinite duration—from 1 to 11 days, most often 3-7 days. The clinical course is extremely diverse. Three forms are distinguished: 1) mild, 2) moderate in severity, or typical, and 3) severe, which is subdivided into a) toxic, b) septic, and c) toxico-septic. Typical, or moderately severe, scarlet fever. Prodromal phenomena are absent; in rare cases, general malaise is observed for 1-2 days. It begins suddenly amidst complete health with an increase in temperature, vomiting, headache; older children complain of pain when swallowing. Upon examination during the first 12 hours, one finds: temperature around 39°, severe weakness, repeated vomiting, pulse very frequent, disproportionate to the temperature, skin clean, cervical glands enlarged and painful, tongue coated, in the throat bright hyperemia of the tonsils, uvula, and soft palate, small deposits in the lacunae or on the surface of the tonsils. At the end of the first or beginning of the second day, a rash appears in the form of delicate pink hyperemia with small dots on the chest and neck and rapidly spreads to the entire body; the cheeks are red, but the chin, lips, and nose are pale. During the second day, the picture of the disease is fully expressed. The 3rd-5th days are the period of the height of the disease, the highest development of all symptoms: temperature 38-40° and higher, sharply expressed headache and general weakness, light delirium at night, but there is no disorder of consciousness, vomiting ceases by the 2nd day, there is no appetite, stool is delayed, the rash is bright over the entire body, the tenderness and swelling of the cervical glands increase, the deposits on the tonsils become membranous and take on the character of necrosis, pulse 140-160, but there are no signs of depression of cardiac activity. Starting from the 5th day, a slow improvement and regression of all symptoms begins: the temperature falls daily by 0.5°-1.0°, the rash pales, the throat clears, appetite appears, well-being improves, and by the 8th-10th day the patient seems recovered (Fig. 13). Symptoms of the initial stage of scarlet fever. Temperature. A characteristic feature of the temperature curve in scarlet fever is a rapid rise, constant temperature during the first 4-5 days, and a lytic fall by the 8th-10th day of the disease. If a fall in temperature does not occur or if a new rise is observed during lysis, this indicates some complication. In general, temperature in scarlet fever serves as a good indicator of the course of the disease. In rare cases, the temperature falls critically on the 3rd-5th day (abortive scarlet fever). Only in mild forms is the temperature subfebrile or even normal. Rash. The basic element is small spots or dots against the background of general hyperemia of the skin (see separate table, Fig. G). These dots do not depend on hemorrhages but correspond to places in the deep layers of the skin where the hyperemia is more strongly expressed. The punctate character of the rash can be revealed more clearly if one stretches the skin with the fingers of both hands and thus eliminates the general hyperemia. With strong pressure of a finger on the skin, both the dots and the general hyperemia disappear. The distribution of the rash is typical. On the face, the nose, lips, and chin are free from rash (the scarlet fever triangle); on the extremities and trunk, the rash is present everywhere, but it is more sharply expressed on the inner surfaces and in the flexures of the extremities, and on the lower half of the abdomen. In these places, the rash can be detected even in those cases when it is generally very weakly expressed. Not infrequently, at the height of the rash, the skin takes on a slightly jaundiced tint; this tint stands out more clearly if one presses hard on the skin with a finger. During the rash, a number of characteristic symptoms can be detected on the skin. White dermographism, or the "white line" of French authors, is obtained if one draws the back surface of a fingernail across the patient's skin. It appears from the 3rd-4th day of the disease and persists for some time after the disappearance of the rash; it is observed in almost all cases of scarlet fever (in 98% according to Molchanov). Its diagnostic value is not great, as it is also encountered in other eruptive diseases, but it has some significance for prognosis: absence, delayed appearance, or sluggish character should be considered an unfavorable symptom. The mechanism of origin is not fully studied; white dermographism should be considered as a direct reaction to mechanical irritation from the skin vessels, which are in a state of moderate hyperemia (Molchanov, L. Müller). Rumpel-Leede symptom—punctate hemorrhages that are obtained if one squeezes the skin between the fingers or applies a rubber bandage to the upper arm. The symptom is constant, but its diagnostic value is also not great: it is observed in measles and some other rashes. Phenomenon of rash extinction (Schultz-Charlton): if 1/4-1 cm³ of serum from those recovered from scarlet fever or normal human serum is injected intradermally, a paling of the rash is obtained at the site of injection (see below—diagnostics). Anomalies of the rash are very frequent: delayed appearance, on the 3rd-4th day; sparse rash in limited, above-mentioned places; scarlet fever without a rash is rare in children, more frequent in adults; sometimes the rash lasts only 1-2 days, or even a few hours; such cases present a great difficulty for diagnosis. The form of the rash is also diverse. Along with the typical fine-punctate, a miliary form is observed in the form of small vesicles; papular or large-spotted—usually on the extensor surfaces of the extremities (Sc. variegata or "double rash"—Doppelexanthem—of German authors); petechial—in the form of small petechiae on the elbow flexures, in the groins; all these forms have no special significance for prognosis.
Pigmentation does not occur after the scarlet fever rash. Peeling usually begins two weeks after the rash disappears, but in the miliary form, it appears while the rash is still present. Peeling on the trunk is branny and fine; on the palms and soles, it is large and lamellar (see separate table, fig. 2). Angina is the most constant symptom; it is absent only in extrabuccal or wound scarlet fever. Its character and intensity are very diverse: catarrhal, lacunar, follicular, membranous (causing the greatest difficulty in distinguishing from diphtheria), and necrotic. Regardless of the character of the angina, an intensely bright redness of the entire throat, uvula, and soft palate, sharply demarcated at the edge of the hard palate, is typical for scarlet fever. In the first hours of the disease, it is sometimes possible to see a punctate (and in serious cases, with subsequent development of necrosis, petechial) rash on the soft palate, which quickly turns into confluent redness (prodromal enanthema). Angina is accompanied by pain upon swallowing, as well as more or less significant swelling and tenderness of the submandibular lymph nodes (lymphadenitis). Oral cavity. Hyperemia of the oral mucosa and a coated tongue are also constant phenomena of scarlet fever. Changes in the tongue are characteristic: from the 3rd or 4th day, it clears, and enlarged papillae stand out clearly on the surface (strawberry tongue). Gastrointestinal tract. Vomiting, either single or repeated, is observed in 70-80% of cases in the first hours of the disease. Vomiting that persists into the second day usually indicates severe intoxication. Stool is delayed; diarrhea is observed in infants and in toxic cases. The liver and spleen are slightly enlarged. Urinary organs. The amount of urine is reduced. Protein and casts (toxic nephrosis) appear only in cases of pronounced intoxication. The diazo reaction is absent. The amount of urobilin is increased. Respiratory organs. Catarrh of the respiratory tract is, as a rule, absent in the initial stage of scarlet fever. In the presence of cough and runny nose, and even more so in cases of tracheobronchitis and pneumonia, one should think of a mixed infection, most often influenza. Heart: frequent pulse not corresponding to the temperature, slightly elevated blood pressure, muffled heart sounds, and sometimes a functional murmur. After the temperature drops, the so-called scarlet fever heart occurs (see below). Blood. In the initial stage, the typical blood picture is: leukocytosis, more or less significant depending on the strength of the infection and the body's reaction (10-30 thousand), neutrophilia, and a sharp shift to the left (up to 30% and higher instead of the normal 8%). Starting from the 2nd or 3rd day of the disease, there is an increase in eosinophils (up to 15% and higher). Changes in other elements are less typical and insufficiently studied. So-called inclusions or Döhle bodies in the protoplasm of leukocytes are a constant phenomenon in the initial stage of scarlet fever. In cases of moderate severity, if there are no complications, the blood picture returns to normal by the end of the 2nd week. Fluctuations in severity and the appearance of complications are sharply reflected in the blood picture. Nervous system. Regarding the central nervous system in cases of moderate severity, there are mild phenomena of excitation or depression (delirium, drowsiness); convulsions at the beginning of the disease occur only in neuropathic individuals and infants (spasmophilia). Regarding the autonomic nervous system, symptoms of sympathicotonia (rapid pulse, elevated blood pressure) are characteristic in the initial stage, which are replaced by vagotonia after the temperature drops (see the genesis of the "scarlet fever heart"). Deviations from the typical picture in the general course of the disease are extremely diverse: from the mildest forms, where the symptoms of scarlet fever are barely expressed, to those in which the patient dies within 1-2 days. Mild scarlet fever. Phenomena of intoxication are negligible or absent; local changes in the throat are insignificant. The onset is the same as in the moderately severe form, sudden, often with vomiting. The temperature does not exceed 38.0-38.5°, and may be subfebrile or even normal. The rash is sometimes clear and typical, with all the features of a scarlet fever rash, and sometimes weakly expressed. Angina is, for the most part, catarrhal or with insignificant, rapidly disappearing superficial coatings; there is no necrosis. Rapid regression of all symptoms by the 5th-7th day of the disease is typical for the mild form. Its frequency varies depending on the nature of the epidemic; in the last epidemic of 1924-30 at the Children's Clinic of the First Moscow State University, it accounted for 30-40% of all scarlet fever cases. The practical significance of this form is great. It sometimes remains unrecognized and becomes a source of epidemic for those around, while for the patient themselves, complications (lymphadenitis, nephritis) come as a surprise. Mortality is insignificant, resulting from complications; it does not exceed 1-2%. Severe scarlet fever. The toxic form is characterized by sharply pronounced toxicosis of the central nervous system and the cardiovascular apparatus, while local lesions of the throat and cervical lymph nodes are expressed relatively moderately. The onset is stormy, with uncontrollable vomiting that continues into the second day, and diarrhea. Consciousness is clouded; the patient is either in a state of hibernation close to coma or is excited, tossing in bed; convulsions may occur. The scleral vessels are hyperemic, and the lips are cyanotic. The rash is not abundant, erupts sluggishly, and has a cyanotic tint; white dermographism is absent; if it occurs, it is weakly expressed with a prolonged latent period. The limbs are cool. The pulse is not only extremely frequent (up to 160 and more) but also very weak, and blood pressure is lowered. Heart sounds are muffled, sometimes embryocardia occurs. At the same time, in the throat, there is not very widespread necrosis; the cervical glands are enlarged and painful but do not show a tendency to fuse with each other or with the skin. In rare cases, death occurs within 1-2 days (hypertoxic, so-called fulminant scarlet fever) (fig. 14). Usually, however, the patient dies on the 3rd-5th day with phenomena of heart failure (fig. 15). In some cases, after a stormy onset of toxicosis, detoxification occurs around the 5th day, and the patient recovers. Such a favorable outcome is most often observed after the timely and sufficient administration of serum (see treatment). Pathogenesis boils down to the damage of the cerebral cortex, autonomic centers, adrenal glands, and the sympathetic system by the scarlet fever toxin (sympathoparalysis) (Hutinel, Abrikosov and Mogilnitsky, Molchanov, Koltypin, et al.). The frequency varies—2-5% of all scarlet fever cases, with a lethality of about 40-50%. The septic form is characterized by severe and widespread damage to the throat and nasopharynx (necrosis), cervical lymph nodes (adenophlegmon), and the picture of septicopyemia developing following this damage. Sometimes, already in the first days of the disease, simultaneously with the initial symptoms of scarlet fever, necrosis appears on the tonsils, rapidly spreading to the entire throat and nasopharynx. More often, the septic scarlet fever syndrome develops around the 5th day from the picture of moderately severe scarlet fever; instead of a gradual decrease, as happens in the normal course of the disease, the temperature rises even higher, up to 40-41.0°, necrosis spreads to the entire throat, oral cavity, and nasopharynx; the patient stops breathing through the nose, the mouth is open, and there is a mucopurulent, corrosive discharge from the nose. The tongue is dry, and there is either small or extensive necrosis on the oral mucosa (aphthous stomatitis); the tonsils are enlarged to the point of touching each other, and they are covered with mucus and necrotic-type coatings. Swallowing becomes extremely painful and impossible; the patient refuses even to drink. The voice takes on a nasal tone. Sometimes the process spreads to the ears and accessory nasal sinuses (profuse purulent discharge from the nose). Simultaneously, the swelling of the cervical glands increases; they become less mobile, fuse with each other and with the skin (periadenitis), and a dense tumor forms around the neck (adenophlegmon).
Due to deep and widespread necrosis, streptococci penetrate the blood, flood the organism (streptococcemia in blood cultures), and lead to a picture of sepsis and septicopyemia. In some cases, the patient dies on the 10th-12th day, before the lymphadenitis progresses to suppuration; at autopsy, along with necrosis in the throat and glands, purulent inflammation of the ears, paranasal sinuses, and sometimes joints is found, with purulent sinusitis and arthritis, especially of the small joints, potentially remaining undiagnosed during life (Fig. 16). In other cases, the disease drags on, and suppuration develops in the glands, ears, mastoid process, and joints, mostly in the large ones (hip joint), and sometimes pneumonia with purulent pleurisy, purulent meningitis, etc. The patient also dies after a more or less prolonged time from the onset of the disease. In rare cases, despite multiple purulent foci and a prolonged course (2-6 months), the patient recovers, although more or less serious defects (deafness, immobility of joints) may remain. The frequency of septic scarlet fever is about 4-6%, and the mortality rate is high: 50-80%, especially high in children under 2 years old. Toxic-septic scarlet fever (mixed form) begins as toxic, but around the 3rd-5th day, severe lesions of the throat and glands develop. In some cases, signs of toxicosis predominate in the clinical picture of the disease, in others—local changes and septicopyemia. The frequency is about 5%, and the mortality rate is intermediate between toxic and septic (about 60%). The frequency of all varieties of severe scarlet fever, as well as mild, fluctuates mainly depending on the nature of the epidemic; in Moscow, during the 1920-30 epidemic, it was about 15%. Extrabuccal (wound, surgical) scarlet fever. The portal of entry for the infection is not the throat, but damaged skin (after burns, abscesses, etc.). A characteristic feature is the absence of angina (enanthema may be present) in the presence of a typical scarlet fever rash on the skin. Some are not inclined to consider a scarlet fever-like rash, e.g., after a burn, as true scarlet fever; indeed, scarlet fever-like rashes can have different origins. However, epidemiological data and the appearance of complications characteristic of scarlet fever do not allow one to doubt the existence of extrabuccal, including burn-related, scarlet fever. The course is usually mild; in exceptional cases, one has had to see a severe course, even with a fatal outcome. According to some (Escherich and Schick, Sokolova, and others), the lungs can also serve as the portal of entry for scarlet fever infection. In such cases, a scarlet fever rash appears during rapidly developing pneumonia; changes in the throat are insignificant. At autopsy, foci of necrosis are found in the lungs; there is no necrosis in the throat (pneumo-scarlet fever). The existence of such scarlet fever cannot be considered proven. Complications. By the time of appearance, one can distinguish early (during the 1st-2nd week) complications and late (in the 3rd-4th week and later) ones. Such a division is partly justified by the difference in pathogenesis. Early complications develop from the symptoms of the initial stage of scarlet fever or directly adjoin it. Their origin is based on scarlet fever toxemia or streptococcal infection. Late ones are often separated from the initial stage by an afebrile period, during which there may be no manifestations of scarlet fever infection. According to modern understanding, they represent an allergic reaction of a sensitized organism to the scarlet fever microbe. According to the view of Pirquet, Schick, and others, the 3rd and 4th weeks are a period of increased sensitivity to this microbe; German authors call this period with a number of late complications the "second scarlet fever," since many complications of this period repeat the symptoms, and sometimes the entire picture, of the initial scarlet fever. Complications involving the heart occupy a special position; they occur both in the early and in the second period of the disease. Their clinical picture and pathogenesis differ depending on the stage and severity of the scarlet fever. Early complications. Cervical lymphadenitis is the most frequent complication (40% according to the data of the children's clinic of the 1st Moscow State University). Swelling of the cervical glands is essentially one of the constant symptoms of the initial stage of scarlet fever. It is considered a complication when the swelling reaches significant size and is very painful. In general, there is a parallelism between the intensity of the throat lesion and the size of the lymphadenitis; however, sometimes there is no parallelism, and the lymphadenitis proceeds as if independently, regardless of the state of the throat. The usual outcome is regression; much less often, suppuration (3%). Signs of purulent infiltration: increase in temperature, the glands become less mobile, fuse with each other and with the skin, the skin reddens, softens, and fluctuation appears. Sometimes (in septic scarlet fever), the glands and the surrounding connective tissue, undergoing inflammatory infiltration, form a dense tumor that does not show signs of softening; on cross-section, there is necrosis of the glands and connective tissue; necrotic masses slough off by themselves, exposing the deep-seated organs of the neck ("dry necrosis"). Such forms of lymphadenitis have a poor prognosis. The serious significance of this complication is due, firstly, to the possibility of streptococci penetrating the blood; secondly, to the sometimes observed fatal hemorrhage from the vessels of the neck, which are destroyed by the necrotic process. - Necrotic angina (scarlet fever diphtheroid, 30%) (Fig. 17). In moderately severe scarlet fever, it is a very frequent symptom; in septic scarlet fever, it is a constant symptom of the initial stage. As a complication, it develops after the 4th-5th day of the disease; thanks to it, the drop in temperature is delayed for a long time. The deposits have a creamy appearance and do not rise or rise little above the level of the mucous membrane. Although the external resemblance to diphtheritic deposits can be great, in essence, these are two different processes: diphtheria bacilli are absent, and fibrinous exudation is weakly expressed in contrast to diphtheria; the essence of the process boils down to deep-penetrating necrosis of the mucosa and submucosa (see separate table, Fig. 3); after the deposits slough off, deep ulcers, perforations, and defects remain in the tonsils, soft palate, and uvula. This is one of the most serious complications; the danger here also lies in the possibility of sepsis and fatal hemorrhage from vessels; more often, however, the inflammatory process directly penetrates into the middle ear and paranasal sinuses. - Necrotic (aphthous) stomatitis (20%). Superficial necroses of the mucosa of the tongue and oral cavity are sometimes small, sometimes more extensive. After the necroses subside, painful ulcers remain. The significance of this complication boils down to difficulty in feeding the patient. Otitis (purulent inflammation of the middle ear, 15%). In septic scarlet fever, it appears as early as the 1st week as a result of the direct transition of the necrotic process from the throat. In moderately severe and mild forms, it usually occurs in the 2nd or at the beginning of the 3rd week, less often later; in late otitis, it is often preceded by an exacerbation of angina. Symptoms: increase in temperature, hearing loss, pain upon pressure on the tragus; children often do not complain of spontaneous pain, which distinguishes scarlet fever otitis from influenza or measles otitis. Another difference is the rapid formation of purulent exudate and spontaneous perforation of the eardrum. With a favorable course, the process ends in 2-3 weeks. Unfavorable outcomes: 1) frequent transition to the mastoid process (see Mastoiditis), less often sinus thrombosis and purulent meningitis, 2) chronic suppuration with significant hearing loss. Upon the transition of the inflammatory process to the inner ear—complete deafness, which in young children leads to deaf-mutism. According to the statistics of German otologists, 1/3-1/2 of deaf-mutes became such after scarlet fever contracted in early childhood (Manasse). Sinusitis (ethmoiditis, frontitis, maxillary sinusitis, 3%). Ethmoiditis and frontitis are more common. In septic scarlet fever, they appear in the 1st week but do not manifest clinically in any way; profuse purulent discharge from the nose is suspicious. The usual outcome is death from general sepsis. In moderately severe cases, it occurs in the 2nd-3rd week. According to Killian, late sinusitis begins even in the early period of scarlet fever. Symptoms: increase in temperature, profuse discharge from the nose, swelling and tenderness in the area of the sinuses; in ethmoiditis—at the upper inner corner of the eye and on the upper eyelid, sometimes protrusion of the eye; in frontitis—in the area of the eyebrow ridges; in maxillary sinusitis—on the cheek and on the lower eyelid.
Outcome - most often complete recovery, in rare cases - sinus empyema, osteomyelitis, purulent meningitis. - Synovitis (scarlatinal rheumatoid, 8-10%). Appears at the end of the 1st or in the 2nd week. Mainly small joints are affected (hand, fingers, etc.). Symptoms: temperature rise, all signs of inflammation of the synovial membrane of the joint: pain, redness, swelling. Exudate is sterile. The genesis is not exactly clarified, probably of a toxic character. One of the most favorable complications. Outcome - spontaneous and complete regression. It should be distinguished, firstly, from purulent arthritis as one of the manifestations of septicopyemia in septic scarlet fever, and secondly, from late polyarthritis (see below) (Figure 18). - Laryngitis, tracheobronchitis, pneumonia, pleurisy. Complications from the respiratory organs are considered rare in scarlet fever. Laryngitis in the form of necrotic-ulcerative is observed exclusively rarely in septic scarlet fever with widespread necrosis. It can lead to stenosis and require tracheostomy. In the pediatric clinic of the First Moscow State University, due to a recurrence of stenosis in the 5th week, a tracheostomy was performed, and the child recovered. Pneumonias are more common (6-8%), but the time of their appearance, etiology, and outcome are different. In septic scarlet fever, pneumonia develops during the 1st week (streptococcus) and gives an extremely poor prognosis. In the recovery period, pneumonia depends on a secondary infection, usually influenza (pneumococcus), the prognosis is not bad. Some complications, e.g., nephritis, predispose to pneumonia and worsen the prognosis. In infants, pneumonias are especially common, and the high mortality of these children in scarlet fever mainly depends on them. All that has been said also applies to purulent pleurisy, which is a frequent companion of pneumonia. Complications from the liver are observed not infrequently. Clinically, they manifest as liver enlargement and jaundice. Liver enlargement often appears in the first days of the disease and can remain for an indefinitely long time. It depends, on the one hand, on parenchymatous and interstitial hepatitis; hepatitis can be detected a long time after scarlet fever, cases of its transition into cirrhosis have been described. On the other hand - liver enlargement of a congestive nature due to circulatory disturbance. The time of appearance and pathogenesis of jaundice are different. With a sharply expressed rash, already in the first days, it is possible to notice an icteric tone of the rash. The origin is partly hematogenous due to increased breakdown of erythrocytes, partly hepatogenous as a result of damage to the liver parenchyma by scarlatinal poison (urobilinogen in urine, increased bilirubin content in the blood). Jaundice observed in septic scarlet fever has the same clinical features (colored stool) and the same genesis as in septic jaundice of other origin. Finally, in the recovery period, jaundice of an apparently congestive nature is observed (discolored stools). Cholecystitis and enlargement of glands in the area of the liver hilum are pointed out as the cause of such jaundice (Pospischill). In some cases, jaundice appears as a result of a combination of scarlet fever with infectious or so-called catarrhal jaundice. Late complications. Lymphadenitis is the most frequent of the late complications. According to Pospischill, 50% of all manifestations of the second scarlet fever. It differs from early lymphadenitis, besides the time of appearance, by localization: most often the glands near the sternocleidomastoid muscle swell; besides, the outcome in suppuration is observed less often (less than 1%). It is observed both as an isolated complication and in combination with other late complications - nephritis, exacerbation of angina, and nasopharyngeal catarrh. It is accompanied by a temperature rise, which sometimes takes an intermittent character. Nephritis. Kidney damage also occurs in the initial stage of scarlet fever, but almost exclusively in a severe form, or in the form of toxic nephrosis ("febrile albuminuria") in toxic scarlet fever, or in the form of septic interstitial nephritis in septic scarlet fever. The clinical picture of early damage stands out little against the background of a severe general disease and does not present anything characteristic of scarlet fever. When speaking about scarlatinal nephritis, one has in mind late kidney damage, which appears in the 3rd-4th week, sometimes even later (5th-6th week), very rarely in the 2nd week, most often around the 20th day of the disease. In the pathological-anatomical respect, this is acute glomerulonephritis or nephrosonephritis (see Nephritis). The frequency according to literature data ranges from 2% to 20%; for most authors, it is about 10%. In the pediatric clinic of the First Moscow State University, out of 1,054 scarlatinal patients, nephritis was observed in 128, i.e., in 12.1%. The onset in some cases is acute: temperature rise, headache, vomiting; simultaneously - changes in urine: it is scanty, macro- and microscopic hematuria, protein in moderate quantity (0.1-2%), casts. In other cases - without temperature rise, if there are no other complications; the first symptom is weight gain, change in urine, and edema, primarily on the face. With regular measurement of blood pressure 2-3 days before the change in urine, one can detect a significant increase in it (115-130 mm), and even earlier with capillaroscopy - spasm of skin capillaries (O. Muller, Bossé). Duration - on average 3-6 weeks. The usual outcome with proper care is complete recovery. An unfavorable course and outcome are very rare; they are caused by: 1) uremia of the eclamptic type (see Uremia) (about 5-10% of all cases of nephritis), 2) heart decompensation (myocarditis), 3) transition to a chronic form, and 4) other complications of scarlet fever joining, e.g., pneumonia. Mortality varies among different authors, in general, it is not high. According to Pospischill - 8%, according to the material of the pediatric clinic of the Second Moscow State University - 4.5% (Hirschberg and Sukhareva). Mortality is higher in cases where patients were already admitted to the scarlet fever ward with nephritis; the mortality of such cases according to Pospischill = 21.8%. This fact is explained in all probability by improper care in the first days of the nephritis disease. Mortality from uremia is also very different; according to the material of the pediatric clinic of the First Moscow State University, it = 0%, in the pediatric clinic of the Second Moscow State University out of 11 patients with uremia, 1 died (Hirschberg and Sukhareva); according to other authors, mortality is significantly higher (up to 40%). How often scarlatinal nephritis turns into a chronic form is not exactly known; according to Rosenfeld, out of 95 patients who left Escherich's clinic with remnants of scarlatinal nephritis, in none was a transition to a chronic form observed, although some patients had chronic albuminuria of the lordotic type. Patients were observed in whom, for 3-5 years after scarlet fever, hemorrhagic nephritis with repeated exacerbations remained; the patients nevertheless recovered with full restoration of the functional capacity of the kidneys (Molchanov). Such observations were reported by Escherich, Heubner, and others. Very mild, rudimentary forms of nephritis with insignificant albuminuria and hematuria, continuing for a short time, are encountered. In these cases, one can also detect both weight gain and increased blood pressure, as well as a spastic state of skin capillaries. The study of scarlatinal nephritis and skin vessels in different periods of scarlet fever (histological, capillaroscopy) confirms the modern view (Volhard, Kylin, and others) on the pathogenesis of glomerulonephritis, according to which glomerulonephritis represents a partial manifestation of a general vascular lesion (capillaropathia universalis), primarily of skin capillaries, which in the 3rd-4th week of scarlet fever show a constant tendency to a spastic state (Bossé) (Figure 19). - In the 3rd-4th week, edema sometimes appears, either obvious on the face and legs or hidden, which can be detected by daily weighing of the patient (weight gain of 500-1,000 g). The urine does not present pathological changes, blood pressure is not increased, kidney function is not impaired, almost always there are symptoms of scarlatinal heart. In some cases, the appearance of edema is accompanied by lymphadenitis and temperature rise, but more often the temperature is normal. These are so-called protein-free edemas. They disappear in 1-2 weeks. The mechanism of their origin (see Edema) in scarlet fever is complex.
First, one must place changes in the capillaries, then metabolic disorders and a disturbance in the balance of the oncotic pressure of blood and tissue colloids; heart damage is of lesser significance. Late polyarthritis is a complication little known to physicians and insufficiently studied. It is observed in the 3rd-6th weeks of scarlet fever and even later. Unlike early synovitis, it mainly affects large joints: the knee, ankle, shoulder, elbow, etc. The duration is 2-3 weeks or more; it shows a tendency to relapse; despite the prolonged existence and relapses, no functional impairment or persistent changes remain. It is very often observed in combination with other late complications: with nephritis (15 cases in Szontagh), recurrence of angina, lymphadenitis, etc. Simultaneously with polyarthritis or immediately following it, benign endocarditis with an outcome of valvular defect often develops (in 14 cases in Molchanov). Regarding the relationship to rheumatism, see below. Recurrence of angina. The character of the angina is varied - from catarrhal without an increase in temperature to necrotic with a severe and prolonged course and high temperature. In some cases, it results in a tonsillar abscess (phlegmonous angina) or a retropharyngeal abscess. In most cases, the angina during a recurrence is milder than the initial angina, but the opposite also happens; it appears, like other late complications, most often in the 3rd-4th week. Its frequency is actually higher than that given by the statistics of various authors, because mild forms are usually not taken into account. According to Pospischill, recurrence of angina accounts for 18% of all manifestations of the second scarlet fever. According to the materials of the Children's Clinic of the 1st Moscow State University, it is observed just as often as late lymphadenitis. -- A full recurrence of scarlet fever, i.e., a return of scarlet fever with all its cardinal symptoms: increased temperature, angina, and typical rash. A necessary condition for recognizing the new appearance of the indicated symptoms as a recurrence of scarlet fever is an unquestionable diagnosis of scarlet fever in the initial stage. The earliest date of recurrence of scarlet fever according to the materials of the Children's Clinic of the 1st Moscow State University is the 11th day of the disease, the latest is the 7th week; in most cases, according to the observations of all authors, it is the 3rd and 4th week. In some cases, it can proceed more severely than the initial scarlet fever, even with a fatal outcome. It is observed more often in mild scarlet fever than in severe cases. It often appears in combination with other late complications: nephritis, polyarthritis, etc. The addition of a new infection to scarlet fever, e.g., influenza, measles, chickenpox, apparently predisposes to recurrence. There are indications of a familial predisposition (in several children in families; in two twins in the Children's Clinic of the 1st Moscow State University simultaneously). After a recurrence, new desquamation and complications characteristic of the initial stage (e.g., otitis) may appear. The frequency, according to Pospischill, is 46 recurrences per 2,605 cases, i.e., 1.76%. The frequency according to other authors ranges from 0.3% to 4%. The pathogenesis is insufficiently studied: some (Henoch, Comby) view it as an outbreak of an unextinguished scarlet fever infection, others (English authors, Pospischill, Rauchfuss, etc.) as the result of a new infection with the scarlet fever virus; Schick's theory about the allergic origin of the recurrence should be recognized as more probable (Fig. 20). Late rashes (Fanconi), post-scarlet fever erythema (Schick), or false recurrence (Thomas). In the 2nd-3rd-4th week and later, a rash appears that differs in its appearance from the fine-spotted scarlet fever rash. Fanconi distinguishes four main varieties: 1) maculopapular, 2) reticular-striated, 3) large-papular, and 4) pityriasis-like. Sometimes it has the appearance of urticaria. It is often observed simultaneously with an increase in temperature, angina, nephritis, and other complications. Localization - buttocks, extensor surfaces of the limbs, trunk, sometimes the face. Duration from 3-5 days to 2 weeks. The basis of the pathogenesis is the same allergy as for other late complications. In Fanconi's opinion, other factors also play a role: mechanical irritation and local changes in the skin under the influence of scarlet fever. Complications of the cardiovascular system. Initial period. In the moderately severe form - pulse rate disproportionate to the temperature, increased blood pressure, transient functional murmurs. Pathogenesis - irritation of the sympathetic system under the influence of the scarlet fever toxin. In toxic scarlet fever - pulse is extremely frequent and weak, lowered blood pressure, dilation of the heart, muffled tones, decline in cardiac activity up to collapse. Pathogenesis - severe damage to the sympathetic system (Abrikosov, Mogilnitsky) and adrenal glands (Hutinel, Molchanov), i.e., the entire sympathoadrenal system. In septic scarlet fever, simultaneously with this, organic changes are observed in the heart muscle itself, and the longer the patient lives, the more sharply these changes appear both in the clinical picture (weak pulse, muffled tones, dilation of the heart, congested liver) and at autopsy (interstitial myocarditis). In septicopyemia, septic endocarditis and pericarditis sometimes join this, which is sometimes discovered only on the autopsy table. Recovery period. After the fall in temperature at the end of the 1st week, or more often in the 2nd-4th week, regardless of the severity of the initial period, disorders of cardiac activity appear, which are customarily called "scarlet fever heart." The pulse, which was normal or rapid, becomes slowed and arrhythmic. The tones become prolonged, muffled, and impure; subsequently, the impurity can turn into a real murmur, and simultaneously, dilation of the heart appears. A characteristic feature is the inconstancy and variability of these symptoms. The general condition does not suffer or is disturbed to an insignificant degree (pallor, lethargy). The duration of existence is from a few days to 2-4 weeks or more. The prognosis is quite favorable. The frequency according to the observations of various authors is very diverse: according to Schick - 5%, according to Koltypin - almost 100%. According to the materials of the Children's Clinic of the 1st Moscow State University - about 35%, if one counts only definitely expressed cases. Pathogenesis - a disturbance of the balance between the sympathetic and parasympathetic systems; the excitation observed in the initial stage of scarlet fever is replaced in the recovery period by its weakening, as a result of which the vagus nerve gains the upper hand, i.e., "scarlet fever heart" is considered a symptom of vagotonia (Molchanov, Koltypin, etc.); one cannot deny, at least for a part of the cases, the possible participation also of myocarditis (Romberg, Filatov). The existence in scarlet fever of so-called benign (non-septic) endocarditis with an outcome of valvular defect is completely denied by some (Pospischill), while others (Heubner, Feer, Schick) recognize it. Its pathogenesis is also understood differently: Schick, Hallez, and Comby consider it a complication of scarlet fever itself. Zischinsky considers it the result of an accidental combination of scarlet fever with rheumatism. According to Molchanov, endocarditis with progression to valvular defect is observed in scarlet fever more often than is commonly thought, but its connection with scarlet fever is not always possible to establish, because it sometimes appears in the 5th-6th week and even later. Often, endocarditis develops simultaneously with other late complications of scarlet fever - nephritis, recurrence of angina, and scarlet fever, but most often with late polyarthritis (Fig. 18). Genetically, it is closely connected with the scarlet fever process, and it can be considered one of the late complications of scarlet fever; at the same time, according to the clinical picture and pathological-anatomical changes (Aschoff bodies), it is rheumatic endocarditis. Rarer complications of scarlet fever. Nervous system. Besides damage to the brain and meninges of a toxic and septicopyemic character in the initial stage of severe scarlet fever and the damage to the sympathoadrenal system characteristic of all forms of scarlet fever, in rare cases in the late period of scarlet fever, hemiplegias of cerebral origin appear, sometimes with aphasia and hearing loss.
In the majority of cases, other late complications are observed simultaneously with them: nephritis, endocarditis. The anatomical cause is encephalitis or circulatory disorders (embolism, thrombosis, hemorrhage). Even rarer is the involvement of the striopallidal system with symptoms of parkinsonism. Old clinicians (Trousseau) often observed chorea as a complication of scarlet fever. At the present time, it is encountered less frequently as one of the manifestations of the rheumatic syndrome developing following scarlet fever (Molchanov). In rare cases, one has to observe polyneuritis with flaccid paralysis and loss of tendon reflexes. Endocrine glands. Besides the aforementioned involvement of the adrenal glands, scarlet fever can, apparently, lead to the manifestation of constitutional inferiority of various glands with internal secretion: the thyroid gland with symptoms of either hyperthyroidism (Basedow's disease in girls) or hypothyroidism, the pituitary gland (acromegalic gigantism), the pancreas (diabetes), and others. Cases of gangrene of the extremities of the Raynaud's disease type as a result of vascular involvement, cases of appendicitis, and others have been described. Scarlet fever in infancy. Age exerts a great influence not only on morbidity (see above: predisposition) but also on the course, frequency, and character of complications, as well as the outcome of scarlet fever. Infancy presents a particularly large number of deviations from the typical course of the disease. The main feature consists in the fact that the symptoms of toxemia are expressed more weakly, while septicopyemia is significantly sharper than in children of older ages. The temperature, if there are no early complications, is not high, falls faster, the rash is less bright, atypical, and lasts for a comparatively short time; white dermographism is often absent regardless of the severity of the course; peeling is also very often absent (40% according to Sokolova); angina often has only a catarrhal character. Of the complications, synovitis, nephritis, and "scarlatinal heart" are encountered much less frequently. Purulent complications—lymphadenitis, otitis, sinusitis—are more frequent and proceed more severely. But what is especially characteristic of scarlet fever in infancy is the frequency of pneumonias and their dangerous character. Mortality is very high: 20-40%; it depends primarily on pneumonias, then on septic complications. Scarlet fever and other infectious diseases. If other infectious diseases are added to scarlet fever, they, as a rule, mutually influence each other, and this influence is the more sharply expressed the closer to the initial stage of scarlet fever the new infection is added. Scarlet fever + measles is the most frequent combination. With the simultaneous eruption of both rashes, the diagnosis is especially difficult. If measles is added after the disappearance of the scarlatinal rash, a delayed appearance of the measles rash and an outbreak of the scarlatinal one are observed. In the late period of scarlet fever, the mutual influence is less expressed; however, it has been necessary to observe relapses of angina and relapses of scarlet fever itself (Pospischill, Molchanov). The number of complications under the influence of measles increases; this especially applies to pneumonias. Mortality in mixed infection is generally higher (Volovin). The widespread use of prophylactic vaccinations, according to Degkwitz, in recent years has sharply reduced the danger of mixed infection. Scarlet fever + chickenpox. Sometimes a severe course of chickenpox is observed with abundant and deep pustules; an outcome into septicopyemia is possible even with scarlet fever of moderate severity. Scarlet fever + diphtheria. If diphtheria is added in the initial stage of scarlet fever, the diagnosis presents great difficulties. Although in typical cases scarlatinal necroses and diphtheritic membranes differ from each other, in septic cases of scarlet fever one sometimes has to observe widespread necroses having the appearance of fibrinous membranes. Bacteriological examination also does not always solve the recognition, since it has long been known (Baginsky, Shabad) that in the initial stage of scarlet fever it is quite often possible to isolate bacilli from the throat that are morphologically similar to Loeffler's bacilli. Depending on the prevalence of the diphtheria epidemic, the frequency of this combination can reach 6% and more (Shabad, Rolly). In any case, at the slightest suspicion of a mixed infection, an injection of anti-diphtheritic serum is necessary. Diphtheria added in the recovery period differs little from the usual course and does not present great difficulties in recognition. Lethality, especially in small children, increases significantly (croup, pneumonia). Scarlet fever and rheumatism. It was said above that in the 2nd allergic period of scarlet fever, polyarthritis and endocarditis are sometimes observed as late complications. By clinical picture, course, outcome, and pathological-anatomical changes, they should be considered rheumatic. The appearance of the rheumatic syndrome in scarlet fever cannot be viewed as a random coincidence of two infections or as an exacerbation of rheumatism under the influence of scarlet fever, although scarlet fever indeed possesses the ability to exacerbate the rheumatic process. According to Molchanov, the connection between scarlet fever and rheumatism is genetic. The allergic theory of rheumatism best allows one to understand this connection. During scarlet fever, an allergic restructuring of the organism occurs in relation to the streptococcus, as a result of which, in the presence of predisposing conditions (rheumatic heredity, preceding sensitization under the influence of angina, housing and living conditions), a certain category of children by the end of the disease can turn into typical rheumatics. The newest pathological-anatomical studies speak in favor of this view. Fahr, Siegmund, Pashchin, and Krich, during autopsies of scarlet fever patients, found Aschoff bodies in the heart muscle. The problem of the connection between scarlet fever and rheumatism requires careful collective study by pathologists, clinicians, and dispensary physicians. VI. Diagnosis and prognosis. In typical cases, the diagnosis of scarlet fever does not present difficulties. The supporting points in the initial stage serve as a sudden onset with high temperature, vomiting, sore throat; angina with bright redness of the entire throat; enlargement of the cervical glands; a fine-spotted rash on a hyperemic background with a triangle on the face; from the 3rd day, a raspberry tongue. In the 2nd (late) period: fine peeling on the torso and lamellar peeling on the palms and soles, "scarlatinal heart," and other late complications (lymphadenitis, nephritis, etc.). In doubtful cases, it has been proposed to use a number of auxiliary methods. Blood: neutrophilic leukocytosis and eosinophilia; inclusions in leukocytes, described by Döhle, are constant phenomena in scarlet fever, but they are not specific, since they are encountered in other diseases as well. Skin reactions. White dermographism is a constant symptom of scarlet fever, but it is also observed in other rashes (measles, erythema from the sun, etc.). The same must be said about the fragility of skin capillaries—the Rumpel-Leede symptom. The blanching phenomenon (Schultz-Charlton). The direct method consists in injecting 0.5-1.0 cm³ of serum from people who have recovered from scarlet fever or healthy people intradermally into a patient with a doubtful rash. The disappearance of the rash at the site of injection speaks for its scarlatinal character. However, the rash in other diseases (measles, rubella) also gives a positive blanching phenomenon. Therefore, an indirect method has also been proposed, which is based on the fact that the serum of scarlet fever patients during the rash does not possess the ability to blanch it. It consists in injecting the serum of a patient with suspected scarlet fever into a patient with an undoubted scarlatinal rash. A positive result speaks against scarlet fever. However, this method also cannot be considered absolutely certain, since in some cases the serum of patients with, for example, rubella, behaves in the same way as the serum of scarlet fever patients (Neumann). The mechanism of the Schultz-Charlton phenomenon cannot be considered clarified. It is assumed that the ability to blanch the rash depends on the presence in the serum of a specific scarlatinal antitoxin. However, it is difficult to reconcile this view with the ability to blanch the rash, often observed in the serum of such convalescents who give a positive Dick reaction, as well as the spontaneous blanching of the scarlatinal rash at the sites of furuncles and impetiginous rash. Bacteriological examination of mucus from the throat for the presence of hemolytic streptococcus cannot serve as a reliable criterion in the diagnosis of scarlet fever, since it, on the one hand, is often encountered in the throat apart from scarlet fever, and on the other, can be absent in undoubted scarlet fever. Differential diagnosis. One should keep in mind, first of all, various rashes of infectious and toxic origin. Cases with anomalies of the rash in measles—confluent measles, on the one hand, and s. papulosa, variegata, on the other—can present difficulty; the diagnosis must be based on cardinal symptoms: angina in scarlet fever, Filatov-Koplik spots, and catarrhs of the respiratory tract in measles. Great difficulties can be presented by the recognition of mild scarlet fever from scarlatinal rubella (4th disease, or Filatov-Dukes' disease). Sharply expressed angina, raspberry tongue, peeling, and the appearance of complications speak for scarlet fever, but all this can also be absent in mild scarlet fever. The epidemiological moment (the simultaneous existence of undoubted cases of scarlet fever) has more significance. Doubtful cases are more correctly considered as mild scarlet fever.
Other scarlatiniform rashes in the 5th and 6th diseases, influenza (see), are encountered less frequently and present fewer difficulties. The prodromal rash (the so-called Rash) in smallpox and chickenpox—the diagnosis is clarified quickly with the appearance of the rash typical for these diseases. Serum sickness—a scarlatiniform rash occurs rarely, but simultaneously with it, other rashes are observed: urticarial, polymorphic erythema. Erythema scarlatiniforme recidivans is encountered very rarely; angina and strawberry tongue are absent. In small children, one must remember prickly heat and erythema from crying. In scarlet fever without a rash, necrotic angina is not easily distinguished from angina of other origins—from diphtheria, Vincent's angina. Besides bacteriological examination, one must remember the typical features of each of these diseases. In general, the recognition of scarlet fever should be based not on any one symptom, but on the entire clinical picture of scarlet fever—on a thorough examination of the patient (e.g., in the apparent absence of a rash, one must look for it in specific places), data from the history, the epidemiological moment, etc. Prognosis. It has long been known that the prognosis in scarlet fever must be made with great caution in view of its tendency toward unexpected changes in the course of the disease. In the moderate form, up to the 5th day, one cannot definitively pronounce even regarding the immediate future, since around the 4th-5th day, a transition to the septic form is possible. The same caution is necessary until the end of the 4th week in view of the possibility of the appearance of nephritis and other late complications. The same must be said regarding the mild form. Complications and relapses in it sometimes result in a more severe course than the initial period of the disease. In severe scarlet fever, the basis for the prognosis should be the degree of general intoxication and the severity of the local process. A very high temperature (41°), an unconscious state, agitation or a comatose state, damage to the cardiovascular apparatus (not only a frequent but also a weak pulse, muffled tones, poorly expressed rash with a cyanotic tint, absence of white dermographism) provide a poor prognosis. The prognosis is even worse if the spread of necrosis to the nasopharynx and nasal cavity, into the accessory sinuses and middle ear is observed simultaneously, especially if adenophlegmon of the neck appears early. Of the purulent complications, purulent lymphadenitis provides the most favorable prognosis; otitis and mastoiditis are much more serious. Purulent lesions of the serous membranes (multiple purulent arthritis, pericarditis, pleurisy, especially in small children) provide a poor prognosis. In nephritis, the prognosis depends not on the amount of protein and formed elements, and not even on the degree of edema, but mainly on the amount of urine and the state of the functional capacity of the kidneys; in the further course, the state of the heart and respiratory organs is very important; complicating pneumonia sharply worsens the prognosis. In general, for the prognosis of scarlet fever, the age and condition of the child before the illness and the external conditions in which he lives (see above) are of great importance. The role of constitution and constitutional anomalies cannot be considered sufficiently clarified. General mortality fluctuates sharply depending on the character of the epidemic, the age composition of the patients, the country, the living conditions of the population, and a whole series of other factors (see statistics). VII. Treatment. Treatment is divided into non-specific and specific; the former, in turn, can be general and symptomatic. In every case of scarlet fever, regardless of the form, general treatment must be in the foreground. It is conducted according to the same principles as in other acute infectious diseases of childhood, but in relation to scarlet fever, some special measures are applied. Bed rest for 3-4 weeks, even in mild cases and with normal temperature. It, admittedly, does not prevent nephritis, but observations show that nephritis proceeds worse if the patient is out of bed in the initial stage of this complication. Changes in the kidneys in scarlet fever occur earlier than the appearance of edema and protein in the urine and are not detected by usual clinical examination (see above). Fresh air—in the summer time, the patient can remain in the air throughout the day; in winter—thorough airing of the room. Baths. In the acute period, daily sponging, washing, and in general, strict observation of the cleanliness of the body; baths are not contraindicated; they are mandatory in the recovery period (every 1-2 days). Drinking. The introduction of a sufficient amount of fluid is a necessary condition for the normal course of the disease in children (up to 800 cm3-1 liter per day). In necrotic angina, as well as in small children, frequent and regular (every 15 min.) introduction through the mouth of small amounts (1 tsp - 1 tbsp) of fluid (water, tea, lemonade, etc.) is necessary. Food in the initial febrile period, in cases of angina with difficult swallowing, should be liquid and semi-liquid (milk with tea, coffee, broths, porridges, fruit jellies, purees, fruit and vegetable juices); solid food and meat should not be given. But after the fall of temperature and the weakening of the local process in the throat, the food should be sufficient in caloric value and complete, i.e., also contain meat. Exclusively milk and milk-vegetable food is not expedient. Observations in many clinics and hospitals, including the children's clinic of the 1st Moscow State University, have shown that with mixed food, nephritis is observed no more frequently, meanwhile, nutrition suffers with milk-vegetable food. Great importance is attached to the care of the oral cavity, throat, and nose. Frequent drinking already contributes to the elimination of dryness and the maintenance of cleanliness in the oral cavity and throat. In addition, regular rinsing with weak disinfectant solutions (2% boric acid, hydrogen peroxide, rivanol, etc.), physiological saline, or boiled water is necessary; for small children, mouth irrigation; for the throat—cold or steam spraying (the same solutions, and also, with a large amount of mucus, alkalis, e.g., 2% soda, lime water—2 tbsp per glass of water). To avoid cracks on the lips—smearing with bismuth ointment (20%) or vegetable oils; for the nose—smearing with the same ointments or 1% Ung. hydrarg. flavi. Treatment of individual symptoms and complications. High temperature does not require special measures; if nervous phenomena are observed simultaneously—cold to the head, sponging and cool wraps, or better, lukewarm baths with a gradual lowering of the water temperature. Angina—smearing should not be done; rinsing and spraying (see above). Lymphadenitis—heat in the form of a warming compress, a bag with hot water, or electric lamps. In case of fluctuation—incision. Early incision is not expedient. Otitis—5% carbolic glycerin, warming compress. With clear signs of purulent exudate (bulging of the eardrum, high temperature)—paracentesis; subsequently, frequent changing of wicks; as a rule, we do not perform washings. In case of suspected mastoiditis (pain upon pressure, temperature)—ice on the mastoid process. Indications for operation: pain, swelling behind the ear, narrowing of the external auditory canal, temperature. One also has to resort to surgery in cases of latently proceeding mastoiditis with intermittent temperature, abundant purulent discharge from the ear, but without a tumor in the region of the mastoid process. Sinusitis—heat, drops with adrenaline solution. Serous synovitis—heat; in case of purulent arthritis—surgical intervention. Circulatory disorders in toxic and toxico-septic scarlet fever—a formidable phenomenon. Agents that increase the tone of the heart and vascular system are indicated: camphor, caffeine, infusion of physiological saline with adrenaline. "Scarlet fever heart"—rest, medicinal treatment is unnecessary. Nephritis. The principles of treatment are reduced to the following. 1) Bed rest, and moreover, keeping warm. Avoid cooling of the body; strive to weaken the spasm of skin capillaries through uniform hyperemia of the skin. The vessels of the skin in a functional respect behave cooperatively with the vessels of the kidneys, therefore, the spasm of the skin vessels upon its cooling causes a spasm of the vessels in the kidneys and thus leads to a worsening of the process. When airing the room, it is especially necessary to take care of warming the body (heating pads, bags with hot water). One can get out of bed after the cessation of the acute process in the kidneys, and one should be guided not only by the examination of urine but also by the examination of blood pressure and the examination of the functional capacity of the kidneys. 2) The diet should be composed on the principle of sparing the diseased kidney, but at the same time be such as to reduce starvation to a minimum. The amount of fluid should be limited to 600-800 cm3 per day. All food without salt; if there is no edema, table salt in an amount of no more than 1-2 g. Animal proteins (meat, eggs) are excluded. Exclusively milk food, besides its one-sidedness, is not expedient already because to cover the caloric value, one would have to introduce a large amount of milk, consequently a significant amount of fluid, protein, and salts. Therefore, in the acute stage, food should consist of a moderate amount of milk (200-400 g) with tea, porridge, soups, primarily from rice, fresh butter, purees from vegetables and fruits, bread, and an abundant amount of sugar.
In recent years, we have begun treatment with 1-2 sugar days (200-400 g of sugar in 600-800 cm3 of tea or liquid coffee, calculated at 40-50 calories per 1 kg of body weight) and then proceed to the aforementioned diet. With prolonged nephritis, such a diet becomes tiresome for a child, so one should not refuse to add a certain amount of salt (in the absence of edema), fresh fish, and meat. 3) Regular bowel movements are of great importance; if there is a tendency toward constipation, enemas are used, and in addition, every 2-3 days, mild laxatives, e.g., Pulv. liq. comp. 4) We do not use baths in the acute period; subsequently, hot baths with subsequent warm wrapping are advisable. In the pre-uremic stage (vomiting, headache), 1-2 sugar days are used; if uremic phenomena continue, and especially in the case of convulsions, bloodletting (about 100 cm3—leeches, venipuncture, or better, venesection) is performed; good results are also obtained from lumbar puncture; enemas of chloral hydrate (0.5-1.0) are used. Diuretics are inappropriate in the acute period. In case of cardiac dysfunction, which often accompanies nephritis, cardiac medications (camphor, caffeine) are indicated. Specific treatment. First of all, anti-streptococcal serum. Of all microbes, the role of the streptococcus in the etiology and genesis of scarlet fever can be considered the most well-founded. As early as the end of the 19th century (1895), Marmorek prepared an anti-scarlatinal serum by immunizing horses with killed cultures of streptococcus isolated from scarlet fever patients. But the Marmorek serum, as well as the Aronson serum, was soon abandoned due to its ineffectiveness. The Moser serum (1902) gained relatively wider distribution. Unlike Marmorek and Aronson, Moser used freshly isolated cultures of scarlatinal streptococcus for immunization, without first passing them through animals. The Moser serum, if applied early (no later than the 4th day of the disease) in sufficiently large quantities (200 cm3) and in appropriate cases (toxic form), as shown by observations on a large body of material, mainly by Russian doctors (Fedynsky, Aksenov, Egiz, Langovoy, Molchanov), demonstrated a noticeable antitoxic effect; the mortality rate of severe forms of scarlet fever decreased. The negative aspects of the Moser serum: the lack of influence on the local process in the throat and septic phenomena, the unequal effectiveness of serums obtained in different institutes, the lack of a standardization method, the need for injecting large doses, and severe serum reactions. In view of this, the Moser serum did not receive general recognition, and it ceased to be used almost everywhere except in Austria and Russia. A new era in the serum treatment of scarlet fever began after the Dicks in 1924 obtained an antitoxic serum by immunizing horses with the toxin of scarlatinal hemolytic streptococcus. At the present time, after numerous observations in America, Germany, and other countries, including the USSR (Egiz, Danilevich, Sokolov, and others), almost everyone agrees that the Dick serum demonstrates an obvious antitoxic effect in the initial period of scarlet fever, which is expressed in a drop, sometimes critical, in temperature, in the improvement of nervous phenomena and circulatory disorders (pulse, blood pressure), in the rapid fading of the rash, and in a persistent change in the white blood count in the sense of a decrease in leukocytosis and a reduction in the shift to the left. However, there are significant disagreements regarding the influence on the local process in the throat and on complications; in the opinion of the majority of authors, such an influence, if it exists, is inconsistent and little noticeable. A uniform method for titrating the serum has not been developed. Some (for example, the Mechnikov Institute in Moscow) use the American method—by neutralizing the skin reaction with toxin on white goats; others (Leningrad)—the German method using the rash-extinction reaction. Indications for the serum: it should be used in severe and serious cases with toxic phenomena; use in mild and septic cases is inexpedient; it is necessary to inject as early as possible, in the first 4 days of the disease. Dosage: 15-20 thousand units of A of titrated serum (1 A neutralizes 100 skin doses of T), in hypertoxic cases 20-30 thousand; of non-titrated serum—50 cm3, in severe cases 100 cm3; in the absence of a noticeable effect, repeat the injection after 24 hours. Although serum reactions are observed frequently, they are not of dangerous significance and should not serve as a contraindication for the use of the serum. The serum of those recovered from scarlet fever has been studied significantly less. In general, in its action, it differs little from the antitoxic anti-streptococcal serum, i.e., it reduces to a favorable influence on the toxic phenomena of the initial stage of scarlet fever; according to the majority of authors, it does not demonstrate a noticeable influence on complications and the septic process. Danilevich obtained good results in small children with septic complications and considers the serum of recovered patients indicated mainly at an early age, but these observations have not yet been confirmed. The difficulty of obtaining the serum of recovered patients narrows the possibility of its use. Dosage: 1-2 cm3 per 1 kg of weight (Hottinger, Schlossmann). Soviet doctors (Danilevich, Prigozhiy, and others) inject 20.0-50.0 cm3 and more intramuscularly. For septic cases, a vaccine of scarlatinal hemolytic streptococcus (1 billion bacterial bodies in 1 cm3) was proposed, administered at 0.1-0.2-0.5 and more every other day under the skin. Despite the favorable reviews of some authors, we in the pediatric clinic of the First Moscow State University could not verify the effectiveness of this method, nor of a number of others recommended for the treatment of septic scarlet fever: Strepto-jatren, milk preparations, colloidal silver in the form of electrargol intramuscularly and collargol in the form of enemas, blood transfusions, etc. A relatively more favorable impression is obtained from hemotherapy (5.0-10.0-20.0 cm3) in the sense of its influence on necrosis and other complications. If for the treatment of toxic scarlet fever we have a more or less effective agent in the form of antitoxic serum, then for septic scarlet fever we do not have a single more or less reliable agent. The question of treating septic scarlet fever is closely connected with the general problem of treating sepsis (see Sepsis). Therefore, in septic forms of scarlet fever, the doctor must pay all the more attention to general non-specific treatment—nutrition, careful nursing, as well as the treatment of complications. We have had to observe very severe cases of septic scarlet fever with numerous purulent foci (in glands, joints, pleura, ears), with prolonged streptococcemia, which, after many (6-8) months, recovered without the use of any of the "specific" agents listed above (O. Molchanova). VIII. Prophylaxis. Two conditions are necessary for contracting scarlet fever: 1) the penetration of the microbe into the human body and 2) the susceptibility of the latter to the microbe. Accordingly, prophylaxis must be carried out in two directions: 1) in relation to the microbe—to try to prevent its penetration into the human body, to kill it if possible, 2) in relation to the person—to make them insusceptible, immune to the scarlet fever virus. 1. In relation to the microbe—general sanitary-hygienic measures are in the foreground: the rational arrangement of housing and children's collectives (schools, kindergartens, hospitals, outpatient clinics, etc.), the elimination of crowding and overcrowding in them, the strictest cleanliness in the care of children, the introduction of cultural habits into daily life, sanitary-educational propaganda, etc. Upon the detection of a case of scarlet fever—immediate isolation of the patient. For the fastest possible isolation, early diagnosis, immediate notification, and close cooperation in the work of dispensary, school, and other doctors with sanitary-epidemiological health authorities are of great importance. Isolation can best be carried out in a hospital; it is difficult to carry it out in home conditions. A patient may be left at home in exceptional cases with the permission of the sanitary doctor after an inspection of the apartment; all children and those adults who work in children's collectives or have a connection to the production or trade of food products must be removed from it. The person caring for the patient must not have contact with healthy individuals. It is very difficult to establish the duration of isolation for a scarlet fever patient. According to the rules of the People's Commissariat of Health, they are considered safe after 40 days from the onset of the disease and in the absence of acute purulent complications. Peeling and testing for hemolytic streptococcus cannot serve as a sufficient criterion, although some authors (Friedemann and Deicher, Yudalevich and Leshkov, and others) do recommend being guided by the presence of streptococcus in the throat. The condition of the throat and purulent complications are of greater importance; in case of an exacerbation of angina, even if it is catarrhal, and purulent discharges, the patient remains contagious for longer than 40 days. On the other hand, in mild cases without complications and with a calm throat, contagiousness apparently ceases before the specified period. Infection by patients discharged from the scarlet fever ward even after 40 days (return cases) is undoubtedly observed, but it is difficult to establish how often this happens.
According to Pospischill, such cases account for 3.15% of all diseases, and according to Schlossmann, 2-3%. Since the scarlet fever virus from fresh patients can reach those recovering before their discharge, it has long been the practice in London hospitals to separate fresh patients and those with severe complications from those recovering, and to have the latter pass through special departments for disinfection (baths, fresh linen, etc.) before discharge. This system ("fractional disinfection") was widely used for many years by Pospischill in the children's hospital of Vienna and in recent years has been used in Berlin (Friedemann and Deicher—"Luftstationen") and in the Botkin Hospital in Moscow. Although the results of this experiment were contradictory (Pospischill did not observe a noticeable decrease in the number of return cases), such a system should be recognized as expedient. Even greater guarantees should be provided by so-called individual isolation. Patients suspected of having scarlet fever (scarlet fever without a rash, very mild, "erased" forms) must be isolated in special hospital wards. For children who have been in contact with scarlet fever patients and have not had this disease, separation from healthy individuals according to the rules of the People's Commissariat of Health continues for 12 days, and for children who have had scarlet fever, as well as for adults in the absence of acute inflammatory phenomena in the throat and nasopharynx, separation ends on the day after the patient's isolation. Along with isolation, disinfection must also be carried out—both current throughout the entire illness and terminal (see Disinfection). 2. Regarding the individual—measures of general prophylaxis are also in the foreground, which boil down to creating conditions for the child for physiologically normal development, and therefore for the greatest possible resistance to infections in general, and in particular to scarlet fever. These measures are: nutrition, light, air, physical education, etc., which are widely carried out in the USSR by the agencies of Mother and Child Protection and the Protection of Health of Children and Adolescents. Some of these measures coincide with general sanitary-hygienic measures aimed against the microbe, for example, the creation of the best housing and living conditions. As for nutrition, it must be complete and sufficient; one cannot agree with the view (Czerny, Belonovsky) that underfeeding contributes to a decrease in the incidence of scarlet fever. Along with measures of general prophylaxis, there is specific immunization. For passive immunization, anti-scarlet fever antitoxic serum is injected intramuscularly in an amount of 10-20 cm3. Its prophylactic effect is less reliable than that of anti-diphtheria serum; the disadvantages of such an immunization method are the same: the short duration of immunity (2 weeks), the need for repeated injections, and the associated possibility of anaphylaxis. It cannot be recommended as a broad measure of prophylaxis; it is used in relation to children who have been in contact with scarlet fever patients. Degkwitz proposed for such cases the serum of convalescents (5-10 cm3) or healthy adults (20-40 cm3). Danilevich recommends adult serum as a broad measure for combating nosocomial scarlet fever infections; however, the effectiveness of such vaccinations against scarlet fever cannot be considered proven; the difficulty of obtaining serum limits the possibility of its widespread use. Of greater importance is active immunization, the founder of which was Gabrichevsky (1905); his vaccine is a broth culture of streptococci isolated from the blood of those who died from scarlet fever and killed by heating to 56°. A large number (several hundred thousand) of children in Russia, Poland, and Romania were immunized with the Gabrichevsky vaccine, but this material was heterogeneous and was often processed without sufficient consideration of age, epidemiological, and other factors; therefore, despite the favorable reviews of many doctors who worked with the Gabrichevsky vaccine, it was soon abandoned, especially since the streptococcal theory of scarlet fever had few supporters at that time. Active immunization became widespread after the work of the Dicks and their discovery of the scarlet fever toxin. At the present time, there are several methods of active immunization: 1) Gabrichevsky vaccine, 2) combined vaccine according to Korshun-Spirina (killed culture of scarlet fever streptococcus + scarlet fever toxin), 3) Zlatogorov vaccine (killed culture of a freshly isolated generation of scarlet fever streptococcus), 4) pure scarlet fever toxin (American method), 5) scarlet fever anatoxin (toxin treated with formalin), 6) double vaccine for simultaneous immunization against scarlet fever and diphtheria (scarlet fever toxin + neutral diphtheria mixture according to Korshun), 7) local immunization according to Belonovsky-Miller (spraying the throat with virus-toxin, which is a filtrate of a broth culture of the first generations of scarlet fever streptococcus). In addition, experiments were conducted in Italy with the Di Cristina-Caronia vaccine, and in Japan with immunization using the blood of scarlet fever patients (Takahashi) in the acute stage, etc. The XI Congress of Bacteriologists placed immunization with combined vaccine (Moscow), pure toxin (Leningrad), and anatoxin in first place among all the indicated methods. Active immunization against scarlet fever is scientifically grounded, tested on a large amount of material, and is currently being carried out in the USSR and other countries as a measure of mass prophylaxis. In large cities of the USSR (Moscow, Leningrad), anti-scarlet fever vaccinations (like anti-diphtheria ones) have been declared mandatory by resolutions of local health departments, primarily for organized children's institutions (nurseries, kindergartens, schools, etc.). Children aged 6 months to 14 years are subject to immunization. Up to 7 years, immunization is carried out regardless of the Dick reaction; after 7 years, only for those whose Dick reaction is positive. The dosage and technique of vaccinations vary depending on the vaccine material and the scheme adopted in one institute or another. In Moscow, with the combined vaccine (1 billion streptococci + 2,000 skin doses of toxin in 1 cm3), vaccinations are given 4 times, of which 3 times with the vaccine in increasing doses and the last time (4th or 5th) with pure toxin (2,000-9,000 skin doses depending on age). The interval between individual vaccinations is 7-10 days. Contraindications: febrile states, acute gastrointestinal diseases, hypo- and atrophy, active tuberculosis, kidney diseases, blood diseases, etc., at the discretion of the doctor. Vaccinations with the correct dosage are safe. In rare cases, toxicosis is observed, which is expressed primarily in the appearance of a strong reaction at the injection site—redness, a fine-spotted rash that quickly spreads to the trunk and limbs; the temperature can reach 39°, sometimes vomiting, white dermographism, hyperemia of the throat; there is no plaque or enlargement of the submandibular glands; the general condition is good, and all phenomena disappear without a trace after 1-2 days. The duration of immunity is 1-2 years; after local immunization, according to Belonovsky, 4 months. Thus, repeated vaccinations are necessary (especially in preschool age) after a year has passed. The criterion for the effectiveness of vaccinations is primarily the Dick reaction (see Dick reaction). According to Korshun and Spirina (Moscow), a positive Dick reaction turned into a negative one after three injections of the combined vaccine in 83.9% of cases, after an additional (fourth) injection of toxin—in 85.4%, after three injections of pure toxin—in 88%, and after four injections of toxin—in 89.2%. In Leningrad, those who underwent a single vaccination with toxin showed a transition of a positive Dick reaction to a negative one in 55% of cases, after three vaccinations—70.8%, and after four—85.1% (Besedin). Many do not consider the Dick reaction to be a true indicator of immunity to scarlet fever; therefore, observations of the vaccinated, both in terms of the incidence of scarlet fever and the course of this disease in them, are more conclusive. In Moscow, the incidence among the vaccinated decreased by 10-15 times compared to control groups of children, and in Leningrad by 5-6 times. A decrease in incidence was also obtained in America and other countries. As for the course of scarlet fever in the vaccinated, according to data from the Botkin Hospital in Moscow (Mikhailov), it proceeds significantly more mildly in them, and the percentage of complications is lower. At the same time, in the Model Children's Hospital of Moscow, no noticeable difference was obtained (Skvortsov). However, the number of cases in both hospitals is small, and they have been examined insufficiently thoroughly, especially those who died, without indications of the Dick reaction, constitutional, socio-living, and other conditions. The question of the course of scarlet fever in the vaccinated remains the least studied. The general result of active immunization at the present time should be recognized as positive, but an exhaustive scheme of active immunization is still needed.
Standard B 1 CJU3 Age Dosage Duration of intervals between vaccinations Duration of immunity Vaccination material combined toxin Combined vaccine 1 billion streptococci + 2,000 skin doses 6 m.-2 y. 3 y.-5 y. 6 y.-10 y. 10 y.-14 y. 0.15 0.25 0.3 0.4 0.3 0.5 0.7 1.0 0.8 M 1.5 2.0 2,000 3,000 6,000 9,000 4,000 6,000 7-10 days 1-2 years Toxin of scarlet fever streptococcus B 0.1-300 - 600 s. d. 6 m.- 3 y. 3 y.- 7 y. 7 y.-14 y. 300 400 600 1,600 2,400 3,000 4,000 6,000 6,000 10,000 15,000 8,000 7-14 days 1-2 years Divaccine 1 y.- 4 y. 4 y.- 7 y. 7 y.-14 y. 0.15 0.25 0.3 0.4 0.6 0.8 0.8 1.0 1.5 6,000 8-10 t. 12-15 t. 7-14 days 1-2 years Virus-toxin according to Belonovsky Pulverization of throat spray 1 cm3 of virus-toxin 4 days in a row 4 months; an assessment can be given only later; not only mass observations over a sufficiently long time are necessary, but also, which is especially important, a thorough and objective processing of the material, taking into account epidemiological, biological, and socio-living conditions. The very organization of vaccination work must be set up correctly; in addition to bacteriologists and epidemiologists, dispensary doctors, pediatricians, and the Soviet public must be involved in it. It should be pointed out once again that for all the importance of active immunization as one of the methods of mass prophylaxis of scarlatina, in the forefront of the fight against scarlatina epidemics, it is necessary to place the above-mentioned general measures of prophylaxis and sanitary-hygienic measures. All these measures on a broad state scale with the coverage of the entire working population can be carried out only under the socialist structure of society. There are all grounds to count on the fact that in the USSR, on the basis of socialist construction, scarlatina will be liquidated along with other infections.
Molchanov. IX. Postpartum scarlatina. The first description of postpartum scarlatina belongs to Malfatti (1799). However, many authors are inclined to consider the observed cases of scarlatina in puerperas as a manifestation of ordinary puerperal infection caused by streptococcus (Helm, Schroeder, Winkel, Ahlfeld, Doleris, Lebedev, and others). The pathogen of postpartum scarlatina is most often hemolytic streptococcus, to which the organism at the moment of infection has increased sensitivity in connection with previously suffered streptococcal diseases. From this point of view, postpartum scarlatina can be called "scarlatinous sepsis," and infection with it occurs more often at the moment of childbirth. In this case, the entry gate for the streptococcus can be not only the area of the throat but also the area of the genital organs (scarlatinae extrabuccalis). The clinical picture of postpartum scarlatina can be diverse. It depends on the nature of the organism's reaction to the invading streptococcus. If the organism's reaction goes in the direction of anaphylaxis, then in its maximum manifestation, in anaphylactic shock, the entire syndrome of the disease characteristic of scarlatina is revealed: fever, exanthema, general severe condition ("pure" form of scarlatina). With a normal normergic reaction of the organism, the disease can be limited only to angina or endometritis (formes frustes) or the disease can proceed according to the type of septicopyemia (septic form). In puerperas, there is also a "pure" form of scarlatina, which often proceeds toxically with a fatal outcome in the first days of the disease, or its septic form (mortality up to 50%). The frequency of postpartum scarlatina is not constant. In addition to single sporadic cases, small epidemics of it were also observed (in Lyon in 1909 and 1921, in Toulouse in 1912, in Paris in 1919-1920, and others), and usually they were simultaneous with epidemics of sepsis. The fight against this disease should be directed towards prophylaxis. Since diseases of the nose and angina, which are widespread among the population, play a large role in the pathogenesis of postpartum scarlatina, it is necessary to examine the condition of the throat in incoming women in labor, as well as in puerperas. Appropriate control must also be carried out over the attending personnel. In addition, it is necessary to emphasize once again the need to observe strict asepsis during childbirth and in the postpartum period, taking into account that streptococci stubbornly retain their virulence, even despite drying (Bürger). Therapy for postpartum scarlatina should be directed at the streptococcus, however, it is necessary to take into account the peculiarities of each case, as well as the nature of the organism's reactions to the pathogen. A. Lebedev. Psychoses in scarlatina - see Infectious psychoses.
Related articles
Mentioned in
Cite this page
“Scapula Alata.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/scapula-alata/