Scapula
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article provides a detailed anatomical description of the scapula, detailing its shape, surface features, muscle attachments, and articulations. It includes illustrations and discusses the spaces between muscles and bones.
Encyclopedia article (1928–1936)
SCAPULA (shoulder blade) belongs to the bones of the upper or anterior limb girdle. In humans, it is a flat, wide, and very thin triangular bone, adjacent to the dorsal surface of the chest from the seventh rib. Its three angles are: the medial (angulus medialis), the lateral (angulus lateralis), and the inferior; the three edges are closed: the vertebral (margo vertebralis), the axillary (margo axillaris), and the superior (margo superior). The dorsal surface (facies dorsalis), accessible for examination through the skin, is slightly convex and is divided by a spine (spina scapulae) running horizontally into the supraspinous fossa (fossa supraspinata) and the infraspinous fossa (fossa infraspinata) (Fig. 1). The latter is significantly larger than the former in size. From several bony ridges of the fossae infraspinatae begin bundles of the infraspinatus muscle (m. infraspinatus), attaching to the greater tubercle (tuberculum majus) of the humerus (rotates the upper limb outward). In the fossa supraspinata begins the supraspinatus muscle (musculus supraspinatus), attaching there (abducts the upper limb). Mm. supra- and infraspinatus are covered by fasciae attaching to the edges of the fossae supra- and infra-spinatae; they form bony-fibrous spaces together with the bones. The m. trapezius covers the fossa supraspinata from above and attaches to the acromial end of the clavicle (pars acromialis claviculae), to the acromion and the spine of the scapula (raises the scapula and brings its medial edge closer to the spine). The bony-fibrous spaces of the fossae supra- and infraspinatae are filled with the same muscles, passing towards the capitulum humeri into terminal tendons covered by loose connective tissue spreading down to the subdeltoid space (spatium subdeltoideum). Therefore, suppurations and hemorrhages starting in one of these spaces can spread to the other. The scapular spine rises in the form of a high ridge at the level of the third thoracic vertebra and proceeds as a bony barrier between the supra- and infraspinatus muscles; the upper edge of it, palpable through the skin of the back, is an important point for the projection of internal organs onto the surface. It turns into a large flattened process at the height of the arm, into the acromion, rising above the shoulder joint from above and behind. At the upper edge of the acromion laterally there is an articular surface of oval shape, serving for articulation with the clavicle (facies articularis acromii). At the lateral angle of the scapula is the glenoid cavity (cavitas glenoidalis), which is the only place where the bone is not flattened and retains its original thickness (Fig. 2). It has an oval concave, slightly pointed surface, the upper edge of which turns into a tuberosity (tuberositas supraglenoidalis), from which begins the tendon of the long head of the biceps brachii muscle, attaching to the tuberosity of the radius (tuberositas radii) (musculus biceps flexes the forearm and supinates it). Directly under the glenoid cavity is the inferior tuberosity (tuberositas infraglenoidalis), where begins the tendon of the long head of the triceps muscle (m. triceps), attaching to the olecranon of the ulna (extends the arm at the elbow joint). Narrowing medially, the articular surface forms the neck of the scapula (collum scapulae), especially clearly expressed on the dorsal surface of the scapula, where the spine of the scapulae does not reach the cavitas glenoidalis. The interval between the spine of the scapula and the edge of the cavity has a semilunar notch; at this place the neck is not covered by muscles, and through the formed space the vascular-nervous bundle (a. transversa scapulae and n. suprascapularis - Fig. 3) goes from the fossa supraspinata into the fossa infraspinata.
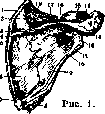
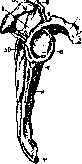
Figure 2.
Figure 1. Scapula from behind (muscle attachment sites outlined); 1- m. levator scap.; 2- m. supra- spinatus; 3 and 14- m. trapezius; 4 and 13- m. deltoid.; 5- m. rhomb. minor; 6- m. infraspinatus; 7- m. rhomb. major; 8- m. teres major; 9- m. teres minor; 10- fossa infraspinatus; 11- m. triceps brachii; 12- angulus lateralis; 15- m. biceps brachii; 16- spine scapulae; 17- m. omohyoid.; 18- m. supraspinatus. Figure 2. Scapula from outside: 1- fossa supraspinatus; 2- acromion.; 3- angulus med.; 4- tuberositas supraglenoidalis; 5- process coracoideus.; 6- cavitas glenoidalis; 7- tuberositas infraglenoidalis; 8- margo axillaris; 9- angulus inferior; 10- fossa infraspinatus (angulus inferior).
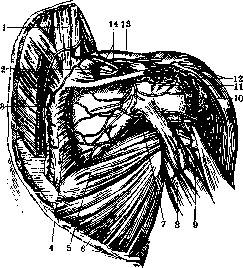
Figure 3. Dorsal surface of the shoulder joint area after removal of mm. supra- et infraspinatus. 1- m. levator scapulae; 2- m. supraspinatus; 3- m. rhomboideus major and m. rhomboideus minor; 4- m. infraspinatus; 5- m. teres major; 6- m. latissimus dorsi; 7- a. circumflexa scapulae; 8- a. circumflexa humeralis posterior et a. axillaris; 9- a. profunda brachii et n. radialis; 10- mm. infraspinatus et teres minor; 11 and 14- n. suprascapularis et a. transversa scapulae; 12- m. deltoid.; 13- lig. transversum scapulae.
Directly under the glenoid cavity is the inferior tuberosity (tuberositas infraglenoidalis), where begins the tendon of the long head of the triceps muscle (m. triceps), attaching to the olecranon of the ulna (extends the arm at the elbow joint). Narrowing medially, the articular surface forms the neck of the scapula (collum scapulae), especially clearly expressed on the dorsal surface of the scapula, where the spine of the scapulae does not reach the cavitas glenoidalis. The interval between the spine of the scapulae and the edge of the cavity has a semilunar notch; at this place the neck is not covered by muscles, and through the formed space the vascular-nervous bundle (a. transversa scapulae and n. suprascapularis - Fig. 3) goes from the fossa supraspinata into the fossa infraspinata.
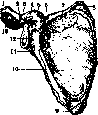
Between the upper end of the glenoid cavity and the scapular notch lies the coracoid process (processus coracoideus), which is bent at a right angle laterally and anteriorly and rounded at the end. It is located somewhat below the acromial process, with which it is connected by a strong flattened ligament (lig. coraco-acromiale), stretching like an arch over the head of the humerus and preventing the raising of the arm above the horizontal line. The m. pectoralis minor, starting from the cartilages of the II-V ribs (pulls the shoulder girdle forward and down, fixes the scapula during arm movement backward), and the short head of the musculus biceps brachii and the coracobrachialis muscle (m. coracobrachialis), united with the previous one and attaching to the middle of the humerus (adducts and raises the arm), begin from the process coracoideus. The coracoid process covers the shoulder joint from above and in front, while the acromion covers it from above and behind. At the base of the coracoid process is the subcoracoid bursa (bursa subcoracoidea), often in communication with the subscapular bursa. Bursae are sometimes found under mm. supraspinatus and infraspinatus. The anterior surface of the scapula (facies costalis) is concave and forms a depression (fossa subscapularis) (Fig. 4), through which run from above downwards to the margo vertebralis small bony ridges (lineae musculares), serving as the beginning of the subscapular muscle (m. subscapularis), attaching to the crest and the lesser tubercle of the humerus (crista tuberculi minoris and to tuberculum minus) (rotates the arm inward). Between this muscle and the joint capsule is the subscapular bursa (bursa subscapularis), communicating with the joint. At the upper and lower angles of the scapula and the margo vertebralis begins the serratus anterior muscle (m. serratus anterior), attaching with massive teeth to the I-IX ribs (shifts the scapula to the side and forward, fixes it on the chest). The upper edge of the scapula (margo superior) is twice shorter than the medial one, has a notch (incisura scapulae), sometimes connected by a bony bridge, so that an opening is formed. The medial edge of the scapula (margo vertebralis) is the longest and is called the base of the scapula (basis scapulae). Above, to the medial angle of the scapula attaches the muscle raising the scapula (m. levator scapulae), starting from four short tendons from the transverse processes of the tuberculum posterius of the four cervical vertebrae (raises the scapula). To the margo vertebralis of the scapula attaches the rhomboid muscle (m. rhomboideus major and minor),
Figure 4. Scapula from the front (muscle attachment sites outlined): 1- m. deltoid.; 2- m. biceps brachii (caput breve); 3- m. coracobrachialis; 4- m. pectoralis minor; 5- process coracoideus.; 6- incisura scapulae; 7- fossa subscapularis; 8 and 9- m. serratus anterior; 10- m. subscapularis; 11- m. triceps brachii; 12- collum scapulae; 13- acromion.
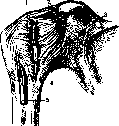
Figure 5. Shoulder joint from the front: 1- m. subscapularis (cut); 2- lig. coraco-humeralis; 3- lig. transversum scapulae sup.; 4- caps. art.; 5- m. biceps.
which originates at the spinous processes of the four upper thoracic and two lower cervical vertebrae (it adducts and elevates the scapula) (see table). The intrinsic ligamentous apparatus of the scapula includes the superior and inferior transverse scapular ligaments [lig. transversum scapulae super. (Fig. 5) et inf.]; the former is bridged across the incisura scapulae and sometimes ossifies; the suprascapular nerve passes through the resulting foramen; the transverse scapular artery with the vein of the same name passes more often above the ligament. The inferior transverse scapular ligament (lig. transversum scapulae inf.) forms a bridge of flat bundles from the root of the spina scapulae to the edge of the cavitas glenoidalis; the aforementioned neurovascular bundle also passes beneath it. The clavicle, being situated above the coracoid process, is connected to the latter by two powerful ligaments, combined into the lig. coraco-claviculare (coracoclavicular ligament); the one located anteriorly is called the trapezoid ligament (lig. trapezoideum), and the one lying posteriorly is the conoid ligament (lig. conoideum). The acromioclavicular joint is reinforced from above by the acromioclavicular ligament (lig. acromio-claviculare), which is 3–4 mm thick (Figure 6). The cavitas glenoidalis is covered with hyaline cartilage, the layer of which is thicker at the periphery; the glenoid cavity is supplemented by the glenoid labrum (labrum glenoidale), which ensures greater congruency of the articular surface. Starting from the edge of the glenoid labrum, and in some places from it, the articular capsule (capsula articularis) begins, attaching to the humerus along the collum anatomicum; the capsule is very wide, loose, thin, and almost everywhere reinforced by interwoven tendon fibers of the mm. supra- and infraspinatus, teres minor, and sub
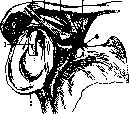
scapularis. It has only one accessory ligament, the coracohumeral ligament (lig. coraco-humerale), which begins on the processus coracoideus and attaches to the capsule in the upper and posterior part. In addition to the surrounding muscles and the two processes of the scapula with the lig. coraco-acromiale, the lig. coraco-humerale and the capsule also act as brakes on movement in the shoulder joint. (Near the lig. coraco-humerale on the inner side and at the lower edge of the glenoid cavity is the weakest point; during a dislocation, the head of the humerus most often exits its articular connections here—luxatio subcoracoidea and axillaris.)
Vessels of the scapula. The scapular transverse artery (a. transv. scapulae) and the transverse artery of the neck (arteria transversa colli) begin from the subclavian artery. The first, covered by bone, runs parallel to the clavicle, directing laterally toward the upper edge of the scapula and, passing above the transverse ligament, penetrates the supraspinatus space. The artery supplies the supraspinatus muscle, rounds under the acromial process of the scapula, and with its terminal branches supplies the infraspinatus muscle, anastomosing with the circumflex scapular artery and the transverse artery of the neck, in particular with the descending ramus. The transverse artery of the neck passes dorsally between the trunks of the brachial plexus, located laterally to the subclavian artery, and divides into the ascending ramus, which goes to the posterior muscles of the neck, and the descending ramus, which directs itself under the rhomboid muscle at the medial angle of the scapula downward and supplies the broad muscles of the back. Sending branches into the supra- and infraspinous fossae, the transverse artery of the neck anastomoses with the transverse and circumflex scapular arteries. The subscapular artery (a. subscapularis), a branch of the axillary artery, begins above the tendon of the latissimus dorsi. Dorsally, through the infracoracoid space, the circumflex scapular artery departs from it, going into the infraspinatus space and anastomosing with the branches of the transverse scapular artery and the transverse artery of the neck (Fig. 3). Lymphatic supply. A group of lymph glands located in the axillary region (cavum axillare) dorsally receives vessels coming from the back and shoulder region; a dense lymphatic network connects these glands and forms the axillary plexus. With this plexus are also connected the subscapular glands, which receive lymphatic vessels from the superficial layers of the chest wall and accompany the subscapular artery and vein. Passing along the anterior edge of the scapula upward, where they at the level of the lateral infracoracoid space join the main trunk, adhering to the subscapular vein, they subsequently flow into the subclavian trunk (truncus lymphaticus subclavius). Innervation. The suprascapular nerve (n. suprascapularis), beginning from the brachial plexus from C5, C6, passes under the lateral edge of the plexus and directs itself together with the transverse scapular artery to the scapular notch, passing under the transverse ligament to the supraspinous fossa; here it innervates the supraspinatus muscle and reaches the infraspinatus muscle, rounding the scapular spine at the lateral angle of the scapula. The subscapular nerves (nn. subscapulares), beginning from C5, C6, C7, C8, consist of two or three trunks emerging from different places of the plexus: the superior subscapular nerve supplies the subscapularis muscle. The middle subscapular nerve supplies the lower part of the subscapularis muscle and the teres major muscle. The inferior subscapular nerve, or thoracodorsal nerve, is longer than the first and is interesting from an operative point of view; sometimes it departs from the axillary nerve, less often from the radial nerve, runs along the lateral edge of the scapula, innervating the latissimus dorsi muscle. Ontogeny. The scapula develops very early; in a human embryo 9 mm long, the scapula represents a small flattened cartilage. In an embryo of 11 mm it already resembles a bony scapula in shape. The ossification process in the scapula proceeds from 7 points: one for the body, two for the coracoid process, two for the acromion, one for the base, and one for the inferior angle. The ossification process begins in the second month of intrauterine life with the neck of the scapula; in the third month a bony plate begins to rise from the scapular spine. The newborn has the greater part of the scapula bony, only the coracoid and acromial processes, the posterior edge and the inferior angle are completely cartilaginous. In the 7th-8th week the ossification nucleus of the coracoid process appears. In the 16th-18th year an ossification nucleus appears on the inferior angle, vertebral margin, and at the articular fossa. By the time of sexual maturity the coracoid process fuses with the body of the scapula. By the 23rd-25th year all parts fuse with the body of the scapula into one whole. Phylogeny. In vertebrate animals, beginning with sharks (Selachia), the shoulder girdle has the form of a paired cartilaginous arch. The part of the arch lying above the glenoid fossa may be called scapular, since in this area in higher forms the scapula subsequently develops. In amphibians one can already distinguish a dorsally located scapula. Amphibians, reptiles, and birds use the coracoid bone for attachment to the sternum; the clavicle is absent in some (e.g., in the crocodile). In birds both scapulae are extremely elongated, saber-shaped; the scapula had the same shape in flying reptiles (Pterosauria). In flightless birds (penguins) it is not saber-shaped, but widened and flattened. The coracoids, powerful and wide bones, rest against the sternum. Mammals, by the structure of the shoulder girdle, are divided into two types: to the first, more primitive, belong egg-laying mammals (Prototheria), having a shoulder girdle close to that of reptiles, to the second the other mammals with a shoulder girdle close to that of man. In egg-laying mammals the scapula fused with the coracoids, resting against the sternum and provided with a process—the acromial process, the rudiment of which is present in lizards. Of the marsupials (Marsupialia), the brushtail possum (Trichosurus) has coracoids in the embryonic period spreading to the sternum and subsequently attaching to the scapula in the form of its process. In this form the scapula exists in all viviparous mammals having a scapula with a spine (spina scapulae) and an acromial process. The wide scapula of man, owing its shape to the development of the shoulder musculature, is not so wide in lower animals, whose forelimbs represent a support organ, especially at the base on its middle and posterior edge. Apparently the greater width of the middle part of the human scapula with powerful development of its spine can be considered a secondarily acquired peculiarity. The structure of the scapula and the distribution of cancellous bone substance in it are noticeable in sections and during radioscopy. The entire triangle of the scapula, thinned and composed of compact substance, is divided by the spine into two unequal parts; cancellous substance is located along the vertebral margin, inferior angle, and lateral margin, where the edge of the bone is especially thickened. The scapular spine, processes, neck, glenoid cavity and partially the superior margin with the medial angle are also composed of cancellous substance. Correspondingly to the structure of the scapula, the resistance to pressure and the strength against fracture of the scapula can be characterized. Greater strength is inherent in the cancellous periphery of the scapula, especially the outer edge, as well as the processes. Sexual differences of the scapula can be taken into account only when describing and characterizing the whole skeleton; it is difficult to speak about sexual differences in individual scapulae. Table of functions of scapular muscle groups in relation to the shoulder joint. Movement Abduction Flexion Extension Rotation / inward outward Typical muscles, i.e., participating in the main movement Supraspinatus Subscapularis Infraspinatus Subscapularis Infraspinatus Repeating movement muscles Deltoideus Pectoralis major Latissimus dorsi »» Deltoideus. Statics and dynamics. The clavicle and coracoid process are connected by a ligamentous apparatus in such a way that the weight of the limb is transferred from the articular end of the clavicle to the points of attachment of the ligaments to the bone. Otherwise, in contrast to four-legged animals, in the vertical position of the body the joint between the scapula and clavicle would be heavily burdened, since the arm and the weight of the entire upper limb hang on the scapula. One of the conditions of the upright position of the body consists in the fact that the clavicle, strengthened by ligaments at the acromial end, can withstand the weight of the scapula and the upper limb. Itself, being strengthened on the chest wall, breaks down into a heavily burdened long arm of a lever reaching to the coracoid process, and a short arm of a lever going to the acromial process and almost completely unburdened. The movements of the scapula are transmitted to the entire upper limb and acquire only thanks to this great freedom. The weight of the upper limb is transferred the more easily, the more the point of attachment is moved from the acromial process to the chest wall.
Ternovsky. Pathology. Among congenital diseases of the scapula, one must note developmental anomalies, which usually occur in conjunction with anomalies in other organs. Thus, in cases of deformity of the head of the humerus, the glenoid cavity is absent. More often, the so-called congenital high standing of the scapula is observed, first described by Sprengel. In such cases, the scapula on one side, more often the left (70%), stands 2-3 cm higher than the scapula on the opposite side and sometimes rotates around the sagittal axis, such that the lower angle is turned toward the midline, and the outer edge is turned downward. Bilateral high standing is encountered less frequently. The condition is discovered at the age of 1-13 years, more often in girls, and occurs both independently and in conjunction with other developmental defects (spina bifida, the presence of cervical ribs, etc.). Sometimes high standing is accompanied by a reduction in the size of the scapula itself, a change in its configuration, shortening of the clavicle and humerus, atrophy and weakness of the muscles of the corresponding side of the chest, and scoliosis in the thoracic region (Lance). The cause was considered to be a spastic state of the musculature due to a congenital lesion of the central nervous system. At the present time, there are indications in the literature that high standing of the scapula is transmitted by a hereditary pattern. Thus, Gottesleben reports two cases in which high standing was repeated in many generations. Treatment is reduced to the application of massage and gymnastics if there is a limitation of movement in the shoulder joint. For curvatures of the spine, orthopedic treatment yields good results. Operative treatment is used in severe cases that do not respond to therapeutic intervention and consists of cutting the upper scapular muscles on the affected side, followed by orthopedic treatment. Traumatic injuries of the scapula are usually associated with direct violence (a blow, a contusion) or occur from a fall. Most frequent are contusions with hemorrhage and paresis of the scapular musculature. Treatment is by rest followed by massage. Wounds are encountered extremely rarely in isolation, more often simultaneously with wounds of other organs; treatment is conducted according to the general principle of open injuries with the application of rest (immobilization) and aseptic dressings. Fractures of the scapula are not observed often: according to Bruns' data—in 0.86%, according to Richter—in 4%, according to Tikhov—in 0.86%, according to Dukhanin—in 0.1%. They are encountered more often in men aged 21-50 years, less often in women, and extremely rarely in children. According to the site of the fracture, the following types are distinguished: 1) fractures of the body and angle of the scapula, 2) fractures of the articular surface of the scapula, 3) fractures of the neck of the scapula, 4) fractures of the acromion and spine, and 5) fractures of the coracoid process. Of the indicated types, fractures of the body, neck, and acromion are observed most often. Fractures of the body occur from direct violence (falling of a heavy object, being run over by a carriage, a blow) and are observed in the form of cracks without displacement or complete fractures: transverse, longitudinal, diagonal, and multiple. The fracture line in transverse fractures runs in a transverse or oblique direction; in longitudinal ones—from the angle of the scapula upward, sometimes also involving the scapular spine; and in diagonal ones—obliquely (Fig. 7


7. Fig. 7. Double transverse fracture of the scapula. Figure 8. Diagonal fracture of the scapula. and 8). Multiple fractures are also called comminuted, since when fracture lines intersect, the bone breaks into small fragments. Recognition of fractures without displacement presents difficulties, since such a fracture of the scapula sometimes does not cause any movement disorders and can easily be mistaken for a contusion. In these cases, radiography also sometimes helps little, since due to the thickness of the chest and the superimposition of the fracture line on a rib, it is difficult to detect the fracture site on the radiograph. In these cases, repeat radiography in inspiration and expiration helps. In complete fractures and those with displacement, abnormal mobility of individual parts, protrusion, and sometimes crepitus and pain upon movement of the scapula are discovered. It is not always possible to palpate the sharp edge of the fracture and the gap between the fragments. Treatment is reduced to rest and the application of a fixing gauze (Desault), adhesive plaster (Sayre), or plaster cast with immobilization of the arm and shoulder in a position that provides the most intimate contact after the fragments have been set. The prognosis is good even if union occurs in an incorrect position, since the function of the arm usually does not suffer.
Fractures of the upper and lower angle occur in isolation or simultaneously with other fractures; they occur more often from direct violence and even from strong muscle tension and are usually accompanied by displacement and even rotation of the fragment (predominantly fractures of the lower angle of the scapula). Recognition is aided by both palpation of the fragments of the scapula, which are mobile in mutually opposite directions, and radiography. Treatment consists of the correct setting of the fragments and fixation of the entire shoulder girdle in this position with an immobile dressing. If the fragments have a tendency to separate, operative suturing may be indicated, mainly in persons of heavy physical labor. With incorrect union, function suffers little or not at all, but an exostosis may subsequently form at the site of the fracture, which will bother these patients during heavy physical work (carrying heavy loads; Schreiber). Fractures of the articular cavity of the scapula usually occur from a fall onto the shoulder and are encountered simultaneously with a dislocation or without it, if the ligaments are strong enough to prevent dislocation of the head of the humerus, causing at the same time an avulsion of the articular cavity (Fig. 9). The fracture is observed in the form of an avulsion of a piece of the articular cavity or a fracture of the entire cavity with the exception of the upper part. Diagnosis is complicated by the presence of hemarthrosis. Slight pain, the possibility of active movements in the joint, and radiography help to clarify the diagnosis. Treatment is conservative if possible, provided the fragments are correctly set. In the presence of a free body in the joint cavity or the impossibility of bringing the fragments into contact, arthrotomy with suturing or removal of the fragment is indicated.
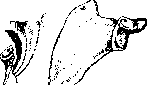
Fractures of the neck of the scapula occur from direct violence and are located immediately below the articular line (fractures of the so-called anatomical neck) and together with the coracoid process (fracture of the surgical neck of the scapula) (Figs. 9 and 10). In the latter case, the fracture line runs from the scapular notch. These fractures are rare. Thus, Lonsdale found 18 scapular fractures out of 1,901 cases of fractures, including 2 neck fractures; Lente found 17 scapular fractures out of 1,772 cases of fractures, including 1 neck fracture. The clinical picture of a neck fracture is the clearest and consists of flattening of the shoulder joint region, drooping of the shoulder, and prominence of the acromion. The head of the humerus is sometimes palpable in the axillary cavity. There, one can also clearly palpate the sharp edge of the fracture; the arm is abducted and appears lengthened, the coracoid process follows the movements of the arm, and crepitus is obtained upon rotation. Examination is supplemented by radiography. Treatment consists of reposition and is usually easily successful. To keep the fragments in contact, a fixing plaster, gauze, or adhesive plaster dressing (Desault, Sayre) is applied with a pad or triangle in the axillary cavity. In order to prevent adduction and rotation, Bardenheuer recommends traction with abduction of the arm outward and upward or upward traction with adduction of the arm. Fractures of the acromion and spine occur from direct violence (such as, for example, a blow directly to the acromion) and are encountered frequently among other scapular fractures. Thus, Lonsdale notes 8 acromion fractures out of 18 scapular fractures. In adults, transverse fractures near the apex or base are more common; in adolescence, epiphyseal fractures. Clinically, it is sometimes difficult to determine the fracture, since function does not suffer and there may be no displacement. With impairment of arm function, pain in the fracture region, especially upon pressure, or prominence of the broken end, it is not difficult to make a diagnosis. Treatment consists of applying a fixing dressing. With displacement and prominence of the fragments, reduction under local anesthesia and the application of a pressure dressing are recommended. Bardenheuer advises traction of the adducted arm upward. Fractures of the coracoid process of the scapula are the rarest, are usually located at the base, and are more often in combination with other fractures of the scapula. Figure 9.
Figure 10. Figure 9. Fracture (dashed line of the neck). Figure 10. Fracture of the scapula. Cavity fracture. Displacement is possible only with the rupture of the lig. coraco-acromialis and lig. coraco-clavicularis. Fractures occur both from direct violence (a blow) and indirect—from muscle tension. As an exception, fractures of the epiphysis are encountered in childhood. Clinically, a fracture of the coracoid process without displacement is determined only by local pain upon pressure and movement of the arm forward. With the rupture of the ligaments, displacement of the coracoid process downward and inward occurs. A reliable diagnostic tool is radiography. Treatment for displacement of the fragment consists of reduction under local anesthesia and a fixation bandage. Treatment with fixation bandages for all types of scapular fractures is limited to 3 weeks, during which complete consolidation occurs. Subsequently, mechano-physiotherapeutic treatment is prescribed. The prognosis for scapular fractures is favorable, as no functional disorders occur.

Inflammatory diseases. Among acute diseases, abscesses and osteomyelitis are noted; among chronic ones—tuberculosis and syphilis. Abscesses can be located superficially behind the scapula and deeply in front of the scapula. The determination and treatment of the former present no difficulties, while the latter may remain undetected for a long time. The presence of high temperature and the absence of local phenomena at the beginning of the disease force one to think about a general infection. The appearance of local pain, difficulty in moving the arm, and the discovery of swelling or an infiltrate in the axillary cavity indicate the true nature of the disease. Upon establishing the diagnosis, it is necessary to immediately make a deep incision in the direction of the inflammatory focus, even if there is only induration. After dissecting the skin and subcutaneous tissue in the axillary cavity, one should bluntly pass with a forceps to the anterior surface of the scapula, where an abscess is usually located in the depth of the muscles. The incision must be large enough to ensure good drainage of pus.
Acute osteomyelitis of the scapula arises similarly to osteomyelitis of other bones on the basis of 1) trauma with subsequent infection, 2) penetration of infection from surrounding parts, or 3) hematogenous origin. Osteomyelitis develops with high temperature and subsequent formation of an abscess and sequestrum. In the acute period, upon discovery of an abscess, treatment can be carried out with punctures with aspiration of pus, and auto-pyo-autovaccine therapy. If treatment with punctures is unsuccessful, when the general condition of the patient does not improve and the temperature does not subside, it is necessary to perform an incision. Preliminary X-ray examination reveals rarefaction of the bone at the site of the lesion or focal changes with sequestra and thickening of the periosteal capsule. An unfavorable aspect of surgical treatment is that a sequestrum, such as we have in osteomyelitis of tubular bones, is encountered extremely rarely in lesions of the scapula, and usually there is a gradual melting of the cancellous bone with the formation of fistulas (Figures 11 and 12). Therefore, surgical intervention should consist of subperiosteal removal of part or the entire scapula (Fig. 14).
Tuberculous lesion of the scapula is encountered rarely and can affect both the body and the neck of the scapula. In the latter case, the process can spread to the shoulder joint and present a picture of joint involvement. The disease usually proceeds chronically with the formation of cold abscesses and fistulas (Fig. 13). Movements of the scapula suffer little at the beginning of the disease, but with the development of the disease, the functions of the scapula are limited, and muscle atrophy sets in. Upon the formation of swelling in the region of the scapula, it is extremely easy to mistake a slowly developing disease for a tumor. X-ray examination shows rarefaction of the bone tissue, sometimes with the formation of cavities without signs of periosteal proliferation. In doubtful cases, a puncture is indicated, which, in the presence of cheesy pus, clarifies the true picture of the disease. The presence of blood in the punctate forces one to think about a tumor (take other signs into account as well). Treatment of tuberculosis of the scapula is conservative: rest, nutrition, aero- and heliotherapy, quartz lamp, iodine therapy; more often encountered is lipoma in the form of a limited subcutaneous node or in the form of a large pendulous tumor on a wide stalk. Slow growth, the consistency of the tumor, lobulation, and sometimes a sensation of crunching upon palpation help in clarifying the diagnosis. Less frequently encountered are fibromas in the form of a solitary, dense, limited, and growing tumor over years, or as a manifestation of general fibromatosis. Chondromas and exostoses, originating from the bone, are located in the depth of the muscles and are therefore sometimes difficult to determine. Radiography helps in clarification. Treatment can only be surgical and is indicated in case of functional impairment, the tumor's tendency for rapid growth, and the possibility of malignant degeneration.
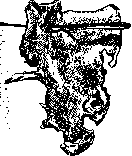
Among malignant tumors, sarcomas (chondro-, osteosarcomas) and carcinomas are observed. The latter are predominantly metastatic. Langenhagen's statistics show that out of 72 cases of scapular tumors, there are 8 exostoses, 14 chondromas, 5 fibromas, 23 carcinomas, and 2 tumors of unknown nature; according to Walder—19 enchondromas, 30 carcinomas, and 16 sarcomas. The tumor can develop in the muscles and bone. At the beginning of the disease, the tumor does not cause any disorders, and only its rapid growth indicates a malignant character. If the tumor develops near the skin, recognition is not difficult. Bone tumors develop from the body of the scapula, from the processes, and the angle of the scapula. More often, tumors are located in the fossa infra- and supraspinata. Sometimes tumors grow from the anterior surface of the scapula, penetrate the muscles, and are then difficult to determine. Left to themselves, tumors rapidly spread to neighboring tissues, mainly muscles, and along them to the shoulder, clavicle, and chest wall. Recognition of a large, rapidly growing tumor that changes the configuration of the scapula, and sometimes the shoulder, and impairs the function of the arm and blood circulation in the form of dilated veins in the affected area, does not present great difficulties. In the case of a deep position of the tumor, when it can give false fluctuation and proceed with great exhaustion and fever, recognition is not easy, as the tumor can be mistaken for an inflammatory disease. X-ray examination helps in clarification, which gives a picture of bone rarefaction.
Figure 13. Position of fistulas in osteomyelitis from the front. In osteomyelitis from the back. In tuberculosis. According to Hotz: in the presence of a cold abscess—punctures with irrigation of the cavity (formalin solution 1/2-1%) and injection of iodoform emulsion into the cavity after extracting the pus from there. In exceptionally rare cases that do not yield to conservative treatment, surgical intervention is indicated in the form of curettage of the foci with subsequent filling of the cavity with iodoform emulsion or resection of the affected part of the scapula. Syphilis of the scapula is observed rarely and proceeds in the tertiary form with the formation of a gumma in the form of a limited tumor with characteristic pain at night. A positive Wassermann reaction usually clarifies the diagnosis. Treatment is specific. Tumors of the scapula are observed in the form of benign and malignant. Among benign tumors in the region of the scapula, the most...
Figure 14. Osteomyelitis of the scapula. Removed scapula (from the Esipov specimen).
or defect at the site of the lesion with fancifully uneven edges and sometimes with bony shadows inside the defect in the absence of a reaction from the periosteum. Treatment is exclusively operative. When the tumor is located in the soft tissues, the tumor is excised within healthy tissue. Bone tumors are removed together with the scapula. In inoperable tumors, when there are metastases, involvement of the axillary glands, or spread to the chest wall, an attempt can be made to treat with X-rays, which often yields no result. After the operative removal of tumors, X-ray therapy is also recommended. The results of operative treatment, according to Doll, are as follows: in 32 cases of complete removal of the scapula—8 deaths, 12 recurrences, 12 recoveries; according to Schultz, after 1875, mortality was 7.14%, from recurrences 17.80%, and 64.29% recoveries, of which 10.71% were prolonged. With the development of technique and the use of local anesthesia, the mortality rate falls. When the tumor spreads to the shoulder girdle, removal of the scapula with the shoulder girdle—inferscapulo-thoracica (see)—is indicated. Kawamura collected 315 cases of removal of the entire girdle from 52 partial resections and 127 total removals of the scapula. Operations on the scapula. Stopping bleeding from the branches of the subscapular space in wounds, suppurations, and from disintegrating tumors presents great difficulties, since the vascular branches are located deep among the muscles and there are abundant anastomoses between all the vessels of the scapula (see above). In some cases of bleeding, in wounds, etc., it is recommended to stop bleeding from the subscapular space by ligating the a. subscapularis from the axillary fossa, where it is most accessible when it separates from the a. axillaris. For tumors of various parts of the scapula that do not invade the surrounding soft tissues, old osteomyelitic processes, tuberculous foci that do not respond to therapeutic treatment, partial resection is indicated. When the acromion process and the spine of the scapula are affected, the bone is exposed from an incision along the spine of the scapula outward and is excised subperiosteally in osteomyelitis and with the periosteum in tumors within healthy tissues. When the lesion is in the region of the angle of the scapula, an angular incision with its convexity downward is used for resection of the affected part. Resection of the articular part of the scapula is more difficult. One can use an Esmarch incision from the acromion along the lower edge 10 cm behind. The deltoid muscle is divided or spread and the articular capsule is exposed, which is vertically opened between the mm. supra-spinatus and infraspinatus. The periosteum of the scapular neck is separated together with the articular sac and the attachment of the tendon of the biceps muscle. Then the scapular neck is severed or sawed off, and the articular cavity is removed. When the scapula is affected over a large area except for the articular cavity, the entire scapula can be resected, leaving only the articular cavity, i.e., along its neck. Complete resection of the scapula is performed for the following indications: 1) tumors that invade over a large extent not only the bone but also the soft tissues, but without spread to the chest wall and the arm, 2) extensive tuberculous and osteomyelitic processes. In inflammatory diseases, however, it is recommended to leave the unaffected parts, especially the articular cavity and the places of muscle attachment (acromion, coracoid process). The incision is made from the acromion backward through the spine of the scapula with an arcuate continuation to the lower angle of the scapula. The acromion and coracoid process are separated and the flap is thrown outward. The posterior part of the m. deltoi-dei is divided and the capsule is exposed. The attachments of the muscles to the humeral head are detached: supra-, infraspinatus, teres minor from the tuberculum majus; subscapularis, latissimus dorsi, teres major from the tuberculum minus. When dividing the m. teres minor, care must be taken not to damage the p. axillaris. Here the a. circumflexa scapulae is ligated. The m. trapezius is separated or divided from the spine of the scapula and the a. thoraco-acromialis is ligated. When the scapula is pulled down, the m. omo-hyoideus and levator scapulae are divided at the upper angle of the scapula. Finally, the attachments of the mm. serrati, rhomboidei are divided, the articular capsule is cut around the neck, and the scapula is removed. If the lesion does not involve the muscles attached to the humerus, it is recommended to divide them as close as possible to the scapula. After removal of the scapula, the remaining muscles of the arm and the capsule are sutured to the chest wall. The incision of the skin and soft tissues may vary depending on the lesion. Technically, complete removal of the scapula does not present great difficulties, but it still gives a significant mortality rate and does not always prevent recurrence. According to Buchanan, in 72 cases of complete resection, mortality was 15.3%, and in 92 cases of partial resection, 18%. Complete removal of the scapula is of interest from the point of view of restoring functional capacity. Observations by most authors show that with complete or partial subperiosteal removal of the scapula, complete restoration of the functions of all corresponding muscles occurs. With removal of the scapula with muscle attachment in tumors, the function of the arm is significantly impaired, but with time it is partially restored.
Related articles
Mentioned in
- Achondroplasia
- Angle
- Arm (Humerus)
- Asthenia
- Axillary Fossa
- Bamberger's Sign
- Bedsores
- Bekhterev's Reflexes and Symptoms
- Biceps
- Bronchophony
- Clavicle
- Deltoid Muscle
- Duchenne-Erb Paralysis
- Dysostosis
- Erast Gavrilovich Salishchev
- Fractures
- Hirsutism (hypertrichosis, hypertrichia, polytrichia,)
- Horseback Riding
- Incisura
- Interscapulothoracic Amputation
Cite this page
“Scapula.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/scapula/