Clavicle
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
The clavicle is a paired bone of the shoulder girdle that articulates with the sternum and scapula in humans. This article covers its embryological development, anatomical structure, and functional significance in the shoulder complex.
Encyclopedia article (1928–1936)
CLAVICLE (clavicula), a paired bone of the shoulder girdle, articulating with the sternum and scapula in humans. Phylogenetically, the clavicle represents a dermal bone, first appearing in bony fishes in the dermal (connective tissue) part of the skin. Only at the next stage of vertebrate development, in amphibians, does the clavicle lie deeper and cover parts of the skeleton forming the primary shoulder girdle on a cartilaginous basis. In lower mammals (monotremes), the primary shoulder girdle consists of the scapula and a powerful beak-shaped (coracoid) bone extending to the sternum (Figure 1). Subsequently, the coracoid bone gradually reduces and transforms into the coracoid process of the scapula. Only the clavicle remains as the connecting link between the scapula and sternum. The episternum—another, also dermal, i.e., not preformed by cartilage bone, which secondarily enters into the composition of the shoulder girdle similar to the clavicle—initially has a T-shape. In humans, the intra-articular disc of the sternoclavicular joint is a remnant of the horizontal branch, while the suprasternal bones, which are far from constantly found at the upper edge of the sternum, represent remnants of the vertical part of the episternum (Fig. 2). In ungulates and carnivorous animals, the clavicle is underdeveloped or absent, as for example in cattle, horses, dogs. The primary ossification center of the clavicle appears in the human embryo already at the end of the 1st week, consequently at a time when bone tissue is not yet present anywhere else. The middle part of the clavicle forms metaplastically from connective tissue; the terminal sections have a cartilaginous basis (Kulchitsky). A secondary epiphyseal-type ossification center appears on the sternal end of the clavicle approximately at the twentieth year of life and soon (after 10-15 months) fuses with the main mass of the clavicle (Testut).
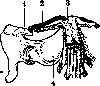
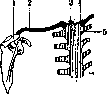
Figure 1.
Figure 1. Coracoid (4); 1-acromion; 2-clavicle; 3-episternum. Figure 2. Suprasternal bone (3); 1- acromion; 2-clavicle; 4-intra-articular disc; 5-manubrium of sternum.
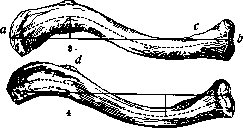

The clavicle (Figs. 3, 4) has the shape of an elongated S, averaging 12-15 cm in length in an adult. The medial convexity faces forward and occupies 2/3 of the length. The lateral third is concave in front and ends in a flattened from top to bottom acromial plate of spongy structure. The middle part of the clavicle is cylindrically narrowed, resembles a tubular bone, and has a bone marrow canal. The sternal spongy end is thickened into a triangular prism with blunted edges and a roughness (tuberositas costalis) on the lower side for the attachment of the costoclavicular ligament. An even greater tuberosity (tuberositas coracoidea) is located on the lower side of the acromial end. It is caused by the attachment of the coracoclavicular ligament, consisting of 2 parts: the trapezoid ligament lying in front and extending in the sagittal direction, and the conoid ligament located behind, in the frontal plane. Both ligaments suspend the entire weight of the upper limb and scapula on the clavicle. Thus, the acromioclavicular joint remains unloaded, and the freedom of its dynamic function is ensured. The mobility in this last joint is considerable due to the thickness of the fibrocartilaginous layer between the bone ends and the weak tension of the strong capsule (Figs. 5 and 6). The layer often forms a more or less isolated disc. On the sternal end of the clavicle, the intra-articular disc is constantly present, has a very irregular shape, is obliquely positioned, with its upper edge closer to the midline of the body, and divides the joint into two chambers. It represents, as mentioned above, a rudimentary bone. The sternoclavicular joint allows active excursions of the acromial end of the clavicle within the dimensions of an oval 10 cm high and 12 cm long (Fig. 7). The remarkable mobility, elasticity, and strength of the joint are due to the powerful development of its ligamentous apparatus.
Fig. 6. fii cartilage tissue. In the posterior-superior part of the joint—cartilage covering of the clavicular end, the transverse diameter of the articular disc and the lining of the sternal fossa taken together form an elastic buffer system up to 13 mm thick. With the first rib, the clavicle is connected by a two-layered, rhomboid costoclavicular ligament. Between the two layers of this ligament, a well-developed serous cavity is sometimes found. In front and behind, the sternoclavicular joint is reinforced by accessory capsular ligaments. Across the jugular notch, the interclavicular ligament is tightly stretched, which, along with the sternoclavicular ligaments, holds the clavicle and the entire shoulder girdle with the upper limb suspended from it in a horizontal position even when all muscles are cut. The ligaments allow excursions of the lateral end of the clavicle only forward and upward (Figs. 5, 7). In rare cases, the lower surface of the clavicle and the apophysis of the coracoid process are articulatively ^rs^m

Fig. 5.
On the surface, there is a longitudinal groove for the short (10 cm) subclavius muscle. Located here is also a small opening for the nutrient artery of the bone, which heads toward the lateral half of the clavicle. On the acromial end of the clavicle, the deltoid muscle attaches at the top front, and the trapezius muscle at the top back. For active movements of the upper limb, the function of both clavicular joints, the sternal and the scapular, is of very great importance. Without the participation of these joints, the shoulder, regardless of the choice of initial position, cannot be raised above the horizontal plane either anteriorly or laterally. To the action of the deltoid muscle on the shoulder, there must be added the rotation of the lower angle and the displacement of the entire scapula forward and upward in order to obtain elevation. The most important role here is played by the serratus anterior, trapezius, and levator scapulae muscles with their antagonists (rhomboidei, pectoralis major and minor). Active retroversion of the shoulder does not occur in the shoulder joint at all, but only in the clavicular-acromial articulation, mainly thanks to the latissimus dorsi muscle. Mechanically playing the role of a hanger for the shoulder and a strut between it and the rib cage, the clavicle simultaneously with increasing the load-bearing capacity of the shoulder girdle regulates the dynamics of the free upper limb. Functionally belonging to the latter, the clavicle in an anatomo-topographical respect represents the boundary between the cervical region and the trunk. Corresponding to the middle third of the clavicle, between the attachment of the deltoid and pectoralis major muscles, behind the clavicle and anterior to the first rib, lies the subclavian artery with the vein of the same name and the brachial nerve plexus. For conduction anesthesia according to Kulenkampff, the needle is inserted in the direction of the II-III thoracic spinous process in a sitting patient, slightly laterally from the site of arterial pulsation at the upper edge of the clavicle, and is advanced deep until clear paresthesia is obtained in the fingers. To avoid damage to the dome of the pleura, it is recommended (Mulley) that the injection site be three finger-breadths above the middle third of the clavicle. In fractures of the clavicle, the muscle belly of the subclavius and its strong fascia protect the vessels and nerves from injury by bone fragments. By pulling the shoulder backward and downward, the neurovascular bundle can be compressed between the clavicle and the first rib. This maneuver achieves preliminary arrest of arterial bleeding. Thus, sometimes due to oversight, when the upper limb hangs over the edge of the operating table, paralyses occur under anesthesia. A wide approach for the surgical treatment of traumatic aneurysms and nerve injuries in this area, especially in gunshot wounds, is obtained only by temporary resection of the clavicle. The small supraclavicular fossa (Zarig's) between the sternal and clavicular heads of the sternocleidomastoid muscle rarely serves as a site for locating and ligating the common carotid artery, more often for auscultation of the jugular vein.

The superficial location of the clavicle and its support-dynamic connection with the upper limb contribute to its injuries. Injuries from direct violence are encountered less frequently than indirect traumas from falling on the shoulder or on an outstretched hand and from excessive muscle tension when lifting weights. Fractures of the clavicle are observed not infrequently even in newborn children (according to Muns, in 1.3% of cases), and not only in connection with difficult artificial delivery but also after normal births, originating even in the intrauterine life of the fetus. In childhood, besides the frequency in general, one is struck by the insignificance and short duration of the disorders, and the large number of subperiosteal and incomplete fractures. Among adults, thanks to the peculiarities of daily life and occupational traumatism, fractures of the clavicle are encountered in men significantly more often than in women. This fracture is a typical injury of cavalrymen, and the mechanism of its origin is uniform: when falling from a horse onto the side, the clavicle is compressed in the direction of its longitudinal axis and breaks from bending at the weakest point, at the border of the middle and outer third.
According to Rachman, among men, the 'sternal' type of clavicle predominates with a large index of medial curvature, while the female sex is more characterized by transitional forms or 'acromial' ones (Figs. 3 and 4). Despite the predisposition of the sternal type to fractures in the medial half, in men, disruptions of integrity occur, just as in women, usually closer to the acromial third of the clavicle, because the sternal part is stronger thanks to the arrangement of trabeculae parallel to the long axis of the bone. The typical displacement (Fig. 8) of the medial fragment with the broken end upward depends on the pull of the sternocleidomastoid muscle, and the displacement of the lateral fragment downward and toward the sternum is caused by the action of the weight of the limb suspended on the coracoclavicular ligament and the contraction of the pectoralis major and minor muscles. Fractures of the acromial third most often occur from a direct blow from above or a push from the front. Least of all are encountered fractures of the sternal third, and in the mechanism of their origin, a role is played by the disproportion of rapid contractions of the sternocleidomastoid, deltoid, and pectoral muscles, e.g., throwing and a sweeping blow into the air or excessive leverage of the clavicle resting on the first rib. Recognition of clavicle fractures does not present difficulties if, in the absence of displacement of fragments, one is guided by locally limited sharp pain upon palpation.

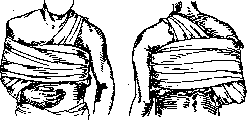
For the treatment of clavicle fractures, about 100 bandages have been proposed, if one counts the authors. The most rational are: 1. The old figure-eight bandage of Petit, bringing both scapulae toward each other. Its action is strengthened (according to Burian) by rubber traction downward at the point of intersection on the back. Or the same bandage is applied using plaster bandages with good modeling of the contours of the shoulder girdle (Fig. 9); for children, the vest bandage of Pirogov follows the same principle. Also belonging here are the stick bandage of Wildbolz (Fig. 10) and the S-shaped splint of Hartel. 2. Plaster bandages that raise and abduct the upper end of the shoulder, leaving the fracture site free (Fig. 11) and resting on the iliac crests (Fig. 12) or capturing the rib cage together with the healthy shoulder girdle. 3. The Desault bandage, applied over a shirt with starch bandages,
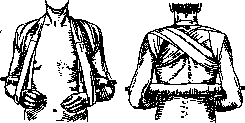
or the Sayre bandage with adhesive plaster strips.
4. The method of Couteaud, i.e., the horizontal position of the patient with the shoulder hanging down over the edge of the bed for self-reduction, with the patient remaining in this position until the formation of the initial callus and with the subsequent application of a bandage.

5. Open reduction and surgical fixation of fragments in cases that do not yield to conservative treatment or are complicated, like gunshot fractures, by injury to vessels or nerves. According to Austrian insurance literature, the duration of treatment is on average 10 1/2 weeks, with full restoration of working capacity in only 52% of cases. A significant role in the remaining functional disorders is played by adduction contracture of the shoulder joint due to
prolonged fixation and improper treatment. Traumatic pseudarthroses are encountered very rarely and restrict movement so little that Kappis proposed improving function in cases of shoulder ankylosis by creating an artificial false joint within the clavicle. Dislocations are encountered not only of one end, more often the sternal one, but also of both ends of one clavicle (Beckmann) and simultaneously of both clavicles (Riedinger). Congenital anomalies of the clavicle belong to rare but typical systemic malformations of the skeleton. Clinically, they manifest in a partial or complete defect of the clavicle (see Dysostosis, Figure 2), combined with anomalies of skull development.
Fig 12 shows a case of hereditary cleido-cranial dysostosis. The genotypic nature of the anomaly is evident from its inheritance according to Mendel's laws: in most cases, it follows a dominant type (in the Carpenter-Langmead case, over four generations); sometimes, it appears to have a recessive mode of inheritance. Parallel to these biological differences between individual cases are clinical differences. For example, there are families in which only a defect of the clavicle is observed, while in others, anomalies of the skull are present. There can be little doubt that under the name hereditary cleido-cranial dysostosis, anomalies are described that differ both biologically and clinically. The opposite anomaly to the hypoplastic cleido-cranial dysostosis was described by Dzerzhinsky under the name familiaris periostal hyperplastic dystrophy. Tower-like (oxycephalic) deformation of the head with a prognathic bird-like facial profile, resulting from premature fusion of the cranial sutures, is combined with thickening of the clavicle and increased curvature of it. Hyperplastic narrowing of the basal foramina, which serve for the passage of blood and lymphatic vessels, leads to increased intracranial pressure and secondarily to atrophy of the optic nerves. Among other anomalies, Bennett described a congenital bifurcation of the clavicle at its acromial end, where one branch articulated normally, while the other was directed backward from the coracoid process and formed a joint with the spine of the scapula. Among acquired diseases of the clavicle, acute and chronic inflammatory processes attract attention early due to the superficial location of the bone. The differential diagnosis of tuberculous and syphilitic lesions, following the general rule, is based on the patient's history, the nature of accompanying symptoms, and serological and other reactions. Arthritides of various (traumatic, infectious, and toxic) etiology are observed predominantly in the sternoclavicular joint and early cause significant pain on movement. Friedrich, in one operated case, found dystrophic changes similar to those in Perthes' disease and Köhler's disease. Among neoplasms with primary localization in the clavicle, sarcomas are most frequently encountered. The prognosis is unfavorable if surgery is not performed early and radically. In relation to tuberculosis and chronic osteomyelitis of the clavicle, total resections should also be more widely applied. Even after complete excision of the clavicle along with the periosteum, the function of the upper limb and the stability of the shoulder girdle are little affected.
Related articles
Mentioned in
Cite this page
“Clavicle.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/clavicle/