Jugular Veins
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the first edition of the Great Medical Encyclopedia (1928–1936) provides a detailed anatomical description of the jugular veins, their embryonic development, and their role in draining venous blood from the head and neck. It covers the classification, topography, and variations of the external, internal, anterior, and posterior jugular veins.
Encyclopedia article (1928–1936)
JUGULARES VENAE, jugular veins (Latin jugulum, diminutive of jugum—yoke, the hollow above the clavicle), vascular conduits that drain venous blood from the tissues of the head and neck through the anonymous and superior vena cava to the heart. As a result of embryonic evolution—from the sole outflow pathways, the anterior cardinal veins (vv. cardinales anteriores, s. jugulares primitivae), to two systems—the external and the newly emerged internal (Figure 1)—in the fully formed state in humans, the primary jugular veins are the external and internal, anterior and posterior (vv. jugulares externae, jugulares internae, anteriores et posteriores). The vv. jugulares externae, together with the anterior and posterior ones, serve the posterolateral region of the skull and the superficial layer of the middle, lateral, and posterior sections of the neck, i.e., the layer which, together with the skin, lies
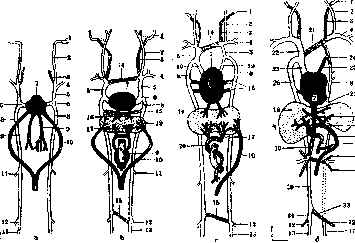
Figure 1. Diagram of embryonic development of venous circulation (a, b, c, d): 1-sin. later.; 2 and 3-v. jugul. ext. et int.; 4-v. subclavia; 5-v. jugul. primitiva, s. cardin. ant.; 6-d. Cuvieri; 7-atrium; 8-vv. cardin. post.; 9-vv. omphalo-mesent.; 10-v. umbilic.; 11-v. renalis; 12 and 13-v. iliaca ext. et int.; 14-v. jugul. transversa; 15-transverse anastomosis; 16 and 17-vv. hepat.; 18-liver; 19-vv. cavae sup.; 20-v. portae; 21-v. anonyma sin., former v. jugul. transv.; 22-v. anonyma dex.; 23-v. cava sup.; 24-v. intercost. suprema sin.; 25-v. obliqua (Marshalli); 26-v. cardin. post. dex. (v. azygos); 27-v. hemiazygos; 28-ductus venosus; 29-ram. sin. v. portae; 30-v. cava inf.; 31-v. suprarenal.; 32-v. spermat.; 33 and 34-v. iliaca comm. sin. et dex. (According to Young and Robinson.)
outward from the first cervical fascia (Bobrov), which includes in its thickness the mm. st.-cl.-mastoideus and trapez. (fascia superficialis of some authors). The internal jugular veins receive blood primarily from the contents of the cranial cavity, the orbits, the posterior part of the nose, the pharynx, and all the deep tissues of the neck lying inward from the aforementioned fascia and the fascia praevertebralis, i.e., in the visceral canal of the neck. Venous blood from the tissues of the anterior facial part of the skull, collected by the facial veins, as well as by other components of the v. facialis communis, can drain into either the external or the internal jugular vein, but most often it drains into both simultaneously (Figure 2). - The external v. jugularis is a continuation of the venous branches located in front of and behind the auricle (vv. auriculares, sometimes also the v. temporalis superficialis), and the veins corresponding to the art. occipitalis. Often, through the venous plexus behind the ear, the emissarium mastoideum drains into the tributaries of the external jugular vein, thereby establishing a collateral outflow from the cranial transverse sinus into the cervical veins. The main trunk of the external jugular vein (Figure 3) is located on the outer surface of the sternocleidomastoid muscle, which it crosses obliquely. In the lower part of the muscle, at its outer edge, just below the m. omo-hyoidei, the vein goes into the depth, piercing the fascia superficialis and fascia media, and drains mostly into the subclavian vein, less often into the internal jugular vein. At the site of the fascia perforation, the vein is firmly fused with the fascia at the edge of the opening, which prevents the possibility of its collapse. The caliber of the v. jug. ext. fluctuates and is inversely proportional to the width of the lumen of the v. jug. internae; it depends on the number and capacity of the branches flowing into the v. jug. ext., and primarily on its relationship with the v. facialis communis. In the presence of large tributaries, the v. jug. ext. can reach a significant width and pose a danger of air embolism during injury. Throughout its length, it has 1-3 bicuspid valves. The lower one—above the site of the vein's entry—is more constant, as is the upper one—in its middle part; less common, in addition to these, is a valve located in the space between the first two. The main branches of the external jugular vein: v. jugularis posterior, v. transversa colli, and v. transversa scapulae (the latter two branches are inconstant), v. facialis communis (inconstant), v. facialis posterior, and v. jugularis anterior. Anteriorly, the external jugular vein is covered for most of its length by the m. platysma myoides. At the inner edge of the m. st.-cl.-mastoidei, it is adjoined by the parotid gland, the branches of the n. cutaneus colli sup., the n. facialis emerging from under the latter, and a group of superficial cervical lymph nodes (Fig. 4). Outward from the vein, in very close proximity to it, the n. auricularis magnus may be located. In the middle of the vein's length, 1-1.5 cm above its crossing of the sternocleidomastoid muscle, the branches of the nervi supraclaviculares emerge from under the edge of the latter, some of which cross the trunk of the vein lower down. The lower part of the external jugular vein is covered in front by the first cervical fascia, and the musculus omo-hyoideus lies behind

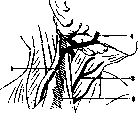
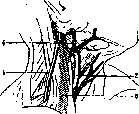
c Figure 2. Types of relationships of the external and internal jugular veins to the v. facial. comm.: 1-v. jugul. ext.; 2-v. jugul. ant.; 3-v. jugul. int.; 4-v. facial. comm.; a-v. facial., drains into v. jugul. int.; b-v. facial., drains into v. jugul. ext.; c (transitional type)-v. facial., consists of an anastomosis between v. jugul. ext. and v. jugul. ant. (Own observation.)
vein; the fascia media is pierced by it immediately before draining into the subclavian or deep jugular vein (Fig. 5). - Variations of the v. jugul. externae come down to changes in its diameter in connection with the state and place of entry of its branches. It may be completely absent on one or both sides; on the other hand, conversely, by receiving a larger or smaller part of the tributaries of the internal jugular vein, it can reach a very large thickness; sometimes veins with a double trunk are encountered. Rare cases have been described (Quain, Gruber) of it draining into the internal jugular vein in the middle of its length or into the subclavian vein below the clavicle in the subclavian fossa, with the position of the vein trunk in front of the clavicle. Cases of unusual branches draining into it are possible, such as the v. lingualis, thoracica accessoria, which loops in front over the clavicle at the outer edge of the m. st.-cl.-mastoidei, the v. cephalica brachii, or one of the veins accompanying the subclavian artery. The v. jugularis posterior (synonym v. subcutanea colli post.)—superficially located veins behind the m. st.-cl.-mast., in the region of the trigoni omo-trapezoides, in the form of a main or scattered system (Figs. 6 and 7). By one or several veins emerging from under the edge of the m. trapezii, the posterior jugular vein communicates with the plexus of vertebral veins. - V. jugulares ante-

Figure 3. Branching of the v. jugul. ext.: 1-v. jugul. ext.; 2-v. auric. post.; 3-v. tempor.; 4-v. occipit.; 5-v. jugul. post.; 6-v. transv. scapulae; 7-anastomosis of v. cephalicae (variation); 8-v. cephalica; 9-n. auricul.; 10-n. occipit. min.; 11-n. cutan. colli; 12-ram. cutan. n. facial.; 13-n. supraclavicularis. (According to Johnston.)
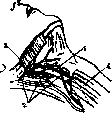
Figure 4. 1-vena jugularis ext.; 2-lgl. cervical. superfic.; 3-ram. cutan. n. facialis; 4-platysma myoides. (Own observation.)
r i o r e s (syn. vv. subcutan. ant., superficial. ant., v. mediana colli Brechet)—subcutaneous veins of the middle section of the neck, above
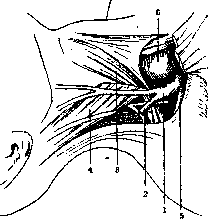
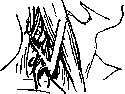
Figure 5. Position of the v. jugul. ext.: 1-v. jugul. ext.; 2-v. jugul. post.; 3-m. omo-hyoideus; 4-m. sterno-cleido-mastoid.; 5-v. transversa scapulae; 6-v. jugul. int. (Own observation.) anastomose with the submental or directly with the facial veins, below they connect behind or (which is rarer) in front of the heads of the m. sterno-cleido-mastoidei with the v. jugularis externa (Fig. 8), draining additionally on one or both sides into the v. subclavia or anonyma. From the network of anterior jugular veins, a transverse arcus venosus juguli can stand out in the lower section, into which vertical branches of the vein drain, one or two on each side (Figure 9). Given the development of transverse anastomoses between them, the latter fall under the knife during a midline incision and can bleed profusely in cases of sharply pronounced venous congestion (tracheotomy). Anastomoses with the external jugular and subclavian veins can create a complex venous network in the lower section of the m. st.-cl.-mast., encircling the named muscle (Figure 7). Figure 6. v. jugul. post. of the main type. (Own observation.) Figure 7. V. jugul. ext. is absent. Functionally, it is replaced by a strongly developed v. jug. ant.: 1-v. jug. ant.; (Own observation.)
2-v. fac. ant.; 3-v. jug. posterior (of the scattered type of v. jug. structure). (Own observation.) The internal jugular vein (Figure 10) is the direct continuation of the transverse venous sinus (sinus venosus transversus) and, as the main collector, drains venous blood from the cranium, while at the same time being subject to pathological processes, in particular infections developing in the sinus and spreading from the cranium via the canalicular route (thrombophlebitis in purulent mastoiditis, etc.). Along its course, the vein receives venous tributaries from the middle and inner ear, from the pharyngeal plexus, the lingual veins, the superior thyroid veins, and thus serves all the visceral organs of the neck. In the case of the common facial vein draining into it, or its separate branches, the blood from the facial part of the cranium also flows into its channel for the most part.
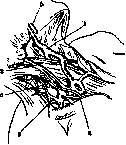
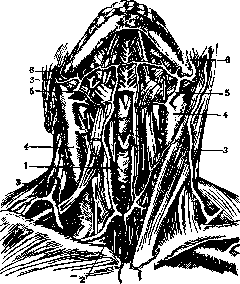
Figure 8. Strongly developed system: v. jug. ant. receives v. fac. It gives abundant anastomoses with v. jug. ext. (doubled), forming a powerful network of vessels with windows on the anterior surface of the m. sterno-cleido-mastoideus: 1-v. jug. ant.; 2-v. jug. ext.; 3-v. jug. post.; 4-n. supraclavic.; 5-a. maxill. ext.; 6-superficial lymph nodes. (Own observation.)

Figure 9. V. jugularis with anastomoses: 1-v. jugul. ant.; 2-arcus venos. juguli; 3-v. jugul. ext.; 4-v. jugul. int.; 5-v. fac. comm.; 6-v. facial. ant. Its trunk has 2 thickenings (superior and inferior bulb of the internal jugular vein). The upper one is located immediately after the vein exits the cranial foramen and fills the depression of the jugular fossa of the temporal bone; the lower one is 20-25 mm above the junction of the internal jugular vein with the subclavian vein (venous angle). The lower bulb is equipped with 1-3 valves (inconstant). In the case of three valves, two are located at its upper edge, one at the lower. A single valve is located in the lower part of the thickening, in the region
of the junction of the subclavian and jugular veins. On the left side, both the bulb (i.e., sinus of the jugular vein of Cruveilhier) and the valves are usually less developed than on the right, and may be completely absent (according to Gruber 1:10). The lower
Figure 10. Junction of v. jug. ext. with v. subclavia: 1-v. jug. ext.; 2-v. jug. int.; 3-v. jug. anterior; 4-deep cervical lymph nodes; 5-m. omo-hyoideus and the associated middle fascia (a window is cut out of the latter below to see the junction of the veins); 6-glandular tissue with deep cervical, resp. supraclavicular nodes; 7-clavicle and severed m. sterno-cleido-mastoideus. (Own observation.) part of the vein, starting from the place where the common facial vein or the external jugular vein enters, is given the name common jugular vein by some authors (Krause, Zernov, and others), but in view of the inconstancy of these tributaries, most authors consider this superfluous.
The trunk of the internal jugular vein is covered anteriorly by the m. sterno-cleido-mastoideus (Vol. X, art. 736, Fig. 1) and is located in the layer of loose connective tissue of the neurovascular bundle under the middle fascia (the second aponeurosis of some authors), which encloses in its splitting the m. omo-hyoideus and the m. sterno-hyo-thyreoidei. In the composition of the neurovascular bundle, the internal jugular vein occupies a posterior-lateral position; being located behind the carotid artery upon exiting the cranium, it gradually shifts anteriorly and in the lower half encompasses it from the outer side.
Besides the carotid artery, the following structures lie adjacent to the trunk of the internal jugular vein from top to bottom: posteriorly - the musculature covered by the prevertebral fascia, connected to the transverse processes of the cervical vertebrae, namely: m. longus capitis, m. scalenus (ant. and others); in addition, the accessory nerve, the roots of the cervical nerve plexus, the sympathetic nerve (Figure 11), medially - the vagus nerve and the hypoglossal nerve.
Figure 11. V. jug. int. with vertebral, and on the left with the thoracic duct: 1-v. jugul. int.; 2-v. jugul. ant.; 3-m. omo-hyoid.; 4-m. scalen. ant. and phrenic n.; 5-n. vagus; 6-sup. thyroid v.; 7-descending branch of the hypoglossal n.; 8-m. digastricus; 9-m. st.-cl.-mast.; 10-submaxillary gland; 11-severed m. st.-cl.-mast.; 12-carotid art.; 13-brachial plexus; 14-accessory n.; 15-laryngeal n. (Own observation.)
Anteriorly and laterally - the posterior belly of the m. digastricus, the m. sterno-cleido-mastoideus, the ansa of the hypoglossal nerve, the m. omo-hyoideus (crossing it). Furthermore, along the entire length of the vein, on all sides in the loose connective tissue enveloping it, are located the lymph nodes of the deep cervical lymphatic drainage (deep cervical lymph nodes), the lymphatic vessels connecting them, and the terminal lymphatic collectors (jugular lymphatic trunk), which drain into the venous angle or into the right lymphatic duct on the right and the thoracic duct on the left (Figure 12). Variations of the internal jugular vein primarily consist of asymmetry in the construction of the entire venous system: the internal jugular vein can on one side be the predominant collector, and on the other, being deprived of tributaries to a greater or lesser extent, yield physiological primacy to the external jugular vein and even the anterior jugular veins. In addition, the caliber of the vein is subject to variations depending on the ratio in the distribution of tributaries between the external and internal systems, uniformly on both sides. Repeating embryological and comparative anatomical stages and forms, the trunk of the internal jugular vein
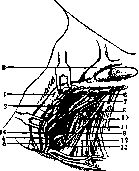
Figure 12. Syntopy of the internal jugular vein corresponding to its posterior surface: 1-internal jugular vein (pulled medially); 2-deep cervical lymph nodes adjacent to it posteriorly; 3-common facial vein; 4-jugular lymphatic trunk; 5-thoracic duct; 6-sympathetic nerve (thyroid ganglion); 7-m. longus colli; 8-ascending cervical artery; 9-inferior thyroid artery; 10-m. scalenus ant.; 11-phrenic nerve; 12-brachial plexus; 13-lymph node from the supraclavicular group; 14-vertebral vein. (Own observation.) can in this case be represented as an insignificant, secondary vessel. Finally, in the third group of variations, one can combine cases of unusual tributaries (vertebral veins, supreme intercostal vein, middle thyroid vein, etc.) or deviations from the average type regarding the place of entry of commonly encountered branches, such as, for example, the early junction of the external jugular vein, etc.
Related articles
Mentioned in
Cite this page
“Jugular Veins.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/jugular-veins/