Genitourinary Organs
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928-1936 Great Medical Encyclopedia explores the comparative anatomy, embryology, and evolutionary development of the excretory and reproductive systems in vertebrates and invertebrates.
Encyclopedia article (1928–1936)
GENITOURINARY ORGANS, excretory organs that are fairly closely linked in most vertebrates with the reproductive organs into a single genitourinary, or urogenital system. In invertebrate animals, such a connection is usually absent—their urinary organs are represented by excretory tubes (nephridia of worms, Malpighian tubules of insects, etc.), and the reproductive organs by gonads, their ducts, and sometimes copulatory organs. Excretory organs serve to remove end products of metabolism dissolved in water—salts and nitrogenous compounds—from the organism. Among the variously constructed excretory organs of invertebrates, the nephridia of worms deserve special attention. In lower, acoelomate worms, as well as in the larvae of higher worms, they are built on the type of "protonephridia," consisting of a system of more or less branched tubes, the terminal branches of which end in special excretory, so-called flame cells, equipped with an intracellular channel containing a ciliary flame. Through the activity of this flame, the fluid secreted by the cells is propelled through the nephridial channel to the excretory opening. In higher worms, the larval protonephridia are replaced by "metanephridia"—segmentally arranged paired tubules opening by a ciliated funnel into the body cavity and leading directly to excretory pores on the lateral surface of the body. Such excretory organs are typically developed in earthworms and leeches. In vertebrates, the excretory organs are built on the metanephridial type and consist of a consecutive series of excretory tubules opening initially by a ciliated funnel into the body cavity and connected with a common duct. In the embryonic development of higher vertebrates, there is a successive replacement of three different excretory organs, which bear the names of the pronephros, or head kidney, the mesonephros, or primary (trunk) kidney, and the metanephros, or permanent (pelvic) kidney. This replacement corresponds to the phylogenetic succession of excretory organs in the vertebrate series. In myxinoids, the head kidney is still sometimes a functioning organ of the adult animal; in other cyclostomes, in fishes, and in amphibians, the trunk kidney turns out to be the permanent excretory organ, while in reptiles, birds, and mammals it is the pelvic kidney. However, upon closer examination, this succession has the character of a gradual evolution of a single initial organ, in which the anterior part develops earlier and has the simplest structure (pronephros), while the main mass of the organ achieves greater complexity with a gradual increase in the number of tubules (trunk kidney). Finally, in higher vertebrates in the posterior part of the organ, development goes even further and leads to the complete isolation of a certain complex of the most complex tubules forming the permanent—pelvic kidney. The excretory tubules of vertebrates develop from the epithelium of the body cavity (Figure 1), into which they open with a wide ciliated funnel. Initially, like the metanephridia of worms, they have a regular metameric arrangement. The head
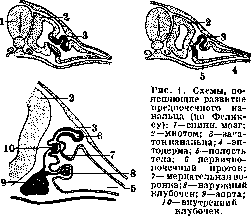
kidney is composed of a few, only anterior tubules, which connect at their ends to form a common duct opening into the cloaca. In addition to the excretory tubules, a special filtration apparatus develops, which is located either in the wall of the body cavity in immediate proximity to the funnels of the pronephros (external chamber with a vascular glomerulus) or in the wall of the tubule itself (internal chamber with a vascular glomerulus or Malpighian corpuscle). The formation of the Malpighian corpuscle is particularly characteristic of the trunk and pelvic kidneys. At the same time, the tubules of the trunk kidney initially also possess ciliated funnels. Later, however, the latter often become overgrown. With the development of the trunk kidney, the duct of the pronephros becomes the mesonephric duct. The tubules of the pelvic kidney are more complex in structure; they always begin exclusively with a Malpighian corpuscle, and funnels are never present in them. The tubules of the pelvic kidney develop, like the secondary tubules of the trunk kidney, from the mesodermal nephrogenic tissue, but not only are they devoid of funnels from the very beginning, they also connect not directly with the mesonephric duct, but with a special outgrowth of the latter—the ureter (ureter) (Fig. 2). The latter completely separates from the mesonephric duct and then opens directly into the cloaca or (in mammals) directly into the urinary bladder. The tubules of the pelvic kidney differentiate into a whole series of successive sections. Beginning with the Malpighian corpuscle, the tubules form an initial convoluted section, then an elongated two-limbed loop of Henle, and finally a connecting tubule flowing into the so-called straight collecting tubules of the kidney. The latter represent in their development the terminal branches of the ureter.
The permanent kidney of mammals is a relatively small, compact organ of a characteristic bean-like shape with a concave inner wall, into the depression of which (hilum) the ureter and blood vessels enter. They are located not in the pelvic, but in the lumbar region, usually one slightly anterior to the other. Already macroscopically on a section through the kidney, one can notice the division into an outer cortical and an inner, radially striated medullary substance. The cortical substance contains Malpighian corpuscles, convoluted and connecting tubules, and the medulla consists chiefly of straight collecting tubules, but loops of Henle also penetrate into it. Mammals are characterized by a fan-shaped arrangement of collecting tubules converging toward a common excretory opening on a papilla protruding into the interior of the expansion of the ureter, the so-called pelvis. Such a group of converging collecting tubules forms the so-called pyramid of the medullary substance. The number and arrangement of such pyramids can be very diverse (Fig. 3). In many small mammals, the medulla consists of a single pyramid ending in
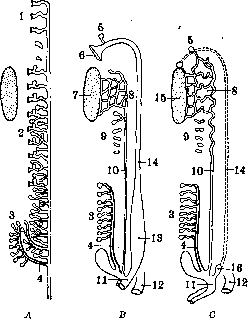
Fig. 2. Scheme of amniote renal tubules and their relation to the gonads: A—indifferent initial stage; B—female; C—male; 1—pronephros; 2—mesonephros; 3—metanephros; 4—ureter; 5—pedunculated hydatid; 6—oviduct funnel; 7—ovary; 8—epididymis and epoophoron; 9—paradidymis and paroophoron; 10—Wolffian duct; 11—urogenital sinus; 12—rectum; 13—uterus; 14—Müllerian duct; 15—testis; 16—uterus masculinus.
a single papilla. In others, the single papilla elongates into a long ridge bearing openings of excretory ducts along its entire length (carnivores, artiodactyls, monkeys). Side ridges may depart from the longitudinal ridge, and finally, such a complex papilla can break down into numerous independent papillas, as is also observed in the human kidney. A completely special type of kidney arises if each papilla, with the corresponding branch of the pelvis and ureter, with a pyramid and part of the cortical substance, becomes isolated and forms an independent lobe. Thus, a multilobed form
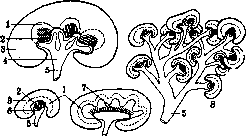
Figure 3. Schemes of the structure of various types of kidneys in mammals (after Gerhardt): 1—medulla; 2—papilla; 3—cortical substance; 4—branched renal pelvis; 5—ureter; 6—renal pelvis; 7—renal ridge; 8—multilobed kidney.
of the kidney arises, as observed in cattle, bears, and cetaceans (Fig. 3). Finally, in the horse and tapir, instead of a pelvis, a long passage develops, penetrating deeply forward and backward into the parenchyma of the kidney. The openings of the collecting tubules flow into this passage without the formation of any papillas. In all land vertebrates, a reservoir for urine—the urinary bladder—develops from the ventral wall of the cloaca, into which, however, only in mammals do the ureters empty directly. The sex glands (see), or gonads, develop completely independently of the kidneys in the walls of the body cavity. Initially, in invertebrates, they have their own special ducts. In higher worms, the reproductive products fall into the body cavity and are removed outward from there through the agency of special genital ducts. The latter, however, frequently fuse with the nephridial ducts. Thus, a connection of the reproductive system with the excretory system is already established here, a connection that is so characteristic of vertebrates. In vertebrate animals, reproductive products are excreted exclusively through the channels of the excretory system. The excretory duct of the primary kidney in the embryo of tailed amphibians splits lengthwise into channels which received the names of the Wolffian and Müllerian ducts (see Wolffian duct and Müllerian tract). The seminiferous tubules of the male gonad enter into connection with the mesonephric tubules (usually the anterior ones) through the agency of cords growing out from the latter, which form the efferent ductules (vasa efferentia). Se
Fig. 4. Scheme of the genitourinary apparatus of tailed amphibians: A—male; B—female; 1—testis; 2—vasa efferentia; 3—Müllerian duct; 4—reproductive part of the kidney; 5—Wolffian duct; 6—ovary; 7—excretory part of the kidney.
miniferous tubules of the male gonad enter into connection with the mesonephric tubules (usually the anterior ones) through the agency of cords growing out from the latter, which form the efferent ductules (vasa efferentia).

is conducted through these tubules into the Wolffian duct, which in lower vertebrates serves simultaneously as both the urinary duct and the vas deferens (Figures 2 and 4). With the development of the pelvic kidney in higher vertebrates, the primitive kidney loses its significance as an excretory organ and is partly reduced. Its anterior, sexual section forms, together with the highly convoluted part of the Wolffian duct, the epididymis, while the posterior, excretory section is sometimes preserved in the form of an insignificant vestige adjacent to the testis (paradidymis); in the female, both sections of the primitive kidney are reduced, and their remnants are sometimes preserved in the peritoneal fold between the ovary and the oviduct (epoophoron, paroophoron).
The mammalian sex glands proper are rather compact organs of oval or kidney-bean shape. The ovaries are located in the posterior part of the abdominal cavity, while the testes shift even further back and, in most mammals, drop out of the abdominal cavity into a special outgrowth of the latter, housed in a pouch formed by the body wall with its muscles—the scrotum (Figure 5). Both the ureters and the genital ducts empty
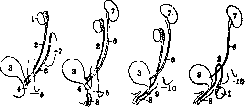
Figure 5. Schematic representation of the male urogenital apparatus of a turtle (A), a monotreme mammal (B), and viviparous mammals (C, D)—side view: 1—testis; 2—vas deferens; 3—urinary bladder; 4—urogenital sinus; 5—cloaca; 6—ureter; 7—kidney; 8—penis; 9—urethra; 10—anus. empty directly into the common cloaca (see) in reptiles and birds. In mammals, its anterior part, connected with the urinary bladder, separates from the cloaca as the urogenital sinus (sinus uro-genitalis), into which the genital ducts empty, and—in monotreme mammals—also the ureters, which in viviparous animals empty directly into the urinary bladder. In viviparous mammals, the cloaca disappears; the urogenital sinus opens independently to the exterior, forming in the female a small section, the so-called vestibule of the vagina, and elongating in the male into a long urethra. Mammals are also characterized by the process of fusion of the oviducts, leading to the formation of more or less significant unpaired sections. In all placental mammals, an unpaired vagina is thus formed. In most of them, however, the process of fusion goes further, encompassing the next expanded section of the oviducts—the uterus, which is "double" in many insectivores, rodents, and elephants, "bipartite" in other rodents, pigs, and some carnivores, "bicornuate" in most mammals, and finally "simple" in some chiropterans, monkeys, and humans, in whom only the initial sections of the oviducts, the so-called Fallopian tubes, retain their paired nature. Various kinds of accessory glands are associated with the urogenital excretory ducts. In male mammals, at the end of the vas deferens, there are large vesicular glands (gl. vesiculares), and in the walls of the urethra, glands develop that differentiate into the paired prostate gland (gl. prostaticae), which in primates fuses into a single unpaired one, and the paired Cowper's gland (gl. Cowperi) at the base of the copulatory organ. In females, corresponding Bartholin's glands are present in the vestibule of the vagina. The copulatory organs of vertebrates can have various origins. In terrestrial vertebrates, they develop in connection with the wall of the cloaca (see). In mammals, this is an unpaired organ (penis) developing in the anterior wall of the cloaca. Embryonically, its primordium arises from the anterior part of the genital tubercle and encloses a part of the urogenital sinus, which elongates along with the growth of the genital tubercle into a long channel. At the base of the genital tubercle, a paired fold develops, giving rise to the walls of the scrotum in the male, and the so-called labia majora in the female of monkeys and humans. In the female, the genital tubercle develops poorly and turns into the clitoris and labia minora. Genitourinary organs of man—see Individual organs.
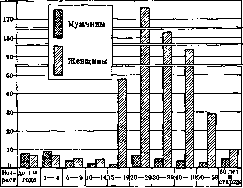
I. Schmalhausen. Statistics of diseases of the genitourinary organs. According to the international nomenclature upon which the statistics given below are built, the section of diseases of the genitourinary organs includes three groups: diseases of the urinary organs, diseases of the male genital organs, and diseases of the female genital organs. This section does not include venereal diseases, malignant neoplasms, and postpartum diseases, but does include benign neoplasms of the female genital organs. — Mortality. For every 10,000 population in European countries, from 2.0 to 4.5 people die annually from diseases of the genitourinary organs, with more men dying than women (Table 1). Table 1. Mortality from genitourinary diseases in European countries. England and Wales: 13,852 (3.5), nephritis 1,125 (0.3); Belgium: 1,232 (1.6), 0.6; Germany: 8,564 (1.4); Denmark: 2.1, 0.1; Italy: 17,410 (4.3); Netherlands: 2,677 (3.5), 0.2; Norway: 2.8; France: 16,282 (4.0), 1,360 (0.3); Switzerland: 1,052 (2.6), 0.7; Sweden: 1,384 (2.3), 0.2; Scotland: 1,834 (3.7), 0.3. As can be seen from the table, nephritis constitutes a significant share of this figure, and in some countries (Italy) pyelitis is also included here. In any case, kidney diseases constitute the most frequent cause of death in the group of genitourinary diseases. Next is mortality from diseases of the female genital organs, which amounts to up to 1.4 persons per 10,000, whereas mortality from diseases of the male genital organs is negligible and is usually not singled out in the data of most countries. Mortality rates from nephritis in the USA significantly exceed the European ones: instead of the maximum figure of 4.0 per 10,000—from 8.5 to 9.6, and in recent years there has been a tendency to grow, as can be seen from the following figures: 1920—8.94; 1921—8.54; 1922—8.85; 1923—9.01; 1924—8.96; 1925—9.63; 1926—9.83. In cities, mortality from genitourinary diseases is higher than in rural areas. Thus, for Prussia (1927), with a coefficient of 3.7 for males and 2.6 for females per 10,000 population (Table 2), 4.8 males and 3.1 females died in Berlin. Table 2. Mortality from genitourinary diseases in Germany. Sex 1913: Males 3.5, Females 2.8; 1925: Males 3.3, Females 2.5; 1926: Males 3.4, Females 2.5; 1927: Males 3.7, Females 2.6. The war years had an effect on the increase in mortality from genitourinary diseases: the pre-war indicator in Germany of 3.5 (males) and 2.8 (females) steadily increased until 1917 (4.5 and 3.1); then followed a drop right up to 1920, when it fell below the 1913 level (3.4 and 2.7). The years of the war blockade thus made themselves felt in this area. For the city of Moscow, published information is available for 1925–28. It amounted to 1.8 per 10,000 population (both sexes). By age, the greatest number of deaths from diseases of the urinary organs falls on the group from 22 to 44 years, from diseases of the male genital organs—on the group from 50 years and older, and from diseases of the female genital organs—on the prime age from 20 to 44 years. Mortality by individual professions is given in English statistics (1900–02). If mortality (of males) from all causes is taken as 1,000, then 35 died from kidney diseases. Below this figure are shown such professions as agricultural workers (14), railway workers (17), teachers (23), clergy (27), etc., and above—butchers (46), musicians (54), day laborers (67), tavern workers (72), etc. Morbidity was most fully traced for the city of Moscow and province for 1926 (detailed processing is timed to the census year). Per 1,000 population, it was 57.8; of these, urinary—8.4, male genital organs—2.5, and female genital organs—46.9, and for the province respectively 35.9, 6.2, 1.4, and 28.3. In the group of urinary diseases in Moscow, 2.3‰ falls on inflammation of the kidneys (for the province—2.0‰). By sex, morbidity from urinary diseases (Figure 6) is higher among women, as can be seen from the following figures (Table 3). Table 3. Diseases of the ... Women Diseases of the urinary organs .... Acute and chronic nephritis .... 4.5 1.6 2.9 7.7 2.4 5.3. Diseases of the male genital organs per 1,000 male population give an indicator of 5.2,

Figure 6. Diseases of the genitourinary organs.
(city) and 3.2 (province), and diseases of the female genital organs respectively—91.7 and 52.4. Diseases of the genital organs among women occur 17 times more often than genital
Diseases in men. The nature of the disease by age is illustrated by Table 4 and Figure 7. Table 4. Nature of the disease of the population with genitourinary diseases by sex and age per 1,000 population of the city of Moscow in 1926. Age Genitourinary diseases Diseases of the urinary organs Diseases of the sex organs M. F. M. F. M. F. Under 1 year......... 11.0 9.5 3.0 2.7 8.0 6.8 From 1- 4 years...... 15.6 12.5 6.2 5.4 9.4 7.1 » 5- 9 » ..... 9.1 10.4 5.1 4.8 4.0 5.6 » 10-14 » ..... 7.2 9.3 5.6 4.4 1.6 5.0 » 15-19 » ..... 7.7 54.1 4.2 6.6 3.5 47.5 » 20-29 » ..... 12.9 188.4 6.4 13.3 6.5 175.1 » 30-39 » ..... 11.7 166.4 7.1 13.8 4.6 152.6 » 40-49 » ..... 10.6 106.9 7.4 13.3 4.2 93.6 » 50-59 » ..... 11.2 38.8 7.9 10.0 3.3 28.8 60 years and older . . . 14.2 16.5 8.9 6.7 5.3 9.8 It can be seen from this that the morbidity of the urinary organs in men increases from the age of 20 and reaches its highest development after the age of 60, while in women the maximum falls on the 20-49 age group. Diseases of the male sex organs are more common at the age under 5 years and in persons aged 20-29 years. Diseases of the female sex organs have a maximum at the age of 20-29 years and 30-39 years, but there are also quite a few of them among adjacent groups. In the reproductive group, sex diseases among women occur 30 times more often than among men. From individual diseases, the age-specific morbidity of nephritis, mastitis, and menorrhagia can be demonstrated (Table 5). Table 5. Morbidity of nephritis (acute and chronic), breast diseases, and menorrhagia (per 1,000 population). Age Under 1 year..... 1- 4 years. ... 5- 9 years. ... . 10-14 » . . . . 15-19 » . . . . 20-29 » . . . . 30-39 » . . . . 40-49 » . . . . 50-59 » . . . . 60 years and older Nephritis Breast diseases Menorrhagia F. F. F. >0.4 >0.2 2.6 2.7 8.5 7.0 4.0 7.5 6.1 0.4 1.2 0.2 0.2 Regarding nephritis, it can be noted that among men it is more common from 30 years and older, and among women from 15 to 59 years, in particular among women more often than among men. Breast diseases were noted mainly in the 20-39 age group (maximum 20-29 years), and menorrhagia from 20 to 49 years, i.e., in the reproductive age. Increased coefficients in infancy are found for diseases of the male sex organs, at the age of 20-39 years for acute and chronic nephritis, diseases of the male sex organs, and especially female sex organs (especially mastitis and menorrhagia), at the age of 40-59 years for acute and chronic nephritis and diseases of the female sex organs (menorrhagia), and finally at the age of 60 years and older for diseases of the urinary organs (especially nephritis). When distributing genitourinary diseases by months of the year, it turns out that, apparently, no definite pattern exists. The role of profession in the morbidity of female diseases according to the study of factory and plant female workers by S. M. Bogoslovsky is less significant than one might assume. Morbidity with loss of working capacity for the city of Moscow and province for 1925-28 ranges within the following limits per 100 insured (Table 6): for genitourinary diseases (both sexes) from 4.0 to 4.8; for diseases of the urinary organs from 0.6 to 0.7; for male sex diseases 0.5; for female sex diseases from 6.9 to 8.6, and in recent years both the absolute number of cases of loss of working capacity and the ratio to the total mass of the insured tend to increase. The average duration of a single case of disability for diseases of the genitourinary organs in men was from 22.4 to 28.8 days, in women from 17.1 to 25.5; for male sex diseases from 14.1 to 17.2, and for female sex diseases from 11.8 to 18.3. Sex. As in the case of general morbidity, morbidity with loss of working capacity in women is almost twice as high for all noted years, and for diseases of the sex organs it is 17 times higher. According to individual industries, it is observed that men show increased morbidity in the garment, food and condiment, and leather industries, and women, in addition to those indicated, also in the metal industry (Table 7). Table 7. Indicators of loss of working capacity in the industry of Moscow and province in 1928 (per 100 insured). Industry Genitourinary diseases Urinary organs Sex organs M. F. M. F. M. F. Metallurgical . . . 1.2 17.3 0.5 1.4 0.7 15.8 Woodworking . . . 1.2 9.0 0.6 0.7 0.6 8.3 0.8 7.3 0.4 0.9 0.4 6.4 1.3 0.5 23.4 6.3 0.7 0.2 1.6 0.9 0.6 0.3 21.8 5.4 Processing of mineral substances 1.3 15.5 0.7 1.7 0.6 13.8 1.7 10.3 0.7 1.4 1.0 8.9 Processing of animal products 1.1 15.5 0.5 1.2 0.6 14.3 1.2 10.6 0.7 1.3 0.5 9.3 Printing . . . . 1.1 17.6 0.5 1.2 0.6 16.4 Increased morbidity of men with sex diseases can be noted in the leather industry, and of women in the garment, printing, metal, food and condiment industries, and in the processing of animal products. The influence of professional labor on the growth of diseases of the female sex organs with loss of working capacity can be traced in the tobacco industry (Table 8). Diseases of the uterus and appendages among production female workers occurred in 3.6 per 100 insured, and among administrative and technical personnel only in 0.6; Table 8. Morbidity of the insured by occupational groups in the tobacco industry (1927). Female diseases Production workers Number of cases of loss of working capacity Inflammation of the uterus and appendages ..... Menstrual disorders .......... 3.6 0.8 2.0 4.6 0.2 3.1 6.4 1.6 3.2 4.4 0.9 2.5 0.6 Uterine hemorrhages at the same time, among tube cigarette machine operators the indicator rose to 4.4, among cigarette machine operators to 4.6, and among machine cigarette packers to 6.4. Uterine hemorrhage is noted more often among packing, cigarette, and tube machine operators compared to production female workers. Disability. Of the total mass of those examined in the Moscow Bureau of Medical Expertise (1925-1926), 1.2% in 1925 and 1.1% in 1926 were transferred to disability due to genitourinary diseases. Thus, in the total mass of causes of disability, the specific weight of genitourinary diseases is small. By production groups, it is lower among employees than among workers, with the exception of medical and sanitary workers (2%) (Table 9). By disability groups due to genitourinary diseases (Table 10), only about half received the right to a pension (1925), since 43.7% were assigned to groups IV-VI, while for all diseases it was 12.4%. Thus, the severity of the loss of working capacity due to genitourinary diseases is small; it cannot be put next to, for example, diseases of the cardiovascular system, where 60.1% were classified as disabled based only on the first two groups. Table 9. Distribution by causes of disability in connection with the occupational group (1925-26). Years Workers Employees Number examined 4,604 57 1,359 1,203 1,886 4,555 1,147 1,752 1,385 102 1,919 6,176 87 561 1,326 1,026 5,280 1,222 982 1,349 275 1,200 Genitourinary diseases (per 100 examined) 0.7 0.3 - 0.2 1.2 - 0.8 2.5 0.8 0.6 0.7 0.8 1.0 0.4 0.4 0.9 0.4 1.8 1.1 1.6 1.2 1.4 0.9 0.5 0.9 0.4 0.2 2.0 0.6 0.9 Table 10. Distribution of labor invalids by causes and disability groups (1925-26). Causes of disability Number examined Percentage distribution by disability groups Abs. In % IV - VI For all diseases.. / Genitourinary \ diseases.. 1 1925 1926 1925 1926 10,472 12,603 126 140 100 100 1.2 1.1 8.2 8.3 7.1 2.1 50.4 51.5 22.2 35.8 29.0 31.1 27.0 32.1 12.4 9.1 43.7 30.0 Pathological morbidity can be traced from the materials of the survey of industrial workers of Moscow (1925-28). The entire mass of workers and employees, divided by production sign, gives the following indicators of morbidity of the genitourinary apparatus (per 100 examined of each sex separately) (Table 11): Table 11. Professions Diseases of the urinary organs Production workers ...... Auxiliary Employees..... 0.3 0.3 0.5 1.0 1.3 0.7 0.4 0.4 0.2 22.4 17.6 11.5 Women have a greater morbidity than men, and everywhere employees give lower indicators than workers, with the exception of diseases of the urinary organs in men. With a more detailed consideration of the group of female diseases, this rule is almost nowhere violated (Table 12).
The complex of occupational hazards of a particular type of labor may exert its influence on increasing the incidence of morbidity in the female reproductive sphere (Table 13). Thus, in Table 14 one can observe that with an increase in the length of service in wage labor, the indicators of inflammation of the uterine appendages also grow, both among auxiliary female workers and among female office workers; furthermore, to exclude the influence of age, the group of the blooming reproductive period from 20 to 39 years was taken. Table 12. Morbidity of female diseases among industrial female workers of the city of Moscow (1925-28) (per 100 examined). i i a a Diseases of the female genital organs Industrial workers (37,423) Auxiliary workers (2,763) Menstrual disorders. 0.4 0.5 0.3 Inflammation of the serous layer 1.0 1.1 0.6 Inflammation of the muscular layer 2.8 3.7 3.2 2.1 2.2 1.6 Inflammation of the mucous membrane of the uterus. Prolapse and falling of the uterus. 0.7 1.3 0.8 1.4 0.1 0.2 Prolapse of the vagina . . . Change in the position of the uterus. 3.2 2.3 1.2 Displacement of the uterus .... 2.5 1.3 1.4 Inflammation of the uterine appendages. 4.6 3.6 2.4 Benign neoplasms of the uterus ...... 0.4 0.2 0.1 Benign neoplasms of the ovaries .... 0.1 0.1 0.2 Benign neoplasms of the vagina . . . - 0.04 Benign neoplasms without indication of localization . 0.1 - Diseases of the external genitalia ....... 0.01 0.04 - Diseases of the vagina . . 0.9 0.3 0.5 Diseases of the cervix uteri 0.05 0.04 - Atrophic conditions 0.1 - 0.04 Cessation of ovarian function 0.1 0.04 Table 13. Increase in the indicator of inflammation of the uterine appendages with an increase in the length of service in wage labor (per 100 examined; age 20-39 years). Professions Up to 5 years 5-8 years 8 and over Total Auxiliary 3.9 1.7 4.8 1.8 6.9 4.0 6.0 2.8 The same correlations can be traced for some other pathological conditions of the female sphere in the group of female industrial workers. As can be seen from Table 14, the regularity of the increase in indicators with an increase in length of service is distinct. Table 14. Influence of length of service in wage labor on the rate of incidence of female diseases per 100 examined. (Female industrial workers; age 20-39 years). Diseases of the female genital organs Length of service Inflammation of the serous membrane of the uterus........ Inflammation of the muscular membrane of the uterus ........ Inflammation of the mucous membrane of the uterus........ Inflammation of the uterine appendages ............. Displacement of the uterus .... Change in the position of the uterus ............. Prolapse and falling of the vagina........... 0.4 0.7 1.9 3.6 3.5 1.6 2.1 0.9 2.1 3.7 4.9 2.2 2.3 1.0 1.3 3.8 4.8 6.6 3.5 3.8 1.3 1.1 3.3 4.5 6.0 3.1 3.3 1.2 Further, not yet completed studies of pathological morbidity among individual professions show that in some cases the rate of incidence of female diseases can be linked both to the labor process and to the production environment. Thus, for example, among female tobacco workers in contact with tobacco, the rate of endometritis is high (5.9% versus 4.5% in the production group of female tobacco workers) and metritis (7.7% versus 3.3%). In other cases, social and domestic factors also play a role, as is noted, for example, among schoolteachers: the morbidity rate of female diseases is 1.7% in unmarried ones, and 12.1% in married ones (births not included).
Related articles
Mentioned in
Cite this page
“Genitourinary Organs.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/urogenital-organs/