Stomach
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This historical article from the 1928–1936 Soviet Great Medical Encyclopedia covers the anatomical, comparative morphological, and developmental aspects of the stomach in vertebrates and humans.
Encyclopedia article (1928–1936)
STOMACH (gaster, ventriculus), an expanded section of the intestine that, due to the presence of special glands, has the significance of a particularly important digestive organ. Clearly differentiated "stomachs" of many invertebrates, especially arthropods and higher mollusks, are of course not directly comparable to the stomachs of vertebrates, which are characterized by their lining of single-layered columnar epithelium with special tubular glands differing in their structure and the nature of their secretion. However, even in vertebrates, the stomach is far from always clearly demarcated from the esophagus, and in some lower vertebrates it is absent altogether. In most fishes and all terrestrial vertebrates, a clearly distinguishable stomach is present, but the external boundary of the stomach even in mammals may not coincide with the physiological boundary determined by the nature of the epithelium and glands (Figures 1 and 2). Sometimes elongated in animals with an elongated body, the stomach is nevertheless more often curved in the shape of the Latin letter U, forming a blind pouch (fundus), which makes it possible to distinguish a concave "lesser curvature" and a convex "greater curvature." From
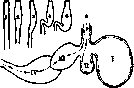
the small intestine, it is always demarcated by an annular pyloric fold. Already in some fishes, as well as in amphibians, two kinds of glands are distinguished in the stomach: fundic glands and pyloric glands. In crocodiles, in the walls of Figure 1. 1-5—simplest forms of the stomach (after Kingsley): 1—stomach of the garfish (Belone), a fish from the order Physostomi; 2—stomach of the tailed amphibian proteus (Proteus); 3—stomach of the common grass snake (Tropidonotus natrix); 4—stomach of the goby (Gobius), a fish from the order Acanthopterygii; 5—stomach of a shark; 6—diagram of the stomach of a ruminant (dashed line shows the path of food); insufficiently chewed food first enters the 1st section—the rumen (rumen), from where peristaltic movements drive it into the second section—the reticulum (reticulum); from the reticulum, food is regurgitated, chewed again, swallowed once more, and directed straight into the third section (III)—the omasum, and then into the 4th section (IV)—the abomasum (abomasus), where it is digested.
the middle part of the pouch-like stomach, a very significant musculature develops. In birds, differentiation goes further and leads to the separation of two independent sections: the anterior, barely inflated glandular stomach, corresponding to the cardiac section, and the lenticular muscular stomach, developed from the pyloric section, the glands of which secrete a hard horn-like lining serving to grind food. The mammalian stomach is characterized by significant development and differentiation of glands, of which the most constant are nevertheless the fundic glands and pyloric glands, while less constant are the cardiac glands, which are reduced in carnivores and primates. Frequently, a rather significant part of the stomach turns out to be lined with the same stratified squamous epithelium as the esophagus. The shape of the stomach can be complicated by the formation of pouch-like protrusions in its various sections, which is observed particularly in herbivorous forms (in some rodents, in artiodactyls). The stomach of ruminants is the most complex; however, of its four sections—the large rumen with numerous sturdy papillae, the reticulum with a honeycomb inner surface, the omasum with leaf-like longitudinal folds, and the elongated abomasum with lower longitudinal folds—only the last one represents a true stomach with fundic and pyloric glands. The first three sections are lined with stratified squamous epithelium. The rumen and reticulum must be considered as sections of the esophagus in which food is only soaked and fermented. The omasum apparently secondarily separated from the stomach, as can be seen from the structure of the stomach of camels.
I. Schmalhausen. Development of the stomach begins immediately upon the formation of the foregut, in the human embryo in the 1st month (4 mm). The head section of the gut forms the pharynx with gill slits and the lung bud; at a certain distance from it, a spindle-shaped expansion of the stomach is formed; the foregut is connected at this place with the walls of the body cavity by the anterior and posterior mesentery (mesogastrium). In the 5th week, the stomach acquires the characteristic shape of a retort with the greater curvature facing backward, but it is still located symmetrically relative to the median plane. Further changes consist in the bending of the stomach and its rotation along

Figure 2. Various forms of the mammalian stomach. Horizontal lines indicate the stratified epithelium of the esophagus and the esophageal section of the stomach; oblique lines indicate the region of cardiac glands; dots indicate the region of fundic glands; crosses indicate the region of pyloric glands: 1—stomach of a rat; 2—dog; 3—human; 4—ruminant; 5—horse; 6—hamster; 7—peccary (American wild boar); 8—sloth (South American xenarthran feeding on buds, young shoots, and fruits). (Figures 1–6 after Hesse, 7–8 after Schimkewitsch.)
its axis, with the greater curvature turning to the left (Figure 3) (see Peritoneum, same figure). The gastric glands begin to develop in the 10th week (Toldt) in the form of depressions of the epithelial layer (mouths), from which narrow sacs (body of the glands) then grow inward. Parietal cells differentiate only at the end of the 4th month. At the end of intrauterine life, the number of tubules flowing into a single mouth reaches 7; after birth, it decreases to 2–3. Phylogenetically, a certain sequence is noted in the development of various glandular fields of the stomach (Figure 4). Thus, main and parietal cells differentiate only in mammals; even later, pyloric and cardiac glands appear.
V. Karpov. Anatomical and topographical data. Like in other vertebrates, the human stomach represents an expanded part of the digestive canal located between the end of the esophagus and the beginning of the duodenum. Its upper (inlet) opening, through which food enters, is called the car-

Figure 3. Forms of the stomach during its development: 1—shape of the stomach in an embryo 5 mm in length; 2—in an embryo 8 mm in length; 3—in 10 mm in length; 4—in 19 mm in length. (After Broman and Lewis.)

dial, i.e., cardiac (from the Greek cardia—heart), because it is located closer to the heart than the exit opening; the lower (exit) opening, through which food passes from the stomach into the duodenum, is called the pyloric, i.e., pylorus (from the Greek pylorus—gatekeeper). The stomach has two surfaces: 1) antero-superior and 2) infero-posterior, and two borders: the anterior (greater curvature) and posterior (lesser curvature). Like any hollow organ consisting predominantly of muscular tissue, the stomach can undergo temporary changes in its volume and shape depending on the amount of its contents, the state in which this content is in (solid, liquid, gaseous), and the physiological requirements of the given moment of the digestive act. Death can catch a patient in any phase of gastric digestion: hence, generally speaking, Figure 4. Glandular fields of the human stomach: i—cardiac glands; ii—glands of the body; iii—intermediated zone; iv—pyloric glands; iv'+v—pyloric glands with parietal cells; sm—lesser curvature.
(After Aschoff.)
such a variety of gastric forms is obtained, which is observed during autopsies and encountered in descriptions of the stomach shape by various authors. The nomenclature of individual parts of the stomach also varies among different authors. This article adopts the nomenclature of Lewis (1912). Lewis gives the following scheme of the stomach and its anatomical subdivisions (Figure 5). A plane passing through the incisura angularis (the point on the lesser curvature where the concavity running along the pars cardiaca transitions into a convexity running along the pars pylorica, on one side, and through the left border of the opposing expansion on the greater curvature—on the other (vesti
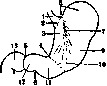
1-antrum cardiacum; 2-cardia; 3-canalis gastricus; 4-incisura angularis; 5-sulcus pyloricus (pylorus); bulum pyloricum), divides the stomach into two parts: left (cardiac) and right (pyloric). The boundary between corpus and vestibulum pyloricum; not the boundary between pars cardiaca and pars pylorica is usually represented in the form of a small depression. Sometimes in this place there is a thickening consisting of muscle fibers, apparently belonging to the deep oblique layer. With full expansion of the stomach, this boundary disappears. The cardiac part occupies approximately 2/3 of the stomach, and the pyloric part 1/3. The cardiac part consists of the corpus and fundus. The fundus is that part of the stomach which projects above the horizontal plane passing through the stomach at the level of the cardia. The pyloric part in turn is also subdivided into 2 parts: the right, or pyloric channel (canalis pyloricus, antrum pyloricum) and the left, or vestibule (vestibulum pyloricum). The plane dividing the pyloric part into the 2 indicated parts passes at a right angle to the long axis of this part through the intermediate sulcus (sulcus intermedius) located on the greater curvature, situated approximately 2.5 cm from the pyloric sphincter. The gastric canal (canalis gastricus, Magenstrasse of Waldeyer) is called the narrow section of the stomach cavity, stretching in the form of a groove along the lesser curvature from the cardia to the incisura angularis (Fig. 30, p. 115).
During the digestive process (Fig. 6), the stomach is divided by a muscular constriction into a large expanded left lobe and a narrow, tube-contracted right one. The muscular constriction usually passes through the body of the stomach, and therefore often does not coincide with the anatomical boundary line between the body and the pyloric part. As the digestive process moves forward, the mentioned delimiting contraction ring moves to the left, i.e., an increasingly larger part of the previously expanded body of the stomach now takes on a tube-like form and in this way gradually enlarges the tube-like (pyloric) part. From this it is clear that the physiological cardiac part can correspond to the anatomical one only at a definite stage of gastric digestion. Being moderately stretched, the stomach has a pear-shaped, curved form. Its upper two-thirds are located more or less longitudinally, while the lower third is more transverse. When the stomach is relaxed, it tends to assume a more vertical position. Knowledge of the shape and position of the stomach in the living person became more precise after the preliminary administration of food mixed with X-ray-impermeable bismuth salts was introduced into practice in the study of the stomach. The shadow of the stomach was fixed on a photographic plate. Based on this method of study, Hertz gives a picture of the shape and position of the moderately stretched stomach in a living person when standing (Fig. 7). The lower boundary is located slightly below the navel. By a voluntary contraction of the muscles of the anterior abdominal wall, this boundary can be raised by 5-13 cm. In the lying position, the lower boundary of the stomach rises upwards. This displacement of the lower boundary of the stomach upwards is not associated with a noticeable rise in the level of the pylorus. Addison places the lowest point of the lower boundary of the stomach (caudal pole) on the corpse 2 cm below the pylorus. Groedel determines this distance in a living person in the vertical position to be 8 cm. The higher position of the lower boundary of the stomach on the corpse is explained, firstly, by the fact that the corpse is usually examined in a horizontal position, and secondly, by the fact that the diaphragm on the corpse is in the state of exhalation, and therefore the stomach must occupy a correspondingly higher level. Gastroscopic anatomy with its color and spatial pictures supplements the shadow pictures of living anatomy and the data obtained on corpses. Gastroscopic anatomy immediately views the stomach in three-dimensional space. According to Sternberg, the axis of the stomach, i.e., that line which connects the centers of the moderately stretched
food mass containing bismuth salts: 1-esophagus; 2-pelvis-filled fundus of the stomach; 3-incisura angularis; 4-pylorus; 5-navel. (After Hertz.)
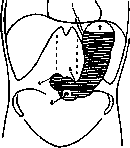
of individual cross-sections of the stomach, represents a spiral line; the stomach is thus a spiral tube with a right-handed thread (right-handed twist). Gastroscopically, the cardia and pylorus lie strikingly close to each other in a straight line. The boundary between the body of the stomach and its pyloric part always exists gastroscopically, and resistance is always encountered to the passage of the gastroscope at this place. Just at this place, a fold extending from the incisura angularis is noted. Moynihan, who has repeatedly observed spasmodic muscle contractions of the stomach walls during operations, says that he saw such contractions on the body of the stomach and on the pylorus, but never saw them on the fundus. Dimensions of the stomach. The stomach increases greatly (Scammon) in the last months of intrauterine life and in the first three months after birth. On the corpse, the average (anatomical) capacity of the stomach at birth is determined to be 30 cm3, while the average physiological capacity, determined during life by weighing before and after eating, is equal to 7 cm3. During the very first day, the average physiological capacity doubles, on the 3rd day it quadruples, on the 4th day it increases 7 times, on the 10th-more than 11 times (about 81 cm3). After the 4th day, the anatomical and physiological capacities approach each other. At the end of the first month, the stomach capacity is from 90 cm3 to 100 cm3. Then the increase proceeds more slowly and by the end of the first year reaches 250-300 cm3, during the 2nd year-from 300 cm3 to 500 cm3, during the 3rd year-from 400 cm3 to 600 cm3. In the period from 4 to 7 years, a deceleration in the increase of stomach capacity occurs, and after 7 years acceleration occurs again, and at 10-12 years the stomach capacity reaches 1,300-1,500 cm3. In an adult, a moderately stretched stomach has a length (from the apex of the fundus to the lowest level of the greater curvature) of approximately 20-22 cm. The distance between the entrance and exit openings varies from 7 cm to 15 cm. The diameter at the widest place is 8-9 cm. The capacity of the stomach in an adult
located above the small intestines, and finally by the transverse colon. The anterior wall of the gastric bed is formed
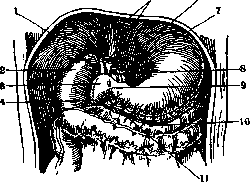
12 13 14 Figure 8. The stomach on its bed. The liver has been removed. 1-right adrenal gland; 2-right kidney; 3-first part of the duodenum; 4-second part of the duodenum; 5-segments of the inferior vena cava; 6-portal vein; 7-hepatic artery; 8-common bile duct; 9-pylorus; 10-transverse colon; 11-right gastroepiploic artery, omentum removed just at the level of this artery. (After Davis.)
on average is determined to be about 3 liters, but it varies greatly depending on the amount of food usually ingested, and especially drink, and on the degree of tonus of the musculature of both the stomach itself and the abdominal walls. Topographical relations of the stomach. The part of the abdominal cavity in which the stomach is housed is called the "gastric bed" (Fig. 8). This bed has a posterior wall and a ceiling of a more or less arched shape, a lower wall (floor), somewhat sloping anteriorly, and an anterior wall more or less straight. The part of the ceiling formed on the visceral surface of the left lobe of the liver, Figure 9. View of the liver and stomach from above and behind after removal of the diaphragm: 1-stomach; 2-left lobe of the liver; 3-esophagus; 4-left triangular ligament; 5-spleen; 6-cross-sectioned diaphragm; 7-right lobe of the liver; 8-inferior vena cava and hepatic veins; 9-anterior leaf of the coronary ligament; 10-right triangular ligament; 11-aorta; 12-falciform ligament of the liver. (After Farabeuf.) while the rest of the ceiling and the posterior wall are formed by the diaphragm (Fig. 9). The floor is a half-bowl on which the lower-posterior surface of the stomach rests. The posterior section of the floor is formed by the apex of the left kidney (with its adrenal gland) and the gastric surface of the spleen (Figs. 10 and 11); more anteriorly-by the broad upper surface of the pancreas; still more anteriorly-by the mesentery of the transverse colon, running from the anterior edge of the pancreas and
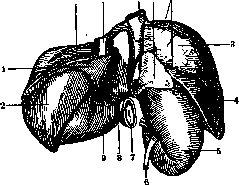
Figure 10. Relation of the stomach to surrounding organs. Posterior view. The figure is made from a model manufactured by the reconstruction method: 1 - stomach; 2 - spleen; 3 - part of the liver surface not covered by peritoneum; 4 - liver; 5 - right kidney; 6 - ureter; 7 - pylorus; 8 - Spigelian lobe of the liver; 9 - omental tuberosity of the liver (tuber omentale); 10 - left lateral (triangular) ligament of the liver; 11 - esophagus; 12 - inferior vena cava; 13 - right adrenal gland; 14 - coronary ligament of the liver. (After Cunningham.)
over the portion of the anterior abdominal wall bounded on the left by the left costal arch and on the right by the liver (Fig. 12). The gastric bed is completely filled by the stomach when it is distended. When the stomach is contracted, it occupies only
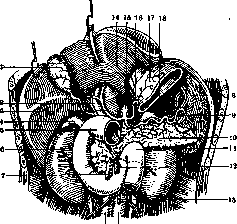
19th Figure 11. The liver is pulled upward. The stomach is resected in a significant part of its extent to show the organs to which its posterior surface is adjacent: 1 - gallbladder; 2 - portal vein; 3 - hepatic artery; 4 - right adrenal gland; 5 - initial section of the duodenum; 6 - right kidney; 7 - superior mesenteric vein; 8 - spleen; 9 - splenic artery; 10 - pancreas; 11 - duodenojejunal flexure; 12 - superior mesenteric artery; 13 - inferior mesenteric artery; 14 - liver; 15 - aorta; 16 - left gastric artery; 17 - stomach; 18 - splenic vein; 19 - inferior vena cava; 20 - aorta. (After Testut.)
the lower part of its bed; the remaining part of the bed is filled in this case by the transverse colon, which, as the stomach contracts, gradually turns upward and ultimately lies anterior and superior to the stomach directly beneath the diaphragm, a fact that must be remembered during clinical
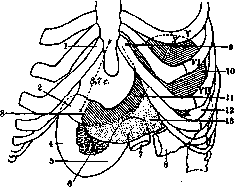
Figure 12. Diagram of the position and anterior relations of the stomach: 1 - seventh costal cartilage; 2 - first section of the duodenum; 3 - pylorus; 4 - second section of the duodenum; 5 - third section of the duodenum; 6 - head of the pancreas; 7 - jejunum; 8 - transverse colon; 9 - location of the cardia; 10 - subdiaphragmatic region of the stomach; 11 - subhepatic region of the stomach; 12 - splenic flexure of the colon; 13 - superficially lying region of the stomach. (After Hughes.)
examination of this region. The cardiac orifice of the stomach is placed at the level of the 11th thoracic vertebra in front of the aorta. It is located approximately 10 cm behind the anterior chest wall and 2.5 cm from the left edge of the sternum, behind the seventh left costal cartilage. When the stomach is empty, the pylorus is located approximately 2.5 cm to the right of the midline at the level of the first lumbar vertebra. This level corresponds fairly accurately to the midpoint of the line connecting the suprasternal (jugular) notch with the upper edge of the pubic symphysis. Upon distension of the stomach, the displacement of the pylorus to the right of the midline can reach 7.5 cm. Structure of the stomach. In the wall of the stomach, as in other sections of the digestive tract, three layers are distinguished: 1) the mucous membrane (tunica mucosa), 2) the muscular coat (tunica muscularis), and 3) the serous coat (tunica serosa) (Fig. 13). The mucous membrane has a thickness from 0.5 mm (in the region of the cardia) to 2 mm (pylorus), of a pale pink color that reddens during digestion. In the collapsed stomach, it lies in longitudinal folds (plicae mucosae), which smooth out when it is filled. On the surface of the mucous membrane, polygonal fields (1-4 mm2) protrude, bounded by shallow grooves (areolae gastricae) and caused by the accumulation of glands (areae gastricae, état mamelonné, see); in the region of the fields, numerous openings (9-18 per 1 mm) are visible, leading into the mouths of the glands (foveolae gastricae). The mucous membrane includes: surface epithelium, glands, proper tissue, muscular layer, and submucosa, which is sometimes distinguished as a special layer. The epithelium represents a peculiar form of mucous epithelium, forming an excretory epithelial surface (see Glands); it consists of cylindrical cells with a nucleus in the middle and mucigen granules in the upper section, where the centrosome and Golgi apparatus are also located (Fig. 14). The upper end of the cells in preparations is usually open, as a result of which they were long considered goblet cells; it is now proven that the free surface is always closed by a thin membrane and the secretion is released through it in small portions; it gives mucous reactions. In view of the presence of fat droplets, this epithelium is sometimes attributed an absorptive function. The gastric glands (glandulae gastricae) belong to the type of branched tubular
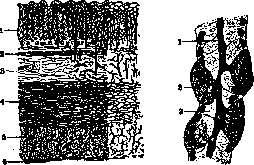
Figure 13.
Figure 14.
Figure 13. Section of the stomach wall at low magnification. Injected vessels on the right. 1 - mucous membrane; 2 - muscularis mucosae; 3 - submucosa; 4 and 5 - muscular coat; 6 - serous coat. (After Lavdovsky.) Figure 14. Surface epithelium of the stomach: 1 - lumen of the glandular tubule; 2 - parietal cells with secretory capillaries; 3 - chief cells. (After Zimmermann.) and are located extremely densely. The beginning for them serves as the gastric pits (foveolae gastricae), which, deepening, form a funnel-shaped mouth of the glands, lined with surface epithelium. This is followed by a refined short section - the neck, from which 2-3 glandular tubules extend, more or less tortuous and expanded at the ends. The total number of glands in an adult is about 25 million, in a newborn about 2 million (Toldt). In the human stomach, 4 types of glands are found: a) Fundic glands (glandulae gastricae propriae, Magensaftdrüsen), the most common type, occupying the greater part of the body and fundus of the stomach. They have a length of 1.5-3 mm, with 1/4 to 1/3 falling on the mouth; the tubules are straight or slightly tortuous, 30-50 µ wide, blind ends slightly expanded. In addition to the basement membrane and flat stellate cells, they have glandular cells of two kinds (Fig. 15); some are called chief cells (R. Heidenhain) or adelomorphous cells (see), others - parietal cells (Belegzellen, R. Heidenhain) or delomorphous cells (of distinct form). There are more chief cells, and they line the lumen; they have a cubic or pyramidal shape, the nucleus is closer to the basal end, in which rod-like striation is noticeable. During life, fairly large, highly light-refracting grains of pepsinogen are visible in the cell; after fixation, the cell body becomes light and stains with hematoxylin. Parietal cells are fewer in number, they are located further from the lumen, covering themselves with the chief cells and protruding the basement membrane; most of all they are in the neck and least of all in the fundus of the gland. In size, they are larger than the chief ones, have a rounded, oval, or polygonal shape, a nucleus in the middle; during life they contain fine granularity and on fixed preparations seem darker than the chief ones; they stain with acid dyes. Silver plating according to Golgi reveals secretory capillaries inside the parietal cells, which in the form of a basket surround the nucleus and communicate with the lumen by a short neck. Chief cells secrete pepsin, parietal cells - HCl. The latter, however, is secreted not as such, but in some compound, passing into the active state only with the participation of the covering epithelium. b) Pyloric glands, occupying the region near the pylorus over an extent of 4-5 cm (sometimes up to 14), are characterized by a greater length of the mouths and a shorter, strongly tortuous body (Fig. 16). The lumen is lined with a single type of light cylindrical cells, with nuclei closer to the base and fine granularity during life. Formerly they were considered mucous (Magenschleimdrüsen, Koelliker), but they do not give reactions for mucus; then they began to be identified with the chief cells of the fundus glands (R. Heidenhain), from which they nevertheless differ in appearance and the nature of the granules, and finally - to be recognized as elements sui generis (Oppel). Pyloric glands pass without a sharp boundary into Brunner's glands of the duodenum; there is an opinion that they secrete pepsin. As a variety of pyloric glands, so-called accessory cells (Nebenzellen of German authors) are described, secreting a serous or serous-mucous secretion. They are located in the region of the neck of the fundus and body glands of the stomach; especially increasing in number towards the pyloric region, where they displace the chief cells, forming together with the parietal cells the so-called intermediary zone. c) Cardiac glands, serving as a continuation of the esophagus glands, occupy a very narrow region (5-6 mm) at the entrance to the stomach in humans and are similar in structure and cell character to the pyloric ones. They do not secrete mucus and sometimes contain parietal cells. d) Lieberkühn glands, completely similar to the glands of the small intestine, very often

Figure 16. Pyloric
glands: 1-mouth of the glands; 2-glandular tubules. (From Lavdovsky.) They occur as islands in the region between the fundus and the pyloric part, rarely in the region of the cardiac zone. The variety in the structure of various sections of the mucous membrane of the stomach may become even greater under pathological conditions; thus, in chronic gastritis, pyloric glands are found as islands in the body of the stomach, Lieberkühn crypts are sometimes found in the cardiac region, and so on. These phenomena are based not only on the factor of heterotopia, but represent a product of pathological regeneration, i.e., certain glands arise in place from the surface epithelium. The proper tissue of the mucous membrane (lamina propria) consists of a delicate connective tissue of a reticular character and is always infiltrated with lymphocytes, which in places can form follicles. Below the base of the glands lies a plate of dense connective tissue (stratum Zeisseli). This is followed by the proper muscular layer of the mucous membrane (muscularis mucosae), in which, besides the outer longitudinal and inner circular layers of smooth muscles, another layer of oblique fibers is described, adjacent to the Zeiss membrane. The submucosa consists of loose connective tissue and sometimes contains fat cells. The muscular coat of the stomach consists of three layers of smooth muscle fibers: outer, middle, and inner (Fig. 17). The outer layer consists of longitudinal fibers, which are a continuation of the longitudinal fibers of the esophagus, which in the region of the cardia begin to diverge radially on the surface of the stomach. These fibers are best expressed along the lesser and greater curvatures; on the anterior and posterior surfaces they appear as a very thin scattered layer, which in the direction of the pylorus again turns into a homogeneous, well-expressed layer; above the pyloric sphincter, the longitudinal fibers split into 2 layers—superficial and deep; the superficial layer continues into the corresponding layer of the duodenum, and the deep layer is directed towards the pyloric sphincter, where it ends in the form of diverging bundles, many of which reach the submucosa. The middle layer of the muscular coat of the stomach consists of circular fibers that are located throughout the entire extent of the stomach, with the exception of its fundus. Towards the pylorus, this layer becomes thicker. The pyloric sphincter is formed by this layer. The inner layer of the muscular coat consists of circular and oblique fibers. Circular
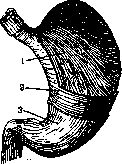
Figure 17. Preparation of the three muscle layers of the stomach wall: 1-inner layer-oblique fibers (fibrae obliquae); 2-middle layer-circular fibers (fibrae circulares); 3-outer layer-longitudinal fibers (fibrae longitudinales). (According to Cunningham.)
fibers of this layer surround the fundus of the stomach in exactly the same way as the circular fibers of the middle layer surround the rest of the stomach. Beginning as a series of rings at the apex of the fundus, they extend as a layer of rings located at right angles to the axis of the stomach down to the cardia. Below the cardia, this layer continues in the form of oblique fibers, which radially diverge from the left side of the esophageal opening downwards and to the right on both surfaces of the stomach. Some of them almost reach the antrum pylori. The oblique fibers terminate by turning sharply towards the greater curvature and passing into the circular fibers of the middle layer. The oblique fibers are best observed by removing the mucous membrane. The upper section of the oblique muscles of the inner layer of the human stomach serves to form a special kind of groove (see above "gastric canal"). It is believed that along this path saliva and liquid parts of food can pass from the esophagus directly into the pars pylorica, bypassing the cardiac region. In ruminants, the oblique fibers form a complete ring and intersect at the second stomach. By their contraction, they close the entrance to the first and second stomachs and pass the regurgitated and chewed food directly into the 3rd and 4th stomachs. The oblique fibers play the role of sphincters, and peristalsis is apparently uncharacteristic of them. In vomiting, which usually originates from the pylorus, the oblique fibers pull the pyloric region towards the cardia, shortening the path between them. A special prepyloric sphincter as a separate anatomical formation apparently does not exist. The right anatomical boundary of the cardiac region of the stomach is the right-sided region of the distribution of the oblique muscles; their closure forms the physiological prepyloric sphincter. As the cardiac pouch empties, an increasingly larger part of the oblique fibers, and apparently also of the circular fibers, is drawn into contraction and forms a tube-like section extending more and more to the left. The filling of the pyloric division throughout digestion remains constant thanks to such a mechanism, and the pressure in various parts of the stomach as it is emptied of food can be maintained at the same level. Forssell believes that the fibers of the oblique layer

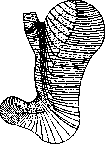
Figure 18. Left-longitudinal muscle fibers of the stomach; right-transverse muscle fibers of the stomach. (After Forssell.)
are arranged in definite tracts (Fig. 18) (sling 1st, 2nd, 3rd), which by their contractions limit certain areas.—Tunica serosa. The outer layer of the stomach is formed by the peritoneum, which surrounds it on all sides, with the exception of two areas extending along the lesser and greater curvatures of the stomach and intended for large blood vessels. The arteries of the stomach originate from three main branches of the celiac artery (a. coeliaca): 1) from the left gastric artery (a. gastrica sinistra, also known as a. coronaria ventriculi superior sinistra), 2) from the hepatic artery (a. hepatica), and 3) from the splenic artery (a. lienalis) (Fig. 19). The branches intended for the stomach,
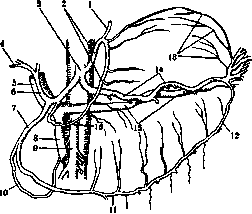
Figure 19. System of the celiac artery—a. coeliaca (3): 1-a. oesophagea; 2-a. gastr. sin., seu a. coron. ventric. sup. sin.; 4-a. cystica; 5-v. portae; 6-a. hepatica; 7-a. gastro-duodenalis; 8-v. mesent. sup.; 9-a. mesent. sup.; 10-a. pancreatico-duoden.; 11-a. gastro-epipl. dextra; 12-a. gastro-epiploica sin.; 13-aa. gastricae breves; 14-a. lienalis; 15-v. lienal.; 16-a. gastrica dex., seu a. coron. ventric. sup. dex. (After Cunningham.)
anastomosing among themselves, form two main arterial arches located along the greater and lesser curvatures between the layers of the peritoneum converging in this place, which clothe the anterior and posterior surfaces of the stomach. The arterial trunks connect to the stomach wall very weakly, which is extremely important in view of large changes in the size of the stomach: when the stomach contracts, the arteries coil; when it stretches, the arteries straighten out. Thin arterial branches penetrate through the muscle layer to the submucosa, where they divide into even thinner branches that freely anastomose with each other. Branches departing from this vascular plexus are distributed in the mucous membrane and in the muscle layers.—V e i n s, just like arteries, form a plexus in the submucosa, from where blood through the left gastro-epiploic vein (v. gastro-epiploica sin.) and short gastric veins is directed into the splenic vein (v. lienalis), through the right gastro-epiploic vein into the superior mesenteric vein (v. mesenterica superior) and through the coronary vein and the gastric exit vein directly into the portal vein (v. portae). These veins, like other branches of the portal system, have a well-defined muscle layer and contain numerous valves (valvulae).—Lymphatic vessels of the stomach begin in its mucous membrane around the gastric glands; then in the submucosa they form a plexus, from which small trunks emerge that run together with blood vessels towards the greater and lesser curvatures and receive along the way branches from the subperitoneal lymphatic plexuses (Fig. 20).
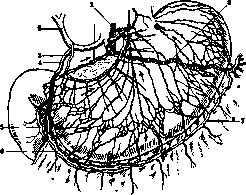
Figure 20. Lymphatic vessels and lymph glands of the stomach: 1-left gastric artery; 2-hepatic artery; 3-right gastric artery; 4-gastroduodenal artery; 5-artery of the duodenum and pancreas; 6-right artery of the stomach and greater omentum; 7-left artery of the stomach and greater omentum; 8-splenic artery. (According to Taylor.)
The lymphatic vessels running along with the blood vessels are connected: 1) with the upper lymphatic gastric glands located along the lesser curvature, 2) with the lower glands located along the greater curvature, and 3) with the splenic glands located between the leaves of the gastrolienal ligament, precisely near its attachment to the spleen. Although free communications exist between the lymphatic vessels of the stomach walls, nevertheless in certain sections of the stomach the lymph flow proceeds in known, strictly defined directions. If a line is drawn from the upper point of the fundus of the stomach towards the pylorus, passing at the level of the junction of the middle and lower thirds of the gastric wall, this line will serve precisely as the boundary between the upper lymph flows directed towards the lesser curvature and the lower ones directed towards the greater curvature. A vertical line running from the cardia downwards to the greater curvature will indicate with a significant degree of probability the place of divergence of the right and left gastroepiploic ducts. In cancer of the stomach (Lengemann), the glands located along the lesser curvature are affected in 50% of cases, the glands along the greater curvature in 37% of cases, and those located below the pylorus in 60%. Innervation of the stomach. In detail, see Autonomic nervous system. At the same time, it is necessary to point out that the opinion exists that the cardiac half of the stomach is supplied with both motor and inhibitory fibers through the vagus nerve, while the pyloric half of the stomach is supplied with motor fibers through the vagus nerve (Fig. 21) and with inhibitory fibers through the sympathetic nervous system with the aid of the celiac plexus. Starling states: "The prevailing motor effect of the vagus nerves in the region of the fundus (cardiac section) will be an increase in tone, and in the pyloric section an increase in peristaltic waves."
a. deshin. II. Physiology. Secretory functions. In its functional respect, the stomach is divided into 2 parts: the fundic and the pyloric. The first part, besides chief cells, has parietal cells and produces, along with enzymes, also free HCl (about 0.5%), which is, among other things, an important factor in the disinfection of food masses. The pyloric part has only chief cells and secretes a pyloric juice of an alkaline reaction, viscous and transparent. Among the enzymes, one must note pepsin (Schwann; 1836), which breaks down protein substances to peptones in an acidic environment, with the optimum action being around 0.15-0.2% HCl. When the juice is mixed with food, an acidity close to the optimum is obtained. Gastric juice very easily digests connective tissue. Hammarsten (Hammarsten; 1872) proved the enzymatic nature of milk coagulation by gastric juice and named this enzyme chymosin. However, I. P. Pavlov expressed the view that the milk-coagulating and protein-dissolving actions may belong to the same enzyme, since in all cases both actions change in exactly the same way. Volhard pointed out
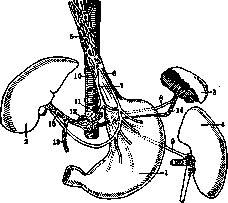
Figure 21. Diagram of the relationship of the branches of the vagus nerves to the stomach: the right vagus nerve spreads along the posterior surface of the stomach and gives off connecting branches to the plexus of the celiac artery, and to the splenic and hepatic plexuses; the left vagus nerve spreads along the anterior surface of the stomach and gives off connecting branches to the right vagus nerve and the hepatic plexus. 1-stomach; 2-liver; 3-spleen; 4-left kidney; 5- esophageal plexus; 6-left vagus nerve; 7-right vagus nerve; 8- branch of the vagus nerve to the splenic plexus; 9-branch of the vagus nerve to the renal plexus; 10- aorta; 11-left gastric artery; 12- plexus of the celiac artery; 13-gastro-duodenal artery; 14-splenic artery; 15-hepatic artery.
and to the presence of lipase in the gastric juice, which many authors could not confirm. In any case, there is very little lipase, and probably these traces depend on the release of intracellular enzymes from the epithelium. Methodology. Heidenhain (Fig. 22) proposed carving out a small stomach for the purpose of collecting pure gastric juice from it. However, during these operations the nerves were severed, so that the small stomach functioned completely differently than the large one (Orbeli). After the significance of the vagus nerve as a secretory nerve was established by Pavlov and Shumova-Simanovskaya, the necessity arose to isolate a small stomach while preserving its innervation (Fig. 22). Through the work of Khijin this task was solved: the bridge was not cut completely through, but only the mucosa and submucosa were cut, at the expense of which
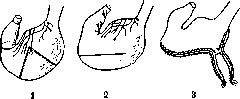
Figure 22. 1-incisions for the Heidenhain pouch; 2-incision for the Pavlov pouch with preservation of innervation; 3-diagram of the Pavlov pouch.
and the division of the large and small stomach took place. If a metal cannula is applied to the large stomach, juice can be collected from the large stomach through the fistula, and from the small stomach through the brought-out opening, thus comparing the quantities of juices obtained under different conditions (stimulation, experiment of sham feeding, introduction of alcohol into the rectum). In the history of the question about the conditions of gastric juice secretion, a cardinal moment is the experiment of the so-called "sham feeding" (I. P. Pavlov and Shumova-Simanovskaya; 1889). The authors based their work on Beaumont's observations of a Canadian hunter in the early 19th century. These observations led to the placement of a gastric fistula in a dog by Basov in 1842 and Blondlot in 1843. With these fistulas, it was still impossible to obtain pure juice. In view of this, the authors added transection of the esophagus and suturing of its ends into a skin wound on the neck. Thus, food during eating fell out of the esophageal incision and did not enter the stomach. In such dogs while fasting, the alkaline reaction of the fundic part could be established. 5-7 minutes after the start of eating, the reaction changed, and then abundant secretion began with an acidity of 0.5-0.55% HCl and a high pepsin content. In these dogs, it could be established that mechanical stimuli cause the secretion not of acid, but only of alkaline mucus. Immediately the question arose about the mechanism of secretion. How are impulses transmitted from the oral cavity to the stomach glands? Transection of both vagus nerves immediately destroyed the effect of sham feeding. Thus, the vagus nerves are the secretory nerves of the stomach. Later Ushakov confirmed this under conditions of acute experiments by direct stimulation. The reflex from the oral cavity to the glands is an unconditioned reflex. Zeleny observed a similar secretion in a dog without hemispheres. On the basis of this unconditioned reaction, conditioned reflexes to sight, smell, etc., can also arise. These very reflexes often confuse researchers. If a dog is constantly fed in a stand, then the very placement in the stand becomes a signal for food and causes "conditioned" secretion. All these factors can also cause constant secretion, which many authors even consider the norm. After transection of the vagus nerve, stomach secretion continues, although the act of sham feeding no longer produces a single drop of juice. True, recently Folbort and Kudryavtsev demonstrated the secretory role of the splanchnic nerves as well by means of direct stimulation after preliminary transection. But in any case, complete denervation does not destroy secretion. Edkins in 1906 pointed to the humoral nature of secretion under the influence of gastrin (a hormone extracted from the pyloric mucosa). However, these works caused criticism, since many various extracts caused the secretion of acidic juice. Much more for understanding was provided by work from Pavlov's laboratory through the isolation of various parts of the stomach using complex operations. These experiments gave the right to conclude that hormones are formed in the pylorus, which condition secretion, since even major destruction of nerves has little effect on it. Consistent with this are Schmidt's data, who observed the loss of the second phase of secretion after resection of the pyloric part. Ivy and Farrell provided new proof of humoral impulses by transplanting an isolated stomach under the skin with transection of all vessels and nerves. Such a stomach begins to secrete juice after eating. In full agreement with this are the data of Razenkov, who observed juice secretion in a dog with a Heidenhain pouch upon infusion of blood from a dog that was in a state of digestion; upon transfusion of blood from a starving dog, there was no gastric juice secretion. Thus, in the secretion of the gastric glands, there is a phase of reflex juice secretion and a phase of chemical secretion, with the secretion of hormones from the pylorus under the influence of various types of stimulants being most probable, such as: water, extractive substances of meat, fish, vegetables, protein digestion products (peptones), soaps, salts, etc. The total amount of juice secreted per nitrogen-equivalent portions of food varies by food type; thus, for 250 g of bread, 42 cm3 was secreted, for 100 g of meat 27 cm3, for 600 g of milk 34 cm3. Each kind of food corresponds to its own curve of secretion (Fig. 23) and its own enzyme content. When the amount of food is doubled, the amount of juice also increases 2 times, and the digestion times relate approximately as the square roots of the food masses (weights). It is necessary to note the role of fat in the course of the secretory work of the fundic glands. Fat, entering the duodenum, inhibits the secretion of acid and enzymes and delays peristalsis. If we take a stomach completely separated from the duodenum, fat has no inhibitory effect. On the other hand, protein breakdown products—peptones—and fat breakdown products—soaps, acting on the pylorus, cause the secretion of acidic juice. Mechanical stimulation of the pylorus causes enhanced pepsin secretion, so that the consistency of the food also exerts its influence on the quantity and quality of the secreted juice. Pyloric juice represents a transparent, thick liquid of alkaline reaction, containing pepsin, secreted in a zymogenic form. Juice secretion is caused by local stimulation by acid, and along with an increase in the amount of acid, there is an increase in the amount of enzymes. If a drainage tube is inserted into the isolated pylorus, juice is secreted all the time more or less evenly; giving food significantly reduces this constant secretion; after transection of the splanchnic nerves, this depression after eating disappears. The role of the vagus nerve cannot be considered fully elucidated. Small doses of pilocarpine, arecoline cause an increase in voluntary secretion, while large doses, conversely, cause depression. Atropine sharply reduces secretion, lowering the pepsin content at the same time. Curiously, acid after atropine no longer causes an enhancement of secretion and an increase in the amount of enzymes.
V. Savich. Motor function. The stomach itself possesses the capacity for peristaltic movements. Peristaltic waves that occur in the pyloric part of the stomach are usually not observed in the cardiac part; the latter serves as a more or less passive storage of food, from where it is gradually directed into the active pyloric antrum. During the digestive process, the contents of the pyloric antrum remain almost constant in volume, whereas the contents of the cardiac part continuously decrease after the end of a meal. Mixing of the contents of both parts of the stomach does not occur. In its mechanical action, the stomach largely resembles the heart. Just as the cardiac part of the stomach represents an expanding reservoir that collects food material for the rhythmically contracting strong pyloric press, the atria of the heart represent a distensible reservoir that collects blood, which then fills the strong, rhythmically contracting pump—the ventricle. Positional function predominates in the atria and the cardiac part of the stomach, while motor function predominates in the ventricles of the heart and in the pyloric part of the stomach. Numerous experiments and observations on the stomach of the frog, cat, dog, and man have shown that in these animals the pyloric part with its well-developed muscular wall performs strong, more or less rhythmic movements, while the cardiac part with its comparatively weakly developed musculature represents a reservoir from which (in Sherrington's expression) the pyloric mill receives its product for grinding. The maintenance of low pressure in the stomach during its filling is achieved not only by the positional activity of its walls, i.e., the ability to respond to an increase in its contents by a kind of active diastole proportional to the volume of the increase, but also by the positional activity of the abdominal wall muscles. By its positional activity, the diaphragm also participates in the regulation of the capacity of the abdominal cavity. The stomach, filling to varying degrees, adapts by changing the tone of its musculature to the amount of its contents, so that the intragastric pressure remains constant, and the level of the upper boundary of the gastric contents in the vertical position does not change with a change in the amount of mass contained in the stomach. The main functional task of the cardiac reservoir of the stomach is that it must easily adapt to rapid and abundant food intake without a noticeable increase in pressure within it. High pressure in the cardiac part would present an obstacle to the further entry of food from the esophagus. Every passage of swallowed food through the cardia is accompanied by a rapid, small expansion of the fundus. The intragastric pressure at this time drops slightly, but then returns to what it was before. This expansion occurs reflexively via the vagus nerve. In the human stomach, not only is there no mixing of the contents of the cardiac and pyloric parts, but even in the cardiac part itself, successively received portions of food do not mix with each other. When a new portion of food enters the partially filled stomach, it penetrates into the central part of the food mass located in the cardiac region, and thus shifts the central portions of this mass to the periphery. Grützner, testing the reaction of various layers of food in the stomach, found that while the contents of the pyloric part were acidic everywhere, in the cardiac part only the outer layer had an acidic reaction, in which digestion apparently occurred with the help of gastric juice. The central layers, however, had an alkaline reaction—there, digestion with the help of saliva apparently still continued. It is very likely that in man, as in other animals, the cardiac part of the stomach in the early stages of gastric digestion serves as the site of action of ptyalin on the food mass. In the upper part of the cardiac part (fundus) swallowed air and gases formed during gastric digestion accumulate. The size of the gas bubble on average is: base diameter 8–10 cm, height 3–5 cm. Peristaltic contractions of the pyloric part, creating a reverse current when the pyloric sphincter is closed, contribute to the best grinding of the food masses and their proper mixing with gastric juice. When the pyloric sphincter is open, peristaltic contractions gradually empty the pyloric part, moving its contents into the duodenum. Insufficient chewing of food enhances the peristalsis of the pyloric part and thus forces this part to perform the work that the jaws should have performed. The pyloric opening of the stomach is surrounded by a very strong ring of circular muscle fibers (sphincter pylori). During life, this opening, located at the end of the pyloric channel, is always tightly closed, except for individual moments of the digestive act, when it opens intermittently, at irregular intervals, to pass the appropriately processed food material from the stomach into the duodenum. Cannon mixed flour food with bismuth subnitrate and observed the movements of the stomach using X-rays in cats. Five minutes after food intake, near the duodenal end of the pyloric antrum, a slight annular contraction is noted, which moves peristaltically toward the pylorus; it is followed by several repeated waves at irregular intervals. Two or three minutes after the first movement is noted, a very slight contraction appears near the middle of the stomach and, penetrating more deeply into the greater curvature, moves slowly toward the pyloric end. Not every contraction wave pushes food through the sphincter pylori. The first region to noticeably decrease in volume is the preantral part of the pyloric part. As the process continues, the middle region of the stomach takes the form of a tube with a rounded cardiac sac on one side and an active antrum on the other. Along the tube, very shallow contractions can be noted following one another in the direction of the pylorus. By the contraction of the longitudinal, circular, and oblique muscles of the spherical cardiac sac, its contents are squeezed into the tubular part. The contractions of these muscles apparently occur in such a way that they as if wash away the superficial food layer altered by the gastric juice secreted by the walls of this part of the stomach, and squeeze this layer into the tubular part, exposing a new food layer to the action of gastric juice in the cardiac part. When the cardiac sac is emptied, the contraction waves carry the contents of the tubular part into the antrum. Cannon summarizes the results of his research as follows: "The stomach consists of two physiologically different parts: 1) the active pyloric part, through which contraction waves run with a continuous rhythm during digestion, and 2) the cardiac part, which is an active reservoir that squeezes out its contents from time to time in small portions, as the mechanism of the pyloric part is prepared to receive them." In the cat, food in the cardiac part when examined 1½ hours after the onset of the appearance of peristaltic waves had the same mushy appearance that it had upon entering the stomach. The contents of the pyloric part had a completely different appearance: it resembled thick soup. The contraction waves observed in the pyloric part perform three functions: 1) mixing, 2) grinding, and 3) pushing food into the duodenum. The regulation of the flow of food in small portions from the cardiac part of the stomach to the pyloric part, according to authors who dealt with this issue (Shemyakin), depends on a sphincter located at the border between the cardiac and pyloric parts, which, at its maximum contraction, completely walls off the pyloric part, so that not a drop of liquid passes from the fundic part. Cathcart believes that the normal activity of the prepyloric sphincter has a dual purpose: 1) to prevent the mechanical pressure of food from the cardiac part into the pyloric part, which could interfere with digestion, and 2) to prevent the backflow of digested material, i.e., to form a chamber or cavity in which digestion or grinding could be carried out most economically. During the 4th month of embryonic life, the mucous membrane of the pyloric part of the stomach, according to its villous appearance, the shape of its glands, and the nature of its epithelium, resembles the mucosa of the duodenum much more than the mucosa of the cardiac part of the stomach. Deshin, based on literature data (Cunningham, Paterson, Batuyev) and his own observations, believes that the key to solving the question of the diversity of stomach shapes in man should first of all be sought in the rhythmic movements of the stomach noted in the process of gastric digestion. Having correlated the shapes of the human stomach observed on the corpse with data from physiology and radiology, one must conclude that the normal human stomach, by virtue of its motor activity, cannot have a constant shape during life. The most numerous group of stomach shapes observed on the corpse undoubtedly represents only individual phases of gastric digestion fixed at the moment of death.
If cardiac activity had ceased in a given subject a few minutes earlier, the shape of the stomach on the corpse would also have been different. Since the part of the stomach adjacent to the pylorus plays a particularly important role in the motor activity of the stomach, it becomes obvious that the antrum pyloricum (canalis pyloricus) will have to be encountered in a contracted state particularly often on corpses. In the dilated state, the antrum pyloricum is indistinctly demarcated from the vestibulum and, under certain circumstances, can completely disappear as a part anatomically separated from the vestibulum. If in the last hours of life the stomach becomes atonic and dilated, a corresponding picture will be observed after death. Since the introduction of formalin into anatomical practice, the motor phases of gastric digestion have begun to be encountered more frequently on the dissection table. This depended, firstly, on the fact that formalin, being an excellent fixative, directly fixed individual motor phases, and secondly, on the fact that, by preventing putrefaction processes, it hindered the development of gases in the stomach that stretched its walls and thus changed the shape of the stomach already post mortem. With maximal uniform relaxation of the walls, for one and the same stomach, the shape must be constant and have that appearance which is inherent in the stomach by virtue of its own anatomical structure and which is the starting point for its transient contractions. This shape, from which all others can be derived, Wernstedt calls the basic shape of the stomach, whereas all transient forms he calls functional forms. An excised stomach, placed in appropriate conditions, performs movements (Hofmeister, Schütz). Magnus believed that the rhythmic movements of the stomach and intestines are caused by the presence of Auerbach's nerve plexus, however, Alvarez, based on his experiments as well as observations of other authors, resolutely speaks in favor of the myogenic nature of these movements, since strips devoid of nerve plexuses could produce rhythmic movements. In the stomach, peristaltic contractions are observed, beginning in the region of the esophagus and proceeding towards the pylorus, while some waves disappear, and others cause corresponding contractions of the pylorus. The peristaltic wave propagates in such a way that from above the irritated place contracts, and below relaxation occurs; at the next moment, the wave of contraction passes to the muscles that were in a state of relaxation, and the places lying even further relax. This creates conditions for the movement of semi-liquid food masses. Both peristaltic and antiperistaltic waves, approaching the corresponding sphincters, cause them to relax. If the animal is starving, one can observe at times periods of strong motor activity of the gastrointestinal tract. From time to time, after 1 hour - 1 hour 20 minutes, periods of strong movements of the stomach and intestines begin, accompanied by the expulsion of bile from the biliary tract, the so-called "periodic activity" of the digestive tract, to which Boldyrev (1904) drew special attention, but which was noted much earlier (Morat, 1882; Rossbach, 1890 and others). Rossbach already associates the sensation of hunger with movements of this type. Irritation of the oral cavity with solid food (for example, eating bones) causes a reflex contraction of the prepyloric sphincter, so that the fundic part is separated from the pylorus. In addition to the oral cavity reflex, the prepyloric sphincter can also close from irritation on the part of the duodenum, for example by fat (Orbeli and Khozroev). In addition to the independent motor functions of the stomach and intestines, their work is regulated on the one hand by the vagus nerve (motor nerve), and on the other by the splanchnic nerve (inhibitory nerve). The study of the motor function of the stomach is conveniently carried out using X-rays after giving gruel with bismuth or barium salts. Finally, the motor function is studied by means of balloons connected to a recording device. In dogs, fistulas are applied in different places for this purpose, through which it is convenient to introduce these balloons; in humans, thin probes with a pear-shaped bulb at the end are introduced into the stomach and duodenum, which records pressure changes. Some questions are conveniently studied after the application of fistular tubes into the stomach and duodenum. Infusion into the stomach can be accompanied by infusion into the intestines, and then a significant slowdown in stomach emptying occurs. This method demonstrated the retarding effect of fat (Lintvarev) and acid (Serdyukov) on the passage of stomach contents into the intestines. High acidity in the duodenum likewise not only delays the transition from the stomach into the intestines, but usually causes regurgitation of duodenal contents into the stomach. In general, with fatty food, regurgitation is a constant phenomenon. 0.5% HCl poured into the stomach is partly neutralized by the regurgitation of alkaline intestinal juices and only then begins to quickly leave the stomach; upon ligation of the pylorus, the change in reaction occurs very slowly and imperfectly, since alkaline juices cannot regurgitate into the stomach here. Curiously, a stomach pouch isolated according to Ivy and Farrell, devoid of nerve connections, nevertheless has independent movements, which disappear after the introduction of fat into the main stomach. Here there seems to be some kind of humoral inhibition mechanism. The symptom of a coated tongue in case of stomach disorders should be noted. Kost gave such patients lycopodium in cachets and the next day could find its spores on the tongue, so that the coating is a consequence of reverse movements of the stomach. The mixing of food from different meals in the stomach occurs quite imperfectly. If a rat is given 3 meals stained in different colors and then killed, frozen, and a section is made through the stomach, it will turn out that the first portion surrounds the stomach at the periphery, the third near the esophagus, and the second between them (Grützner).
A. Deshin, V. Savich. III. Methods of stomach investigation. The methods of investigating the stomach can be subdivided into the following categories: 1) logical deductions from the patient's complaints and history, 2) physical methods of investigation—inspection, palpation, percussion, auscultation, 3) functional investigation using thick and thin tubes, 4) chemical, physico-chemical, and microscopic investigations of the gastric contents, 5) gastroscopy (see), 6) X-ray diagnostics. A thorough analysis of the patient's complaints and anamnesis often makes it possible, if not to make a diagnosis, to come very close to it. Keeping always in mind the physiological scheme of the stomach's work, an experienced physician will correctly evaluate fasting vomiting of food taken the previous day, bloody vomiting, sour eructations, the nature of pains, and similar symptoms, and on the basis of these data will often be able to make a presumptive diagnosis. Inspection of the epigastric region in the recumbent and standing positions frequently yields valuable results: with thin abdominal integuments, mainly in asthenics, as well as in young children and in severely emaciated individuals, in cases of gastroptosis, one can see the contours of the bloated stomach as a whole or the contour of the greater curvature, or peristaltic waves. With an empty stomach during intractable vomiting or esophageal obstruction, a characteristic diagnostic depression in the epigastric region is observed. In the standing position of the patient with gastro- and enteroptosis, there is a depression of the abdominal region above the umbilicus and a protrusion and sagging of the region below the umbilicus. Pathological movements in the stomach area occur in the direction from the fundus of the stomach to the pylorus and more rarely—reverse antiperistaltic movements (e.g., in high degrees of pyloric stenosis). Pathological movements of the stomach are especially clearly visible in neuropathic children and most often with pylorospasm and stenosis in young children. Here also belongs the peristaltic unrest described by Kussmaul and a special kind of spasmodic contraction of the stomach according to Boas (see below). Palpation. Superficial (exploratory) palpation of symmetrical areas can reveal painful points, tension of a certain muscle area, or a stomach tumor (with a thin, flabby abdominal wall). Deep palpation (with bent legs or with a raised pelvis with a deep position of the head and upper body) has been especially developed by Russian clinicians (Obraztsov, Hausmann, Strazhesko). The method of gliding palpation with four more or less bent fingers of one hand, with both hands, or, in bilateral palpation, with two hands, makes it possible to palpate the large curvature in the form of a "step." With a dropped stomach, on the spine itself in the form of two steps one can feel both curvatures, and 10–12 cm to the left and right of it during deep breathing of the patient in the form of an "arcuate ridge" to trace the greater curvature (Hausmann in 45%, Strazhesko in 50–60% of all examined patients in general). The normal pylorus is often accessible to palpation (Obraztsov, Hausmann, Strazhesko) immediately behind the right rectus muscle at various heights from the level of the umbilicus; sometimes the antrum pyloricum is also palpated. Especially with a dropped stomach, the pylorus is often palpated in the form of a seal either of a round shape, the size of a hazelnut, or oblong, in the form of a rifle bullet. Upon relaxation of the contracted pylorus during palpation, fine murmurs are felt under the fingers, resembling the squeak of a mouse (Obraztsov). The pylorus periodically relaxes and then tightens again. The tightening lasts 40–50 seconds, relaxation 15–30 seconds (Strazhesko). In spasms (ulcer, erosions, increased tone of the vagus nerve), the periods of tightening are prolonged. In atony, contractions of the pylorus occur less frequently. Percussion. Despite the great importance of fluoroscopy, percussion has not lost its significance in determining the position, size, and shape of the stomach. The lower, upper, right, and left boundaries are determined with the patient in the supine position. The lower border, where the low, loudly resonating sound of the stomach is replaced by a higher and less resonating sound of the colon, is determined by quiet percussion. Obraztsov recommends performing it with one finger (Fingerperkussion according to Boas). If the percussion border is unclear, 1 liter of water is introduced into the fasting stomach (Piorry, Penzoldt) or sequentially ¼ liter and at short intervals twice more ¼ liter (Dehio). In the latter case, the dull strip formed at the border of the stomach and colon will expand upward if the tone of the stomach musculature is in good condition; with atony, the dull strip will shift downward. In some cases, the stomach should be inflated through a tube inserted into it using an inflation bulb or by having the patient successively drink a solution of tartaric acid (2.0 in half a glass of water) and immediately after that sodium bicarbonate (2.0 in half a glass of water). Often in this case, with thin abdominal walls, one can see the contours of the stomach, its shape, and check the boundaries by percussion. Normally, according to Obraztsov, the lower border of the stomach in the recumbent position is located above the umbilicus, at the border of the lower and middle thirds of the distance between the umbilicus and the xiphoid process. Auscultation in the study of the stomach does not play a significant part. Still, in some cases it is possible to apply it not without use. If one listens during swallowing to the stomach under the xiphoid process or behind at the level of the 10th thoracic vertebra, 2 sounds are heard: the 1st, immediately after swallowing, has the character of a noise formed when fluid is pushed with force through a space containing air [Durchspritzgeräusch according to Meltzer, primäres Geräusch according to Ewald]; after 1–2 seconds, a 2nd sound is heard, less clear and sonorous. The second sound is more constant than the first. In some cases, both may be absent. With esophageal strictures, the 2nd sound can be delayed by 50–60 seconds and has the character of a jerky noise observed when fluid passes with a murmur through a narrowed opening. Auscultatory percussion. Even Laennec in studying the delimitation of cavities in pneumothorax recognized the value of combining auscultation and simultaneous percussion. At a later time, auscultatory percussion again attracted attention (Henschen, Runeberg) and was used to delimit cavities containing air or fluid, and parenchymatous organs, in particular to delimit the stomach from the large intestine, to delimit the part of the stomach covered by the liver from the free part, etc. The technique is as follows: to delimit the lower border of the stomach from the large intestine, a stethoscope is placed below the left costal arch, in the place of the anatomical projection of the part of the stomach not covered by the liver, then one percusses quietly with one finger (according to Obraztsov) or strokes with the tip of the index finger (Friction auscultation) down to the transverse line through the umbilicus and to the right beyond the midline. The auscultated sound when passing from the stomach area to the colon instead of clear tympanic becomes duller. The method is applicable in individuals with a thin abdominal wall. Large fat deposits, sharply tense musculature often exclude the possibility of its application. Functional investigation of the stomach using thick and thin tubes. Investigation using a thick tube has the purpose of determining the state of the secretory and motor functions of the stomach. For this, first of all, the stomach contents are examined first on an empty stomach, and then after a test breakfast by Boas-Ewald, consisting of 35 g of bread and 2 glasses of tea or 400 g of water. Thus, at each examination, the tube is introduced to the patient twice (see below—gastric expression). This method does not provide certainty that the stomach contents have been completely extracted. Meanwhile, by the amount of contents, one can judge both the secretory function of the stomach and the motor, more correctly—evacuation function. One hour after the Boas-Ewald breakfast (and according to other indications after 45 minutes), the gastric contents are evacuated, yielding 120–150 cm3. Figures above and below indicate a pathological deviation. Indirect methods for determining the amount of stomach contents include a number of methods, of which the method of Mathieu-Remond must be considered first. One hour after the test breakfast, the stomach contents are evacuated (portion b), and immediately through a funnel connected to the tube, 200 cm3 of distilled water is introduced; the funnel is repeatedly lowered and raised in order to thoroughly mix the water with the remaining contents. The resulting mixture constitutes the second portion of the gastric contents. The Töpfer reagent is used to determine the amount of HCl (a) in the first portion (b) and in the second (a'). The second portion consists of x [the stomach contents remaining after the evacuation of the first portion (b)] plus q—the amount of introduced water. The acidity of the 2nd portion x+q will be inversely proportional to the amount of added water; hence, from the formula: a : a' = (q+x) : x, one can determine x, which is equal to a · q / (a - a'), and to obtain the entire contents of the stomach, one must add b, i.e., the amount of juice extracted the first time, and the formula will take the form (a · q) / (a - a') + b. Example: one hour after the test breakfast, 50 cm3 with an acidity of 40 was extracted. After the introduction of 200 cm3 of distilled water and rinsing of the stomach, contents with an acidity of 20 were obtained.
If these figures are substituted into the above formula, the total contents of the stomach will be expressed by the figures: The Mathieu-Rémond method has become quite widespread, especially in combination with the Elsner method (see below), and, taking into account the acidity of the gastric contents, makes it possible to evaluate the motor function of the stomach, although, of course, quite approximately. A number of other methods (Sahli, Boas, Fuld, Strauss, Martinet, and others) have not come into general use for a variety of reasons. The Elsner method consists of the following: after determining the stomach contents according to Mathieu-Rémond, the stomach is washed until a transparent liquid is obtained. All the wash water is collected in several graduated cylinders and the liquid is allowed to stand for 24 hours. Normally, the total amount of residue one hour after the Ewald test breakfast is subject to significant fluctuations (30-100 cm3). A residue exceeding 100 cm3 unquestionably indicates motor insufficiency. If the increase in food residues does not run parallel with the increase in the total volume of the residue, then the motor disorders are not accompanied by hypersecretion. On the other hand, an increase in gastric contents without an increase in food residues indicates hypersecretion. The most acceptable from a physiological point of view and practically clinical is the testing of the motor function of the stomach (resp. pylori) and even the degree of its impairment according to the Riegel method or the method of Bourget and Kemp. Riegel gives 400 cm3 of soup, 150-200 g of beefsteak, 50 g of mashed potatoes, and 35 g of roll. Normally, upon aspiration after 7 hours, the stomach should be empty. Kemp gives the fasting patient the following dinner: 250 cm3 of oatmeal soup, 50 g of chopped boiled veal, 4 pieces of bread with butter, 8 boiled plums, and 1 tablespoon of lingonberry compote. If food residues are found in the stomach after 6 hours, there is a decrease in motor function. Examination with a thin tube. Over the past 16 years, some clinics have begun to widely use a thin tube (of the Bondi-Einhorn duodenal tube type) for fractional investigation of the work of the gastric glands, since a number of studies have proved that the maximum acidity may not occur 3/4-1 hour after the test breakfast, but later or (more rarely) earlier. The thin tube provides a fractional "cinematographic picture" of the work of the stomach glands (Figure 24), while the thick tube provides a "photographic snapshot of a single moment of work" (Ehrenreich). The presence of the tube itself in the stomach is not a reason for the manifestation of secretory and alteration of the motor function of the stomach. Zimnitsky, based on experiments from I. P. Pavlov's laboratory on dogs, also attempts to establish types of secretion in the clinic: 1) normal, 2) asthenic, or labile, 3) inert, or torpid. To do this, Zimnitsky evacuates as much of the stomach contents as possible on an empty stomach through a thin tube using a syringe (in 10-20 cm3). Through the same tube, 200 cm3 of warm broth is introduced. Every 15 minutes, a sample of 5-10 cm3 of gastric contents is taken, in which the total acidity is determined by titration with n/10 NaOH solution (indicator: 1% alcohol solution of phenolphthalein) and free HCl by the same method (only using an indicator: 0.5% alcohol solution of dimethylaminoazobenzene). After an hour, all stomach contents are evacuated and 200 cm3 of broth is reintroduced. Then, by quarters of an hour, the same procedure is carried out as in the 1st hour. The figures expressing total acidity and separately free HCl for the 1st and 2nd hours are added up. 1st type (normal): the summary acidity for the 2nd hour is greater than for the 1st, but by no more than 20-30 units. 2nd type (asthenic, or labile): the sum of acidity for the 2nd hour is less than for the 1st hour. 3rd type (inert, or torpid): the figures for the 2nd hour are much higher than those for the 1st (e.g., 60 and 165, 100 and 214). Certain clinical forms of gastric diseases have a definite pathological type of secretion, which returns to normal upon recovery. Age deviations must also be taken into account (see Infant). A good deal of work has been devoted to the study of "subsequent secretion," when it is assumed that the stimulant that caused the maximum work of the glands has been removed and the glands by inertia continue to secrete pure gastric juice. In 1903, Gurevich proposed using the method of determining "subsequent secretion" in the clinic, establishing clinically that the intensity of "subsequent secretion" depends on the degree of preceding secretory excitation of the glands and on the quality of the stimulant (broth, 2% solution of Liebig's extract, Boas-Ewald breakfast, water). Leporsky was the first (1918) to introduce "cabbage juice" into clinical practice as a test breakfast and with its help began to study the chemical phase of juice secretion. After introducing 200 cm3 of cabbage juice into the stomach and a preliminary test after 10 minutes, complete evacuation of the stomach is performed after 25 minutes using a syringe through a thin tube, then evacuation is repeated every 15 minutes until juice secretion ceases. Measurements of each portion, mucus measurement, and chemical study of total acidity and free HCl are performed. Normally, for the former, 60-40, and for the latter, 40-20 cm3 of n/10 NaOH solution is considered standard. Since the introduction of the thin tube for fractional investigation of stomach work, the problem has arisen (Ehrenreich; 1912) regarding the various types of secretory curves in individual individuals and in various diseases depending on a specific stimulus. As test breakfasts, the following were used: the Boas-Ewald breakfast or oatmeal (Rehfuss), the alcohol breakfast according to Ehrmann (introducing 300 cm3 of 5% ethyl alcohol and evacuating after 30-45 minutes), or the caffeine breakfast (Katsch and Kalk), and others. Despite many objections, besides the Boas-Ewald breakfast, certain others deserve attention, such as the alcohol and caffeine breakfasts (Coffeini puri 0.2, Aq. destill. 300.0, and 4 drops of 0.5% Methylenblau solution). Extraction of contents of 10 cm3 after the test breakfast is performed every 10 minutes (2-21/2 hours) as long as secretion is obtained. Rehfuss gives various types of secretory curves: 1) normal curve, if the maximum secretion is observed after 60 minutes, and in the following 60 minutes secretion ends; 2) hyperacid form, if after 60 minutes secretion reaches a higher acidity than normal (above 60% per n/10 NaOH solution); 3) persistent hyperacid form, if secretion reaches a maximum after 60 minutes and remains high for a long time; 4) masked hyperacid form (larvierte Hyperacidität), when the curve gives a maximum rise after 30 minutes and rapidly falls; 5) hyperacid form creeping upward with remissions (Klettertyp), characteristic of duodenal ulcer (Figure 25). Sometimes gastric juice secretion is observed in cases of anaciditas only after the introduction of 0.5 mg of histamine (Katsch and Kalk) intramuscularly. The method of chromoscopy, proposed in the clinic by Glassner and Wittgenstein, has greatly helped in the study of types of secretion. 4 cm3 of a 1% aqueous solution of neutral red is administered intragluteally on an empty stomach. A normal stomach excretes the dye through the mucosa within 12-15 minutes with the gastric juice. With increased HCl secretion, neutral red excretion occurs in 8 minutes; with decreased secretion, in 25-45 minutes; with achylia, neutral red is not excreted at all. Luria and Mirkin, applying the combined method of studying curves after a caffeine breakfast and chromoscopy, deepened the differential diagnosis of various forms of gastric secretory disorders. Examples of typical curves of gastric secretion during a caffeine breakfast and a caffeine breakfast with subsequent administration of histamine can serve as the presented curve samples (Figure 25). Evacuations after breakfast were performed every 10 minutes. Levin proposed a method that makes it possible to account for the amount of secreted juice and the amount of gastric contents evacuated into the intestine. Phenol red is introduced into the test breakfast.
Every 15 - 20 minutes, the amount of gastric contents is measured by its complete extraction and re-infusion through a tube. By colorimetric examination of all left-over portions, the quantitative remainder of the test breakfast and secretion in the stomach at separate moments is determined. Using formulas, secretion, evacuation, and absolute acidity are calculated. Despite the widespread development of fractional investigation methods with a thin tube, the thick tube and the Boas-Ewald test breakfast have not lost their significance. Macroscopic, chemical, and microscopic examinations of gastric contents. In addition to accounting for the gastric contents on an empty stomach and after a test breakfast, already macroscopically in some cases a whole range of properties (layering of gastric contents) and pathological impurities can be seen: mucus, blood, bile, pus, pieces of tissue, food remains. In some cases, an unpleasant odor of decomposing contents (H2S) is mixed in. All these signs are characteristic of one or another clinical form of a stomach disease. Macroscopically visible remains of bread, poorly comminuted, with a low content of liquid secretion, indicate a violation of secretory function and poor chemical processing of the test breakfast. Normally, on an empty stomach, the stomach is empty or contains a small amount of juice and mucus, amphoteric or weakly acidic to litmus reaction. A large amount of mucus (more than 40 cm3 on an empty stomach according to Kutner) indicates catarrhal changes in the gastric mucosa. Mucus is a means of defense. The lack of the ability to form it presents the picture of a disease of the gastric mucosa—amyxorrhoea gastrica (Kaufmann). Mucus is characterized by certain external features and stringiness when pouring the gastric contents from one vessel to another. In myxorrhoea gastrica, or gastromyxorrhoea, a particularly large amount of mucus comes to the fore. Vomiting of bile and large amounts of bile in the gastric juice can constantly occur with a narrowing of the descending part of the duodenum. Bile, frequently regurgitated along with duodenal contents into the stomach during a test breakfast, distorts the secretion picture, sharply lowering the acidity of the gastric secretion. Chemical examination of the gastric secretion obtained by a thick tube is performed on an empty stomach after a test breakfast and in some cases 3 hours after a test meal (at the height of digestion). When examining with both the thick and thin tubes, the main significance is the chemical determination of total acidity and the amount of free hydrochloric acid. HCl is first determined qualitatively: the turning blue of a Congo paper moistened with gastric juice, the cherry-red coloration when heating on a porcelain cover of contacting drops of juice and Günzburg reagent, the reddening of gastric juice upon adding 1-2 drops of a 0.5% alcohol solution of dimethyl-amido-azobenzene, Töpfer's reactions, and finally the sharp reddening, ruby-red coloration of a yellowish-brown Tropaeolin 00 solution upon adding gastric juice containing free HCl to it—all these signs characterize a positive reaction for HCl. By the intensity of the coloration of the Congo paper, one can also approximately judge the amount of HCl: an insignificant content of HCl gives a grey-blue coloration, normal content—a violet-blue, exceeding normal—an intensely blue. All the above-mentioned reagents, characteristically reacting to the presence of free HCl, do not act indifferently towards other components of the gastric juice, such as, for example, acid phosphates under normal conditions, lactic and acetic acids under pathological conditions. According to Boas, the reagents that take on a characteristic coloration only from the presence of free HCl include Günzburg's reagent and Boas's reagent (Resorcini resublimati 5,0, Sacchari albi 3,0, Spirit. diluti ad 100,0). When drying by heating on a small flame in a porcelain dish 5-6 drops of gastric juice containing free HCl with 3-5 drops of Boas's reagent, after complete drying, a pinkish and even more intense—up to cinnabar color—tint is obtained, which gradually disappears upon cooling. Before determining the amount of free and bound HCl, the presence of organic acids (lactic, butyric, and acetic) formed in the stomach during fermentation, most often in motor insufficiency or stasis due to impaired pyloric patency (neoplasms, catarrhs), should be excluded. To exclude lactic acid entering the stomach with meat food, milk, sour milk, sauerkraut, etc., Boas recommends (especially if food given the day before is found in the portion of gastric contents on an empty stomach) washing out the stomach in the evening and giving Knorr's oatmeal soup with salt (up to 1 l), pumping out the contents in the morning and examining it for lactic acid. For practical purposes, it is usually sufficient to examine after the usual test breakfast. The simplest method for determining lactic acid is to use the Boas or Uffelmann test. The remaining organic acids, such as butyric, acetic, valeric, formed during sharply expressed decomposition processes in the stomach, most often during prolonged food stasis, are easily driven off by heating, and in the vapors of a test tube with a characteristic odor, litmus paper turns red. Isolated qualitative determination of these acids has no clinical significance. The next stage is the quantitative analysis of gastric juice. In the absence of organic acids, as indicated by qualitative analysis, the total acidity of the gastric juice depends on free and bound HCl and to a small extent on acid phosphates. The introduction of physico-chemical principles into the concept of acidity has shown that true acidity, i.e., the amount of free hydrogen ions (pH), can only be determined using the physico-chemical method of concentration cells or the simpler and more applicable in clinical work indicator method proposed by Michaelis and Davidsohn. The method developed by L. Michaelis specifically for gastric juice is as follows: crystal violet is used as an indicator, from which a standard solution is prepared at a dilution of 0.03 per 150 cm3 of water. In 7 test tubes provided with labels indicating pH, n/10 HCl is poured in the following amounts: tube No.
n/10 HCl (cm3) . . 6,35 4,0 2,5 1,6 1,0 0,63 0,4 pH (labels) . . 1,1 1,3 1,5 1,7 1,9 2,1 2,3 Then in each test tube the contents are supplemented with distilled water up to 10 cm3. Into the 8th test tube, or if 2–3 gastric juices are being investigated, into the 9th and 10th, 10 cm3 of gastric juice giving a positive reaction with congo are poured. After then adding 5 cm3 of standard crystal violet solution to all test tubes in a Walpole comparator, the test tube with gastric juice is compared with each of the 7 test tubes; observation in the comparator is performed only with frosted glass. With a scanty amount of gastric juice, it can be taken in half the amount, but should not be diluted. The identity of the color of the test tube containing the gastric juice with one or the other of the 7 test tubes indicates the pH of the gastric juice (indicated on the label). By this method, active H-ions, "true acidity," are determined. Titration with indicators congo, phenolphthalein, dimethylamidoazobenzene, etc., determines the so-called "potential H-ions." In the gastric juice obtained after a test breakfast, part of the HCl is in a bound state; it is neutralized by salts, proteins, peptones, and alkaline contents regurgitated from the duodenum. During titration with n/10 NaOH, the incoming OH-groups cause the release of H-ions and reveal the bound HCl. Thus, titration gives an idea of the sum of "active" and "potential" ions, i.e., what was formerly called total acidity. The amount of so-called bound HCl equals the total acidity minus the "true acidity." During chemical analysis of gastric juice, one should first perform qualitative reactions for HCl and lactic acid and determine the total acidity by titration with n/10 NaOH using phenolphthalein as an indicator. If in the absence of lactic acid 5 cm3 of n/10 NaOH was consumed per 10 cm3 of gastric juice, then 50 will be consumed per 100 cm3 of it, i.e., its total acidity is 50. And since 1 cm3 of n/10 NaOH = 3.65 mg of HCl, 5 cm3 = 3.65 x 5 = 18.25 mg, i.e., 10 cm3 of gastric juice contains 18.25 mg, or 1.825°/00 of HCl. In the absence of free HCl in the stomach, the HCl "deficit" is determined: 10 cm3 of gastric juice is titrated with n/10 HCl with dimethylamidoazobenzene as an indicator until a red color appears, i.e., traces of free HCl. The amount of consumed n/10 HCl in percent indicates the HCl deficit in the given juice. Further, one can determine the so-called free HCl by the described Michaelis indicator method. The use of other indicators during titration, e.g., dimethylamidoazobenzene, will give a somewhat lower figure for total acidity, since dimethylamidoazobenzene changes its color at pH < 7, i.e., in an acidic reaction, while phenolphthalein changes at pH > 7, i.e., in an alkaline reaction. Of the three enzymes of the stomach—pepsin, rennet, and lipases—methods for determining the first two are of clinical importance. - Mett's method: raw chicken egg white is drawn carefully without air bubbles into glass tubes 1–2 mm in diameter, the tubes are immersed in a beaker of boiling water, the protein coagulates, and the tubes can be used for the experiment. They are kept in a cylinder with glycerin. In experiments, pieces 2 cm long are immersed in a small beaker with 3–5 cm3 of gastric juice (acidified with HCl if the congo reaction is negative) and placed in a thermostat for 24 hours after adding 3–5 drops of toluene. After 24 hours, the length of the digested protein in millimeters is measured. In healthy individuals, 6 to 12 mm are digested. There are also other methods (Gross with casein, Fuld-Levison with edestin, Jacobi-Solms with ricin, etc.). Labferment is sufficiently determined qualitatively by Leo's method: 5–10 cm3 of milk (raw or boiled) is mixed with 3–5 cm3 of gastric juice and heated in a water bath at 37° for 10 minutes; if the enzyme is present, coagulation occurs after 10 minutes. A quantitative method has also been proposed by Fuld and Blum (Fuld, Blum). - Blood in the gastric juice is often determined already macroscopically. A bright scarlet color of blood or one resembling coffee grounds is characteristic of ulcers of the stomach, on the one hand, and of an ulcerating carcinomatous tumor, on the other. The microscopic picture makes it possible to judge small bleedings, invisible to the naked eye, by the presence of erythrocytes. The determination of occult hemorrhages of the stomach by chemical reactions for blood requires, first of all, a milk or vegetable diet. The examination of gastric contents after a test breakfast and vomiting should be supported by repeated, careful examinations for blood in the stool. The main chemical methods for determining occult hemorrhages in the gastric contents are the same as in the examination of stool: Weber's guaiac test (see), its modification by Schumm, the same by Boas, the benzidine test (see), etc. Microscopic examination of the contents of the stomach on an empty stomach and after a test breakfast. In both cases, one can encounter a greater or lesser amount of mucus, epithelial cells, erythrocytes, leukocytes (or their nuclei), food remnants, tissue fragments, bacteria, yeast fungi. The data obtained by this method and summarized with the general picture of the state of the stomach can be of very great importance. For example, the finding of Boas-Oppler bacilli in hypo- or achlorhydrias, the finding of specific cells in neoplasms, the detection of sarcinae are very characteristic of certain clinical forms. The so-called long Boas-Oppler bacilli during stagnation phenomena in the stomach (pyloric obstruction, atonia in carcinoma) produce lactic acid, causing lactic acid fermentation of sugar. They are characterized by their shape and intense light refraction. Sarcinae in the stomach occur either in the form of regular commercial bales or in the form of shapeless clusters of individual spheres. They belong to plant organisms (cellulose reaction). They are found in the stomach during stagnation, but in the presence of HCl, both in hypo- and hyperacidities. They are absent in carcinomatous achylia (Boas). Along with sarcinae, yeast fungi can also be encountered in every gastric juice: shiny, oval, double-contoured, either as individual specimens or in the form of chains connected to each other. They are especially numerous when gastric contents are retained. - Urine and stomach functions. Indirect methods for assessing the motor and secretory functions of the stomach include counting the amount of urine and determining pepsin in the urine. With water retention in the stomach (dilution, pyloric obstruction, atonia), the amount of urine per 24 hours can be below 500 cm3 (severe impairment of the evacuation capacity of the stomach); with an amount of urine from 500 to 1,000 cm3 per 24 hours—moderate impairment (Boas). The absence of pepsin in the urine is characteristic of achylia and often of stomach cancer. The test for pepsin is performed according to the method of Fuld and Hirayama with edestin.
A. Korkhov. Pumping of the stomach, evacuation of gastric contents using a tube. The method of pumping with a soft tube was introduced into medicine more than 50 years ago by Oser and Ewald; the hard tube is considerably older, but is currently not used. Technique: a thick rubber tube with a diameter of 12–14 cm (on the thin tube see above) with a moistened end is introduced into the mouth to the root of the tongue; the patient is asked to keep the head slightly tilted downwards and make several swallowing movements, during which the tube is advanced past the epiglottis, which at this time closes the entrance to the larynx; further, the tube is pushed without the help of the patient to a depth of 50–60 cm,
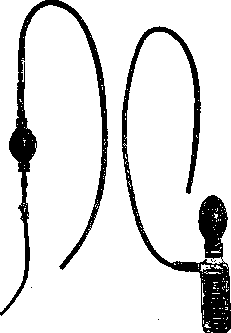
Figure 26.
and with the help of light movements of the tube, a siphon is established. Before introducing the tube, the patient's dentures should be removed (if any). With sufficient skill, the entire procedure takes only a few minutes and is easily tolerated. When

Resorting to cocaine application to the mucous membrane of the pharynx is necessary only in exceptional cases—with severe irritation of the nasopharynx or phenomena of spasmophilia. Sometimes, during the backward withdrawal of the tube, a strong spasm of the musculature of the esophagus or pharynx is observed—then one should introduce a little warm water through the funnel to relax the spasm. Usually, after introducing the tube, it is sufficient to make the patient tense the abdominal press so that the contents of the stomach begin to come out through the tube ("expression"). For the complete evacuation of all contents, a glass jar with an aspiration bulb can be attached to the tube (Fig. 26). Too energetic aspiration can lead to the suction of the stomach wall and even to slight injury of the mucous membrane. The rubber bulb proposed by Kuttner, which is attached to the tube already after introduction into the stomach, is very appropriate (Fig. 27). Application: 1) for diagnostic purposes to examine the stomach contents on an empty stomach or after a test meal, 2) therapeutically: a) for phenomena of stagnation in the stomach, fully replacing the washing which is more tiring for the patient or preceding it, b) for acute poisonings to remove poison from the stomach followed by washing.—Contraindications: gastric hemorrhages, severe heart diseases, aortic aneurysm, severe hypertension, angina pectoris, severe arteriosclerosis, and severe weakness of the patient. However, in acute poisonings, a severe state of the heart cannot serve as an obstacle to removing the poison with a tube.
J. Lorio. X-ray examination.—The stomach does not differ from surrounding parts in its ability to absorb X-rays. When transilluminating the abdominal cavity without preparation, only the gas bubble in the upper section of the stomach and accidental accumulations of gases in the intestine are visible. When inflating the stomach with air, its image can be obtained in the form of a light area. This method, however, is rarely used, because it yields comparatively little. Systematic development of the study of the stomach with X-rays began since the time Rieder introduced filling the stomach with a mush mixed with bismuth (Bismuti subnitrici 30.0 per dose). Cases of poisoning forced the transition to harmless bismuth carbonate, while at present, mainly a mush mixed with barium sulfate (Barium sulfuricum)—an insoluble, extremely stable compound which passes without being absorbed in an unchanged form throughout the entire gastrointestinal tract—is used. In view of the high toxicity of soluble barium salts, absolutely pure preparations are necessary; the usual dose is 50.0–100.0 and more per dose. When using these heavy metal salts, a dark image of the organ filled with them is obtained during transillumination. The advantage of Rieder's method is its approximation to physiological conditions. With this methodology, the image is obtained not of the organ itself, but of the contrast mixture filling its cavity, bounded consequently not by the serous, but by the mucous membrane. When the subject takes the contrast mixture, it can be gradually observed how it accumulates first in the upper section of the stomach in the form of a triangle with its base directed upward and located directly below the gastric bubble (Fig. 28-1). This triangle gradually lengthens downward and to the right, and subsequently the rounded contour of the lower section of the stomach begins to be gradually outlined. According to Forssell's works, the shape of the stomach is determined by the architecture of its musculature, forming an arch at the top, and below—the body of the stomach, pocket, and canal: fornix, corpus, sinus, and canalis. Corresponding to the muscular fibers of the pylorus, a light strip is visible during transillumination between the accumulations of the contrast agent in the stomach and in the duodenum. Since the shape of the stomach is determined by smooth muscle with variable tone, it cannot be constant. Even in the same subject, the silhouette of the stomach in the form of a bull's horn (the normal type of stomach according to Holzknecht; Fig. 28-2) can turn into the shape of a hook (the normal type of stomach according to Rieder). Between the latter and the elongated stomach in ptosis (Fig. 28-3) there exist a whole series of transitions. The position and shape of the stomach are influenced by its filling, muscle tone, organs surrounding the stomach, the standing of the diaphragm, intra-abdominal pressure, and peritoneal ligaments. According to radiological research data, the stomach of infants is located horizontally depending on a lower transverse diameter of the chest that is wider than in adults and the abundance of gases in the intestine under the stomach. Since the stomach itself contains a lot of air, it is well visible even without a contrast agent. In children older than one year, the vertical position already prevails (see separate table, Fig. 1). Functional moments are of no less importance than purely anatomical ones. For this reason, the constitutional types of the stomach—a high transversely located stomach in the form of a horn in a pyknic, an elongated, vertically located stomach in the form of a hook in an asthenic—do not differ in constancy. The influence of the autonomic nervous system on the shape of the stomach has been proved experimentally both by direct irritation of nerve trunks and pharmacologically. Irritation of the vagus nerve increases the tone of the stomach, and irritation of the sympathetic nerve decreases it. A hypertonic stomach appears in the form of a narrow tube, with the cardiac part somewhat expanded and the pylorus gaping (Fig. 28-4). Such a state is observed in neuroses, in lead colic, and sometimes in tabetic crises. Conversely, with lowered tone, the stomach appears in the form of a flabby sack (see separate table, Fig. 5). Food taken into such a stomach immediately drops to the bottom, locating in a semicircle with the upper horizontal level below the navel (Fig. 28-5). Such a state is a sign of impaired compensation of the musculature in pyloric stenosis, but can also be caused by a number of functional moments; thus, it is observed after taking large doses of morphine. A valuable sign of stomach dilation is the displacement of the pyloric part to the right, with the described semicircular shadow located in the middle and not on the left, as with pure ptosis. With simple prolapse of the stomach, there are no disorders of motor functions. However, intra-abdominal pressure also affects the tone of the stomach, therefore, when the abdominal press relaxes, both the prolapse of the stomach and a decrease in its tone are observed. Both in hyper- and in hypotonia of the stomach, there are gradual transitions from barely noticeable tone disorders to a pronounced vivid picture (Fig. 28-4 and 5).
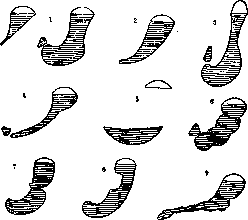
Fig. 28. Diagram of stomach shapes: 1—gradual filling of the stomach of the Rieder type; 2—stomach of the Holzknecht type; 3—prolapse of the stomach; 4—increased stomach tone; 5—atony of the stomach; 6—segmenting peristalsis; 7—ulcer of the lesser curvature; 8—cancer of the lesser curvature; 9—scirrhus of the stomach.
Peristalsis is expressed by the fact that wave-like indentations appear along the greater and lesser curvature, which glide toward the pylorus (Fig. 28-6). One wave follows another; with an open pylorus, they lead to the transition of food into the duodenum, and with a closed one, they are important for mixing food. When peristalsis is enhanced, these indentations are especially deep. They begin near the cardia and quickly follow one another, as a result of which a real segmentation of the stomach appears. With sharply increased tone, peristalsis is weakly expressed, and with hypo- and atony, it is often increased. Such a combination of increased peristalsis with lowered tone is often observed in pyloric stenosis and should be considered as a compensatory phenomenon (see separate table, Fig. 6). After 3-4 hours, when a normal stomach would have already emptied, a significant residue with the described signs of atony is still determined in it in such cases. Another valuable sign of pyloric stenosis is...

Figure 1. Normal stomach of a child. Figure 2. Folds of the mucous membrane of a normal stomach.
Figure 3. Mucous membrane of the stomach (folds deformed). Figure 4. Gastrospasmus. Figure 5. Atony of the stomach (retention). Figure 6. Pyloric stenosis (segmented peristalsis). To the article Shemdok. peristaltic waves are observed moving in the opposite direction—the so-called antiperistalsis. Both the tone and peristalsis, as well as the related evacuation of the stomach, are influenced by a number of purely functional factors. Peristalsis can be enhanced by massage of the stomach region, repeated tension and relaxation of the abdominal wall. Morphine sharply delays stomach evacuation. With high acidity, gastric evacuation is slowed down; with low acidity, it is accelerated. A direct sign of hypersecretion is the so-called intermediary zone between the upper level of the contrast medium and the air bubble in the cardiac part. It must be kept in mind that a similar zone is obtained even in the absence of secretion if a rapidly settling contrast powder with liquid is used. In the diagnosis of organic diseases of the stomach, it is necessary to distinguish direct signs caused by anatomical changes and indirect ones associated with impaired function (Fig. 28-#). The latter include limited persistent spastic retraction of the greater curvature at the level of the ulcer on the lesser curvature. A direct sign of an ulcer is the protrusion of the wall, the so-called niche sign. A sign of cancer is a filling defect (Fig. 28-8). A neoplasm protruding into the stomach cavity fills it partially, so that the contrast medium cannot settle in this place. Scirrhus, infiltrating the wall, leads to the cessation of peristalsis in a limited area or—with large distribution—turns the shadow of the stomach into a narrow, irregularly bounded strip (Fig. 28-9). After taking a small amount of the contrast mixture, if it gradually flows down along the folds of the mucous membrane or is distributed in a thin layer over the surface due to kneading of the stomach region, an image of the relief of the mucous membrane can be obtained. The clearest pictures are obtained after taking a small amount of barium sulfate in a thick solution of Gummi arabici. Here too, rather unstable pictures are obtained in connection with the motor function of the muscularis mucosae (see separate table, Figs. 2 and 3). Under normal conditions, regular longitudinal folds are visible; in some cases of gastric catarrh, a peculiar spotty pattern is obtained (état mamelonné); in mucosal atrophy, an uneven distribution of barium over the surface without clearly expressed folds. This new method is apparently destined to play a major role in the early diagnosis of ulcer and cancer of the stomach. For a complete X-ray examination of the stomach, both fluoroscopy and radiographs are needed; the former mainly for studying motor function (roentgenocinematography was also used with complete success for this purpose), the latter for a more accurate depiction of details. In the clinic of gastric diseases, the X-ray method is currently indispensable; the signs of organic diseases obtained by it are of great diagnostic importance, although X-ray data do not always coincide with pathologico-anatomical ones. Data on motor function have opened new broad horizons. Thus, they pointed to the importance of local spasms (see separate table, Fig. 4) in organic diseases of the organ itself (cancer, ulcer—the spasmogenic theory of gastric ulcer, according to Bergman) or neighboring ones (stomach spasm in biliary colic, enhanced stomach peristalsis in duodenal ulcer, etc.). X-ray observations are also of great importance for the doctrine of vegetative neuroses (sympathicotonia and vagotonia or disturbed balance between the two systems according to newest views), their connection with organic diseases of the central nervous system (tabes), with intoxications (opium, lead), with psychological factors, with constitutional signs (hypotonia with ptosis in asthenics). O. Den. IV. Motor and secretory disorders of the stomach. Pathology of the motor function of the stomach. Corresponding to the two main types of the motor function of the stomach—the function of the so-called peristaltic and the evacuation function (motor in the narrow sense)—their pathological impairment can also be twofold. The first group of disorders includes: atony, respectively hypotonia, hypertonia of the stomach, and its spasm. The second group includes those disorders in which the movement of the stomach suffers due to damage to the motor mechanism of the entire stomach or its parts—cardia, body, and pylorus. By the name of atony, respectively hypotonia of the stomach is understood a state of absence or weakening of the peristaltic function of the stomach, respectively the tonic function of its musculature (Stiller), i.e., a state of inability of the stomach wall to tightly enclose the contents in the stomach, while the evacuation and motor capacity of the stomach is thereby reduced (more often), but may remain usual, and in a number of cases even increased. Atony of the stomach can lead to, respectively be accompanied by, a weakening of the supporting apparatus of the stomach, as observed in gastroptosis and splanchnoptosis, as well as a decrease in the elasticity of the stomach wall; atony of the stomach can also develop due to a disorder of stomach innervation in general nerve weakness, in states of general hypotonia, in the presence of general constitutional weakness or without it, in a general decline in nutrition; it can be observed further in infectious diseases (such as typhoid, dysentery) and in other exhausting diseases accompanied by adynamia, as well as in a number of organic diseases of the stomach. Since stomach atony is more often observed in gastroptosis, the clinical picture is similar to that in gastroptosis. Stomach atony is established precisely only by X-ray examination, in which, in the case of stomach atony, it is determined that the contrast food collects in the lower parts of the stomach; the stomach is not only elongated in length, but its sinus part turns out to be wide and low-located; the walls of the stomach in the middle part approach each other, a 'waist' is formed, and the gas bubble has the appearance of an elongated pear. Filling of the stomach occurs in such a way that the first portions of food quickly descend to the lower pole of the stomach and it fills 'from bottom to top.' The determination of the splashing sound is an unreliable method for determining stomach atony. The treatment of atony is similar to that in gastroptosis and asthenic states. The main things are: general strengthening treatment, elimination of dyspeptic phenomena and constipation, prescription of enhanced nutrition, treatment by lying down, general strengthening of the nervous system. The state of increased tone of the stomach wall is called hypertonia of the stomach. Hypertonia of the stomach can be observed with increased excitability of the nervous system, both general and in particular the nervous system of the stomach or other organs of the abdominal cavity. It occurs in biliary and renal colic, in stomach ulcers, in general nervous increased excitability, in lead and nicotine poisoning, etc. In the presence of stomach hypertonia, upon X-ray examination, the stomach assumes a more transverse position, is pushed further to the right, its greater curvature approaches the anterior abdominal wall and has a sharply pronounced horn shape, the pyloric part appears narrower than the cardiac part, and upon filling with contrast food, greater resistance is observed than usually happens with normal stomach tone. Often in the presence of hypertonia, a picture of increased motor excitability of the stomach is observed in the form of enhanced peristalsis, enhanced evacuation, and in particular phenomena of spasm. Phenomena of altered secretion (hypersecretion, hyperchlorhydria, etc.) may be added to this. Some forms of organic lesions of the stomach (scirrhus, linitis plastica, shrunken stomachs, e.g., after acid poisoning, in syphilis) upon fluoroscopy can give a picture largely resembling simple stomach hypertonia. In such cases, prolonged observation, repeated X-ray examination, and the use of atropine make it possible to differentiate organic organ reduction from the functional state of increased stomach tone. The highest degree of enhancement of stomach tone is represented by a state which is called stomach spasm. Stomach spasm is observed in biliary colic, in the infringement of a stone in the ureter, in tabes, in morphine poisoning, both acute and chronic, in intestinal colic, in pancreatitis; stomach spasm can be observed especially often in ulcers of the stomach and duodenum, as well as in inflammatory processes in their surroundings, in perigastritis; thus, stomach spasm can arise both as a result of local irritation of the stomach and as a result of the so-called 'viscero-visceral reflex' (Bergmann). Stomach spasm can be 1) partial, 2) regional, 3) complete. In partial spasm, only a small limited part of the stomach musculature is involved, as observed, for example, in stomach ulcer, in perigastritis. An example of regional spasm can serve as the complete contraction of the entire pyloric region, which is observed with superficial ulcerations either in the pylorus itself or near it. Regional spasm can also capture the entire body of the stomach, which is observed when the ulcer is located in the corpus ventriculi. Complete spasm, capturing the entire stomach as a whole, has been observed in poisonings, in tetany (Walvogel, Schwarz).
Depending on its duration, gastric spasm can be either prolonged or intermittent. In a number of cases, it proceeds without any subjective sensations, but more often it is accompanied by attacks of pain of varying intensity. The diagnosis of gastric spasm is established by X-ray examination. The treatment of gastric spasm reduces to the treatment of the underlying disease that caused the spasm, e.g., gastric ulcer, gallstone disease; as a symptomatic treatment, atropine (0.0005-0.001) or Papaverin (0.04) is prescribed subcutaneously or intravenously. Motor disorders in the proper, narrow sense of the word can be various depending on the nature of the affected function and the site of the lesion of the stomach. Regarding localization, the disorder may affect the entire stomach as a whole or only one or another of its parts, e.g., the cardia or the pylorus. The main types of motor disorders of the stomach reduce to the following. 1. Disorders associated with a disturbance of the activity of the cardia. The most important type of such a disorder is cardiospasm. 2. Disturbances of the motor capacity of the stomach can be expressed in a change in the character of gastric peristalsis. Among such disorders are known: decrease, increase in peristalsis, general contraction of the hypertrophied and dilated stomach (Magensteifung), and its antiperistalsis. - Weakening of peristalsis can be encountered in infectious diseases and states of cachexia, in states of paresis or complete paralysis of the stomach (see below), often in its atonies. In a number of diseases of the stomach, such as cancer of one or another part of the stomach, ulcus callosum, an inflammatory disease around the stomach (perigastritis), various conditions leading to fixation of the stomach, only local, focal weakening and decrease of peristalsis are observed. - With an increase in gastric peristalsis, fluoroscopy reveals an increased frequency of peristaltic waves, an increase in their size up to the formation of functional constrictions ("segmenting peristalsis"), and an acceleration of the movement of the waves. Strengthening of peristalsis of the entire stomach can be observed in healthy individuals during severe hunger, in neuropathic conditions, and chiefly in the presence of an obstacle to the emptying of the stomach, e.g., in pyloric spasm, ulcers of the stomach or duodenum, cancer thereof, pericholecystitis, and the like. - When the obstacle to emptying reaches a high degree, a disturbance of coordination and a sharp increase in peristalsis occur with enhanced tonic contraction of the musculature of the entire stomach, accompanied by an attack of pain - the so-called Magensteifung appears. In this condition, most often associated with dilation and significant hypertrophy of the gastric musculature, there is a significant bloating of the gastric region of a dense consistency with peristaltic waves slowly running across it. - In severe pyloric stenoses, antiperistalsis may be observed, i.e., the peristaltic wave begins from the pylorus and passes along the greater curvature toward the cardiac region. 3. Most important in practical terms are motor disorders associated with impaired activity of the pylorus. Among such disorders should be indicated: a) pyloric spasm, b) its insufficiency, c) its stenosis. - By the name of pyloric spasm (pylorospasm) is understood a state of more or less prolonged closure of the pylorus with the simultaneous absence of stomach emptying. The duration of this spasm can be different - from several minutes to several hours; in the latter case, a delay in stomach emptying up to 12 hours and more is observed. Pronounced spasm of the pylorus of the stomach is accompanied by attacks of pain, sometimes taking on a colic-like character; these attacks disappear after vomiting or after removal of the stomach contents. Pyloric spasm is observed predominantly in ulcers located in the pylorus itself or near it, as well as in duodenal ulcers and inflammatory processes thereof. In exceptional cases, pyloric spasm can be caused by foreign bodies, as well as under the influence of morphine. The treatment of pyloric spasm reduces to the treatment of the underlying disease, and symptomatically to the prescription of atropine and Papaverin. - The state of the pylorus opposite to spasm, when its ability to retain food is weakened and it cannot close, is called its insufficiency. Pyloric insufficiency can be functional and organic. The former occurs in achylia gastrica, in duodenal stenoses with simultaneous stretching of its bulb, in paralysis and paresis of the stomach, and in the so-called "spastic pyloric insufficiency" (Schlesinger), caused by tonic contraction of the longitudinal musculature of the pylorus. Organic pyloric insufficiency is observed with its infiltration: inflammatory, cancerous, ulcerative, with its tuberculosis and syphilitic lesions. Narrowing of the pylorus [former designations: "gastric dilation" (Riegel), "motor insufficiency" (Rosenbach), "mechanical insufficiency" (Boas), "ischochymia" (Einhorn)] develops as a consequence of inflammatory conditions of the pylorus with the formation of erosions and fissures of its mucosa, pyloric ulcer; it is also observed as a consequence of the development of a cancerous tumor, pyloric tuberculosis, sclerosing pyloritis, in certain poisonings (acids, alkalis). Inflammatory processes around the pylorus and duodenum leading to adhesions in their vicinity, pericholecystitis, and other local peritoneal inflammations also often lead to the development of pyloric stenosis. From a functional point of view, the following forms of pyloric stenosis are distinguished: a) Compensated stenosis, when in the presence of stenosis the emptying time remains either normal or only slightly delayed. In compensated stenosis, gastric peristalsis is increased due to the resistance to the passage of food through the pylorus, and its increase is strong enough to achieve stomach emptying in a normal or slightly increased period; the musculature of the stomach in this case is usually hypertrophied. b) Decompensated stenosis, when the increase in peristalsis is insufficient to empty the stomach in due time, or when a weakening of peristalsis occurs due to overwork of the hypertrophied musculature of the stomach - in other words, when the ratio between the strength of the stomach musculature (the magnitude of its emptying), on the one hand, and the degree of its stenosis, on the other, is disturbed. Transitional states exist between these forms. - At the first degree of stenosis, subjective phenomena may not be observed at all; in a number of cases, a slight restlessness ("peristaltic") in the upper abdomen after eating is noted; in a number of cases, belching and heartburn are observed, intensifying after eating, predominantly acidic; in the presence of an ulcer or cancer, there are symptoms characteristic of these diseases. Objectively: upon examination with a test breakfast - often a normal state of secretion, more often hypersecretion, superaciditas, prolongation of the secretory period. Examination with a test dinner gives a prolongation of the period of stay of food in the stomach (more than 5 hours) with an abundant amount of gastric juice. X-ray examination reveals a hypertonic form of the stomach, more often in the form of a horn, increased resistance at the first portions of food, lively, deep peristalsis starting high in the cardiac part, serrated contours of the greater curvature, uneven emptying - first rapid emptying, then significantly delayed; complete emptying of the stomach after taking regular contrast food is delayed up to 6-8 hours. - In order to differentiate the diagnosis of pyloric stenosis from diseases that can give a similar picture and in which only functional spasm may be observed (e.g., in nervous conditions, in hypersecretion), it is necessary to pay attention to phenomena that can indicate the cause of the development of stenosis (ulcer, cancer, etc.); the use of a test dinner is also recommended, as well as atropine. In decompensated pyloric stenosis, subjectively observed are: a feeling of fullness in the stomach region, attacks of cramp-like pains; appetite, although preserved and even often increased, is accompanied by a feeling of early satiety; "peristaltic restlessness" is observed to a large degree, often in attacks; the sensation of stomach movements, rumbling, sour or foul-tasting belching, vomiting of masses of various appearance and properties. Often the vomit contains a significant amount of food residues taken many hours and days before the onset of vomiting; often a large amount of light gastric juice is vomited (hypersecretion), which resembles attacks of Reichmann's disease. In severe stenoses, thirst develops, the amount of urine decreases, the stool is retained despite even the use of laxatives, but stubborn diarrhea, nutritional decline, loss of strength, tendency to fainting, sharp emaciation, and sometimes phenomena of tetany also often develop. Upon objective examination, there are observed: emaciation, decrease in skin turgor, often complete disappearance of subcutaneous fat, thinning of the skin; upon inspection - striking sharp outlining of the contours of the stomach, the presence of visible peristaltic waves on it, contraction of the entire stomach, accompanied by attacks of pain, the appearance of belching and vomiting.
On palpation: succussion splash on an empty stomach, easy palpability of the greater curvature. Examination with a tube in the morning on an empty stomach reveals a significant amount of contents and food residues, especially when a heavy dinner was given the eve before, with the formation of three layers in the contents: upper mucous, middle secretory, and lower food layer; chemical examination of the contents in a number of cases shows an increase in total and free acidity, in others a decrease and even achylia; with reduced secretion of gastric juice, there is often a large amount of organic acids, and in cancerous stenosis of the pylorus, lactic acid. With increased acidity in stagnant contents, microscopic examination reveals an abundance of yeast cells and sarcinae; with reduced secretion, undigested muscle fibers and Boas-Oppler bacilli. X-ray examination reveals irregularity of filling, silhouette irregularities (ellipsoidal, egg-shaped, bowl-shaped form), the lower pole is often lowered to the pubis, a significant secretory layer giving a faint shadow, a wide shadow of the body of the stomach without the formation of a "waist," significant displacement of the body to the right, increased peristalsis, deep accelerated waves, alternation of phases of increased muscular work and rest due to complete fatigue of the stomach musculature. Depending on the degree of stenosis and the magnitude of the obstruction, X-ray examination determines delayed emptying of the stomach: after 8, 12, 24, and more hours, residues of contrast food can still be seen in the stomach. - The diagnosis of pyloric stenosis is established if a succussion splash is determined in the morning on an empty stomach, if there are signs of Magensteifung, etc.; probing reveals phenomena of stasis, vomiting of food taken long before the onset of vomiting, gas eructation, slowing of emptying of the second degree (see below), distinct peristalsis. Complications of pyloric stenosis are tetany and Reichmann's syndrome (see below). Treatment of stenosis can be a) surgical, b) dietary, and c) medicinal. Surgical treatment is indicated in cases where stenosis is uncompensated, where improvement of the process is impossible, where there is an indication of progressive cicatrization increasing the stenosis, and if there is suspicion of the development of a malignant tumor of the pylorus. - Dietary treatment is conducted in two directions: 1) the selection of food by character and consistency is made in accordance with the magnitude of the stenosis, and 2) the selection of food is made in accordance with the state of secretion in one or another case of pyloric stenosis. In the first case, Boas's scheme can be used, which consists in establishing the degree of passage of various food substances through the pylorus by administering various food substances in the evening with subsequent morning retrieval of the stomach contents. Boas recommends the following tests. 1. Passability for rice. On the eve, 200 g of milk rice porridge, bread with butter, one egg, and a little soup are given. The next morning, the stomach is washed out to determine the amount of food remaining in the stomach. 2. Passability for vegetable purees, mashed potatoes, porridges. 3. Passability for white bread, biscuit, rusks. 4. Passability only for liquid food. With the help of these kinds of diets, the degree of endurance, resp. the degree of stenosis in relation to the consistency of food is established; along with this, the endurance of the stomach in relation to the amount of food taken is also established, since the degree of food retention in the stomach depends on the absolute amount of food taken. When the degree of difficulty in emptying has been established with the help of these test diets, a diet is prescribed in accordance with the degree of stenosis. When prescribing such a diet, it is necessary to ensure 1) that the food is fully adequate in terms of calories and can ensure an increase in the patient's weight, and 2) that the food can pass through the pylorus without lingering in the stomach. Finally, the food must be selected taking into account the nature of secretion in one or another case of stenosis (superaciditas, subaciditas, hypersecretio - see below). In addition to these basic rules, the following must be taken into account: quantitatively - in terms of volume - food should be limited, meals should not be frequent, and the intervals between them should be quite long - i.e., small and rare meals are necessary. - Boas recommends such sample diets for pyloric stenosis. For mild cases of pyloric stenosis: in the morning - 200 g of milk soup seasoned with wheat or oat flour, with plenty of butter or cream, one egg, soaked rusks, cookies; at 12 noon - 200 g of thick milk-flour soup, pureed vegetable soups with butter, 100 g of mashed potatoes or vegetable puree with a large amount of butter or cream, 100 g of finely chopped meat, 50 g of pureed compote of apples, plums, and 50 g of pudding; at 7 p.m. - scrambled eggs, potato (50 g) or vegetable puree, white bread (50 g), butter, tea with milk or cream. - For moderate pyloric stenosis, the following diet is recommended: in the morning - the same as in the diet described above; at 1-2 p.m. - 100 g of thick milk-flour or vegetable soup, 50 g of potato or vegetable puree with a large amount of butter and 50 g of pureed meat; in the evening - one soft-boiled egg with butter, 50 g of mashed potatoes, 50 g of white bread, butter, pureed cheese, tea with cream or milk. - In severe cases of stenosis, the following is prescribed: in the morning - 200 g of milk-flour soup; at 12 noon - 200 g of the same or vegetable soup with butter and egg, 50 g of calf's foot jelly or meat aspic; in the evening - 200 g of milk-flour soup with butter and egg, 100 g of tea with cream. The latter diet, in view of its low calorie content and insufficiency in vitamin content, cannot be prescribed for a long time. - A diet taking into account the magnitude of secretion is prescribed in accordance with the degree of these changes (superaciditas, subaciditas, hypersecretio). - Drug therapy for pyloric stenosis has only symptomatic significance: in the presence of spasm, atropine and papaverine preparations are recommended; to improve and increase tone in an atonic stomach - strychnine; if pyloric stenosis proceeds with phenomena of reduced acidity, the administration of HCl is recommended; in the presence of increased acidity or phenomena of acidism, therapy is directed against these latter conditions (see below). Systematic gastric lavage in both morning and evening hours is of essential importance. 4. Motor disorders of the stomach can also be expressed in disturbances of its emptying time. Emptying can be accelerated or slowed down, or finally may not occur at all. Various methods are used to determine the speed and nature of emptying. Of these methods, the most generally accepted are: the Boas-Ewald breakfast method with determination of the solid residue according to Eisner and the total amount of gastric contents according to Mathieu-Remond, the method of fractional evacuation of gastric contents after a colored test meal, the Riegel test dinner method, and the X-ray examination method. All these methods have largely conditional significance depending on the stimulus applied, and therefore cannot be considered precise methods. When determining motor ability with the Boas-Ewald breakfast, the Riegel dinner, and X-ray examination, one is guided either by establishing the time when complete emptying of the stomach occurs after taking a certain food, or by the amount of gastric contents obtained after a certain interval of time, or rather - the residue of the taken test food. For example, if when giving a Boas-Ewald breakfast, upon evacuation of the contents after 60 minutes, nothing is found in the stomach, this may indicate accelerated emptying; if the amount of evacuated gastric contents reaches 100-300 cm3 and more, this may indicate both slowed emptying and a disorder of motor ability (insufficiency of the second degree in pyloric stenosis, gastric paresis, nervous disorders of the motor function of the stomach, etc.). The amount of contents within the range of 20 to 100 cm3 is considered a value indicating normal emptying. If after giving a Riegel dinner, food residues are found after 7 hours, they speak of motor insufficiency of the first degree; if this time is extended to 12 hours, then of the second degree. Since the test dinner makes significant demands on the emptying mechanism due to its properties, in a number of cases its use makes it possible to detect less pronounced motor disorders than when using the Boas-Ewald breakfast. The most valuable method for determining motor disorders is X-ray examination, which makes it possible to determine many details of movement disorders by individual moments and stages, as well as acceleration or deceleration in various degrees, or a phenomenon such as the Kreuzfuchs phenomenon, which consists in the fact that initially, during increased peristalsis, rapid emptying of the stomach occurs (in the first hour up to 2/3 of the barium mixture leaves the stomach, while the other part leaves slowly and in small portions).
The latter symptom is characteristic of pylorospasm. In X-ray examination, rapid and stormy evacuation is observed in achylia, sometimes in cancerous infiltration of the pylorus (incontinentia pylori). With a duration of evacuation of 2.5 to 3 hours, the motor capacity is considered normal; such a duration in the presence of enhanced and pronounced peristalsis may also be observed in some cases of compensated stenosis. If the duration of evacuation reaches 4-8 hours, this indicates a decrease in the motor capacity of the stomach. When the evacuation time increases to 12 hours, it is referred to as 2nd-degree evacuation insufficiency. The 3rd degree of this disorder is determined when the evacuation lasts 24 hours or more. Various liquid test stimuli (broth, vegetable juices, solutions of alcohol, caffeine, etc.) with or without the addition of coloring agents, using fractional examination with a thin tube, also find wide application in determining the nature of motor disorders. A valuable property of this method is that it determines the motor properties, resp. disorders of the stomach with simultaneous consideration of the regulating role of acidity in the evacuation process. Determination of the degree of gastric motor disorders is carried out along the course of the acidity curve or by the time of disappearance of the color of the contents (when a coloring agent is added to the stimulus). According to Katsch, there are several types of secretion curves by which it is possible to judge the nature of motor disorders. These types are as follows: 1) The type of early appearance of significant acidity: a rapid and steep rise of its curve, rapid evacuation, as can be observed in ulcers of the stomach, duodeni with or without phenomena of compensated stenosis; in a number of cases, marked hypersecretion and hyperchlorhydria are observed. 2) The acidity curve of normal height with a normal rate of rise, as observed in cases of normal motor capacity of the stomach, or slightly weakened. 3) The type of curve when acidity appears with a delay: the curve is stretched, which indicates a slowdown in evacuation caused by organic lesion of the pylorus or its functional state («pylorospasm»). 4) A low type of curve with rapid disappearance of color: indicates accelerated evacuation with insufficient acidity. Each of the listed methods for determining the motor function of the stomach, having its positive and negative sides, can yield valuable practical results for judging the nature of gastric motor disorders, but taken separately, none of them can be considered a method that is fully exhaustive, and each of them serves as a supplement to the other in understanding the phenomena of the indicated disorders. 5. In the clinic of motor disorders of the stomach, there are two forms of the disease in which a sharp weakening of the gastric musculature is observed, the result of which, even in the absence of a mechanical obstacle, is a significant disruption of stomach evacuation and food stasis in it. These forms are named: 1) gastroparesis and 2) paralysis of the stomach. In gastroparesis, chronic muscular weakness of the stomach is observed. In contrast to atony of the stomach, in which predominantly only a disturbance of peristole is observed, and evacuation can be normal, in gastroparesis, mainly evacuation suffers. According to Schlesinger, chronic «gastroparesis is the cause of severe motor insufficiency with a free pylorus.» Gastroparesis, being a manifestation of fatigue of the stomach musculature, can occur with malnutrition, starvation, due to reflex influences, fright, fainting, lesions of the biliary tract, appendix, with cancerous, tubercular cachexia, with atony of the stomach after infectious diseases. It can be observed in organic stenoses of the pylorus and, what is important in diagnostic terms, in gastric ulcers in the region of the lesser curvature. The cause of gastroparesis in this latter case is presumed to be a lesion of the conducting system of the stomach (Keith) or Auerbach's plexus. Clinically, gastroparesis manifests with symptoms similar to those in decompensated pyloric stenosis; importance is attached to the sign that the vomit contains an extremely abundant amount of bile; essential data are provided by X-ray examination: an increase in the size of the stomach, a sharp slowdown in evacuation in the absence of narrowing or obstruction in the pyloric region. It should be borne in mind that gastroparesis also occurs in organic stenosis of the pylorus in its decompensated form. Treatment consists in the selection of food that is nutritious in composition and not burdensome in volume, restriction of fluid intake per os and replacing this with enemas, evening gastric lavage, administration of strychnine; in the presence of organic pyloric stenosis, surgical treatment is indicated. The state of sharp weakening of the musculature and complete cessation of movement constitutes acute paralysis of the stomach. In this disease, the tone of the stomach disappears, its movements cease, the stomach stretches and fills in abundant amounts with secretion («acute gastric dilatation»). It is observed more often after operations, especially in the abdominal cavity, under the influence of anesthesia, in severe infectious diseases (typhoid), in damage to the central nervous system, with excessive intake of food, in particular liquid, with contusion of the abdominal region, etc. Clinically, the disease usually occurs suddenly and develops rapidly and stormily; facial features change sharply, the pulse becomes small, sharp pains appear in the upper abdomen, severe thirst, abundant vomiting of liquid (in greater quantity than the patient introduces into themselves); there is a sharp bloating of the stomach region with simultaneous retraction of the lower abdomen; at the same time, in contrast to peritonitis, reflex muscular tension is absent. Very abundant vomiting is observed, often reaching up to 30 liters in volume. The result of this is severe thirst, a decrease in skin turgor, a sharp loss of weight, and a decrease in diuresis to complete anuria. The disease can last from several hours to several days and in 2/3 of cases ends in death. The cause of this lesion is considered to be severe atony of the stomach and stenosis of duodeni due to its kinking over the vascular-mesenteric bundle or due to irritation and damage to extragastric nerves, as well as the intramuscular nervous apparatus of the stomach. The diagnosis of the disease is established on the basis of the clinical picture described above. In differential diagnostic terms, one must keep in mind ileus (fecal vomiting), acute stenosis of the pylorus or duodeni (preserved sharp peristalsis), acute pancreatic necrosis (attacks of sharpest pains). Treatment: gastric lavage, complete abstinence from food, position on the right side (Kussmaul) or knee-elbow («a la vache»), drip enemas, administration of strychnine and physostigmine, as well as choline. The use of morphine, adrenaline, and atropine is contraindicated. Pathology of the secretory function of the stomach. Pathological disorders of the secretory activity of the stomach can be expressed in changes in gastric secretion both in quantitative and qualitative respects. Changes in gastric secretion of a quantitative character include: hyperchylia (hypersecretio) and hypochylia (subsecretio), achylia; qualitative changes in secretion include superaciditas, resp. subaciditas, and hyperchlorhydria, resp. hypochlorhydria. I. Gastric hyperchylia (supersecretio, hypersecretio) is a state of gastric secretion when, without the presence of a food stimulus, a significant amount of gastric juice is secreted and accumulates, or when for a certain stimulus secretion continues for an abnormally long time and in large quantities. Clinically, several forms are distinguished: 1) Reichmann's syndrome, or gastrosuccorrhea, syn. chronic constant secretion of gastric juice (Riegel), parasecretion (Ewald); 2) periodic intermittent hyperchylia, observed in migraines, angioneurotic edema (Quincke) and mainly in the form of so-called gastric crises in tabes dorsalis, and 3) hyperchylia as a symptom of a number of organic lesions of the stomach, predominantly in ulcers of the stomach and duodenum. 1. In Reichmann's form, excessive secretion of gastric juice is observed, accompanied by the onset of sharp pains in the stomach towards evening; the pains last all night, reach their maximum by morning and spread throughout the abdomen; during the day they subside, also easing after food intake, but the next night the attack repeats. Severe heartburn is observed, increased appetite, stools are delayed, belching is never observed. Upon objective examination, up to 1 liter of gastric juice with a strongly acidic odor is pumped out of the stomach. Reichmann's syndrome is considered either as a secretory neurosis of the stomach, and then they speak of «genuine» gastric juice outflow, or as a concomitant symptom in ulcer of the pyloric region and benign pyloric stenosis and duodenal ulcer. The latter form of Reichmann's syndrome is observed more often.
Regarding the mechanism of Reichmann's syndrome, it is assumed either that under the influence of an ulcer a special state of excitation of the nervous system of the stomach develops, especially in the presence of autonomic disharmony, or that this syndrome represents a symptom of a stagnant stomach, in which retained food residues, even microscopic ones, are able to maintain a prolonged and strong secretion of gastric juice. 2. In periodic gastric hyperchylia, there is a periodically occurring excessive secretion of gastric juice, wherein the periods do not occur regularly, usually lasting no more than 24 hours, rarely (in hysteria) a week. Between attacks, patients feel healthy. In the group of periodic gastric hyperchylia, several distinct sub-types are clinically distinguished. The first sub-type can include cases which represent variants of chronic constant secretion of gastric juice, as observed in ulcers of the stomach and duodenum. The periodicity of the onset of hyperchylia in this case is an expression of the exacerbation of the ulcer process. Periodic hyperchylia is most pronounced in the second sub-type, in tabes dorsalis, and is called gastric crises. The onset of pain occurs suddenly, rapidly reaches the degree of spasmodic pain in the region of the stomach and is accompanied by severe, constantly returning vomiting, almost indomitable—first of food masses, and then of gastric juice along with bile and mucus. The general condition deteriorates sharply. The attack ends suddenly, just as it began, and the next day the patient feels completely healthy. It is characteristic of these conditions that between attacks no deviations from the norm are found in the stomach and that the usual means for reducing the phenomena (stomach lavage, alkalis) do not have a mitigating effect here. - The third sub-type of periodic gastric hyperchylia is called gastroxynsis (see) and was described by Rossbach. - As a special sub-type of periodic hyperchylia, periodic gastric hypersecretion occurring with Quincke's angioneurotic edema is also considered. In this condition, attacks are observed accompanied by vomiting, seizures of pain in the stomach region, in the left hypochondrium, nausea; when eating food, these phenomena intensify. The attack usually ends in 10-12 hours. The diagnosis of this form is based on the alternation of these periods of seizures and periods of the onset of edema. 3. Hyperchylia is most often a symptom of a number of organic diseases of the stomach. In these lesions of the stomach, a form of the constant type (hyperchylia continua) is distinguished, when gastric juice is secreted for a long time, rapidly, and, most importantly, independently of the physiological stimulus, and moreover in a significant amount; in another form of hyperchylia, the so-called alimentary hyperchylia, in response to one or another food stimulus, gastric juice is secreted in a much larger amount than is observed in normal cases, and for a long time. In constant hyperchylia, gastric juice with a significant degree of acidity in an amount from 100 to 500 cm3 is usually obtained from the fasting stomach. In alimentary hyperchylia, the fasting stomach is either empty or contains an insignificant amount of gastric juice; upon introduction of a stimulus, a significant amount of gastric juice is obtained, more than 60-100 cm3 per 1 hour. Both of these forms are clinically close to each other, and transitions from one to the other are observed: alimentary passes into constant during exacerbations, and conversely, constant passes into alimentary during periods of improvement. In a number of cases, alimentary and constant hyperchylia are expressed only in an increase in the duration of the secretion of gastric juice, while the amount of juice is not sharply increased. Alimentary and constant hyperchylia represent a functional disorder which is caused by greater excitability of the secretory apparatus and the presence of significant irritation. They are observed in ulcers of the stomach, duodenum, in pyloric stenosis and in stagnation of contents in the stomach, in certain forms of gastritis, and finally in various strong food and toxic irritations of the gastric mucosa. Often, gastric hyperchylia is observed with lesions of other internal organs besides the stomach: in cholecystitis, cholelithiasis, appendicitis, as well as in certain forms of metabolic diseases. Clinically, hyperchylia is subjectively often expressed by pain in the stomach region, but often proceeds without any symptoms. Objectively, the diagnosis is made mainly on the basis of the results of studying the amount of secretion on an empty stomach and after the application of a food stimulus, using a tube, especially by the fractional method. X-ray examination of the stomach reveals a high secretory, the so-called intermediary layer. The treatment of hyperchylia, resp. hypersecretion, is identical to the treatment of stomach and duodenal ulcers and reduces to: 1) treatment of the underlying disease that caused the large secretion of gastric juice; 2) diet therapy—prescription of food capable of causing a decrease in secretion; fat diets (Yarotsky and others) and dry diet with restriction of NaCl content in food are used; 3) treatment with systematic gastric lavage, especially in the presence of stagnation; 4) treatment with mineral waters (Slavyanov source, hot Narzan in Pyatigorsk, etc.); 5) prescription of atropine preparations, Magnesium-perhydrol, etc. II. Gastric hypochylia—decreased secretion of gastric juice both in terms of reducing its amount (subsecretio) and in terms of lowering its acidity (subaciditas). In the latter case, the total acidity is lowered, and often free HCl is completely absent; upon examination with a liquid stimulus (vegetable juice, alcohol, Liebig's extract or broth), low values of free HCl are usually found. When examining simultaneously for the chloride content of gastric juice in a state of hypochylia, in some cases the secretion curve is found to be either normal (normochlorhydria) or slightly lowered; in other cases, the chloride curve is sharply reduced—these are cases of hypochylia with hypochlorhydria. Hypochylia occurs as a functional disorder of the stomach in anemia, gallstone disease, and also as a symptom of organic lesions of the stomach—in chronic catarrhs, mild dyspeptic conditions, cancer, and sometimes even stomach ulcer. When diagnosing hypochylia, it must be borne in mind that hypochylia can be caused by delayed stomach emptying, and the acidity curve can reach its maximum very late, only after 60 and even 120 minutes; such a course of the curve is the stronger expressed, the more sharply the secretory capacity of the stomach is lowered. In most cases of hypochylia, the pepsin content in the gastric juice is lowered. To accurately identify the various degrees and types of hypochylia, the fractional method is used with the application of a breakfast: vegetable, fish or meat broth, caffeinated, alcoholic, or a histamine test (0.0005 subcutaneously) is performed. In its clinical significance and picture, hypochylia is very close to achylia, which is the highest degree of hypochylia. Regarding the pathology of such qualitative changes in gastric secretion as hyperchlorhydria, superaciditas, it must be borne in mind that the very question of the possibility of these changes in secretion cannot be considered finally resolved. Until recently, a divergence has existed between the physiological understanding and the clinical view on this issue, consisting of the following: according to the view of physiologists (Heidenhain, Pavlov, Bickel, and others), the concentration of HCl in gastric juice is a constant value—there is isochlorhydria. The variation in the degree of acidity and the value of HCl concentration depends only on the rate of secretion, resp. on its magnitude, as well as on the state of the leveling apparatus (amount of mucus, etc.) and the motor mechanism of the stomach. In accordance with this view, the concepts of supersecretio and hyperchlorhydria, resp. superaciditas, are synonymous concepts. This view is also shared by many clinicians (Einhorn, Modrakowski, and others). - According to another view, the concentration of HCl in gastric juice both physiologically and under pathological conditions can change; the magnitude of the concentration depends both on the degree of irritation and on the individual excitability of the secretory apparatus of the stomach. Changes in excitability in the direction of its increase, the resulting increased tendency of the stomach to give the maximum concentration of HCl, necessitate the term "hyperchlorhydria" as a concept of a state not synonymous with the concept of hypersecretion (Katsch, Gregersen, and others). Finally, according to a third view (Rosemann), both physiologically and pathologically there is poikilochlorhydria, i.e., fluctuations in the concentration of gastric juice depending on the strength of the stimulus. - With the current state of this issue in the clinic of gastric diseases, two forms of disturbance of HCl secretion are distinguished: 1) an increase in the concentration of HCl of the gastric juice (hyperchlorhydria) and 2) an increase in the secretion of HCl (superaciditas). - Under the name hyperchlorhydria (according to Katsch), an increased excitability with respect to the concentration of HCl is understood; accordingly, hyperchlorhydria represents a symptom indicating the degree of reaction, the magnitude of excitability, similarly to the concept of, for example, "increased dermographism".
Accordingly, hyperchlorhydria can also be a gastric symptom, as well as a symptom of general excitability of the autonomic nervous system. In the first case, it is a symptom of increased irritability of the secretory apparatus of the stomach. Practically, hyperchlorhydria refers to those cases where the acidity of the gastric contents is determined to be above 100 (0.365% HCl). The causes for the development of increased irritability of the secretory apparatus of the stomach, resp. hyperchlorhydria, are considered to be: the habitual use of harsh food stimulants (spices, vodka, abundant food in general, and meat in particular), further the presence of a gastric ulcer, acute and subacute catarrh of the stomach, a state of increased excitability of the nervous system in general or its individual parts, a change in the general hormonal setup, in the state of acid-base balance, general metabolism, etc. By the term superaciditas is meant such a pathological state of gastric secretion when a larger amount of HCl is secreted than normal and when the total acidity exceeds 70. The increase in HCl secretion can occur due to an increase in the acidity of the gastric juice, i.e., due to hyperchlorhydria, or due to an increase in the amount of secreted gastric juice, i.e., due to hyperchylia. Thus, the concept of superaciditas is broader and includes both forms just named. In the origin of superaciditas, the following are of significance: 1) individual characteristics (constitutional in the broad sense of the word) of the secretory apparatus of the stomach, expressed in the presence of a certain proportionality between the strength of the stimulus and the degree of response; 2) variability of the HCl concentration in the secreted gastric juice (see above); 3) in the presence of the latter, the state of the neutralizing apparatus of the stomach (the amount of mucus secretion, prepyloric juice, and the regurgitation of duodenal juice); 4) the magnitude of secretion; 5) the character of emptying, depending on the state of the tone of the stomach, the activity of the pylorus, and other factors affecting the motor and emptying capacity of the stomach; 6) the chemical composition of the blood (hyperacidemia, Foldes) and the disturbance of the acid-base balance (Balint, Arnoldi) can also have an influence. This multiplicity of conditions influencing the origin of superaciditas indicates that we are still far from understanding the causes of its occurrence. Superaciditas occurs frequently (from 30 to 51% of all cases of stomach diseases) at all ages, more often after 40 years. It is especially frequent in ulcers of the stomach and duodenum, in acid catarrh, in the initial stages of pyloric cancer, in chronic appendicitis, cholecystopathies, in vagoneuroses, in general neuroses and gastric neuroses in particular; finally, superaciditas can also occur in healthy individuals (Boas, Kuttner, and others). Clinically, superaciditas proceeds differently: 1) without the presence of any painful symptoms ("constitutional or latent hyperchlorhydria" by Riegel; "non-pathological superaciditas" by Einhorn); 2) superaciditas exists for a long time, on its own, and sometimes jointly with hypersecretion, but manifests itself only periodically, in attacks; 3) superaciditas can manifest itself in a special symptomatology, which bears the name of acidism (Bergmann, Katsch, and others). In the case where a state of "acidism" is observed, the latter is expressed by special attacks, which consist of the following. Usually 2-3 hours after eating, a feeling of pressure and discomfort in the epigastric region appears, a feeling of warmth in the stomach, heartburn, subjectively very sharply felt by the patient; a need for eructation develops, upon the onset of the latter—a sensation of sharp acid in the mouth and an unpleasant sensation in the teeth (setting the teeth on edge), often severe salivation. The attack sometimes disappears after eructation, sometimes after defecation, often after taking soda. There are cases when the attack intensifies despite the onset of eructation or taking soda and lasts the next day as well. The degree of severity of the attack can vary significantly in different patients—from barely noticeable in strength and duration to the degree of attacks similar to those in biliary colic. The "companions" of superacidism are constipation, increased thirst, and usually an increased appetite. It should be kept in mind that "acidism" can be observed in the presence of only superaciditas alone, as well as often with superaciditas + hypersecretion, very frequently in stomach ulcers, in its neuroses; in normal individuals—upon dietary disturbance or consumption of food in large quantities or containing a number of substances belonging to the group of strong stimulants of gastric secretion. Objectively, superaciditas is expressed by: the finely crumbly appearance of the gastric contents obtained with a Boas-Ewald test breakfast, a high Strauss coefficient; tests for free HCl are sharply positive (Kongo, Gunzburg); upon titration, the total acidity is above 60, free HCl is above 50, pH is 1.5-1.7. The maximum acidity usually occurs after 60 minutes. Investigation by the fractional method using liquid stimulants (alcohol, caffeine, vegetable juices) yields secretion curves that substantially elucidate the details of the character of secretion and acidity by the degree of their magnitude, duration, course, etc. Treatment of superaciditas coincides with that for hypersecretion; strengthening of the nervous system, regular meals are recommended; the latter in composition is predominantly fat-carbohydrate and achloric; of medicinal substances—atropine, hydrogen peroxide (1/4%), alkalis. Hypochlorhydria and subaciditas from the point of view of physiological concepts of isochlorhydria do not exist and depend only on a decrease in the rate of outflow of gastric juice, resp. a decrease in secretion (Leo). Clinically, however, cases are observed when gastric juice is secreted with a reduced concentration of HCl—these cases can be attributed to hypochlorhydria. By the name subaciditas is meant a condition in which a reduced content of HCl is found in the gastric contents, resp. juice. In the origin of subaciditas, a number of factors play a role, acting in the direction of reducing the acidity of the gastric juice. Such factors are a decrease in secretion, a decrease in the concentration of HCl in the juice, the state of the motor, resp. emptying mechanism of the stomach. Subaciditas occurs in various general conditions (anemia, avitaminoses, infectious diseases, lesions of the nervous system), as well as in various diseases of the stomach (catarrh, cancer, in a number of cases of gastric ulcers, etc.). Objectively, examination reveals a decrease in both total acidity (below 30) and free HCl (below 0.08%), pH—2.0-2.9. When examining states of reduced acidity, it is necessary to use the fractional method with the use of strong secretion stimulants; the use of histamine (0.0005 subcutaneously) provides significant services here. The emptying capacity in subaciditas is more often increased, but often normal or even reduced. Subaciditas is very frequently combined with hypochylia. Clinically, in its signs and course, subaciditas is similar to achylia gastrica. A disorder of gastric secretion was described by Einhorn, which was expressed in the abundant entry into the stomach of fluid containing neither HCl nor enzymes and representing a transudate. Such a disorder was named by the author "gastrohydrorrhea". It was observed in cases where there was simultaneously a pyloric stenosis and atrophic cirrhosis of the liver. As a rare disease, it has no practical significance.
V. Dislocation of the stomach downward (gastroptosis). To give a precise definition of the concept of "gastroptosis" at the present time does not seem possible. To the extent that in pronounced cases the picture of a "dislocated stomach" leaves no room for doubt, to that same extent in a number of other cases the boundaries between a dislocated and long stomach, or a hook-shaped stomach in women, appear unclear. Neither the navel nor the iliac line can serve as an orientation in this regard, since their height, as well as the very shape of the stomach, depends on the structure of the entire organism and the ratio of its parts. Gastroptosis often represents a partial manifestation of splanchnoptosis, but it is also observed in isolation, and in this case it is necessarily combined with coloptosis, whereas the liver and other organs may remain undislocated. Radiologically, three degrees of stomach dislocation are distinguished: 1) the lesser curvature lies above the iliac line, 2) at its level, 3) below it. The stomach in this case is often not only dislocated, but atonic and dilated [see separate table (pp. 75-76), Fig. 5]. There are two main forms of organ dislocation and in particular of the stomach: 1) acquired and 2) constitutional. Acquired dislocation is the result of prolonged mechanical stretching of the abdominal walls, causing a decrease in the tone of the abdominal muscles as a consequence of pregnancies, tumors, ascites, significant fat deposition in the abdominal cavity, followed by sharp emaciation (Landau type). The constitutional form of gastroptosis is observed mainly in individuals of the so-called asthenic type (Stiller's type), but in relatively rare cases also in individuals with a normal physique. Since the abdominal integuments and the ligamentous apparatus of the abdominal viscera in asthenics are much more easily amenable to stretching than in pycnics and normosthenics, if conditions arise that cause acquired forms of ptosis, these latter will develop all the more readily on a favorable asthenic soil. Thus, a third, so-called "mixed form" of stomach dislocation is also obtained. The pathogenesis of acquired forms of gastroptosis, which are based on the purely mechanical causes outlined above, appears quite clear. Much more complex is the pathogenesis of the constitutional forms of dislocation, for the explanation of which numerous theories exist. The oldest of these is the so-called "corset theory," according to which the cause of dislocation was considered to be the pressing influence of a corset or tightly constricting lacing (Hertz, Meinert, and others). That prolonged wearing of a corset or tight lacing, especially at a young age, can alter the shape of the skeleton and disrupt the function of the abdominal muscles and diaphragm, admits of no doubt, and this mechanical factor must be recognized as having a certain pathogenetic significance, but the circumstance that gastroptosis is also encountered in men and among women of such tribes as have never known either a corset or lacing (Becher, Lennhoff) deprives this theory of its generalizing significance. The second theory in time sees the cause of dislocation in the weakness of the ligamentous apparatus (Glenard and others). But since the ligamentous apparatus (in the fair opinion of Quincke) merely regulates the position of organs and is not their bearer, the relaxation of the ligaments must be considered as a secondary phenomenon or, more correctly, as a partial manifestation of the asthenic constitution, in which, as a rule, weakness of all connective tissue is noted (Tuffier, Veer, Strauss, and others). With this understanding of the question, Credé's doctrine of primary pyloroptosis as a mandatory prerequisite for gastroptosis drops away by itself. Braitsev draws attention to the relationship between the stomach and the transverse colon. In gastroptosis, the transverse colon is always anchored on an excessively long (high) mesentery (mesocolon). Corresponding to the height of its mesentery, the intestine appears long and descends deep into the pelvis, describing an arch open upward and forming acute angles in the region of the hepatic and splenic flexures, of which the right one stands lower than the left. In contrast to this, the gastrocolic ligament is usually short, sometimes so much so that the transverse colon almost touches the greater curvature of the stomach. With such a relationship, any movement of the transverse colon, especially when filled with fecal masses, must be transmitted to the stomach and stretch its musculature, mainly in the cardiac part, since by the nature of the anatomical relations the traction from the intestine must be transmitted precisely to this part of the stomach. Consequently, the stomach primarily descends as a result of its stretching along its length, while its dilation occurs subsequently, when its musculature ceases to cope with the obstacle that has arisen in the region of the flexure of the duodenum and the ascending limb of the stomach, when its atonia sets in and its motor function falls. The described relations are congenital, but the clinical manifestations of gastroptosis develop only with age as a consequence of the increasing decrease in tissue elasticity and the impact of unfavorable factors created by life, among which the peculiarities of labor and nutrition are of great importance. The theory currently enjoying the greatest recognition considers organ dislocation as an act of their adaptation to the primary changes in the shape and capacity of the abdominal cavity, which are the result of the asthenic constitution. The latter is characterized by a number of signs that are usually not all fully encountered in the same individual, but which, even in their partial manifestation, make it possible to easily grasp the features of this constitution. The lowered tone of the abdominal integuments accompanying the asthenic constitution, as a consequence of the congenitally weak development of the abdominal musculature or its lowered tone, is one of the most essential moments in the development of organ dislocation in asthenics. Such integuments easily yield and stretch under the influence of gravity acting from within (previous pregnancy, tumor, ascites, etc.). The narrowed and elongated abdominal cavity in asthenics forces their stomach to assume a vertical position. Not encountering sufficient resistance in the weakened abdominal integuments, it descends downward, following in this respect the intestine descending downward, on which it lies as on a bedding. A contributing factor is also the hypotonic state of the musculature of the stomach itself and of the entire ligamentous apparatus. The elongated shape of the dislocated stomach, resp. its vertical position, depends predominantly on the fact that its upper pole is fixed at the cardia and mainly at the diaphragm, so that under these conditions only the caudal part of the stomach descends. Taking into account that the asthenic constitution places its stamp not only on the muscular and ligamentous apparatuses, but also on the nervous system, it is easy to understand the resulting lowered functional capacity of the stomach on the one hand and its increased excitability on the other. It is not for nothing that among this category of individuals there are so many persons with disorders of the functions of the nervous system in general and the autonomic in particular, and in describing the clinical picture (see below) of gastroptosis, it will be seen that the nervous element sometimes predominates in the picture of the disease over the gastric one. The described pathogenesis of gastroptosis also explains the majority of encountered clinical symptoms: antropyloroptosis leads to a flexure between the upper horizontal part of the duodenum and its vertical part, hence the delayed emptying of the duodenal contents and frequent colicky pains; the transverse colon descends downward for the above-indicated reasons (Braitsev) or under the weight of the dislocated stomach and forms acute angles in the region of both flexures, hence frequently accompanying constrictions and pains in the abdomen; the stretching ligaments cause irritation of the nerves embedded in them (Rovsing) and thus cause unpleasant sensations and pains in various places of the abdomen. Katz believes that all the static deviations in the abdomen described here depend on the altered nervous set-up in asthenics, thanks to which the synergism between the tone of the abdominal musculature and the organs located inside the abdomen is disrupted. By the apt proposal of Volkov and Delitsyn, the entire abdominal musculature together with the pelvic floor bears the name circumstrictor abdominis. Passing to the symptomatology of gastroptosis, one must first of all point out that both the pronounced constitutional Stiller's type of gastroptosis and the acquired Landau type can proceed without any painful sensations and functional disorders. From this stems the basic proposition that organ dislocation is only a predisposed moment for disease. The disease itself arises only when life makes demands on such an organism that are beyond its capacity. The complaints of patients relate mainly to the digestive tract and the nervous system. Heaviness, pressure, and distension in the epigastric region even after an uncopious meal, rapid satiation, eructation—such are the most frequent complaints of gastroptotics. All these unpleasant sensations last for 2–3–4 hours, until the stomach is freed from the greater part of its contents. Patients try to alleviate their condition by stretching and untying their constraining clothing, lying on their back or on their stomach, etc. Quite often patients complain of a sensation of pressure in the stomach region on an empty stomach. Their appetite is very changeable, most often lowered, but is also normal. A part of the patients experiences a certain fear of taking food (sitophobia).
Frequent companions of gastroptosis must include chronic constipation, which often significantly contributes to the deterioration of the general condition of patients. Pains in the region of the stomach and in various places of the abdomen, in the lower back and sacrum, especially after strenuous walking or physical labor, pass fairly quickly or at least are alleviated after the patient assumes a horizontal position. Characteristic should also be considered those sudden, acute, rapidly passing pains that appear in a limited place of the abdomen, for example, during a jump, when lifting a weight, with a sharp raising of the hands, etc. In addition, patients most often complain of pulling pains in various parts of the body, headaches and dizziness, mild excitability, rapid fatigue, reduced working capacity, mood variability, etc. The painful signs listed here apply equally both to Stiller's type of gastroptotics and to Landau's type, but in the former, deviations on the part of the nervous system play a particularly prominent role. Here, deep neurasthenic and asthenic phenomena are particularly often joined, thanks to which all the complaints of patients acquire a special brightness and variety. According to Strauss's apt expression, the asthenic constitution turns the central nervous system into a resonator of bodily sensations. Upon objective examination of persons with the acquired form of gastroptosis, one's eyes are caught first of all by a pendulous abdomen (venter propendens), depending on severe relaxation of the abdominal muscles and often accompanying divergence of the rectus abdominis muscles. In the constitutional form, however, there are certain signs of an asthenic habitus; the abdomen appears flat, but in the standing position of patients, its lower part is somewhat protruded—especially when compared with the sunken region of the stomach and flattened chest. The beating of the abdominal aorta stands out quite clearly; the abdominal walls are very yielding, which makes it possible to easily palpate the colon throughout its entire extent (boudin coecal, corde colique, cordon sigmoïdal of Glenard), while the low standing of the transverse colon is determined. It is also possible to palpate other dropped organs or parts of organs: kidneys, liver, and also one or two curvatures of the stomach according to Hausmann. The succussion splash in the region of the stomach determined by palpation has no pathognomonic significance; it is certainly easier to elicit in gastroptosis due to relaxed abdominal coverings and lowered tone of the walls of the stomach itself. The position of the stomach before the X-ray era was determined by inflating the stomach, feeling the probe inserted into the stomach, and gastrodiaphanoscopy. All these methods are now superseded by X-ray examination of the stomach. During fluoroscopy of the dropped stomach, first of all, an elongated stomach catches the eye, the lower pole of which is located far below the navel, often at the level of the symphysis ossium pubis, and sometimes in the lesser pelvis. In this case, the antropyloric part does not pass to the right (the difference from the dilated stomach); the pylorus is more or less lowered, often mobile, which can be verified when the patient is lying on their right side; the sinus is slightly expanded, whereas in the region of the body of the stomach, the greater and lesser curvatures are brought closer to each other; the upper pole remains in the same position as in the norm, thanks to its attachment to the diaphragm; only the antropyloric part and often the pars horizontalis duodeni are lowered, which appears oblique, running from left-bottom to right-top. In very many, but far from all cases, a decrease in the tone of the stomach is stated (hypotonia, atonia); at the same time, the contrast mass accumulates mostly in the bag, and the left knee of the stomach is filled only partially. Disturbances of stomach function may be completely absent. The chemism may be normal. Superaciditas is often noted, but subacid states also occur. The motor function is either normal or slightly delayed. A significant slowdown in the movement of gastric contents (eight-hour residue) according to K. Faber is observed only in 10% of cases. As a result of the kinking of the duodenum, the outflow of bile can be difficult, and jaundice can occur (Pertpes); stagnant gastric hemorrhages are observed (Pertpes), which can give rise to the thought of a stomach ulcer. Differential diagnosis. Recognition of gastroptosis does not present special difficulties if one uses X-ray examination of the stomach, but it should be remembered that gastroptosis not only does not exclude other very serious organic diseases—ulcer, cancer, pylorospasm—but also has many common manifestations with them at times. Pains associated with meals and reaching quite a significant degree at times, sitophobia, the presence at the same time of increased acidity—can make one think of an ulcer, especially since, according to Stiller's teaching, supported by Bier and others, gastroptosis is a moment predisposing to the development of an ulcer. In these cases, the question is resolved by repeated examination of feces for occult blood and repeated fluoroscopy of the stomach. Sometimes the onset of bloody vomiting immediately dispels all doubts. In older persons with unclear gastric complaints and progressive emaciation, one should not forget the possibility of the appearance of a malignant tumor, and in order not to miss the moment for surgical intervention, it is important to keep this very possibility in mind and not try to reduce all unclear complaints to the simultaneously existing ptosis. It is also clear that the narrowing of the pylorus associated with the dilation of the stomach and its low standing can give rise to confusion with gastroptosis. Here the question is resolved on the basis of signs of motor insufficiency with a sharp slowdown in the evacuation of food masses. The differential diagnosis between the constitutional and acquired forms of gastroptosis is resolved on the basis of anamnesis data and the general appearance of the patient. Treatment. Only those cases of gastroptosis require treatment that cause some suffering. But prophylactically, it should be especially borne in mind that the asthenic constitution predisposes to the so-called mixed forms of ptosis with all its sufferings and that therefore, on the one hand, it is necessary to spare the neuromuscular apparatus in such people, avoiding first of all everything that is able to weaken it, and on the other hand—it is desirable to systematically strengthen it with reasonable physical culture. It is also necessary to monitor the state of general nutrition, preventing any significant drop in body weight. It is necessary by all means to fight against the fashionable hobby for weight loss in women with an asthenic constitution. Children with an asthenic constitution must be accustomed to reasonable sports accessible to them (swimming, rowing, outdoor games) and to hygienic gymnastic exercises. Attention should be paid to non-restrictive clothing, especially in girls, etc. Preventive measures also include the hygiene of pregnancy (wearing a bandage) and the postpartum period (bandaging the abdomen and strengthening the abdominal muscles). In the therapy of acquired forms of gastroptosis, a properly fitted bandage plays a dominant role. The latter should not be higher than the most protruding point of the abdomen (up to the navel or slightly higher) and should not slip, for which purpose it is equipped with reinforcing straps made of tubular rubber or garters attached to stockings. Modern women's rubber corsets, tightly embracing the lower abdomen and reaching only to the navel, are quite suitable for this purpose. Such a bandage should be put on in a lying position, in which all the intestines move away to the back wall of the abdomen and are lifted upwards with the help of the bandage. You can check whether the bandage is applied correctly in front of the X-ray screen. In purely constitutional forms of gastroptosis, the bandage does not bring significant benefit, and its use is significantly hampered by the fact that it is almost impossible to adapt it to the flat abdomen of asthenics. In these cases, you can use a kidney-shaped pad, which exerts an even pressure on the lower part of the abdomen. To combat the asthenic habitus, a general strengthening of the body is necessary. For this purpose, enhanced nutrition is first of all appropriate, the brilliant results of which, especially during periods of exacerbation of suffering, have been proven on a huge number of cases. It should be carried out according to general principles, with frequent and small meals designed for high caloric content. Not only the accumulation of intra-abdominal fat plays a role here, but also the improvement of the general nutrition of the body, which has a favorable effect on the nervous system and on the endocrine glands, which function insufficiently in asthenics. Therefore, the auxiliary action of insulin as a means of increasing appetite and improving the assimilation of carbohydrates is sometimes especially appropriate here (5-10 units per day 1/2 hour before meals). All other methods of therapeutic action should be aimed at toning the body and strengthening the muscles, which is achieved by a number of physical methods of treatment: massage, gymnastics (specifically gymnastics of the abdominal muscles), hydrotherapy, electrification, reasonable sports, staying in a mountainous area or on the seashore. With a very sharply expressed pendulous abdomen with divergence of the rectus muscles, gymnastic exercises are for understandable reasons inappropriate. In these cases, attempts have been made to surgically contract the abdominal coverings and often with success.
Chronic constipation is treated according to general principles. All the physical methods of treatment indicated above, in conjunction with an appropriate choice of food, undoubtedly exert a favorable effect on constipation. Arsenic, iron, and especially strychnine are widely used in the form of subcutaneous injections (solutio "Triplex") or as pills. As for the methods of surgical treatment of gastroptosis, even among surgeons there is no unanimity of views. In any case, surgical intervention is permissible only in those cases where therapy proves helpless, but even here one has to think twice about the methods proposed so far (see below), since most of them proceed from incorrect pathogenetic concepts. Liek completely denies the usefulness of surgery in gastroptosis, finding that surgery in many cases yields no more than a simple bandage, and in psychically unstable individuals even worsens the condition. In general splanchnoptosis, surgery should have no place, since it presents few prospects for cure. Among the operative methods, the following are used. 1. Gastroenterostomy with a loop of 15-16 cm. It is indicated for atonic dilatation of the stomach with persistent stagnation of gastric contents, and for mechanical obstacles to evacuation (kinking of the duodenum). Its use is limited, as it gives complications (circulus vitiosus). 2. Gastroplication (see above); it cannot be considered a physiological method (see figures 1, 2, and 3, volume VI, article 321). 3. Gastropexy (see above); the question of its impeccability is doubtful (Rovsing's method) or remains not fully resolved (Perthes and Vogel's method, Hammesfahr's, etc.; see figures 1-4, volume VI, articles 319-320). 4. Beya-Bier's method (Beya, Bier) - suturing of the lesser omentum; the purpose of the operation is to lift the prolapsed stomach to its normal place and straighten the kink of the pylorus and duodenum. However, the lesser omentum is often very thin, difficult to suture, and the strength of the new position of the stomach is problematic. There are modifications of this method proposed by Roth and Malushev (Roth, Maluschew). According to Roth, 3 strips of broad fascia measuring 5x1.5 cm are sewn along the axis of the body onto the omentum sutured according to Bier; Malushev passes the stitches through the omentum not right under the liver, but about 2 fingers lower, so that its upper part remains free; after this, he applies another row of stitches, which on one side captures the omentum near the liver itself, and on the other - the stomach below and parallel to the lesser curvature, while the surface of the stomach is lattice-etched for the strength of adhesions with the omentum. Douglas, after suturing the lesser omentum, sews the gastropancreatic ligament (lig. gastro-colicum) for a distance of several centimeters to the anterior abdominal wall above the navel. 5. Coffey's and Braitsev's methods stand somewhat apart. Coffey fixes the greater omentum near the transverse colon in the transverse direction to the anterior abdominal wall in the upper third of the incision above the navel, thanks to which a support for the stomach is created from the transverse colon and transverse mesocolon. Braitsev, upon opening the abdominal cavity with a midline incision between the xiphoid process and the navel, performs extra-mucosal pyloroplasty; dissects the gastrocolic ligament in the transverse direction; sews the transverse mesocolon to the anterior abdominal wall in the transverse direction at the level of the 10th rib, with the left half of the mesocolon being sutured particularly carefully. A total of 6-7-8 stitches are required. The dissected gastrocolic ligament is caught with 2-3 stitches from above and below to the attachment site of the mesocolon. As a result of this method, the stomach occupies a normal position, retains the freedom of all its movements, empties quickly, decreases in volume, and after some time returns to normal; the transverse colon occupies a high position; its traction on the stomach is eliminated. 6. Deryuzhinsky, Schlesinger, and Martin are proponents of stomach resection, with Deryuzhinsky performing pyloric resection, and Schlesinger and Martin performing transverse resection. One can limit oneself to these methods. The question of the advantages of one or the other of them will be decided by the experience of the future.
I. Bichunsky, V. Braitsev. VI. Neoplasms of the stomach. Tumors of the stomach are divided into benign and malignant. Among the benign ones, myomas, fibromas, angiomas, and lipomas are described; all of them are located mainly in the submucosal, muscular, or subserosal layer of the organ; in general, they are rare and may not produce any clinical symptoms, being discovered mostly by chance at autopsy. In individual cases, when tumors are located on a stalk in the pyloric region, phenomena of invagination or strangulation in the pyloric ring are noted. Among epithelial benign tumors of the stomach, one can point to submucosal adenomas, arising apparently on the basis of developmental anomalies or regenerative processes in previously existing ulcerous changes. Such adenomas may ulcerate, produce stenosing phenomena, or serve as the starting material for new vegetations described by authors as misplaced pancreatic rudiments, displaced Brunner's glands, gastric adenomyomas, etc. Conventionally, polyps of the stomach, both single and multiple (polypositas ventriculi), can be classified in the category of benign tumors. Polyps are located mainly in the pyloric part, and are of various sizes and shapes, e.g., in the form of barely protruding rounded warts, in the form of papillae, sometimes mushrooms on a thin stalk (Figure 29), or resembling cauliflower; the surface of the polyps is sometimes ulcerated and bleeds. In their structure, they sometimes resemble the normal structure of the stomach, being as it were an eversion of the submucosal layer with the mucosa covering it; sometimes, however, they present significant atypism of structure. Depending on the content of blood vessels, glands, and the development of granulation tissue in the mass of the polyp, they are called angiomatous, glandular, or granulation polyps. Since a significant part of the polyps is of inflammatory origin, being a product of excessive regeneration (polypous gastritis), and another part is based on anomalies in the formation of the gastric mucosa itself, the classification of gastric polyps as tumors is conventional; malignant degeneration of polyps is sometimes observed (e.g., transition into cancer).
Cancer occupies the first place among malignant tumors of the stomach; gastric cancer is also the most frequent cancer among others and the most frequent malignant tumor in general. According to the statistics of Anschütz and Konjetzny, almost half of the fatal ca
ses of gastric polyps (a); b - pylorus.
cases of cancer falls on stomach cancer. According to data from Moscow prosectoriums for 1923–27, stomach cancer accounts for 37.86% of all cancers. These same data show that when calculated for adults (from 16 years of age), every 19th to 20th person dies from stomach cancer. The disease is observed significantly more often in men; thus, according to Kalb, mortality from stomach cancer in men in relation to the number of all deaths from cancer is: in France 60%, in Bavaria 85.9%, in Hungary 84.3%, in Italy 84.5%, in Sweden 84.8%, in Switzerland 90%, in England 73%; in tropical countries stomach cancer is rarer. The preferred age is between 40 and 60 years, but cancer of the stomach is not a great rarity even before 40 years of age; cases are observed in youth and even in childhood. There is an indication of a different relation of races to stomach cancer; thus, among North American Indians it allegedly almost never occurs (Levin). There are definite data testifying to the increased frequency of stomach cancer in recent years. Stomach cancers in the overwhelming majority of cases lie in the region of the lesser curvature, more often closer to the pylorus than to the cardia. However, in contrast to stomach ulcer, the cardial location of cancer is by no means a rare phenomenon. The size, shape, and character of growth of the cancer vary greatly. Thus, fungoid cancers [see separate table (pp. 115–116), Fig. 3] or flat ones, barely rising above the level of the mucosa, are observed; sometimes stomach cancer has no clear boundaries at all, manifesting as a diffuse thickening and induration of the entire stomach wall from the cardia to the pyloric ring (see separate table, Fig. 1); sometimes strong disintegration of the tumor is observed, encompassing its main mass, as a result of which certain difficulties arise in differentiating it from a stomach ulcer. On the other hand, some stomach cancers undoubtedly arise at the edges of chronic ulcers (in 2–10% of the latter); cicatricial changes at the base, along the serous cover, and along the borders of ulcers, and on the other hand, the development of cancer somewhere on one side of the ulcer indicate malignant degeneration of the latter. The boundaries of stomach cancer are not always determined by its external appearance and contours: there is a tendency of many cancers to grow for a considerable distance under the mucous membrane, for a long time without causing special changes on the part of the latter; this should be remembered during surgical resection of stomach cancers. Stomach cancers are distinguished into: glandular (adenocarcinoma, or cylindrical cell cancer), colloid (mucous), medullary, fibrous (scirrhus), squamous cell (rare). Such a subdivision is not entirely correct in the sense that almost any stomach cancer, if not in form, then in origin, is a glandular cancer, and only depending on its tendency to mucous degeneration (colloid cancer), on the quantity and degree of predominance of the cancer parenchyma (medullary cancer) or connective tissue stroma (scirrhus), does the corresponding nomenclature change. Soft white fungoid ulcerating, more or less distinctly limited cancers for the most part have the type of adenocarcinoma, while diffuse tumors without distinct boundaries more often have the character of colloid cancer and scirrhus. Regarding the latter, one should keep in mind the sometimes presence of sharp shriveling of a more or less significant part of the organ and even of the entire stomach, wherein cases are possible when even with the aid of microscopic examination individual groups of cancer cells are discovered only with difficulty among the proliferated stroma and sharply hypertrophied bundles of stomach musculature (linitis plastica maligna of French authors); certain (organic) forms of pyloric stenosis apparently belong here, presenting the theoretical interest of demonstrating as it were the process of spontaneous healing of cancer, its outcome into gastric cirrhosis. Stomach cancer metastasizes via the lymphatic, circulatory system, and also by implantation along the omentum, peritoneum, especially mucous cancers; in the first case, the glands of the lesser omentum, periportal, frequently upper retroperitoneal glands are affected, from where the spread of metastases can go both downward along the aorta and upward into the mediastinal glands, lower neck glands, in particular into the so-called Virchow's gland behind the left clavicle (in connection with the lesion of the thoracic duct). Via the circulatory system, metastases primarily affect the liver (via the portal vein system); the number and size of nodes in the latter can be most diverse, up to the simulation of a huge primary liver cancer. Metastases in distant organs are also noted, such as: lungs, pleura (with hemorrhagic pleurisy), kidneys, less often in bones, ovaries; the latter (especially in colloid stomach cancer) are often affected in pairs (retrograde via lymphatic pathways), wherein the contours of the organ can remain preserved for a long time (Krukenberg tumor of the ovaries, see). Growing through the entire stomach wall, cancer cells can implant along the peritoneum, omentum; solid dissemination of abdominal organs with cancer nodes is frequently observed with simultaneous fibrinous-hemorrhagic exudate in the peritoneal cavity; the omentum is thereby strongly thickened, shortened; subsequent stenoses of parts of the intestine are also possible. Perforation of stomach cancers is not a frequent phenomenon in view of the early development of adhesions. Complications with phlegmonous processes in the stomach itself are occasionally observed. The rest of the mucous membrane of the stomach not affected by cancer is usually in a state of more or less sharply expressed atrophy.—Secondary cancers of the stomach are observed relatively rarely; thus, cancer of the pancreas, large intestine, liver can grow into the stomach and subsequently, ulcerating from the inside, simulate primary stomach cancer; metastases to the stomach are observed in individual cases of bronchial cancer.

Figure 1. Scirrhus of the stomach (engulfs the entire organ): a-sharp thickening of the stomach walls and its folds (b); c-cardia; Py-pylorus. Figure 2. Fat necroses (o) of the omentum in pancreatitis. (After Ghon.) Figure 3. Multiple acute ulcers (a) of the stomach; b-small punctate hemorrhagic erosions; c-two acute ulcers cleansed of blood pigment; A-direction toward cardia; Py-toward pylorus. Figure 4. Fatty degeneration of the heart muscle: a-fiber with preserved cross-striation (fat droplets stained black with osmium). (Figures 1, 3, and 4 from preparations of the Path.-Anat. Inst. of the 1st Moscow State University). not having clear boundaries, more often have the character of colloid cancer and scirrhus. Regarding the latter, one should keep in mind the sometimes presence of sharp shriveling of a more or less significant part of the organ and even of the entire stomach, wherein cases are possible when even with the aid of microscopic examination individual groups of cancer cells are discovered only with difficulty among the proliferated stroma and sharply hypertrophied bundles of stomach musculature (linitis plastica maligna of French authors); certain (organic) forms of pyloric stenosis apparently belong here, presenting the theoretical interest of demonstrating as it were the process of spontaneous healing of cancer, its outcome into gastric cirrhosis. Stomach cancer metastasizes via the lymphatic, circulatory system, and also by implantation along the omentum, peritoneum, especially mucous cancers; in the first case, the glands of the lesser omentum, periportal, frequently upper retroperitoneal glands are affected, from where the spread of metastases can go both downward along the aorta and upward into the mediastinal glands, lower neck glands, in particular into the so-called Virchow's gland behind the left clavicle (in connection with the lesion of the thoracic duct). Via the circulatory system, metastases primarily affect the liver (via the portal vein system); the number and size of nodes in the latter can be most diverse, up to the simulation of a huge primary liver cancer. Metastases in distant organs are also noted, such as: lungs, pleura (with hemorrhagic pleurisy), kidneys, less often in bones, ovaries; the latter (especially in colloid stomach cancer) are often affected in pairs (retrograde via lymphatic pathways), wherein the contours of the organ can remain preserved for a long time (Krukenberg tumor of the ovaries, see). Growing through the entire stomach wall, cancer cells can implant along the peritoneum, omentum; solid dissemination of abdominal organs with cancer nodes is frequently observed with simultaneous fibrinous-hemorrhagic exudate in the peritoneal cavity; the omentum is thereby strongly thickened, shortened; subsequent stenoses of parts of the intestine are also possible. Perforation of stomach cancers is not a frequent phenomenon in view of the early development of adhesions. Complications with phlegmonous processes in the stomach itself are occasionally observed. The rest of the mucous membrane of the stomach not affected by cancer is usually in a state of more or less sharply expressed atrophy.—Secondary cancers of the stomach are observed relatively rarely; thus, cancer of the pancreas, large intestine, liver can grow into the stomach and subsequently, ulcerating from the inside, simulate primary stomach cancer; metastases to the stomach are observed in individual cases of bronchial cancer.
-I. Davydovsky. The etiology and pathogenesis of gastric cancer remain unclear. Hereditary predisposition undoubtedly plays a certain role. In 10–15% of patients with gastric cancer, a hereditary predisposition to the disease with neoplasms can be found. Families have been described in which the majority of members died of gastric cancer. The clinical opinion has been established that the occurrence of cancer is promoted by prolonged irritation of the gastric mucosa (irritation theory). The observations of Konetchny (in 90% of the surgically removed gastric cancers he examined, he found changes characteristic of gastric catarrh and atypical proliferation of the glandular epithelium) created the theory according to which chronic gastritis is a prerequisite for the disease of gastric cancer. The symptomatology and clinical manifestations of gastric cancer are quite diverse, which depends on the nature of the tumor and mainly on its localization. Soft forms of gastric cancer give rise to metastases more readily and to sharply pronounced phenomena of cancerous intoxication; whereas those localized at the outlet and inlet, causing narrowing of the inlet or outlet orifice of the stomach, contribute to the rapid development of difficulty in the passage of food and, together with intoxication—cancerous and putrefactive-fermentative—rapidly undermine nutrition and cause the development of secondary anemia and cachexia. The most favorable form in its symptoms and course is the scirrhous form of cancer of the body of the stomach. Developing slowly, without causing hemorrhages and intoxication, and without hindering the passage of food into the intestine, scirrhus of the body of the stomach runs a latent course for a long time, without symptoms or characterized only by the usual clinical signs of ordinary chronic gastritis. But even fungoid-polypoid cancer of the body of the stomach, prone to disintegration and hemorrhage, still does not produce such severe phenomena as cancer of the inlet and outlet of the stomach. Cancer of the body of the stomach creeps up slowly and imperceptibly. Initially, patients complain of a decrease in appetite, of mild dyspeptic phenomena expressed in the form of an indefinite feeling of pressure in the epigastrium after meals, and at times of belching and nausea. They willingly eat spicy, savory food, but plain healthy food is not to their taste; meat and fatty foods become repulsive to many. In other cases, until disintegration of the tumor occurs and a secondary severe gastric catarrh and putrefactive and fermentative processes develop, a satisfactory appetite is maintained for a long time; dyspeptic phenomena do not attract attention thanks to preceding chronic gastritis with achylia or hypochylia over a number of years. After a rather long period (4–8 months), pain frequently joins the indicated phenomena, which, however, does not bear such a character as in ulcer. The pain is dull, in the form of pressure or heaviness, intensifying after food intake, but not reaching the sharpness of the pain in gastric ulcer. Only in the case of extension of the tumor to the pancreas or its growth through the solar plexus do the pains become very intense, sharp, radiating to the back, to the spine and to the sides, preventing patients from lying and sleeping. Vomiting may be absent for a long time. But when putrefactive and fermentative processes begin to develop in the stomach, stinking, disgusting belchings and vomiting of stinking masses (smelling of carrion) of a coffee color due to admixture of blood appear. Vomiting in most cases does not occur frequently (not every day) and depends mainly on the quantity and quality of food, appearing a few hours after dinner, and in other cases immediately after eating. Women suffer from vomiting more often than men. Bowel movements are normal at first, but then constipation alternating with diarrhea may appear. Diarrhea usually sets in during the same period as vomiting and is caused by an accompanying catarrh of the intestines, caused by irritation by food entering the intestine, which has putrefied and has not been processed in the stomach. A patient who has already lost sufficient weight and grown pale begins to rapidly lose weight by this time, acquires an earthy complexion, loses strength; finally, edema appears, which portends near death. Examination of the patient in the first period of the disease yields indefinite results for a long time. Only progressive paleness and emaciation are noted. But there is a certain group of patients with cancer of the body of the stomach who, belonging to well-nourished people with a good complexion of athletic build, retain a blooming appearance for a long time even with an already developed and palpable tumor. Then these patients do not escape the general fate of cancer patients—they begin to lose weight, grow pale, and frequently general edema develops in them, depending, on the one hand, on the hydremic state, and on the other hand, on the accompanying heart weakness [dropsical type of gastric cancer (Ivanov)]. Most patients with gastric cancer, losing their subcutaneous adipose tissue, become as if mummified. Body temperature in most patients is below normal, but cases of gastric cancer are observed in which it is elevated and bears a septic character, accompanied by chills and sweats. The tongue, until secondary gastric catarrh and vomiting develop, is often clean, smooth, and shiny, resembling the Hunterian tongue in pernicious anemia. Toward the end of life, it becomes coated and dirty. Upon abdominal inspection and palpation, no deviations are detected for a long time. Methodical deep palpation, even in experienced hands with nutrition still well preserved in this initial period, rarely yields positive results. But as the patient emaciates and the tumor grows, the conditions for palpation improve; first, something indefinite in the form of «resistance» begins to be felt, and then in the standing position or in the lying position, better on an empty stomach and after bowel evacuation, a node or ridge can be palpated in the region of the stomach. At the moment of palpation, the patient feels pain. «The diagnosis is ready, and the sentence is almost ready» (Obraztsov). With further tumor growth and progressive emaciation, the tumor sometimes becomes visible, and if there are no adhesions around it, its respiratory excursions are noticeable. Examination of the gastric contents often yields characteristic changes from the very beginning. Free HCl disappears; with a reduced pepsin content, a significant amount of lactic acid appears (in 80–93% of cases), then blood, Boas-Oppler bacilli, pus, tumor particles. The absence of free HCl, however, is far from mandatory—according to Boas's statistics, HCl is preserved in 24.5%. The presence of gastric hemorrhages, determined by «examination of fecal masses for so-called occult blood, is an early and constant sign for gastric cancer (94.5%, Boas). Upon X-ray examination of the stomach, a filling defect at the site of the tumor [see separate table (p. 75–76), Fig. 12], disfigurement of the stomach silhouette are discovered, which is especially clear in the shrunken, as if crumpled stomach in scirrhus [see separate table (p. 75–76), Fig. 11]; peristalsis at the site of wall infiltration is absent (Groedel), food evacuation occurs at an abnormal rate. The filling defect is better detected on a radiograph than upon fluoroscopy, even in cases where the tumor captures the lesser or greater curvature. Small tumors of the posterior or anterior wall of the stomach are not revealed by a radiogram. In this case, a positive result is more likely yielded by gastroscopy. Blood examination reveals the presence of hypochromic secondary anemia, occasionally acquiring the features of malignant or severe aplastic anemia. Sometimes anemia comes to the foreground among other symptoms. The hemoglobin percentage drops to 20 and lower, poikilocytosis, polychromatophilia, normoblasts, myelocytes, and myeloblasts appear; a hemorrhagic diathesis may also develop. Cancer of the pyloric part of the stomach, characterized by the same symptoms, differs, however, in that dyspeptic phenomena, thanks to the rapidly ensuing narrowing of the outlet and stasis of the gastric contents, occur faster. Signs of gastric expansion appear fairly quickly: a sensation of heaviness and fullness in the epigastrium, belching, nausea and periodic vomiting, increase in stomach volume, visible peristalsis. Upon examination of the gastric contents, besides the absence of HCl, the presence of lactic acid, blood, Boas-Oppler bacilli, etc., stasis and the presence of fermentation acids are soon discovered, increasing the total acidity of the gastric contents (30–40–50 according to Ewald) with achlorhydria. Thanks to rapidly developing emaciation and better conditions for palpation, the pyloric tumor is diagnosed at a smaller volume than a tumor of the body of the stomach. Simple cancerous infiltration of the wall, thanks to the development of narrowing and muscle hypertrophy, already makes it possible to palpate a painful, uneven pylorus and diagnose the development of a tumor at the very beginning of the disease. X-ray examination yields a filling defect in the pyloric part [see separate table (p. 75–76), Fig. 10 and 12], increased peristalsis, later secondary atonia and delayed evacuation. Cancer of the cardial part of the esophagus, if it does not affect the cardia itself, runs a long time with indefinite symptoms of latent cancer of the body of the stomach and is diagnosed by a radiogram [see separate table (p. 75–76), Fig. 11]; the latter yields a distinct picture with high localization of the tumor, often only when producing a radiograph in the lying position of the patient. When the cardia itself is involved, the symptom of a cancerous, low-seated narrowing of the esophagus develops (see Esophagus).
Course. Patients with stomach cancer who are not operated on in the earliest period die within 1-2-3 years. Cancer of the body of the stomach proceeds more slowly; cancer of the pyloric and cardiac parts is more rapid. The life expectancy of a patient with scirrhus of the body of the stomach is from 2 to 5 years. Diagnosis of stomach cancer is difficult at first, while there are only indefinite dyspeptic phenomena and progressive anemia and cachexia, but no palpable tumor and blood in the gastric contents and fecal masses. Diagnosis is based on three cardinal signs: 1) the repeated detection of occult blood in the stool and gastric contents using an impeccable method for its determination (after an appropriate diet), 2) a palpable tumor in the stomach area, and 3) a filling defect on the radiogram. Although these signs can also be observed in other stomach tumors (sarcoma, polyps, syphilis, etc.), this is of almost no practical significance due to the rarity of these tumors (1-1.5%). It is most difficult to differentiate stomach cancer from a callous peptic bleeding ulcer, since all the indicated cardinal symptoms can be observed with it. The proposed biological reactions for cancer: Abderhalden, Maragliano, Bothelo (Abderhalden, Maragliano, Bothelo), etc., and the reactions of Zaleski (in urine), Daweys, etc., are not specific for cancer. One can use the Bothelo and Daweys reactions in view of the simplicity and convenience of their performance, but one must be cautious with conclusions. In case of doubt, it is better to resort to exploratory laparotomy, and microscopic examination of the resected area establishes the diagnosis. Therapy. Thorough suspicion of stomach cancer already requires surgical intervention—exploratory laparotomy, since internal treatment does not cure cancer, and early surgery gives a lasting effect in 33% (Schmieden-Kallmann). But cancer of the vault and cardia of the stomach is inoperable and, just like large tumors of the body and pylorus with obvious metastases or far-advanced cachexia, is not radically operated on. For cancer of the entrance part, only gastrostomy is performed; for cancer of the pylorus, gastroenterectomy. With internal treatment, one must first of all take care of maintaining the patient's hope for recovery and try to alleviate their inevitable death. It is necessary to prescribe an easily digestible, light, nutritious diet with high caloric content and a large amount of protein, as for example with a less strict diet for a stomach ulcer, with the addition of light salty snacks, cream ice cream, a little cognac, good wine, fruit juices. Of the medications, bitters, hydrochloric acid, gastric juice, anti-fermentative substances, and painkillers are prescribed. It is recommended not to spare morphine, pantopon, narcophine, etc. for the patient's suffering, and subcutaneous cardiac remedies in the development of dropsy and asystole. With narrowing of the pylorus by a tumor and the absence of bleeding, systematic washing of the stomach with lukewarm water with the addition of sodium salicylate (1:1,000) is useful. For vomiting and cachexia—nutritious enemas of glucose. X-ray and radiotherapy do not bring benefit. Sarcoma of the stomach is a fairly rare condition (1% of all stomach tumors); it is observed more often in the pyloric region and on the greater curvature; microscopically, sarcomas are of various characters: round-cell, spindle-cell, polymorphic, angiosplastic, lymphosarcomas, myosarcomas. The low tendency of stomach sarcomas to ulcerate is noted; they grow slowly, but can reach gigantic sizes, which usually does not happen with cancer; stenoses are rare; metastases are not observed in the majority of cases. Sarcoma develops in the stomach secondarily more often than cancer. Usually this is a lymphosarcoma infiltrating the stomach wall. Metastases in the glands soon appear, and the spleen enlarges. Sarcoma of the stomach is observed at a young age (between 15 and 30 years) and is distinguished by a rapid course (6-7 months), ending in death. The symptomatology of stomach sarcoma differs almost not at all from that of stomach cancer and is conditioned mainly by the localization of the tumor. The difference is the fairly frequent enlargement of the spleen and lymph glands and leukocytosis with lymphocytosis. It is possible to recognize stomach sarcoma and distinguish it from cancer only by microscopic examination of pieces obtained by probing or excised metastases from the skin, from the glands. Therapy in the early period is surgical, in the late period—dietary-symptomatic; X-ray and radiotherapy. The technique of surgical intervention boils down to partial and circular resection, as in stomach cancer.
N. Strazhesko. Surgical treatment of stomach tumors. Benign stomach tumors (adenomas, polyps, fibromas, fibromyomas, adeno-myomas, myomas, lipomas, angiomas, and lymphangiomas) sometimes disrupt the activity of the stomach to such an extent that surgical intervention becomes necessary. Depending on the case, the operation usually amounts to a partial or circular resection of the stomach. In stomach cancer, the main task is to remove the neoplasm in the earliest possible stages of its development. Modern surgical technique makes it possible to resect stomach cancer with any localization and any extent of involvement of the stomach itself. Nevertheless, in reality, the number of cases subjected to radical operation constitutes a small percentage of the total mass of stomach cancer diseases. There are several reasons for such discrepancies between reality and theoretical possibility. First of all, neither the size of the tumor nor the duration of the disease is in direct connection with the dissemination of the neoplasm; involvement of the glands begins in most cases early, and in some cases dissemination by other pathways (peritoneum, liver) proceeds even faster than along the lymphatic pathways. The tumor itself remains free from adhesions only in a minority of cases, but for the most part merges with enlarged glands into a single mass, and then grows into neighboring organs as well. The possibility of radical operation depends chiefly on the stage of the disease. Meanwhile, many forms of cancer, especially of the body of the stomach, do not manifest themselves with any symptoms for a long time, and the first thing that attracts the attention of the patient, those around them, and even the doctor is developing causeless cachexia; in most cases, early stages of cancer are overlooked either due to the absence of any clinical manifestations or because the symptoms are attributed to other forms of stomach diseases. On the other hand, the patients themselves seek medical help too late or do not decide in time on the operation offered to them. But even in cases that seem early, in the presence of a small tumor, dissemination through the glands sometimes manages to go beyond the limits accessible for removal. Resection of the stomach for cancer can only be considered more or less radical when the neoplasm is excised widely within completely healthy walls. From the diagram of the arrangement and course of the lymphatic pathways of the stomach itself, it is evident that from the pyloric section the lymph, and consequently the possible spread of the tumor, goes predominantly along the lesser curvature towards the cardia; therefore, the excision along the lesser curvature must be performed at a distance of 5-6 cm from the visible borders of the neoplasm; practically this leads to the fact that the resection must almost always reach almost to the cardia itself. Conversely, in the direction of the duodenum, the neoplasm does not tend to spread and rarely crosses the borders of the pylorus; this makes it possible here to resect at a distance of 2 cm. However, the main difficulty of radical operation lies in the removal of the affected lymph glands. The first to be affected are the glands lying along the lesser curvature; their chain reaches the site of entry of the esophagus. From them, the lymph is directed to the glands surrounding the celiac artery and further to the glands lying at the aorta. The glands of the lesser curvature often merge with the tumor mass into a single whole, and through them the tumor fuses with the liver and diaphragm. From the greater curvature, the lymph flow is directed to the glands embedded between the leaves of the gastrocolic ligament, and from there to the glands at the head of the pancreas. The efferent ducts of these latter glands are directed to the glands lying along the upper edge of the pancreas and along the hepatic artery. The removal of these glands sometimes presents an unachievable task, as well as the aortic glands. In addition, in the presence of involvement of these glands, one can be sure of the involvement of even more distant glands, and resection becomes pointless. Thus, the contraindication to excision is not so much the size of the tumor itself as the degree of involvement of the lymph glands, dissemination, and finally adhesions and immobility of the tumor. Absolute contraindications are ascites and dissemination through the peritoneum, metastases in other organs, ingrowth of the tumor into the liver (unless the underlying part of the liver can be resected together with the tumor). Ingrowth of the tumor into the mesentery of the transverse colon and its transition to the bowel itself allow resection on condition of simultaneous excision of the bowel as well. Similarly, partial excision of the head of the pancreas is also possible. Adhesions of the tumor with the abdominal walls and other organs make the tumor poorly mobile and usually preclude resection; however, much depends here on the peculiarities of the case and individual evaluation of the feasibility and difficulty of the operation. Details deciding the question of the removability of the tumor, in most cases, even those that seem very favorable, can be established only with the abdominal cavity opened, and therefore the question of exploratory laparotomy must be posed broadly. Of the patients referred to surgical departments, hardly a fourth part is accessible to radical operation (24.6% according to Weil, 30% according to Spasokukotsky). However, these figures have relative significance; some surgeons go further in the indications for resection, operating even under conditions that obviously do not allow hope for the radical removal of the tumor, and, giving preference to resection under all conditions over gastroenterostomy, bring the number of resections to 62% of patients referred to surgical departments (Finsterer). As for the outcomes of stomach resections for cancer, the immediate postoperative mortality, if we compare the data of previous years and recent times, has significantly decreased, yet it still remains high, as can be seen from the following data: in Pauchet, out of 260 resections for cancer, fatal outcomes constituted 27%, in Persson out of 361 cases—28%, in Petrov out of 48 cases—35%, in Velikoretsky out of 110 cases—42%. Any complications and expanded indications in the application of resections significantly worsen the prognosis. If all cases are divided into groups depending on the stage of the disease and the complexity of local conditions, the figures of immediate mortality fluctuate within wide limits—from 7% to 37%. In total and subtotal resections, mortality is not lower than 50%. In the future, the overwhelming majority of those who underwent the operation perish from recurrence originating predominantly from the glands; the average life expectancy after resection, if we take large statistics, is equal to 11/2 years. Only about 1/4, at best 1/3 (Finsterer, Weil, Hartmann, Mayo) of those who underwent the operation remain without recurrence for more than 3 years. 16% live for more than 5 years, 14% for more than 10 years, but in individual cases recurrences also occurred after the expiration of 13 years. After total extirpations in the cases of Wrede and Moynihan, patients remained alive 31/2-4 years later. For the majority of cases, resection is a palliative operation, but even with obviously non-radical removal of the tumor, patients after resection are in a more favorable position than after gastroenterostomy, already because they are spared from a decaying or bleeding tumor. Thus, the results of radical operation at the present time still remain far from satisfactory, and further successes should be expected not so much from the development of surgical technique as from the earliest possible diagnosis and the earliest possible operation. With the current state of the question of diagnosing stomach cancer in the early stages of its development, which is often very uncertain, patients should be persuaded to undergo surgery at the first suspicion of cancer, without stopping at exploratory laparotomies. In these stages, exploratory laparotomy does not present great danger and cannot be put on the same footing with exploratory operations relating to the late period, when indeed even such an innocent intervention as exploratory laparotomy presents a great danger in view of successive complications on the part of the heart, lungs, and so on. The operative methods used for the excision of stomach cancer always consist of circular resection. In cancers occupying the pyloric region and spreading from here further to the body of the stomach, the resection begins from the duodenum and captures the body of the stomach, depending on the spread of the neoplasm, to a greater or lesser extent, while, as indicated above, from the side of the lesser curvature, the boundaries of excision must go far towards the cardia, often to the site of entry of the esophagus. With extensive involvement of the stomach, subtotal or total resection is performed. In exceptional cases, when the tumor occupies the middle of the greater or lesser curvature and has moreover limited dimensions, circular resection of the body of the stomach is used, and both segments of the stomach are sutured end-to-end. The usual methods of resection are the first and second methods of Billroth (see Billroth operations on the stomach). (Regarding other modifications of resections, see below — operations on the stomach). For cancer occupying the cardiac section of the stomach, resection of the cardia is possible, but the methodology of the method is not yet developed to such an extent that to this day case studies number only a few dozens of cases with a mortality of about 70%.
(see resection of the cardia). - Palliative operations for stomach cancer. In cases of unresectable stomach carcinomas, practically important palliative operations on the stomach are: gastrectomy and gastroenterostomy. Both find application in cases accompanied by stenosis of the cardia, resp. the pylorus. Gastroenterostomy in cases of closure of the pylorus by a tumor can give a brilliant, sometimes quite prolonged effect, but is completely useless for those cases where one is dealing with a carcinoma of the body of the stomach without phenomena of motor insufficiency; therefore, if during laparotomy in such cases it turns out that the tumor is unresectable, it is preferable to refuse to create an anastomosis and to close the wound. (On the outcomes of gastroenterostomy in cancer, see Gastroenterostomy.) With very extensive lesion of the stomach walls, sometimes no space is found for creating a gastroenterostomy; in such cases, one has to resort to jejunostomy. In cancers of the cardia, palliative intervention in the form of gastrostomy is indicated only at that stage when the patency of the cardia is impaired to such an extent that a sufficient amount of semi-liquid food is introduced with difficulty and patients begin to experience hunger and lose weight. Only in those cases when the patient has already undergone exploratory laparotomy and the tumor has been recognized as unresectable, should one, in the presence of a cardiac tumor, nevertheless conclude the operation by creating a gastric fistula in case of a very probable subsequent obstruction; the creation of a fistula in itself will only slightly complicate the exploratory laparotomy and will not aggravate the patient's condition. V. Dobrotvorsky.
VII. Stomach ulcer. Stomach ulcer was first isolated into a separate clinical unit by the Frenchman Cruveilhier between 1829 and 1838. Stomach ulcer is one of the most frequent diseases of the stomach. It is characterized by a tendency to relapse. The etiology and pathogenesis of stomach ulcer have not been finally elucidated. Stomach ulcer is not equally distributed in all countries. Statistical data. There are indications that stomach ulcer is rarely encountered in Negroes and southern Chinese, as well as in some parts of Brazil. According to summary data from Moscow prosectoriums for 1923–1927, chronic stomach ulcer as the main disease figures in 1.17% of all adult deaths from 16 years of age (251 cases out of 21,388 autopsies), and in recent years (1926–1927) the percentage is lowest (0.9 against 1.3 for 1923–1925). The question of the frequency of stomach ulcer in its entirety cannot be considered elucidated, in particular the significance of nutritional conditions, starvation, and various general diseases is not entirely clear. The significance and participation of autonomic neuroses are more or less considered elucidated; apparently, the mass development of such neuroses influences the increased frequency of the development of stomach ulcer; on the other hand, one must not forget about the better diagnostics of ulcers in recent years. In women, the disease is encountered approximately twice as often as in men; the age is usually from 20 to 40 years, but children also fall ill (both newborns and older ones). Pathological anatomy and pathogenesis. It is customary to distinguish acute and chronic stomach ulcers. Both in turn can be single and multiple. Acute ulcers [see separate plate (art. 103–104), fig. 3] constitute a very frequent phenomenon; their size ranges from a barely noticeable point to several centimeters in diameter; the shape is usually rounded or oval. Usually these ulcers have a more or less superficial character, as a consequence of which they are also commonly called erosions; in rarer cases, the defect concerns the entire thickness of the mucosa or extends beyond its limits, and finally in individual cases acute ulcers can have a perforative character. The bottom of the ulcer is either clean or (more often) brownish-black; the latter is associated with hemorrhage and the formation of hydrochloric acid hematin under the influence of gastric juice (hence the term "hemorrhagic erosions of the stomach"). Hemorrhages should apparently be considered both as a factor directly traumatizing the mucosa and as a factor producing the ulcer; the subsequent digesting action of the gastric juice at the site of such tissue destruction produces a defect of it; in other cases, the possibility of primary necrosis of the mucosa and subsequent bleeding is not excluded. Acute erosions are observed in various areas of the stomach, predominating however in the body and in the prepyloric region; punctiform erosions are more often located closer to the greater curvature, while larger ones are closer to the lesser curvature. The stomach contents in the presence of erosions are colored a more or less clear brown color, especially the mucus covering the defects. Already by the end of the first day, clear reactive (inflammatory and regenerative) processes arise at the bottom and edges of the ulcer, and in the majority of cases after 3–6 days, depending on the size of the ulcer and other circumstances (see below), the ulcer heals without a trace or (with larger ulcers) leaves a small stellate scar, sometimes covered with not entirely typically constructed mucosa. Experiments on animals have shown that even very significant mucosal defects heal in this way. Chronic stomach ulcers have the greatest practical interest. Usually they are single, less often 2–3 or more ulcers are observed; the shape is usually round (ulcus rotundum), sometimes ovally elongated, irregular; often along the line of the lesser curvature, butterfly-like ulcers are observed with wings located on the anterior and posterior walls. As a rule, chronic ulcers lie close to the lesser curvature or directly on the latter along the "stomach pathway" (Fig. 30) or closer to the anterior wall; the pyloric region, as well as the region of the vestibuli, isthmus of the stomach ("narrow places" of the stomach) give the main number of chronic ulcers. These ulcers are distinguished first of all by the significant density of their bottom and edges, as if callousedness of the latter (ulcus callosum); sclerosis can encompass the entire thickness of the stomach and extend beyond the limits of the latter (perigastritis), whence fibrous adhesions of the stomach with the liver, spleen, pancreas, and transverse colon frequently arise. The bottom of the ulcer is smooth or rough, sometimes clearly grainy, e.g., when parts of the pancreas underlie it; sometimes a bleeding or thrombosed vessel is visible at the bottom (see separate plate, Fig. 1). Especially frequently, the coronary arteries of the stomach (more often the upper), as well as the splenic and gastroduodenal arteries, are subjected to erosion; the significant caliber of these arteries and well-developed anastomoses cause the special danger of these hemorrhages and their frequent fatal outcome. The depth of the ulcer is unequal in various places

Figure 30. Magenstrasse. (After Aschoff.)
stomach; it is considered characteristic when the edge of the ulcer directed toward the cardia is deeper, steeper, and somewhat undermined; conversely, the opposite edge is low, gradually descending in a terraced manner. Such relationships give the profile of the ulcer an irregularly funnel-shaped appearance with an acute angle facing the cardia. This phenomenon is explained by the fact that the ingested food, on the one hand, and strong peristaltic movements, on the other, produce a purely mechanical shift of the mucous membrane in the pyloric direction, as a result of which the cardiac side forms a sort of overhanging ledge, while the pyloric side is flattened and smoothed out, and the musculature beneath it is partially exposed (see below). The steep and deep cardiac edge of the stomach ulcer is clearly revealed during fluoroscopic examination in the form of the formation of the so-called niche [see separate table (p. 75-76), Fig. 7, 8, and 9]. In the already formed ulcer, and specifically beneath its steeper cardiac edge, a certain stagnation of the acidic contents of the stomach occurs, which also contributes to the corrosion and deepening of this exact part of the ulcer base, increasing its funnel-shaped nature. The former opinion, which explained the funnel shape and the undermining of the cardiac edge by a peculiarity of the vascular supply of the wall (of the infarct-formation type), has now been abandoned. The terraced nature (step-like structure) of the pyloric side of the ulcer is caused by the layer-by-layer corrosion of the muscle bundles of the stomach wall and specifically by the fact that this corrosion, as it deepens, encompasses an increasingly limited area of musculature. Strong peristaltic movements here also produce a certain shift of the muscle layers as their continuity is disrupted. Microscopically, the base of the ulcer is represented by granulation tissue of various ages and maturity; the most superficial layer of the tissue is often in a state of necrobiosis or is covered by a scab, exudate, in connection with the action of the stomach contents, as well as possible secondary infections, including fungal ones; thus, on the question of the progressive growth of the ulcer, Askanazy puts forward the special significance of the thrush fungus. In long-standing stomach ulcers, their base is completely devoid of musculature, and a more or less dense scar tissue is visible with perivascular infiltrates that usually extend onto the serous cover and nearby parts of the organs. When studying the edges of the ulcer, however, it turns out that muscle bundles do exist; at the cardiac (steep) edge they are located very high, as if directly fusing with the mucous membrane; at the opposite (pyloric) end, the muscle layers lie deep beneath the mucosa, appearing on the surface of the ulcer at the sites of the terrace steps. The vessels of the base of the ulcer are often sclerosed, which, however, is explained by the presence of a chronic process in the surrounding tissue and cannot be interpreted as the moment causing the development of the ulcer. It is not excluded, of course, that such a state of the vessels lowers the regenerative capacities of the tissues and contributes to the progressive development of the ulcer. Sometimes
Figure 1. Round ulcer of the stomach with perforation (e), with corrosion and thrombosis of vessels (g); a - cardia; b - pylorus; c - greater curvature with phenomena of etat mamelonne; d - lesser curvature. (From the museum specimen of the Pathologo-Anatomical Institute of the 1st Moscow State University). Figure 2. Three diverticula of the duodenum: 1 - duct. pancreat. accessor.; 2 - papilla Vateri. (From the museum of the 1st City Hospital named after N. I. Pirogov). Figure 3. Fungous (fungoid) cancer of the stomach (a) near the cardia (b); c - pylorus; d - the so-called etat mamelonne in the region of the greater curvature. The tumor has an uneven, partly ulcerated surface, of a delicately spongy appearance in the remaining parts. (From the museum specimen of the Pathologo-Anatomical Institute of the 1st Moscow State University).
To the article Diverticulum, Stomach. occasionally deep in the base of the ulcer, a strong proliferation of nerve fibers of the amputation neuroma type is found—a circumstance of definite interest in explaining the particularly intense pains in this affliction. It can be considered established that a chronic stomach ulcer develops from an acute one, and the only question that arises is under what conditions the latter heals and under what conditions it transitions into a chronic one. A completely exact answer to this cannot be given; only the following is known: 1. The depth and width of the erosion are of very relative significance; induced experimentally, such erosions and ulcers as a rule heal well, and only very significant defects with simultaneously severe circulatory disorders (such as, for example, upon the introduction of adrenaline into vessels) could sometimes be converted into a chronic ulcer. Other things being equal, the size and depth of the ulcer will matter, for example, with increased acidity, with a corresponding general predisposition (vegetative neuroses, etc.). 2. The most important factor influencing the transition of an acute ulcer into a chronic one is the fact of its particular localization: acute ulcers can arise everywhere, but the transition into chronic ones is as a rule observed only along the lesser curvature, i.e., the "stomach pathway," and in the pyloric region. This depends primarily on functional-mechanical factors, specifically the constant traumatization of the arising ulcers by the food passing here; such traumatization is especially promoted by the presence of narrow places in the stomach (isthmus, vestibulum, pyloric region), which in fact are the most frequent sites of ulcers. Acting in the same unfavorable direction in the sense of healing of acute ulcers are: weak mobility, a certain rigidity of the folds of the mucous membrane of the lesser curvature, relatively weak anastomosing of the vascular network in the region of narrow places (not shared by all); the insignificant thickness of the mucosa itself, low production of mucus which would cushion the traumatization, significant duration of irrigation by gastric juice of this region (even with an empty stomach), and finally the very structure of the glands of this region, their special sensitivity and weak regenerative capacity. All this turns the entire question of the transition of an acute ulcer into a chronic one into a question of the localization of the ulcerous process itself. Nauwerk and Konjetzny put forward their theory of the development of chronic stomach ulcer, pointing to the significance of primary chronic ulcerative gastritis. One of the usual outcomes of chronic stomach ulcer is its healing with a scar; the latter is always stellate in character, resembling the scar from a purse-string suture; microscopic examination reveals in the scar an atrophic and often atypically constructed mucosa lying directly on scar tissue very rich in elastic fibers. Scars of the pyloric region frequently give rise to stenoses and phenomena of obstruction; the latter may arise, however, even with small stenoses and apparently in the absence of such, depending mainly on accompanying spastic moments caused by the ulcer itself. Deep disfiguring scars of the vestibulum region can produce changes in the shape of the stomach in the form of the so-called hourglass stomach. The transition of a stomach ulcer into cancer is apparently not a great rarity (according to various authors, the percentage of such ulcers varies greatly, with the majority accepting figures from 2% to 10%). In each such case, the transition must be verified by histological examination (see above—tumors of the stomach), but even with this, significant difficulties may arise. Perforation of the ulcer is one of the most frequent complications in its course; it can occur into the peritoneal cavity, the lesser omentum, less often into the large intestine, with symptoms of the so-called lientery, into the liver, into the spleen. Perforation into the peritoneum does not always end in acute general fatal peritoneal inflammation; the acidic, bacterial flora-poor contents in a stomach ulcer sometimes produce the picture of chronic adhesive peritonitis with encapsulation of food particles, which during surgery or autopsy can simulate peritoneal tuberculosis. From the above-mentioned classical ulcers of an acute and chronic character, one should fundamentally distinguish the ulcerative processes in the stomach observed in acute and chronic gastritis, in tuberculosis, poisonings by caustic substances, as well as ulcers arising from surgical interventions, for example, upon placing clamps on the stomach and the like.
I. Davydovsky. Etiology. In the USSR, stomach ulcers, as can be seen from the cited data, were previously rare, especially among the rural population. Recently, the number of patients with stomach ulcers has increased significantly; however, there are no exact statistical data on this issue. The increase in the number of stomach ulcer patients in the USSR is explained by the changed nutritional conditions of the population, the mass development of vegetative neuroses, as well as the improvement in the diagnosis of stomach ulcers. A stomach ulcer is a disease predominantly of adults between 20 and 40 years of age; it also occurs in children. Heredity and constitution play a significant role in the etiology of stomach ulcers. Families are observed where the majority of members suffer from stomach ulcers. Predisposing factors include chronic catarrh, arteriosclerotic changes in the gastric vessels, chronic inflammatory processes in other abdominal organs (such as, for example, appendicitis, cholecystitis, adnexitis in women, etc.) and, chiefly, a change in the tone of the autonomic nervous system, and perhaps also altered influences of trophic nerves on the tissues of the gastric wall. There are many theories to explain the occurrence of stomach ulcers. It must be thought that the occurrence of stomach ulcers is caused by a whole series of sets of conditions, which are operative in various combinations with each other and with a certain constitutional predisposition. The main factors contributing to the occurrence of a stomach ulcer and its transition to a chronic state, as well as to relapses, according to modern views, are: a) circulatory disturbances depending on functional anomalies in the vascular system (O. Müller, Heimberger, Skulsky) or on arteriosclerosis and thrombosis of the gastric vessels and hemorrhage into the wall (Gruber, Virchow); b) a decrease in the viability of the gastric mucosa due to disturbed circulation in it and the special environmental conditions in which its cells live (Ballowitz, Zimnitsky), consisting in acidosis; c) an increase in gastric juice secretion, and d) mechanical damage to the mucous membrane by coarse and irritating food, especially in narrow parts of the stomach (Aschoff). The manifestation of the influence of the above factors is facilitated by a disorder in the equilibrium of the autonomic nervous system (Kraus, Bergmann), on the basis of which cellular and tissue metabolism throughout the organism, salt balance, acid-base equilibrium are altered, and blood circulation in the gastric mucosa is easily disturbed under the influence of spasm of both the gastric musculature and the vessels themselves, hypersecretion arises, especially in the presence of constant irritation in the celiac ganglion, which sends secretory, motor, vasomotor, and trophic nerves to the stomach. Irritation in the celiac ganglion arises and is maintained thanks to an inflammatory process in it itself or reflexively from the side of inflamed organs connected with it by nerve pathways (Rössle). Under these conditions, any bruising in the gastric mucosa resulting from trauma or mechanical irritation, ischemia from prolonged spasm or thrombosis of its vessels easily contribute to the formation of an erosion on the mucosa, which, due to hypersecretion and constitutionally lowered tissue viability and the special state of the environment (acidosis), does not heal with a firm scar, but turns into an ulcer, especially if the ulcer surface becomes infected (for details on the pathogenesis of peptic ulcers, see Duodenal ulcer). Clinical picture. The symptomatology of a stomach ulcer is extremely diverse. Sometimes a stomach ulcer runs without symptoms and heals with a scar or causes stomach perforation without giving prior notice of itself either to the patient or the attending physician. This is observed more often when an uncomplicated ulcer is localized on the lesser curvature or on the walls of the body of the stomach; however, with a systematic study of the gastric contents or feces, the presence of blood can also be periodically detected in these cases (Boas occult bleeding). The asymptomatic course of a stomach ulcer still represents an exception. Most stomach ulcers in a typical course are accompanied by characteristic subjective and objective symptoms. Of these, the typical ones are: "ulcer pains," acidism, bloody vomiting, bloody stools (melaena), constipation, changes in the sensitivity of the abdominal wall in the region of the stomach and in the corresponding peripheral zones, changes in stomach secretion (hypersecretion), the presence of blood in the gastric contents, and X-ray symptoms characteristic of a stomach ulcer. Only in rare cases are all without exception of the enumerated signs present—in the majority of cases of stomach ulcers, one or another is absent (atypical course of stomach ulcer). The most typical course is an ulcer of the pyloric region of the stomach and an ulcer of the lesser curvature. An ulcer of the pyloric part of the stomach is characterized by the periodicity of pain, the late onset of pain and often nocturnal hunger pains [pyloric syndrome of Cynn (Soupault)], as well as, even in the absence of complications, a painful sensation of fullness and pressure in the stomach region and a tendency to vomit; these phenomena are explained by the longer duration of the gastric digestion period, slow evacuation of food from the stomach due to supersecretion and pyloric spasm. With this localization of a stomach ulcer, periods of exacerbation in the form of paroxysms similar to tabetic crises are replaced by periods of relative calm; this is explained rather by the restructuring of the whole organism and the autonomic nervous system influencing the diseased organ than by anatomical changes in the stomach ulcer itself and around it (Bergmann). The restructuring itself occurs thanks to the law of cyclicity of the course of biological processes in the organism (Goldscheider, Pletnev). Pains in the form of either pressure or burning or pure cutting pain radiating to the back and under the right shoulder blade occur not immediately after eating, but two, three, four hours later, sometimes considerably later. They often reach great intensity, with the patient striving to find a specific position in which the pain is less, and remaining motionless until it passes. These pains can be caused by various reasons—in the majority of cases, especially in uncomplicated ulcers, they depend on convulsive contractions of the stomach, in particular pylorospasm on the basis of an enhanced reflex from the duodenum upon the entry there of more acidic gastric contents than normal. Less commonly, pains arise as a result of a perigastritis complicating the ulcer and adhesions of the stomach with other organs. Even normal movements of the stomach in these cases can cause pain. Pains are accompanied by heartburn, eructation, even vomiting of acidic masses, after which relief occurs. Late pains are explained by the highest rise in the secretion curve at this time and prolonged pyloric spasm. Then the pains subside, only to resume in five or six hours, usually at night. The patient, knowing about them, goes to bed having placed a glass of milk near him or having prepared a dose of soda. He knows that these pains will wake him and that they can be quieted only by the introduction of food, soda, etc. These nocturnal pains are sometimes accompanied by acid, abundant vomiting without food, after which they pass. Pains are caused by the accumulation of gastric juice in the stomach due to its constant secretion. Upon objective examination of the patient, emaciation and pallor are often noted, depending on inadequate nutrition due to the fear of causing pain by taking food, and sometimes on periodically recurring blood loss. Examination of the stomach region in most cases yields nothing. With significant emaciation, two to three hours after dinner, the tense stomach is visible through the abdominal walls. Upon palpation, especially in emaciated subjects, the pyloric part of the stomach is easily felt in the form of a tumor, constantly painful, sometimes nodular (in ulcus callosum). Palpatory mobility of the pylorus is limited in the case of perigastritis. Percussion and palpation in the region of the entire stomach and pylorus in uncomplicated cases are usually not accompanied by pain, although there are exceptions. With complication by perigastritis, hyperalgesia appears above the navel, in the region of the right rectus abdominis muscle, pain in this place upon percussion (Mendel's sign), tension in this area and limited tympanitis in the region of the right costal arch, between the nipple and parasternal lines (Strazhesko's sign), and sensitive paravertebral Boas points between the 10th and 12th vertebrae on the right, sometimes tenderness of the 9th–12th spinous processes of the vertebrae (Oppenchowski / Oppenkowski's points) and less commonly horizontally located hyperesthetic Head zones in the region of the 9th–11th intercostal spaces on the right. Upon examination of the gastric contents, supersecretion is revealed in the majority of cases, especially during periods of exacerbation, when abundant juice secretion is observed with an empty stomach. If hypersecretion in stomach ulcers in general is encountered no more often than in half of all cases and ulcers are observed with subsecretion, then for a pyloric ulcer supersecretion is the rule, and exceptions are rare. Supersecretion appears with the Ewald-Boas test breakfast, but even more sharply with fractional prolonged examination after liquid breakfasts, as well as with repeated loading according to Zimnitsky. Figures of total acidity reach 100–110, free HCl 80–90. In this connection, secretio continua is frequently observed, and on an empty stomach one can find 80–100 cm3 of gastric contents of high acidity in the stomach. At the same time, not only an increase in acidity is observed, but also an increase in the digestive power of the gastric contents. An increased amount of mucus is often found in the contents, which is an expression of concomitant gastritis. The presence of blood cannot always be detected, but upon repeated examinations it is usually possible. During an X-ray examination, during fluoroscopy and simultaneous palpation, as well as on radiographs (a series of radiographs and moreover in various positions is obligatory), one often finds not only completely clear symptoms of an ulcer, but also of its specific localization; furthermore, the deeper the ulcer and the more complications it has given, the more definite signs characterize it. However, it must be remembered that not all gastric ulcers, even with the best technique, are diagnosed by X-ray examination. During fluoroscopy, enhanced peristalsis is detected, sometimes segmenting; with simultaneous palpation, tenderness of the pyloric region, limitation of its mobility and its displacement to the right in the case of perigastritis, an indentation on the opposite side in the contour, prolonged spasm of the pylorus; on radiographs, a small niche with deformation of the contours of the stomach is sometimes discovered. The intermediate layer is large due to hypersecretion; because of it, even before the introduction of the contrast medium on an empty stomach, liquid contents can be detected in the stomach by fluoroscopy. Upon repeated fluoroscopy, delayed evacuation is discovered, and after 5–6 hours 2/3 of the contrast mass is often found in the stomach, significantly diluted due to supersecretion. An ulcer of the pyloric part is rarely accompanied by reflex spasm of the cardiac part of the stomach; if this is observed, in most cases the spasm depends on a concomitant general vegetative neurosis or a second ulcer near the entrance of the stomach. Irradiation of pain to the left side is also not characteristic of it. On the contrary, for a gastric ulcer localized on the lesser curvature near the entrance to the stomach, pain during the very act of swallowing food, radiating to the left scapula and back, and phenomena of dysphagia depending on the spasm of the musculature of the cardia are extremely characteristic. The closer the ulcer is to the cardiac sphincter, the more intense the pain and dysphagia; whereas an uncomplicated ulcer of the lesser curvature far from the sphincter may proceed without any symptoms. The situation is different in the case of a penetrating, so-called penetrating ulcer with perigastritis. With it, the pains are intense. Both pain points and zones are localized on the left, in the region of the X–XII vertebrae and corresponding segments. Hypersecretion is far from mandatory; the presence of blood is detected upon repeated examinations. Characteristic of a cardiac ulcer is often the easy vulnerability of the mucosa during probing, especially with a thick probe. Upon X-ray examination, a spastic stenosis of the cardia with successive dilatation of the esophagus and an indentation or niche on the lesser curvature may be discovered. When the ulcer is localized in the cardiac part of the stomach, far from the cardia itself, a series of radiographs must be persistently recommended: a single fluoroscopy may not yield indications. Among gastric ulcers, ulcers of the body of the stomach most frequently give no symptoms, especially when they are localized on the anterior or posterior wall or the greater curvature in the absence of complications. In this case, the characteristic pain syndrome may be absent, and the gastric ulcer is accompanied only by the usual dyspeptic symptoms characteristic of gastric catarrh. Objective and X-ray examinations frequently yield a negative result, and only the presence of blood in the gastric contents, resp. in the fecal masses, gives reason to suspect a gastric ulcer. In some cases, with a calloused ulcer located on the posterior or anterior wall, it is possible to palpate an ulcus-tumor, and during fluoroscopy to discover a persistent spasm of the musculature and serration of the contours of the stomach at the site of the ulcer, caused by the spasm of the muscularis mucosae [see separate table (p. 75–76), Fig. 7]. However, when a complication occurs in the form of perigastritis or penetration with previously existing adhesions, ulcer symptoms appear and gradually increase. Early pains appear (3/4–1–11/2–2 hours after eating) with radiation into the spine, into both sides of the chest, severe pains in the back if adhesions or penetration involve the pancreas or solar plexus; at the same time, skin hyperalgesia in the region of the stomach, Boas' and Oppenchowski's points in the region of the IX–XII segments, and Head's zones on both sides are observed. Examination of the gastric contents far from always (in approximately half of the cases) reveals hyperacidity and hyperpepsia, as well as the presence of blood and mucus. X-ray examination frequently reveals a persistent spasm of the stomach musculature in the form of an indrawing of the greater curvature [see sep. table (p. 75–76), Fig. 7] and, conversely, on the lesser curvature—a Haudeck niche [see sep. table (p. 75–76), Fig. 7 and 8] or else a limitation of mobility in some area of the stomach, and sometimes disfigurement of the stomach in the form of an hourglass or cascade stomach [see sep. table (p. 75–76), Fig. 9]. An ulcer located on the posterior wall, even complicated by perigastritis, is easily missed on radiography—here a whole series of radiographs in lateral positions is sometimes required. Complications in gastric ulcer are observed quite frequently in the form of a) hemorrhages, b) perforation of the stomach wall, c) perigastritis, d) various strictures developing as a result of scarring of the ulcer, and e) cancerous degeneration of the ulcer. Frequently, various complications are combined with each other or are observed during the chronic course of a gastric ulcer in sequential order. Many authors, for example Knud Faber, believe that hemorrhages in the form of profuse hemorrhage or an insignificant admixture of blood to the gastric contents, detected only by chemically sensitive reactions to blood, are an obligatory symptom of a gastric ulcer. Not all clinicians agree with this. And while some, like Boas, attach great importance to occult hemorrhages, considering them pathognomonic for ulcer and cancer, others, like Bergmann, think that "occult hemorrhages" can also be observed in other diseases of the stomach. Of decisive importance for the diagnosis of a gastric ulcer are only profuse hemorrhages in the form of bloody vomit (haematemesis) or bloody stool (melaena), which are observed in approximately 19% of all cases. Profuse hemorrhage can be the first and only sign of a gastric ulcer, sometimes threatening life (mortality from hemorrhage ranges from 1% to 3–5% with repeated hemorrhages). The first signs of hemorrhage are not bloody vomit or tarry stool, but indirect signs, such as: paleness of the integuments, dizziness, a sensation of weakness, sometimes loss of consciousness, increased pulse rate, and phenomena of collapse; at the same time, the pains that tormented the patient every day frequently disappear. After some time (1–3 hours), vomiting appears. However, in other cases, vomiting may not follow, and confirmation of gastric hemorrhage is then melaena and a tarry stool several hours (5–12 hours) after the hemorrhage occurred. A more severe complication of gastric ulcer is perforation of the stomach wall, which can occur both in fresh ulcers several hours after their onset and in chronic ulcers as a result of the gradual corrosion of the stomach wall. Perforation can occur both with a small gastric ulcer and with a huge one. About 10% of all gastric ulcers result in perforation. The clinical picture of acute ulcer perforation is characterized by: a) the sensation of severe pain in the upper abdomen, radiating to the back or shoulder; b) a rapid decline in strength, the appearance of cadaveric pallor (facies hippocratica), and cold sweat; c) an increased rate of respiration and pulse. The slightest touch to the upper abdomen causes severe pain. Vomiting frequently appears, temperature drops. The abdominal press is tense, especially in the region of the stomach, and tympanitis appears at the site of the liver. Peritonitis develops. 5% of patients with perforative peritonitis recover, half die on the second day (Schnitzler). However, if at the site of the progressing ulcer there were adhesions of the serous membrane of the stomach with surrounding organs, perforation may not entail acute peritonitis, since adjacent organs (liver, pancreas, omentum, intestines) close the defect. In this case, after perforation, only an exacerbation of the former inflammatory process occurs, accompanied by an increase in pain, a rise in temperature, an increase in the tension of the abdominal press, and other clinical phenomena of local peritonitis—perigastritis. The developing plastic fibrinous infiltrate, sometimes accompanied by pain and a rise in temperature, also involves neighboring organs into adhesions, e.g., the pancreas, and promotes the formation of an inflammatory tumor detectable by palpation. Upon the formation of such infiltrates and adhesions with neighboring organs (liver, pancreas, etc.), the ulcerous destruction spreads to these infiltrates and organs ("penetration" of the gastric ulcer). In other cases, perigastritis takes on a purulent or putrid character in the form of a free abscess in the abdominal cavity or located beneath the diaphragm on the right or left, often containing not only pus, but also food substances that have escaped from the stomach during perforation, and foul gases that have developed due to putrid infection. In some cases, an abscess formed among adhesions carves a path for itself into the stomach, after which, alongside the stomach, a separate cavity is formed among the adhesions that communicates with the stomach and produces the "niche symptom" on X-ray examination. Perigastritis formed due to the fibrous degeneration of exudate often contributes, together with a scarring ulcer, to the narrowing of the stomach at the site of the ulcer and the formation of an hourglass stomach or a cascade stomach [see separate table (p. 75-76), fig. 9], which impedes the function of the stomach when sufficiently developed. In this regard, narrowing of the pylorus or cardia causes particularly serious consequences. Narrowing of the pyloric part is accompanied by clinical symptoms of dilatation of the stomach, such as an increase in its volume, stasis of contents, visible peristalsis after eating, and a characteristic X-ray symptom complex (see above—disorders of the motor function of the stomach); narrowing of the esophagus is accompanied by dysphagic phenomena and symptoms of esophageal dilatation (for details, see Esophagus). — Complication of an ulcer by cancer, which develops at the site of a former scar or due to cancerous degeneration of the edges of the ulcer in ulcus callosum, is not so frequent (see above—tumors of the stomach). With this complication of a gastric ulcer, free hydrochloric acid, despite the presence of gastric cancer, is often observed in an increased percentage and often remains until the very end. The course of a simple ulcer is extremely variable. In general, every formed ulcer has a tendency to a chronic course and relapses. Some acute ulcers soon heal. The possibility of permanent healing of even a chronic ulcer cannot be denied. In both cases, all observed symptoms of the ulcer may completely disappear not only in a simple ulcer, but also in a chronic one complicated by a niche or callously degenerated (Bergmann). — Regarding prognosis, gastric ulcers can be divided into two groups: simple, uncomplicated ulcers, which heal well with appropriate regimen and treatment, and calloused ulcers, which scar with difficulty and easily produce the complications described above. Mortality from gastric ulcer, according to the summary statistics of Hauser, based on the materials of German internal medicine clinics, averages 10.6% (without subdivision into the two groups just mentioned). The diagnosis of a gastric ulcer in some cases, in the presence of cardinal symptoms (pain syndrome, hypersecretion, hyperaciditas, bleeding, characteristic X-ray picture) is very easy; in others, proceeding atypically, it is quite difficult. It is necessary to conduct differential diagnosis between other diseases of the stomach, such as achylia, catarrh, cancer, syphilis, and functional neuroses, as well as between diseases of the liver, pancreas, appendicitis, and crises in tabes dorsalis. A carefully collected and subjected to comprehensive clinical analysis anamnesis, skilled objective examination of the abdominal cavity, study of the secretory function of the stomach, analysis of its contents and fecal masses, as well as X-ray examination and simple observation of the patient, providing the physician with a complex of clinical symptoms characteristic of one or another of the listed diseases, currently allow in the vast majority of cases to make the diagnosis of a gastric ulcer completely unerringly. The greatest difficulties are encountered in differentiating a gastric ulcer from neuroses of the stomach and gallstone disease or cholecystitis, especially since these diseases are frequently combined with a gastric ulcer. A careful objective examination of the patient, the persistence of symptoms, the insignificant dependence of complaints on the mental state of the patient, the dependence of pain on the quality and quantity of food, and above all—the periodic presence of blood in the gastric contents and fecal masses, and the X-ray signs characteristic of a gastric ulcer, finally make it possible to distinguish a gastric ulcer from its functional disorders or to recognize their combination. Affections of the liver and gall bladder are differentiated by characteristic pain, tenderness of the liver on percussion and palpation, increased bilirubin content in the serum, an increase in urobilin in the urine, a slight leukocytosis with a shift to the left according to Arneth-Schilling, the time of onset of pain (in diseases of the gall bladder and liver, in most cases, pain appears immediately after meals), as well as on the basis of X-ray examination (cholecystography). It is extremely difficult or even impossible to establish the primary source of the disease in cases where there are phenomena of pericholecystitis and peripyloritis and no cardinal symptoms of the ulcer, such as bleeding, etc., especially since cholecystitis is frequently joined to an ulcer of the pyloric part of the stomach complicated by perigastritis and periduodenitis. (On differential diagnosis from gastric cancer, see above—new growths of the stomach). When recognizing a gastric ulcer, one should not be limited to ascertaining the presence of an ulcer, but it is also necessary to determine as accurately as possible both the localization of the ulcer and its character: simple ulcer, calloused, penetrating, etc. The characteristic features for each localization of the ulcer in the stomach and the peculiarities of the manifestations and course of a simple, calloused ulcer, etc., were indicated above. An ulcer of the pyloric part of the stomach produces a picture of the disease very similar to the picture of a duodenal ulcer, located most often in its very initial part. (On the differential diagnosis between an ulcer of the pyloric part of the stomach and the duodenum, see Duodenum, ulcer). Prophylaxis of a gastric ulcer consists in improving the social living conditions of the population, regulating nutrition issues, rationing the time of food intake, and limiting alcohol consumption, since abuse of it entails the development of catarrhs of the stomach and contributes to the development of neuroses of the autonomic nervous system, which play a large role in the pathogenesis of a gastric ulcer. A normal, calm, hygienic life, with attention paid to physical culture and correct dietary nutrition, is of tremendous importance not only for the state as a whole, but also for each individual, especially for people with an unstable nervous system and for persons in whose family stomach diseases, especially peptic ulcer, have already been observed. Correct and timely treatment of inflammatory processes, in particular appendicitis and cholecystitis, therapeutic or surgical, is also of no small importance regarding the prophylaxis of a gastric ulcer. The same rules of life must be observed by a patient cured of an ulcer in order to prevent relapses, since a patient who has suffered an ulcer differs in constitutional terms, as well as in the function of his autonomic system, from a normal person and is predisposed to a relapse of the ulcer. A patient cured of an ulcer must be under the observation of an experienced physician all his life and periodically undergo examination both regarding the function of his stomach and the presence of blood in the fecal masses in order to notice the onset of a relapse in time; to prevent relapses, he must constantly eat predominantly milk-and-vegetable food and completely exclude alcoholic beverages, meat and fish broths, spicy and salted dishes, and generally all those nutrients that are energetic secretagogues from his diet. Treatment of gastric ulcer consists in the application of a special diet, medicines, and physiotherapy, as well as in operative assistance (see below). Every patient with a gastric ulcer must be subject to therapeutic treatment, especially in fresh cases. Only in cases of severe and persistent pain, large and moreover repeated bleedings, signs of an impending or fresh, just occurred perforation (the first 6-8 hours), purulent perigastritis, narrowing of the entrance or exit opening of the stomach, as well as sharp narrowing in the region of the body of the stomach (hourglass stomach, cascade stomach) and an old calloused ulcer with suspicion of cancerous degeneration—the patient is operated on. In this regard, one should be guided by the general rule that the failure of therapeutic treatment of an ulcer, strictly carried out for 6-8 weeks, generally requires operative assistance. The task of internal treatment is to achieve the healing of the gastric ulcer in the shortest possible time by prescribing an appropriate regimen, diet, and medications and then to prevent its relapses. Treatment must be strictly individual depending on the localization of the ulcer, the complications observed with it, the state of the nervous system and the causative moments that caused the gastric ulcer, as well as the observed symptoms, i.e., it must be individually-causally-symptomatic. When prescribing a regimen, diet, and medications, two goals must be pursued: to create complete rest for the patient and his stomach, reducing spasms, enhanced peristalsis and secretion of the stomach, and to facilitate evacuation. As a rule, a patient with a gastric ulcer, at least during the first two weeks of treatment, is prescribed bed rest, which must be carried out especially strictly and for a long time in complicated gastric ulcer. When prescribing a diet, one must take care that the nutrition is sufficient; only in the first days of treatment is a reduced diet permissible; at the same time, nutrition should be built on the physiological principles of Pavlov's school. Several courses of dietary treatment have been proposed, approximately meeting the requirements of physiology and the indicated principles (Leube, Lenhartz, Senator, Bouveret, Sippy, Yarotsky, and others). (For details, see Duodenal ulcer.) Milk food has long enjoyed a good reputation, but in its pure form it is not particularly suitable for the treatment of pyloric ulcer occurring with spasms and gastrosuccorrhoea, and especially with concomitant colitis; instead of milk in such cases, cream and butter should be used for nutrition, which as fats reduce secretion and have high caloric value and are therefore generally suitable food for an ulcer patient. Liquid, raw, or half-raw eggs (6-8 pieces per day) are also well tolerated for these reasons. Carbohydrate food in the form of all kinds of mucous porridges from groats, boiled in water with butter or in milk or cream, finely puréed vegetables with butter, as well as delicate rusks are the best nutrition. Meat products are not permitted during the first 4-6 weeks of treatment; later, due to their taste properties, they are allowed in limited quantities and only in minced and puréed form. Meat soups, vegetable soups, fish soup, coffee, strong tea, and alcoholic beverages, due to their juice-stimulating action, must be completely prohibited. Food should be low in salt and not seasoned with acidic fruit juices. The regimen, depending on the severity of the case, the degree of bleeding of the ulcer, the strength of the pains, the stoutness of the patient, and the freshness of the case, should be divided into three types. A. Strict regimen (immediately after bleeding, with a tendency of the stomach ulcer to perforation and with fresh ulcers) consists of a 3-4-day abstinence from all food and drink with the introduction of glucose into a vein or in the form of drip enemas, in the gradual increase of the most suitable of the above-mentioned products, namely, cream, milk, butter, liquid eggs, and so on, with the calculation that by the beginning of the 3rd week one reaches milk porridges and rusks soaked in milk and a caloric value of up to 2,000-2,400 calories. B. Less strict regimen (for patients with fewer complaints and insignificant bleeding) begins with the prescription of cream, butter, milk, eggs, milk and mucous porridges, vegetable purées, with a caloric value of up to 1,500 calories at the beginning and with a gradual increase by the end of the 3rd week to 3,000 calories. C. Mild regimen (for patients who have not had bleeding in the last 5-6 weeks and have no great suffering) consists only in abstaining from coarse, salty food, raw fruits, marmalades, acidic fruit juices, meat broths, fish soup, all kinds of spices, delicacies, alcohol, and smoking, with the greatest possible restriction of meat and fish dishes. In essence, such a diet should be observed by every ulcer patient almost for the whole life in order to avoid relapses. The ulcer patient should take food not in a hot form and in small portions with a regular 2-hour interval. Medicinal treatment consists in the systematic prescription of alkalis and agents that reduce secretion and eliminate spasms and pain. The prescription of alkalis has the purpose of lowering the acidity of the gastric contents, eliminating hypersecretion and the phenomena of acidism, as well as restoring the acid-base balance in the body and tissues, since in the case of acidosis the conditions for healing a stomach ulcer are unfavorable, especially since acidosis is accompanied by hypertonus of the parasympathetic nervous system (Zimnitsky). Alkalis are given either simply in the form of purified soda (1.5-2.0 per dose up to 10.0 per day) in the morning on an empty stomach and 11/2-2 hours after eating or in the form of alkaline mineral waters (Borjomi, Vichy). Excessive introduction of alkalis in the Sippy course (32.0 sodium bicarbonate + 7.5 magnesium oxide + 8.0 calcium carbonate) is superfluous and can cause alkalosis. It is useful to prescribe a 0.2-0.4% solution of sodium hydroxide in 1/1 glass of water half an hour before meals (Glaessner). The prescription of bismuth preparations (in the morning on an empty stomach Bismuth carbonate 4.0-10.0 according to Fleiner), with the purpose of reducing gastric secretion, as well as covering the ulcer surface with a layer of bismuth protecting it from irritation by food, must be recognized as useful. The prescription of belladonna preparations to lower the hypertonus of the vagus nerve and peristalsis, eliminating spasm and hypersecretion, is quite rational. Extract of belladonna is prescribed at 0.015-0.02 three to four times a day after meals, with alkalis. A course of treatment with atropine for a month is more rational (0.001 atropine sulfate one-two-three times a day under the skin). The dose depends on the degree of hypertonus of the vagus nerve. For the treatment of stomach ulcer, silver nitrate is also used (0.1-0.2% solution three times a day by tablespoon in 3/4 glass of water 15 minutes before meals), especially in cases of stomach ulcer complicated by catarrh. Little attention is deserved by the treatment of stomach ulcer by means of parenteral introduction of protein (vaccinevrin, novoprotin, Yatren-Casein, etc.), i.e., according to the principle of protein therapy. Even less significance must be attached to the treatment of the ulcer by deep roentgenization. The prescription of the listed agents also satisfies the principle of symptomatic treatment, since alkalis eliminate the phenomena of acidism and indirectly pain. Atropine does the same. However, in some cases, to eliminate spasms and pain, it is necessary to prescribe papaverine (Papaverine hydrochloride 0.02-0.04, two to three times a day) and pantopon (0.015) subcutaneously. Physiotherapy in the form of simple poultices or a thermophore (cave bleeding!) on the stomach region deserves attention; applied systematically (2 times a day for 1 hour before and after meals), it contributes to the elimination of spasm and reduction of pain, and perhaps to faster healing (Leube). Treatment of stomach ulcer with diathermy is accompanied by a lesser effect. Among the physical methods undoubtedly bringing benefit to ulcer patients, general balneo-hydro-electrotherapy should be included, especially in resort areas where patients use alkaline and alkaline-Glauber waters, observe a dietary regimen, and rest (Zheleznovodsk, Carlsbad, Vichy, etc.). This contributes to the healing of the ulcer not only directly—thanks to treatment with a certain diet and alkalis, but also indirectly—thanks to the impact of the mentioned physical factors and rest on the nervous system. In general, it must be recognized as useful for every patient who has suffered from an ulcer to periodically undergo not only a stricter dietary regimen, but also to conduct a course of treatment with physical methods. The treatment of some complications of stomach ulcer has a special character and deserves consideration. With heavy bleeding that has occurred for the first time, surgery is contraindicated. If severe bleedings repeat and threaten life in themselves, surgery may be necessary, but it should be performed only after preliminary blood transfusion. As a rule, after heavy bleedings, strict bed rest is maintained; an ice bag on the stomach, intravenous introduction of 10% NaCl or calcium chloride or a 20-40% glucose solution in the amount of 10 cm3, 40-100 cm3 of Merck gelatin subcutaneously, ergot preparations intramuscularly, 10-20 cm3 of a 10% calcium chloride solution in an enema—with complete abstinence from food and drink in the first 3-4 days stop the bleeding. For large blood losses, drip enemas of 10-15% glucose with the addition of 1-5 cm3 of a 1‰ adrenaline solution are recommended, and with threatening bleeding, immediate infusion into the blood of 300-400 cm3 of a 10% glucose solution or even blood transfusion. When the pulse drops—cardiacs subcutaneously (camphor, Digalen, etc.). A strict course of ulcer treatment must be immediately applied (see above). Treatment for perforation is approximately the same, but with the exclusion of hemostatic agents and with greater attention to maintaining heart activity through the prescription of various cardiacs subcutaneously and intravenously (Digalen, Digipurat, Strophanthin, camphor, caffeine, cardiazol, hexeton, etc.) and morphine. At the first signs of perforation or within the first 6-8 hours after it, surgical intervention is mandatory.
N. Strazhesko. Surgical treatment of stomach ulcers. Indications for surgical treatment in stomach ulcers, as well as in duodenal ulcers, are either 1) complications, such as hemorrhages, perforation, pyloric stenosis, deformations of the stomach itself, cancerous degeneration of the ulcer, or 2) a non-healing ulcer in itself. In the first case, the indications are much more definite and for the most part do not cause hesitation; cases of this group are discussed separately below. There is much more uncertainty regarding the second group. Here there are major disagreements both on the question of indications and on the methods of operation. At the present time, after the experience gained by surgery over the past decade and a half, it has become completely clear that in uncomplicated ulcers, treatment must in all cases begin and be carried out by therapeutic measures, that surgical and therapeutic methods cannot be regarded as parallel or competing with one another, and only after a long-term therapeutic treatment conducted lege artis does not yield the desired result does the question of surgical intervention come to the fore. Furthermore, even after surgery, even a radical one, the prolonged regimen usual for ulcer patients is just as necessary. Indications for surgical intervention are pain, vomiting, inadequate nutrition, emaciation, progressive general weakness, and anemia due to recurrent blood loss. In many cases, indications depend on living and individual conditions: the type of occupation, dietary conditions, degree of security, etc. Regarding the methods of surgical treatment, not only have strictly defined views and indications not been developed, but on many points opinions are diametrically opposed. All operative methods can be divided into two groups: "radical" and "palliative". The former include all methods aimed at removing the ulcer, exclusion by sutures (Sattler), cauterization, excision of the ulcer itself, wedge-shaped or longitudinal resection of the lesser curvature (Kaiser), circular resections of the stomach: pylorectomy, gastropylorectomy, median circular resection of the stomach (Riedel), saddle-shaped resection (Schmieden). Palliative operations include gastroenterostomy, pyloroplasty, cholecystogastrostomy (Bogoraz). Sattler's operation—exclusion of the ulcer by surrounding it with full-thickness sutures through both walls of the stomach—has not received sufficient clinical verification. The simplest "radical" operation—cauterization of the ulcer from the outside (according to Balfour) with sequential suturing and gastroenterostomy—has not found wide application and, in essence, can take place only for small and non-callous ulcers. Partial wedge-shaped or segmental excision of the ulcer or Kaiser's longitudinal resection also have a limited scope, but in suitable cases—with small-sized ulcers located on the lesser curvature, without significant cicatricial degeneration of the stomach walls—these operations deserve full attention; sometimes they can be supplemented by the creation of a gastroenteroanastomosis. The main objection raised against them is that after excision of the ulcer, a huge defect may result in the walls of the stomach, upon the closure of which the stomach is deformed, which can affect its motor function; but this is true only for cases of large callous ulcers, which should not be operated on by this method. Leaving aside these methods as relatively rarely used, in all other cases the "radical" operation for an ulcer consists of a partial circular resection of the stomach. The extent of resection depends on the size of the ulcer itself, the extent of cicatricial degeneration of the surrounding stomach walls, adhesions, and penetration into neighboring organs. In the vast majority of cases, the excision involves the pyloric part of the stomach and a greater or lesser portion of the body of the stomach. For ulcers located in the middle of the lesser curvature, Riedel proposed the method of median circular resection of the body of the stomach while preserving the pyloric part; in this case, the resection becomes a more economical operation. Some surgeons make the extent of resection dependent not only or, rather, not so much on the size of the ulcer as on general pathological considerations. Lorenz considers it necessary to always excise the entire antro-pyloric part of the stomach, proceeding from the premise that in order to avoid recurrence, it is necessary to remove the source of the physiological reflex from the pyloric part to the fundic section of the stomach. Finsterer goes even further and "preventively" removes a significant part (up to 3/4) of the body of the stomach in order to reduce the secreting surface of the mucosa. The proposals of Lorenz and Finsterer, naturally, do not find followers due to their complexity and groundlessness. Much more rational is Schmieden's proposal, proceeding from the same preventive goals: along with the circular excision of the section occupied by the ulcer, to also excise the entire lesser curvature, the "gastric pathway" as the place most predisposed to the development of stomach ulcers. Practically, the benefit of this method, however, has not been proven; the theoretical premises are also hardly correct. Thus, the prevailing method of operations remains the circular resection of the section of the stomach occupied by the ulcer. Resection is usually performed according to Billroth's method; other modifications (Balfour, Polia) find few followers. Of the two Billroth methods, Haberer particularly advocates the first one as more physiological and providing a better guarantee against the development of secondary peptic ulcers (see Billroth's operations on the stomach), but the majority use Billroth's second method. The attitude of modern surgery to the question of indications for resection and other operations for ulcers remains uncertain. Among the proponents of resections, there is a large number of prominent German surgeons (Haberer, Enderlen, Eiselsberg, Finsterer), a number of American (Mayo) and French surgeons (Pauchet, Duval), but the majority treat resections with restraint, applying them only in special indications; some surgeons are almost negative towards them, and some (Bier) after extensive experience with resections have returned to gastroenterostomy. The fact is that resection, in essence, is not a radical operation and does not exclude the possibility of recurrence, the frequency of which is determined to be up to 10%. Although the percentage of cure after resections is higher than after palliative operations, and the functional results are better, the technical difficulty of the operation itself and the higher postoperative mortality outweigh the scales in favor of simpler operations, such as gastroenterostomy or pyloroplasty. Immediate mortality after resections for ulcer varies in the hands of various surgeons, reaching up to 12% and averaging 6%, whereas after gastroenterostomy the mortality, averaging 3%, in the hands of individual surgeons over large series of cases drops to 0. However, under certain conditions, resection has undeniable advantages over gastroenterostomy. The latter gives an excellent result in ulcers accompanied by pyloric stenosis or a sharp violation of motor function, whereas in ulcers remote from the pylorus, a good result is obtained in only 50%. On the other hand, if resection is faulted for the fact that recurrences are observed after it, then after gastroenterostomies an even greater percentage of cases fail to heal the primary ulcer, especially the callous one. Furthermore, gastroenterostomy does not guarantee against either perforations or hemorrhages from the ulcer; finally, as an argument in favor of resections, the fact is put forward that an ulcer often serves as a soil for the development of cancer, and therefore resection in this regard is a preventive operation. However, the frequency of cancerous degeneration is estimated very differently: Hauser defined it at 5–6%, modern pathomorphologists, according to sectional material, from 2–5% (Aschoff, Konjetzny) to 8% (Lubarsch). According to the study of preparations obtained during operations, cancerous degeneration was found in a significantly higher percentage of cases: 25% (Ewald, Payr, Riedel), 43% (Küttner), and even 70% (Mayo, Kelling). Konjetzny explains such a discrepancy between sectional and clinical material by the fact that in cases of the first kind, the cancerous process manages to go so far that establishing a connection with the ulcer appears no longer possible. Which figures correspond to reality remains controversial; however, too high figures are unlikely. In any case, ulcers arousing suspicion of cancerous degeneration should be resected. Such are often old callous ulcers, which even during surgery are sometimes difficult to distinguish from cancer, and since they themselves are not very prone to healing after gastroenterostomies and often give other complications, it is preferable to excise such ulcers. Ulcers giving recurrent hemorrhages are preferably removed, as well as ulcers threatening perforation. (Regarding the results of gastroenterostomies for stomach ulcers, indications, and subsequent functional changes, see Gastroenterostomy and Duodenal ulcer.)—If one looks at pyloric spasm as a moment predisposing to the occurrence of an ulcer, it would be consistent to apply pyloroplasty according to Heineke-Mikulicz or extramucous as a method of treatment. Braïtsev gives preference to pyloroplasty over gastroenterostomy for ulcers remote from the pylorus and in cases where ulcers are not detected during surgery.
Other surgeons (Fedorov, Grekov, Petrov) use this same method with good results. Surgical diseases and surgical treatment of stomach diseases. Injuries and wounds of the stomach. Due to the protected position of the stomach, its subcutaneous injuries, especially isolated ones, are observed relatively rarely; more often they are combined with injuries to other organs. Usually, such injuries are observed as a result of direct trauma inflicted on the epigastric region by a hoof or a vehicle pole, by a blow against some object, or from compression by buffers, during which the walls of the stomach are crushed against the vertebral bodies. Rupture is favored by overfilling of the stomach or pathological changes in its walls; in these latter cases, the violence can be so negligible that one can speak almost of a spontaneous rupture. Damaged areas are located most often near the lesser curvature, but may also be found in other parts of the stomach. According to the degree of damage, one can distinguish contusions, incomplete, and complete ruptures. With more or less severe contusions, hemorrhages occur, predominantly in the submucosal layer, sometimes reaching enormous proportions; in such cases, the matter ends in necrosis of the mucous membrane; in other cases, the entire thickness of the walls is imbibed with blood over a large extent, which can also lead to necrosis and perforation. With incomplete ruptures, there is a violation of integrity of either only the mucous membrane or also the muscular layer; partial ruptures easily lead to secondary perforations. Complete ruptures of the gastric wall have the appearance either of a slit or an opening with irregular outlines. If these openings are relatively small, they are lip-like protruding (the mucous membrane protrudes). With a small opening, the prolapsed mucous membrane plugs the opening like a cork, and if protective adhesions manage to form, the case may end in recovery. With large ruptures, as with other types of stomach wounds, general peritonitis usually develops, but even then the process can localize in the form of a subdiaphragmatic abscess or an isolated collection of pus in the omental bursa if the posterior wall was damaged. In cases of open perforation into the free abdominal cavity, the gastric contents are poured into the latter. For the clinical manifestation and for the entire further development of the picture, the state of the stomach at the moment of trauma (empty, overfilled) is of enormous importance. The first constant symptom of a more or less severe stomach injury is shock, sometimes with loss of consciousness, sharp pallor, cold sweat, shallow respiration, frequent, barely perceptible pulse. All these phenomena represent a reflex from the sympathetic system and can equally occur both as a result of a contusion and due to the effusion of gastric contents into the abdominal cavity; therefore, the severity of the injury cannot be judged by the degree of initial phenomena of general shock. But already after a short time—1-2 hours—the severity of the injury may be revealed: if there is no complete rupture, the phenomena of shock pass, and the patient completely recovers; on the contrary, in the case of severe injury, the phenomena of shock drag on or even worsen, or other phenomena directly join, already depending on peritonitis. The primary pain felt by the patient can reach extreme intensity, but then it decreases and with the development of peritonitis takes on a different character: pressure on the epigastric region becomes painful, whereas in the absence of peritonitis, pressure is often completely painless. Vomiting is not a constant symptom, although it is rarely absent; a direct indication of stomach injury is only vomiting mixed with blood. The abdominal walls are tense as a board, and this tension remains if peritonitis develops, but the abdomen begins to swell at the same time. The most valuable and early sign of complete stomach rupture is the presence of air in the abdominal cavity (pneumoperitoneum). Clinically, this is characterized by the disappearance of hepatic dullness, but is even more clearly detected by fluoroscopy. The further course of the injury depends on very many conditions. With partial damage, complete recovery can quickly occur, however, one should keep in mind the possibility, even in mild cases, of sequentially manifesting symptoms of perigastritis. In cases of complete rupture, symptoms of peritonitis develop, local or diffuse, sometimes ending in the formation of a local abscess. In cases of general peritonitis, the phenomena usually develop immediately after the trauma, but one should never forget that perforation can also occur as a secondary one, after an initially incomplete rupture of the stomach walls or after rupture of delimiting adhesions, and therefore a free interval from several days to two weeks can be observed between the trauma and the ensuing deterioration. Diagnosis of subcutaneous stomach injuries presents a difficult task in the first hours, and meanwhile in cases of complete rupture all hope for salvation lies in early surgery. The initial phenomena of shock, despite their severity, as already mentioned, are not decisive, since they can also be observed with a simple contusion of the abdominal walls. Characteristic are two symptoms: vomiting mixed with blood and the presence of air in the abdominal cavity, but both these symptoms are often absent or cannot be detected. In addition, the presence of injuries to other organs and abdominal blood vessels cannot be excluded. Practically, it can be taken as a rule that if the patient's condition does not improve a few hours after the injury, then one should assume the presence of stomach perforation or some other severe injury to abdominal organs, and surgery becomes necessary without further delay. (On operation methods, see below.) Stab and incised wounds of the stomach are most often inflicted from the front—through the anterior abdominal wall, or from the side—from the chest side, with the pleura and diaphragm being wounded at the same time. The size of the stomach wound corresponds to the wounding instrument; with small sizes, its edges have no tendency to diverge or the opening is plugged, like a cork, by the prolapsed mucous membrane, which favors spontaneous healing. However, usually the wound entails the development of peritonitis, especially if the stomach was overfilled with food. In addition, stomach wounds can cause by themselves, not to mention the concomitant injuries of other organs and mesenteric blood vessels, significant bleeding into the stomach cavity or into the free abdominal cavity, especially from wounds inflicted in the area of the greater or lesser curvature. Unlike subcutaneous injuries, stab and incised wounds are usually not accompanied by phenomena of shock, and pains are usually insignificant. Diagnosis of a stomach wound becomes obvious only in the case when the stomach wall falls out of the wound or there is an outflow of gastric contents, which in general is observed relatively rarely; much more often one can only make assumptions about a stomach wound based on the position of the wound and its direction. Gunshot wounds. Isolated stomach wounds are encountered relatively rarely, much more often they are complicated by wounds of other organs, which increases their seriousness. The size of the wound opening in the stomach walls is usually somewhat larger, and sometimes significantly larger than the caliber of the projectile, especially with non-jacketed bullets. The shape of the wound opening is either circular or irregular, with torn edges—contused, if the direction of the wound channel is tangential. In wounds inflicted by modern small-caliber bullets, cases are observed when very small bullet openings can close spontaneously or the matter is limited to the formation of a local abscess. One can assume the presence of a stomach wound by the direction of the wound channel, if the wound is through-and-through; it is more difficult to navigate if there is no exit wound and the direction of the wound remains unknown. To resolve the issue, careful observation of the patient in the first hours of the wound is necessary, at least within the period allowed by surgery for perforated wounds. Treatment of all kinds of complete stomach injuries must be operative. Expectancy is permissible in cases that have already survived one or two days, in the absence of indications of peritonitis, but expectancy must also be "armed" here. In early cases, expectancy harbors more dangers than a surgery performed perhaps in vain sometimes. The state of general shock is not a contraindication to surgical intervention, especially since under anesthesia the phenomena of shock weaken; besides, circumstances more often turn out so that the wounded arrive after a certain period of time has elapsed since the wound, and the severe general condition is an expression not of primary shock, but of other complications that have set in—bleeding or incipient peritonitis. The prognosis of surgical intervention worsens with each hour of delay. Surgical intervention for stab and incised wounds is better started by expanding the already existing wound, since such wounds do not always turn out to be penetrating. If the wound is not located on the anterior abdominal wall or generally lies inconveniently for examining the stomach, the incision is made along the midline. When opening the abdominal cavity, it is necessary to examine not only the stomach, but also neighboring organs.
In gunshot wounds, it is also necessary to examine the posterior wall of the stomach, for which it is best to go through the gastrocolic ligament. In cases of a deep position of the gastric wound and the impossibility of gaining access to it, as a last resort, the omentum can be brought up to the wound and fixed with sutures. In fresh cases, the abdomen may be closed tightly. In cases of late operations, already complicated by contamination of the entire peritoneum and peritonitis, additional incisions are used in the lower floor of the abdominal cavity for drainage. The outcomes of surgical treatment of various forms of stomach injury depend primarily on the timing of the intervention; stab wounds give the best prognosis, since the operation is undertaken early and recovery after early interventions is almost a rule, provided it is an isolated stomach injury. In gunshot wounds, the outcomes of surgical intervention must be considered separately for peacetime cases and for wartime field conditions; according to the data of the last war, Quenu gives a mortality rate after surgery of 44%. In subcutaneous injuries, timely intervention most often turns out to be delayed due to uncertainty in diagnosis. Petri determined the mortality figure in these cases to be 50%, Zeidler 70%. The latest statistics show significantly better outcomes. Stomach injuries must include burns of the stomach both with inorganic compounds of the acid and alkaline series (sulfuric, hydrochloric, nitric acids, caustic alkalis, sublimate) and organic ones (most often carbolic acid). These substances, entering the stomach, usually cauterize two points—the oral part of the lesser curvature and the pylorus; these points are determined by the peculiarities of the anatomical structure of the stomach and its physiological contractions upon irritation. The clinical picture, usually severe with all kinds of complications in the form of perforation and peritonitis, is especially severe in cases of severe burns; in cases of mild burns, the matter may end in recovery, with various stomach deformations—scar stricture of the pylorus, hourglass stomach, changes in the cardiac part. Surgical intervention for this type of injury falls into two categories: 1. Emergency operations for perforations and peritonitis. In this case, it is very often necessary to abandon suturing the stomach walls at the site of perforation due to the extent of damage to neighboring areas; in such cases, one has to be satisfied only with tamponade. Sometimes it is necessary to apply a small intestine fistula in order to give rest to the affected stomach. 2. Late period operations: a) gastrostomy for retrograde bougienage in case of stenosis of the cardiac part, b) gastroenterostomy in case of an hourglass stomach or in case of stenosis of the pyloric part. Sometimes in cases of the first injury, resection of the stomach is required. Foreign bodies of the stomach—see Foreign bodies. Volvulus of the stomach (volvulus) is rarely observed; the stomach in this case rotates around its longitudinal axis from left to right by 180°, so that its posterior surface turns out to face forward; following the stomach in such cases, there is also a displacement of the transverse colon with its mesentery and sometimes the spleen. The fixed points remain the lower end of the esophagus and the duodenum; thus, the stomach turns out to be impassable from both ends. In other cases, the volvulus does not reach the degree of completeness, or only twisting of the outflow part of the stomach along the length of the organ itself is observed, as was sometimes observed in bilocular stomach, gastroptosis, and stomach neoplasms. In such cases of partial volvulus, the twisting sometimes occurs from right to left, reaching 360°. More than 40 cases of stomach volvulus have been described (Niosi). Among the contributing pathological moments are noted: 1) overfilling of the stomach with food masses, especially in cases of its dilation, with weakness of the ligaments, 2) trauma, 3) tumors of the pylorus. The disease usually proceeds with severe and rapidly developing symptoms of obstruction: pain in the abdomen, mainly on the upper left, vomiting or rather fruitless attempts to vomit, since the exit from the stomach into the esophagus is closed; reflex intestinal paresis. Following this, a tumor-like swelling appears in the left hypochondrium due to the distension of the stomach with gases and increased transudation of fluid into its cavity, sometimes of a hemorrhagic character. Distension of the stomach can reach enormous proportions. A general severe condition with a decline in heart activity, which is then joined by peritoneal phenomena and an inevitable fatal outcome. In some cases, however, with partial volvulus, the picture develops not so rapidly and less definitely; in some cases, stomach volvulus turned out to be even an accidental finding. Diagnostic signs can be bloating in the epigastric region and left hypochondrium, the absence of vomit masses with a persistent tendency to vomit, and the inability to introduce a probe into the stomach due to a bend at the cardia. Treatment of such cases is only surgical. The method of operation is determined by the peculiarities of the case and local conditions that caused the volvulus (up to extensive resection inclusively). The stomach is translated into its normal position and then fixed with sutures to the abdominal walls or gastroenterostomy is added. In cases of the presence of an "hourglass"—plastic operations on the pylorus or on the stomach itself; in the presence of a tumor, adhesions, appropriate causal surgical intervention is used. The result of operations is not always complete. Kocher in one case had to operate on the patient 3 times. Therefore, it is sometimes more profitable to immediately decide on an extensive resection. Out of 23 cases that underwent surgery, there were 15 complete volvuli with 10 recoveries, 8 partial ones with 7 recoveries. Acute dilatation of the stomach. The most frequent causes of this disease, which is very close in clinical picture to stomach volvulus, are considered to be paralysis of the stomach or arteriomesenteric bend of the duodenum. Regarding pathogenesis, there is no consensus of opinion as to whether paralysis is the first moment and the closure of the duodenal lumen is secondary or vice versa; there are facts of both orders: it is known that the small intestines lowered into the small pelvis and fixed there are capable of causing intestinal obstruction of the duodenum and leading to dilatation of the stomach; on the other hand, the distended and lowered to the small pelvis stomach with rapid filling can in turn cause the closure of the duodenal lumen. This disease is observed with stretching of the stomach by food with abundant alcohol consumption, after operational trauma (plastic operations on the stomach itself, operations on the biliary tract, on other organs of the abdominal cavity, as well as extraperitoneal operations). Postoperative acute dilatations of the stomach were sometimes attributed to chloroform anesthesia, less often to ether. Further, acute dilatation of the stomach in some cases was observed with spinal cord trauma. Usually in this disease, if there are no purely local contraindications, probing, washing, and certain body positions are first used, but in the majority of cases surgical intervention is necessary—removal of the intestine from the small pelvis and the creation of a gastrointestinal anastomosis. Pylorospasm. Along with acute dilatation of the stomach, cases of stomach dilatation on the basis of pylorospasm in early childhood are observed, as well as in some cases of stomach atony without pathological changes in the pyloric part of the stomach in adults with gastroptosis and with a violation of anatomical relations in the region of the pylorus and the body of the stomach. Pylorospasm in young children occurs in the presence of congenital hypertrophy of the pyloric musculature. This disease is often a reason for surgical intervention and even emergency intervention in view of the catastrophic decline in nutrition caused by it. Three methods of surgical intervention have been used: a) typical pyloroplasty according to Mikulicz, b) gastrointestinal anastomosis, c) extramucosal pyloroplasty according to Weber-Ramstedt or Payr. Dilatation of the stomach is sometimes observed with descents of the stomach, which are most often an expression of general descent of the organs of the abdominal cavity (splanchnoptosis). Severe clinical phenomena, sometimes confused, not always diagnosed in a timely manner, lead to prolonged suffering, up to severe cachexia inclusive. Exhausted by the inefficiency of therapeutic and passive treatment with bandages, patients pass into the hands of surgeons. Surgical treatment consists in reducing the volume of the stomach when descent and dilatation of the stomach are present simultaneously—gastroplication. A number of operations have been proposed to strengthen the position of the stomach in its normal place: sutures on the anterior wall of the stomach over a greater (Rovsing) or lesser extent with its fixation to the anterior abdominal wall (see volume VI, art. 319, fig. 2), suturing of the gastrohepatic ligament lig. hepato-gastricum, fixation of the liver according to Bier, fixation by means of the round ligament according to Perthes (the ligament is separated at its end, stretched or sewn along the lesser curvature and strengthened with sutures at the left hypochondrium). Sometimes gastrointestinal anastomoses are performed, sharply condemned by Rovsing, and finally partial resection of the sac-like stretched body of the stomach according to Orth. Pyloric stenosis. Pyloric stenosis can be of spastic, organic, or mixed origin. The cause of organic stenosis is various processes occurring in the walls of the pylorus or outside the stomach.
Besides neoplasms and ulcers (see below) and aside from the aforementioned deformations after burns, a number of other causes of stenosis lying outside the stomach should be noted. Of these, the most frequent place is occupied by adhesions developing on the basis of duodenal ulcers, cholecystitis, pancreatitis, or local peritonitis of other origins. In some cases, the adhesions are so extensive that the stomach is fixed by them entirely; but usually they are limited in extent, deforming the stomach or causing narrowing of the pylorus, more rarely of the cardia, and fusing the stomach with neighboring organs. In some cases, the perigastric inflammatory process is so markedly expressed that it simulates a neoplasm; the true nature of the inflammatory pseudotumor is revealed only upon microscopic examination. Surgical treatment of pyloric strictures varies depending on the nature of the stricture. In the presence of cicatricial stricture, gastroenterostomy is most often applicable; with a little-altered pylorus, Heineke-Mikulicz pyloroplasty or Payr's extramucosal pyloroplasty is possible. In strictures caused by perigastritis, simple division of adhesions achieves its goal only when there are constrictions by individual bands, or in cases where it is possible to successfully peritonealize or apply omentoplasty; otherwise, recurrence easily occurs, and therefore the operation must be supplemented by gastroenterostomy. Hourglass stomach—a characteristic disorder of the shape of the stomach—is occasionally observed as a congenital phenomenon, but usually is a consequence of a callous ulcer of the lesser curvature, more rarely of cancer, tuberculosis, or syphilis. The deformation may be combined with cicatricial narrowing of the pylorus or with the presence of a second analogous constriction of the stomach body (ventriculus trilocularis), or cascade stomach. The variety of local conditions explains the difference in methods of surgical treatment. In a bilocular stomach, the best method is circular resection of the body of the stomach or resection of the entire pyloric pouch, but in the presence of extensive adhesions this can present significant difficulties. Alongside circular resection, wedge resection from the greater curvature to the lesser can be placed; its disadvantage is that the most altered part of the stomach—the lesser curvature—remains in place. The Finney operation is analogous to wedge resection. Anastomosis between the two halves of the stomach (gastrogastrostomy) is a simple operation if there are no adhesions, and gives good results. Gastroenterostomy on the cardiac section of the stomach is especially appropriate where there is simultaneously a narrowing of the pylorus, but only on the condition that the pyloric pouch

Figure 31. Operations for bilocular stomach: 1 - transverse resection; 2 - wedge resection; 3 - gastrogastroanastomosis; 4 - double gastroenterostomy.
the shock is slight; otherwise, stagnation may occur in it, which is why it is necessary to apply an anastomosis also on the pyloric pouch, i.e., to perform a double gastroenterostomy (fig. 31). The plastics of the narrowed stomach by the pyloroplasty type must be completely rejected. In the presence of a trilocular stomach, the relations are naturally even more complex, and a way out of the situation in each individual case can be found in various combinations of the just-mentioned techniques. Phlegmonous inflammation of the stomach develops either as an independent disease or complicates general infections—typhoid, smallpox, pyemia—being thus a metastatic process; it more often develops after burns and injuries of the stomach, including surgical trauma—gastroenterostomy, expansion of the pylorus; finally, it complicates other gastric diseases, such as stomach cancer, ulcer, and even gastritis, especially in alcoholics. Usually, phlegmonous inflammation assumes a diffuse character, and less often the matter ends in the formation of a localized abscess that opens into the stomach cavity, into neighboring organs, or outward. The disease begins and proceeds with severe general symptoms: high temperature, chills, general prostration, frequent, small pulse, shallow breathing, severe thirst and general restlessness; of local symptoms, pain and swelling in the epigastric region, tenderness upon palpation, vomiting, meteorism are usually observed; to these initial symptoms are added phenomena of local and then general peritonitis, or from the very beginning the clinical picture of the disease proceeds as acute general peritonitis. The disease always has a very grave prognosis, and only in exceptional cases does the matter end with the spontaneous emptying of the abscess into the stomach or by other means. In several cases, it was possible to save patients by a timely operation—resection of the stomach or isolation of the stomach with packs introduced into the abdominal cavity. Hemorrhages. When there are indications for surgical intervention regarding hemorrhages from gastric ulcers, two forms should be distinguished: 1) profuse hemorrhages, usually in the form of abundant bloody vomit, and 2) recurrent, chronically proceeding, not abundant, but leading to general anemia and general exhaustion blood losses. In acute cases, the source of bleeding is the arterial branches of the wall or one of the main arterial trunks of the stomach (a. coronaria, a. gastro-duodenalis, a. splenica). In chronic, recurrent cases, the bleeding may—true, in exceptional cases—have its source in the veins of the stomach. It should also be noted that sometimes the source of bleeding is not established even at autopsy, despite the most careful searches. Surgical intervention for profuse hemorrhages does not have, generally speaking, a large number of supporters, and the majority of modern surgeons prefer a wait-and-see attitude and conservative treatment in such cases. The reason for this attitude is the fact that in the vast majority of cases, abundant hemorrhages are single and not prone to repetition, at least in the coming days. Haberer, one of the most active and radical surgeons in the field of the stomach, who obtained very good results from surgical intervention in acute hemorrhages on his material, nevertheless stated that out of those cases in which the operation was rejected due to its apparent hopelessness, not a single patient died from hemorrhage. The second reason for the restrained attitude towards this kind of hemorrhage is the danger of the intervention itself in weakened, exsanguinated patients; besides, the operation in itself appears rather indefinite: what exactly should be done? Practically, two cases may present themselves: a callous ulcer, easily discovered during the operation, or a "soft" ulcer, not found upon external inspection of the stomach. In the first case, to stop the bleeding directly at its source, there are three possibilities: excise the ulcer itself, ligate the feeding vessels, as Witzel recommends, or open the stomach and stitch around the bleeding vessel from the inside at the bottom of the ulcer. Resection in sharply anemized patients represents a very serious intervention, stitching around the feeding vessels from the outside is also not an easy task and, besides, a less reliable method. Stopping bleeding by stitching may fail completely due to the cutting through of sutures; cauterization with a Paquelin cautery may also fail to achieve the goal. In the second case, i.e., with ulcers not found immediately, one has to perform a wide gastrotomy to find the ulcer. With this kind of ulcer, it is of course easier to cope with bleeding by stitching from the inside, cauterization, and subsequent oversewing of the ulcer, but finding the ulcer from the stomach cavity also does not appear to be an easy matter; besides, ulcers can be multiple. All these circumstances explain the very high mortality rate, reaching 25–37–65% (Hartman, Mayo-Robson, Deaver), and the restrained attitude of modern surgery to activity in acute abundant hemorrhages. It should also be noted that the wide introduction into the clinic of blood transfusion as a hemostatic method and of hypertonic solutions is a new argument in favor of a wait-and-see attitude. As for palliative operations for ulcer bleeding, gastroenterostomy should be put in first place here. Its role in this regard comes down to the fact that the stomach is unloaded from distension by blood, its cavity collapses, and thus conditions are created for the spontaneous cessation of bleeding, but the main thing is that the movements of the stomach are reflexly calmed—irritation of the small intestine inhibits the motor activity of the stomach. However, gastroenterostomy does not always, contrary to expectations, lead to the goal—according to Kenu's statistics, in 25% of cases, patients died from continuing hemorrhage. The second group of cases—chronic recurrent hemorrhages that do not respond to therapeutic measures—is unconditionally subject to surgical treatment, which comes down to excision of the ulcer, gastric resection, or gastroenterostomy; the latter has chances of success in parapyloric ulcers, duodenal ulcers, and concomitant pylorospasm. Perforations. In ulcers that have resulted in perforation of the stomach, surgical intervention has an absolute indication and, moreover, as early as possible. Cases ending sometimes in spontaneous recovery constitute such an insignificant exception that they should not be taken into account. The question boils down practically only to the timely diagnosis and the organization of assistance as quickly as possible. In most cases, perforation occurs suddenly and unexpectedly for the patient and physician, sometimes at the height of an exacerbation of ulcer pain. The main and first symptom of perforation is sharp pain in the epigastric region, accompanied by symptoms of shock. This is very quickly followed by tension of the abdominal walls and local tenderness upon palpation of the scaphoid-drawn abdomen. Vomiting initially does not constitute an obligatory sign. It should always be remembered that sometimes very sharp tenderness appears quite soon in the right iliac fossa, which is explained by the rapid descent of the stomach contents down along the canalis lateralis dexter. This sign is practically important because on its basis a false diagnosis of perforated appendicitis is often made and the operation does not begin in the proper place. Following the initial, already very characteristic signs of perforation, increasing phenomena of general peritonitis appear. In the presence of old adhesions, the process can become localized and lead to the formation of a local abscess. The operation, as already mentioned above, must be performed as early as possible, and the outcome is determined precisely by this circumstance. General anesthesia is necessary almost always. The incision must be large enough to provide freedom in examining and suturing the perforation site. Usually, it is made along the midline above up to the navel, but if necessary, it must be extended to the right or left by transecting the rectus muscle. Finding the site of perforation usually does not pose a major difficulty if the perforation is located on the anterior wall or on one or the other curvature of the stomach; it is more difficult to orient oneself if the perforation occurred on the posterior wall towards the omental bursa. After finding the site of perforation and toilet of the immediate surroundings, they proceed to close the perforation opening by applying sutures; the difficulty of this moment lies in the fact that the edges of the ulcer are infiltrated and the sutures easily cut through, therefore the nearest non-infiltrated areas of the walls have to be taken into the suture. In extensive callous ulcers, direct closure may fail, then it remains to apply omental plastics on a pedicle. The impossibility of applying a strong suture to the infiltrated edges of the ulcer forces many surgeons to resort to some other techniques: freshening the edges of the ulcer, up to its complete excision (Finsterer), or conversely—refusal to suture the perforation, introduction of a drainage into the perforation opening, fixation of the perforation site to the abdominal wall. In extreme cases, the introduction of isolating packs is used (Petrov).
In those cases where the ulcer occupied the pyloric section of the stomach or where suturing resulted in narrowing of the outlet, gastroenterostomy is used as an additional operation; some authors consider gastroenterostomy never superfluous, while others never resort to it. Finally, some surgeons resort to resection in operations at early stages. Upon completion of all manipulations with the closure of the perforation site, the abdominal cavity is toilet-cleaned. If the perforation occurred with an empty stomach and there are no food masses in the abdominal cavity, it is easiest to limit oneself to wiping with damp gauze wipes and closing the abdominal cavity tightly. In the presence of a large amount of food masses, one either resorts to the same technique or washes the abdominal cavity with large quantities of hot saline solution. If the operation is already performed in the stage of purulent peritonitis, drainage of the abdominal cavity is necessary both through the surgical incision and through additional incisions above the pubic bone, in the iliac and lumbar regions. The outcomes of surgical intervention depend, as already indicated, on the time elapsed; mortality according to large statistics reaches on average 16-30%, but if we take cases of early interventions, operations in the first hours give 0-4% mortality, after 10 hours-25%, after a day the mortality percentage rises to 75; later recovery is noted only in isolated cases. Syphilis and tuberculosis. Surgical intervention for gastric syphilis is indicated in those cases that ended with pyloric stenosis or stomach deformation of a persistent nature, with successive disruption of motor activity; in such cases, there is no essential difference from analogous cases of a different etiology. For open gastric ulcers of syphilitic origin, specific therapy is indicated if the diagnosis is established at least provisionally; surgical intervention may also prove inevitable here if severe complications occur in the form of hemorrhages and subsequent cachexia, or if fistulas or perforations form. In some cases, a tumor palpable in the epigastrium was mistaken for a pyloric cancer and removed by resection, while the diagnosis was established only by microscopic examination. Surgical treatment for tuberculous ulcers of the stomach in the form of radical excision is possible only in rare cases due to the extent of adhesions or multiple gland involvement or dissemination along the peritoneum. In Bobrov's case, due to an extensive tuberculous ulcer, it was necessary to extirpate 3/4 of the stomach with recovery as the outcome. More often, with tuberculosis of the stomach, palliative operations take the form of gastroenterostomy in the presence of pyloric stenosis or jejunostomy if it is necessary to completely exclude the stomach from the act of digestion. Further, in cases of other complications in the form of the formation of internal fistulas or external fistulas, various palliative surgical techniques are undertaken with the aim of excluding these fistulas. Finally, in all other complications of tuberculous ulcers, surgery is indicated on the same grounds as for a simple gastric ulcer. Operations on the stomach. Stomach resection. Stomach resection is understood to mean the excision of a greater or lesser portion of the stomach walls. According to shape, three types of resection are distinguished: wedge-shaped, segmental, and circular resection. The scope of resection in individual cases varies within wide limits, up to the removal of the entire stomach (total resection, stomach extirpation); along with these terms, partial or complete gastrectomy are equally customary. The prevailing methods of circular resection remain two methods proposed by Billroth (see Billroth's operations on the stomach). The main modifications introduced by other surgeons are as follows: Kocher in 1890 modified Billroth's 1st method in the sense that he implanted the end of the duodenum not into the stomach incision, but into its posterior wall, retreating 1-2 cm from the tightly sutured end (Figure 32). The purpose of this modification is to avoid the junction of two suture lines as the most dangerous place in terms of cutting through. In order to weaken the tension in the sutures, Kocher preliminarily mobilizes the duodenum by making an arcuate incision at its upper corner. Hacker and Mikulicz introduced a change into Billroth's second method, which consisted in the fact that instead of a typical gastroenterostomy, the lower end of the stomach was implanted into a loop of the jejunum, while the upper half of the gastric incision was previously sutured tightly. Polya (1911) and Balfour (1912) modified this latter modification (Fig. 33), implanting the entire extent of the gastric incision into the jejunum. The purpose of this latter proposal: 1) to avoid narrowing of the anastomosis, 2) to avoid the development of perverse movement of food masses, 3) to shorten the duration of the operation by eliminating the occlusion suture of the stomach. All these benefits are actually illustrated


Figure 33. Resection according to Polya-Balfour.
resections,

£3<
faded, and none of the modifications of Billroth's method finds a large circle of followers. The Riedel method—circular resection of the middle part of the stomach and suturing of the segments end-to-end—in essence does not differ from Billroth's method. Saddle resection according to the Schmieden method (Fig. 34) is a combination of Billroth's 1st method or the Riedel method with excision of the lesser curvature of the stomach in order to remove the entire extent of the Waldeyer pathway as the area of preferential development of gastric ulcers. Partial resections of the stomach walls, not to mention atypical operations sometimes used in the removal of benign gastric tumors, consist in the excision of a part of the lesser curvature in the form of a wedge or in the form of a segment, depending on the shape and spread of the process (Fig. 35). In the first case, the closure of the defect is performed in the transverse direction, in the second—in the longitudinal. With these forms of re-proposed by Mikulicz and Kaiser, after applying the sutures, the stomach is somewhat deformed, taking the shape of a pouch or a long elongated narrow channel. But in a sharp form, these deformations occur only after more extensive resections; in such cases, the operation should be supplemented by the creation of a gastroenteroanastomosis to avoid stagnation in the stomach, since in addition to deformation, the function of the antral part of the stomach suffers due to the transection of the vagus nerve. Gastrotomy was performed three centuries ago for the removal of swallowed foreign bodies (Schwabe; 1635). At present, gastrotomy is performed either to remove foreign bodies from the stomach, or as a preliminary act of other stomach operations (dilation of the cardia, retrograde bougienage of the esophagus), or to stop bleeding from ulcers, or simply to examine the stomach from the inside. Depending on the goals, the size of the opening in the stomach is made from 1-2 cm to dimensions allowing the introduction of four fingers and even the entire hand into its cavity. The incision is made as close as possible to the place where further manipulations are expected, and in order to get rid of excessive bleeding, it is carried out either in the direction of the vessels, from the greater curvature to the lesser, or along the anterior wall of the stomach, along the axis of the stomach, at an equal distance from both curvatures. Before opening the stomach, the abdominal cavity must be well Figure 34. Saddle resection according to Schmieden.


Figure 35. Segmental and wedge resections of the lesser curvature.
protected with gauze wipes, and to hold the stomach, ligatures are passed through its walls or various clamps are applied. When closing the stomach incision, attention should be paid to thorough hemostasis of the mucous membrane. The incision itself is sutured with a two-tier suture. As a method of gastrotomy, in recent years it has again been widely used to dilate the cardia in cardiospasm. The operation in this form was proposed in 1900 by Mikulicz and consists in the fact that after a wide opening of the stomach, four fingers or even the entire hand are introduced into it, the cardia is found and gradually stretched, first introducing one finger, then two, three and even four; thus, the diameter of the cardia can be stretched to 10-12 cm. The results of such an operation are usually brilliant and persistent, but of course the possibility of relapse is not excluded. Of the 60 operations described in the literature, fatal outcomes were observed only in isolated cases. Pyloroplasty. Plastic expansion of the pylorus for its cicatricial strictures was proposed by Heineke-Mikulicz in 1887. The operation consists in the fact that a longitudinal incision 5-6 cm long is made through the entire thickness of the walls through the narrowed pylorus, the edges of the incision are pushed apart to the sides with hooks and the wound is sutured in the transverse direction, with the first suture applied in the middle as a guiding one (Fig. 36). Practice has shown the low applicability of this operation
in cicatricial strictures, and in any case it is permissible to resort to it only on condition of the mobility of the pylorus and the absence of extensive scars; otherwise the operation is either unfeasible, or results in recurrences, or even proves useless from the very beginning. If the indication for it is not a cicatricial stricture, but pylorospasm or congenital stenosis of the pylorus (spasm and hypertrophy of the pylorus), then technically the operation becomes easily feasible, but here it is competed with by another modification of it—extramucous pyloroplasty: the incision is made in the same way as in the first, i.e., longitudinal, 2 cm long; the pyloric muscle is prepared and transected transversely or a piece 1 cm long is excised from it, after which the incision is sutured in the transverse direction (Weber, Payr). It should be noted that during this operation it is easy to open the gastric mucosa, but this is of no great importance. As an operation standing on the border of pyloroplasty and gastroduodenostomy, one must consider Finney's method. Operations on the cardiac part of the stomach. Some of these are of a plastic nature and aim at correcting mechanical obstacles on the basis of spasm, scars from burns, etc. Others are undertaken to remove neoplasms and therefore must be radical and amount to resection. In addition to the Mikulicz operation described above (digital dilation of the cardia) for cardiospasm, other methods serve the same purpose: cardiotomy, cardioplasty, esophago-gastroenterostomy, esophago-jejunostomy. Transverse cardiotomy according to Marwedel, with successive suturing of the incision in the transverse direction, appears to be a difficult operation due to the poor accessibility of the operative field. Out of 14 cases of operations by this method, 1 ended in death, in 2 a relapse occurred, and in 9 recovery. Simpler and safer is Heller's operation—extramucous cardiotomy on the anterior and posterior walls with subsequent wrapping with the omentum. Out of 49 cases, cure was obtained in 28, and improvement in 10. Esophagogastroenterostomy according to Heyrovsky between the fundus of the stomach and the esophagus is possible if the lower end of the esophagus is dilated and descends into the abdominal cavity, sometimes in the form of a pouch. In cicatricial stricture of the cardia with cicatricial shrinkage of the entire stomach after a burn, Hesse performed an anastomosis between the mobilized abdominal section of the esophagus and the preserved area of the fundus of the stomach on one hand, and the jejunum on the other. The result of the operations was excellent. The literature describes 15 such cases with 12 good outcomes. Resection of the cardiac region of the stomach by the abdominal route is one of the difficult operations. The indication for it is cancer of the cardia; the first attempt to excise this kind of tumor belongs to Mikulicz, but the case ended in failure. The operation is possible and makes sense only when the tumor does not extend to the diaphragm and neighboring organs, therefore the question of resectability can be finally decided only after laparotomy. The operation requires wide access, which is provided either by the Marwedel incision or by a midline incision with the addition of a transverse incision to the left. The excision should begin with the mobilization and elongation of the abdominal section of the esophagus, for which the peritoneum is incised, both vagus nerves are transected, and by blunt dissection with a finger, the esophagus is freed from the cellulitis, with main attention paid to not opening the pleura. Then the upper section of the stomach is mobilized together with the tumor and the left gastric artery is ligated. Clairmont recommends starting the entire operation precisely with the ligation of this artery, after which further manipulations are also facilitated. The freed and elongated esophagus is fixed with sutures to the edges of the esophageal hiatus. After excision of the tumor, the connection of the end of the esophagus with the stomach is performed in various ways: it is possible to sew the esophagus end-to-end, but it is more profitable to sew the stomach tightly and sew the esophagus into a new opening made in the stomach. Bircher immersed the end of the esophagus into an incision in the stomach and sutured it higher up. Gerhammer proposes to sew the end of the esophagus with a seromuscular cuff from the walls of the stomach. The main dangers associated with this operation consist in the possibility of suture dehiscence due to tension or due to marginal necrosis of the end of the esophagus, and finally due to infection of the peritoneum and especially the pleura and mediastinal tissue. To date, 33 cases of abdominal resection of the cardia with 9 recoveries and 70% mortality have been described (Borchers). In conclusion, it is necessary to mention repeated operations on the stomach after gastroenterostomies and after resections undertaken for so-called peptic ulcers, requiring excisions, anastomoses, and resections of the stomach and intestines—small and large.
V. Dobrotvorsky. IX. Stomach neuroses. By stomach neuroses one must understand those pathological nervous reactions that arise in it as manifestations of a general neurasthenic constitution and are caused by psychic affects. From a symptomatological point of view, stomach neuroses include, on the one hand, those of its diseases where, in the presence of a number of subjective disorders, the most thorough examination fails to reveal any objective signs of organic stomach disease, and on the other hand, those in which the intensity of subjective sensations sharply does not correspond to objectively ascertained changes. The main contingent of patients with stomach neuroses are constitutional psychoneurotics; but stomach neuroses can also arise on the basis of organic stomach diseases, with a certain predisposition of the nervous system. The mechanism of the occurrence of stomach neuroses appears as follows. A psychic trauma caused a disturbance of psychic equilibrium—an affect. The central nervous system strives to "unload", to restore the lost equilibrium—to "react the affect". This reaction proceeds along the autonomic nervous system and, due to certain secondary causes, may proceed precisely in the direction of the stomach and cause this or that pathological reaction in it. The main condition for the occurrence of a stomach neurose is a psychically and autonomically stigmatized personality. It has a number of features, a number of deviations in the psychic and emotional structure, namely: overestimation of oneself with insufficient faith in one's own strengths, weakness of will and easy distractibility, irritability and hence an unfair attitude towards others and, as a consequence, self-absorption, hypochondria—fear of possible disorders on the part of one's organs. Such a personality easily comes into conflict with the surrounding world and cannot withstand the demands placed upon it by the latter. Hence arises a psychic trauma, i.e., a disturbance of equilibrium in the central nervous system. Persons of this kind are generally distinguished by the instability of equilibrium in the sphere of the autonomic nervous system (G. Bergmann). If at the same time its department controlling the functions of the digestive apparatus is distinguished by increased excitability, then the autonomic nerve pathways running from the central nervous system to the stomach offer less resistance to impulses coming from the central nervous system, and in particular to the "reaction" of affects arising in it. A secondary cause of the development of gastric neurose can also be the inferiority of the stomach itself, the irritation threshold of which is significantly lower than that of other organs. Thus, stomach neuroses can occur if in a psychasthenic the affect of displeasure repeatedly coincides in time with some accidental gastric disorder: the resulting engram sensitizes the nervous system of the stomach so much that the repetition of the affect of displeasure will cause the same picture of gastric suffering (by the type of formation of Pavlovian conditioned reflexes). Stomach neuroses also arise in such a way that a nervous-stigmatized person develops an acute stomach disease, after which they retain a fear of the repetition of the disease, and therefore attention is fixed on the stomach. This is enough for the picture of gastric neurose to develop. In addition, with increased excitability of the autonomic nervous system and its gastric department in particular, stomach neuroses easily arise due to the reflex transmission of irritation from other organs, especially from the organs of the abdominal cavity when the latter are affected by this or that pathological process (diseases of the liver, intestines, uterus, peritoneum, etc.). Stomach neuroses include the so-called gastric dyspepsia (see below). Other stomach neuroses, namely—sensory neuroses: bulimia, anorexia, gastralgia, pyrosis nervosa, gastralgokenosis (see); motor neuroses: nervous eructation, nervous rumination, peristaltic unrest of the stomach, nervous vomiting (see below)—are isolated from a purely symptomatological point of view by this or that prominent manifestation. Gastric dyspepsia is predominantly a polysymptomatic disease, while the remaining stomach neuroses are monosymptomatic. Stomach neuroses undoubtedly include many of those diseases that are considered disorders of the secretory and motor functions of the stomach: independent (primary) forms of hypersecretion, hypo- and achylia, pylorospasms, atonia, etc. However, in view of the fact that in these forms a disease picture develops that is characteristic of a certain form of disturbance of one or another function of the stomach, they are separated into a special department—"disorders of the secretory and motor function of the stomach", where they are described in parallel with disorders of the same functions of the stomach developing on the basis of organic diseases and manifesting with the same seemingly independent disease picture. Nervous gastric dyspepsia. By gastric dyspepsia most authors understand those forms of stomach neuroses in which a number of subjective disorders on the part of the stomach are observed in the absence of signs of this or another more persistent disturbance of the function of the secretory and motor apparatus of the stomach. In essence, between the concepts of intestinal and gastric dyspepsia there is a fundamental difference: whereas intestinal dyspepsia is determined by a violation of digestive processes in the intestine, e.g., a violation of fermentation or putrefaction processes in the absence of not only organic changes in the intestine itself, but also its neurose, under gastric dyspepsia, as indicated, now most authors understand only a special and moreover most important group of stomach neuroses. Many do not consider all cases of gastric dyspepsia to be neuroses. Thus, Cohnheim divides gastric dyspepsias into various types, with nervous gastric dyspepsia considered only one of the types, and besides it, dyspepsia is also distinguished in anaemic subjects, in those with gastroptosis (enteroptotics), and in those suffering from tuberculosis. Most authors, however, recognize that in essence, even in these latter types of gastric dyspepsia, disturbances of the nervous system function lie at the base, with the only difference that in addition to the general neurasthenic constitution, there is also a general asthenia with this or that already developing or developing on this basis suffering: enteroptosis, pulmonary tuberculosis, etc., which in turn further weaken, resp. irritate the nervous system and thereby contribute to the development of stomach neurose. Dreyfuss, who considers all gastric dyspepsias to be psychogenic diseases, divides gastric nervous dyspepsia into purely psychopathic, congenital hysterical, resp. neurasthenic forms, into psychogenic and cyclothymic-circular forms. In any case, the most accepted opinion is the one considering all dyspepsias to arise on a nervous basis. History of the doctrine of gastric dyspepsia. The doctrine of nervous gastric dyspepsia over the past 50 years is closely connected with the names of Leube, Ewald, Stiller, Glenard, Strümpell, and Dejerine. In 1879, Leube first described a strictly delimited symptom complex, to which he gave the name of nervous dyspepsia, and he considered it a pure sensory neurose of the stomach, believing that the cause and essence of this disease is the increased irritability of the peripheral nerves of the stomach, to which the entire nervous system reacts only secondarily. Ewald held a diametrically opposite point of view, believing that dyspepsia in general is not a clinically delimited disease, but only a symptom complex that is a partial manifestation (and often the sole manifestation) of general neurasthenia or hysteria. At the same time, he expressed the assumption that in dyspepsia, a disturbance of the secretory and motor work of both the stomach and intestines without organic stomach disease is also often observed. Nevertheless, the thought of clinicians turned towards searching for organic bases for nervous dyspepsia. In this regard, a major role was played by the views of Glenard (1885), who in a number of cases of nervous dyspepsias found anatomical changes not in the stomach, but in the position of the abdominal viscera, which is why he considered general enteroptosis responsible for the occurrence of this suffering. According to his observations, all subjective and objective disorders of these patients disappeared after eliminating the indicated anomalies in the position of the abdominal viscera with the help of these or those therapeutic measures. Glenard considered neurasthenia and neurasthenic symptoms observed in such patients to be a consequence of their dyspeptic disorders. Stiller drew attention to the constitutional moment in the pathogenesis of gastric dyspepsia in 1907. He believed that nervous dyspepsia is only a partial manifestation of congenital general asthenia (asthenia universalis congenita), and not a morbus sui generis or a symptom of general neurasthenia, and that dyspepsia represents a phenomenon coordinated with the latter and is based on a congenital constitutional predisposition.
According to Stiller, the painful sensations in neurodyspeptic patients are based on nerve disorders, depending partly on hyperesthesia of the abdominal sympathetic nerve (resp. solar plexus), partly on hyperesthesia of central origin, as well as on the general psychological attitude of the patient. This psychological factor in the pathogenesis of nervous dyspepsia is especially emphasized by Strümpell, who even introduces a new designation for so-called psychogenic dyspepsies, believing that the overwhelming majority of nervous dyspepsies depend on primary changes in the emotional life of the patient, among which he places the feeling of fear in the first place. Strümpell's doctrine on the paramount role of the psychological factor in the pathogenesis of gastric dyspepsia is further developed by Dubois and Déjerine, who even give such patients a corresponding name: pseudogastropaths. In modern times, the French school, without denying the role of the psychogenic factor, returns once again to the opinion that the cause of dyspepsies is hyperesthesia of the solar plexus. Finally, in very recent times, Strauss and Kraus attach particular importance in the etiology and pathogenesis of dyspepsies to constitutional inferiority, heredity, and endocrine imbalance. Etiology. Gastric dyspepsies can be of purely psychogenic origin as a result of the so-called acting out of psychological affects in the direction of the autonomic nervous system; therefore, they are observed in psychoneuroses, but they can also be of reflex origin (in the sense of Pavlovian reflexes) in diseases of a wide variety of organs of the abdominal and even non-abdominal regions. The disorders characteristic of gastric dyspepsia are caused by increased irritability, apparently predominantly of the sympathetic plexus of the stomach, and generally a disturbance of equilibrium in the autonomic nervous system. Under such conditions, even the most insignificant stimuli, e.g., normal contractions of the stomach, are sufficient to cause unpleasant subjective sensations. Alongside this increased irritability of the stomach nerves, an increased irritability of the central nervous system plays a large role. This is why nervous dyspepsies are frequently encountered as a partial phenomenon in general neurasthenia, resp. hysteria, although it cannot be denied that sometimes dyspepsia also occurs as an independent neurosis (monosymptomatic hysteria - Lewin). Frequently, the cause of the disease can be psychological excitement, grief, worry, a feeling of fear, etc. Fear of infection, fear of falling ill with cancer, unhappy love, grief, family and business worries and agitation, and, generally speaking, all psychological traumas are quite frequently the etiological factor in gastric dyspepsia. Disturbance of normal sexual life, excesses in baccho et in venere, masturbation, coitus interruptus, etc., can also serve as a cause for the occurrence of gastric dyspepsia; but physical trauma with the subsequent development of traumatic neurosis can also play a certain role. In a large number of cases, gastric dyspepsia, as already stated, occurs reflexly, and the excitation can come from a wide variety of, even very distant, organs. Thus, in diseases of the liver and intestines, dyspeptic phenomena originating from the stomach may appear. Often, with stubborn constipation or with worms (K. Faber), gastric dyspepsia may arise. It is frequently observed in diseases of the female genital sphere (Kehrer) and even in physiological changes in the genital sphere, during menstruation and especially during pregnancy, in the form of appetite disorders, appetite paresthesia (Stiller), disorders of the motor function of the stomach, vomiting, etc. A special name—dyspepsia uterina (Kisch)—has even been proposed for these disorders. Similar changes can be observed in men with prostatitis, prostatorrhea, spermatorrhea, phosphaturia, and sexual neurasthenia. Of course, all these disorders cannot be considered the main causes of the occurrence of neurodyspeptic phenomena originating from the stomach. For the most part, they are coordinated, and the primum movens for the occurrence of the typical phenomena of the disease under discussion is a general neuropathic constitution (status enteroptoticus, asthenia universalis). It cannot be further denied that the diseases already listed above, which are pointed out by French and partly German authors (syphilis, tuberculosis, anemia, malnutrition, etc.), quite frequently play a certain role in the etiology of neurodyspeptic disorders, creating a predisposition to the occurrence of dyspepsia. The mechanism of development of gastric dyspepsia in the indicated diseases may consist in the fact that, in constitutional enteroptosis, the vertically positioned stomach drops even more upon emaciation, which entails a number of nerve disorders. In turn, subjective disorders in nervous dyspepsia often lead to malnutrition due to loss of appetite or fear of eating, and this causes even greater emaciation. Thus, a circulus vitiosus is frequently created, which is not always easy to break. Symptomatology. Among the subjective signs of gastric dyspepsia, the symptoms of general neurasthenia play the main role. The latter imparts a characteristic coloring to the patients' complaints. Sometimes local symptoms originating from the stomach play the dominant role, and sometimes general nervous phenomena predominate. But in both cases, the subjective symptoms are characterized by three moments. First, the complete irregularity and capriciousness of the onset of these symptoms and the variability of their intensity. Almost always in these patients, there are intervals during which they experience no disorders at all; but even in periods of poor health, the intensity and character of the symptoms change. The second moment is the dependence of subjective disorders on psychological disturbances, excitations, depressions, and dissatisfaction, which either themselves cause subjective disorders or worsen already existing ones. Finally, the third moment is the absence of any kind of other factors that could cause a disturbance of the sensory equilibrium of the stomach. Thus, the intake of food, its quality and quantity, bed rest, warm procedures, etc., have no significance in the appearance or change in intensity of neurodyspeptic disorders. Frequently, heavy food is well tolerated, whereas there are periods of psychological excitation when even light food causes severe pain. As for the character of these subjective disorders, their picture is so diverse that it is difficult to fit it into definite frameworks. Among general nervous disorders, general irritability and a hypochondriacal-depressive state come to the fore on the one hand, and rapid fatigue, reluctance to work, a tendency toward pessimistic ideas about the curability of the disease, and a feeling of heaviness in the head, constant or in attacks, on the other; headache occurring shortly after eating, and sometimes even on an empty stomach, polyuria and pollakiuria, back pain, especially between the shoulder blades, dizziness, and palpitations, which are associated with constipation or generally insufficient stool output, are frequently observed. Frequently, insomnia or restless sleep troubles these patients. Local phenomena originating from the stomach are distinguished by the same diversity. These include salivation, eructations, pain, nausea, vomiting, attacks of shortness of breath, and sometimes even asthmatic attacks after eating. These symptoms are observed either separately or combine into a variegated picture of the disease, replacing one another or occurring simultaneously. Heartburn in dyspeptics must be specially noted, in contrast to burning stomach pains in hypersecretion and gastritis. Heartburn in gastric dyspepsia is completely independent of food intake. It is frequently observed on an empty stomach (gastralgokenose of Boas). It does not disappear either from the horizontal position of the patients or from therapeutic procedures in the form of warmth or hot compresses. At the same time, psychological irritation (even the most minimal) can undoubtedly significantly worsen the painful sensations in the stomach area. Complete loss of appetite is frequently observed, sometimes reaching complete aversion to food; however, it must be pointed out that sometimes there is no real lack of appetite, but sitophobia is noted, i.e., fear of eating due to disorders that may arise after eating. Bowel function is also extremely variable. Periods of constipation can alternate with periods of normal stool or periods of diarrhea. Upon objective examination, a general habitus asthenicus s. enteroptoticus and a whole series of general nervous phenomena are most often noted—weakening or enhancement of skin reflexes and reflexes from the mucous membranes, frequently a sharp increase in knee reflexes and reflexes from the tendo Achillis, pupil dilation and vasomotor disorders in various areas of the body, easy excitability, tremor of the hands and tongue, and phenomena of dysfunction in the autonomic nervous system. Nutrition is frequently undermined, since patients, out of fear of eating, try to limit food intake, and as a result of malnutrition they become even more nervous and irritable, which in turn leads to a worsening of subjective disorders. Insomnia also leads to malnutrition (Mathieu, Roux).
When examining the abdomen, patients with gastric dyspepsia quite often exhibit flaccid abdominal walls with a reduced amount of fat, low placement of all organs, and a descent of the lower border of the stomach. A splashing sound in the stomach is elicited extremely easily, which indicates hypotonia of the gastric walls. Painful points upon pressure are frequently observed; hyperesthesia of the solar plexus can often be found. The sensitivity in this case is sometimes so great that even difficulty arises regarding the differential diagnosis between nervous dyspepsia and gastric ulcer. Not infrequently, besides hyperesthesia of the indicated region, there are also painful points corresponding to the superior and inferior mesenteric plexus. Sometimes the entire linea alba from the navel to the xiphoid process and even McBurney's point are sensitive, which can lead to confusion with appendicitis; sometimes an increased sensitivity upon pressure on the spinous processes of individual vertebrae is also noted. As for the function of the stomach, according to Boas, three types of gastric dyspepsia can be observed. In the first, both motor and secretory functions are completely normal; in the second, there is a disturbance of either the one or the other function lasting for a more or less long period; and finally, the third type, when sharp fluctuations are observed in both functions. Sharp fluctuations are especially characteristic of the secretory function, when a few days after hypochylia one can observe hypersecretion and vice versa, i.e., there is so-called heterochylia (Hemmeter). The fluctuations observed in the third type can bear a bizarre, sometimes even contradictory character. Thus, atony is sometimes observed simultaneously with increased acidity, or reduced acidity simultaneously with increased motor activity. X-ray examination sometimes yields an equally bizarre picture: there is gastroptosis and atony, then enhancement of peristole and peristalsis, then finally normal relations. In any case, a decrease in motor activity in the sense of a longer stay of food in the stomach in this disease has not been established. In the large intestines, sometimes spastic, sometimes atonic conditions are observed. Diagnosis. To establish a correct diagnosis, one must first take into account those three characteristic features indicated above; second, the complete inutility of a strict diet and other usual therapeutic measures in terms of their influence on subjective disorders; finally, the discrepancy between subjective disorders and objective examination in the sense that the severity of subjective sensations does not correspond at all to the insignificance of the objective symptoms found during the examination of the abdominal cavity organs. In differential-diagnostic terms, it is necessary to distinguish nervous dyspepsia from chronic gastritis, gastric ulcer, cholelithiasis, and hernia of the linea alba. The differential diagnosis must be made extremely cautiously in order not to overlook, even in the presence of a general neuropathia, some organic affliction which in its picture may closely resemble gastric dyspepsia, since even in gastric cancer, neuro-dyspeptic symptoms can be observed, and gastric ulcers, according to modern views, are observed especially often in people with an unbalanced nervous system. Finally, when making a diagnosis, besides a detailed examination of the gastrointestinal tract, one must examine the general state of the nervous system and, what is no less important, the state of various organs that can serve, as indicated above, as a starting point for the development of the neuro-reflex form of dyspepsia. In any case, in the differential diagnosis, one must first exclude all organic diseases of the stomach, and only in their absence can one settle on the diagnosis of gastric dyspepsia. Prognosis of nervous dyspepsia appears rather doubtful; as for cure, a prolonged disappearance of neuro-dyspeptic disorders can be expected only where the exclusive cause of them is a primary disease in some other organ. The elimination of the latter can lead to the disappearance of dyspeptic phenomena on the part of the stomach. But such cases are relatively rare. As a rule, recovery from nervous dyspepsia is only temporary. However, with the appropriate therapeutic measures, all subjective disorders can be made to disappear for a longer or shorter period of time. Therapy. In view of the fact that gastric dyspepsia most often arises on the basis of general instability of the nervous system, which manifests itself already in childhood, prophylaxis is of great importance in treatment, as a result of which in such cases from early childhood all measures must be applied to bring to naught or reduce the predisposition to a general neurosis. Appropriate nutrition, hardening, strengthening of musculature, elimination of all harmful factors that can lead to a general neurosis, regulation of sexual and mental life are the main points in the prevention of this disease. As for the treatment of nervous dyspepsia itself, here, in view of the extreme diversity of the picture of this disease, individualization plays a role more than anywhere else. First of all, it is necessary to clarify the underlying affliction that serves as the starting point for the onset of neuroses—disease of the liver, female genital sphere, etc.—and direct treatment in this direction. Then causal therapy also entails strengthening the nervous system. Here, rest therapy must be placed in first place. It is especially indicated where there is a nutritional disorder and especially its reduction. Removal from the usual home environment to a sanatorium or favorable climatic conditions, prohibition of professional work for a more or less prolonged period soothe the nervous system and reduce dyspeptic disorders. As for dietary treatment, forced nutrition stands in the first place (Weir-Mitchell). Quite often, with an increase in weight in patients, their subjective disorders also disappear. Frequently, hard-to-digest dishes lead to a quicker disappearance of subjective disorders than easily digestible ones. A predominantly vegetarian regimen is recommended, and parallel with it, the restriction of protein and especially animal food. Light massage, electro-hydrotherapy, especially gentle hydrotherapeutic procedures not associated with sharp temperature changes, bring extremely great benefit. Drug therapy should be reduced to a minimum. For insomnia, it is sometimes necessary to use hypnotics—veronal, trional, hedonal, luminal. For sharp excitation of the nervous system, valerian and bromides are given. In nervous diarrheas, sometimes parallel with a change in diet, it is necessary to use calcium (Calcium carbonicum, Calcium phosphoricum), sometimes bismuth. It is not recommended to use narcotics (opium and morphine). It is almost never necessary to use drinking of any mineral waters except those used for anemia and containing iron (Zheleznovodsk waters, Levico, Roncegno, etc.). M. Guberngrits. Gastralgia (gastralgia nervosa), a term applied only to those paroxysmal pains arising in the stomach that are not caused by organic diseases of the stomach. These are usually periodically or irregularly occurring attacks of sharp pains in the epigastric region, independent of food intake, accompanied by nausea and sometimes vomiting, and often radiating to the hypochondria, chest, and back. These attacks last from several minutes to many hours and are observed most often in neurasthenics and hysterics, appearing in them mostly under the influence of excitement, grief, etc. One should be very cautious with the diagnosis of gastralgia, because with the development of diagnostic methods, an ever greater and larger part of so-called nervous gastralgias turns out to be pains caused either by organic diseases of the stomach (ulcer, cancer, perigastritis) or diseases of neighboring organs (hepatic, renal, and pancreatic stones, floating kidney, angina pectoris and abdominal angina, hernias of the linea alba, etc.). Gastralgia is caused in all probability by spastic contraction of the stomach, most often the pylorus (pylorospasm). Gastralgia is also of reflex origin, and the source of the reflex can be chronic appendicitis, inflammation of the peritoneum, and diseases of the genital sphere in women (with irregular menstruation, diseases of the ovaries and tubes, with incorrect uterine positions) and in men (with hypertrophy of the prostate gland, spermatorrhea, etc.). Gastralgias can also arise in diseases of the central nervous system (brain tumors, myelitis, tabes dorsalis, etc.), in chronic nicotine poisoning, etc. But it should be remembered that pylorospasm—this main source of stomach pains in general and nervous gastralgias in particular—in the vast majority of cases is caused by organic diseases. The very attack of nervous gastralgia does not present anything typical, and its neurotic character is established only by excluding the organic diseases listed above on the one hand and establishing the presence of neuropathic constitutional factors on the other. Nervous heartburn (pyrosis nervosa).
By nervous heartburn, unlike pyrosis hydrochlorica, is understood that type of heartburn which is caused not by increased acidity of the gastric contents, but by some other, not always clear factors (see Heartburn). Nervous rumination (ruminatio, merycismus) differs from simple regurgitation (regurgitatio) in that the food that has passed from the esophagus into the mouth is chewed and swallowed again. (On the pathogenesis and clinical features of this phenomenon, see Rumination.) The special treatment of nervous rumination consists in making the patient suppress the act of regurgitation by an effort of will. It is very advisable to make such patients eat in the presence of others so that the patients closely monitor themselves. It should be insisted that the patient eat slowly and chew the food thoroughly. Proceeding from the fact that liquids or a combination of solid and liquid food more often cause regurgitations, Boas recommends a "dry diet," which in a number of cases has proved to be very effective. Nervous eructation (eructatio nervosa, aerophagia, morbus ructuosus). Nervous eructation is eructation of air in the form of separate attacks following each other rapidly, independent of food intake. At night these attacks usually cease. Patients, without realizing it themselves, swallow a significant amount of air (inructatio), which accumulates in the esophagus or in the stomach and is then expelled outward (eructatio). In rarer cases, almost exclusively in hysterical women, eructation is accompanied by a loud convulsive squeal (eructatio tonans). It arises most often on the basis of hysteria under the influence of such affects as fear, grief, etc., but there is a significant contingent of patients in whom the initial moment of this functional disorder is other stomach diseases accompanied by a feeling of tension in the region of the stomach. This sensation in some such patients causes a desire to get rid of it through peculiar movements of the pharynx and esophagus, which contribute to the gradual swallowing of atmospheric air. Having accumulated in a significant amount, it is then expelled outward by a loud, prolonged eructation. At the same time, the patient receives momentary relief and, having experienced this, then begins to resort to this technique frequently, imagining that he is thus getting rid of gases formed in the stomach. Of particular note is aerophagia in cardiac patients, whose condition, as is known, deteriorates sharply under the influence of the filling of the stomach and intestines with gases, resp. high standing of the diaphragm. Aerophagia patients sometimes accumulate so much air in the stomach that their condition takes on a threatening character. In such cases, the best remedy is the rapid introduction of a stomach tube, immediately relieving the patient from the distressing condition. Special treatment of nervous eructation consists first of all in the use of appropriate psychotherapy. It is necessary to explain in detail to the patient that his disease depends on his swallowing air. Suggestion and hypnosis often lead to good results here as well. Systematic training of such patients also plays a major role. To aid psychotherapy, it is recommended (Bouveret, J. Ch. Roux, and Mathieu) to keep the mouth open for a long time, forcing such patients to hold a cork or a wide cigar holder with their teeth. The results of such a technique appear quite quickly. Boas advises introducing a stomach tube into such patients daily for 5-7 days. All these techniques are nothing more than "instrumental psychotherapy." Peristaltic unrest of the stomach (Kussmaul) (tormina ventriculi nervosa). At the basis of this motor neurosis of the stomach lies gastric hyperperistalsis ["segmenting" peristalsis (see above-X-ray examination)]. In the vast majority of cases, hyperperistalsis is caused either by organic pyloric stenosis or duodenal ulcer. In only an insignificant number of cases is it not a reflex act, but a pure motor neurosis of the stomach on the basis of pathological function of the autonomic nervous system. Such conditions are most often observed in exhausted individuals, with very flabby abdominal walls, mainly in women, and alongside the stomach, the entire intestine also participates in the peristaltic unrest (tormina ventriculi et intestinorum). During such visible peristaltic waves, rumbling and gurgling noises can be heard all over the abdomen even at a distance, and patients complain of pain and a feeling of tension in the abdomen. Only gradually, sometimes after many hours, does calming occur. Only the most careful clinical and, in particular, radiological examination can save from erroneous diagnoses, especially in the sense of missing the recognition of stenosis in the region of the stomach or intestines. As with all neuroses, treatment must first of all be directed at the general neurosis. The use of bromides and atropine proves to be very effective in such cases as symptomatic treatment. Nervous vomiting (vomitus nervosus). Under this term, applying it to designate a neurosis of the stomach, is understood not vomiting caused reflexively, and not vomiting caused by pathological conditions of the central nervous system, but vomiting of a purely psychogenic nature, arising under the influence of severe experiences, excitement, grief, worry, mental overwork, a sense of fear, disgust, etc. This type of vomiting is especially common in young girls and women on the basis of hysteria and neurasthenia. Nervous vomiting is characterized by independence from the quality and quantity of food, extraordinary ease of appearance, frequent absence of preliminary symptoms (nausea, heaviness, and pain in the stomach region), absence of secretory and motor disorders from the stomach, and a sharp dependence on causes affecting the patient's mood. Treatment of all neuroses described here coincides with the treatment of nervous dyspepsia.
X. Tuberculosis of the stomach. Frerichs found tuberculosis of the stomach in 2.4% of all autopsy cases of tuberculous patients; Simmonds and Glaubitt only in 0.4–0.76%, wherein in Simmonds' material 92% of stomach tuberculosis was accompanied by intestinal tuberculosis. Consequently, the stomach is affected by tuberculosis much less often than the intestines. This is explained by a number of reasons causing the low susceptibility of the stomach to tuberculous infection, namely: 1) the scarcity of lymphatic follicles in the stomach (...), the latter being found in somewhat greater numbers only in the pyloric part of the stomach, which is indeed a favorite site for the localization of tuberculous follicle lesions; 2) the high resistance of the gastric mucosa to infections, and 3) the layer of mucus covering the mucosa (Arloing); 4) the bactericidal influence of HCl (according to Weichselbaum; at present this influence is disputed). Due to all these reasons, tuberculous sputum usually passes through the stomach without infecting it. Nevertheless, contact infection of the stomach by sputum appears to be one of the frequent modes of infection of the stomach with tuberculosis. The question of whether swallowed sputum containing tubercle bacilli can infect a simple gastric ulcer remains open for now. Another pathway of infection of the stomach, lymphogenous, occurs in tuberculosis of the peritoneum or lymph glands. The third pathway, hematogenous, according to Arloing, is the sole method of infection of tuberculosis of the stomach. Taking into account the significance that the hematogenous pathway has for the spread of tuberculosis in general, this pathway must also be recognized as frequent; in miliary tuberculosis it is beyond doubt. Tuberculosis of the stomach manifests in 4 main forms. 1. Miliary tuberculosis in general acute and subacute miliary tuberculosis. 2. Solitary caseous-purulently disintegrated tubercles, sometimes in the form of conglomerates (e.g., in the pyloric region). 3. Tuberculous ulcers of various kinds: a) small crateriform ulcers, deep, involving the submucosa, having an undermined, overhanging margin infiltrated above the ulcer; the base of the ulcer consists of granulation tissue; b) flat ulcers of various sizes (from a pea to a palm), often multiple; they either do not reach the submucosa or involve only its superficial layer. 4. The hyperplastic diffuse form, the so-called tuberculose inflammatoire of Poncet, in which specific tubercular tissue elements are absent, and there is a development of diffuse granulation and subsequently sclerosing tissue. The favorite site for tuberculous processes in the stomach, as already mentioned, is the pylorus and prepyloric region. The clinical manifestations of gastric tuberculosis present nothing characteristic. General dyspeptic phenomena and pains of a gastrospastic character cannot serve as an indication of a tuberculous lesion of the stomach. In tuberculous ulcer, pain is less sharply expressed than in a simple ulcer, and bloody vomiting is rarer due to obliterating processes in the arteries in tuberculosis. Organic disease of the stomach becomes evident when signs of pyloric stenosis appear, forming either as a result of ulcer scarring, or as a result of a hyperplastic process, or as a result of a pyloric abscess, or due to the extension of the process to the pylorus from caseous glands fused with it. In tuberculous ulcer of the stomach and in tuberculous pyloric stenosis, either a decrease in the acidity of the gastric contents or the absence of free HCl is usually observed. To determine the tuberculous character of the process, valuable service can be rendered by a trial injection of alt-tuberculin: if during the general reaction a sharp exacerbation of local gastric phenomena (focal reaction) is also noted, then this indicates a tuberculous lesion of an organ lying in the epigastric region (liver, stomach, pancreas, etc.). In disease of the stomach raising the suspicion of its tuberculous character, the thoracic cavity should always be examined particularly thoroughly. On the other hand, in the presence of pulmonary tuberculosis, dyspeptic phenomena on the part of the stomach and even signs of gastric ulcer do not yet give the right to diagnose gastric tuberculosis, since in pulmonary tuberculosis, especially in later stages, dyspeptic phenomena due to accompanying gastritis are observed very frequently; the combination of pulmonary tuberculosis and a simple ulcer is also a frequent phenomenon. Since tuberculous processes in the stomach can spontaneously scar over, the prognosis depends not so much on the local process in the stomach as on the nature of the pulmonary process and the general condition of the patient. Tuberculin therapy is indicated provided there are indications on the part of the lungs. If there is a fibrous process in the lungs, such therapy yields good results both with respect to the lungs and with respect to the stomach. In pyloric stenosis, surgical intervention is indicated. Climatotherapy and other measures recommended in tuberculosis in general are also beneficial in tuberculosis of the stomach, although it must not be forgotten that dyspeptic phenomena make it difficult to carry out forced feeding. XI. Syphilis of the stomach. Syphilis of the stomach compared to syphilitic lesions of other internal organs (aorta, liver, etc.) is rare. Chiari in autopsy material of 343 syphilitics found syphilis of the stomach 2 times, Stolper in 61 autopsies of syphilitics 1 time, and Gmelin in general autopsy material in 10,000 cases 2 times. In the clinic of internal diseases, the diagnosis of gastric syphilis is made considerably more often than by pathologists at autopsies, since clinicians not infrequently attribute various functional disorders of gastric activity in syphilitics—having no specific pathologico-anatomical basis—to gastric syphilis; such non-specific phenomena on the part of the stomach in syphilitics may yield to specific therapy; they find an explanation in the histological studies of Rudnev, who discovered specific changes in the stomach in the early period of syphilis. Already during the early secondary period of syphilis, pathological phenomena on the part of the stomach are frequent, and the study of gastric juice in the majority of cases reveals a more or less decreased secretory activity of the stomach (Neugebauer, Luria). Under specific treatment, this specific early process passes just like all other phenomena. During the tertiary period, more definite changes on the part of the stomach are already encountered, wherein Hausmann pathologico-anatomically distinguishes: 1) chronic syphilitic gastritis; 2) gummata in the form of flat plaques of varying size (from a pea to the size of a palm) consisting of a gummatous infiltrate of the mucosa, subsequently extending to the submucosa; sometimes in cases of old syphilis, infiltration begins in the submucosa and extends to the mucosa; 3) syphilitic ulcer on the basis of a disintegrated gummatous plaque (Fig. 37); the base of the ulcer consists of sclerosed submucosal tissue; a syphilitic ulcer can scar over or perforate; in case of adhesion, a callous-altered ulcer can penetrate into a neighboring organ with which the stomach is fused (Hausmann)—ulcus callosum penetrans; 4) scars, usually of a stellate shape, formed either on the basis of an ulcer or by direct sclerosis of a gummatous plaque; 5) diffuse gummatous infiltrate, or hyperplastic...
Figure 37. Multiple gummatous ulcers of the stomach. (After Frankel.)
plastic form of syphilis of the stomach involving the mucosa, muscular layer, and mainly the submucosa, sometimes reaching a thickness of one or more centimeters (linitis plastica). This process involves either the entire stomach or only the prepyloric part and the pylorus. Subsequently, cirrhotic shrinking of the stomach occurs (microgastria). In the stage of scarring and complete shrinking, their syphilitic nature is histologically difficult to prove. Endophlebitis and endarteritis are also observed in non-specific chronic inflammation and are by no means characteristic of specific inflammation, as was previously thought. The symptomatology of syphilis of the stomach has nothing characteristic of syphilis and depends 1) on the form of syphilis, 2) on the localization of the process. Sometimes there are phenomena of an ulcer of the stomach—either of the body or of the pylorus; in the latter case, the phenomena of stenosis come to the foreground. Bloody vomiting also occurs, but it is not yet proof of a syphilitic ulcer of the stomach, since it can also occur with syphilitic cirrhosis of the liver and with syphilitic lesion of the mediastinum. Pain is inconstant. The cause of pain is most frequently syphilitic stenosis and perigastritis. Pain is either prolonged or appears only after eating. Characteristic of all types of syphilis of the stomach is a decrease in the secretion of the stomach down to achylia (Hausmann). As for palpation, a gumma of the stomach is usually not palpable. Syphilitic lesions of the stomach create the impression of a tumor in the following cases: 1) when dense adhesions to neighboring parts have formed at the site of the syphilitic ulcer, and especially when a callous syphilitic ulcer penetrates into a neighboring organ; 2) when there is a hyperplastic form of syphilis of the stomach—sometimes the entire stomach is palpable in the form of a large elastic balloon resembling a pregnant uterus. The shrunken stomach, lying high in the epigastric region, is palpable by means of deep palpation in the form of a dense cord lying closer to the xiphoid process. In palpation diagnosis, one must bear in mind that a retroperitoneal gummatous tumor can easily be confused with a tumor of the stomach. If the retroperitoneal tumor lies behind the stomach, the greater curvature, mobile during respiration, is palpable on the tumor; if the retroperitoneal tumor lies below the stomach, the curvature is palpable above the tumor; if the tumor lies above the stomach, the curvature is palpable below the tumor. Inflation of the stomach in doubtful cases sometimes also answers the question of whether the tumor belongs to the stomach or not. In recognizing syphilis of the stomach, one proceeds from the premise that with normal or increased acidity, one is hardly dealing with syphilis of the stomach. First, an attempt is made to establish the presence of stenosis, the tumor is palpated and localized (gastric or extragastric tumor, tumor of the body of the stomach or pylorus), and only then is the question of the possible etiological role of syphilis raised. Personal and family history, and the Wassermann reaction, can serve as an auxiliary element of diagnostics, while it must be remembered that both the history and the Wassermann reaction may be absent, as is generally the case in visceral lues. Strictly speaking, gastric phenomena of any kind caused by neurolues of the vegetative nerves (Mogilnitsky, Luria), which can cause either hypersecretion, hyposecretion, gastrospastic, or gastrotonic states, or, by disrupting trophics, erosions and simple ulcers and hemorrhages (Lenzmann), must be distinguished from syphilis of the stomach. Therapy for syphilis of the stomach should be combined. Along with iodine, treatment with arsenic preparations, mercury, and bismuth should be prescribed. F. Hausmann. XII. Parasites of the stomach. The human stomach is a stage through which various parasites penetrate the digestive tract. Cysts of the dysenteric amoeba and Ascaris eggs pass through the stomach without opening. Conversely, trichina capsules, the shell of encysted cercariae of flukes, and the eggs of some worms (e.g., the pork tapeworm Taenic solium) open under the action of gastric juice. Parasites are encountered in the stomach itself as an exception. Giardia (Giardia intestinalis) have been found in the stomach in the presence of a cancerous tumor in it. The opening of an amoebic liver abscess into the stomach is possible. Among parasitic worms, cases of atypical localization of Ascaris in the stomach are known. The fluke Fasciolopsis can live in the human stomach, which has been established experimentally. Larvae of various flies can live in the human stomach as false parasites. Cheese mites (Tyroglyphus siro) can cause gastric catarrh. It is claimed that there have been cases of slugs coming out with vomit.
GASTRIC JUICE
166 logie innerer Krankheiten, herausgegeben von F. Kraus u. Th. Brugsch, B. V, T. 1, B.-Wien, 1921 (lit.). Anatomy and Physiology.—Babkin B., External Secretion of the Digestive Glands, M.-L., 1927; Batuev N., Varieties of the Form of the Human Stomach in Connection with its Development, Structure, Function, and Position, Rus. vrach, 1913, no. 27-28; Deshin A., On the Question of the Diversity of Forms of the Human Stomach, Byul. Mosk. ob-va ispytateley prirody, Novaya seriya, v. XXXII, v. 1-2, 1923-24; London E., Physiology and Pathology of Digestion, M.-P., 1924; Pavlov I., Lectures on the Work of the Principal Digestive Glands, L., 1924; Alvarez W., The mechanics of the digestive tract, N. Y., 1928; Cannon W., The mechanical factors of digestion, L., 1911; Handbuch der normalen u. pathologischen Physiologie, hrsg. v. A. Bethe, G. Bergmann u. a., B. III, B., 1927; Heidenhain R., Absonderungsvorgange im Magen (Hndb. der Physiologie, hrsg. v. L. Hermann, B. V, Lpz., 1880; Russian edition - Petersburg, 1886). Research Methods.—Gorshkov M., The Permanent Thin Probe as a Method of Investigating Human Gastric Activity, Arkh. klin. i eksp. med., 1922, no. 1; Gurevich G., A New Method for Obtaining Gastric Juice in Humans, diss., SPb, 1903; Den O., Fundamentals of Roentgenology, L., 1928; Zimnitsky S., On Disorders of the Secretory Activity of the Gastric Glands from the Standpoint of Functional Diagnostics, M., 1926; Levin A., On the Methodology of Functional Investigation of the Stomach, Terapeuticheskiy arkhiv, v. V, issue 2, 1927; Leporsky N., On a New Test Breakfast, Sib. med. zhurnal, 1922, no. 7-8; Pletnev D., X-ray Diagnostics of the Organs of Respiration, Circulation, and Digestion, M.-L., 1926; Strazhesko N., Fundamentals of Physical Diagnostics of Abdominal Cavity Diseases, Odessa, 1924; Luria R. und Mogilewsky E., Neue Beitrage zur Magenchromoskopie, Arch. f. Verdauungskrankheiten, B. XLIV, 1928; Schlesinger E., Die Rontgendiagnostik der Magendarmkrankheiten, B., 1927; Stierlin E., Klinische Rontgendiagnostik des Verdauungskanals, B., 1928; Retzlaff K., Methodik der funktionellen Diagnostik der Abdominalorgane (Klinische Laboratoriumstechnik, hrsg. v. Th. Brugsch u. Schittenhelm, B. III, B.-Wien, 1928). Gastroptosis.—Braitsev V., An Experiment in the Surgical Treatment of Gastroptosis, Vestnik khirurgii, v. VIII, bk. 23, 1926; Volkov M. and Delitsyn S., Pathogenesis of the Mobile Kidney, SPb, 1897; Vvedensky K., Results of the Operative Treatment of Gastroptosis, Vest. khir., v. V, bk. 14, 1925; Golubinin L., Enteroptosis, its Pathogenesis, Symptomatology, and Treatment, M., 1912; Morozova A., Gastropexy in Gastroptosis (Yubil. sbornik prof. I. Grekova, P., 1921); Faber K., Die Gastroptosenfrage, Klin. Wochenschr., 1923, no. 18; Glenard F., Les ptoses viscerales, P., 1899; Liek E., Sollen wir den Senkmagen operieren? Arch. f. klin. Chir., B. CXXXVII, 1925; Maluschew D., Uber die verschiedenen Modifikationen der Bierschen Gastroptoseoperation, Zentralbl. f. Chir., 1923, no. 2; Martin B., Behandlung der Gastroptose durch Resektion, ibid., 1925, no. 40. Ulcer and Tumors of the Stomach.—Blumenthal N., On the Question of Perforation of Ulcers of the Stomach and Duodenum, Nov. khir. arkh., v. II, bk. 2, no. 6, 1922; Bogoraz N., A New Principle in the Surgical Treatment of Gastric Ulcer, ibid., v. III, bk. 2, no. 10, 1923; Braitsev V., On the Etiology and Treatment of Round Ulcers of the Stomach and Duodenum, ibid., v. III, bk. 4, no. 12, 1923; Galperin Ya., 548 Operations on the Stomach, ibid., v. III, bk. 1, no. 9, 1923; the same, Causes of Relapses after Operations for Gastric Ulcers, ibid., v. III, bk. 2, no. 10, 1923; Hesse E., Resection of the Stomach in Ulcer, XV Congress of Russian Surgeons, M., 1922; Dobrotvorsky V., On the Question of Gastroenterostomy, diss., SPb, 1909; Martynov A., Ulcus ventriculi, XV Congress of Russian Surgeons, M., 1922; Petranevsky G., Perforated Ulcers of the Stomach and Duodenum, Vestnik khirurgii, v. XIV, bk. 42, 1928; Spasokukotsky S., Repeat Operations on the Stomach, Nov. khir. arkh., v. III, bk. 1, no. 9, 1923; Yarotsky A., Dietary Treatment of Round Ulcer of the Stomach and Duodenum, L., 1928; Bruell H., Das perforierte Magen- u. Duodenalgeschwur, Erg. d. Chir., B. XVI, 1923; Konjetzny G., Das Magenparkom, Ergebnisse der Chirurgie und Orthopadie, B. XIV, 1921; Pauchet V. et Hirchberg A., Cancer d'estomac, P., 1928; Starlinger F., Ergebnisse 25-jahriger operativer Therapie der Geschwurskrankheit des Magens und Zwolffingerdarms, Archiv f. klin. Chir., B. CXLVII, 1927. Syphilis and Tuberculosis of the Stomach.—Gausman F., On Syphilis of the Stomach, Prakt. vrach, 1912, no. 27-28; Luria R., Syphilis and the Stomach, M., 1928; Mogilnitsky B., Syphilis of the Autonomic Nervous System and the Endocrine Apparatus (Syphilis of the Nervous System, ed. by A. Abrikosov, P. Gannushkin, and M. Margulis, M.-L., 1927); Svetukhin K., On Syphilis of Internal Organs, Kharkov, 1904; Boas K., Syphilogene Erkrankungen des Magens im Lichte moderner Forschungsergebnisse, Zentralbl. f. Haut- u. Geschlechtskrankheiten, B. XIII, 1924.
Related articles
Mentioned in
Cite this page
“Stomach.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/stomach/