Median Nerve
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
Detailed overview of the median nerve from the 1st edition of the Soviet Great Medical Encyclopedia, covering its anatomy, clinical pathology, paralysis, sensory disorders, and surgical exposure techniques.
Encyclopedia article (1928–1936)
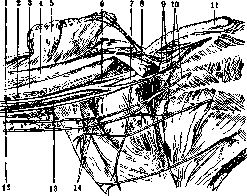
MEDIANUS NERVUS, the median nerve, is one of the main nerves of the upper extremity; functionally it belongs to the mixed nerves. The median nerve is formed in the axillary fossa from the brachial plexus (plexus brachialis), from which it originates by two roots: an outer, lateral root originating from the fifth and sixth cervical spinal nerves, and an inner, medial root originating from the eighth cervical and first thoracic spinal nerve; thus the median nerve corresponds to the sixth, seventh, eighth cervical, and first thoracic segments. The roots of the median nerve surround the axillary artery—one from above, the other from below—and unite at an acute angle on its anterior surface; after joining, the nerve lies on the outer side of the artery and descends with it along the inner margin of the biceps muscle (Figure 1). Gradually curving around the artery from the outside inward and crossing it at the middle of the arm, in the lower half of the arm the median nerve (Figure 2) already lies on the inner side of the artery, and at the elbow crease it is located one finger's breadth medial to the artery. These relationships, however, are inconstant (see Axillary fossa). Along the course of the arm, the median nerve gives off no branches. Deep in the elbow crease, the median nerve passes beneath the margin of the pronator teres muscle and extends down to the wrist along the midline of the forearm between the flexor digitorum sublimis and
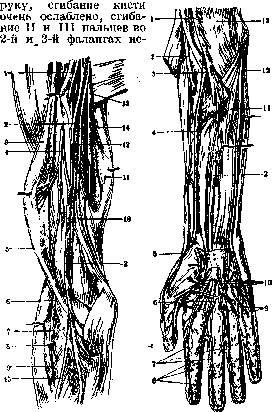
Figure 1. Position of the median nerve in the axillary fossa: 1 - median nerve; 2 - brachial artery; 3 - coracobrachialis muscle; 4 - biceps muscle (short head); 5 - pectoralis major muscle; 6 - musculocutaneous nerve; 7 - axillary artery; 8 - pectoralis minor muscle; 9 - anterior thoracic nerves; 10 - intercostobrachial nerves; 11 - clavicle; 12 - ulnar nerve; 13 - medial antibrachial cutaneous nerve; 14 - medial brachial cutaneous nerve. flexor digitorum profundus; on the forearm it gives numerous branches to all flexors except for the head of the flexor digitorum profundus closest to the ulna and the flexor carpi ulnaris (see below). After passing (together with the tendons of the digital flexor muscles) beneath the transverse carpal ligament, the median nerve divides into 4 branches: the outer one innervates the muscles of the thenar eminence (except for the deep head of the flexor pollicis brevis and the adductor pollicis) and the skin of the radial margin of the thumb; the other three—the common palmar digital nerves—having supplied the skin of the radial half of the palm and two lumbrical muscles, run to the spaces of the first three fingers, at the base of which each divides into two branchlets (proper palmar digital nerves) located along the margins of the fingers and innervating the skin of the facing surfaces of the first, second, third, and fourth fingers (Figure 3). The median nerve gives off branchlets to joints, bones, periosteum, and vessels; along its path it anastomoses with the musculocutaneous nerve in the region of the arm, and on the palm with the ulnar and radial nerves. Regarding the function of the median nerve, see Human nerves; regarding the function of the muscles it innervates, see Human muscles. Pathology. The etiological factors causing disease of the median nerve are diverse: trauma (contusions, various wounds, ruptures), pressure (e.g., tumors), other mechanical causes producing muscle overstrain, or frequent and repeated pressure on the nerve (most often in the palm region) in certain occupations (locksmiths, turners, tanners, tailors, ironers, lace-makers, dentists, etc.). Infections and intoxications can cause inflammation of the median nerve and neuralgia; neuritis may be isolated or concurrent with involvement of other nerves. For pathological anatomy and pathogenesis, see Neuritis, Polyneuritis. Diseases of the median nerve are accompanied by flaccid paralysis or paresis (depending on the intensity of the process) of the muscles it innervates (see Human nerves) with altered electrical excitability, sensory disorders, and vegetative phenomena (trophic and vasomotor). Paralysis of the muscles innervated by the median nerve causes movement disorders and a characteristic hand posture. Among movements, pronation, flexion of the hand, movement of the thumb, and of the second and third phalanges of the second and third fingers of the hand are impaired. The intensity and extent of the paralyses depend on the localization of the process. When the median nerve is damaged in the arm region, impairment of all the above-described movements is observed: pronation is impossible,
Figure 2.
Figure 3.
Figure 2. Position of the median nerve at the level of the arm: 1 and 4 - musculocutaneous nerves; 2 - median nerve; 3 - biceps muscle; 5 - antibrachial cutaneous nerve; 6 and 13 - radial nerve; 7 - supinator muscle; 8 - deep branch of the radial nerve; 9 - superficial branch of the radial nerve; 10 and 12 - ulnar nerve; 14 - brachial artery; 15 - radial artery. Figure 3. Position of the median nerve on the forearm and hand: 1 - median nerve; 2 - radial nerve; 3 - brachial artery; 4 - radial artery; 5 - superficial branch of the radial nerve; 6 - common palmar digital artery; 7 - proper palmar digital nerves of the median nerve; 8 - nerve endings (Vater-Pacini corpuscles); 9 - common palmar digital nerves of the ulnar nerve; 10 - common palmar digital nerves of the median nerve; 11 - ulnar artery; 12 - ulnar nerve; 13 - brachialis muscle. movements of the thumb—flexion, abduction, opposition to other fingers—are impossible; flattening of the thenar eminence is observed due to atrophy of its muscles; the hand assumes a characteristic appearance—main du simie (simian hand) (Figure 4). When the median nerve is damaged in the lower parts of the forearm or on the hand, only the thenar muscles are paralyzed—emaciation of the thenar eminence is observed, along with restriction of movements of the first finger, mainly its opposition to other fingers. medianus nervus Sensory disorders are observed in the form of anesthesia, hypoesthesia, or hyperesthesia on the outer two thirds of the palm, the palmar surface of the first three fingers and the outer half of the fourth finger, and on the dorsal surface of the last two phalanges of the second and third fingers (Figure 5). Trophic disorders are manifested in the formation of pemphigus-like blisters on the palm and the eminence of the thumb, in the appearance of glossy atrophic skin, in the deformation or loss of nails, in pigmentation, sweating disorders, and cyanosis. In injury and inflammation of the median nerve, joint afflictions are also observed, most often in the form of stiffness, and sometimes ankylosis. Neuritis of the median nerve is characterized by very lively spontaneous pains, pain upon pressure on the nerve trunk and corresponding muscle masses; elbow extension and supination are very painful; cutaneous hyperesthesia or hypoesthesia and trophic disorders are present, especially concerning the nails; paralysis of the corresponding muscles, flexion contracture
of the fingers ("griffe du median").
Very frequently in diseases of the median nerve, causalgias are observed (see), which is explained by its abundance of sympathetic fibers and connections with the arterial system and perivascular sheaths. Often, paralysis of the median nerve is combined with paralysis of the ulnar nerve. Diagnosis of median nerve diseases presents no difficulties; one must rule out primarily progressive spinal muscular atrophy (involvement of both hands without sensory disturbances), syringomyelia, and amyotrophic lateral sclerosis. Loss of working capacity upon lesion of the median nerve at the arm is equal to 45% (according to Tinel), 15–20% upon injury of the forearm or hand; the right side increases disability, as does the presence of causalgia. Prophylaxis relates mainly to the prevention of median nerve diseases from occupational hazards. Depending on the severity of the case or the conditions of work impact on the median nerve, a change of profession or temporary suspension of work is recommended; in other cases, modification of work methods or the introduction of new production technology is possible. Treatment is predominantly causal and includes rest; electrical stimulation, ionization, warm hand baths, massage with passive and active exercises, and later resistive gymnastics are used. In sprains, bone fractures, and nerve injuries, treatment is surgical and surgical-orthopedic. Operative technique. The median nerve can be exposed in the axillary fossa, the middle third of the arm, the elbow crease, the upper third of the forearm, and at the level of the wrist. In the first case, the upper extremity is abducted at an obtuse angle; an incision is made along the edge of the pectoralis major protrusion from the apex of the fossa to the angle formed by the pectoralis major with the inner surface of the arm; after incision of the skin and subcutaneous tissue, the sheath of the coracobrachialis muscle is incised; retracting the muscle upward, the aponeurosis is opened; the sheath of the vascular-nerve bundle discovered is opened by blunt dissection: the nerve exposed anterior to the others is the median nerve. In the middle third of the arm, the median nerve is exposed along a line running from the apex of the axillary fossa to the middle of the elbow crease, by a 5 cm long incision of the skin and subcutaneous tissue; then the aponeurosis of the biceps muscle is incised, retracting it outward with a blunt hook; the second aponeurosis beneath the biceps muscle is opened, and the median nerve is discovered. Exposure of the median nerve in the elbow crease is performed along its middle by a perpendicular vertical
Figure 5. Variations of the area of sensory impairment to light touch in complete injury of the median nerve. Anesthesia is shaded in black, hypoesthesia with dots. (After Head.)

with an incision of 5-8 cm: after incising the skin and subcutaneous tissue, the skin veins are ligated and the aponeurosis is incised with a grooved probe, beneath which the vessels are exposed: 1 cm medial to them is the median nerve. In the upper third of the forearm after an incision of the skin and subcutaneous tissue 5-8 cm long from the middle of the elbow crease along the middle of the anterior surface of the forearm, the aponeurosis of m. pronator teres and m. palmaris longus is incised; the latter is retracted medially - in the anterior angle of the wound the median nerve is found, lying deeply. When exposing the median nerve at the wrist, a vertical incision of the skin and subcutaneous tissue 3-4 cm is made medial to the tendon of m. palmaris longus for several cm, incising the aponeurosis of the latter; then another aponeurosis is incised medially as well and the median nerve is exposed
MEDK.4
Related articles
Mentioned in
Cite this page
“Median Nerve.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/median-nerve/