Nerves
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This historical encyclopedia article from the 1930s details the anatomy, physiology, and pathology of peripheral nerves, covering their structural composition, classification into cerebrospinal and autonomic types, and various forms of trauma and inflammation.
Encyclopedia article (1928–1936)
NERVES, the peripheral part of the nervous system, conducting impulses from the central nervous system to the periphery and back; they are located outside the craniospinal canal and diverge in the form of cords to all parts of the head, trunk, and extremities. They are divided into cerebrospinal and autonomic; the former are white in color due to the presence of myelin, while the autonomic are devoid of myelin and have a gray color. The shape of the nerves is in most cases cylindrical; large nerves are mostly flattened. The thickness of the nerves varies, the diameter ranges from 0.8 mm to 8 mm and depends not only on the number of nerve fibers making up the nerve, but also on the thickness of the connective tissue sheaths. The density of nerves averages 1.037 (1.014-1.052); unmyelinated fibers are denser (1.040) than myelinated ones (1.028). The tensile strength of nerves upon stretching is very great (in terms of resistance among tissues, nerves occupy third place). The coefficient of resistance (i.e., the force required to tear a nerve) averages 1.351 kg for a nerve with a diameter of 1 mm. The coefficient of resistance of the sciatic nerve is 80 kg, the median nerve 30 kg, the facial nerve 5-6 kg. Nerves are divided into cranial (12 pairs) and spinal (31 pairs). The former originate or terminate in the brainstem (see respective nerves), the latter in the spinal cord. The latter are formed by two functionally distinct roots—the anterior, containing centrifugal or motor fibers, and the posterior, through which centripetal or sensory fibers pass (see Spinal cord); upon it lies an enlargement—the spinal ganglion (ganglion spinale); laterally from the ganglion, both roots join together and form a single common trunk—a mixed nerve, lat. n. spinalis, french n. mixte (Figure 1). Sympathetic fibers from the sympathetic trunk enter the mixed nerve; this nerve is very short and divides into two mixed branches—ramus anterior and ramus posterior. The posterior branches are thinner branches and in turn divide into medial and lateral branches, which innervate the skin and muscles of the posterior surface of the trunk from the occiput to the coccyx. The anterior branches of all cervical nerves, the upper two thoracic, the 12th thoracic, all lumbar, sacral, and coccygeal form plexuses, i.e., their trunks connect with each other in the form of triangular loops, and from these connections are formed the peripheral nerves which innervate the muscles and skin of the neck, chest, abdomen, upper and lower extremities, and perineum. The anterior branches of the thoracic nerves or intercostal nerves do not participate in the formation of plexuses, but terminate in the skin and muscles of the ribs and the anterior surface of the trunk.
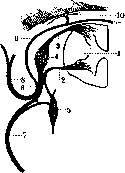
Figure 1. Formation of a mixed peripheral nerve: 1 - spinal cord; 2 - anterior root thereof; 3 - posterior root; 4 - spinal ganglion; 5 - sympathetic ganglion; 6 - mixed peripheral nerve; 7 - anterior branch thereof; 8 - posterior branch thereof; 9 - ramus meningeus; 10 - dura mater; 11 - vertebra. intercostal nerves do not participate in the formation of plexuses, but terminate in the skin and muscles of the ribs and the anterior surface of the trunk. Nerves emerging from the plexuses are located some deeply, others superficially; they run in a straight, most direct path between the centers and the corresponding organs, resembling the course of fibers in an embryo, in which nerves from the medullary tube run to the nearest myomere. Superficial nerves run together with veins in the subcutaneous fatty tissue; deep nerves run between muscle layers together with vessels, forming a neurovascular bundle surrounded by loose tissue, from which septa depart inward, separating nerves from vessels. In the neurovascular bundle, the nerve occupies a superficial position; on the extremities, it is placed more outwardly in relation to the axis of the extremity. Along their path, nerves exchange anastomoses; these anastomoses can be simple, single, or complex, multiple; they can be reduced to three types: 1) simple anastomosis, when part of the fibers of one nerve passes into another; 2) double, when two nerves exchange part of their fibers; 3) complete anastomosis, or cross. In addition, anastomoses can be recurrent, when fibers from one nerve, having entered another, run in an ascending direction; finally, there are also false anastomoses, when fibers leave a nerve for a short interval and return to it completely again. Gradually toward the periphery, nerves become depleted due to the fact that they give off collaterals for the innervation of surrounding formations—skin, muscles, ligaments, tendons, bones, etc. At their termination, nerves divide into several branches, which, after very rich anastomosis with surrounding nerves, terminate in the corresponding vasa nervorum (see Fascia). The veins of the nerve have the same arrangement as the arteries, but for each artery, there is only one vein. Lymphatic vessels in the form of separate channels are found only in the perifascicular tissue, never penetrate inside the nerve, and do not communicate with the subarachnoid space. Nervi nervorum for the most part belong to vasomotor nerves (unmyelinated), they are distributed in the neurilemma; these nerves accompany the arteries of the nerve, forming plexuses around them; besides these fibers, there is a small number of myelinated nerve fibers which probably belong to sensory fibers and terminate in the endoneurium. Most nerves are mixed; they include motor, sensory, and autonomic fibers; there are nerves that are exclusively sensory, while exclusively motor nerves are very few. The trophic center for motor fibers is served by cells of the anterior horns of the spinal cord and the motor nuclei of the medulla oblongata; the trophic center of sensory fibers is served by cells of the intervertebral ganglia. Each nerve always innervates the same skin territory and the same muscle groups; if the nerve is mixed, the skin surface innervated by it covers the muscle group which is innervated by the same nerve. Due to numerous anastomoses between nerves, it is difficult to precisely demarcate the area in the skin innervated by one or another nerve; in addition, it should be noted that many places in the skin are innervated not only by one main trunk of some nerve, but also by branches of nerves adjacent to it. This collateral innervation is revealed upon the loss of innervation from the main trunk—the insensate area of the skin is very insignificant in comparison with what one might expect from the distribution in the skin of the given nerve (see Sensitivity). Some muscles also receive innervation from many nerves, but within the muscle itself, some part is innervated by only one nerve. (General physiology of the nerve fiber—see Nervous system, Nerve fibers, Nerve cells.) Autonomic fibers are part of even the smallest cerebrospinal nerve and together with its branches penetrate into all tissues and formations. To internal organs, autonomic nerves run in isolation (see Autonomic nervous system). Pathology. Among pathological processes affecting nerves, one can note: traumatic injuries of nerves, inflammation—neuritis (see), and tumors. Inflammatory processes affect either a single nerve—neuritis (see) or many simultaneously—polyneuritis (see). Neoplasms of peripheral nerves can be divided into 3 categories: neoplasms that have spread to the nerve from surrounding tissues; they can be of various origins—sarcomatous, cancerous; metastases from other organs into nerves are very rare.
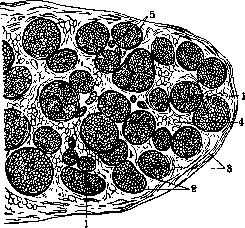
Figure 2. Histological structure of a peripheral nerve: 1 - endoneurium; 2 - perineurium; 3 - epineurium; 4 - adipose tissue; 5 - vessels.
ing tissues by special endings (see Nerve endings). Medullated and unmedullated fibers, combined into bundles, take part in the formation of nerve trunks. Usually, a nerve trunk consists of numerous separate nerve bundles and is clothed in loose connective tissue—the epineurium (Fig. 2), from which layers extend between the individual nerve bundles (perineurium); from the perineurium, connective-tissue septa (endoneurium) extend into the thickness of the bundle, dividing the bundle into finer bundles; from it, a tiny collagenous fiber goes to each nerve fiber, running along the nerve fiber and forming the sheath of Key-Retzius. Very small nerves have only one bundle of nerve fibers. When the trunk breaks up into bundles, the epineurium disappears, the perineurium thins out, and around the thinnest bundles there remains a thin membrane clad with flat endothelial cells, the so-called Henle's sheath. Bundles of nerve fibers in nerves do not remain isolated from one another, but exchange anastomoses; thus, plexuses are formed within the nerve itself, thanks to which there is no isolated conduction along a single bundle, but the entire nerve takes part in it. On a cross section, it can be seen that the caliber of the fibers entering the nerve is uneven; there are large fibers and very small ones; throughout the course of the nerve, the distribution of these fibers is uneven, changing depending on the height of the section (histological structure of nerves—see Nerve fibers). A nerve is very rich in vessels, which it receives from surrounding arteries; large vessels lie first in the epineurium, then divide several times and penetrate into the peri- * Tables of "Human Nerves" (alphabetical list indicating origin, topography, function, etc.)—see Volume XXI. are rare. Belonging to the second category are tumors peculiar only to nervous tissue: neuroma, neuroglioma, neuromyxoma (see); finally, multiple tumors of cutaneous nerves are encountered—neurofibromas (see), the source of which is the sheath of the nerve fiber and which, by the totality of clinical phenomena, form a special disease—multiple neurofibromatosis, or Recklinghausen's disease (see Neurofibromatosis). Sometimes neurofibromas form large local tumors outwardly resembling plexuses, neurofibroma plexiforme, or reticular neuroma. One of the first signs of nerve involvement in a tumor is very severe pain along the tract of the nerve; subsequently, anesthesia, paresis, or paralysis with degenerative muscle atrophy in the region of the affected nerve sets in, yielding a picture identical to that of nerve transection. Treatment is exclusively surgical. Nerves may also participate in a special general disease—lipomatosis dolorosa, or Dercum's disease (see). Anatomically, neuritis of the terminal branches is observed in this condition. Traumatic nerve injuries. The mechanism of nerve injury can be very diverse: 1) one of the most frequent forms of nerve trauma is their compression (pinching of the trunk through the skin by a foreign body during sleep, by a bandage during surgery, etc., at fractures by a displaced bone or its callus, by fibrous adhesions, or by a tumor growing from neighboring tissues toward the nerve, etc.); 2) nerve contusion; 3) excessive stretching or traction of the nerve, observed during forceful abduction of a limb both during surgery and under accidental circumstances; 4) nerve dislocations, which are a very rare phenomenon (more frequently observed in two nerves—the ulnar and peroneal); 5) violation of nerve integrity—incision, rupture. Depending on the injury, the changes in the nerve trunk also turn out to be dissimilar. In nerve compression, the continuity of the fibers is not disrupted, but greater or lesser deep changes occur in them depending on the force and duration of compression—ranging from slight edema to complete degeneration of nerve fibers in the area of applied compression. Nerve contusion is accompanied by edema, hemorrhagic infiltrates with secondary fibrous growths inside the nerve itself, which dissociate and compress the nerve fibers. With a complete violation of nerve integrity, both of its ends either remain approximated in a simple transection or diverge at a great distance from each other, so that it is difficult to bring them together (in severe wounds with loss of soft parts); microscopically, degenerative changes occur in both segments of the nerve—secondary degeneration in the peripheral segment and retrograde in the central segment (see Wallerian degeneration, Nerve fibers, Neuritis). Regeneration phenomena are possible in nerves, occurring the faster the closer both segments are located (see Nerve fibers—regeneration). Disorders of the nervous system developing with peripheral nerve injuries encompass the motor, sensory, and vegetative spheres, but the same combination of symptoms is not present in all cases; everything depends on which fibers are more subjected to injury, as well as on the mechanism of injury. With a complete violation of the integrity of a mixed nerve, there is complete and immediate paralysis of all muscles innervated by the damaged nerve, the reaction of degeneration in the paralyzed muscles, their gradual atrophy, decreased tone, in general the so-called flaccid paralysis (see Paralysis); complete loss of all types of sensitivity in the area innervated by this nerve, more extensive in the first days and gradually narrowing in subsequent ones (due to collateral innervation and anastomoses); absence of pain upon pressure on the nerve and on the corresponding muscles; absence of paresthesia upon pressure on the nerve below the site of the lesion; extinction of tendon reflexes. Vegetative phenomena boil down to edema, cyanosis, dryness of the skin; tissue necroses are sometimes observed. When only a sensory nerve is damaged, there are sensory disorders and vegetative disorders; in trauma to a motor nerve, there are movement disorders. Nerve compression is manifested by approximately the same symptoms, but their development is more gradual, the symptoms are not so sharply expressed—there is relative preservation of muscle tone, and the reaction of degeneration is partial. Both in compression and contusion of a nerve, damage to only a part of the fibers making up the nerve trunk is possible, and the damage itself amounts not so much to a violation of the continuity of the nerve fibers as to their traumatization; therefore, a discrepancy can be observed in the degree of development of symptoms in the sphere of movement and in the sphere of sensation, just as paralysis and anesthesia may be incomplete. A nerve disease accompanied by severe pain is known under the name of neuralgia (see), and a special form of peripheral nerve injury involving the vegetative sphere is singled out under the name of causalgia (see). The further course of the disease in nerve trauma depends on the state of the nerve fibers. In those cases where the nerve trauma has not caused a violation of the continuity of the nerve fibers or where the possibility of their regeneration is not excluded, the symptoms gradually smooth out, paresthetic phenomena appear in the form of tingling and crawling sensations in the area of the diseased nerve; objective sensitivity improves, first deep, then superficial; vegetative disorders disappear, and muscle tone and movements in the paralyzed muscles appear. Conversely, the clinical picture remains persistent in those cases where, due to the nature of the trauma, regeneration phenomena are excluded. Treatment depends on the nature of the trauma: in those cases where nerve damage in itself cannot constitute an obstacle to the revival of the traumatized trunk, therapy is used that promotes a more successful course of the regeneration process and maintains muscle tone: electrization, massage, and warm baths are prescribed. In those cases where there is a cause constantly traumatizing the nerve (a tumor of neighboring tissues, bone callus, bone fragments) and preventing the regeneration of fibers, or when the ends of the nerve have diverged too far, surgical intervention is resorted to (see Nerve suture). Reduction of nerve dislocations is performed either by a bloodless method or operatively—through the formation of a channel from connective tissue or muscles.
E. Kononova. Wounds of Nerves. According to Foerster's statistics, which coincide with the data of other authors, gunshot wounds of peripheral nerves were encountered significantly more often than traumatic lesions of other origins, which constituted only 1.4% of all peripheral nerve wounds and were caused by tearing, piercing weapons, contusion by stone or earth, a kick by a hoof, fracture or dislocation, pressure from a knapsack, crutches, bone callus, etc. The total figure of traumatic injuries of peripheral nerves during previous wars (Russo-Japanese, Balkan) was determined to be from 0.75% to 3.2% of all wounds. According to the statistics of the first year of the imperialist war (Lewandowsky; 1914), their number is estimated at 1.5% of all wounds. Marburg (Marburg; 1916) determines them already at 4%. Authors explain the increasing frequency of these injuries by the end of the war by the increase in the penetrating power of projectiles, which does not give the nerve the opportunity to deflect to the side and avoid injury. If at the beginning of the war the ratio of rifle wounds to artillery wounds was 7 : 1, then in 1918 it changed to 1 : 2.5. In addition to direct injury to the nerve, the latter can also suffer indirectly, being involved in a phlegmonous or suppurative process. It can suffer from a fragment of a developed bone or from a bone callus. The nerve can rupture above and below the direct injury, can suffer from hemorrhage, from ischemia during the ligation of an injured artery, from bone fractures, tissue inflammations, scars, etc. Some authors even to the present time attach special importance in trauma to the moment of nerve concussion (commotio) and explain by the latter the functional changes and even degeneration of the proximal segment of the nerve in cases of violation of its integrity. However, even with the visible integrity of the nerve, where the so-called "commotio" is assumed, adhesions and scars are often found inside it (Foerster), depending on hemorrhages or other circulatory disorders. In some cases, blood or lymph circulation disorders in the nerve lead to its death. According to the materials of the vast majority of authors, wounds of the radial nerve are in first place. According to Foerster's statistics, out of 3,963 cases of peripheral nerve lesions, there were 3,907 gunshot wounds. Of these, the radial nerve suffered in 936 cases, the median in 800, the ulnar in 742, the sciatic in 523, the brachial plexus in 287, the peroneal nerve in 183, the tibial in 112 cases. Strikingly frequent are lesions of the trigeminal (215 times) and facial nerves (120 times). Wounds of other nerves are calculated in tens or units. Often several nerves were wounded simultaneously, among them comparatively often the nerves of the base of the skull, such as e.g., the last 3–4 nerves of one side (syndrome of the foramen lacerum). Surgical intervention in wounds of the peripheral nerves comes down to the removal of scars both around the nerves and inside the nerve fiber itself, the suturing of the central segment of the nerve into its muscle, and the connection of both nerve segments after freshening their edges and removing scar tissue. After such re-neurotizations, function is often restored only several years later and then under the condition of persistent treatment with electrification and mechanotherapy, and the faster, the shorter the path from the interrupted nerve to the muscle. Thus, according to Foerster, after the suture of the radial nerve, the long head of the triceps muscle is restored after 3 months, the middle and lateral heads after 4 months, the long supinator after 7, the long radial extensor of the wrist after 9, the short supinator and extensor after 13, the common extensor of the fingers after 14, the long abductor muscle of the thumb after 15, the ulnar extensor of the wrist after 16, the extensors of the fingers after 19 months, and so on. In wounds of the nerve plexus, the functions of the proximal nerves are restored comparatively quickly, and extremely slowly—sometimes years later—the distal muscles. In rare cases, however, significantly less time passes before the restoration of the function of the wounded nerve. With too large a distance between the nerve segments from each other, they have to be connected by forming a bridge (see Nerve suture). What has been said about the restoration of peripheral nerves also applies to wounds of the roots, in particular to wounds of the cauda equina. With the complete death of the nerves supplying a muscle group and absolute hopelessness of functional recovery by neurotization, surgical measures remain either in the form of transplantation of muscles or tendons, or in the form of fixation of the joint in a position more favorable for function (tenodesis, arthrodesis, osteodesis). Sometimes, in wounds of the peripheral nerves, instead of paralysis of the corresponding muscles, contractures occurred (see). The latter are tonic in nature. After excision of the scar (neurolysis) in which a branch of the sensory nerve is entrapped, the contracture disappears, unless prolonged fixation has caused secondary shrinking of the tendons, muscles, and joints. In some cases, especially in predisposed individuals, a psychic fixation of the limb in a given position can also occur, which can continue even after the surgical removal of the scar causing irritation of the centripetal nerve. War wounds of the sciatic nerve produced particularly frequent contractures.
M. Kroll.
HUMAN NERVES
ciliare Bulbus oculi Glandula lacrimal. Glandula submaxillaris Glandula sublingualis Glandula parotis Glandula thyreoid. Ganglia trunci sympathici G. cervicale superius G. cervicale medium G. cervicale inferius G. stellatum G. thoracale II G. thoracale III G. thoracale IV G. thoracale V G. thoracale VI G. thoracale VII G. thoracale VIII G. thoracale IX G. thoracale X G. thoracale XI G. thoracale XII G. lumbale I G. lumbale II G. lumbale III G. lumbale IV G. lumbale V G. sacrale I
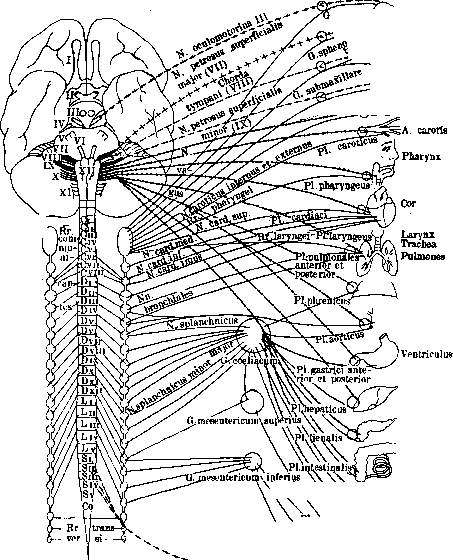
Diaphragma Aorta abdominal. Hepar Pancreas Intestinum Pl. suprarenalis suprarenalis Glandula supraren renalis Rectum Vesica urinaria Plexus pelvicanus Uterus, vagina, ovarium Figure 1. Scheme of the sympathetic and parasympathetic nervous system.
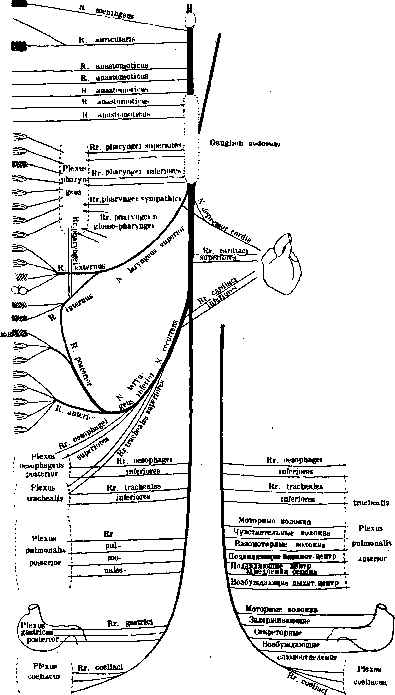
For sinus transversus and occipitalis N. auricularis n. facialis Auricle (posterior surface) and external auditory meatus (posterior-lower wall) N. glosso-pharyngeus Ganglion cervicale superius N. accessorius Ganglion cervicale superius N. hypoglossus M. levator veli palatini M. uvula Mucosa of the pharynx below velum palatinum M. constrictor pharyngis superior M. constrictor pharyngis medius M. constrictor pharyngis inferior M. palato-glossus M. palato-pharyngeus M. constrictor pharyngis inferior M. crico-thyreoideus Mucosa of the larynx (posterior wall) Thyroid gland Mucosa of the larynx above the vocal cords (Mucosa of the epiglottis and root of the tongue) Mucosa below the vocal cords M. arytaenoideus M. crico-arytaenoideus posticus M. crico-arytaenoideus lateralis M. thyreo-arytaenoideus M. vocalis M. thyreo-epiglotticus M. ary-epiglotticus Ganglion jugulare R. internus n. accessorii R. lienalis R. renalis R. suprarenalis oesophageus anterior Plexus Vagus dexter Vagus sinister Figure 2. Scheme of the vagus nerve. Threads to pia mater R. anastomoticus cum n. vago R. anastomoticus cum ramo auriculari nervi vagi R. anastomoticus cum nervo sympathico (e ganglione cervicali superiore) R. anastomoticus cum nervo faciali (r. gastrico) Rr. pharyngei (sup.) nervi vagi Plexus pharyngeus Mixed plexus on the lateral surface Ramuli tympanici Mucosa of the tympanic cavity and mastoid cells Ramus tubae in the Eustachian tube N. petrosus superficialis minor Ganglion oticum N. carotico-tympanicus superior (n. petrosus profundus minor) N. carotico-tympanicus inferior Rr. pharyngei (inf.) nervi vagi Rr. laryngo-pharyngei from ganglion cervicale superius Mucosa of the tonsils and palatine arches Mucosa of the posterior third of the tongue
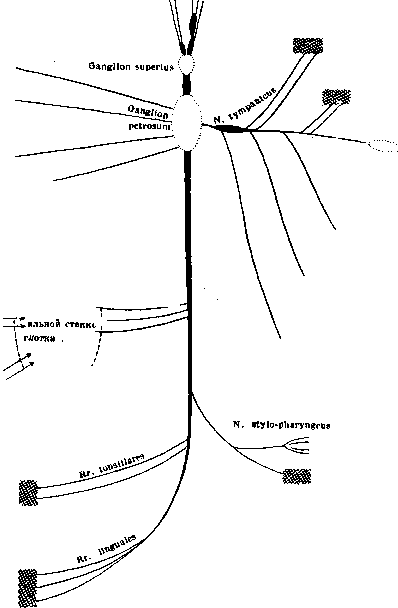
R. anastomoticus n. facialis cum plexu tympanico M. stylo-pharyngeus Mucosa around m. stylo-pharyngeus Figure 3. Scheme of the glossopharyngeal nerve. Mucous membrane of the upper and middle conchae, nasal passage, upper part of the pharynx and auditory tube Mucosa of the hard palate and gums Soft palate and uvula Mucosa of the palatine arches, tonsils, and soft palate
le. Figure 4. Diagram of the trigeminal nerve. E. t. XX. 67ft Ganglion spheno-palatinum Plexus tympanicus M. stapedius Anterior two thirds of the tongue. R. auricularis n. vagi iM. auricularis posterior M. auricularis anterior M. transversus auriculae. =^ M. obliquus auriculae M. antitragicus M. occipitalis M. digastricus (posterior belly) M. stylo-hyoideus M, orbicularis oculi M. corrugator supercilii M. frontalis M. auricularis anterior M. auricularis superior 5 M. tragicus. M. helicis. major. M. helicis minor M. orbicularis oculi M. zygomaticus .M. quadratus labii superioris M. zygomaticus M. risorius M. caninus M. buccinator Mm. incisivi M. orbicularis oris M. triangularis M. quadratus labii inferioris M. triangularis M. risorius M, mentalis. Platysma N. petrosus superficialis_Jtiaj2I-R. anastomojicu^mn^pje^^^ N. stapedius
Figure 5. Diagram of the facial nerve. M. genio-glossus M. hyo-glossus M. stylo-glossus Mm. linguae (longitudinales, verticales, transversi) M. genio-hyoideus M. omo-hyoideus M. sterno-hyoideus^i=? M. sterno-thyreoideus M. thyreo-hyoideus Skin of the retromastoid region up to the temple N. occipitalis maj. auricula-ris magnus Skin of the parotid-masseteric region anterior surface of the auricle Skin behind the ear and posterior surface of the auricle Skin of the suprahyoid region Skin of the infrahyoid region M. sterno-cleido-mastoideus Skin of the sternal end of the clavicle Skin of the upper lateral region of the chest up to the IV rib Skin of the deltoid muscle of the shoulder joint M. trapezius Pericardium Pleura Diaphragm Plexus phrenicus
32 S. v. M. levator scapulae M. rhomboideus major et minor M. serratus anterior M. subclavius M. supraspinatus M. infraspinatus Shoulder joint M. pectoralis major M. pectoralis minor M. pectoralis major M. deltoideus M. teres minor Shoulder joint
:.„>---------~p=- Skin over the posterior half of the m. deltoidei M. subscapularis M. teres major M. latissimus dorsi M. brachialis M. capsula brachii M. biceps brachii M. brachio-radialis
D i. N. intercosto-brachialis II Skin of the medial surface of the arm Elbow joint Skin of the anterior lateral surface of the forearm Skin of the radial margin of the forearm M. pronator teres M. palmaris longus M. flexor carpi radialis M. flexor carpi ulnaris M. flexor digitorum sublimis M. flexor pollicis longus M. flexor dig. profundus (radial head, ulnar head) Periosteum and bones of the forearm Vasa interossea M. pronator quadratus M. triceps (long head) M. anconaeus M. triceps (medial head) M. triceps (lateral head) of the arm and forearm brachio-radialis M. extensor carpi radialis longus M. extensor carpi radialis brevis M. supinator M. extensor carpi ulnaris ;M. extensor dig. com. M. extensor pollicis brevis -=M. extensor pollicis longus S-M. abd. pollicis longus =M. extensor indicis proprius Membrana interossea Wrist joint from the dorsal side Carpal and carpometacarpal joints Figure 7. Diagram of the brachial plexus. Skin of the lateral surface of the pelvis over m. glutaeus medius Skin over annulus inguinalis M.
transversus abdominis M.
obliquus abdominis externus M.
obliquus abdominis externus M. obliquus abdominis internus s^ M. transversus abdominis Skin over mons pubis and scrotum (labia majora) Skin of the medial surface of the thigh in its upper part M. cremaster Tunica dartos Skin of the anterior surface of the thigh Skin of the lateral surface of the thigh over m. tensor fasciae latae Skin of the medial surface of the thigh M. obturator externus M. adductor brevis M. adductor longus M. gracilis Hip joint M. adductor magnus et minimus M. pectineus Knee joint M. iliacus M. psoas major et minor Skin of the anterior surface of the thigh M. pectineus M. sartorius M. rectus femoris M. vastus medialis M. vastus intermedius M. vastus lateralis M. articularis genu; Skin of the medial side of the knee Skin of the medial surface of the leg up to the skin over the malleolus
Figure 9. Diagram of the pudendal plexus.
M. glutaeus minimus
M. glutaeus medius M. glutaeus minimus M. glutaeus medius M. tensor fasciae latae M. piriformis M. glutaeus maximus Hip joint Skin over m. glutaeus maximus Skin of the inner surface and scrotum (labia majora) Skin of the thigh posteriorly down to the popliteal fossa Hip joint M. obturator internus M. quadratus femoris Mm. gemelli M. semitendinosus M. semimembranosus M. biceps femoris (long head) M. adductor magnus Knee joint M. biceps femoris (short head) Skin of the lateral side of the leg down to the malleolus R. anastomoticus peronaeus M. peronaeus longus M. peronaeus brevis M. tibialis anticus M. extensor digitorum longus M. extensor hallucis longus Figure 10. Diagram of the sacral plexus.
Figure 11. Course of the cranial nerves inside the skull: 1 - a. carotis int.; 2 - n. trigeminus - ramus motorius; 3 - n. trigeminus - ramus sensitivus; 4 - a. cerebri post.; 5 - a. cerebelli sup.; 6 - gangl. semilunare Gasseri; 7 - aquaeductus Sylvii; 8 - ventriculus IV; 9 - a. cerebelli inf. post.; 10, 12 and 13 - n. accessorius Willisi; 11 - n. hypoglossus; 14 - n. vagus; 15 - n. glosso-pharyngeus; 16 - n. acusticus; 17 - n. intermedius Wrisbergi; 18 - n. facialis; 19 - n. trigeminus; 20 - n. mandibularis; 21 - n. ophthalmicus; 22 - n. maxillaris; 23 - n. oculomotorius; 24 - n. opticus.
Figure 12. Nerves of the orbit from the lateral side: 1 - n. frontalis; 2 - n. trochlearis; 3 - n. lacrimalis; 4 - a. carotis int.; 5 - n. ophthalmicus; 6 - n. oculomotorius; 7 - n. abducens; 8 - gangl. semilunare Gasseri; 9 - n. trigeminus - radix sensitiva; 10 - n. trigeminus - radix motoria; 11 - gangl. ciliare; 12 - n. maxillaris; 13 - m. rectus oculi inf. with its nerves; 14 - a. ophthalmica; 15 - n. opticus; 16 - nn. ciliares breves; 17 - nn. ciliares longi; 18 - n. naso-ciliaris; 19 - m. rectus oculi sup. with its nerves. Figure 13. Diagram of the cervical plexus: 1 - n. auricularis magnus; 2 - n. occipitalis minor; 3 - ramus anastomoticus for m. sterno-cleido-mastoideus; 4 - ramus anastomoticus for m. sterno-cleido-mastoideus; 5 and 8 - r. anastomoticus for m. trapezius; 6 - n. accessorius Willisi; 7 - n. subclavius; 9 - r. descendens plexus cervicalis; 10 - n. phrenicus; 11 - first branch of plexus brachialis; 12 - v. descendens n. hypoglossi; 13 - nerve for m. thyreo-hyoideus; 14 - nerve for m. genio-hyoideus; 15 and 17 - r. descendens plexus cervicalis (root); 18 - nn. for mm. scaleni; 17a - r. descendens; 18 - anastomotic fibers of ansa cervicalis, I; 19 - nerves for the anterior muscles of the neck; 20 - nerves for the anterior muscles of the neck; 21 - r. meningeus.
HUMAN NERVES
Figure 14. Nerves of the base of the brain, medulla oblongata, and cervical part of the spinal cord (ventral view): 1 - n. oculomotorius; 2 - n. trochlearis; 3 - n. abducens; 4 - n. glosso-pharyngeus; 5 - n. vagus; 6 - n. cervicalis I; 7 - gangl. cervicalis sup.; 8 - n. hypoglossus dext.; 9 - n. accessorius Willisi; 10 - n. hypoglossus sin.; 11 - n. accessorius Willisi; 12 - n. acusticus; 13 - n. intermedius Wrisbergi; 14 - n. facialis; 15 - n. trigeminus; 16 - radix sensitiva n. trigemini. (After Bourgery.)
Figure 15. Innervation of the pancreas: 1 - a. gastro-duodenalis; 2 and 7 - n. splanchnicus dext. et sin.; 3 - a. hepatica propria; 4 and 5 - n. vagus dext. et sin.; 6 - a. gastrica sin.; 8 - a. lienalis; 9 - a. pancreatico-duodenalis inf.; 10 - a. mesenterica sup.
Figure 16. Mandibular nerve with its branches: 1 - gangl. semilunare (Gasseri); 2 - n. ophthalmicus; 3 - n. canalis pterygoidei (Vidii); 4 - n. maxillaris; 5 - gangl. spheno-palatinum; 6 and 19 - n. tensoris veli palatini; 7 - r. mylo-hyoideus; 8 - gangl. submaxillare; 9 - n. lingualis; 10 - n. pterygoideus int.; 11 - n. alveolaris inf.; 12 - n. auriculo-temporalis; 13 - n. facialis; 14 - gangl. oticum; 15 - n. trigeminus - radix sensitiva; 16 and 17 - n. trigeminus - radix motoria; 18 - radix sensitiva ganglii otici; 20 - n. lingualis; 21 - n. alveolaris inf.; 22 - gangl. oticum; 23 - radix sympathica ganglii otici; 24 - nerve for m. tensor tympani; 25 - root from n. facialis and glosso-pharyngeus; 26 - gangl. semilunare (Gasseri); 27 - n. trigeminus - radix sensitiva.
Figure 17. Maxillary nerve with its branches (lateral view): 1 - nervus maxillaris; 2 - nervus ophthalmicus; 3 - ganglion semilunare Gasseri; 4 - nervus trigeminus - radix motoria; 5 - nervus trigeminus - radix sensitiva; 6 - nervus mandibularis; 7 - nervus canalis pterygoidei Vidii; 8 - ganglion spheno-palatinum; 9 - nervus palatinus posterior; 10 - nervus palatinus medius; 11 - nervus palatinus anterior; 12 - nervi alveolares superiores posteriores; 13 - nervi spheno-palatini; 14 - one of the branches of the facial nerve anastomosing with the branches of the infraorbital nerve; 15 - pes anserinus minor; 16 - ramus anastomoticus nervi zygomatici; 17 - nervus lacrimalis.
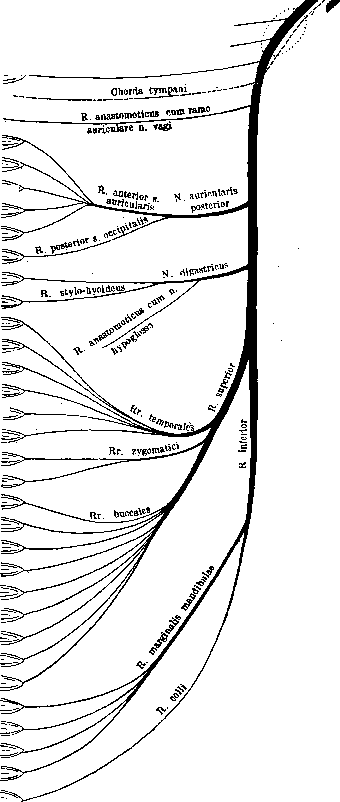
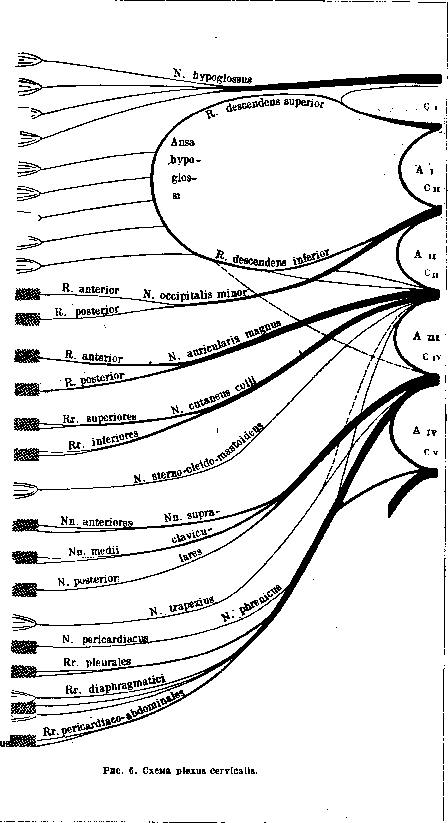
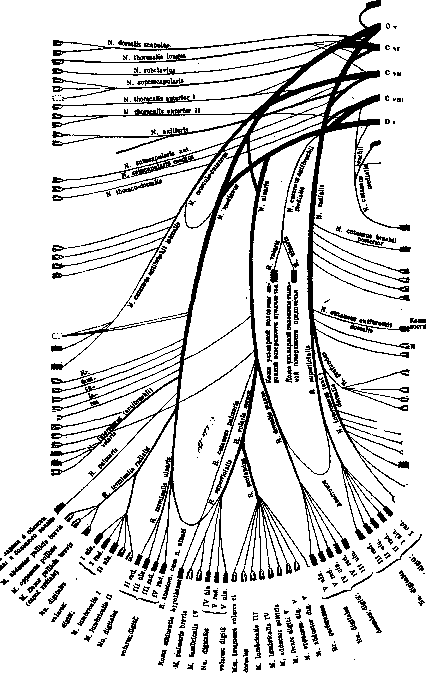
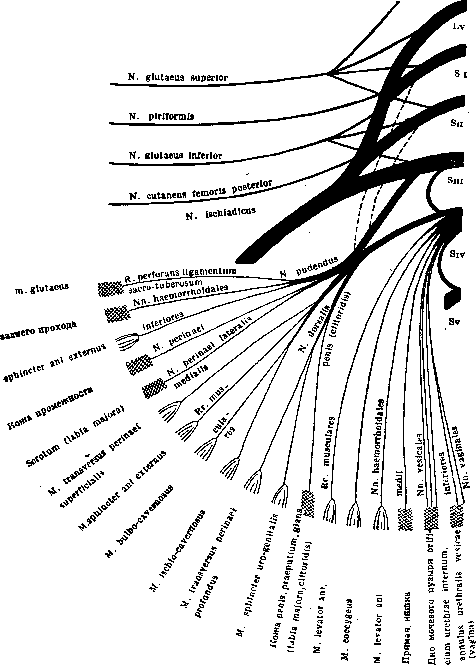
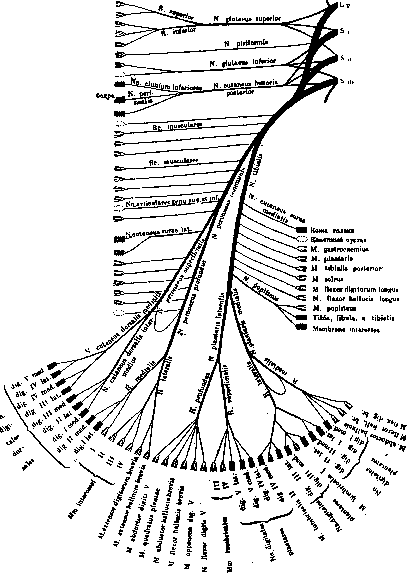
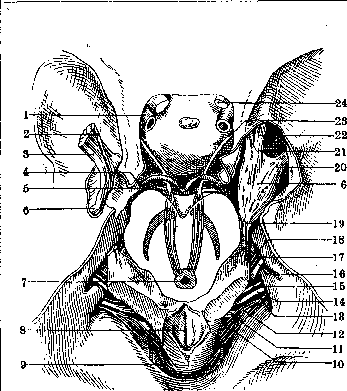
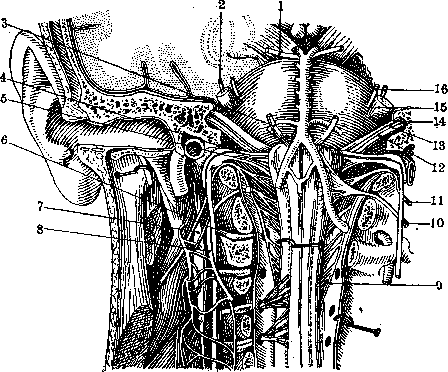
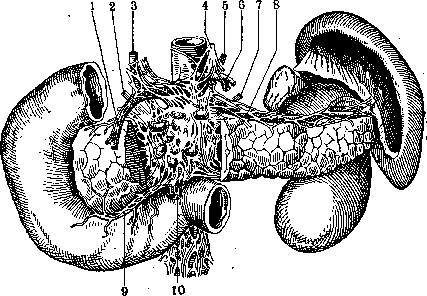
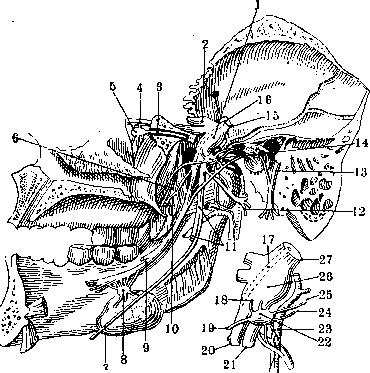
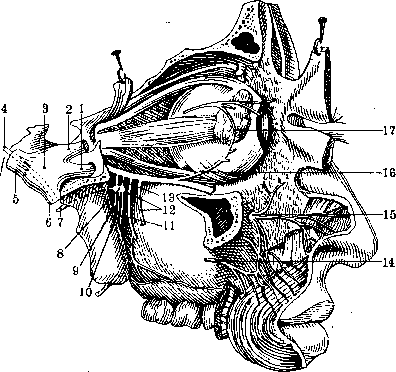
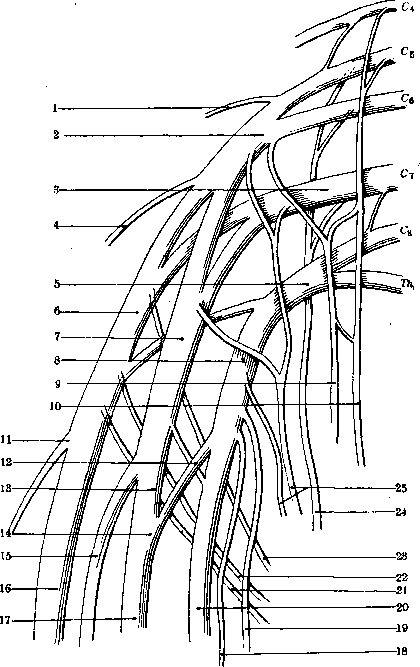
Figure 18. Scheme of the brachial plexus: 1 - n. dorsalis scapulae; 2 - fasciculus primarius sup.; 3 - fasciculus primarius medius; 4 - n. suprascapularis; 5 - fasciculus primarius inf.; 6 - fasciculus post.; 7 - fasciculus lateralis; 8 - fasciculus medialis; 9 - n. subclavius; 10 - n. phrenicus; 11 - n. axillaris; 12 - radix medialis nervi mediani; 13 - radix lateralis nervi mediani; 14 and 17 - n. medianus; 15 - n. musculo-cutaneus; 16 - n. radialis; 18 - n. cutaneus antibrachii medialis; 19 - n. cutaneus brachii int.; 20 - n. ulnaris; 21 - n. thoraco-dorsalis; 22 - n. subscapularis inf.; 23 - n. subscapularis sup.; 24 - n. thoracalis longus; 25 - nn. thoracales ant. primus and secundus; C4-C8 - IV-VIII cervical nerves; Th1 - first thoracic nerve.
Figure 19. One of the unusual forms of the brachial plexus. In this case, the ventral branch of the fifth cervical nerve does not directly connect with the sixth, and the upper primary trunk consists only of fibers of the fifth nerve; subsequently, after giving off the n. dorsalis scapulae, this nerve divides, as is normal, into two secondary trunks—posterior and lateral; the fibers of the sixth nerve also divide into two trunks and merge into the mass of the aforementioned secondary trunks. Otherwise, all other nerves do not differ from the norm. 1 - n. dorsalis scapulae; 2 - n. suprascapularis; 3 - fasciculus post.; 4 - n. axillaris; 5 - n. radialis; 6 - n. ulnaris; 7 - radix lat. nervi mediani; 8 - radix medialis nervi mediani; 9 - fasciculus medialis; 10 - fasciculus lat.; 11 - fasciculus primarius inf.; 12 - fasciculus primarius medius. Figure 20. One of the unusual forms of the brachial plexus, sharply differing from the norm. The plexus has, as always, three primary trunks, wherein the upper primary trunk presents no departures from the norm and consists of fibers of the fourth, fifth, and sixth cervical nerves; the middle primary trunk is fused from the fibers of the seventh and eighth cervical nerves and part of the fibers of the first thoracic, and finally the lower primary trunk consists only of the remaining fibers of the first thoracic nerve. As for the secondary trunks, they present the greatest departures from the norm, wherein the actual posterior secondary trunk is normal, the lateral one begins, as is normal, from both primary trunks (upper and middle), but subsequently it also takes in all fibers from the lower primary trunk; thus, the secondary medial trunk in the plexus as such does not exist; from the secondary lateral trunk there depart already all the nerves of the medial trunk. The entire plexus clearly reveals a primitive division into dorsal and ventral layers. 1 - n. dorsalis scapulae; 2 - fasciculus primarius sup.; 3 - n. suprascapularis; 4 - fasciculus post.; 5 - n. axillaris; 6 - n. radialis; 7 - n. medianus; 8 - n. ulnaris; 9 - fasciculus lat.; 10 - fasciculus primarius inf.; 11 - fasciculus primarius medius. Figure 21. One of the unusual forms of the brachial plexus. All three primary trunks and the posterior secondary trunk are formed normally, but in the formation of the medial and lateral secondary trunks a departure from the norm is observed. The lateral secondary trunk is formed only from fibers emerging from the upper primary trunk; the middle primary trunk takes no part in its formation; instead, the medial secondary trunk sends part of its fibers in the form of two bundles that merge into the median nerve; thus the latter has only one lateral root from the upper primary trunk, while the medial root from the middle primary trunk as such is absent; the middle primary trunk divides into two bundles, of which one, as is normal, passes into the dorsal secondary trunk, and the other, as a departure from the norm, passes into the medial secondary trunk; however, the latter, as indicated above, sends an anastomosis into the median nerve. 1 - n. dorsalis scapulae; 2 - fasciculus primarius sup.; 3 - fasciculus post.; 4 - n. suprascapularis; 5 - n. axillaris; 6 - n. radialis; 7 - n. medianus; 8 - n. ulnaris; 9 - radix medialis nervi mediani; 10 - radix lat. nervi mediani; 11 - fasciculus medialis; 12 - fasciculus primarius inf.; 13 - fasciculus primarius medius. (To the illustr. of the art. Nerves of man.)
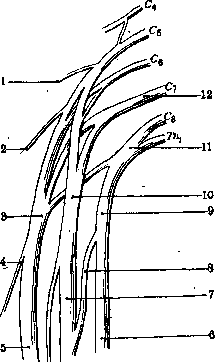
Figure 19.
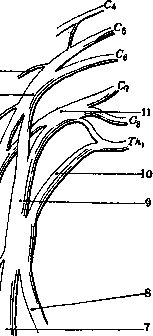
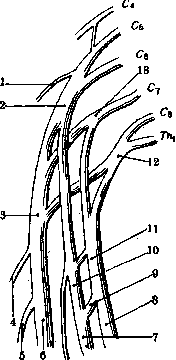
Figure 20.
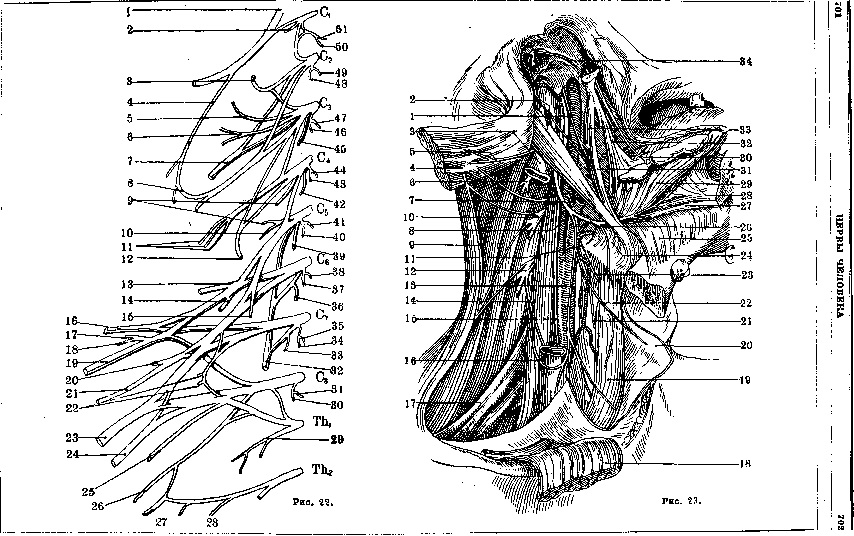
Fig. 21. Figure 22. Scheme of the right cervical and brachial plexus from the front: 1 - n. hypoglossus; 2 - branch for m. rectus capitis lat.; 3 - n. occipitalis minor; 4 - ramus descendens n. hypoglossi; 5 - n. auricularis magnus; 6 - n. cutaneus colli; 7 - branch for m. trapezius; 8 - ansa hypoglossi; 9 - branches for m. levator scapulae from n. dorsalis scapulae; 10 - branch for mm. rhomboidei from n. dorsalis scapulae; 11 - nn. supraclaviculares; 12 - n. phrenicus; 13 - n. suprascapularis; 14 - n. subscapularis; 15 - n. subclavius; 16 - n. axillaris; 17 - n. subscapularis; 18 - n. thoraco-dorsalis; 19 - n. radialis; 20 - branch for m. coraco-brachialis; 21 - n. musculo-cutaneus; 22 - nn. thoracales ant.; 23 - n. medianus; 24 - n. ulnaris; 25 - n. cutaneus antibrachii medialis; 26 - n. cutaneus brachii medialis; 27 - nn. intercosto-brachiales; 28 - n. intercostalis II; 29 - n. intercostalis I; 30 - branch for m. scalenus medius; 31, 34, 43, 46, 48 - branches for mm. intertransversarii; 32 - n. thoracalis longus; 33 - branch for m. scalenus medius; 35 - branch for m. scalenus ant.; 36 and 39 - branches for m. scalenus medius; 37 and 40 - branches for m. scalenus ant. and intertransversarius; 38 - branch for m. longus colli; 41 - branch for m. longus colli; 42 - branch for m. scalenus medius; 44 - branch for m. longus colli; 45 - branch for m. levator scapulae; 47 - branch for mm. longi capitis et colli; 49 and 50 - branches for m. longus capitis; 51 - branch for m. rectus capitis ant.; C1-C4 - plexus cervicalis; C5-Th2 - plexus brachialis. Figure 23. Lower cranial nerves in the neck: 1 - n. glosso-pharyngeus; 2 - n. facialis; 3 - v. jugularis interna; 4 - m. sterno-cleido-mastoideus; 5 - n. accessorius Willisi; 6 - n. cervicalis secundus; 7 - a. occipitalis; 8 - a. carotis int.; 9 - m. trapezius; 10 - n. cervicalis tertius; 11 - n. laryngeus superior; 12 - n. cervicalis quartus; 13 - ramus desc. n. hypoglossi; 14 - ramus desc. plexus cervicalis; 15 - n. vagus; 16 - ansa hypoglossi; 17 - plexus brachialis; 18 - m. sterno-cleido-mastoideus; 19 - m. sterno-thyreoideus; 20 - m. omo-hyoideus (venter ant.); 21 - n. laryngeus superior (ramus externus); 22 - n. musculi omo-hyoidei (venter ant.); 23 - n. laryngeus superior (ramus superior); 24 - m. hyo-glossus; 25 - m. mylo-hyoideus; 26 - n. hypoglossus; 27 - m. genio-hyoideus; 28 - m. genio-glossus; 29 - m. hyo-glossus; 30 - n. lingualis; 31 - m. stylo-hyoideus; 32 - m. stylo-glossus; 33 - m. stylo-pharyngeus; 34 - chorda tympani. (To the illustr. of the art. Nerves of man.)
M. sterno-cleido-mastoideus (n. access. + C1+2) Mm. colli and nuchae (C1-IV) M. trapezius (n. access. + C1-III) M. rhomboideus (CIII-IV) Diaphragma (CIII-IV) Mm. supra- and infraspinatus (CIV-V) M. deltoideus (CV-VI) M. biceps brachii (CV-VI) M. serratus (CV-VII) M. pectoralis (CV-VIII) M. triceps brachii (CVI-VIII) M. brachialis (CV-VI) Mm. extensores carpi and digitorum (CVI-VII) Centrum cilio-spinale (CVIII-DII) Centrum sympathicum cordis (CVIII-DIV) M. latissimus dorsi (CVI-VIII) Mm. flexores carpi and digitorum (CVI-DII) Mm. interossei (CVIII-DI) Thenar (CVIII-DI) Mm. intercostales and dorsi (DI-XII) Mm. abdominis (DVIII-LI) Centrum sympathicum ventriculi, duodeni and jejuni (DVI-VIII) Centrum sympathicum vesicae felleae (DIX-X) Centrum sympathicum colonis (DXI-XII) Centrum sympathicum vesicae urinariae (L1) M. ilio-psoas (LI-III) M. cremaster (LII-III) M. adductor femoris (LII-IV) M. quadratus femoris (LIII-IV) M. tibialis anterior (LIV-V) Mm. gastrocnemius and soleus (LV-SII) M. tensor fasciae latae (LIV-V) Mm. glutaei (LIV-SI) M. semitendinosus (LIV-SI) M. semimembranosus (LIV-SI) M. biceps femoris (LIV-SII) Mm. extensores hallucis and digitorum (LIV-SI) Mm. peronaei (LV-SI) Mm. flexores digitorum and hallucis (LV-SII) Mm. interossei (LV-SII) Centrum erectionis, ejaculationis et defecationis (SII-V)
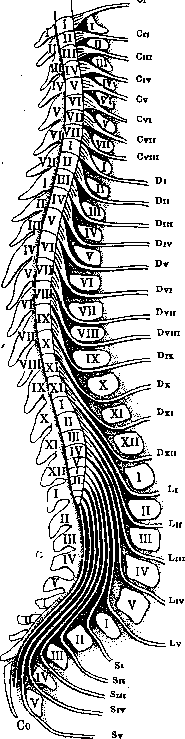
Figure 24. Scheme of the emergence of nerves from the spinal cord with indication of the place of their origin, the place of their exit through the intervertebral foramen, the height of their exit from the spinal cord in relation to the spinous processes of the vertebrae and the segmental innervation of muscles. (View from the right side.)
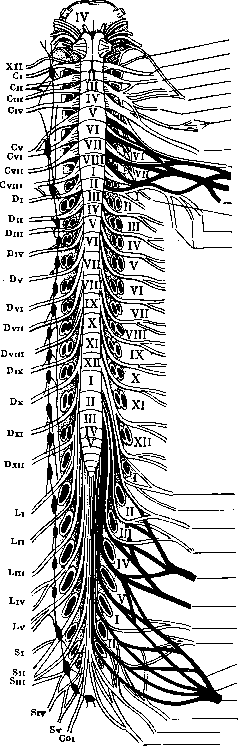
N. accessorius (XI) N. suboccipitalis (CI) N. occipitalis minor (CII-III) N. auricularis magnus (CIII) N. cutaneus colli (CIII) N. accessorius (CI-III) Nn. supraclaviculares (CIII-IV) N. phrenicus (CIII-IV) N. musculo-cutaneus (CV-VI) N. medianus (CV-DI) N. radialis (CV-DI) N. axillaris (CV-VI) N. thoracalis (CV-VI) N. ulnaris (CVIII-DI) Nn. cutanei brachii and antibrachii (CVIII-DI) Biceps reflex (CV-VI) Triceps reflex (CVI-VII) Radius reflex (CVII-VIII) Upper abdominal reflex (DV III-IX) Lower abdominal reflex (DX-XII) Nn. intercostales (DI-XII) Cremasteric reflex (LII-III) Knee reflex (LII-IV) Achilles tendon reflex (LV-SII) Anal sphincter reflex (SV) N. ilio-hypogastricus (D XII-LI) N. ilio-inguinalis (LI) N. genito-femoralis (LI-II) N. cutaneus femoris lateralis (LII-III) N. femoralis (LI-IV) N. obturatorius (LII-IV) N. glutaeus superior (LIV-SI) N. glutaeus inferior (LV-SII) N. peronaeus (LIV-SII) N. tibialis (LIV-SII) N. ischiadicus (LIV-SIII) N. cutaneus femoris posterior (SI-III) Plexus pudendus Plexus coccygeus. 25. Diagram of the origin of nerves from the spinal cord, indicating the level of their origin, the place of exit through the intervertebral foramen, and the formation of peripheral nerves. (View from the ventral surface.)
7 18 1
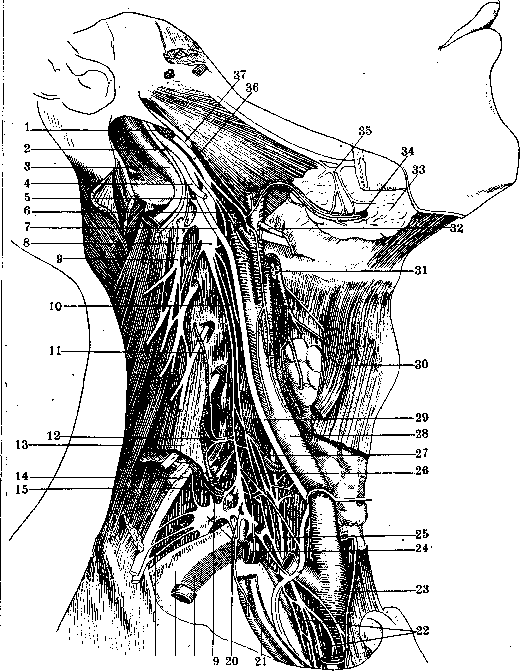
Figure 26. Sympathetic nervous system of the cervical region on the right: 1-a. carotis int.; 2-r. spinalis nervi accessorii Willisi; 3-v. jugularis int.; 4-n. hypoglossus; 5-ramus anastomoticus nervi cervicalis I cum ganglio cervicali superiori; 6-n. laryngeus sup.; 7-n. vagus; 8-gangl. cervicale sup.; 9-n. cervicalis sup.; 10-n. cardiacus sup.; 11-a. cervicalis ascendens; 12-gangl. cervicale medium; 13-m. scalenus; 14-truncus thyreo-cervicalis; 15-a. cervicalis prof.; 16-a. intercostalis suprema; 17-pleura; 18-a. subclavia; 19-n. vertebralis; 20-gangl. cervicale inf.; 21-a. et v. mammaria int.; 22-n. cardiacus inf.; 23-a. anonyma; 24-a. subclavia; 25-n. laryngeus inf.; 26-n. cardiacus medius; 27-a. thyreoidea inf.; 28-a. carotis communis; 29-n. vagus; 30-m. omo-hyoideus; 31-a. thyreoidea sup.; 32-n. hypoglossus; 33-glandula submaxillaris; 34-a. maxillaris externa; 35-gangl. submaxillare; 36-truncus sympathicus; 37-n. glosso-pharyngeus. 7 09
HUMAN NERVES
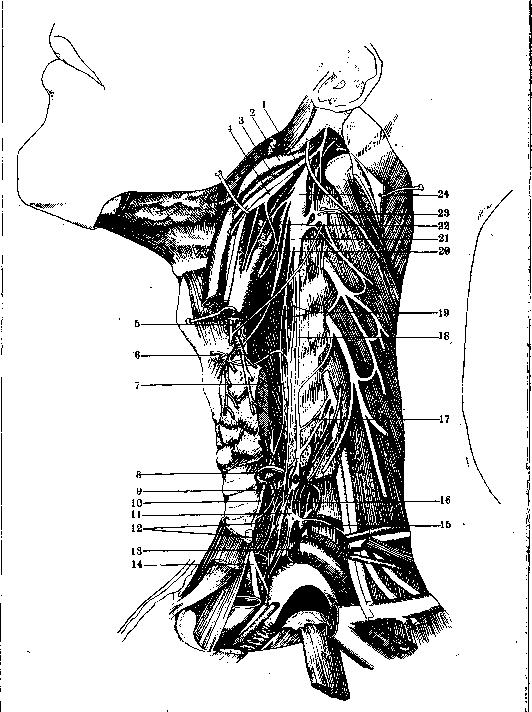
Figure 27. Sympathetic nervous system of the cervical region on the left (another form): 1-n. hypoglossus;
\ 2-v. jugularis int.; 3-a. carotis int.; 4-n. vagus; 5-m. descendens nervi hypoglossi; 6-n. thyreoideus
\ sympathicus; 7 and 9-r. anastomoticus sympathicus cum n. recur.; 8-a. thyreoidea inferior and n. thyreoideus
.4 sympathicus; 9-r. anastomoticus sympathicus recurrens; 10-n. recurrens; 11-gangl. cervicale inf.
; * praearticulare; 12-nn. cardiaci; 13-ansa Vieussenii; 14-n. vagus; 15-gangl. cervicale inf. retroarticulare
i 16-n. vertebralis; 17-r. anastomoticus V cervicalis sympathicus; 18-truncus sympathicus; 19-a.
]: cardiacus sup.; 20-n. laryngeus sup.; 21-r. sympathicus ad n. laryngeum sup.; 22-r. sympathicus
j plexus carotici; 23-n. cervicalis secundus; 24-gangl. sympathicum sup.
1
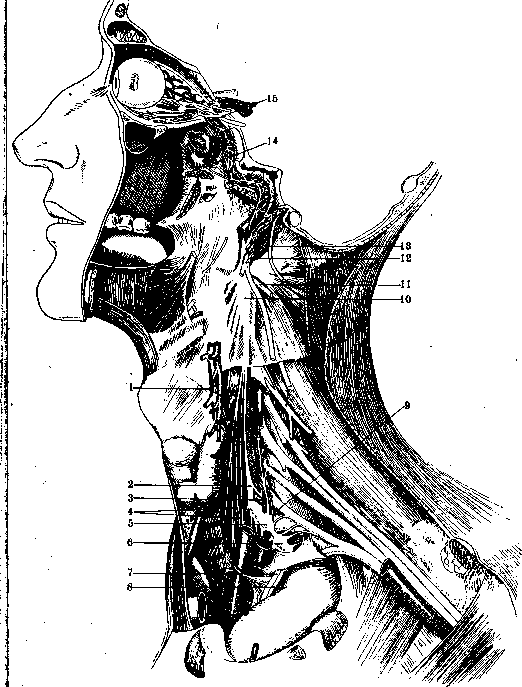
Figure 28. Sympathetic nervous system of the cervical region on the left (another form): 1-a. et v. thyreoidea superior; 2-gangl. cervicale medium; 3-a. thyreoidea inf.; 4-n. cardiacus; 5-gangl. cervicale inf.; 6-gangl. thoracale I; 7-n. vagus; 8-n. phrenicus; 9-n. vertebralis; 10-gangl. cervicale sup.; 11-n. hypoglossus; 12-n. vagus; 13-n. accessorius Willisi; 14-ramus sympathicus ganglii spheno-palatini; 15-ramus sympathicus ganglii ciliaris.
Related articles
Cite this page
“Nerves.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/nerves/