Arthritis
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
A comprehensive overview of arthritis from the 1928-1936 Soviet medical encyclopedia, covering various types including infectious, rheumatoid, and non-inflammatory forms, with emphasis on etiology, clinical manifestations, and treatment approaches of the period.
Encyclopedia article (1928–1936)
Arthritis (from Greek arthron - joint), an extensive group of diseases of the joints of inflammatory and non-inflammatory origin (the latter would more correctly be called arthroses). The phenomena of arthritis can be caused by very diverse irritants of bacterial, toxic, and chemical types; these irritants lead to certain changes in the individual elements of the joint, and it has been established that different irritants can cause the same patho-anatomical changes in the joint, which further complicates the precise classification of A. by groups. At present, it is still not possible to consider and classify A. exclusively according to the causal factor. Similarly, the patho-anatomical nomenclature does not satisfy in all cases. Therefore, it is more convenient to adhere to the classification of A. according to clinical characteristics, combining them, as far as possible, with patho-anatomical and bacteriological data. Among the numerous types of A., there are those where it is possible not only to establish with certainty the inflammatory nature of the disease, but also to determine the etiological factor. Such are, for example, gonorrheal, pneumococcal, typhoid, and paratyphoid A. The role of the gonococcus as an etiological factor in many A. of the 'rheumatoid' type was established long ago (1896 - Thayer, Blumer and later Hordes).-P nevmokokkovye A. are caused by the diplococcus of Fränkel, although cases of mixed infection with diplococcus and other pyogenic cocci have been noted. This form of A. is most often observed in childhood, proceeds relatively peacefully in the form of 'rheumatoid' (arthralgia) serous synovitis and more rarely in the form of purulent A. L e-ch e-n i e-repeated aspirations and vaccine therapy (Tasso). For severe purulent forms-arthrotomy with subsequent washing of the joint. In recent years, especially Russian authors (Kozlovsky, Novotel'nov), note the importance of pneumococcal infection in the development of tuberculosis of the joints.-A. after typhoid fever and paratyphoids are caused by the corresponding bacteria, which was established by a number of authors (Klemm, Hübener, Schneider) and confirmed by Russian scientists in recent years. Typhoid A. manifest in the form of indefinite rheumatoid-type pains in the joints (pseudorhumatisme typhique of the French), in the form of synovitis with non-purulent effusion and in the form of purulent A. with destructive changes in the articular surfaces, with subsequent dislocation or subluxation, especially frequent in the hip joint. Joint disease in connection with relapsing and typhus fevers was also observed by Russian authors during the epidemic of 1919-23. Non-purulent A. proceed favorably, without giving serious complications. The main thing in such forms is the prevention of contractures and subluxations. For purulent forms, interventions applicable in general for purulent A. (aspirations followed by washing with various solutions, arthrotomies, in severe cases-resections) can be used. During the disease, it is necessary to prevent contractures and path. dislocations by traction, k-rye also have their effect in fresh path. dislocations, especially in the hip joint. In chronic cases, surgical treatment is indicated. A whole series of other acute infectious diseases also give complications in the form of A.: such are scarlatinal A., in which streptococcus is almost always found. They proceed in the form of polyarthritis, often with subsequent formation of contractures and ankylosis of many joints. Serous synovitis take a more favorable course. Relatively rare are joint diseases in measles, smallpox, diphtheria, cholera. Malleus also causes joint diseases.- Arthritis in dysentery deserve special mention. Kofoid and Swi-zi (Kofoid, Swezy) in a careful study of the resected head of the femur found amoeba cells in necrotic foci directly at the eburnated articular surface. They tend to consider this amoeba as Entamoeba dysenteriae, the combination of k-roy with chronic A. is a frequent phenomenon. It should be assumed that A., arising in connection with the disease of bacillary dysentery and proceeding more often in the form of polyarthritis, also have a specific etiology. In treatment, all types of physiotherapy in combination with orthopedic manipulations are indicated. It should be mentioned about A. in acute and chronic osteomyelitis, when the focus is localized in the metaphysis or epiphysis, and metastatic A. in septicopyemia (see). To acute lesions of the joints can be attributed their pains and swellings, which are observed as an anaphylactic phenomenon during serum treatment. A large group of chronic A. with specific etiology deserves more detailed description and is given in the corresponding sections. Such are tuberculous A. (see Tuberculosis) and syphilitic A. (see below). Mixed forms of joint damage with gonorrheal infection and syphilis and syphilitic-tuberculous A. (hybrid forms) also occur, which are carefully analyzed in the classical works of Veliaminov. Rarer A. in sporotrichosis, Madura disease deserve only mention.-Joint diseases in hemophilia do not yet have a sufficiently precise scientific explanation, just like hemophilia itself (see). Such A. manifest more often in children and adolescents in the form of hemarthrosis with a slightly thickened capsule or in the form of chronic A. with phenomena of capsule wrinkling, with a tendency to contractures and even fibrous ankylosis. The latter form can easily be confused with other types of chronic A., in particular with tuberculosis. A careful history in doubtful cases facilitates therapy, k-roya comes down exclusively to conservative measures and prevention of deformities.-A somewhat similar picture is given by A. in scurvy, which also represents one of the manifestations of hemorrhagic diathesis (see Scurvy). Among arthritis with unclear etiology, the so-called 'rheumatic' A. occupy a prominent place, k-rye can proceed in the form of polyarthritis rheumatica infectiosa acuta or in the form of polyarthritis rheumatica infectiosa chronica. For most researchers, the infectious nature of such A. is the most explainable, and many English and American authors attach great importance to the so-called focal infection ('focal infection'). However, Lindsay (Lindsay) in a very careful study of 172 cases found the supposed foci of infection only in 50%. Bassler (Bassler) in 35 cases of chronic polyarthritis out of 45 found the supposed source, in the other 10 cases no traces of infection could be established. Removal of foci in 35 patients could not stop the development of the disease. Individual researchers tend to recognize the role of non-hemolytic streptococcus in most polyarthritis. The source of focal infection is most often the tonsils, nasopharynx, root abscesses of teeth, sinusitis. Smith (Smith), studying 100 cases of polyarthritis, performed 60 abdominal operations and was convinced of the role of intestinal infection, which is also confirmed by Taylor (Taylor) on the basis of radiological studies of the intestine. Attempts by individual authors (Nichols and Richardson) to explain the clinical and pathological manifestations of such A. by incorrect metabolism (see) do not agree with the data of Ely and the very careful patho-anatomical studies of T. Fischer (T. Fischer). The small-cell infiltration, usually noted in such A., is evidence of the inflammatory process in chronic forms. Here, as a result of proliferation of the joint capsule, a layer of granulation tissue is formed, which sooner or later grows over the articular cartilage and causes its destruction. Proliferation of the perichondrium leads to the formation of new cartilage or bone at the edges. These true inflammatory changes, characterizing proliferative A., lead to partial or complete destruction of the joint with subsequent fibrous or bony ankylosis. One can share the opinion of Pemberton (Pemberton) about the influence of several factors in the development of the patho-substrate of such arthritis: various types of infection, the influence of humidity and cold, intestinal intoxication, violation of endocrine balance. One cannot also deny the importance of some constitutional predisposition to the so-called 'rheumatoid' A., which occur more often in subjects of 'visceroptotic' or hyper-onomorphic type of Bean (Bean). Acute 'rheumatic' A. usually respond to large doses of sodium salicylate (salicylic preparations in the vein, trypaflavin, collargol, etc.) and pass without leaving serious destructive changes in the joints. However, if they pass into a chronic form, the outcome is less favorable. Removal of the supposed sources of infection (tonsils, carious teeth, etc.) does not always give the desired effect and cannot be expected in advanced cases. Similarly, treatment with vaccine and non-specific protein therapy have not fully justified expectations. True, the latest data of Stockman and Campbell (Stockman, Campbell) are more encouraging. They used for intravenous injections standard typhoid vaccines in doses from 125 to 200 million, achieving a significant general reaction. In 80% of cases, there was undoubtedly improvement, in 57% the course of the disease stopped, and in some chronic cases there was a return. In k. cases, all types of physiotherapy are indicated: dry-air baths, non-irritating massage, active movements, diathermy, etc. Prevention of deformations by traction, splints, orthopedic appliances is a very important moment.
Prolonged fixation reduces blood supply to the area of the diseased joint and increases atrophy. Surgical intervention in chronic forms of rheumatic A. is also indicated. Synovectomy on the knee joint is used by a number of English and American surgeons (Swett and Jones, 1923, present a large amount of material). This operation is better applied early in order to preserve other elements of the joint. Key experimentally proved that the synovial membrane is replaced by a fibroblastic pathway without impairment of function. In the presence of significant destructive changes in the joint, resection is indicated. Arthroplasty on such joints has less success. The next large group of chronic joint diseases constitutes the so-called osteo-A. of English authors or degenerative (hypertrophic) A. of American authors. Although the etiology of this group of A. is just as unclear as the preceding group, the patho-anatomical changes and the distinctive clinical course justify considering 'osteo-A.' separately. These A. occur in patients of middle and above middle age. Climate, conditions, moments of cooling, 'colds' rarely play a role in them. The first changes in the joints, accessible to clinical and X-ray examination, are slight localized swelling of the joint, pointedness of the joint ends, bone-cartilage proliferations at the border of the cartilages. With further development of the process, the joint cartilage disappears, the eburnated bone is exposed, often of irregular shape. Changes of this kind on the fingers are called Heberden's nodes, changes in the hip joint-malum coxae senile. Similar changes are noted in the joints of the spine (see Spondylitis and Spondyloses). To this group should probably also be included the primary, chronic, deforming polyarthritis, in which the process affects the limbs more or less symmetrically, starting with the fingers of the hands (Golubov). Whether to consider such a polyarthritis as a trophoneurosis or whether it should be attributed to disorders of internal secretion-this question should for the present be considered not finally resolved. From such deforming polyarthrites one should strictly distinguish the disfigurement of joints after inflammatory processes in the joints-gonorrheal, typhoid, tuberculous, syphilitic, and others. From Fischer's point of view, osteo-A. is not a disease, but a series of pathologic and physiologic changes in the joint subjected to prolonged and repeated mechanical or toxic injuries of moderate degree. The main feature distinguishing osteo-A. from the more acute and presumably infectious 'rheumatic' A. is the almost constant absence of small-cell infiltration in osteo-A.-To the group of chronic non-inflammatory degenerative A. should also be included those forms of osteo-A. in women that coincide with the onset of the climacteric (A. of the menopause according to Cecil and Archer). The disease occurs more frequently in the knee joint, interphalangeal articulations, lumbar region of the spine in obese women of middle age. The course is slow. There is no tendency to involve other joints in the process. Treatment-regulation of nutrition, diathermy, iodine and thyroidin. Ovarian preparations usually have no effect. To the number of chronic arthritides standing in unquestionable dependence on anomalies of internal secretion should be included polyarthritis progressiva chronica thyreotoxica (Velyaminov), running in the form of polyarthritis on the basis of dysthyreosis; further-A. in hypothyroidism (Hagen-Thorn) and osteo-arthritis deformans endemica of Beck (joint diseases in metabolic diseases, see Gout).-Attention should also be drawn to a group of neuropathic A., among which arthropathia tabidorum and arthropathies in syringomyelia deserve the greatest attention (see Arthropathy).-As for traumatic A., in connection with more precise diagnosis, their circle has recently been constantly narrowing. To the number of a. traumatic should be included proper distortions and contusions with subsequent hemarthrosis (see). The so-called 'internal injuries of the knee joint' (derangement interne) at the present time are divided into 1) injury to the menisci, 2) injury to the cruciate ligaments, 3) rupture of the lateral ligament, 4) injury to plicae alares, 5) fracture of the patella, 6) habitual dislocation of the patella, 7) intra-articular fracture. In accordance with the established diagnosis, the corresponding therapy should be applied, mainly operative. The general position in traumatic A. is, as far as possible, to avoid prolonged fixation.-Summarizing the data presented regarding chronic A., it should be noted that in certain forms the etiological factors are not yet precisely established, and in connection with this the therapy of such A. is not yet on the absolutely correct path. However, the recent tendency toward the union of the internist and orthopedist in the study of A., more profound biochemical, bacteriological, and patho-histological investigations in individual forms of A. are bringing more clarity and definiteness to the pathology and clinic of chronic joint diseases.
Syphilitic arthritis. Clinically, in early syphilis, the following forms are observed: 1. Arthralgia syphilitica praecox—the most frequent form, often encountered predominantly at the end of the second incubation period or in early secondary syphilis; it affects mostly women and is expressed only by pain, mainly in many large joints, which objectively show no changes; the pain causes little disturbance during the day and during movement, sharply intensifying at night in bed. Pain points are noted either at the sites of attachment of tendons or articular ligaments, or along the line of the joint itself. Lingering for whole months in the absence of treatment, arthralgia passes with remarkable speed upon treatment. 2. Arthritis pseudo-rheumatica secundaria (Fournier), i.e., synovitis syphilitica subacuta, not often observed in the first months of the secondary period, is characterized by gradually increasing pain in one or several, usually few and large, joints, to which is gradually added a moderate diffuse swelling of the joint with insignificant effusion, with normally colored or slightly reddened, but somewhat warmer to the touch skin. The existing constant pains, without depriving patients of the ability to move, only more or less hinder movements and do not allow rest in bed; the temperature either remains normal or rises by 1–1.5°. Passive movements are painful but unimpeded. The occasionally observed involvement of several joints at once and a temperature up to 40° can simulate rheumatic polyarthritis. The discrepancy between the patient's complaints of pain and the movements they perform; nocturnal exacerbation of pain, not increased by movement; the absence of migration from joint to joint; the insignificance of the effusion; the absence of sweating; the ineffectiveness of salicylate preparations and the usual presence of syphilids—are the guiding signs for diagnosis. As a rule, in syphilitic arthritis, there are no cardiac lesions. For differential diagnosis with gonorrheal arthritis, a lesser severity of objective and subjective phenomena is characteristic, in the absence of gonorrhea and the presence of signs of syphilis. Specific treatment quickly eliminates all phenomena of arthritis. Without treatment, the development of chronic "dry arthritis" with crepitus and erosion of cartilage and bone is possible. 3. Synovitis chronica secundaria s. hydrarthrosis syphilitica secundaria. More frequent than the previous form, syphilitic dropsy can develop at any time of the secondary period, especially in the 2nd or 3rd year. Affecting most often the knee joint and frequently bilaterally, it is not multiple, usually develops gradually, without subjective sensations and disturbances of the general condition, and, causing effusion into the joint, does not differ in symptoms from hydrarthrosis of other origin. Quickly yielding to specific treatment, but prone to relapses, it persists for many months without treatment and can lead to immobility of the joint from shrinkage of the capsule and erosion of cartilage. The only characteristic, but not mandatory symptoms indicating a syphilitic origin are symmetry and development without visible causes, especially trauma. Practically, with any apparently causeless dropsy of a joint, along with tuberculosis and gonorrhea, it is necessary to think about the possibility of syphilis and conduct an investigation in this direction. Late arthritis, observed (Ge) in 5% of all men with gummatous syphilis and 3% of women, as X-ray examination has clarified, has as its anatomical basis either changes in the synovial membrane and perisynovial tissues, or, in addition, changes in the cartilage and bone epiphyses: 1) involvement of the synovial membrane in the form of a gummatous infiltrate, either diffuse or focal, with its usual outcomes—synovitis gummosa, besides the usually serous or serous-fibrinous effusion, is often expressed by hyperplasia of the villi with the possibility of the formation of intra-articular bodies and semi-closed cavities between fused villi, even in the form of lipoma arborescens articulorum (Velyaminov); 2) the same, of varying massiveness, infiltration of the joint capsule leads either to a huge, sometimes long-existing and usually uneven, with greater or lesser outward protrusions, thickening with the possibility of softening of individual foci, opening either outward or into the joint cavity, or to its gradual cicatricial shrinkage with greater or lesser stiffness of the joint; 3) lesions of the cartilage (chondritis gummosa of Virchow), permeated by either isolated or more diffuse gummatous infiltrates, are essentially expressed by: a) the presence on their surface of erosions and ulcerations filled with granulation tissue and leaving, upon healing, stellate scars, b) fraying with the formation of thin villi, which in the end can lead to the complete destruction of the cartilaginous coverings of the epiphyses; 4) epiphyseal changes of greater or lesser depth can create: a) osteophytes often visible on an X-ray, and b) epiphyseal gummas, more often surrounded by an eburnated hard-stone mass, giving a dense shadow on an X-ray around a pale gummatous infiltrate. In the absence of treatment, these gummas open with fistulas either outward or into the joint cavity, which leads to purulent arthritis, usually ending in bony ankylosis, less often causing prolonged pyarthrosis with fistulas and the discharge of necrotic carious particles of the epiphysis. The combination of both the mentioned four main lesions in one grouping or another, and phenomena of sclerosis and gummatous decay in the affected tissues creates a diverse clinical picture of syphilitic joint lesions, the classification of which is still far from perfect. Provisionally, one can distinguish the following three main clinical types, allowing for the possibility of more complex transitional forms: I. Perisynovitis gummosa, a form affecting predominantly the knee joints; bones and cartilage are unaffected. A specific infiltrate in the form of separate nests permeates the joint capsule and, affecting the synovial membrane, causes: effusion, which can reach large sizes, or possible hyperplasia of the villi. The joint rounds out, the contours smooth out; upon palpation—patella natans; the contour of the joint is irregularly spherical, in places denser, in places softer. Pain is minimal, as is the impairment of function. Development is slow, gradually progressive. With abundant effusion and significant soft crepitation, indicating extensive proliferation of the synovial villi, joint laxity is possible. Subsequently, with perisynovitis productiva, dense sclerotic cords and discs begin to be felt in the thickness of the capsule, limiting the mobility of the joint and capable of ankylosing it. Upon softening of individual nests, fistulas arise, leading either outward or into the joint cavity, with the possibility of pyarthrosis and subsequent erosion of cartilage. Rapid success in the early stages from specific treatment. II. Pseudotumor albus s. osteo-chondro-arthropathia tardiva, a relatively rare disease, especially of the knee, less often elbow, and even less often sternoclavicular and other joints. Primarily, the articular ends of the bones are affected with the initial symptom of pain, clearly felt upon pressure on certain points, followed by a gradually progressive thickening of the epiphysis with deformity of the joint. On an X-ray—a combination of phenomena of osteoporosis with osteosclerosis. The epiphyseal syphiloma, progressing, captures the cartilage, which becomes necrotic and ulcerated, and reaches the joint cavity, from which effusion and hypertrophy of the synovial villi arise with sharp deformity of the joint, limitation of movements, and muscle atrophy. The emptying of the gumma into the joint cavity leads to pyarthrosis with subsequent formation of fistulas. Since restitutio ad integrum is impossible, even with treatment, traces remain in the form of deformities and stiffness. A difficult differential diagnosis from true tumor albus of tuberculosis is based on the following data: symmetry of the lesion; long course without significant changes in the joint; weak pain; slight and late impairment of joint function without contractures; preservation of a satisfactory general condition in the absence of fever and involvement of local glands; late appearance of fistulas; effusion without blood admixture, etc., speak in favor of syphilis and against tuberculosis. The existence of hybrid (tuberculosis + syphilis or syphilis + gonorrhea, etc.) arthritis makes the diagnosis sometimes very difficult, and only laboratory studies along with trial specific treatment can clarify the matter in such cases. III. Arthritis tabidorum—the most intense form of specific osteochondritis, in which bone-cartilage lesions can reach colossal degrees from tissue hypotonia and traumatism, thanks to a decrease in sensitivity, and perhaps also from a change in the "trophism" of tissues. Subluxations, dislocations, intra-articular bone fractures, ulcerations of bone epiphyses with massive osteophytes characterize these most severe in terms of deformity arthritis, the clinical picture of which, without establishing tabetic disorders, can arouse suspicion of a neoplasm, which is easiest to exclude by X-ray. Arthritis of late congenital syphilis presents a complete analogy with the just-described late syphilitic arthropathies.
A feature of early congenital syphilis, a feature of a purely age-related nature, is syphilitic osteochondritis or epiphysitis, observed in the first three months of life. On the long tubular bones and ribs, at the border of the epiphysis and diaphysis, the ossification zone is widened, irregularly serrated, and on cross-section is yellow-red in color and softened. Radioscopically, one finds a lightening of the shadow of the epiphyses with two serrated lines of ossification. Histologically, there is a proliferation of cartilage cells at the border between bone and cartilage with sparse formation of osteoblasts, sometimes containing treponemes; slow growth of enchondral bone, which ossifies unevenly. The infiltrate forming in the medullary spaces, sometimes with the character of a gumma, can cause separation of the epiphysis, which is thickened due to periostitis. A constant phenomenon in stillborn fetuses or rapidly dying infants, epiphysitis in a milder or initial form is observed in almost all surviving infants with congenital syphilis and is often discovered during radioscopy. Its clinical expressions are: 1) clamor heredo-syphiliticus (G. Sisto), a prolonged, continuous, and causeless cry and weeping of the child, intensifying at night, upon any touch to the patient and shaking of his crib, and especially violent upon pressure on the epiphyses; 2) in severe cases, when the epiphysis separates spontaneously or due to a minor injury, Parrot's pseudoparalysis is observed with complete impossibility of active movements, functional intactness of the muscles, and crepitation in the region of the epiphysis. Cases have been described where periepiphyseal, periarticular, and even intra-articular suppurations were also observed, sometimes purely syphilitic, sometimes caused by secondary infection.
G. Meshchersky. Gonorrheal arthritis was described in 1507 (long before the discovery of the gonococcus) by the Dutch physician Foreest. The connection between joint lesions and gonorrheal processes in the genital organs was subsequently proven by finding gonococci in the joint effusion of patients. Gonorrheal arthritis appears within the first two to three weeks from the onset of the gonorrheal disease, but cases of gonorrheal arthritis occurring after only a few days have been described. Cases of the appearance of arthritis in the incubation period are also known. Characteristic of gonorrheal arthritis is the involvement of the ligamentous apparatus and tendon sheaths; the cavity of the joint itself is involved in the process relatively rarely. Lesions of the mucous bursae behind the olecranon, at the lower angle of the scapula, at the acromial process, but most often of the calcaneal and subcalcaneal mucous bursae, are frequently observed, causing a lesion typical for gonorrhea—achillodynia. Pain upon pressure on the attachment sites of the Achilles tendon to the calcaneus, on the sole at the location of the subcalcaneal bursa, at the attachment sites of tendons to bones, and lesions of tendon sheaths in other places are characteristic symptoms of gonorrheal arthritis. Statistical data on the frequency of involvement of various joints by the gonorrheal process are not the same among different authors. The knee joint is affected more often than others, followed by the ankle joint, wrist, shoulder, etc. Gonorrheal polyarthritis is encountered significantly more often than gonorrheal monoarthritis. The multiplicity of joint involvement in gonorrhea is also fully confirmed by modern views on the pathogenesis of this disease. The majority believe that gonorrheal arthritis represents metastases from the genital organs infected with gonococci, but a positive blood reaction to the presence of gonorrheal toxin, in the presence of negative results of cultures from the blood and joint effusion, suggests that gonorrheal arthritis can also be the result of toxemia of the organism. One can distinguish three main forms of gonorrheal arthritis. Toxic—as a result of intoxication of the organism during acute inflammation of the seminal vesicles; it is distinguished by an acute course, multiple involvement of joints and tendon sheaths, and proceeds without effusion, without pus, and without gonococci in the affected joints. This form gives the highest degree of the Bordet-Gengou reaction, and its course is in direct connection with the course of the vesiculitis. The second form—metastatic gonorrheal arthritis, in which usually one joint is affected; in the cavity of the latter, there is pus with gonococci. The course of this form of arthritis is independent of the course of the disease in the primary focus of infection and gives a weak degree of the Bordet-Gengou reaction. The third form—septic gonorrheal arthritis—is characterized by a sluggish course of the disease and multiple involvement of joints; the Bordet-Gengou reaction is usually negative. Many authors have pointed to the connection of gonorrheal arthritis with vesiculitis. Fuller indicated that after vesiculotomy, the arthritis also disappears. Toxic gonorrheal arthritis proceeds very acutely, with high temperature, severe pain, and a generally grave condition. The acute and subacute course of gonorrheal arthritis is quite rapidly replaced by a chronic condition. A tendency of the muscles near the affected joints toward atrophy and limitation of joint mobility appears very quickly, with a greater limitation of active movements compared to passive ones being characteristic of gonorrheal arthritis. Metastatic gonorrheal arthritis is usually not accompanied by a generally grave condition, and the patient's complaints are limited only to the affected joint. The prognosis in mild forms of toxic gonorrheal arthritis is quite favorable. In severe cases, it is in direct proportion to the treatment methodology. Metastatic gonorrheal arthritis often ends in ankylosis. The most unfavorable prognosis is in septic gonorrheal arthritis, when atrophy of the muscles gradually develops in the patient. Treatment of gonorrheal arthritis must be based on increasing the general defensive forces of the organism, the use of immunotherapy in all its forms, and appropriate action on the source of the generalization of the infection. Clinical observations on the vaccine treatment of gonorrheal arthritis (Fronshtein, Dembskaya, and others) have yielded a very large difference in terms of the success of treating gonorrheal arthritis compared to the pre-vaccine period. Local treatment of gonorrheal arthritis consists of the application of all types of heat. Immobilizing bandages are contraindicated, as they contribute to the development of ankyloses in the affected joints. Immediately upon the reduction of acute symptoms, one should resort first to passive and then to active movements in the joints and massage. Many authors note success from the local treatment of gonorrheal arthritis with Bier's passive hyperemia, iontophoresis, and diathermy. Mud treatment of chronic gonorrheal arthritis has always enjoyed great popularity.
P. Timofeev. Arthritis deformans, a disease of the joints accompanied by their deformation and disfigurement. In earlier times, all chronic diseases of the joints accompanied by their curvature and disfigurement were designated as arthritis deformans; however, subsequently, tuberculous, chronic rheumatic, and gouty arthritis, as well as neuropathic arthropathies, were excluded from this concept, and the name arthritis deformans was retained only for a special, primarily arising disease of the joints, in which the basis of the process is a combination of atrophic-degenerative and proliferative
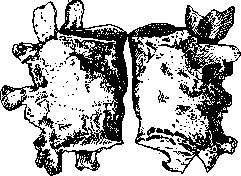
Figure 1. Bony ankylosis of the III lumbar vertebra in arthritis deformans (after Schwalbe).
changes on the part of the cartilage and bone. The disease can involve only one joint, usually the hip or knee (monoarthritic form of arthritis deformans), or it spreads to many (sometimes all) joints (polyarthritic form of arthritis deformans); in the latter type of cases, the disease often affects predominantly the small joints of the upper or lower extremities. A corresponding disease of the spine is also observed (see Figure 1), which is designated as spondylitis deformans. The diseased joints are often crooked and deprived of their normal configuration due to uneven thickening and displacement of the articular ends of the bones; the mobility of the joints is limited. Upon autopsy of a diseased joint, changes in the articular cartilages are found in the form of fibrillation, softening,

Figure 2. Destructive and productive process in the region of the femoral head in arthritis deformans (after Kuester).
disintegration and disappearance of the cartilaginous plates in places of greatest pressure from the opposing articular surface; in such places the bone is exposed, which is sclerosed and, due to friction during joint movement, as if polished and shiny. In addition, in the bone, in areas exposed from cartilage and under still preserved cartilage, focal resorption is observed, as a result of which small superficial defects and areas devoid of bony trabeculae arise in the bone of the articular heads. This reduction of bone substance results in the flattening of the articular heads and is the basis for the appearance of cracks and fractures in them. Along with these atrophic-type changes, proliferative processes also develop from the bone (see Figure 2); of these, the most characteristic for deforming arthritis is the overgrowth of cartilage-covered bone along the edges of the articular surfaces, which gives the formation of a typical for the patho-anatomical manifestations of this disease smooth "marginal ridge", as it were surrounding the altered articular surface like a crown. In addition, near the articular surfaces, irregular bony outgrowths often originate from the periosteum, sometimes reaching enormous sizes (see Figure 3). Thickening of the joint capsule is observed, either uniform or in the form of the formation of branching villi directed into the joint cavity; these changes in the capsule are usually most pronounced in its parts closest to the articular surfaces. Finally, rounded cartilaginous and bony formations (cap- Figure 3. Arthritis deformans of the right hip joint—cartilaginous chondromas and osteomata) can develop in the capsule; in those cases, when they, being connected to the joint capsule by a thin stalk, separate into the joint cavity, they acquire the significance of free joint bodies ("joint mouse"—see). Regarding the pathogenesis of deforming arthritis, there are many theories, from which some the beginning of the process

deformed head
of the thigh and the exostoses projecting along its edges (according to Aschoff). Some assume the process begins in the bone, others in the cartilage; at present, the most probable view is that the beginning and basis of the disease are atrophic-degenerative changes in the articular cartilage, while all other changes should be considered as secondary. The etiology of deforming arthritis is not yet fully elucidated. The functional theory (Pommer) has the most supporters, according to which the etiological factor is the functional mechanical overload of the articular cartilages, leading as it were to their wear, which manifests itself in atrophic-degenerative changes of the cartilaginous tissue; in particular, this theory is partly confirmed by the connection of deforming arthritis with certain professions (locksmiths, bakers, dishwashers). Views that emphasize the importance of intestinal autointoxication, constitution, or the influence of endocrine organs (for example, the thyroid gland) cannot be considered convincing. The physicochemical approach of Seeliger deserves attention, indicating an increase in the acidity of the synovial fluid in deforming arthritis, which can serve as the basis for degenerative changes in the cartilage. It should be added that some researchers also include in deforming arthritis cases of similar patho-anatomical manifestations affecting a single joint, arising after trauma (traumatic deforming arthritis), and, in addition, the so-called chronic ulcerative dry arthritis (arthritis chronica ulcerosa sicca), observed in old age usually in one joint, for example, in the hip joint (malum coxae senile), more rarely in several joints; in this form of the disease, the same atrophic-degenerative changes are present in the cartilage and bone as in typical deforming arthritis, but there is no proliferation of bone tissue.
Related articles
Mentioned in
Cite this page
“Arthritis.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/arthritis/