Spina Bifida
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Great Medical Encyclopedia describes the anatomical features, classification, and clinical significance of congenital malformations known as spina bifida, including rachischisis, various cystic forms, spina bifida occulta, and anterior spina bifida.
Encyclopedia article (1928–1936)
SPINA BIFIDA (literally split spine), a collective term for congenital anomalies characterized by the incomplete closure of the vertebral canal and defective development of the spinal cord or its membranes. The name was given by Tulpius in 1641. Pathological anatomy description is a service of Recklinghausen (1886). The classification prevailing at the present time and given below was developed by Hildebrand. Proceeding from the most severe degrees of retardation of the evolutionary process, the following types of spina bifida are distinguished: I. Rachischisis (rhachischisis), i.e., a defect in the posterior wall of the spinal canal and the absence
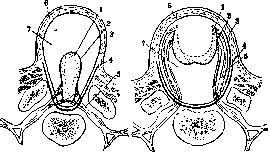
Figure 1. Complete rachischisis: 1 - medullary plate; 2 - pia mater; 3 - arachnoid; 4 - dura mater; 5 - nerve roots.
of closure of the neural groove into a tube. The spinal cord is spread out on the surface, not covered posteriorly by either skin or membranes (Fig. 1). The cleft can extend over the entire spinal column (rhachischisis totalis, s. holorhachischisis) and be accompanied by acrania or cranioschisis (see Cranioschisis), amielia (see), or secondary destruction of the brain substance. In other cases, only a limited section of the spine is affected, and the spinal cord, less spread out, retains the shape of a gutter [rhachischisis partialis (Fig. 2), s. merorhachischisis].
II. Cystic forms of spina bifida: 1. Myelocele represents a partial rachischisis with a dropsical accumulation of cerebrospinal fluid ventrally beneath the unclosed cerebral plate, which is protruded posteriorly (Figs. 3 and 4). Fluid accumulates between the pia mater and the arachnoid, and the nerve roots pass freely through the cavity of the cyst. 2. Myelomeningocele differs from the previous form only in that dropsy has developed between the leaves of the arachnoid. As a consequence, not only the cerebral plate with the pia mater is protruded posteriorly, but also the arachnoid leaf adjacent to the latter (Fig. 5). The nerve roots are located in the thickness of the wall. A strict boundary between myelocele and myelomeningocele cannot be drawn, since in the formation of the wall in the former, the pia mater takes a significant part, and distinguishing it from the arachnoid is often impossible due to secondary degenerative and inflammatory changes. Special attention is deserved by the so-called terminal myelomeningocele in the sacral region (Fig. 6). With this form, the central spinal canal opens only by its distal end on the surface of the tumor-like spina bifida. Mention can be made
Figure 3. Myelocele: 1 - medullary plate; 2 - pia mater; 3 - arachnoid; 4 - dura mater; 5 - nerve roots.
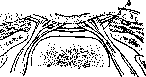
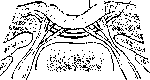
Figure 4. Myelocele: 1 - medullary plate; 2 - pia mater (two leaves); 3 - arachnoid; 4 - dura mater; 5 - nerve roots.
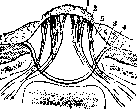
of another variety of myelomeningocele, depicted by de Quervain (Figs. 7 and 8). Rachischisis here is incomplete, i.e., the central cerebral canal is closed, but the spinal cord protrudes in a loop through the cleft in the spine. The protrusion is caused by a dropsical accumulation on the anterior (ventral) side. The protruding section of the spinal cord is covered with the pia mater only on the sides. 3. Myelocystocele (syn. hydromyelocele, hydromyelocele, syringomyelocele) is characterized by the accumulation of dropsical fluid inside the closed central canal of the spinal cord (Fig. 9). The skin over the tumor is more or less preserved, the dura mater is missing, and a cleft gapes in the vertebral arch part. Thus, the posterior wall of the cyst is formed by the skin, the arachnoid, the pia mater, and the stretched, thinned dorsal half of the spinal cord. Nerve roots are never located inside the cavity, but pass in the wall of the cyst. 4. Myelomeningocystocele is a variety in which the dropsical accumulation formed not only inside the central canal, but also in the subarachnoid space (Figs. 10 and 11). Under the pressure of the fluid, the wall of the cerebral cyst may burst (Fig. 12), a circumstance that accelerates the destruction of the neural elements. If the rupture occurred on the dorsal side of the myelocyst or the latter has very small dimensions and is hidden in the depths of a large meningocele, then the wall of the protruding tumor above the skin level contains only a narrow strip, which cases are usually mistaken for meningocele. 5. Meningocele in its pure form represents a hernia of the meninges, filled with cerebrospinal fluid and protruded through the cleft of the vertebral canal, most often in the sacral region. The wall is formed by the skin and the arachnoid; the dura mater is preserved only at the base of the sac, and is absent on the dome (Fig. 13). According to Hildebrand and Marchand, dropsy can develop in the subarachnoid or subdural space, and the wall of the tumor can be formed by the skin, dura mater, and arachnoid, or only by the skin and dura mater. The spinal cord is sometimes secondarily drawn into the cyst and adhered to its inner wall (Fig. 14). III. Spina bifida occulta (hidden spinal cleft) formally means only a defect in the closure of the vertebral arches without a noticeable hernial protrusion of the tumor through the cleft, which is determined in rare cases by palpation, but usually only radiologically. However, since we are talking about a clinical concept, its content is broader. It includes, in addition to bone anomalies, changes in nervous tissue. IV. Spina bifida anterior differs significantly from all the forms mentioned above in that it is not the posterior, arched parts that are split, but the bodies of the vertebrae (Fig. 15). This anomaly was already known to Tulpius. Compared to the posterior cleft, it is a great rarity. The clinical significance of one or another variety is greater the more often this form occurs and the less the anomaly itself as a developmental defect threatens viability. Newborns with rachischisis, myelocele, and myelomeningocele are doomed to early death, because infection is inevitable and fatal. If the central canal of the spinal cord is closed and the skin over the myelocystocele is intact, then by surgical means at best it is possible to prevent secondary infectious and traumatic complications, but paralysis of the sphincters and limbs remains unchanged; children drag out a miserable existence for a short time. Moreover, the cystic forms of spina bifida are often combined with other malformations of the spine, with hydrocephalus (most often with myelocystocele), with defects of the abdominal wall, bladder ectopia, hip dislocation, and clubfoot. The prognosis is relatively favorable, with timely surgery, for the meningocele variety, which is much rarer than others. In terms of frequency of observations, scientific and practical interest, spina bifida occulta occupies first place. Finally, spina bifida anterior, if one does not know about the possibility of the development of such cystic tumors in the pelvis, can give rise to fatal errors in gynecology.
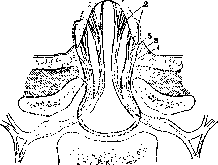
Figure 6. Terminal myelomeningocele: 1 - central canal of the spinal cord; 2 - pia mater; 3 - arachnoid; 4 - dura mater; 5 - nerve roots; 6 - area medullovasculosa; 7 - area epithelioserosa.
Figure 7. Myelomeningocele: 1 - central canal of the spinal cord; 2 - pia mater; 3 - arachnoid; 4 - dura mater; 5 - nerve roots; 6 - area medullovasculosa; 7 - area epithelioserosa. (After de Quervain.)
Figure 8. Myelomeningocele: 1 - central canal of the spinal cord; 2 - pia mater; 3 - arachnoid; 4 - dura mater; 5 - nerve roots. (After de Quervain.)
Causal factors upon which the occurrence of various forms of spina bifida depends are unknown. The essence of the pathogenesis of spina bifida must be sought in the primary defectiveness of the primordium or development of the ectoblast. What this defectiveness is caused by, i.e., the question of the etiology of spina bifida, remains unclear. Experimentally, a number of authors and under the influence of qualitatively very different factors—thermal, mechanical, and chemical—managed to obtain spina bifida.
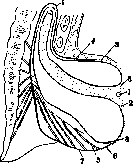
Figure 2. Partial rachischisis: 1 - medullary plate; 2 - pia mater; 3 - arachnoid; 4 - dura mater; 5 - nerve roots.
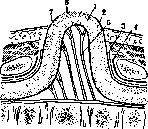
Figure 5. Myelomeningocele: 1 - medullary plate; 2 - pia mater; 3 - arachnoid (two leaves); 4 - dura mater; 5 - nerve roots.
Figure 9. Myelocystocele: 1 - central canal of the spinal cord; 2 - pia mater; 3 - arachnoid; 4 - dura mater; 5 - nerve roots; 6 - area medullovasculosa; 7 - area epithelioserosa. (After de Quervain.)
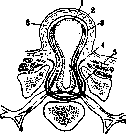
Figure 10. Myelomeningocystocele: 1 - central canal of the spinal cord; 2 - pia mater; 3 - arachnoid; 4 - dura mater; 5 - nerve roots; 6 - area medullovasculosa.
Figure 9. Myelocystocele: 1 - wall of the myelocyst; 2 - pia mater; 3 - arachnoidea; 4 - dura mater; 5 - nerve roots; 6 - skin. S. b. in animal embryos. The conclusion from this can be only one: not the irritant, but the reaction is specific. Pathoanatomical changes are schematically outlined above in the classification of the various forms of S. b. The features characteristic of each group are revealed sometimes during external inspection immediately, sometimes only during surgery and after careful examination of the preparation under a microscope. But it happens not infrequently that degenerative and inflammatory changes dull or distort the initial picture. - In rachischisis, the vertebral canal is converted into a shallow trough; rudimentary arches adjoin the vertebral bodies or are completely absent. The trough is filled with a red-brown, moist, velvety ribbon, along which a median cord with an abundantly developed network of blood vessels sometimes stretches. The cord represents a rudimentary spinal cord and can be double (see Diastematomyelia). If rachischisis occupies only a known section of the spine, then at the upper and lower ends, corresponding to the transition of the flattened into the tubular spinal cord, pits with an opening, cranial and caudal, of the central canal can be found. - Myelocele differs from partial rachischisis only in that the medullary plate is protruded by fluid accumulated subarachnoidally on the ventral side, where the membranes have been preserved and adjoin the vertebral bodies. The dorsal surface of the myelocele and myelomeningocele facing the viewer presents a tumor with characteristic, in fresh cases, three zones named by Recklinghausen zona medullo-vasculosa, zona epithelio-serosa, and zona dermatica (Figure 16). The median zone of oval or heart-shaped form has a red-brown color and corresponds to the medullary plate, with a thickness not exceeding a few millimeters, but in width and length reaching Figure 10. Myelomeningocystocele: 1 - wall of the cyst of the central canal; 2 - pia mater; 3 - arachnoidea; 4 - dura mater; 5 - nerve roots; 6 - skin; 7 - subarachnoid cyst.
arachoideal cyst. inflammatory changes, hemorrhages, ulcerations with fibrinous deposits and purulent decay, the wall is translucent and through it the roots of nerves vibrating in the cavity of the dropsical sac are visible. On the surface at the upper and lower poles, punctate openings of the central spinal canal are noticeable. The medullary zone is surrounded by a meningeal, smoother, pearly-grayish zone formed of pia mater and epithelium growing from the edges. Maceration and hemorrhages can cause secondary changes even during the intrauterine period. The sac is not covered by skin, only at its base is it bordered by the cutaneous zona dermatica. The dimensions of the tumor range from a five-kopeck coin to the width of the palm, the shape is round, the base is wide. Myelocystocele and myelomeningocystocele in size and shape, in frequent localization in the lumbosacral region and due to the translucency of the wall, are similar to the previous group, but are essentially different from it in that the central canal of the spinal cord is closed and the surface of the cyst-like tumor is always covered by skin. Under the influence of infectious and dystrophic processes, the integrity of the skin cover can be broken. Then the deeper layers of the wall, arachnoidea, pia, and the stretched medullary tube are exposed, undergoing decay. The cleft in the vertebral canal can be median or lateral, wide or narrow. Least common and reaching the largest sizes are cyst-like spina bifida, the sac of which consists only of the meninges, i.e., meningocele in its pure form. Their localization is almost exclusively the sacral region. The bone cleft and accordingly the pedicle
Figure 11. Myelomeningocystocele: 1 - wall of the cyst of the central canal; 2 - pia mater; 3 - arachnoidea; 4 - dura mater; 5 - nerve roots; 6 - skin; 7 - subarachnoid cyst.
Figure 12. Myelomeningocystocele: 1 - wall of the cyst of the central canal; 2 - pia mater; 3 - arachnoidea; 4 - dura mater; 5 - nerve roots; 6 - skin; 7 - subarachnoid cyst. of the tumor are narrow. The primary participation of the dura mater in the formation of the sac remains controversial; secondarily, the cauda equina and conus medullaris can be pulled through the cleft and turn out to be adherent to the wall. - Spina bifida occulta should be considered patho-anatomically, as was already noted in the classification, not only as a bone, but, mainly, as a spinal cord developmental anomaly. Recklinghausen defined it as a ruptured and healed intrauterine cyst-like S. b., Dénucé holds the same opinion, but emphasizes that we can only speak of myelocystocele or myelocele. In any case, various gradations of the teratological process, various times of the onset of reparative changes, and a corresponding variety of outcomes are permissible. Natural correction of a developmental defect can create a new, secondary pathological process, which by virtue of a third element is added to the anomalies of the spinal cord and vertebral canal. Teratogenesis, as we saw, assigns the first place in seniority to the brain defect. The bone anomaly is subordinate to it, developing later or independently of it. This explains those cases of S. b. occulta in which the severity and localization of brain disorders do not correspond to the size and location of the bone defect or the latter does not manifest itself in any way. However, it would be wrong to completely deny the possibility of a reverse influence, i.e., the dependence of brain disorders on a bone anomaly. The growth of the spinal column and spinal cord occurs disproportionately. After the 4th month of intrauterine life
Figure 13. Meningocele. For designations see Figure 10.
ni, the growth of the spinal cord lags behind the growth of the spine, the former shortens in comparison with the latter, is gradually pulled out of the sacral canal upward and by the time of birth turns out to be already at the level of the LII vertebra. Therefore, if the spinal cord, thanks to a developmental defect, remains fixed below, it is stretched by the faster-growing spine. A simple mechanical explanation, however, is far from sufficient here either.
Clinically, S. b. occulta often manifests itself only in adolescence, when until adulthood the difference between the growth of the spinal cord and the surrounding bone canal does not exceed the height of one vertebra. In addition, cases have been described (Branner-Ribbert) where with a typical patho-anatomical picture of S. b. occulta, the conus medullaris was at a normal level in the vertebral canal. Furthermore, one sometimes encounters a unilateral growth anomaly incompatible with the growth of the spinal cord in length: 1 - spinal cord; 2 - skin; 3 - arachnoidea; 4 - dura mater. Finally, mechanically one cannot explain
the origin and action of those peculiar changes that develop on the integuments and in soft tissues in S. b. occulta. By these changes, S. b. occulta differs significantly from S. b. aperta or cystica. They can be considered as a new moment included in pathogenesis if S. b. occulta developed from a spinal cyst that ruptured in the embryonic period. Then they are a reaction of embryonic tissues to this rupture. Skin changes consist of umbilical or flat scars surrounded by an area of hypertrichosis (Figure 17). In other cases, there is no local excessive hair growth, but the skin is hypertrophied and thickened, protruding as an appendage resembling a turkey
wattle. Local teleangiectasias are common. Dissecting the skin, one often discovers a cord extending from the surface into the depth and penetrating through the bone cleft into the vertebral canal to the meninges. Of greatest interest are the changes in nervous tissue. Unfortunately, only a few cases have been published so far where the clinical diagnosis of S. b. occulta was supplemented by a patho-anatomical analysis. Far from every cleft in the arches represents an anomaly, a delay in the normal development process of the nature of aplasia. The lumbosacral region of man abounds in variants, since it is still in the period of rapid phylogenetic restructuring associated with the transition from a horizontal to an orthograde position. A. D. Speransky established that one of the manifestations of this process
270
SPINA BIFIDA



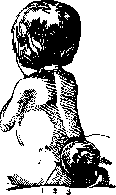
one must consider posterior clefts of the sacrum, starting from those with notches on the spinous processes and ending with a wide gaping of the sacral canal. In contrast to this regular and progressive reduction process, the bone defect in S. b. occulta is of a random, pathological character. The location of the cleft, if it occupies the thoracic or cervical region, is abnormal. The form is very diverse. The cleft is usually narrow, has an oblique direction; the spinous process is underdeveloped, absent, or displaced. In many cases in S. b. occulta, in contrast to S. b. aperta or cystica, there can be no question of aplasia of bone tissue. Both halves of the arches are not shortened, but elongated; they grew toward each other and did not fuse. It was also necessary to observe patients where, with a typical clinical picture of S. b. occulta, the arch had a normal appearance, and the ossification of the posterior wall of the sacral canal occurred excessively and asymmetrically. Denys called forms in which, instead of a fibrous plate, there is a bony closure of the former cleft, S. b. occlusa.
Symptomatology. Functional disorders in S. b. primarily depend on its localization and on the size of the defect in nervous tissue. Newborns with rachischisis and an unfused medullary tube are non-viable not due to the extent of motor paralysis, but due to the inevitability of secondary infectious complications. Deformities of the limbs, most often clubfoot, develop in utero. In other cases, on the contrary, the normal configuration of the skeleton and musculature of the limbs is affected, indicating that their development in the fetus can proceed correctly without motor impulses, due to the preservation of the spinal ganglia, which separated from the spinal cord before its formation into a tube. The deceptive appearance of such newborns can influence the decision regarding surgical help. In Myelocystocele, the greatest stretching is experienced by the dorsal wall of the brain cyst and, due to its lateral location, one half is larger than the other. Correspondingly, trophic and sensory disorders predominate, hemiplegia instead of paraplegia. Curvatures of the legs are the same as in S. b. occulta, i.e., claw-like contractures of the fingers, combinations of transverse flatfoot with pes cavus.
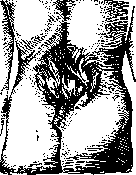
Figure 17. Spina bifida occulta with hypertrichosis. Varus and planus, ulcerative processes on the skin and bones, mixed with spastic pareses. Motor disorders may have a predominant localization in the musculature of the perineum (see Prolapse of the uterus, vagina). In pure forms of meningocele, there is usually not even that sign which is most frequently observed in S. b., namely enuresis. Basically, it must be remembered that S. b. occulta in small children does not manifest itself in any special way, that the first, unclear signs begin insidiously, by 6-10 years or even later, differing in great variety and progressive course. The diagnosis of cystic forms of S. b. presents no difficulties if on the weeping surface of the congenital tumor the 3 zones of Recklinghausen and the pinpoint openings of the central spinal canal are distinguishable. Maceration of the initially preserved skin coverings in Myelomeningocele can be misleading, all the more so since then translucence does not give positive results, and the question of the passage of nerve roots through the cavity is not resolved. In such cases, the analysis of functional disorders is more important than the data of examination. The practical significance is especially important in the diagnosis of brain hernias, in the formation of the sac of which the spinal cord does not directly participate. The absence of paralyses and other deformities, the localization in the sacral region and the significant size of the cyst speak in favor of meningocele, but the secondary involvement of the spinal cord, cauda equina or nerve roots in the sac is not excluded by this. Trial incisions or punctures are dangerous and clarify little. Recognition of S. b. occulta is impossible in small children if there are no skin signs, since the cartilaginous state of the vertebral arches on x-rays simulates clefts. The coccygeal fossa (foveola coccygea) or an unusual skin groove, longitudinal or oblique, in the sacral region is a variant only bordering on an anomaly. Typical forms of clubfoot in newborns usually have nothing in common with S. b. occulta. More convincing are the atypical curvatures of the legs in the absence of traces of amniotic bands. Only the course, namely the progressive nature of the deformation (despite correct treatment), the admixture of spastic phenomena to paretic ones and the special tendency to trophic disorders confirm the diagnosis of clubfoot on the basis of S. b. occulta. X-ray examination of patients after 10 years of age may be decisive, but the bone clefts thus found are often found without any functional disorders, local or reflected. On the other hand, the combination of a bone anomaly in the arch part of the sacral vertebrae with skin anomalies in the form of sacrococcygeal scars or capillary telangiectasias and local hypertrichosis should serve as proof of S. b. occulta. Future pathological-anatomical studies of clinical cases will show how often and in what form 'myelodysplasias' accompany the bone-skin anomaly. The prognosis of cystic forms of S. b. with the participation of the spinal cord in the formation of the wall is almost absolutely unfavorable without operation. Accompanying deformities and existing functional defects must be taken into account when assessing viability if the operative interventions aim to prevent at least infection of the brain hernia. It is impossible to influence the functional disorders, to eliminate or alleviate them by operation, since we are dealing with nervous tissue devoid of regenerative capacity. A special place in prognostic respect is occupied by meningoceles not complicated by hydromyelia of the central canal. The prognosis of these cases is even favorable without operation. As for cases of spina bifida occulta with trophic and spastic-paretic phenomena, the severing of bands and the liberation of the spinal cord from stretching or pressure may have a good result. Treatment of S. b. cystic does not achieve its purpose without careful care of the child, without prevention of secondary infectious and traumatic complications. The task of the operation is to eliminate the protrusion and to reliably close the hernial gates. The faulty development of the spinal cord remains. Only some of its consequences in the form of contractures and deformations can be more or less corrected. Cystic S. b. should be subjected to the earliest operative treatment if the child is viable at all and the condition of the coverings at the site of the tumor is satisfactory. Otherwise, one is limited to protective bandages preventing maceration of the skin and the introduction of infection, promoting epithelization. Pressure bandages, adhesive and collodion bandages, which are supposed to reduce tension and protect the cyst from rupture, do more harm than good. It is best to recommend the horizontal position on the abdomen in well-fitting plaster beds supporting the head and lower extremities. For protection during bathing, it is best to smear cystic S. b. devoid of skin with sterile petrolatum. Previously used systematic punctures of the cyst with subsequent introduction of Lugol's solution or other iodine solutions, with the aim of causing adhesive inflammation and wrinkling of the walls, are now obsolete. Similarly, ligature methods, which are even more destructive and act blindly, have been abandoned. The only rational method is the operative one, allowing reduction of the hernia without unnecessary sacrifice of preserved nerve elements and closure of the parietal defect by plastic means. The technique varies according to the type of S. b. In myelocele, a modular plate is presented, which must be disinfected, separated from the zona dermatica and reduced, then covered with normal and stable tissues, without compression of the spinal cord. There are somewhat fewer technical difficulties in myelocystocele due to the fact that the central canal is closed and the sac is not devoid of skin cover. With a flap, upwardly convex incision, the wall of the cyst is exposed, it is emptied by a median incision, i.e., where the brain tissue is most stretched and therefore functionally already unsuitable. Small cysts that are reducible without emptying are not opened. The membranes are sutured with catgut sutures. Many methods have been proposed for closing the bone cleft of the vertebral canal. In particular, Russian surgeons (Zenenko, Bobrov, Lysakov) have developed bone-plastic methods. The conditions under which one has to operate - early childhood, low tissue resistance and questionable asepsis - force one to give preference to muscle-fascial flaps from the nearest neighborhood (Bayer). Due to the narrowness of the hernial gates in meningocele, the operation in these cases can be limited to liberation of the sac, examination of its contents, isolation of the nerves from the wall and their reduction, then excision and suturing of the sac. Spina bifida anterior has no direct relation to posterior S. b. Clefts of the vertebral bodies are observed mainly in combination with rachischisis and anencephaly, with diastematomyelia and ectopias of parts of the gastro-intestinal tract. Without such deformities excluding the viability of the fetus, anterior S. b. is extremely rare. The described clinical cases can be divided into two groups. The first group consists of gynecological patients, girls and multiparous women, in whom cysts displacing the pelvic organs and fused with the sacrum were found. Punctures of these cysts through the vaginal vault or rectum led to fatal meningitis. Autopsies showed that through a defect in the sacrum a meningocele protruded into the pelvic cavity. The second group includes small girls with kyphoscoliosis of the cervico-thoracic region of the Klippel-Feil type (see Spine, developmental defects and deformities), but with clefting or even with lateral divergence of the vertebral bodies. Remarkably, in contrast to sacral forms, there is no hernial protrusion and no spinal cord phenomena at all. Sacral forms may be accompanied by clubfoot. The origin of anterior S. b. is connected by Budde with incomplete or untimely closure of the neuroenteric canal, the connection between the neural tube and the primitive intestine. In favor of this assumption are cases where the bottom of the vertebral cleft was lined with gastric mucosa or connected with loops of the intestine. The very early teratogenesis is also evidenced by the fact that in normal conditions the vertebral bodies develop from an unpaired cartilaginous primordium. Consequently, the cleft must have occurred earlier than this primordium of the vertebra differentiated from the somites of the mesoblast.
Related articles
Mentioned in
Cite this page
“Spina Bifida.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/spina-bifida/