Spine
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Soviet medical encyclopedia details the comparative anatomy and embryonic development of the vertebral column in vertebrates. It describes the evolution of the notochord into the vertebral column, the formation of vertebral arches, and the structural differences in vertebral bodies across various classes of animals.
Encyclopedia article (1928–1936)
VI. Occupational pathology of the spine. . . 157. The spine, the axial skeleton of vertebrate animals, consists of a metameric series of more or less movably connected skeletal elements that protect the spinal cord and serve as attachment points for the trunk musculature. I. Comparative anatomy and ontogenesis. The primary axial skeleton of vertebrates is the elastic cylindrical rod—the notochord, which forms the sole skeletal axis of lower 'chordate' animals. In vertebrates, the notochord is present at least embryonically, and is later supplemented or, more often, completely replaced by cartilaginous or bony vertebral elements. In the early stages of development, the notochord appears as a cellular cord of endodermal origin, lying directly below (i.e., on the ventral side) the central nervous system. On the outer surface of the notochord, a thin 'elastic' sheath develops, and beneath it a thicker 'fibrous' sheath, as a product of the activity of the notochord cells themselves (Figure 1). The notochord cells become strongly vacuolated. The skeletal role of the notochord is due to the strength and elasticity of its sheaths under significant internal pressure (turgor). In all vertebrates, from the inner angles (sclerotomes) of the primary mesodermal segments (somites), a mass proliferation of mesenchymal cells occurs, which then arrange themselves around the notochord and the central nervous system. This embryonic connective tissue forms a particularly dense condensation around the notochord and penetrates from there into the spaces between the muscle segments, as well as into the septum between the dorsal and ventral sections of the latter. The skeletal axis, the animal's notochord, is thus connected to a complex system of connective tissue septa, which together form a fairly strong framework. These are the stages of the 'membranous' axial skeleton. Such is the lifelong axial skeleton of lower chordate animals (amphioxus). In lower vertebrates, elements of the axial skeleton develop within the connective tissue sheaths and septa, initially in the form of isolated paired cartilages adjacent to the notochord on the dorsal and ventral sides. Lampreys have only a paired row of small cartilages sitting on the notochord in the connective tissue layer, on the sides of the spinal cord. These are very thin rods, alternating quite regularly with the exits of the spinal nerve roots, with two pairs of such 'upper' or 'neural' arches for each segment. In cartilaginous fish, these cartilages grow larger and fully enclose the spinal canal, with one posterior arch usually predominating in each segment, while the anterior one develops more weakly and appears as an 'intercalary' cartilage (intercalare). In addition to the upper arches, 'lower' or 'haemal' arches develop in all true fish, initially also in the number of two pairs in each segment. The notochord itself is preserved in this case as a permanent organ not only in cyclostomes (lampreys) but also in holocephalans (chimaeras), in sturgeons (Fig. 2), and in lungfish. The spine in this case consists of well-developed paired upper and lower arches, often even ossifying, but sitting directly on the notochord (the 'vyaziga' of sturgeons); 'vertebral bodies' do not exist in this case. In connection with the primary vertebral arches, all true fish develop

Figure 1.
Figure 2. Figure 1. Sheaths of the notochord in the larva of the midwife toad (Alytes obstetricans): 1—fibrous sheath; 2—perichordal connective tissue; 3—layer of skeletoblasts; 4—elastic sheath; 5—chordal epithelium. Figure 2. Part of the spine of a sturgeon from the posterior part of the trunk region (cartilage is indicated by dots). ...and some further parts of the axial skeleton. By the paired connection of the neural arches over the spinal canal, unpaired upper spinous processes (proc. spinosus neuralis) are formed (Fig. 2). The lower arches, growing out to the sides along the myosepta, give rise to ribs, which then detach from the main part—the lateral process (parapophysis). In vertebrates, the formation of two types of ribs is observed: some of them are located between the peritoneum and the ventral section of the trunk musculature—these are the lower, or pleural, ribs, characteristic of most fish; others are located in the horizontal connective tissue septum between the dorsal and ventral sections of the musculature—these are the upper ribs, present in some fish (sharks), sometimes alongside the lower ones (in lobe-finned fish) (Fig. 3), but especially characteristic of terrestrial vertebrates. In the caudal region of the spine, the lower arches grow not to the sides, but downward, enclosing from the sides the continuation of the dorsal aorta—the caudal artery and vein (forming here a special 'haemal' canal for them)—and fusing beneath them to form the lower spinous process (proc. spinosus haemalis) (Fig. 3). The vertebral bodies themselves are derivatives of the described 'arches,' although they subsequently acquire a seemingly independent significance. In many fossil fish and amphibians (Fig. 4), the vertebral bodies consisted of separate parts (up to 4 pairs in each segment), which were the product of the growth of the bases of the arches around the notochord. In modern vertebrates
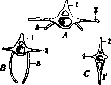
Figure 3. Figure 4. Figure 3. Vertebrae of the lobe-finned fish Polypterus (A-C): 1 and V—upper and lower spinous processes; 2—upper rib; 3—lower rib; 4—lateral process. Figure 4. Trunk (a and b) and caudal (c-f) vertebrae of a stegocephalian (Archegosaurus). The vertebral bodies, if present, are always solid. The history of their development shows that in fish, amphibians, and higher terrestrial vertebrates, they have essentially different origins and therefore formed in these groups independently of each other. The vertebral bodies of amphibians were formed by the bases of the main (posterior) upper and lower arches that grew around the notochord. The vertebral bodies of higher terrestrial vertebrates were formed mainly by the intercalary (i.e., anterior, cranial) elements, with which the bases of the upper arches fused. Remnants of the main lower elements are sometimes still observed in the form of special 'intercentra,' with which the lower arches and lower spinous processes are also connected in the caudal region. In any case, such lower (haemal) arches are always attached intervertebrally in both reptiles and mammals. In fish, the vertebral bodies have a cylindrical shape and are deeply concave anteriorly and posteriorly (cranially and caudally). Thus, there is a free space between adjacent vertebral bodies, in which remnants of the notochord are preserved for life. In lower terrestrial vertebrates, a biconcave (amphicoelous) form of vertebrae with remnants of the notochord between adjacent bodies is also sometimes still preserved, however, in the vast majority of them, the notochord is completely displaced by ossifications of the bodies growing from the outside or by special intervertebral cartilages. However, insignificant remnants of the notochord are preserved even in mammals between the bodies of adjacent vertebrae within the intervertebral cartilages in the form of a special * gelatinous nucleus (nucleus gelatinosus, s. pulposus). In higher fish, as well as in terrestrial vertebrates, the vertebrae ossify completely. Adjacent vertebrae are connected to each other more or less movably. These connections are particularly mobile in more primitive terrestrial vertebrates (amphibians and reptiles), which move with the help of lateral body bends (especially snakes). In connection with this, the shape of the vertebral bodies is concave-convex, and a true joint develops between the bodies. The articular processes (zygapophyses), which are also present on the neural arches in fish, develop much more strongly in terrestrial vertebrates and are sometimes supplemented by a system of additional unpaired processes (for example, in snakes). In animals with a less flexible body, the anterior and posterior surfaces of the vertebral bodies acquire a flatter shape, and sometimes intervertebral discs or menisci develop between them (in crocodiles, in mammals); in this case, adjacent vertebral bodies are firmly connected by means of syndesmosis. In terrestrial vertebrates, the connections of the spine with the skull and the first vertebrae with each other achieve special mobility. On the first vertebra, articular surfaces develop for articulation with the unpaired (in reptiles and birds) or paired


Figure 5.
Figure 6.
Figure 5. Formation of the atlas and axis in the fossil reptile Ophiacodon: 1-atlas; 2-axis. Figure 6. Anterior thoracic vertebra of an alligator: 1-spinous process; 2-articular process; 3-rib; 4-transverse process. [The spine connects] with the occipital condyle of the skull (in amphibians and mammals). Furthermore, in higher vertebrates (reptiles, birds, and mammals), a peculiar composition and relationship between the first two vertebrae are discovered (Fig. 5). The first vertebra is composed only of the upper arch, closed on the ventral side by an intercentrum, and takes the form of a ring. The body of this vertebra connects with the body of the second vertebra (and its intercentrum), forming its prominent 'odontoid' process (processus odontoideus), which enters inside the ventral half of the aforementioned ring. Thus, the first vertebra, the 'atlas,' gains the ability to rotate quite freely on the odontoid process of the second vertebra, the 'axis.' The mobility of the head achieved in this way is further enhanced by the development of a generally more mobile cervical region of the spine, in which the ribs are reduced (in some reptiles, there are mobile ribs even on the atlas). The strengthening of the pelvic girdle on the spine (specifically by means of ribs) causes in terrestrial vertebrates the separation of yet another (sacral) region, inserted between the trunk and caudal regions (in fish, there are only these two regions). Finally, the trunk region is also divided into an anterior, comparatively less mobile, thoracic region, characterized by fully developed ribs forming here, together with the sternum, the rib cage, and a posterior, more mobile, lumbar region, in which the ribs are reduced. Ribs in terrestrial vertebrates belong, as has been said, to the type of upper ribs. Their connection with the spine is transformed through the division of the proximal part of the rib into two branches, to which corresponds the division of the lateral process supporting the rib into two parts—the dorsal part develops more strongly and moves (especially in the cervical and thoracic regions) onto the neural arch (Fig. 6), while the ventral part remains on the posterior edge of the body (initially the process and the rib sit on the intercentrum) and is reduced. The upper branch of the proximal end of the rib receives the name of tubercle (tuberculum), and the lower branch—the head (capitulum). The former usually, especially in mammals, shrinks (Fig. 7). Ribs, as a rule, do not ossify throughout their entire length—their sternal part remains cartilaginous (in crocodiles, birds, monotremes, and xenarthran mammals, the sternal part of the rib also ossifies).
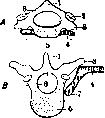
Figure 7. Diagrams of cervical vertebrae of mammals: 1-spinous process; 2-articular process; 3-transverse process; 4-rib; 5-vertebral body; 6-neural arch; 7-head of the rib.
The number of vertebrae in vertebrates is highly variable: in fish, this number ranges from 2-3 tens to 200-400 vertebrae in forms with a long body; in terrestrial vertebrates, this number is usually lower, although in snakes it also reaches 200-400. However, the number of presacral vertebrae is much more constant. Although this number also fluctuates quite significantly, according to paleontological data, the starting point for higher vertebrates (reptiles, birds, and mammals) is apparently 26 vertebrae. Amphibians have only 1 sacral vertebra, modern reptiles—2. Birds also have 2 primary sacral vertebrae, but a whole series of lumbar vertebrae in front and caudal vertebrae behind fuse with them, so that a complex sacrum of 9-22 vertebrae is formed. In mammals, there are initially 2 sacral vertebrae, but then up to 4 further vertebrae can join them. These vertebrae fuse with each other and bear on the lateral parts, corresponding to the transverse processes (and partly to the ribs), articular surfaces for the iliac bones of the pelvis. The caudal vertebrae that attach to the sacrum from behind, which do not participate in this articulation, are called secondary or false sacral vertebrae. The number of vertebrae in the cervical region of mammals is established as quite constant—7 vertebrae (exceptions: manatee—6 vertebrae, sloths—6-9 vertebrae, pangolin—8). In the thoracic region, there are usually 12-15 vertebrae (most often 13), in the lumbar region usually 6-7. The number of caudal vertebrae varies depending on the length and significance of the tail, usually fluctuating between 15-30.
I. Schmalhausen. Ontogenesis. The human spine also passes through three stages of development: membranous, cartilaginous, and bony; but the notochord appears even earlier. The process of cartilage formation in humans begins at the start of the second month. In certain areas of the young connective tissue, nests of cells appear, which, by secreting the cartilaginous ground substance, move apart from each other as they grow. Initially, such nests of cartilage cells appear in the body and in the arches of the vertebrae, then the arches grow onto the body, and only in the 4th month of intrauterine life do the arches (or rather, the halves of the arches) fuse with each other, closing the vertebral column from the dorsal side. The cartilaginous processes of the vertebrae appear later in separate places, the spinous process being the last of all. The entire cartilaginous skeleton of the human embryo has a special appearance, significantly different from the bony skeleton. Even before the complete formation of the cartilaginous spine, from the end of the 2nd month of intrauterine life, ossification of the spine begins in humans, proceeding from the head to the tail. Certain areas of the cartilaginous skeleton ossify, while others do not, so that the cartilaginous skeleton is not completely replaced by the subsequent bony stage of development. Thus, the bony spine of an adult contains remnants of all the stages of development passed through. Each vertebra has 3 main ossification points: one in the body and 2 in the arch; the ossification points in the arch fuse with each other in the first year of life and connect with the body in the 3rd year, with the bony substance of the anterior parts of the arches extending into the vertebral body. Thus, the posterior lateral part of the future vertebra, with which the future head articulates, is formed from the anterior section of the arch. From the ossification points of the arch, not only the bony arch is formed, but also the processes: spinous, transverse, and articular. Additional points appear later—in the 15th–16th year of life: one on the tip of the spinous process, two on the tips of the transverse processes, and in addition, two points on the upper and lower surfaces of the vertebral body, forming two thin, wide epiphyseal plates. The lumbar vertebrae have additional points for the processus mammillaris. The fusion of the listed additional ossification points with the rest of the vertebral mass occurs by the 25th year of life. The rudiments of the ribs also take a significant part in the formation of the vertebrae, with separate ossification points in the cervical, lumbar, and upper sacral vertebrae. In the cervical ribs, even in the cartilaginous stage, the processus costarius connects at one end to the vertebral body and at the other to the tip of the transverse process, due to which an opening (foramen transversarium) is formed, which then persists in the bony state for life. In the thoracic region, the ribs are independent and do not take any part in the formation of the vertebrae. In the lumbar region, the rib rudiments completely fuse with the transverse processes, giving a complex formation, the processus costotransversarius. In the upper sacral vertebrae, the rib rudiments fuse into lateral masses, as will be indicated below. In the two lower sacral and all coccygeal vertebrae, rib rudiments are absent. The first and second cervical vertebrae have peculiarities. The atlas has one ossification point for each massa lateralis with the corresponding half of the posterior arch; in addition, one or two additional ossification points appear in the anterior arch in the first year. The body of the atlas grows onto the body of the axis even in the cartilaginous stage, forming the odontoid process; therefore, the axis has an additional ossification point (sometimes two) for the odontoid process, which fuses with the bony body of the axis in the 3rd–5th year. The sacral vertebrae have, like the others, three main ossification points, which fuse, starting from the lower vertebrae, in the 2nd–6th year of life; in addition, the three upper vertebrae also have lateral points for rib rudiments (sacral ribs), which take part in the formation of the lateral masses of the sacrum (massa lateralis). The fusion of the sacral vertebrae occurs late—in the 14th–25th year. The coccygeal vertebrae have one ossification point each (for the vertebral bodies), which appear from the 1st to the 20th year. The fusion of the vertebrae occurs from below; first, the three lower vertebrae fuse, and then, after 30 years, the first vertebra also fuses with them.
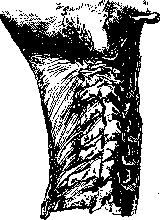
II. Anatomy. The human spine is the main, fairly flexible rod to which all other parts of the skeleton of the trunk are attached; in it, one distinguishes the cervical region with 7 cervical vertebrae, the thoracic with 12, the lumbar with 5, the sacral with 5, and the coccygeal with 4 or 5 vertebrae. Each vertebra has a massive body lying in front (corpus vertebrae) and an arch located behind (arcus vertebrae); the arch and the body bound an opening (foramen vertebrale); in the entire spine, these openings, merging, form a canal (canalis vertebralis) intended for the spinal cord. The vertebral body is usually oval in shape, its anterior and lateral surfaces are slightly convex from left to right and concave from top to bottom; the posterior surface is slightly concave, and the upper and lower are flat and also slightly concave. The anterior, posterior, and lateral surfaces bear numerous openings for blood vessels; these openings are especially large on the posterior surface facing the vertebral canal. The arch consists of two symmetrical halves extending from the lateral parts of the body and merging behind along the midline. The initial parts of the arch on both sides are narrowed and are called roots (radices arcus vertebrae); on the upper and lower edge of each root of the arch there are notches (incisura vertebralis superior et inferior), with the lower one being significantly deeper. In the entire spine, when one vertebra is placed on another, the notches of two adjacent vertebrae form intervertebral foramina (foramina intervertebralia) on both sides, leading into the vertebral canal. From the arch, two paired processes extend to the sides—transverse processes (processus transversi), then two pairs of articular processes upwards and downwards (processus articulares superiores et inferiores), and finally one unpaired process extending posteriorly from the middle of the arch—the spinous process (processus spinosus). The size and shape of the vertebrae vary depending on the region of their location. Starting from the cervical ones, the size increases, with the upper sacral ones being the largest, and below them, there is a rapid decrease. Each of the individual groups of vertebrae possesses special features, which are most pronounced in the middle vertebrae of each group; these features make it possible, even from individual parts of the vertebra (by the body, arch, or process), to determine to which group it belongs. They are smoothed out at the ends of each group, where the vertebrae acquire forms transitional to the adjacent group. The vertebrae of a human can be considered as a complex lattice-like structure (Bardeleben). They consist for the most part of spongy substance (substantia spongiosa), covered on the surface only by a thin layer of dense substance (substantia compacta). The bony trabeculae in the vertebral body are arranged vertically from the upper surface to the lower, horizontally and obliquely—from the upper articular process to the lower surface and from the lower articular process to the upper surface. In the middle of the body, the bony trabeculae are weakly expressed, and here it comes to the formation of more or less significant cavities. The dense bony substance is more strongly developed in the region of the upper and lower notch, in the roots of the arches, due to which the arches have a more solid structure compared to the bodies and other parts of the vertebra, which explains the rarer fractures of the roots of the arches. The cervical vertebrae (Fig. 8) (vertebrae cervicales), seven in number, are small; a distinctive feature is the opening in the transverse processes (foramen transversarium) for the a. et v. vertebrales; the vertebral artery, emerging from the subclavian, usually enters the opening of Cvi, and sometimes only Cv, Civ, and even Ciii. The upper surface of the transverse process from Ciii to Cvii is provided with a wide

Figure 8. Cervical region of the spine with the nuchal ligament.
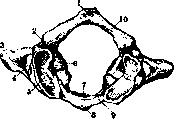
Figure 9. Cervical vertebra of a newborn. Figure 10. Atlas from above: i-tuber-
groove (sulcus n. spinalis). The bodies of the cervical vertebrae are more elongated in the transverse direction than in the sagittal; the width of the vertebrae, starting from Cvi, increases downwards. The upper and lower surfaces of the body are slightly saddle-shaped. The articular processes are broad and flat; the upper ones face backward and slightly upward, the lower ones forward and slightly downward. The spinous processes (proc. spinosi) are directed generally horizontally and only very slightly downward; their tips are usually split into two tubercles, with the exception of Cvii and Cvii; short in the upper vertebrae, they gradually increase downwards, especially the spinous process of Cvii, which exceeds all others in length and width. The latter, lying almost horizontally, protrudes further backward and is comparatively easily palpable through the skin, thanks to which Cvii has been given the name vertebra prominens. The vertebral foramen of the cervical vertebrae is of significant size with rounded corners (Fig. 9-14).
The anterior part of the transverse process of Cvi (processus costarius) usually protrudes more strongly forward, thanks to which it is more accessible to palpation through the skin. This protrusion in topographic anatomy has received the name of the carotid tubercle (tuberculum caroticum); the carotid artery can be pressed against it. The first two cervical vertebrae have different distinctive features, which make understandable the possibility of rotation of the head around a vertical axis, which is why the two upper cervical vertebrae have received the name of rotational vertebrae, in contrast to all the others, which are flexion (vertebrae). For the description of Ci and Cii, see Atlas and Epistropheus.
The thoracic vertebrae (vertebrae thoracales, s. dorsales), 12 in number, are the simplest typical vertebrae, since the rudiments of ribs, which in this region are independent and develop separately from the vertebrae, do not take any part in their formation. A distinctive feature of these vertebrae is the presence of articular surfaces on the bodies and on the transverse processes for articulation with the heads of the ribs and their tubercles (Fig. 15). These surfaces appear on the majority of thoracic vertebrae in the form of two demifacets, lying on the lateral surface of the body, anterior to the root of the arch, the upper one at the upper edge, the lower one at the lower edge (fovea costalis superior et inferior); each of these demifacets, connecting with the same one of the adjacent vertebra, forms a facet for the head of the rib. The upper demifacet serves for connection with the corresponding rib, and the lower one with the one lying below. An exception is Di, which has a whole facet for the first rib and a demifacet for the II rib, Dx, which has only one upper demifacet for the X rib, and Dxi, Dxii, which have whole facets for the corresponding ribs. The bodies of the thoracic vertebrae are in form, in all directions, significantly larger than the bodies of the cervical ones. Their appearance gradually changes from a triangular shape with rounded edges to a kidney shape.


The transverse processes of the thoracic vertebrae are somewhat deflected backward; on their anterior surface near the tip there are roundish, flat-concave articular facets (foveae costales transversales) for the tubercles of the ribs; on Dxi and Dxii these facets are absent. The spinous processes are triangular in shape, long, and inclined sharply downward, arranging themselves tile-like one above the other, especially in the middle vertebrae.
The vertebral foramen is cylindrical in shape and smaller than in the cervical and lumbar vertebrae. The articular processes stand frontally, with the upper ones facing backward and the lower ones forward. The lumbar vertebrae (vertebrae lumbales), 5 in number, are the largest. Their massive bodies are larger in all directions compared to the thoracic ones, the shape is kidney-like; the edges of the bodies always protrude sharply, sometimes forming outgrowths, especially posteriorly (Figure 16).
The spinous processes are well developed and have an almost horizontal direction, thanks to which a needle inserted during the greatest possible kyphotic flexion between the spinous processes of the lumbar vertebrae (between Liii and Liv) does not encounter resistance and easily reaches the vertebral canal.
The transverse processes are long and flat and represent rudiments of fixed ribs; at the base of the transverse processes there is a small sharp spike, the accessory process (processus accessorius).
SPINE
The articular processes are thick and stand sagittally; the upper ones are cylindrically concave, and the lower ones are correspondingly convex. On the lateral side of the upper articular process protrudes a small mammillary tubercle (processus mammillaris). The vertebral foramen is triangular in shape and of significant width.
The cervical, thoracic, and lumbar vertebrae are called movable, or true (vertebrae verae), while the lower sacral-coccygeal vertebrae, which fuse into
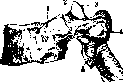

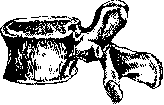
Figure 15. Thoracic vertebra from the side: 1-fovea costalis sup.; 2-incisura vertebralis sup.; 3-processus articularis sup.; 4-fovea costalis transversalis; 5-processus articularis inf.; 6-processus spinosus.
the sacrum and coccyx have received the name of fixed, or false (vertebrae spuriae). For a description of the lower section of the spine, see Sacrum, Coccyx. Variations and anomalies of the spine are numerous and diverse; some of them are so significant that they disrupt the functioning of the spine, while others are insignificant, do not manifest themselves in any way during life, and are discovered on a cadaver only during special anatomical examinations. Variations concern both the forms of the vertebrae and the numerical composition in various sections. Thus, congenital scoliosis, associated with developmental defects, in most cases depends on the presence of additional underdeveloped wedge-shaped vertebrae. Located usually on one side only between normal ones, such wedge-shaped formations affect the development of neighboring vertebrae, which ultimately results in a curvature of the spine. The described formations can be observed in all sections of the spine and can be either single or multiple; sometimes they replace normal vertebrae. The formation of the described half-wedge-shaped rudiments can be explained only by incorrect segmentation of the mesenchyme in that initial period of development when the primary vertebra consists of a double paired primordium. From a diagnostic point of view, it should be noted that in some cases congenital scoliosis becomes noticeable at an older age, and not immediately after birth. Furthermore, the vertebral arches may not fuse, the spinous processes then do not form, as a result of which the vertebral canal is more or less gaping (spina bifida) and the spinal cord together with the membranes can prolapse through the formed gap like a hernia. Such non-fusion of the arches is observed more often in the lumbar and sacral, as well as in the cervical section of the spine (see Spina bifida). The most interesting in morphological terms are the numerical variations of the vertebrae; in many cases they depend on the number of ribs. Thus, in the presence of 13 pairs of ribs, the number of thoracic vertebrae increases and, conversely, in the presence of 11 pairs of ribs, the number of lumbar vertebrae increases; the number of free, presacral vertebrae in these cases remains the same—24 vertebrae. But there are, however, cases when the total number of free vertebrae decreases or increases; this depends on what place the sacrum occupies. It should be noted that the sacrum can consist of 4, 5, or 6 vertebrae and the first sacral vertebra could be XXIV, XXV, XXVI, and XXVII. The last sacral vertebrae can be vertebrae from XXVIII to XXXI, and in general the human spine can consist of 32-35 vertebrae; in the case of extreme elongation of the spine, there are 36 or even 37 vertebrae. Numerical variations of the vertebrae cannot be considered as a random phenomenon, depending on various random deviations in development, but as a phylogenetic phenomenon. For a relatively long time, the coherent hypothesis of Rosenberg, based on data from comparative anatomy, embryology, and easily explaining all such deviations, prevailed on this issue. Rosenberg claims that in a human embryo, the XXX vertebra is usually laid down as the sacral vertebra, the XXV as the last lumbar, and the XX as the thoracic. In further development, the XXX vertebra loses its connection with the sacrum, the XXV connects with the sacrum, and the ribs of the XX vertebra disappear. Thus, in ontogeny, the sacrum approaches the head, and the lower end of the chest shortens. Based on the cited data and facts of comparative anatomy of anthropoid and lower monkeys, Rosenberg claims that such changes also occurred during phylogenetic development. Therefore, he classifies vertebrates in which the sacrum is located low and the lower border of the chest lies low as primitive, atavistic forms, and those with a high-standing sacrum and a high chest as forms of the future, progressive ones. Furthermore, Rosenberg notes that in a human embryo, an independent pair of ribs is laid down at Cvii and that this pair of ribs loses its independence, and thus, in the period of ontogeny, the upper end of the chest also shortens. Based on this, he claims that the same reduction occurred during phylogenetic development, and this reduction did not stop at the Cvii ribs, but is beginning to affect at the present time also the Cviii (Di) ribs. Thus, according to Rosenberg, the chest decreases from both sides during ontogeny; the same reduction, in his opinion, occurred during phylogeny; now it is beginning to spread further to the ribs of the VIII and XIX vertebrae. Rosenberg considers the process in question to be finite and does not assume a significant shortening of the spine, because in his opinion the loss of individual vertebrae is compensated by the growth in height of the vertebral bodies. Rosenberg's hypothesis, which satisfactorily explains all numerical variations of the vertebrae, was initially accepted by the majority, being a useful working hypothesis for many studies, which even its opponents acknowledge. Over time, the number of voices denying the correctness of this hypothesis has increased, and a whole series of authors (Peterson, Bardeen, Dwight, Fischel) have spoken out against it, some on the basis of theoretical reasoning, others on the basis of their embryological studies. More than half a century has passed, the hypothesis has withstood the harshest criticism, but even now it cannot be considered refuted; only its application should be somewhat narrowed and limited to primates, and its dogmatism should be eliminated. Of course, all observed variations in the spine cannot be explained by phylogenetic processes alone, but one should also take into account the diverse functions and adaptations that different sections of the spine experience during the period of ontogeny. Among other anomalies, one should mention the fusion of Ci to a greater or lesser extent with the skull, as well as the fusion of individual vertebrae with each other—congenital synostoses of the spine (see below). On the lower surface of the occipital bone, anterior to the foramen magnum, bone protrusions of various shapes are often encountered, which are nothing more than various stages of the manifestation of the last occipital vertebra (manifestatio vertebrae occipitalis), indicating the origin of the occipital bone from the fusion of vertebrae. In some cases, it comes to the formation along the midline at the anterior edge of the foramen magnum of a more or less sharp protrusion, homologous to the anterior tubercle of the atlas. The manifestation of the occipital vertebra depends on the preservation by the occipital region of sclerogenic tissue, representing the remains of the hypochondral arch and corresponding in shape to Ci.
Ligamentous apparatus. Connections between the bodies, arches, and processes are distinguished. The connection between the vertebral bodies occurs by means of intervertebral discs (fibrocartilago intervertebralis), (Fig. 17). In the latter, the following are distinguished: 1) the fibrous ring (annulus fibrosus), located on the periphery of the disc and consisting of ring-shaped layers of fibrous cartilage, 2) the gelatinous nucleus (nucleus pulposus), consisting of a gelatinous soft mass of fibrous cartilage and overgrown remains of the notochord, 3) two thin plates of hyaline cartilage adjacent to the surfaces of the vertebral bodies. In an adult, the disc contains neither blood vessels nor nerves. The shape of the intervertebral disc corresponds to the vertebral bodies. In the cervical and lumbar sections, the cartilages are significantly higher in front than behind; this difference is especially great in the disc between the sacrum and the last lumbar vertebra. In total, there are 23 intervertebral discs in the spine; the last one is absent only between Ci and Cii, but it is present between Lv and Si; the total height of the intervertebral discs reaches up to 1/4 of the entire mobile part of the spine. With age, the height of the disc decreases, and this circumstance serves as the main reason for the decrease in height in old age. The connection between the vertebral bodies by means of the intervertebral cartilage is extremely strong; nevertheless, mutual movements of two adjacent vertebrae are possible in all directions due to the fact that the cartilaginous discs possess not only significant strength but also very high elasticity. The role of the disc here can be compared to a compressed spring or an air cushion. The magnitude of movements depends on the height of the discs—the smaller the surface of the vertebrae and the higher the discs, the greater the mobility. The discs are constantly under pressure of two kinds: internal, coming from the compressed gelatinous nucleus, and external from the pressure of the overlying parts; when the disc is dissected, the nucleus expands and prolapses. In cold water, it rapidly increases to four times its original volume. Congenital anomalies of the intervertebral discs consist mainly of improper development of the notochord; they do not give clinical symptoms and can be discovered only on a radiograph.

Besides the intervertebral discs, the vertebral bodies are connected by common ligaments—the anterior and posterior. The anterior longitudinal ligament (lig. longitudinale anterius) extends from the base of the occipital bone to the sacral vertebrae (Fig. 18). The deep fibers of this ligament con-
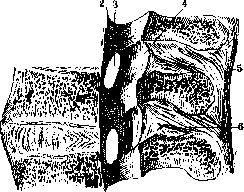
Figure 18. Connection of the vertebrae in the lumbar region, view from the left in cross-section: 1-lig. longitudinale ant.; 2-lig. longitudinale post.; 3-for. intervertebrale; 4-lig. flavum; 5-lig. supraspinale; 6-lig. interspinale.
connect only adjacent vertebrae, while the superficial ones pass over 4-5 vertebrae; downwards the entire ligament becomes wider and thicker. This ligament is firmly connected to the bodies of the vertebrae, and it only passes over the intervertebral discs, without entering into close connection with them. In the region of SI and SII, the ligament thins out and transitions into the periosteum. The posterior longitudinal ligament (lig. longitudinale posterius) is located along the posterior surface of the vertebral bodies, facing the cavity of the vertebral canal. The ligament is less developed compared to the anterior one and is wider at the top than at the bottom, extending from the skull to the sacrum. Along its length, the ligament is tightly connected to the edges of the vertebral bodies and to the intervertebral discs, while in the middle of the bodies the ligament narrows and moves away, due to which a space is formed under it, occupied by venous plexuses. Due to the bilateral alternation of narrowing and widening, the ligament takes on the appearance of a double-sided saw. The vertebral arches are connected by strong inter-arch ligaments, or yellow ligaments (lig. intercruralia, s. flava). These ligaments consist almost entirely of elastic fibers, which give them a yellowish color; the middle part of the ligament is the thickest. When the Spine is flexed, the yellow ligaments tense and stretch, and then return to their previous state, always maintaining their smooth surface. The transverse processes are connected by relatively weak intertransverse ligaments (lig. intertransversalia); in the lumbar region they are stronger, in the thoracic region they consist of thin plates closely connected with the musculature, in the neck they are formed by thin, few fibers, sometimes they are completely absent here. The spinous processes are connected by interspinous ligaments (lig. interspinalia), filling the spaces between adjacent spinous processes and consisting mainly of collagen fibers with an admixture of a small amount of elastic fibers; in the lumbar region these ligaments are strongly developed. At the tips of the spinous processes, these ligaments transition into a continuous round cord, the supraspinous ligament of the spine (lig. supraspinale, s. apicum). In the neck, the lig. supraspinale expands into the nuchal ligament (lig. nuchae), which extends from the spinous process of CVII to the external occipital protuberance; strong bundles depart from each spinous process into it, weaving into the general mass. In animals, the nuchal ligament reaches powerful development and consists mainly of elastic fibers, whereas in humans it represents a thin fascial plate, which is a septum between the muscles of the nape on one side and the other. The articular processes of two adjacent vertebrae are connected by joints (articulationes intervertebrales); their capsule, which attaches along the edge of the articular cartilage, is very weak in the cervical vertebrae, but thicker in the lumbar region; the joints are immobile and should be classified as amphiarthroses. Lumbosacral connection. The last V lumbar vertebra connects to the sacrum according to the type of all free vertebrae: the intervertebral cartilage here is significantly higher in front than behind, the amphiarthroses do not present any peculiarities, all private and general ligaments are present, analogous to the overlying vertebrae. The sacrococcygeal connection belongs to the type of synchondroses, but with the peculiarity that in the cartilage there is a cavity in most cases. The horns of the sacrum and coccyx are connected by means of a paired sacrococcygeal ligament (lig. sacro-coccygeum articulare), which corresponds to the amphiarthrosis of the overlying vertebrae. From the lower end of the lateral sacral crest to the vertebral process of CoI goes a paired ligament (lig. sacro-coccygeum lat.). The listed ligaments are quite often absent. A continuation of the anterior longitudinal ligament is the lig. sacro-coccygeum anterius, consisting of two crossing bundles running along the anterior surface of the sacrum and coccyx. A continuation of the posterior longitudinal ligament is the lig. sacro-coccygeum posterius profundum, running along the posterior surface of the body of SV and CoI. In addition, from the edges of the sacral hiatus, closing this opening, goes the lig. sacro-coccygeum posterius superficiale, corresponding to the yellow ligament. Cranio-vertebral ligamentous apparatus. The connection of CI and CII with each other and the connection between CI and the occipital bone are mobile connections, forming two joints: the upper head joint between the atlas and the occipital bone and the lower head joint (Fick) between the atlas and the epistropheus. The upper head joint is combined from two paired joints between the articular processes of the occipital bone and the articular fossae of the atlas - atlanto-occipital joints (articulationes atlanto-occipitales). By the shape of the articular surfaces, they can be classified as ellipsoid joints with two mutually perpendicular axes of movement. The longitudinal dimensions of the articular processes of the occipital bone and the articular cavities of the atlas converge anteriorly, and the anterior ends of the opposite sides are 21-25 mm apart, while the posterior ones are 30-34 mm apart. The articular capsule is weakly stretched, starting along the edge of the articular surfaces. Various individual differences in the shape of the articular surfaces are observed. There is often a bifurcation of the articular surfaces into a larger anterior and a smaller posterior segment. Their shape can be either wide and low, or narrow and high. Complete symmetry in the shape of the articular surfaces is rarely observed, the right one is mostly flat and low, and the left one is high and narrow. The gaps between the occipital bone and the atlas behind and in front are covered by fibrous membranes. The anterior atlanto-occipital membrane (membrana atlanto-occipitalis ant.) starts from the upper edge of the anterior arch and goes to the lower surface of the body of the occipital bone; in the middle, it is reinforced by the anterior longitudinal ligament. The posterior atlanto-occipital membrane (membrana atlanto-occipitalis post.) starts from the posterior arch of the atlas and goes to the posterior edge of the foramen magnum; this membrane is thinner than the anterior one. The described membranes are quite strong plates containing not only collagen fibers but also a significant amount of elastic ones. Due to the presence of the described membranes, the wide gaps between the atlas and the occipital bone are completely closed, and only on the side does an opening remain for the passage of the vertebral artery and nerve trunks. The lower head joint is combined from four joints between the first and second vertebrae (articulationes atlanto-epistrophicae). Of these four joints, two lateral paired ones are formed between the lower articular surface of the atlas and the upper articular surface of the epistropheus. The articular capsules are wide and weakly stretched. Two joints are at the odontoid process: one, anterior, between the articular surface of the odontoid process and the anterior arch of the atlas, the second, posterior, between the odontoid process and the transverse ligament of the atlas. The capsular ligaments of these joints are very thin, giving off sac-like protrusions to the sides, which can connect the anterior and posterior joints with each other, as well as connect the latter with the lateral joints. Auxiliary ligaments of these joints are: 1) the apical ligament of the odontoid process (lig. apicis dentis), stretched between the upper end of the odontoid process and the middle of the anterior edge of the foramen magnum. This ligament corresponds to the nucleus pulposus of the intervertebral disc and the notochord originally passed through it. This ligament is extremely weak and has no mechanical significance. 2) Alar ligaments (lig. alaria), two paired ligaments running from the apex of the odontoid process to the sides and upwards to the medial edge of the articular processes of the occipital bone and the lateral edges of the foramen magnum. 3) Transverse ligament of the atlas (lig. transversum atlantis) connects the lateral masses of the atlas behind the odontoid process. This ligament is very strong, it is wider in the middle, and on the surface facing the odontoid process, it is covered with cartilage. 4) Tectorial membrane (membrana tectoria) is a dense plate covering the cruciate ligament from behind and running from the clivus to the body of the epistropheus; downwards it continues into the posterior longitudinal ligament. The upper and lower head joints are very complex mechanisms that facilitate the most diverse movements of the head. The upper one (articulatio atlanto-occipitalis) is a combined ellipsoid one, in which movements occur along two axes. Around the main transverse axis, flexion of the head forward and backward occurs, around the second additional sagittal axis, insignificant flexion of the head to one side or the other occurs. The lower head joint (articulatio atlanto-epistrophica) represents a combined, rotational joint consisting of 4 joints - two on the sides and two in front and behind the odontoid process. The vertical axis of this joint passes through the odontoid process. Both articular surfaces in the lateral joints are incongruent, convex, which is why they touch each other not with their entire surface, but only with the middle part. Due to this, during rotational movements of the head, screw movements also occur in them simultaneously (Henke). When the head rotates, the atlas plays the role of only an intercalated meniscus, and the movements occur exclusively in the lower head joint.
Both head joints—the upper and lower—should be considered mechanically as one combined joint with three axes of movement, i.e., as arthrodia (H. Meyer). Statics and mechanics of the spine. When analyzing the mechanism of the vertebral column, it is necessary to distinguish two main parts, the combined actions of which result in those complex and diverse movements that are possible in the spine. The first mechanical part consists of a column formed by the vertebral bodies, connected by intervertebral cartilages and the anterior and posterior longitudinal ligaments; this column, with the arches sawed off, is a very flexible, elastic rod, allowing for the most extensive and extremely diverse movements in all directions. The strength of this rod is so great that it allows for the removal of 3-7 vertebral arches with impunity, as is done during laminectomy. Even the removal of arches in the cervical region does not disrupt the function of the spine. There are no sufficient grounds to fear that the spinal cord will lose its bony protection and that the mechanism of the spine will be disrupted. The second mechanical part, which strengthens and restrains the movements of the rod, consists of vertebral arches connected to each other by strong ligaments (lig. flava) and joints. The row of arches, or the articulated arch plate, as it can be called, not only strengthens the vertebral rod but also limits its movements and directs them along strictly defined lines. The musculature surrounding the arch plate and having the most diverse points of attachment not only strengthens the spine but also gives it certain shapes and determines the paths along which movements occur within it. Both mechanical parts—the vertebral rod and the arch plate—are extremely firmly connected to each other, forming a single whole that has equal resistance to fracture in all its parts. This explains why dislocations of the vertebrae in their pure form, without bone fractures, are observed extremely rarely, and then primarily in the cervical, most mobile region. In general, the vertebral column is built according to a spiral system having multiple curvatures. In the lumbar region, there is a convexity forward, followed by the concavity of the thoracic part, then again the convexity of the cervical region; from below, the concavity of the sacrum and coccyx is attached. Thus, we have four curvatures in the spine: two facing with convexity forward and two backward. These curvatures are clearly visible when examining the spine from the side and stand out distinctly in the straightened, so-called military position. In this position, one can spend whole hours experiencing little fatigue, since muscular force is almost not expended; a perpendicular line dropped in such a position from the anterior tubercle of the atlas passes through the body of CVI, DX, SI and exits through the tip of the coccyx. With a slouching posture, the curvature in the thoracic region increases, while in the cervical and lumbar regions it decreases; in old age, the curvature in the thoracic region increases especially. The indicated curvatures of the spine exist, however, not only in the vertical position but also in the horizontal, when lying down; the bends, admittedly, decrease, but by no means disappear. In the human embryo, the shape of the spine has a great resemblance to the shape of the spine of quadrupeds, in which the ventral bend of the lumbar region and the promontory (promontorium) are absent. In the newborn, the bends are barely outlined; only with further growth and under the influence of repeated exercises do the typical adult bends gradually develop, the degree of which is subject to individual variations. Thus, by the 8th week, the cervical curvature appears more or less clearly; in the second half of the first year, the thoracic curvature is clearly expressed; the lumbar curvature becomes noticeable later than the others (at the beginning of the second year, when the child begins to walk; Gundobin). Two factors undoubtedly play a role in the formation of the spine: heredity and mechanical adaptation acquired through experience. Besides the bends in the sagittal plane, bends are also noted in the frontal plane, mainly the curvature of the thoracic part of the spine to the right. But it should be noted that the curvature to the right represents only one link in a whole system of curvatures in the frontal plane, connected together with the sagittal curvatures into a single whole (Hasse). Sometimes a curvature of the thoracic region is observed not to the right, but to the left. The height of the spine as a spiral does not have a constant value, but depends on the load. In an adult male, the average height of the spine is 70-73 cm, in a female 66-69 cm, and with a height of 73 cm, the cervical region accounts for 13 cm, the thoracic for 30 cm, the lumbar for 18 cm, and the sacrococcygeal for 12 cm. In the fetus and infants, the vertebral column is relatively longer, but then, compared to the limbs, it lags in growth. The spine reaches its final height in different peoples and in different sexes at different times: from 23 to 25 years. Women reach maximum height a year earlier, although this is not observed in all peoples. In the elderly, the length of the spine decreases, and sometimes this decrease reaches 7 cm. The height of the spine, besides individual differences, depends on its loading or release from weights; in the first case, the bends become sharper and increase, in the second they decrease, and the length of the spine, conversely, increases. If the loading lasted for a long time, the intervertebral cartilages are compressed, although each of them to an insignificant degree, and during a prolonged vertical position of the body, the spine becomes shorter. This explains the difference in the height of the spine in the morning and evening, which sometimes reaches up to 2.0-2.5 cm, as well as the increase in height after a prolonged disease, when the patient was in bed for a long time. The movements of the spine occur around three axes: frontal, sagittal, and vertical. Around the frontal axis, flexion and extension of the spine occur; the former is the most extensive movement; this movement is not uniform in all parts of the spine: in the cervical part it is more extensive, in the lumbar somewhat less, and the thoracic part is the least mobile. Around the sagittal axis, lateral flexion occurs; these movements are most possible at the border between the lumbar and thoracic parts. Around the vertical axis, rotation occurs, which is most extensive in the cervical region and almost impossible in the lumbar. To these movements is added the so-called spring movement, during which the magnitude of the spine's bends changes, e.g., during jumping. Thus, the cervical region is the most mobile, followed by the lumbar; the thoracic region is less mobile. The magnitude of movements in various directions depends mainly on the thickness of the intervertebral cartilages, as well as on the strength and extensibility of the ligaments and articular capsules; the articular surfaces of the articular processes allow movements only in certain directions. The middle part of the spine is connected to the ribs, which connect in front to the sternum and form the thoracic cage as a whole; thanks to these connections, which significantly restrain movements in the spine, the thoracic region is the least mobile. A rib connects to the spine at two points: its head connects to the vertebral body, and the rib tubercle to the transverse process. The joint between the head of the rib and the body (articulatio capitulae) is formed by the articular surface of the rib head and the articular fossae of the vertebral bodies, and from DII to DX, the rib head connects to two adjacent vertebral bodies. The cavity in these joints is partitioned by an interarticular ligament (lig. capituli costae interarticulare), extending from the crest of the rib head to the intervertebral cartilage; this ligament divides the joint cavity into two compartments. The articular capsule is thin and reinforced anteriorly by rather thick fibrous bundles, radiating from the rib head to the bodies of two adjacent vertebrae and to the intervertebral cartilage (lig. capituli costae radiatum). The joints of the first and the last two ribs have a single cavity, and their heads connect only to the corresponding vertebrae. The joint of the rib tubercle with the transverse process (articulatio costo-transversaria) exists only for the 10 upper ribs. The joint capsule is thin and is reinforced posteriorly by thick bundles of fibers extending from the tip of the transverse process to the rib tubercle (lig. tuberculi costae). In addition, there are short, strong fibers extending from the neck of the rib to the corresponding transverse process (lig. colli costae). Two comparatively weak ligaments (lig. costo-transversarium anterius et posterius), extending from the upper edge of the rib neck to the overlying transverse process, complete the ligamentous apparatus. The muscles of the spine are located mainly in a mass on its posterior surface; on the anterior surface, there are only individual representatives, and only in the cervical and lumbar regions, while in the thoracic region they are completely absent. On the posterior surface of the spine, there is a powerful muscular layer consisting of extremely diverse muscular systems, with broad muscles belonging to the shoulder girdle lying in the superficial layers of this layer, and long muscles located in the deep layers in such an order—the deeper they lie, the shorter they are. Despite the extreme diversity of the muscles, their arrangement testifies to their metameric structure. The arteries of the spine, running both along its walls and in adjacent parts, are in general insignificant. In the thoracic region, they originate from the intercostal arteries, each of which divides into a ramus anterior and a ramus posterior.
The posterior branch, passing backward into the opening between the vertebra and the anterior costotransverse ligament, divides into two branches: the muscular branch and the spinal branch. The first of these, the muscular one, supplies the muscles and skin of the back, while the second penetrates through the intervertebral foramen into the vertebral canal and with its twigs forms arterial networks that nourish the bony walls of the vertebral canal, the meninges, and the spinal cord itself. The branching of the posterior twigs in the lumbar region (originating from the lumbar arteries) and in the cervical region (from the vertebral arteries) is similar. In the lower part of the neck, twigs from the ascending cervical artery (from the thyrocervical trunk) and from the deep cervical artery (from the costocervical trunk) participate in the blood supply of the Spine. In the lumbar region, twigs of the iliolumbar artery (from the hypogastric artery), the median sacral artery, and the lateral sacral arteries (the first from the aorta and the latter from the hypogastric artery) participate. The veins of the Spine represent dense vascular plexuses located both inside and outside along the entire length of the Spine (Fig. 19). Exter-
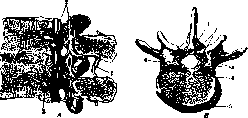
Figure 19. Venous plexus. A—median section from the left: 1—posterior vertebral venous plexus; 2—internal vertebral venous plexus; 3—basivertebral vein; B—horizontal section from above: 1—posterior vertebral venous plexus; 2—vertebral venous network; 3—internal vertebral venous plexus; 4—basivertebral vein; 5—anterior vertebral venous plexus; 6—intervertebral vein.
nal venous plexuses (plexus venosi vertebrales externi) are divided into anterior and posterior; they anastomose with each other. In the occipital region, the posterior external venous plexuses (plexus venosi vertebrales externi) reach powerful development and connect with the venous sinuses of the brain and with the external veins of the skull. The internal venous plexuses also divide into anterior and posterior, anastomosing with each other. The anterior internal venous plexuses (plexus venosi vertebrales interni ant.) consist of two venous sinuses (sinus venosi vertebrales longitudinales), representing venous plexuses lying on the posterior surface of the vertebral bodies on both sides of the posterior longitudinal ligament of the Spine. Into the anterior venous sinuses of both sides flow the veins of the vertebral bodies (vv. basivertebrales), running inside the vertebral bodies, in the canals of the spongy substance. The posterior internal venous plexuses (plexus venosi vertebrales interni post.) represent two venous sinuses (sinus vertebrales longitudinales) descending from top to bottom along both sides of the vertebral arches. Both the anterior two plexuses and the two posterior ones are connected by anastomoses, forming venous rings at the level of each vertebra. The entire plexus of the vertebral canal lies between the layers of the dura mater (if one considers the periosteum of the vertebrae as the outer layer of the dura mater). The blood flow from both the internal and external venous plexuses has mainly a horizontal direction and reaches at the level of each vertebra the vertebral, azygos, and hemiazygos veins (through the intercostal and lumbar veins), and the hypogastric veins (through the lateral sacral and iliolumbar veins). The lymph vessels of the Spine are directed to the intercostal lymph nodes lying in the region of the rib heads, forming plexuses here; the efferent vessels of these plexuses are directed into the thoracic duct. Cruikshank was the first to see lymph vessels emerging from the bodies of the thoracic vertebrae, which was then confirmed by Sömmerring and Bonomy. The efferent vessels of the upper intercostal nodes on the right side are directed into the right bronchomediastinal trunk. In the lumbar and sacral regions, the intercostal nodes are replaced by lumbar and sacral lymph nodes; their efferent vessels are directed into the sacral lymphatic plexus, and then into the aortic plexus, which pours its lymph into the lumbar lymphatic trunks, which are on each side the roots of the thoracic duct. In the cervical part, the lymph vessels of the Spine go to the superior and inferior deep cervical lymph nodes. N. Bushmakin. III. Methods of examination. Anatomical changes associated with a disturbance of the external form of the Spine lead, as a rule, to a limitation of mobility, and often to spinal cord disorders; on the other hand, functional disorders very often make it possible to judge such pathological-anatomical changes of the Spine that at the given moment are not reflected in its external form. Therefore, in the clinical examination of the Spine, it is necessary to take into account the form, mobility, and spinal cord phenomena. In contrast to the normal (Fig. 20) form of the Spine (see above)
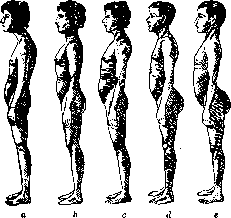
Figure 20. Types of posture according to Haglund: a—round back; b—normal posture; c–e—changes in posture depending on the tilt of the pelvis.
in the elderly, thoracic kyphosis increases, lumbar lordosis decreases, and mobility is sharply limited. But even in the young, the strengthening of normal thoracic kyphosis sometimes reaches the degree of the so-called "round back" (dorsum rotundum) — a painless, uniform, arcuate kyphosis of the interscapular region without any pathological changes (Fig. 21). On the other hand, there may be the opposite variant — a decrease or flattening of the normal thoracic kyphosis, a flat back (dorsum planum). These variants depend, on the one hand, on certain skeletal features, in particular the tilt of the pelvis and the structure of the sacrolumbar region, and on the other hand, on the degree of muscle tone, and determine the so-called posture of a person. Examination of the Spine begins with observing the patient's behavior and movements. An unnatural position of the trunk and head, tension, stiffness of movements, and gait disturbance speak of functional disorders, so often associated with anatomical changes of the Spine. A general inspection allows one to judge the posture, the proportionality of anatomical relationships, or disproportions in them. When examining the back in profile, one establishes the physiological curves, their greater or lesser prominence and uniformity, as well as deformational changes of the Spine — angular and arcuate kyphoses, increased or corrected lordoses, and deformities of the chest. From behind, lateral scoliotic curvatures of the spine, asymmetric positioning of the shoulder blades, pelvis, and rib deformity are determined.
Palpation — feeling the line of the Spine — clarifies the data of the inspection of the external form and reveals hidden deformities. Determining the abnormal protrusion of individual spinous processes is best done with the Spine bent, with arms crossed on the chest, by running the tip of the middle finger (with the index and ring fingers on the sides) along the line of the spinous processes, moving from bottom to top (in this case, the finger "stumbles" on every protrusion (Broca)), or by running the ball of the palm along the Spine (Turner). The counting of vertebrae is performed from the most protruding spinous process CVII, but one must keep in mind the indication of Menard that in children DI protrudes more. One can count from top to bottom from CII or from bottom to top from LV ("tubercle in the fossa"), and also use reference lines connecting the lower ends of the shoulder blades (at DVII) or the upper edges of the iliac crests (at LIV); in thin people, DXII can be determined by the last rib. During such an examination, the number of vertebrae involved in the pathological process, the apex of the curvature, as well as its boundaries, defects of the spinous processes, and asymmetric positioning of the transverse processes are determined. With the help of palpation, the sensitivity of the Spine is examined, which is more sharply manifested when tapping on the spinous processes with the tip of a finger or a percussion hammer, as well as when displacing-wiggling the spinous processes, grasped from the sides with two fingers, or with careful tapping with a fist. Examination of the mobility of the Spine is performed along three axes in relation to flexion-extension, lateral inclinations, and rotations around the axis (torsio). The examination begins with determining the mobility of the head: in normal conditions, during maximum flexion, the chin rests on the chest, and during extension, the head is thrown back so that the occipito-mental line forms an angle with the vertical, open anteriorly; when tilting to the side, the ear almost touches the corresponding shoulder, and rotations to the right and left are possible almost to the frontal plane. Then the mobility of the trunk is determined: during flexion, occurring mainly at the expense of the boundary regions
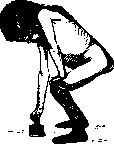
of the cervicothoracic and thoracolumbar [junctions], kyphosis increases sharply and lordoses are corrected. Upon extension, the thoracic part straightens and the lumbar and cervical lordoses increase sharply; with normal lateral mobility, bending the torso to the side is possible until the false ribs touch the iliac crest, and rotation around the axis is possible until the arms, spread out horizontally, are moved from the frontal plane to the sagittal plane without rotating the pelvis. When picking up an object from the floor, a subject with normal function of the spine bends downward evenly, flexing the back and freely extending it; in pathological states, however, especially with muscle contractures, patients spare the spine, do not bend (Fig. 22), but squat, bending the knees and hip joints, supporting themselves with their hands on their thighs; likewise, when extending, patients spare the spine and, as it were, climb up their thighs with their hands, lifting the rigid torso; this symptom is especially important in inflammatory diseases and lumbar pain. Examination of mobility can also be performed in the prone position, both to determine flexion by placing hands under the abdomen and lifting the patient, and mainly for extension and determining lateral mobility by placing one hand on the middle of the back and lifting the head end of the torso with the other hand in cases of lesions of the upper section, or the foot end (by the legs) in cases of lesions of the lower section. Normally, the physiological kyphosis is corrected and the lordoses are increased (Fig. 23); in pathological states, the affected area remains immobile (Fig. 24). During these examinations, muscle tension, rigidity, and the degree of pain of these movements in the region of one or another section of the spine are also simultaneously determined. Finally, the degree of endurance of the vertebral column and the tenderness of its individual segments are determined by so-called dynamic loading, which is performed either by pressure on the shoulders and head, or by cautious tapping with a fist on the back of the examiner's hand placed on the patient's crown, or by the jolt resulting from lifting the patient onto their toes and quickly dropping them onto their heels. Measurements of the spine are most easily performed by the Kirchhoff method, based on measurements in centimeters of the levels of curvatures (deformities) and the distances of maximum deviations of various sections of the spine (lumbar and cervical lordoses) from the vertical passing through the rearmost point of the torso (from a centimeter tape with a weight, suspended from a collar and moved backward to the apex of the kyphotic curvature) (Fig. 25). The same method is used to determine lateral curvatures
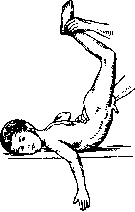
Figure 23. Normal mobility.
, their height and distance from the midline of the body. However, this method is not sufficiently accurate. Graphic methods are of greater importance. Sketching the shape of the spine is performed in the prone position using a thick lead wire, a probe, or a lead strip the width of a finger, which are placed on the spine, well-modeled on it, and carefully transferred to paper (the patient's history), where the contours are traced with a pencil. The sketch is made from the occipital protuberance to the coccyx with a mark at the level of LIV and SII. Such sketches are made repeatedly during the course of the disease. To measure the mobility of the spine, two sketches are produced: during maximum flexion, by placing a pillow under the abdomen, and during maximum extension—lordosis, by placing bolsters under the clavicles and thighs (Pitzen). Figure 24. Rigidity of the spine.


can be achieved with plaster casts: longitudinal strips for determining anteroposterior curvatures and transverse ones for lateral ones, or rather for changes in the chest associated with lateral curvatures. To sketch lateral curvatures, one can also use a simple window pane in a frame placed against the back of a seated patient—a direct sketch with a wax pencil (Lange). The most important condition for all these measurements and sketches is the constancy of the position of the subject, as changes in position make the measurements incomparable. In all these examinations, one should also keep in mind spinal cord disorders, which are closely related to the state of the spine and are often early, and in some cases the first and only signs of diseases and injuries of the spine. This applies to all three functions of the spinal cord—motor, sensory
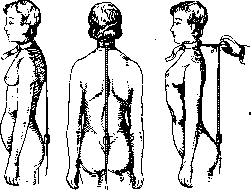
Figure 25.
and trophic in their various combinations. Radicular phenomena—girdle and shooting pseudoneuralgic pains, increased tendon reflexes, muscle tone reaching the degree of spastic phenomena, increasing weakness of the limbs—paresis and paralysis, changes in sensitivity both in the direction of its increase and decrease, disorder of the function of the pelvic organs—retention and incontinence, as well as trophic disorders—bedsores, trophic ulcers, etc.—this is the range of spinal cord disorders that must be taken into account when assessing the state of the spine. X-ray diagnostics is the most important and necessary auxiliary method for examining the spine. With X-ray images, not only changes in the bones are determined, but also processes in the soft tissues (e.g., abscesses) that complicate bone foci. An X-ray, being the most valuable objective indicator of the anatomical state of the spine, can, with incorrect production technique and incorrect interpretation, be a source of gross diagnostic errors that obscure the clarity of the clinical picture. One cannot make a diagnosis and give a conclusion based only on X-ray data, which should only supplement clinical examinations. In order for an X-ray to truly clarify and deepen the data of a clinical examination and reveal what is inaccessible to our eye or touch, it must first of all be technically high-quality and clear. It is necessary in principle to strive for images in two projections, because in many cases only profile images reveal changes in the bones, especially in the anterior parts of the vertebral bodies. In children, lateral images can be obtained in all sections; in adults, it is significantly more difficult in the thoracic section and relatively easier in the lumbar and cervical sections. Reading X-rays of the spine should be performed in a certain sequence, according to a certain system, moving from a general overview of the spine to the relationship and shape of individual vertebrae and intervertebral cartilages and ending with a detailed assessment of the bone structure. When studying X-rays, one must take into account both gross changes in the shape of the vertebrae and their integrity, as well as detailed signs: 1) the substance of the bone itself—its density, pattern, and clarity of contours, 2) focal changes in the bone—cavities, sequestra, etc., 3) contact changes between vertebrae—gaps, their shape, erosion of discs and joints, 4) lateral contours—deposits, growths, bone defects. X-ray conclusions should be accompanied by a determination of the exact localization of the image site and lesions, as well as compliance with normal anatomical structure. It must be remembered that only more significant changes in the spine are revealed on an X-ray, that in most diseases X-ray changes lag behind clinical symptoms, and that processes of different etiologies can give an approximately identical picture. Finally, for a correct assessment of pathological states, it is also necessary to take into account biological reactions (blood morphology, erythrocyte sedimentation rate, specific reactions, etc.), which are of particularly great importance in the absence or insufficiency of X-ray data, especially in inflammatory diseases, for establishing an early diagnosis or judging the subsidence of the process. Clinical examinations should be supplemented by two auxiliary equivalent methods—radiological and laboratory.
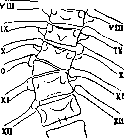
Figure 26. IV. Pathology of the Spine. Developmental defects and congenital deformities of the spine. Congenital developmental defects of the spine can manifest in changes in the number, shape, and connection of the vertebrae to each other, as well as their connection to other bones—the skull, pelvis, and ribs. A change in the number of vertebrae, as mentioned above, is observed extremely rarely. More common are inclusions of incomplete, so-called wedge-shaped vertebrae (Fig. 26), or rather hemivertebrae, which are the cause of congenital scoliosis [see separate plate (pp. 135-136), Figs. 1 and 2], which differ from static and rachitic scoliosis by a relatively small angular flexion without rotation around the axis, which gives them some resemblance to scoliosis of tubercular origin. Congenital complete bony fusions between normal vertebrae—true synostoses—are almost never encountered or are encountered as exceptions. Asymmetric synostoses with wedge-shaped and underdeveloped vertebrae are observed more often—single or multiple. - The disease, or Klippel-Feil syndrome (Klippel, Feil) (Fig. 27), is characterized by multiple synostoses of the lower cervical and sometimes upper thoracic vertebrae, which merge into one shapeless bony mass and are accompanied by various developmental defects: wedge-shaped inclusions, cleft arches, etc. Clinically, this deformity manifests as a sharp shortening or disappearance of the neck ("frog neck") and is accompanied by kyphoscoliotic curvatures, a sharp restriction of the mobility of the upper part of the spine, and often asymmetric positioning of the scapulae. In rare cases, this deformity can be accompanied by spinal cord and radicular disorders. In terms of differential diagnosis, this developmental defect is most often confused with cervical spondylitis, rachitic kyphoscoliosis, and other deformities, in particular with de-r 97 k
Sprengel's deformity, which is characterized by unilateral or bilateral high standing of the scapula and is accompanied by a whole series of changes in the ribs and spine, as is the Klippel-Feil syndrome. Changes in the shape of the vertebrae often depend on developmental defects in the posterior sections forming the spinal canal. Either complete splitting of the vertebral canal in the form of an open furrow-cleft (rachischisis) or partial non-fusion of the arches-spina bifida posterior-is observed. Longitudinal splitting can also be in the anterior sections of the spine-in the bodies, bearing the name spina bifida anterior (see Spina bifida). To the same category of developmental defects belongs a peculiar separation of the arches in the interarticular section-congenital interarticular spondylolysis (spondylolysis interarticularis congenita of Neugebauer), at the basis of which lies an incorrect development of the vertebra with the formation of two non-fusing ossification points instead of one in the area of the gap between the upper and lower articular processes standing obliquely one under the other. Spondylolysis itself does not cause special disorders, but it has decisive importance as a predisposing cause for anterior displacement of the fifth lumbar vertebra-slipping of the latter-spondylolisthesis (see). The diagnosis of all the listed changes is complex, as is the entire pathology of these so-called transitional sections of the spine in general, especially the lumbosacral one, the diverse developmental defects and deformities of which are distinguished under the general name of "dysplasias" of the lumbosacral section and are characterized by a decrease in the endurance of this section of the skeleton, a decrease in mobility, lumbosacral pains, lumbalgias, radiculitis, and other so-called myelodysplastic changes, about which we have already spoken above. If one takes into account that almost the same symptoms can accompany inflammatory diseases of the sacrolumbar section, as well as the nervous-muscular and rheumatic diseases so frequent here (see Lumbago), then the entire complexity of the pathology and diagnosis of these diseases becomes understandable. In this complex of dysplasias, the aforementioned sacralization has the greatest significance in terms of frequency and complexity of the picture. With true sacralization, a complete fusion of the body of the fifth lumbar vertebra with the sacrum and of the enlarged transverse processes with the iliac bones occurs. With the more frequent incomplete sacralization, various degrees of enlargement of the transverse processes of the fifth lumbar vertebra on one or both sides and their fusion with the iliac bones are observed. Painful symptoms are most often observed with incomplete sacralization, mostly after 20 years, i.e., after the end of the ossification process, more often in men. The onset of pain is often associated with heavy physical labor, an increase in load and mobility in the lumbosacral section. The appearance of pain caused by sacralization always lowers the working capacity of these patients, which, in case of treatment failure, leads to a change of profession or even disability. The diagnosis of sacralization is suspected upon the appearance of the indicated clinical symptoms and is established by X-ray examination, which reveals a decrease in the number of lumbar vertebrae due to an increase in sacral segments. The counting of vertebrae is best performed from the twelfth thoracic vertebra (one must remember the possibility of underdevelopment of the twelfth rib), for which the thoracolumbar part must also be captured on the image. Recognition is facilitated by comparison with the healthy side in case of unilateral sacralization. With complete fusion, the sacrum is projected higher accordingly, and the sacrolumbar articulation is determined on the line connecting the crests of the iliac bones, which is usually the boundary between the fourth and fifth lumbar vertebrae. It is necessary, however, to keep in mind that in this very section, the slightest inclination of the pelvis during the image or displacement of the X-ray tube changes the X-ray images so much that the same anatomical changes can give rise to diverse interpretations, which is why special caution is needed in interpreting these pictures. Lumbalization (lumbalisatio) is encountered less frequently; also, this congenital anomaly less frequently serves as a cause of painful symptoms. The latter also occur with an increase in load and as a manifestation of the reduced stability of the lumbosacral section in connection with its greater mobility. Usually, however, lumbalization is suspected by radiologists in those cases where two free lumbar vertebrae are discovered below the horizontal line connecting both crests of the iliac bones, and not one, as under normal conditions, in contrast to sacralization, where the sacrum rises to this line (Reinberg). It remains to mention also the frequently observed deformities of the body of the fifth lumbar vertebra, which are, on the one hand, a cause for the development of scoliotic changes (in some cases, conversely, scoliosis leads to a change in the fifth lumbar vertebra), and on the other-to dysplastic symptoms. All the listed bone dysplasias have only relative significance in the origin of the above-mentioned painful sensations, since, on the one hand, not every discovered bone change is accompanied by painful phenomena, and on the other-similar painful symptoms can occur even without any bone changes. Therefore, both the clinical diagnosis and the radiological interpretation of the images present great difficulties. As for the treatment of these dysplasias, it is divided into conservative-providing rest to the affected section with the use of physiotherapeutic procedures and a fixing corset-and operative-osteoplastic fixation of the sacroiliac section of the spine. Prevention of these diseases boils down to early recognition of congenital anomalies as predisposing causes and the elimination of moments that could cause failure of the spine. In particular, the correct choice of profession is of enormous importance. A change in the shape of the spinous processes, their lengthening or shortening, rarely causes painful phenomena by itself, but most often can give rise to diagnostic errors. Thus, excessive lengthening of the third cervical, seventh cervical, twelfth thoracic, and fourth and fifth lumbar vertebrae gives button-like protrusions of the corresponding spinous processes and serves as a reason for assuming tuberculous deformities, but the preservation of mobility, the absence of compensatory lordoses, and painlessness, especially during dynamic load, decide the matter. In rare cases, excessive lengthening of the processes serves as a reason for the operative removal of the latter. Acquired deformities on the basis of non-inflammatory changes of the spine. Regarding deformities developing on the basis of uneven loading of the vertebrae in the process of their growth and formation without disease of the vertebrae themselves-see Scoliosis, Lordosis, Kyphosis. Rickets is one of the frequent causes of this kind of deformity of the spine (Fig. 28) (see Rickets). Very rarely is a change in the spine observed also in osteomalacia. Juvenile kyphosis (kyphosis adolescentium), Scheuermann's disease (Scheuermann, May), has at its base a peculiar change in the apophyses of the vertebrae, entailing a change in the bodies of the vertebrae as well. This disease of the spine is analogous to a whole series of other osteochondropathies of juvenile age, affecting various epiphyseal or apophyseal formations and causing subsequent deformities of the developing bones (Perthes' disease, Schlatter's disease, etc.). In the vertebrae, the role of epiphyseal formations is carried by cartilaginous rings, in which ossification nuclei appear at the age of 10-12 years, determined on profile X-ray images in the form of small narrow wedge-shaped shadows at the upper and lower corner of the vertebral body with the base on the anterior longitudinal ligament [see Figure 29 and separate table (art. 135-133), Fig. 3]. By 18-20 years (somewhat earlier in women), the process of additional enchondral ossification ends, thanks to which the shape of the vertebral bodies turns from biconvex to biconcave. In juvenile kyphosis, the ossification nuclei loosen, fragment, their contours become unclear, sinuous, the regularity of the cartilaginous strip separating them from the surface of the vertebral bodies is disturbed, and then the bodies themselves begin to be involved-first in the form of a change in the contours of the upper and lower surface of the bodies, and then a kind of impression of the apophyseal shadows into the anterior part of the vertebra is obtained, which is compressed in this place; the structure of the bone becomes unclear and, in the end, wedge-shaped deformities of several vertebrae occur, usually 3-4, with maximum changes in the middle one. A characteristic feature of these changes is, in the presence of destructive changes...


Figure 28. Kyphoses in children: a-normal kyphosis in a 4-month-old child; b-rachitic kyphosis.
changes and irregularities of the contours of the bodies, the preservation of the intervertebral discs, which only rarely narrow, but usually widen (in contrast to tuberculous changes); furthermore, the pointed anterior corners of the wedge-shaped narrowed vertebral bodies extend forward in a lip-like manner, forming an irregular notch in the middle. The mid-thoracic vertebrae are predominantly affected (more often from VII to X). The process usually ends in 1–1.5 years and is observed in male adolescents from 15 to 17 years old and female from 12 to 14 years old, being 4 times more frequent in the former, which is placed in some dependence on excessive early physical exertion. The process is benign, without any general complications, has a cyclical course, but leaves behind a persistent deformity—a painless, uniform, arcuate kyphosis. This disease is considered rare and is accurately diagnosed exclusively on the basis of the characteristic X-ray picture of a profile image. Osteochondropathy of the vertebral body, Calvé's disease, is an even rarer disease and can be considered analogous to juvenile malacic changes of the tarsal and carpal bones (Morbus Köhler I, Morbus Kienböck). In children, a small hump forms with limited mobility of the Spine, painful upon pressure and percussion. On the X-ray image at the beginning of the disease it is deter-
Figure 29. Osteochondropathy of the vertebral apophyses: a—initial changes; b—height of the disease—destructive changes of the bodies; c—stage of recovery—wedge-shaped deformity of the bodies with extended anterior corners.
mined in the center of the body is a compact shadow. Subsequently, the vertebra flattens, narrows to 1/3–1/2 of its normal size, and slightly lengthens, extending anteriorly beyond the general line of the Spine. A characteristic feature is the widening of the intervertebral spaces. The prognosis is favorable; the vertebra slowly recovers. In diagnosis, one must keep in mind the equally rare congenital flattening of the vertebral body, "platyspondylia," and the so-called "ivory vertebrae" (vertèbres d'ivoire of French authors)—a sharp densification of the vertebral bodies with preservation of normal shape, sometimes observed in cancer metastases, primary sarcomas, and in some cases without clear etiology. Among the same rare diseases of the spine, determined mainly radiologically, one must include changes in the nuclei pulposi. The discs can undergo calcification, which is encountered quite rarely. In 200 images, Geist (E. Geist) found only one case of calcification. Quite often, partial prolapse of the disc is observed (according to Geist—in 38%), with the nucleus playing a predominant role. Most often, prolapse occurs in the lumbar or cervical region, singly or multiply. The cause of prolapse is damage to the cartilaginous disc or adjacent vertebral bodies from various painful processes or from direct trauma to the Spine in the form of small cracks or even fractures of the cartilaginous discs. Disc prolapse is of various sizes; sometimes the prolapsed part gradually fills the entire vertebral body; in the latter, a reaction may appear, expressed in the new formation of bone substance around the prolapsed part of the disc. Sometimes prolapse occurs into the spinal canal and leads to various kinds of disorders requiring surgical intervention. The prolapsed part of the disc either remains stationary, sometimes becoming vascularized and ossifying, or bone-like degeneration occurs. Disc prolapse is more often observed in strong men of athletic build. Symptoms of prolapse manifest under the load of weight on the Spine. This may also explain in adolescence lumbar 135
SPINE
pain, juvenile kyphosis. Slouching posture with a sharply pronounced poor physique may also depend on multiple disc herniations. Senile change consists of degeneration of the disc, as a result of which the latter becomes thinner. In various diseases of the spine—in spondylitis, osteomalacia, tuberculosis, osteomyelitis, syphilis, cancer—the intervertebral disc is usually involved in the pathological process. Upon damage to the cartilaginous shell of the intervertebral cartilage, the nucleus is extruded into the spongy part of the vertebra, depending on which, according to the data of Calvé and Galland, the following may develop: 1) hernia of the nucleus pulposus, which, in the opinion of these authors, is in all probability the main cause of juvenile kyphosis; 2) penetration of the cartilaginous nucleus into the middle of the vertebral body, when there is sharp osteoporosis of the latter; 3) displacement of the nucleus into the spinal canal during the formation of kyphosis, which is accompanied by compression of the spinal cord and paralysis; 4) deposition of lime in the thickness of the nucleus, determined on X-ray images. In generalized fibrous osteodystrophy of Recklinghausen (osteodystrophia fibrosa generalisata Recklinghauseni), along with characteristic changes in other bones, mainly the long ones, peculiar changes in the vertebrae are also observed with the formation of cyst-like defects, which on an X-ray image have the appearance of soap bubbles against the general background of transparent vertebrae, which usually retain their integrity, do not collapse, and do not lead to curvature. To the group of non-inflammatory diseases of the spine causing persistent rigidity or even complete immobility of the spine belong: 1) so-called deforming spondylitis (spondylitis deformans), which is more correctly called, by analogy with joint diseases, deforming spondylosis (see), and 2) ankylosing spondylarthritis (see separate table, fig. 4), or Marie's disease (see Marie's disease). Deforming spondylitis usually affects and fuses two or three vertebrae, whereas spondylarthritis gradually involves the entire spine and even the hip and shoulder joints. Ultimately, a true "stiffness" of the spine in a bent position occurs. Something similar, but to a lesser extent, is observed in senile changes of the spine. To the category of deforming spondylosis also belongs tabetic spondylopathy (see separate table, fig. 5), observed in the lumbar region in elderly people and entailing varying degrees of curvature, which are completely painless. Radiologically, combinations of severe deformities of the vertebrae with huge calcareous deposits enveloping them are determined. The diagnosis is facilitated by the presence of other symptoms of tabes. In rare cases, the same chaotic and atypical changes in the vertebrae can also occur with syringomyelia. Kümmell's disease (Kümmell), traumatic spondylitis (spondylitis traumatica), is a deforming process in the vertebra developing after a relatively mild injury without gross anatomical changes. At the basis of the disease lies a chronic non-inflammatory aseptic destructive process, and therefore this disease should be attributed to spondylosis, and not to spondylitis. This disease is observed in the majority of cases in men engaged in heavy physical labor and is characterized by three stages. The first stage—immediately after the injury, sharp pains, which gradually subside over 2–6 weeks; the second stage—a lucid interval, complete absence of any pathological phenomena—painful, functional, anatomical; it lasts from 2–6 weeks to 2–3 years, most often 6–8 months, after which the third stage ensues—a relapse of spontaneous pain, occurring gradually without a definite cause or after a minor repeated injury. Tenderness of the vertebra upon pressure and loading, limitation of mobility, muscle rigidity occur, and subsequently, the protrusion of one spinous process and a slight curvature of the spine appear. Radiologically, both in the first and in the second stage, no signs of a compression fracture or other changes are determined, and only in the third stage do typical changes appear—phenomena of softening of the vertebra, its wedge-shaped flattening without any focal changes; the contours remain clear and smooth, sometimes small bony outgrowths are observed, and in some cases, in the region of the anterior longitudinal ligament, longitudinal strips of calcification may appear. Most often, this disease is treated as tuberculous spondylitis, from which it is distinguished with difficulty on the basis of, mainly, X-ray data: the absence of narrowing or disappearance of intervertebral cartilages and contact changes in neighboring vertebrae, good contouring and the absence of erosion of the edges, the absence of shadows of cold abscesses. However, the indicated radiological and, in particular, clinical data are "very shaky and far from always convincing to exclude tuberculosis, in view of which long-term observation and biological control are required. In the same way, it is often difficult to distinguish this disease from a compression fracture of the spine, from which it differs first of all anamnestically—by the presence of the second lucid stage, although according to the observations of Kornev, a lucid interval can also occur with fractures. On profile X-ray images, fractures are determined from the very beginning, and fragments and triangular pieces are often visible, protruding from the anterior edge of the body and remaining in connection with the longitudinal ligament, which does not happen with the Kümmell form. The course is long with exacerbations, but in general, it is relatively favorable: large deformities and spinal cord disorders do not occur, the pain gradually begins to subside, but weakness of the back may remain. Treatment—rest, a supporting corset, in persistent cases—fixation of the spine. Injuries of the spine. Subcutaneous injuries of the spine are caused either by direct violence—a blow from behind, a fall on the back, or by indirect impact—longitudinal compression of the spine and its excessive violent movements during a fall or being crushed by a weight. Depending on the degree of damage and the anatomical changes caused by them in the spine, bruises, sprains, dislocations, and fractures are distinguished, both in isolated form and in various combinations. Bruises and sprains have relatively little significance, rarely causing serious consequences, whereas dislocations and fractures present a great danger, mainly depending on complications from the spinal cord, which in 2/3 of all cases
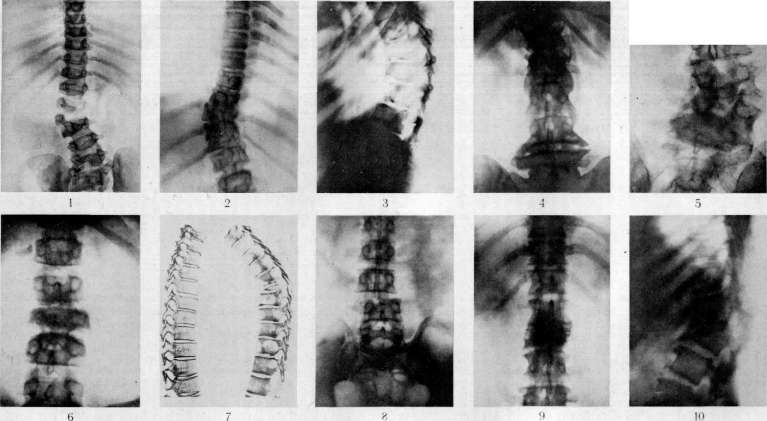
Figure 1 and 2. Congenital scoliosis due to accessory wedge-shaped vertebrae: fig. 1 between LIII and LIV; fig. 2 between DX and DXI with an accessory rib. Figure 3. Osteochondropathy of the vertebral apophyses (Scheuermann-Mau disease). Figure 4. Spondylosis of the lumbar region (spondylosis deformans and spondyloarthritis). Figure 5. Spondylopathy; tabetic changes of LIV and LV. Figure 6. Chronic osteomyelitis of the third lumbar vertebra. Figure 7. Tumor of the spine (on the right, cancerous metastases in the vertebrae; on the left, a normal spine). Figure 8. Dislocation of the third lumbar vertebra. Figures 9 and 10. Compression fracture of two vertebrae with breaking off of the anterior edge: fig. 9 en face; fig. 10 in profile
Regarding the spine: it is compressed or damaged. Fractures of the spine occur 10 times more often than dislocations, but in relation to fractures of all other bones, they constitute only 0.5%, and only depending on professional conditions does this percentage rise to 2% and higher, as is the case, for example, in mining regions and mines, where cave-ins, falls from a height, etc., are more often observed (observations by Wagner-Stolper in the mining regions of Upper Silesia, observations in the Donbas). Bruises (contusions) of the spine are caused by direct impacts and are characterized by damage to soft tissues and the surface of the bones without violating the integrity of the latter. Clinical phenomena—bruising, pain, partial limitation of mobility—are usually transient, but in some cases, bruises can cause a concussion of the spinal cord and even hemorrhage within it, which leads to spinal cord disorders, also mostly transient. Stronger bruises can lead to unrecognizable superficial fractures and apical avulsions in the processes, as well as cracks and hemorrhages in the bodies themselves, which may only subsequently manifest as nonspecific inflammatory changes, the so-called Kümmell's traumatic spondylitis (see above). Treatment: temporary rest, massage, unloading. Sprains (distortions) occur under the influence of excessive violent movements (flexion, extension, rotations), causing a rupture of the ligamentous apparatus of the spinal joints, but without persistent displacement, which is how they differ from dislocations, being, as it were, a preliminary stage of the latter. These injuries can also affect the intervertebral cartilages. Most often, distortions are observed in the same places as dislocations, i.e., in the cervical region, less often in the lumbar, and are accompanied by painful limitation of mobility and pain, which is especially severe in cases of incomplete ruptures (Kocher). It is not always easy to distinguish a distortion from a fracture without displacement. More severe injuries can be complicated by spinal cord phenomena, as with all other types of spinal injury. Treatment: rest, in some cases—light traction.
Dislocations of the vertebrae can be limited to only the lateral joints or be accompanied by displacement of the bodies themselves during fractures of the latter and damage to the intervertebral cartilaginous discs. Isolated dislocations of the lateral joints are observed almost exclusively in the cervical vertebrae and depend either on excessive rotation—rotational dislocations, usually unilateral, or on excessive flexion—flexion dislocations, usually bilateral. The upper vertebra is considered dislocated if its articular surfaces slide anteriorly and upward along the articular surfaces of the underlying spine. If the articular facet of the upper process shifts only to the anterior edge of the articular facet of the lower one, there is an incomplete dislocation, subluxation (subluxatio); if the upper process shifts beyond the anterior edge of the lower one, jumps over it, and catches in the notch in front of the articular process of the lower vertebra, then this is a true dislocation (luxatio). With a unilateral (Fig. 30) subluxation, due to oblique displacement forward and upward, i.e., the raising of the articular processes, an elongation of the affected side of the spine occurs, depending on which the head tilts to the opposite side, and with a dislocation, when the articular processes overlap each other, a shortening of this side occurs, and the head tilts to the affected side (Wagner). The spinous process of the upper dislocated vertebra rises, shifts slightly anteriorly, and deviates from the midline, while the transverse process protrudes on the side of the dislocation. At the same time, the head shifts slightly anteriorly, and movements become limited. With a bilateral dislocation, the head stands straight, without lateral bending, but tilts slightly, as if shifting anteriorly. The spinous process of the upper displaced vertebra also shifts anteriorly, without deviating to the sides, and the distance between the spinous processes increases. Bilateral dislocations (Fig. 31) are significantly more severe than unilateral ones and are rarely isolated; they are more often accompanied by displacement of the bodies themselves (complete dislocation according to Kocher's classification), which as a rule entails phenomena of compression of the spinal
Figure 30. Unilateral rotational dislocations: a - complete dislocation; b - incomplete dislocation.
Figure 31. Dislocations (a - normal position): b -
incomplete dislocation; c - rotational bilateral dislocation. cord depending on the narrowing of the spinal canal. Diagnosis of dislocations is made on the basis of a characteristic history, typical displacement of the head (Fig. 32), palpation of the spinous and transverse processes, limitation of movements, and phenomena from the spinal cord. Often, a swallowing disorder is observed. Sometimes the displacement of the upper cervical vertebrae can be felt with a finger through the mouth on the posterior wall of the pharynx. X-ray diagnostics (see separate table, Fig. 8) is of particular importance. Unilateral dislocations have a better prognosis and in fresh cases can be corrected by constant traction using a Glisson loop or by reduction of the dislocation under anesthesia, for which, having placed the patient on the Figure 32. Unilateral dislocation of the cervical spine...
abdomen, traction is performed on the head with subsequent flexion to the healthy side (one can simultaneously perform a turn to the healthy side) until the hooked articular processes disengage; then the head is turned to the affected side and fixed with a plaster cast. Bilateral dislocations (Fig. 33) are also reduced by traction with subsequent pushing and
Figure 33. Bilateral dislocation of the VI cervical vertebra.
extension of the dislocated part of the spine, or they attempt to reduce the dislocation alternately according to the method indicated above from one side and then the other. In general, however, the reduction of bilateral dislocations is rarely successful. Any reduction must be done very carefully (danger of spinal cord compression) and, if possible, immediately, because after a few days and especially weeks, reduction becomes impossible. Particularly dangerous are dislocations of the upper two vertebrae: the very rare dislocations of the head, i.e., between the occipital bone and the atlas, and the more frequent ones between the atlas and the axis. The narrowing of the spinal canal caused by the displacement can in itself lead to severe phenomena of spinal cord compression, and the ruptures of the cruciate ligament and fractures of the odontoid process so often observed in this case as a rule lead to death from the insertion of the odontoid process into the spinal cord and damage to the latter. Dislocations in other parts of the spine, especially in the lumbar region, are more often combined with separation in the region of the intervertebral cartilages or with fractures. Kocher divides vertebral fractures into partial (isolated) and complete, combined with dislocations and displacements (fracture-dislocations). Partial (isolated) fractures can be in the processes, arches, and bodies. Fractures of the spinous processes occur most often under the influence of direct violence—a blow from behind, usually on the most prominent processes (C7, upper and lower thoracic), less often from muscle contraction or from the processes pressing against each other during excessive extension. These fractures are recognized by the abnormal mobility of the process, its displaceability, crepitus, local swelling, and pain upon pressure. In difficult cases, an X-ray decides. These injuries do not require special treatment; in case of excessive and persistent pain, it is sometimes necessary to remove the fragment. Violence acting on the spinous processes can be transmitted to the vertebral ring, causing fractures of the arches, often bilateral, with the insertion of a fragment into the spinal canal and compression of the spinal cord (Fig. 34), which is especially dangerous in the cervical region, where fractures of the arches are observed more often. Diagnosis is not always easy. An X-ray decides the matter [see separate table (p. 135-136), Fig. 9 and 10)], and if compression of the spinal cord by the inserted arch fragment is detected, surgical elimination of the pressure is indicated—lifting and repositioning of the fragment or its removal. Fractures of the odontoid process are more often observed in pathological conditions (tuberculosis), less often in traumatic dislocations and fractures with displacements. The broken-off odontoid process can insert itself into the spinal cord and damage
Figure 34. Fracture of the vertebral ring with compression of the spinal cord.
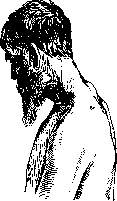

injure it, which as a rule leads to sudden death. However, in reality, fatal outcomes are observed much less frequently than previously believed (according to Jefferson, in approximately 20%), which depends on the preservation of the ligamentous apparatus, which holds the fragment in place, preventing its impaction. Rupture of the cruciate ligament is a decisive moment not only in fracture of the odontoid process, which due to this can shift and impact into the spinal cord, but also in anterior displacement-dislocations of the atlas without fracture of the odontoid process, when the latter, not held by the ruptured ligament, remains in place and injures the spinal cord, which, shifting together with the upper segment anteriorly, moves onto it. Fractures of the lateral articular processes are relatively rarely observed in an isolated form, more often in combination with dislocations and more extensive fractures. Relatively more often, isolated fractures of the processes of the sacrum articulating with L1 (Henle) are observed. Finally, isolated fractures of the transverse processes, observed almost exclusively in the lumbar region and caused either by direct violence or by excessive muscle contraction, are among the rare injuries. Usually, diffuse tenderness in the lumbar region on the injured side is observed, radiating to the legs or abdominal integuments. Pain increases with bending and turning; bending to the affected side is less painful. Patients spare the lumbar region, hold the torso bent and inclined to the affected side, where contracture of the m. psoas is also often observed. In diagnosis, one must consider deep contusions, distortions, lumbago, and exacerbations of chronically occurring inflammatory diseases of the spine (tuberculosis), which can produce similar symptoms. A good X-ray decides the matter, a film on which the detachment of the outer, more narrowed part of the transverse process is visible. In rare cases, retroperitoneal hemorrhage is observed, leading to paralytic intestinal obstruction (Volkovich). Fractures of the vertebral bodies are least of all dependent on the action of direct violence—a blow from behind, but more often on longitudinal compression and bending of the spine forward or backward, falls from a height onto the feet, onto the buttocks or head, falls of a weight from above onto the head or shoulders with excessive bending (whereby a fracture of the sternum may simultaneously occur), or finally from a fall onto the back onto a hard protrusion with excessive bending backward. The degree and form of the fracture are influenced not only by the magnitude and direction of the violence, but also by the localization, age, and condition of the spine itself. In contrast to dislocations, which are encountered most often in the most mobile segments, fractures of the bodies are observed in places where the immobile part of the spine transitions into the mobile one, mainly in the thoracolumbar region. According to Ménard, almost half of all fractures fall on D12 and L1 and in decreasing progression on the vertebrae lying above and below, with a fracture at the apex of the thoracic curve D5,6 being relatively common. In children, with their more elastic ligamentous apparatus and especially with wide, resilient discs, which act as buffers between the vertebrae, fractures occur as a result of relatively greater violence (more often distortions and dislocations) than in the elderly, in whom the buffering capacity and elasticity progressively decrease. Especially brittle are fused, ankylosed vertebrae after spondylitis and spondylosis, not to mention active destructive processes (especially in cancerous metastases), in which a fracture can occur even with minimal trauma, as if spontaneously. Isolated fractures of the vertebral bodies are most often observed in the form of so-called compression fractures (Fig. 35-38). Under the influence of longitudinal compression, usually combined with bending, the unstable cancellous bone tissue of the body is wedge-shapedly flattened and spreads to the sides. Depending on the elasticity of the bone mass and the force of compression, various degrees and forms of injuries are observed—cracks, fissures, compressions, transverse and oblique fractures, comminuted fractures, and complete crushing. The injury can involve one or two vertebrae, less often more.
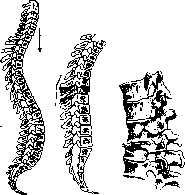
Figure 35.
Figure 36.
Figure 35. Mechanism of vertebral fractures: a—from compression; b—from bending. Figure 36. Compression fracture without narrowing of the canal.


Figure 37. Compression fracture with narrowing of the canal and breaking off of the anterior edge of the vertebral body: a—specimen; b—radiograph of the specimen.
Collapse of the anterior parts of the spine leads to relatively small kyphotic curvatures of the spine. The most dangerous complications are spinal cord disorders caused by the displacement of fragments and pieces of the bodies into the spinal canal. A fracture with dislocation, a luxation fracture, occurs under the action of more significant violence, leading to simultaneous displacement in the lateral joints. Kocher calls the complete displacement of the upper segment of the spine, the shift of the overlying vertebra anteriorly and "downward", a complete fracture with dislocation (totale Luxationsfractur). These injuries are classified as particularly severe and in the vast majority of cases lead to death depending on compression (Fig. 39-41) or even ruptures of the spinal cord. A complete transverse fracture of the vertebral body itself can be combined with the most diverse injuries of all other parts of the spine, sprains, dislocations, fractures of the processes, and damage to the cartilaginous discs, and finally, rupture of the ligamentous apparatus; the rupture of the anterior and posterior longitudinal ligaments is of particular importance. Irregular fracture lines of the vertebral body usually run from behind-above to the front-below, and in the same direction occurs the displacement of the upper segment—sliding forward and downward, so that the overlying vertebrae move onto the injured one ("like a hat on the forehead") or may even stand in front of the latter. In turn, the posterior edge of the lower, undisplaced vertebra can protrude at an angle into the spinal canal and impact into the spinal cord. In some cases, lateral displacement or a combination of both occurs.

Figure 38. Healed compression fracture.
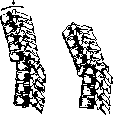
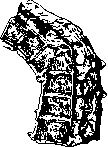
Figure 39.
Figure 40. Figure 39. Mechanism of complete fracture with dislocation. (According to Matti). Figure 40. Complete fracture with dislocation with compression of the spinal cord by the posterior protrusion of the vertebra. (According to Matti). Symptomatology of fractures. Curvature of the spine in fresh cases is usually insignificant and in luxation fractures is naturally expressed much more sharply than in a simple compression fracture. In the latter, there is usually only some divergence and protrusion (elevation) of the spinous process of the overlying vertebra. In a luxation fracture, depending on the displacement of the overlying vertebra forward and downward, the spinous process of the latter also shifts anteriorly, as if disappearing, while the spinous process of the injured vertebra protrudes (in case of injury to several—the upper of the injured ones). Curvatures are more pronounced in the thoracic region and less in the cervical and lumbar, where there is physiological lordosis. Sometimes the protrusion of the anteriorly displaced vertebra can be felt as a prominence on the posterior wall of the pharynx in case of a fracture in the cervical region.
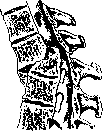
Figure 41. Fracture with dislocation and narrowing of the canal. (According to Okinczyc).
or palpate through the abdominal wall in the lumbar region. In older cases, kyphosis may increase and acquire an angular or arcuate character. Spinal cord disorders in all injuries of the spine are the most important symptoms and the most dangerous complication. Uncomplicated fractures without spinal cord phenomena relatively quickly lead to consolidation and healing and in themselves do not present a great danger, in contrast to cases complicated by spinal cord phenomena, which, on the one hand, very often lead to death, and on the other, leave behind serious functional disorders for a long time. Diagnosis and course. In fresh cases, immediately after trauma, it is not always easy to determine the true nature of the spine injuries. The main symptoms of fractures—pain, limitation of mobility, curvature of the spine, and spinal cord disorders—have only relative significance. On the one hand, very severe pain, as well as sharp limitation of mobility—the inability not only to stand but even to turn in bed—can be observed in distortions and contusions, and on the other hand, even significant fractures without displacement can be relatively painless and cause moderate difficulty in movement. The magnitude and shape of kyphotic curvatures also do not always resolve the question of the nature of anatomical changes, since deformations of the spine are observed in sprains and displacements without fractures; at the same time, even significant initial curvatures can correct themselves—reduce—so quickly that they remain unnoticed. Finally, the intensity of spinal cord disorders also does not always correspond to the severity of the injuries, since even complete paralyses often recover quickly, especially since transient spinal cord disorders can depend on a simple concussion of the spinal cord. Likewise, there is not always a correspondence between the level of bone injuries and spinal cord disorders, since the latter can extend significantly higher than the former in cases of hemorrhages and ascending degenerations of the spinal cord. The matter is decided by X-ray examination, which, however, must necessarily be compared with the clinical picture, without which one can fall into a gross error when interpreting the images. In compression fractures, on frontal images, some densification of the body of the flattened vertebra is revealed, a decrease in its height and an increase in its diameter (from crushing of the bone mass) with clear contours and preservation of the intervertebral cartilage; the fracture line is usually not visible, it is revealed only on profile images; on the latter, the wedge-shaped compression of the body and bone fragments are visible with particular clarity, which usually protrude from the anterior edge and are held by the preserved longitudinal ligament in front of the narrowed anterior edge of the body. The clarity of the contours and the preservation of the intervertebral discs or some narrowing of them is of importance. In frequent injuries of 2-3 vertebrae, the cartilaginous discs are usually destroyed, disappear, the upper vertebra embeds into the lower one, so that the X-ray picture becomes very close to tuberculous lesions. The diagnosis is made based on the totality of all data. It is even more difficult to distinguish radiologically a healed fracture of two or more vertebrae with their complete fusion and arcuate collapse from similar pictures of reparative changes after suffered inflammatory diseases (tuberculosis, osteomyelitis). Fatal outcomes occur both immediately after the trauma from shock (in almost half of all cases) and in the further course from various kinds of complications. In the near future, the patient is threatened by hypostatic pneumonia, which so often accompanies severe injuries of the spine, especially in elderly people. Then, in the further course, in spinal cord disorders, the most dangerous complication is paralysis of the urinary bladder, or rather paralysis of the detrusor, which, with sphincter spasm, leads to urinary retention and prolonged catheterization, which always carries the danger of bladder infection, purulent cystitis, and ascending pyelonephritis. To prevent this fatal complication, sometimes from the very beginning, a fistula is placed on the bladder, which does not always save the patient, but only delays the fatal outcome. With overfilling of the bladder, the sphincter can stretch, and urine begins to be involuntarily excreted in drops (ischuria paradoxa), which sharply complicates the care of the patient, especially with bedsores that so often develop after fractures of the spine. The latter can lead to deep necrosis, involving the bone, and be accompanied by phlegmonous inflammations leading to sepsis. Paralysis of the anal sphincter leads to fecal incontinence (incontinentia alvi); in those cases where there is simultaneously paralysis of the abdominal wall muscles and a disturbance of peristalsis in the lower sections of the intestines, retention and accumulation of feces in the ampulla recti and above can occur, which can cause ulceration of the mucosa. Sometimes paralysis of the abdominal muscles can cause violent phenomena of meteorism and intestinal obstruction, requiring surgical intervention. The prognosis depends on the level and degree of injury, as well as on the causes inducing the clinical phenomena. The higher the injury, the more serious it is. Injuries in the upper cervical region are especially dangerous, often leading to sudden death; injuries of the lumbar region—below the termination of the medullae spinalis—proceed significantly more easily. According to Burrell, in a fracture in the upper cervical region, mortality reaches 85%, in the upper thoracic—76%, in the lower thoracic—56%, and lumbar—50%, with an overall mortality of 64.5%. Of decisive importance for the prognosis is the question of whether a complete transverse rupture of the spinal cord has occurred or only its partial injury and compression. However, the question is not clarified immediately, but a few days after the trauma, since even complete paralyses during this interval of time can improve or even disappear completely. The preservation of knee reflexes and normal activity of the pelvic organs in spastic and asymmetric paralysis immediately exclude a complete interruption of the spinal cord. In those cases where, after 10-15 days, a complete flaccid symmetric paralysis remains with loss of sensitivity, absence of knee reflexes, and pelvic disorders, one can speak with certainty about a complete transverse interruption of the spinal cord. Such patients die sooner or later. In partial injury or compression of the spinal cord, initially complete paralyses can either pass completely or leave behind some trace in the form of pelvic disorders or disturbances in the motor and sensory sphere. These disturbances can have both a symmetric and an asymmetric character, with various levels and degrees of motor and sensory disorders. The prevalence of sensory disorders over motor ones speaks more in favor of radicular phenomena. Finally, the prognosis is also influenced by the cause inducing the spinal cord disorders and the degree of its remediability. In some cases, this cause lies only in the mechanical compression of the undamaged spinal cord by bone displacements and fragments, after the reduction or removal of which the function of the spinal cord can be fully restored; in other cases, the cause lies in the spinal cord itself, in its injuries and changes, essentially not mechanically remediable, but undergoing successive processes of degeneration or healing. A special place among these causes is occupied by the so frequent hemorrhages into the spinal cord (see Haematomyelia), which are observed either in the brain tissue itself, more often in the gray matter, or in the central canal. Such hemorrhages can be insignificant, punctate, but can also reach a significant size; spreading along the spinal cord up and down for a significant distance, they can cause spinal cord phenomena significantly higher than the site of injury, which complicates diagnosis. Gradually resolving, the hemorrhage can either be completely eliminated or leave behind changes in the form of delimited cavities in the central canal (syringomyelia traumatica), degenerative changes in the brain itself, adhesions, cicatricial changes with corresponding symptoms of deficit in the motor and sensory sphere. Haematomyelia is observed predominantly in the cervical region. Extramedullary hemorrhages with intact membranes present less danger. In individual cases, these accumulations of blood can exert transient pressure on the spinal cord, sometimes leaving behind a trace in the form of cicatricial adhesions and radicular phenomena. Even more rarely, paravertebral hemorrhages are observed, which can sometimes accumulate on the anterior surface of the spine, simulating cold abscesses. As already mentioned, the prognosis is determined in the first 10-15 days after the trauma. If the phenomena from the spinal cord do not improve, then all the indicated dangers remain in force; if, however, by this time the phenomena decrease, then one can expect gradual improvement and even complete recovery, despite the severity of the anatomical injuries of the spine. However, in a significant percentage of cases, some disorders remain.
In cases of complications with spinal cord disorders, partial anesthesia or hyperesthesia, limited paralyses and pareses, contractures, urinary incontinence, impotence, trophic ulcers on the feet, and symptom complexes resembling tabes (see) may remain. But even after uncomplicated fractures, pain, gait instability, and reduced endurance may persist for a long time. According to Haumann (1926), restoration of working capacity after 2 years is observed in only 25% of cases, after 6 years in 61%, and after 9 years in 80% of patients. Such outcomes largely depend on the untimeliness and irrationality of treatment, which in turn depends on the difficulty of early recognition of spine fractures, which in almost half of all cases remain without timely recognition (Volkovich). Therefore, a thorough examination of the spine after any trauma with the use of X-ray diagnostics is a fundamental condition for improving the treatment outcomes of these injuries. Treatment of any spine injury must begin primarily with protecting the patient from possible further traumatization during carrying, transport, transfer, and examination, when a careless movement can displace fragments and thereby injure the spinal cord. Therefore, the greatest caution is required in fresh cases immediately after the trauma. By placing the patient on a flat, non-yielding bed, complete rest is ensured, and by raising the head end of the bed and fixing the head with a Glisson loop, gradual relaxation of the spine and its straightening are achieved, which is especially important in fractures, whereas in contusions and sprains simple rest is sufficient, and in dislocations, reduction is required. In fractures in the upper section, traction by the head is the most convenient method, whereas in the lower section, a reclination position with a small cushion, preferably made of flaxseed, placed under the affected area, is of greater importance. Volkovich recommends a prone position for straightening the spine in the lower section. To create complete rest, especially with insufficiently trained personnel, it is better to apply a plaster bed to the patient, capturing the head, torso, and hips, but one must remember about bedsores. Rest and bed confinement should continue until the moment of fracture consolidation, approximately for 1 1/2-2 months. It is better to keep the patient in bed longer than to put them on their feet too early, as in such cases, incomplete restoration of working capacity is more often observed. The absence of pain, deficit symptoms, resistance to load, and an X-ray picture of consolidation allow patients to be put on their feet in a supporting apparatus, a plaster or removable corset, which the patient must wear for 1/2-1 year. Persistently continuing pain, instability to load, and restricted movement force one to either keep patients in bed or a corset longer or to resort to operative fixation of the spine according to Albee and its modifications (see Spondylitis). In cases of complications with spinal cord phenomena, it is necessary to determine the cause of compression and try to eliminate it mechanically. However, the resolution of this question is very difficult, because even with good X-ray images, it is not always possible to establish the cause of compression, and in cases of intramedullary hemorrhages and spinal cord injuries, such an external cause may be completely absent, therefore the operation proposed for eliminating spinal cord compression—laminectomy (see)—in many cases may turn out to be, as it were, exploratory and not bring the desired results. This operation is of particular benefit in fractures of the arches, especially bilateral ones, when by removing or lifting them, the spinal cord is relieved of compression, just as it is when removing a separate fragment or bone splinters from the spinal canal. This operation also has some significance in cases of spine displacement, when the arch of the overlying vertebra compresses the spinal cord. There are proponents of early intervention, but the majority of authors adhere to a wait-and-see position, performing the operation after some time, after clarifying the success of conservative measures and the subsidence of acute phenomena, in particular, the reduction of hemorrhages. However, this waiting should not be too long, as cicatricial changes may occur, although, on the other hand, even old cases can be operated on with success (Polenov). The danger of early operations is great—from 25% (de Quervain) to 72% (Lloyd) mortality—and is justified by the exceptional severity of these injuries (in Haumann's 204 cases, 330 patients died shortly after admission). Spine wounds. Spine injuries with a breach of the integrity of the integuments are divided into contused-lacerated, stab-cut, and gunshot wounds; they, in turn, are divided into those penetrating into the spinal canal and non-penetrating ones. These injuries are encountered in peacetime even more rarely than closed injuries, but they carry a greater danger in comparison with the latter, depending, on the one hand, on the possibility of introducing infection (meningitis) into the depth, especially into the spinal canal, and on the other—due to the significantly greater frequency and severity of spinal cord injuries. Contused-lacerated wounds, inflicted by the action of a blunt instrument, are encountered most rarely and have comparatively little clinical significance, as they are usually more superficial and rarely penetrate into the spinal canal. The danger of these, usually contaminated, wounds lies in the infection of tissues and damage to the spinous processes and arches. Stab-cut wounds of the spine are encountered somewhat more frequently. They are inflicted from behind with a sharp instrument, usually in the upper section of the spine, at the level of the striking hand. More often, these wounds do not penetrate into the spinal canal thanks to the protection from the vertebral arches. Less often, the instrument passes between the arches or violates their integrity and penetrates into the spinal canal. Most often, spinal cord injuries are asymmetric and are accompanied by cross-paralysis of the Brown-Séquard type, but there can be other types of injuries—from injury to the membranes only to complete transection of the spinal cord. Upon transection of only the roots, motor and sensory disorders appear on the corresponding side. Injury to the spinal meninges can sometimes be recognized by the discharge of cerebrospinal fluid from the wound. These wounds, according to Wagner, yield a comparatively small percentage of mortality (about 20%) and approximately the same small percentage of complete recovery, while in 60% of cases, some or other impairments remain. Gunshot wounds of the spine are encountered just as rarely as stab wounds, constituting no more than a quarter of a percent of all gunshot wounds in general. In the majority of cases, one is dealing with penetrating wounds, accompanied by fractures of the spine bones, and in some cases, complicated by injuries to internal organs, especially in cases of wounds from the front. Wounds can be through-and-through or blind, whereby the bullet can get stuck either in the vertebral body or in the spinal canal. Penetrating through the soft spongy substance of the vertebral body, the bullet forms smooth channels, so-called "perforated" fractures, and upon hitting dense processes and arches, it produces comminuted fractures; the fragments, penetrating into the canal, can damage the spinal cord. Spinal cord injuries in gunshot wounds are encountered more frequently than in closed fractures and are more dangerous, because, on the one hand, the anatomical destruction in them is more serious, and on the other, there is always a threat of introducing infection. Clinical symptoms, depending on the degree of damage to the bones and spinal cord, are analogous to those in closed fractures. The prognosis of gunshot injuries is very serious and depends mainly on the degree of spinal cord disorders. The majority of patients perish in the first hours after the wound. In those cases where the person wounded in the spine copes with the initial shock, they are threatened by a second danger—compression and injury of the spinal cord by bone fragments, which can be displaced during transport. Therefore, such wounded in a military setting must, for the first time, most often remain on the spot or in the nearest rear and be evacuated only after 10-15 days, when acute phenomena subside and the degree of spinal cord injury is clarified. Nevertheless, the danger of even such lighter wounds is great. Thus, according to Kornev's data during the imperialist war, per 100,000 wounded evacuated from the front and having passed through the infirmaries of the Union of Cities in Leningrad, spine wounds occupied the last place among other wounds, constituting only 0.3%, whereas their mortality stood in the very first place, constituting 11% with a general mortality from all wounds of 1.8%. This mortality depends mainly on complications from the pelvic organs and rapidly developing bedsores. According to the same data, complete recovery occurred in 20% of all cases, while the remaining wounds resulted in varying degrees of disability. The treatment of gunshot injuries of the spine is different, depending on the anatomical conditions and the nature of the wound. In non-penetrating wounds without spinal cord disorders, the therapy is conservative: aseptic treatment of the wound, complete rest, and traction in cases of bone injuries.
In penetrating wounds with spinal cord disorders, surgical treatment may be used to eliminate the latter. Theoretically, surgical treatment is indicated for the elimination of mechanical compression of the spinal cord by a foreign body or bone fragments, as well as for their removal when they are embedded in the spinal cord with partial damage to the latter; the operation is contraindicated in cases of complete rupture of the spinal cord and extensive hematomyelia. However, accurate recognition of the nature and degree of damage is extremely difficult, especially immediately after the injury. X-ray diagnostics also do not provide sufficient data to establish the anatomical causes of spinal cord disorders, except in cases where the presence of a foreign body or bone fragments in the vertebral canal is detected. Early laminectomy can immediately eliminate the above-mentioned causes that induce spinal cord disorders, thereby preventing subsequent inflammatory and degenerative phenomena, but at the same time, it may prove not only useless in the absence of removable anatomical causes but even dangerous due to the addition of surgical shock and the possibility of introducing infection. Late operation has the advantages of greater safety and the possibility of operating with clear indications, since by this time the hemorrhage is resorbed and inflammatory changes have passed, but waiting can cause persistent degenerative changes in the spinal cord, even with simple compression without damage to the spinal meninges, while timely elimination of compression leads to the restoration of spinal cord function. There are supporters of both early and late interventions. The experience of the last war showed the entire severity and danger of these wounds and strengthened the position of supporters of earlier interventions. However, for urgent operations, the indications are still very limited, and the majority adheres to a conditionally expectant tactic, depending on the course and changes in spinal cord phenomena over the course of 10-15 days after the injury, when significant improvements may occur. If by this time it becomes clear that there is a complete interruption of the spinal cord (see above, fractures of the Spine) or, conversely, rapid restoration of movement and sensitivity occurs, then the operation is not indicated; if, however, signs of undoubted compression persist, but there is no complete interruption, then surgical intervention is fully indicated and often yields a favorable result. Infectious diseases of the Spine. Inflammatory diseases of the Spine can be acute and chronic, localizing either in the joints or in the bones themselves. Acute inflammatory diseases of the intervertebral joints are observed in acute articular rheumatism and as a complication after various acute infections, primarily after influenza and scarlet fever. These synovites manifest themselves with transient sharp pains and diffuse limitation of the mobility of the Spine. The larger joints of the upper cervical vertebrae are more often affected, unilateral damage to which leads to painful unilateral muscular contracture (torticollis), pain during certain movements, and radiating neuralgic pains. Acute osteomyelitis of the vertebrae is rare, accounting for only about 2% of all osteomyelitis cases (Hahn). According to Volkmann, this disease is observed more often in adolescence (50% of all patients from 8 to 17 years old), predominantly in males (72%) and mainly in the lumbar region; in 58% it affects the arches and processes, in 34% the bodies, and in 8% the entire vertebra. The causative agent is most often staphylococcus, and the entry portals for it are panaritiums, furuncles, and other purulent diseases. The disease arises acutely, sometimes lightning-fast, proceeds stormily, and in 2/3 of all cases leads to death, especially with involvement of the bodies. Only in 1/3 of cases is the diagnosis made correctly, mainly when the posterior sections are affected; more often appendicitis, peritonitis, typhoid fever, pneumonia, or meningitis are suspected. Usually, the temperature rises to 40° and above, a septic general condition sets in, leukocytosis reaches 40 thousand, pains are sometimes very strong, more often radiating to different sections depending on the localization—to the nape, to both shoulder blades, to the iliac regions, to the limbs. With involvement of the lower thoracic and lumbar vertebrae, meteorism, dilation of the veins of the abdominal walls (Plenz), and dysuria (Petersen) are often observed; the patient lies with bent legs. Often there is a Kernig's sign. Complications from the spinal cord and meninges are often noted (up to 64%, according to Schonbauer), especially with localization in the cervical region. The resulting abscesses, accumulating on the lateral surfaces of the vertebral bodies, can descend and break through into the pleura, bronchi, esophagus, and abdominal organs; sometimes psoas abscesses are formed. With involvement of the posterior sections of the arches, the disease proceeds significantly more easily and is more often correctly diagnosed by local limited tenderness upon pressure, edema, swelling of the outer coverings, and accumulations of pus, the examination of which for pyogenic bacteria in many cases decides the matter. Usually, one vertebra is affected, rarely two or more; in 14% osteomyelitis of other bones is also observed. Deformation of the Spine is observed relatively rarely, and pathological fractures even more rarely. Prognosis to a significant degree depends on the localization (2/3 of deaths fall on involvement of the bodies and 1/3 on involvement of the arches), while the general mortality rate according to previous statistics reached 72%, and only recently with the improvement of early diagnostics has it dropped to 41% (Oglobina). X-ray diagnostics in acute cases helps little, as more or less clear changes occur only in later stages during prolonged processes. Treatment boils down to determining the abscess and opening the latter, if this is technically possible. This is easiest to achieve with involvement of the posterior sections and significantly more complex (and more often impossible) with involvement of the bodies; in the thoracic region, one can resort to costotransversectomy (first used by Heidenhain), in the lumbar region to opening a psoas abscess, in the cervical region to opening an abscess in front of the sternocleidomastoid muscle or behind it. Chronic osteomyelitis of the vertebrae [see separate table (art. 135-136), fig. 6] is observed either as an outcome of an acute one with the formation of fistulas and sequestra or as an independent form - primary chronic staphylococcal spondylitis (Oehlecker). This disease is observed extremely rarely (only about 30 cases have been described); in its course, it very much resembles tuberculous spondylitis, especially the fistulous one, with which it is usually confused. On the material of about 700 cases of tuberculous spondylitis, osteomyelitis of the Spine was established in 4 cases (P. G. Kornev). The lumbar region is predominantly affected, as in acute forms, but in contrast to the latter, the bodies are affected more often than the arches and processes. The disease, subsiding at times, can drag on for decades, the general condition suffers little, local and radicular pains are not always constant, spinal cord disorders are rarer than in acute processes, but cold abscesses and fistulas are quite frequent, in particular fistulas on the thigh, giving reason to suspect tuberculous spondylitis or osteomyelitis of the femur. Deformations of the Spine are observed relatively rarely, mainly in the form of smoothing of the lumbar lordosis, sometimes a small gibbus is formed with insignificant limitation of mobility. Upon X-ray examination, sharp sclerosis and bone overgrowth are striking; the affected vertebra or two adjacent vertebrae collapse and flatten, especially at the edges; their lateral and anterior sections protrude beyond the general line of the vertebral bodies, forming periosteal growths, which in the form of bridges can stretch to adjacent vertebrae, which prevents stronger collapse. However, it should be noted that these characteristic features do not appear earlier than 3-6 months after the onset of the disease, and before this period, usually no changes are detected radiologically. Diagnosis is based on a thorough anamnesis (often acute onset) and course, bacteriological examination of pus, the presence of other osteomyelitic foci, and the indicated characteristic X-ray picture, which, however, has conditional significance, since sclerosis of the vertebrae and the presence of periosteal growths can also be observed in syphilis and post-typhoid spondylitis. The presence of staphylococci in pus in fistulas can be a secondary phenomenon, but at the same time, it is not always easy to determine the pyogenic infection in closed old abscesses and in osteomyelitis, therefore many (in particular Yeletsky and Demidov) attach great importance to the antistaphylolysin reaction. Of course, it is also necessary to use other biological reactions: agglutination, Wassermann reaction, Pirquet reaction, focal reaction with Koch's tuberculin, erythrocyte sedimentation rate, examination of blood morphology, etc. With a high degree of probability, one can exclude tuberculosis of the Spine if, after opening the cold abscess or aspirating pus and using an autovaccine, the clinical signs of the disease disappear relatively quickly (Yeletsky and Demidov).
In this case, autovaccine is a treatment ex juvantibus. Prognosis is significantly better than in acute forms (out of 23 published cases, 4 were fatal). Therapy for diagnosed osteomyelitis is operative, where possible, mainly in cases of involvement of the posterior sections: opening of abscesses and removal of sequestra. In case of involvement of the bodies—only opening of accessible abscesses. Auxiliary treatment—vaccine therapy with autovaccine or polyvalent staphylococcal vaccine. Post-typhoid spondylitis is a more benign disease than staphylococcal osteomyelitis of the spine. It occurs more often after relapsing fever, less often after typhus and typhoid fever, and is generally observed rarely. In the USSR, these complications were well studied during past typhus epidemics, when post-typhoid spondylitis was encountered and described significantly more often. They arise on average a month after having had typhus and manifest as a new rise in temperature, an attack of sudden severe pain in the lumbar region, sharp limitation of mobility, and sometimes swelling of soft tissues. These acute phenomena begin to gradually subside, and the disease usually ends within a few months, leaving behind a limitation of mobility in a small section of the spine, sometimes with a slight curvature. Neither cold abscesses nor fistulas are observed. The most characteristic feature of these diseases is the destruction of the intervertebral cartilage and bony outgrowths fusing the affected vertebrae. Radiological changes are determined already a few weeks after the onset of the disease and initially manifest as clouding and narrowing of the intervertebral spaces, which may subsequently disappear altogether. Changes in the bodies themselves are not always pronounced; sometimes foci of softening reaching the cortical layer are observed; more often, the body of one or two vertebrae is uniformly compressed. Later, proliferation and thickening of the periosteum occur, changing the lateral contours of the vertebrae, then massive lateral bony adhesions appear, which, in the form of bridges, stretch from one vertebra to another at the base of the transverse processes symmetrically on both sides and fuse them. Simultaneously, the anterior longitudinal ligaments in the area of the lesions also ossify, and ultimately complete bony ankylosis of two or three vertebrae occurs. Syphilis of the spine. Syphilitic spondylitis is encountered very rarely (about 20 cases have been published in Russian literature, up to 150 in foreign literature) and is diagnosed even less often due to the extreme similarity in clinical and radiological picture to tuberculous spondylitis. Three forms of syphilitic lesions of the spine are distinguished (Sinakevich): 1) spondyloarthritis luetica—lesion of the intervertebral joints in the form of acute (in the secondary period) or chronic synovitis, more often encountered in combination with other syphilitic arthritides (arthrolues tardiva of Schlesinger), usually passing without a trace under the influence of treatment and only in rare cases leading to ankylosis, especially with simultaneous involvement of the bodies and processes. 2) Spondylitis luetica simplex—simple osteo-periosteal lesion of the bodies and processes without destruction, manifesting in radicular pain, rigidity of the spine, swelling and edema of the outer integuments in the area of the lesion; these phenomena usually easily yield to specific treatment and pass without leaving noticeable traces behind, except for slight periosteal thickenings and exostoses. 3) Spondylitis luetica destructiva, s. gummosa, in contrast to the first two forms, causes clearer changes—destruction in the vertebrae, and therefore is diagnosed more often. As in other bones, the process can have either a more diffuse infiltrating character or a more limited one, affecting both the bodies and the processes, usually starting from the periosteum and spreading to the bone. Milder cases of bone gummas are characterized by a sharply limited rarefying process, while with more intense bone neoformation, complete narrowing of the Haversian canals can occur, which leads to circulatory disturbance, severe necrosis, and sequestration. Intervertebral cartilages are also involved in the process. Relatively rapidly developing reparative processes and periosteal growths prevent excessive collapse of the vertebrae, which is why large humps are not observed in syphilitic spondylitis. According to Zlesch, spondylitis luetica is observed mainly in adults (in the 3rd-4th decade) and three times more often in men than in women. The preferred localization is the cervical region, the four upper vertebrae, especially the atlas and axis, which many German authors (Neumann, Petren, Schlesinger) explain by the transition of the ulcerative process from the pharyngeal mucosa to the vertebrae, as a result of which destruction of the anterior sections and the shedding of sequestra can occur. French authors (Fournier, Hallopeau) consider the lesion of the vertebrae to be primary, and the ulceration of the pharyngeal wall to be secondary. Lesion of the spine is often encountered in combination with lesions of other bones in particularly malignant forms of syphilis, which gave the right to speak of a special "osteotropic" strain of the spirochete. The disease usually appears in the tertiary period, several years after infection; an acute onset is rarely observed, usually the disease develops slowly and is characterized by inconsistent, intermittent spontaneous pain with nocturnal exacerbations. Sometimes the pain reaches an extreme degree, especially with localization in the cervical region, radiating to the occiput, ear, and mastoid process; there may be pain upon swallowing. The hump is usually less pronounced than in tuberculosis; often, edema and infiltration of soft tissues over the affected vertebra, limitation of mobility, and muscle rigidity are observed; in cervical lesions—torticollis. In approximately 1/4 of all cases, spinal cord phenomena are also observed (R. Hunt). The general mortality rate according to previous data reaches 40% and depends mainly on the destruction of the upper cervical vertebrae, their displacement, and compression of the spinal cord; in rare cases, fatal hemorrhages from the external carotid artery were observed. With the refinement of diagnostics, the prognosis has improved sharply. In differential terms, the greatest difficulties are presented by tuberculous lesions, in particular lesions of the two upper vertebrae, proceeding with almost the same clinical phenomena. Radiological changes are also insufficiently characteristic; in any case, they are not very reliable (Wimmer). In the initial stages, there may be no periosteal changes in syphilis. Infiltrates on the posterior wall of the pharynx and edema on the occiput can also be observed in tuberculosis, but true cold abscesses are not encountered in syphilis (the described cases are doubtful), unless infection and the formation of purulent tracks occur. The diagnosis is based on general signs of syphilis, especially in the presence of specific lesions of other bones and joints. The Wassermann reaction has less significance than specific treatment ex juvantibus, which quickly calms the pain, whereas rest and unloading by no means always calm it, in contrast to tuberculosis. It must also be kept in mind that syphilitic spondylitis can occur in a tuberculous patient, just as tuberculosis of the spine can occur in a syphilitic. When diagnosing, one must also keep in mind traumatic spondylitis, tumor of the vertebrae, chronic osteomyelitis, and post-typhoid lesions. Treatment is applied both general anti-luetic (medicinal) and local-orthopedic. Tuberculosis of the spine—see Spondylitis. Actinomycosis of the spine is encountered very rarely and is a secondary disease upon the spread of the process to the spine from the mucous membranes of the oral cavity, pharynx, esophagus, intestine, or from the lungs. One or several vertebrae can be affected; the infiltrating process can seize the entire vertebra and penetrate into the vertebral canal, not causing, however, spinal cord disorders, but more often being limited only to radicular phenomena (Wullstein). The bone appears as if eaten by worms; in rare cases, collapse of the destroyed vertebra can occur. Actinomycosis (see) is determined by the presence of a primary progressive focus, the formation of a dense, "board-like" infiltrate in the area of the affected vertebrae, and the appearance of purulent decay with characteristic drusen. The prognosis is poor, as the process spreads to the spine in far-advanced cases. The applied iodine treatment (KI from 3 to 5 g per day) rarely halts the process. Tumors of the spine are encountered rarely, constituting approximately 1.5% of all tumors in general. Benign tumors of the spine have relatively little clinical significance, acquiring the latter either with particularly strong growth or when the tumor narrows the vertebral canal and intervertebral foramina, causing compression of the spinal cord and roots. More often, cartilaginous exostoses and enchondromas are encountered, in the majority of cases multiple. Occasionally, osteomas, lipomas, and also angiomas are observed. Malignant neoplasms of the spine are encountered significantly more often; according to Schlesinger, for one benign there are 10 malignant ones.
Primary tumors are observed less frequently than secondary ones, among which cancer metastases occupy the first place, constituting the vast majority of all tumors of the spine. Primary sarcomas of the spine—osteogenic, originating from the bodies and arches—are encountered in younger subjects and on average last 10-12 months, leading to death. Developing initially in the center of the bone, the tumor may for a comparatively long time not produce visible changes in the shape of the spine; its curvature, which occurs after the collapse—a compression fracture of the vertebra—is often sudden and may be accompanied by symptoms of compression of the spinal cord. Radiologically, the development of the tumor manifests as large foci of rarefaction [see separate table (p. 135-136), fig. 7], which disappear upon compression of the body. Osteosclerosis in sarcoma is a great rarity (Reinberg). The intervertebral cartilages remain unchanged. Clinical symptoms depend on the direction and degree of tumor growth. Intraosseous growth manifests with persistent pains. Then, soon, radicular phenomena join in the form of attacks of severe neuralgic pains. Further growth into the spinal canal leads to compression of the spinal cord, after which death usually soon follows. The tumor may grow outward or inward, spreading to adjacent tissues and organs. Less frequently observed are periosteal sarcomas, the recognition of which is difficult due to the lesser clarity of the X-ray picture. These tumors are sometimes difficult to distinguish from paravertebral sarcomas originating from surrounding tissues—ribs (chondrosarcomas), pleura, etc.—since the former can grow through and infiltrate surrounding tissues, and the latter can secondarily involve the spine. Significant difficulties for recognition are presented by isolated tumors inside the spinal canal, which usually originate from the membranes of the spinal cord and are located either extradurally or intradurally. For the most part, these are either sarcomas or tumors of a mixed type—angio-, myxo-, fibrosarcomas—which early on compress the spinal cord, which is why the differential diagnosis in these cases is made on the basis of the sequence of occurring phenomena—first radicular, then spinal, and only at the end, bone; the latter usually do not have time to develop, in contrast to tumors of the vertebrae, which more often give bone changes first (even if only X-ray), and then radicular and spinal (see Spinal cord). Multiple myelomas are observed in elderly people and, when localized in the vertebrae, can cause bending of the spine and compression fractures with angular and arcuate curvatures. Radiologically, the bone appears as if porous with a multitude of rounded defects having sharp and regular contours. One has to differentiate from cancer metastases, Recklinghausen's disease, and osteomalacia. Cancer of the spine is encountered almost exclusively in the form of metastatic nodes, for the most part multiple, rarely solitary. In percentage terms, the most frequent transfer to bones is given by cancers of the prostate gland, then the thyroid and mammary glands, less often the uterus and other organs, but in absolute figures, bone metastases are observed more often in the most common of the indicated diseases—cancer of the mammary gland. The spine, and especially its lumbar part, along with the pelvic bones, is the most frequent localization of metastases to the skeletal system. Usually, such metastases appear already in far-advanced stages of the disease, shortly before death, but they can also be detected comparatively early. Cancer of the spine, like other tumors, in the majority of cases, although not necessarily, manifests itself first of all with attacks of persistent local and radiating radicular pains, passing into constant unbearable suffering, not calmed by either rest or medicinal and physical therapy means. Subsequently, phenomena of compression of the spinal cord and bone destructive changes occur—collapse of the vertebra with the formation of a deformity of the spine. Of the greatest importance for recognition—especially early—is X-ray examination, which can detect cancer metastases even before the primary neoplasm manifests clinically, especially in the prostate and thyroid gland (Reinberg). Radiologically, cancer metastases are observed in two forms—osteoclastic and osteoplastic. More often, osteoclastic destructive metastases are encountered with resorption of tissue and the absence of reactive proliferation of bone substance, manifesting in the form of multiple small rounded homogeneous bone defects with clearly outlined [see separate table (p. 135-136), fig. 7], but uneven contours (in myelomas, the contours are even); these forms are more often observed in metastases, mainly from the thyroid gland, less often the mammary. One has to differentiate from multiple myelomas, Recklinghausen's disease, primary sarcoma of the spine, and in the case of compression—from inflammatory destructive diseases (it differs from the latter by the absence of changes in the intervertebral cartilage). On the contrary, osteoplastic metastases lead to sharp densification, sclerosis of the bone, depending on the developing reactive deposition of bone around the smallest cancer nodules; on the X-ray, the vertebral body, retaining its external shape, appears either in the form of a solid dense shadow or in the form of vaguely outlined merging sclerotic spots. Usually, osteoplastic metastases are observed in cancer of the prostate gland. One has to differentiate these forms from other sclerosing processes—osteomyelitis, syphilis, Calvé's disease, etc. Approximately the same picture can be given by bone metastases in hypernephroma, which can be detected significantly earlier than the primary disease, as well as in multiple metastases of malignant adenomas of the thyroid gland. Echinococcus of the vertebrae is encountered extremely rarely. According to Reinberg, in total about 75 cases of echinococcus of the bones have been published, of which the bones of the pelvis and the vertebrae are most often affected. More often, infiltrating multilocular echinococcus is observed, which permeates the spongy substance with small vesicles, resorbs it, and forms rounded cystic defects. The bone becomes tuberous, as if swollen, the cortical layer thins, necroses, sequestra, and pathological fractures easily occur. Reactive changes in the bones are absent. The growth of echinococcus in the vertebrae is slow—over years, by which it differs from a tumor. Of surgical interest is unilocular echinococcus. Growing into the spinal canal, echinococcal vesicles can cause phenomena of compression of the spinal cord, which usually serves as an indication for surgical interventions. Most often, echinococcus develops from the posterior mediastinum in the region of DII-VI and from the retroperitoneal tissue in the vicinity of the lumbosacral part of the spine. Correct recognition is made rarely, more often at autopsy or during an operation for phenomena of compression of the spinal cord. One has to keep in mind tumors of the spine, cystic osteodystrophies, etc.—Treatment is operative: removal of large vesicles and especially vesicles pressing on the spinal cord. Infiltrating forms are inoperable. According to Borchard and Rothmann, who collected 48 cases of echinococcus of the spine, 17 patients were operated on with 4 cases of recovery. The authors believe that with timely recognition, the majority of the 30 deceased patients could have been saved by operation. V. Operations on the Spine. As was already said above, surgical intervention on the spine has the goal of either eliminating and removing various harmful factors acting mainly on the spinal cord, or strengthening the weakened spine. To the first category of operations belong: opening of abscesses and their aspiration in inflammatory diseases, opening of echinococcal vesicles, removal of tumors, bone fragments, and foreign bodies from the spinal canal, as well as expansion of the latter by means of removing the arch in cases of narrowing of the bone canal. For access to abscesses forming in the posterior parts of the spine, simple incisions of soft tissues serve; for access to pathological accumulations located in the anterior parts of the spine, the same interventions are used as for cold abscesses in tuberculous spondylitis (see). Accumulations in the spinal canal can also be eliminated by means of either punctures or laminectomy (see). Laminectomy is used both for the purpose of examining the spinal cord and for the purpose of removing one or another harmful factor. Removing the arch and opening the spinal canal, one can first of all remove everything that presses on the spinal cord from behind: fragments of arches, foreign bodies, tumors originating from the walls of the arch and spinal membranes. Having severed one or two nerve roots, which according to the studies of Sherrington does not entail significant disorders, one can pull aside the spinal cord, examine the anterior part of the bone wall of the spinal canal, and in case of need remove foreign bodies, fragments, as well as remove wedge-shaped protrusions of vertebral bodies in fractures and displacements of the latter, on which Urban especially insists. At the same time, one can also remove remnants of hemorrhages. If the membranes of the spinal cord are damaged, then after examination of the spinal cord and removal of hemorrhages, one can apply a suture; in cases of the presence of significant defects of the membranes, one can resort to free transplantation of fascia.
Finally, to examine the spinal cord while keeping its membranes intact, it is necessary to open the latter and, depending on the circumstances, remove tumors, hemorrhages, etc. The indications for laminectomy are mainly injuries of the spine and tumors inside the spinal canal, whereas in inflammatory diseases, especially in tuberculosis, they are very limited (see Spondylitis). Operative osteoplastic fixation of the spine—the Albee operation and its modifications—has recently become very widespread, mainly for tuberculous spondylitis, and less frequently for other diseases and injuries. The indication for fixation is insufficiency of the spine and its destructive changes leading to curvature. Thus, operative fixation is used for juvenile kyphosis, traumatic spondylitis, certain forms of compression fractures, as well as for various kinds of dysplasia of the spine, especially in the lumbosacral region, where it is best to use two plates placed to the side of the spinous processes according to Henle. For the technique of osteoplastic fixation of the spine, see Spondylitis.
VI. Occupational pathology of the spine. When describing individual forms of diseases, the causes influencing the occurrence of these or other pathological conditions have already been indicated. Among these causes, occupational working conditions and occupational hazards are of great importance, which boil down to the following factors: prolonged forced position of the spine, its uneven loading, excessive strain, traumatization, cooling, intoxications, and other working conditions affecting the general state of the organism. In turn, the listed factors can have varying degrees of impact on the state and changes of the spine, depending on whether they affect a normal, abnormal, or already pathologically changed spine, given certain age, constitutional, and conditional characteristics of the organism. The influence of occupational hazards on a normal spine affects both the developing and the formed spine. Uneven loading of the spine, improper sitting, excessively prolonged stiffness of movements, and weakness of the musculature lead to "school" scolioses (see) and kyphoses, which are so common in children; the rational fight against them lies in physical education, school gymnastics, correct posture, and the correct alternation of studies and rest. Likewise, heavy physical labor started too early in an adolescent can lead to incorrect posture, round back, scoliosis, etc. Occupational influences on posture and the shape of the back, and consequently on the endurance (work capacity) of the spine, also affect adults. Thus, a round back, bordering on kyphosis, is, as it were, an occupational disease of professions associated with a prolonged forced bent position, especially in persons of heavy physical labor, e.g., loaders (up to 30%), then locksmiths, molders, seamstresses, clerical workers, etc. (Golyanitsky). These changes of the spine impair the function of the chest and the organs of the latter—the lungs, heart. On the other hand, some professions lead to the formation of a flat back, as, for example, in tailors (Hoffa). The weaker the musculature and the longer the forced position, the more the spine assumes a passive position of "fatigue" already at the expense of the support of the bony parts, which ultimately leads to persistent changes in the skeleton, "uncompensated" kyphoses and scolioses. This loss of elasticity, leading to an increase in the pressure of the vertebrae on each other, affects the state of the intervertebral joints and discs and is expressed by changes in the cartilages, narrowing of the gaps, limitation of mobility, and the appearance of pain. If excessive strain and, in particular, injuries—even small but repeated ones—are added to this, conditions are created for a whole series of secondary pathological changes: spondyloarthritis, osteoperiostitis, deforming and ankylosing spondylosis, leading, on the one hand, to limited or diffuse rigidity of the spine, and on the other, to neuralgic and radicular pains (especially lumbosciatica). Uneven or excessive cooling, suffered acute infections, as well as intoxications, aggravate the painful phenomena. Even more than with a normal spine, the influence of occupational conditions affects an abnormal, and therefore inferior, spine. All congenital deformities of the spine, clefts, asymmetries, synostoses, inclusions, and underdevelopment, and especially lumbosacral dysplasias, are that locus minoris resistentiae on which the influence of occupational hazards tells with special force, early putting these patients out of action and making them invalids. The same applies to the influences of occupational hazards on a pathologically changed spine, whether it is a latent process in the vertebrae (e.g., tuberculosis) or the consequences of a suffered disease that caused certain deformities, adhesions, etc., not to mention active processes, in which any strain has a particularly unfavorable effect. Therefore, a preliminary thorough examination of the spine, especially X-ray, and proper selection can, on the one hand, prevent the possibility of serious complications in such persons, and on the other, provide a key to the correct choice of profession. Finally, it is necessary to emphasize the influence of spinal trauma. In the section on fractures, it was already mentioned that some professions, e.g., miners, are particularly often exposed to severe spinal trauma with all its disastrous consequences. However, even less significant injuries in many professions associated with lifting heavy weights and vibrations can often, without causing clear clinical symptoms at first, subsequently lead to various kinds of diseases; these include traumatic spondylitis of the Kümmell type, changes associated with damage to the nuclei pulposi, unrecognized compression fractures, cracks, avulsions, etc. Thus, the influence of occupational factors on the spine is very diverse, which forces one to study working conditions with special attention to eliminate occupational hazards and prevent their impact on the spine. At the same time, it is necessary to thoroughly examine the spine of persons sent to work to determine its strengths and weaknesses (musculature, elasticity, posture, anomalies, pathological conditions) in order to correctly choose a profession corresponding to the identified characteristics of the given subject and his spine. P. Kornev.
Related articles
Mentioned in
Cite this page
“Spine.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/vertebral-column/