Spinelli
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
A biographical sketch of Pier Giuseppe Spinelli (1862-1929), a prominent Italian gynecologist and surgeon known for his work in operative gynecology and the pathology of female reproductive organs.
Encyclopedia article (1928–1936)
SPINELLI (Pier Giuseppe Spinelli, 1862-1929), a prominent Italian gynecologist, brilliant surgeon, one of the pioneers of operative gynecology, former assistant to the famous Morisani. Spinelli received his medical education
in Naples, where from 1900 until his death he headed the gynecological department at the Ospedale di S.M. della Pace. He left a large literary legacy; among his works, studies on tuberculosis of the female genital sphere, ectopic pregnancy, and uterine inversion are particularly well known. Spinelli was one of the first to persistently emphasize the necessity of a public campaign against cancer. SPINAL CORD. Contents: I. Phylogeny.....................279 II. Ontogeny.....................284 III. Anatomy.....................287 IV. Physiology.....................302 V. Pathology.....................310 VI. Surgery.....................321 Spinal cord (medulla spinalis), the posterior or lower part of the central nervous system, located in the vertebral canal. I. Phylogeny. The spinal cord progressively develops at various stages of the animal kingdom. In the most primitive stage of development in Amphioxus, it has the shape of an irregular tube (Fig. 1), in the center of which runs the central canal. The anterior and posterior roots depart,
alternating not at the same level of their periphery. The peripheral processes branch strongly. The initial cells of the anterior roots are not yet localized with precision, but
Figure 1. Cross section of the spinal cord of Amphioxus: 1 - myotome; 2 - anterior and posterior roots; 3 - spinal cord.
lie at the level of root exit. The posterior roots contain three types of fibers: somatosensory (for the skin), viscero-sensory (for mucous membranes), and motor fibers (for visceral musculature). The cells of the posterior roots are bipolar and lie partly intramedullary and partly on the extramedullary segment of the root; at the entrance of the roots are cells whose axons form the second sensory neuron. In cyclostomes (Cyclostomata), the cross section of the spinal cord has an oval shape, as does the central canal; the anterior and posterior roots also alternate (Fig. 2). The gray matter
of the canal and corresponds to the mixed anterior and posterior horns (Figure 3); within it are cells giving rise to the anterior roots. The posterior root also contains three types of fibers: somatosensory, viscerosensory, and visceromotor; part of the root fibers originates in intramedullary bipolar cells, while the rest originate in cells lying outside the substance of the brain.
Figure 3. Cross section of the spinal cord of Cyclostomata: 1 - sensitive dorsal cells; 2 - posterior column; 3 - lateral column; 4 - gray matter; 5 - Müllerian fibers.
The central process of these cells runs in the dorso-lateral region of the spinal cord and sends collaterals into the gray matter. The arrangement of the cells of the visceromotor fibers is not precisely known. The secondary systems of the spinal cord are better developed
Figure 4. Cross section of the spinal cord of Plagiostomi: 1 - posterior root fibers; 2 - posterior column; 3 - central fibers; 4 and 6 - anterior roots; 5 - anterior columns; 7 - tractus octavo-spinalis lateralis cruciatus; 8 - lateral column; 9 - marginal plexus of dendrites; 10 - ascending and descending fibers of the posterior roots.
than in Amphioxus: ventral arcuate fibers of the secondary sensory pathways running in the anterior columns, short intersegmental fibers, short ascending pathways to the cells of the substantia reticularis of the medulla oblongata, and finally a system of fibers formed by Müllerian fibers running from the frontal zone of the brain through the entire spinal cord. The fibers are devoid of myelin. The spinal cord of Plagiostomi is the prototype of the spinal cord of higher animals; its fibers are surrounded by myelin, and the gray matter has a structure similar to that of higher animals (Fig. 4). The anterior and posterior roots join and give fibers to the viscera and blood vessels; the sympathetic boundary trunk does not yet exist, and cervical and lumbar enlargements are also absent. The posterior sensory part of the spinal cord differs from the anterior by the arrangement of the posterior horns, which connect with each other, whereas the anterior horns are clearly demarcated. In the anterior roots, besides somatomotor fibers, there are visceromotor ones; the posterior roots contain the same fibers as in cyclostomes; they originate already in the spinal ganglia, their central processes partly terminating in the posterior horns and partly running into the spinal cord in an ascending direction. The cells of the anterior horns are connected by dendrites with fibers or collaterals
Figure 5. Cross section of the spinal cord of Teleostei (fish); 1 - nucl. cervicalis ventralis motor.; 2 - nucl. cervicalis dorsalis motor.; 3 - n. spinalis motor.
Figure 6. Cross section of the spinal cord of Amphibia (frog); 1 - posterior column; 2 - posterior root; 3 - anterior root; 4 - lateral column.
anterior roots; 4 - lateral column.
very small. Ascending endogenous fibers conducting sensitivity, homo- and heterolateral (tract. spino-bulbaris, spino-mesencephalicus, spino-cerebellaris). In amphibians (Amphibia), the spinal cord is greatly reduced
Figure 8. Cross section of the spinal cord of Reptilia (schematic representation of cells and fibers): 1 - fasc. dors.; 2 - posterior horn; 3 - posterior root; 4 - lateral horn; 5 - marginal plexus of dendrites; 6 - commissura ant.; 7 - sensitivo-motor collaterals.
compared to the spinal cord of Plagiostomi (Fig. 6); the number of spinal nerves in tailless amphibians is 10-11 (whereas in sharks it is about 100), while in tailed amphibians there are more nerves because the tail is also innervated. Cervical and lumbar enlargements appear for the first time. In the anterior horns, two groups of cells can be distinguished: one, inner, extends throughout the entire spinal cord; the other, outer, only at the levels of the enlargements. The cells give rise to the anterior roots; the dendrites of the cells, forming plexuses, cover the surface of the spinal cord. The posterior roots originate from cells of the spinal ganglia (in the embryo from intramedullary cells); their central process forms two bundles: one is located in the marginal zone of the posterior horns, the other in the posterior columns; the reflex arc is effected by collaterals from the fibers of the posterior columns terminating at the cells of the anterior horns. Of the secondary pathways, crossed sensory ones are known (tract. spino-bulbaris, spino-mesencephalicus), in addition to the uncrossed tr. spino-cerebellaris. The short pathways are the same as in fish. Of the descending fibers, the roots of nerves V, VIII, and X enter the spinal cord; the root of nerve V extends to the lumbar segment.
The spinal cord of reptiles (Reptilia) can be regarded as a preliminary stage in the structure of the mammalian spinal cord (Fig. 7). It differs from the spinal cord of the frog (amphibians) in that it fills the entire vertebral canal, which is associated with the existence of metameric tail musculature. In this class, three types of spinal cord can be distinguished depending on the development of the musculature: 1) in the lizard, the back and limb musculature is well developed, and the spinal cord has enlargements; 2) in snakes, only the back musculature is developed, and there are no enlargements in the spinal cord; 3) in the turtle, the back musculature is not developed at all, only that of the neck, limbs, and tail, and the spinal cord in the thoracic part is very thin. In the anterior horns of the cervical region, besides motor cells, there are also sympathetic cells. Figure 9. General view of the spinal cord of a bird (ostrich): 1 and 7 - sulcus medianus post.; 2 - posterior roots; 3 - posterior column; 4 - lumbosacral sinus (sinus rhomboidalis); 5 - sulcus lateralis; 6 - sulc. lateralis post.; 8-14 - anterior roots.
The marginal plexus covering the periphery of the spinal cord is greatly reduced, and marginal cells appear in its place. The posterior roots originate from the spinal ganglia, the number of fibers in them is increased; the ascending central process runs in the posterior columns in the lizard and in the lateral columns in the snake and turtle. The nuclei of the posterior columns appear for the first time (Fig. 8), which send fibers into the medial




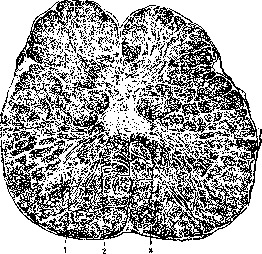
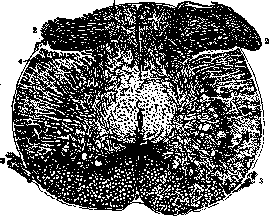
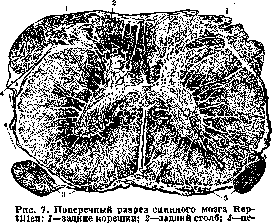
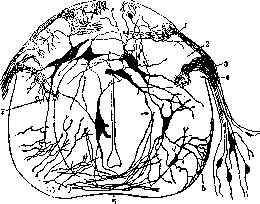

Figure 10. Cross section of the spinal cord in birds: 1 - posterior horn; 2 - cells of the anterior horn. loop. The complication of the central sensory apparatus occurs in parallel with the development of the peripheral sensory apparatus, which depends on the lifestyle. In all other respects, the structure is the same as in amphibians. The spinal cord of birds (Aves) differs from the spinal cord of reptiles by the greater length of the cervical region and the presence of a lumbosacral sinus between the posterior columns (Fig. 9). The swellings are very well developed; in flying birds, the lumbosacral swelling is better developed; the anterior roots and horns are better developed than the posterior; in the anterior horns, the inner and outer cell groups are well developed (Fig. 10). The marginal plexus is weakly expressed, and in its place the number of marginal nuclei is increased. The posterior roots originate in the spinal ganglia, and their fibers in the spinal cord run in the posterior columns and in the marginal zone; due to the small size of the posterior roots, the posterior columns are rather poorly developed. The nuclei of the posterior columns are small. Endogenous fibers are more numerous than in reptiles, especially short intrasegmental fibers. Tractus spino-bulbaris and spino-mesencephalicus are very well developed, the dimensions of tr. spino-cerebellaris are also increased; descending bundles of tract. cerobollo-spinalis, tr. vestibulo-spinalis, rubro-spinalis, tr. tecto-spinalis appear, and they pass in the anterolateral column. The spinal cord of birds is under the great influence of higher centers. In mammals, the general structure of the spinal cord corresponds to the structure of the human spinal cord, with only minor changes in details depending on the presence of a tail, lifestyle, and the absence of lower limbs. For example, in the whale, due to the absence of lower limbs, the lumbar swelling is absent; it is very well developed in the kangaroo. The nucleus and fasciculus of Goll are less developed in animals lacking lower limbs. The size and length of some bundles also change. Pyramidal bundles gradually increase: in dogs they make up 10% of all white matter of the spinal cord, in monkeys 20% and in man 30%. II. Ontogeny. The rudiment of the central nervous system is the neural or cerebral plate - a long and wide
j strip of ectodermal cells, consisting of two halves separated by the neural groove (Fig. 11); the edges of the plate rise, meet each other and connect, due to which first a neural groove is formed, and then a cerebral, fig. 11, OR neural
medullary plate
Breathing in various stages of development or canal,
development. A neural plate (Figure 12). Furthermore,
ka, or strip: 1 and 3-medullary plate; e - medullar
y, or neural groove, 4-protovertebrae; b-chorda dorsalis; b-neural groove:
da dorsalis; b-neural groove: 7-neural groove;
box; 2-ganglionic plate;
s-pleuroperitoneal cavity; 4-skin-fibrous plate; 5-fibromuscular plate; 6-neural tube. 1 - cardiac fossa; 2 - endodermal plate; 3 - ectodermal plate; 4 - double mesodermal plate.
shin, which divide into ganglia spinalia and ganglia sympathica. The cerebral plate, groove and tube lie on chorda dorsalis. The closure of the neural groove begins at the level of the midbrain, and last of all occurs at the level of the spinal cord. The cerebral tube in the early period of development is in communication with the epidermal tube and with the gastral-canalis neurentericus.
Cross section 28S On the fourth week of development, the spinal cord in the embryo is formed by two thick lateral walls (Fig. 13) connected above and below by poorly developed commissures. The longitudinal lateral furrow divides the lateral walls into two plates: the anterior - basal (lame fondamentale de
Figure 12. Cross section of the medullary plate at a later stage of development: 1 - medullary tube; 2 - intervertebral ganglion; 3 - pharynx; 4 - pleuroperitoneal cavity; 5 - pericardial part; 6 - rudiments of heart cells; 7 - ectodermal pocket of the lower surface of the head.
His), giving rise to all motor nerves, and the posterior (lame alaire de His), receiving sensory fibers. The ventral commissure connects the basal plates, and the dorsal - the posterior ones. The cavity of the spinal cord has the shape of a slit elongated in the anteroposterior direction. In the second month of development, the lateral walls bend, due to which the shape of the central canal changes (Fig. 14); in it, 4 furrows can be noted - anterior and posterior, very narrow, and lateral furrows, wider. The anterior and posterior parts of the wall are connected by an intermediate plate. The anterior plate is bounded by a cylindrical furrow, from which the anterior and lateral horns develop, anterior
Figure 13. Cross section of the spinal cord of a human embryo of 4 weeks: 1 - posterior plate; 2 - anterior plate; 3 - ventral commissure; 4 - motor roots; 5 - meningeal limiting septum;
of the plate, anterior roots, anterior part of the lateral horns, posterior part of the lateral plate give rise to the posterior horns and radicular zone of white matter (cordon ovale de His). The intermediate plate, located between the cylindrical furrow and the marginal furrow, corresponds to the wide part of the canal; it gives rise to the neck of the posterior horn, Clarke's column, processus reticularis, and the posterior part of the lateral column; in this region, the crossed pyramidal bundle and Flechsig's bundles appear later. With the increase in the gray matter of the spinal cord, which sends fibers into the columns, the anterolateral columns also increase, which in development outpace the posterior columns, which develop only by the end of the 2nd month; at the same time, changes occur in the central canal, which narrows and occupies the central part of the spinal cord and connects with the periphery along the posterior surface of the septum posticum (Fig. 15). The development of gray and white
matter does not occur simultaneously in the entire spinal cord, but from top to bottom: the cervical region is ahead of the lower sections of the spinal cord in development. During the 2nd and 3rd months of intrauterine life, the spinal cord occupies the entire spine, and starting from the 4th, the spine develops faster, due to which the spinal cord segments do not maintain relations with the corresponding vertebrae; in the 6th month, the end of the spinal cord reaches the sacrum, and at birth to the III lumbar vertebra. The roots and membranes grow like the spine, due to which the lower roots depart from the spinal cord not at a right angle, as in the cervical region, but with an inclination downward and outward, and this inclination is greater the lower the roots are. All fibers of the spinal cord are covered with myelin not simultaneously, but in strict sequence. In the 5th month of intrauterine life, the fibers of the main bundle are covered with myelin. Starting from the 6th month, there appears
Figure 14.
Figure 15.
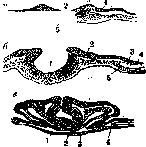
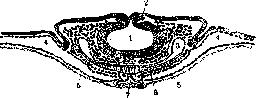
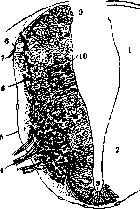
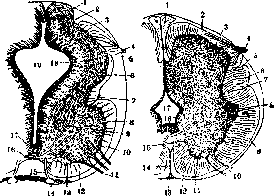
Figure 14. Cross-section of the spinal cord of a human embryo 41/2 weeks, 12.5 mm in length (thoracic region); 1 - outer gray lamina; 2 - inner gray lamina; 3 - root zone; 4 - posterior, sensory roots; 5 - marginal groove; 6 - intermediate lamina; 7 - cylindrical groove; 8 - lateral horns; 9 - arcuate fibers; 10 - anterolateral column; 11 - anterior roots; 12 - anterior column; 13 - a. spinalis ant.; 14 - groove artery; 15 - anterior commissure; 16 - base of the central canal; 17 - ependyma; 18 - central canal. Figure 15. Cross-section of the upper thoracic region of the spinal cord of a 3-month human embryo: 1 - Goll's tract; 2 - Burdach's tract; 3 - posterior horn; 4 - posterior, sensory root; 5 - marginal groove; 6 - lateral column; 7 - cylindrical groove; 8 - lateral horn; 9 - anterolateral column; 10 - anterior, motor root; 11 - anterior horn; 12 - anterior column; 13 - a. spinalis ant.; 14 - anterior median groove; 15 - anterior commissure; 16 - ependyma; 17 - central canal. Myelin appears in the fibers of the flexor tract, while in the Govers tract the fibers become myelinated later and in the newborn are not yet fully covered with myelin. The fibers of Goll's and Burdach's tracts do not become myelinated simultaneously; in Goll's tract it appears later. The fibers of the pyramidal tract are covered with myelin last (even in the newborn it is still poor in myelin), the development of which ends in the 2nd year of life.
Histogenesis. At the moment of development, the medullary groove or tube consists of cylindrical epithelium, the neuroepithelial cells of which are arranged in a single layer. The cells are located between two partitions (membr. limitans externa and membr. limitans interna), which limit the cavity of the central canal. The cells consist of ectoplasm and endoplasm containing a nucleus, which lies closer to the outer partition; near the inner partition 'among the epithelial cells there are very large round cells, lying at some distance from each other; they have very large nuclei, some in a state of rest, others in a state of karyokinesis; these are cellulae germinativae (Keimzellen de His); these cells besides the neural plate are also in the ganglionic plate. The epithelial cells multiply rapidly and due to this they are compressed and stretched, the nuclei begin to be placed at different levels, thereby giving a multilayered appearance to the lateral wall (fig. 16), but in reality the layer remains one, and each cell retains connection with both partitions; in this layer three parts, or zones, can be distinguished: the middle - nuclear zone, and two lateral, devoid of nuclei: internal - columnar zone, in which the germinal cells are located; it forms the supporting framework for the gray matter; outer - marginal zone, forming supporting tissue for the white matter.
The number of germinal cells in a very small embryo (4 weeks) is very large, in places they form a continuous row, later their number decreases. Their size varies from 10 to 14 μ. Epithelial and germinal cells give rise to the elements of the nervous system: epithelial cells turn into spongioblasts, forming the ependyma, and from germinal cells develop neuroblasts - nerve cells and neuroglia. Neuroblasts have a pear-shaped form, and on the thin end the axial cylinder develops by the displacement of protoplasm from the cell. Neuroblasts partially migrate into the deeper layers of the wall.
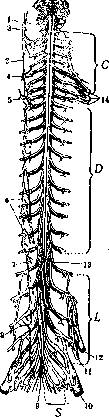
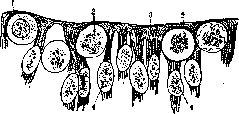
Figure 16. Internal spongioblastic and germinal cells: 1 - membrana limitans externa; 2 - germinal cell; 3 - columnar zone; 4 - spongioblasts.
III. Anatomy. The spinal cord above without sharp boundaries passes into the medulla oblongata, below it ends in a cone (conus medullaris), from which a thread-like continuation (filum terminale) extends (fig. 17). In filum terminale there are 2 parts - internum and externum. Fil. terminale internum, 16 cm in length, is located inside the sac of the dura mater between the lumbar and sacral roots, extends to the II sacral vertebra. Fil. terminale externum, 8 cm in length, is surrounded by the dense dura mater (vagina terminalis), which forms filum durae matris spinalis and ends in an expansion on the II coccygeal vertebra. The upper end of the spinal cord is considered the place of exit of the first cervical roots and the beginning of the decussation of the pyramidal fibers. Along its entire length, nerves originate from the spinal cord, beginning with two roots - the anterior motor (radix anterior medullae spinalis) and the posterior sensory (radix posterior); both roots of the spinal cord, connecting, form the spinal nerves, which exit through the intervertebral foramina.
The spinal cord has a symmetrical cylindrical shape, flattened in the dorsoventral direction, especially on the anterior surface. Along its length there are two bends - cervical and thoracic, merging into each other at the level of the VII cervical vertebra. The spinal cord is divided into departments or parts (pars): cervical (pars cervicalis medull. spinalis), thoracic (pars thoracalis), lumbar (p. lumbalis), sacral (p. sacralis) and coccygeal (p. coccygea). Each department in turn is divided into segments, of which there are 31-33. A segment is a portion of the spinal cord (fig. 18) giving rise to two pairs of roots; thus the number of segments corresponds to the number of roots: in the cervical department there are 8 segments, in the thoracic - 12, in the lumbar - 5, in the sacral - 5 and in the coccygeal - 1-3 segments. The first cervical nerve leaves the vertebral canal between the occipital bone and the I cervical vertebra, the second between the I and II cervical vertebrae, etc. Since the spinal cord is shorter than the spine (it ends at the level of the II lumbar vertebra), the roots must pass a more or less long distance in the vertebral canal (fig. 19) to reach their exit opening; this distance is particularly significant for the lumbar, sacral and coccygeal roots; together with filum terminale these roots form the so-called 'horse's tail' (cauda equina).
The spinal cord does not maintain the same thickness, width and shape throughout its entire length; in those places where large nerves for the limbs depart from the spinal cord, there are spindle-shaped thickenings; the upper, cervical Figure 17. Spinal cord, above connected to the medulla oblongata: 1 - p. accessories spinalis; 2 - border column; 3,4,5 - upper, middle and lower cervical sympathetic nodes; 6 - thoracic sympathetic nodes; 7 - lumbar sympathetic nodes; 8 - rami communicantes; 9 - filum terminale; 10 - n. ischiadicus; 11 - n. obturatorius; 12 - n. cruralis; 13 - conus terminalis and beginning of filum terminale; 14 - plexus brachialis. C, D, L, S - cervical, thoracic, lumbar and sacral roots. thickening (intumescentia cervicalis) is formed by the four lower cervical segments and the first thoracic; the lower, lumbar thickening (intumescentia lumbalis) includes lumbar segments from II to V and sacral I and II. On the spinal cord there are several longitudinal grooves (fig. 17,18 and 20); the anterior longitudinal groove (fissura mediana ant.) penetrates to a depth of 4 mm, lies on the anterior surface, extends upward to the foramen caecum
spinal cord
heights. in men and 41-42 cm in women. The transverse diameter in the thoracic region is 10 mm, the sagittal is 8 mm; in the widest part of the cervical enlargement it is 13-14 mm, in the lumbar enlargement 12 mm. The weight of the spinal cord is 34-38 g; specific gravity 1.034, volume 39 cm3. Topography. In relation to the skeleton, the upper end of the spinal cord corresponds to the upper margin of the first cervical vertebra, and the conus terminalis to the upper margin of the second lumbar vertebra. The cervical enlargement begins at the level of the third cervical vertebra and ends at the second thoracic. The lumbar enlargement begins in the region of the tenth thoracic vertebra, with the twelfth thoracic corresponding to the widest part of the enlargement. Structure of the spinal cord. On transverse sections of the spinal cord, it can be seen that it consists of two symmetrical halves connected in the middle by commissures. In the spinal cord, two substances are distinguished - gray and white (substantia grisea and substantia alba) (Fig. 20); the gray substance lies in the center and is surrounded by the white substance. The gray substance
12 11
Figure 20. Transverse section of the spinal cord: 1 - fissura mediana post.; 2 - septum posticum; 3 - posterior columns; 4 - commissura alba post.; 5 - apex; 6 - cervix of the posterior horn; 7 - lateral horn; 8 - lateral column; 9 - commissura grisea; 10 - commissura alba ant.; 11 - anterior column; 12 - fissura mediana ant.; 13 - anterior horn; 14 - sulcus lateralis ant.; 15 - formatio reticularis; 16 - Clarke's column; 17 - substantia gelatinosa Rolandi; 18 - sulcus lateralis post.; 19 - central canal. forms paired projections, horns (cornua), syn. gray columns or pillars (funiculi cinerei, s. columnae griseae). The large projection of gray substance turned toward the anterior surface forms the anterior horns (cornu anterius, s. columna anterior, s. funiculus cinereus anterior), its posterior part passes into the posterior horn (cornu posterior, s. columna posterior, s. funiculus cinereus posterior); the posterior horn first narrows into the neck (cervix columnae posterioris), and further posteriorly expands into the head (caput columnae posterioris) and finally narrows again into the apex (apex cornu posterioris), which corresponds to the sulcus lateralis posterior; at the apex is the substantia gelatinosa columnae posterioris Rolandi, s. substantia gelatinosa Rolandi, to which a narrow layer of the zona spongiosa, or zonal layer of the posterior column, adjoins posteriorly. Besides the anterior and posterior horns, at certain levels of the spinal cord (thoracic region) lateral horns (columnae laterales) are also well expressed, which depart from the base of the anterior horn; from the lateral horn to the posterior through the lateral columns go reticular trabeculae of the gray substance, forming the formatio or processus reticularis. The gray substance of both halves of the spinal cord is connected to each other by a bridge, an isthmus of gray substance (commissura grisea), in the center of which is the central or spinal canal (canalis centralis medullae spinalis), lined with ependyma. The shape of the central canal is very varied - slit-like, round, oval, triangular; sometimes the canal is filled with ependymal cells; it is surrounded by gelatinous substance (substantia gelatinosa centralis). Closer to the medulla oblongata, the central canal turns into a sagittal slit. In the conus medullaris, the canal approaches the posterior central sulcus and expands at the end of the cone into the ventriculus terminalis Krause. Anterior to the commissura grisea lies the anterior commissure, or adhesion (commissura alba anterior), and posterior to it the posterior adhesion (commissura alba posterior), formed by a small number of fibers. The white substance of the spinal cord consists of longitudinal ascending and descending myelin fibers separated by partitions of neuroglia; running in the transverse direction are root bundles, fibers in the commissures, and fibers or their collaterals terminating in the gray substance. The white substance of the spinal cord is divided into columns or funiculi: the anterior column lies between the fissura mediana anterior and the anterior roots; the lateral column between the anterior and posterior horns; and the posterior column between the posterior horn and the sulcus medianus posterior and its continuation into the depth down to the commissura alba posterior - septum posticum. Figure 21. Cell groups in the gray substance of the thoracic spinal cord (I). 1 - cells of the anterior horn; 2 - internal group of the lateral horn; 3 - nucleus sympathicus lateralis sup.; 4 - group of Knyazhkovsky's cells; 5 - commissural group of cells.
The amount of gray substance, the shape of its horns, and its relation to the white substance vary depending on the level: in the cervical region the anterior horns are larger in size and significantly wider than the posterior, with a large amount of white substance; in the thoracic region the size of the anterior horns decreases, the figure of the gray column resembles the letter H; in the lumbosacral region not only the anterior but also the posterior horns increase, and their shape bears a great resemblance to a butterfly (see separate table, pp. 295-296). The spinal cord is formed by nerve cells and fibers surrounded by a supporting framework consisting of two tissues - connective tissue processes of the pia mater and neuroglia (see). The neuroglia does not have the same appearance everywhere; three of its types can be distinguished: ependyma (see), neuroglia of the gray substance, and neuroglia of the white substance. In the gray substance there is a large number of fibers and neuroglia cells; in the white substance they have a more regular arrangement between the longitudinally running nerve fibers; on the outer surface of the white substance the neuroglia forms a thin, dense layer - the cortical layer, the subpial layer of Waldeyer, covered on the outside by the pia mater. The nerve cells of the spinal cord are scattered throughout the gray substance, in places forming accumulations or groups or nuclei of the spinal cord in it. The basis for the classification of nerve cells
can be taken as either their topographical arrangement or the course and termination of their axon. On the basis of the topographical arrangement of nerve cells, the following are distinguished (Fig. 21): 1) Anterior horn groups - anterior and posterior medial groups, anterior and posterior lateral; they extend throughout the entire spinal cord continuously down to
Figure 22. Cell groups in the gray substance of the cervical spinal cord (CVI); 1 - antero-internal group; 2 - middle group; 3 - antero-external group; 4 - central group; 5 - center of m. deltoidei; 6 and 7 - outer and inner divisions of the posterior group; 8 - cells of the posterior horn; 9 - commissura grisea. III sacral segment; at the level of the enlargements, other groups join them (Figs. 22 and 23); the cells of these groups belong to the largest nerve cells, reaching a size of 100 µ; a group of cells at the base of the anterior horn, near the anterior commissure - tractus cellularum medio-ventralis (Jacobson's).
Figure 23. Cell groups of the lumbar spinal cord (IV): 1 - antero-internal group of cells; 2 - central group of cells (for m. semitendinosus); 3 - antero-external group (for m. glutaeus sup.); 4 - group of cells for m. gastrocnemius; 5 - group for m. tibialis anticus; 6 - group for extensors of the toes; 7 - group for flexors; 8 - group for m. plantaris; 9 - central canal; 10 - central group of cells (for m. biceps femoris). 2) The group of the lateral horn (s. intermedius lateral. tract. Clarke's, s. nucleus sympathicus lateralis superior Jacobson's) consists of small oblong cells that can be found in the processus reticularis; this nucleus is located between the eighth cervical segment and the fourth lumbar (Fig. 21); another vegetative nucleus (nucleus sympathicus lateralis inferior) lies between the anterior and posterior horn from the second sacral segment to the coccygeal, and a third (nucleus sympathicus medialis inferior) - at the inner wall of the posterior horn from the fourth lumbar segment to the coccygeal. Between the posterior and lateral horns there are scattered cells (tractus cellularum intercornualis Jacobson's). 3) Clarke's cells (nucleus dorsalis, s. nucl. columnae Clarki, or Clarke's column) - a group of cells at the base of the posterior horn on the inner side (Figs. 21 and 24); very well expressed in the thoracic segments and in the upper two lumbar. In other divisions of the spinal cord - in the cervical, lumbosacral - in the corresponding places of the gray substance there are only individual cells - Stilling's cells, or nucleus dorsalis Stillingi; they are regarded as a continuation of Clarke's column; the cells of this column contain pigment. 4) In the posterior horn, such large pigmented cells are partly scattered along the periphery
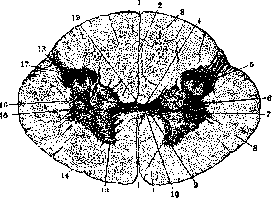

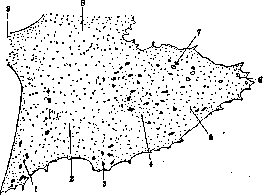
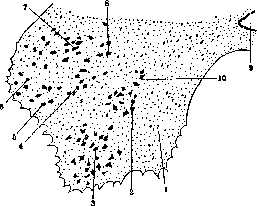
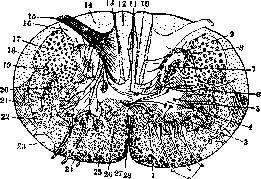
Figure 24. Cross-section of the spinal cord; schematic representation of the main cell groups and main bundles: 1-internal-anterior group of the anterior horn; 2-anterior roots; 3-external-anterior group of cells; 4-central group; 5-external-posterior group; 6-group of cells of Clark's column; 7-group of cells 'caput' of the posterior horn; 8-substantia gelatinosa; 9-stratum zonale; 10-main bundle of the posterior column; 11-oval field of Flechsig; 12-bundle of Goll; 13-comma of Schultze; 14-bundle of Burdach; 15-posterior root; 16-zona Lissaueri; 17-pyramidal crossed bundle; 18-bundle of Flechsig; 19-bundle of Monakow; 20-main bundle of the lateral column; 21-bundle of Gowers; 22-fasc. testo-spinalis along with fasc. vestibulo-spinalis and fasc. spino-reticularis post.; 23-fasc. Helwegi; 24-fasc. spino-reticularis ant.; 25-main bundle of the anterior column; 26-fasc. commissuralis; 27-direct pyramidal bundle; 28-fasc. sulco-marginalis. (cellulae marginales Waldeyeri, nucleus pericornualis Jacobsoni), and partly form the central group in the posterior horn (nucleus magnocellularis centralis cornus posterioris Jacobsoni). In substantia gelatinosa there are small nerve cells-Girke-Virchow bodies, and in zona spongiosa-individual marginal or border cells. According to their location and axon termination, nerve cells are divided into (fig. 25 and 26): 1) Root cells (cellulae radiculares) in the anterior-lateral parts of the anterior horns, multipolar in shape, the largest in size, motor in function; their axon cylinder is directed into the anterior root. 2) Commissural cells (cellulae commissurales), located in the internal parts of the anterior horn, in close proximity to the central canal; they are also in the posterior horn; their axon crosses through the commissure to the anterior column of the opposite side; they are thus commissural-columnar cells (van Gehuchten). Cells are described whose axon branches in the anterior horn of the opposite side-commissural cells with short axons, commissural cells of the 'type'
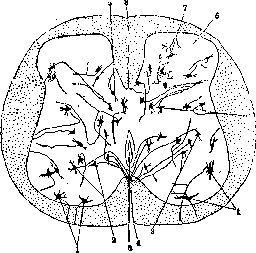
Figure 25. Cells of the spinal cord and the course of their axon cylinders: 1-root cells; 2-commissural cells; 3-commissura ant.; 4-fissura mediana ant.; 5-posterior column cells; 6-substantia gelatinosa Rolandi; 7-cells with short processes; 8-fissura mediana post. , Golgi. 3) Columnar cells (cellulae funiculares), constituting the largest number of cells; they are found everywhere, their neurites are directed to the anterior, lateral and posterior columns; most cells are in the lateral column, especially many in the external parts of the gray
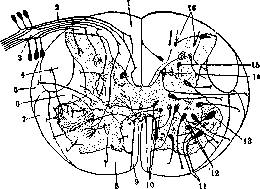
Figure 26. Diagram of the structure of the spinal cord: 1-posterior column; 2-posterior roots; 3-intervertebral ganglion; 4-crossed pyramidal tract; 6-bundle of Flechsig; 6-main bundle of the lateral column; 7-bundle of Gowers; 8-anterior column; 9-direct pyramidal tract; 10-commissural cells; 11-anterior root; 12-columnar cells (of the anterior-lateral bundle); 13-root cells; 14-cells of Clark's column; 15-cells of type II Golgi; 16-cells of the posterior horn- substantia gelatinosa Rolandi.
substance; very few cells in the posterior column; they lie in the posterior horns and in substantia gelatinosa. The neurites of these cells form centripetal pathways; there are short and long pathways. The neurite of a cell is directed to the corresponding column and there, bending, goes upward or divides in a T-shape, with one branch going in the ascending direction, the other in the descending, or one goes to the lateral column and the other to the anterior. 4) Cells with short axons (syn. cells of Golgi type II, s. cellulae axiramificatae); they are most often found in the posterior horn and in substantia gelatinosa; their neurite divides near its origin; sometimes along the anterior commissure the neurite goes to the gray matter of the opposite side, where it ends with branches (s. cellulae commissurales axiramificatae); these cells are interneurons, their purpose is to transmit irritation from the posterior roots to other cells of the gray matter. 5) A special group is formed by the cells of the posterior roots (cellulae radiculares post.); they lie outside the spinal cord in the spinal ganglia or spinal ganglia. Some authors assume that there is a small part in the anterior horns, and their neurite penetrates into the posterior root. The cells of the spinal ganglia are pseudounipolar; their process divides in a T-shape; the central end of the process-neurite-forms the posterior roots, while the peripheral process-a long dendrite-ends in peripheral organs (fig. 27). The root cells of the anterior horn are the motor centers of the spinal cord, as indicated by their connection with the anterior roots. Two groups of cells in the anterior horns-internal and external-are found throughout the spinal cord, while at the level of the enlargements other groups are added to them (fig. 21-23). The first group is related to the muscles of the trunk: the anterior-internal innervates the muscles of the spine, it extends to the upper sacral segments; the anterior-external is related to other muscles of the neck and trunk. The groups of cells that appear only in the enlargements must be related to the muscles of the limbs; there are several such groups in each enlargement, but they do not form regular columns-some groups disappear, being replaced by others. In the upper cervical segments, in addition to the usual two groups, a central and a posterior-external are also distinguished, which serve as the beginning of the spinal root of the n. accessorius, being its nuclei-nucleus n. accessorius pars spinalis. The question of what the groups of cells correspond to-whether to individual muscles, peripheral nerves, or segments of the limbs-has not yet been finally resolved; in recent years, there has been a tendency towards the functional
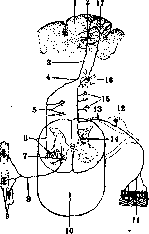
Figure 27. Course of the pyramidal crossed tract and the sensory tract of the posterior bundles: 1-cerebral cortex; 2-Betz cell; 3-pyramidal tract; 4-its decussation; 5-its collaterals; 6-pyramidal tract in the spinal cord and its termination in the cells of the anterior horns; 7 and 8-anterior root; 9-muscles; 10-spinal cord; 11-nerve endings in the skin; 12-intervertebral ganglion1; 13-posterior root, which enters the posterior column (bundle of Goll), sends collaterals (14 and 15) to the gray matter of the spinal cord; 16-nucleus funiculi gracilis; 17-cerebral cortex.
theories—each cellular group innervates muscles connected by one function. Groups controlling movements of more peripheral parts of the body lie outside and behind groups controlling more central muscles. Neuritis of root cells in the anterior horn of the spinal cord forms the anterior roots (radix motoria), while neuritis of cells of the spinal ganglia forms the posterior roots (radix sensi-tiva). The anterior roots consist of centrifugal fibers, while the posterior ones consist mainly of centripetal fibers (the presence of a small number of centrifugal fibers is noted in them). Outside the spinal ganglia, in the intervertebral foramen, the anterior and posterior roots connect to form a mixed spinal nerve (n. spinalis), which, upon exiting the spinal column, divides into ramus posterior (posterior branch), ramus anterior (anterior), ramus com-municans (to the sympathetic border column), and ramus meningeus. The anterior branches, being more significant, connect with each other except in the thoracic region to form plexuses—cervical plexus (see), brachial plexus (see), lumbosacral and coccygeal (see Lumbosacral plexus). The posterior branches innervate the skin and muscles of the occiput and back. From the plexuses arise peripheral nerves, which thus contain fibers from various segments of the spinal cord. White matter of the spinal cord. The white matter of the spinal cord consists of separate bundles, of separate systems. These bundles were identified by special research methods—Flexig's embryological method and the method of secondary degeneration. The first method is based on the asynchronous development of myelin sheaths in the fibers of different bundles; this development occurs strictly sequentially for different bundles and always in the same order. The method of secondary degeneration is even more valuable; thanks to it, many bundles were identified, the direction in which a given bundle passes was studied, and even its origin was determined. All fibers of the spinal cord can be divided into endogenous, or intrinsic fibers of the spinal cord, and exogenous, or foreign ones. Endogenous fibers include those originating in the spinal cord; they can be long and short: long ones—fibrae spino-cerebrales and spino-cerebel-lares, short ones—intersegmental fibers (fibrae intersegmentares), connecting different segments of the spinal cord. Short endogenous fibers lie in the inner parts of the white matter of the spinal cord, while long ones lie in the outer parts. Exogenous fibers are divided into descending (fibrae cerebro-spinales) and ascending—fibers of the posterior roots (fibrae ganglio-spi-nales and ganglio-bulbares). Fibers of the posterior roots enter the spinal cord in the area of Lissauer's marginal belt (syn. marginal zone of Lissauer, s. zona Lissauer'a), located between the end of the posterior horn and the periphery, and in the adjacent part of the posterior column—root zone, then divide into ascending and descending branches. The ascending fibers, varying in length, also differ in direction and termination (fig. 24 and 28): 1) the longest of them from the root zone deviate somewhat inward and occupy the posterior columns, forming two bundles—Goll's bundle and Burdach's bundle; in the lower parts of the spinal cord, only Goll's bundle (funi-culus Golli) exists, which carries fibers from the lower
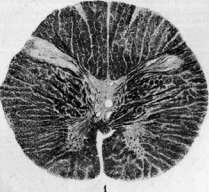
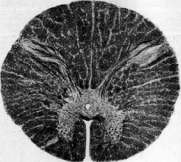
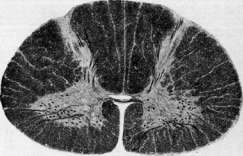
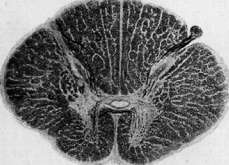
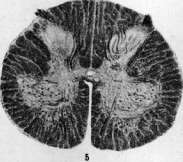
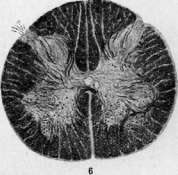
Fig. 1-6, Cross-sections of the spinal cord at various levels. Fig. 1. Transition from the first cervical segment to the medulla oblongata. Fig. 3. First cervical segment. Fig. 3. Seventh cervical segment. Fig. i. \ thoracic segment. Fig. b. Third lumbar segment. Fig. c. First sacral segment. 2»7 limbs and lower parts of the trunk, in the upper parts of it Burdach's bundle (funiculus Burdachi) is added, which carries fibers from the upper parts of the trunk and from the upper limbs. In the upper cervical regions, the boundary between them is very clear—septum paramedianum; there they are renamed: funiculus Burdachi into funiculus cuneatus (cuneate bundle), funiculus Golli into funiculus gra-ciiis (thin, delicate bundle) and end in
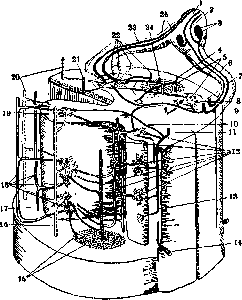
Fig. 28. Main formations of the spinal cord on cross-section and longitudinal section: 1-nervus spinalis; 2-ganglion spinale and cell in it; 3 and 4-fasc. spino-cerebellaris dorsalis; 5-secondary reflex pathway; 6-posterior root; 7-collaterals to posterior horns; 8-bundles of the posterior column; 9-descending pathways of the posterior column; 10-reflex pathway; 11-ascending fibers of the posterior column; 12-secondary reflex pathways; 13-descending fibers of the posterior column; 7 s!-fibers of the posterior root; 15-fasc. cerebro-spinalis laterals; 16-fasc. rubro-spinalis; 17-fasc. vestibulo-spinalis; J 8-fasc. spino-cerebellaris ventralis et fasc. spino-tectalis; 19 - substantia grisea; 20 - fasc. spino-reticnlaris ventralis; SI-fasc. cerebro-spinalis ant.; 22-fasc. reticulo-spinalis; and 85- anterior root; 2i-fasc. cerebro-spinalis late-ralis.
in the medulla oblongata in the nuclei of the posterior columns or funiculi—in nucl. funiculi cuneati and in nucl. funiculi gracilis. All the time fibers from Burdach's bundle pass into Goll's bundle, and new root fibers take their place. 2) Shorter fibers from the root zone go to the cells of the anterior horns, these are reflex fibers; together with the cell and anterior roots they form a reflex arc, in which they are the efferent part (fig. 28). Besides special fibers, collaterals also end near the cells of the anterior horns, these are reflex collaterals of Kölliker. Not only do collaterals end near the cells of the anterior horns, but also near the cells of Clarke and other cells of the posterior horn on the same and opposite sides. Besides the direct reflex arc—there is also an indirect reflex arc, which is carried out by the inclusion of a reflex cell or rather a reflex neuron between the motor and sensory roots. 3) Part of the fibers ends at the cells of Clarke's column and in the cells of the posterior horns. Descending fibers of the posterior roots are shorter, in the lower parts of the spinal cord they are located closer to the midline, and in the upper parts—closer to the gray matter. In the posterior column, besides posterior root fibers, there are also endogenous fibers; the shorter ones occupy the more anterior part of the posterior column zona ventralis, syn. anterior girdle; long endogenous fibers go in the posterior part of Goll's bundle, at the same time they occupy different positions at different levels: in the cervical and thoracic region the bundle of fibers has the shape of a comma—'Schultze's comma', occupies the space between Goll's and Burdach's bundles. At the same level in the posterior part of the column there are scattered fibers, which downward gather at the septum posticum-tractus or fasc. septo-marginalis Ho-che. In the lumbar region they have the shape of a semi-oval—Flexig's oval field, s. tractus cervico-lumbalis dorsalis (Flexig), located at the posterior septum; in the sacral region on the periphery there is Gombault et Philippe's sacral triangle; the last three areas pass into each other and possibly belong to the same endogenous system, while 'Schultze's comma' is a mixed formation consisting of descending posterior root fibers and endogenous ones. In the anterior-lateral column, fibers go in ascending and descending directions. Of the bundles going in the ascending direction, the following bundles should be noted: 1. Fasciculus spino-cerebellaris dorsalis, s. fasc. lateralis, syn. direct cerebellar bundle or Flexig's bundle (see); it consists of neurites of Clarke's column cells of the same side, goes to the cerebellum. 2. Fascicul. spino-cerebellaris ventralis, s. fasc. anterolateralis superficialis, syn. crossed cerebellar bundle, Gowers' bundle (see); originates from cells of the posterior horn of the opposite side. Part of the fibers of Gowers' bundle ends already in the cervical region of the spinal cord, in the nuclei of the medulla oblongata (fibrae spino-bulbares dorsalae), in the quadrigeminal tubercles (fibrae spino-tectales) and finally the large bundle goes to the thalamus (fibrae spino-thalamicae, s. fasc. spino-thalamicus lateralis). It is located inward from Gowers' own bundle, which goes to the cerebellum through its superior peduncles. 3. Part of the fibers of fasc. spino-thala-mici after the decussation does not go into the lateral column, but into the anterior, forming fasc. spino-thalamicus anterior. 4. At the boundary between the anterior and lateral columns, between the anterior roots lies fasc. or tractus spino-olivaris, going to the base of the medulla oblongata; it is separated from the periphery by Goll's bundle (see below). 5. The ascending bundle of the anterior column [fasc. sulco-marginalis ascendens (Marie)] occupies the edge of the anterior sulcus and the nearest part of the anterior column; this bundle is crossed, originates from cells of the opposite side, part of the fibers goes to the medulla oblongata, forming fasc. spino-bulbaris ventralis, part—to the higher parts of the brainstem. Of the bundles going in the descending direction, the following should be noted: 1. Pyramidal bundles, s. tractus cerebro-spinalis, which after decussation in the medulla oblongata divide into two bundles: one goes into the lateral column of the opposite side—tractus cerebro-spinalis lat., syn. lateral or crossed pyramidal
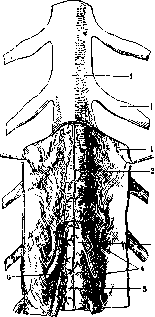
bundle; it lies lateral to the posterior horn, medial to Flechsig's bundle, and terminates in the cells of the anterior horn of its own side (Fig. 27); another pyramidal bundle runs in the anterior column of the same side along the anterior median fissure, part of its fibers terminating in the anterior horn of the opposite side, crossing through the anterior white commissure, while another part terminates in the anterior horn of its own side. The anterior pyramidal bundle is considerably smaller than the crossed one; both bundles gradually decrease downwards, the anterior terminating in the lower thoracic region, and the crossed one reaching the lower end of the spinal cord. 2. Fasciculus rubrospinalis, syn. Monakow's bundle, lies anterior to the lateral pyramidal bundle and medial to Gowers' bundle, originates in the red nuclei, upon emerging from which it undergoes a decussation (Forel's), and terminates in the cells of the anterior Figure 29. Spinal cord and its membranes: 1-dura mater and its
extension onto the roots; 2
arachnoidea; 3-pia mater; 4
lig. denticulatum; 5-arterial
plexus; 6-posterior root.
horns. 3. Fibrae reticulospinales laterales are located lie. around and between the pyramidal bundles and Monakow's bundle, originate from the reticular formation of the opposite side, and terminate in the cells of the anterior horns. 4. Fibrae reticulospinales ventrales run in the lateral parts of the anterior column, in its ground bundle, and originate in the reticular formation of their own side. 5. Fasciculus or tractus vestibulospinalis, s. fasc. Löwenthal'i, syn. anterior marginal bundle, lies along the periphery of the anterior column at the exit of the anterior roots, originates from the cells of Deiters' nucleus, and terminates in the cells of the anterior horns; this bundle is distinguished as the anterior vestibulospinal tract, while part of the fibers or the lateral vestibulospinal tract runs in the lateral column. 6. Helweg's bundle (syn. triangular bundle, s. tractus praeolivaris) is located peripherally at the border of the anterior and lateral columns, between the anterior roots, descends only to the cervical enlargement, and constitutes the continuation of the central tegmental tract. 7. Fasciculus longitudinalis posterior, s. dorsalis, syn. posterior longitudinal bundle, occupies the internal part in the anterior column near the pyramidal bundle, or in its absence lies along the anterior fissure, consists of fibers originating from various cell groups of the brainstem, and terminates in the cells of the anterior horns. 8. Tractus tectospinalis (s. fasciculus praedorsalis, s. tractus marginalis anterior, syn. pretectal bundle) originates in the colliculi, forms Meynert's fountain decussation, and ends in the anterior horns of the spinal cord. 9. Fasciculus praepyramidalis Thomas begins in the outer parts of the reticular formation of the medulla oblongata, runs parallel to the outer edge of the anterior horn, and ends in the anterior horns of the cervical region. The descending fibers in the anterior column together have the shape of a crescent—faisceau en croissant Marie et Guillain. In the lateral columns, besides the above-described pathways, vegetative pathways run not as separate bundles, but as individual fibers mixed with other systems. In the inner parts of the anterolateral column, directly near the gray matter, lie short endogenous fibers, forming the ground bundles (fasciculus proprius) for each column—the anterior ground bundle and the lateral ground bundle; these bundles contain intersegmental fibers connecting various segments of the spinal cord. Membranes of the spinal cord (meninges spinales). The spinal cord is covered by three membranes: the pia mater, the arachnoid (arachnoidea), and the dura mater. The pia mater and arachnoid together form the leptomeninx (Fig. 29). In the region of the foramen magnum, the spinal part of the membranes continues into the cranial part. The pia mater, or vascular membrane, closely adheres to the surface of the spinal cord and penetrates into the furrows; it consists of 2 layers separated by a very narrow space; blood vessels lie between both leaflets and penetrate from the inner leaflet into the brain substance through the adventitial sheath; the initial parts of the sheath form funnels of the pia mater, which connect with the systems of clefts of the pia mater, which are its lymphatic spaces. The nerves of the arachnoid originate from the sympathetic nerve, and spinal nerves are also present; they form a nervous plexus of the pia mater in the outer layer of the membrane. The arachnoid adheres by one surface to the dura mater, being separated from it by the slit-like subdural space (spatium subdurale, s. cavum subdurale medullae spinalis); with its inner surface, the arachnoid fuses with the pia mater by means of numerous trabeculae and membranes; between both membranes lies the subarachnoid or subarachnoid space of considerable width,
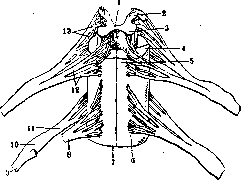
Figure 30. Lower part of the spine with the spinal cord and its membranes: 1-dura mater spinalis; 2-XII radix dorsalis; 3-transverse process of the first lumbar vertebra; 4-conus medullaris; 5-ramus post. n. lumbalis I; 6-ramus ant.; 7 and 9-continuation of the dura mater onto radix lumbalis III; 8-cauda equina; 10-arachnoidea spinalis; 11-gangl. spinalis IV; 12-sacrum; 13-ramus post. n. sacralis I; 14-ramus ant. n. sacralis II; 15-canalis sacralis; 16-filum durae matris spinalis; 17-n. sacralis V; 18-n. coccygeus; 19-coccyx.
filled with cerebrospinal fluid; thus, the arachnoid covers the spinal cord in the form of a wide, loosely fitting sac. The dura mater forms a long and wide sac (dural sac) of cylindrical shape, which is wider than the spinal cord; at the top, it attaches to the edge of the foramen magnum, and at the bottom, at the level of the third lumbar vertebra, it narrows and descends together with the filum terminale of the spinal cord to the coccygeal bone, forming the filum durae matris spinalis (Fig. 30). The dura mater is connected to the walls of the spine by means of connective tissue cords in the form of the anterior ligaments of the dura mater, dorsolateral ligaments of the dura mater, cervical intervertebral ligaments, and the dura mater on the roots. Inwardly, it is connected by subdural threads to the outer surface of the arachnoid. From the pia mater to the dura mater run two symmetrical rows of flat teeth (19-23 teeth each)—the denticulate ligament, or ligamentum denticulatum, s. lig. serratum medullae spinalis; this ligament serves to maintain a straighter position of the spinal cord (Fig. 31). The first tooth is attached below the first root, and the last between the twelfth thoracic and first lumbar roots; lower down to the end runs a lateral strip. By these ligaments, the subarachnoid space is divided into anterior and posterior parts; the anterior subarachnoid space, intersected by the anterior roots, represents a continuous free space; in the posterior subarachnoid space run the posterior roots; with
Figure 31. Membranes of the spinal cord: 1-vertebral body; 2-vena vertebralis; 3-art. vertebralis; 4-intervertebral ganglion; 5-transverse process of the vertebra; 6-anterior root; 7-ligamentum denticulatum; 8-posterior root; 9-septum subarachnoidale post.; 10-spinous process of the vertebra; 11-dura mater; 12-ligamentum flavum; 13-cavum epidurale; 14-bone tissue; 15-cavum subarachnoidale; 16-cavum subdurale; 17-pia mater; 18-ramus post. n. spinalis; 19-ramus ant.; 20-ramus communicans.
the help of the posterior subarachnoid septum, it is divided into right and left halves. Blood supply of the spinal cord. The arteries of the spinal cord belong to the anterior spinal artery and two posterior spinal arteries. The anterior spinal artery originates from the vertebral artery as it emerges from the canal in the transverse processes; both arteries head downwards and towards the midline and merge into an unpaired artery located in the anterior median fissure (Fig. 32), which descends to the filum terminale. The posterior spinal arteries depart at the same level from the vertebral artery, do not unite into a single artery, but run along the sides of the posterior column at the entrance of the posterior roots. The anterior spinal artery along its entire path sends branches through the anterior fissure into the gray matter of the brain, into its anterior horns, to Clarke's cell column; branches from the posterior spinal artery go to the posterior horns of the spinal cord. Besides these two arteries, the spinal cord is also nourished by
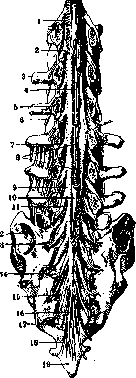
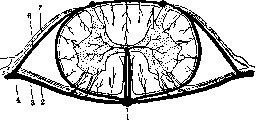
Figure 32. Diagram of arterial circulation on a cross-section of the spinal cord: 1-art. spinalis ant.; 2-anterior root of the spinal cord; 3-anterior branch of the root arteries; i-root artery; 5-intervertebral node; 6-posterior branch of the root artery; 7-posterior root of the spinal cord; 8-art. spinalis post. ramuli medii-spinal branches from the aa. vertebralis, intercostales, lumbales, ilio-lumbales, sacrales, which penetrate along the roots to the spinal cord and, anastomosing with each other and with the aa. spinales, form an arterial network on the surface of the spinal cord, mainly nourishing the white matter. From the vascular network in the spinal cord, radial branches penetrate, which give rise to a network of capillaries densely covering the white and especially the gray matter. From the capillary networks, venous blood collects into two large internal veins-vv. centrales. The external veins are vena spinalis anterior and posterior. e. Konova. IV. Physiology. The spinal cord represents a department of the central nervous system that has to the greatest extent preserved, both in morphological and physiological aspects, the features of the primitive central organ of the nervous system-the segmental apparatus, which is the original organ of the evolution of the central nervous system. The basic fact of this evolution is the superstructure over the segmental apparatus of the mantle department of the brain. One of the anatomophysiological features of the suprasegmental apparatus is that it has no direct connection with the periphery, but is always connected with the latter through the segmental apparatus. Accordingly, in the spinal cord two main functions can be distinguished: 1) reflex activity or the function of the spinal cord's own apparatus and 2) conductive function, i.e., the role of the spinal cord as an intermediate stage between the higher brain and the periphery. The relationship between the brain and the spinal cord can be generally defined as the inhibition by the brain of the mechanisms of the spinal cord's own apparatus and the subordination of the latter to cortical innervations. The basic essence of the function of the spinal cord's own apparatus is determined by its participation in the reflex act. The gray matter of the spinal cord is part of the segmental reflex arc, being the area of synaptic switching of the impulse from the receptor peripheral apparatus, i.e., sensory nerves entering the spinal cord through the posterior roots, to the effector peripheral apparatus represented by the motor cell of the anterior horn of the spinal cord and its process, i.e., the motor fiber of the peripheral nerve. The propagation of the impulse from the periphery along the receptor fiber through the gray matter of the spinal cord to the motor cell and along its process to the muscle determines the role of the spinal cord as a mechanism carrying out the reflex function. The reflex act represents a segmental function of the spinal cord in the sense that the basic mechanism for carrying out this function is the spinal cord's own apparatus and that this function is not directly dependent on the conductive apparatus of the spinal cord. Segmentation should not however be understood in this case in the sense that the reflex is carried out by any single segment. In view of the existence of anatomophysiological connections between individual segments by means of the so-called internsegmental fibers, irritation of a given segment spreads to a greater or lesser number of neighboring segments: reflex reactions are represented not only as "isomeric", i.e., corresponding directly to the irritated segment, but also as "allomeric", i.e., corresponding to several segments. The physiological significance of this plurisegmentality or allomericity of spinal cord reactions lies in the fact that both in reflex and in voluntary motor acts, the contraction of not individual muscle fibers and not individual muscles, but of entire groups of muscles is required; the anatomophysiological basis for such combined participation of a group of muscles consists of internsegmental associative connections. The cells of the anterior horns of the spinal cord have significance for the trophicity of the contractile substance of the muscle fibers innervated by them. Isolation of the muscle from these cells, as occurs when the latter die or when conductivity in the peripheral motor nerve is impaired, leads not only to the loss of motor function but also to a special disturbance in the vital activity of the muscle, consisting in the gradual decrease of the contractile substance. This process of so-called "muscular atrophy" can reach the degree of complete disappearance of muscle substance with its replacement by connective tissue. If the anterior horns represent the segmental motor centers of the spinal cord, then the posterior horns have the sensory segmental function: with the exception of the fibers of conscious proprioceptive receptors ("muscle-joint sensitivity"), which enter directly into the white matter, forming the bundles of the posterior columns (Burdach's bundles), all other sensory fibers of peripheral nerves enter the posterior horns of the gray matter. Here, in the posterior horns, the synapse between the first and second sensory neurons occurs; from the cells of the posterior horns begin fibers which, proceeding to the lateral and anterior columns of the white matter of the spinal cord, form the system of ascending conductors of the spinal cord, conductors carrying impulses from the segmental centers of the spinal cord to various departments of the suprasegmental area (spinothalamic, spinocerebellar, spinotectal, spinobulbar bundles). But besides the aforementioned role of the posterior horns as the area of switching impulses from the first (peripheral) neuron to the second (spinosuprasegmental), the posterior horns must also be attributed their own conductive function. Among the conductors passing in the gray matter of the posterior horns are the internsegmental fibers mentioned above, establishing connections between different segments of the spinal cord. In addition, part of the conductors of pain and temperature sensitivity, without undergoing decussation and not entering the spinothalamic bundle (see below), is directed upward through the gray matter of the spinal cord, namely through the area of the posterior horns. The existence of such conduction of sensitivity in the area of gray matter (Grisealleitung, Forster) apparently explains the cases of failure of chordotomy, i.e., cases of preservation of pain despite the transection of the spinothalamic bundle. The relative amount of sensitivity conductors passing in the gray matter of the homonymous half of the spinal cord is apparently subject to individual fluctuations, which may explain why the results of chordotomy are not in all cases identical.
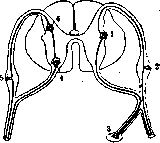
- Sympathetic cells of the lateral horns with their processes emerging through the anterior roots constitute the efferent element of the spinal sympathetic centers. Haskell considers these elements analogous to internuncial neurons establishing connection between the posterior and anterior horns (Fig. 33). Afferent fibers of the sympathetic system enter the spinal cord through the posterior roots and posterior horns. Thus the gray matter of the spinal cord, along with somatic reflexes, also carries out reflexes of the sympathetic nervous system. Summarizing the data concerning the physiology of the gray matter of the spinal cord, one can characterize the function of this department of the spinal cord as an active process of formation, combination, and distribution of impulses. In contrast to this, the white matter represents a system of fibers carrying out the passive function of conductors, serving for communication between the segmental centers of the spinal cord and suprasegmental departments of the central nervous system. The entire system of conductors of the spinal cord can be subdivided into two main groups, corresponding to the direction in which the propagation of impulses occurs: 1) ascending conductors, serving for conducting impulses from the segments of the spinal cord to suprasegmental departments, 2) descending conductors, serving for conducting impulses from suprasegmental departments to segmental centers of the spinal cord.
The system of ascending conductors performs the function of conducting receptor impulses from segmental centers of the spinal cord to suprasegmental divisions. With regard to the correspondence of individual conductors to certain types of sensitivity, the following data can be considered established. The main conductor of pain sensitivity is the spino-thalamic tract. The aforementioned tract is a common conductor for all forms of pain sensitivity—deep and superficial, protopathic and epicritic. This commonality of spinal cord conductivity for all types of pain sensitivity is the reason that in lesions of the spino-thalamic tract, there is an even loss of all the aforementioned types of sensitivity, and the dissociation between deep and superficial or protopathic and epicritic sensitivity, often observed in lesions of peripheral nerves and the brain, is not observed in spinal cord lesions. In contrast to the previous view of the spino-thalamic tract as the only conductor of pain impulses in the spinal cord, at present the conviction is becoming increasingly firm that pain impulses can also spread along other pathways. In addition to the aforementioned possibility of the spread of pain impulses by fibers passing in the area of the posterior horns of gray matter, the possibility (Forster) of their conduction in the posterior columns and the posterior-lateral parts of the lateral columns is admitted. The degree of development of such accessory pain conductivity in the spinal cord is subject to individual variations; however, their existence is beyond doubt and is important for explaining certain, at first glance paradoxical phenomena, when e.g. in lesions of the spinal cord, not affecting the spino-thalamic tract, there are phenomena of loss of pain sensitivity, or conversely, when there is a definite impairment of the conductivity of the spino-thalamic tract, pain sensitivity is not completely lost. If we take into account that according to recent data, the point of entry of pain impulses into the spinal cord is not only the posterior roots but also the anterior ones (Forster), then, without denying the importance of the spino-thalamic tract as the main and predominant conductor of pain impulses, we must keep in mind the possibility of the passage of pain impulses, at least in some individuals, in other areas of the spinal cord. Forster summarizes the modern data on the conduction of pain sensitivity as follows: "pain impulses penetrate the central nervous system not through a narrowly limited trunk of fibers, but through a multitude of winding paths, and if we block the main path, there always remains some hidden path, by which pain finds access to the brain." In the area of the spino-thalamic tract, fibers corresponding to temperature sensations immediately adjoin the pain fibers; however, pain and temperature conductors remain isolated from each other, therefore in spinal cord lesions it is possible to have loss of only pain or only temperature sensitivity; similarly, there are isolated conductors for heat and cold stimuli, which explains the possibility of dissociation of disorders of heat and cold sensitivity in lesions of the conducting apparatus of the spinal cord. Similar to pain sensitivity, temperature sensitivity does not have separate fibers for protopathic and epicritic stimuli; therefore in spinal cord lesions, protopathic and epicritic temperature sensitivity are lost to the same degree.--With regard to the conduction in the spinal cord of impulses of tactile sensitivity, there is a difference depending on the protopathic or epicritic character of the tactile impulses. Impulses arising from touch to the skin surface and from pressure on the skin, like the conductors of pain and temperature sensitivity, undergo decussation in the spinal cord, but upon entering the white matter of the opposite side, they separate from the pain and temperature conductors, not being located in the lateral columns as the latter are, but in the anterior ones. This bundle, conducting protopathic tactile elements (pressure and touch), is designated by the term "anterior" or "ventral" spino-thalamic tract, in contrast to the lateral spino-thalamic tract, described above as the conductor of pain and temperature sensitivity (tractus spino-thalamicus lateralis). It should be mentioned that the fibers of the lateral spino-thalamic tract, i.e. the conductors of pain and temperature sensitivity, undergo decussation very soon after their entry into the spinal cord, whereas the fibers corresponding to the anterior spino-thalamic tract, for several segments, run on the side of their entry into the spinal cord before undergoing decussation. This explains the fact that in some lesions of the spinal cord, the level of loss of tactile sensitivity does not coincide with the level of loss of pain and temperature sensitivity. Epicritic, or "discriminative" forms of tactile sensitivity (light touch, precise recognition of Weber's compass points, localization of touch) are conducted in the spinal cord in the posterior columns. In addition to conducting certain types of tactile sensitivity, the function of the posterior columns is to conduct impulses of proprioceptive sensitivity, so-called muscle-joint feeling or sense of position. Finally, in the posterior columns, impulses of vibratory sensitivity are conducted. In the most lateral parts of the lateral columns, impulses of reflex proprioceptors are conducted, which form the basis of the automatic regulation of movements and have the cerebellum as their central apparatus. According to their direction, these conductors are designated by the term "spino-cerebellar tracts". Topographically: a ventral (Gowers) and a dorsal (Flexig) spino-cerebellar tract are distinguished (fig. 34). There is no difference in function between these tracts. The descending system of conductors of the spinal cord is a collection of bundles, the fibers of which conduct impulses from the suprasegmental apparatus to the spinal cord. The final stage of the spinal cord, through which impulses from the suprasegmental apparatus spread to the muscles, are the cells of the anterior horns (see Human Motorics, Motor Centers). Functionally, the descending conductors can be characterized as a system of fibers that perform the motor function. The conductors of cortical "volitional" impulses are the so-called pyramidal or cortico-spinal tracts (tr. pyramidalis, cortico-spinalis), located in the posterior parts of the lateral columns (fig. 34). Directly with their terminal branches or with the help of short intercalary neurons, the fibers of the pyramidal tract come into anatomophysiological contact with the cells of the anterior horns. The functional effect on the latter from the pyramidal tracts consists of a combination of stimulating influences with inhibitory ones. This at first glance paradoxical fact of the simultaneous performance of two opposite functions by the same apparatus is a common feature of the relationship
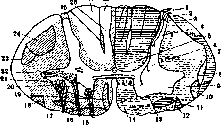
Figure 34. Diagram of a cross-section of the spinal cord in the middle part of the cervical region: 1-dorsal root; 2-dorsolateral tract; 3-dorsal spino-cerebellar tract; 4-posterior horns; 5-dorsal proprius fasciculus; 6-lateral proprius fasciculus; 7-ventral spino-cerebellar tract; 8-lateral spino-thalamic tract; 9-anterior horns; 10-spino-tectal tract; 11-ventral spino-thalamic tract; 12-spino-olivary tract; 13-ventral proprius fasciculus; 14-sulcomarginal fasciculus; 15-anterior roots; 16-vestibulo-spinal tract; 17-tecto-spinal tract; 18-olivo-spinal tract; 19-anterior cortico-spinal tract; 20-ventrolateral nucleus; 21-ventromedial nucleus; 22-dorsolateral nucleus; 23-rubro-spinal tract; 24-lateral cortico-spinal tract; 25-interfascicular fasciculus; 26-septomarginal fasciculus; 27-Burdach's fasciculus [the inner part of Burdach's fasciculus (see the right half of the figure) corresponds to segments I-IV thoracic, and the outer part corresponds to cervical segments]; 28-Goll's fasciculus [the innermost part of Goll's fasciculus (see the right half of the figure), separated by the first groove, indicates the shape of this fasciculus in the sacral region; the second groove delimits the part of Goll's fasciculus corresponding to the lumbar region, and the outermost part of Goll's fasciculus corresponds to segments V-XII thoracic]]
between the segmental mechanisms of the spinal cord and the suprasegmental centers. As indicated above, the cerebral cortex in the process of phylogenetic evolution is built over the segmental apparatus, and this latter does not lose the automatic function inherent in it, but only becomes subordinate to cortical innervation. To carry out cortical innervation, however, a certain degree of inhibition of the reflex mechanisms of the segmental apparatus is necessary. Thus, the cerebral cortex, sending stimulating impulses to the spinal cord in the sense of activating the activity of motor spinal cells, at the same time exerts an inhibitory effect on the reflex function of the spinal cord's own apparatus. In other words, the cerebral cortex through the mediation of the pyramidal tracts moderates the reflex activity of the spinal cord. Connected with this is the role of the pyramidal tract in the function of tone. Muscle tone, i. e., a certain degree of tension of muscle tissue, is determined by a number of various factors. The own apparatus of the spinal cord, i. e., the reflex mechanism, represents a factor that increases tone: constant impulses arising at the periphery, spreading along reflex arcs to the muscles, maintain a certain degree of contraction in the muscles; thus, the reflex function is a tonogenic factor. Conversely, the pyramidal tracts, which inhibit reflex activity, moderate muscle tone. This explains the increase in tone observed in lesions of the pyramidal tract. The descending conductor of cerebellar impulses into the spinal cord is the so-called Monakow's bundle (tr. rubro-spinalis), located in the lateral columns anterior to the pyramidal tract (Fig. 34); the intermediate stage between the cerebellum and the spinal cord are the red nuclei. But these same red nuclei represent an intermediate stage between the spinal cord and the corpus striatum. Thus, the rubrospinal tract contains two different systems of descending fibers: cerebellospinal and striarospinal. Physiologically, cerebellospinal impulses constitute the main factor of automatic coordination of movements, synergy of muscle contractions, and regulation of tone in the sense of proper distribution of tension in the muscles participating in the execution of a given motor act. The function of striarospinal impulses consists in regulating the tone of the musculature and carrying out amorphous diffuse contractions of the musculature, against the background of which fine movements of a limited number of segments are created by stimulating and inhibiting cortical innervations. On the basis of experimental data, the red nucleus and the rubrospinal tract must be assigned the function of inhibiting postural tone (see Postural reflexes). The data presented above on the role of various spinal cord apparatuses in the function of muscle tone can be summarized as follows. The influence of the spinal cord on muscle tone is carried out through the cells of the anterior horns of the spinal cord. These cells are subjected to a stimulating effect regarding tone from the receptor section of the reflex arcs. Irritations constantly flowing from the periphery, spreading from the receptor part of the reflex arc to the motor one, constitute the basis of the so-called "reflex tone" of the musculature. Thus, the reflex act is a factor stimulating tone. Of the suprasegmental apparatuses, a stimulating effect on tone is exerted by the cerebellum via tr. rubro-spinalis and Deiters' nucleus of the vestibular nerve via tr. deitero-spinalis (s. vestibulo-spinalis; Fig. 34), located in the spinal cord in the anterior columns. Factors inhibiting tone are: the cerebral cortex via tr. cortico-spinalis and the corpus striatum (pallidum) via striarospinal fibers forming part of tr. rubro-spinalis. Thus, in connection with lesions of the spinal cord, the following changes in tone can be observed: disturbances in the conductivity of the reflex arc lead to a weakening or loss of tone; disturbances in the conductivity of the pyramidal tract and loss of pallidal influences lead to an increase in tone. In addition to suprasegmental conductors in the spinal cord, there are intersegmental fibers connecting various spinal segments among themselves; these conductors are also designated by the term "spinospinal." The presence of these connections constitutes the anatomical and physiological basis of the combined action of a group of segments in the spinal cord. Most of the intersegmental conductors are located in the immediate vicinity of the gray matter, forming the so-called "fundamental bundle," or fasciculus proprius (Fig. 34), but some of them pass as part of the white matter; these include: Schultze's bundle (Fig. 34) and fasciculus septo-marginalis (Fig. 34). A part of the intersegmental fibers is located in the anterior columns tr. sulco-marginalis; in functional terms, it is a continuation of the posterior longitudinal fasciculus of the brain stem (the function of the combined rotation of the eyes, head, and trunk). As for the localization of functions in the spinal cord, the relationship between the segments of the spinal cord and the distribution of cutaneous sensitivity see Metamerism. The correspondence between the segments of the spinal cord and certain muscle groups can be summarized as follows: I-IV cervical segments correspond to the cervical musculature; V-VIII cervical and I-II thoracic - to the muscles of the upper extremities; from III thoracic to I lumbar - to the muscles of the trunk; II-V lumbar and I-II sacral segments innervate the lower extremities, III-V sacral segments - the muscles of the perineum, anus, and urogenital organs. As indicated above, each muscle is innervated not by one, but by 2-3 segments; however, there is a predominant dependence of individual muscles on certain segments. This connection between individual muscles and segments of the spinal cord is presented in Table 1. Tab. 1. Segments of the spinal cord Muscles Segments of the spinal cord Muscles Civ Diaphragm Lr Iliopsoas Cv Deltoideus Lii Quadriceps Cvi Biceps Liii Adductors of the thigh Cvii Triceps Liv Tibialis ant. Cviii Flexors of the fingers of the hand Si Gastrocnemius Di Hypothenar Sii-iii Small muscles of the foot Dii-xii Intercostal muscles Siii-iv Muscles of the perineum On the reflex centers of the spinal cord see Reflexes. The localization of the centers of the sympathetic nervous system corresponding to internal organs is given in Table 2. Tab. 2. Internal organs Segments of the spinal cord Internal organs Segments of the spinal cord Heart . . . Aorta . . . Stomach . Intestine . Rectum . Di-iii Dii-iii Dvi-ix Dix-xii Sii-iii Liver . . . Kidney . . . Bladder and genital organs . . . Dvii-x Dxi and Li Sii-iv The indications given in Table 2 must be supplemented by the following explanations. The centers of the urinary and genital organs localized in the II, III, and IV sacral segments, also designated by the terms centrum "vesico-spinale" and centrum "genito-spinale," represent not sympathetic, but parasympathetic centers. The sympathetic innervation of the urinary and genital organs is carried out by fibers originating in the sympathetic centers of the I and II lumbar segments. These fibers pass through gangl. mesentericum inferius and follow further in the form of n. hypogastricus to the bladder and internal genital organs. Irritation of n. hypogastrici causes contraction of the sphincter and relaxation of the detrusor; irritation of parasympathetic fibers (n. pelvicus), on the contrary, leads to contraction of the detrusor and relaxation of the sphincter. Deserving special mention is centrum cilio-spinale - the spinal center for pupillary dilation. This center and the fibers corresponding to it form part of the cervical sympathetic nerve. The ciliospinal center is localized in the spinal cord at the level of the I-II thoracic segments; the fibers starting from here emerge from the spinal cord as part of the anterior roots of the VIII cervical, I, and II thoracic nerves and then as part of the cervical sympathetic nerve reach the upper cervical sympathetic ganglion, from whence they, intertwining the internal carotid artery in the form of a periarterial sympathetic plexus, enter further into the composition of the upper branch of the trigeminal nerve, with the fibers of which they enter the eyeball, ending in the radial musculature of the pupil. Irritation of these fibers causes pupillary dilation; ciliospinal fibers are an antagonist of parasympathetic fibers innervating the pupillary sphincter and entering into the oculomotor nerve. V. Pathology. Clinical manifestations of spinal cord lesions can be subdivided, according to the two main apparatuses of the spinal cord, into two groups: segmental and tract disorders. In segmental lesions, functional disorders are observed only on the part of the directly affected segments. In tract disorders, due to the disruption at a certain level of communication between the periphery and the brain, there is a diffuse loss of functions corresponding in their innervation to the sections of the spinal cord lying below the level of the lesion. Since the motor central conductor and conductors of muscle sense in the spinal cord do not undergo decussation, when they are damaged, disorders are observed on the side homolateral to the lesion; in contrast to this, in a tract lesion of the spinothalamic tract, the loss of pain and temperature sensitivity is observed on the side opposite to the localization of the lesion, since these conductors undergo decussation in the spinal cord.
The principal data for the topical diagnosis of spinal cord lesions are as follows: I. Segmental disorders (lesions of the gray matter and roots). 1) Symptoms of posterior root lesions: pain corresponding to the innervation area of the given posterior root; disorder of all types of sensitivity, loss or attenuation of reflexes. 2) Posterior horns: loss of pain and temperature sensitivity in the given segment while tactile and muscular sense is preserved; attenuation or loss of reflexes. 3) Anterior horns and anterior roots: motor paralysis, muscle atrophy, loss of reflex, degeneration reaction in the area of the affected segment. 4) The area of gray matter anterior to the central canal: bilateral loss of pain and temperature sensitivity at the level of the affected segment. II. Tract disorders. 1) Posterior columns: disorder of muscular sense and tactile sensitivity below the level of the lesion. 2) Lateral columns: central (spastic) paralysis on the side of the lesion, loss of pain and temperature sensitivity on the opposite side. The clinical picture of spinal cord lesions is determined, in addition to the spread of this lesion to various parts of the cross-section of the spinal cord, also by the height of localization of this lesion. In this regard, the following main types of symptom complexes can be distinguished. A complete diffuse lesion of the spinal cord leads to the so-called paralytic syndromes, which differ as follows depending on the height of the localization of the disease process: 1) Syndrome of the medullary conus (conus medullaris): anesthesia in the perineal region and around the anus; disorder of urination and defecation (paralysis of the sphincters); loss of erection. 2) Syndrome of the lumbosacral enlargement: paralysis of the lower extremities of the atrophic type; disorder of urination in the form of urinary retention or intermittent incontinence; anesthesia of the lower extremities. 3) Syndrome of the thoracic spinal cord: spastic paralysis of the lower extremities and anesthesia below the level of the lesion; disorder of urination. 4) Syndrome of the cervical enlargement: atrophic paralysis of the upper extremities; spastic paralysis of the lower extremities; anesthesia below the level of the lesion; disorder of urination. 5) Syndrome of the upper cervical spinal cord: spastic paralysis of the upper and lower extremities; anesthesia below the level of the lesion; paralysis of the diaphragm; disorder of urination. 6) Syndrome of hemisection of the spinal cord (Brown-Séquard paralysis): central paralysis and disorder of muscular sense on the side of the lesion; loss of pain and temperature sensitivity on the opposite side. In the initial periods of acute diseases of the spinal cord (trauma, inflammation), a picture is sometimes observed that at first glance contradicts the general rule about the spastic character of the paralysis of the lower extremities in high spinal cord lesions; in the acute period of spinal cord lesions, despite the high localization of the process (thoracic, cervical region), there is hypotonia and loss of all reflexes in the lower extremities. This fact is explained by the state of shock developing in the segmental centers located below the site of injury. This state of shock usually lasts from several days to 3-4 weeks, after which the automatic activity of the reflex centers that were in a state of shock is restored, a gradual increase in muscle tone and an increase in reflexes occurs; at the same time, the symptom of spinal cord automatism appears in the form of the so-called "protective reflexes": in response to skin stimuli applied to areas below the level
SPINAL
paralysis, muscle atrophy, loss of reflex, degeneration reaction in the area of the affected segment. 4) The area of gray matter anterior to the central canal: bilateral loss of pain and temperature sensitivity at the level of the affected segment. II. Tract disorders. 1) Posterior columns: disorder of muscular sense and tactile sensitivity below the level of the lesion. 2) Lateral columns: central (spastic) paralysis on the side of the lesion, loss of pain and temperature sensitivity on the opposite side. The clinical picture of spinal cord lesions is determined, in addition to the spread of this lesion to various parts of the cross-section of the spinal cord, also by the height of localization of this lesion. In this regard, the following main types of symptom complexes can be distinguished. A complete diffuse lesion of the spinal cord leads to the so-called paralytic syndromes, which differ as follows depending on the height of the localization of the disease process: 1) Syndrome of the medullary conus (conus medullaris): anesthesia in the perineal region and around the anus; disorder of urination; defecation (paralysis of the sphincters); loss of erection. 2) Syndrome of the lumbosacral enlargement: paralysis of the lower extremities of the atrophic type; disorder of urination in the form of urinary retention or intermittent incontinence; anesthesia of the lower extremities. 3) Syndrome of the thoracic spinal cord: spastic paralysis of the lower extremities and anesthesia below the level of the lesion; disorder of urination. 4) Syndrome of the cervical enlargement: atrophic paralysis of the upper extremities; spastic paralysis of the lower extremities; anesthesia below the level of the lesion; disorder of urination. 5) Syndrome of the upper cervical spinal cord: spastic paralysis of the upper and lower extremities; anesthesia below the level of the lesion; paralysis of the diaphragm; disorder of urination. 6) Syndrome of hemisection of the spinal cord (Brown-Séquard paralysis): central paralysis and disorder of muscular sense on the side of the lesion; loss of pain and temperature sensitivity on the opposite side. In the initial periods of acute diseases of the spinal cord (trauma, inflammation), a picture is sometimes observed that at first glance contradicts the general rule about the spastic character of the paralysis of the lower extremities in high spinal cord lesions; in the acute period of spinal cord lesions, despite the high localization of the process (thoracic, cervical region), there is hypotonia and loss of all reflexes in the lower extremities. This fact is explained by the state of shock developing in the segmental centers located below the site of injury. This state of shock usually lasts from several days to 3-4 weeks, after which the automatic activity of the reflex centers that were in a state of shock is restored, a gradual increase in muscle tone and an increase in reflexes occurs; at the same time, the symptom of spinal cord automatism appears in the form of the so-called "protective reflexes": in response to skin irritations applied to areas below the level of the BRAIN
cord
lesions, there occurs flexion of the lower limb in the hip and knee joints and dorsal flexion of the foot and toes. The main principle of classification of spinal cord diseases is their division into systemic and diffuse. By systemic are meant such pathological forms in which there is selective damage to a certain specific system, i.e., a complex of anatomical elements that perform a specific function; for example, there exist diseases in which pathological-anatomical changes affect only the central or peripheral motor neurons (lateral sclerosis, spinal progressive muscular atrophy). In other cases, the anatomical changes affect only the sensory neurons (for example, tabes dorsalis, which is based on degeneration of the posterior columns). Finally, in some of the systemic diseases there is a combination of damage to two or more systems, for example, funicular myelitis, in which there is a combination of degeneration of the pyramidal tracts and conductors of muscle-joint sense in the posterior columns. In diffuse diseases, the matter concerns lesions that spread diffusely throughout the substance of the spinal cord, regardless of the functional properties of the affected elements. The main signs of systemic and diffuse diseases of the spinal cord can be characterized by the following features. Systemic diseases are based on degenerative processes; their etiology consists of chronic intoxications and chronic infections. Clinically, systemic diseases develop slowly, gradually, and have a chronic progressive course. For the diagnosis of a systemic disease, the limitation of clinical phenomena to certain functional systems is of importance. The prognosis in systemic diseases, due to their progressive nature, is unfavorable; treatment can have only palliative significance. Diffuse diseases of the spinal cord are characterized by an acute onset; their etiology consists of acute infections, injuries, hemorrhages, tumors. In diffuse diseases, the maximum of symptoms usually occurs at the beginning of the disease; subsequently, death or recovery is observed, but there is no chronic progression of the disease. In this sense, the prognosis in diffuse diseases can be considered more favorable. In the clinical picture of diffuse diseases, there is a mixture of symptoms from the segmental and conduction apparatus and a combination of disorders from various functional systems. It goes without saying that this division of spinal cord diseases into systemic and diffuse is artificial and schematic, since there are forms of diseases that do not quite correspond to any of these groups. For example, brain tumors, representing a diffuse disease, have a chronic progressive course. Syringomyelia, also representing a diffuse disease, has a progressive course and gradual development. On the other hand, some of the systemic diseases do not always limit their manifestations to a specific functional system. In view of this, some authors use the term 'pseudosystemic' diseases instead of the term 'systemic'. Many diseases of the spinal cord, both diffuse and systemic, do not limit themselves to the spinal cord, but also extend to the brain. Of the diffuse diseases of the spinal cord, the most common are injuries, inflammations, vascular disorders, and tumors. Traumatic injuries of the spinal cord, according to their mechanism of origin, can be divided into two main groups: 1) Direct injuries, in which there is penetration of foreign piercing objects into the spinal cavity with direct violation of the integrity of the spinal cord. 2) Indirect injuries, occurring without violation of the integrity of the covering tissues and without penetration of foreign bodies into the spinal canal; the essence of these injuries consists in severe concussions causing contusion of the spinal cord (contusio medullae spinalis), its ruptures, hemorrhages into the substance of the spinal cord or its membranes due to rupture of vessels. The causes of such indirect injuries are severe bruises to the back, falls from a height, etc. It should be especially noted that bullet, bayonet, etc., wounds occurring in the vicinity of the spine can cause injuries to the spinal cord, mainly hemorrhages, by simple concussion without direct penetration of a foreign body into the spinal canal. It goes without saying that injuries to the spinal cord can also occur under the influence of the introduction of bone fragments in fractures of the vertebrae, compression in dislocations and displacements of the vertebrae, etc. Hemorrhage into the spinal cord, so-called hematomyelia (haematomyelia), usually affects the gray matter, which is explained by its greater looseness and more abundant blood supply. Therefore, one of the main symptoms of hematomyelia is segmental dissociated sensory disorder; to this is added pressure from the spilled blood on the white matter; in cases where this pressure is significant, it can lead to complete disruption of conductivity at a certain level. Subsequently, under the influence of absorption of the hemorrhage, the initial picture of complete 'transection' of the spinal cord may be replaced by a picture of combination of segmental disorders with partial disruption of conductivity. Symptoms characteristic of hematomyelia are the absence of blood in the cerebrospinal fluid and the absence of radiating 'radicular' pains. Thus, the presence of a complex of symptoms of disruption of spinal cord conductivity (paraplegia, urinary retention, etc.) after traumatic injury, in the absence of blood in the cerebrospinal fluid and absence of radicular pains, speaks in favor of hematomyelia. Hemorrhage into the membranes of the spinal cord (haematorrhachis) can also lead to a picture of complete disruption of conductivity of the spinal cord, but unlike hematomyelia, in meningeal hemorrhage there are always present radicular pains, signs of irritation of the membranes (Kernig's symptom), painful tension of the neck muscles, and the cerebrospinal fluid is found to be colored with blood. However, since hemorrhage into the membranes can be combined with hematomyelia and the latter may be hidden behind the signs of meningeal hemorrhage, the diagnosis of 'pure' meningeal hemorrhage in most cases appears not entirely reliable. This same combination of symptoms of paraplegia with irritation of the roots and membranes is observed in cases of direct injuries to the spinal cord, i.e., in cases of penetration of foreign bodies into the spinal canal. Such injuries, in addition to violation of the integrity of the spinal cord, are almost always accompanied by hemorrhages and irritation of the roots and membranes. Only simple pressure of a foreign body on the spinal cord without violation of the integrity of the brain membranes may not be accompanied by the phenomena mentioned above, but such injuries are a rarity. The considerations presented show that in many cases the exact determination of the nature of traumatic injury to the spinal cord presents significant difficulties. Thus, with clear signs of irritation of the roots and membranes and the presence of blood in the cerebrospinal fluid, one can with confidence recognize meningeal hemorrhage, but one cannot with full categoricality decide the question of whether, in addition to meningeal hemorrhage, there is hematomyelia, whether there is penetration of bone fragments, a foreign body, etc., into the spinal canal. In all these cases, the same picture will be observed: paraplegia with signs of irritation of the roots and membranes. Data from radiography are of substantial help for clinical diagnosis in some of these cases. The clinical picture of traumatic injuries to the spinal cord can be presented in general terms as follows. At the moment of injury, unconsciousness is often observed, which is explained by concussion of the brain occurring under the influence of the injury. In cases where consciousness is preserved, the victim usually experiences a peculiar sensation 'as if the body were cut in half'. The victim instantly falls or, if he was in a lying position, finds himself unable to get up. In the presence of injury to the roots, patients experience severe pains. It should be noted that localized pains in the spine, no matter how intense, have no significance for the diagnosis of spinal cord injury; on the contrary, radicular pains radiating along the course of certain nerves should always arouse suspicion of intraspinal irritation. Sometimes the symptoms of spinal cord injury do not develop immediately after the injury, but after several hours; in these cases, the matter usually concerns hematomyelia; the delayed development of symptoms is explained in such cases by the fact that at the moment of traumatic injury only the vessel wall is torn and only after some time, under the influence of accidental increase in blood pressure, complete disruption of the vessel wall occurs with hemorrhage into the substance of the spinal cord. The prognosis in traumatic gunshot wounds of the spinal cord, of course, depends on the degree of injury and its localization. In general, injuries manifesting as a picture of complete disruption of spinal cord conductivity (paraplegia, disorders of urination) give a fairly high percentage of mortality. Particularly unfavorable course is observed in injuries of the cervical region and the region of the conus.
A significant percentage of patients with injuries to the spinal cord die from complications in the form of bedsores, cystitis, and sepsis. In wartime, wounds and injuries to the spinal cord constitute about 5% of all wounds to the nervous system. Wounded persons with spinal cord injuries present considerable difficulties in front-line conditions because, on the one hand, they require rapid evacuation, and on the other hand, their evacuation in the first period is dangerous due to the possibility of increasing the existing injury, especially hemorrhages, because of shaking, sharp changes in body position, etc. The treatment of spinal cord injuries in the initial stages consists in maintaining complete rest and measures to prevent complications in the form of bedsores and cystitis: water or air mattress, maintenance of cleanliness; when a bedsore begins (epithelial detachment, redness)-rubbing with camphor alcohol, dusting with powder. For a developed bedsore: ointments: Bals. Peruv. 1.0, Lanolini 30.0; or Dermatol 3.0, Camph. tr. 2.0, Vaselini 30.0. Blue light, heated air. After the initial shock has passed-treatment of paralysis with massage and passive gymnastics. For atrophic paralyses-electrization, baths. In later periods, especially in cases with meningeal hemorrhages, spa treatment in the form of local mud and sulfur baths. Regarding surgical treatment, the following must be kept in mind: 1) Structural injuries to the spinal cord, such as: direct destruction by foreign bodies, hemorrhages, contusions, etc., cannot be eliminated surgically. 2) Hematomyelia is not subject to surgical treatment, because the removal of spilled blood or clot cannot restore the functions of nerve elements destroyed by hemorrhage. The restoration of elements that are not destroyed but only involved in the process due to edema, pressure, concussion, etc., occurs even without surgical treatment. 3) Meningeal hemorrhages usually resolve quite quickly and completely, and therefore the phenomena they cause, such as compression of the roots and spinal cord, do not require surgical treatment. If adhesions, limited accumulations of fluid, etc., form, they can be the subject of surgical treatment 2-3 months after the injury, not in the acute period. 4) In the initial periods (the first 2-3 weeks) after injury, laminectomy is associated with the danger of new hemorrhage. Therefore, early surgical intervention should in any case be considered undesirable. 5) A direct indication for surgical intervention is cases of unquestionable pressure on the spinal cord from bullets, fragments of vertebrae, etc. However, even in these cases, the operation can only eliminate symptoms that depend on compression of the spinal cord; the consequences of ruptures and destructions of the spinal cord and hemorrhages into its substance cannot be eliminated by surgery; if there is an immediate threat to life (pressure of a foreign body on the cervical section of the spinal cord), then early surgery, although dangerous, is still the only method that offers a chance of saving life. Inflammatory diseases of the spinal cord are usually secondary, i.e., they arise as complications of various infectious diseases (see Myelitis); they represent acute diseases. Chronic inflammatory processes of the spinal cord are observed in syphilis of the spinal cord (see Nervous diseases).- Abscesses of the spinal cord, especially compared with abscesses of the brain, represent a very rare disease. The main etiological factor of spinal cord abscess is trauma; in some cases, the development of spinal cord abscess was associated with bronchiectasis, tuberculous spondylitis, purulent meningitis, etc. Clinically, the disease is expressed by a rapidly developing picture of transverse myelitis with high temperature. The diagnosis presents difficulties in distinguishing it from myelitis, extradural abscess, edema of the spinal cord in spondylitis, etc. Treatment is surgical-see also below. Vascular lesions are observed in the spinal cord much less frequently than in the brain. Hemorrhage into the spinal cord, if we do not count the traumatic hematomyelias mentioned above, is such a rare phenomenon that it has almost no practical significance. Nevertheless, the existence of such 'spontaneous' hematomyelias cannot be doubted. In most cases, they occurred under the influence of a factor, in its nature close to trauma, namely during excessive physical exertion; a predisposing factor are blood anomalies (purpura, malignant anemia, hemophilia, alcoholism). Even rarer than spontaneous hematomyelia are embolisms of the spinal cord. The latter can include caisson disease. The most common vascular disease of the spinal cord is thrombosis, which usually develops on the basis of syphilitic lesions of the spinal cord vessels. There is no doubt that a significant part of the changes underlying the so-called syphilis of the spinal cord is nothing other than thrombotic softening of the spinal cord (myelomalacia). Vascular lesions of the spinal cord on the basis of arteriosclerosis cannot of course be denied, but their practical significance appears immeasurably smaller compared to similar diseases of the brain. In any case, arteriosclerotic changes in the blood supply to the spinal cord must be attributed a significant role in the pathogenesis of paretic phenomena characteristic of old age. Tumors of the spinal cord represent a rather rare disease: according to Schlesinger's statistics, out of 35,000 autopsies, spinal cord tumors were found in 104 cases, including in this number tumors of the vertebrae, secondarily compressing the spinal cord. Regarding the anatomical nature of spinal cord tumors, they represent considerable diversity. Intramedullary, i.e., originating from the substance of the spinal cord, tumors usually belong to the group of gliomas; tuberculomas are also observed intramedullary. The majority of extramedullary tumors grow from the meninges or roots. Regarding the terminology of these tumors, there is no unity. Tumors originating from the meninges were designated by the terms: 'sarcoma', 'meningioma', 'meningoblastoma', etc. According to the latest classification by Elsberg, these tumors are designated by the term 'meningeal fibroblastoma'. The same diversity of terminology exists also for tumors originating from the roots: 'fibroma', 'Schwannoma', 'neuroma', 'fibroglioma', etc. Elsberg designates these tumors by the term 'perineural fibroblastoma'. The tumor groups mentioned above, developing inside the dura mater, can be isolated into a special group called intradural tumors. Compression of the spinal cord can also occur from tumors developing outside the dura mater; these are so-called extradural tumors. Extradural tumors can originate from the dura mater itself, from vertebrae, etc. Metastatic tumors of the spinal cord usually have an extradural location; their number includes carcinoma, sarcoma, hypernephroma. Lipomas growing from the epidural fatty tissue are also located extradurally; however, cases of intradural location of lipomas are known. Cysts of the spinal cord represent accumulations of fluid in encapsulated cavities of the pia mater (meningitis serosa circumscripta spinalis). Tumors of the spinal cord are usually solitary and limited in their spread. As multiple tumors, fibromas are observed, more rarely sarcomas. The latter sometimes grow diffusely in the form of 'diffuse sarcomatosis of the pia mater' and surround the substance of the spinal cord in the form of a sheath. Cases of such sarcomatosis of the meninges, occupying the entire length of the spinal cord, have been described. The clinical picture of spinal cord tumors is characterized by a slowly increasing symptom complex of transverse damage to the spinal cord at a certain level. The overwhelming majority of extramedullary tumors begin with root pains due to irritation of the posterior roots. These pains, radiating to the area of innervation of the root corresponding to the level of the tumor's location, can long precede the appearance of spinal cord symptoms, which are detected when the tumor begins to compress the spinal cord; since such compression is often unilateral, the initial form of compression of the spinal cord by a tumor is often expressed by a more or less typical picture of Brown-Séquard paralysis, after which the symptom complex of complete diffuse transverse section of the spinal cord at a certain level develops (paraplegia, loss of sensation, disturbance of pelvic organs). In addition to root pains in extramedullary tumors, there is often tenderness on tapping the spine at the level corresponding to the tumor's location. Often, with such tapping, the pains radiate to the area of innervation of the root corresponding to this level. Intramedullary tumors as a rule are not accompanied by pains. Starting mostly from the gray matter, they initially give a picture resembling syringomyelia: dissociated disturbance of sensation, atrophic paralysis; later, a gradual diffuse lesion of the spinal cord develops. It should be noted that compression of the pain-conducting fibers usually does not cause pain. Only in rare cases have pains been observed that had to be attributed to pressure on the spinothalamic tract at the level of the growing tumor.
In even rarer cases, during the stage of Brown-Séquard paralysis, a combination of convulsions on the side of the tumor (pressure on the pyramidal tract) with pains on the opposite side below the level of the tumor (pressure on the spinothalamic tract) was observed. This syndrome, described under the name 'spasmodynia cruciata', represents a great rarity. The diagnosis of a spinal cord tumor is based on the gradual development of compression of the spinal cord. In regard to differential diagnosis, one should keep in mind syphilis, disseminated sclerosis, syringomyelia, and tuberculous spondylitis. Certain auxiliary diagnostic methods are of great importance for establishing a spinal cord tumor. Particularly valuable indications in this regard are provided by the examination of the cerebrospinal fluid. Characteristic changes in the cerebrospinal fluid in spinal cord tumors are: a sharp increase in protein without lymphocytosis and a yellowish color of the fluid, which retains its transparency (Nonne's compression syndrome); often the fluid soon after its extraction takes on a gelatinous consistency; characteristic of spinal cord tumors is also the manner of fluid outflow during lumbar puncture: at first the fluid flows out in a continuous stream, after which the flow of fluid completely ceases. The Queckenstedt test (see Queckenstedt's symptom) gives a negative result in spinal cord tumors (pressure on the jugular veins does not increase the outflow of fluid). The localization of the tumor is determined on the basis of general data on topical diagnosis of the spinal cord. The introduction into the spinal canal of solutions that give shadowing on the X-ray can serve as an essential aid for the precise localization of the tumor. The most commonly used substance is lipiodol (see). It is introduced in the amount of 1 cm3 through a suboccipital puncture. Descending, the solution stops at the site of impaired patency in the spinal canal and can be detected by X-ray examination. In addition to this 'descending lipiodol' procedure, an 'ascending lipiodol' is sometimes used, i.e., a solution of lipiodol with a specific gravity less than that of the cerebrospinal fluid is introduced by lumbar puncture; when rising upward, the introduced solution stops at the lower end of the tumor if there is impaired conductivity. The treatment of spinal cord tumors is exclusively surgical (see below). Systemic diseases of the spinal cord, in regard to their nature and basic features, have been characterized above. Spinal tabes (see Tabes dorsalis) is considered the typical systemic disease of the sensory conductors, in which there is degeneration of the posterior roots and posterior columns. Systemic diseases of the motor apparatus of the spinal cord can affect both the peripheral neuron and the central one. Chronic progressive degeneration of the anterior horns of the spinal cord, so-called Aran-Duchenne muscular atrophy (see Atrophy of muscles in diseases of the nervous system, Aran-Duchenne muscular atrophy), can serve as an example of a systemic disease of the peripheral motor neuron. Isolated lesion of the central motor neuron is clinically expressed by the picture of so-called 'lateral sclerosis': a chronically developing spastic paralysis without sensory disturbances, without disturbances of pelvic organs, without change in abdominal reflexes. There also exist forms of diseases of the spinal cord that represent a combination of progressive degeneration of peripheral and central motor neurons—amyotrophic lateral sclerosis. Some systemic diseases of the spinal cord simultaneously affect known motor and sensory conductors. Thus, in Friedreich's disease or 'hereditary ataxia,' there is chronic degeneration of the posterior columns, pyramidal and cerebellar pathways (tr. spino-cerebellaris). Clinically, the disease is expressed by a combination of cerebellar, tabetic and pyramidal symptoms. The disease has hereditary-familial distribution. Combined degenerations of the motor and sensory systems also include funicular myelitis (synonyms: myelosis, combined sclerosis of the lateral and posterior columns, ataxia spastica progressiva, anemic paralysis, etc.). This disease attracts special attention due to its marked increase in frequency in all countries in the post-war period—a fact which many put in parallel with the increase in cases of pernicious anemia at the same time. The connection between funicular myelitis and pernicious anemia is not subject to doubt at present; however, there are disagreements regarding the nature of this connection: some consider funicular myelitis a consequence of the blood disease. Such a view is contradicted by the circumstance that funicular myelitis can for a long time precede the phenomena of anemia; moreover, the phenomena of funicular myelitis often increase despite improvement in the course of anemia; finally, it should be borne in mind that in many cases of pernicious anemia, phenomena from the spinal cord are not observed. A very frequent symptom accompanying funicular myelitis is also achylia, often accompanied by changes in the mucous membrane of the tongue, characterized by smoothing of the papillae and the associated 'lacquered' appearance of it (so-called 'Hunter's tongue'). Clinically, the disease is expressed by a combination of ataxia with spastic paraparesis. The following triad of symptoms is considered cardinal: paresthesias, disturbance of deep sensation (early loss of vibratory sensation), and muscular weakness. Depending on the degree of lesion of the lateral and posterior columns, the clinical picture is dominated by phenomena of spastic paralysis or tabetic symptoms. The disease has a slow, progressive course. The diagnosis in typical cases, with clearly expressed anemia, presents no difficulties. In the early stages, especially in cases where the disease develops in the pre-anemic period, confusion with disseminated sclerosis, spinal tabes, or neuritis is possible. The prognosis in most cases is unfavorable; remissions are sometimes observed in the course of the disease; the possibility of complete recovery in rare cases is not subject to doubt. The treatment consists in liver therapy, i.e., treatment of anemia. In recent years, the systematic consumption of brains in food has been recommended. As a preventive measure, hydrochloric acid is proposed in the presence of achylia. The symptom complex of combined sclerosis is observed besides anemia in pellagra, scurvy, latirism, and cancerous cachexia. Diseases of the membranes of the spinal cord usually accompany changes in the spinal cord or are only the initial stage in the development of their combined lesion. Therefore, as an isolated disease, they have no practical significance. However, as was indicated in the example of hemorrhages of the spinal cord, recognizing the presence of membrane lesions (see above) has substantial practical significance. Establishing phenomena of membrane irritation also has important significance in phenomena of compression of the spinal cord, e.g., as one of the early signs of gradual spread of the process from the vertebrae to the surface of the spinal cord (tuberculous spondylitis, tumors). Signs of involvement of the membranes in the process are: Kernig's symptom, pain on sharp forward bending of the head; in limited lesions of the spinal cord membranes, pain from both these procedures radiates to the area corresponding to the level of the membrane lesion. Tapping on the vertebrae corresponding to this level also causes pain. The presence of these symptoms, especially if it is accompanied by root pains, indicates, for example, in tuberculous spondylitis, the spread of the process from the vertebra into the spinal canal. In recent times, the value of the specific symptom of membrane lesion was attributed to so-called spinal spots—taches spinales. The essence of this symptom is the easy appearance of long-lasting strips of cutaneous hyperemia with slight irritation of the skin. This symptom, which represents a consequence of disturbance of the vasomotor innervation, is in essence identical to dermographism. It cannot be assigned substantial diagnostic value for membrane disease, since this symptom can also be observed independently of membrane lesions. Developmental defects of the spinal cord in the mildest degrees may not manifest with definite clinical symptoms, but may only serve as a soil for the development of various spinal cord diseases. Among such defects should be included incomplete fusion of the posterior commissure of the spinal cord with cavities remaining in its substance. This developmental defect is considered a pathogenetic factor of syringomyelia (see). In some cases, developmental defects of the spinal cord are combined with external deviations that do not go beyond the limits of physiological variations, but represent an inadequacy of the organ and constitute a constitutional predisposition to the development of various pathological phenomena (status dysraphicus, myelodysplasia). In more severe developmental defects, there are present this or that disturbances of function. These include, for example, delays in development of the spinal cord, accompanied by non-fusion of the vertebrae (spina bifida).
The extreme degree of this developmental defect is so-called rachischisis—a delay in the development of the spinal cord at the stage before the formation of the neural tube; in this case, the spinal cord at a certain level is completely absent, and instead of nervous tissue, there is an amorphous mass of epithelial tissue. In this case, the developmental defect of the spinal cord is accompanied by a developmental defect of all other tissues: skin, vertebral bone substance, muscles, etc. Rachischisis is usually accompanied by other severe developmental defects and has no particular practical significance, as subjects with this defect are found to be nonviable. In other cases, where the vertebrae fail to close, the substance of the spinal cord is developed but not perfectly, and due to the lack of support from the vertebrae and the accumulation of cerebrospinal fluid in the corresponding area, a cystic protrusion (spina bifida cystica) forms; this phenomenon is most often observed in the lumbo-sacral region (see Spina bifida). There are no independent, isolated functional diseases of the spinal cord. The term 'spinal neurasthenia' (myelasthenia) should be considered inconsistent with modern views on the nature of functional diseases; in the past, this term was applied to forms of neuroses in which phenomena of rapid fatigue in the lower extremities, pain in the back, etc., predominated—phenomena generally characteristic of subjects with an asthenic constitution, suffering from overwork, etc. Similarly, the term 'spinalgia' or 'spinal neuralgia' should be considered inappropriate. The conditions denoted by these terms represent various kinds of pain and paresthesias in the back region. The basis of these disorders is not 'hyperemia of the spinal cord,' as was previously assumed, but neuralgia of the posterior branches of the spinal nerves and myalgia (myositis) of the back muscles, which are associated with metabolic disorders, overwork, injuries, etc.; in some of these cases, it is a matter of hysterical suggestibility and autosuggestion (rachialgia hysterica). To the category of functional disorders, incorrectly previously attributed to lesions of the spinal cord, should also be included the so-called 'spinal reflex paralysis,' the occurrence of which was attributed to various peripheral irritations, for example, catheterization of the bladder ('paraplegia urinaria'). The paralyzes described under this name are not 'reflex' disorders, but either organic diseases (myelitis) or hysterical paralysis. The disorder of gait previously attributed to 'irritation of the spinal cord,' designated by the term pseudoparalysis agitans or dystaxia agitans, represents a variety of hysterical abasia (spastic abasia). This is a hysterical disorder of gait, often observed after hysterical paraplegia, characterized by the appearance of severe tension in all muscles of the lower extremities when attempting to walk; the patient makes considerable efforts to lift the feet off the ground and balances with the arms; at the same time, tremor is observed in the lower extremities (abasia trepidans). This disorder responds well to psychotherapy.
M. Astiatsaturov. VI. Surgery. The beginning of spinal cord surgery was laid in 1886 by the Scottish surgeon Macewen, who proposed laminectomy (see), which provided access to the spinal cord. As early as 1887, Horsley first removed a spinal cord tumor, and from this moment, spinal cord surgery began to develop rapidly and in the last 20 years has become extremely common and widely available. With the improvement of both surgical technique and the technique of the operation itself and the application of strictest asepsis, laminectomy has become almost a safe operation, especially if it is performed under local anesthesia, and at present the question is being raised about trial laminectomy in diagnostically unclear cases. Laminectomy is a preliminary step in operations on the contents of the vertebral canal or a therapeutic decompression operation for various types of injuries and diseases that cause compression of the spinal cord, such as fractures of the spine, tuberculous spondylitis, and inoperable tumors of the meninges and spinal cord. Spinal cord surgery is divided: 1) into surgical treatment of injuries and diseases of the meninges and the spinal cord itself, 2) into surgical treatment of diseases of the peripheral nervous system. Surgical treatment of injuries and wounds of the spinal cord before the imperialist war was strictly conservative, and surgery was undertaken only after 1-2 months. The experience of American and French surgeons during the imperialist war showed that early intervention has great advantages, preventing those complications that often lead to the death of the wounded or leave them disabled for life. Particularly convincing are the experiments of Sozon-Yarovich on dogs, which showed that primary wound treatment within the first 6-8 hours after injury prevents the spread of infection and all complications associated with compression of the spinal cord. At present, the same measures should be taken for spinal cord injuries as are applied for injuries to other parts of the body. Usually, those wounded in the spinal cord are in severe shock, which often makes it difficult to determine the extent of the spinal cord injury, therefore, all efforts should first be directed at eliminating the shock by using stimulants, heat, blood transfusions, etc. (see Shock). After eliminating the shock and determining the extent of the spinal cord injury, within the first 6-8 hours after injury, primary wound treatment should be performed with excision of the wound canal, crushed tissues, removal of projectile fragments, damaged bones, and careful stopping of bleeding. If the dura mater is intact, it should be avoided to open the subarachnoid space to prevent the introduction of infection. Only indication of brain damage and bleeding gives the right to make an incision in the dura mater to stop bleeding and determine the extent of the spinal cord injury. After this, the dura mater is sutured. In case of injury to the dura mater, the wound opening is enlarged and the spinal cord is examined. If a rupture of the spinal cord is established, it is recommended to perform the connection of the separated ends of the spinal cord and suture them through the pia mater with catgut sutures, since observations on wounded who underwent suturing show partial restoration of spinal cord function and improvement of trophicity (Stewart, Hart, Grekov). When there is damage to the roots of the spinal cord, it is recommended to suture them or, if this is not possible, implant them into healthy roots. After this, bleeding is carefully stopped, all clots are removed from the subarachnoid space, and the dura mater is sutured. In case of a large defect of the dura mater, a flap can be formed by splitting it according to Bruning (Brunning). The muscles are sutured in several layers with catgut sutures, and the skin is closed tightly. It is recommended to avoid drains and tampons. Subsequently, complete immobilization of the spine and avoidance of transport are carried out. When a wounded person in the spinal cord arrives more than 8 hours after injury, after refreshing the wound, removing fragments and foreign bodies, open treatment is carried out. When a wounded person in the spinal cord was not given revision and primary wound treatment immediately after injury and the latter has healed, but symptoms of injury or compression of the spinal cord remain, there are two time frames for surgical intervention: early and late. Most consider the early time frame most convenient—from 6 to 8 days, others prefer a later time frame—4-6 weeks, when shock phenomena are already passing. The operation consists in removing foreign bodies, fragments and spinal cord

bones, releasing the membranes and spinal cord from pressure, removing scars and adhesions, restoring the circulation of the cerebrospinal fluid with hermetic closure of the dura mater and soft tissues. Mortality in injuries to the spinal cord without surgical intervention ranges from 65% to 80% (Pansky). Early operations yield a 60% mortality rate, and it should be taken into account that the most severe cases are operated on, which without surgery usually perish or result in severe complications requiring surgery in the late period, which yields up to 30% mortality. Despite the high percentage of mortality in early operations, the advantage still lies with them, since more patients survive with them than with conservative treatment, and in addition, the development of persistent paralyses is prevented. In injuries of the spinal cord with persistent paralyses existing for several years, decompressive laminectomy with release of the spinal cord is also indicated, which sometimes yields good results (Polenov). Surgical treatment of inflammatory diseases of the spinal cord in the acute stage -- see Meningitis; in the chronic stage it reduces to the treatment of meningitis serosa chronica circumscripta, occurring often with symptoms of an extramedullary tumor, and consists in the incision and excision of adhesions, strands, and the restoration of the free circulation of the cerebrospinal fluid, and the treatment of meningitis chronica fibrosa, which reduces to the excision of scar membranes on the dura mater sometimes over the extent of several vertebrae. The dura mater sometimes appears up to 7a cm in thickness and constricts the spinal cord and roots so that it has to be split and the outer part excised, leaving only a thin layer of it. The results are sometimes striking. In the disease syringomyelia (see), Poussep's operation has recently been successfully used. Treatment of abscesses of the spinal cord consists in laminectomy and opening of the abscess, while avoiding the flow of pus into the subarachnoid space of the spinal cord. The most developed chapter of spinal cord surgery is the surgical treatment of tumors. Depending on the location, size of the tumor, and the disorders caused by it, the operation can be of varying severity. Therefore, the earliest possible surgical intervention is necessary, and the indication for the operation should be not only the establishment of a diagnosis of a tumor, but even the suspicion of a tumor. In the latter case, the operation has the character of exploratory. Contraindications can be only the grave condition of the patient,
Figure 36.
advanced age, and the presence of extensive paralyses with elevated temperature and bedsores. In most cases, the operation can be performed under local anesthesia. In case of insufficiency of local anesthesia, ether anesthesia can be added. In intramedullary tumors, after laminectomy performed under local anesthesia, ether anesthesia is added if necessary. The position of the patient is usually on the side with a roll under the lumbar region with the foot end of the operating table raised to prevent the outflow of cerebrospinal fluid. When the tumor is located
extradurally, the operation consists in removing the tumor after laminectomy without opening the dura mater, if the tumor does not grow through it. In case of germination of the dura mater, the latter is excised, and if it is impossible to sew up its defect, it is left open or closed with a flap formed Figure 37. Subdural tumor: 1--dura mater; 2 and 3--parietal and visceral arachnoid membrane; 4--subdural space; 5--lig. denticulatum; 6--pia mater; 7--subarachnoid space. by the splitting of the dura mater along
dura mater along
subdural space; 5--lig. denticulatum; 6--pia mater; 7--subarachnoid space.
subarachnoid space. If the tumor grows through the roots, transverse processes, or the body of the vertebra, it is excised with the roots and scraped out of the bone with subsequent smearing with liquid carbolic acid and alcohol. After removal of the tumor and cessation of bleeding, the soft tissues are sutured tightly. In case of intradural location of the tumor, it can be extra- or intramedullary. Often already upon exposing the dura mater, it is easy to determine the presence of a tumor by the bulging, density, and special bluish coloration of the dura mater at the site of the tumor. If this is not observed, the presence or absence of brain pulsation can serve as a landmark. The absence of pulsation indicates the location of the tumor above the exposed dura mater, where one should direct one's measures; in the presence of pulsation, the tumor is located lower or it is absent. If free circulation of the cerebrospinal fluid is preserved with the tumor, this sign may not be present. Then, upon opening the dura mater,
Figure 38.
spinal cord 32 s\,
Figure 39.
subarachnoid space, trying if possible to keep the arachnoid membrane unopened, probing is performed up and down with a special narrow spatula bent at an angle, which encounters an obstacle in its path in the presence of a tumor. When the tumor is found, it is necessary to make its upper and lower ends accessible for removal. If it is extramedullary and the tumor is still located posteriorly, its removal usually does not present difficulty (Figs. 35-37). If the tumor is soldered to or has grown through the dura mater or a root, it is removed together with them. To remove a tumor from the anterior surface of the spinal cord, it is usually necessary to cut 1 or 2 roots and, turning the spinal cord by the denticulate ligament, it is easy to isolate the tumor (Fig. 38). In the cervical part, one must be careful when cutting the roots to avoid damaging the phrenic nerves. Operations are much more difficult with an intramedullary location of the tumor, when one has to dissect and peel the tumor away from the brain (Figs. 39-41). Isolation of the tumor is facilitated by suturing the tumor with threads, by which the tumor is pulled and carefully peeled out of the brain. After removal of the tumor, bleeding is carefully stopped, blood clots are removed, and the dura mater is sutured (Fig. 42). The muscles in several tiers are sutured with catgut stitches and the skin is closed tightly. In non-removable, infiltrating tumors, the latter are left and the dura mater is not sutured to create decompression. Mortality in the removal of spinal cord tumors, according to Adson, is 7%; according to Elsberg, out of 120 cases 11%; Heuer, out of 46 cases 19.5%; Petit-Dutailis, out of 20 cases 10% after the operation and 30% from 2 months to 3 years after the operation. Mortality depending on the location of the tumor: according to Elsberg, out of 106 extramedullary tumors 9.5%, out of 14 intramedullary 21%; according to Petit-Dutailis, out of 4 extradural 0 deaths and 2 cases from 1 to 3 years after the operation, out of 12 extramedullary 1 case and 2 from 3 to 4 months after the operation, out of 4 intramedullary 1 case and 2 from 2 months to 2 years after the operation. As can be seen from the cited results, the immediate unfavorable outcome depends to a large extent on the location of the tumor extradurally, extra- or intramedullary. Exactly the same are the long-term results. Part of the patients die from relapses, another part from the consequences of compression--paralysis, cystitis, pyelonephritis, bedsores. The prognosis depends on the time, degree, and nature of the paralysis. If paralyses have existed for more than 6 months, the prognosis is unfavorable, although in rare cases paralyses existing for years undergo regression after treatment; the prognosis is better in spastic and worse in flaccid paralyses. Long-term results are clearly presented by Elsberg: out of 95 removed tumors with 8 fatal outcomes, a good result was obtained in 72%, unsatisfactory in 10.6%, relapses in 3%, and unknown in 5%. In addition to the above-mentioned surgical interventions, a number of operations for spastic paralyses have been proposed. This includes resection of the posterior roots of the spinal cord--radicotomy (see) for shooting pains in tabetics, for neuralgic pains in cases of non-removable tumors, their metastases, and the consequences of trauma. Transection of the posterior roots Dvi-ix is performed, according to
Figure 40.
Figure 41.

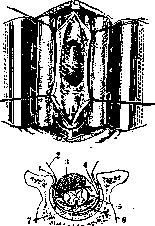
For theoretical crises, according to Förster, intradurally or, according to Guleke, extradurally. In view of the recurrence of pain in half of the cases, it is recommended to perform a more extensive resection from D10 to L1 and even with the severing of the anterior roots, where, according to Lehmann, pain-conducting fibers also pass. For spastic paralyzes of the upper extremities, the severing of the roots C4-5, C6-8 and D1 is performed, according to Förster; for the lower extremities-L2-3, L4 and S5. The results of the operation are not always good, therefore it is used only in severe cases not responsive to any other treatment. According to Eleckiy, out of 97 cases, death occurred in 13 and success only in 49 cases. Resection of the posterior roots for peripheral pains is now almost abandoned as not achieving success. A similar operation has been proposed for severe forms of spastic torticollis. With an incision in the upper part of the neck from behind, the spinous processes and arches of the I-III cervical vertebrae and the lower part of the occipital bone are exposed and excised. The dura mater is incised, the medulla oblongata with the upper part of the spinal cord is exposed, and one- or bilateral severing of the I-III spinal roots and one- or bilateral severing of the spinal part of the accessory nerves is performed. The best result is obtained from the severing of the 1-2 first cervical roots with bilateral severing of the accessory nerve (Olivecrona, Polenov).
For the treatment of paralysis of the lower extremities, urinary bladder, anastomoses between the roots of the cauda equina have been proposed (Burdenko, Girgov, Shevkunenko), where the paralyzed root is sutured into a healthy one from the opposite side or into a root of the same side but lying above the injury. As a result of such operations, improvement in the function of the paralyzed organ is noted. For malignant tumors, recurrences of tumors causing unbearable pain,
tabetic crises, causalgias, pains in amputation stumps,
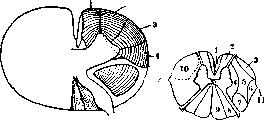
Figure 43.
Figure 44.
Figure 43. Location of conductors of various types of sensitivity: 1-pressure; 2-touch; 3-pain; 4-temperature sensitivity. Figure 44. Scheme of anterolateral cordotomy: 1- direct pyramidal tract; 2-anterior column; 3-Gowers' tract; 4-commissural fibers of gray matter; 5-lateral column; 6-tract of Flechsig; 7-lateral pyramidal tract; 8-tract of Burdach; 9-tract of Goll; 10-scheme of anterolateral cordotomy; 11-denticulate ligament. When irradiating pains do not respond to any conservative and operative treatment on peripheral nerves and posterior roots, severing of the spinothalamic anterolateral tract (fig. 43 and 44) in the spinal cord is proposed - cordotomy (Frazier, Robineau). The operation consists in the resection of 2-3 arches at the level of D8-9 or D10-11. The dura mater is carefully opened without damaging the arachnoid to avoid the outflow of cerebrospinal fluid for better orientation in the roots. The lateral surface of the spinal cord is exposed, the denticulate ligament is severed and the spinal cord is further turned with a clamp so that its anterolateral part is turned backward. Often a root is an obstacle to this, which has to be severed. Then it is easy to see in front of the denticulate ligament a light, glistening, poorly vascularized strip 2 mm wide between it and the anterior root. An incision is made on this space with a special Frazer knife to a depth of 2.5-3 mm. The operation is performed on the side opposite to the pain. In bilateral pains, the severing is done from both sides 1-2 cm below one another to avoid thinning of the cord. Immediately after the severing, pain sensitivity ceases to the corresponding level on the side opposite to the severing. If the incision is made to sufficient depth, the result is permanent. The mortality from the operation for malignant neoplasms reaches up to 25%, but is lower at present. Polenov has 2 deaths out of 40 cordotomies. The result in most cases is good, although in some cases a recurrence of pain occurs, but less intense than before. For pains from malignant neoplasms of internal organs and gastrointestinal crises, where it is necessary to bilateral cessation of pain sensitivity, Armour proposed to sever the anterior commissure, where all pain-conducting fibers terminate at the level of D11-12 and L1. The operation is extremely delicate, as it is difficult to make an incision strictly along the median line in front of the spinal cord and avoid injury to the anterior spinal artery. The operation was performed by Armour with a fatal outcome from pneumonia.
Related articles
Cite this page
“Spinelli.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/spinelli/