Cerebellopontine Angle
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This historical article from the 1928-1936 Soviet Great Medical Encyclopedia details the anatomy, pathology, and surgical approaches concerning the cerebellopontine angle. It focuses extensively on acoustic nerve tumors, differential diagnosis, and historical neurosurgical techniques by prominent surgeons.
Encyclopedia article (1928–1936)
CEREBELLOPONTINE ANGLE (Klein-hirnbruckenwinkel, angle ponto-cerebelleuse, according to some, angle ponto-bulbo-cerebelleuse) occupies a peculiar place in neuropathology, neurohistopathology, and neurosurgery. This name designates the angle between the cerebellum, the medulla oblongata, and the pons. On the cerebellar side, the angle corresponds to the extremely anterior section of the lower surface of the organ, at the site of exit of the middle cerebellar peduncle. Through this space in the frontal direction and almost horizontally enters a bundle consisting of cranial nerves VII, VIII, and the nervus intermedius. Immediately posteriorly and medially in the lateral diverticulum of the fourth ventricle lies the choroid plexus of the fourth ventricle; Cushing in his cases found lesions of cranial nerves VI and VII in two-thirds of the total number. Geymanovich did not observe such a high frequency of lesion of the sixth cranial nerve. cerebral symptoms are an early sign of cerebellopontine angle tumors, processes in the pyramid of the temporal bone must under certain circumstances be differentiated from

Figure 1.
Figure 2.
Figure 1. Acoustic nerve tumor growing into the canal. Figure 2. Relation of the acoustic nerve tumor to the canal. early stages of cerebellopontine angle tumors. A specific tumor of the angle is the fibroma, resp. neurofibroma of the eighth cranial nerve (fibrosarcoma, etc.). The history of the question of the symptomatology and pathology of the angle is connected with the history of tumors of this nerve (the first description was apparently made by Sandifort in 1777). Acoustic nerve tumor (Fig. 1 - 3), Acusticus-tumor, can be a manifestation of generalized neurofibromatosis. On this basis, both bilateral angle tumors and a combination of an angle tumor with neurofibromatosis of other areas can develop. As for tumors of the cerebellopontine angle region originating not from the acoustic nerve, they can be related either to diffuse or limited tumors of the skull base (meninges, bones, in particular cholesteatomas of the base), or to tumors originating from the brain substance itself [see separate table (p. 71 - 72), Fig. 3]. Other formations capable of producing similar symptom complexes can be aneurysms and hematomas, parasitic formations (cysticercus, echinococcus), abscesses (mainly otogenic), syphilis, rarely tuberculosis. Syphilis
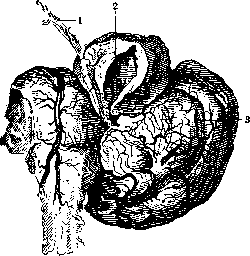
Figure 3. Acoustic nerve tumor (1) with cystic (2) degeneration; 3-cerebellum.
may manifest here in a gummous or serous-cystic form (Akopodzhanyants, Robustov), sometimes on both sides (bilateral syphilitic cyst simulating a bilateral cerebellopontine angle tumor - Geymanovich). Changes in the cerebrospinal fluid in a typical acoustic nerve tumor (at least in the early stage) boil down to hyperalbuminosis (extracerebral compression), usually without cellular elements, and with high pressure - to xanthochromia. Hyperalbuminosis, phenomena on the part of the acoustic nerve, and corneal hypesthesia (especially if cerebellar phenomena are added to this) serve as early symptoms of a cerebellopontine angle tumor. Radiologically, widening of the internal acoustic meatus is detected, but there may
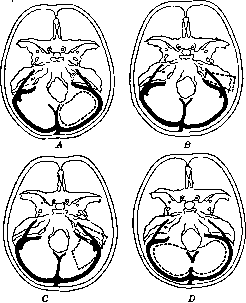
Figure 4. The dotted line indicates the position of the bony openings in relation to the sinuses: A-with unilateral intervention; B-through the labyrinth; C-combined and D-with bilateral intervention.
also occur narrowing of it due to reactive hyperostosis.
A. Geymanovich. Surgery of the cerebellopontine angle. When establishing the diagnosis of a pontine-cerebellar tumor, the operation is performed similarly to that for a cerebellar tumor or through the labyrinth (Fig. 4). The latter is recommended by otologists. Before proceeding into the depths of the posterior cranial fossa (see Cerebellum, surgery), it is necessary to thoroughly examine the state of the cerebellar hemispheres - compare their size, position, consistency, blood supply, and pay attention to the relationship of the medulla oblongata to the foramen magnum and to the degree of protrusion of the hemispheres from the opening of the dura mater. Too significant prolapse of the hemispheres characterizes a intracerebellar tumor rather than a pontine-cerebellar tumor. In the absence of sharp changes in the hemispheres, the cerebellopontine angle is examined. The hemisphere is usually retracted with a large spatula medially and upwards (Fig. 5). Often in the cerebellopontine angle, serous cysts are found, in front of which true tumors are located. Searching for tumors sometimes presents significant difficulties, and it is necessary to displace the cerebellar hemisphere considerably, which is very undesirable. When the tumor is discovered, its removal is performed either by enucleating it with a fin
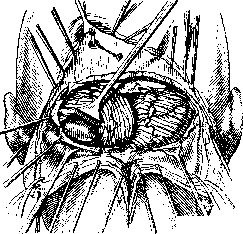
Figure 5. ger (a method no longer finding supporters) or by means of careful removal in parts. First, the tumor capsule is opened (Fig. 6), then the tumor is removed in parts with a spoon (Fig. 7 and 8), which in most cases is easily accomplished in view of its fatty degeneration. During removal and after removal, there is significant bleeding from the walls of the capsule - it is stopped either by tamponade or by some fixing liquids (formalin solution, Zenker's fluid). The second method, which at one time attracted the attention of surgeons, is the "tumor suction method" (Krause; 1903). In this method, a glass tube is brought to the surface of the tumor, sucked onto it, and pulled; at the same time, the capsule, adjacent healthy tissues, and vascular bundles are pulled, which it is recommended to ligate. The latter is very difficult in view of the tightness, and usually during suction it is more a matter of tearing, which is accompanied by significant bleeding. The third method of access to cerebellopontine angle tumors is through the dissection of the cerebellar hemisphere or by means of its removal (Borchardt, Frazier). Although these operations are tolerated by patients, and functional disorders are not so severe, they have found few followers, since in most cases such trauma is excessive. During operations in the cerebellopontine angle region, especially when removing acoustic nerve tumors, an extremely important moment is the preservation of the acoustic and facial nerves, and in neoplasms of the cerebellopontine angle region in the true
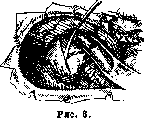
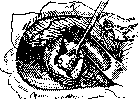
Figure 7.
sense of the word, one has to think about the trigeminal nerve and abducens nerve. Preservation of these nerves is not always possible, besides, it must be noted that the listed nerves are sometimes themselves affected by the disease process (see above). Along with neoplasms of the acoustic nerve and tissue neoplasms in the cerebellopontine angle region, during surgical intervention one most often has to find serous restricted meningitis, syphilitic and tuberculous meningitis. These diseases in symptomatology in some cases are difficult to distinguish from true neoplasms, and only during the operation is the correct diagnosis established. Recently in the literature one increasingly encounters reporting data from various authors indicating the successes of topical and functional diagnosis in relation to cerebellopontine angle tumors, but errors are still inevitable: a number of processes leading to erroneous diagnosis have been described: Meniere's disease, Bell's palsy, facial nerve neuralgia, multiple sclerosis, multiple neuritis of cranial nerves, occipital neuralgia, torticollis, progressive bulbar palsy, bulbar syndrome, tabes dorsalis, tumors of the corpora quadrigemina, psammoma of the third ventricle, temporal lobe tumors, tumor of the Gasserian ganglion, and finally frontal lobe tumor. The surgeon must be aware of the possibility of such processes so that in case of negative examination results he can change the course of the operation and use the operation for diagnostic purposes. - Results of surgical intervention. Mortality in surgical interventions is quite high. Until the beginning of the last decade, it fluctuated between 68 - 75 - 86.6% (statistics of Tooth, Henschen, Krause, Eiselsberg). During the last 15 years, Cushing has published a series of reporting papers indicating that the mortality rate fell successively from 40 to 33.3, 30, 24, 20, and to 11.1%. As for functional results, the figures for cure and significant improvement are still small.
N. Burdenko.
535 VI. Surgery of the cerebellum..................562 Cerebellum, small brain, cerebellum, cervelet, Kleinhirn, one of the constituent parts of the brain, managing the coordination and regulation of all movements, both voluntary and reflex. The cerebellum is an unpaired, symmetrical organ; the cerebellum lies in the posterior cranial fossa (see Craniocerebral topography); it forms the posterior wall, or roof, of the fourth ventricle; it is located posteriorly to the medulla oblongata and pons, inferiorly to the corpora quadrigemina, beneath the posterior lobes of the cerebral hemispheres, from which it is separated by a process of the dura mater (see), the so-called tentorium (tentorium cerebelli) (Fig. 1 and 18). I. Phylogenetic development of the cerebellum. The cerebellum in various classes of animals develops in parallel with the entire central nervous system: rudimentary in lower animals, it reaches its maximum
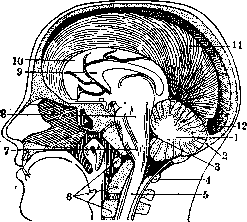
Figure 1. Sagittal section of a human head: 1-cerebellum; 2-internal occipital protuberance; 3-fourth ventricle; 4 and 6-upper cervical vertebrae; 5-spinal cord; 7-medulla oblongata; 8-pons; 9-corpus callosum; 10-frontal lobe of the brain; 11-falx cerebri of the dura mater; 12-confluence of sinuses.
development in mammals. The histological structure of the cerebellum in animals of all classes, with the exception of the most primitive ones, is essentially identical; it consists of gray and white matter; the gray matter, forming its cortex, is divided into three layers (molecular, granular, and between them a single row of large Purkinje cells) and covers the entire surface of the cerebellum. In addition to the cortex, accumulations of gray matter are also found in the deep parts of the cerebellum, forming subcortical nuclei. Beneath the cortex lies the white matter, formed by various functionally related fibers—association, commissural, and projection. In amphioxus and myxines, which live as parasites in the bodies of other fish or on stones by attaching themselves to them, the cerebellum is absent. The most primitive cerebellum is found in
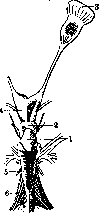
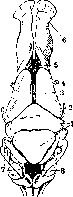
Figure 2.
Figure 3.
Figure 2. Brain of a shark: 1—cerebellum; 2—optic tectum (corpora bigemina); 3—olfactory lobe; 4—diencephalon; 5—medulla oblongata; 6—vagus nerve. Figure 3. Brain of a salamander: 1—cerebellum; 2—trochlear nerve; 3—optic tectum; 4—optic nerve; 5—cerebral hemispheres; 6—olfactory lobe; 7—medulla oblongata; 8—fourth ventricle. the lamprey (Petromyzon): it has the appearance of a plate located behind the optic tectum and is, as it were, a continuation of the nuclei of the medulla oblongata (nuclei of the lateral and vestibular nerves). This plate possesses grain cells characteristic of the cerebellum; as for the Purkinje cells, there is no true layer of them, but rather scattered large cells distributed irregularly among the cells of the granular layer. This primitive cerebellum nevertheless has its afferent pathways—the lateral and vestibular nerves; the existence of a connection with the spinal cord has not been proven, but there are fibers connecting it crosswise with the hypothalamus, as well as with the midbrain. Efferent fibers originate in the large cells of the cerebellum and terminate in the motor region of the medulla oblongata and midbrain, partially decussating. Besides the cortical cells, there is also an accumulation of gray matter at the border with the medulla oblongata—the subcerebellar nucleus; fibers from it run after decussation to the nuclei of the oculomotor nerve. Figure 4. Brain of a salmon: 1—cerebellum; 2—optic tectum; 3—cerebral hemispheres; 4—olfactory lobe; 5—cranial nerves; 6—medulla oblongata. Thus, the cerebellum here is not a simple plate, a simple fusion of the nuclei of the medulla oblongata, but an organ connected by afferent and efferent pathways with the surrounding formations. The cerebellum of fish. The cerebellum of cartilaginous fish (Plagiostomata), such as the shark and ray, is also located behind the
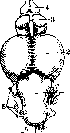
optic tectum; more complex in its structure, it has the appearance of an elongated outgrowth attached by its base to the brainstem and free at the back (Figures 2 and 4). In teleost fish, its surface is smooth; in cartilaginous fish, it is divided by furrows into convolutions analogous to the convolutions of higher vertebrates. In the cerebellum of fish, one can distinguish a middle part—the corpus cerebelli—and two lateral formations—the cerebellar auricles (auriculae cerebelli), which are homologs of the flocculi in mammals. In most fish, a transverse furrow divides the corpus cerebelli into anterior and posterior parts, which in turn in large fish are subdivided into a series of convolutions: the larger the animal, the more convolutions and the more complex the cross-section pattern; sometimes the division of the corpus cerebelli into parts is uneven—the anterior part is smaller than the posterior. The histological structure of the cerebellar cortex in higher fish is more differentiated, and its connections are more complex. Inside the cerebellum there is a ventricle, the place of which in higher animals is occupied by white matter, whereas in fish the white matter is poorly developed and has the appearance of a narrow strip located directly beneath the layer of Purkinje cells; it consists of centrifugal and centripetal fibers. There are no true subcortical nuclei in the fish cerebellum, with the exception of a small accumulation of cells in the outer parts of the cerebellum (the lateral cerebellar nucleus, which connects with the nuclei of the vestibular and lateral nerves). The connections of the cerebellum with surrounding formations are very rich—terminating in the cerebellum, besides a portion of the fibers of the vestibular nerve, are fibers from the spinal cord, partially decussating, then fibers from the medulla oblongata and from the midbrain. Among the efferent fibers are described: 1) fibers running from the Purkinje cells to the motor centers of the medulla oblongata and spinal cord; a very small part of them ends near the nucleus of the oculomotor nerve; 2) the brachia conjunctiva, originating in the lateral cerebellar nucleus and partly in the Purkinje cells; their fibers decussate and end for the most part in the reticular nucleus of the medulla oblongata, near the nucleus of the third nerve, with the remainder in the primitive red nucleus and in the hypothalamus; 3) the cerebellovestibular and cerebellobulbar tracts, the fibers of which coordinate between the cerebellum and the medulla oblongata. In amphibians (Amphibia), a difference in the structure of the cerebellum is observed between tailed and tailless forms—in the latter it is better developed. In general, the amphibian cerebellum is more primitive than that of fish; on the one hand, it resembles the lamprey cerebellum—having the appearance of a plate with thickenings on the sides; on the other hand, the fish cerebellum due to the presence of cerebellar auricles. In tailed amphibians (salamander), the latter are very large and adjoin the lateral walls of the midbrain, fusing with it (Figure 3); inside they contain a very wide cavity—the lateral recess. The corpus cerebelli is located above the fourth ventricle and consists symmetrically of two thickenings connected by commissural fibers, among which small clusters of nerve cells can be seen. The molecular layer covers the entire surface of the cerebellum; in the corpus cerebelli there are also large nerve cells—a rudiment of Purkinje cells; there are no grain cells. Of the afferent fibers, some terminate in the corpus cerebelli and some in the cerebellar auricle, consequently there is the same division as in fish. The former fibers include the spinocerebellar system (ventral and dorsal spinocerebellar tracts), fibers running from the hypothalamus (crossed connection), and the tectocerebellar tract. In the cerebellar auricle terminate the fibers of the lateral and vestibular nerves. The axons of the large cells form the efferent fibers of the cerebellum (motor cerebellar tract), partially decussating and terminating in the nuclei of the oculomotor nerves; the other efferent system—the brachium conjunctivum—after partial decussation terminates in the tegmentum of the midbrain, where the red nucleus is located in higher animals. Finally, in the amphibian cerebellum there are intrinsic fibers connecting both halves of the corpus cerebelli and forming the commissural system. In tailless amphibians (frog), the difference in the structure of the cerebellum lies in the fact that the corpus cerebelli is much better developed, whereas the cerebellar auricles remain poorly developed and in parallel with this the vestibular system is poorly developed. The cortex covering
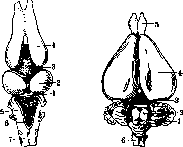
Figure 5.
Figure 6.
Figure 5. Brain of a snake: 1—cerebellum; 2—optic tectum; 3—diencephalon; 4—cerebral hemisphere; 5—medulla oblongata; 6—fourth ventricle; 7—spinal cord. Figure 6. Brain of a rabbit: 1—cerebellar hemispheres; 2—cerebellar vermis; 3—corpora quadrigemina; 4—cerebral hemisphere; 5—olfactory lobe; 6—medulla oblongata. the corpus cerebelli consists of two layers—molecular and granular, between which Purkinje cells are regularly distributed. The connections of the cerebellum with surrounding formations are the same as in tailed amphibians. The cerebellum of reptiles (Reptilia) presents great diversity in size and shape. In snakes, due to the fact that they have only a trunk and no limbs, the cerebellum is very small in size and has the appearance of a thin transverse plate thrown across the fourth ventricle (Figure 5); Purkinje cells are very numerous and lie close to one another. The lizard cerebellum has a very peculiar structure in the form of a curved plate covering also the posterior part of the optic tectum; the molecular and granular layers are very well developed. In turtles and crocodiles, the cerebellum has a well-developed form with a cavity inside, partially filled by the choroid plexus; true cerebellar furrows
appear only in the crocodile. There are two transverse furrows that divide the corpus cerebelli into three parts—anterior, middle, and posterior lobes; the latter is connected with the cerebellar auricle, which is very poorly developed, weaker than in fish. The cerebellar cortex is constructed according to the general principle. One can note the accumulation of cells that are homologs of the central nuclei of the cerebellum, namely the tegmental nuclei and dentate nuclei. Among the afferent pathways, the spinocerebellar fasciculus is very well developed; of the efferent ones, there are bundles originating in the nuclei (brachium conjunctivum), the hook-shaped bundle (uncinate fasciculus), and one bundle from the cortical cells (motor cerebellar tract).
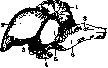
In birds (Aves), the cerebellum reaches a very large development even in relation to the cerebral hemispheres (Figure 7); it Figure 7. Brain of a pigeon: 1-cerebellum; 2-cerebral hemisphere; 3-III ventricle; 4-hypophysis; 5-quadrigeminal plate; 6-pons; 7-spinal cord; 8-medulla oblongata. is formed almost exclusively by the middle lobe, and lateral lobes or hemispheres appear for the first time only in some birds: they are barely outlined in the goose, chicken, and sparrow, and are clearly visible in the pigeon, ostrich, duck, and stork. In general, in those birds that rise into the air and can stay there, the lateral parts are better developed. The middle lobe is rich in sulci dividing it into transverse lamellae, the number of which varies from 10 to 20 (according to Leuret); the larger the bird, the more developed are the sulci and lamellae. When comparing the weight of the cerebellum in various bird species, it was noted that its development is associated with a certain functional ability—in seabirds, which have to stay in the air longer, the cerebellum is better developed. The cerebellum of birds consists of a cortex, white subcortical matter, and four central nuclei (two middle and two lateral); in addition, in the peduncles connecting the cerebellum with the medulla oblongata, there is a nucleus belonging to the VIII pair of cranial nerves. In the avian cerebellum, the presence of several systems of afferent fibers going into the cerebellum from the base of the posterior horns of the spinal cord, from the nuclei of the posterior columns, from the corpus bigeminum, and terminating in the cerebellar cortex was established. Fibers originating in the cerebellar cortex belong to commissural, association, and also projection fibers; of these, the latter terminate in the central nuclei. The greater part of efferent fibers originates in the central nuclei and goes to the nuclei of the vestibular nerve, to the motor nuclei of the trigeminal nerve, facial nerve, and spinal cord, to the olives of the medulla oblongata, and into the posterior longitudinal fasciculus, with which they reach the nuclei of the oculomotor nerves and the spinal cord. The cerebellum of mammals (Mammalia) is characterized by an increase in the size of the lateral lobes forming the hemispheres, as well as the flocculi (Figures 6 and 8). The hemispheres, as newly appearing formations, are given the name neocerebellum, and the middle part (vermis and flocculus), as old formations, is called palaeocerebellum. The development of the neocerebellum is linked to the development of the main olive and the cortex of the cerebral hemispheres (corticopontine fibers). The development of sulci occurs in a strict order. Initially, the main sulci appear, dividing the cerebellum into three lobes—anterior, middle, and posterior (as in birds), and thus the middle lobe is singled out, which serves as the basis of the cerebellum in lower animals. The main role is played by the posterior part, designated by Bolk as the lobus complicatus. The ratio between the central part (vermis) and the lateral parts (hemispheres) varies depending on the animal species: the central part is very well developed in rodents, much less so in ruminants and herbivores. The hemispheres are very strongly developed already in monkeys and reach a maximum in man; their development is subordinate to the development of the cerebral hemispheres, and the development of the pons and middle cerebellar peduncles proceeds in the same direction; in monkeys, for example, the sizes of the pons, middle peduncles, and cerebellar hemispheres are very significant, as are those of the cerebral hemispheres. The number of sulci and convolutions increases with the size and weight of the cerebellum. In mammals, there is a very close relationship between the central nuclei of the cerebellum and the nuclei of the vestibular nerve; Bechterew's nucleus extends almost to the nucleus fastigii itself in the form of separate small islands of gray matter; the inferior olive reaches a very large development and takes on a scalloped appearance; its phylogenetically old part (accessory olives, frontomedial part of the main olive) connects with the vermis, which is also a phylogenetically older formation; the remaining part of the olive connects with the cortex of the hemispheres. In mammals, in addition to the cerebellar pathways >
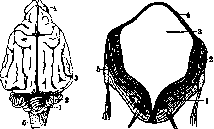
Figure 8.
Figure
9.
Figure 8. Brain of a dog: 1—cerebellar hemisphere; 2-vermis; 3-cerebral hemisphere; 4-olfactory lobe; 5-medulla oblongata. Figure 9. Cross section of the posterior brain vesicle of a human embryo of 41/2 weeks: 1-basal plate; 2-alar plate; 3-IV ventricle; 4-roof of the IV ventricle; 6-vagus nerve. existing in lower animals, new ones appear, namely the cerebro-ponto-cerebellar pathways, connecting the cortex of the cerebral hemispheres with the cortex of the cerebellar hemispheres through the nuclei of the pons. The cerebellar nuclei in the lowest mammals (Insectivora) are found in the amount of one; in other lower ones—two (nucleus fastigii and nucleus dentatus) or three (plus nucleus interpositus), and finally in the highest—four central nuclei; each of the nuclei corresponds to a specific section of the cortex, with which it is connected by projection fibers. The principle of dividing the cerebellum into the palaeocerebellum, or vermis, and the neocerebellum, or hemispheres, is generally accepted. The correctness of such a division is confirmed by phylogenetic, ontogenetic, anatomical, and patho-anatomical data. When studying phylogenetic development, one can note the presence of the vermis in all classes of animals, whereas hemispheres appear in higher ones. Ontogeny teaches that the development and differentiation of the cerebellar cortex occur earlier in the vermis and the flocculus; sulci also develop earlier in the palaeocerebellum; the presence of myelin fibers is already clearly expressed in the 7th month of intrauterine life, whereas in the hemispheres there is still no myelin even at birth; connections with surrounding formations are different—the vermis is connected with the lower divisions of the central nervous system (spinal cord and medulla oblongata), and the hemispheres with the upper ones (brain, midbrain), while in histological respect there is no difference between them. In some patho-anatomical processes, such as in atrophies, the neocerebellum changes more often as a young and therefore less stable formation. But despite all these data, the principle of dividing the cerebellum in the longitudinal direction into the vermis and hemispheres is not recognized by everyone, and it is proposed to divide the cerebellum in the transverse direction; according to these authors, the vermis cannot be separated from the hemispheres; by means of experiments, it was possible to prove that the same systems partly terminate in the vermis as in the hemispheres; during patho-anatomical examination of atrophy cases, changes were also found in the vermis. According to these authors, the oldest parts of the cerebellum should be sought not along the midline, but in its basal and peripheral parts, which form the foundation upon which younger parts can develop; the terms "vermis" and "hemispheres" are used by them to define only the central or lateral parts of individual lobes. In contrast to the division into the vermis and hemispheres, Bolk distinguishes only two parts in the cerebellum—the lobus anterior, very insignificant, covered with transverse sulci, and the lobus posterior, housing almost the entire cerebellum; between them lies the primary fissure; the lobus posterior in turn is divided by Bolk into 2 parts—anterior and posterior: the anterior (lobus simplex) is relatively little developed and also covered with transverse sulci, while the posterior part consists of a common middle lobule and two lateral ones; the middle one of small sizes is bounded on the sides by the paramedian fissure and is subdivided into 3 parts—anterior, middle, and posterior. In the lateral lobules, three parts are also distinguished—lobulus ansiformis, lobulus paramedianus, and formatio vermicularis; this division is especially clear in the dog's brain. II. Ontogenetic development of the cerebellum. The neural tube, from which the entire central nervous system develops, has the appearance of thick curved lateral plates connected by anterior and posterior commissures; each of these plates breaks down into two—ventral (basal) and dorsal (lateral, alar) (Figure 9); these plates have unequal morphological significance. The neural tube is divided into head and spinal divisions, transitioning into each other; the head division is divided first of all into three primary brain vesicles located one after another—forebrain, midbrain, and hindbrain. These vesicles undergo a number of changes; the hindbrain vesicle divides into the vesicles of the metencephalon and myelencephalon. The cerebellum along with the pons originates from the metencephalon vesicle; the cavity inside the vesicle turns into the fourth ventricle. In connection with enhanced growth in length, the almost straight neural tube begins to bend in the sagittal plane; three bends are obtained—two with the convexity in the dorsal direction and one in the ventral. The posterior dorsal bend corresponds to the hindbrain or cerebellum. The cerebellum develops from the lateral (alar) plates of the neural tube in the region of the hindbrain. These plates at the end of the second month of intrauterine life are connected to each other by a curved leaflet, the convexity of which protrudes into the cavity of the fourth ventricle; it is the rudiment of the central part of the cerebellum—the vermis (Figure 10). Further development proceeds faster in the vermis (Figures 11–14), which thickens and

Figure 10.
Figure 11.
Figure 10. Sagittal section of a human embryo cerebral hemisphere at 2 1/2 months: 1 - cerebellum; 2 - fourth ventricle; 3 - spinal cord; 4 - medulla oblongata; 5 - pons Varolii; 6 - third ventricle; 7 - thalamus opticus; 8 - cerebral hemispheres; 9 - corpora quadrigemina; 10 - cerebral aqueduct. Figure 11. Brain of a 3-month human embryo: 1 - cerebellar hemisphere; 2 - vermis; 3 - corpora quadrigemina; 4 - longitudinal sulcus of the midbrain; 5 - cerebral hemispheres; 6 - fourth ventricle; 7 - medulla oblongata; 8 - spinal cord. On the hemispheres of the cerebellum, convolutions begin to stand out only in the middle of the fourth month; at the end of the second month, a small protrusion appears on the lower surface of the cerebellum, which corresponds to the flocculus. In the fifth month, the cerebellum acquires its final shape; four deep sulci divide it into five major parts: the first corresponds to the upper surface of the hemispheres and the vermis, the second to their posterior margin, and the third, fourth, and fifth to the lower surface. Along with the development of the cerebellar hemispheres, the pedunculi cerebelli ad pontem Varoli appear; the fibers run forward and inward and, surrounding the pyramidal tracts, form the basis of the pons Varolii. At the end of the third month, the nuclei dentatus et fastigii appear inside the cerebellar hemispheres; from the former, the pedunculus cerebelli ad corpora quadrigemina departs, which also develops from the lateral plate at the level of the isthmus; fibers of the vestibular nerve are directed to the nucleus fastigii. During the last months of intrauterine life, the cerebellum increases in size, and the number of secondary

Figure 12.
Figure 13. Figure 12. External surface of the brain of a 3 1/2-month human embryo: 1 - cerebellum; 2 - corpora quadrigemina; 3 - cerebral hemispheres; 4 - temporal lobe. Figure 13. Internal surface of the brain of a 4 1/2-month human embryo: 1 - cerebellum; 2 - corpora quadrigemina; 3 - occipital lobe; 4 - cerebral hemispheres; 5 - thalamus opticus; 6 - third ventricle; 7 - pons Varolii; 8 - cerebral aqueduct; 9 - medulla oblongata; 10 - fourth ventricle. and tertiary sulci and fissures appears, which divide the lobes of the cerebellum into smaller lobules, convolutions, and lamellae, thereby giving it a very complex structure, which is especially characteristic of cerebellar sections. Myelinization of the cerebellum [see separate table (pp. 63-64), Figures 1, 2, and 3]. In a 42 cm long fetus, the cerebellar hemispheres do not have a single myelin fiber, whereas in the vermis there are already quite a few of them; fibers of the anterior commissure (see below) stain particularly intensely according to Weigert (a specific stain for myelin), while in other parts of the vermis there are fewer myelin fibers and their staining is very weak. In the white matter of the hemispheres, myelin fibers belong mainly to the corpus restiforme; near the hilus of the dentate nucleus, fibers covered with myelin and belonging, apparently, to the pedunculus cerebelli ad corpora quadrigemina are visible. Figure 14. Lower surface of the brain of a 3 1/2-month human embryo: 1 - cerebellum; 2 - temporal lobe; 3 - frontal lobes; 4 - lobus olfactorius; 5 - floor of the third ventricle; 6 - pons Varolii; 7 - medulla oblongata. In the newborn, myelin fibers enter all small ramifications of the lobules, but they are still insufficiently intensely stained, as is the white matter of the hemispheres; myelinization of cerebellar fibers continues after birth and ends by 9-10 years. III. Anatomy and histology of the cerebellum. The shape of the cerebellum is very irregular; it is compared to a sponge growing on trees [see separate table (pp. 515-516), Figures 1 and 2]. The cerebellum consists of a middle part, the vermis, and two lateral parts, the haemisphaeria cerebelli (hemispheres).

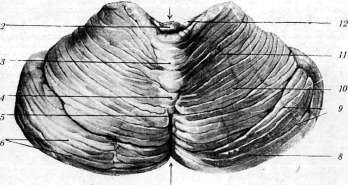
Dimensions of the cerebellum: transverse diameter from 10 to 11 cm, sagittal diameter for the vermis 3-4 cm, for the hemispheres 5-6 cm. The weight of the cerebellum is about 150 g. The cerebellum has two surfaces—upper and lower, or according to some authors (Thomas), three, including an anterior one facing the fourth ventricle; and two margins—anterior and posterior. The upper surface is divided into three parts: the vermis and 2 hemispheres; the division between them is not particularly clear; on each side of the vermis, there is a depression—fissura longitudinalis superior. The cerebellar hemispheres are longer in the anteroposterior direction than the vermis; they are separated from each other by a notch—incisura cerebelli posterior, or incisura marsupialis; the notch on the anterior margin of the cerebellum embracing the brainstem is called incisura cerebelli anterior, s. incis. semilunaris. The lower surface of the cerebellum is less even, the hemispheres are more strongly developed and protrude more downward than the vermis; between them and the vermis lie large depressions—the vallecula, or valley of Reil. The third, anterior surface turned toward the fourth ventricle can be seen by removing the cerebellar peduncles and separating the cerebellum from the pons Varolii and medulla oblongata. Along the posterior margin of the cerebellum between the upper and lower surfaces runs a deep sulcus—sulcus horizontalis magnus of Vicq d'Azyr; it runs from the incisura cerebellaris posterior to the middle cerebellar peduncles. On a sagittal section, the vermis has the appearance of a leaf [see separate table (pp. 515-516), Figure 3], the veins of which are formed by white matter; overall, a complex picture is obtained, which was named "arbor vitae" by older authors. On the anterior side at its base, there is a notch corresponding to the tent of the fourth ventricle. The apex (fastigium) of this tent is formed by the white matter of the vermis itself, the anterior upper wall by the superior medullary velum (velum medullare superius, s. anticum), and the posterior wall is partly formed by the inferior medullary velum (velum medullare inferius, s. posticum), passing downward into the epithelial membrana obturatoria. The vermis and hemispheres are divided by sulci into lobes (lobi cerebelli), which are divided by less deep sulci into lobules (lobuli), convolutions (gyri), and lamellae (lamellae). There is no complete correspondence between the lobules and convolutions of the hemispheres and the vermis [see separate table (pp. 515-516), Figs. 1 and 2], and the relationships between them are established only on the basis of embryological data.
Superior lobes of the hemisphere Lingula Central lobule (Malacarna) Culmen
Lobus anterior Lobus quadrangularis Monticulus Declive
Lobus lunatus > quadrangularis / Declive Lobus superior / Folium cacuminis
Superior semilunar lobe Superior vermis Frenulum lingulae Ala of the central lobule Inferior vermis Tuber valvulae or inferior lobes of the hemisphere Inferior semilunar lobe Tuber cerebelli (tuber) Gracile lobe Pyramid (Malacarna)
Biventer lobe, or cuneiform lobe Uvula
Amygdala (see), or tonsil Nodulus Flocculus The anterior convolutions of the superior vermis—lingula, central lobule, diverticulum of the fourth ventricle—and the anterior convolutions of the inferior vermis—nodulus, uvula—correspond to the anterior surface of the cerebellum. Among the sulci, one should note on the upper surface the deep sulcus between the superior semilunar lobe and the quadrangular lobe—the superior sulcus of Vicq d'Azyr, at the bottom of which is a deep convolution; the quadrangular lobe is divided into two parts by the superior anterior sulcus. On the lower surface, a deep sulcus (inferior sulcus of Vicq d'Azyr) runs between the inferior semilunar lobe and the gracile lobe, and anterior to it is the inferior anterior sulcus. On the vermis, the sulci bear the names of the lobules near which they pass, with the addition of the particle prae or post [see separate table (pp. 515-516), Figs. 1 and 2]. The relationship between the division of the cerebellum into lobes... Bolk: Scheme of Bolk
Vermis Anterior lobe Central lobule
Culmen Lob. simplex Declive P. Lob. medianus Lob. ansi- 5 I formis Tuber valvu- lae Pyramis Uvula Nodulus... [OCR artifacts omitted or translated literally as part of figure labels]. Microscopic structure of the cerebellum. On a section of the cerebellum, one can see that it consists of gray and white matter [see separate plate (articles 515-516), figure 4]; the gray matter forms the cortex and central nuclei, while the main mass of the cerebellum is formed by white matter, in the thickness of which the nuclei are located. The cortex covers the entire surface of the cerebellum; its thickness is uneven not only on various convolutions, but even on different slopes of the same convolution, and ranges from 1 to 2.5 mm. On transverse sections, two layers are distinguished in it: a superficial, or molecular layer (A), stratum cinereum, and a deep, or granular layer (B), stratum granulosum. On the boundary between these two layers lies a very narrow layer, stratum gangliosum, formed by a single row of large Purkinje cells (1) (figure 15). Purkinje cells are more or less evenly distributed along the convolutions; there are somewhat more of them at the apex of the convolution than in the depths; they are very large in size—60 µ in length, 30 µ in width, and 25-30 µ in thickness; they have a pear shape, located with their long diameter perpendicular to the granular layer, into which their thick end projects; from this end departs an axis-cylinder process, penetrating through the granular layer into the white matter; almost at its very beginning, it gives off collaterals which terminate partly in the granular layer and partly near neighboring Purkinje cells. From the thin or upper end, powerful dendrites depart into the molecular layer, branching into a multitude of processes and giving the cell the characteristic appearance of stag antlers. The Purkinje cell has this appearance on sagittal sections, since all its protoplasmic processes branch in a single plane; on frontal sections, the appearance of the cell is completely different (figure 16). The branching of the processes always occurs in a single plane perpendicular to the length of the convolutions, i.e., in the anteroposterior direction; they terminate freely and are covered with perpendicular spines. The molecular layer, besides these
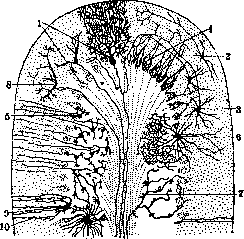
Figure 15. Microscopic structure of the cerebellar cortex: A - molecular layer; B - granular layer; C - medullary layer; 1 - Purkinje cells; 2 - small superficial cells of the molecular layer; 3 - basket cells; 4 - baskets around Purkinje cells; 5 - granule cells; 6 - large stellate cells; 7 - mossy fibers; 8 - climbing fibers; 9 - cellules empânachées; 10 - Bergmann fibers; 11 - glial astrocyte cells of the granular layer. ... branching contains stellate nerve cells of two kinds: small multipolar ones (2) are located superficially and have a short branching axon (Golgi type II cells); large cells are located in the depths of the molecular layer (3), dendrites from them go in all directions, while the axon stretches parallel to the surface of the convolution and, after a rather long path, terminates by branching near a Purkinje cell and forming a plexus around it in the form of baskets (4) (Kölliker), which is why the cells themselves are called basket cells; along its path, the axon uniformly gives off collaterals which also branch near Purkinje cells, thus one basket cell is related to many Purkinje cells. In the molecular layer, axis cylinders from the granular layer and from the white matter also branch. The granular layer consists of round cells, the smallest in size in the central nervous system (from 5 to 10 µ); their granule cells (5) surround neighboring cells with their numerous protoplasmic processes, while the axis-cylinder process is directed into... [Figure captions for figures 1, 2, 3, 4 omitted for brevity in translation matching context]
4 3 2
Sh 20 19
the molecular layer and there divides in a T-shape into 2 branches that run parallel to the surface of the convolutions and terminate in a free button. In the deep parts of the granular layer, there are also large stellate multipolar cells with a short axon (Golgi type II) (6), which branches around its own cell and around some of the granules; the protoplasmic processes terminate in the granular or in the molecular layer; from the white matter...
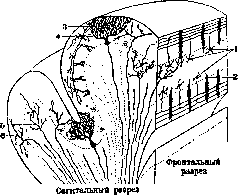
Figure 16. Schematic drawing of the cerebellar cortex: 1 - granule cells and their axons dividing in a T-shape; 2 - Purkinje cells on frontal section; 3 - Purkinje cell on sagittal section; 4 - basket cells; 5 - mossy fibers; 6 - climbing fibers.
Into this layer penetrate the mossy fibers (7) (Cajal), terminating near the granule cells; other so-called "creeping" fibers (8) merely pierce this layer and terminate in the molecular layer. The myelin fibers do not form in the cortex of the cerebellum laminae medullares, which are so characteristic of the cerebral cortex; the parallel fibers and axons are not covered with myelin; the granular layer is somewhat richer in medullated fibers and, besides radial fibers, also has transverse fibers, which are especially abundant beneath the Purkinje cells. The excitation that has reached the cortex of the cerebellum is transmitted simultaneously to several Purkinje cells either directly or through the granules. Each Purkinje cell is connected by collaterals with neighboring ones; in addition, association fibers form a close connection between individual laminae. Since these cells are the only elements of the cerebellar cortex whose axis cylinders reach the subcortical nuclei, their dominant functional significance is obvious. The arrangement of the neuroglia in the cerebellar cortex presents certain peculiarities: the absence of a glial network in the superficial layers and the presence of special cells—cellules empanachees de Cajal (9), whose bodies are located in the outer parts of the granular layer, while the processes, known as Bergmann fibers (10), pierce the molecular layer and terminate beneath the membrane in the form of a button-like thickening. Neuroglial fibers are few in the cortex (11), but they and astrocytes are very numerous in the white matter. The central nuclei in the cerebellum are four in number on each side: nucl. dentatus, nucl. fastigii, nucl. emboliformis, and nucleus globosus (see separate table, figure 4). Nucleus dentatus (s. olivacerebelli, dentate nucleus, olive of the cerebellum) is located in the white matter of the hemispheres in its inner-lower section, formed from a plate of gray matter, zigzag-bent and open on the inner side, where the hilum of this nucleus, or hilus nuclei dentati, is located; this plate is surrounded by a large number of myelin fibers that form the capsula nuclei dentati cerebelli. Nucleus emboliformis (s. embolus, emboliform nucleus) is located in the white matter of the hemisphere, adjacent and medial to the upper edge of the dentate nucleus, with which it is connected by a thin stalk. Nucl. globosus (globulus, globular nucleus) is located medial to the preceding one. Both of these nuclei are considerably smaller in size and do not have a scalloped shape; they are regarded as nucl. dentati accessorii. All three of these nuclei have the same structure: they contain a very large number of cells, myelin fibers, and branched nerve endings; the cells are medium-sized, multipolar; in the nucleus dentatus, their axis cylinders are directed toward the hilum; the nerve endings belong mainly to fibers coming from the cerebellar cortex (from the Purkinje cells), but there are also extracerebellar ones. Nucleus fastigii (s. nucl. tecti, s. noyau du toit, roof nucleus, nucleus of the tent, Kölliker's nucleus) belongs entirely to the vermis, located in its white matter directly at the midline, above the fourth ventricle; its cells are much larger (40–70 µ) and heavily pigmented; this nucleus has a connection with Bechterew's and Deiters' nuclei, its protoplasmic processes are few, finely branching, but very long and thick. The white matter occupies the central part of each cerebellar lamina, and from there fibers enter the cortex; more inwardly, the white matter of all laminae and lobules gathers together and collectively forms a very large mass in the hemispheres, whereas in the vermis there is much less white matter. Subcortical nuclei are located among the white matter. According to their function, the fibers making up the white matter are divided into association, commissural, and projection fibers. Association fibers are divided into short and long; short ones occupy the periphery of each convolution and connect neighboring convolutions (Stilling's garland fibers), while long ones occupy the center of the white matter of each lobule and connect widely separated lobules of the same hemisphere. Commissural fibers connect the opposite hemispheres. The commissures of the cerebellum (commissura cerebelli) are especially well visible on a sagittal section; a small posterior commissure is located near the declive, tuber valvulae. The large anterior commissure is located anterior and superior to the nucl. fastigii. Projection fibers are divided into centripetal and centrifugal. Centripetal fibers are the terminal fibers of the inferior and middle cerebellar peduncles (pedunculi cerebelli inferior et medius); centrifugal fibers running from the cortex (from the Purkinje cells) terminate in the subcortical nuclei, fibers from the cortex of the vermis terminate in the nucl. fastigii, and from the cortex of the hemispheres in the nucl. dentatus; the centrifugal fibers of the subcortical nuclei emerge from the cerebellum and head to other parts. The cerebellum is connected to other parts of the central nervous system by means of three pairs of peduncles (see separate table) pedunculi cerebelli infer., medius, super. At that, two peduncles consist mainly of afferent fibers—pedunc. cerebelli infer. and medius, while the third—ped. cerebelli super.—belongs to the efferent fiber system. The inferior cerebellar peduncle (pedunculus cerebelli infer., s. ped. cerebelli ad medullam oblongatam, s. corpus restiforme, restiform body) connects the cerebellum with the spinal cord and medulla oblongata and consists of two systems—spinal and bulbar. The center of the restiform body is Burdach's external nucleus or Monakow's nucleus, which gives fibers to the restiform body; then the central part is occupied by Flechsig's tract, originating in the spinal cord, a small number of fibers from Gowers' tract, which, deviating posteriorly, enter the restiform body, fibers from the nuclei of the gracile and cuneate fasciculi forming the posterior external arcuate fibers (fibrae arcuatae externae poster.), fibers from the nuclei of the lateral column of the medulla oblongata and from the nucleus arciformis of the opposite side, entering into the composition of the anterior external arcuate fibers (fibr. arcuat. ext. anter.). The peripheral part of the restiform body is formed mainly by fibers running from the inferior olive of the opposite side (fibr. olivo-cerebellar.) and in a very small amount from the olive of its own side. Having penetrated into the cerebellum, the fibers of the restiform body bypass the nucleus dentatus externally and terminate in the cortex of the hemispheres and vermis, and a very small part in the central nuclei. There is a constant relationship between the individual parts of the olive and the cerebellum; the lateral parts of the olive are in connection with the cortex of the opposite hemisphere, while the internal parts of the olive are connected with the cortex of the vermis and the part of the hemisphere adjacent to it; the ventral folds of the olive connect with the inferior surface, and the dorsal folds connect with the superior surface of the cerebellum. The olives do not receive fibers from the cerebral cortex, but receive fibers of the so-called central tegmental tract, which originates in the upper parts of the brainstem; thus, the olives connect the mesencephalon and rhombencephalon with the cortex and with the nucleus dentatus of the opposite side of the cerebellum. The second, or middle, cerebellar peduncle (pedunculus cerebelli ad pontem Varolii, s. pedunculus cerebelli medius, s. brachium pontis) runs to the cerebellum from the pons Varolii; it reaches its maximum development in man, since its development is proportional to the development of the corticopontine and pyramidal fibers; it is formed by the proper fibers of the pons Varolii (fibrae propriae pontis Varolii), which originate in the gray matter, resp. in the nuclei of the basis pontis; upon emerging from the nuclei, these fibers are divided by the pyramidal fibers into 3 layers—stratum superficiale, complexum, profundum, pass to the opposite side, forming a decussation, and at the outer edge of the pons Varolii gather together to form the middle cerebellar peduncle, which constitutes the main bulk of the white matter of the cerebellum. The middle peduncles terminate in the cortex of the cerebellar hemispheres. A small number of fibers in these peduncles run in the opposite direction—starting in the cortex and ending in the nuclei of the pons. In the gray matter of the pons, where the cerebellar peduncles originate, fibers coming from the cerebral cortex of the same side terminate, namely, collaterals from the pyramidal fibers, the frontopontine, temporopontine, and occipitopontine systems; thus, the nuclei of the pons serve as a link between the cerebral cortex of its own side and the cerebellar cortex of the opposite side and, together with the pedunculus cerebelli ad pontem Varolii, enter into the systems: occipito-, temporo-, and fronto-ponto-cerebellaris, as well as the pyramidal-cerebellar...
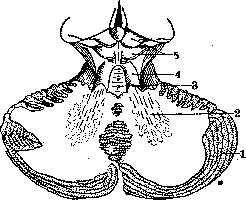
Figure 17. Section of the cerebellum (diagram): 1—cerebellum; 2—nucleus dentatus; 3—velum medullare anticum; 4—pedunculus cerebelli ad corpora quadrigemina; 5—corpora quadrigemina.
cerebellar. It is assumed that each region of the brain cortex is connected with a specific part of the nuclei of the pons and with a specific region of the cerebellar cortex. Among the fibers related to the cerebellar cortex and not passing through the mentioned pathways, one should note the striae medullares, which run along the floor of the fourth ventricle and do not belong to the auditory fibers. They originate in the nuclei of the substantiae reticularis and terminate in the cortex of the flocculus. The third, superior cerebellar peduncle (pedunculus cerebelli superior, s. pedunculus cerebelli ad corpus quadrigeminum, s. brachium conjunctivum) consists of efferent fibers originating in the cerebellum in the dentate nucleus (Figure 17); heading upwards and forwards, the superior cerebellar peduncles form the walls of the fourth ventricle and penetrate into the tegmentum of the pons, and then into the cerebral peduncle, in the lower sections of which their complete decussation occurs—decussatio Wernekinki; after the decussation, the brachium conjunctivum divides into two branches—descending and ascending. The descending branch, which is very thin, terminates very quickly in the reticular nuclei of the pontine tegmentum. The ascending branch, larger in volume and significance, penetrates the red nucleus, to which it gives a significant number of fibers, and terminates in the thalamus opticus, in
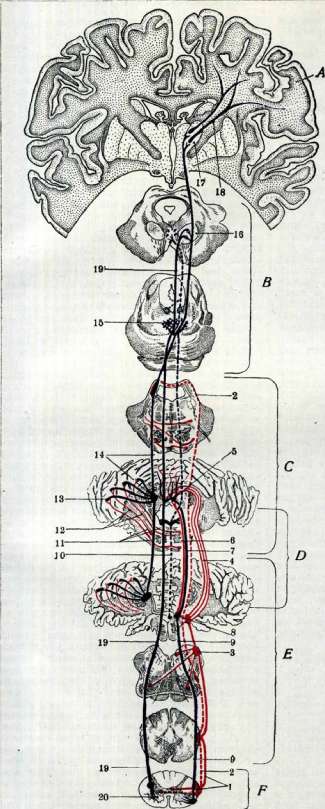
CEREBELLAR PATHWAYS: A—cerebral hemispheres; B—cerebral peduncles; C—pons Varoli; D—cerebellum; E—medulla oblongata; F—spinal cord; 1—Flechsig's tract; 2—Gowers' tract; 3—corpus restiforme; 4—pedunculus cerebelli ad medullam oblongatam; 5—nucleus fastigii; 6—fibrae vestibulo-cerebellares; 7—fibrae cerebello-vestibulares; 8—nucleus vestibularis; 9—fasciculus vestibulo-spinalis; 10—fibrae vestibulo-oculomotoriae; 11—fibrae propriae pontis Varoli; 12—pedunculus cerebelli ad pontem Varoli; 13—fibrae cerebello-dentatae; 14—pedunculus cerebelli ad corpora quadrigemina; 15—decussatio pedunculi cerebelli; 16—nucleus ruber; 17—thalamus opticus; 18—fibrae thalamo-corticales; 19—fasciculus rubro-spinalis; 20—anterior horns of the spinal cord. B. M. E. Vol. XVII. Cerebellum. the cerebellum of the ventral part of its outer nucleus. The rubrospinal tract originates from the large cells of the red nucleus, the fibers of which terminate in the anterior horns of the spinal cord after crossing. Pedunculus cerebelli ad corpus quadrigeminum represents the efferent pathway for the cerebellar hemispheres. The efferent fibers of the vermis pass through the inner section of the inferior cerebellar peduncle; they originate in the nucleus fastigii, in the nucleus globosus, and possibly in the embolus, and terminate in the nuclei of the vestibular system—Deiters' nucleus, Bechterew's nucleus, and the dorsal triangular nucleus; a part of the fibers running to these nuclei from the nucleus fastigii of the opposite side curves around the outside of the superior cerebellar peduncle upon exiting the dentate nucleus and is distinguished under the name of Russell's hook bundle (faisceau en crochet Russel). The vestibular nuclei, together with the cerebellum and all the fibers connecting them with the vestibular nucleus, form the vestibulocerebellar system. Fibres originate from the nuclei of the vestibular nerve, which partly go through the vestibulospinal tract to the cells of the anterior horns of the spinal cord and partly through the posterior longitudinal fasciculus are directed to the nuclei of the third nerve. Projection fibers originate in the cerebellar cortex and terminate in the central nuclei. The dentate nucleus and embolus receive fibers from the cortex of the hemispheres, while the fastigial nucleus and globosus receive them from the cortex of the vermis and flocculus. According to some authors, the fastigial nuclei receive fibers from the cortex of the hemispheres and the vermis; the relationships are direct, i.e., the cortex sends fibers to the nuclei of its own side. Association fibers are few and short; longer ones are located in the vermis, but have an anteroposterior direction, so they do not extend beyond the limits of the cerebellum. The vermis and hemispheres are almost independent, since a small number of fibers go from the vermis only to the lobules of the hemispheres closest to it. The existence of commissural fibers between the two hemispheres has not been proven. Thus, based on the connections that exist between the cerebellum and other formations, two systems can be distinguished in it: the vermis is connected with the spinal cord and medulla oblongata by means of the inferior cerebellar peduncle and forms the spino-cerebellar system, while the hemispheres are connected with the brain through the fibers of the middle and superior cerebellar peduncles, forming the cerebro-cerebellar system. Meninges of the cerebellum. The cerebellum, like the brain, is surrounded by three membranes—dura mater, arachnoidea, and pia mater: the dura mater at the level of the cerebellum gives off two processes—the tentorium cerebelli, which separates the cerebellum from the inferior surface of the brain (Figure 18), and the falx cerebri minor, which projects between the two cerebellar hemispheres. The pia mater enters into all the small subdivisions of the cerebellum, connecting them; between the pia mater and arachnoidea at the level of the cerebellum, cisterns are formed in which, in pathological cases, a large amount of cerebrospinal fluid accumulates (see Brain, Meninges). — Blood supply to the cerebellum. The cerebellum receives blood from three pairs of cerebellar arteries: superior cerebellar artery, anterior inferior cerebellar artery, and posterior inferior cerebellar artery, which are branches of the basilar artery
this artery begins with two trunks and from the vertebral artery.
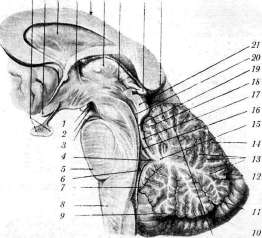
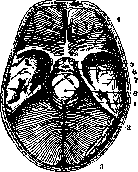
and vertebral artery. According to some data (Jakob), there is also a fourth artery—the middle inferior cerebellar artery, but this artery is inconstant. In general, there are many variations regarding the number of arteries, their place of origin, and their branching, which indicates large individual deviations in the blood supply to the cerebellum. The posterior inferior cerebellar artery originates from the vertebral artery (in 68.5%), more rarely from the basilar artery, or on one side from the basilar artery, and on the other from the vertebral artery, or finally is covered by the tentorium cerebelli: 1—cerebellum; 2—tentorium cerebelli; 3—confluens sinuum; 4—anterior cranial fossa; 5—optic nerve; 6—oculomotor nerve; 7—middle cranial fossa; 8—cerebral peduncle with the cerebral aqueduct. and then they unite into a single common trunk, which supplies blood to the medulla oblongata, and then, curving around the tonsil, goes to the inferior surface, where it divides into two secondary branches (more rarely into three or four)—medial and lateral, which subdivide into a number of smaller arteries supplying the inferior surface of the vermis and hemispheres, and the anterior surface of the flocculus (Figure 19). — The anterior inferior cerebellar artery originates from the basilar artery, sometimes by a common trunk with the previous artery, then divides into two, more rarely three secondary branches; on its way it gives branches to the cerebellopontine angle, to nerves VII and VIII, and to the choroid plexus. In the cerebellum, it supplies blood to the nodulus, flocculus, and outer sections of the inferior surface of the cerebellum (Figure 20). — The superior cerebellar artery is the most constant of the cerebellar arteries; it originates from the basilar artery, posterior to its division into terminal branches, and posterior to the oculomotor nucleus it divides into two (more rarely three) large branches—lateral and medial; each of these branches in turn divides in various combinations and variously in number into tertiary branches. The outer branch supplies the upper surface of the hemispheres (Figure 21), at the outer edge anastomoses with the anterior inferior cerebellar artery, and in case of weak development or absence of the latter, takes over the vascularization of the outer sections of the inferior surface of the cerebellum as well. The medial branch supplies the upper surface of the vermis and the inner sections of the hemispheres. Between the arteries there are anastomoses both between the large trunks and between the secondary and tertiary
Figure 20. Inferior surface of the cerebellum: a—area of vascularization of the anterior inferior cerebellar artery (various variants of artery distribution are indicated on one and the other side); b—area of vascularization of the middle inferior cerebellar artery; 1—pons Varoli; 2—quadrangular lobule (anterior part); 3—flocculus; 4—quadrangular lobule (posterior part); 5—biventer lobule; 6—tonsil; 7—inferior semilunar lobule; 8—medulla oblongata.
typical; between the arteries of the same side an anastomosis occurs in the hemispheres, and between the arteries of different sides in the vermis. The dentate nucleus is very rich in vessels, which it receives mainly from the secondary medial trunk; according to some data, the posterior inferior cerebellar artery and the anterior inferior cerebellar artery take part in the supply of this nucleus. The arteries of the dentate nucleus are a frequent cause of hemorrhage in the cerebellum. The fastigial nucleus receives blood from almost all the arteries supplying the vermis. For the chemical structure of the cerebellum, see Brain. Vessel injection. To study the angio-architectonics of the brain (to determine the terminal vessels in the brain and the ratio of vessel distribution to myeloarchitectonics and cytoarchitectonics, particularly in connection with the doctrine of pathoclises), in particular the cerebellum, the brain vessels are injected with colored solutions, which must necessarily be "solidifying." Several such solutions have been proposed: 1) a gelatin solution to which cinnabar or India ink was added (Tandler's method), 2) gypsum or chalk and talc in equal doses, to which is added
surface of the cerebellum. [OCR garbled text]
Area of vascularization - ... [The text continues describing methods of vascular injection of the brain using glycerin, India ink, etc., through the vertebral and carotid arteries, followed by anatomical and physiological studies of the cerebellum, detailing the history of cerebellar research from the 17th to the 20th century, including the works of Willis, Haller, Rolando, Flourens, Magendie, Wagner, Ferrier, and others regarding the functions of the cerebellum, coordination, equilibrium, and the effects of its experimental lesion or electrical stimulation, which were fully confirmed by clinical observations of cerebellar patients.]
The initiator of the second period of the doctrine of the cerebellum is Luciani. His early works (1884) mark the beginning of the period of strict analysis of all phenomena appearing following the destruction of the cerebellum; they played a very large role in elucidating the functions of the cerebellum. Thanks to the improvement of surgical techniques, he managed to ensure that animals survived the operation for a fairly long time and could be examined in detail over an extended period. Luciani viewed the cerebellum not as an aggregate of organs with different functions, but as a central organ, completely homogeneous in functional terms, each segment of which has the same function and can replace another. In its normal state, the cerebellum exerts a sthenic, tonic, and static action on the neuromuscular apparatus; sthenic action is a very complex function through which the cerebellum increases the potential energy of the neuromuscular apparatus; tonic action is manifested by the enhancement of the tension of the neuromuscular apparatus at the moment of its functional phase; static action accelerates the rhythm of elementary impulses during their activity and ensures the fusion and correct duration of contractions. Through its efferent pathways, the cerebellum directly or indirectly exerts a trophic influence; upon its removal, various dystrophic disorders are observed: degeneration of the skin, muscles, a slower growth rate, and a decrease in the body's resistance in the fight against external harmful agents; the life of such animals is shorter, and so on. The influence of the cerebellar hemispheres extends to the corresponding side of the body, whereas the connection between the cerebellum and the cerebral hemispheres is crossed. Upon experimental destruction of the cerebellum, the author observed symptoms of two kinds—irritation symptoms, appearing immediately after the operation, and deficit symptoms, developing some time after it. Irritation phenomena manifest themselves in strong excitation and frequent crying. In the case of unilateral destruction, there is a curvature of the spine in the direction opposite to the operation, tonic extension of the limbs on the corresponding side, strabismus, nystagmus, rotation of the body around its axis from the damaged side to the healthy one; upon complete destruction of the cerebellum, the spine is curved backward, when walking the animal crawls backward and falls, strabismus convergens is revealed, tonic convulsions in the front paws, and clonic convulsions in the hind ones. Gradually, the irritation phenomena weaken and disappear, and then deficit symptoms come to the fore, characterized by the disruption of the three main functions of the cerebellum—sthenic, tonic, and static: operated animals develop asthenia, atonia, and astasia. The rotation of the animal around its axis was explained by a sudden disturbance of equilibrium in the activity of the brain centers; it was suggested that the limbs play a large role in this phenomenon, since if all four limbs of the animal are bound, the rotation phenomenon does not occur. Subsequent authors who worked in this field (Russel, Ferrier, Turner) generally confirmed the phenomena observed by Luciani and introduced only some details regarding reflexes, sensitivity, and so on. Bianchi, based on his experiments, noted the possibility of a substitutional function of the cerebrum upon the removal of the cerebellum, which is confirmed, in his opinion, also anatomically by the enhanced development of the anterior parts of the brain (gyrus sigmoidalis) in cases of cerebellar destruction. According to Schiff, the cerebellum contains mechanisms that make muscle groups work, necessary for the execution of complex movement, and not only the muscle group that directs movement, but also the groups that fix the limb (ligaments, joints, muscles) and thereby provide a point of support; these muscles are generally antagonists of the directing muscles. Of the later works on the physiology of the cerebellum, the most interesting are the studies of the French school, namely André Thomas. He performed a large number of diverse experiments—complete removal of the cerebellum, removal of the hemispheres, the vermis, and sectioning of the cerebellar peduncles. He performed his experiments on dogs and monkeys, and although his work did not yield anything new for the physiology of the cerebellum, they are valuable because they confirmed the conclusions of previous authors on a large amount of material; his explanations of the results obtained are interesting, as well as the fact that he provides an anatomical basis for all data obtained experimentally. According to his data, the phenomena observed upon destruction of the cerebellum can depend on the irritation of the damaged areas, or on the loss of their functions, or finally on the replacement of lost cerebellar functions by the function of neighboring areas. The earliest phenomena are irritation symptoms; they can occur even on the operating table, but are usually short-lived. Then deficit phenomena are discovered, and lastly, substitution symptoms appear. Upon removal of half of the cerebellum, rotation of the body around the longitudinal axis is observed, appearing immediately upon awakening; bending of the body with concavity toward the operated side; strabismus—the eye on the operated side looks down and inward, while on the opposite side it looks upward and outward (Hertwig-Magendie eye position), nystagmus; tonic and clonic convulsions of the limbs, rotation of the head in the direction opposite to the operation. For the first time, the animal lies motionless; it cannot walk or stand. After some time, the condition begins to improve, but muscle weakness and abnormal limb positioning during movements remain on the operated side; the limbs are overly abducted, and their movements are disproportionate and very sweeping. In monkeys with extirpation of half of the cerebellum, muscle weakness and ataxia are observed even more sharply than in dogs, and are especially noticeable during finer movements in the front limb. The operation of removing the entire cerebellum is very difficult, because neighboring parts, such as the vestibular nuclei, are often captured along with the cerebellum, which distorts the picture of a purely cerebellar lesion. Rotation around the axis is not observed or is observed very rarely; opisthotonus, rigidity of the limbs, and the inability to either stand or walk are noted; then later, upon the first attempts to stand and walk, the body sways from side to side and the animal falls; gradually the gait becomes more confident, but the animal walks not in a straight line, but in zigzags; coordination impairment is observed in the limbs, when walking they are raised very high and lowered very quickly to the ground; with changes in position, balance becomes less stable. Thomas drew special attention to the fact that after the destruction of the cerebellum, movements became less automatic, i.e., more conscious, deliberate. In a similar operation in monkeys, ataxia was more pronounced than in dogs, and such phenomena as an unsteady gait, clumsiness, uncertainty in the limbs, and slight tremor remained for life; nevertheless, the animal could climb. Destruction of the vermis caused somewhat different phenomena—opisthotonus, strong backward throwing of the head, hyperextension of the limbs, strong vertical nystagmus. When trying to stand, at first the animal fell backward, tremor was observed in the trunk; after a few days, although the animal could walk, it did so with great difficulty, staggered, and often fell backward. Subsequently, the condition gradually improved, although some abnormality in walking remained all the time. Destruction of the fastigial nucleus caused approximately the same symptoms as the destruction of the vermis. After sectioning the vermis along the midline, there was initially a very small disturbance of equilibrium, which quickly passed. Irritation of the cerebellum did not yield such clear symptoms as its destruction, and moreover, of all the stimulants (cauterization, heat, cold, mechanical irritation, etc.), the cerebellum reacted only to electric current. At the same time, when irritated by a weak current, the cortex remained unexcitable, whereas with a strong current, contraction was obtained in the entire corresponding half of the body; irritation with a weak current near the subcortical nuclei of the cerebellum (dentate nucleus, fastigial nucleus, Deiters' nucleus) caused movement of the eyes, head, trunk, and limbs. Experiments with cerebellar stimulation were also performed by other authors. In the experiments of Horsley, Lowenthal, Thiele, and others, stimulation of the cerebellum had an inhibitory effect on tone; in animals in a state of contracture after decerebration, faradization of the upper surface of the cerebellum caused relaxation of the muscles of the neck, head, and lower limbs, mainly on the corresponding side. By analogous experiments, Bremer proved that mainly the cortex of the cerebellar mantle (vermis) has an inhibitory effect on the rigidity of the limbs and trunk. In general, it must be said that works on the physiology of the cerebellum done by the stimulation method are not particularly conclusive and demonstrative. Destruction of the cerebellar peduncles gave approximately the same symptoms as the destruction of the hemispheres, only apart from cerebellar phenomena, symptoms from the surrounding formations—the pons, medulla oblongata, and vestibular system—were also observed.
From the above data it can be seen that the destruction of the cerebellum does not cause very strong and persistent disorders, especially if the operation is performed on one side; it is assumed that the remaining half assumes the function of the removed one; upon removal of the entire cerebellum, disorders in the motor sphere are observed, initially in the form of convulsive phenomena, and then in the form of impairment of the coordination of movements or so-called cerebellar ataxia. Thus, on the basis of experimental data, the conclusion can be drawn that the cerebellum takes part in movements, coordinating them. The same is indicated by the data of phylogeny, the anatomical structure of the cerebellum, and its connections. Anatomical data indicate that the cerebellum is connected by centrifugal and centripetal fibers with a large number of formations—with the spinal cord, with the vestibular apparatus, with nuclei in the telencephalon (nucleus ruber), with the thalamus opticus, and with the cerebral hemispheres. In this complex system, the cerebellum is located between the sensory and motor pathways: on the one hand, it receives sensory impulses from the skin of the entire body and from deep parts (ligaments, muscles, tendons, and bones) associated with movements (through Flechsig's tracts and the corpus restiforme), then from the semicircular canals the sensation of the position of the body in space (through the vestibular system—see), as well as an impulse from the cerebral cortex through the pyramidal, cortico-pontine fibers and fibers of the pedunculi cerebelli ad pontem Varolii; on the other hand, the bulk of its centrifugal fibers goes to the motor centers: partly from the nucleus dentatus through the red nucleus into the rubrospinal tract, partly from the nucleus fastigii through Deiters' nucleus into the vestibulospinal tract. Both tracts—vestibulo- and rubrospinal—terminate in the motor cells of the anterior horns of the spinal cord. These anatomical connections indicate that the cerebellum belongs to the motor system and that it is a reflex organ capable of functioning without the participation of will and consciousness. As a higher reflex center, it is connected with muscle centers only through the agency of intermediate centers, such as the red nucleus, Deiters' nucleus, the reticular substance, and so on. Under the influence of peripheral irritation or irritation coming from the cerebral cortex, the cerebellum becomes active, and its influence through centrifugal fibers is transmitted to the cells of the anterior horns of the spinal cord and further to the corresponding muscles. According to the data of phylogeny, we see that in lower animals, in which movements are very monotonous (swimming, crawling), the cerebellum is very poorly developed, but as we ascend the zoological scale, movements become more diverse and complex, and in connection with this, the cerebellum increases in size and its structure becomes more complex; in such animals, removal of the cerebellum causes more clear-cut movement disorders in the form of impaired coordination of movements and balance. On the basis of all the foregoing, the conclusion can be drawn that the cerebellum is an apparatus that regulates the action of muscles coming into contraction during standing, walking, and during voluntary, reflex, and automatic movements, and ensures their correct coordination, i.e., making all movements synergistic. The coordination of muscle contractions during walking and standing leads to the maintenance of equilibrium—static equilibrium in a resting state and kinetic equilibrium during movements; to maintain equilibrium, synergy in the work of the corresponding muscles is necessary. In the body, each muscle unit consists of an agonist and an antagonist, which work synergistically. In static equilibrium, the contraction of agonists and antagonists is completely balanced, resulting in so-called isosthenia. When the trunk moves, the center of gravity also moves, and in order to restore the disturbed balance, both agonists and antagonists must contract, but the agonists contract stronger, so that physiological anisosthenia is obtained; the cerebellum regulates these contractions reflexively; the system connecting the cerebellum with the spinal cord (spinocerebellaris) and terminating in the vermis takes part in this work; this function of it can be imagined as follows. Impulses from the periphery of the body and from the semicircular canals flow into the cerebellum all the time and maintain tonic excitation in it; any change in body position through afferent fibers reaches the cortex of the cerebellum and causes a response reaction in it, which through the corresponding systems is transmitted to the cells of the anterior horns and regulates the contraction of muscles necessary at a given moment to maintain balance. Any attempt to shift equilibrium around the horizontal or vertical axis acts as an irritating moment on the corresponding centers of the cerebellum, which forces the antagonists and compensatory elements to function, thanks to which equilibrium is preserved. - In addition to maintaining balance, the cerebellum has an influence on the coordination of movements in general, as well as on their synergy. For correct voluntary movement, very strict coordination of muscle work is necessary: the entry into activity of strictly defined groups of muscles; the contraction of each muscle separately with such force as is required for a given task; the observance of a strict sequence in the contraction of muscles. In addition, for each movement, the activity of not only agonists and antagonists is necessary, but also of other muscles that fix the interested part of the body. The cerebellum takes part in all this coordinatory work of muscles; in complex movements, apart from coordination, with its participation, the association of individual elementary movements into a complex one occurs, i.e., the cerebellum also manages the synergy of movements. By a special tonic influence, the cerebellum regulates movements in such a way that they occur with minimal expenditure and achieve the goal, so that the movements included in a single act are synchronous; thus, when walking, moving the foot forward, it is necessary at the same time to transfer the center of gravity of the body to it, which is absent in patients with a lesion of the cerebellum (Fig. 22); bending backward, a healthy person bends his knees (Fig. 23), while a patient cannot do this (Fig. 24); during rapid alternating movements, for example, supination and pronation, the agonist and antagonist muscles must contract proportionately so that these movements are smooth and sequential. The cortex of the cerebellar hemispheres takes part in these voluntary movements, which comes into action under the influence of irritation coming from the cerebral cortex; consequently, during voluntary movements, the cerebro-cerebellar system functions. - The coordinating influence of the cerebellum also extends to the oculomotor apparatus. Its connection with the oculomotor apparatus is as follows: the cerebellum through the nucleus fastigii is connected with Deiters' nucleus, which sends fibers through the posterior longitudinal fasciculus to the nucleus of the abducens nerve of its own side and to the nucleus of the oculomotor nerve of the opposite side; with unilateral action, the eyes are skewed to the corresponding side, while normally the bilateral impulses mutually balance each other. - The cerebellum also exerts a coordinating effect on the muscles of the speech apparatus, respiratory, swallowing, and masticatory apparatuses, thanks to its connections through the reticular substance with the nuclei of the corresponding nerves. Here it is appropriate to
Figure 22.
Figure 23.
Figure 24.
to pose the question of what kind of coordinative action this is for the cerebellum: does it send coordinating impulses itself, or, as a higher center, does it act through the mediation of other divisions? Anatomy points rather to the second assumption, since nowhere in the cerebellum is there a grouping of cells or a special central apparatus that could be regarded as a center of coordination. Is the cerebellum functionally homogeneous or, conversely, can it be divided into strictly limited centers, each of which individually governs special functions? This question of the localization of functions is a debatable one. Some authors recognize the presence of the same kind of separate centers in the cerebellar cortex as exist in the cerebral cortex; others speak out against this. The dissimilar attitude of parts of the cerebellum to the afferent systems, the difference in the time of development of its lobules, as well as clinical data (the difference in symptoms observed upon the destruction of the vermis and the hemispheres)—all these facts suggest that the cerebellum is a heterogeneous organ throughout its entire mass and that there must be a certain localization within it. The cerebellar cortex apparently possesses a single function, and localization consists merely in assigning this function to one or another part of the body, to various muscle groups that act in a given direction. The first attempt to elucidate localization belongs to Bolk. On the basis of comparative anatomical studies, he gave a new division of the cerebellum, and then, upon comparing the cerebellums of various animals, he found that there is a certain relationship between the development of the cerebellar lobules and the functional development in animals of one or another body part or muscle groups: in accordance with these observations, he distributed the centers in the cerebellum (cf. Bolk's scheme). Muscles functioning jointly with muscles of the other side (muscles of the trunk, neck, larynx, tongue, and eyes) are served by unpaired centers lying in the middle lobule. Limbs, however, working both jointly and separately, are innervated by centers of a twofold kind—unpaired (in the middle lobule) and paired (in the lateral lobules). Bolk's studies provoked a whole series of experimental works. Experiments with irritation of the cerebellum by an electric current were performed by many investigators. Irritation with a faradic current of the lobi quadrangularis in a monkey caused movements of the fingers of the upper limb on the same side, wherein irritation of the more anterior parts of this lobule caused extension, and irritation of its posterior parts caused flexion of the fingers (Rothmann). Irritation of the anterior lobule (according to Bolk) produced abduction of both upper limbs. In Bremer's experiments, irritation of the cortex of the cerebellar hemisphere and of the red nucleus had no effect on the tone of decerebrate animals, whereas irritation of the cortex (vermis), especially at two points—at the level of the lobulus centralis and in the pyramis (places of termination of the spinocerebellar tract),—exerted an inhibiting, relaxing effect on tone. All these experiments at the present time do not, however, give the right to definite and final conclusions. Experiments with the destruction of the cerebellum yielded more precise results. The data of experiments by Rijnberk, Rothmann, Thomas, and others speak in favor of functional localization. They showed that the removal of limited parts of the cerebellar cortex causes a disturbance of movement coordination, atonia, and asthenia of the muscles on the operated side in various, but definite parts of the body, in accordance with the removed section; if the destruction is very limited, then the function of some single group may be impaired—flexors, extensors, abductors, or adductors; this change in function manifests itself in a disturbance of tone—in hypotonia of muscles acting in one direction and hypertonia of others acting in the opposite, thanks to which, during contractions, a disturbance of equilibrium occurs in the muscles and hence an incorrect limb position, which the animal either does not correct at all or corrects with great delay. With very limited damage, the animal does not correct displacements of the limb in one direction or another, but corrects it in others, e.g., does not correct when the limb is strongly abducted, and corrects when the limb is in a state of adduction; at the same time, the experimenter encounters no resistance whatsoever upon setting the limb in a given position—it remains passive. Thus, upon the destruction of a small section of the cerebellum, a dual effect is observed: hyposthenia (decrease in resistance) in muscles acting in one defined direction, and hypersthenia (increase in resistance) in muscles acting oppositely, i.e., anisosthenia in antagonist muscles. This disturbance in the function of antagonists leads to abnormal positions that the limb assumes. Anisosthenia and passivity lie at the basis of dysmetria observed in cerebellar disease. It was established (Rothmann) that there exist in the cerebellum four separately located ("localized") centers for 4 groups of skeletal muscles, namely: for the muscles of the neck, back, forelimbs, and hindlimbs. Further work in this direction led to the conclusion that destruction of the vermis causes a disorder of equilibrium in standing and walking, while destruction of the hemispheres gives ataxia, resp. asynergy in the movements of the limbs of the corresponding side; the forelimb is dependent on the lobus quadrangularis, the hindlimb on the lobus ansiformis. Damage to the very anterior sections of the lobulus anterior (lobus centralis) is accompanied by a disorder of movements of the jaw and larynx; destruction of the lobus simplex causes a disorder in head movements. Relatively recently, an attempt was made to determine the cerebellar centers in humans. Bárány, when studying nystagmus, drew attention to reactive movements in the trunk, limbs, and sometimes even in individual joints of the limbs; these movements are analogous to those that appear in diseases of the cerebellum. These data forced him to assume that centers directing movements in joints must exist in the cerebellum, or rather a totality of directing centers, since for each joint or even for each movement in a joint there exists its own center. These are centers for the direction of movements inward, outward, upward, and downward. They exert a constant tonic influence on the muscles. Under normal conditions, they act simultaneously and with equal force, which is why their influence mutually balances out; upon irritation of some center, the limb deviates in the corresponding direction, and upon the fallout of a center, its antagonist takes the upper hand. Centers that influence the position of the trunk are located in the cortex of the vermis, while limb movements are dependent on centers located in the cortex of the cerebellar hemispheres and connected with the cerebral hemispheres. Bárány attempts to localize some limb centers along the surface of the cerebellar hemispheres, and from the side of some clinical observations he found confirmation for himself, but this localization is contested by other clinicians. Thus, the existence of localization in the cerebellum is beyond doubt, but the arrangement of individual centers along the surface of the cerebellum and in its depths and the very nature of these centers have not yet been definitively established. V. Pathology of the cerebellum. Being an integral part of the brain, the cerebellum can be seized by a disease process simultaneously with other parts of the brain, which is observed in diffuse processes in the brain (e.g., in inflammations, arteriosclerosis, syphilis) or in processes arising in the vicinity of the cerebellum and upon further development seizing the cerebellum as well, but in addition the cerebellum also has its own pathology, when the process arises primarily in the cerebellum and the maximum of changes is observed in it (various degenerative processes, tumors, abscesses, cysts, etc.), while other parts of the brain, if they suffer, do so secondarily. All processes occurring in the cerebellum are analogous in their character to those observed in the brain, and therefore their etiology, statistics, pathoanatomical changes, prevention, and treatment are identical (cf. Brain). Symptomatology of cerebellar diseases. In disease of the cerebellum, regardless of the character of the process, a whole series of symptoms develops, the totality of which constitutes the so-called cerebellar syndrome (syndrome cérébelleux). Some of these symptoms are more constant and constitute as it were an inseparable part of the cerebellar syndrome, while others are rarer and are not observed in all cerebellar diseases. Variations in the intensity of symptoms, in their number and localization, can be very great even in diseases knowingly localized in the cerebellum. In some progressive cerebellar diseases, sometimes at the beginning of the disease, it is difficult to reveal a symptom that would be pathognomonic; this is explained by many factors, and especially by the substitute function of the brain, which, although not adapted to the regulating function, but thanks to the fact that it receives numerous impulses from all parts of the trunk and from all sense organs, mainly sensations from the labyrinth and visual ones, assumes to a certain extent that role which is normally performed by the cerebellum. Aside from the motor zone, associative processes and certain mental functions such as will, attention, memory, and so forth take part in this substitution.
In unilateral disease of the cerebellum, the function of the diseased hemisphere may be partly compensated by the healthy hemisphere; it has been noted by many authors that unilateral cerebellar disease produces fewer symptoms than bilateral or diffuse disease. Recently, in connection with a more detailed acquaintance with the physiology of the basal ganglia, the question has been raised regarding the possible substitution of these latter for the lost functions of the cerebellum. Thus, when examining a patient with a cerebellar disease, one must bear in mind all the above-stated possibilities. The cerebellar syndrome is characterized by: 1) cerebellar ataxia, expressed by a disturbance of balance and coordination of movements; 2) dizziness; 3) muscle hypotonia; 4) involuntary movements, muscle weakness, and disorders of speech, writing, and nystagmus. The disturbance of balance, which is one of the characteristic and frequent symptoms of cerebellar damage, can exist in isolation from all other movement disorders of the lower and upper limbs. It can be kinetic and static, i.e., observed during walking and standing: the patient stands with widely spaced legs, the head is tilted forward, backward, or to the sides, the upper limbs are in a state of abduction, as if regulating balance, but there is no complete immobility, and the body sways either back and forth or to the sides; in rare cases, these sways are so strong that the patient cannot hold their balance and falls to one side or the other. This inability to stand (astasia) depends either on the muscles of the trunk, or the muscles of the lower limbs, or both simultaneously. For a short time, the patient can maintain balance with the feet together; closing the eyes does not affect the maintenance of balance (consequently, Romberg's sign is absent), though perhaps swaying is somewhat increased; standing on one leg is impossible, and the patient falls at the very attempt to lift a leg. The disturbance of balance also manifests when sitting with arms crossed on the chest: the body sways in various directions depending on the localization of the process; this instability is clearer at the beginning of the test and with any change of position, which is performed very uncertainly and slowly; during the transition from a sitting to a standing position, the patient grabs onto surrounding objects until able to assume a more stable position. All these phenomena can vary in intensity depending on the disease. With a disturbance of balance, walking also suffers greatly—the patient walks slowly, uncertainly, cautiously, with widely spaced legs, in very small uneven steps (marche à petits pas); they walk not in a straight line, but deviating to the sides, in zigzags ("drunken man's gait"); in unilateral cerebellar disease, they deviate toward the side of the affected hemisphere. When walking, the patient lifts their legs very high and abruptly and lowers them just as quickly; swaying of the trunk is noted; the upper limbs are in a state of abduction and do not swing during walking. Uncertainty is especially pronounced at the beginning of walking, at the end, and during turns. Walking backward and to the sides is even more difficult, and the patient cannot run at all. Any unusual actions reveal the disturbance of balance more strongly. When walking, the patient fixes their gaze not on their own legs, but on the surface along which they are walking. Closing the eyes does not worsen the gait particularly much. Fatigue (asthenia) sets in very quickly upon damage to the hemispheres. True cerebellar paralyses are observed very rarely; usually, in most patients with unilateral damage, there is no noticeable difference in strength between the sides, and very rarely in some a decrease in strength is noted on the affected side. The speed for most movements is reduced, especially for movements performed on command; to reveal this symptom, the patient is forced to perform movements simultaneously with both hands, for example, bringing a finger to the nose: usually, the finger on the affected side lags behind. The amplitude of movements, on the contrary, is increased on the affected side, and movements are performed with a certain abruptness, haste, and mostly overshoot the set target. This lack of measure was described both in humans and in animals, and the name dysmetria (Luciani), hypermetria (Babinski) was proposed for it. The lack of measure in movements is observed not only in relation to space, but also to time—the limb retains the position assumed by it for some act even after the completion of this act. To detect dysmetria, several tests have been proposed, e.g., touching the tip of the nose with a finger; in this case, the finger usually overshoots the target, touches the cheek, but cannot remain in one place, and a whole series of oscillatory movements occurs in it, moving the finger from one place to another; a similar experiment with touching the tip of the ear with a finger; this experiment is more complex and succeeds with greater difficulty; in the patient's lying position, there are even more errors. In the lower limbs, dysmetria manifests during walking; when trying to place the heel on the opposite knee, the patient lifts the leg very high and places it on the thigh; the same excessive range of movements is observed when the patient places the foot on a chair. Dysmetria worsens insignificantly with closed eyes, which is of very great diagnostic significance (see also Dysmetria). Phenomena of dysmetria also include the phenomenon of "past-pointing" (Vorbeizeigen), which consists of the following: the subject is asked to touch the index finger of an outstretched arm to the finger of the doctor sitting opposite and holding his finger outstretched forward. First, this experiment is done with open eyes, and then with closed eyes; the patient usually misses, deviating toward the healthy side. The preceding elicitation of nystagmus (by rotation or caloric stimulation of the labyrinth) does not have a large effect on the deviation of the finger, whereas if the latter experiment is done with a healthy person, they will have a very strong deviation of the finger. Sometimes dysmetria consists in the fact that when performing some action, the patient's limb stops short of the target, and then slowly with oscillations reaches the target; thus the act is performed in two moments; this phenomenon is called bradyteleokinesia (Schilder) and is observed in both the upper and lower limbs. Due to a disruption in the ability to associate individual elementary movements in relation to each other in order, time, and space into a single complex movement, the execution of a complex act is disrupted; this disorder is called asynergia and dyssynergia, and it is demonstrated by a series of experiments. One of the experiments, known as flexion combinée de la cuisse, consists of the following: the patient is placed on their back with arms crossed on the chest and asked to assume a sitting position—upon the attempt to sit up, usually on the affected side (Figure 25) rises
Figure 25.
upward the leg, whereas in a healthy person the legs remain motionless (Fig. 26) (see Asynergy). In cerebellar disease, there is also a disorder of complex sequential motor acts in the form of slowed or impossible alternation of movements—adiadochokinesia (see). Dysmetria and tremor cause a disorder of writing—one of the frequent symptoms of cerebellar disease; the letters are very irregular, of varying length and width, the lines of the letters are uneven, sometimes wide and sometimes narrow, with steps; the patient cannot draw a straight line, it turns out to be sinuous; the writing disorder is especially demonstrative when drawing a zigzag line; if the patient writes in small letters, it is difficult to read anything; if the patient is asked to draw a line between two points, they either overshoot the intended point or fall far short of it. Tremor very frequently accompanies cerebellar diseases; it can be observed either only during movements or also in a calm state, i.e., it can be kinetic and static. In milder cases, only the smoothness of movements is disrupted: they become abrupt, fragmentary; in more severe cases of cerebellar damage, the tremor resembles intention tremor, i.e., it intensifies upon reaching the target. Sometimes, if the patient performs the movement slowly and monitors themselves, tremor may be absent. Tremor is very clearly revealed in the following experiment: take a glass filled to the brim with water or shot and carry it to the mouth. In the head and trunk, tremor is stronger when the patient performs some action while standing; when sitting or lying down, it decreases. Tremor is also explained by the abruptness of movements and the lack of measure, which under normal conditions is corrected by antagonistic muscles. Despite all desire and effort, the patient does not

Figure 26.
can stop the tremor, but can reduce it; distraction increases the amplitude of the tremor. Static tremor appears in certain individuals always under the same conditions and in the same positions, for example, when carrying a weight in an outstretched arm or during strong pronation of the arm, etc. In cerebellar patients, a special ability is observed to maintain a fixed position of the body or a limb longer than is possible for a normal subject; this condition is called cerebellar catalepsy. In sharply pronounced cases, the fixed part remains completely immobile until the investigator gives it a normal position; absolute catalepsy is observed very rarely, for the most part there are small swinging movements, especially at the beginning of the experiment at the moment of setting the limb. Dizziness is observed very often in diseases of the cerebellum; it has a rotational character, i.e., it seems to the patient that all objects are spinning around him or he himself is spinning around them. Dizziness can be constant and increase with any movements or appear in attacks, for the most part when changing position, e.g., from lying to sitting or from sitting to standing. Dizziness is always accompanied by nausea, and sometimes by vomiting (see Dizziness). Speech is mostly impaired; a scanned, monotonous speech with a nasal tint is observed; each syllable is pronounced gradually; speech, like other motor symptoms, depends on dysmetria, adiadochokinesia, and the intermittency of movements. Mimics are very poor during speech and laughter, which is also a result of adiadochokinesia. Nystagmus is not particularly strong, horizontal, appearing at extreme eye positions; rotatory or vertical ones are much rarer; with unilateral lesions of the cerebellum, nystagmus appears when looking toward the affected side. In diseases of the cerebellum, changes in muscle tone are observed: upon palpation they are more flabby, hypotonic; during passive movements, the muscles of the affected side offer no resistance, the amplitude of passive movements is more significant due to the fact that the reflex of antagonists is lowered—there is hypotonia or hyposthenia, but sometimes, conversely, an increase in the reflex of antagonists is observed; then the resistance during passive movements increases, and hypersthenia results. The state of tone manifests itself not only during passive movements, but also during reflex movements and those caused by mechanical irritation of the muscles; there is a series of experiments allowing one to check the state of tone (see Tone). Tendon reflexes are altered, response movements to stimuli are faster and their amplitude is increased; in some patients, a pendular type of knee reflexes is observed, to reveal which the patient is placed on a table with dangling legs and struck on the ligamentum patellae: the shin, instead of responding to this stimulus once, describes several swinging movements of flexion and extension; on the affected side, these phenomena are much more sharply expressed; the same applies to the reflexes of the upper limb from the triceps muscle; the plantar reflex is livelier on the side of the lesion. Postural reflexes fade. Movements caused by mechanical irritation of the muscle have a wider amplitude on the affected side, which is explained by stronger muscle contraction; it especially deserves attention that the limb does not immediately transition to a state of rest, but describes several pendular movements. The patient cannot exert any influence on these involuntary movements, despite all efforts. During electrical examination with galvanic or faradic current, muscle contraction is stronger on the affected side. Superficial sensitivity is preserved; of deep sensitivity, sometimes the sense of weight and joint sensitivity are impaired: the patient less quickly orients himself in movements produced on the affected side; in the literature, there are observations of cerebellar wounds in which patients overestimated the weight and spatial dimensions of some object; the threshold of irritation for differentiating the sense of pressure increases. Finally, among the symptoms observed in diseases of the cerebellum (true, rather rarely), associated movements should be noted, more strongly expressed in the lower limbs and sometimes extending to all four limbs. Symptoms of cerebellar irritation include violent movements that appear suddenly: the body moves forward, backward, to the sides; sometimes such movements occur only in the limb: during some voluntary movement, the arm is thrown aside by a sudden movement; these movements can be explained either by irritation of agonists or inhibition of antagonists; the phenomena when patients drop objects on the floor are explained by relaxation of agonists or irritation of antagonists. The above-described cerebellar syndrome develops either suddenly or gradually and remains more or less persistent depending on the process. Isolated cases of periodic cerebellar ataxia have been described: in a patient, a disorder of equilibrium, gait, writing, speech suddenly develops without any prodromal symptoms, nystagmus and other symptoms appear; after a few hours, everything passes, and the patient becomes completely healthy. There is a tendency to consider such a form of cerebellar ataxia as an equivalent of epilepsy with localization in the cerebellum. The combination of the above-described symptoms varies depending on the localization of the pathological process, since anatomical and physiological data indicate various connections and functions in different parts of the cerebellum. The syndrome of the vermis lesion and the syndrome of the cerebellar hemisphere lesion, which can be unilateral or bilateral, are distinguished. In diseases of the vermis, there is a disorder of equilibrium when walking, standing, a tendency to fall backward, severe dizziness, speech disorders, nystagmus, tremor. Since the functions of the upper and lower vermis differ, it can be assumed that the syndromes of their disease also differ. Loss of function of the upper vermis produces a disorder of equilibrium in the head muscles, speech disorders, nystagmus, while a lesion of the lower vermis leads to a disorder of equilibrium in the trunk muscles. The unilateral syndrome of the cerebellar hemispheres is characterized by a coordination disorder in the limbs on the corresponding side, sometimes with a predominant lesion of the upper or lower limb (adiadochokinesia, dysmetria, asynergia, tremor, change in muscle tone, nystagmus). Cerebellar hemisyndrome may depend either on a lesion of the cerebellar cortex or its nuclei, or involve fibers leaving or entering the cerebellum, most of which undergo decussation along their path; in cases where the cortex, subcortical nuclei, and fibers before decussation are affected, the cerebellar hemisyndrome is observed on the same side; upon lesion of fibers after decussation or those centers where they end or begin (red nucleus, thalamus opticus, gray matter of the pons), the hemisyndrome will be on the opposite side. All symptoms are more intensely expressed if the process captures the cerebellar subcortical nuclei. An assumption was made about the participation of the dentate nucleus in the myoclonic syndrome. In diseases of the cerebellar peduncles, the cerebellar syndrome is almost always associated with other symptoms indicating the simultaneous participation in the process of surrounding formations—cranial nerves or nuclei, motor, sensory pathways, the sympathetic system—and these accompanying symptoms facilitate topographic diagnosis. Among the cerebellar peduncle syndromes, the syndrome of Wallenberg or the posterior inferior cerebellar artery is the most famous. In most cases, thrombosis of its branches is observed, which leads to softening in the retro-olivary region. At the beginning of the disease—nausea, vomiting, swallowing disorders, headaches—then cerebellar symptoms join—equilibrium disorders, dizziness, dysmetria, adiadochokinesia on the affected side; besides, sensitivity disorders in the area of the trigeminal nerve, crossed hemianesthesia, pharyngo-laryngo-palatal hemiparesis, sympathetic eye symptoms are observed. Cerebellar symptoms in this case depend on a lesion of Monakow's nucleus and the lateral nucleus of the medulla oblongata, sending fibers to the restiform body, olivocerebellar fibers or the restiform body itself, Gowers' tract, or finally on a lesion of the fibers or nuclei of the vestibular system (see Alternating syndromes). The superior cerebellar peduncle syndrome varies depending on whether the peduncle is captured before or after decussation. Before decussation, the peduncle can be captured simultaneously with the tegmentum of the pons, and then cerebellar symptoms are present on the affected side, while sensitivity disorders are on the opposite side. If the lesion is very significant and extends low, it can simultaneously capture the inferior cerebellar peduncle, and then cerebellar disorders are very strongly expressed. Disease of the peduncle at the place of its exit from the dentate nucleus is often accompanied by a lesion of the trochlear nerve, so that there is paralysis of the superior oblique muscle.
Lesion of the cerebral peduncles after the decussation is accompanied by disease of the red nucleus as well, so that there is no longer a syndrome of the peduncles, but a syndrome of the red nucleus, or Benedict's syndrome (see Alternating syndromes); when the process extends to the base of the peduncle, in addition to Benedict's syndrome, Weber's syndrome is present. A syndrome of the middle cerebellar peduncle is observed with a focus at the base of the pons Varolii, and since the pyramidal fibers are also simultaneously damaged, a very complex syndrome is obtained in general, characterized by hemiplegia and bilateral cerebellar symptoms (owing to the lesion of the pontine nuclei, proper fibers of the pons, and peduncles). Frequently under these conditions, the so-called pontocerebellar form of pseudobulbar palsy develops. Rotation around the axis is not noted in all cases. Diagnosis of cerebellar diseases. In the presence of a complete cerebellar syndrome, the diagnosis does not present great difficulty, but in clinical practice one has to deal more often not with a sharply expressed syndrome, but with an incomplete one or with individual symptoms, and therefore the establishment of a diagnosis, especially at the beginning of the disease when many of the characteristic symptoms have not yet appeared, frequently presents difficulties. At the same time, in certain diseases of the cerebellum (tumors, abscesses, etc.), an early diagnosis makes it possible to save the patient through timely surgical intervention. Cerebellar ataxia must be differentiated from ataxias of other origins—ataxia in diseases of the frontal lobe of the brain, in disease of the labyrinth (see Labyrinthitis), ataxia of tabetic origin (see Tabes), and finally from ataxia in general diffuse diseases of the central nervous system with localization in the cerebellum (multiple sclerosis, syphilis, encephalitis, etc.). Disease of the cerebellum in its symptomatology closely approximates disease of the labyrinth, in which there are also disorders of equilibrium, coordination, gait, nystagmus, dizziness, and others, and therefore it is very difficult to differentiate them (see Labyrinthitis, Labyrinth). Usually, in labyrinthine disease, all symptoms except the equilibrium disorder are less sharply expressed, and in addition, phenomena from the side of hearing (decreased hearing, noises) are observed, while the main aid to diagnosis is various methods of examining vestibular functions (see Barany's method of investigation). The second question that must be resolved is the localization of the lesion in the cerebellum itself, which also presents great difficulties, since the process rarely affects any single part of the cerebellum, but usually spreads from the vermis to the hemisphere or vice versa, and therefore a pure syndrome is not observed, and only with a detailed interrogation is it sometimes possible to ascertain where the process began. Special pathology of the cerebellum. Anomalies of cerebellar development. These include: 1) agenesis, 2) hypoplasia, and 3) dysgenesis. Agenesis is understood as the complete or partial absence of the cerebellum. Complete agenesis is a fairly rare phenomenon. In place of the absent cerebellum, thickened meninges are found, which fold and form the roof of the fourth ventricle; the vessels running into the cerebellum are very thinned. Among the membranes in place of the cerebellum, there are mostly small formations somewhat resembling the cerebellum or some of its lobules (amygdala, flocculus, etc.). In partial agenesis, one or another part of the cerebellum is absent, more often a hemisphere, but cases of absence of the vermis have been described. The missing part is replaced by a stump giving the impression of a hemisphere in miniature, the size of a cherry stone or a walnut; it is grooved by sulci and convolutions, the cortex is absent, but the white matter and nuclei are preserved. At the level of the missing parts, the membrane is thickened and forms a pocket filled with fluid. In the absence of the hemispheres, the adjacent parts of the vermis may also suffer, whereas when the vermis is absent, the cerebellum is as if divided into two parts. Agenesis of the cerebellum is sometimes accompanied by changes in other parts of the nervous system. Due to the rarity of observations, the clinical picture of agenesis is not sufficiently elucidated. Movement disorders of the cerebellar type are observed in patients: the child begins to walk late, walking is very difficult, all movements are awkward. At the same time, there is also inferiority on the part of the mental sphere—dementia, idiocy, and inadequacy in physical development. Isolated cases have been described in which cerebellar insufficiency manifested itself at a very late age (45 years, 53 years). In the anamnesis of such patients, syphilis is mostly noted, giving meningoencephalitis in the fetus, which can have an effect on abnormal development. Hypoplasia of the cerebellum is characterized by the fact that the general configuration of the cerebellum is preserved, but its dimensions are much smaller than normal. Two groups of hypoplasia are distinguished: in the first group, the general structural plan is disrupted, various parts did not develop in parallel, some are developed more strongly, others more weakly. In the second group, the structure of the cerebellum is completely correct, all parts are developed proportionally, only its dimensions are very small. In examining cases of the first group, traces of disease during intrauterine life (mostly meningitis) are found: the pia mater is thickened, injected; the cerebellum is of very small size, sclerotic, hard to the touch; sometimes only the peripheral lamellae suffer, in severe cases almost the entire cortex is affected, the lamellae fuse together, their white matter disappears, while the subcortical nuclei remain normal; the brachia conjunctiva retain their size, since they originate in unchanged dentate nuclei. This contrast between the state of the cortex and the subcortical nuclei is characteristic of this form of hypoplasia. Very frequently such a state of the cerebellum is combined with changes in other parts of the nervous system—the membrane of the cerebral hemispheres is also thickened and injected, the ventricles are dilated, the cortex is thinned, the number of Betz cells is reduced; similar changes can be noted in the spinal cord, so that in general the entire central nervous system is reduced in size. The second group of hypoplasia is characterized by a very small cerebellum, the weight of which may not exceed 20 g (normal 140–150 g), but all the sulci and convolutions of the cerebellum, as well as the subcortical nuclei, have a normal appearance; the membrane and vessels are not altered; on the basis of weight, size, and general development, it is possible to establish at what month of intrauterine life the development of the cerebellum slowed down or stopped. Pure cases of hypoplasia are very rare. It is noted that other parts of the central nervous system are also significantly reduced in volume. Clinically, such patients exhibit cerebellar symptoms—a staggering, uncertain gait, impaired balance, coordination disorder, speech disorder, nystagmus; in the majority of patients, these symptoms appear already in early childhood, but cases have been described when they appear later—at 10 years, and finally there are indications in the literature of such cases when during life the cerebellar change was manifested by nothing and was discovered only at autopsy. Along with cerebellar symptoms, some others are observed, indicating a broader lesion of the nervous system; the intellect is greatly reduced up to complete idiocy. Agenesis and hypoplasia can be combined with dysgenesias in the form of: 1) heterotopias—the presence in the white matter of accumulations of gray matter having the structure of the cortex or subcortical nuclei, incorrectly located; 2) irregularities in the orientation of convolutions and lamellae, in places giving the impression of their doubling. In addition to the cerebellum, heterotopias are also found in other parts of the nervous system. Dysgenesias can also be observed in isolation in a cerebellum having a completely normal appearance. With anomalies in the development of the cerebellum, irregularities in the development of the skull are also observed, namely its posterior parts—the occipital fossae are reduced in size, more so on the side of the cerebellar lesion; the internal occipital protuberance is poorly developed and can be shifted more to one side, as well as other protrusions on the inner surface of the occipital bone. With a unilateral cerebellar lesion, the difference between the two halves of the occipital bone is very significant: at first glance, it seems that this bone deformation is the cause of the insufficient development of the cerebellum, whereas it is most likely only a consequence. It should be noted that various developmental defects, as well as atrophies, are observed mainly in the cerebellar hemispheres (neocerebellum), whereas the vermis and flocculus (palaeocerebellum) suffer less or remain completely normal. This fact is explained by the fact that phylogenetically younger parts of the cerebellum are more vulnerable. Cerebellar atrophies (atrophia cerebelli) are divided into two groups: secondary atrophies, developing as a result of brain disease [see separate table (pp. 551–552), Fig. 6] and primary atrophies, depending on the localization of the pathological process directly in the cerebellum, in its membranes or vessels. Secondary cerebellar atrophies (atrophia cruciata cerebelli, atrophie croisée du cervelet) depend on the primary lesion of the opposite cerebral hemisphere; they are observed in hemiplegics. Cerebellar atrophy is most sharply expressed in cases where brain disease developed at an early age or intrauterinely; atrophies are also observed in adults, but very rarely: the necessary conditions for their occurrence are extensive lesions in the brain and a long life after the process in the brain.
During post-mortem examination, very extensive changes both on the surface and in depth are found (hemorrhages, softenings on the basis of thrombosis) in the cerebral hemispheres, atrophy of the base of the corresponding half of the cerebral peduncle and the pons Varolii, and atrophy of the opposite pedunculus cerebelli ad pontem Varoli and the opposite hemisphere of the cerebellum; the vermis does not participate in the process due to the absence of connection with the cerebrum. In the cerebellum, the atrophy involves the cortex and the white subcortical matter, and among the subcortical nuclei, the dentate nucleus and emboliform nucleus. The cerebellum atrophies unevenly; those of its lobules that have the closest connection with the cerebral cortex (lobus quadrangularis) suffer more; in the affected lobules, the convolutions are very thinned, mainly due to the atrophy of the white matter; Purkinje cells are atrophic, less numerous, or even completely absent; with the participation of the dentate nucleus in the process, the pedunculus cerebelli ad corpora quadrigemina taking origin in it is altered. Many theories have been proposed to explain the mechanism of these atrophies: 1) the myelogenous theory—the reflection of a brain disease onto the cerebellum through the mediation of the spinal cord; 2) the coincidence of a brain disease and the disease of the opposite cerebellar hemisphere—the simultaneous lesion of two formations cross-connected with each other; 3) the transneural or indirect impact theory—a disease of the cerebrum via the corticopontine and pyramidal tracts caused changes in the proper nuclei of the pons Varolii, entailing the atrophy of the middle cerebellar peduncles originating there and of the opposite cerebellar hemisphere, which is the site of termination of the middle peduncles. The most acceptable is the third theory, which was confirmed by experimental work (Monakow): in newborn animals, the brain was severely damaged, and after several years, autopsy revealed atrophy of the opposite cerebellar hemisphere. In these cases, it is impossible to isolate the clinical picture of the cerebellar atrophy due to the presence of hemiplegia, which is usually very strongly expressed and obscures the cerebellar symptoms. Since these cerebellar atrophies are discovered only at autopsy, there can be no question of therapy. Primary cerebellar atrophies are also subdivided into two groups depending on the presence or absence of changes outside the cerebellum, namely in the membranes and vessels. Cerebellar atrophy may be observed as a result of a disease of its membranes or vessels. Meningitis arising on the basis of various infectious diseases, especially in childhood, can cause atrophy in the cerebellum; arteriosclerosis, especially early arteriosclerosis, by lowering nutrition, can lead to atrophy; syphilis can influence the development of atrophy either by a direct action on the cerebellar vessels or by creating a certain predisposition thanks to which the cerebellum becomes more vulnerable. Trauma can also be the cause of cerebellar atrophy through the mediation of hemorrhage in the membranes. At the autopsy of such cases, the cerebellum is found to be of smaller size, sclerosed, hard to the touch; the changes are unevenly distributed throughout the cerebellum: sometimes the hemispheres suffer more, in other cases the vermis; at the same time, some lobes or parts of lobes suffer more strongly than neighboring ones. The pia mater is thickened, cloudy, and fused with the cerebellar cortex. On section, it can be seen that the superficial convolutions are atrophied more strongly than those lying in the depth. The cerebral membrane, together with vessels penetrating between the laminae of the cerebellar lobules, is strongly thickened and fused with the laminae, which are sometimes strongly destroyed and replaced by fibrous tissue and neuroglial sclerosis. Fibrous strands extend from the membrane into the depth. In processes less intensively expressed, the structure of the cortex, the presence of Purkinje cells (more or less strongly altered), and strong glial proliferation can already be seen in the convolutions. The vessels are strongly altered, and a certain parallelism exists between the intensity of the vascular and meningeal changes and the degree of atrophy and sclerosis of the cerebellar cortex. In the central nuclei of the cerebellum, secondary changes of the projection fibers leading to them are observed, caused by a lesion in the cortex or possibly also by vascular disease; the number of fibers in the nuclei is decreased, the cells are less numerous and of smaller size, and in general the nuclei are reduced in size. If death occurs a long time after the onset of the disease, the cortical lesion affects not only the central nuclei, but also the cerebellar peduncles. Simultaneously with the change in the cerebellum, changes are also observed in other parts of the central nervous system (hydrocephalus). In the acute phase of the disease, the participation of the cerebellum in the process is characterized by a clearly expressed cerebellar syndrome, and then a gradual improvement of symptoms is observed, but complete recovery never occurs: the gait remains unsteady, staggering, the patient walks with legs widely spaced; in the limbs, there is impaired coordination, tremor; speech difficulty, etc. Very frequently there is a lowering of the intellect, which depends on the simultaneous lesion of the brain. The symptoms can be uneven: more strongly expressed on the part of the limbs or on the part of the trunk. Partial improvement of symptoms after the acute onset of cerebellar phenomena during an infectious disease is the main feature of cerebellar atrophies on the basis of meningo-cerebellitis. When the cerebellum is in the stage of atrophy, all therapy is powerless. The second group of primary cerebellar atrophies includes those cases in which there is a lesion of the cerebellar tissue itself, whereas the membranes and vessels are not altered. Among the parenchymatous diseases of the cerebellum, several types are distinguished: 1. Pure atrophy of the cerebellar cortex (atrophie lamellaire Thomas), in which the lesion exclusively affects the cortex: Purkinje cells in some convolutions disappear completely, whereas in neighboring ones they are more or less preserved; the disappeared cells are replaced by a dense network of glial fibers; in the molecular layer, the number of glial elements is increased. The disease is diffuse; both the vermis and the hemispheres are affected; the membranes and vessels are normal. In general, the entire cerebellum is reduced in size sometimes by one-quarter; clinically, the disease is expressed by a disorder of equilibrium during standing and walking, and by tremor. To this form is joined familial cerebellar degeneration (Holmes), characterized by primary and progressive degeneration of the nerve elements of the cerebellar cortex; the efferent system is switched off, whereas the afferent system remains normal; clinically, the process is characterized by a disorder of gait, speech, unsteadiness of movements, tremor of the head and limbs, nystagmus, and absence of pyramidal and sensory disorders. Onset between 33 and 40 years. 2. Atrophia olivo-ponto-cerebellaris of Déjerine, one of the most precisely described forms of atrophy; onset of the disease at the age of 40; the course is slow, gradual; with careful questioning, it is possible to find indications that even at younger ages there was difficulty in walking and in performing certain movements. Anatomically, this form is characterized by: 1) symmetrical atrophy of the cerebellar cortex, more pronounced in the hemispheres; 2) complete atrophy of the gray matter of the pons and complete degeneration of the middle cerebellar peduncles, with good preservation of the brachia conjunctiva; 3) sharply expressed atrophy of the inferior olive, accessory olives, and arcuate nuclei, degeneration of the external arcuate fibers and restiform body. Cortical atrophy consists in the atrophy of all 3 layers of the cortex, as well as the myelin fibers of the convolutions; Purkinje cells are unevenly distributed: in places absent, in places very rare; the dentate nucleus is of smaller size, has fewer bends, but the cells are numerous and normal. The white matter of the cerebellum is greatly reduced in volume. Clinically, a disorder is observed in the movements of the entire trunk, upon transition from a sitting position to a standing position and vice versa; the entire body makes oscillatory, jerky movements upon this. When standing, the patient spreads his legs wide and is unable to maintain balance. When walking, all phenomena increase. Isolated movements of the limbs are comparatively preserved, although slow, trembling, and unsteady. Strength and sensitivity are preserved, speech is scanning. Reflexes are somewhat increased. The development of the disease is slow, but progressive; death usually occurs from an accidental cause. 3. Atrophia olivo-rubro-cerebellaris (described by Lhermitte in 1909), a very rare disease, anatomically characterized by 1) sclerosis and complete demyelination of the inferior olive, as a consequence of which olivo-cerebellar fibers have disappeared in large numbers, the restiform body is partially reduced; 2) global atrophy of the cerebellar cortex, expressed in the disappearance of Purkinje cells and the majority of grain cells with their replacement by glial elements; 3) atrophy of the dentate nucleus and almost complete disappearance of the brachium conjunctivum, as well as changes in the red nucleus. Clinically, the disease proceeds in the form of a clearly expressed cerebellar syndrome. 4. Atrophia olivo-cerebellaris (described by Holmes) is very close to the previous form.
It is anatomically characterized by: 1) symmetrical and generalized atrophy of the cerebellar cortex with the disappearance of Purkinje cells and cells in the molecular layer, their replacement by glial tissue, and atrophy and sclerosis of the white matter of the cerebellum; 2) alteration of the inferior olives and accessory olives with degeneration of the cerebello-olivary fibers. The nuclei remain normal. The clinical picture resembles that of multiple sclerosis. 5. Senile atrophy of the cerebellar cortex is characterized by glial thickening in the molecular layer and glial proliferation in the Purkinje cell layer and around the blood vessels. Such changes do not occur throughout the entire extent of the cortex, but are partial and selective with respect to certain convolutions. 6. Cerebellar atrophy, or primary atrophy of the central nucleus, is characterized by: 1) small size of the cerebellum with preservation of the cortex and white matter, 2) atrophy of the dentate nucleus with a decrease in the number of its folds and cell atrophy, 3) significant atrophy of the superior cerebellar peduncle, 4) reduction of the red nuclei and Forel's fields of the thalamus, 5) preservation of the inferior olive. 7. Hereditary cerebellar atrophy, or hereditary cerebellar ataxia (Marie's and Friedreich's disease) - see Ataxia. - Etiology. As can be seen from the above, some cerebellar atrophies are acquired and therefore can develop at any age - in the fetus, in childhood, adolescence, and in adults. Their development is associated with infection or trauma. Depending on the age at which the cerebellum was affected, there are various developmental anomalies or atrophies. Another group of atrophies belongs to hereditary and specifically dominant diseases (hereditary cerebellar ataxia) with a slow and progressive course. A separate description is given to atrophies which, in their slow and progressive course and anatomical changes, resemble the previous group, whereas indications of heredity and familial occurrence are absent in them; sometimes such atrophy is detected in individuals who have reached adulthood (40-50 years), but it can also be observed in childhood; the late appearance of symptoms is explained by the broad compensatory function of the opposite hemisphere (in unilateral lesions) or other parts of the brain; in children, such compensation by neighboring formations occurs better. The question of the etiological factor remains open for now. It is possible that these sporadic progressive atrophies are only sporadic cases of hereditary forms. Thus, olivopontocerebellar atrophy was originally described as a sporadic disease, but subsequently familial cases of this disease were described. Diagnosis. The symptomatology observed in cerebellar atrophies resembles the clinical picture that develops in other diseases of the cerebellum - tumors and abscesses. Differential diagnosis is carried out on the basis of the presence of general cerebral symptoms in tumors, elevated temperature, and changes in the blood composition in abscesses; it is more difficult to differentiate these atrophies from multiple sclerosis and various forms of atrophy from each other; symptoms are more intensely expressed when the central nuclei are involved. - The course of the disease varies depending on the etiological factor: atrophies that developed on the basis of meningitis or encephalitis may gradually improve, but sometimes after improvement, deterioration is noted again for some time and then improvement again, so that an intermittent course is obtained. In atrophies of another etiology (hereditary abiotrophies), the disease slowly and progressively worsens. - Prognosis for life is favorable, for recovery hopeless. - Therapy: symptomatic treatment. - Prophylaxis: see Infantile paralysis. Wounds of the cerebellum are very rare; during the last war, according to Marie and Chatelin, out of 5,000 skull wounds, there was only one wound of the cerebellum, and according to Chiray, 2 out of 4,100; more correctly, such patients rarely come under clinical investigation, which is explained by the position of the cerebellum adjacent to formations of vital importance (medulla oblongata), which almost inevitably are affected by a cerebellar wound and cause a fatal outcome, if not directly following the wound, then within a very short time, as a result of which only very mild wounds came under observation. The cerebellum can be damaged either directly by the wounding object or by fragments of the skull that fractured upon a tangential wound. Often, the cerebellar tissue in the vicinity of the wound also suffers as a result of hemorrhage, edema, malnutrition, or finally suppuration; part of the tissue under the influence of adverse factors can become necrotic and be eliminated from the wound. Clinically, upon wounding the cerebellum, the most typical picture of the cerebellar syndrome is observed, which varies depending on the localization of the wound (see above). Gradually, the cerebellar symptoms subside somewhat (due to the disappearance of edema and resorption of the hemorrhage) and only those depending on the destruction of the cerebellum remain; the exceptions are cases where wound contamination and abscess formation occur, then the picture changes and general cerebral symptoms join the cerebellar symptoms. - Diagnosis does not present great difficulty in the presence of a wound. - Prognosis remains in doubt for a long time, and only after a few months can one speak of a favorable outcome. - Therapy: depending on the possibility of surgical intervention (see below). - In addition to wounds, other traumatic factors can affect the cerebellum - a blow, a fall on the back of the head; even if they are not accompanied by skull fractures, they can still produce greater or lesser hemorrhages in the cerebellum, commotion of the cerebellum. - The clinical picture of the cerebellar syndrome depends on the intensity and localization of the lesion. In favorable cases, gradual improvement is associated with the resorption of the hemorrhage; complete restoration of all functions can be expected. - Diagnosis presents no difficulties. - Therapy: rest, ice to the occipital region. Circulatory disorders in the cerebellum are observed in various forms. In anemia, hyperemia, arteriosclerosis affecting the entire central nervous system diffusely, the cerebellum suffers on a par with its other parts, and therefore its symptoms are included as part of the general picture of central nervous system damage. Hemorrhage into the cerebellum is a rather rare disease. The clinical picture is not particularly clear, since it is difficult to separate which symptoms are due to cerebellar damage and which depend on damage to surrounding formations. Cerebellar hemorrhages are much rarer than cerebral hemorrhages, their frequency being 1:12 (Rochoux), 1:30 (Hillairet), and they depend on the same causes as hemorrhages into the brain - arteriosclerosis, syphilis and other infections, intoxications, trauma (especially in newborns) (see Cerebral apoplexy). The highest frequency of hemorrhages is observed at the age of 50 to 80 years; they occur as a result of the rupture of miliary aneurysms. According to size, large and small hemorrhages are distinguished. Hemorrhages from the artery of the dentate nucleus can be so significant that they involve not only the corresponding hemisphere, but the vermis and the hemisphere on the opposite side, as well as the fourth ventricle. Small hemorrhages are found in the vermis and in the hemispheres - in the white matter, in the central nuclei, and in the cortex. Multiple foci are not uncommon. Among the cerebellar peduncles, hemorrhages in the middle one are generally observed more often. The clinical picture varies greatly depending on the size of the hemorrhage, which is often preceded by prodromal symptoms in various combinations: headaches in the occipital region, vomiting, pulse irregularity, dizziness, transient general weakness. The disease can begin suddenly, in a stroke-like manner; in these cases, the patient mostly dies immediately or after a short time. Less extensive hemorrhages are less violent - prodromal symptoms intensify, especially vomiting, involuntary movements, balance disorders, general malaise appear, then loss of consciousness; in severe cases, respiratory and pulse disorders, nystagmus, conjugate movements of the head and eyes, tonic and clonic seizures are observed; this complex of symptoms indicates the rupture of hemorrhage into the fourth ventricle and the medulla oblongata; in more favorable cases, consciousness is restored, and then a number of cerebellar symptoms appear, which either gradually improve or remain forever, gradually decreasing in intensity. Cerebellar symptoms are mostly observed on one side. Improvement progresses and sometimes all symptoms seem to disappear completely - only a very subtle examination allows one to detect one or another symptom; some of the above-described symptoms do not belong to the cerebellum, but indicate the involvement of the medulla oblongata, meninges, and the fourth ventricle.
Differential diagnosis must be made 1) with cerebral hemorrhages; in the latter, paralyses, pyramidal symptoms, and pathological reflexes are observed; 2) with meningeal hemorrhages accompanied by rigidity of the neck and extremities, and convulsions; 3) with hemorrhages into the brain stem, producing alternating syndromes (see); and 4) with various processes within the cerebellum itself. Prognosis depends on the intensity and localization of the hemorrhage: almost instantaneous death after severe hemorrhages or complete recovery after small hemorrhages, with various outcomes of the disease between these two extremes. Treatment and prophylaxis—see Cerebral apoplexy. Softening of the cerebellum is observed even more rarely than hemorrhage due to the fact that cerebellar arteries branch off from the basilar artery at a wide angle, which prevents emboli from entering them; softening on the basis of thrombosis due to arteritis (arteriosclerosis, syphilis) is also very rare due to anastomoses between the arteries. Softening can be observed in all parts of the cerebellum, more often in the cortex than in the white matter or nuclei; foci can be single or multiple. In large softenings of long standing, deformation of the cerebellum is observed; cyst formation is possible at the site of softening [see separate table, figures 2 and 4]. At autopsy of a cerebellum with fresh thrombosis, it can be noted that the softened tissue differs sharply from healthy tissue by its pale color and softness; the pia mater is infiltrated, edematous, and appears elevated above the underlying tissues; later, the softened tissue assumes a yellowish color and sinks; foci of hemorrhage are very frequently seen at the border; in softening of the cortex, only a neuroglial framework remains of the nervous tissue. Symptoms vary depending on the localization of the foci and their extent. The onset of the disease is preceded by a more or less prolonged prodromal period (up to several days), but a sudden onset is also observed, with the patient immediately falling into a comatose state. The prodromal period is characterized by headaches in the occipital region, dizziness, and involuntary head movements. Clinically, softenings present a typical cerebellar syndrome, the intensity and character of which vary depending on the localization of the focus; sometimes mental disorders and conjugated deviation of the eyes and head toward the affected side are observed. Cases of rather extensive softenings of the cerebellar hemispheres without involvement of the vermis have been described, proceeding without any cerebellar symptoms. With an apoplectic onset, the outcome is most often fatal—the patient dies in the first days of the disease, being in a comatose state before death—loss of reflexes, sphincter paralysis, convulsive movements on the affected side. With small softenings, symptoms gradually disappear; with involvement of the subcortical nuclei, improvement is very slow and some cerebellar symptoms always remain. In acute cases with a sudden onset, it is difficult to decide whether we are dealing with a hemorrhage or softening of the cerebellum, but the further course of the disease sometimes settles the question. Softening may also simulate multiple sclerosis or chorea, and again only the course can decide.
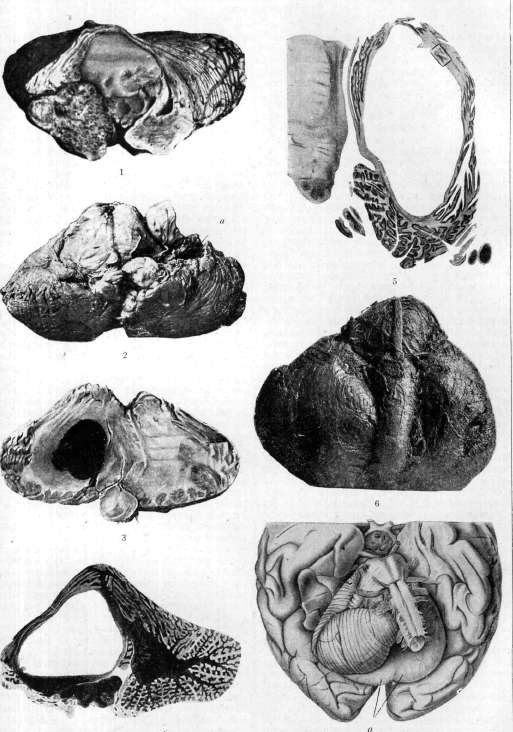
Figure 1. Tumor of the cerebellopontine angle that has grown into the cerebellum and undergone colloid degeneration in it. Figure 2. Cyst (a) of the left cerebellar hemisphere formed as a result of softening. Figure 3. Hemorrhage into the white matter of the right cerebellar hemisphere. Figure 4. Cyst of the right cerebellar hemisphere. Figure 5. Cystically degenerated cerebellar tumor. Figure 6. Atrophy of the left cerebellar hemisphere. Figure 7. Cyst (a) of the left cerebellar hemisphere.
To the article Cerebellum. Question. - T r e a t m e n t. In patients at a young age, antisyphilitic treatment must be carried out; at a more mature age, such treatment should be carried out with caution. There is no specific treatment for softening. Abscesses of the cerebellum. Among purulent diseases of the brain in general, abscesses of the cerebellum occupy the second place in terms of frequency (brain abscesses occupy the first place). They are observed: 1) in head injuries in the occipital region with damage to the bones of the skull and with the penetration of the wounding object or bone fragments inside the skull; they are significantly less common in simple contusion of the occipital region without violation of the integrity of the integuments. 2) In diseases of the bones of the skull of the same region (osteomyelitis of various origins). 3) In diseases of the middle ear (otitis media), an abscess is a relatively rare complication; according to French statistics, one case of cerebellar abscess is encountered per 1,100 cases of purulent ear disease; in chronic otitis, an abscess is observed more often (80-88% of all cases of cerebellar abscesses of ear origin) than in acute ones (10-12%) (Neumann, Heiman); abscesses are rare up to 10 years of age and after 30 years; the period of development of the abscess after the onset of ear disease is very indefinite - from several days to several years; some infectious disease, trauma can activate the process in the ear and cause the formation of an abscess in the cerebellum. Usually, the abscess arises on the side where the ear disease is present. 4) Cerebellar abscess of metastatic origin - in septicaemias, pyemias, endocarditis, in broncho-, pleuropneumonia, in certain infectious diseases. - P a t h o l o g i c a l a n a t o m y. Upon opening the skull, certain changes can be noted: the dura mater is hyperemic, edematous, strongly tense in the posterior sections due to the bulging of the underlying parts; upon opening the dura mater, the altered cerebellum can be seen; significant asymmetry is observed in it - since the abscess is localized mostly in the white matter of the cerebellar hemisphere, the corresponding hemisphere increases in size not only due to the presence of pus, but also due to edema; the vermis deviates to the healthy side; the contours of the medulla oblongata and the pons Varolii are also strongly altered. The convolutions located above the abscess are strongly stretched, the sulci are smoothed out; when the abscess is located directly beneath the cortex, the color of the cerebellar cortex also changes, taking on a greenish-yellowish hue; the size of the abscess varies greatly - from a small hazelnut to the complete replacement of the cerebellar hemisphere, and the cerebellum itself can be reduced to a very thin membrane in which the elements of the cerebellar cortex can be found with difficulty; in the majority of cases, the abscess is single, rarely there are two or more; simultaneous development of an abscess in the brain is also observed. Sometimes one can note the presence of a fistula that leads from the abscess to the surface of the cerebellum, and then in this place there are adhesions of the cerebellum with the dura mater. The cortex can be covered with a membrane, more or less infiltrated with pus. Pus does not always have the same appearance: it is thick or more liquid, yellowish or greenish, sometimes with a very strong repulsive odor; among microbes in the pus, staphylococci, streptococci, diplococci are found, but the pus can also be sterile. Two anatomical forms of abscess are described - diffuse abscess and encysted abscess. In the first case, the abscess does not have its own membrane, but infiltrates the nerve tissue; in the second case, it has a very dense membrane giving it the appearance of a purulent cyst. The nerve tissue at the site of the cyst is destroyed, around the cyst it is edematous, softened; cells adjacent to the abscess are also strongly altered, up to their complete disintegration; neuroglia is strongly proliferated. - S y m p t o m a t o l o g y. Despite the almost constant localization of abscesses in the cerebellar hemisphere, nevertheless, in addition to the hemisphere syndrome, the syndrome of the vermis is also observed, which suffers as a result of edema, compression, displacement; besides, in an abscess of ear origin, the vestibular system also suffers, so that in general a very complex syndrome is obtained. If the abscess develops as a complication of otitis media, general cerebral phenomena usually join the labyrinth symptoms: headaches in the occipital region, vomiting, dizziness, elevated temperature, general emaciation, fatigue, lethargy, nystagmus; later on, choked disc and cerebellar phenomena join, which are sometimes difficult to identify due to the severe general condition of the patient. When the general symptoms subside somewhat, the symptoms of cerebellar disease appear, changing depending on the localization of the process and the greater involvement of one or another part of the cerebellum (see above). To these are added nuchal rigidity, pyramidal symptoms, and other symptoms depending on the compression of the medulla oblongata or pons Varolii; all these symptoms can be observed on the other side, whereas cerebellar symptoms are observed on the side of the lesion. Examination of the cerebrospinal fluid may yield nothing pathological, sometimes hyperalbuminosis, hyperglycosis are noted; in superficial abscesses, cellular elements are found in it (polynuclear leucocytosis, lymphocytosis, etc.); the fluid usually flows out under pressure (see Cerebrospinal fluid). In later stages of the disease, mental phenomena are observed - confusion, stupor, etc. The development of symptoms is gradual or sudden, depending on the severity of the infection. - D i a g n o s i s of an abscess of traumatic origin does not present great difficulties - trauma in the anamnesis, severe general condition, cerebellar symptoms; the diagnosis of an abscess of ear origin is usually facilitated by the presence of otitis media, to which cerebellar symptoms are added; one also has to differentiate with sinus thrombosis, with meningitis (see). - P r o p h y l a c t i s consists in the careful treatment of skull wounds, ear diseases, and other purulent inflammatory processes in the body. - P r o g n o s i s is very serious. - T r e a t m e n t upon recognition of a cerebellar abscess is solely surgical (see below). With timely intervention, recovery is possible; the statistics of results are contradictory: according to Bourgeois, recovery in 21 cases out of 38; according to Wildenberg, in 32 out of 63; according to Neumann, in 40 cases out of 196. - Inflammatory processes in the cerebellum are not observed in isolation, but the cerebellum is affected together with other parts of the central nervous system, but sometimes the cerebellum is affected more strongly than other parts, and then one speaks of encephalitis with localization in the cerebellum (see Encephalitis). Tumors of the cerebellum [see separate table III (art. 551-552), fig. 1 and 5] are one of the frequent diseases of this organ; they are especially common in children, in whom, among all parts of the central nervous system, tumors in the cerebellum occupy the first place in terms of localization. (Statistics and structure of tumors - see Brain.) In their structure and origin, cerebellar tumors do not differ from tumors of the cerebral hemispheres. They are divided into true tumors and false tumors (pseudotumor). The former can be primary and secondary (metastases). Primary tumors originate in the cerebellum itself or in its surrounding membranes; these include: 1) gliomas, the size of which can vary from the size of a small pea to a chicken egg; they develop either in the tissue of the cerebellum itself or from the ependyma of the fourth ventricle, and then grow into the cerebellum. Sometimes myelin fibers and nerve cells (neurogliomas) are found in the glial elements of the tumor. 2) Sarcomas develop either from the dura mater, or from the periosteum, or from the pia mater and vessel adventitia, and reach very large sizes; they begin at the periphery of the cerebellum and then grow into it; they are encountered quite frequently (13 cases of sarcoma out of 86 cases of cerebellar tumor, according to Starr), especially in children (10 cases out of 35). Psammomas, endotheliomas, lipomas, myxomas, cholesteatomas, angiomas are also encountered. - Secondary tumors are also not uncommon (in 13 cases out of 63); they can be single or multiple; their primary focus is various: lungs, stomach, kidney, adrenal gland, etc. Pseudotumors include tubercles, gummas, aneurysms, encapsulated meningitis, and serous cysts of the soft membranes. Tubercles are encountered in the cerebellum more often than in the cerebral hemispheres; their size is very diverse, they can be single or multiple, with localization in the cortex and in the white subcortical matter; they are usually well demarcated from the surrounding brain substance; initially they have a grayish-pink color, later yellowish as a result of caseous decay. - Gummas are rarer, and can be located either in the cerebellum or in the membranes, from where they already penetrate into the cerebellar cortex. - Aneurysms of the cerebellar arteries are rare. S y m p t o m a t o l o g y. The symptoms observed in cerebellar tumors can be divided into three groups: 1) general cerebral symptoms due to increased intracranial pressure; 2) cerebellar or focal symptoms, and 3) compression symptoms. General cerebral symptoms usually appear first, which are not characteristic only of cerebellar tumors, but are observed in all tumors within the cranial cavity, but in cerebellar tumors they usually appear more intensely and earlier, which is explained by the position of the cerebellum in the posterior cranial fossa - a very narrow space tightly covered from above by the tentorium cerebelli.
The slightest change in the size of the cerebellum can compress the great vein of Galen and the sinuses passing near it (straight sinus, transverse sinus), which causes the early appearance of general cerebral symptoms and their rapid development. Among the general cerebral symptoms are: headaches in the occipital region, spontaneous or under the influence of external irritations (percussion, movement); they radiate across the entire posterior surface of the head and into the neck muscles; they can be constant or appear in the form of attacks accompanied by dizziness and vomiting; vomiting appears generally quite early and is very frequent. Choked disc in tumors of the cerebellum appears almost always early, increases very rapidly, and leads to blindness. Dizziness exists in all cerebellar tumors, even in the absence of other cerebellar symptoms, and thus is a symptom dependent on increased intracranial pressure rather than a focal symptom; dizziness can be observed both upon change of position and in all positions, depends on edema of the inner ear and compression of the labyrinth; it is often accompanied by vasomotor reactions. During a lumbar puncture, due to increased intracranial pressure, fluid flows out under very high pressure (30-45 cm, sometimes up to 100 cm in a lying position instead of the normal 15 cm). In general, when a tumor in the posterior cranial fossa is suspected, puncture is contraindicated, since a drop in pressure may cause a displacement of the vital formations located in the posterior cranial fossa (medulla oblongata, pons varolii), which can lead to sudden death. In young children, increased intracranial pressure can cause separation of the sutures and enlargement of the fontanelles. - Cerebellar symptoms at the beginning of the disease can be very unnoticeable and lost among the general cerebral symptoms caused by the tumor, which, once they appear, gradually increase; the nature of the cerebellar symptoms changes depending on localization: in disease of the vermis, a disorder of gait and equilibrium appears, whereas in a tumor of the hemispheres, a disorder of movement coordination (see above cerebellar syndromes); developing gradually, the tumor passes from the vermis to the hemispheres or vice versa, due to which the purity of the syndromes is lost - symptoms of the disease of the vermis join the symptoms of the hemispheres and vice versa. Only by a very rigorous analysis is it possible to establish which symptoms appeared first. - Symptoms appearing as a result of compression are very numerous due to the large number of surrounding formations that can be compressed; the majority of cranial nerves are affected, with the VI, VII, and VIII cranial nerves suffering first and foremost as being in the immediate vicinity of the cerebellum; their lesion causes paralysis or insufficiency of the external rectus muscle of the eye, paralysis orparesis of the facial mimic muscles, decreased hearing or, conversely, upon irritation of the eighth cranial nerve, tinnitus in the ears; the fourth pair and the fifth pair (disorder of sensitivity on the face, especially on the mucous membranes) may also be involved, as well as the tenth pair (change in pulse, vomiting); the remaining nerves also suffer. Compressions of the pyramidal tracts are also observed - paralysis, paresis with pathological reflexes on the opposite side or on the same side; sometimes the combination of observed symptoms takes the character of alternating syndromes. - The onset of the disease is usually slow and imperceptible, with general cerebral symptoms, to which cerebellar symptoms gradually join; their increase may be gradual or in the form of attacks (tumors of vascular origin); in development, very short-term remissions may also be observed, after which progressive development continues. The duration of the disease is several months (as an exception, several weeks) or the disease drags on for a year or more. Death is mostly sudden, from hemorrhage into the tumor, but may also depend on compression or on gradually increasing cachexia. - The diagnosis is made on the basis of the presence of cerebellar symptoms and symptoms of increased intracranial pressure. With the existence of only the latter and in the absence of focal symptoms, the diagnosis is made on the basis of the localization of headaches, the presence of severe dizziness, frequent vomiting, early appearance and rapid development of choked disc. If cerebellar symptoms join these symptoms, it is necessary to differentiate with a cerebellar abscess. The presence of elevated temperature, polynucleosis in the blood, and the corresponding etiological moment (otitis media, skull injury) speak in favor of an abscess. Extracerebellar tumor (cerebellopontine angle) is characterized by an onset from auditory phenomena, the involvement of a large number of cranial nerves, and significantly less pronounced cerebellar symptoms. Frontal lobe tumors can be accompanied by phenomena of cerebellar ataxia, but the existence of other focal symptoms makes it possible to make a correct diagnosis (see Frontal lobe). The establishment of the localization of the tumor in the cerebellum itself is based on physiological data (see above physiology and symptomatology). The nature of the tumor in some cases can be suspected (e.g., in gumma, tuberculosis, metastatic tumors) due to the presence of symptoms from other organs and the results of certain laboratory studies (Wassermann reaction, chemical change in cerebrospinal fluid, tuberculin reaction, etc.), while in all other cases its nature is concluded on the basis of the course, intensity of symptoms, etc. - Treatment is symptomatic; lumbar puncture can improve the condition for a short time - reduce headache, dizziness, cerebellar symptoms; but since it presents a danger of sudden death, it is recommended to use it not for therapeutic purposes, but only for diagnosis. Radical treatment is surgical (see below). Cerebellar cysts in their symptomatology approach tumors, from which they differ in their origin and course. Cerebellar cysts can be a consequence of developmental anomalies and originate from normal brain cavities and from diverticula of the ventricles - these cysts are called primary by some authors. Others are formed either as a result of tissue softening, resorption of hemorrhages, or are the result of atrophic or inflammatory processes (e.g., encysted meningitis - meningite enkystée, arising on the basis of chronic inflammation of the membranes; its favorite site is the cerebellopontine angle; its origin is linked by some authors to tuberculosis, syphilis, ear disease - see Meningitis). Of greatest interest are the so-called primary cysts as a quite independent and definite form. There is no firmly established view on the origin of these cysts; they are explained by developmental anomalies: 1) during the development of the cerebellum, a temporary protrusion of the fourth ventricle and the formation of the His-Bolk cleft occurs; the detachment of this cleft leads to the formation of a preformed cavity, which, stretching by the accumulating fluid, turns into a cyst (Henschen); 2) the ingrowth in the embryonic period of life into the cerebellar substance of parts of the pia mater, which is then detached and forms the cavity from which subsequently, due to the accumulation of fluid in it, a cyst is formed (Verzilov); 3) a congenital disease of the ependyma of the fourth ventricle and the surrounding neuroglia - congenital ependymitis with sclerosis of the neuroglia; similar changes explain hydrocephalus and syringomyelia, uniting these three diseases into one nosological group (Muratov); thus, a cerebellar cyst from the point of view of this doctrine is nothing other than a syringomyelic cavity in the cerebellum. The cavity of the cyst may have a connection with the fourth ventricle or be independent; sometimes neoplasms are simultaneously observed in the cerebellum. The size of the cyst is very different; it can occupy the entire cerebellar hemisphere, due to which it is stretched in a sac-like manner [see separate table (p. 551-552), figure 7]; its configuration is thereby changed, convolutions and sulci are smoothed out, compressed; sometimes the cyst occupies only a part of the cerebellar substance, but small cysts can depart from the main cavity deep into the substance; cysts are also observed in the hemispheres and in the vermis. The cavity of the cyst is lined with a smooth shiny membrane; the contents of the cyst can be liquid or semi-liquid (colloid); the amount of fluid can reach 30 cm3; the specific gravity of the fluid is about 1.006, it contains small amounts of protein. With very large cysts, displacement of the medulla oblongata and pons varolii is noted. The walls of the cerebellar cyst consist of strongly proliferated neuroglia; glial fibers intertwine in all directions; spider-like Deiters cells are visible between the fibers; on the inner wall in places there are single cuboidal cells, apparently ependymal, poorly preserving their structure; a solid continuous ependymal covering is rarely observed; usually, hyperplasia of the ependymal covering is simultaneously noted in the ventricles, which protrudes in the form of massive projections into the cavity of the ventricles and into the underlying white matter. Sometimes near large cavities, small independent closed cavities or islands of ependymal cells are found. Very often, cavities in the spinal cord having the same structure as the cavity in the cerebellum are simultaneously found.
Around the cyst, the white matter is softened and loosened, with a rarefaction of nerve fibers observed; the cortex adjacent to the cyst is thinned, and Purkinje cells are reduced in number. The pia mater presents no special changes. Thus, cerebellar cysts may be a congenital condition that remains in a latent state for a long time; they are discovered at a young age—between 20 and 30 years. Out of 37 cases of cerebellar cysts, 19 cases fell into this age group; up to 10 years there were 4 cases; from 10 to 19 years—7 cases; between 30 and 50 years—9 cases; and older than 50 years—3 cases (Verzilov). The disease begins gradually with general cerebral symptoms, which are soon joined by cerebellar symptoms depending on localization (see above). Sometimes cerebellar symptoms onset simultaneously with general cerebral symptoms, and sometimes they precede them. Later, symptoms of compression of surrounding formations appear. Short-term remissions may be observed in the course of the disease. Death results from the same causes as in tumors; the duration of the disease is from 2 months to 2-3 years. It is almost impossible to differentiate cerebellar cysts from cerebellar tumors; some authors admit the possibility of diagnosis based on the course of the disease with fluctuations and remissions. Neisser-Pollack trial puncture (Neisser, Pollack) was proposed as an auxiliary method for differential diagnosis (see below). Therapy consists solely of surgical intervention. Parasites of the cerebellum are a very rare disease; among parasites, one must note cysticercus (Cysticercus cellulosae) and echinococcus (Echinococcus). Cysticercus has the appearance of a vesicle the size of a millet grain, but can reach the size of a walnut; in rare cases, there is only one such vesicle, but more often there are very many of them; sometimes the vesicles do not sit separately one from another, but developing from the main one, remain connected with it (Cysticercus racemosus). Cysticercus can develop anywhere in the cerebellum—in the cortex, in the white matter, in the peduncles, in the walls of blood vessels, as well as in the leptomeninges, mainly at the base of the cerebellum near the pons varolii. Echinococcus has the appearance of a vesicle or tumor ranging in size from a pea to a man's1 fist; it can be isolated, multiple, and multilocular; it is located either on the surface or deep within the brain tissue. The development of the cysticercus and echinococcus vesicle is accompanied by a reaction from the surrounding tissue—local encephalitis, softenings (upon blockage of a nearby blood vessel), small hemorrhages; with localization in the membranes—fibrous meningitis; in the case of echinococcus, this reaction is more pronounced. The clinical picture is not sufficiently well-differentiated due to the rarity of the disease. When the parasites reach large sizes, they produce the clinical picture of a tumor or cyst of the cerebellum (see above), while sometimes during the patient's life they do not manifest themselves in any way and are found only at autopsy; cases with psychiatric phenomena have been described. Diagnosis is very difficult, sometimes facilitated by the presence of eosinophilia. The duration of the disease is evaluated differently by various authors, from 3 to 20 years. Therapy is exclusively surgical. Prophylaxis is of great importance for preventing infection with these parasites (for details, see the respective parasites). Syphilis and tuberculosis, besides infectious granulomas, can also cause diffuse diseases, but then the cerebellum suffers on a par with other parts of the nervous system (see Nervous system, pathology). Lesions in general infectious diseases: in very many infectious diseases at the moment of highest development of the disease or in the convalescent period, disorders on the part of the nervous system are observed, and cerebellar symptoms occupy not the last place. Among these diseases, one must note malaria, typhus (relapsing, epidemic, and typhoid), pneumonia, diphtheria, rheumatism, etc. Malaria attacks in severe cases are accompanied by nervous symptoms, which can give the picture of a cerebellar syndrome; gradually the symptoms subside, to resume with a new attack; sometimes the syndrome is not particularly typical and is expressed by unsteadiness in walking, tremor in the hands, speech disorder. In mild cases, the symptoms disappear with the use of quinine, while in more severe cases they are persistent and do not respond to treatment. In epidemic typhus, complications on the part of the cerebellum have also been observed; after the disappearance of general cerebral symptoms, symptoms of localization of the infection in the cerebellum come to the stage; after recovery from the primary disease, the symptoms begin to improve very slowly but progressively; in mild cases, complete recovery is possible, while in more severe cases1 a number of cerebellar symptoms remain for life—unsteadiness in walking, in performing various actions, speech difficulty, nystagmus. In relapsing typhus, cerebellar symptoms may increase after each attack, and then, as the disease improves, sometimes gradually disappear completely, while sometimes some of them remain, indicating a disease of the cerebellum. The same is observed in other infectious diseases. Pure cerebellar syndromes, which are observed quite rarely, are mostly accompanied by symptoms indicating the involvement of other divisions of the nervous system in the process (for details—see Acute ataxia and corresponding infectious diseases). In intoxications, both acute and chronic, the central nervous system is affected, in particular the cerebellum. The external manifestation of acute alcohol poisoning somewhat resembles the picture of a cerebellar disease—unsteady, staggering gait, uncertain, uncoordinated movements, tremor in the extremities, in the tongue, speech and writing disorder; besides these symptoms, others are observed indicating that besides the cerebellum, other divisions of the nervous system are also affected; in chronic alcoholism, more or less persistent changes in the cells of the cerebellar cortex are noted. Cerebellar symptoms are also observed in uremia (where, besides the moment of intoxication, edema and vascular changes play a role), as well as in other intoxications. Thus, cerebellar syndromes were described in castor bean seed poisoning. Involvement of the cerebellum in diseases of the central nervous system: involvement of the cerebellum is also noted in many diseases of the central nervous system. In multiple sclerosis, plaques are almost always found either in the cerebellum or in its peduncles, which is why this disease is so rich in cerebellar symptoms and some of them are even characteristic of the classical form of multiple sclerosis. In Sydenham's and Huntington's chorea, along with other symptoms, some cerebellar symptoms are observed, which indicates the involvement of the cerebellum in the process as well. At autopsy in Sydenham's chorea, insignificant changes in the cerebellar peduncles or diffuse hyperemia throughout the cerebellum were found; autopsies in this disease are very rare. In Huntington's chorea, small foci of softening, a decrease in the size of Purkinje cells, their deeper position in the granular layer, and a decrease in the size of the cerebellum itself were observed in the cerebellar cortex. In tabes dorsalis, changes were observed mainly in the cortex, in the molecular layer, a decrease in the number of myelin fibers and an increase in glial fibers; in the dentate nucleus—wrinkling, cell deformation, and the presence of pigment. These changes are not considered specific for tabes. In progressive paralysis, various changes were found in the cerebellum: a decrease in the number of Purkinje cells, their atrophy, changes in their neurofibrillar apparatus, atrophy of nerve fibers, reduction of the granular layer, proliferation of glial elements. In addition, as in other parts of the nervous system, changes in blood vessels and meninges were noted; by these changes, some authors wish to explain such symptoms as tremor, speech difficulty, etc. Developmental anomalies of the cerebellum (agenesis, hypoplasia, atrophy) and the brain are very often associated with idiocy. Cerebellar changes were noted in amaurotic idiocy; they appear quite early and are characterized by the disappearance of the granular layer, small cells of the molecular layer, basket cells, mossy and climbing fibers; Purkinje cells remain more or less normal, but their processes change, giving atypical collaterals; due to strong neuroglial proliferation, the entire cerebellum acquires a denser consistency; clinically, these symptoms were expressed by a cerebellar gait and balance disorder. In dementia praecox, very markedly expressed hemiatrophy of the cerebellum or diffuse atrophy of both hemispheres, a decrease in the number and size of Purkinje cells, as well as cells of the granular layer, were found; clinically, besides catatonia, balance disorder, tremor, adiadochokinesia, asynergia, speech disorder, etc., were observed. In diseases based on thyroid gland insufficiency (myxedema), cerebellar symptoms are very often observed in various combinations, indicating that the endocrine disorder of the thyroid gland has affected the cerebellum; improvement from organotherapy confirms this. At autopsy of myxedematous patients, atrophy of the cerebellar cortex and a gelatinous appearance of the cortex of the vermis are found. There are no such professional neurotoxins that would affect exclusively only the cerebellum. Usually, the entire central nervous system suffers, and cerebellar symptoms enter as separate components into the general picture of poisoning of the nervous system.
Sometimes, in certain occupational poisonings (mercury, lead), cerebellar symptoms may predominate, and they are distinguished as the "cerebellar form" of a particular poisoning.
E. Kononova. VI. Surgery of the cerebellum. Surgical intervention on the cerebellum takes place in cases of trauma, certain forms of inflammatory processes (mainly abscesses), and finally in cases of tumors in the broad sense of this word (cysts, parasites, neoplasms). To this, one must also add surgical intervention in the region of the cerebellum for internal hydrocephalus, as well as the dissection and removal of hemispheres in cases of acoustic nerve tumors. For hydrocephalus, two types of surgical intervention are used. In cases of hydrocephalus of the hydroceph. aresorptivus and hydroceph. hypersecretorius type, an opening of the cisterna cerebello-medullaris cavity is performed through an incision of the membrana atlanto-occipitalis posterior (Anton-Schmieden operation). The edges of the opened wall of the cistern are sutured to the occipital muscles, or a more or less wide rhomboid opening is made in the membrane, and thus the possibility is created for cerebrospinal fluid to seep into the intermuscular spaces of the cervical musculature. This operation is not complex. A longitudinal incision (10-12 cm long) is made along the midline of the neck, starting slightly below the protuberantia occipitalis to the spinous process of CII-III. The muscles along the entire length of the incision are separated from the underlying bony structures: above from the squama of the occipital bone, below from the arches of the cervical vertebrae. Thus, the posterior edge of the foramen occipitale magnum, the arch of the atlas, and the membrana atlanto-occipitalis stretched between them are exposed, in which the opening is made. Bleeding during this is very insignificant. From this approach to the cisterna cerebello-medullaris, it is also possible to open the cavity of the IV ventricle, which must be done in cases of closed hydrocephalus (hydroceph. internus) and in particular when the hydrocephalus is caused by the closure of the foramen Magendii and both foramina Luschka. In such cases, the distended IV ventricle protrudes into the cavity of the cistern and is easy to open. However, this cannot always be done confidently, and sometimes it is necessary to proceed to the exposure of the hemispheres and the vermis, with resection of the occipital bone. The hemispheres are separated, the vermis is lifted, and the protruding wall of the distended IV ventricle is exposed, which is then opened. In isolated cases, the opening of the cavity was performed by dissecting the vermis. - The second group of cerebellar diseases subject to surgical intervention is traumatic injuries and their complications (mainly cerebellar abscesses). The third group of cerebellar diseases is abscesses, which occur either as a result of trauma to the region of the posterior cranial fossa or are of aural origin. - Treatment consists of emptying the abscess cavity, by widely opening it with subsequent drainage—with gauze, rubber, or glass (according to Witzel) or by the Lemaitre method—without wide opening, by draining the abscess cavity with gradual expansion of the drainage entry, through the use of drains of a larger diameter or by repeated punctures (Spasokukotsky). The outcomes of surgical treatment of cerebellar abscesses, as well as brain abscesses in general, are gradually but progressively improving; in general, recovery is observed in 65-70% (Delvaux, Razumovsky); for cerebellar abscesses of aural origin, the figures are less favorable—from 10.45% (Nussmann, 1920) to 52.8% (Körner). The fourth group of cerebellar diseases requiring surgical intervention consists of cerebellar tumors. Surgical intervention for diseases of the brain regions located in the area of the posterior cranial fossa (subtentorially) is divided into operations: 1) for diseases of the cerebellum itself—cerebellar diseases, 2) for diseases of extracerebellar formations lying in the region of the posterior cranial fossa; this includes a) tumors of the n. acusticus and b) diseases of the meninges in the form of tumors or meningitis circumscripta, of the bones, such as cholesteatomas, further aneurysms, hematomas, parasitic formations, granulomas, syphilis, tuberculosis, and finally abscesses. All these formations, different in their histogenesis, are, by the general consensus of neuropathologists and surgeons, to be subjected to surgical treatment. Access to subtentorial tumors is made through the occipital bone either by its resection or by an osteoplastic method. The osteoplastic flap in this case is cut with the base facing downward. It can be cut wider or narrower depending on whether it is necessary to expose and make accessible one or both cerebellar hemispheres. Corresponding to the different methods of creating access to the posterior cranial fossa, i.e., with the removal of the occipital bone or with its preservation, skin incisions are also made. At the present time, two types of incisions are practiced—in the form of the letter U over one or both hemispheres, or the Cushing incision in the shape of a crossbow figure. Both with one and the other incision, a very good access to the region of the occipital bone is created. If it is necessary to perform a resection, the skin-muscle-periosteal layer is carefully separated from the bone up to the foramen occipitale magnum. Then an opening is made in the bone with a large burr corresponding to the most convex posterior part of the hemisphere, and from there, the bone is resected with Luer forceps to the desired extent: upward until the exposure of the transverse sinuses, and to the sides up to the location of the cellulae mastoideae, which are better not to be opened at all to avoid possible infection of the operative field. When removing the section of bone where the protuberantia occipitalis lies, there is significant bleeding from the sinuses, which is successfully stopped by applying muscle pieces. It must be said that even during the detachment of the periosteum from the bone, significant bleeding sometimes occurs from the emissary foramina, which is easily stopped by means of muscle tissue. The exposed area of bone allows for easy orientation regarding the position of the cerebellar hemispheres, the vermis, the sinus occipitalis, the tension, the pulsation, and the presence of inflammatory changes in the meninges. Opening of the dura mater over both hemispheres can be performed only with preliminary ligation of the sinus occipitalis. The ligation is done through two incisions parallel to the sinus, preferably in its upper section. Then a flap with the base facing downward is cut from the dura mater. The upper edge of this flap runs 1/2-2/3 cm below and parallel to the transverse sinus, bending from the sides parallel to the descending part of the transverse sinus. With the osteoplastic method, unilateral or bilateral, there are a number of significant disadvantages: when the flap is folded downward, the foramen occipitale magnum is usually opened. This moment is very dangerous, as shock often occurs (apparently from concussion). Therefore, it is recommended not to violate the integrity of the foramen occipitale magnum when cutting the osteoplastic flap. Not without reason, some authors point to a higher mortality rate with the osteoplastic method. In 75 cases of Burdenko during operations in the region of the posterior cranial fossa, the plastic method was used in only 5%. The osteoplastic unilateral or bilateral method in the region of the posterior cranial fossa is usually called the Krause method, although the principle of osteoplastic and plastic operations on the skull was proposed by Wagner and was used before Krause's description (1906) by a whole series of surgeons (e.g., Eiselsberg in 1894). - After exposure of the hemispheres, one proceeds (depending on the purpose of the operation) to the inspection and examination of various sections of the cerebellum, nerves, or sections of the posterior cranial fossa. In this, it is necessary to remember that any examination of the cerebellar hemispheres is easily accompanied by bleeding. This is observed especially during careless retraction of the hemispheres in the caudal direction and insertion of a spatula between the tentorium and the upper surface of the cerebellar hemisphere. The bleeding depends on the rupture of veins running from the cerebellum to the veins of the tentorium. To avoid sometimes very severe bleeding, they should be ligated beforehand. Ligation makes it possible to perform a complete and perfect inspection of various parts of the cerebellum and, most importantly, the course of the nerves. In addition to the general methodology of operations on the posterior cranial fossa, it is necessary to point out the method of preparation for the operation, the choice of the patient's position during the operation, the performance of the operation in one or two stages, anesthesia, and the control of bleeding. Methods of preparation for brain operations must be simple and must not exhaust the patient—laxatives should be given in very limited quantities. During the operation, patients are placed in various positions—Cushing considers the horizontal position with the face down to be especially appropriate: the patient lies with the abdomen and chest on the table, the shoulders rest on supports attached to the table, and the head rests with the forehead on a special support, to which various positions can be given; of many models, the most simple is the Cushing model and the model of the Leningrad Orthopedic Institute (Polenov). Other authors place patients in a sitting position (de Martel), others in a lateral position. Cushing considers the prone position (face down) especially advantageous. Burdenko believes that each position has its conveniences and its disadvantages. A very important question is anesthesia; while some authors use exclusively local anesthesia (de Martel, Forster), others (Cushing) use both local and general anesthesia or a combination of both.
In some cases, especially in patients exhausted by pain, vomiting, and the awareness of the gravity of their condition, it is difficult to manage without general anesthesia. Recently, Burdenko has tested avertin anesthesia for brain operations; this type of anesthesia has many positive data points in its favor. Whatever type of anesthesia is chosen for operations in the region of the posterior cranial fossa, it is necessary to conduct careful monitoring of blood pressure, pulse, and respiration. It is best to monitor blood pressure by means of instrumental measurement. Often during operations on the posterior cranial fossa, with a good pulse, respiratory arrest occurs either gradually or suddenly. Caffeine in large doses and inhalation of carbon dioxide in most cases help to restore respiration. Sometimes one has to resort to artificial respiration for a prolonged period (up to nearly 6 hours). If the control of bleeding is a general surgical rule for all operations, then for brain operations, and in particular for subtentorial operations, it must be carried out with special care. During these operations, even the initial acts, such as the detachment of the periosteal-muscular-cutaneous flap, and the resection of the occipital bone to one extent or another, cause a catastrophic drop in blood pressure, so that the question arises of the necessity to interrupt the operation and divide it into two stages. These operations, in the main, have brought forward the question of great fundamental importance regarding one-stage and two-stage methods of performing brain operations. Two-stage methods should not be elevated to a rule—they are not safe in terms of infection, and one must only reconcile oneself to them. Cushing explains his brilliant achievements mainly by careful attention to the arrest of bleeding. In this regard, enormous importance must also be attributed to preliminary puncture of the posterior horn of the lateral ventricle with the aim of weakening intracranial pressure and creating more favorable conditions for blood circulation and reducing phenomena of stasis, and thereby bleeding as well. Puncture of the ventricles must be done before opening the dura mater. It is useful, as already mentioned above, to use tamponade with muscles, and in case of bleeding from bone, with wax or wooden plugs. Sometimes it is very useful during bleeding to place the patient in an elevated position if the operation is being performed with the patient in a horizontal position. During the performance of the operation, repeated intravenous administration of glucose is recommended when pressure drops. In case of bleeding from the bed of the removed tumor or from the tumor itself, if it has to be removed in parts, the control of bleeding is best achieved with the help of an electrocautery. In its absence, muscle tamponade, irrigation with saline solution, and tamponade with saline compresses made of gauze in many cases allow one to cope with bleeding. Some authors recommend vivocol, but it has not found wide application. During an operation on the posterior cranial fossa, postoperative care is also very important in terms of maintaining blood pressure and very strict control of respiratory movements. Repeated inhalation of CO2 and permanent intravenous infusion of glucose in small portions are very useful (Forster). Departures from these general rules are made in some cases, in particular with cerebellopontine tumors, or, more precisely, with tumors of the n. acusticus. Panse (1904) proposed an approach through the labyrinth to the n. acusticus, with proximity to the n. facialis and exposure of the a. carotis int., bulbus v. jugularis, sinus sigmoideus, sinus petrosus superior. This method has the advantage that it represents the shortest path to the tumor; a small tumor can easily be removed by this route. In practice, however, it turned out that some tumors remained overlooked, and the postoperative period resulted in fistulas and secondary infection. Also, the combined petro-occipital method with partial resection of the os petrosum and ligation of the sinus sigmoideus (Eiselsberg, Borchardt, Eiselsberg) proved to be little practical. Both these methods have the goal of making access to the tumor shorter, but they have so many drawbacks that this advantage is not worth the risk and the small number of positive results after these operations. The different nature of tumors, their number, and location create specific indications for each intervention, which is why it is impossible to give general rules for operative technique. A technique suitable for a well-demarcated tumor will be completely unsuitable for an infiltrating tumor. The same applies to cysts of various origins: in one case, for example, with a dermoid cyst, its complete removal is possible, whereas with cysts representing hydrocephalus of the IV ventricle, surgical intervention must be limited to opening it and partially removing the wall. A pedunculated cyst can be removed in its entirety. In the absence of obvious changes on the surface of the cerebellum, it is sometimes necessary to perform a puncture. With a positive finding, the properties of the punctate allow one to easily orient oneself in the situation and develop a plan for further surgical intervention. When accessing the tumor, it is necessary to perform excision of one or another part of the cerebellum—the hemispheres or the vermis. This excision is tolerated relatively easily. Sectioning of the hemispheres was performed either only on one side or simultaneously on both sides. Few cases of such interventions have been published, and the absence of any severe deficiency symptoms was noted (e.g., the Krause case, verified by autopsy 4 years after the sectioning of the hemispheres). Sectioning of the hemispheres was also proposed for access to tumors of the cerebellopontine angle. In the case of tumors involving one of the cerebellar hemispheres, it is necessary to perform resection of significant portions of it, up to complete removal with opening of the cavity of the IV ventricle. It is interesting that severe deficiency symptoms do not develop in this process. The same must be done with the vermis—sectioning of it must be performed in cases of suspected cysticercus in the IV ventricle or in cases of suspected tumor of both the ventricle and one or another part of the vermis itself. Sometimes a tumor develops in the vermis itself, in its posterior or upper section. In these cases, it is necessary to remove the entire affected part until the entire cavity of the IV ventricle is exposed, and with removal of the velum medullare. The gaping wound is easily closed by the cerebellar hemispheres (case of lymphangiosarcoma plexiforme—Krause). In tumors with cystic degeneration or in serous cysts, one of the hemispheres and the vermis may simultaneously be affected almost to the point of complete disappearance of the brain substance. In cases of tumors of significant size in one of the hemispheres and simultaneously in the vermis, it is necessary to perform resection of both parts of the cerebellum. These severe interventions were undertaken for myxosarcoma, sarcoma with secondary cystic degenerations. Most interventions ended lethally. Surgical intervention for tuberculoma does not essentially differ from the techniques for removing solitary tumors at the stage when there is no liquefaction yet or when petrification has already occurred. In these cases, the tuberculoma is removed with exceptional ease. When removing solitary tuberculomas, especially those located superficially, bleeding is very insignificant. It is more difficult to remove infiltrating tumors of a tubercular nature. Here, one has to perform resection of parts of the brain substance without sufficient certainty, not having precise anatomical orientation regarding the boundaries of healthy and affected tissue. Tubercular tumors are sometimes arranged in a conglomerate, affecting the surface of the cerebellum and the dura mater. Gummata were less frequently the object of intervention; in appearance and relation to adjacent areas of brain tissue, these granulomas differ little from some forms of tumors. The prognosis of surgical intervention depends on many conditions that can be subjected to more or less precise analysis—the duration of the disease, the nature of the disease, the structure of the tumor, its consistency, size, and its malignancy or benignity. The most favorable prognoses and outcomes are provided by extramedullary serous inflammatory cysts and, subsequently, serous cysts. Borchardt presented statistics of 36 cases with a good outcome in 35 cases. Tumors of significant size, during the removal of which it is necessary to sacrifice significant portions of one or another part of the cerebellum and open the ventricle, carry a grave prognosis. Cases where there is secondary cystic degeneration of a cerebellar tumor also have a poor outcome in the final result. In these cases, if complications do not always occur directly during the operation, then as a rule, recurrences appear. The most grave prognosis is for angiosarcoma. Very often, due to various complications from important vital centers located in the vicinity of the area of surgical intervention, or due to bleeding, or due to the extent of pathological changes, or due to the impossibility of finding the tumor or clarifying the cause of severe symptoms from the posterior cranial fossa, the operation is not brought to an end and essentially turns into an operation of a palliative nature, i.e., decompressive trepanation.
Sometimes this operation is undertaken deliberately, wishing to limit oneself to it, for example, in very emaciated patients. Decompression operations as palliative measures sometimes alleviate the difficult situation for a more or less prolonged time, but sometimes they only worsen the condition. Operations performed for tuberculous granulomas are often very effective at first, but subsequently, the majority of cases end in tuberculous meningitis (Cushing, Krause, Burdenko). However insignificant the surgical achievements in this area may be, one thing must be admitted: the condition of patients with a disease of the cerebellopontine angle is so difficult and hopeless that if anything can create any chances for improvement, it is only surgery. Attempts to treat with X-rays or radium have not yet gone beyond the testing stage, and the results of these attempts are very modest and controversial.
I. Burdenko.
Upon graduating from the university, he was retained at the Department of Pathological Anatomy of Kharkov University in the position of assistant prosector, which he held until 1894, when he moved to St. Petersburg. In 1894, he published his dissertation: "On the Structure and Development of Glanders Nodules" (St. Petersburg). From 1894 to 1896, he held the position of prosector at the Prince Oldenburg Children's Hospital, and from 1896 to 1902, prosector of the Obukhov Hospital. At the same time, he served as a privat-docent

at the Military Medical Academy. In 1902, he was elected professor of pathological anatomy at the Military Medical Academy and held this position until 1930, when he retired due to length of service. M. was one of the founders of the Society of Pathologists in Leningrad and served as its chairman many times. M. created his own school of pathologists, from which a whole number of individuals emerged who hold positions as professors of pathological anatomy and pathological physiology in the USSR. The subject of M.'s main scientific research was infectious diseases: glanders, diphtheria, pneumonia, intestinal infections; in this area, M.'s works provided a great deal of valuable information in terms of clarifying the pathological anatomy of these diseases. Of very great importance is the methodology created by M. and his school for the experimental reproduction of arteriosclerosis by feeding animals cholesterol-containing material; the works related to this, which placed the experimental study of arteriosclerosis on a firm footing and contributed much to the clarification of the essence of this disease of the arterial system, brought M.'s school world renown. In recent years, M. and his school have developed a number of issues related to the pathological anatomy of alcoholism, as well as diseases of the heart, liver, and hematopoietic organs.
Related articles
Mentioned in
Cite this page
“Cerebellopontine Angle.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/cerebellopontine-angle/