Medulla Oblongata
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
The medulla oblongata is the lowest part of the brain, serving as a pathway between the brain and spinal cord while housing vital reflex centers for functions like swallowing and breathing.
Encyclopedia article (1928–1936)
Medulla Oblongata (syn. medulla oblongata, s. bulbus medullae spinalis), the lowest part of the brain (myelencephalon), very complex in structure and having important functional significance: 1) it serves as a conductor for fibers connecting various parts of the brain with the spinal cord, and through it with the periphery; 2) it has significance as a central apparatus—in it are located reflex centers, moreover it is the site of origin of complex combined acts, such as swallowing, breathing. Together with the intermediate, middle, and hindbrain, it forms the brainstem. It develops from the primary hindbrain vesicle (see Brain). The medulla oblongata lies between the pons Varolii above, from which it is sharply demarcated, and the spinal cord below, into which it passes without sharp boundaries; the boundary between them is considered to be the decussation of the pyramids and the exit of the first pair of cervical roots. At the place where the medulla oblongata transitions into the spinal cord there is a bend (occipital). On the skeleton, the lower boundary of the medulla oblongata corresponds to the upper
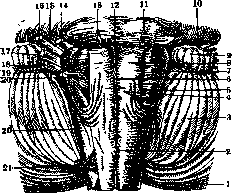
Figure 1. Anterior surface of the medulla oblongata: 1- spinal cord; 2- decussatio pyramidum, boundary between medulla oblongata and spinal cord; 3- cerebellum; 4- medulla oblongata; 5- fasciculus lateralis ant.; 6- fasciculus mediana ant.; 7- olive of the medulla oblongata; 8- pyramid of the medulla oblongata; 9- flocculus of the cerebellum; 10- pedunculus cerebelli ad pontem; 11- pons Varoli; 12- foramen caecum; 13- n. abducens; 14- n. facialis; 15- n. Wrisbergi; 16- n. acusticus; 17- n. glosso-pharyngeus; 18- n. vagus; 19- n. hypoglossus; 20- n. accessorius-bulbar and spinal (20') its root; 21- first cervical root.
which in the medulla oblongata receive the name fasciculus gracilis (gracile fascicle) and fasciculus cuneatus (cuneate fascicle); they are separated from each other by septum paramedianum. Fasciculus gracilis ends with an enlargement-clava (clava), fasciculus cuneatus-with a tubercle (tuberculum cuneatum). In the upper part, the posterior surface of the medulla oblongata forms the floor of the fourth ventricle (ventriculus quartus) or rhomboid fossa, its lower triangle; the apex of this triangle passes into the spinal canal; the narrowest part of the triangle is called calamus scriptorius (writing pen), above it passes the transverse lamina-obex (bolt). The base of the triangle corresponds to the widest part of the fourth ventricle, which, expanding outward, forms a recess or recessus lateralis. Along the floor of the fourth ventricle, on the border of the lower and upper triangles (corresponding to the posterior surface of the pons Varoli), pass striae medullares, s. acusticae. On the sides, the rhomboid fossa is bounded by the restiform bodies (corpora restiformia). Along the median line of the rhomboid fossa runs a groove (sulcus medianus, fossae rhomboideae); on each side of it is a triangular elevation (trigonum hypoglossi), corresponding to the nucleus of the XII nerve; its apex is turned downward, base upward; outward from it lies another triangle, turned, conversely, with apex upward, of smaller size, grayish in color-ala cinerea or fovea vagi; in this place is located the nucleus of the X nerve; this place is also called the vital node, since its destruction (nucleus of the X nerve) leads to death. In the outer angle of the floor of the fourth ventricle,
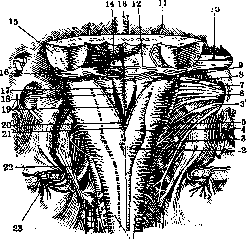
Figure 2. Posterior Surface of the medulla oblongata; floor of the fourth ventricle: 1- spinal cord; 2- medulla oblongata; 3- n. accessorius and 3'-its spinal root; 4- nucleus fasciculi gracilis; 5- nucleus fasciculi cuneati; 6- n. vagus; 7 and 8- n. glosso-pharyngeus; 9- recessus lateralis of the fourth ventricle; 10- n. acusticus; 11- n. abducens; 12- pons Varoli; 13- a. basilaris; 14- eminentia teres; 15- pedunculus cerebelli ad pontem; 16- tuberculum acusticum; 17- fissura mediana post.; 18- trigonum n. hypoglossi; 19- ala cinerea; 20- calamus scriptorius; 21- obex; 22- a. vertebralis; 23- dura mater (cut).
in the so-called area acustica, there is an elevation (tuberculum acusticum, or auditory tubercle), from which white stripes (striae acusticae) go to the median line. From the cerebellum to the outer walls of the lower part of fossae rhomboideae goes an epithelial plate (velum medullare posticum-posterior medullary velum); above its edge Ct. The length of the medulla oblongata is from 2.5 to 3 cm, the anteroposterior diameter is 12-15 mm, the transverse diameter is 10-12 mm below and 22-25 mm above. Weight is 6-7 g (1/216 of the weight of the entire brain).- The medulla oblongata has the shape of a truncated cone, slightly flattened in the anteroposterior direction: in it are distinguished anterior, posterior, lateral surfaces, base and apex. On the anterior surface (fig. 1) runs a groove (fissura mediana ant.), which is a continuation of the same groove of the spinal cord and ending at the pons Varolii with a blind opening (foramen caecum inf.); below at the border with the spinal cord it is interrupted for 6-8 mm by the decussation of the pyramidal fibers occurring here; along its sides lie thick bundles-pyramids, bounded outward by a groove (fissura lateralis ant., or antero-lateralis, s. fissura praeolivaris, s. fissura n. hypoglossi). On the lateral surface of the medulla oblongata is located the olive (oliva inf., olive of the medulla oblongata), of oval shape, white color, 12-15 mm in length, 4-5 mm in width; behind it passes a groove (fissura lateralis post., s. fissura retroolivaris). Along the entire length of this groove emerge the roots of three cranial nerves IX, X and XI (n. glosso-pharyngeus, vagus, accessorius); the root of n. XII emerges in the fissura lateralis ant. Between the medulla oblongata and the pons Varolii, at the level of the pyramids, emerges n. abducens (VI), and in the angle near the cerebellum-pp. facialis and acusticus (VII, VIII). The posterior surface of the medulla oblongata in its lower and upper parts shows a significant difference (fig. 2). In the lower part along the median line runs fissura mediana post., s. fissura longitudinalis post.; on each side of it are located continuations of the posterior columns of the spinal cord-fasciculi of Goll and Burdach,
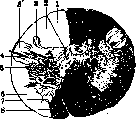
Figure 3. Cross section of the medulla oblongata at the level of its lower border: 1- fasciculus of Goll; 2- fasciculus of Burdach; 3- posterior horn; 3'- substantia gelatinosa Rolandi; 4- posterior roots; 5- crossed pyramidal tract; 6- lateral column; 7- anterior horn; 8- direct pyramidal tract.
The rhomboid fossa is covered by the tela chorioidea, and then by the cerebellum. The microscopic structure of the medulla oblongata changes depending on the level: in the lower sections, it resembles the spinal cord in its structure to some extent (Fig. 3); characteristic of this section is the decussation of the pyramidal fibers (decussatio pyramidum), which occurs along the anterior surface of the medulla oblongata, as a result of which the anterior median fissure decreases in depth, filling with fibers crossing from one side to the other. The anterior horns are still intact but have lost their connection with the posterior ones; the accessory nerve (XI) originates in them; the substantia gelatinosa of Rolando increases in size, and the descending, or spinal, root of the trigeminal nerve (V) is located along its periphery; along the periphery of the lateral column lie the Flechsig and Gowers tracts and the vestibulospinal tract (Fig. 4), and more medially, the rubrospinal tract. The posterior columns are sharply demarcated into 2 bundles—the funiculus gracilis and the funiculus cuneatus; nuclei appear in these bundles—the nucleus of the funiculus gracilis and the nucleus of the funiculus cuneatus; the first sensory neuron terminates in them; the substantia reticularis has increased in size; the central canal is located posterior to the decussation, and near it is the dorsal or bulbar nucleus of the accessory nerve. Somewhat higher, the pyramids form powerful bundles (pyramis medullae oblongatae) located on the sides of the anterior median fissure; an arcuate nucleus (nucl. arcuatus, s. arciformis, s. praepyramidalis) lies on the surface of the pyramid. Somewhat posterior and lateral to the pyramids are the inferior olives (olivae inf., s. nucl. olivaris inf.), and medial to them is the accessory olive (oliva accessoria medialis, s. interna, s. nucl. olivaris accessorius ant.). The nuclei of the posterior columns have increased significantly in size, and their white matter has decreased, as it gradually terminates in these nuclei; the second sensory neuron—the internal arcuate fibers (fibrae arcuatae internae)—begins in them; they bypass the central canal and decussate anterior to it with fibers from the opposite side, forming the sensory or upper decussation (decussatio lemniscorum); after the decussation, the fibers are located in the interolivary layer, forming the medial lemniscus, or medial fillet. Near the central canal anteriorly is the posterior, or medial, longitudinal fasciculus and the nucleus of the hypoglossal nerve (XII), lateral to it is the vagus nerve (X), and posterior and lateral is the accessory nerve (XI). The Flechsig tract begins to deviate posteriorly, forming the anterior external arcuate fibers, which take a large part in the formation of the restiform bodies; the Gowers tract lies anteriorly, and the substantia gelatinosa of Rolando, the descending root of the trigeminal nerve (V), the rubrospinal tract, and the vestibulospinal tract lie medially. The entire remaining part is occupied by the substantia reticularis, in which nuclei and fibers are located; a large accumulation of nuclei in the lateral sections is distinguished under the name of the lateral reticular nucleus, or nucleus of the lateral funiculus. The midline is occupied by the raphe; the nuclei lying near the raphe are distinguished under the name of the raphe nuclei. In the more superior sections of the medulla oblongata, at the level of the opening of the fourth ventricle, along its floor, which is covered by ependyma, in the gray matter (stratum cinereum fossae rhomboideae) are located the nucleus of the hypoglossal nerve (XII), the dorsal nucleus of the vagus nerve (X), and the posterior longitudinal fasciculus; somewhat anterior to the nucleus of the vagus nerve (X) lies the solitary fasciculus or tract (fasciculus solitarius), surrounded by the nucleus of the solitary tract (nucl. funic. or tracti solitarii, s. nucl. terminalis, s. subst. gelatinosa vagi et glossopharyngei); the fibers of the solitary fasciculus gradually terminate in this nucleus. The nuclei of the funiculus gracilis and cuneatus decrease in size, as do the bundles themselves; lateral to the cuneate nucleus appears a new nucleus, the so-called external nucleus of the funiculus cuneatus (syn. Monakow's nucleus, nucleus of the restiform body); it is, as it were, the center around which the restiform body is formed; the Flechsig tract also takes a large part in the formation of the restiform body, the fibers of which, in the form of anterior external arcuate fibers, deviate posteriorly and lie around the external nucleus of the funiculus cuneatus; in addition, a small number of fibers from the posterior columns enter the restiform body (posterior external arcuate fibers). From the nuclei of the posterior columns, internal arcuate fibers continue to emerge, forming a decussation and joining those previously decussated in the medial lemniscus, which is located along the midline in the interolivary layer. From the arcuate nucleus, anterior external arcuate fibers depart, which pass along the anterior surface of the pyramids, heading toward the restiform body. Near the inferior olive lie two accessory olives (olivae accessoriae, s. nucl. olivaris accessorius medialis et dorsalis); fibers from the olives
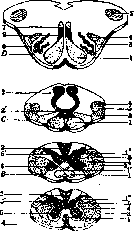
Figure 4. Transverse sections through the cervical spinal cord (A) and through the medulla oblongata (B, C, and D) at various levels. Comparative arrangement of various bundles in the spinal cord and medulla oblongata: 1—pyramidal tract; 1'—its decussation; 1''—decussated pyramidal tract; 2—posterior columns; 2'—decussation of fibers from the nuclei of the posterior columns (decussatio lemniscorum); 3—Gowers tract; 4—its sensory part (fasciculus spinothalamicus); 5—corpus restiforme; 6—anterior horns of the spinal cord; 6'—posterior horns; 7—posterior longitudinal fasciculus; 8—inferior olive.
(olivocerebellar fibers) also take part in the formation of the restiform body, mainly from the opposite side. In the substantia reticularis, in addition to other nuclei, the nucleus ambiguus appears—the motor nucleus of the vagus nerve. Gradually, upward, the floor of the fourth ventricle widens (Fig. 5); the restiform body increases. Along the floor of the ventricle, starting from the midline, lie the following structures: medial longitudinal fasciculus, or posterior longitudinal fasciculus, tectospinal tract, nucleus of the funiculus teres, or nucleus of the medial eminence, nucleus of the hypoglossal nerve (XII), nucleus of the vagus nerve (X); between these latter nuclei is wedged a nucleus of very small cells—the intercalated nucleus of Staderini; in the lateral angle of the ventricle is the medial vestibular nucleus (Schwalbe), and near the restiform body is the descending root of the vestibular nerve. The remaining structures are the same as in the lower sections, only in the substantia reticularis, between the nucleus ambiguus and the olive, lies the sympathetic nucleus—the sympathetic nucleus of the medulla oblongata, or inferior salivatory nucleus of Kohnstamm; its fibers are part of the glossopharyngeal nerve (IX). At the very highest levels of the medulla oblongata, the fourth ventricle widens significantly, forming lateral recesses; the very diameter of the medulla oblongata becomes wider due to the strong development of the restiform bodies; on their outer surface is located the acoustic tubercle (tuberculum acusticum), the site of termination of a part
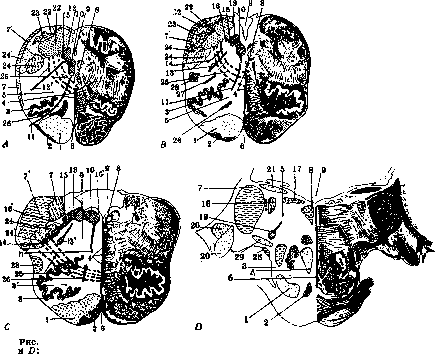
5. Transverse sections of the medulla oblongata at various levels A, B, C 1—pyramids; 2—arcuate nucleus; 3—inferior olive and 3'—its hilus; 4—decussatio lemniscorum and 4'—medial lemniscus; 5—substantia reticularis; 6—raphe; 7—Flechsig tract and 7'—corpus restiforme (its internal part); 8—posterior longitudinal fasciculus; 9—central canal and 9'—fourth ventricle; 10—nucleus of the hypoglossal nerve and 10'—nucleus of the funiculus teres; 11—hypoglossal nerve; 12—nucleus of the accessory nerve and 12'—accessory nerve; 13—dorsal nucleus of the vagus nerve and 13'—nucleus ambiguus; 14—vagus nerve; 15—solitary fasciculus; 16—nucleus of the glossopharyngeal nerve and 16'—glossopharyngeal nerve; 17—dorsal vestibular nucleus; 18—Deiters' nucleus; 19—nucleus of the facial nerve; 20—ventral cochlear nucleus; 21—acoustic striae; 22—posterior columns and 22'—their nuclei; 23—external cuneate nucleus (Burdach's nucleus); 24—substantia gelatinosa of Rolando and 24'—descending root of the trigeminal nerve; 25—external arcuate fibers; 26—medial accessory olive; 27—dorsal accessory olive; 28—lateral funiculus of the medulla oblongata and its nucleus; 29—trapezoid body.
fibers of the auditory nerve; another part of them ends in the nucl. ventralis n. cochleae, located more ventrally. Along the floor of the fourth ventricle are located nucl. funic. teretis, nucl. praepositus; in front of them passes the fasc. longitud. post.; the rest of the floor of the fourth ventricle is occupied by the nucleus of the vestibular nerve [nucl. medialis (dorsalis) n. vestibularis]. In the inner part of the corp. restiform. is located nucl. p. vestibul. lat. (nucleus of Deiters) and tract, nucleo-cerebellaris, connecting these nuclei with the cerebellum. Along the very floor from the tubercul. acust. go the striae acusticae, which, approaching the midline, descend into the depth of the Medulla Oblongata. In the other parts of the Medulla Oblongata at this level, the changes are not significant: the lemniscus med. forms a more compact bundle, between it and the fasc. longit. post. lies the central nucleus of Roller (nucl. centralis inf.); the olives decrease in size; in the subst. reticul. instead of the p. ambiguus lies the nucleus of the p. facialis. In the lateral column is the bundle of Gowers and the fasc. rubro-spinalis; in front of the pyramidal fibers appear the own fibers of the bridge of Varolius. B l o o d s u p p l y o f t h e M e d u l l a O b l o n g a t a. The arteries of the Medulla Oblongata depart from the initial part of the a. basilaris, from the a. vertebralis and from its branches - the a. spinalis and a. cerebellaris inferior. These arteries divide into 1) aa. radiculares, entering together with the roots of the cranial nerves into the Medulla Oblongata, where they divide into two branches - one goes along the root to the periphery, the other - into the tissue of the Medulla Oblongata to the nuclei of the corresponding nerves; 2) aa. centrales, mediales, s. a. sulci bulbaris, passing through the entire thickness of the Medulla Oblongata to the fourth ventricle and nourishing the formations located near the midline - pyramids, lemniscus medialis, parts of the inferior olives. some nuclei of cranial nerves. Depending on the height of the aa. centrales, they depart from different arteries; the upper ones from the a. basilaris, the lower ones from the a. spinalis ant.; 3) aa. periphericae, departing from the arteries of the soft meninges and nourishing the white matter of the brain and nuclei in the substantia reticularis. The Arteriae chorioideae take origin from the a. cerebellaris, which nourishes the lateral parts of the medulla oblongata. Physiology of the Medulla Oblongata. Despite its comparatively small size, the Medulla Oblongata is an extremely important organ functionally, as indicated by its extremely complex structure. Due to the presence in the Medulla Oblongata of accumulations of nerve cells, it has the significance of a central apparatus; in it are laid the nuclei of the following cranial nerves: n. hypoglossi, n. accessorii, n. vagi, n. glossopharyngei, nervi acustici (vestibular and cochlear), then the nucleus of the n. facialis and the sensory nucleus of the n. trigemini; the nuclei of the last three nerves also extend into the pons (function of the nerves - see the corresponding nerves and Autonomic Nervous System). The motor nuclei of these nerves are the motor centers of individual muscle groups and muscles and associated with the function of simple reflexes, due to the termination near them of sensory fibers. But the activity of the medulla oblongata is not exhausted by only such reflexes, it is also the place of origin of complex coordinated movements, automatic acts, in the formation of which several motor and sensory systems participate; such are for example the acts of swallowing, breathing, chewing, sneezing, vomiting (see the corresponding words). These latter data led to assume the existence in the Medulla Oblongata of special coordinating mechanisms and for each complex act of special coordination centers; which would connect various simple centers for a certain physiological purpose, not being themselves directly connected with the muscles. In microscopic study of the Medulla Oblongata, they tried to find such groups of cells in which it would be possible to localize various centers, as for example the center of swallowing, the center of breathing, etc.; especially many works were devoted to the center of breathing; Flourens localized it in the angle of the rhomboid fossa, this place was called the vital node (noeud vital), then it was localized in the nucleus funic. solitarii, in the subst. reticul. etc., but even to this day no final conclusions have been reached about the localization in general of coordinating mechanisms for the above-mentioned acts; on the contrary, many scientists began to deny the possibility of the existence of such centers, and assumed that the connection, which undoubtedly exists between individual simple centers, occurs through association neurons, reaching a great development in the Medulla Oblongata, namely in the substantia reticularis, which is called the associative field of the Medulla Oblongata. The cells of the subst. reticul. are mostly with short axons, but there are also with long ones, connecting with all the motor centers of the Medulla Oblongata, the pons, and the spinal cord; the sensory fibers entering the Medulla Oblongata end with their collaterals in the substantia reticularis, near its cells, which for example explains why respiratory reflexes can be caused by irritation of the mucous membranes and skin. The occurrence of the respiratory reflex is conditioned not only by the transmission of irritation along the sensory nerves, but also by its own mechanisms, for example by the difference in the ratio of O and CO2 in the blood. The influence of the Medulla Oblongata on cardiac activity see Vagus nervus, Autonomic Nervous System. In the Medulla Oblongata there are groups of cells having a toning influence on the spinal centers of the vasomotor apparatus, but they in turn are under the influence of the main vasomotor centers in the diencephalon. An influence of the Medulla Oblongata on sweating, on the pupil is assumed due to a possible interruption of the central sweating conductors and the ocular sympathetic pathway in a group of cells located in the substantia reticularis of the Medulla Oblongata and playing the role of relay stations. It has been suggested that in the Medulla Oblongata there are centers for metabolism, because in diseases of the Medulla Oblongata the presence of sugar in the urine is often noted; a prick of the floor of the fourth ventricle (prick of C. Bernard) at the level of ala cinerea causes glycosuria; a prick somewhat higher, on the contrary, leads to a decrease in sugar in the blood. From these data it follows that in the posterior nucleus of the n. X (in ala cinerea) there are 2 groups of cells acting antagonistically, one parasympathetic (inhibiting the formation of sugar and standing in close connection with the pancreas), the other - sympathetic (causing the formation of sugar and having a connection with the liver).- Finally the Medulla Oblongata also has relation to salivation due to the presence in it of the nucl. salivatorius inf. The Medulla Oblongata also plays the role of a conductor, because in it pass fibers in various directions and different in function: In the Medulla Oblongata occurs the crossing of motor fibers; in it ends the first sensory neuron and begins the second, which also undergoes crossing. Through the Medulla Oblongata occurs communication between the periphery and the cerebellum and the brain1. Pathology of the Medulla Oblongata. Due to the complex anatomical structure, the pathology of the Medulla Oblongata is very complex. Disease of the Medulla Oblongata or the so-called bulbar syndrome is characterized by a disorder of the function of cranial nerves, the nuclei of which are located here, of movement, sensitivity, of the vasomotor apparatus, of the cerebellum, of cardiac activity, of metabolism, etc. Of the motor disorders, hemiplegia can be noted, and if the focus is close to the midline, then quadriplegia; crossed or alternating paralysis (paralysis of the arm on one side and of the leg on the other). The disorder of sensitivity can manifest in three different forms: 1) complete loss of sensitivity; 2) preservation of deep sensitivity; 3) dissociation of sensitivity of the syringomyelia type. Alternating disorders of sensitivity are also observed. Very often a change in sensitivity is accompanied by vasomotor disorders in the form of asymmetry in body temperature (up to 1° and more), in the filling of the vessels, in blood pressure (checked by means of a plethysmograph); all these changes are observed on the side opposite to the focus. Cerebellar phenomena are quite frequent in diseases of the Medulla Oblongata, they occur on the side of the focus, depend on the lesion of the corpus restiforme, of the cerebellar bundles or of the olivae inf. (giving fibers to the corp. restiforme). Of the cranial nerves, the nn. XII, XI, X, IX, VIII and partly the n. VII and VI can be affected (see Bulbar paralysis). Unilateral paralysis of the pharynx, soft palate is distinguished under the name of Avellis' syndrome, and if in addition there is paralysis of the n. XI, then Schmidt's syndrome results. In lesions of the Medulla Oblongata, on the side of the focus, Horner's syndrome or the sympathetic ophthalmic syndrome is observed (see Horner's symptom complex). Lesion of cranial nerves can be combined with paralysis and disorders of sensitivity on the opposite side, giving alternating syndromes. In the clinic, the most diverse combinations of the above-mentioned disorders are observed. Dissociated hemianesthesia and hemiplegia on one side, hemiasynergy, lateropulsion and miosis on the other - are distinguished as the alternating syndrome of Babinski and Nageotte. The syndrome of Cestan and Chenais is characterized by hemiplegia, hemianesthesia on one side, hemiasynergy, Horner's syndrome and Avellis' syndrome on the opposite.
Quite often the focus spreads to the pons or to the spinal cord, and in the first case there is a complex syndrome of the medulla oblongata and the pons (syndrome bulbo-protuberantiel), which, in addition to bulbar phenomena, is characterized by simultaneous involvement of the V, VI and VII pairs of cranial nerves or of the spinal cord. The retroolivary syndrome is characterized by disturbance of superficial sensitivity on one side, cerebellar phenomena, and paralysis of the pharynx, larynx, and soft palate on the other; paralysis of the extremities, as well as disturbance of deep and tactile sensitivity, are absent due to the integrity of the pyramids and the interolivary layer. When the nucleus of Deiters is involved in the process, a syndrome is observed, expressed by dizziness, oculomotor disturbances, weakness in the legs, nausea, disturbances of hearing, and pain in the temporal region. All these symptoms are explained by the connections that the nucleus of Deiters has with the surrounding formations. - Since the medulla oblongata contains the anatomical substrate for some important vital functions - for respiration, cardiac activity, metabolism, swallowing, etc., - damage to the medulla oblongata is accompanied by disturbance of these functions; various types of respiratory disturbance are observed - Cheyne-Stokes respiration, stertorous respiration, dyspnea of varying intensity with or without cyanosis; respiratory disturbance can lead to death. Of the cardiac disturbances, the Adams-Stokes syndrome, slow pulse (pouls lent permanent), tachycardia, embryocardia can be noted. - In many diseases of the medulla oblongata, glycosuria (syn. mellituria), simple polyuria (diabetes insipidus) or with albuminuria are observed. Finally, there is the so-called anxietas paroxysmalis (s. paroxystique)--anguish, appearing in the form of attacks, mostly nocturnal, with sudden onset, accompanied by trembling, cold sweats, marked pallor of the face, and a suffering expression; it depends on the disturbance of nutrition of the medulla oblongata. Special pathology. In the brain stem, the same processes are observed as in the brain: vascular diseases (softenings and hemorrhages), tumors, traumatic injuries, inflammations. Of the vascular diseases of the medulla oblongata, thrombosis, embolism leading to softening, and hemorrhage should be noted. Thrombosis of the arteries of the medulla oblongata is observed more often than embolism, and is a consequence of arterial disease (arteriosclerosis, atheromatosis, syphilitic arteritis, etc.). The focus of softening is most often unilateral, it can be both single and multiple; sometimes it simultaneously involves the pons or the spinal cord. Around the focus of softening, diffuse edema, dilatation of capillaries, phenomena of diapedesis are observed; as a result of the change in circulation, the nutrition of the tissue surrounding the focus also changes, sometimes over a considerable extent. The onset can be sudden or the disease may be preceded by prodromal symptoms - headaches, dizziness, nausea, brief losses of consciousness, syncope. The clinical picture depends on the localization of the process in the area of one or another artery - the above-mentioned symptoms are observed in various combinations. Two syndromes have been distinguished, observed: 1) in thrombosis of a. cerebellaris; it is characterized by hemianaesthesia alternans, paralysis of the X nerve and the cervical part of the sympathetic nerve (Horner's syndrome) on the side of the focus, disturbance of statics, more often of the cerebellar type, dizziness, and 2) in thrombosis of a. sulci bulbaris; it is expressed by tetraplegia, bilateral paralysis of the XII nerve, paralysis of the X nerve, disturbance of deep sensitivity leading to disturbance of statics. The development of the disease can be acute or subacute. More acute is observed in embolisms; embolism of a. vertebralis is accompanied by very severe bulbar phenomena and in most cases ends in death, either suddenly or after some time due to disturbance of swallowing and subsequent bronchopneumonia.
Hemorrhages into the medulla oblongata depend on the same causes as hemorrhages in other parts of the central nervous system - chronic arteritis, syphilis, intoxications, acute infectious diseases, injuries to the skull, falls from a height, rapid change in atmospheric pressure. Hemorrhage can be unilateral, bilateral, single and multiple. (Patho-anatomical changes - see Apoplexy.) The onset of the disease is sudden, apoplectic, with loss of consciousness. The clinical picture, as in softening, depends on the localization of the process. In extensive hemorrhages, instantaneous death occurs, but even small hemorrhages most often end in death after a short time. Hemorrhage rarely involves only the medulla oblongata, but spreads upward into the pons or downward into the spinal cord. In the presence of bulbar phenomena, the diagnosis presents no difficulty; it is necessary to differentiate from pseudobulbar paralysis (two successive strokes, disturbances of mentality, forced laughter and crying decide the question in favor of pseudobulbar paralysis) and from amyotrophic lateral sclerosis (see). The etiological diagnosis - softening or hemorrhage - is very difficult; knowledge of the development of the disease can help - a more sudden onset speaks for hemorrhage. The localization of the process can be determined by the combination of symptoms. Prevention and treatment - as in vascular diseases of other parts of the brain (see Brain - pathology, Apoplexy); with bulbar phenomena, special care is required (see Bulbar paralysis, Amyotrophic lateral sclerosis). Tumors of the medulla oblongata develop in the medulla oblongata itself or grow into it from neighboring formations. Tumors of the medulla oblongata itself are not particularly frequent; they can be single or multiple; tumors are of the same structure as in other parts of the central nervous system: gliomas, mostly of ependymal origin (more often in children), papillomas, epitheliomas (very rare). Even rarer than neuroepithelial tumors are mesenchymal tumors - sarcomas, endotheliomas, angiomas, fibromas, psammomas, tumors originating from plexus chorioideus; in addition, simple or parasitic cysts are observed - cysticercus, echinococcus. Simple cysts, mostly of traumatic origin, have a transparent thin membrane and contain a transparent fluid. Parasitic cysts (see Echinococcus) can be the size of a small nut. Cysticerci can cause extensive inflammatory and necrotic changes involving the membrane; sometimes they simulate gummatous processes. Of the infectious neoplasms, gumma, tuberculosis are very rare; abscesses have been described as metastases in suppurative foci in the lungs and in the liver. Tumors are more often localized on the posterior surface, masking the cerebellum; the tumor can bulge into the cavity of the fourth ventricle. - The clinical picture - as in tumors of other parts of the central nervous system, general cerebral symptoms and focal symptoms are observed. Of the general cerebral symptoms, headaches appear quite early, are localized in the occiput with irradiation
BLOWING
into the neck, shoulders, upper extremities, accompanied by rigidity when moving the head; vomiting can be considered both as a general cerebral symptom and as a focal one; in addition, drowsiness, lethargy, apathy, asthenia, decreased intellect, delusional ideas (delusions of grandeur, persecution), choked discs with rapidly occurring blindness are noted. Symptoms of increased intracranial pressure may also be absent. Focal symptoms depend on the location of the tumor, its size, and partly on its nature; bulbar phenomena, movement disorders, sensory disorders - unilateral, bilateral, alternating; deafness, neuralgia, dizziness, cerebellar disorders, choreiform convulsions, profuse salivation, taste disorders and finally metabolic disorders - sugar, water (glycosuria, albuminuria); cardiac and respiratory disorders.--The onset is slow and unnoticed; development is rather rapid, within several months, rarely a year. Death from bulbar phenomena. A tumor developing from the medulla oblongata into the cavity of the fourth ventricle is characterized by fluctuations during the disease - there are periods of improvement and worsening; headaches, dizziness, vomiting, hiccups, respiratory and pulse disorders alternate with periods of improvement, the patient feels well, sometimes only a slight nystagmus, cerebellar phenomena remain; during such a good state, sudden death is possible. Abscesses are accompanied by severe headaches; large fluctuations in temperature. - Diagnosis of a medulla oblongata tumor is very difficult, sometimes it is only established at autopsy if there are no general cerebral symptoms.-Treatment is possible only for gummata, for other tumors there is no treatment, since surgical intervention in this area is impossible. Traumatic injuries. Due to its location, the medulla oblongata is less protected from trauma than other parts of the central nervous system. Compression of the medulla oblongata is observed with dislocations of C1 or C2, then gunshot wounds or wounds with a sharp instrument. In all these cases, instantaneous death occurs. Slow compression of the medulla oblongata is observed with osteitis of the occipital bone,1 the first cervical vertebrae, with malum Potti suboccipitalis, with bone tumors, with tumors of the meninges or originating from surrounding formations, with aneurysms of the a. basilaris, a. vertebralis, with hemorrhages in the brain or ;in the cerebellum. The first symptom is neuralgic pain from compression of the roots, unilateral or bilateral, along the course of the occipital nerve or the first cervical roots; then sensory disorders in the areas innervated by these roots, rigidity of the neck, phenomena from the cranial nerves, more often the XII nerve (hemiatrophy of the tongue), the XI nerve (paralysis of the m. cucullaris and sterno-cleido-mastoidei), and other symptoms described above. In an aneurysm, it is sometimes possible to hear a noise on the posterior surface of the skull.-Diagnosis of compression in some cases does not present major difficulties, in others it is difficult to recognize the cause of compression; in these cases, the development of the disease, various: studies (lumbar puncture, encephalography, X-ray, RW in blood and cerebrospinal fluid and others) can help with the diagnosis.--The prognosis is serious, sudden death is not uncommon.-Treatment depends on the cause of compression. Inflammatory diseases of the medulla oblongata.-see Poliomyelitis. See also Bulbar paralysis.
Related articles
Mentioned in
- Abducens Nerve
- Alternating Syndromes
- Ambiguous Nucleus
- Analgesia
- Anarthria
- Anesthesia
- Anesthetic Agents
- Apomorphine
- Arbor Vitae
- Area
- Atropine
- Auditory Pathways
- Avellis Syndrome
- Barium
- Bernard's Sugar Injection
- Blinking
- Brain (551 General diagnostics of brain diseases)
- Brain (cerebrum, a comprehensive term for the entire)
- Brushtein
- Bulbar Palsy
Cite this page
“Medulla Oblongata.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/medulla-oblongata/