Thoracoplasty
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This historical article from the 1928-1936 Soviet Great Medical Encyclopedia details the development and techniques of thoracoplasty, a surgical operation on the chest wall used to mobilize the chest and collapse the lung for conditions such as pulmonary tuberculosis.
Encyclopedia article (1928–1936)
THORACOPLASTY (a term introduced into surgery by C. Spengler in 1890) is an operation performed on the chest wall with the aim of mobilizing it and creating new conditions affecting the function of the lungs, pleura, or heart. Increasing the compliance of the chest wall is achieved by partial or complete removal of the ribs, their cartilages, the clavicle, and the sternum, or by removing the soft tissues of the intercostal spaces and the parietal pleura together with the ribs. In the former case, the method is performed without opening the pleura and can therefore be considered extrapleural; in the latter, radical plastic surgery of the chest wall belongs to intrapleural methods. In relation to the lung, extrapleural thoracoplasty is used as a collapsing method similar to artificial pneumothorax (see), and has a comparable effect. The chest wall, having lost its elasticity over the extent of the removed ribs, yields to the elastic tension of the adjacent lung tissue. The lung collapses and reduces its respiratory excursions. The altered dynamic conditions promote the collapse of pathological cavities contained within the lung and weaken their expansion during breathing, thereby limiting the absorption of lung tissue breakdown products, reducing destructive phenomena, and leading to the scarring of the affected area. This effect is the reason why thoracoplasty has found wide application in cavernous-productive forms of pulmonary tuberculosis. Historically, however, the idea of influencing pulmonary disease by surgical intervention on the chest wall was first proposed by Freund, but from different, opposing motives. After studying degenerative changes in the costal cartilages in certain diseases, Freund linked congenital anomalies of these cartilages and the indurations within them to the occurrence of apical pulmonary tuberculosis and pulmonary emphysema, and in 1859 expressed the idea of the possibility of treating them by resection of the cartilages. By excising the cartilage of the first rib, he hoped to achieve an expansion of the pathologically narrowed ring and the elimination of excessive respiratory rest, which favors the development of the tuberculous process in the apex. Freund also supposed it possible to achieve such a restoration of respiratory movements in pulmonary emphysema by applying the indicated plastic surgery to other costal cartilages as well. Developing his idea in a 1901 work, he based it on the grooves at the apex of the lungs noted by the pathologist Schmorl caused by the indentation of the first rib in apical tuberculosis, and the curvatures and narrowings of the apical bronchi noted by Birch-Hirschfeld. Freund's theoretical considerations caused great excitement in the development of the question of the influence of the shape and movements of the chest wall (ribs and cartilages) on pulmonary processes, but the explanations of this influence proposed by him, i.e., the causal role of the found lung changes, were rejected by the majority of researchers (Morriston-Davies, Ulrici, and others). The operation proposed by Freund for emphysema was first performed on a patient in 1908 by Hildebrandt at the suggestion of Kraus; as for tuberculosis, the first publication of 2 cases of Freund's operations occurred in the same year and belongs to Seidel. Rubashev in his dissertation (1912) was able to collect 72 cases for Freund's operation. Dieterichs (1923) cites 9 French cases up to 1914, 9 German cases, and 2 of his own. At present, this type of thoracoplasty retains its relative indications for pulmonary emphysema; for the treatment of pulmonary tuberculosis under modern standards of collapse therapy, it is insufficient and has only historical significance. The correct path to understanding the collapsing significance of thoracoplasty and its curative value for pulmonary cavities was first pointed out by Quincke. In 1888, he stated the proposition that a cavity is maintained in the lung because it is stretched: "to close it, it must be squeezed." Quincke's first attempts to achieve the closure of pulmonary cavities with the help of thoracoplasty date back to this period, and since then the application of this method began to develop, and the success of its effect in tuberculosis is supported by reports from Spengler (1890), Turban (1899), Landerer (1902), Bier (1904), Mikulicz and Garre (1904), and others. Rib resection progressively increases in its extent. Performed at Quincke's suggestion over the cavity, thoracoplasty, under the influence of the desire for a greater collapse effect, begins to be performed even at a distance from the cavity. Spengler already performs thoracoplasty from a periscapular incision and removes ribs from the III to the VII posteriorly, extending the resection at the spine to the rib angle. The doctrine of artificial pneumothorax, developing since 1882, and especially its growing popularity since 1894 after the international congress in Rome, accumulates material explaining the mechanism of the influence of collapse therapy on the course of pulmonary tuberculosis and refines the requirements for thoracoplasty as well. The introduction into clinical practice of the X-ray method discovered in 1896 drastically changes the conditions for studying the clinical aspects of tuberculosis and provides the key to understanding cases of insufficient effectiveness of artificial pneumothorax and the causes of thoracoplasty failures. These possibilities were utilized by Brauer. Following his work on improving artificial pneumothorax, he expanded the ideas of his predecessors and published in 1906 his method of extensive extrapleural thoracoplasty. Recognizing limited measures as insufficient, Brauer set himself the task of achieving operatively the same complete collapse of the entire lung as is obtained with artificial pneumothorax. In the operation he proposed, he demanded the complete subperiosteal removal of all ribs, a complete "decostation" (Entknochung) of the chest wall, utilizing in his idea Schede's method used for extensive empyemas. The operation was first performed by Friedrich. The first patient operated on by him gave a favorable and lasting effect, however, subsequent cases convinced him of the excessive severity of this kind of thoracoplasty. Out of 27 patients operated on by Friedrich, 8 people died within the first 20 days after the operation (Quincke), while the survivors tolerated the postoperative period with difficulty. The soft, compliant chest wall devoid of ribs created severe shortness of breath due to paradoxical respiration (retraction during inspiration and bulging during expiration), tremor of the diaphragm, mediastinum, and pendular movement of air in the chest cavity. The severity of the operation and its indicated negative aspects prompted the search for new operative paths. In 1911, Wilms and independently in 1912 Sauerbruch published new methods of extrapleural thoracoplasty. The excision of 10-11 ribs in them was performed from a paravertebral incision (Fig. 1). In Wilms' pillar paravertebral thoracoplasty (Pfeilerresection), the ribs were removed in two stages posteriorly over a very small extent of 3-4 cm in length, and in the event of an apparent insufficient effect, a 3rd stage added resection of the costal cartilages anteriorly along the sternum. In Sauerbruch's more radical method, it was proposed to remove, also paravertebrally, predominantly in 2 sessions, significantly larger sections of ribs - 8-10-15-20 cm in length, depending on the required degree of collapse and the localization of the process; the lower ribs are longer, the upper ones shorter. In the first operations, the removal of the 1st rib was not considered mandatory, but in subsequent ones it was recognized as an integral part of thoracoplasty. Both methods—of Wilms and Sauerbruch—had many similar features at the beginning of their proposals and were based on the same idea: to make the operation easier by performing it in several sittings and, using the most advantageous place of rib excision for the effect, namely its most posterior section (Fig. 1), to eliminate the possibility of obtaining too compliant a chest wall and the severe above-mentioned complications created by it that occurred after the Friedrich-Brauer operation. Certain discrepancies in the details of the operation (the length of the excised pieces, the mandatory removal of the X rib, which affects the elevation of the diaphragm, whether to start from above or below, etc.) in the practice of both authors after a series of mutual concessions were largely smoothed out. Not satisfied, however, with the effect of Sauerbruch's thoracoplasty and even more so that of Wilms, and taking into account the negative aspects of his first proposal together with Friedrich, Brauer in 1914 published a new modification of his method—subscapular thoracoplasty. Its main requirements sought: 1) to weaken the excessive trauma of the intervention of the first modification, 2) to enhance the collapse by removing a significantly greater extent of the ribs than the Sauerbruch-Wilms operation provides, 3) to use the scapula as a plate pressing and fixing the ribless chest wall during breathing. Of the last 3 proposals—by Wilms, Sauerbruch, and Brauer—at the present time, the most popular operation is paravertebral thoracoplasty according to Sauerbruch's method in its final modification, i.e., with the removal of the 1st rib and resection of ribs of a length depending on the localization of the cavity, its volume, and the prevalence of the process. Under the influence of such a subperiosteal thoracoplasty extending throughout the entire chest cavity, the lung, having received a weakening of the traction from...
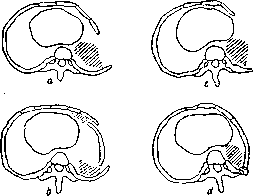
Figure 1. Graphic diagram by Gourget illustrating the advantages of removing ribs posteriorly paravertebrally (d) compared to laterally (a-c).
side of the chest wall collapses due to elasticity, the ends of the resected rib are displaced (the peripheral one drops) and approach each other; at the same time, the diaphragm rises thanks to the resection of the first rib. Upon regeneration from the preserved periostium, the rib becomes shorter, i.e., the thoracic cavity and the diseased lung contract throughout the entire resected section, contracting irreversibly. In view of this, life naturally set the task, when lung damage is limited, to apply thoracoplasty not along the entire length of the chest, but only within the limits of the affected section of the lung so as to preserve normal respiratory excursion in the healthier parts. Such partial thoracoplasty may be required along the lower, and more often one upper lobe of the lung, where in most cases the greatest lesion is concentrated. However, with upper thoracoplasty, there is always a threat of aspiration pneumonia for the lower lobes, regarding which there is still no complete consensus today. Some authors, starting with Wilms, consider the fear of aspiration exaggerated, while others insist on its danger (Sauerbruch and others). In order to mitigate this risk, combined types of thoracoplasty have been created: plasty with basal pneumothorax [proposed by Jessen], plasty of the upper half after preliminary phrenicectomy for compression of the lower half, and the like. To the category of combined thoracoplasties, one can also add thoracoplasty of the lower sections with a plombage along the upper lobe. Despite, however, the entirely real possibility of aspiration during upper thoracoplasty without mitigating its risk by any measures in the lower sections, in recent years the use of upper thoracoplasty alone has begun to acquire great popularity. Revision
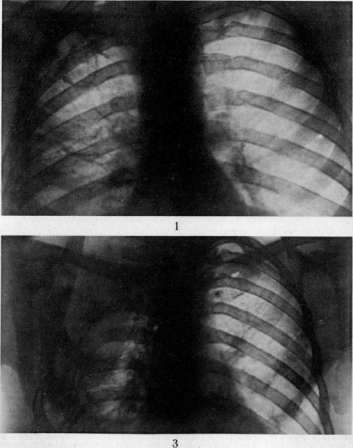
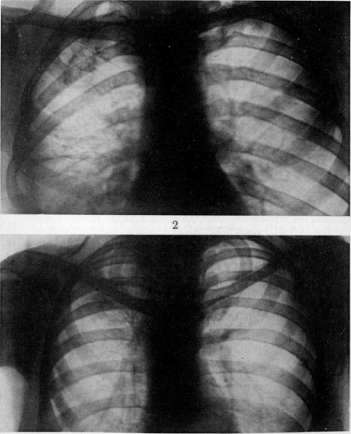
Figure captions: [ Figure 2. Large apical cavity at the level of the upper two ribs. Figure 3. The same case after total thoracoplasty, complete closure of the cavity. Figure 2. The same case 4.5 months after the first phase of thoracoplasty: the cavity has significantly narrowed. Clinical effect during 5 years of observation: no cavity, no tubercle bacilli and elastic fibers, full working capacity. Figure 4. Apical valvular cavity along the upper 4 ribs.
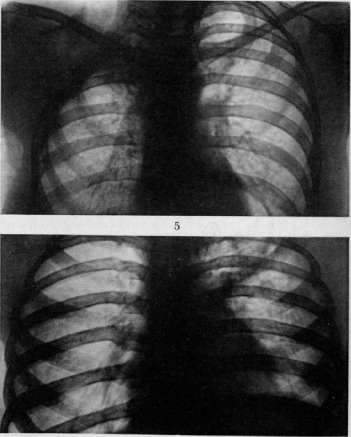
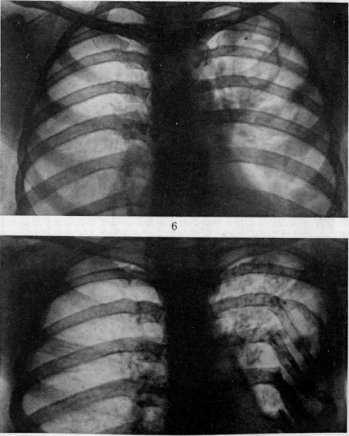
Fig. 5. The same case (see fig. 4) after upper thoracoplasty (4 ribs removed): collapse of the cavity and compression of the lung; lasting effect; no tubercle bacilli and elastic fibers. Fig. 6. Thoracoplasty as a concluding method after an inadequate effect from phrenicectomy; roentgenogram before surgical intervention; cavity at the level of the IV-V ribs on the left. Fig. 7. The same case a month after phrenicectomy; the cavity is smaller, but tubercle bacilli and elastic fibers are present. Fig. 8. The same case. 3 years after thoracoplasty from the IV to the VIII ribs, a lasting effect.
clinical effect; no cavity, no elastic fibers; full working capacity. However, this question cannot yet be considered settled, as observations by individual institutions argue against ignoring the possibility of complications from aspiration, especially in cases of very large cavities and with abundant sputum. The relative severity for weak patients not only of complete thoracoplasty, but also of limited upper thoracoplasty, which requires the removal of no less than 7 ribs, and the presence of contraindications from the other lung when the cavitary process is limited only to the very upper sections of the lung have created the need to limit thoracoplasty to a single apical region. Responding to this demand, the American surgeon Coffey published in 1929 his method of applying in these cases the removal of a piece of the first rib from an anterior subclavian incision with the simultaneous transection of the scalene muscles previously proposed by the surgeon Sato, along with phrenicotomy and excision of the long thoracic nerve. This type of partial thoracoplasty, combined with phrenicotomy and at the same time limited in extent, attracted the general attention of phthisiologists, but did not receive sufficiently wide distribution, however. In our Union, it is promoted by the Sukhumi doctors Bodungen and Antelava who developed it. Based on his experimental research on the approach to the first rib and clinical observations shared with Bodungen, Dr. Antelava somewhat modified Coffey's method (see below) and, having convinced himself of its insufficiency, supplemented it with the resection of the second and third ribs from the anterior incision proposed by him. The fundamental property of extrapleural thoracoplasty to reduce the volume of the thoracic cavity prompted, soon after the introduction of paravertebral thoracoplasty into surgical practice, its extension to purulent pleurisies to reduce the pleural cavity in open forms of chronic and fresher empyemas (residual cavities with unhealing fistulas) and closed ones (in tuberculous purulent pleurisies) in combination with washing with rivanol, weak iodine solutions 1 : 10,000, etc. This method of thoracoplasty, being successful also with regard to empyemas, especially when using a 2-3-stage operation, replaces the methods of Simon, Küster, Estlander, Subbotin, and others for more extensive cavities (see Pleurisy), but is not always sufficiently effective in very old empyemas with very powerfully developed shwarts. In these cases, a more radical intrapleural type of thoracoplasty comes into its own, in which pleural costal shwarts are removed together with the ribs along the entire extent of the empyema. To this category of thoracoplasty belongs the operation proposed in 1890 by Schede (see below) and other methods striving to lessen the trauma of Schede's operation and the dangers arising from it by limiting the extent or dividing it into several sessions (modifications of Friedrich, Helferich, Beck, Krause, etc.). Among the varieties of thoracoplasty, mention should be made of the extensive rib resection in the heart region proposed by Brauer for pericardial adhesions with the anterior chest wall that impede cardiac activity. The operation bears the widespread, but not entirely correct name of "cardiolysis" or thoracolysis praecardiaca. It must be mentioned that paravertebral thoracoplasty has also found application for the purposes of correcting the shape of the chest wall itself and spinal curvature in scoliosis (see). Indications and contraindications for thoracoplasty. Thoracoplasty of any kind comes into its own when artificial pneumothorax is impossible or insufficiently effective. Yielding to artificial pneumothorax in the strength and gentleness of its action, extrapleural thoracoplasty occupies the most prominent place as a surgical method that collapses the lung. Most often, thoracoplasty is performed for pulmonary tuberculosis, chronic empyemas, and residual cavities in empyemas, but it also has indications when it is necessary to collapse cavities in the lung arising from various pathological processes (echinococcus, drained lung abscess, etc.). However, clinical experience with the use of thoracoplasty for bronchiectasis has revealed the insufficiency of the effect obtained from thoracoplasty. After a more or less short-lived success, the severe symptoms of bronchiectasis usually return. Large cavities with a completely compressed lung provide indications for operations of the Schede type. In pulmonary tuberculosis, thoracoplasty generally has indications in cases of a productive cavitary process and, chiefly, in its fibro-cavitary type with a healthy or stable state of a subsided or productive process in the second lung (see separate table, figures 1-8). Total thoracoplasty should be used for widespread tuberculous processes extending over large areas of lung tissue and for large residual pleural cavities. Limited lesions provide a choice between thoracoplasty, phrenicectomy (see), plombage, and thoracocaustics according to Jacobaeus, used when artificial pneumothorax is insufficiently effective and in cases of partial pulmonary adhesions (see Thoracoscopy). In such cases, one should strive to use partial thoracoplasty, and especially of a combined type with artificial pneumothorax, phrenicectomy, etc. Cavities of the upper lobe of the lung located in the posterior "dead angle" (at the heads of the ribs) can provide indications for expanded thoracoplasty by means of additional excision of transverse processes and disarticulation of the rib heads, according to the proposal (1929-1932) of Proust, Maurer, and Rolland. Very limited apical cavities provide grounds for using the Coffey-Antelava operation, but can be successfully and more easily collapsed with paravertebral upper thoracoplasty with the modification described above. For cavities located anteriorly and medially ("sternal"), anterior thoracoplasty is applicable, which is practiced as a 3rd stage when paravertebral thoracoplasty is insufficiently effective and can be performed according to the method of Wilms, Brauer, Sauerbruch, or Antelava. "Hilar-adjacent" cavities, i.e., those located close to the roots of the lung, are not eliminated by paravertebral thoracoplasty even in its most widespread form and therefore are contraindications to such surgical intervention. The introduction since 1927 of bilateral artificial pneumothorax has prompted attempts to expand the indications for thoracoplasty in bilateral processes as well. However, observations on this type of intervention cannot be considered settled. While combined thoracoplasty on one side with artificial pneumothorax on the other apparently provides grounds for cautious use, the still few attempts to use thoracoplasty on both sides do not yet give the right to one conclusion or another. Contraindications to thoracoplasty are as follows: 1) cachexia and severe general weakness and intoxication; 2) active process in the other lung; 3) exudative form of tuberculosis; 4) specific ulcerous lesions of the intestine; 5) kidney disease; 6) cardiovascular system insufficiency. Relative contraindications are: age over 45, laryngeal ulcer processes, bronchiectasis, hilar-adjacent cavities. Technique of thoracoplasty. The operation for all types of thoracoplasty is performed with the patient positioned on the healthy side with the upper part of the torso elevated. The overwhelming majority of authors perform it under local anesthesia. The latter is especially urgently indicated for pleuropulmonary diseases. Despite the vast extent of the operational field, paravertebral anesthesia of the intercostal nerves or according to Vishnevsky's method by infiltration into each intercostal space can provide complete anesthesia, and the operation is well tolerated even by weaker patients. This deep anesthesia can be performed immediately following skin-muscle infiltration anesthesia along the line of the intended incision or after dissection of the skin and the superficial layer of muscles, making injections paravertebrally into the intercostal spaces by eye. Finally, the third general question for all types of thoracoplasty is the question of the periosteum. Although some authors insist on excising it to prolong the period of the greatest possible lung collapse, most surgeons do not do this, because experience speaks against it: a fully sufficient collapse of the lung is obtained even when the periosteum is preserved; it is only required to observe the proper length of the removed ribs. Extrapleural thoracoplasty according to Friedrich-Brauer (figure 2). An extensive horseshoe-shaped incision exposes ribs II to X along their entire length. The anterior vertical part of this incision begins at the level of the second rib, turns posteriorly at the 7th-8th rib, and connects via the horizontal part above the 9th-10th rib with the posterior vertical line, which descends along the spine, beginning at the level of the 3rd spinous process. Along the line of this incision, all layers from the skin to the ribs are transected with a single stroke of the knife, after which the entire outlined skin-muscle flap, together with the scapula and the serratus anterior muscle, is separated from the chest wall and, with the patient's arm strongly raised, the flap is retracted upward and outward. After stopping the hemorrhage, subperiosteal resection of the ribs is undertaken, starting from the lowest one and exposing each rib with a longitudinal incision of the periosteum from the head to the sternal cartilage. Transection of the ribs is performed first at the anterior end and then at the posterior end, as close as possible to the transverse process.
The rib ends are carefully rounded off with bone rongeurs (to prevent neuralgic pains). Concluding the operation, Friedrich recommends excising all the intercostal musculature along the length of the removed ribs together with the remaining periosteum and resecting the nerves high up. These additions, however, are not recognized as mandatory by everyone, and are even considered harmful by some authors (Küttner). The musculocutaneous flap is placed in place, and the wound is sutured in layers. Anteriorly and posteriorly, to the deepest parts of it, to avoid easily forming hematoma, a rubber drain is inserted for 2-3 days. An aseptic dressing, over which strips of adhesive plaster are applied transversely from the sternum to the spine to somewhat strengthen the excessively compliant wall. The arm is bandaged in a sling to the trunk. The postoperative period is conducted in a semi-sitting position of the patient with the application of all measures to combat the adverse consequences of the Friedrich-Brauer method described above. Paravertebral subscapular thoracoplasty of Brauer.

Figure 2. Soft tissue incision according to Friedrich-Brauer.
The modification of this operation described in 1914 by Becker upon the suggestion of Brauer boils down to reducing the wound surface and adopting a more conservative attitude towards the components of the wall. The ribs are removed subperiosteally from two incisions—posterior and anterior. The posterior one is made paravertebrally along the edge of the scapula, and pieces of ribs from X to II are resected from it as close to the heads as possible. After this, the patient, who had been lying on the healthy side until now, is turned onto his back, and an anterior soft tissue incision is made along the anterior axillary line. After resection of the ribs from this incision in the front, the intermediate part of the ribs (remaining unresected between the excised posterior and anterior parts) is isolated from under the scapula with the help of specially adapted Brauer raspatories in a tunnel-like manner from the periosteal sheath. The pieces of ribs thus freed are pulled out from under the scapula, and the latter, having lost a firm support, can thereafter easily, in the form of a pad, be pressed in and press the collapsed lung. The intervention can be performed in one session or, depending on indications, divided into 2-3 or more sessions. The operation is completed by layer-by-layer suturing of the muscles and skin with fixation of the chest wall section freed from the ribs by strips of adhesive plaster over the aseptic dressing. Paravertebral thoracoplasty according to Sauerbruch. The operation is performed mostly in 2 stages. In the 1st session, 6-7 lower ribs are removed, in the 2nd—4-5 upper ones. With sufficient strength of the patient and good anesthesia, it is possible to remove all ribs in 1 session. If thoracoplasty was preceded by phrenicotripsy, one can limit the removal to 8-9 ribs. The interval between sessions is usually established at a month. In some cases, with good strength of the patient, the 2nd session can be carried out in 18-20 days. The length of the removed rib pieces depends on the location of the cavity and the prevalence of the pulmonary process. Along the length of the lobe containing the cavity, the longest pieces are resected, and, conversely, shorter pieces of ribs are excised in the area of the healthiest part of the lung. The patient is placed on the healthy side with the upper half of the trunk elevated. The position should be the most restful, by no means forced. A bolster is placed under the side, somewhat arching the operated side, which facilitates the spreading of the ribs to ease their resection. A support is given to the gluteal region either in the form of a bolster in a towel loop catching the buttocks (the loop is fixed in the front part of the table) or a metal bracket fixed on the edge of the operating table (Fig. 3). The patient's head is placed on a pillow in a position slightly tilted toward the chest.
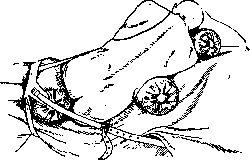
Figure 3. Patient position according to Sauerbruch.
For the greatest spreading of the scapulae, the arms are retracted anteriorly, and the patient is given a rolled pillow to hug. The skin incision is started at the level of the V-VI spinous process three fingerbreadths laterally from the spine, which corresponds to half the distance between the retracted scapula and its spinous processes. With a greater length of the excised ribs, it is more advantageous to make the incision closer to the spine than to the scapula (so that the scar does not fall on its edge). The incision line is run parallel to the spine down to the IX rib, whence it bends arcuately anteriorly and laterally, crosses the X rib, and ends on the axillary line. Skin, muscles (m. trapezius, latissimus dorsi, part of rhomboidei) are immediately incised right down to the ribs. According to Sauerbruch's suggestion, it is more expedient to start the resection with the X rib, then quickly shorten the IX-V ribs, and only after that excise the XI rib. The length of the lengthened pieces is from 8 to 15-20 cm, depending on indications. When freeing the posterior sections of the ribs and spine from the periosteum, the heads of the long muscles of the back are carefully and thoroughly separated. Careful attitude toward them eliminates the risk of subsequent scoliosis (Brauer). If it is possible to continue the operation and finish it in one session, the remaining ribs are also removed. To perform this 2nd phase of the operation, the upper thoracoplasty, the Sauerbruch incision is lengthened. The muscles cut simultaneously with the skin down to Cvii (mm. trapezius, rhomboideus, serratus post. sup.) are strongly pulled back together with the freed scapula by a hook anteriorly. Starting from the lower one, the ribs are resected along a length of 6-8 cm one after another up to the II rib inclusively. All the time during the operation, during coughing jolts, the assistant counteracts the bulging of the lungs by pressing with a gauze tampon. To remove the I rib, the incision is lengthened again, this time turning it arcuately across the shoulder girdle anteriorly to the anterior edge of m. trapezii. By this fractional execution of the incision, Sauerbruch strives to reduce the severity of the operation, limit blood loss and nerve trauma resulting from the sudden dissection of tissues over the entire length of the chest from top to bottom (Fig. 4). With the upper incision looping around the scapula, two arteries are usually cut and ligated: aa. cervicalis superficialis and transversa colli. With very strong retraction by hooks and pulling of the outer edge of the wound (mm. trapezius and levator scapulae) and especially the scapula deep in the wound, the I rib can be seen right up to the subclavian artery and the nerve brachial plexus, if one first cuts and pulls up the posterior scalene muscle (attaching to the II rib) and the middle one (Fig. 5). The first rib is resected according to Sauerbruch's requirement over a length of 3 cm from the transverse process right down to Lisfranc's tubercle. The anterior scalene muscle is cut at the very edge of the rib. After removing all ribs, blood vessels are ligated, the wound is toileted, and catgut sutures are applied in layers to the muscles and
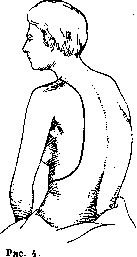
Incision according to Sauerbruch.
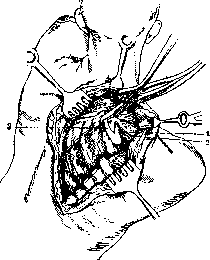
Figure 5. Approach to the I rib according to Sauerbruch: 1 and 2—subclavian neurovascular bundle; 3—I rib.
silk sutures to the skin. A rubber drain is inserted deep into the wound right down to the bed of the I rib for 2-3 days to avoid a hematoma. Aseptic dressing; 2-3 spiral fixing strips of plaster from the healthy shoulder to the anterior abdominal wall. Gauze-cotton dressing with the arm bandaged to the trunk. In the concluding part of the described type of thoracoplasty, the most difficult is the resection of the I rib. The depth of the wound in the Sauerbruch incision method creates a significant obstacle to calm operating by sight and ...
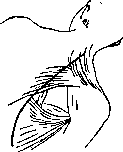
Figure 6. Straight incision according to Fedorov.
horn approach to the rib. Meanwhile, the best effect of thoracoplasty is obtained by resection of the largest piece of the first rib, and for certain localizations of cavities it is necessary to remove its entire extent from the head right up to the cartilage (Graf, 1925). Significant alleviation of conditions can be achieved by a certain modification of Sauerbruch's operation method (Esipov). First, the musculocutaneous incision is continued upward without slope along the shoulder girdle anteriorly, parallel to the spine to the level of CVI-VII (Fig. 6). By dissecting the short horizontal fibers of the trapezius muscle, retraction of the levator scapulae muscle, freed in its upper parts, together with the scapula, is facilitated (Esipov, Nalivkin). Second, immediately after the dissection of the musculocutaneous layer, exposure and anesthesia of the ribs, the slip of the serratus anterior muscle is subperiosteally displaced from the second rib; unlike others, it is located very close to the spine and, more than all other slips, prevents good retraction of the scapula and exposure of the first rib (Esipov) (Figs. 7-8). In this modification, upper thoracoplasty sharply changes the conditions of access to the first rib, making it clearly visible not only to the operating surgeon but also to surrounding observers of the operation and making it possible to manipulate with simpler instruments with short jaws (Fig. 9). The pillar paravertebral thoracoplasty according to Wilms (Pfeiler resection) is characterized by shorter segments of resected ribs—3-4 cm from 2 incisions: posterior and anterior. In the initial variant of the operation, from a longitudinal skin incision along the spine, 3 transverse muscle dissections were made along the fibers at the level of the II, V, and VII ribs. Resection began from the VIII rib, VII and VI from the lower muscle cleft, then the V-IV ribs were removed from the middle, and the III, II, and I ribs from the upper. After 34 thoracoplasties, Wilms's method took the following form: a) in limited processes of the upper part of the upper lobe: 1st stage—paravertebral resection from the VII to the I rib; 2nd stage (provisionally, in case of insufficiency of the 1st)—parasternal resection of cartilages from the I to the V rib; 3rd stage (also provisionally)—parasternal resection of the clavicle so that its outer remnant during collapse rests with its medial end into the clavicular notch of the sternum, held from above by the sternocleidomastoid muscle and from below by the subclavius. b) In case of lower lobe lesion: 1) 1st stage—paravertebral resection from the VIII-IX
Figure 7. Relation of Esipov's straight incision to the paravertebral muscles: 1—splenius muscle; 2—levator scapulae muscle; 3—rhomboideus muscle; 4—trapezius muscle; 5—incision line.
rib to the I; 2nd stage—parasternal resection of the 5th-6th cartilages; the 2nd or 1st stage is divided into two: short resection of the upper 6 ribs,
Figure 8. Muscle and vascular relationships in the approach method to the first rib according to Esipov: 1—levator scapulae muscle; 2—posterior scalene muscle; 3—brachial plexus; 4—upper 2 slips of the serratus anterior muscles displaced by an elevator.
in the second step—the VII, VIII, IX ribs over a large extent (10-15 cm). The operation, if necessary, is completed by a third step, in which
Figure 9. Exposure of the first rib according to Esipov: 1—levator scapulae muscle; 2—middle and posterior scalene muscles; 3 and *—rhomboideus muscle; 4—first rib; 5—brachial plexus; 6—subclavian artery; 7—serratus anterior muscle.
not earlier than 6-8 weeks after the first, the sternal cartilages are resected from the front. Coffey's operation belongs to the category of interventions on the first rib performed from a supraclavicular incision (Figs. 10-11). Access 61S
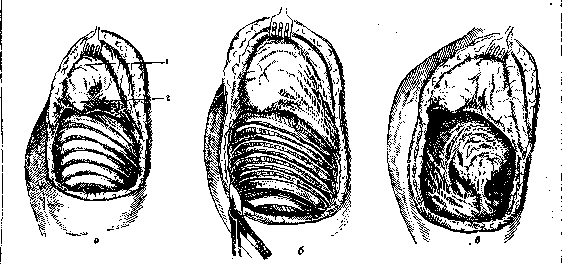
I K, Ch Figure 10. Incision according to Coffey. to the rib is carried out from an incision made along the bisector of the angle between the sternocleidomastoid muscle and the clavicle. Penetrating deeper into the soft tissues, it is necessary along the way to transect the platysma muscle, ligate the external jugular vein, transect the omohyoid muscle, ligate and transect the transverse cervical and transverse scapular arteries and veins. Perform phrenicotomy, detach the anterior and middle scalene muscles from the rib, expose and transect the long thoracic nerve running along the edge of the last muscle to enhance the collapse of the lung by causing paralysis of the serratus anterior muscle, and finally, taking the subclavian artery and brachial plexus on a loop and retracting the edge of the trapezius and posterior scalene muscles with a hook, proceed to the subperiosteal removal of the first rib. The latter is excised over an extent of 3 cm at the posterior edge of the bed of the subclavian artery and at the transverse process of DI. Coffey's method was modified and supplemented by the Soviet surgeon Antelava, who, excluding the transection of the long thoracic nerve from the operation, added the wide extrapleural apicolysis proposed in 1929 by Lauwers during the removal of the first rib and added the resection of the first rib (Fig. 12). Antelava's anatomical studies proved that Coffey's operation is performed more easily in the brachymorphic and mesomorphic type of the upper thoracic aperture and encounters great difficulties in dolichomorphic ones (Fig. 13), since the posterior section of the first rib in them is covered by the brachial plexus and it is almost impossible to isolate the subclavian artery, which, together with the plexus, must be displaced anteriorly and medially. Thoracoplasty in empyema. Of the plastic operations for empyema, Schede's thoracoplasty (Fig. 14) (see Pleurisy) is the most radical, but at the same time the most severe operation. Schede's method (intrapleural thoracoplasty) with the patient lying on the healthy side. With a bulky horseshoe-shaped incision penetrating through all layers, a musculocutaneous flap is outlined corresponding to the entire extent of the empyema. Its anterior vertical begins from the IV rib, at the lower edge of the pectoralis major muscle, the posterior—at the level of the upper edge of the scapula, the lower horizontal—on the X rib along the axillary line. All musculature, including the serratus anterior muscle, is separated from the ribs. Upon release, the musculocutaneous flap together with the scapula is pulled upward with hooks while the arm is strongly abducted and raised upward. Upon stopping
Figure 11. Incision according to Coffey-Antelava: 1—phrenic nerve; 2—anterior scalene muscle; 3—brachial plexus; 4—subclavian artery; 5—subclavian vein; 6—clavicle.
bleeding, subperiosteal resection of the ribs along their entire extent from the X to the II follows. The next step is the release of a new, deep, ribless flap from scar tissue (shvarts) and its mobilization. For this purpose, the pleural cavity is penetrated either by widening a fistula with a longitudinal incision along the intercostal space or a flap is immediately fashioned through the thickness of the intercostal spaces and periosteum along the edge of the first musculocutaneous flap, starting from behind. Along the way, the intercostal vessels are ligated and nerve trunks are transected. The operation is completed by the final release of the flap from scar tissue, toilet of the wound, and layer-by-layer suturing with interrupted sutures of the mobilized second and first flaps fitted to the lung until complete contact is achieved. Rubber drains are inserted into the depth of the wound along the edge of the anterior and posterior vertical incisions. Aseptic dressing, over which is laid
Fig. 12. Removal of the first rib according to Coffey-Antelava: 1—brachial plexus; 2—first rib; 3—clavicle; 4—stump of the anterior section of the first rib.
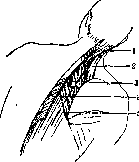
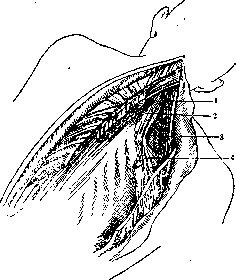
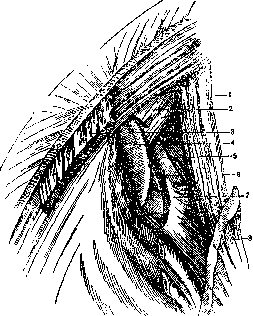


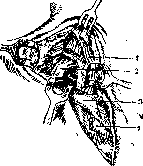

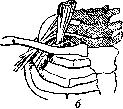
Fig. 13. Two extreme types (a and b) of the upper aperture of the chest according to Antelava. Oblique and transverse strips of adhesive plaster are applied to fix the chest wall. The arm is bandaged tightly to the torso with a Desault bandage. Some authors open the pleura and fashion a flap without performing subperiosteal rib resection or resorting to it partially, as required by the compression of the flap to obliterate the cavity. The severity of the extensive Schede operation, which historically served as the prototype for subsequent proposed methods of thoracoplasty, can be alleviated by performing it in several stages. For better mobilization and imparting greater plasticity to the flap, Zudeck proposed performing one of these sessions in the same way as Beck and Krause perform an extensive resection of the scapula; Helfrich used an H-shaped incision in a lying position (I), excised the ribs with the periosteum, and removed the entire thickness of the deep layer of the wall. Technique of paravertebral extrapleural thoracoplasty for empyema. Thoracoplasty for empyema according to Sauerbruch is also performed in one or several sessions, as in pulmonary tuberculosis. It is only necessary, for a more favorable placement of pus, to begin the operation with the upper thoracoplasty. To avoid infection of the wound cavity from the fistula, first of all, the fistula opening should be isolated with two semi-lunar incisions and sutured along the edge above the fistula, covered with a gauze tampon. The ribs are removed above and below the fistula, separating them with particular care from the periosteum near the fistulous tract. To avoid opening it, especially in cases where the fistula is surrounded by a bone ring, a small piece of bone near the fistula can be left untouched, transecting the rib behind and in front of the fistula (Esipov). Postoperative regimen. The postoperative period after thoracoplasty often proceeds with certain severe symptoms for the patient, especially after one-stage thoracoplasty. To eliminate and alleviate them, it is necessary to use the following methods. More or less pronounced difficulty in breathing depends on the loss of fixation of the lung to the chest wall in the area of the resected part. Dyspnea is significantly alleviated by the use of adhesive plaster or by sewing, according to Brushger and Sauerbruch, strips of bandage rubber that stretch during inspiration and collapse during expiration into the plaster strips. The patient's arm must be well bandaged to the torso, but circular turns of the bandage should not strongly tighten the other side of the chest. The patient is calmly placed in bed in a semi-sitting position with support under the head and under the buttocks to avoid sliding. The first 1-2 days, for painful coughing, narcotic drugs are used; thereafter they are contraindicated and replaced by expectorants. Cardiac activity is supported by camphor, infusions of glucose and saline, and in more severe cases, by the administration of digitalis. In cases of shock, morphine is prescribed. The rise in temperature in the first days may depend on the intoxication of the organism by products of a specific nature; often the reason lies in the development of a hematoma. At high temperature rises, early dressing and careful examination of the wound for the possibility of infection are necessary. At the first signs of it, partial removal of sutures, drainage, and, if suppuration is undoubted, urgent radical measures are required. Immediately after the operation, the amount of sputum decreases, patients forcibly hold back a cough, and the delay in expectoration can be a causal factor for raising the temperature. The doctor is required to combat this by a timely transition to expectorants and suggestion to the patient. Drainage from the wound at normal temperature is removed on the 2nd-3rd day. In empyema, if drainage was not inserted during the operation, it is inserted again into the fistula (with great caution to avoid rupturing the fistula wall) at the first signs of pus retention in the pleural cavity (temperature rise), usually on the 2nd-3rd day. The bandaged arm is freed on the 7th-12th day, after which active movements with it are permitted. The patient is usually got up after 3-4 weeks, in some cases it is possible to allow walking even on the 10th day. Outcomes of thoracoplasty. The material for thoracoplasty in tuberculosis is usually cases of ineffective artificial pneumothorax. Under these conditions, in the practice of all authors, the success of thoracoplasty depends mostly on the correctness of indications, experience, and technique of the operator. Brauer defines the outcomes by the following ratios: 1/3 of cases give a complete clinical recovery, 1/5 improvement (relative working capacity), and the last third unsatisfactory outcomes and death. According to Sauerbruch's largest statistics, recovery is noted in 33%, improvement in 27%, mortality is calculated at 25%, with 12% being connected with the operation and 13% in the long-term result. Summary statistics of various authors in 740 cases give 34% clinical cure, 28% improvement, and 38% failure of thoracoplasty (including mortality). The calculation of long-term results of thoracoplasty for 10 years of work (1923-33) of the Moscow Regional Tuberculosis Institute led to the following data for 158 thoracoplasties: 1. Total performed for pulmonary tuberculosis 105 thoracoplasties. Of these, recovery was in 45 people = 48% (full working capacity), improvement - 25 people = 24% (tubercle bacilli at times); no change - 6 people = 6%. Death - 21 people = 22%. No information - 11 people. Of this number, complete thoracoplasty was performed in 57 patients: recovery - 24 people = 52%, improvement - 13 people = 28%. Death - 9 people = 20%. No information - 11 people.
Figure 14. Various phases (a, b, c) of the Schede operation: 1-reflected upward osteoplastic flap; 2-projecting lower angle of the scapula.
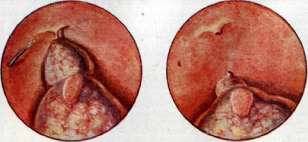
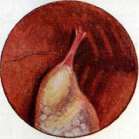
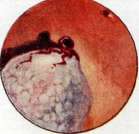
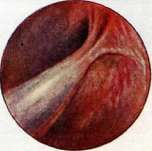
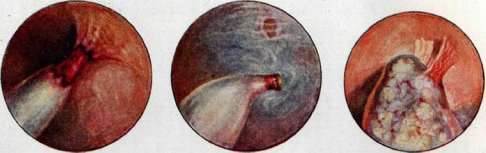
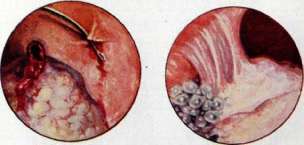
Fig. 1 and 2. Visible after thoracoplasty... intrathoracic burning of the pulmonary apex before and after pneumolysis. Fig. 3. Plate-like, red-colored, rich in blood vessels cord. Upper lobe with a cavity pulled to the wall. Fig. 4. Cord burned. Lung expands independently. Fig. 5. Unfavorable cord with strong tension of the lung and the cone of the parietal pleura. Shape of the cord, most dangerous. The upper lobe after transection of the cord (Fig. 2) has strongly contracted. The lung has contracted. Cultus ... cutting with scissors ... and in the sense of stretching the myelin of the lung tissue. Figure 6. Repeated burning. Burning of the capsule and parietal pleura. The lung, freed from all its own connective tissue, pulls and thins the cord with further burning of it. Fig. 7. Cord burned. The lung has expanded, contracted. Indium for several days placed on the wall - trace of eliminated tension. Figure 8. Two apical membranous cords. Fig. 9. Parietal stump after burning bled heavily (stream). Stopping bleeding by pressing a cold pellet. Figure 10. Lamellar, curtain-like, folded cord. At the base - bursting bubbles on the surface of the lung (oedema bullosum). Upon their rupture, spontaneous pneumothorax develops. To Art. Thoracoplasty. Partial upper thoracoplasty in 34 patients. a) With artificial pneumothorax on the same side - 22 people. Recovery - 12 people = 54%. Improvement - 5 people = 28%. No change - 1 = 28%. Death - 4 = 18%. b) Without artificial pneumothorax - 12. Recovery - 6 = 50%. Improvement - 4 = 33%. Death - 2 = 17%. With upper thoracoplasty without basal artificial pneumothorax, aspiration pneumonia - 3 times; in one case with a fatal outcome on the 16th day after the operation. Partial lower thoracoplasty - 14 patients. Recovery - 3 people = 22%. No change - 3, deterioration - 2 = 35%. Death - 6 people = 43%. 2. Total thoracoplasties performed for empyema (after spontaneous pneumothorax and for residual cavities) - 43. Recovery - 7 = 20%. Significant improvement - 7 people = 20% (fistula remains, but full working capacity). Improvement - 10 = 29%. Death - 11 = 31%. No long-term information - 8 people. 3. Thoracoplasty for bronchiectasis - 7. No change - 2, slight improvement - 2. Long-term death - 3. 4. Thoracoplasty for lung abscesses: recovery - 1, improvement - 1, death after 2 months - 1. Regarding functional results, usually despite the extensive transection of the scapular muscles, the movements of the shoulder girdle are restored to the full extent (Fig. 15). Scoliosis with careful and cautious work on the long muscles of the back at the moment of isolation of the posterior angle and end of the ribs never occurs. The chest sinks significantly, most strongly in complete thoracoplasty, due to the shortening
Figure 15.
of the ribs in length and the lowering of the entire chest downwards. The cavities of the caverns in tuberculosis as a result should turn out to be collapsed. Only in this case does a complete recovery occur with the disappearance of all signs of the disease.
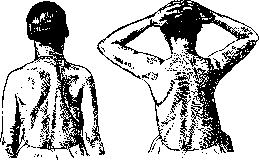
Related articles
Mentioned in
Cite this page
“Thoracoplasty.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/thoracoplasty/